Healthcare Professionals’ Beliefs and Concerns About the Use of Doxycycline Post-Exposure Prophylaxis (doxyPEP): A Systematic Review

 ,
Abstract
1. Introduction
2. Method
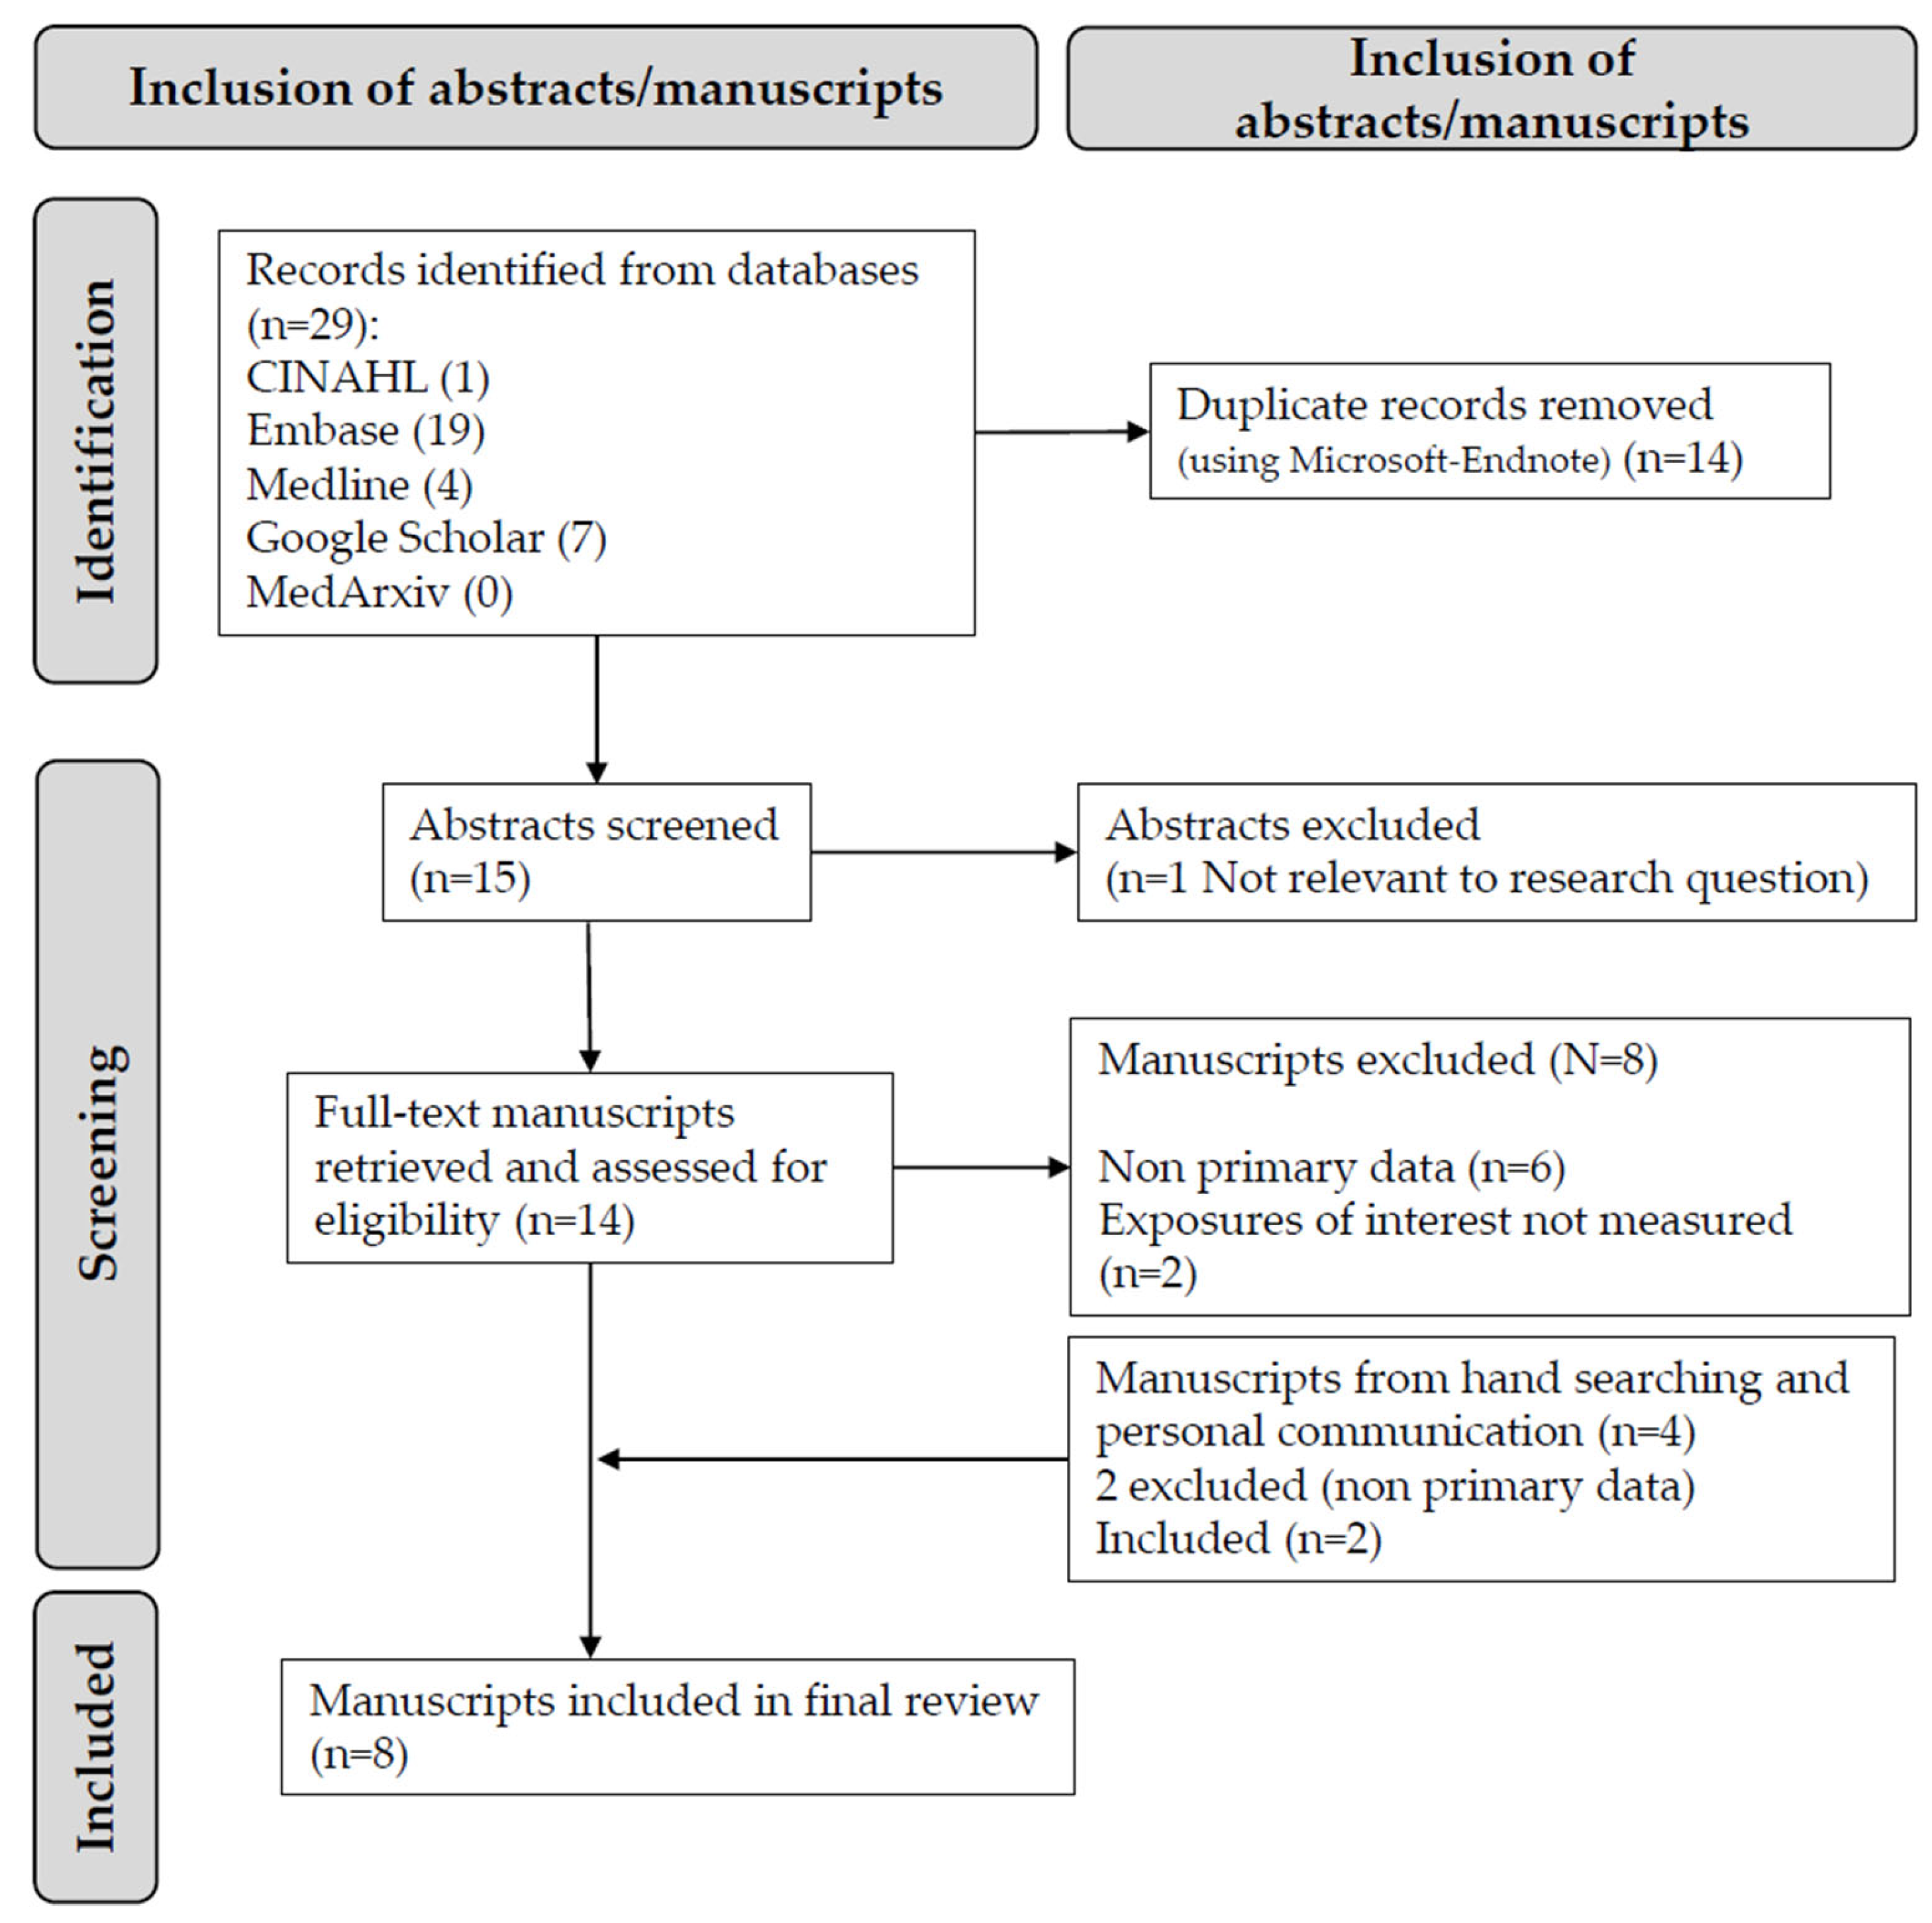
2.1. Search Strategy and Selection
2.2. Study Selection and Risk of Bias
2.3. Data Extraction and Synthesis
3. Results
3.1. Providing doxyPEP to MSM
3.2. Concerns About doxyPEP
4. Discussion
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Data Availability Statement
Conflicts of Interest
References
- Geretti, A.M.; Mardh, O.; de Vries, H.J.C.; Winter, A.; McSorley, J.; Seguy, N.; Vuylsteke, B.; Gokengin, D. Sexual transmission of infections across Europe: Appraising the present, scoping the future. Sex. Transm. Infect. 2022, 98, 451–457. [Google Scholar] [CrossRef] [Scilit]
- Kenyon, C. Screening is not associated with reduced incidence of gonorrhoea or chlamydia in men who have sex with men (MSM); an ecological study of 23 European countries. F1000Research 2019, 8, 160. [Google Scholar] [CrossRef] [Scilit]
- Roberto Queiroz, P.; Dos Santos, M.M.; Lopes, A.K.B.; da Silva, J.A.; Aranha Filho, B.; Costa, T.G.; Bezerra, A.C.N.; Lima, K.C. Prevalence and factors associated with syphilis among men who have sex with men in Brazil. Front. Public Health 2025, 13, 1465799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, H.; Chen, Y.; Shi, L.; Liu, X.; Xu, Z.; Sun, L.; Zhao, X.; Zhou, Y.; Lu, J.; Zhang, Z.; et al. Prevalence of syphilis and Chlamydia trachomatis infection among men who have sex with men in Jiangsu province, China: A cross-sectional survey. Front. Public Health 2022, 10, 1006254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gilmour, L.S.; Walls, T. Congenital Syphilis: A Review of Global Epidemiology. Clin. Microbiol. Rev. 2023, 36, e0012622. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hooshiar, M.H.; Sholeh, M.; Beig, M.; Azizian, K.; Kouhsari, E. Global trends of antimicrobial resistance rates in Neisseria gonorrhoeae: A systematic review and meta-analysis. Front. Pharmacol. 2024, 15, 1284665. [Google Scholar]
- Molina, J.M.; Charreau, I.; Chidiac, C.; Pialoux, G.; Cua, E.; Delaugerre, C.; Capitant, C.; Rojas-Castro, D.; Fonsart, J.; Bercot, B.; et al. Post-exposure prophylaxis with doxycycline to prevent sexually transmitted infections in men who have sex with men: An open-label randomised substudy of the ANRS IPERGAY trial. Lancet Infect. Dis. 2018, 18, 308–317. [Google Scholar] [CrossRef] [Scilit]
- Luetkemeyer, A.F.; Donnell, D.; Dombrowski, J.C.; Cohen, S.; Grabow, C.; Brown, C.E.; Malinski, C.; Perkins, R.; Nasser, M.; Lopez, C.; et al. Postexposure Doxycycline to Prevent Bacterial Sexually Transmitted Infections. N. Engl. J. Med. 2023, 388, 1296–1306. [Google Scholar] [CrossRef] [Scilit]
- Szondy, I.; Meznerics, F.A.; Lőrincz, K.; Kemény, L.V.; Walter, A.; Mohammed, A.A.; Hegyi, P.; Kiss, N.; Bánvölgyi, A. Doxycycline prophylaxis for the prevention of sexually transmitted infections: A systematic review and meta-analysis of randomized controlled trials. Int. J. Infect. Dis. 2024, 147, 107186. [Google Scholar] [CrossRef] [Scilit]
- Mason, L.C.E.; Richardson, D.; Charles, H.; Simms, I.; Mitchell, H.D.; Manuel, R.; Godbole, G.; Jenkins, C.; Baker, K.S. Using demographics of patients to inform treatment of shigellosis in England. Lancet Microbe 2024, 6, 101026. [Google Scholar] [CrossRef] [Scilit]
- Kenyon, C.; Baetselier, I.; Wouters, K. Screening for STIs in PrEP cohorts results in high levels of antimicrobial consumption. Int. J. STD AIDS 2020, 31, 1215–1218. [Google Scholar] [CrossRef] [Scilit]
- Vanbaelen, T.; Manoharan-Basil, S.S.; Kenyon, C. Doxy-PEP could select for ceftriaxone resistance in Neisseria gonorrhoeae. Lancet Infect. Dis. 2025, 25, e316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Halloran, C.; Croxford, S.; Mohammed, H.; Gill, O.N.; Hughes, G.; Fifer, H.; Allen, H.; Owen, G.; Nutland, W.; Delpech, V.; et al. Factors associated with reporting antibiotic use as STI prophylaxis among HIV PrEP users: Findings from a cross-sectional online community survey, May–July 2019, UK. Sex. Transm. Infect. 2021, 97, 429–433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ringshall, M.; Cooper, R.; Rawdah, W.; Perera, S.; Bannister, A.; Nichols, K.; Fitzpatrick, C.; Richardson, D. Chemsex, sexual behaviour and STI-PrEP use among HIV-PrEP users during the COVID-19 pandemic in Brighton, UK. Sex. Transm. Infect. 2022, 98, 312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kohli, M.; Medland, N.; Fifer, H.; Saunders, J. BASHH updated position statement on doxycycline as prophylaxis for sexually transmitted infections. Sex. Transm. Infect. 2022, 98, 235–236. [Google Scholar] [CrossRef] [Scilit]
- Nadarzynski, T.; Smith, H.E.; Richardson, D.; Ford, E.; Llewellyn, C.D. Sexual healthcare professionals’ views on HPV vaccination for men in the UK. Br. J. Cancer 2015, 113, 1599–1601. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Moola, S.; Munn, Z.; Sears, K.; Sfetcu, R.; Currie, M.; Lisy, K.; Tufanaru, C.; Qureshi, R.; Mattis, P.; Mu, P. Conducting systematic reviews of association (etiology): The Joanna Briggs Institute’s approach. Int. J. Evid. Based Healthc. 2015, 13, 163–169. [Google Scholar] [CrossRef] [Scilit]
- Park, J.J.; Stafylis, C.; Pearce, D.D.; Taylor, J.; Little, S.J.; Kojima, N.; Gorin, A.M.; Klausner, J.D. Interest, Concerns, and Attitudes Among Men Who Have Sex With Men and Health Care Providers Toward Prophylactic Use of Doxycycline Against Chlamydia trachomatis Infections and Syphilis. Sex. Transm. Dis. 2021, 48, 615–619. [Google Scholar] [CrossRef] [Scilit]
- Pearson, W.S.; Emerson, B.; Hogben, M.; Barbee, L. Use of Doxycycline to Prevent Sexually Transmitted Infections According to Provider Characteristics. Emerg. Infect. Dis. 2024, 30, 197–199. [Google Scholar] [CrossRef] [Scilit]
- Mogaka, F.O.; Kwach, B.; Odira, A.; O’Malley, G.; Hearst, M.; Bukusi, E.A.; Stewart, J. Stakeholder perspectives on integrating doxycycline postexposure prophylaxis into Kenyan HIV PrEP programmes. Sex. Transm. Infect. 2025, 056535, Online First. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cornelisse, V.J.; Riley, B.; Medland, N.A. Australian consensus statement on doxycycline post-exposure prophylaxis (doxy-PEP) for the prevention of syphilis, chlamydia and gonorrhoea among gay, bisexual and other men who have sex with men. Med. J. Aust. 2024, 220, 381–386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phillips, C.; Vinuesa, M.; Fowler, C.; Soni, S.; Richardson, D. Doxycycline postexposure prophylaxis (doxyPEP): Sexual health clinicians’ knowledge and readiness. Sex. Transm. Infect. 2025, 101, 132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allan-Blitz, L.T.; Traeger, M.; Gitin, S.; Smith, K.; Mayer, K.H.; Khan, T. Facilitators and Barriers to the Rollout of Doxycycline Postexposure Prophylaxis for Sexually Transmitted Infections in a Boston Community Health Center. Sex. Transm. Dis. 2025, 52, 585–590. [Google Scholar] [CrossRef] [Scilit]
- Imerlishvili, E.; Lake, J.; Todorovic, S.; Gonzalez, C.; Boos, E.M.; Hart-Malloy, R. Doxycycline post-exposure prophylaxis for preventing bacterial sexually transmitted infections (STIs): Are clinical providers supportive? Int. J. STD AIDS 2025, 36, 297–303. [Google Scholar] [CrossRef] [Scilit]
- Perkins, R.; Beima-Sofie, K.; Christopoulos, K.; Cohen, S.E.; Dright, A.; Dombrowski, J.C.; Gougougui, A.; Kohler, P.; Luetkemeyer, A.F.; Pintye, J.; et al. Another Tool for the Sexual Health Toolkit: US Health Care Provider Knowledge and Attitudes About Doxycycline Postexposure Prophylaxis to Prevent Bacterial Sexually Transmitted Infections Among Men Who Have Sex With Men. Sex. Transm. Dis. 2025, 52, 129–134. [Google Scholar] [CrossRef] [Scilit]
- Bachmann, L.H.; Barbee, L.A.; Chan, P.; Reno, H.; Workowski, K.A.; Hoover, K.; Mermin, J.; Mena, L. CDC Clinical Guidelines on the Use of Doxycycline Postexposure Prophylaxis for Bacterial Sexually Transmitted Infection Prevention, United States, 2024. MMWR Recomm. Rep. 2024, 73, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Sherrard, J.; Gokengin, D.; Winter, A.; Marks, M.; Unemo, M.; Jensen, J.S.; Cusini, M.; Mårdh, O. IUSTI Europe position statement on use of DoxyPEP: June 2024. Int. J. STD AIDS 2024, 35, 1087–1089. [Google Scholar] [CrossRef] [Scilit]
- Werner, R.N.; Schmidt, A.J.; Potthoff, A.; Spornraft-Ragaller, P.; Brockmeyer, N.H. Position statement of the German STI Society on the prophylactic use of doxycycline to prevent STIs (Doxy-PEP, Doxy-PrEP). J. Dtsch. Dermatol. Ges. 2024, 22, 466–478. [Google Scholar] [CrossRef] [Scilit]
- Fitzpatrick, C.; Richardson, D.; Sherriff, N.; Whetham, J. Pilot evaluation of PrEP EmERGE—A novel digital health innovation designed to support sexual health clinics and HIV-PrEP users. HIV Med. 2023, 24, 502–506. [Google Scholar] [CrossRef]
- Tweed, M.; Fortescue-Talwar, K.; Finn, R.; Buonsenno, L.; Nichols, K.; Frem, J.; Darking, M.; Nicholson, S.; Williams, D.; Richardson, D. Delivering a community-based monkeypox vaccination programme in partnership. Int. J. STD AIDS 2023, 34, 427–429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nadarzynski, T.; Frost, M.; Miller, D.; Wheldon, C.W.; Wiernik, B.M.; Zou, H.; Richardson, D.; Marlow, L.A.V.; Smith, H.; Jones, C.J.; et al. Vaccine acceptability, uptake and completion amongst men who have sex with men: A systematic review, meta-analysis and theoretical framework. Vaccine 2021, 39, 3565–3581. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vanbaelen, T.; Kenyon, C. Primum non-nocere: Is it time to stop screening for Neisseria gonorrhoeae and Chlamydia trachomatis in men who have sex with men taking HIV pre-exposure prophylaxis? Sex. Transm. Infect. 2024, 100, 337–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pitt, R.; Unemo, M.; Sonnenberg, P.; Alexander, S.; Beddows, S.; Cole, M.J.; Clifton, S.; Mercer, C.H.; Johnson, A.M.; Ison, C.A.; et al. Antimicrobial resistance in Mycoplasma genitalium sampled from the British general population. Sex. Transm. Infect. 2020, 96, 464–468. [Google Scholar] [CrossRef] [Scilit]
- O’Flanagan, H.; Siddiq, M.; Llewellyn, C.; Richardson, D. Antimicrobial resistance in sexually transmitted Shigella in men who have sex with men: A systematic review. Int. J. STD AIDS 2023, 34, 374–384. [Google Scholar] [CrossRef] [Scilit]
- Wahab, N.; Dubey, V.; Sivachandran, V.; Llewellyn, C.; Richardson, D. Campylobacter spp. in men who have sex with men: A systematic review. Int. J. STD AIDS 2024, 35, 1094–1102. [Google Scholar] [CrossRef] [Scilit]
- Frem, J.A.; Russell, A.; Fitzpatrick, C.; Williams, D.; Richardson, D. Gastrointestinal Escherichia coli in men who have sex with men: A systematic review. Int. J. STD AIDS 2025, 36, 176–184. [Google Scholar] [CrossRef] [Scilit]
- Sivachandran, V.; Wahab, N.; Dubey, V.; Richardson, D.; Llewellyn, C. Demographic, Behavioural, and Biological Factors Seen in Men Who Have Sex with Men with Salmonella spp.: A Systematic Review. Venereology 2024, 3, 162–171. [Google Scholar] [CrossRef] [Scilit]
- Jensen, J.S.; Unemo, M. Antimicrobial treatment and resistance in sexually transmitted bacterial infections. Nat. Rev. Microbiol. 2024, 22, 435–450. [Google Scholar] [CrossRef] [Scilit]
- Truong, R.; Tang, V.; Grennan, T.; Tan, D.H.S. A systematic review of the impacts of oral tetracycline class antibiotics on antimicrobial resistance in normal human flora. JAC Antimicrob. Resist. 2022, 4, dlac009. [Google Scholar] [CrossRef] [Scilit]
- Kohli, M.; Reeves, I.; Waters, L. Homophobia in the provision of sexual health care in the UK. Lancet HIV 2024, 11, e125–e130. [Google Scholar] [CrossRef] [Scilit]
- Venkateswaran, N.; Swetschinski, L.R.; Fastl, C.; Bari, C.D.; Criscuolo, N.G.; Mulchandani, R.; Zhao, C.; Meštrović, T.; Ikuta, K.S.; Martins, S.B.; et al. Using priorities between human and livestock bacterial antimicrobial resistance (AMR) to identify data gaps in livestock AMR surveillance. BMC Infect. Dis. 2024, 24, 1027. [Google Scholar] [CrossRef] [Scilit]
- Stewart, J.; Oware, K.; Donnell, D.; Violette, L.R.; Odoyo, J.; Soge, O.O.; Scoville, C.W.; Omollo, V.; Mogaka, F.O.; Sesay, F.A.; et al. Doxycycline Prophylaxis to Prevent Sexually Transmitted Infections in Women. N. Engl. J. Med. 2023, 389, 2331–2340. [Google Scholar] [CrossRef] [Scilit]
- Heskin, J.; Dickinson, M.; Brown, N.; Girometti, N.; Feeney, M.; Hardie, J.; Evans, C.; McOwan, A.; Higgs, C.; Basnayake, S.; et al. Rapid reconfiguration of sexual health services in response to UK autochthonous transmission of mpox (monkeypox). Sex. Transm. Infect. 2023, 99, 81–84. [Google Scholar] [CrossRef] [Scilit]
- Frem, J.A.; Russell, A.; Nichols, K.; Buonsenno, L.; Tweed, M.; Fitzpatrick, C.; Darking, M.; Whetham, J.; Richardson, D. PrEP2U: A novel community partnership HIV pre-exposure prophylaxis clinic. Sex. Transm. Infect. 2023, 99, 574. [Google Scholar] [CrossRef] [Scilit]
- Coukan, F.; Thamm, W.; Afolabi, F.; Murray, K.K.; Rathbone, A.P.; Saunders, J.; Atchison, C.; Ward, H. Co-designing interventions with multiple stakeholders to address barriers and promote equitable access to HIV Pre-Exposure Prophylaxis (PrEP) in Black women in England. BMC Public Health 2025, 25, 1831. [Google Scholar] [CrossRef] [Scilit]


| Manuscript | Study Method | Study Characteristics | Healthcare Professionals’ Attitudes | Risk of Bias | Comments |
|---|---|---|---|---|---|
| Park JJ, et al. California, USA (2021) [19] | Cross-sectional study of healthcare professionals using purposive sampling through established provider networks and local community-based clinics | n = 76 responses from healthcare providers with prescribing authority in Southern California. HCP specific data: Doctor of Medicine (67%) or Doctor of Osteopathic Medicine (5%). Nurse practitioners (17%) and physician assistants (8%). 58% had more than 10 years of clinical practice. | 43% of healthcare professionals would agree or strongly agree to prescribe doxyPEP/PrEP to MSM: and if recommended by the CDC, 90% would prescribe doxyPEP 80% of healthcare professionals expressed concerned about drug resistance regarding use of prophylactic antibiotics | High | Recruitment through convenance sampling my indicate recruitment bias. Closed question survey limited data. More information on GBMSM than HCP attitudes, although able to focus on HCP data. Appropriate statistical analysis. |
| Pearson WS, et al. USA (2024) [20] | Cross-sectional survey of healthcare providers. | n = 1504 healthcare professionals, including family physicians (457, 30%), internists (545, 36%), obstetrician/gynecologists (251, 17%), and nurse practitioners/physician assistants (251, 17%). 761 (51%) were STI care providers. | 47% of STI care providers agreed that the benefits of DoxyPEP outweigh the risk of increased antimicrobial resistance (compared to 36.6% of non-STI care providers) (p < 0.01). 64% of STI providers and 62% of non-STI providers agreed or strongly agreed that “prophylactic use of doxycycline contributes to antibiotic resistance” (p = 0.57) | Medium | Study settings and subjects where not discussed in detail. Closed question survey limited data. Cleary defined inclusion criteria. Appropriate statistical analysis. |
| Mogaka FO. Kenya (2025) [21] | Qualitative interviews with Kenyan HIV and STI policy makers, healthcare providers, and HIV-PrEP users | 40 interviews with Kenyan HIV and STI policy makers (n = 7), HCPs involved in HIV-PrEP provision (n = 17), and HIV-PrEP users (n = 16) working within or using services within Kisumu County. | (1) Acceptability: Aware of high burden of STIs amongst HIV-PrEP users. Concerned over pill burden, antimicrobial misuse and antimicrobial resistance. Expressed the need for internationally recognised clinical guidelines. Expressed the need for user/community opinions. (2) Feasibility: Integration into HIV-PrEP services as a low-cost strategy. Concerned about waiting times, workload and prescribing logistics. (3) Sustainability: Concerns regarding ownership, implementation and cost. Awareness and demand creation is crucial, including community involvement (peer educators and advocacy groups). | High | Ethical approval was sought and approved. Small qualitative study of healthcare professionals in Kenya |
| Cornelisse VJ et al., Australia (2024) [22] | Mixed method study from a national committee of stakeholders | n = 49. 9 steering committee members (two co-chairs) and 40 participants from across Australasia. Community representatives, clinicians, researchers and experts in infectious diseases, public health, epidemiology, microbiology, and antimicrobial stewardship, | Consensus agreement that: doxyPEP should be considered primarily for the prevention of syphilis in GBMSM who are at risk of syphilis, although for some individuals the reduction in chlamydia and the lesser reduction of N. gonorrhoeae might be important. Concern expressed regarding driving further N. gonorrhoeae antimicrobial resistance | Medium | One participant withdrew due to concerns about antimicrobial resistance therefore wasn’t represented in the research. Consulted a diverse range of clinical experts in gathering opinions on doxyPEP. Open ended format permitted wide range of exploration of themes. |
| Phillips C et al., UK 2025 [23] | Cross sectional survey of sexually transmitted infection clinic clinicians | n = 52 doctors (n = 20), nurses (n = 28), sexual health advisors (n = 4) | 85% were aware of doxyPEP, median Likert score rating knowledge was 3/5 (where 5 was good, 1 was poor). Clinicians scored median 4/5 on Likert scale that they would be happy to provide doxyPEP (where 5 was happy, 1 not happy). Reduction in STIs, reduced clinical attendances, improved patient self-advocacy as advantages of doxyPEP. Concerns were antibiotic resistance, drug interactions, the impact (increase or decrease) in service demand, and access for women and trans-masculine people. | Medium | Small anonymous quantitative study of sexual health clinicians working in the south of England. |
| Allan-Blitz LT et al., 2025, USA [24] | Cross sectional study of community centre health workers | 14 or 45 health providers completed survey (all prescribers) | Median score of comfort having conversations about doxyPEP increased from 78 (interquartile range, 52–100) out of 100 after the second training to 100 (interquartile range, 88–100) after the third training. Barriers were sufficient time, lack of electronic record resources, lack of guidelines, concerns re antimicrobial resistance | medium | Small mixed method (patients and healthcare workers) cross-sectional analysis |
| Imerlishvili E et al., 2025, USA [25] | Cross sectional online survey of clinical providers | 91 out of 575 clinical providers responded. | Reported willingness to recommend doxyPEP (98%, 77%, and 67% for chlamydia, syphilis, and gonorrhea, respectively); preferred doxyPEP administration for MSM and transgender populations; believed recurring bacterial STIs (88%) and reported condomless sex (85%) were the most important characteristics to consider for recommending doxyPEP; and were concerned about antibiotic resistance (90%) (primarily for Neisseria gonorrhoeae). Insurance costs were the most perceived community-associated barriers (35%). | Low | Large (90) cross-sectional online survey |
| Perkins RC. Washington, USA 2025 [26] | Qualitative interviews of healthcare professionals known to be advocates of sexual health | n = 30 HCPs completed interviews. 43% of HCPs reported working with GBMSM. 47% were 31–40 years old, 53% identified as male, and 47% reported their sexual orientation as gay or queer. | (1) doxyPEP provides another tool to prevent STIs (2) Concerns about prescribing doxy-PEP as a strategy for STI prevention, including antibiotic resistance (3) Need for more data to understand the long-term safety of doxyPEP (4) Development of doxyPEP guidelines to facilitate and motivate prescriptive practices and inform implementation. | Medium | Limited opinions from Black and Hispanic HCP. No evidence of potential influence of researcher bias. HCP’s asked had previous experience of prescribing HIV-PrEP so may have bias towards prescribing doxyPEP. Good congruity between research methodology and research objectives. |
| Providing doxyPEP to MSM | Recognition of the high burden of bacterial STIs in MSM |
| DoxyPEP should be available to MSM to reduce syphilis (and to a lesser extent C. trachomatis and N. gonorrhoeae) | |
| Willingness to provide doxyPEP with the support of national guidelines | |
| Implementation of doxyPEP into existing HIV-PrEP services should be feasible | |
| Awareness and knowledge of doxyPEP needs to improve amongst STI clinicians | |
| Concerns about doxyPEP | Concerns regarding antimicrobial resistance and drug interactions |
| Concerns regarding pill burden, cost, implementation logistics, clinic service demand | |
| Research and access for other groups (trans people and cis-gendered women) | |
| Need for patient involvement in doxyPEP implementation |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Spence, M.; Fowler, C.; Absalom, S.; Roper, T.; Williams, D.; Richardson, D. Healthcare Professionals’ Beliefs and Concerns About the Use of Doxycycline Post-Exposure Prophylaxis (doxyPEP): A Systematic Review. Venereology 2026, 5, 9. https://doi.org/10.3390/venereology5010009
Spence M, Fowler C, Absalom S, Roper T, Williams D, Richardson D. Healthcare Professionals’ Beliefs and Concerns About the Use of Doxycycline Post-Exposure Prophylaxis (doxyPEP): A Systematic Review. Venereology. 2026; 5(1):9. https://doi.org/10.3390/venereology5010009
Chicago/Turabian StyleSpence, Molly, Clare Fowler, Saxon Absalom, Tom Roper, Deborah Williams, and Daniel Richardson. 2026. "Healthcare Professionals’ Beliefs and Concerns About the Use of Doxycycline Post-Exposure Prophylaxis (doxyPEP): A Systematic Review" Venereology 5, no. 1: 9. https://doi.org/10.3390/venereology5010009
APA StyleSpence, M., Fowler, C., Absalom, S., Roper, T., Williams, D., & Richardson, D. (2026). Healthcare Professionals’ Beliefs and Concerns About the Use of Doxycycline Post-Exposure Prophylaxis (doxyPEP): A Systematic Review. Venereology, 5(1), 9. https://doi.org/10.3390/venereology5010009