


Abstract
Accessing the built environment poses many challenges for people with disabilities, severely affecting their independence and quality of life. A panel of experts with a lived experience of disabilities co-designed a survey capturing the challenges in New Zealand’s public places. There were 319 survey respondents with impairments related to mobility (66.5%), vision (18.8%), hearing (5.0%), sensory processing and cognition (8.8%). They perceived sports stadiums as the least accessible venue, followed by bars, boutique shops and public toilets. The most accessible venues were supermarkets, libraries and shopping malls. The type of disability affected the main accessibility challenges. Significant outdoor barriers included uneven and cluttered paths, inadequate provision of curb cuts, seating and accessible parking spaces, and obscure wayfinding. Entrance barriers included heavy doors, complex access control, remote ramps and narrow, obscure entrances. Interior problems included cluttered paths and poor signage. The top priorities for improvement were simplifying layouts, keeping paths clear, and providing clear, inclusive signage, communication and assistance for people with varying impairments. Providing lower counters, better colour contrast, hearing loop facilities and better control of lighting and acoustics also improve accessibility. This research contributes novel experiential data from people with disabilities that is critical to achieving an inclusive built environment.
1. Introduction
The World Health Organization estimates that 16% of the world’s population identify as people with disabilities [1]. In New Zealand 17% of the population are people with disabilities, with 35% of this cohort aged 65 and older [2]. New Zealand is a signatory to the United Nations Convention on the Rights of People with Disability [3] and, as such has a commitment to meeting the United Nations sustainable development goals (SDGs). Sustainable cities and communities (SDG 11) require the built environment to be inclusive and accessible to everyone [4]. However, this requirement is not met, either in New Zealand or globally; accessibility of public buildings and spaces remains challenging for people with disabilities and application and enforcement of the principles of Universal Design is limited [5,6]. The consequences of poor accessibility are profound; people with disabilities experience social exclusion, isolation, depression and poorer health, all of which equate to a diminished quality of life. The number of people with disabilities and the correlation between ageing and developing a disability means that it will impact most people (either directly or indirectly), so the problem of poor accessibility needs to be addressed.
Providing inclusive accessibility in the built environment is complex for two main reasons. Firstly, the many different types of disabilities place different, and sometimes conflicting, requirements on the optimal design [7]. For example, a person with vision impairment prefers an environment with bright lighting and clear colour contrast which may be very challenging for a person with sensory impairment. Secondly, researchers tend to focus on one area of the problem and fail to view the problem holistically. Three such areas (discussed in [8]) are studies on the main barriers to inclusive accessibility for single types of disability, studies reporting accessibility of specific building types measured by audit tools or customised checklists [9,10,11], and studies looking at accessibility legislation. In New Zealand, the legislation governing the built environment consists of the Building Act 2004, the New Zealand Building Code and the New Zealand Standard NZS 4121:2001 Design for access and mobility—buildings and associated facilities [12]. Compliance is mandatory for all buildings, but ambiguous specifications and recommendations coupled with lack of enforcement mean that many accessibility problems exist [13]. A synthesis of the literature in these areas is provided in Table 1.
Table 1.
Synthesis of literature on accessibility in the built environment for people with disabilities.
Aside from focusing on one area, researchers frequently fail to use input from people living with disabilities and produce solutions that theoretically improve access (for example, by complying with legislation) but that in practice fail the end-users [5]. The lack of studies that capture the lived experience of people with disabilities in accessing the overall built environment, including both public buildings and their surrounds, is the research gap addressed in this study.
The aim of this work was to use an online survey of a representative sample of New Zealand residents with different disabilities and the guidance of a panel of experts (people with a lived experience of many different disabilities) to capture their difficulties accessing New Zealand’s public built environment. The research objectives were:
- To rank different types of public spaces (buildings and their surrounds) by perceived ease of access for people with widely varying disabilities;
- To determine the effect of different types of disabilities on the perceived main barriers (a) outside buildings, (b) at the entrance to buildings and, (c) inside buildings;
- To identify the top priorities for improving inclusive access to the built environment.
The limitation of the research is that the survey was restricted to only adults (people aged 18 or older) with disabilities, excluding the opinions of children and carers. This restriction was imposed by the human ethics committee reviewing the research because of concerns that the opinions of carers might not accurately reflect the experience of people with first-hand experience of disabilities. A further limitation is that the survey responses were primarily from people with physical impairments, so few inferences can be made for people with sensory, cognitive and neurodiverse impairments.
The findings identify and prioritise the main barriers for accessing New Zealand’s public spaces, as perceived by people with many different disabilities and widely varying demographics (such as age, income, health status, etc.). This end-user view, based on a broad sample, is useful for construction practitioners, city planners and government stakeholders in achieving real improvements in inclusive accessibility in the built environment for all people with disabilities.
2. Materials and Methods
The research reported here is part of a larger research project reported in [50]. It was approved by Massey University’s Human Ethics Committee Ohu Matatika 1 (ID OM1 24/20).
An Accessibility Partnership Panel (APP) was convened, having seven members with expertise in impairments related to cognition, sensory, neural, mobility, vision and hearing. Panel members were chosen through purposive sampling; organisations supporting people with disabilities and individuals living with disabilities and being active advocates were invited to participate both in nominating panel members and in advertising the survey on their social media platforms. Final selection of APP members aimed to capture people with the widest range of disability expertise. The panel and researchers co-designed survey questions in an iterative process beginning with APP members giving their perspectives on the different types of public places that should be included (independent of whether or not the APP members visited them) and the common access-related problems they encountered. The building types were chosen to represent common public places in the built environment that everyone should be able to access. The researchers used this information and their review of the literature to draft initial survey questions on the experience of people with disabilities in accessing public places. Feedback from the APP members was then used to modify the questions. The survey was administered using Qualtrics XM software(September 2024) for the online version, together with hard copy and phone survey options. Prior to activating the survey, the online and hard copy versions were checked by the APP members for functionality, and for compatibility with screen reader software (JAWS 2023 for Windows; SuperNova 2022; and VoiceOver for Apple devices) to accommodate individuals with vision impairment. New Zealand organisations associated with people with disabilities were asked to announce the survey on their social media platforms. They were given an information sheet describing the research purpose and the options available for completing the survey, namely online, in hard copy or by phone, the latter to assist people with cognitive and/or sensory disabilities in understanding questions, providing responses, and navigating the survey. The inclusion criteria to complete the survey were:
- The respondent lived anywhere in New Zealand;
- The respondent lived with a disability of any type or types, including but not limited to their mobility, vision, hearing, age, cognition, and sensory abilities;
- The respondent visited any public buildings or spaces regularly, for example, monthly—this criterion excluded people who mostly remained in residences and medical facilities;
- The respondent was eighteen years or older—people under the age of eighteen and carers were excluded from the survey as a condition imposed by the university’s ethics committee.
Every respondent gave their consent for the use of survey data in research publications. Survey responses were collected from September to November 2024.
The number of people with disabilities in New Zealand is 17% or 851,000 people [2]. For a confidence level of 95% that the real value is within +/−5% of the measured/surveyed value, statistical power analysis estimated the target number of responses to be 217 [51]. This target was exceeded; 319 valid survey responses were collected. Power analysis by disability type was not attempted because the country’s population for each disability type is not known and because twenty-eight participants experienced two or more different disabilities.
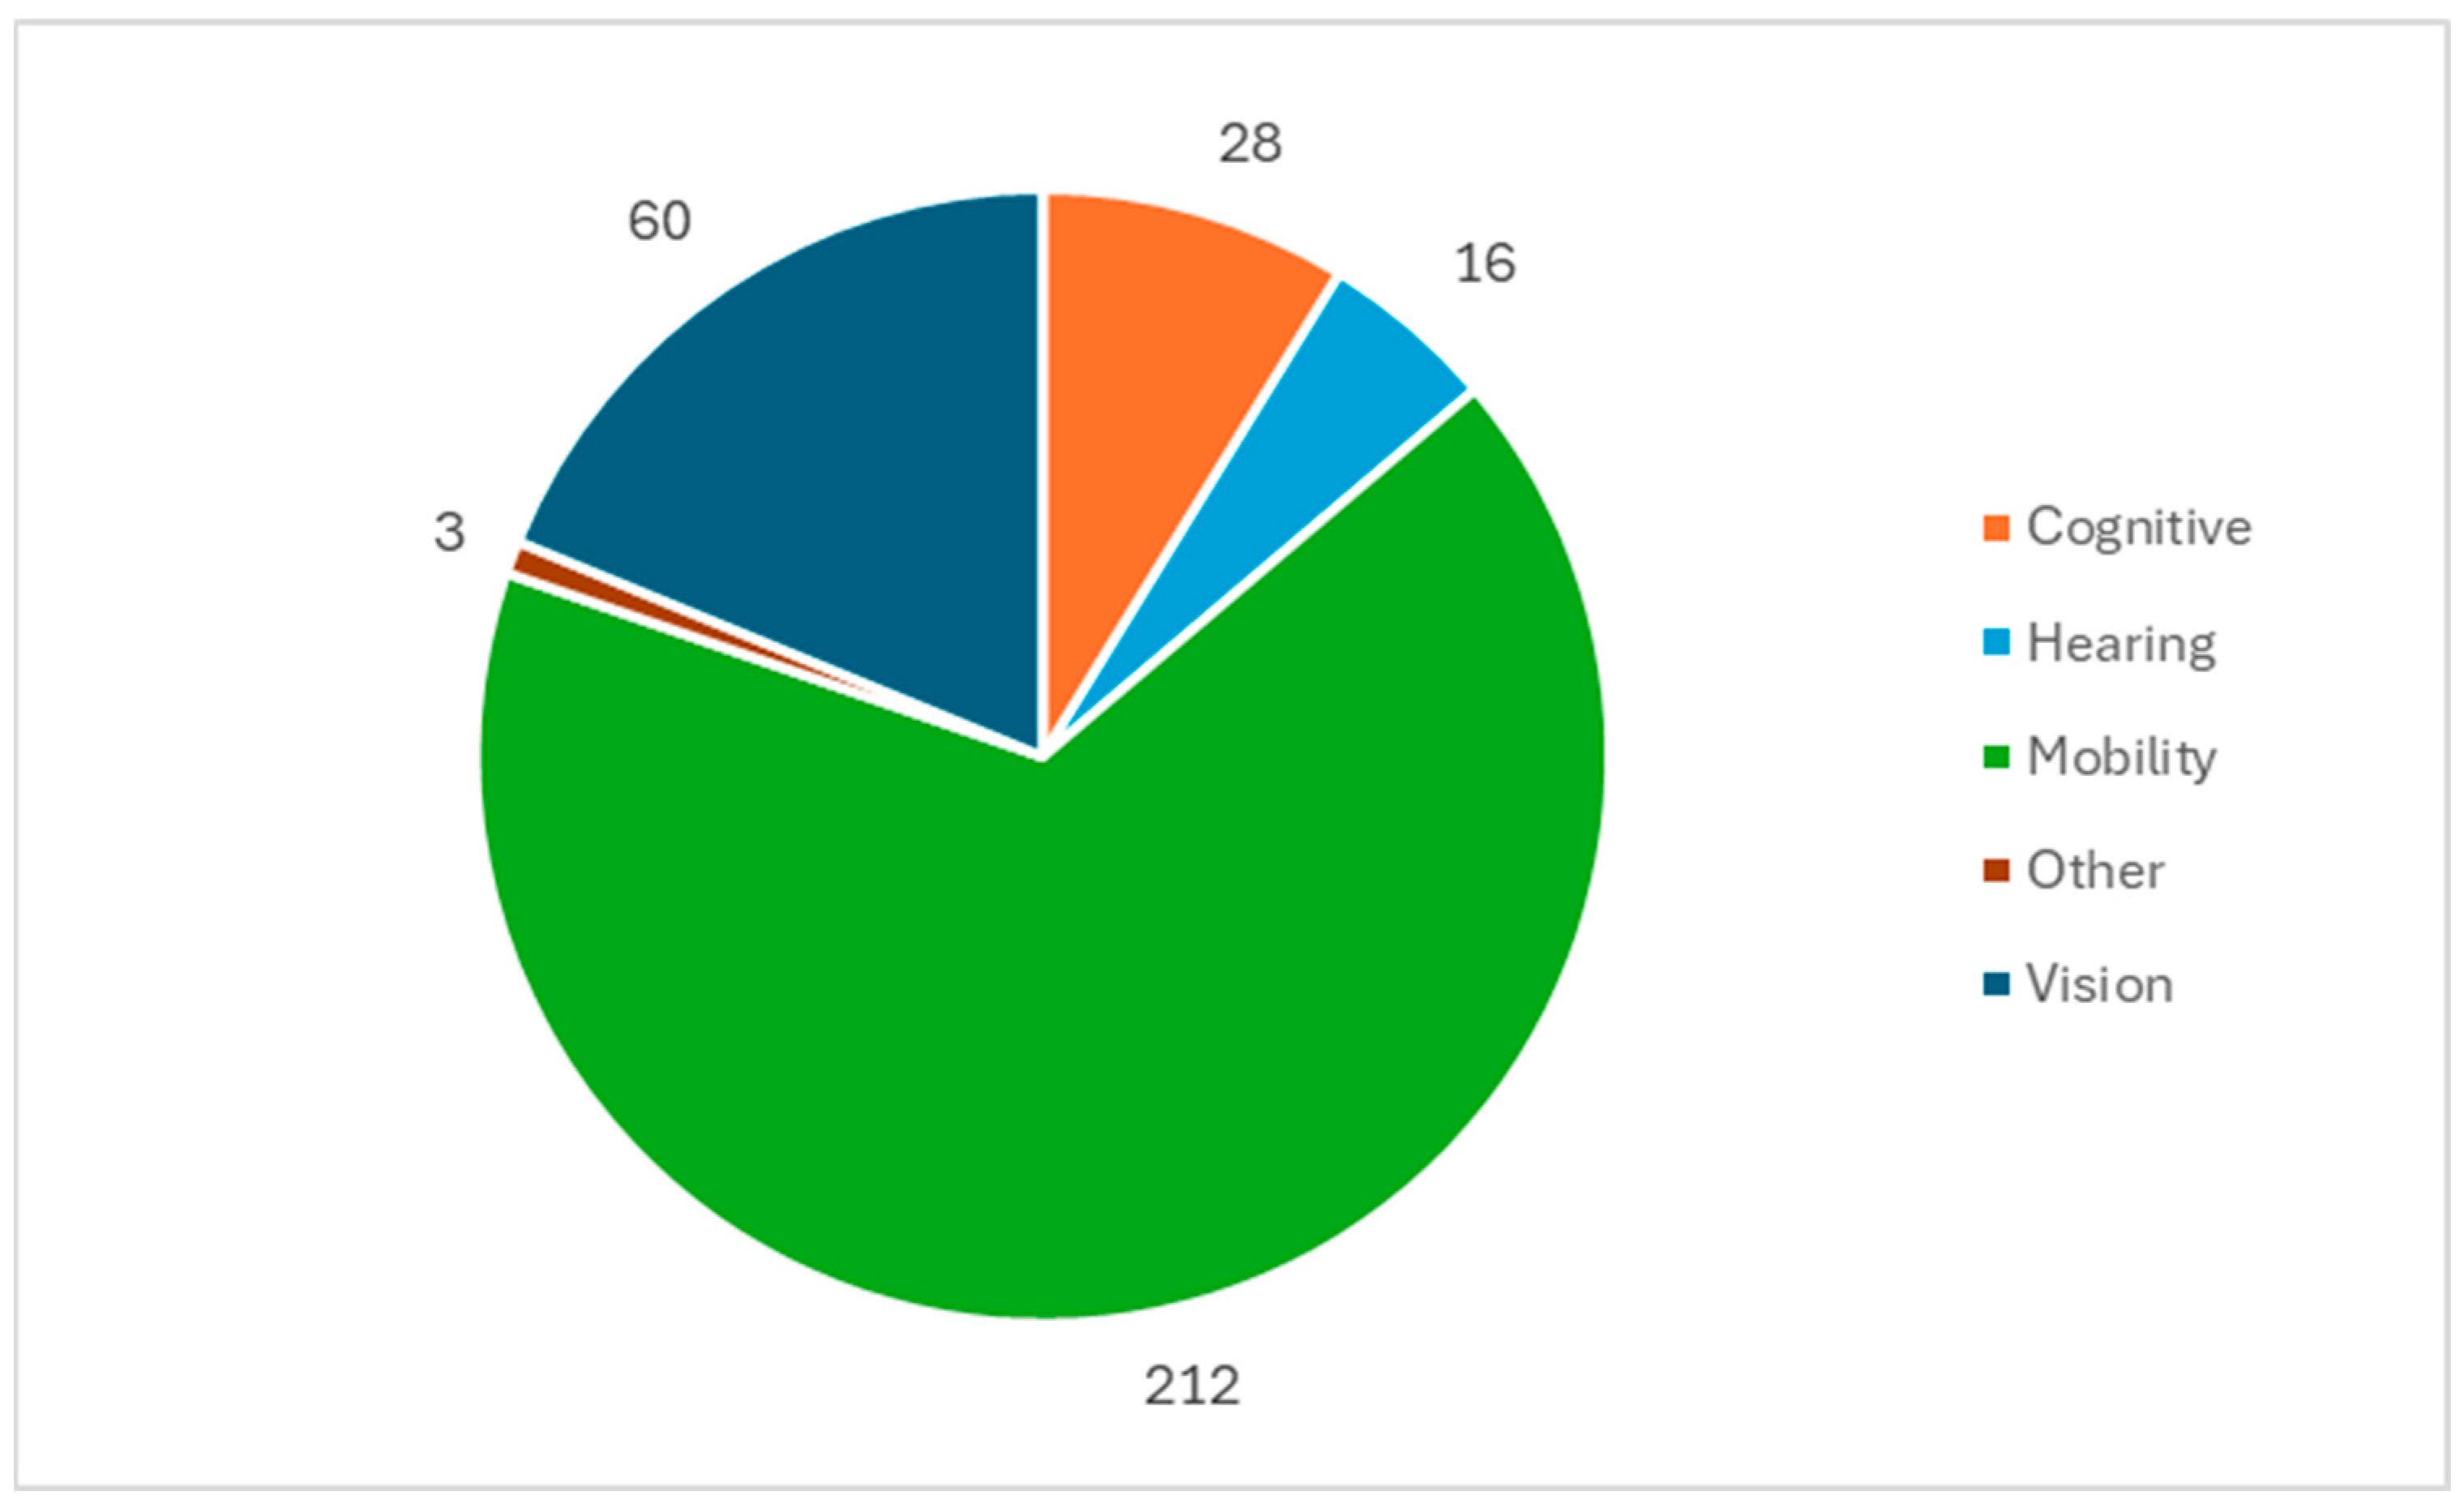
Figure 1 shows the types of impairment of the survey respondents. Where a respondent had more than one type of impairment, their perceived main impairment type was used.
Figure 1.
Type of impairment of respondents (N = 319).
The most common types of impairment are mobility (66.5% of respondents) and vision (18.8% of respondents). A total of 16 (5.0%) of the respondents reported hearing impairment and the remaining 28 (8.8%) experienced a variety of impairments such as sensory processing disorder (SPD), auditory processing disorder (APD), autism, dyslexia, schizophrenia, depression, anxiety, and trauma which were loosely categorised as “cognitive/sensory” impairment. Three respondents (0.9%) did not identify their type of disability and were categorised as “Other”.
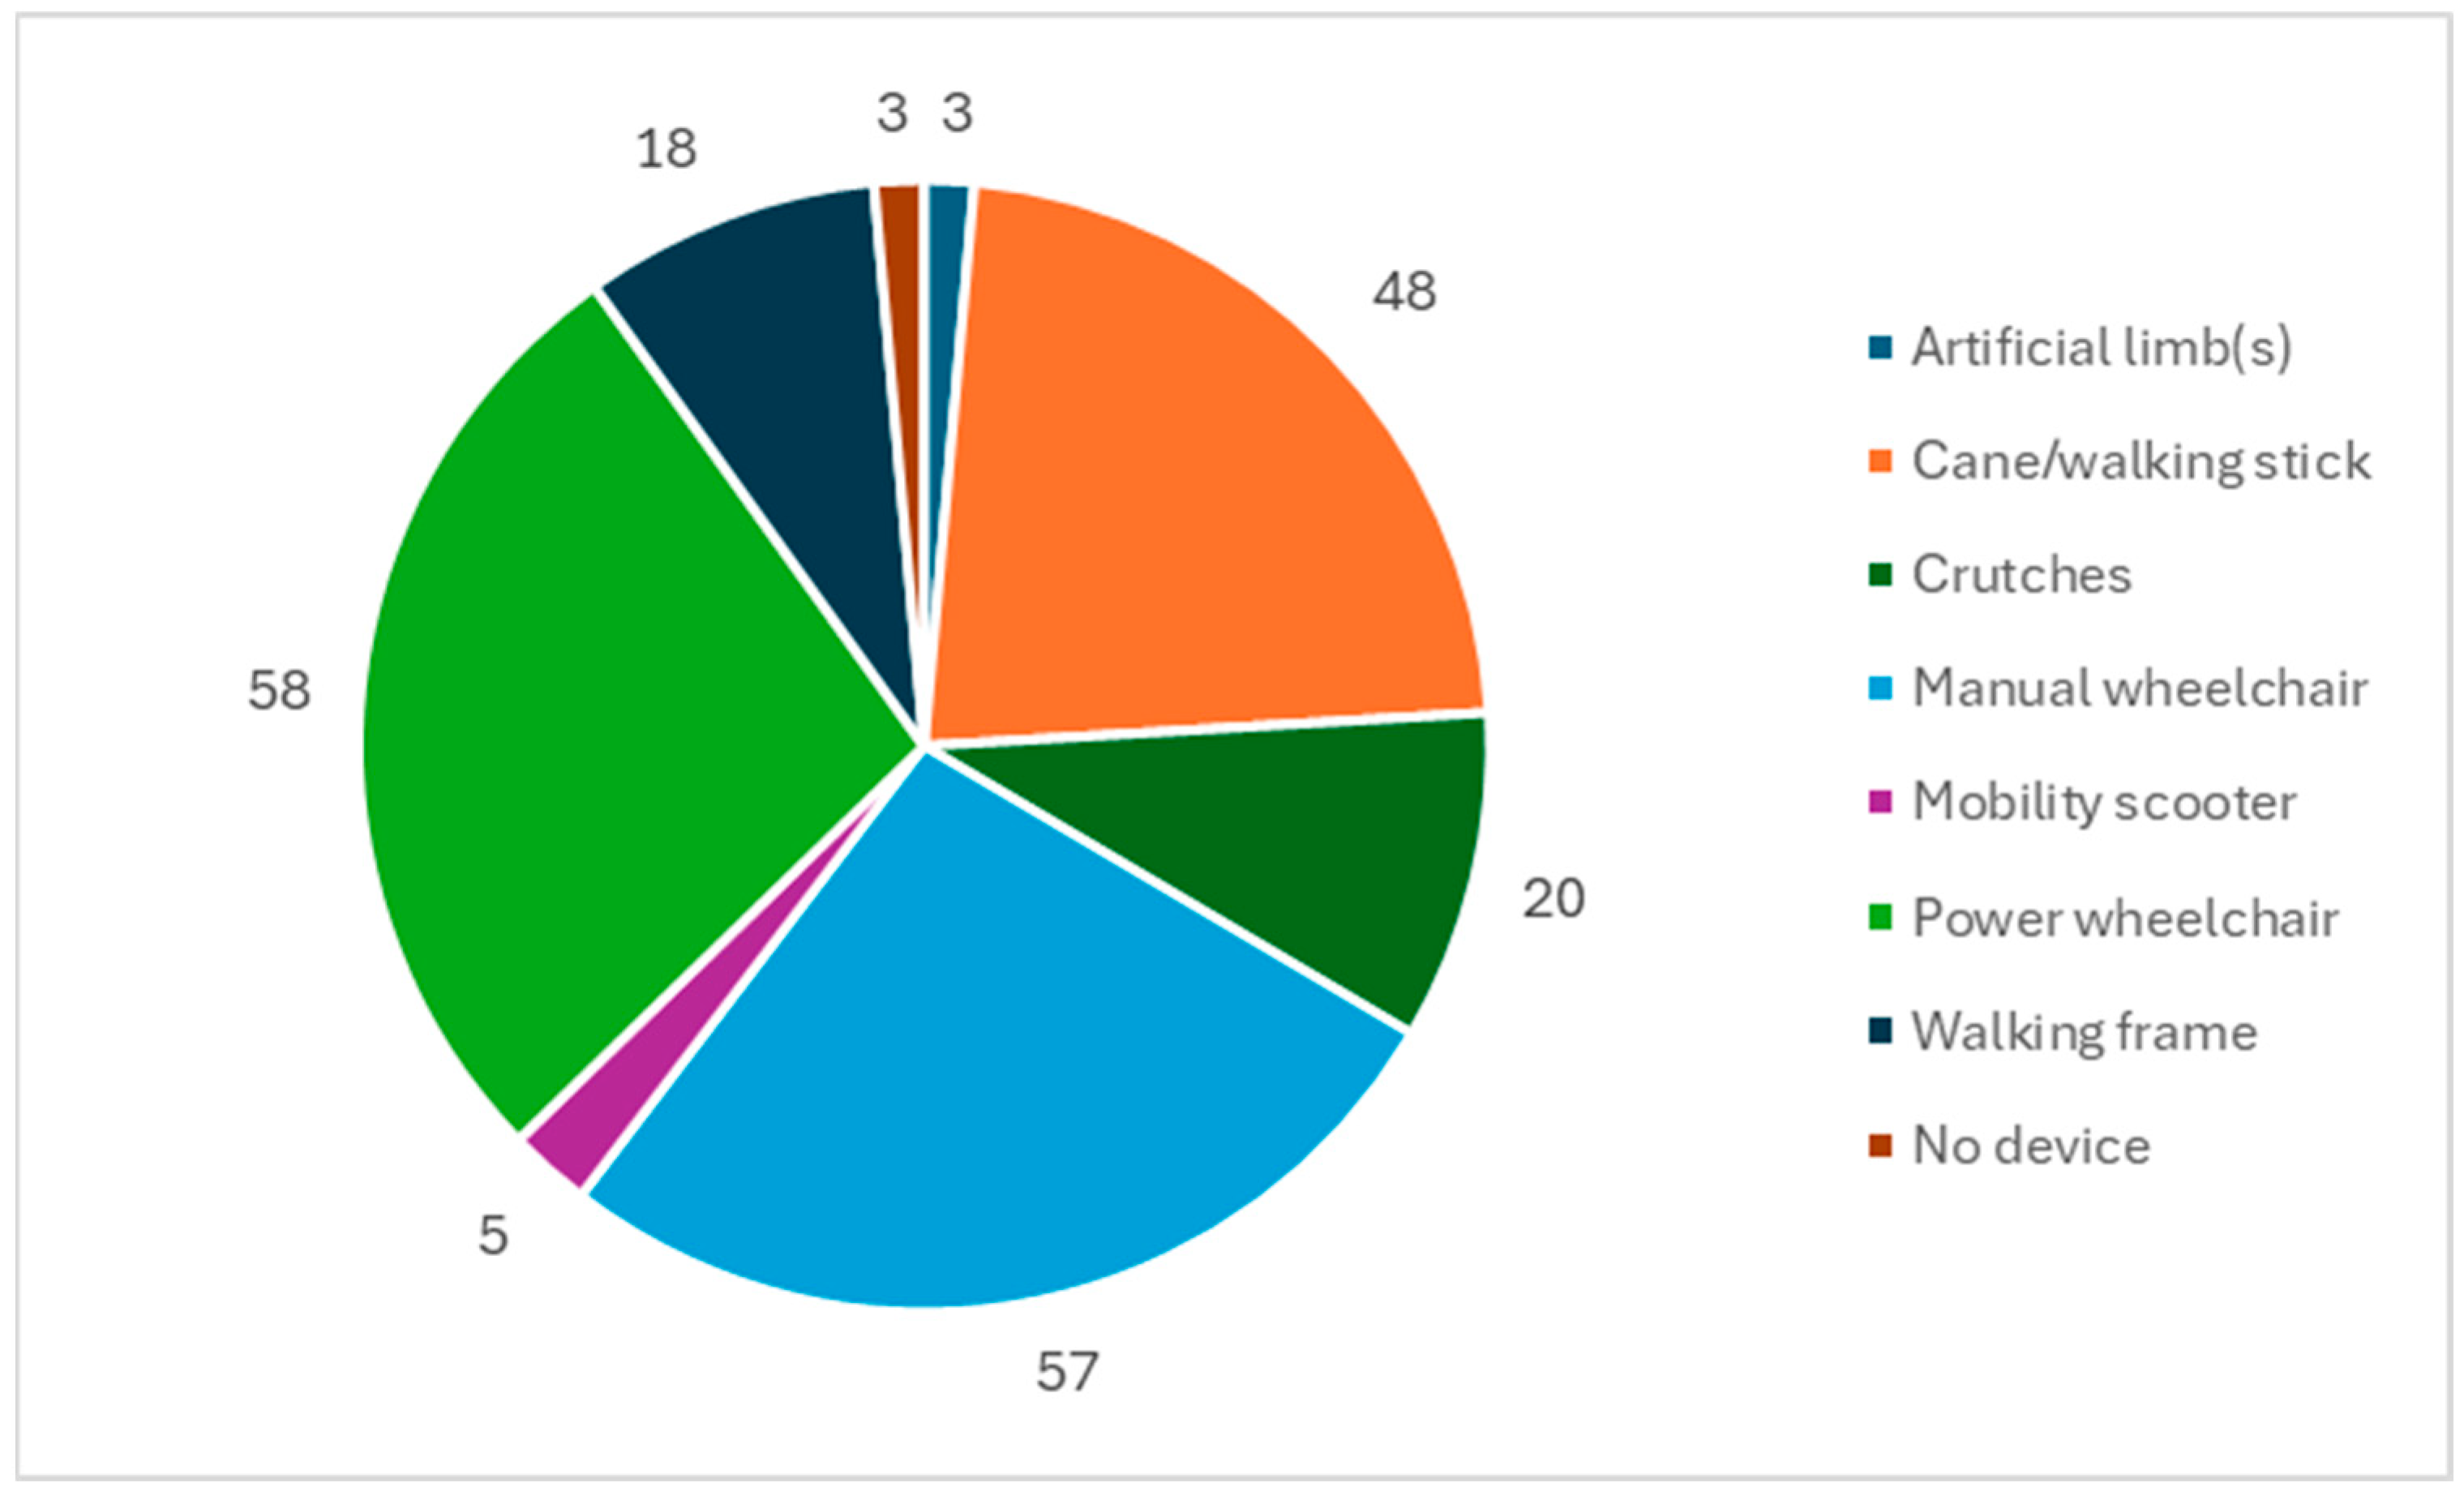
Figure 2 shows the range of assistive devices used by the 212 respondents with mobility impairment.
Figure 2.
Type of assistive device for respondents with mobility impairment (N = 212).
Respondents with mobility impairment were predominantly wheelchair users (54%), with approximately equal numbers using mobility scooters and manual wheelchairs. The next most common assistive device was a cane/walking stick.
The survey collected data on the following:
- Ease of access of 29 different types of public buildings or spaces (Table 2) using a 5-point Likert scale where 5 is Very Hard; 4 is Hard; 3 is Ok; 2 is Easy; and 1 is Very Easy. Respondents could choose an additional option: “I do not go there”.Table 2. Types of public buildings or spaces considered in the survey.
- Open-ended responses to the most challenging aspect outside or around buildings.
- Open-ended responses to the most challenging aspect of the building entrance.
- Open-ended responses to the most challenging aspect inside the building.
- Open-ended responses on the top priority for improving access to the built environment.
The open-ended response data were manually examined to remove nonvalid responses and arranged within common themes, with a simple count of comments in each theme. The survey results are presented in the following section.
3. Results
This section reports the respondent demographics, survey responses relating to difficulty accessing different types of public buildings and spaces, significant barriers outside, at the entrance and inside buildings and the priorities for improving the access experience.
3.1. Demographics of the Respondents
Aside from the disability type discussed in Section 2, the survey collected demographic information on age, gender, ethnicity, gross income, work status, living situation and health status. Overall, 55% of respondents were female, 32% were male and the remainder did not identify their gender. Respondents were primarily European (74%), Māori (9%) and other ethnicities (such as African, Pacific Islander, and Asian). Of the 280 respondents who reported their living situation, 65% lived with family or friends, 32% lived alone and 3% lived in residential care facilities. Table 3 summarises the remaining demographics, namely, age, gross income, work status and health status.
Table 3.
Demographics of the survey respondents with number of respondents (N).
Of the respondents, 78% were 25 to 64 years old. There was a fairly even distribution of income, work status and health status across all respondents. However, as mentioned in Section 2, most (66.5%) respondents reported mobility impairment, followed by vision impairment (18.8%) and hearing impairment (5.0%). People with impairments related to sensory and cognitive conditions may find surveys too challenging unless additional efforts are made to increase their participation [52].
3.2. Ranking Different Types of Public Buildings by Difficulty of Access (Research Objective One)
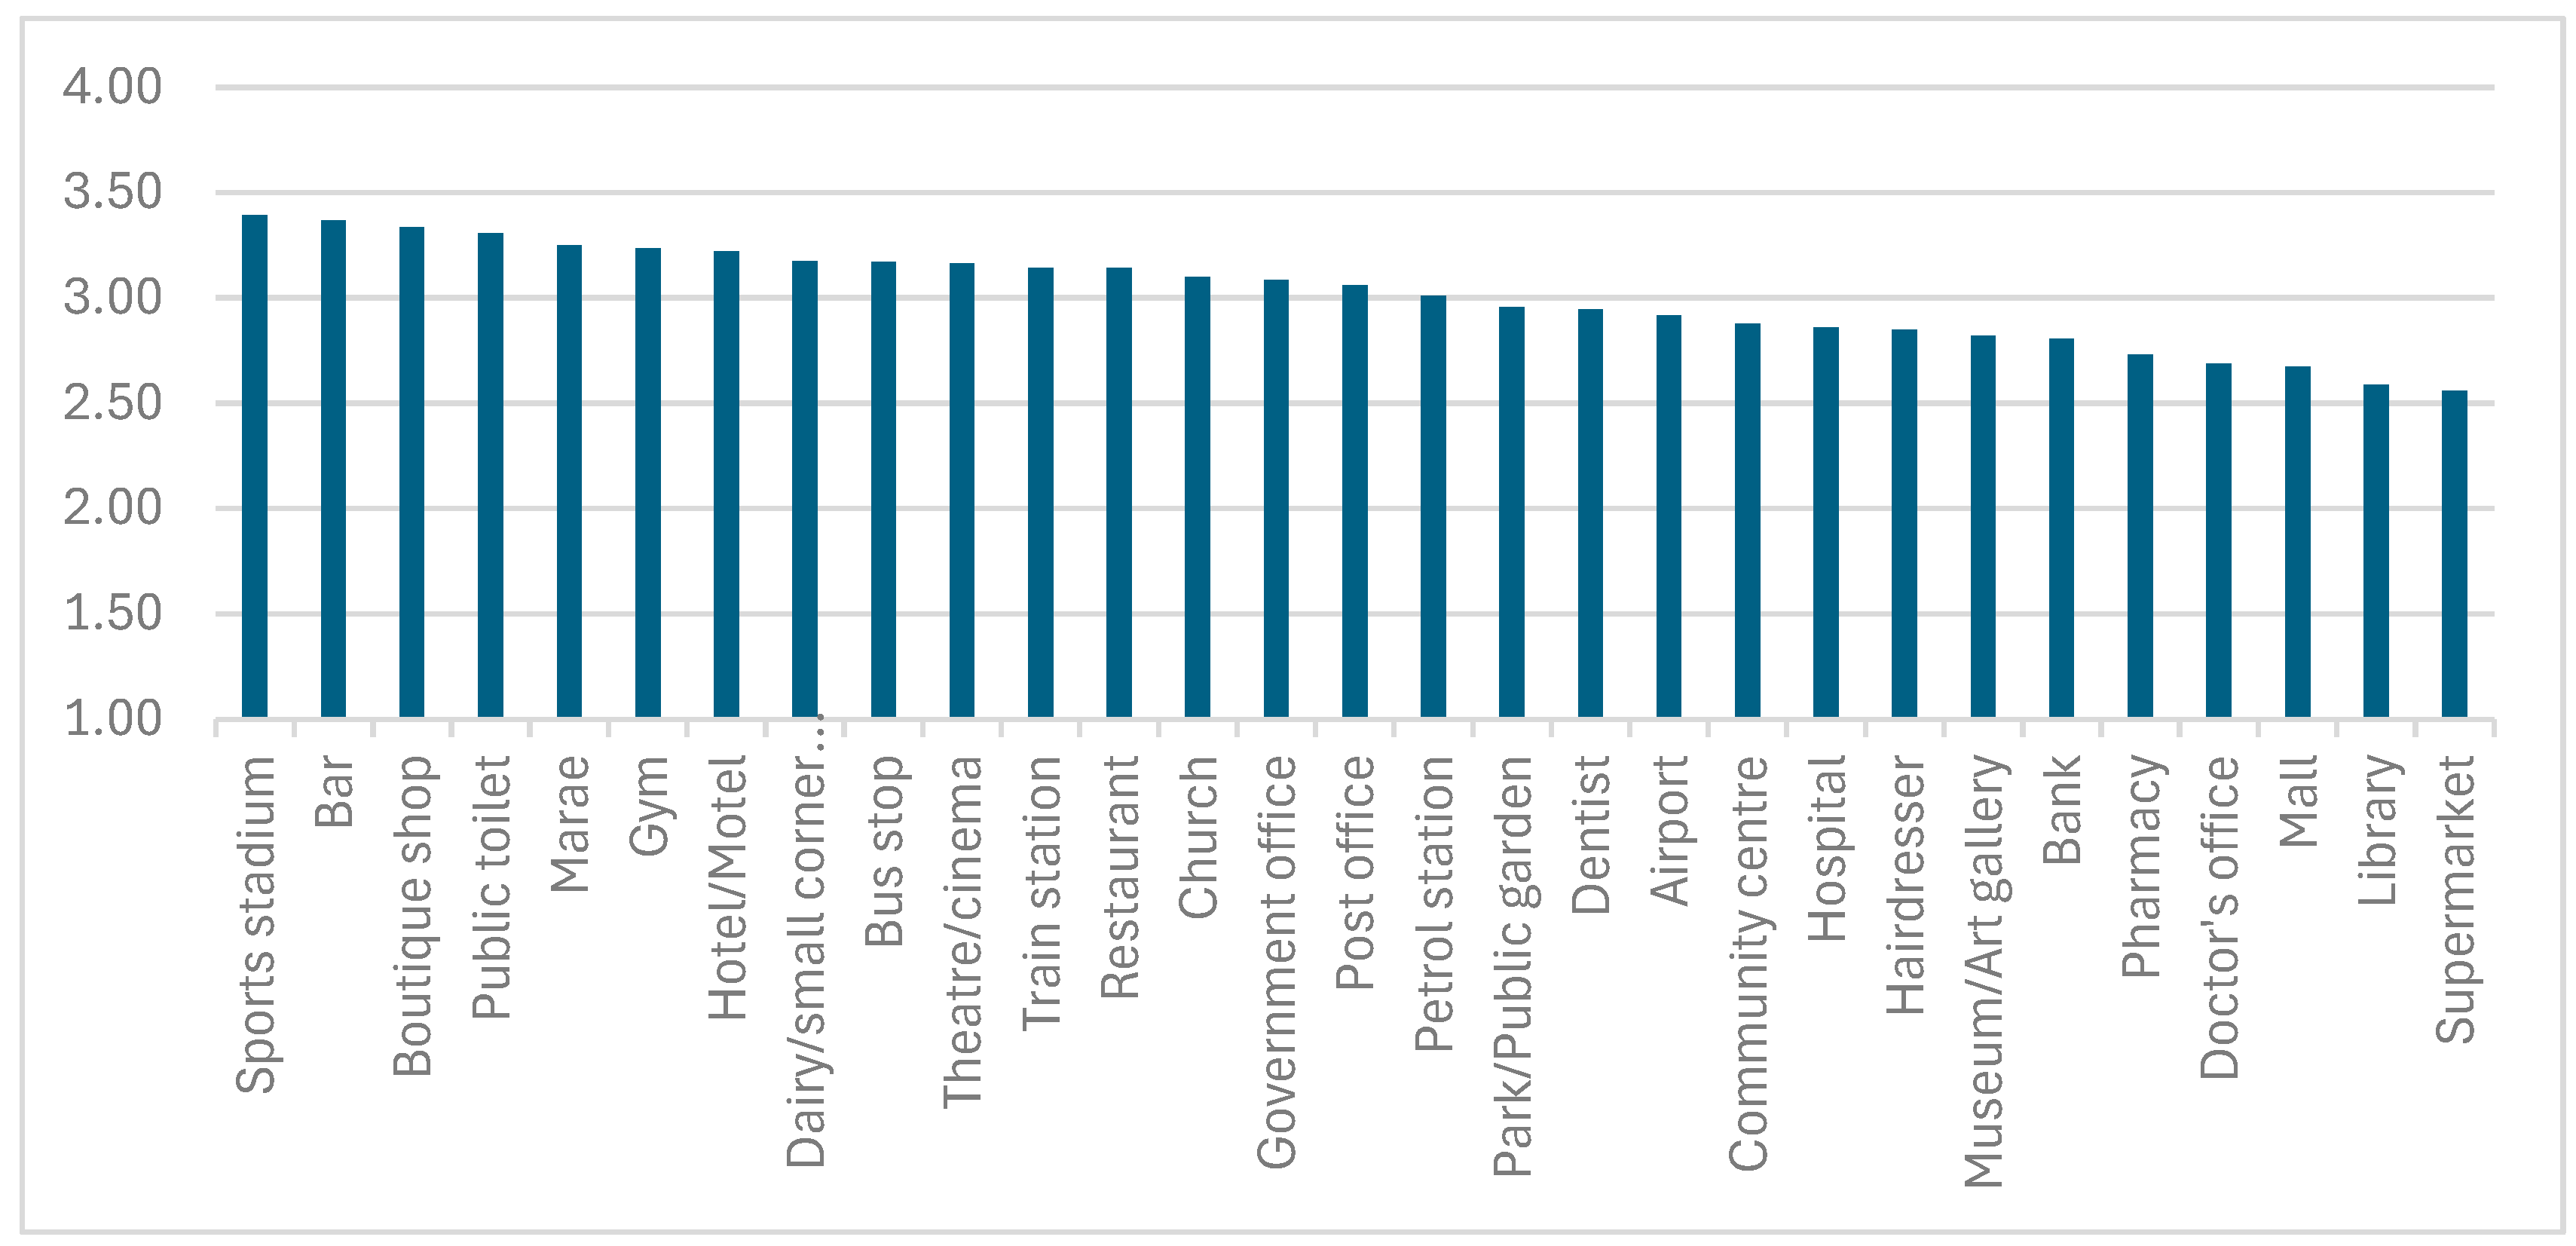
Figure 3 shows the perceived difficulty in accessing different types of public buildings ranked by all respondents from most difficult (sports stadium) to least difficult (supermarket), expressed on the 5-point Likert scale.
Figure 3.
Ranking of perceived accessibility of different building types from hardest to easiest.
The ten least accessible building types are, in order of difficulty: sports stadiums, bars, boutique shops, public toilets, maraes (Māori community places), gyms, motels/hotels, dairies/small corner shops, bus stops, and theatres/cinemas. The most accessible places are supermarkets, followed by libraries, shopping malls, doctor’s offices and pharmacies.
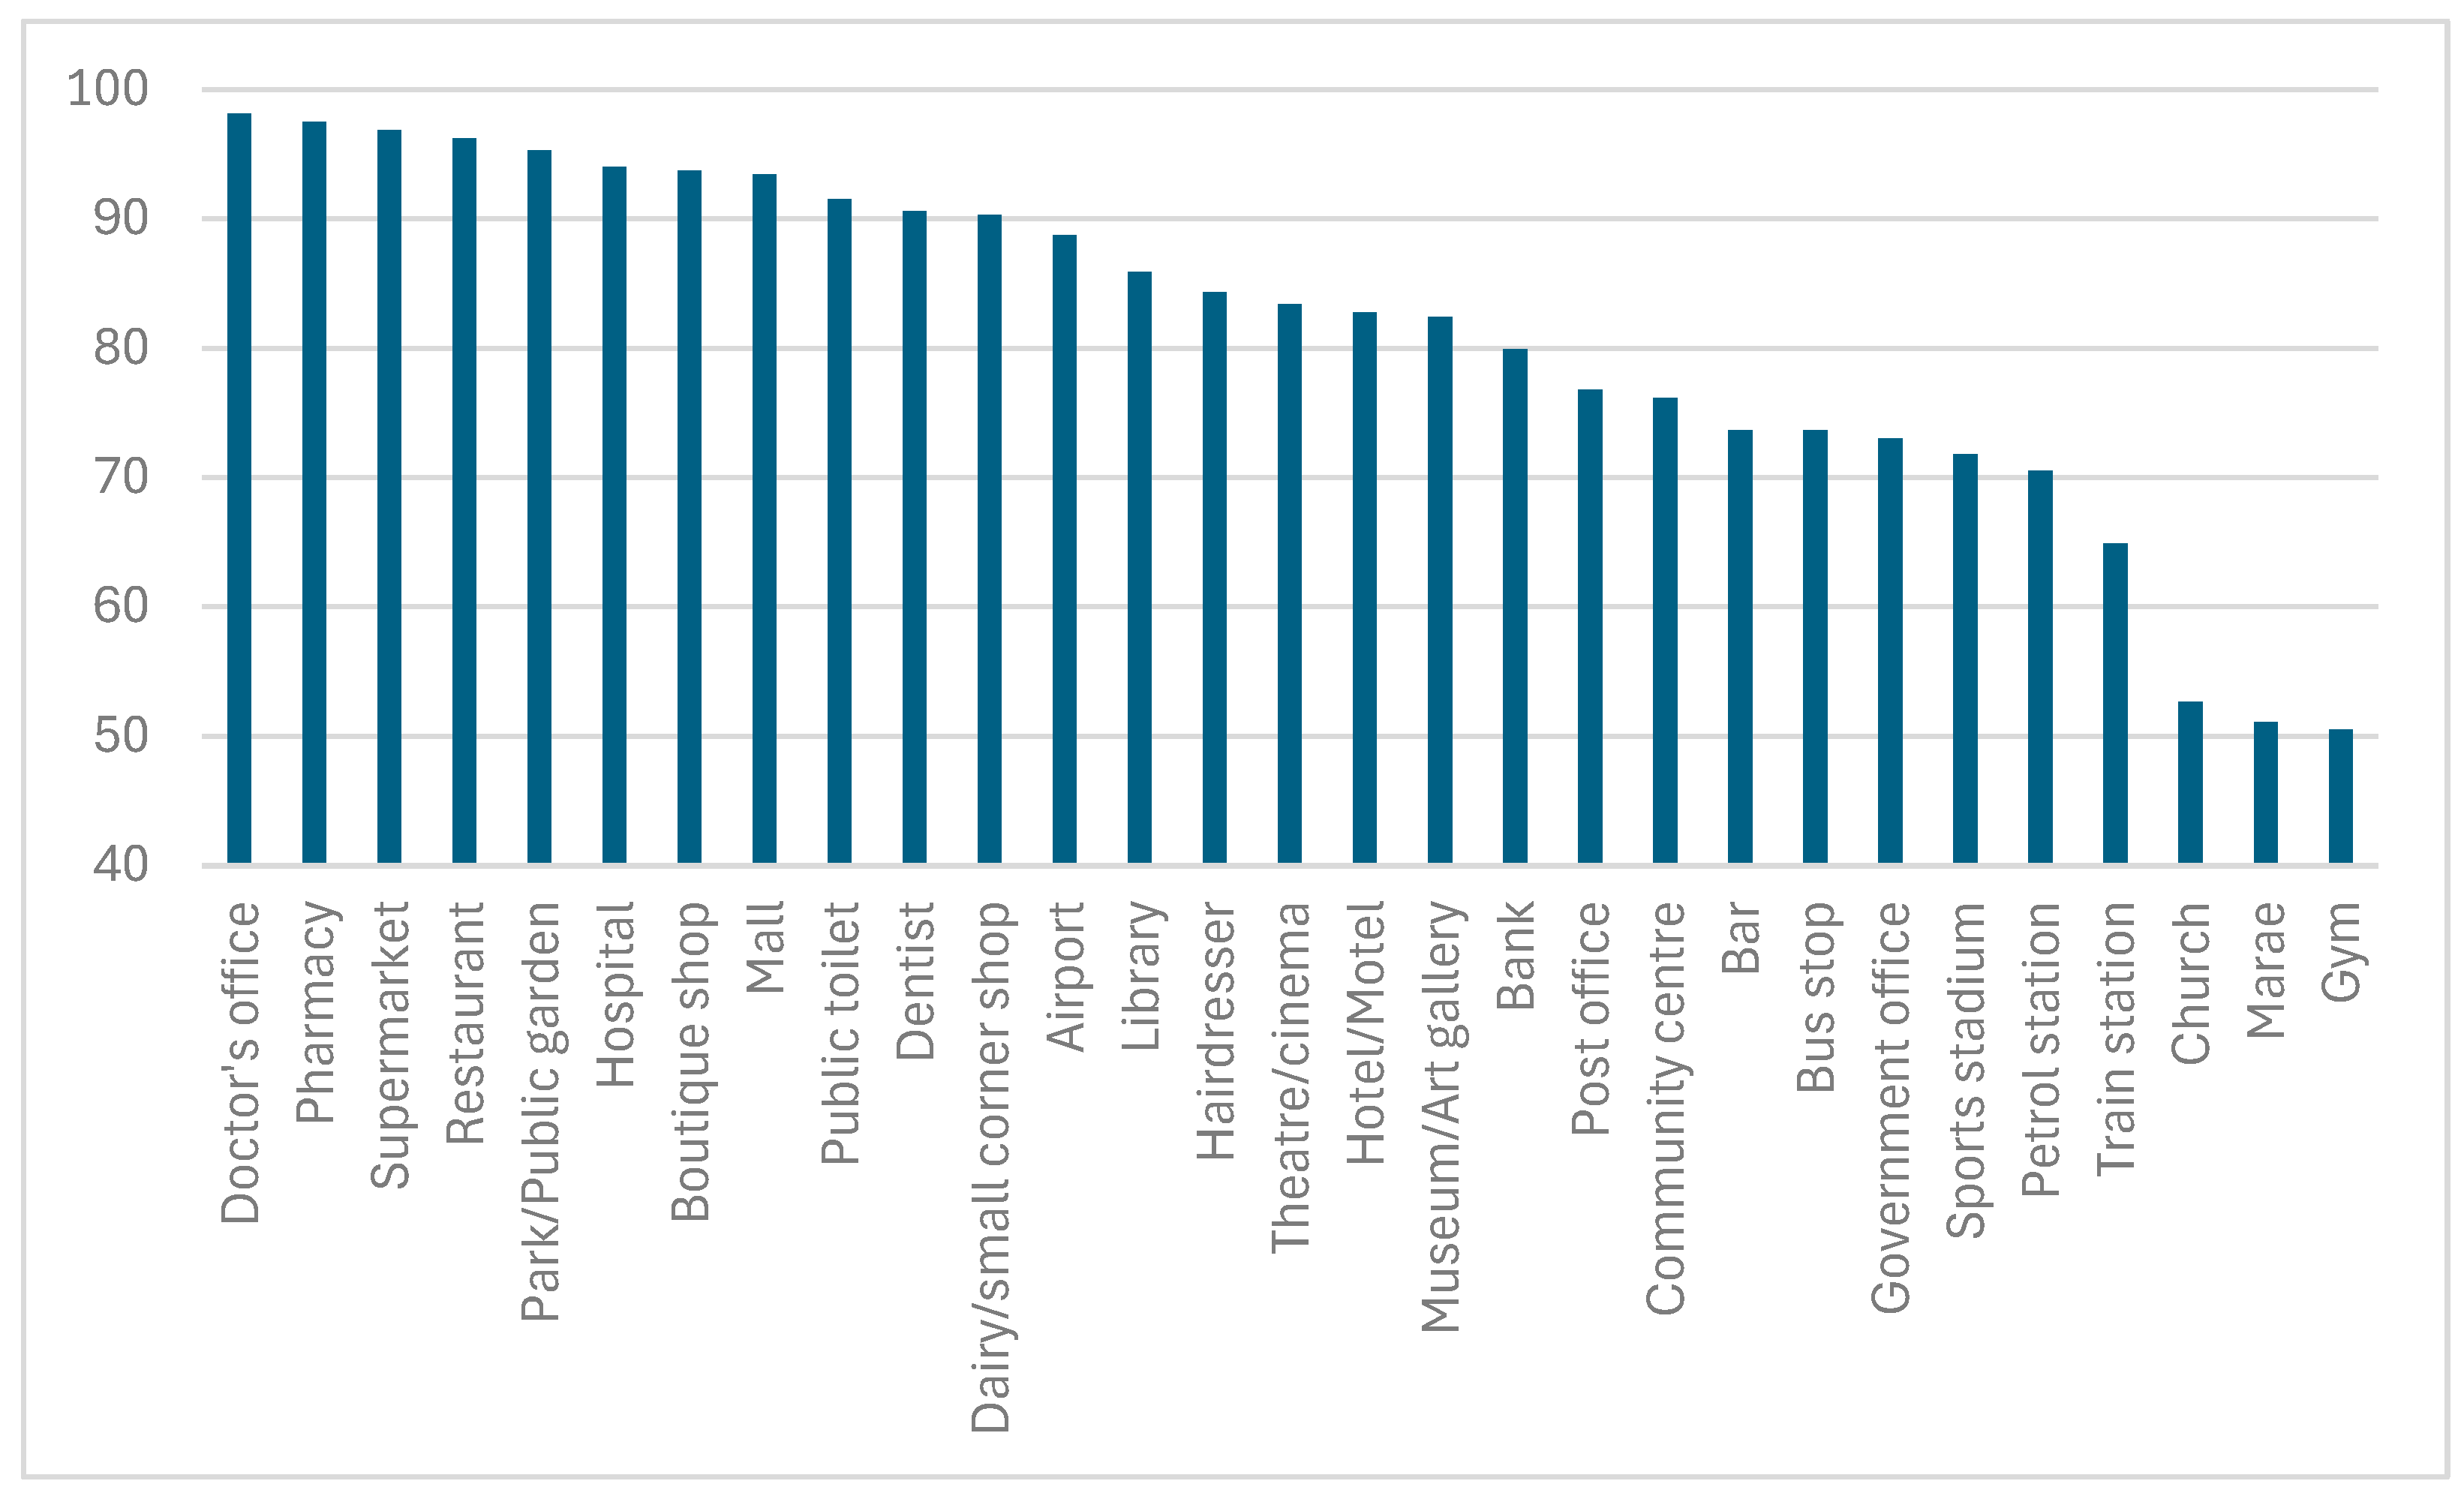
The number of respondents varied for each building type because the survey offered an additional response of “I do not go there”. Figure 4 shows the percentage of respondents who did access each type of building. The survey did not investigate the frequency of access to the different types of spaces. People visit certain places, such as supermarkets, more frequently than others, for example, airports and sports stadiums. Frequent access to particular types of spaces might make the person more familiar with that environment and lead to them having a perception of a more accessible space.
Figure 4.
Percentage of respondents accessing the different types of building.
Only about half of the respondents visited gyms, churches and maraes but this could either be from personal choice or from perceived access difficulty.
An important distinction needs to be made between the results reported here and published studies on accessibility for a single building type (such as those listed in Table 1). The latter research considers factors such as the location, age and condition of the building since these affect accessibility. For example, new buildings and buildings that have been recently renovated are generally more accessible. In the research reported here, these factors are not considered since the aim is to capture the perception of average accessibility of different types of public spaces over all locations, ages and conditions. The survey participants (people with different disabilities) live anywhere in New Zealand and are not usually aware of the age or renovation status of the public spaces.
3.3. Accessibility Challenges for People with Mobility Impairments
The cohort of people with mobility impairment numbered 212 and wheelchairs were the most commonly used assistive device, followed by walking sticks (Figure 2). Their perceived main barriers in accessing public buildings are discussed in Section 3.3.1 and Section 3.3.2 presents the respondents’ priorities for improving their access.
3.3.1. Main Barriers Outside, at the Entrance and Inside Buildings (For People with Mobility Impairment)
Respondents reported their main barriers outside, at the entrance and inside the buildings (Table 4, Table 5 and Table 6, respectively). They could report multiple barriers, so the number of comments varies. The number of responses (N), the number of comments (C) and the percentage of comments related to each type of barrier are stated. Barriers that were mentioned in fewer than 10% of the comments are categorised as “Other”.
Table 4.
Ranking by people with mobility impairment of barriers outside buildings (N = 190; C = 362).
Table 5.
Ranking by people with mobility impairment of barriers at entrance to buildings (N = 188; C = 346).
Table 6.
Ranking by people with mobility impairment of barriers inside buildings (N = 190; C = 362).
The most reported barrier outside buildings (Table 4) is the condition of the path; rough surfaces, cracks and potholes are problematic. This is followed by difficulties with accessible parking (not available, inadequate clearance, too far away), navigating around obstacles, lengthy travel distance, inadequate curb cuts and suboptimal wayfinding (poorly marked, unsafe).
The main problems with the entrance to buildings (Table 5) is the door itself; both in terms of type of door (too heavy, too narrow, poorly marked, closing too quickly) and the access control. Obstacles such as steps, thresholds, mats and plants make the entrance harder to use.
Barriers inside buildings (Table 6) are most commonly narrow paths and obstacles (primarily merchandise stands). Poor signage makes navigation difficult, and more rest areas are needed. People in wheelchairs struggle to reach counters and shelves. There is inadequate provision of accessible bathrooms with easy-use doors, adult changing facilities, good clearance space and proper maintenance. A noteworthy finding is that many of the stated barriers related to other types of disabilities indicating that while many people (66% of all survey respondents) have a mobility impairment, they also have other impairments (related to vision, hearing and sensory conditions). This reinforces the importance of addressing accessibility issues for all types of disability.
3.3.2. Priorities for Improved Accessibility (For People with Mobility Impairment)
Respondents were asked: “What is the one thing (related to building access) that you would fix that would make things easier for you?”—179 people with mobility impairment responded to this question; 158 making one or more specific comments (Table 7), while the remaining 21 made general comments such as:
Table 7.
Ranking by people with mobility impairment of priorities for improved building accessibility (N = 158; C = 220).
- All design should be Safe, Obvious and Step-free (SOS);
- Adopt Universal Design in all buildings, not as an afterthought;
- Consult with the community;
- Make access a law for all public buildings—give building owners two years to comply;
- Provide online accessibility information for venues to help with planning.
Doors that are easy to open (particularly automatic ones) are the top priority, followed by wide, clear paths with level, smooth, non-slip surfaces and the provision of ramps at or near all entrances. The respondents require ramps to be not too steep and fitted with handrails. Other areas for improving accessibility are clearer signage, better lifts and stairs, more seating and more accessible bathrooms with adequate space, adult changing facilities, and proper maintenance. A significant finding is that many of the priorities were related to multi-dimensional disabilities.
3.4. Accessibility Challenges for People with Vision Impairments
The 60 survey responses from people with vision impairment on their accessibility challenges outside buildings, at the entrance to buildings, and inside buildings are given in Section 3.4.1 (Table 8, Table 9 and Table 10, respectively). Section 3.4.2 describes the respondent’s priorities for improving access to buildings.
3.4.1. Main Barriers Outside, at the Entrance and Inside Buildings (For People with Vision Impairment)
Table 8, Table 9 and Table 10 show the results of thematic analysis of the responses of the 60 respondents with vision impairment on the main barriers outside, at the entrance and inside buildings, respectively. Some participants did not respond, so the number of respondents (N) varies. Responses in other languages (mostly Chinese) were translated into English using Google Translate. Some respondents cited more than one barrier, so the number of comments (C) varies. If a barrier was mentioned in fewer than 10% of the comments, it was categorised as “Other”.
The greatest challenge outdoors (Table 8) is obstacles in the path, either from the condition of the path itself (having a rough surface and being poorly differentiated) or from people, cars, signs, display stands and other objects. Wayfinding and signage are other major challenges. Respondents report being unable to find the main entrance, correct door, steps, and ramps because signage is missing or inadequate (with small text) and because there is low colour contrast (for example, doors blend in with walls). The addition of better signage (including Braille and audio signs), bright lighting, tactile marking and good colour contrast would reduce this challenge. Safety is a priority, and the outdoor environment should be designed in a way that keeps people safe from traffic and other obstacles. Finally, people who have vision impairment report feeling self-conscious and isolated as they interact with other people.
Table 8.
Ranking by people with vision impairment of barriers outside buildings (N = 56; C = 75).
Table 9.
Ranking by people with vision impairment of barriers at entrance to buildings (N = 55; C = 78).
People with vision impairment prefer wide, automatic-open doors that do not require an access card or pin to operate (Table 9). The entrance itself should be clearly marked, particularly when it is identical in appearance to the façade of the building. Other challenges are perceived dim lighting (as eyes adjust from sunlight outside) directly inside the entrance, obstacles (such as threshold lips/steps, plants, people, canopies) in the entrance, narrow entrances, and lack of appropriate signage.
Table 10.
Ranking by people with vision impairment of barriers inside buildings (N = 56; C = 92).
Inside the building, the main challenges (Table 10) relate to complex wayfinding, poor signage and obstacles in the paths. Paths should be clear, wide enough to accommodate a guide dog, well-differentiated, plain matte surface, and have tactile marking (particularly in large open spaces). Signage should be both visual (with large text) and non-visual (braille or sound-based) and include directions to the lift, restroom and service area. Trained assistants, seating areas, good acoustics (low background noise and no echoes) and good lighting would improve the experience inside public buildings.
3.4.2. Priorities for Improved Accessibility (For People with Vision Impairment)
Only 37 of the 60 people with vision impairment responded to the question “What is the one thing (related to building access) that you would fix that would make things easier for you?”, with some describing more than one priority. The specific priorities are summarised in Table 11. General comments were:
Table 11.
Ranking by people with vision impairment of priorities for improved building accessibility (N = 37; C = 47).
- Consider safety, predictability and reliability;
- Unfortunately, there isn’t only one thing;
- While physical access has improved, little has been done for access for blind people; Better signage would help but one needs to know it’s there and where it is; feeling around the walls is not “a good look” and is not helpful;
- Acceptance of and provision for guide dogs;
- Provision of affordable public transport;
- More accurate entrance location on Google Maps.
Safety, predictability and reliability are important to people with visual impairments in accessing public buildings. Paths should follow simple layouts, keep people safe from cars and other obstacles and should have tactile marking. Uniform, well-differentiated steps with continuous handrails and lifts with braille or audible messages are essential. Key building features should be clearly marked, with good colour contrast. Instructions and directions should be given in large text, braille and audible format. Restroom layout should be standardised. Low background noise, good lighting (adequately bright but without glare), and plain, matte flooring will all help people with vision impairment to access buildings.
3.5. Accessibility Challenges for People with Hearing Impairments
Only 16 of the 319 survey respondents were people with hearing impairment and, of these, two reported other impairments related to brain injury and trauma. The limited data prohibited thematic analysis, but the main findings are discussed below. The cohort commonly reported feeling anxiety, depression and low self-esteem in describing their experiences accessing buildings. Several respondents reported barriers associated with other types of impairments, such as mobility- and vision-related.
3.5.1. Main Barriers Outside, at the Entrance and Inside Buildings (For People with Hearing Impairment)
Twelve people with hearing impairment provided a total of 14 comments on their perceived barriers outside buildings. These included safety concerns from being unable to hear traffic and traffic signals, difficulty getting assistance (being unable to hear the response) and inadequate support for people with hearing impairment at cultural/entertainment, education and sports places.
The main barrier at the entrance to buildings (N = 12, C = 14) arose from locked entrances with inaudible voice message instructions and no alternative communication such as screens or printed text. A call button usually summoned verbal assistance but again, this was not helpful.
Inside buildings (N = 14, C = 17), challenges arose from inaudible public announcements and assistants only being unable to communicate verbally. Background noise from music, machines and construction interfered with the respondent’s ability to hear and electrical noise disrupted hearing aid function.
3.5.2. Priorities for Improved Accessibility (For People with Hearing Impairment)
The top priorities for people with hearing impairment (N = 11, C = 11) include use of visual/electronic displays of all messages, showing item prices (since they cannot ask and hear a person’s response), and provision of vision-based assistance from building staff. They also wanted more accessible restrooms.
3.6. Accessibility Challenges for People with Sensory, Cognitive and Neuro-Diverse Impairments
Twenty-eight of the survey respondents reported a wide range of impairments not related to mobility, vision or hearing, such as pain, sensory processing disorders, autism, cognition, autoimmunity, speech, brain injury, anxiety, depression, fatigue and multi-dimensional age-related problems. The impairments included both acute/permanent and chronic/variable issues. For convenience, and without intending to marginalise any type of impairment, these respondents are referred to as people with sensory/cognition impairment. The results from thematic analysis of the comments by these respondents are summarised below.
3.6.1. Main Barriers Outside, at the Entrance and Inside Buildings (For People with Sensory/Cognition Impairment)
Twenty-two respondents provided 31 comments on their perceived barriers outside buildings. The main barriers were wayfinding and obstacles in the path. Other challenges related to lack of accessible parking nearby and anxiety (about parking/transport to places, danger, unfamiliar environments and noise).
The main barriers at the entrance to buildings (N = 21, C = 26) arose from locating the entrance and confusing signage/instructions. Additionally, people, noise and unfamiliarity were anxiety-triggering issues.
Inside buildings (N = 24, C = 39), challenges arose from wayfinding (understanding directions/instructions) and obstacles in the path that were mostly related to sensory issues, such as crowds, noise (electronic beeping and crowd noise), bright colours, lights (too bright, flashing, flickering or humming), smells, and close spaces (such as queues). People with sensory/cognition impairment also struggled with social anxiety, self-consciousness, insecurity and fatigue.
3.6.2. Priorities for Improved Accessibility (For People with Sensory/Cognition Impairment)
The top priority for improving the experience of people with sensory/cognition impairment (N = 25, C = 32) was improved wayfinding with better signage (simple, unobstructed, English/universal picture) for directions and for place markings. The second priority related to the sensory environment, with either a scheduled period with low/no background noise and dimmer lighting, or a separate “quiet room” with dim lighting, acoustic insulation and muted colours where they could recover and rest. People with sensory/cognition impairment also wanted safe paths (non-slip surfaces, no loose mats), more seating, more assistants trained in different types of non-physical impairments and online information about the environment so that they could prepare (for example, bringing ear protection for noisy spaces).
4. Discussion
The survey respondents ranked their perceived difficulty accessing different types of public buildings (research objective one). The ten least accessible building types are, in order of difficulty: sports stadiums, bars, boutique shops, public toilets, maraes (Māori community places), gyms, motels/hotels, dairies/small corner shops, bus stops, and theatres/cinemas. The most accessible places are supermarkets, followed by libraries, shopping malls, doctor’s offices and pharmacies. Not all respondents visited all types of buildings; only about half of the respondents went to gyms, churches and maraes, but this could either be from personal choice or from perceived difficulty of access.
Respondents (with all types of disabilities) reported their main barriers outside buildings, at the entrance to buildings and inside buildings (research objective two). The priorities for improving accessibility (research objective three) include the following:
- Outside buildings: Keep paths short (or provided with seating), smooth, wide, properly differentiated, clear of objects, well-maintained (no cracks and potholes), safe from cars, and with adequate curb cuts. Provide enough accessible parking spaces with adequate clearance (including overhead). Use direction and information signs for all important features, such as parking, main entrance, and ramps. Signage should be inclusive, i.e., in large text, braille, universal images, and audio messages.
- Building entrances: Use automatic- or easy-open doors, that are prominent, remain open long enough, and are clear of obstacles such as steps, lips, canopies, notice boards, mats and plants. Avoid card/pin access control systems and call button assistance that is non-inclusive (for example, requiring the person to have quick responses, good vision or good hearing). Provide stairs and ramps (not too steep) with handrails close to the entrance. Increase light level in the entrance to accommodate eyes adjusting from sunlight outside.
- Inside buildings: Use simple layouts with clear and inclusive navigation and information signage (easy to understand, visual, braille and audible) for all key features (such as the reception/assistance area, lifts, and accessible bathrooms) and for public announcements. Keep paths level, smooth, non-slip, plain matte finish, well-differentiated (e.g., with tactile marking), clear of obstacles (particularly display stands) and adequately wide. Use clear markings and continuous handrails on stairs and ensure that lifts have adequate space and inclusive operation/information. Provide accessible bathrooms with easy-open doors, standard layout, adult changing facilities, good clearance space and regular maintenance. Control lighting and acoustics to minimise glare, flashing/strobing lights, beeping and loud noises and provide seating/rest areas, particularly where people need to walk far or stand for long periods.
Some requirements vary depending on the type of impairment. People using wheelchairs should be able to reach counters and shelves. Good colour contrast and accommodation for guide dogs helps people with vision impairment. Installation of hearing loop systems that transmit audio directly to hearing aids in entertainment, education and sports facilities improves the experience of people with hearing impairment. Controlling the sensory environment either through scheduled times, during which lights are dimmed and background noise is lowered, or provision of a separate quiet space helps people suffering from sensory overload. Finally, educating assistants on how to interact with people with a range of disabilities will make the built environment more inclusive for everyone.
Previous studies have similar findings. Common accessibility barriers are poor/non inclusive direction and information signage [21,53]. Entrances should have automated doors and nearby ramps [14,54]. Adequate, well-maintained accessible bathrooms are essential [55,56,57]. Finally, research shows that inclusivity is greatly enhanced when assistants are properly trained to help people with different disabilities [58].
There are some limitations in this research. Firstly, two-thirds of the survey respondents reported mobility impairment, heavily skewing the findings to this demographic. Few (7%) of the respondents reported sensory/cognitive/neurological impairments, and they demonstrated a wide variation in their conditions. These types of disabilities are seldom addressed in access-related research [19,59], but there are some cases where their needs are considered [23,24]. Future research should actively target solutions for non-physical types of impairment.
5. Conclusions
A panel of experts (people with a lived experience of many different disabilities) co-designed a survey on the experiences of people with disabilities accessing a wide range of public places in the New Zealand context. Over 80% of the 319 survey respondents had mobility- and/or vision-related impairments, while the remainder reported hearing impairment and a wide range of sensory/neurological/cognitive impairments. Access was most difficult in places such as sports stadiums, bars, boutique shops, public toilets, maraes and gyms, which indicates where improvements in inclusivity are most needed. Only about half of the respondents ever visited gyms, churches and maraes either because of personal preference or perceived access difficulty. Supermarkets, libraries, shopping malls, doctor’s offices and pharmacies were easiest to access.
The main challenges in accessing New Zealand’s built environment were identified for different types of disabilities. Top priorities for improving outdoor accessibility related to paths, curb cuts, seating, accessible parking spaces and inclusive direction and information signs (in large text, braille, universal images, and audio messages). Entrances to buildings should have easy-open/automatic doors, that are clear of obstacles and avoid non-inclusive access control systems. Stairs and ramps (not too steep) with handrails should be close to the entrance. Building interiors need simple layouts with clear, inclusive navigation and information signage for all key features (such as the reception, lifts, accessible bathrooms) and for public announcements. Other priorities related to user-friendly paths, well-marked stairs continuous handrails, spacious lifts with inclusive operation/information, more and better-equipped accessible bathrooms, rest areas and control of the lighting and acoustics. Certain priorities are specific to the type of impairment. Counters, shelves and refrigerators need to be usable by people in wheelchairs. Good colour contrast helps people with vision impairment and hearing loops at entertainment and education venues facilitates use by people with hearing impairment. Quiet, low-lit environments are easiest for people with sensory difficulties and can be provided either on a regular schedule, or via a separate room.
Unlike other studies that focus on a single impairment and accessibility issues in one type of building, this research presents a holistic view of access to New Zealand’s public built environment from the perspective of people with widely varying disabilities. Disability is very common, particularly amongst older people, and it can affect everyone whether it be temporary or permanent and directly or indirectly through family and friends. Provision of an inclusive built environment helps reduce the negative impact of disability on quality of life. This research outlines ways to improve accessibility, making cities and communities more inclusive and enjoyable for everyone.
Author Contributions
Conceptualisation, C.F. and A.M.; methodology, C.F.; software, C.F.; validation, C.F. and A.M.; formal analysis, C.F.; investigation, C.F. and A.M.; resources, C.F. and A.M.; data curation, C.F.; writing—original draft preparation, C.F.; writing—review and editing, C.F. and A.M.; project administration, C.F.; funding acquisition, C.F. and A.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Building Research Levy provided by the Building Research Association of New Zealand (BRANZ), grant number LR18113.
Institutional Review Board Statement
The study was conducted in accordance with the Massey University Code of Ethical Conduct for Research and was approved by the Massey University Human Ethics Committee Ohu Matatika 1 (protocol code: OM1 24/20, 9 April 2024).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The datasets presented in this article are not readily available because the data are part of an ongoing study.
Acknowledgments
The authors would like to acknowledge the guidance of the Accessibility Partnership Panel (APP), with members from Be.Lab, Blind Low Vision NZ, CCS Disability Action, Deaf Aotearoa, Independent Living Charitable Trust, Making Trax Foundation, New Zealand Spinal Trust, and People First NZ (Taranaki). The APP members, with their lived experience of disabilities, were actively involved in every stage of the research. They provided advice, review and feedback, without which this research would not have been possible. Finally, the authors would like to thank all the individuals and organisations who participated in the research.
Conflicts of Interest
The authors declare no conflicts of interest. The funder had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Disability Language/Terminology Positionality Statement
The authors are academic researchers with both prior and ongoing research interests in collaboration with people with disabilities and disability advocates or support organisations. Drawing on these established and ongoing research relationships, they were advised on all aspects of the research by an Accessibility Partnership Panel comprising seven experts with a lived experience of a range of different dimensions of disabilities. Person-first language is used consistently throughout the manuscript in accordance with current New Zealand Ministry of Social Development recommendations and the research partners’ preference for person-first language consistent with the social model of disability.
Abbreviations
The following abbreviations are used in this manuscript:
| APD | Auditory Processing Disorder |
| APP | Accessibility Partnership Panel |
| SDG | Sustainable Development Goals |
| SPD | Sensory Processing Disorder |
| UN | United Nations |
| UNCRPD | United Nations Convention on the Rights of People with Disability |
| WHO | World Health Organization |
References
- WHO World Health Organization. Disability: Key Facts, 7 March 2023. 2023. Available online: https://www.who.int/news-room/fact-sheets/detail/disability-and-health (accessed on 18 June 2025).
- Statistics New Zealand. Household Disability Survey: 2023, ISBN 978-1-991307-44-6, pp. 1–36. 2025. Available online: https://www.stats.govt.nz/reports/household-disability-survey-2023-findings-definitions-and-design-summary/ (accessed on 18 June 2025).
- UNCRPD, 2006 United Nations, 2006. Convention on the Rights of Persons with Disabilities (UNCRPD)—Articles. Available online: https://www.un.org/development/desa/disabilities/convention-on-the-rights-of-persons-with-disabilities/convention-on-the-rights-of-persons-with-disabilities-2.html (accessed on 18 June 2025).
- United Nations 2015. Sustainable Development Goals: Goal 11. Available online: https://sdgs.un.org/goals/goal11 (accessed on 18 June 2025).
- Watchorn, V.; Hitch, D.; Grant, C.; Tucker, R.; Aedy, K.; Ang, S.; Frawley, P. An integrated literature review of the current discourse around universal design in the built environment–is occupation the missing link? Disabil. Rehabil. 2021, 43, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Zallio, M.; Clarkson, P.J. Inclusion, diversity, equity and accessibility in the built environment: A study of architectural design practice. Build. Environ. 2021, 206, 108352. [Google Scholar] [CrossRef] [Scilit]
- Carlsson, G.; Slaug, B.; Schmidt, S.M.; Norin, L.; Ronchi, E.; Gefenaite, G. A scoping review of public building accessibility. Disabil. Health J. 2022, 15, 101227. [Google Scholar] [CrossRef] [Scilit]
- Flemmer, C.; McIntosh, A. Equitable access to the built environment for people with disability. Athens J. Technol. Eng. 2024. Available online: https://www.athensjournals.gr/ajte/forthcoming (accessed on 14 August 2025). [CrossRef] [Scilit]
- Mosca, E.I.; Capolongo, S. Design for all AUDIT (Assessment Universal Design & Inclusion Tool). A tool to evaluate physical, sensory-cognitive and social quality in healthcare facilities. Acta Biomed. 2023, 94, e2023124. [Google Scholar]
- Badawy, U.I.; Jawabrah, M.Q.; Jarada, A. Adaptation of accessibility for people with disabilities in private and public buildings using appropriate design checklist. Int. J. Mod. Trends Sci. Technol. 2020, 6, 9–20. [Google Scholar] [CrossRef] [Scilit]
- Rimmer, J.H.; Padalabalanarayanan, S.; Malone, L.A.; Mehta, T. Fitness facilities still lack accessibility for people with disabilities. Disabil. Health J. 2017, 10, 214–221. [Google Scholar] [CrossRef] [Scilit]
- NZS 4121:2001; Design for Access and Mobility—Buildings and Associated Facilities. Standards New Zealand: Wellington, New Zealand, 2001.
- Stefanitsis, M.; Flemmer, C.; Rasheed, E.; Ali, N.A. Accessibility to the Built Environment for Mobility-Impaired Persons: A Review. In Proceedings of the International Conference on Engineering, Project, and Production Management, Auckland, New Zealand, 29 November–1 December 2023; Springer Nature: Cham, Switzerland, 2023; pp. 111–127. [Google Scholar]
- Chidiac, S.E.; Reda, M.A.; Marjaba, G.E. Accessibility of the built environment for people with sensory disabilities—Review quality and representation of evidence. Build 2024, 14, 707. [Google Scholar] [CrossRef] [Scilit]
- Kapsalis, E.; Jaeger, N.; Hale, J. Disabled-by-design: Effects of inaccessible urban public spaces on users of mobility assistive devices—A systematic review. Disabil. Rehabil. Assist. Technol. 2022, 19, 1–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Torkia, C.; Reid, D.; Korner-Bitensky, N.; Kairy, D.; Rushton, P.W.; Demers, L.; Archambault, P.S. Power wheelchair driving challenges in the community: A users’ perspective. Disabil. Rehabil. Assist. Technol. 2015, 10, 211–215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ayoung, D.A.; Baada, F.N.A.; Baayel, P. Access to library services and facilities by persons with disability: Insights from academic libraries in Ghana. J. Librar. Inf. Sci. 2021, 53, 167–180. [Google Scholar] [CrossRef] [Scilit]
- Jeamwatthanachai, W.; Wald, M.; Wills, G. Indoor navigation by blind people: Behaviors and challenges in unfamiliar spaces and buildings. Br. J. Vis. Impair. 2019, 37, 140–153. [Google Scholar] [CrossRef] [Scilit]
- Keerthirathna, W.A.D.; Karunasena, G.; Rodrigo, V.A.K. Disability access in public buildings. In Proceedings of the International Research Conference on Sustainability in Built Environment, Colombo, Sri Lanka, 18–19 June 2010; pp. 94–104. [Google Scholar]
- Malcolm, M. Environmental accessibility for autistic individuals: Recommendations for social work practice and spaces. Aotearoa New Zealand Soc. Work Rev. 2022, 34, 103–115. [Google Scholar] [CrossRef] [Scilit]
- Ijadunola, M.Y.; Ojo, T.O.; Akintan, F.O.; Adeyemo, A.O.; Afolayan, A.S.; Akanji, O.G. Engendering a conducive environment for university students with physical disabilities: Assessing availability of assistive facilities in Nigeria. Disabil. Rehabil. Assist. Technol. 2018, 14, 354–360. [Google Scholar] [CrossRef] [Scilit]
- Kinnaer, M.; Baumers, S.; Heylighen, A. Autism-friendly architecture from the outside in and the inside out: An explorative study based on autobiographies of autistic people. J. Hous. Built Environ. 2016, 31, 179–195. [Google Scholar] [CrossRef] [Scilit]
- Grangaard, S.; Hedvall, P.-O.; Lid, I.M. Universal design and accessibility as an act or a state—A comparison of policies in Norway, Sweden, and Denmark. Stud. Health Technol. Inform. 2024, 320, 2–9. [Google Scholar]
- Warnicke, C.; Kristianssen, A.-C. Safety and accessibility for persons with disabilities in the Swedish transport system—Prioritization and conceptual boundaries. Disabil. Soc. 2024, 39, 2357–2374. [Google Scholar] [CrossRef] [Scilit]
- Perry, M.; Cotes, L.; Horton, B.; Kunac, R.; Snell, I.; Taylor, B.; Wright, A.; Devan, H. “Enticing” but not necessarily a “space designed for me”: Experiences of urban park use by older adults with disability. Int. J. Environ. Res. Public Health 2021, 18, 552–571. [Google Scholar] [CrossRef] [Scilit]
- Fisher, K.R.; Purcal, C. Policies to change attitudes to people with disabilities. Scand. J. Disabil. Res. 2017, 19, 161–174. [Google Scholar] [CrossRef] [Scilit]
- Heylighen, A.; Schijlen, J.; Van der Linden, V.; Meulenijzer, D.; Vermeersch, P.-W. Socially innovating architectural design practice by mobilising disability experience. An exploratory study. Archit. Eng. Des. Manag. 2016, 12, 253–265. [Google Scholar] [CrossRef] [Scilit]
- Carnemolla, P.; Mackinnon, K.; Darcy, S.; Almond, B. Public toilets for accessible and inclusive cities: Disability, design and maintenance from the perspective of wheelchair users. Smart Sustain. Built Environ. 2024. [Google Scholar] [CrossRef] [Scilit]
- Smith, M.; Calder-Dawe, O.; Carroll, P.; Kayes, N.; Kearns, R.; Lin, E.-Y.; Witten, K. Mobility barriers and enablers and their implications for the wellbeing of disabled children and young people in Aotearoa New Zealand: A cross-sectional qualitative study. Wellbeing Space Soc. 2021, 2, 100028. [Google Scholar] [CrossRef] [Scilit]
- Sharon-David, H.; Siekanska, M.; Tenenbaum, G. Are gyms fit for all? A scoping review of the barriers and facilitators to gym-based exercise participation experienced by people with physical disabilities. Perform. Enhanc. Health 2021, 9, 100170. [Google Scholar] [CrossRef] [Scilit]
- Tutuncu, O. Investigating the accessibility factors affecting hotel satisfaction of people with physical disabilities. Int. J. Hosp. Manag. 2017, 65, 29–36. [Google Scholar] [CrossRef] [Scilit]
- Tutuncu, O.; Lieberman, L. Accessibility of hotels for people with visual impairments: From research to practice. J. Vis. Impair. Blind. 2016, 110, 163–175. [Google Scholar] [CrossRef] [Scilit]
- Wazzan, W. My accessible room is not accessible, applying human factors: Principals to enhance the accessibility of hotel rooms. Proced. Manuf. 2015, 3, 5405–5410. [Google Scholar] [CrossRef] [Scilit]
- Gamache, S.; Routhier, F.; Morales, E.; Vandersmissen, M.-H.; Boucher, N. Mapping review of accessible pedestrian infrastructures for individuals with physical disabilities. Disabil. Rehabil. Assist. Technol. 2019, 14, 410–422. [Google Scholar] [CrossRef] [Scilit]
- Zając, A.P. City accessible for everyone–improving accessibility of public transport using the universal design concept. Transp. Res. Proc. 2016, 14, 1270–1276. [Google Scholar] [CrossRef] [Scilit]
- Carter, E.W.; Tuttle, M.; Spann, E.; Ling, C.; Jones, T.B. Addressing accessibility within the church: Perspectives of people with disabilities. J. Relig. Health 2023, 62, 2474–2495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fortuna, J.; Harrison, C.; Eekhoff, A.; Marthaler, C.; Seromik, M.; Ogren, S.; VanderMolen, J. Identifying Barriers to Accessibility for Museum Visitors Who Are Blind and Visually Impaired. Visit. Stud. 2023, 26, 103–124. [Google Scholar] [CrossRef] [Scilit]
- Tsami, C.A.; Chrysikou, E. Towards specialized accessibility standards for healthcare facilities: A mixed-methods study on the needs of people with dis-abilities in hospitals. Stud. Health Technol. Inform. 2024, 319, 103–115. [Google Scholar]
- Swainea, B.; Labbé, D.; Poldma, T.; Baril, M.; Fichten, C.; Havel, A.; Kehayia, E.; Mazer, B.; McKinley, P.; Rochette, A. Exploring the facilitators and barriers to shopping mall use by persons with disabilities and strategies for improvements: Perspectives from persons with disabilities, rehabilitation professionals and shopkeepers. J. Disabil. Stud. 2024, 12, 123–145. [Google Scholar] [CrossRef] [Scilit]
- Schulze, F.; Berget, G. Inclusive public libraries: How to adequately identify accessibility barriers? Stud. Health Technol. Inf. 2024, 320, 141–148. [Google Scholar]
- Sarsak, H.I. Assessing building accessibility for university students with disabilities. MOJ Yoga Phys. Ther. 2018, 3, 69–75. [Google Scholar] [CrossRef] [Scilit]
- Whaley, B.A.; Martinis, J.G.; Pagano, G.F.; Barthol, S.; Senzer, J.; Williamson, P.R.; Blanck, P.D. The Americans with Disabilities Act and equal access to public spaces. Laws 2024, 13, 5–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lund, E.; Bringa, O.R. From visions to practical policy: The Universal Design journey in Norway. What did we learn? What did we gain? What now? In Proceedings of the 3rd International Conference on Universal Design, York, UK, 21–24 August 2016. [Google Scholar]
- Eisenberg, Y.; Heider, A.; Labbe, D.; Gould, R.; Jones, R. Planning accessible cities: Lessons from high quality barrier removal plans. Cities 2024, 148, 104837. [Google Scholar] [CrossRef] [Scilit]
- Arditi, A. Rethinking ADA signage standards for low-vision accessibility. J. Vis. 2017, 17, 8. [Google Scholar] [CrossRef] [Scilit]
- Stewart, B. Legislative recognition of the human right to accessible housing in Aotearoa New Zealand. Pub. Int. LJNZ 2021, 8, 128–150. [Google Scholar]
- Calder, A.; Sole, G.; Mulligan, H. The accessibility of fitness centers for people with disabilities: A systematic review. Disabil. Health J. 2018, 11, 525–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saha, M.; Chauhan, D.; Patil, S.; Kangas, R.; Heer, J.; Froehlich, J.E. Urban accessibility as a socio-political problem: A multi-stakeholder analysis. Proc. ACM Hum-Comp. Inter. 2021, 4, 209. [Google Scholar] [CrossRef] [Scilit]
- Larkin, H.; Hitch, D.; Watchorn, V.; Ang, S. Working with policy and regulatory factors to implement universal design in the built environment: The Australian experience. Int. J. Environ. Res. Pub. Health 2015, 12, 8157–8171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flemmer, C.; McIntosh, A. Making New Zealand’s Built Environment Inclusive and Accessible for Everyone. BRANZ Research Report ER104, 2025; pp. 1–55. Available online: https://www.branz.co.nz/pubs/research-reports/er104/ (accessed on 3 June 2025).
- Calculator.net. Available online: https://www.calculator.net/sample-size-calculator.html?type=1&cl=95&ci=5&pp=24&ps=5400000&x=Calculate (accessed on 18 June 2025).
- Öhrvall, A.M.; Wennberg, B.; Käcker, P.; Lidström, H. Experiences of participation in people with intellectual disability, in relation to service support received, and views from professionals in the field of disability. J. Intellect. Disabil. 2024. [Google Scholar] [CrossRef] [Scilit]
- Müller, K.; Engel, C.; Loitsch, C.; Stiefelhagen, R.; Weber, G. Traveling more independently: A study on the diverse needs and challenges of people with visual or mobility impairments in unfamiliar indoor environments. ACM Trans. Access. Comp. 2022, 15, 1–44. [Google Scholar] [CrossRef] [Scilit]
- Burns, S.P.; Mendonca, R.J.; Smith, R.O. Accessibility of public buildings in the United States: A cross-sectional survey. Disabil. Soc. 2024, 39, 2988–3003. [Google Scholar] [CrossRef] [Scilit]
- Salimi, N.; Gere, B.; Mora, E.; Chen, R.K. Navigating the Path: Understanding and overcoming challenges for college students with disabilities. In Innovative Approaches in Counselor Education for Students With Disabilities; IGI Global Scientific Publishing: Hershey, PA, USA, 2025; pp. 141–196. [Google Scholar]
- Alhusban, A.A.; Almshaqbeh, S.N. Delivering an inclusive built environment for physically disabled people in public universities (Jordan as a case study). J. Eng. Des. Technol. 2024, 22, 1980–1998. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.-F.; Zhang, D.; Dulas, H.M.; Whirley, M.L. Academic learning experiences and challenges of students with disabilities in higher education. J. Postsecond. Stud. Success 2024, 3, 79–102. [Google Scholar] [CrossRef] [Scilit]
- Okezue, O.C.; Uzoigwe, M.; Ugwu, L.E.; John, J.N.; John, D.O.; Mgbeojedo, U.G. Level of independence, anxiety and relevant challenges among persons with disabilities towards their use of facilities in public buildings. Facilities 2024, 42, 472–484. [Google Scholar] [CrossRef] [Scilit]
- Fangfang, H.; Xiao, H.; Shuai, Z.; Qiong, W.; Jingya, Z.; Guodong, S.; Yan, Z. Living Environment, Built Environment and Cognitive Function among Older Chinese Adults: Results from a Cross-Sectional Study. J. Prev. Alzheimer’s Dis. 2021, 9, 126–135. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).