


Abstract
Medical and technology development have drastically the improved quality of life and, consequently, life expectancy. Nevertheless, the more people who enter the third-age, the more geriatric syndromes expand in the elderly. Sarcopenia and Type 2 diabetes mellitus (T2DM) are common diseases among the elderly and the literature has extensively studied these two diseases separately. Recent evidence, however, revealed that there is a bidirectional relationship between sarcopenia and T2DM. The aims of the present review were: (1) to present diet and exercise interventions for the management of sarcopenia and T2DM and (2) identify which diet and exercise interventions can be used simultaneously in order to effectively deal with these two disorders. Exercise and a balanced diet are used as effective countermeasures for combating sarcopenia and T2DM in older adults based on their bidirectional relationship. Lifestyle changes such as exercise and a balanced diet seem to play an important role in the remission of the diseases. Results showed that chronic exercise can help towards glycemic regulation as well as decrease the incidence rate of muscle degradation, while diet interventions which focus on protein or amino acids seem to successfully treat both disorders. Despite the fact that there are limited studies that deal with both disorders, it seems that a combined exercise regime (aerobic and resistance) along with protein intake > 1gr/kg/d is the safest strategy to follow in order to manage sarcopenia and T2DM concurrently.
1. Introduction
Skeletal muscle loss is an expected outcome of the aging process and is considered to be a significant factor in strength deterioration, loss of functional mobility, and independence [1,2]. While the causes for muscle loss are many, sarcopenia describes the progressive and generalized skeletal muscle disorder involving the accelerated loss of muscle mass and function. Sarcopenia is a term derived from the Greek phrase “poverty (penia) of flesh (sarco)” and is defined as the progressive loss of skeletal muscle and strength due to the age-related disability to keep muscular metabolism in equilibrium, affecting quality of life, fragility, and mortality. The term sarcopenia is used to differentiate this condition from other causes of muscle loss such as immobility or neurological damage [3,4]. Sarcopenia is gradually identified as a common disease in older adults, and it is among the major public health problems that must be addressed [5].
Despite the precise definition for sarcopenia, there have been multiple criteria for identifying this condition. Consensus statements regarding diagnostic criteria have been developed by European Working Group on Sarcopenia in Older People (EWGSOP) [6], the International Working Group on Sarcopenia (IWGS) [7], the Asian Working Group for Sarcopenia (AWGS) [8], and the American Foundation for the National Institutes of Health (FNIH) [9]. According to the EWGSOP, sarcopenia can be classified in prosarcopenia, sarcopenia, and severe sarcopenia based on muscle mass, strength, and physical performance. Older adults suffering from prosarcopenia exhibit only a lower muscle mass volume when compared to average healthy older adults, while individuals suffering from sarcopenia, apart from low muscle mass, also exhibit reduced strength or physical performance. Finally, in severe sarcopenia, all three factors are present. Sarcopenia can also be classified according to its duration (i.e., acute or chronic). Acute sarcopenia is caused by disease or injury and lasts no more than 6 months. Chronic sarcopenia is caused by progressive diseases and is suggested to last more than 6 months. The diagnosis of sarcopenia can be easily confused with other diseases that can lead to muscle loss (i.e., cachexia, frailty, sarcopenic obesity) [3,10]. Since the prevalence of sarcopenia largely depends on diagnostic clinical criteria, it varies vastly among different studies [11,12,13,14,15,16,17]. It should be noted that reduced muscle strength is not necessarily accompanied by reduced skeletal muscle mass and, therefore, EWGSOP precedes muscle functioning assessment to muscle mass loss as tools for diagnosing sarcopenia [12]. Specifically, the criteria for diagnosing sarcopenia should include the examination of muscle functioning and muscle mobility. Of interest, the physical status of the individual in entering the third-age is a critical factor for developing sarcopenia [18,19].
Diabetes mellitus is a common disease affecting older adults, coined as a metabolic disorder characterized by ineffective insulin secretion, defective insulin action, or both. Diabetes mellitus can be caused either by the insufficient secretion of insulin (Type 1) or/and by development of insulin resistance (Type 2). In skeletal muscles, insulin binds to the insulin receptor (GLUT4) and allows glucose to be absorbed by the muscle cells. In case of insulin resistance, there is a decrease in glucose absorption by the muscle tissue, which in turn leads to increased blood glucose levels while there is a shortage of energy in the skeletal muscle [20,21]. In 2017, approximately 462 million individuals were affected by Type 2 diabetes mellitus (T2DM) corresponding to 6.28% of the world’s population (4.4% of those aged 15–49 years, 15% of those aged 50–69, and 22% of those aged 70+) [22].
Sarcopenia is a common trait for older adults suffering from diabetes mellitus. Recent studies suggested that sarcopenia may not only be a cause for diabetes but also a consequence, indicating a bidirectional relationship between the two conditions [23,24]. Specifically, it has been found that both men and women with diabetes had low values of skeletal mass index [23], while it was found that the frequency of T2DM was higher in sarcopenic subjects when compared to their non-sarcopenic counterparts [24]. Lifestyle changes can serve in the prevention and treatment of both sarcopenia and diabetes in older adults.
Exercise, either aerobic or resistance, is widely used to combat degrading consequences of the aging process in older adults [25]. Indeed, participation in a regular exercise program can help people to improve glycemic control, to preserve their cardiovascular function, to reduce insulin resistance, to improve lipid profile, and to control their body mass [26]. During aging, energy requirements along with energy intake are reduced, with an average reduction of 25% in energy intake between the age of 40 to 70. This reduction inevitably leads to weight and muscle loss, leading to negative effects in strength and body function [27]. Moreover, diet interventions seem to be important strategies, not only for the management of muscle mass and strength, but also in the prevention of diseases related to malnutrition. In the literature, there is evidence that diet interventions have a positive effect in supervising older adults and result in the better adoption of treatment strategies [28]. It should be noted that reduced energy intake and monotonous diets impair exercise adaptations related to muscle mass enhancement, mainly due to the reduction of energy intake and consequently due to reduced intake of important macro- and micro-nutrients that are important for the anabolic processes [29].
To the best of our knowledge, there are no studies in the literature in which sarcopenia and T2DM were treated simultaneously. Therefore, the aim of this review was to evaluate the diet and exercise interventions that have been applied for the treatment of sarcopenia and T2DM individually, and which exercise and diet interventions can be used simultaneously in order to effectively deal with the two disorders. The present review is mainly focused on studies which have focused on exercise treatment techniques (aerobic, resistance, or combined aerobic and resistance) as well as diet interventions that are known to best combat the two disorders.
2. Methods
In the present review, we used studies using chronic exercise or/and diet intervention and clinical trials which included older adults suffering from sarcopenia or T2DM. We focused on treatment techniques that involved aerobic training, resistance training, or both trainings, as well as diet interventions or nutrition analysis. We also selected studies that used biomarkers of muscle mass and/or glycemic status.
An electronic search was performed using the following databases: PubMed and Google Scholar using the following search terms for each individual database:
- “resistance training” OR “resistance exercise” OR “strength training” OR “aerobic exercise’’
- “frailty” OR “muscle loss” OR “sarcopenia”
- “muscle hypertrophy” OR “muscle strength” OR “skeletal muscle mass”
- “diabetes mellitus” OR “type 2 diabetes mellitus OR “insulin resistance”
- “diet” OR “nutrition” OR “amino acids” OR “protein” OR “antioxidant” OR “life-style modification” OR “omega-3 supplementation” OR “vitamin D supplementation”
- “older adults” OR “elderly”
Recent literature published after 2000 was considered. We analyzed both titles and abstracts to decide whether a study could be included in our review. Articles were included if they fulfilled the following criteria: being peer-reviewed and/or research-based, met the search criteria, and being considered well-conducted studies. We also included seven reviews that were closest to our criteria.
In order to assess the impact of the selected studies in sarcopenia we have included markers that are meaningful in the diagnosis of sarcopenia as stated from the various Consensus Group Statements [6,7,8,9,30]. In this context, sarcopenic markers should involve: muscle mass, muscle strength, and physical performance measurements (i.e., MWD, TUG, etc.). Similarly, we have included in the results (diabetic) the markers that have been related to the diagnosis of T2DM according to the ADA diagnosis criteria [21,31], such as blood pressure, cholesterol levels, triglyceride levels, insulin resistance, serum insulin levels, fasting plasma glucose, 2-h post-feeding glucose levels, HbA1c, and several hormones (i.e., glucagon, growth hormone, etc.). We also included IGF-1 in the diabetic markers [32].
3. Sarcopenia and T2DM
Sarcopenia and T2DM affect different systems of the human body, however, a bidirectional relationship between the two disorders has been gradually recognized. Sarcopenia is mainly characterized by type II muscle fiber atrophy, a reduced number of motor neurons and mitochondria, along with increased fat accumulation within the muscles [5,33]. Moreover, during the aging process, changes in hormonal levels contribute to sarcopenia. Indeed, lower levels of growth hormone, testosterone, thyroid hormones, and insulin-like growth factor may contribute to both muscle mass and strength loss [33]. Hormonal changes occur in both sexes indiscriminately and lead to a chronic inflammatory situation [33]. Regarding inflammation, while the aging process reveals an increase in inflammation markers, such as interleukin-6 (IL-6), tumor necrosis factor-alpha (TNF-α), and C-reactive protein (CRP), it is questionable as to whether this increase is due to the aging process or due to the diseases that accompany older adults [33]. Additionally, the function of muscle synthesis is restrained and muscles cannot be regenerated effectively, a situation known as anabolic resistance, while immobility seems also to be an important factor for muscle loss and vice versa [5].
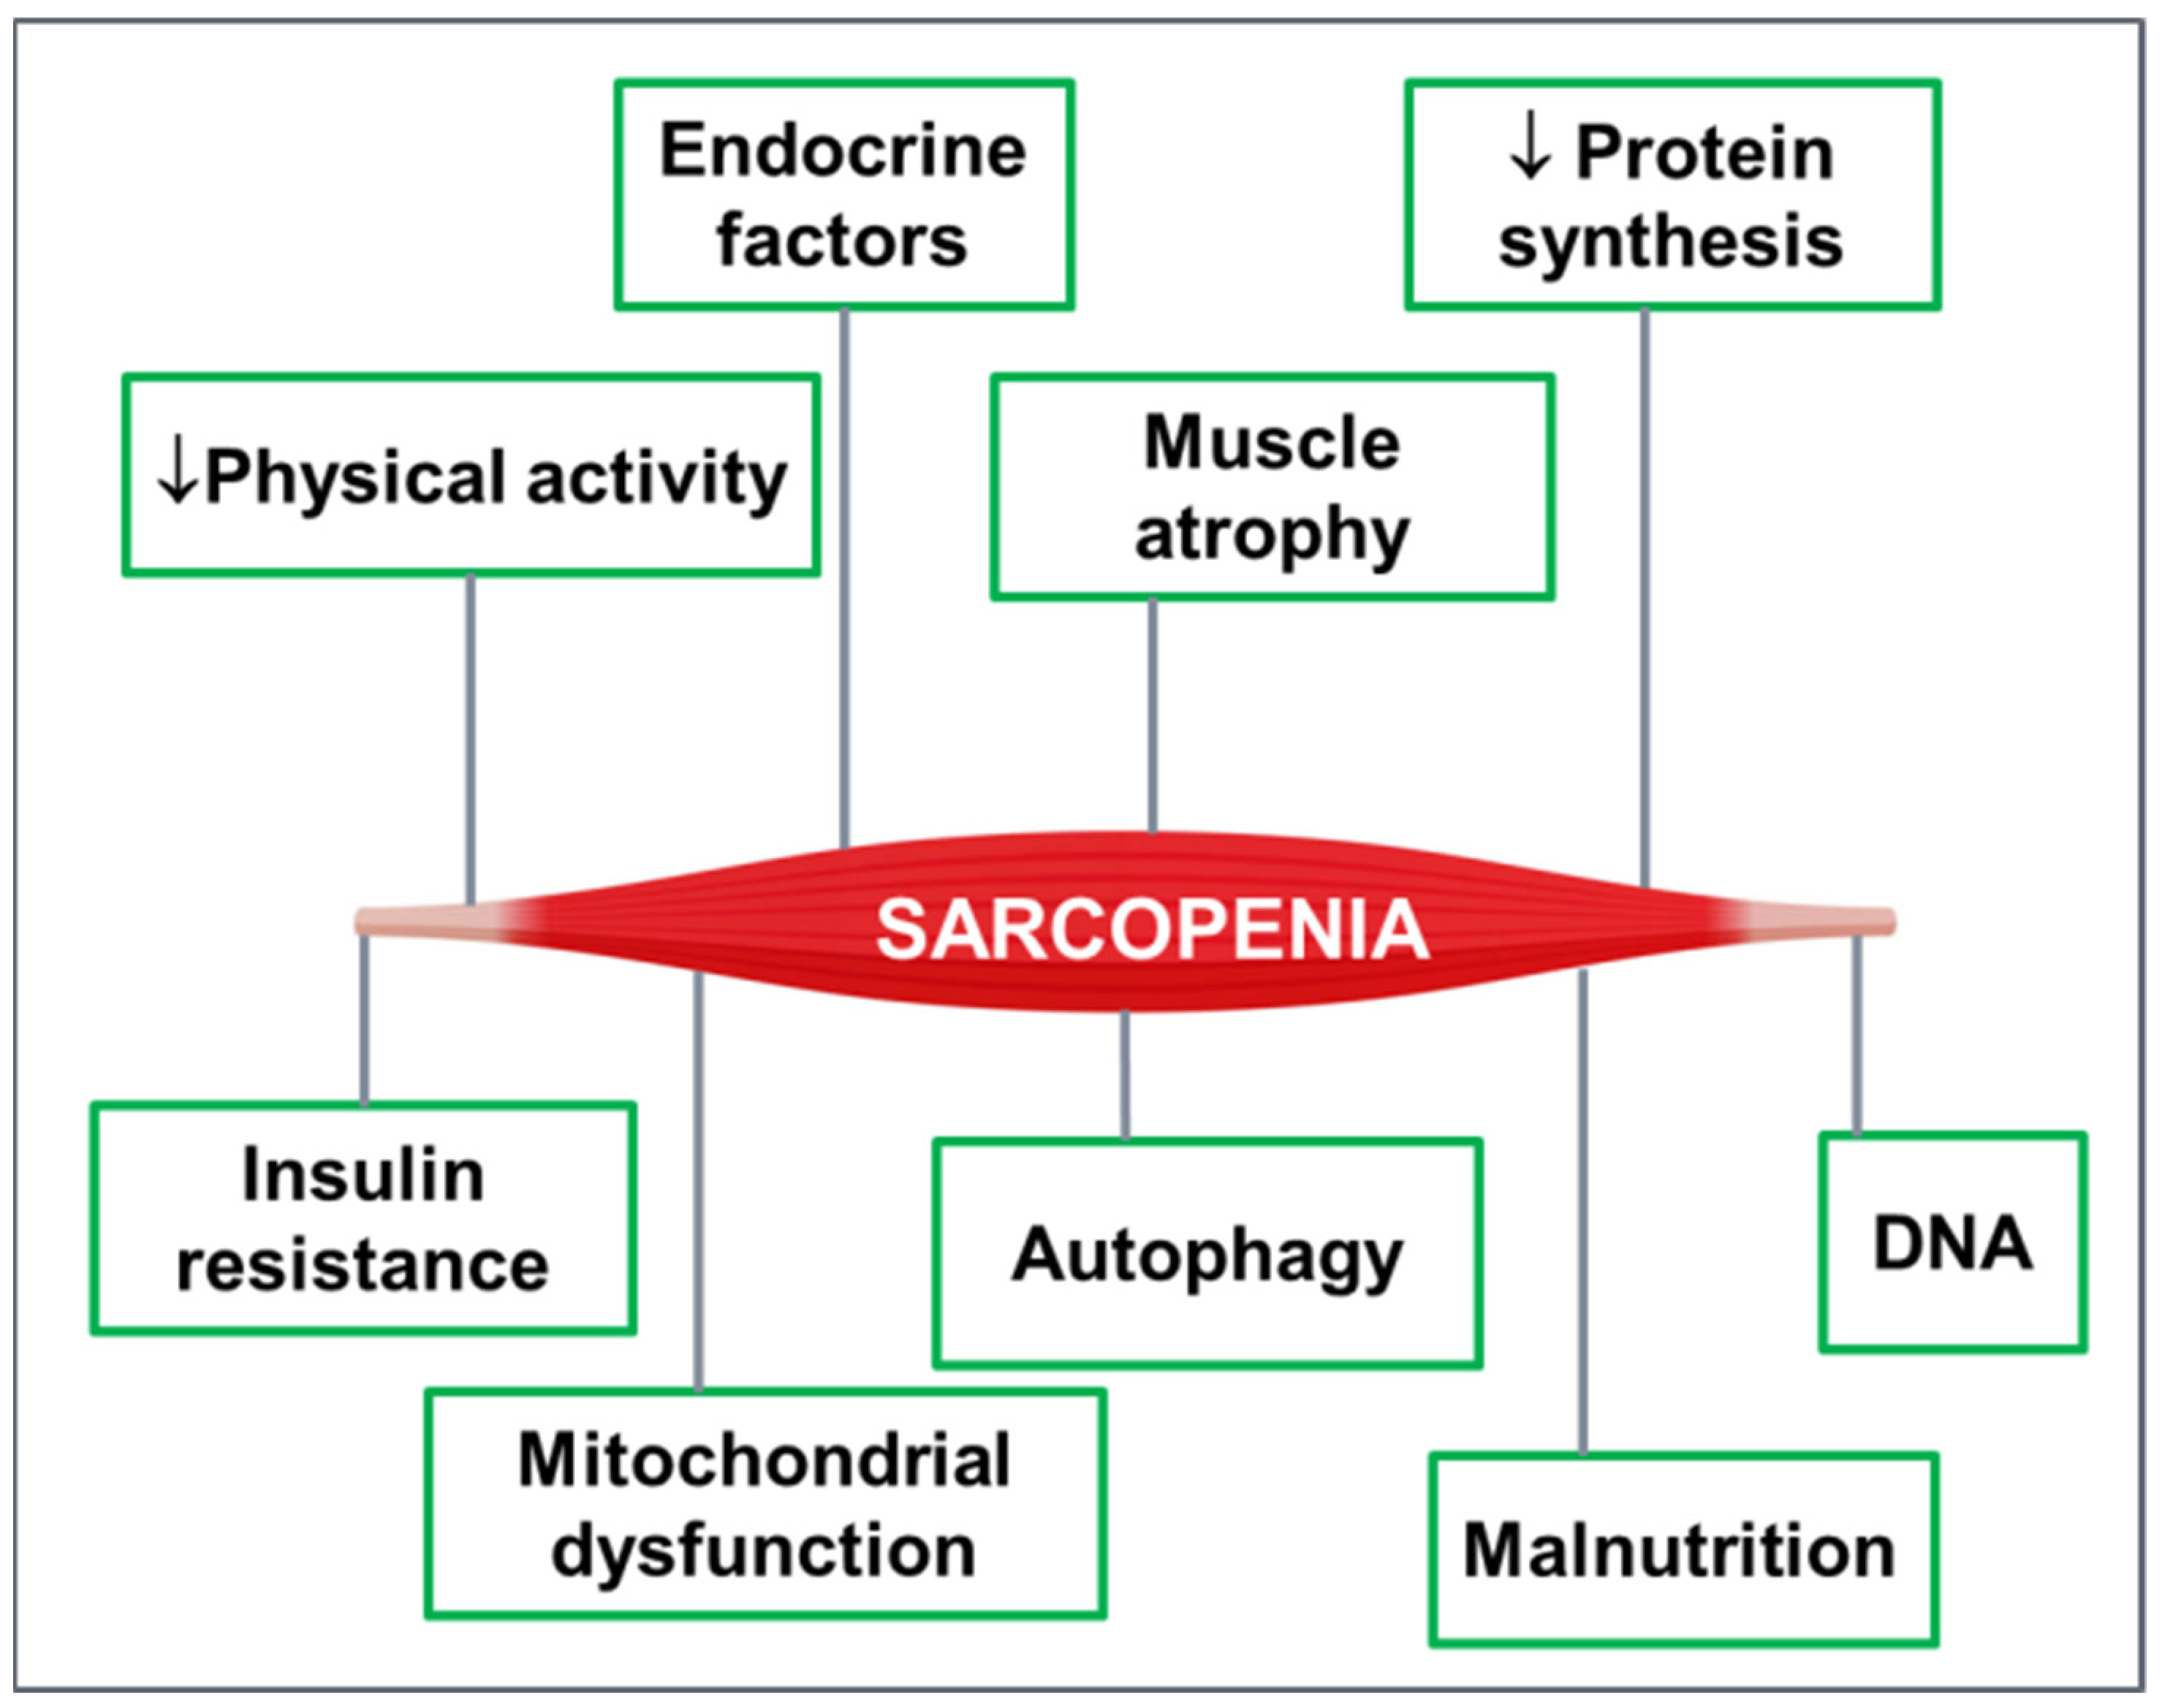
Low protein intake and low levels of vitamin D are considered emerging nutritional imbalances among older adults, since they either both or separately are related to reduced muscle performance [33]. Generally, older adults consume 25% less food than they consumed during their adulthood, while the quality of food is also compromised. Data reveal that sarcopenia can be affected by a genetic predisposition that relates to the structure, function, and metabolism of skeletal muscle fibers [18]. The level of muscle mass and strength that can be achieved in older adults is not only related to muscle tissue loss but is also related to the level of muscle performance that has been achieved during adulthood [18]. In summary, the main factors that lead to sarcopenia include low physical activity levels, low energy intake, progressive fibrosis increase, dysfunction of muscle metabolism, chronic inflammation, oxidative stress, and neuromuscular degeneration (Figure 1). As a result of the above factors, the human body gradually loses muscle fibers by the age of fifty, while by the age of eighty, 50% of skeletal muscle tissue has been lost. This loss rate is also observed in older adults who were athletes as adults [34].
Figure 1.
Pathophysiological factors of sarcopenia.
The main factors that contribute to the prevalence of diabetes are genetic, increased body weight, and an unhealthy lifestyle. The consumed food is converted to glucose, through digestion, and then is diffused in the blood stream. Through glycolysis, glucose provides the energy that the body needs in order to cope with its daily activities. Insulin is a hormone secreted by the pancreas and allows glucose to be absorbed by cells. In people suffering from diabetes mellitus, the quantity of secreted insulin is never enough in order to induce sufficient glucose absorption, leading to the continuous circulation of glucose in the blood stream. One reason for this limited absorption is insulin resistance in skeletal muscle tissues. In this case, these tissues cannot detect the circulating blood stream glucose, cells starve, and the pancreas is then pressed to increase insulin production. Contrary to the skeletal muscle, which lacks glucose, other human organs and tissues are exposed to unhealthily high glucose levels (e.g., refinery, kidneys, brain, cardiovascular, central neural system) [35,36]. Another reason for insufficient glucose absorption is the dysfunction of the β-cells of the pancreas, in which case the produced insulin cannot overcome the demand of skeletal tissues [35,36]. It has been suggested that the insulin resistance is the primary cause preceding the later dysfunction in β-cells’ production [37].
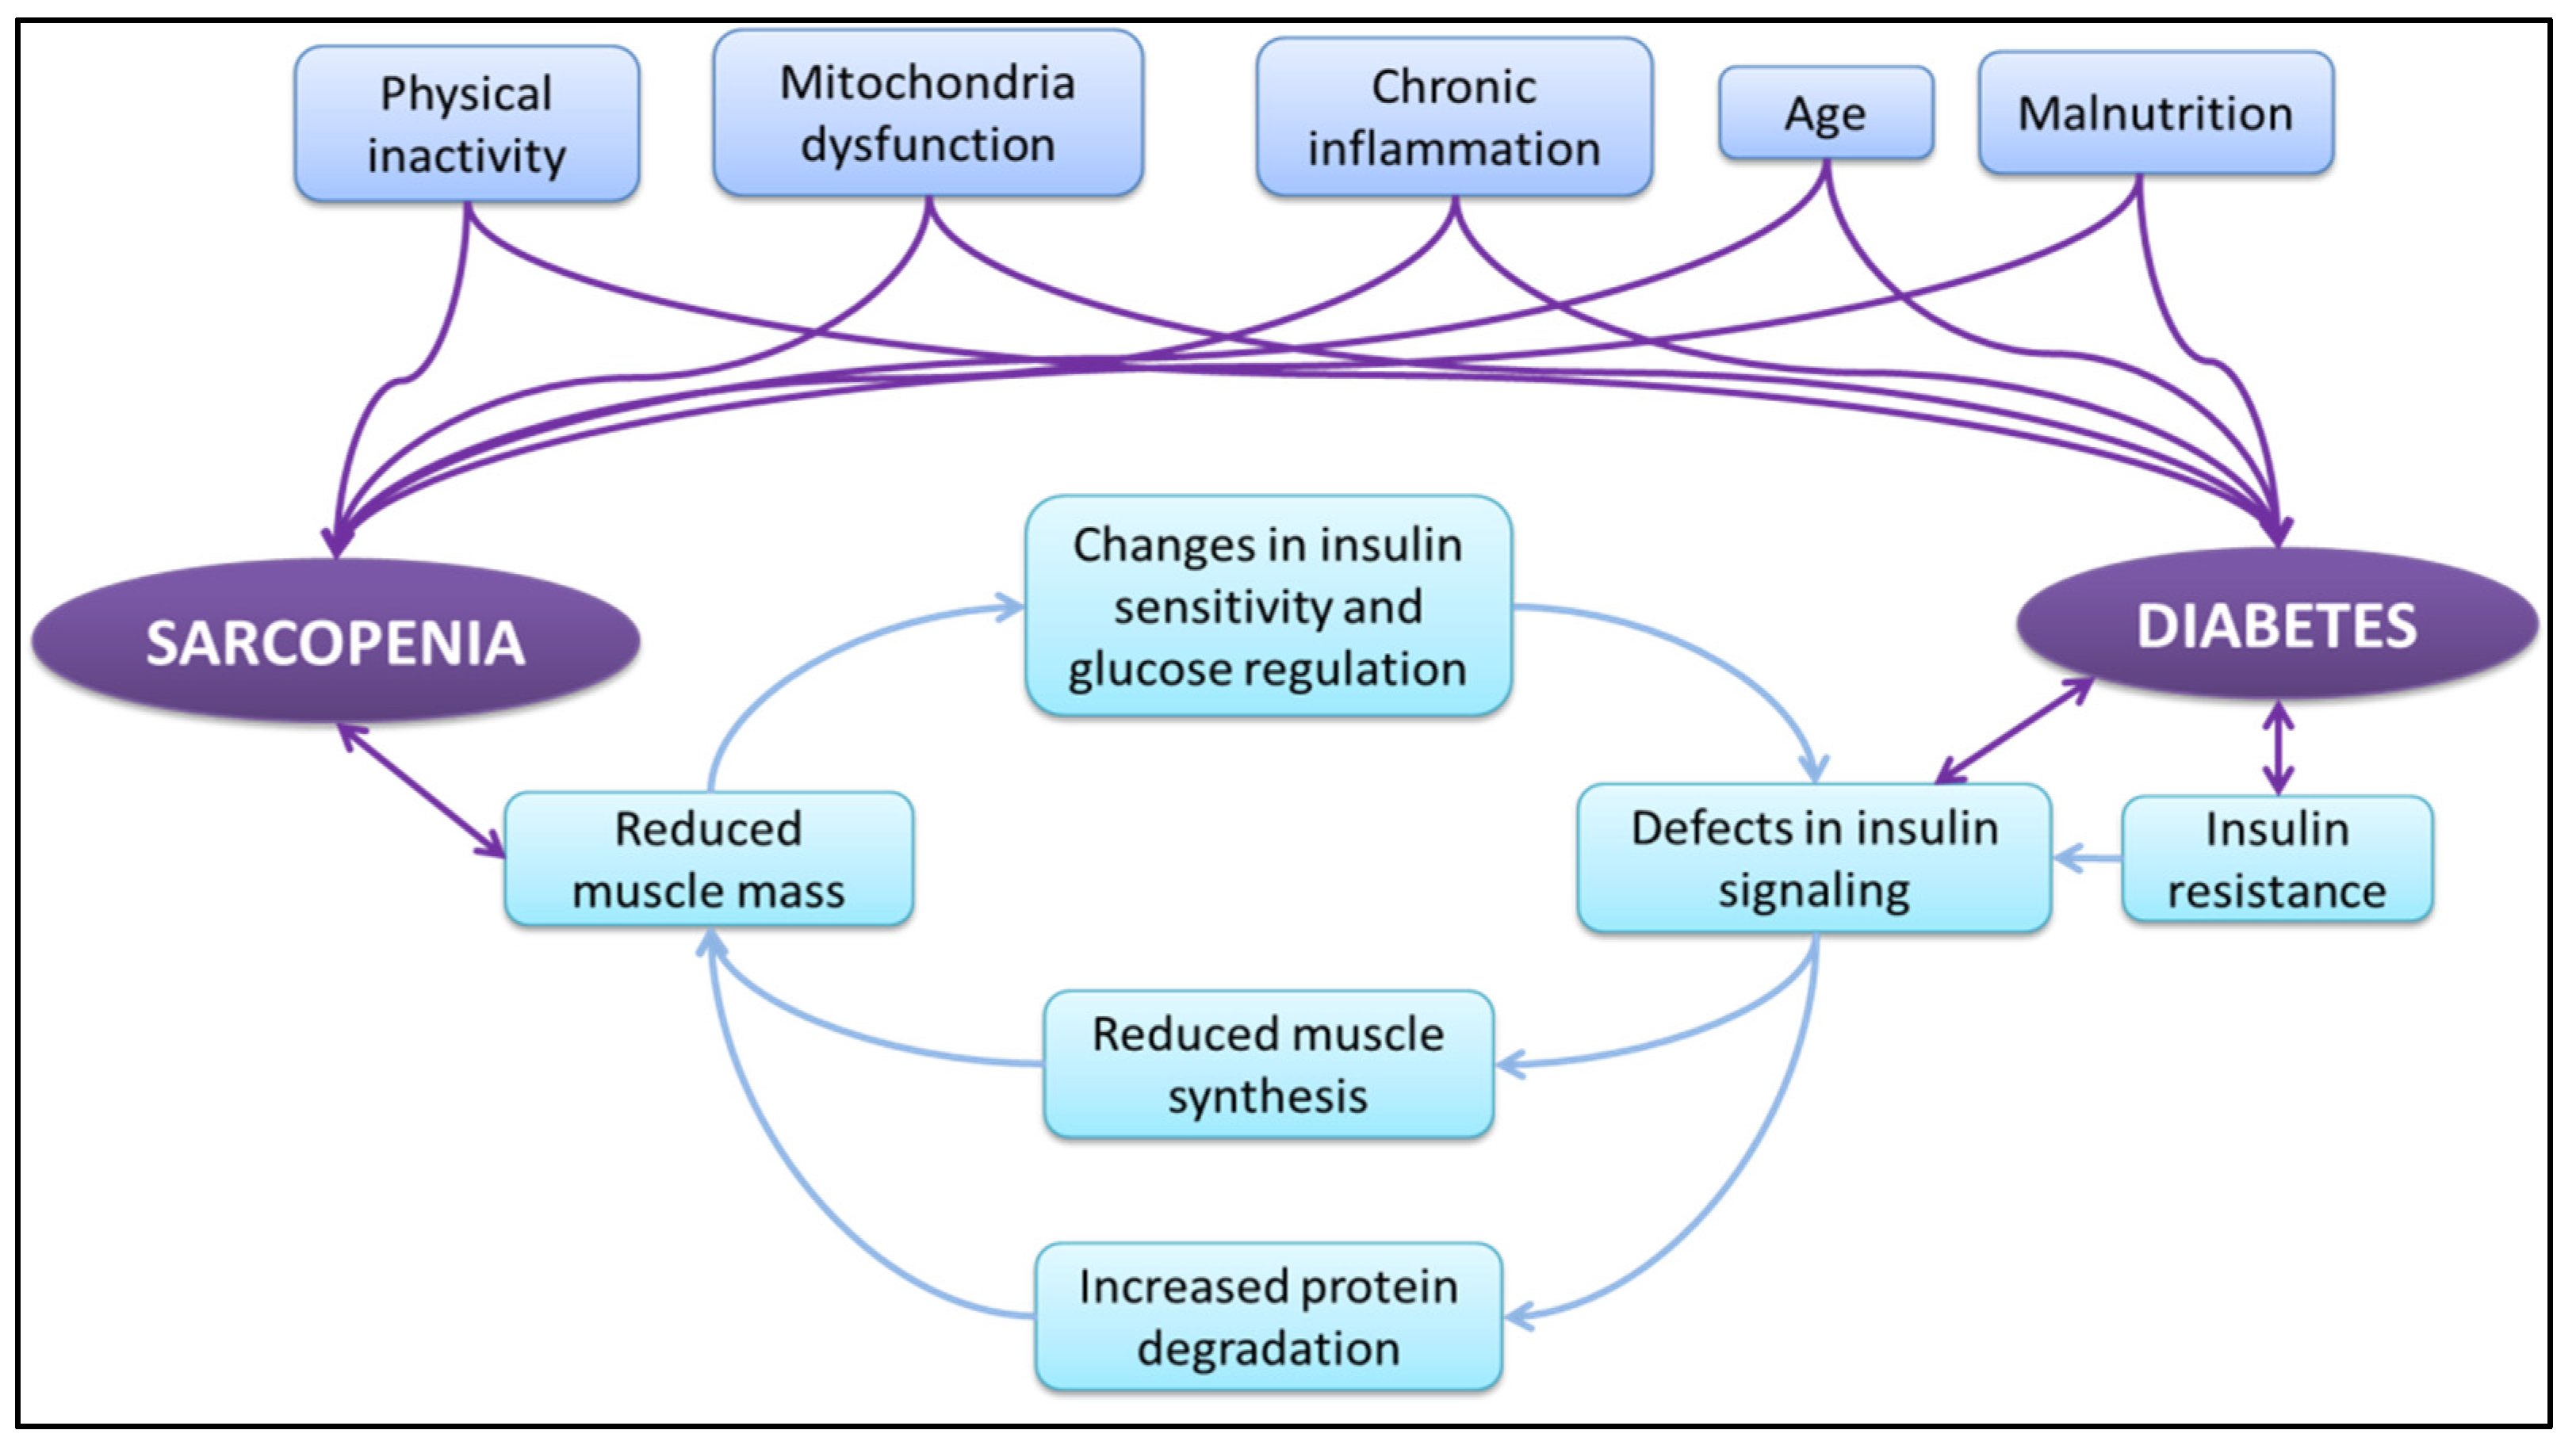
Diabetes mellitus and sarcopenia share common causes (e.g., reduced physical activity and low levels of anabolic hormones, such as insulin growth factor-1, testosterone, and ghrelin), while in diabetic patients the intramuscular fat storage is up to three times greater when compared to healthy older adults [36,38,39]. Insulin resistance in skeletal muscle is the most important factor that amplifies sarcopenia in T2DM patients. Proteins and amino acids are the main macronutrients that preserve muscle tissue. Protein synthesis takes place mostly in the postprandial state, when the concentrations of insulin and amino acids reach their maximum levels [40,41]. Specifically, insulin function promotes protein synthesis in skeletal muscle cells only when there is an increased availability of intramuscular amino acids, while a lack of insulin leads to protein breakdown [40,41]. It is clear that low insulin levels may lead to insufficient protein synthesis and increased protein degradation, which in turn may lead to sarcopenia [42]. Consecutive muscle loss provokes metabolic changes, which gradually amplifies hyperglycemia and chronic inflammation. Of importance, hyperglycemia relates to metabolic abnormalities that can also lead to muscle wasting [20,43]. The anabolic effect of insulin on muscle mass in combination with adequate amino acids intake could be an effective countermeasure for muscle loss, not only for people who suffer from diabetic mellitus, but generally for older adults [44,45]. In Figure 2, a generic view of sarcopenia and diabetes interactions can be seen.
Figure 2.
Interaction of sarcopenia and diabetes.
Relevant studies highlight this bidirectional relationship, which in turn accelerates the progress of both sarcopenia and T2DM, while it is strongly suggested that clinical examinations should involve both conditions [45,46]. Multiple studies provide evidence that sarcopenia relates to diabetes mellitus and vice versa (Table 1). From the included studies, it can be easily observed that patients with sarcopenia have a high prevalence of T2DM [24,47,48] and vice versa [23,47,48,49,50,51]. It is also evident that low-value muscle mass markers are strongly related to reduced glycemic control [38,52,53].
Table 1.
Studies establishing that sarcopenia and diabetes mellitus are closely related.
4. Exercise and Diet to Control Sarcopenia and Type 2 Diabetes Mellitus in Older Adults
Exercise of the aerobic component mainly improves metabolic regulation and cardiovascular function, while aerobic exercise is known to induce positive effects in combating sarcopenia and T2DM [55]. An improved glycemic profile is observed through reductions in glycosylated hemoglobin (HbA1c) [56], fasting plasma glucose [51], and insulin resistance [57]. Moreover, high-intensity interval training is very effective and has the advantage of being very time-efficient [55,56,58]. Aerobic exercise has also been found to improve skeletal muscle mass, especially leg strength [56,59,60] and this is the reason why it is highly recommended in older adults [61].
Resistance training, on the other hand, is known to increase muscle mass, muscle strength and physical performance [57,60,62,63]. Indeed, resistance training is especially appropriate to older frail adults [59,64,65]. With resistance training, leg strength is improved [64,65,66,67] and subjects perform much better in physical performance [60,64,65]. Of importance, resistance exercise has also been found to exert beneficial effects on glycemic profile and insulin sensitivity [68,69]. Another study noted that while HbA1c did not change significantly [67,70], a great response was observed in diabetes medication [70]. Resistance training has also been found to greatly elevate IGF-1 [59], which in turn affects insulin sensitivity [71]. IGF-1 secretion is also known to be greatly associated with muscle generation, muscle mass, and muscle strength [59]. Of interest, one study noted that no significant results have been observed on older adults while, exercise was found to increase the risk of musculoskeletal injury [72].
Many studies combining aerobic and resistance training have been used in order to maximize the benefits of both types of exercise. In particular, a combined aerobic and resistance regime was found to improve glucose regulation by reducing fasting glucose [73], levels of fructosamine [63], or triglycerides [68], while it caused increases in serum IGF-1 levels [59] and in insulin sensitivity [68]. Sarcopenic individuals should also be benefited by using combined training, since it improves muscle mass [59], strength [59,73,74], and physical performance [73], despite the fact that combined exercise is not as effective as pure resistance training to cause improvements in skeletal muscle [59].
In older adults, an adequate protein intake could be a successful strategy for combating sarcopenia. Indeed, dietary proteins provide amino acids, which are essential for the synthesis of muscle protein [66,74,75] and glucose control, and result in reduced fasting glucose [66], reduced levels of triglycerides [66], and even improved insulin responses [76]. Improvements in physical performance have also been observed [74]. There is no significant association between diabetes and total dairy intake, although a high intake of milk may reduce T2DM risk among men [77]. In some studies, low levels of vitamin D have been observed to be related with muscle mass loss and sarcopenia [78,79]. However, the infusion of vitamin D in frail older patients did not show any significant result [72]. Vitamin D is also associated with an elevated risk of future diabetes in older people [80]. Vitamin B12 might also play a role in the muscle mass loss, however, this relationship is not established [72]. Omega-3 fatty acid intake was negatively associated with the presence of sarcopenia [81]. Sarcopenia seems also to be related to the concentration of carotenes, since higher plasma concentrations were associated with a reduced risk of low grip, hip, and knee strength [82].
Finally, it seems that a combination of exercise and diet has positive effects in improving muscle mass, muscle strength and physical performance [62,63,83].
Table 2 summarizes the reviewed studies. The first four examined both markers: sarcopenia and T2DM. The next eight studies examined only sarcopenic markers, and the last seven studies included only T2DM markers.
Table 2.
Treatments for people with diabetes mellitus or sarcopenia and results in T2DM/sarcopenic markers.
5. Discussion and Conclusions
Sarcopenia and T2DM seem to coexist among patients suffering of either disorder, since it is not only the progression of diabetes mellitus that may lead to muscle mass loss, but also the progression of sarcopenia may lead to a diabetic condition [23,24]. This means that studies and compensation techniques should include measurements and clinical examinations that involve both disorders. Aerobic and resistance exercise and diet independently have a significant positive impact on each of the diseases. Aerobic and resistance exercise are the most well-studied types of training and therefore the most preferable for older individuals with health complications. Results have shown that all types of exercise greatly contribute to both disorders. In particular, aerobic exercise improved the glycemic profile through reductions in glycosylated hemoglobin (HbA1c) [56], fasting plasma glucose [56], and insulin resistance [68]. Studies in a healthy population have also revealed a positive impact on insulin resistance [68]. This means that aerobic exercise has a clear beneficial effect on T2DM patients, since they exercise under supervision [86,87]. Aerobic exercise also improves skeletal muscle mass, especially leg strength [51,55] and is recommended for the older adults [61], although it is more efficient when combined with resistance training [59,61,73]. Aerobic exercise contributes to the mitochondrial biogenesis and restoration of mitochondrial metabolism, which in turn reduces the expressions of catabolic genes and increases muscle protein synthesis, enhancing by this way muscle hypertrophy [73]. High-intensity interval training is very effective and has the added benefit of being very time-efficient [55,56]. Apart from those, aerobic exercise greatly improves aerobic capacity to prior sedentary subjects and even to older adults with cardiovascular disease [25]. Specifically, regular aerobic exercise decreases aortic stiffness and enhances blood flow, resulting in the better control of vascular circulation, whilst increases in HDL-C improve the atherogenic profile and reduce risk factors for cardiovascular events [25]. Moreover, a lower score in depression is also experienced by exercising subjects [25], which is very important to improve the quality of life.
Resistance training, on the other hand, is mainly known to increase muscle mass, muscle strength, and physical performance. This makes resistance training especially appropriate to older, frail adults. Improvements in muscle quality [59,64,65] and strength [64,65,66] along with the increased skeletal mass reduce the risks of falls and improve physical performance [57,64,65], making resistance exercise an appropriate physical activity for sarcopenic individuals [86]. However, participation in resistance exercise programs definitely needs supervision since this type of exercise increases the risk of musculoskeletal injury in older adults [72]. Moreover, resistance training reduces intramuscular fat and improves insulin sensitivity [68,86], although aerobic exercise has a better impact on metabolic markers [25]. Resistance training also greatly elevates IGF-1 [59], which in turn affects insulin sensitivity [71]. IGF-1 secretion is also known to be greatly associated with muscle generation, muscle mass, and muscle strength [59]. Of importance, resistance exercise has also been found to exert beneficial effects on health-related parameters such as bone mineral density, blood pressure, lipid profiles, and cardiovascular health [55,88]. It should be stressed that during physical activity, a strict blood pressure control is required for the avoidance of diabetic retinopathy or nephropathy [89]. A reduction in obesity is another important factor for glycemic profile improvement, since reductions in intramuscular fat can improve insulin sensitivity [59]. However, caution should be taken during resistance exercise since it may increase the risk of injury, while also leading to dropouts due to the unvaried nature of exercises [86].
In the literature, many studies have used combined aerobic and resistance training in order to maximize the benefits of both types of exercise. In particular, a combined aerobic and resistance training program along with improvements in cardiovascular function and metabolic factors not only achieves better glycemic control, but also improves muscle mass, strength, and function [59,73,84,86,90,91]. However, it should be noted that some studies did not observe an improvement in HbA1c [84]. Since both types of training contribute to health improvement, the American Diabetes Association and the Japan Diabetes Society recommend daily participation in activities that include both the aerobic and resistance type of exercise [92,93]. Nonetheless, despite the fact that there is no specific health factor to avoid exercise, older adults who suffer from diabetes mellitus do not participate in organized exercise programs due to a lack of time, an inability to control glucose during exercise, denial in recognizing obesity as a health problem, a lack of appropriate infrastructure, and other social factors [89,94].
Nutritional interventions/therapies in people who suffer from diabetes mellitus aim to achieve healthy levels of glucose, lipid profile, and blood pressure. Energy intake restriction is an effective strategy for obese or overweight individuals in order to control their body mass, while it is critical for the avoidance of metabolic syndrome [59]. However, while fat loss may be an essential parameter for older adults suffering from T2DM, it may also lead to muscle mass loss and cause the exacerbation of sarcopenia. The observed skeletal muscle loss during energy restriction could be a result of inadequate protein intake [95,96]. This means that this strategy should be avoided, especially in older adults who suffer from endogenous muscle loss [97].
In older adults, an adequate protein intake could be a successful strategy for combating sarcopenia. Regarding dietary proteins, two main research areas have been developed. The first deals with the effect of protein intake on weight loss and glycemic control and the second deals with the long-standing interest of the preservation of muscle mass [98]. Indeed, dietary proteins provide amino acids that are essential for the synthesis of muscle protein [66,75] and glucose control and which result in reduced fasting glucose [66], triglycerides [66], and improved insulin responses [76], independently of age [93,94]. Specifically, branch-chain amino acids (i.e., leucine, isoleucine, and valine) regulate the release of hormones (for example, leptin, GLP-1, and ghrelin) that can potentially affect food intake and glycemia levels [87,99]. Amino acids and insulin are anabolic signals that activate the mammalian target of rapamycin complex 1 (mTORC1) and protein kinase, altering the growth of energy-consuming tissues and decreasing protein breakdown [87]. It is reported in the literature that a mixture of amino acids enriched with leucine may compensate for the reduced muscle synthesis in older adults, since leucine can increase anabolic response [33,100]. B-hydroxy-β-methylbutyrate (HMB) is a basic metabolite of leucine that contributes to protein synthesis; however, it is found to be reduced during aging [100]. Undeniably, in older adults HBM supplementation caused reductions in muscle mass degradation was and found to improve muscle strength [101,102].
Low levels of vitamin D have been observed to be related with muscle mass loss and enhanced sarcopenia [29,78,79,103]. Specifically, low levels of vitamin D are also related to reduced glycemic control, since vitamin D receptors located inside the pancreas and skeletal muscle contribute to glucose and muscle homeostasis [29,33,104,105]. However, due to equivocal results regarding the effects of vitamin D on physical strength and performance, more studies are needed to determine the exact role of vitamin D in sarcopenia [29,72]. Vitamin B12 might also play a role in the muscle mass loss, however, this relationship is not established [72]. There is no significant association between diabetes and total dairy intake, although a high intake of milk may reduce T2DM risk among men [77].
Sarcopenia is increasingly recognized as an inflammatory condition caused by cytokines and oxidative stress [29]. Specifically, polyunsaturated fatty acids have found to be strong anti-inflammatory agents and therefore they may improve muscle function [81,103]. This is also holds true in older adults, since it has been found that increased strength occurs after consumption of fishes, however more studies are needed to further support this finding [29,103]. Cooperatively, oxidative stress can damage biomolecules, such as DNA, lipids, and proteins, since reactive oxygen species (ROS) are present in every cell compartment. Reactive oxygen species are normally compensated for by antioxidant defense mechanisms, including the enzymes peroxide dismutase and glutathione peroxidase, as well as exogenous dietary antioxidants such as selenium, carotenoids, tocopherols, flavonoids, and other polyphenols [106,107,108]. In older adults, excessive ROS concentrations may lead to oxidative stress and result in the loss of muscle mass and strength [29]. Generally, there is a limited number of studies examining the effects of antioxidant supplements on muscle strength, and therefore the results are debatable [82,109].
Undoubtedly older adults need much more dietary proteins than younger individuals in order to support their wellness, recovery from injuries, and to maintain their independence in everyday life activities. Older adults must compensate for changes related to protein metabolism, while at the same time they need more protein to counteract inflammation and catabolism caused by acute and chronic diseases [41]. The existing guidelines for dietary proteins suggest 0.8 g of protein per kilogram of body mass per day (gr/kg BM/d) independently of sex or age [42]. Unfortunately, this is a rather general recommendation and does not account for changes caused by the aging process (e.g., metabolism, immunity, hormonal levels, and progressive frailty). Based on data of recent investigations, it has been suggested that lean body mass can be better preserved if older adults consume larger quantities of dietary proteins than the general population [57]. In the PROT-AGE project [57] it was proposed that an average daily protein intake of 1–1.2 gr/kg BM/d (or approximately 25–30 gr/meal) be consumed by healthy older adults in order to preserve their muscle mass. For the older adults suffering from acute or chronic diseases, in the PROT-AGE project it is proposed that an increased protein intake (i.e., 1.2–1.5 gr/Kg BM/d) should be dependent on the characteristics of the disease (e.g., the severity of the disease, the patient’s dietary condition before disease, and the impact of disease on patient’s diet). Of importance, it has been suggested that a protein consumption of up to 2 gr/kg BM/d be adhered to for older adults suffering from severe disease/injury/starvation [57].
To the best of our knowledge, studies that combine both exercise and nutritional interventions are mainly focused on obese people [110,111,112,113]. Apart from that, there exists very limited research on proposing methods to simultaneously compensate for both diseases. In a relevant study, diabetic mice were supplemented with a ginseng diet and followed aerobic exercise, and were found to have improvements in muscle mass and on insulin resistance [114]. Generally, while there is an agreement that both diseases should be treated simultaneously, researchers seem to ignore people suffering from both diseases and prefer to examine the treatment techniques separately. Nevertheless, sarcopenia and diabetes mellitus have high prevalence among the older adults, which in turn may lead to a low quality of life. The available data show that a combination of supervised combined training along with protein intake > 1 gr/kg/d seems to be the safest treatment, if not the best, in order to compensate both sarcopenia and T2DM. Of note, nutrition counseling is also important to achieve diet adherence [28,115]. Due to the fact that one disorder fuels the other, more studies are needed involving people suffering both disorders. Since sarcopenia and T2DM have been widespread among the population in the modern era, it is imperative to find the best combination of exercise and diet interventions that will be succeed in managing sarcopenia and diabetes mellitus.
Author Contributions
Conceptualization, D.A. and V.P.; methodology, D.A., N.D.G., T.N. and V.P; investigation, D.A.; data curation, N.D.G., T.N. and V.P.; writing—original draft preparation, D.A., V.P.; writing—review and editing, N.D.G., T.N. and V.P.; supervision, N.D.G., T.N. and V.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ADA | American Diabetes Association |
| ASM | Appendicular skeletal mass |
| AT | Aerobic training |
| AWGS | Asian Working Group for Sarcopenia |
| BMI | Body mass index |
| DEXA | Dual Energy X-ray Absorptiometry |
| EWGSOP | European Working Group on Sarcopenia in Older People |
| FNIH | Foundation of National Institute of Health |
| GNRI | Geriatric nutritional risk index |
| HbA1c | Glycosylated hemoglobin |
| HDL-C | High density lipoprotein cholesterol |
| IWGS | International Working Group on Sarcopenia |
| LMM | Low Muscle Mass |
| LMS | Low Muscle Strength |
| LSMI | Low Skeletal Mass Index |
| MWD | Minutes walking distance |
| N | Number of participants |
| RASM | Relative appendicular skeletal muscle index |
| RT | Resistance training |
| SD | Standard deviation |
| SMI | Skeletal mass Index |
| TSM | Total body skeletal mass |
| TUG | Timed Up and Go test |
| WHO | World Health Organization |
References
- Janssen, I. Influence of Sarcopenia on the Development of Physical Disability: The Cardiovascular Health Study. J. Am. Geriatr. Soc. 2006, 54, 56–62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sreekumaran Nair, K. Aging muscle. Am. J. Clin. Nutr. 2005, 81, 953–963. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wiedmer, P.; Jung, T.; Castro, J.P.; Pomatto, L.C.D.; Sun, P.Y.; Davies, K.J.A.; Grune, T. Sarcopenia—Molecular mechanisms and open questions. Ageing Res. Rev. 2021, 65, 101200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cruz-Jentoft, A.J.; Bahat, G.; Bauer, J.; Boirie, Y.; Bruyère, O.; Cederholm, T.; Cooper, C.; Landi, F.; Rolland, Y.; Sayer, A.A.; et al. Writing Group for the European Working Group on Sarcopenia in Older People 2 (EWGSOP2); and the Extended Group for EWGSOP2. Sarcopenia: Revised European consensus on definition and diagnosis. Age Ageing 2019, 48, 601. [Google Scholar] [CrossRef] [Scilit]
- Ali, S.; Garcia, J.M. Sarcopenia, Cachexia and Aging: Diagnosis, Mechanisms and Therapeutic Options—A Mini-Review. Gerontology 2014, 60, 294–305. [Google Scholar] [CrossRef] [Scilit]
- Cruz-Jentoft, A.J.; Baeyens, J.P.; Bauer, J.M.; Boirie, Y.; Cederholm, T.; Landi, F.; Martin, F.C.; Michel, J.P.; Rolland, Y.; Schneider, S.M.; et al. European Working Group on Sarcopenia in Older People. Sarcopenia: European consensus on definition and diagnosis: Report of the European Working Group on Sarcopenia in Older People. Age Ageing 2010, 39, 412–423. [Google Scholar] [CrossRef] [Scilit]
- Chumlea, W.C.; Cesari, M.; Evans, W.J.; Ferrucci, L.; Fielding, R.A.; Pahor, M.; Studenski, S.; Vellas, B. International Working Group on Sarcopenia Task Force Members. Sarcopenia: Designing phase IIB trials. J. Nutr. Health Aging 2011, 15, 450–455. [Google Scholar] [CrossRef] [Scilit]
- Chen, L.K.; Woo, J.; Assantachai, P.; Auyeung, T.W.; Chou, M.Y.; Iijima, K.; Jang, H.C.; Kang, L.; Kim, M.; Kim, S.; et al. Asian Working Group for Sarcopenia: 2019 Consensus Update on Sarcopenia Diagnosis and Treatment. J. Am. Med. Dir. Assoc. 2020, 21, 300–307.e2. [Google Scholar] [CrossRef] [Scilit]
- Menetski, J.P.; Hoffmann, S.C.; Cush, S.S.; Kamphaus, T.N.; Austin, C.P.; Herrling, P.L.; Wagner, J.A. The Foundation for the National Institutes of Health Biomarkers Consortium: Past Accomplishments and New Strategic Direction. Clin. Pharmacol. Ther. 2019, 105, 829–843. [Google Scholar] [CrossRef] [Scilit]
- Lo, J.H.; Pong, U.K.; Yiu, T.; Ong, M.T.; Lee, W.Y. Sarcopenia: Current treatments and new regenerative therapeutic approaches. J. Orthop. Translat. 2020, 23, 38–52. [Google Scholar] [CrossRef] [Scilit]
- Cruz-Jentoft, A.J.; Landi, F.; Schneider, S.M.; Zúñiga, C.; Arai, H.; Boirie, Y.; Chen, L.K.; Fielding, R.A.; Martin, F.C.; Michel, J.P.; et al. Prevalence of and interventions for sarcopenia in ageing adults: A systematic review. Report of the International Sarcopenia Initiative (EWGSOP and IWGS). Age Ageing 2014, 43, 748–759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spira, D.; Norman, K.; Nikolov, J.; Demuth, I.; Steinhagen-Thiessen, E.; Eckardt, R. Prevalence and definition of sarcopenia in community dwelling older people. Z. Gerontol. Geriatr. 2015, 49, 94–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patil, R.; Uusi-Rasi, K.; Pasanen, M.; Kannus, P.; Karinkanta, S.; Sievänen, H. Sarcopenia and osteopenia among 70–80-year-old home-dwelling Finnish women: Prevalence and association with functional performance. Osteoporos. Int. 2012, 24, 787–796. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Volpato, S.; Bianchi, L.; Cherubini, A.; Landi, F.; Maggio, M.; Savino, E.; Bandinelli, S.; Ceda, G.P.; Guralnik, J.M.; Zuliani, G.; et al. Prevalence and Clinical Correlates of Sarcopenia in Community-Dwelling Older People: Application of the EWGSOP Definition and Diagnostic Algorithm. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2013, 69, 438–446. [Google Scholar] [CrossRef] [Scilit]
- Lee, W.-J.; Liu, L.-K.; Peng, L.-N.; Lin, M.-H.; Chen, L.-K. Comparisons of Sarcopenia Defined by IWGS and EWGSOP Criteria Among Older People: Results From the I-Lan Longitudinal Aging Study. J. Am. Med. Dir. Assoc. 2013, 14, 528.e1–528.e7. [Google Scholar] [CrossRef] [Scilit]
- Landi, F.; Liperoti, R.; Fusco, D.; Mastropaolo, S.; Quattrociocchi, D.; Proia, A.; Russo, A.; Bernabei, R.; Onder, G. Prevalence and Risk Factors of Sarcopenia Among Nursing Home Older Residents. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2011, 67A, 48–55. [Google Scholar] [CrossRef] [Scilit]
- Tanimoto, Y.; Watanabe, M.; Sun, W.; Sugiura, Y.; Tsuda, Y.; Kimura, M.; Hayashida, I.; Kusabiraki, T.; Kono, K. Association between sarcopenia and higher-level functional capacity in daily living in community-dwelling elderly subjects in Japan. Arch. Gerontol. Geriatr. 2012, 55, e9–e13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sayer, A.A.; Syddall, H.; Martin, H.; Patel, H.; Baylis, D.; Cooper, C. The developmental origins of sarcopenia. J. Nutr. Health Aging 2008, 12, 427–432. [Google Scholar] [CrossRef] [Scilit]
- Murphy, R.A.; Ip, E.H.; Zhang, Q.; Boudreau, R.M.; Cawthon, P.M.; Newman, A.B.; Tylavsky, F.A.; Visser, M.; Goodpaster, B.H.; Harris, T.B. Transition to Sarcopenia and Determinants of Transitions in Older Adults: A Population-Based Study. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2013, 69, 751–758. [Google Scholar] [CrossRef] [Scilit]
- DeFronzo, R.A.; Tripathy, D. Skeletal Muscle Insulin Resistance Is the Primary Defect in Type 2 Diabetes. Diabetes Care 2009, 32, S157–S163. [Google Scholar] [CrossRef] [Scilit]
- American Diabetes Association. Diagnosis and classification of diabetes mellitus. Diabetes Care 2014, 37 (Suppl. 1), S81–S90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Kaabi, J.; Mustafa, H.; Govender, R.D.; King, J.K.; Hashim, M.J.; Khan, M.A.B. Epidemiology of Type 2 Diabetes—Global Burden of Disease and Forecasted Trends. J. Epidemiol. Glob. Health 2019, 10, 107–111. [Google Scholar] [CrossRef] [Scilit]
- Kim, T.N.; Park, M.S.; Yang, S.J.; Yoo, H.J.; Kang, H.J.; Song, W.; Seo, J.A.; Kim, S.G.; Kim, N.H.; Baik, S.H.; et al. Prevalence and Determinant Factors of Sarcopenia in Patients with Type 2 Diabetes. Diabetes Care 2010, 33, 1497–1499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Souza, A.B.F.; Nascimento, D.A.C.; Rodrigues, I.J.M.; Charone, C.C.O.; Lopes, G.L.; Lima, R.S.; Sá, A.A.; Carneiro, T.X.; Moraes, N.S. Association between sarcopenia and diabetes in community dwelling elderly in the Amazon region—Viver Mais Project. Arch. Gerontol. Geriatr. 2019, 83, 121–125. [Google Scholar] [CrossRef] [Scilit]
- Nomura, T.; Kawae, T.; Kataoka, H.; Ikeda, Y. Assessment of lower extremity muscle mass, muscle strength, and exercise therapy in elderly patients with diabetes mellitus. Environ. Health Prev. Med. 2018, 23, 20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lambers, S.; Van Laethem, C.; Van Acker, K.; Calders, P. Influence of combined exercise training on indices of obesity, diabetes and cardiovascular risk in type 2 diabetes patients. Clin. Rehabil. 2008, 22, 483–492. [Google Scholar] [CrossRef] [Scilit]
- Goodpaster, B.H.; Park, S.W.; Harris, T.B.; Kritchevsky, S.B.; Nevitt, M.; Schwartz, A.V.; Simonsick, E.M.; Tylavsky, F.A.; Visser, M.; Newman, A.B. The loss of skeletal muscle strength.;mass.;and quality in older adults: The health, aging and body composition study. J. Gerontol. A Biol. Sci. Med. Sci. 2006, 61, 1059–1064. [Google Scholar] [CrossRef] [Scilit]
- Chan, L.-C.; Yang, Y.-C.; Lin, H.-C.; Wahlqvist, M.L.; Hung, Y.-J.; Lee, M.-S. Nutrition counseling is associated with less sarcopenia in diabetes: A cross-sectional and retrospective cohort study. Nutrition 2021, 91–92, 111269. [Google Scholar] [CrossRef] [Scilit]
- Robinson, S.M.; Reginster, J.Y.; Rizzoli, R.; Shaw, S.C.; Kanis, J.A.; Bautmans, I.; Bischoff-Ferrari, H.; Bruyère, O.; Cesari, M.; Dawson-Hughes, B.; et al. Does nutrition play a role in the prevention and management of sarcopenia? Clin. Nutr. 2018, 37, 1121–1132. [Google Scholar] [CrossRef] [Scilit]
- Cooper, C.; Fielding, R.; Visser, M.; van Loon, L.J.; Rolland, Y.; Orwoll, E.; Reid, K.; Boonen, S.; Dere, W.; Epstein, S.; et al. Tools in the assessment of sarcopenia. Calcif. Tissue Int. 2013, 93, 201–210. [Google Scholar] [CrossRef] [Scilit]
- American Diabetes Association Professional Practice Committee. 2. Classification and Diagnosis of Diabetes: Standards of Medical Care in Diabetes-2022. Diabetes Care 2022, 45 (Suppl. 1), S17–S38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teppala, S.; Shankar, A. Association between serum IGF-1 and diabetes among U.S. adults. Diabetes Care 2010, 33, 2257–2259. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papadopoulou, S. Sarcopenia: A Contemporary Health Problem among Older Adult Populations. Nutrients 2020, 12, 1293. [Google Scholar] [CrossRef] [Scilit]
- Korhonen, M.T.; Cristea, A.; Alén, M.; Häkkinen, K.; Sipilä, S.; Mero, A.; Viitasalo, J.T.; Larsson, L.; Suominen, H. Aging, muscle fiber type, and contractile function in sprint-trained athletes. J. Appl. Physiol. 2006, 101, 906–917. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chawla, R.; Chawla, A.; Jaggi, S. Microvascular and macrovascular complications in diabetes mellitus: Distinct or continuum? Indian J. Endocrinol. Metab. 2016, 20, 546. [Google Scholar] [CrossRef] [Scilit]
- Park, S.W.; Goodpaster, B.H.; Strotmeyer, E.S.; de Rekeneire, N.; Harris, T.B.; Schwartz, A.V.; Tylavsky, F.A.; Newman, A.B. Decreased Muscle Strength and Quality in Older Adults with Type 2 Diabetes. Diabetes 2006, 55, 1813–1818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palicka, V. Pathophysiology of Diabetes Mellitus. EJIFCC 2002, 13, 140–144. [Google Scholar]
- Park, S.W.; Goodpaster, B.H.; Lee, J.S.; Kuller, L.H.; Boudreau, R.; de Rekeneire, N.; Harris, T.B.; Kritchevsky, S.; Tylavsky, F.A.; Nevitt, M.; et al. Excessive Loss of Skeletal Muscle Mass in Older Adults with Type 2 Diabetes. Diabetes Care 2009, 32, 1993–1997. [Google Scholar] [CrossRef] [Scilit]
- Fielding, R.A.; Vellas, B.; Evans, W.J.; Bhasin, S.; Morley, J.E.; Newman, A.B.; Abellan van Kan, G.; Andrieu, S.; Bauer, J.; Breuille, D.; et al. Sarcopenia: An Undiagnosed Condition in Older Adults. Current Consensus Definition: Prevalence, Etiology, and Consequences. J. Am. Med. Dir. Assoc. 2011, 12, 249–256. [Google Scholar] [CrossRef] [Scilit]
- Wolfe, R.R. Effects of insulin on muscle tissue. Curr. Opin. Clin. Nutr. Metab. Care. 2000, 3, 67–71. [Google Scholar] [CrossRef] [Scilit]
- Morley, J.E.; Argiles, J.M.; Evans, W.J.; Bhasin, S.; Cella, D.; Deutz, N.E.P.; Doehner, W.; Fearon, K.C.H.; Ferrucci, L.; Hellerstein, M.K.; et al. Nutritional Recommendations for the Management of Sarcopenia. J. Am. Med. Dir. Assoc. 2010, 11, 391–396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cui, M.; Gang, X.; Wang, G.; Xiao, X.; Li, Z.; Jiang, Z.; Wang, G. A cross-sectional study: Associations between sarcopenia and clinical characteristics of patients with type 2 diabetes. Medicine 2020, 99, e18708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, P.G.; Halter, J.B. The Pathophysiology of Hyperglycemia in Older Adults: Clinical Considerations. Diabetes Care 2017, 40, 444–452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinclair, A.; Morley, J.E.; Rodriguez-Mañas, L.; Paolisso, G.; Bayer, T.; Zeyfang, A.; Bourdel-Marchasson, I.; Vischer, U.; Woo, J.; Chapman, I.; et al. Diabetes Mellitus in Older People: Position Statement on behalf of the International Association of Gerontology and Geriatrics (IAGG), the European Diabetes Working Party for Older People (EDWPOP), and the International Task Force of Experts in Diabetes. J. Am. Med. Dir. Assoc. 2012, 13, 497–502. [Google Scholar] [CrossRef] [Scilit]
- Landi, F.; Onder, G.; Bernabei, R. Sarcopenia and Diabetes: Two Sides of the Same Coin. J. Am. Med. Dir. Assoc. 2013, 14, 540–541. [Google Scholar] [CrossRef] [Scilit]
- Umegaki, H. Sarcopenia and diabetes: Hyperglycemia is a risk factor for age-associated muscle mass and functional reduction. J. Diabetes Investig. 2015, 6, 623–624. [Google Scholar] [CrossRef] [Scilit]
- Anagnostis, P.; Gkekas, N.K.; Achilla, C.; Pananastasiou, G.; Taouxidou, P.; Mitsiou, M.; Kenanidis, E.; Potoupnis, M.; Tsiridis, E.; Goulis, D.G. Type 2 Diabetes Mellitus is Associated with Increased Risk of Sarcopenia: A Systematic Review and Meta-analysis. Calcif. Tissue Int. 2020, 107, 453–463. [Google Scholar] [CrossRef] [Scilit]
- Veronese, N.; Pizzol, D.; Demurtas, J.; Soysal, P.; Smith, L.; Sieber, C.; Strandberg, T.; Bourdel-Marchasson, I.; Sinclair, A.; Petrovic, M.; et al. Association between sarcopenia and diabetes: A systematic review and meta-analysis of observational studies. Eur. Geriatr. Med. 2019, 10, 685–696. [Google Scholar] [CrossRef] [Scilit]
- Wang, T.; Feng, X.; Zhou, J.; Gong, H.; Xia, S.; Wei, Q.; Hu, X.; Tao, R.; Li, L.; Qian, F.; et al. Type 2 diabetes mellitus is associated with increased risks of sarcopenia and pre-sarcopenia in Chinese elderly. Sci. Rep. 2016, 6, 38937. [Google Scholar] [CrossRef] [Scilit]
- Kim, K.-S.; Park, K.-S.; Kim, M.-J.; Kim, S.-K.; Cho, Y.-W.; Park, S.W. Type 2 diabetes is associated with low muscle mass in older adults. Geriatr. Gerontol. Int. 2014, 14, 115–121. [Google Scholar] [CrossRef] [Scilit]
- Ai, Y.; Xu, R.; Liu, L. The prevalence and risk factors of sarcopenia in patients with type 2 diabetes mellitus: A systematic review and meta-analysis. Diabetol. Metab. Syndr. 2021, 13, 93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalyani, R.R.; Metter, E.J.; Egan, J.; Golden, S.H.; Ferrucci, L. Hyperglycemia predicts persistently lower muscle strength with aging. Diabetes Care 2015, 38, 82–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leenders, M.; Verdijk, L.B.; van der Hoeven, L.; Adam, J.J.; van Kranenburg, J.; Nilwik, R.; van Loon, L.J. Patients with type 2 diabetes show a greater decline in muscle mass, muscle strength, and functional capacity with aging. J. Am. Med. Dir. Assoc. 2013, 14, 585–592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chung, S.M.; Moon, J.S.; Chang, M.C. Prevalence of Sarcopenia and Its Association With Diabetes: A Meta-Analysis of Community-Dwelling Asian Population. Front. Med. 2021, 8, 681232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirwan, J.P.; Sacks, J.; Nieuwoudt, S. The essential role of exercise in the management of type 2 diabetes. Clevel. Clin. J. Med. 2017, 84, S15–S21. [Google Scholar] [CrossRef] [Scilit]
- Mitranun, W.; Deerochanawong, C.; Tanaka, H.; Suksom, D. Continuous vs interval training on glycemic control and macro- and microvascular reactivity in type 2 diabetic patients. Scand. J. Med. Sci. Sports 2014, 24, e69–e76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bauer, J.; Biolo, G.; Cederholm, T.; Cesari, M.; Cruz-Jentoft, A.J.; Morley, J.E.; Phillips, S.; Sieber, C.; Stehle, P.; Teta, D.; et al. Evidence-Based Recommendations for Optimal Dietary Protein Intake in Older People: A Position Paper From the PROT-AGE Study Group. J. Am. Med. Dir. Assoc. 2013, 14, 542–559. [Google Scholar] [CrossRef] [Scilit]
- Terada, T.; Friesen, A.; Chahal, B.S.; Bell, G.J.; McCargar, L.J.; Boulé, N.G. Feasibility and preliminary efficacy of high intensity interval training in type 2 diabetes. Diabetes Res. Clin. Pract. 2013, 99, 120–129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, H.-T.; Chung, Y.-C.; Chen, Y.-J.; Ho, S.-Y.; Wu, H.-J. Effects of Different Types of Exercise on Body Composition, Muscle Strength, and IGF-1 in the Elderly with Sarcopenic Obesity. J. Am. Geriatr. Soc. 2017, 65, 827–832. [Google Scholar] [CrossRef] [Scilit]
- Vlietstra, L.; Hendrickx, W.; Waters, D.L. Exercise interventions in healthy older adults with sarcopenia: A systematic review and meta-analysis. Australas. J. Ageing 2018, 37, 169–183. [Google Scholar] [CrossRef] [Scilit]
- Fleg, J.L. Aerobic exercise in the elderly: A key to successful aging. Discov. Med. 2012, 13, 223–228. [Google Scholar] [PubMed]
- Yoshimura, Y.; Wakabayashi, H.; Yamada, M.; Kim, H.; Harada, A.; Arai, H. Interventions for Treating Sarcopenia: A Systematic Review and Meta-Analysis of Randomized Controlled Studies. J. Am. Med. Dir. Assoc. 2017, 18, 553.e1–553.e16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, P.Y.; Huang, K.S.; Chen, K.M.; Chou, C.P.; Tu, Y.K. Exercise, Nutrition, and Combined Exercise and Nutrition in Older Adults with Sarcopenia: A Systematic Review and Network Meta-analysis. Maturitas 2021, 145, 38–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lustosa, L.P.; Silva, J.P.; Coelho, F.M.; Pereira, D.S.; Parentoni, A.N.; Pereira, L.S. Impact of resistance exercise program on functional capacity and muscular strength of knee extensor in pre-frail community-dwelling older women: A randomized crossover trial. Rev. Bras. Fisioter. 2011, 15, 318–324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seynnes, O.; Fiatarone Singh, M.A.; Hue, O.; Pras, P.; Legros, P.; Bernard, P.L. Physiological and functional responses to low-moderate versus high-intensity progressive resistance training in frail elders. J. Gerontol. A Biol. Sci. Med. Sci. 2004, 59, 503–509. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, J.-H.; Cheng, F.-C.; Tsai, L.-C.; Lee, N.-Y.; Lu, Y.-F. Appropriate physical activity and dietary intake achieve optimal metabolic control in older type 2 diabetes patients. J. Diabetes Investig. 2014, 5, 418–427. [Google Scholar] [CrossRef] [Scilit]
- Irvine, C.; Taylor, N.F. Progressive resistance exercise improves glycaemic control in people with type 2 diabetes mellitus: A systematic review. Aust. J. Physiother. 2009, 55, 237–246. [Google Scholar] [CrossRef] [Scilit]
- Kadoglou, N.P.; Fotiadis, G.; Kapelouzou, A.; Kostakis, A.; Liapis, C.D.; Vrabas, I.S. The differential anti-inflammatory effects of exercise modalities and their association with early carotid atherosclerosis progression in patients with type 2 diabetes. Diabet. Med. 2013, 30, e41–e50. [Google Scholar] [CrossRef] [Scilit]
- Hovanec, N.; Sawant, A.; Overend, T.J.; Petrella, R.J.; Vandervoort, A.A. Resistance Training and Older Adults with Type 2 Diabetes Mellitus: Strength of the Evidence. J. Aging Res. 2012, 2012, 284635. [Google Scholar] [CrossRef] [Scilit]
- Castaneda, C.; Layne, J.E.; Munoz-Orians, L.; Gordon, P.L.; Walsmith, J.; Foldvari, M.; Roubenoff, R.; Tucker, K.L.; Nelson, M.E. A randomized controlled trial of resistance exercise training to improve glycemic control in older adults with type 2 diabetes. Diabetes Care 2002, 25, 2335–2341. [Google Scholar] [CrossRef] [Scilit]
- Moses, A.C. Insulin resistance and type 2 diabetes mellitus: Is there a therapeutic role for IGF-1? Endocr. Dev. 2005, 9, 121–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Latham, N.K.; Anderson, C.S.; Lee, A.; Bennett, D.A.; Moseley, A.; Cameron, I.D.; Fitness Collaborative Group. A randomized, controlled trial of quadriceps resistance exercise and vitamin D in frail older people: The Frailty Interventions Trial in Elderly Subjects (FITNESS). J. Am. Geriatr. Soc. 2003, 51, 291–299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tan, S.; Li, W.; Wang, J. Effects of six months of combined aerobic and resistance training for elderly patients with a long history of type 2 diabetes. J. Sports Sci. Med. 2012, 11, 495–501. [Google Scholar] [PubMed]
- Børsheim, E.; Bui, Q.U.; Tissier, S.; Kobayashi, H.; Ferrando, A.A.; Wolfe, R.R. Effect of amino acid supplementation on muscle mass, strength and physical function in elderly. Clin. Nutr. 2008, 27, 189–195. [Google Scholar] [CrossRef] [Scilit]
- Tieland, M.; van de Rest, O.; Dirks, M.L.; van der Zwaluw, N.; Mensink, M.; van Loon, L.J.C.; de Groot, L.C.P.G.M. Protein Supplementation Improves Physical Performance in Frail Elderly People: A Randomized, Double-Blind, Placebo-Controlled Trial. J. Am. Med. Dir. Assoc. 2012, 13, 720–726. [Google Scholar] [CrossRef] [Scilit]
- Van Loon, L.J.; Kruijshoop, M.; Menheere, P.P.; Wagenmakers, A.J.; Saris, W.H.; Keizer, H.A. Amino acid ingestion strongly enhances insulin secretion in patients with long-term type 2 diabetes. Diabetes Care 2003, 26, 625–630. [Google Scholar] [CrossRef] [Scilit]
- Moslehi, N.; Shab-Bidar, S.; Mirmiran, P.; Sadeghi, M.; Azizi, F. Associations between dairy products consumption and risk of type 2 diabetes: Tehran lipid and glucose study. Int. J. Food Sci. Nutr. 2015, 66, 692–699. [Google Scholar] [CrossRef] [Scilit]
- Takahashi, F.; Hashimoto, Y.; Kaji, A.; Sakai, R.; Kawate, Y.; Okamura, T.; Kondo, Y.; Fukuda, T.; Kitagawa, N.; Okada, H.; et al. Vitamin Intake and Loss of Muscle Mass in Older People with Type 2 Diabetes: A Prospective Study of the KAMOGAWA-DM Cohort. Nutrients 2021, 13, 2335. [Google Scholar] [CrossRef] [Scilit]
- Bischoff, H.A.; Stahelin, H.B.; Urscheler, N.; Ehrsam, R.; Vonthein, R.; Perrig-Chiello, P.; Tyndall, A.; Theiler, R. Muscle strength in the elderly: Its relation to vitamin D metabolites. Arch. Phys. Med. Rehabil. 1999, 80, 54–58. [Google Scholar] [CrossRef] [Scilit]
- Lucato, P.; Solmi, M.; Maggi, S.; Bertocco, A.; Bano, G.; Trevisan, C.; Manzato, E.; Sergi, G.; Schofield, P.; Kouidrat, Y.; et al. Low vitamin D levels increase the risk of type 2 diabetes in older adults: A systematic review and meta-analysis. Maturitas 2017, 100, 8–15. [Google Scholar] [CrossRef] [Scilit]
- Okamura, T.; Hashimoto, Y.; Miki, A.; Kaji, A.; Sakai, R.; Iwai, K.; Osaka, T.; Ushigome, E.; Hamaguchi, M.; Yamazaki, M.; et al. Reduced dietary omega-3 fatty acids intake is associated with sarcopenia in elderly patients with type 2 diabetes: A cross-sectional study of KAMOGAWA-DM cohort study. J. Clin. Biochem. Nutr. 2020, 66, 233–237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Semba, R.D.; Blaum, C.; Guralnik, J.M.; Moncrief, D.T.; Ricks, M.O.; Fried, L.P. Carotenoid and vitamin E status are associated with indicators of sarcopenia among older women living in the community. Aging Clin. Exp. Res. 2003, 15, 482–487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, C.-D.; Chen, H.-C.; Huang, S.-W.; Liou, T.-H. The Role of Muscle Mass Gain Following Protein Supplementation Plus Exercise Therapy in Older Adults with Sarcopenia and Frailty Risks: A Systematic Review and Meta-Regression Analysis of Randomized Trials. Nutrients 2019, 11, 1713. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Egger, A.; Niederseer, D.; Diem, G.; Finkenzeller, T.; Ledl-Kurkowski, E.; Forstner, R.; Pirich, C.; Patsch, W.; Weitgasser, R.; Niebauer, J. Different types of resistance training in type 2 diabetes mellitus: Effects on glycaemic control, muscle mass and strength. Eur. J. Prev. Cardiol. 2012, 20, 1051–1060. [Google Scholar] [CrossRef] [Scilit]
- Amamou, T.; Normandin, E.; Pouliot, J.; Dionne, I.J.; Brochu, M.; Riesco, E. Effect of a High-Protein Energy-Restricted Diet Combined with Resistance Training on Metabolic Profile in Older Individuals with Metabolic Impairments. J. Nutr. Health Aging 2017, 21, 67–74. [Google Scholar] [CrossRef] [Scilit]
- Fragala, M.S.; Cadore, E.L.; Dorgo, S.; Izquierdo, M.; Kraemer, W.J.; Peterson, M.D.; Ryan, E.D. Resistance Training for Older Adults: Position Statement from the National Strength and Conditioning Association. J. Strength Cond. Res. 2019, 33, 2019–2052. [Google Scholar] [CrossRef] [Scilit]
- Lynch, C.J.; Adams, S.H. Branched-chain amino acids in metabolic signalling and insulin resistance. Nat. Rev. Endocrinol. 2014, 10, 723–736. [Google Scholar] [CrossRef] [Scilit]
- Algoblan, A.; Alalfi, M.; Khan, M. Mechanism linking diabetes mellitus and obesity. Diabetes Metab. Syndr. Obes. Targets Ther. 2014, 7, 587–591. [Google Scholar] [CrossRef] [Scilit]
- Advika, T.S.; Idiculla, J.; Kumari, S.J. Exercise in patients with Type 2 diabetes: Facilitators and barriers—A qualitative study. J. Family Med. Prim. Care 2017, 6, 288–292. [Google Scholar] [CrossRef] [Scilit]
- Phu, S.; Boersma, D.; Duque, G. Exercise and Sarcopenia. J. Clin. Densitom. 2015, 18, 488–492. [Google Scholar] [CrossRef] [Scilit]
- Yoo, S.-Z.; No, M.-H.; Heo, J.-W.; Park, D.-H.; Kang, J.-H.; Kim, S.H.; Kwak, H.-B. Role of exercise in age-related sarcopenia. J. Exerc. Rehabil. 2018, 14, 551–558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Colberg, S.R.; Sigal, R.J.; Yardley, J.E.; Riddell, M.C.; Dunstan, D.W.; Dempsey, P.C.; Horton, E.S.; Castorino, K.; Tate, D.F. Physical Activity/Exercise and Diabetes: A Position Statement of the American Diabetes Association. Diabetes Care 2016, 39, 2065–2079. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neville, S.E.; Boye, K.S.; Montgomery, W.S.; Iwamoto, K.; Okamura, M.; Hayes, R.P. Diabetes in Japan: A review of disease burden and approaches to treatment. Diabetes/Metab. Res. Rev. 2009, 25, 705–716. [Google Scholar] [CrossRef] [Scilit]
- Mumu, S.J.; Saleh, F.; Ara, F.; Afnan, F.; Ali, L. Non-adherence to life-style modification and its factors among type 2 diabetic patients. Indian J. Public Health 2014, 58, 40–44. [Google Scholar] [CrossRef] [Scilit]
- Greco, M.; Chiefari, E.; Montalcini, T.; Accattato, F.; Costanzo, F.S.; Pujia, A.; Foti, D.; Brunetti, A.; Gulletta, E. Early Effects of a Hypocaloric, Mediterranean Diet on Laboratory Parameters in Obese Individuals. Mediat. Inflamm. 2014, 2014, 750860. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sardeli, A.; Komatsu, T.; Mori, M.; Gáspari, A.; Chacon-Mikahil, M. Resistance Training Prevents Muscle Loss Induced by Caloric Restriction in Obese Elderly Individuals: A Systematic Review and Meta-Analysis. Nutrients 2018, 10, 423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weinheimer, E.M.; Sands, L.P.; Campbell, W.W. A systematic review of the separate and combined effects of energy restriction and exercise on fat-free mass in middle-aged and older adults: Implications for sarcopenic obesity. Nutr. Rev. 2010, 68, 375–388. [Google Scholar] [CrossRef] [Scilit]
- Bilsborough, S.; Mann, N. A review of issues of dietary protein intake in humans. Int. J. Sport Nutr. Exerc. Metab. 2006, 16, 129–152. [Google Scholar] [CrossRef] [Scilit]
- Borack, M.S.; Volpi, E. Efficacy and Safety of Leucine Supplementation in the Elderly. J. Nutr. 2016, 146, 2625S–2629S. [Google Scholar] [CrossRef] [Scilit]
- Robinson, S.; Cooper, C.; Aihie Sayer, A. Nutrition and Sarcopenia: A Review of the Evidence and Implications for Preventive Strategies. J. Aging Res. 2012, 2012, 5108016. [Google Scholar] [CrossRef] [Scilit]
- Wilkinson, D.J.; Hossain, T.; Hill, D.S.; Phillips, B.E.; Crossland, H.; Williams, J.; Loughna, P.; Churchward-Venne, T.A.; Breen, L.; Phillips, S.M.; et al. Effects of leucine and its metabolite β-hydroxy-β-methylbutyrate on human skeletal muscle protein metabolism. J. Physiol. 2013, 591, 2911–2923. [Google Scholar] [CrossRef] [Scilit]
- Kuriyan, R.; Lokesh, D.P.; Selvam, S.; Jayakumar, J.; Philip, M.G.; Shreeram, S.; Kurpad, A.V. The relationship of endogenous plasma concentrations of β-Hydroxy β-Methyl Butyrate (HMB) to age and total appendicular lean mass in humans. Exp. Gerontol. 2016, 81, 13–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mesinovic, J.; Zengin, A.; De Courten, B.; Ebeling, P.R.; Scott, D. Sarcopenia and type 2 diabetes mellitus: A bidirectional relationship. Diabetes, Metabolic Syndrome and Obesity: Targets Ther. 2019, 12, 1057–1072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stockton, K.A.; Mengersen, K.; Paratz, J.D.; Kandiah, D.; Bennell, K.L. Effect of vitamin D supplementation on muscle strength: A systematic review and meta-analysis. Osteoporos. Int. 2010, 22, 859–871. [Google Scholar] [CrossRef] [Scilit]
- Beaudart, C.; Buckinx, F.; Rabenda, V.; Gillain, S.; Cavalier, E.; Slomian, J.; Petermans, J.; Reginster, J.-Y.; Bruyère, O. The Effects of Vitamin D on Skeletal Muscle Strength, Muscle Mass, and Muscle Power: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J. Clin. Endocrinol. Metab. 2014, 99, 4336–4345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Facchini, F.S.; Humphreys, M.H.; DoNascimento, C.A.; Abbasi, F.; Reaven, G.M. Relation between insulin resistance and plasma concentrations of lipid hydroperoxides, carotenoids, and tocopherols. Am. J. Clin. Nutr. 2000, 72, 776–779. [Google Scholar] [CrossRef] [Scilit]
- Cesari, M.; Pahor, M.; Bartali, B.; Cherubini, A.; Penninx, B.W.; Williams, G.R.; Atkinson, H.; Martin, A.; Guralnik, J.M.; Ferrucci, L. Antioxidants and physical performance in elderly persons: The Invecchiare in Chianti (InCHIANTI) study. Am. J. Clin. Nutr. 2004, 79, 289–294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hozawa, A.; Jacobs, D.R.; Steffes, M.W.; Gross, M.D.; Steffen, L.M.; Lee, D.-H. Associations of Serum Carotenoid Concentrations with the Development of Diabetes and with Insulin Concentration: Interaction with Smoking. Am. J. Epidemiol. 2006, 163, 929–937. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Franz, M.; Boucher, J.L.; Evert, A.B. Evidence-based diabetes nutrition therapy recommendations are effective: The key is individualization. Diabetes Metab. Syndr. Obes. Targets Ther. 2014, 7, 65–72. [Google Scholar] [CrossRef] [Scilit]
- Fukushima, Y.; Kurose, S.; Shinno, H.; Cao Thu, H.; Takao, N.; Tsutsumi, H.; Kimura, Y. Importance of Lean Muscle Maintenance to Improve Insulin Resistance by Body Weight Reduction in Female Patients with Obesity. Diabetes Metab. J. 2016, 40, 147–153. [Google Scholar] [CrossRef] [Scilit]
- Ross, R.; Janssen, I.; Dawson, J.; Kungl, A.M.; Kuk, J.L.; Wong, S.L.; Nguyen-Duy, T.B.; Lee, S.; Kilpatrick, K.; Hudson, R. Exercise-induced reduction in obesity and insulin resistance in women: A randomized controlled trial. Obes. Res. 2004, 12, 789–798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weinstock, R.S.; Dai, H.; Wadden, T.A. Diet and exercise in the treatment of obesity: Effects of 3 interventions on insulin resistance. Arch. Intern. Med. 1998, 158, 2477–2483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suh, S.; Jeong, I.-K.; Kim, M.Y.; Kim, Y.S.; Shin, S.; Kim, S.S.; Kim, J.H. Effects of Resistance Training and Aerobic Exercise on Insulin Sensitivity in Overweight Korean Adolescents: A Controlled Randomized Trial. Diabetes Metab. J. 2011, 35, 418–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takamura, Y.; Nomura, M.; Uchiyama, A.; Fujita, S. Effects of Aerobic Exercise Combined with Panaxatriol Derived from Ginseng on Insulin Resistance and Skeletal Muscle Mass in Type 2 Diabetic Mice. J. Nutr. Sci. Vitaminol. (Tokyo) 2017, 63, 339–348. [Google Scholar] [CrossRef] [Scilit]
- Takahashi, F.; Hashimoto, Y.; Kaji, A.; Sakai, R.; Kawate, Y.; Okamura, T.; Kitagawa, N.; Okada, H.; Nakanishi, N.; Majima, S.; et al. Association between Geriatric Nutrition Risk Index and The Presence of Sarcopenia in People with Type 2 Diabetes Mellitus: A Cross-Sectional Study. Nutrients 2021, 13, 3729. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).