


Abstract
Introduction: Youth-friendly sexual and reproductive health (SRH) interventions are essential for the health of adolescents (10–19 years). Co-designing is a participatory approach to research, allowing for collaboration with academic and non-academic stakeholders in intervention development. Participatory action research (PAR) involves stakeholders throughout the planning, action, observation, and reflection stages of research. Current knowledge indicates that co-producing SRH interventions with adolescents increases a feeling of ownership, setting the scene for intervention adoption in implementation settings. Objectives: This scoping review aims to understand the extent of adolescents’ participation in PAR steps for co-designed SRH interventions, including the barriers and facilitators in co-designing of SRH intervention, as well as its effectiveness on adolescents’ SRH outcomes. Methods: Database searching of PubMed, Medline, Embase, CINAHL, Scopus, Web of Science, Google Scholar, and organisational websites was performed, identifying 439 studies. Results: Upon screening, 30 studies (published between 2006–2021) met the inclusion criteria. The synthesis identified that adolescents were involved in the planning and action stages of the interventions, but not in the observation and reflection stages. Although the review identified the barriers and facilitators for co-designing SRF interventions, none of the included studies reported on the effectiveness of co-designing SRH interventions with adolescents; therefore, meta-analysis was not performed. Conclusions: While no specific outcome of the interventions was reported, all papers agreed that adolescent co-designing in ASRH interventions should occur at all stages to increase understanding of local perceptions and develop a successful intervention.
1. Introduction
The period of the maturation and development of adolescents into adulthood is an important phase of one’s life that is often accompanied by heightened sexual attention, thought, and experimentation. The chance of contracting sexually transmitted infections (STIs), unintended pregnancies, or early childbearing increases with ill-informed early sexual experimentation [1]. Adolescents across the globe face sexual and reproductive health (SRH) complications, due to a lack of informative services, barriers to such services, social stigmas, laws, and policies [1]. The adolescent period involves significant development; thus, it can be determinative of SRH risks in later life. Consequently, adolescence is an optimal stage for targeted SRH interventions [2,3]. Providing suitable adolescent sexual and reproductive health (ASRH) interventions at the appropriate time and setting makes it possible to improve these statistics in the future.
Co-designing is a participatory action research (PAR) approach that allows community and individual involvement in developing and implementing interventions by providing a personal opinion, expertise, and life experience on the relevant topic [4]. This gives the investigator a deeper understanding of the community’s requirements, which might otherwise be misunderstood or misinterpreted [4,5,6,7].
Co-designing has been applied to various fields that require scientific understanding to be balanced with the public’s knowledge, information, and experience. This has resulted in many valuable improvements, as adolescents and academics benefit from knowledge sharing and exchange [3,6]. Overall, academics view the collaboration with non-academic stakeholders as a rewarding and enriching experience of learning contextual knowledge [8]. Co-designing addresses power imbalances in research partnerships, whereby design partners are involved and treated as equals in all decision-making [5]. Further, studies that involved co-designing with adolescents indicated that adolescent involvement in the planning, design, and development stages ensured the intervention met the adolescent’s needs and captured their perspectives, insights, and lived experiences, thus providing a better context [5]. One review of the effectiveness of initiatives to improve adolescent access to and utilization of SRH services in low and middle income countries (LMICs) found that adolescent involvement in project stages created more than a twofold increase in the self-reported use of SRH services, compared to when such initiatives were not made [9]. Although this review was not specific to co-design, it still provides evidence of the benefits of adolescent involvement.
Co-designed health programs and interventions are increasingly being implemented into different settings across the globe to induce health improvements in communities. Consequently, there is a need to understand how these can best be delivered across health systems and diverse settings [6]. There is also a need to understand the barriers to co-designing and how these can be overcome [6]. ASRH issues and interventions can be subject to limited funding and political challenges, similar to any other health issues, in general, that may limit the scale, scope, and methodologic rigor. In turn, this can limit the reproducibility, generalizability, and dissemination of the research [10]. The current understanding of co-designed interventions is that co-producing implementation strategies with non-academic stakeholders enable stakeholder ownership of these implementation strategies, setting the scene for their adoption in implementation settings. However, this has not yet been reviewed systematically [6]; hence, the existence of this systematic review.
This scoping review aims to understand the extent of adolescents’ participation in PAR steps for co-designed SRH interventions, including the barriers and facilitators in the co-designing of SRH intervention and its effectiveness on adolescents’ SRH outcomes, such as improved contraception use, utilization of sexually transmitted infections (STI)/HIV services, unintended pregnancies, etc.
2. Methodology
The review followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses Extension for Scoping Reviews (PRISMA-ScR) 2018 guidelines [11] to complete the review (Supplementary Table S1).
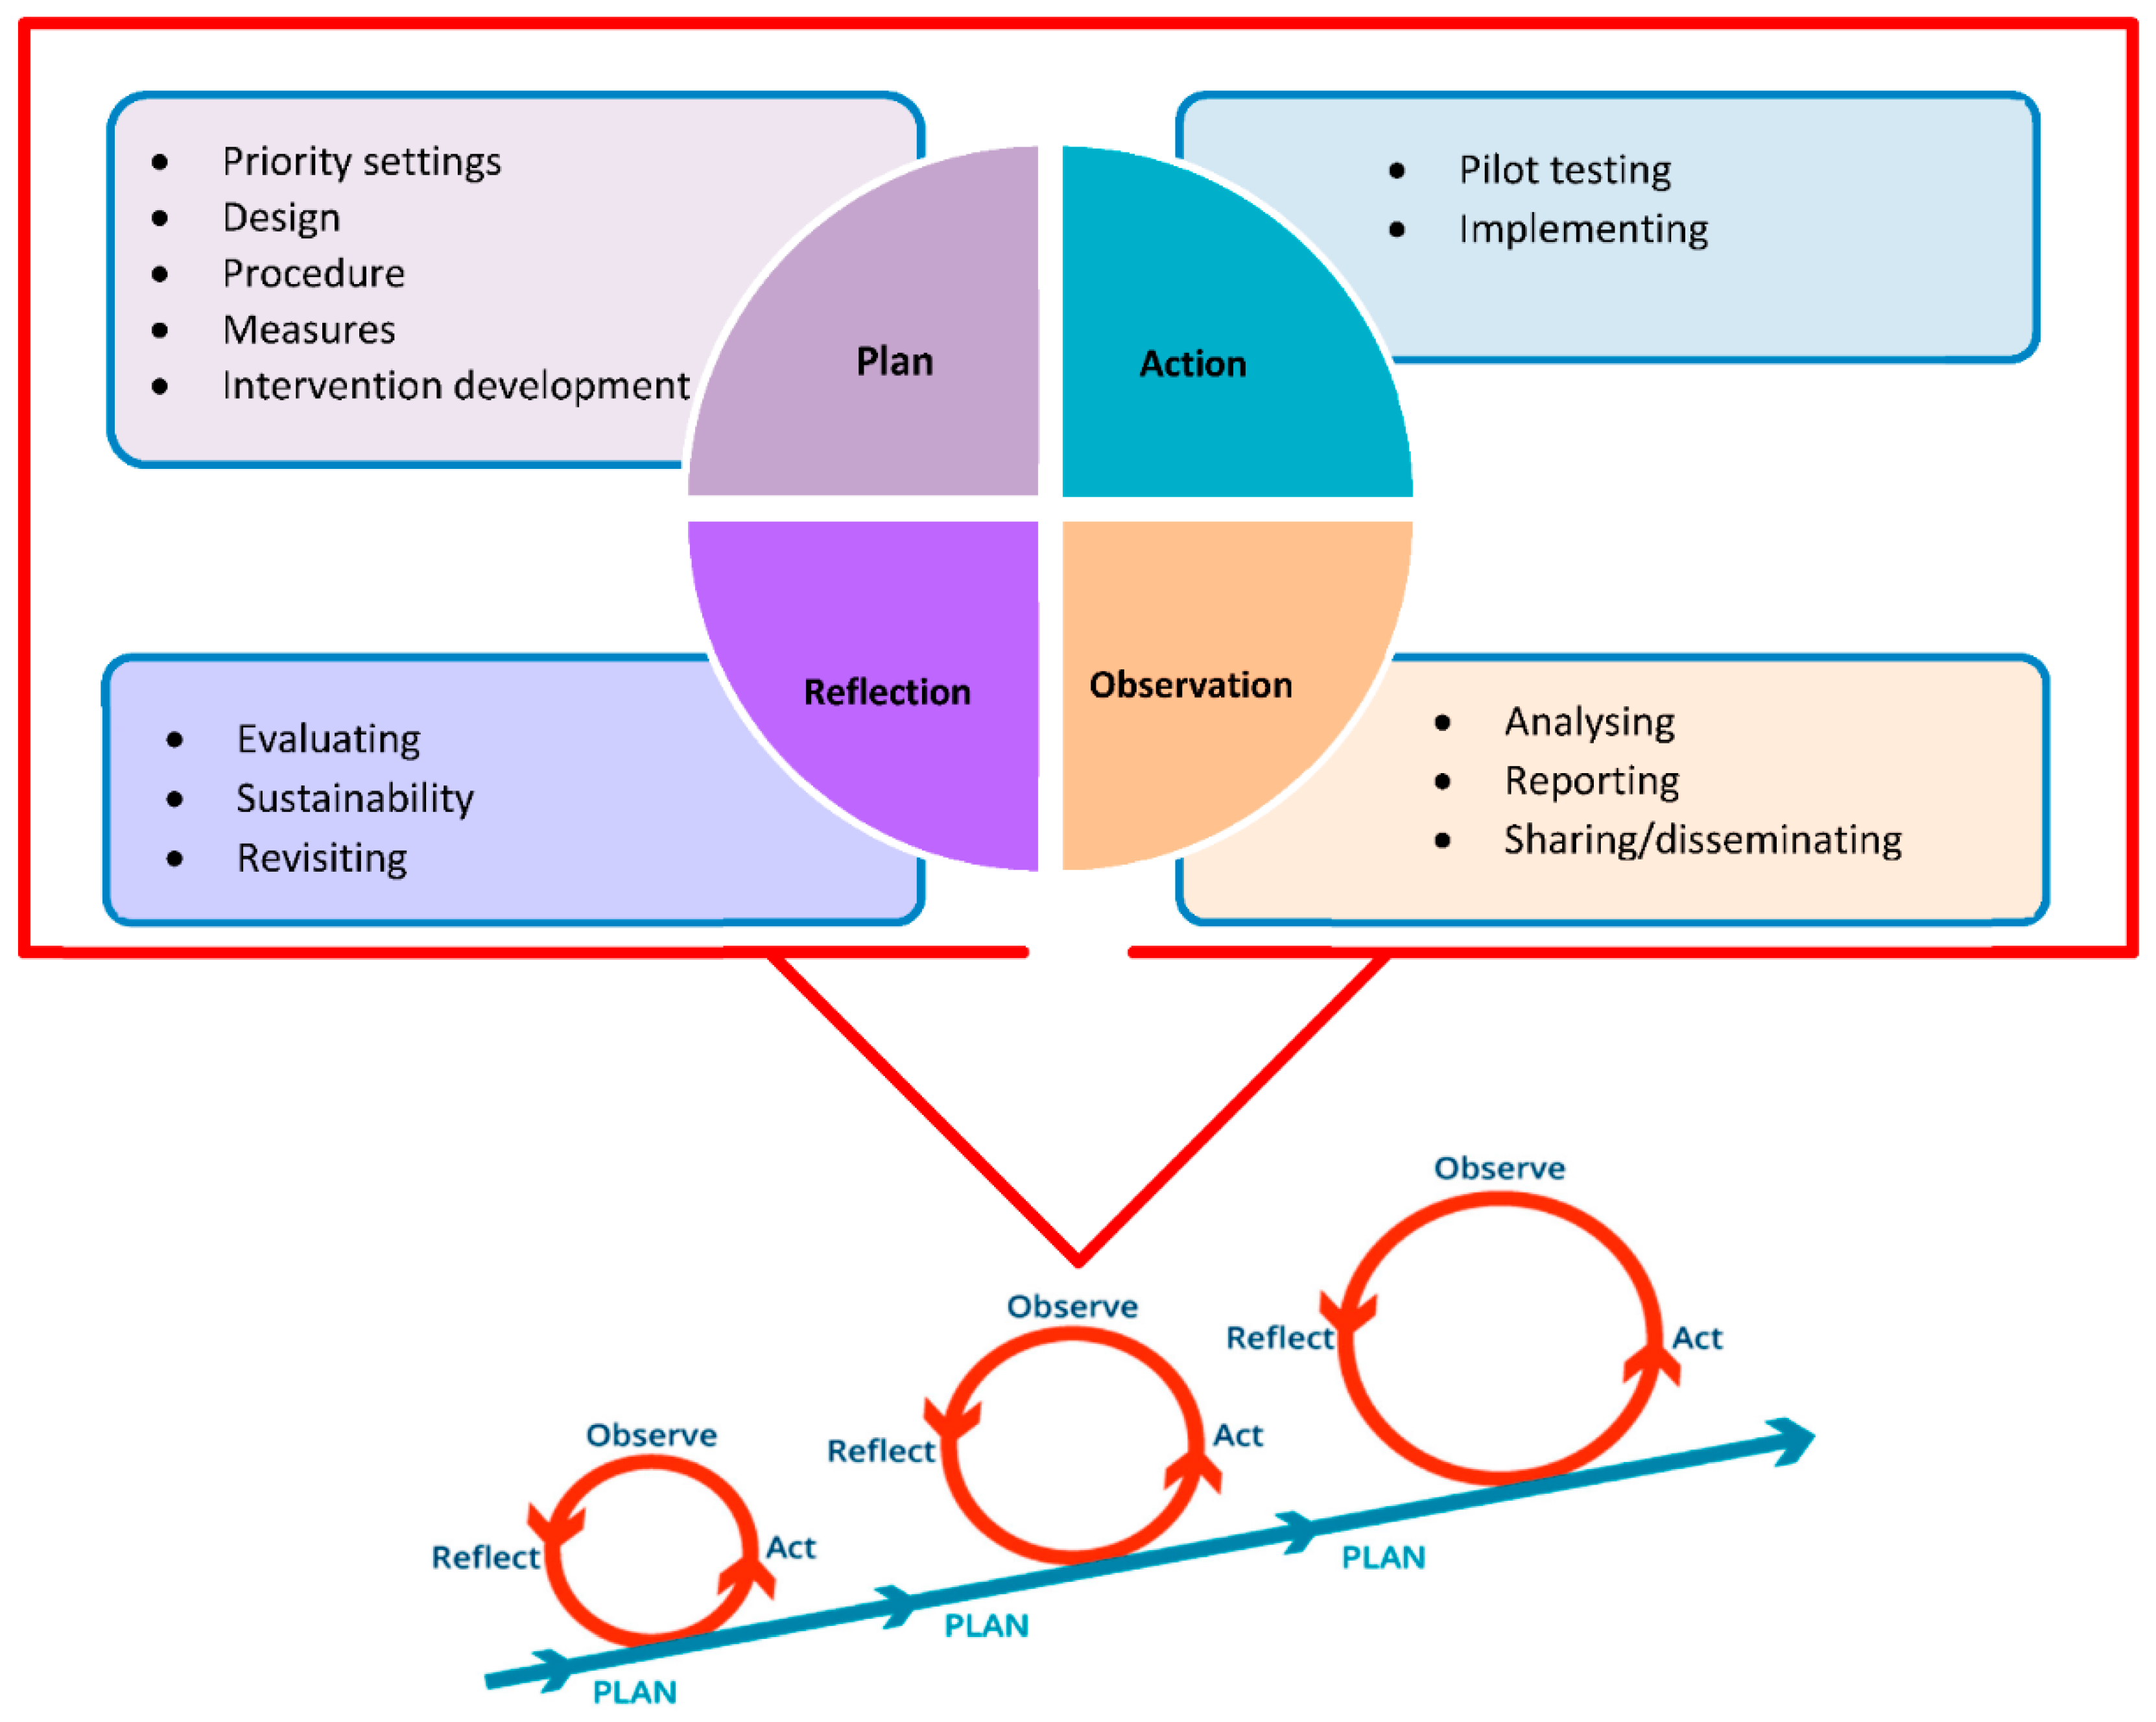
The review included all experimental, observational, and qualitative studies, based anywhere globally, that involved adolescent participants aged 10–19 years. Studies that included youth aged up to 24 years were included, as long as the data, relating to the age group of interest, was included. The review focused on studies that involved co-designing ASRH interventions and reported PAR process (Figure 1), barriers, facilitators, and effectiveness of co-designed interventions on improved SRH outcomes. The review was gender-neutral and we avoided gender specific terminologies to avoid stereotyping, as it was interested in specific role of adolescents (regardless of their sex and gender roles) in co-designing interventions for SRH.
Figure 1.
Steps for participatory action research framework.
The literature search was conducted on the following electronic databases: PubMed, Medline, Embase, CINAHL, Scopus, and Web of Science, as well as grey literature on Google Scholar and organizational websites. These databases were searched using a combination of natural language vocabulary and controlled terms (subject headings) wherever they were available. Natural language terms were derived from three main concepts: (1) sexual and reproductive health, (2) co-designing of interventions, and (3) adolescents. Publication date, language, and study type restrictions were not applied to increase search sensitivity. Other search methods were employed to retrieve additional evidence. The following search strategy was used to search the databases: “((Sexual) AND (reproductive) AND (health)) AND (adolescent* OR young OR teen OR teenage) AND (co-design OR codesign OR “community-based participatory research: OR “community-based participatory research” OR “consumer participation” OR “action research” OR “participatory design” OR co-production)”.
All primary research studies from the databases were uploaded on Covidence, a web-based tool that helps to identify studies and involves data-extraction processes [12]. Two reviewers (BA and EN) independently screened all potential articles. In case of disagreement, both reviewers read the paper and discussed it with the senior reviewer (ZL) until they reached a consensus. The reviewers (BA and EN) independently screened all title/abstracts and eligible full-text articles and included papers in this review that satisfied the inclusion criteria.
We extracted relevant data from each study, including the year, study design, setting, target population, sample size, and co-designed activity for SRH intervention, and the results were measured and reported (see Table 1). Two reviewers (BA and EN) extracted data, and the senior reviewer (ZL) resolved the consensus.
3. Results
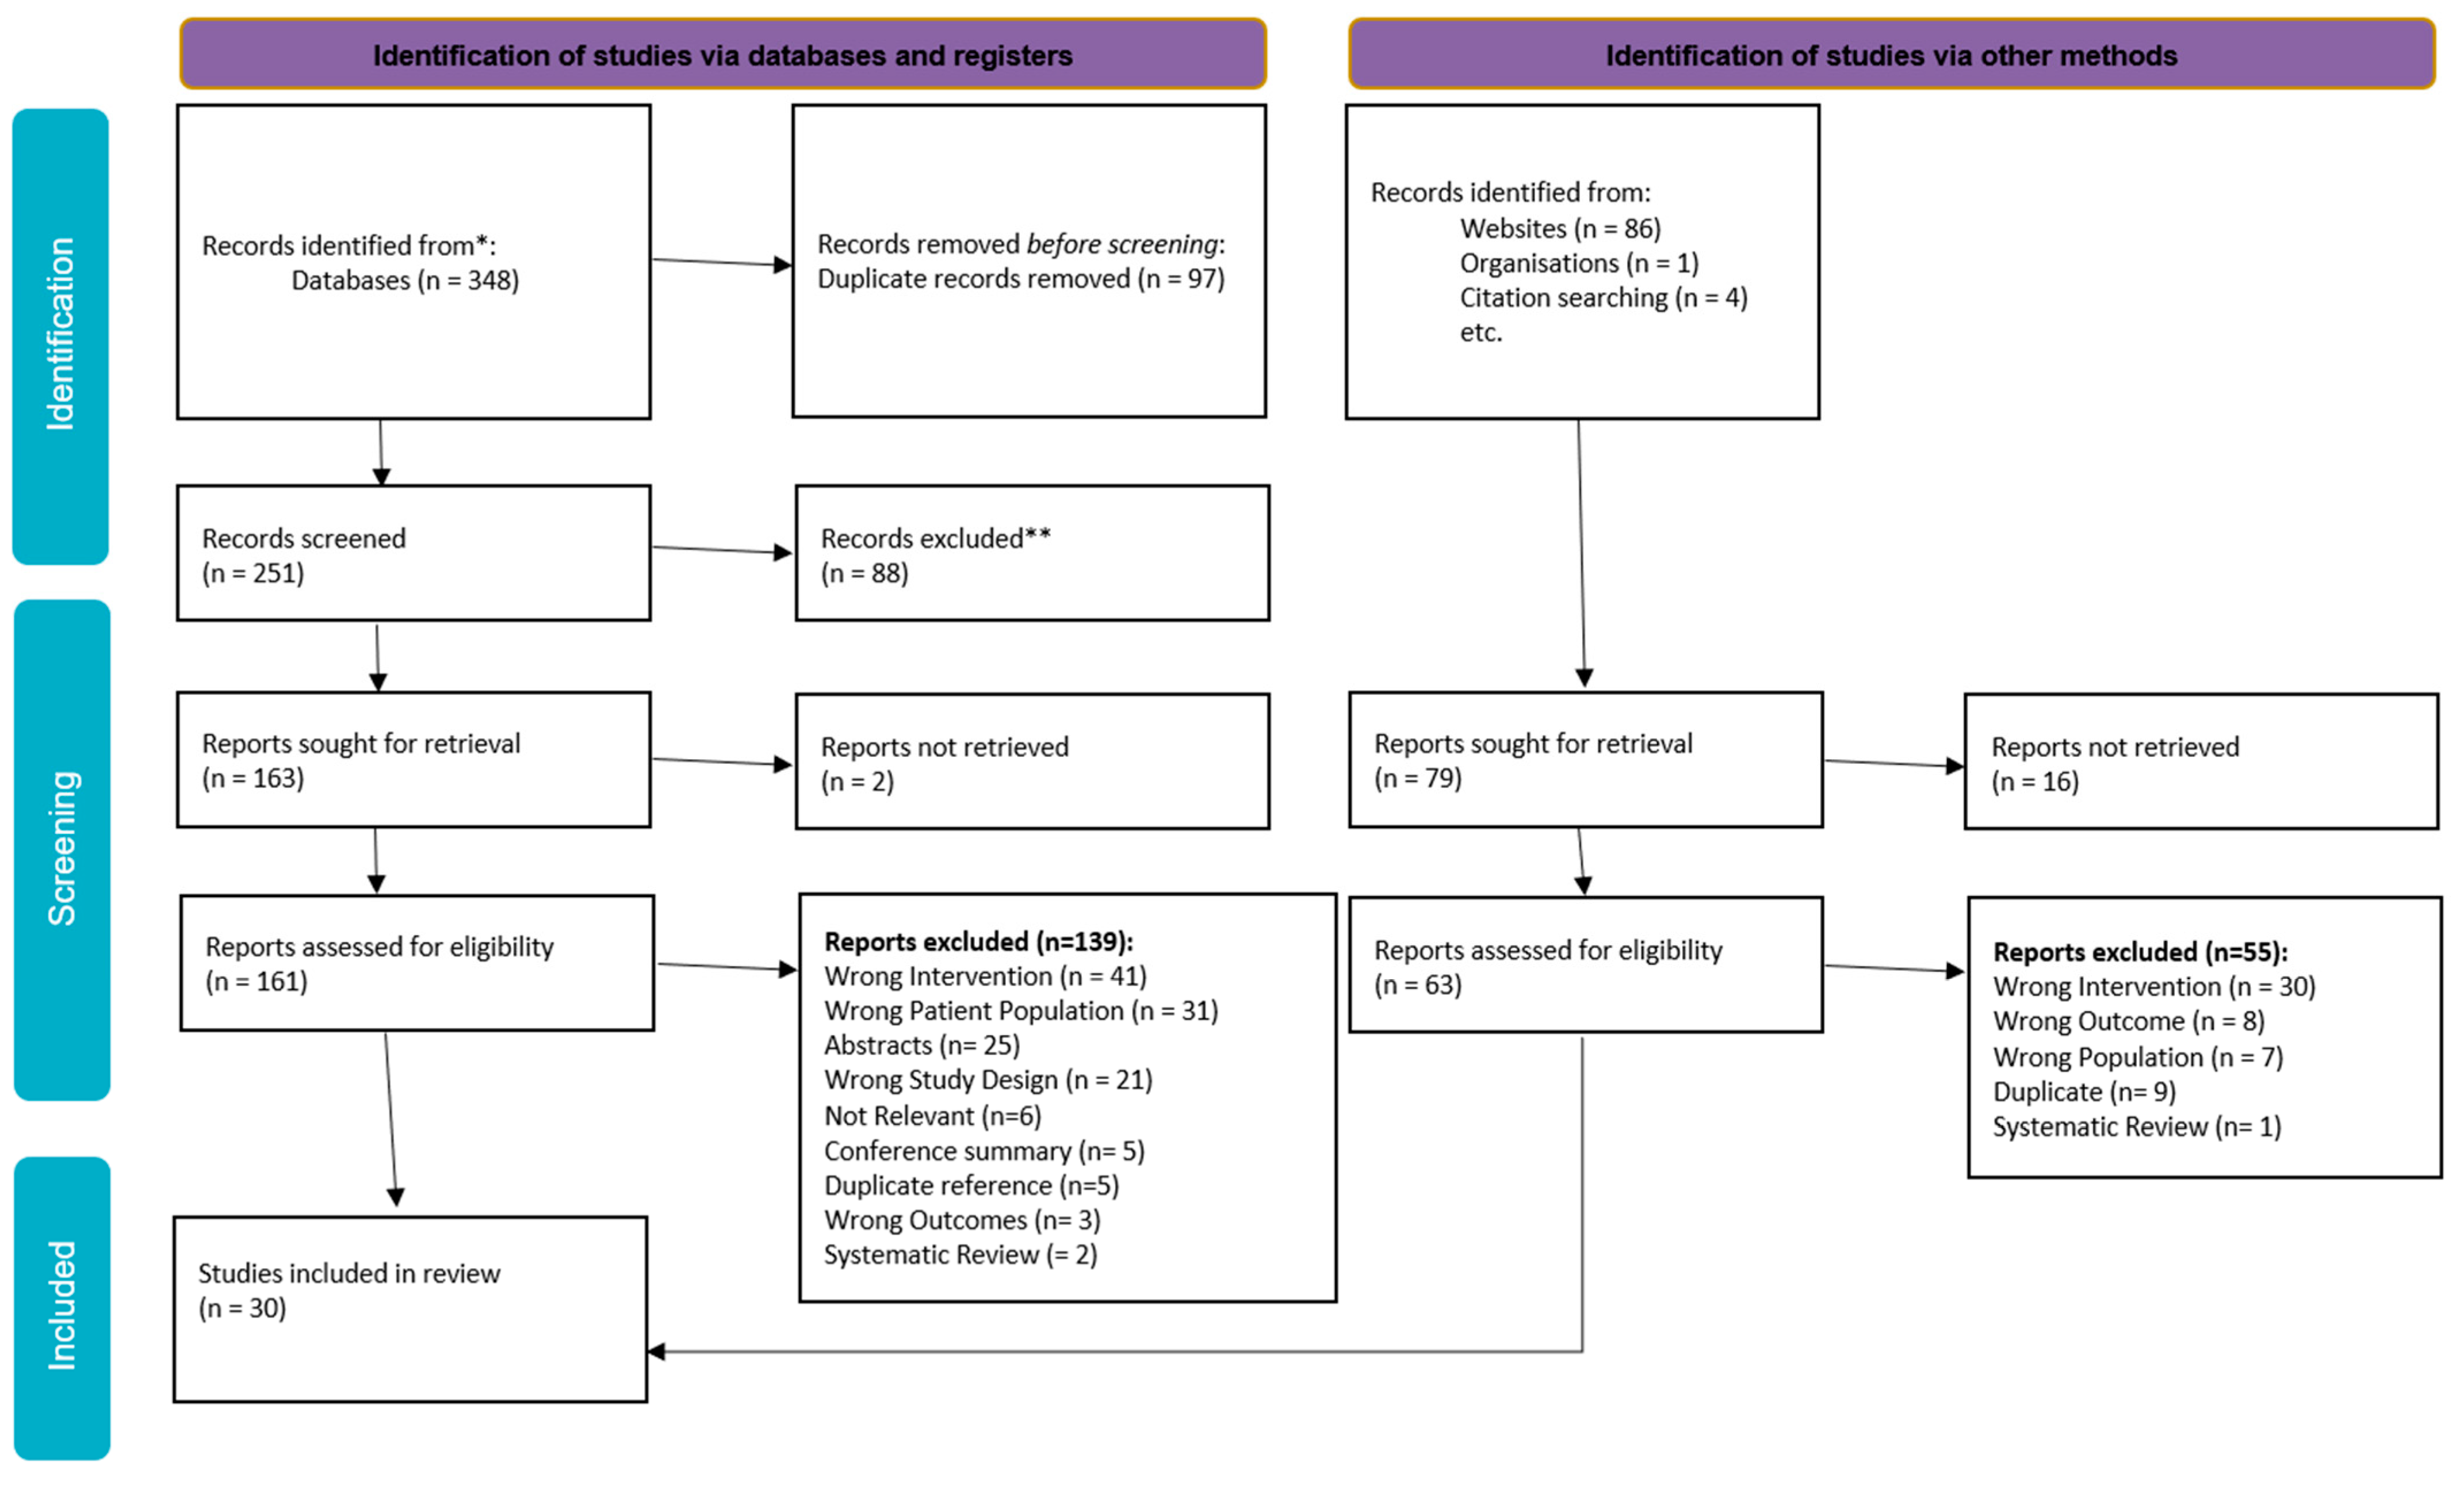
The search identified 439 papers; from those, 97 duplicate papers were removed. After the initial title and abstract screening, 88 papers were excluded, leaving 242 full-texts to be reviewed. Of these, 194 papers were excluded for not meeting our criteria, leaving 30 studies selected for extraction and synthesis (Figure 2), published between 2006–2021.
Figure 2.
PRISMA Flow diagram.
The characteristics of included studies are reported in Table 1. Of the 30 included studies, two studies involved younger adolescents (aged 10–14 years) [13,14], 14 involved older adolescents (aged 15–19 years) [5,15,16,17,18,19,20,21,22,23,24,25,26,27], and 13 studies involved both [13,28,29,30,31,32,33,34,35,36,37,38,39]; however, one study did not define the age groups [40].
Table 1.
Characteristics of included studies.
The studies were based in a range of different settings. Approximately half (n = 16) of the studies were conducted in high-income countries (HIC) [5,13,15,17,18,19,20,21,22,23,27,28,29,30,33,39], and the other half (n = 14) was conducted in low- and middle-income countries (LMIC) [14,16,24,25,26,31,32,34,35,36,37,38,40,41]. There were nine from the USA [13,20,22,23,27,29,30,33,39], three studies from Australia [5,15,17], two each from Canada [18,19], and South Africa [24,26], one each from China [14], Kenya [38], Mexico [34], Peru [31], Rwanda [40], Tanzania [32], Thailand [41], The Netherlands [28], the UK [21], Uganda [36], and Zambia [25]. There were three multi-country studies (South Africa and Lesotho) [16], (Bolivia, Ecuador, Nicaragua) [35], and sub-Saharan Africa [37].
Of those studies that defined settings, 12 studies based in an urban setting [15,18,19,21,23,28,30,32,33,34,40,41], with six of those conducted in schools [21,23,28,32,33,41] and six in community [15,18,19,30,34,40], as well as 12 studies in rural settings [13,14,16,17,24,25,27,31,35,36,37,39], with four of those based in schools [14,17,36,39] and eight in community [13,16,24,25,27,31,35,37].
Sample sizes ranged from 9 to 2643 participants. Of all the included studies, 2 were experimental studies [13,32], 23 were observational or qualitative [14,16,18,19,20,21,22,23,24,25,26,29,30,31,33,34,35,36,37,38,39,40,41], and 5 were mixed methods [5,15,17,27,28].
Participatory action research (PAR) framework: We used the PAR framework to assess the studies and synthesize the data. The adolescents were involved in the planning and action stages of the implementation, through various co-designing ways. Some used one method and others used a combination of co-designed workshops, focus group discussions, semi-structured interviews, in-depth interviews, photovoice sessions, and youth advisory committees or youth working groups/youth club meetings. The PAR framework for co-designing was used for preparing intervention programs for abortion [15], sex education material [16,21,23,27,28,31,32,41], contraception [17,40], risky sexual behaviour leading to STI/HIV [14,18,20,22,24,25,29,33,37,38,39], adolescent pregnancy [30,34,35], preconception health [5], and peer education program [19,26,36]. Each of the included studies was assessed to understand the stages of PAR incorporated in co-designing SRH interventions for adolescents.
Planning: Studies have reported several different ways of involving adolescents in the planning phase. A study reported that the youth leadership council involved preparing and submitting the proposal to fund the research, identifying the target population, developing the study design, and disseminating the study findings [29]. Another study, through a series of workshops, involved youth in brainstorming ideas for intervention content and design and developed rapid prototypes alongside the design team [13]. Adolescents were also utilised in developing SRH education and HIV/AIDS prevention curriculum [41] and provided insight into what they would like to gain from the intervention [19,24,38].
Action: Action involves adolescents co-designing the pilot testing and actual implementation. The studies involved adolescents in one-on-one semi-structured interviews to gain an in-depth understanding of the adolescent experience and care trajectories [15] and explore the range of issues connected to how pupils experienced sexuality education at school [28]. Additionally, they built advisory groups to consult on how best to engage with the broader community for a successful project, address culturally-sensitive issues, and adapt the intervention [13,30]. They also shared their knowledge on HIV and STI prevention, attitudes regarding HIV and STIs, and self-stigma. Adolescents feel fear, as well as alone, and some are in denial about their status [19,33,38]. On the other hand, adolescents were involved in the implementation phase of a few studies, where they facilitated the condom-mapping workshops, prototype testing, and supplied feedback on improvements [22,24,25,31,32,33,34,39,40].
Observation: Only one study reported involving the youth leadership council in disseminating the study findings [29].
Reflection: No studies involved adolescents in the reflection stages.
Barriers: Twenty-one studies identified barriers to co-designing SRH interventions, including adolescents confidentiality concerns regarding the sharing of their personal information [21,34], cultural taboos, culturally appropriate communications [5,14,16,20,22,27,35,37], stereotyping adolescence, and making assumptions or judgments [26,28]. Additional barriers were voiced to potentially negative community reactions [39] and access to health care professionals and information [31,35,36]. Barriers regarding external factors included fear due to parents being undocumented immigrants [23], lack of safe space, poor transport, and misinformation from caregivers [18,19,24,33,40].
Facilitators: Twenty-two studies identified facilitators to co-designing, including cultural adaptation [16,30,39], culturally relevant content [20,23], a reliable, professional, and friendly tone of researchers [31,36], and a safe atmosphere [24,28,32]. Furthermore, peer navigators were seen as facilitators of co-designing as adolescents were more comfortable sharing SRH issues, such as condom use, with their peers rather than adults. Additional facilitators identified include reliable content [31,32], adolescents feeling as though their involvement was effective in addressing critical problems [32], and a continuous feedback loop with community inputs [33]. Four studies found that using technological devices was useful to overcome the barriers of remoteness and poor transport and effective use of technologies in remote areas [34,35,40]. Further facilitators were identified as engaging youth as critical informants [5,18,19,25,26,37,41], and interventions that support school policy, values, standards, and behavioural expectations facilitated co-design partnerships [14,41].
Effectiveness of co-designing of SRH interventions: The studies did not report on the effectiveness of co-designing of SRH interventions with adolescents; therefore, meta-analysis was not performed.
4. Discussion
This review aimed to understand adolescents’ participation in PAR for co-designed ASRH interventions. The studies included in this review collectively indicate the benefits of co-designing ASRH interventions and different ways adolescents can be involved. Following the PAR framework, adolescents were engaged in developing SRH interventions through the planning and action stages. During the planning aspects of the interventions, adolescents were involved in preparing and submitting the proposal [13,29]. This information was provided by adolescents’ involvement in youth leadership groups and workshops, which aided the design team in the rapid development of the intervention [13,29].
The information and insight provided by the adolescents allow the primary research to gain an improved understanding of their current knowledge on SRH topics and what they want to gain from the intervention [19,24,38,41]. Throughout the action stages, adolescents were involved in trialing, collecting data, questioning fellow adolescents, and other pilot testing interventions. Adolescent-led, semi-structured, one-on-one interviews, group discussions, and advisory groups were used to explore a range of SRH issues and consult on how best to engage with the broader community for a successful project to address culturally-sensitive issues [13,28,30]. Through the implementation and troubleshooting of the interventions, adolescents were able to supply feedback and improvements to adapt to the intervention [24,25,31,32,33,34,39,40]. Only one study planned on involving the adolescent in the observation stage, through a youth leadership council that was involved in disseminating the study findings, although this stage of the intervention had not yet occurred at the time of publication [29]. However, no studies involved or mentioned the future involvement of adolescents during the reflection stages.
Although the age groups, number of participants, and setting of the studies were identified, there was no difference in the extent to which adolescents were involved between the study characteristics. The only identified difference was that smaller participation groups allowed for slightly more detail in their explanations of their current knowledge on ASRH and what knowledge they wanted to gain [19,24,38,41]. Although these findings indicate that adolescents can be successfully involved in the planning and action stages of the PAR framework, the collective theme of the included studies concluded that with the development of a SRH intervention and a greater understanding of local perspectives, adolescents play a vital role in co-designing ASRH interventions.
Furthermore, this review identified many barriers and facilitators to co-designing ASRH interventions. Barriers stemming from cultural and social influences, judgment, and taboos were highlighted throughout the studies [16,20,23,30,39]. However, the physical barriers, relating to remote communities and poor transport, identified in some studies were directly identified by other studies and used technology to connect and overcome geographical and transportation limitations [18,19,24,33,34,35,40]. An overarching facilitator of the studies was that the research was conducted in a friendly and professional manner, as well as to remind the adolescents that they are in a safe environment at all times [24,28,31,32,36]. This review provided a broad insight into the barriers and facilitators associated with co-designing ASRH intervention during the planning and action stages of the PAR framework, which can be used to inform future research.
Another objective of this review was to assess the effectiveness of co-designing on adolescents’ SRH outcomes. However, as the identified studies did not report on the effectiveness of co-designing ASRH interventions, this objective could not be met.
To the best of our ability, we believe that this review is thorough, regarding adolescents’ involvement in PAR for co-designed ASRH interventions. We believe we have included all possible published studies, concerning the topic, as we have conducted extensive literature searching on multiple databases and grey literature sites, as well as title searching of included studies. Potential biases were not identified, and no quality assessment was performed on these studies, as it was a scoping review. To identify potential bias, an investigation should occur to see if the author and/or primary researcher of each study have the potential of personal gain for the success of the intervention. No previous systematic reviews exist, concerning PAR for co-designed ASRH interventions; therefore, we could not determine whether there are any discrepancies within the findings and if they agree or disagree with previous reviews.
5. Conclusions
This review aimed to understand adolescents’ participation in PAR for co-designed ASRH interventions, including the barriers and facilitators, and assess the effectiveness of co-designing on adolescents’ SRH outcomes.
The collective theme of the included studies concluded that with the development of a SRH intervention, as well as a greater understanding of local perspectives, adolescents play a vital role in co-designing ASRH interventions.
As there is no current systematic review on this topic, it is suggested that the barriers and facilitators, verbalised by the adolescents, be accommodated in future research to improve the effectiveness of the interventions. Future studies should also involve adolescents in these interventions’ observation and reflection aspects, in order to complete the PAR cycle. Furthermore, future systematic reviews should assess the outcomes of these designed interventions documented to assess their effectiveness.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/sexes3010015/s1, Table S1: PRISMA-SR Checklist.
Author Contributions
Conceptualization, Z.S.L. and S.M.; methodology, Z.S.L.; software, Z.S.L.; data curation, E.G.N. and B.M.A.; writing—original draft preparation, Z.S.L., E.G.N., B.M.A. and P.H.A.; writing—review and editing, Z.S.L.; supervision, Z.S.L. All authors have read and agreed to the published version of the manuscript.
Funding
No funding has been received for this work. Zohra Lassi is supported by an NHMRC Australia Public Health and Health Services Early Career Research Fellowship (AP1141382).
Institutional Review Board Statement
Not applicable. This review did not require ethical clearance.
Informed Consent Statement
Not applicable.
Data Availability Statement
The corresponding author can be contacted for detailed data extraction sheets for all the included studies.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Salam, R.A.; Faqqah, A.; Sajjad, N.; Lassi, Z.S.; Das, J.K.; Kaufman, M.; Bhutta, Z.A. Improving adolescent sexual and reproductive health: A systematic review of potential interventions. J. Adolesc. Health 2016, 59, S11–S28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chandra-Mouli, V.; Lane, C.; Wong, S. What does not woerk in adolescent sexual and reproductive health: A revew of evidence on interventions commonly accepted as best practices. Glob. Health Sci. Pract. 2015, 3, 333–340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lassi, Z.S.; Salam, R.A.; Das, J.K.; Wazny, K.; Bhutta, Z.A. An unfinished agenda on adolescent health: Opportunities for interventions. Semin. Perinatol. 2015, 39, 353–360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goodyear-Smith, F.; Jackson, C.; Greenhalgh, T. Co-design and implementation research: Challenges and solutions for ethics committees. BMC Med. Ethics 2015, 16, 78. [Google Scholar] [CrossRef] [Scilit]
- Gilbert, E.; Collins, R.; Webster, V.; Boyd, N.; Maple-Brown, L.; Boyle, J.; Smith-Vaughan, H. Using co-design to develop a culturally responsive reproductive health learning resource for Aboriginal and Torres Strait Islander youth. Health Promot. J. Aust. 2021, 32, 179–185. [Google Scholar] [CrossRef] [Scilit]
- Mbachu, C.O.; Clara Agu, I.; Onwujekwe, O. Collaborating to co-produce strategies for delivering adolescent sexual and reproductive health interventions: Processes and experiences from an implementation research project in Nigeria. Health Policy Plan. 2020, 35 (Suppl. 2), ii84–ii97. [Google Scholar] [CrossRef] [Scilit]
- Thabrew, H.; Fleming, T.; Hetrick, S.; Merry, S. Co-design of eHealth interventions with children and young people. Front. Psychiatry 2018, 9, 481. [Google Scholar] [CrossRef] [Scilit]
- Vindrola-Padros, C.; Barbosa, E.C.; Ramsay, A.I.; Turner, S.; Morris, S.; Agble, R.; Caldwell-Nichols, A.; Fulop, N.J. Mixed methods evaluation of a hospital group model using an embedded research approach: Study protocol. BMJ Open 2019, 9, e027086. [Google Scholar] [CrossRef] [Scilit]
- Denno, D.M.; Hoopes, A.J.; Chandra-Mouli, V. Effective strategies to provide adolescent sexual and reproductive health services and to increase demand and community support. J. Adolesc. Health 2015, 56, S22–S41. [Google Scholar] [CrossRef] [Scilit]
- Mehta, S.D.; Seeley, J. Grand challenges in adolescent sexual and reproductive health. Front. Reprod. Health 2020, 2, 2. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.; Horsley, T.; Weeks, L.; et al. PRISMA extension for scoping reviews (PRISMA-ScR): Checklist and explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Covidence Systematic Review Software. Veritas Health Innovation: Melbourne, Australia. Available online: www.covidence.org (accessed on 28 September 2021).
- Decker, M.J.; Gutmann-Gonzalez, A.; Price, M.; Romero, J.; Sheoran, B.; Yarger, J. Evaluating the effectiveness of an intervention integrating technology and in-person sexual health education for adolescents (in the know): Protocol for a cluster randomized controlled trial. JMIR Res. Protoc. 2020, 9, e18060. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hong, J.; Fongkaew, W.; Senaratana, W.; Tonmukayakul, O. Development of a theory-based sexual and reproductive health promotion and HIV prevention program for Chinese early adolescents. Nurs. Health Sci. 2010, 12, 360–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Assifi, A.R.; Kang, M.; Sullivan, E.; Dawson, A.J. Assessing care trajectories of adolescent females seeking early induced abortion in New South Wales: Multistage, mixed-methods study protocol. BMJ Open 2020, 10, e039819. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aventin, Á.; Rabie, S.; Skeen, S.; Tomlinson, M.; Makhetha, M.; Siqabatiso, Z.; Lohan, M.; Clarke, M.; Lohfeld, L.; Thurston, A.; et al. Adaptation of a gender-transformative sexual and reproductive health intervention for adolescent boys in South Africa and Lesotho using intervention mapping. Glob. Health Action 2021, 14, 1927329. [Google Scholar] [CrossRef] [Scilit]
- Cook, S.M.; Grozdanovski, L.; Renda, G.; Santoso, D.; Gorkin, R.; Senior, K. Can you design the perfect condom? Engaging young people to inform safe sexual health practice and innovation. Sex Educ. 2021, 22, 110–122. [Google Scholar] [CrossRef] [Scilit]
- Gill, R.; Black, A.; Dumont, T.; Fleming, N. Photovoice: A strategy to better understand the reproductive and sexual health needs of young mothers. J. Pediatr. Adolesc. Gynecol. 2016, 29, 467–475. [Google Scholar] [CrossRef] [Scilit]
- Jaworsky, D.; Larkin, J.; Sriranganathan, G.; Clout, J.; Janssen, J.; Campbell, L.; Flicker, S.; Stadnicki, D.; Erlich, L.; Flynn, S. Evaluating youth sexual health peer education programs: “Challenges and suggestions for effective evaluation practices”. J. Educ. Train. Stud. 2013, 1, 227–234. [Google Scholar] [CrossRef] [Scilit]
- Markus, S.F. Photovoice for healthy relationships: Community-based participatory HIV prevention in a rural American Indian community. Am. Indian Alsk. Nativ. Ment. Health Res. 2012, 19, 102–123. [Google Scholar] [CrossRef] [Scilit]
- Newby, K.V.; Brown, K.E.; Bayley, J.; Kehal, I.; Caley, M.; Danahay, A.; Hunt, J.; Critchley, G. Development of an intervention to increase sexual health service uptake by young people. Health Promot. Pract. 2017, 18, 391–399. [Google Scholar] [CrossRef] [Scilit]
- Patchen, L.; Ellis, L.; Ma, T.X.; Ott, C.; Chang, K.H.K.; Araya, B.; Atreyapurapu, S.; Alyusuf, A.; Lanzi, R.G. Engaging african american youth in the development of a serious mobile game for sexual health education: Mixed methods study. JMIR Serious Games 2020, 8, e16254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pensak, M.J.; Lundsberg, L.S.; Stanwood, N.L.; Cutler, A.S.; Gariepy, A.M. Development and feasibility testing of a video game to reduce high-risk heterosexual behavior in spanish-speaking latinx adolescents: Mixed methods study. JMIR Serious Games 2020, 8, e17295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahmanesh, M.; Okesola, N.; Chimbindi, N.; Zuma, T.; Mdluli, S.; Mthiyane, N.; Adeagbo, O.; Dreyer, J.; Herbst, C.; McGrath, N.; et al. Thetha Nami: Participatory development of a peer-navigator intervention to deliver biosocial HIV prevention for adolescents and youth in rural South Africa. BMC Public Health 2021, 21, 1393. [Google Scholar] [CrossRef] [Scilit]
- Simuyaba, M.; Hensen, B.; Phiri, M.; Mwansa, C.; Mwenge, L.; Kabumbu, M.; Belemu, S.; Shanaube, K.; Schaap, A.; Floyd, S.; et al. Engaging young people in the design of a sexual reproductive health intervention: Lessons learnt from the Yathu Yathu (“For us, by us”) formative study in Zambia. BMC Health Serv. Res. 2021, 21, 753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wood, L.; Hendricks, F. A participatory action research approach to developing youth-friendly strategies for the prevention of teenage pregnancy. Educ. Action Res. 2017, 25, 103–118. [Google Scholar] [CrossRef] [Scilit]
- Zaleski, N.; Martin, P.; Messinger, J. Given and chosen: Youth-led research on family-supported conversations about sexuality. Fam. Community Health 2015, 38, 131–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cense, M.; Grauw, S.; Vermeulen, M. ‘Sex is not just about ovaries’. Youth participatory research on sexuality education in the netherlands. Int. J. Environ. Res. Public Health 2020, 17, 8587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cordova, D.; Munoz-Velazquez, J.; Mendoza Lua, F.; Fessler, K.; Warner, S.; Delva, J.; Adelman, N.; Counlic, Y.L.; Fernandez, A.; Bauermeister, J. Pilot study of a multilevel mobile health app for substance use, sexual risk behaviors, and testing for sexually transmitted infections and HIV among youth: Randomized controlled trial. JMIR Mhealth Uhealth 2020, 8, e16251. [Google Scholar] [CrossRef] [Scilit]
- Garwick, A.W.; Rhodes, K.L.; Peterson-Hickey, M.; Hellerstedt, W.L. Native teen voices: Adolescent pregnancy prevention recommendations. J. Adolesc. Health 2008, 42, 81–88. [Google Scholar] [CrossRef] [Scilit]
- Guerrero, F.; Lucar, N.; Garvich Claux, M.; Chiappe, M.; Perez-Lu, J.; Hindin, M.J.; Gonsalves, L.; Bayer, A.M. Developing an SMS text message intervention on sexual and reproductive health with adolescents and youth in Peru. Reprod Health 2020, 17, 116. [Google Scholar] [CrossRef] [Scilit]
- Haruna, H.; Zainuddin, Z.; Mellecker, R.R.; Chu, S.K.; Hu, X. An iterative process for developing digital gamified sexual health education for adolescent students in low-tech settings. Inf. Learn. Sci. 2019, 120, 723–742. [Google Scholar] [CrossRef] [Scilit]
- Holliday, R.C.; Phillips, R.; Akintobi, T.H. A community-based participatory approach to the development and implementation of an HIV health behavior intervention: Lessons learned in navigating research and practice systems from project Happy. Int. J. Environ. Res. Public Health 2020, 17, 399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hubert, C.; Estrada, F.; Campero, L.; Heredia-Pi, I.B.; Villalobos, A.; Suárez-López, L.; Ibáñez-Cuevas, M.; Barrientos, T. Designing digital tools capable of reaching disadvantaged adolescents and improving their sexual health: A mexican experience. J. Health Care Poor Underserved 2021, 32, 62–84. [Google Scholar] [CrossRef] [Scilit]
- Ivanova, O.; Cordova-Pozo, K.; Segura, Z.E.; Vega, B.; Chandra-Mouli, V.; Hindin, M.J.; Temmerman, M.; Decat, P.; De Meyer, S.; Michielsen, K. Lessons learnt from the CERCA Project, a multicomponent intervention to promote adolescent sexual and reproductive health in three Latin America countries: A qualitative post-hoc evaluation. Eval. Program Plan. 2016, 58, 98–105. [Google Scholar] [CrossRef] [Scilit]
- Jones, A.C. Exploring Ugandan Secondary School Students’ Sexual Health Education Needs and Developing School-Based Sexual Health Interventions through Participatory Action Research. Master’s Thesis, University of Alberta, Edmonton, AB, Canada, 2012. [Google Scholar]
- Lofton, S.; Norr, K.F.; Jere, D.; Patil, C.; Banda, C. Developing action plans in youth photovoice to address community-level HIV risk in rural Malawi. Int. J. Qual. Methods 2020, 19, 1609406920920139. [Google Scholar] [CrossRef] [Scilit]
- Marinkovich, Z.A.H. Growing up with HIV in Kisumu, Kenya: Participatory Action Research with Young People Living with HIV. Ph.D. Thesis, University of San Francisco, San Francisco, CA, USA, 2014. [Google Scholar]
- Shegog, R.; Craig Rushing, S.; Gorman, G.; Jessen, C.; Torres, J.; Lane, T.L.; Gaston, A.; Revels, T.K.; Williamson, J.; Peskin, M.F.; et al. NATIVE-it’s your game: Adapting a technology-based sexual health curriculum for american indian and alaska native youth. J. Prim. Prev. 2017, 38, 27–48. [Google Scholar] [CrossRef] [Scilit]
- Nolan, C.; Packel, L.; Hope, R.; Levine, J.; Baringer, L.; Gatare, E.; Umubyeyi, A.; Sayinzoga, F.; Mugisha, M.; Turatsinze, J.; et al. Design and impact evaluation of a digital reproductive health program in Rwanda using a cluster randomized design: Study protocol. BMC Public Health 2020, 20, 1701. [Google Scholar] [CrossRef] [Scilit]
- Fongkaew, W.; Fongkaew, K.; Muecke, M. HIV/sexual and reproductive health program for HIV prevention: The youth-adult partnership with schools approach. J. Med. Assoc. Thailand 2006, 89, 1721–1732. [Google Scholar]
Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).