


Abstract
Background: This study aims to characterize the clinical features and outcomes of tattoo-associated sarcoid-like uveitis using a multicenter uveitis registry given the limited existing data. Design: This is a retrospective study. Participants: Ten patients (20 eyes) diagnosed with tattoo-associated sarcoid-like uveitis took part in the study. Methods: The data of patients newly evaluated at participating registry centers from January 2000 to June 2025 were reviewed. Demographic data, treatments, visual acuity, recurrence, glaucoma/intraocular pressure (IOP)-lowering therapy, extraocular involvement, and histologic confirmation were extracted when available. Main Outcome Measures: Recurrence, glaucoma/IOP-lowering therapy, extraocular involvement, and change in logarithm of the minimum angle of resolution (logMAR) from presentation to final follow-up were measured. Results: Seven (70%) patients were male, and the patients’ mean age was 35.1 ± 7.8 years. All patients exhibited bilateral ocular involvement. Histologic confirmation at the tattoo site was documented in five (50%) patients. The mean logMAR visual acuity was 0.12 ± 0.31 at presentation and 0.16 ± 0.42 at the final follow-up (median follow-up: 20 months). All patients received topical corticosteroids; periocular steroids were administered in seven cases (70%), oral systemic steroids in four (40%), adalimumab in two (20%), and cyclosporin in one (10%). Seven cases (70%) developed uveitis recurrence, and eight received glaucoma/IOP-lowering therapy (80%). Extraocular inflammation affected the skin/tattoo in seven patients (70%) and the axillary lymph nodes in one (10%). This finding is definitive; however, this is also true even when the organ/body part is plural (e.g., lungs). Conclusions: Tattoo-associated sarcoid-like uveitis often follows a chronic course with frequent recurrence and uveitic glaucoma. Thus, close ophthalmic monitoring and coordinated systemic evaluation may be warranted.
1. Introduction
Tattooing has become increasingly prevalent worldwide, particularly among younger individuals [1,2,3,4], and cutaneous reactions to tattoo pigments range from acute inflammation to chronic granulomatous disease [1]. During tattooing, ink is injected into multiple skin layers, where it becomes fixed within the dermis. The process is intended to temporarily suppress local immune responses, but trace ink particles are transported systemically by circulating white blood cells. A proportion of pigment remains at the injection site through uptake by tissue-resident macrophages and persists via a “capture–release–recapture” mechanism, ensuring long-term visibility [5,6].
Tattoo granuloma with uveitis is recognized as a distinct clinical entity, often overlapping clinically and histopathologically with sarcoidosis [7,8,9,10]. According to prior reports and reviews, tattoo-associated uveitis is commonly bilateral and recurrent, and may be accompanied by systemic sarcoidosis or sarcoid-like inflammation [7,8,9,10,11,12,13,14]. However, the existing evidence is limited to single-center series and case reports, and comprehensive data on the treatment patterns and outcomes remain scarce [8,10]. To address this gap, the present study aimed to explore the clinical spectrum, treatments, recurrence, and glaucoma-related outcomes of tattoo-associated sarcoid-like uveitis in Japan using a national coverage-multicenter uveitis registry.
2. Materials and Methods
Study design and setting: We conducted a retrospective analysis of the data obtained from patients enrolled in a national coverage-multicenter uveitis registry. Patients newly presenting to the participating registry centers from January 2000 to June 2025 were included.
Definition: In the present study, tattoo-associated sarcoid-like uveitis was defined as follows: (1) uveitis with granulomatous features clinically consistent with ocular sarcoidosis; (2) a temporal association with tattoo inflammation or pigment-related cutaneous findings; and (3) physician attribution of uveitis to tattoo-associated sarcoid-like disease.
Data collection: Demographic data (age and sex), laterality, laboratory results, extraocular involvement, treatments (topical corticosteroids, periocular corticosteroid injections, systemic corticosteroids, and immunomodulatory therapy), and clinical outcomes were extracted from the patients’ medical records. Missing data were assessed for each variable. The analyses were primarily conducted using available-case (pairwise) data; the denominator, therefore, varies across analyses depending on data availability. No imputation was performed because missingness reflected incomplete documentation in routine clinical care.
Outcome measures: The primary outcomes included uveitis recurrence, glaucoma/intraocular pressure (IOP)-lowering therapy, extraocular involvement, and change in logarithm of the minimum angle of resolution (logMAR) visual acuity from presentation to final follow-up, with visual acuity analyzed at the eye level (20 eyes). Uveitis recurrence was defined as disease activity requiring the initiation or escalation of anti-inflammatory treatment, and glaucoma/IOP-lowering therapy was defined as the need for the initiation or escalation of IOP-lowering treatment.
Statistical analysis: Continuous variables are presented as means ± standard deviations or medians (interquartile ranges), whereas categorical variables are provided as counts (percentages).
3. Results
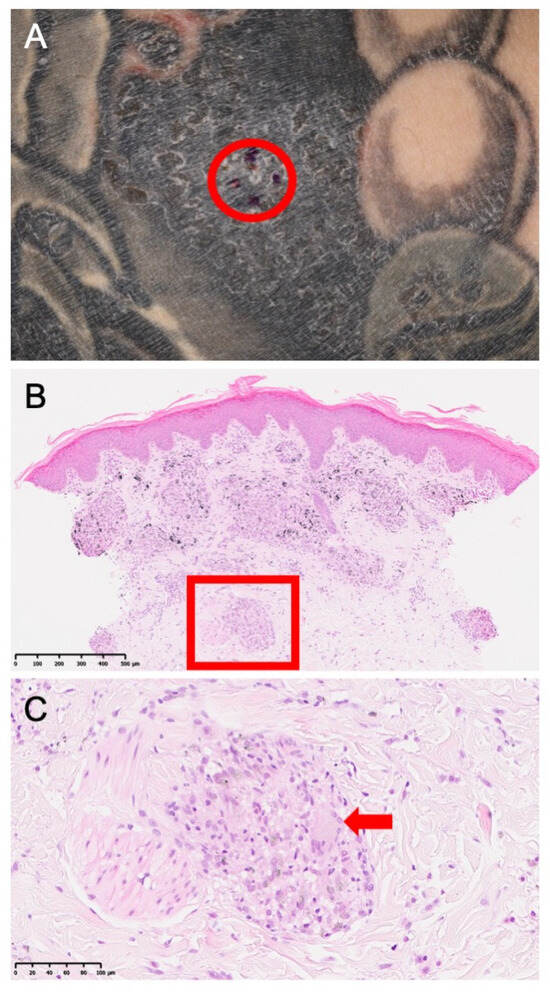
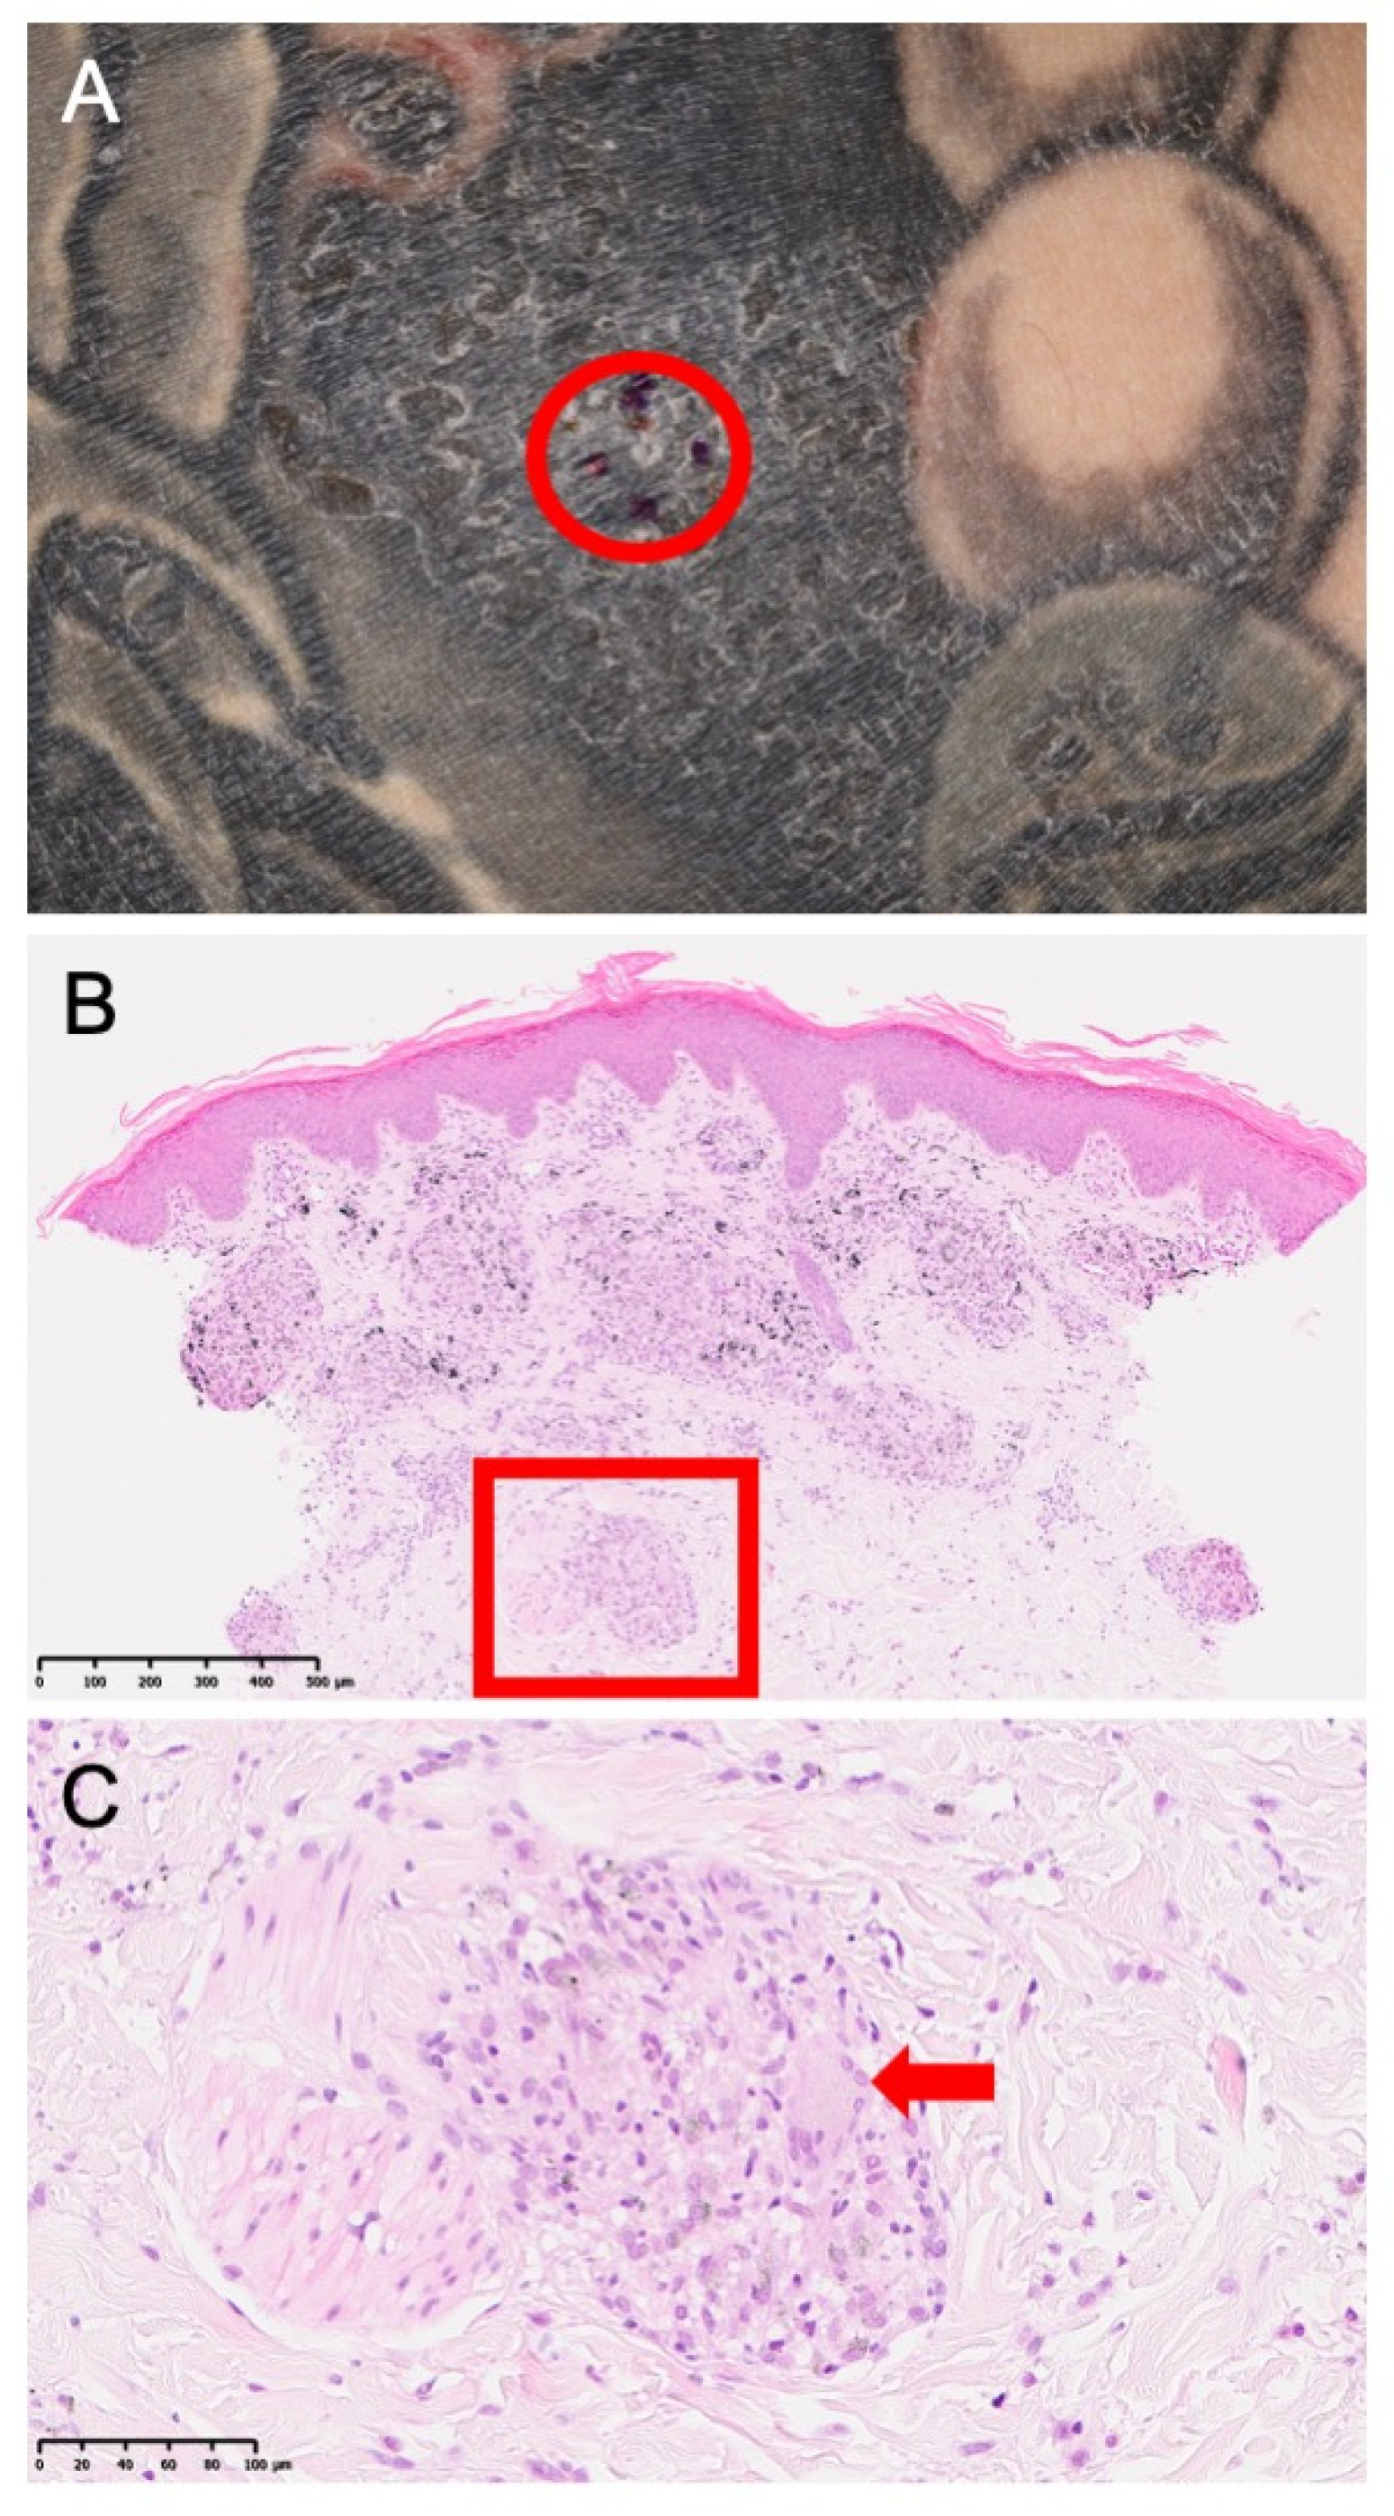
Ten patients (20 eyes) met the inclusion criteria, representing 100% of the patients enrolled in the registry (Table 1). Among these, seven (70%) were male, and the mean age was 35.1 ± 7.8 (27–44) years. The median follow-up duration was 19.1 (interquartile range: 8.3–26.0) months. Histologic confirmation at the tattoo site was obtained in four patients (40%, Figure 1). Bilateral hilar lymphadenopathy was not observed in any case (0/10). Elevated angiotensin-converting enzyme and elevated soluble IL-2 receptor levels were documented in 2/10 and 4/10 cases, respectively (Table 2). T-spot testing was negative in patients in whom it was performed, with several cases not assessed (Table 2). Data on latency from tattooing to uveitis onset, which ranged from 1 to 29 years, were available in four cases (Table 2).
Table 1.
Baseline characteristics and systemic findings.
Figure 1.
A patient’s tattooed skin, punch biopsy, and histopathology. (A) Right upper arm showing infiltration and scaling limited to the intensely pigmented black area. A punch biopsy sample was obtained from the marked site (red circle). (B) Hematoxylin-and-eosin-stained section of the biopsy (original magnification: ×50) showing multiple foci in the upper to mid dermis. The region outlined by the red box is shown in panel (C). (C) A higher power view (original magnification: ×200) showing black pigment deposits surrounded by epithelioid cell granulomas with minimal lymphocytic infiltration. Langhans-type giant cells with peripheral, horseshoe-shaped nuclei are visible (red arrow).
Table 2.
Patient-level demographics and visual acuity.
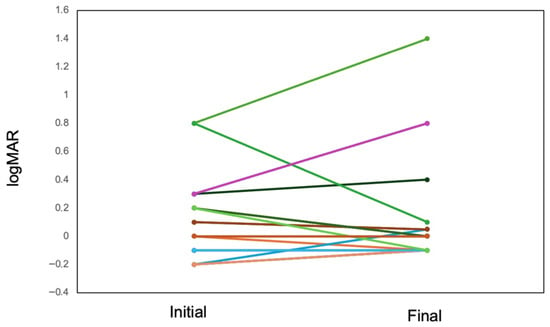
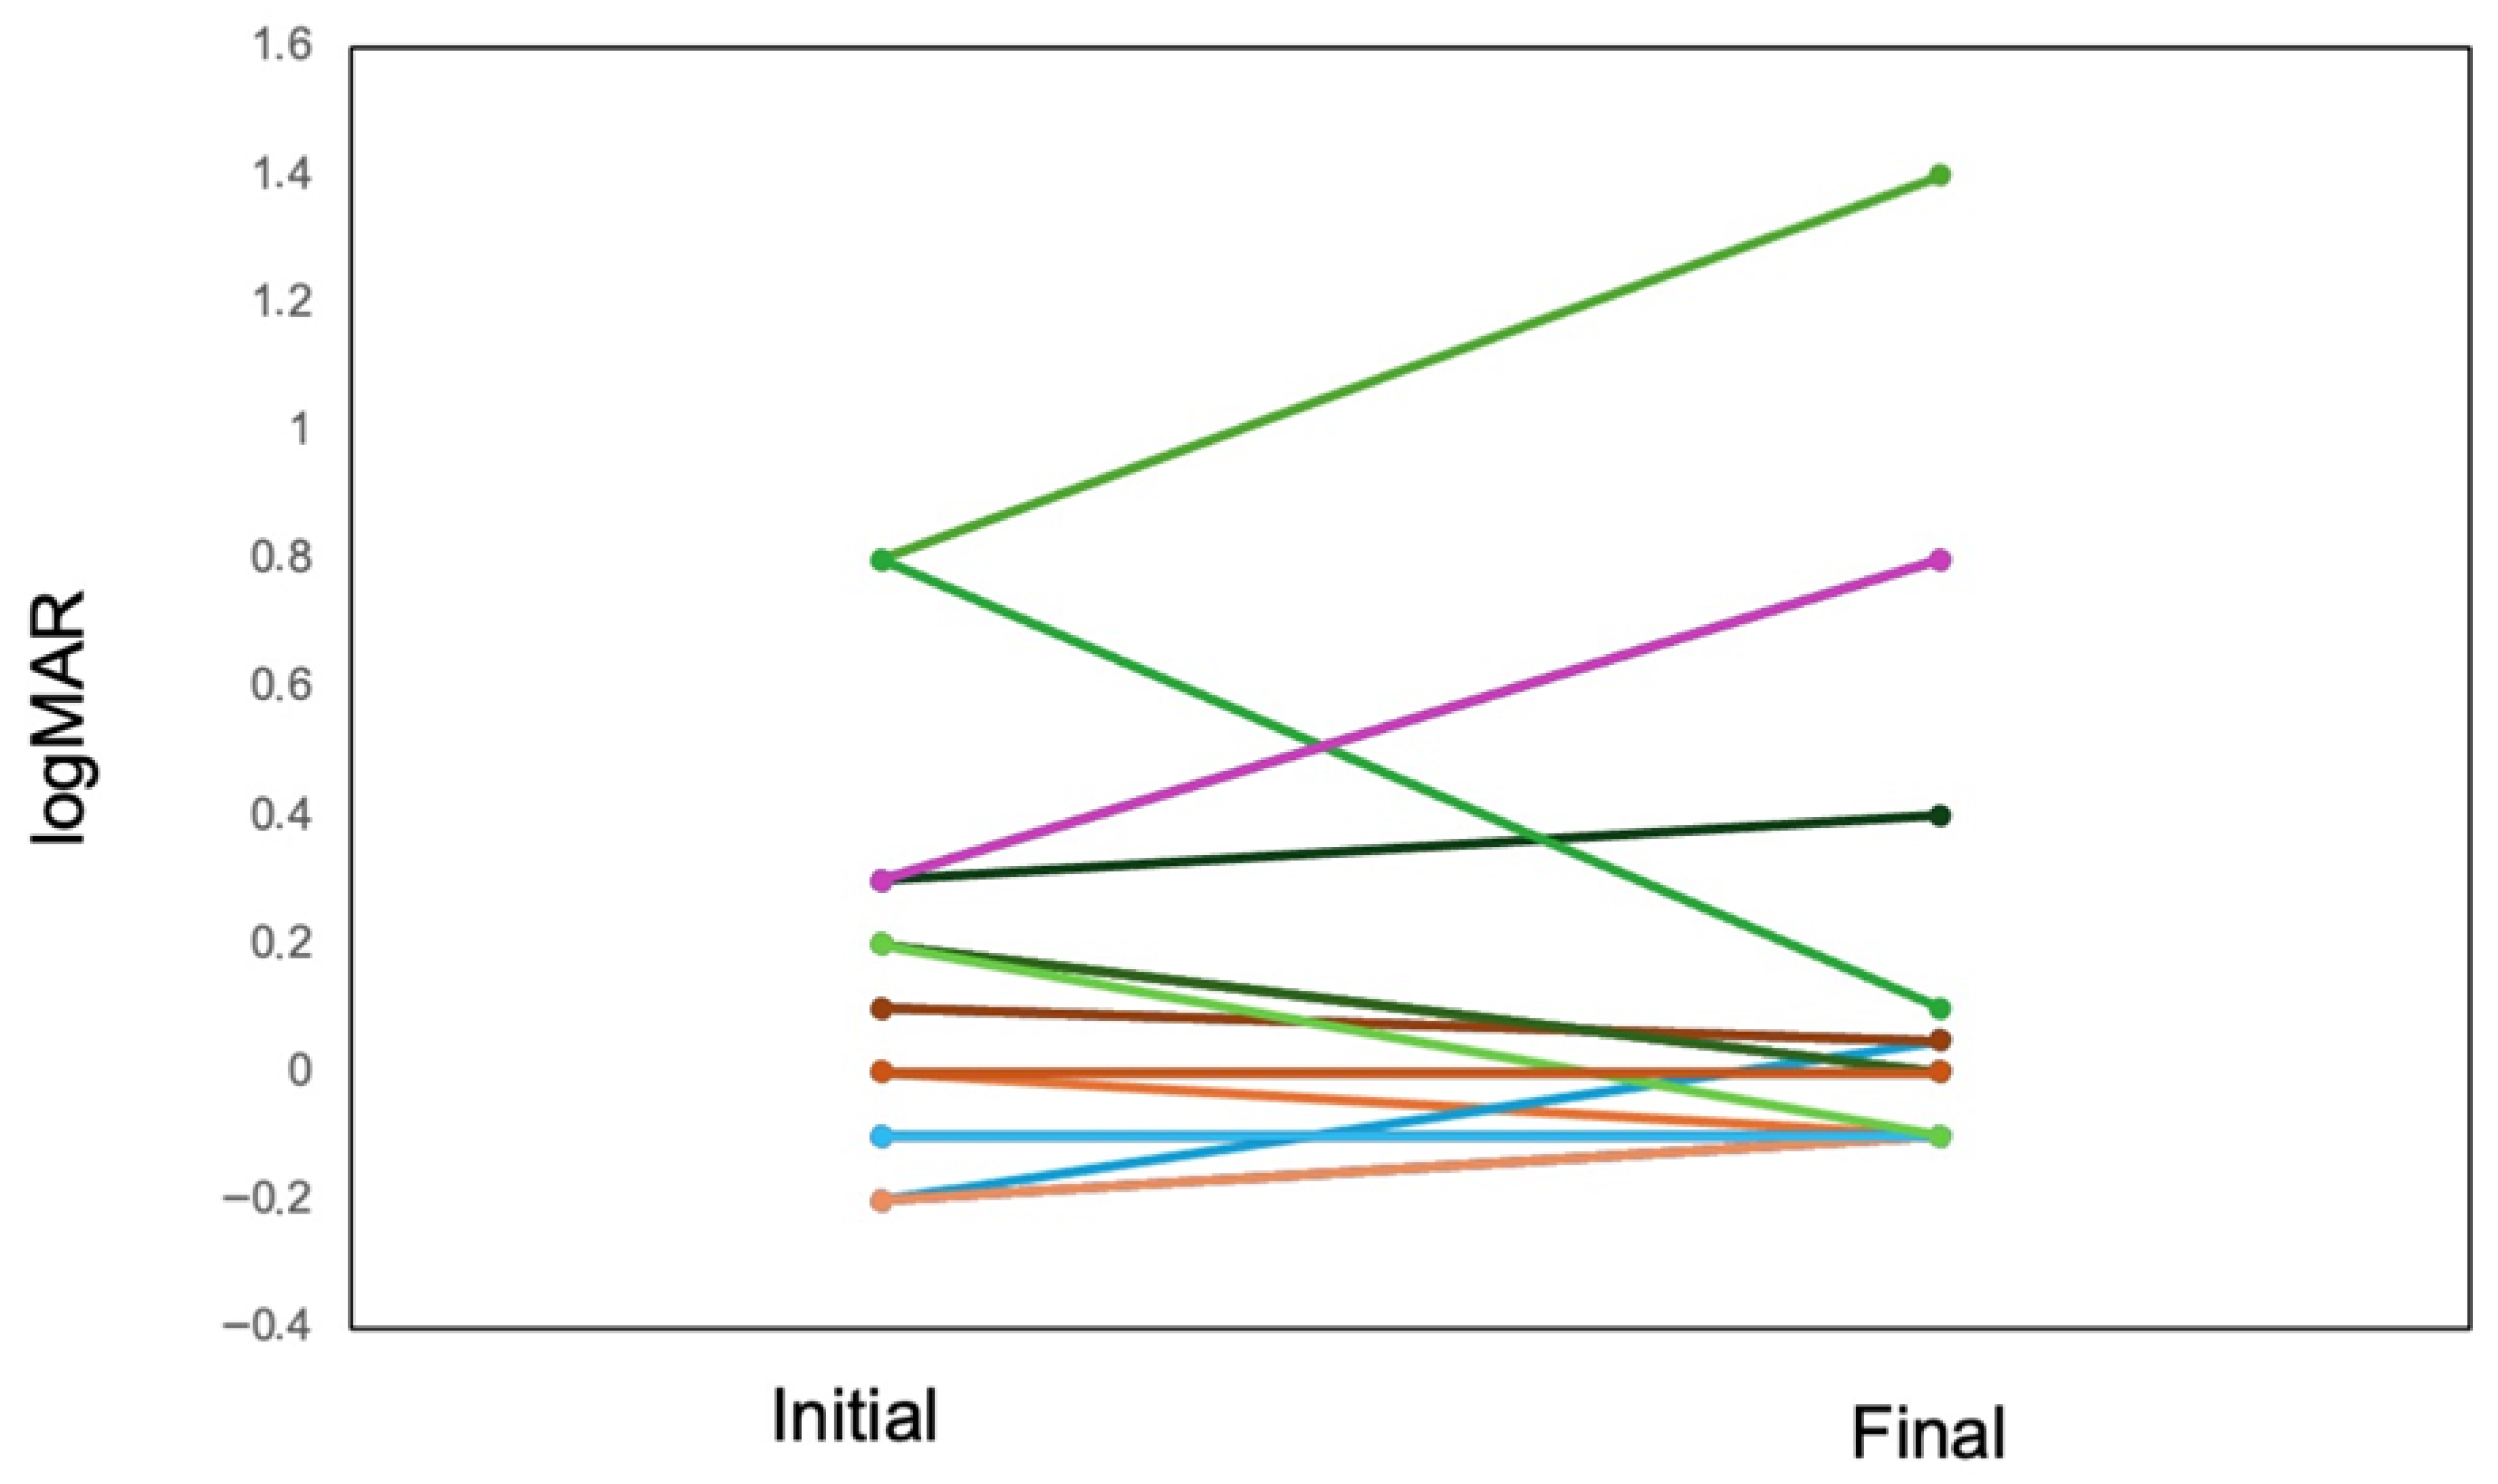
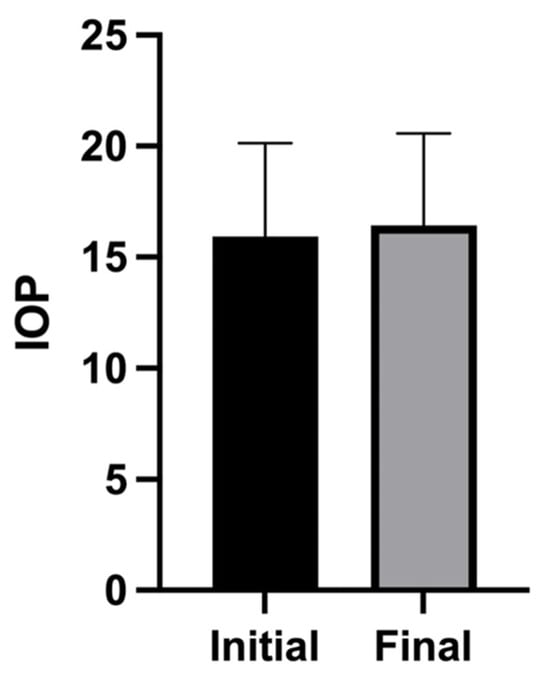
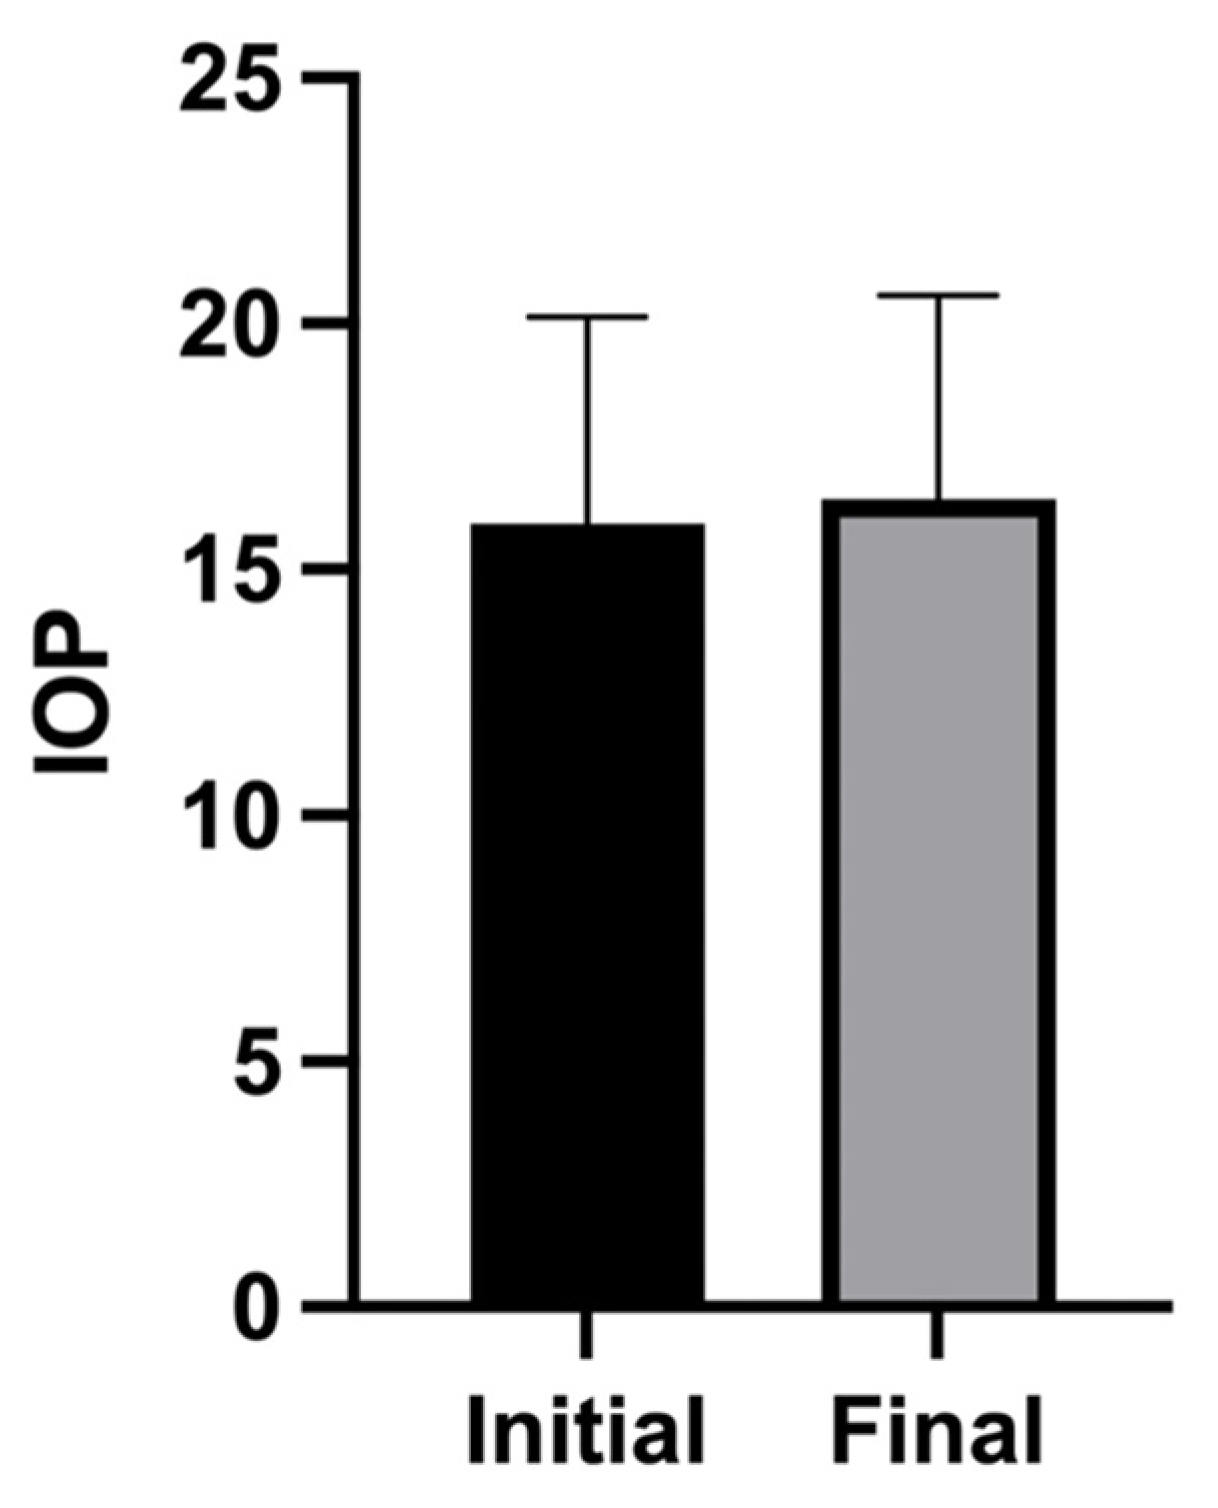
At the eye level, the mean logMAR visual acuity across 20 eyes was 0.12 at presentation and 0.15 at the final follow-up (Figure 2). Consistent with this, the patient-level mean logMAR values showed a limited overall change between baseline and final follow-up across individual cases (Table 2). The IOP changed from 14.5 ± 4.1 mmHg (mean ± standard deviation) at the initial visit to 17.6 ± 4.0 mmHg at the final visit (Figure 3). Macular edema was frequently observed, occurring bilaterally in seven patients and unilaterally (left eye) in one patient, affecting a total of 15 out of 20 eyes (75%) (Table 2). Anterior segment inflammation (anterior chamber inflammatory cells) was frequently observed. Vitreous involvement—manifesting as clumped and/or diffuse vitreous opacities—was also common. Posterior segment vasculitic features, including retinal periphlebitis, perivascular nodules, and candle-wax-like retinochoroidal exudates, were variably present. Granulomatous lesions involving the optic disc and/or choroid were noted in a subset of eyes. Structural complications, including tent-shaped/trapezoidal peripheral anterior synechiae and photocoagulation-like retinochoroidal atrophic lesions, were also observed in some cases (Table 3). All cases in the present study had bilateral glaucoma associated with uveitis. Etiologically, 70% of the patients were classified as having glaucoma related to sarcoidosis/uveitis, 50% as having steroid-induced glaucoma, and 40% as having mixed (overlapping) mechanisms. Recurrence occurred in seven cases (70%), and glaucoma/IOP-lowering therapy was required in eight cases (80%) (Table 4). Extraocular inflammation affected the skin/tattoo in seven patients (70%) and the axillary lymph nodes in one (10%) patient.
Figure 2.
Change in visual acuity at the eye level from the initial visit to the final visit.
Figure 3.
Change in intraocular pressure from the initial visit to the final visit.
Table 3.
Clinical findings in an eye diagnosed with tattoo-associated sarcoid-like uveitis.
Table 4.
Treatments and outcomes.
All patients received topical corticosteroids. Periocular corticosteroid injections were administered in seven patients (70%), oral systemic corticosteroids in four (40%), cyclosporin in one (10%), and adalimumab in two (20%) (Table 4 and Table 5).
Table 5.
Patient-level treatments and outcomes.
4. Discussion
A key strength of the present multicenter registry study is its presentation of a comprehensive case series, which included substantially more patients in the analysis compared with prior reports. Tattoo-associated sarcoid-like uveitis was consistently bilateral and frequently recurrent, with over half of the patients requiring IOP-lowering therapy. These findings align with previous case series and comparative reviews, which describe a chronic course and an overlap with systemic sarcoidosis or sarcoid-like granulomatous inflammation [8,9,10].
The high rates of recurrence and glaucoma/IOP-lowering therapy provision suggest that ongoing inflammation can cause secondary structural complications. The proposed mechanisms include persistent antigenic stimulation by tattoo pigments and delayed hypersensitivity or foreign-body granulomatous reactions, potentially extending from the skin to the ocular tissues [10,15]. Elevated IOP was attributed to chronic inflammation in three eyes, steroid-induced glaucoma in one eye, and both mechanisms in four eyes. These findings also indicate that persistent ocular inflammation is a key feature of tattoo-associated sarcoid-like disease and highlight the need for careful differentiation between inflammation-driven and steroid-induced IOP elevations in clinical management.
Notably, not all tattoos pose the same health risks. In traditional Japanese hand-poked tattooing (tebori), famously depicted in Jun-Ichirō Tanizaki’s debut novella Shisei (“The Tattooer”), carbon-based sumi ink, which is regarded as less allergenic owing to carbon’s relative biocompatibility, is often used. Contrarily, modern machine tattoos may incorporate chemically diverse pigments, including azo dyes, quinacridones, phthalocyanines for vivid blue and green hues, and inorganic pigments (e.g., iron oxides and titanium dioxides). These mixtures have been implicated in hypersensitivity reactions and may pose infectious and systemic safety risks [16,17,18,19].
Beyond pigment composition, experimental and ex vivo human studies have indicated that tattoo pigments and trace-element impurities are not confined to the dermis. Using synchrotron-based analyses, colored pigments and associated metals were detected in the regional lymph nodes of tattooed donors, providing evidence of translocation via the lymphatic pathways. Although the clinical significance of such deposition remains unclear, pigment accumulation in the lymph nodes could promote chronic immune activation, complicate lymphadenopathy interpretation, and contribute to sarcoid-like granulomatous responses in predisposed individuals [20].
Most patients were treated with topical and periocular corticosteroids, whereas systemic corticosteroids and biologic therapies were used selectively. Given the potential for systemic involvement, including lymphadenopathy and pulmonary disease, as reported previously [3,10,12], coordinated evaluation with dermatology and internal medicine may be warranted when tattoo-associated inflammation occurs alongside uveitis [21].
The present study has several limitations, including the small sample size, variable data completeness across centers, and lack of standardized, detailed phenotyping, such as uniform anterior chamber cell grading or imaging biomarkers. However, its multicenter registry design provides pragmatic real-world data on the treatment patterns and clinically meaningful outcomes of this rare condition. From a clinical perspective, our findings underscore the importance of considering the presence of tattoo-associated sarcoid-like disease in patients with recurrent uveitis, particularly when ocular flares coincide with inflammation or swelling of the tattooed skin and support the need for coordinated ophthalmologic and systemic evaluations to guide the diagnosis and management of this condition. Another limitation is that the patients’ visual acuity was analyzed at the eye level, whereas the other outcomes were evaluated at the patient level. Although clinically appropriate for bilateral disease, this difference in analytic units may introduce bias in interpretation.
Author Contributions
Conceptualization, R.Y., M.E. and Y.M.; Formal analysis, Y.M. and S.N. (Shido Nagaki); Investigation, S.N. (Shido Nagaki) and Y.M.; Resources, Y.M.; Data curation, Y.M., K.S., T.K., S.N. (Suguru Nakagawa), Y.H., K.T., S.-H.U., T.A., K.N., S.K. and N.Y.; Writing—original draft, R.Y.; Writing—review and editing, Y.U. and C.S.; Supervision, K.-H.S.; Project administration, R.Y. The Multicenter Tattoo-Associated Sarcoid Uveitis Registry, organized within the Japanese Ocular Inflammatory Association (JOIS), contributed to this study by enabling multicenter patient recruitment, standardized data collection, and case validation across participating institutions. The registry framework facilitated the aggregation of rare cases and ensured consistency in diagnostic criteria and clinical data acquisition. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by a grant from the JSPS KAKENHI [Grant Number JP24K12808 to R.Y.].
Institutional Review Board Statement
The Institutional Review Board of Tokushima University Hospital approved the present study (No. 4697-1, 29 September 2025). This study was conducted following the tenets of the Declaration of Helsinki.
Informed Consent Statement
Patient informed consent was not obtained, because the present study was a secondary analysis of existing clinical data collected during routine clinical practice, with no additional interventions or data collection performed. An opt-out procedure was implemented via a public information dis-closure notice on the Tokushima University Hospital website, which was approved by the Tokushima University Hospital Life Science and Medical Research Ethics Review Committee. For questions or to opt out, please contact the principal investigator (Ryoji Yanai; Department of Ophthalmology, Tokushima University Hospital; Tel.: +81-88-633-7163).
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.
Acknowledgments
The corresponding author affirms that all individuals who substantially contributed to the work have been acknowledged and that written consent was obtained from those who are not authors. During the preparation of this work, the authors used ChatGPT (OpenAI, 5.1) to edit the English language. After using this tool/service, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article. No artificial intelligence tools were used for data analysis or image generation.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Kluger, N. Epidemiology of tattoos in industrialized countries. Curr. Probl. Dermatol. 2015, 48, 6–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kluger, N.; Seité, S.; Taieb, C. The prevalence of tattooing and motivations in five major countries over the world. J. Eur. Acad. Dermatol. Venereol. 2019, 33, e484–e486. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Theune, L.E.; Ghoreishi, N.; Weikert, C.; Müller-Graf, C.; Engel, C.; Wirkner, K.; Baber, R.; Laux, P.; Luch, A.; Giulbudagian, M. Characteristics of a tattooed population and a possible role of tattoos as a risk factor for chronic diseases: Results from the LIFE-adult-study. PLoS ONE 2025, 20, e0319229. [Google Scholar] [CrossRef] [Scilit]
- Baranska, A.; Shawket, A.; Jouve, M.; Baratin, M.; Malosse, C.; Voluzan, O.; Vu Manh, T.P.; Fiore, F.; Bajénoff, M.; Benaroch, P.; et al. Unveiling skin macrophage dynamics explains both tattoo persistence and strenuous removal. J. Exp. Med. 2018, 215, 1115–1133. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Strandt, H.; Voluzan, O.; Niedermair, T.; Ritter, U.; Thalhamer, J.; Malissen, B.; Stoecklinger, A.; Henri, S. Macrophages and fibroblasts differentially contribute to tattoo stability. Dermatology 2021, 237, 296–302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, C.; Marquardt, Y.; Rütten, S.; Liao, L.; Rahimi, K.; Haraszti, T.; Baron, J.M.; Bartneck, M. Macrophage-like rapid uptake and toxicity of tattoo ink in human monocytes. Immunology 2024, 171, 388–401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ostheimer, T.A.; Burkholder, B.M.; Leung, T.G.; Butler, N.J.; Dunn, J.P.; Thorne, J.E. Tattoo-associated uveitis. Am. J. Ophthalmol. 2014, 158, 637–643.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kluger, N. Tattoo-associated uveitis with or without systemic sarcoidosis: A comparative review of the literature. J. Eur. Acad. Dermatol. Venereol. 2018, 32, 1852–1861. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Castro-Abeger, A.; Gangaputra, S. Tattoo inflammation and sarcoid uveitis. Ophthalmology 2019, 126, 1089. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muñoz-Ortiz, J.; Gómez-López, M.T.; Echeverry-Hernández, P.; Ramos-Santodomingo, M.F.; de-la-Torre, A. Dermatological and ophthalmological inflammatory, infectious, and tumoral tattoo-related reactions: A systematic review. Perm J. 2021, 25, 20–225. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Jacob, J.; Van Calster, J. Skin tattoos and the development of uveitis. Acta Ophthalmol. 2013, 91, e650–e652. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rorsman, H.; Brehmer-Andersson, E.; Dahlquist, I.; Ehinger, B.; Jacobsson, S.; Linell, F.; Rorsman, G. Tattoo granuloma and uveitis. Lancet 1969, 2, 27–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nso, N.; Toz, B.; Ching, T.H.; Kondaveeti, R.; Abrudescu, A. Tattoo-associated sarcoidosis with severe uveitis successfully treated with mycophenolate mofetil: A report of two cases. Cureus 2021, 13, e17197. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Correia, M.S.; Romana, J.; Madeira, M.F.; Guedes, M.; Cordeiro, M. Tattoo-associated uveitis successfully controlled with methotrexate-case report and review of literature. Indian J. Ophthalmol. Case Rep. 2025, 5, 503–508. [Google Scholar] [CrossRef] [Scilit]
- Bose, R.; Sibley, C.; Fahim, S. Granulomatous and systemic inflammatory reactions from tattoo ink: Case report and concise review. SAGE Open Med. Case Rep. 2020, 8, 2050313X20936036. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Schubert, S.; Kluger, N.; Schreiver, I. Hypersensitivity to permanent tattoos: Literature summary and comprehensive review of patch tested tattoo patients 1997–2022. Contact Dermat. 2023, 88, 331–350. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoon, S.; Kondakala, S.; Daddy-Gaoh, S.; Foley, S.; Kweon, O.; Kim, S.J. Causes, patterns, and epidemiology of tattoo-associated infections since 1820. Lancet Microbe 2025, 6, 101006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kondakala, S.; Yoon, S.; Daddy-Gaoh, S.; Foley, S.; Kweon, O.; Kim, S.J. Microbiology of tattoo-associated infections since 1820. Lancet Microbe 2025, 6, 101005. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nielsen, C.; Jerkeman, M.; Jöud, A.S. Tattoos as a risk factor for malignant lymphoma: A population-based case-control study. eClinicalMedicine 2024, 72, 102649. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Schreiver, I.; Hesse, B.; Seim, C.; Castillo-Michel, H.; Villanova, J.; Laux, P.; Dreiack, N.; Penning, R.; Tucoulou, R.; Cotte, M.; et al. Synchrotron-based ν-XRF mapping and μ-FTIR microscopy enable to look into the fate and effects of tattoo pigments in human skin. Sci. Rep. 2017, 7, 11395. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Mansour, A.M.; Chan, C.C. Recurrent uveitis preceded by swelling of skin tattoos. Am. J. Ophthalmol. 1991, 111, 515–516. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.