


Abstract
Background/Objectives: The purpose of this scoping review was to identify the effects of exercise therapy on patient-reported outcome measure(s) (PROM(s)) after concussion, and to highlight the current knowledge gaps in the literature. Methods: A search of EMBASE, MEDLINE, SCOPUS, BIOSIS, and Cochrane Libraries was performed on 1 December 2023 (from database inception) and updated on 19 June 2025 to review the available literature. The Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) extension for scoping reviews was used to report the scoping review. An online review management system was used to remove duplicates and perform article screening. Results: Following the removal of duplicates, 5434 articles were identified for screening. After applying the inclusion/exclusion criteria, 27 articles remained for data extraction. The available literature has found that applying structured aerobic exercise following concussion can improve patient-reported symptom severity compared with control groups. Conclusions: There is currently a paucity of research reporting on the impact of aerobic exercise therapy following concussion on PROMs aside from patient-reported symptom severity. Additional PROMs recommended as common data elements should be included in future studies investigating the effects of aerobic exercise therapy following concussion.
1. Introduction
Exercise therapy for the treatment of numerous health conditions and diseases is well recognized [1]. More recently, the concept that ‘Exercise is Medicine’ has expanded to the management of concussions [2]. Previously, the avoidance of exercise following a concussion was recommended, as it was suggested that exercise early after a concussion may increase the time to recovery [3,4] and put individuals at risk during a time when neuronal cells may be vulnerable to further injury [5,6]. Additionally, prolonged rest following a concussion may be associated with delayed return to school/work [7]. However, there are now many clinical trials, systematic reviews, and meta-analyses showing that exercise therapy (specifically sub-symptom threshold aerobic exercise) can improve time to medically determined recovery and increase the rate of symptom resolution.
Currently, the mechanistic actions of exercise therapy on the concussed brain are not fully elucidated [8,9]. Equally important, or possibly more important, is understanding the effect that exercise therapy has on patient-reported outcome measures. As previously mentioned, evidence indicates that sub-symptom threshold aerobic exercise therapy can improve patient-reported symptoms when initiated acutely after a concussion or in individuals with persisting post-concussive symptoms. However, patient-reported symptoms are just one component of the patient-reported outcome measures that are recommended as common data elements for concussion and mild traumatic brain injury [10,11]. Therefore, the purpose of this scoping review is to identify the effects of aerobic exercise on patient-reported outcomes and to identify the current gaps in the literature.
2. Materials and Methods
This scoping review followed the Cochrane Handbook for Systematic Reviews and the scoping review extension of the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) [12]. Approval from the Institutional Research Ethics Board was not required for this scoping review. The protocol was registered with the Open Science Framework (https://osf.io/2dcb5/. Accessed on 18 September 2025).
2.1. Research Question
The research question was as follows: “What is the effect of structured aerobic exercise therapy on patient-reported outcomes following concussion?”
For this review, a healthcare professional needed to diagnose the individual as having a concussion, and the patient needed a Glasgow coma scale (GCS) score ≥ 13. For studies that did not note patient GCS, descriptive information on symptom severity and any limitations in daily activities, etc., were identified, and author judgment was used.
Any mode of exercise (i.e., cycle ergometer, treadmill, track, etc.) that was at a submaximal intensity was included as aerobic exercise.
All outcomes directly reported by the patients relating to their symptoms, quality of life, health status, or functional status were included as PROMs. Appendix A contains a full list of search terms.
2.2. Search Strategy
On 1 December 2023, EMBASE, MEDLINE, SCOPUS, BIOSIS, and Cochrane Libraries were searched for relevant literature, with an updated search performed on 19 June 2025 to ensure currency. The databases were searched back to inception, and reference sections for included papers were also searched for additional literature. Two researchers who were topic experts and had experience designing and conducting scoping reviews developed the search strategy (DMC and FAZ). The removal of duplicates and article screening were performed using an online software for scoping review management (Rayyan, Cambridge, MA United States of America. https://www.rayyan.ai) by three researchers (DMC, SCLB, and IM). A sample search strategy is available in Appendix A, and the PRISMA checklist is available in Appenidx B.
2.3. Eligibility Criteria
2.3.1. Inclusion Criteria
Articles must have been published in peer-reviewed journals and needed to have an aerobic exercise intervention initiated after a concussion or mild TBI to be included. Human studies with participants of any age were included. The participants must have been diagnosed with a concussion or mild TBI without any reported polytrauma.
2.3.2. Exclusion Criteria
All conference abstracts/papers, case reports, case series, or literature that were not original research were excluded. Studies that incorporated multiple interventions or did not involve an aerobic exercise intervention were excluded. All studies that utilized an animal model were excluded. Additionally, studies that did not measure any PROMs, were non-English, or included moderate and/or severe TBI populations where it was not possible to discern outcomes specific to concussion/mild TBI population were excluded.
2.4. Article Selection Process
For the screening process, titles and abstracts were initially screened by two researchers (DMC and SCLB), and all identified full-texts were reviewed by the same researchers. In the case of a disagreement, a third researcher (FAZ) was included to reach consensus.
2.5. Data Charting Process
All full-text articles that met the inclusion and exclusion criteria had their data extracted (see Table A2 and Table A3). Each study had data extracted to identify the study design, characteristics of the study participants, general study methodologies, detailed description of the aerobic exercise intervention, all study outcome measures, detailed PROMs collected in relation to the aerobic exercise intervention, study results specific to the PROMs, and study conclusions.
2.6. Data Items
The extracted data included patient characteristics (including sample size, biological sex, and age), study design, exercise intervention, outcome measures, study results, and general conclusions of the study.
2.7. Bias Assessment
A formal bias assessment was not conducted, as the purpose of this scoping review was to provide an overview of the current literature investigating the influence of an aerobic exercise intervention on PROMs following mild TBI/concussion. However, few of the studies were primary randomized clinical trials [13,14,15,16,17], with many studies at risk of being inappropriately powered due to being pilot studies [18,19,20,21,22,23,24,25,26,27,28] or secondary analyses [29,30,31,32,33]. The remaining study designs included cohort [34,35], case series [36], and quasi-experimental studies [37,38], which all have their own associated risks of bias.
2.8. Synthesis of Results
No statistical analysis was performed. The extracted data were described to outline their results and an overview was provided.
3. Results
3.1. Search Results and Study Characteristics
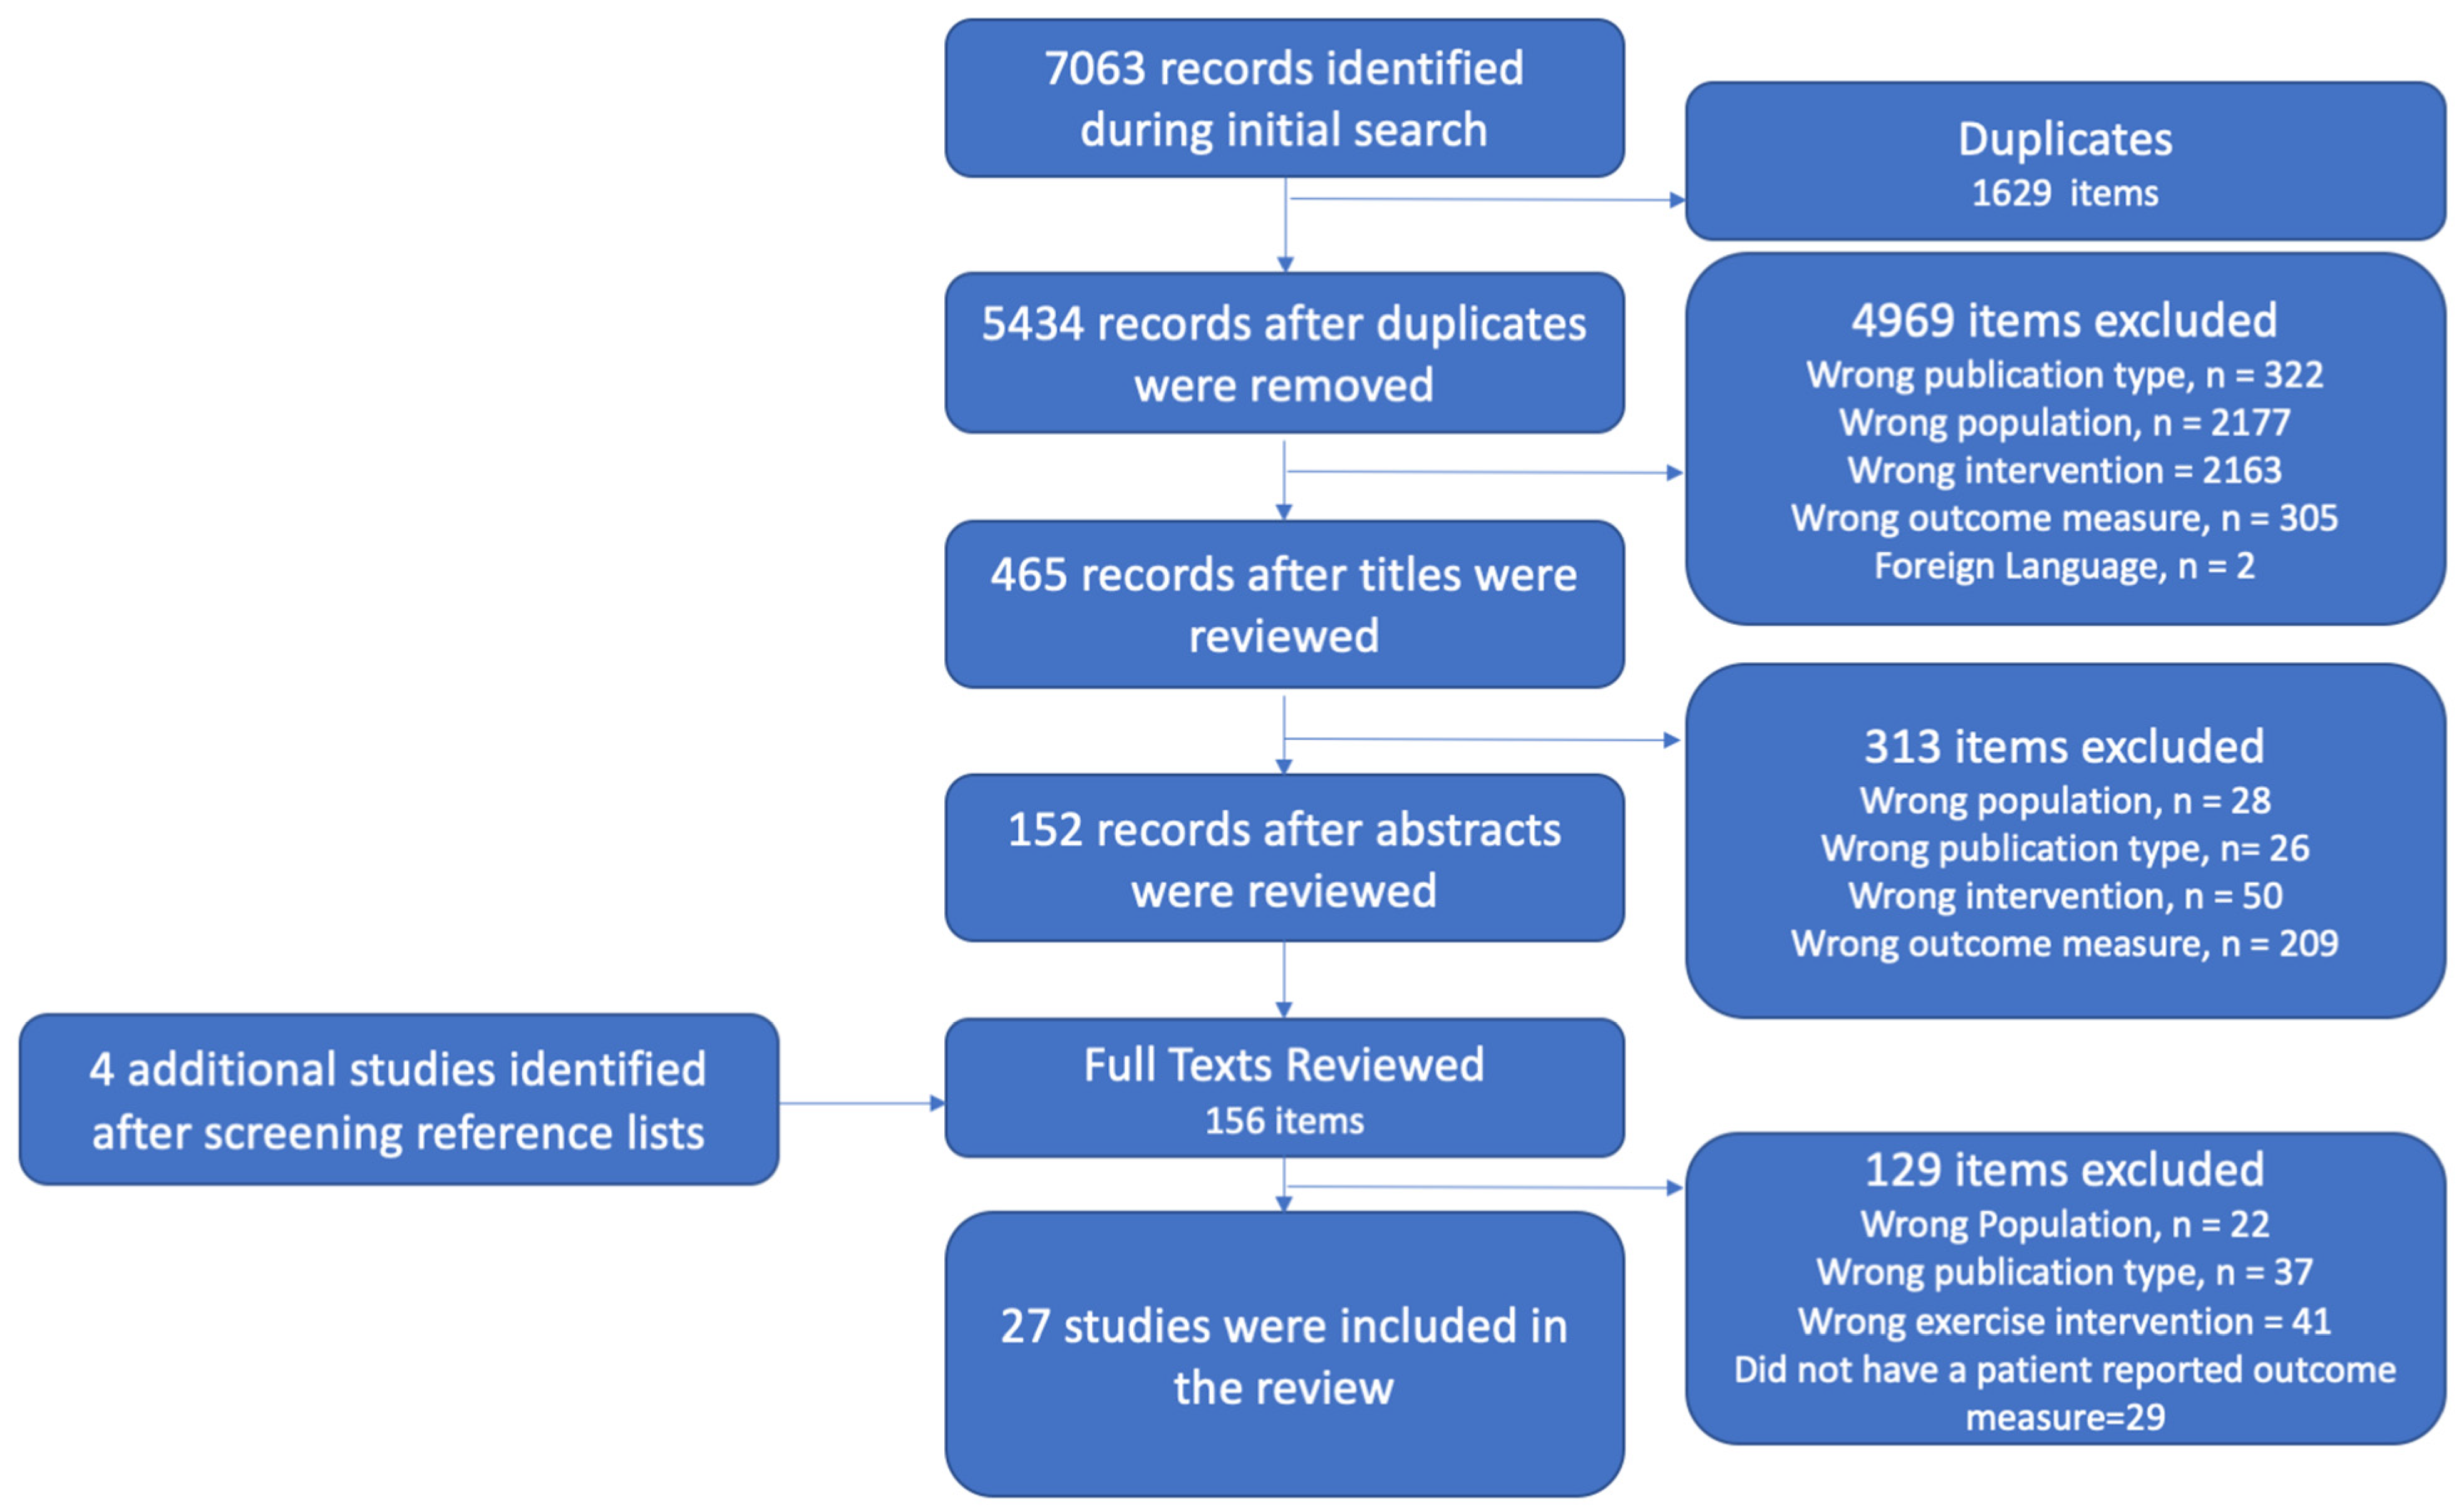
A total of 7063 articles were identified from all included databases upon the initial search. There were 1629 duplicates identified and deleted, leaving 5434 studies for title screening. Title screening resulted in 4969 articles being identified as not relevant. The abstracts of 465 articles were reviewed, and a total of 152 articles remained for full-text screening. Full-text screening resulted in the removal of 128 articles, leaving 24 studies to be included. Reviewing the references of the studies included resulted in four additional studies being identified for full-text review, three of which met the inclusion/exclusion criteria. Implementation of the search strategy and our inclusion/exclusion criteria resulted in a total of 27 studies being included for this review (see Figure 1 for the PRISMA flow diagram).
Figure 1.
PRISMA flow diagram.
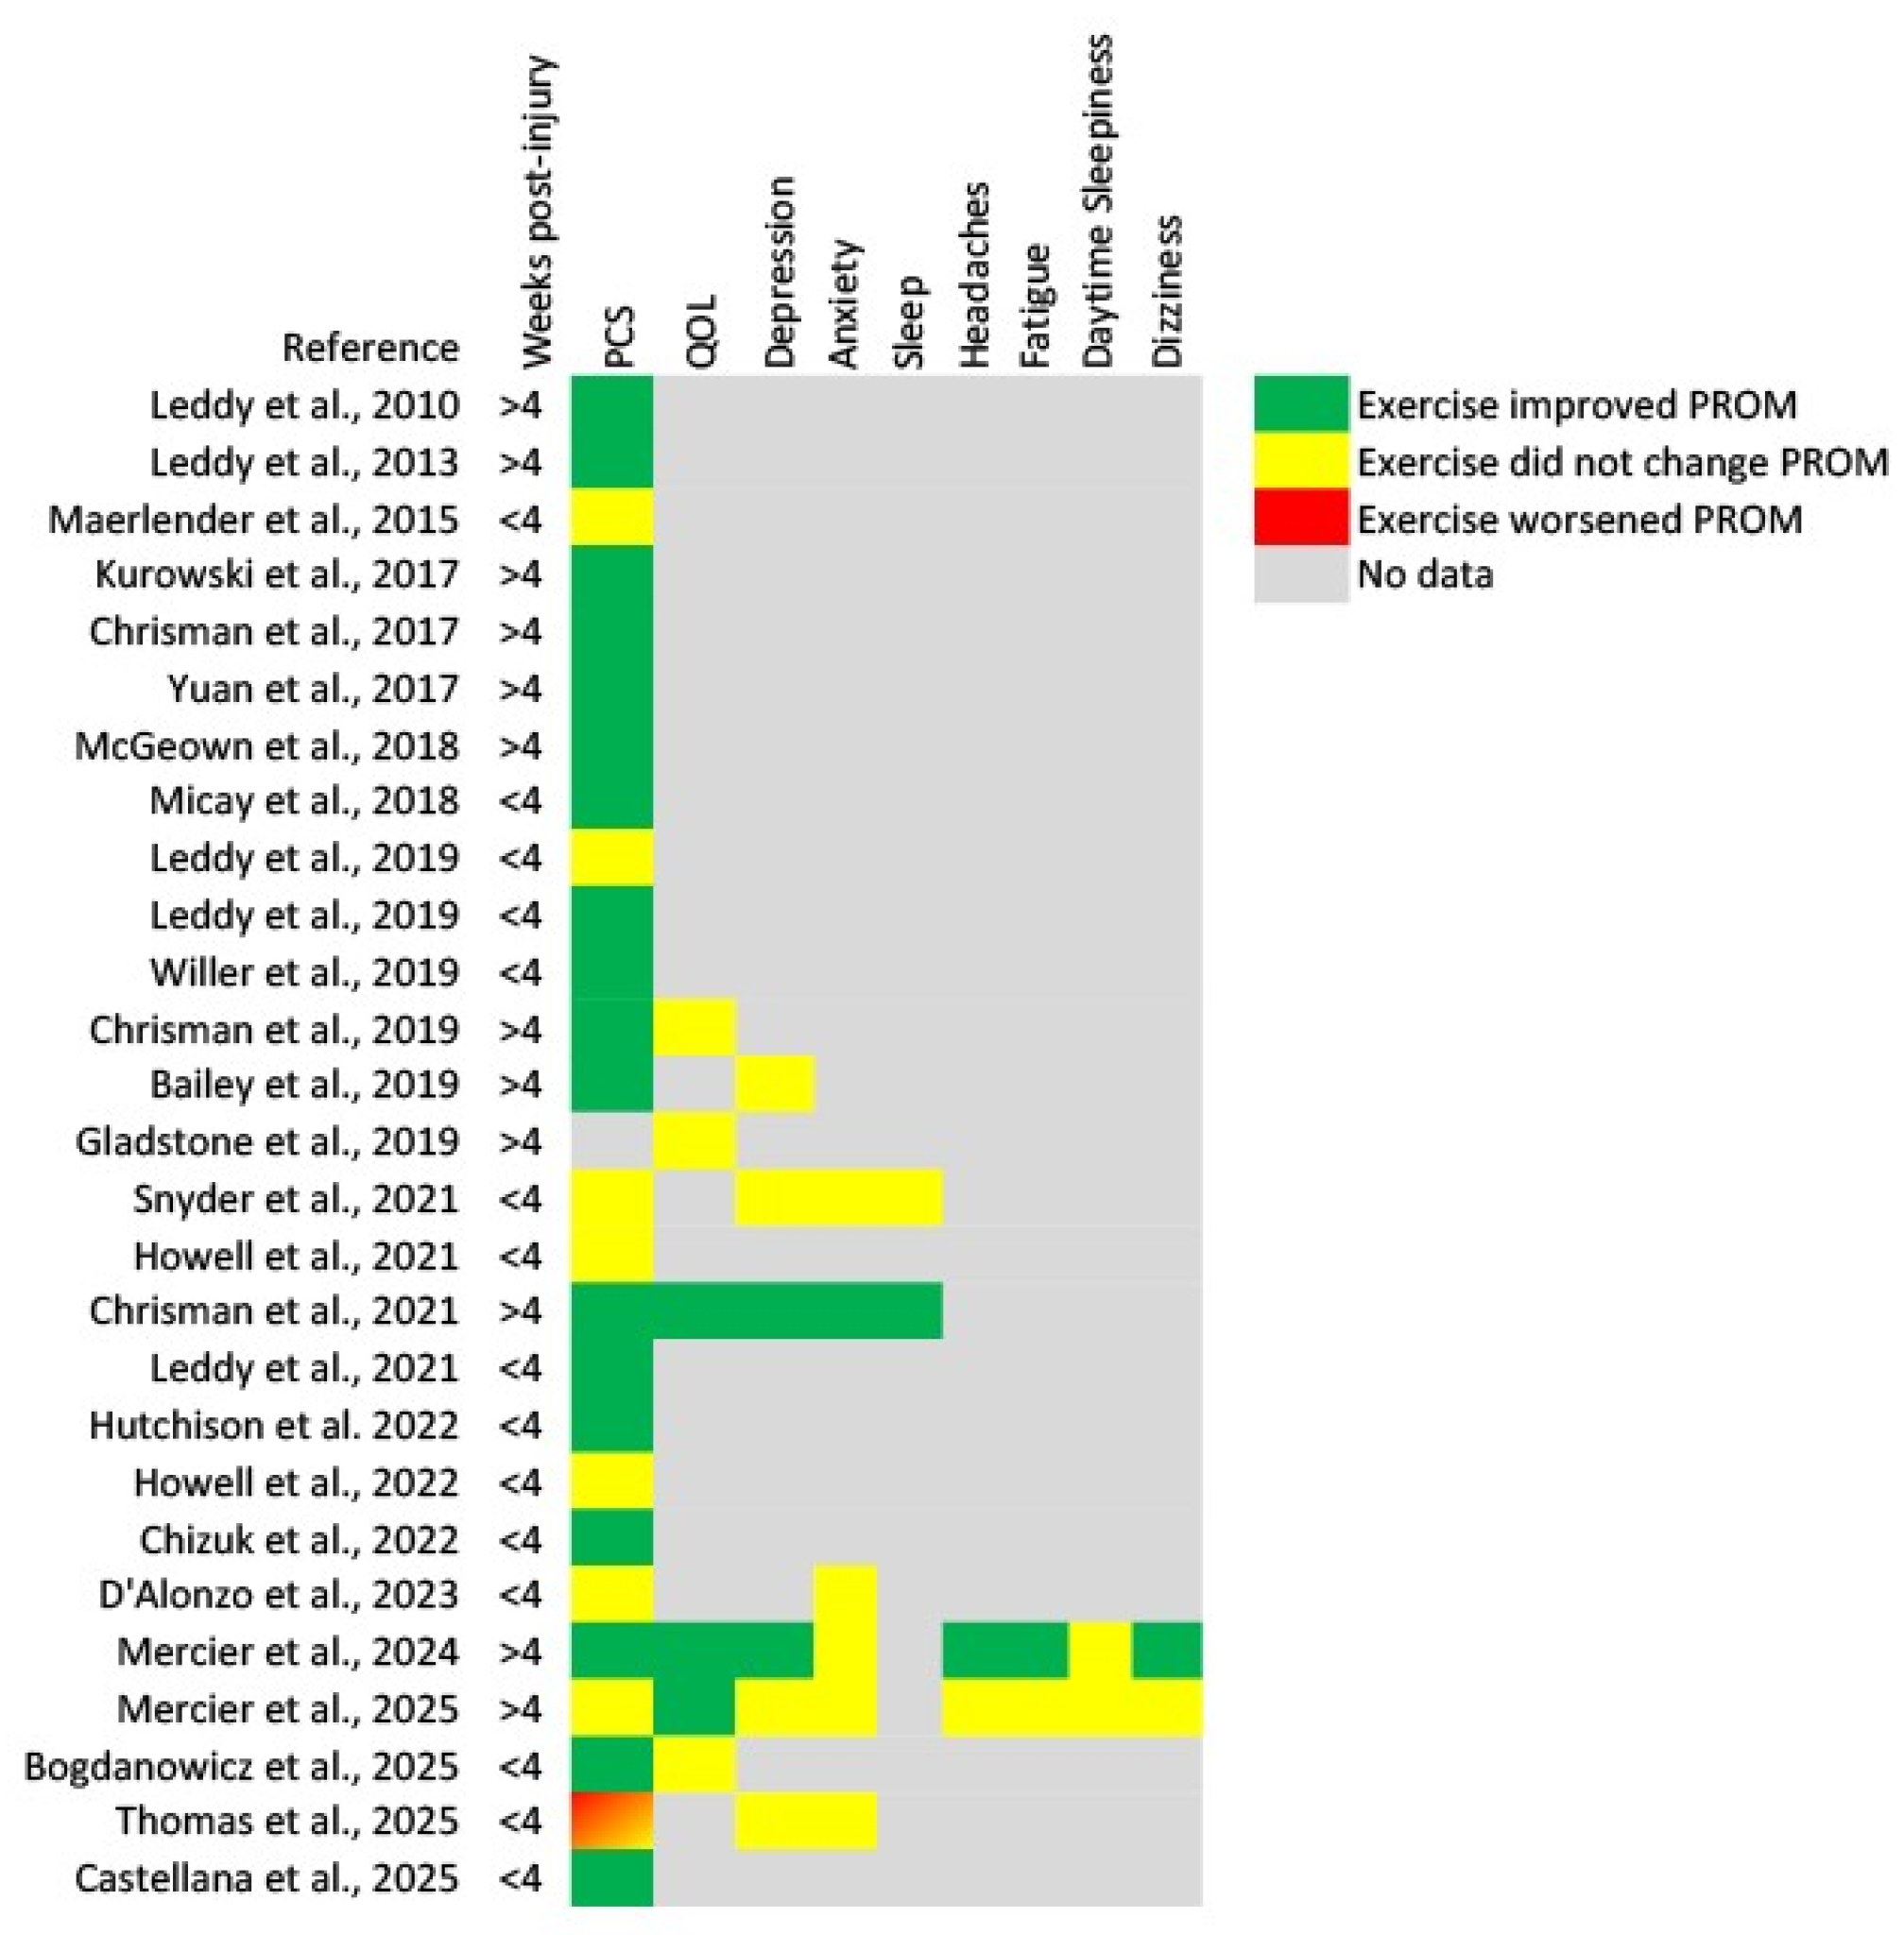
The majority of identified studies included both men and women participants [13,14,15,16,17,19,21,22,23,24,25,26,27,28,29,30,31,32,33,35,36,37,39], while only two studies included only men [20,38]. There were 12 studies that included participants who were more than four weeks post-concussion [14,19,22,23,24,25,27,28,33,35,36,39], and 16 studies that included participants who were enrolled less than four weeks post-concussion [13,15,16,17,18,20,21,26,29,30,31,32,34,37,38]. Additionally, varying prescribed exercise interventions were utilized between studies. The exercise interventions were prescribed based on perceived exertion [13,26], target heart rate [19], a target heart rate based on a percentage of the participant’s age-predicted maximum [16,20,21,28], or individualized based on the participants performance during an exercise tolerance test [14,15,17,18,22,23,24,25,27,29,30,31,33,34,35,36,37,38,39]. Patient-reported symptom severity was consistently reported throughout studies; other PROMs evaluated explored patient quality of life, anxiety and depression, and sleep. Relevant PROMs and study characteristics are listed in Table A2, while PROMs’ responses to an aerobic exercise intervention following mild TBI/concussion are noted in Table A3. A summary of the results for each PROM is found in Table 1, and a summary for each study is found in Figure 2.
Table 1.
Summary of results.
Figure 2.
Heat map of results for each patient-reported outcome measure from each identified study [13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39]. PCS, post-concussion symptoms; QOL, quality of life.
3.2. Symptom Severity Response to Aerobic Exercise Therapy
The most common PROM evaluated in the included studies was symptom severity. The earliest study by Leddy et al. (2010) was conducted in a cohort of adolescent and adult patients with persistent post-concussion symptoms between 6 and 40 weeks post-injury [36]. It was demonstrated that sub-symptom threshold aerobic exercise results in decreased symptom severity and improved rates of symptom recovery when typical recovery, as assessed during the ‘baseline’ phase, is controlled for [36]. A follow-up study that added a placebo group (assigned a stretching protocol) evaluated the same sub-symptom threshold aerobic exercise program in a group of adults with persistent concussion symptoms [24]. Interestingly, they found that the group who performed the sub-symptom threshold aerobic exercise improved their number of symptoms (p < 0.0004), while the placebo group did not change (p = 0.16). These findings have since been corroborated, establishing the efficacy of aerobic exercise therapy in improving patient-reported symptoms in individuals with persistent concussion symptoms [19,22,23,25,27,28,35,39]. However, interventions need to be of sufficient duration, as a six-week aerobic intervention in adults with persisting post-concussion symptoms did not result in improved symptom burden compared to a stretching protocol [14].
Studies have also investigated aerobic exercise therapy in patients who had symptoms for <4 weeks. The earliest identified study by Maerlender et al. (2015) found no difference in the time it took for adolescent concussion patients to be symptom-free between a mild-to-moderate exercise group and a standard care group [26]. More recently, additional studies have supported the finding that an individualized aerobic exercise program may not improve patient-reported symptoms compared to standard care [13,18,21,31,34]. However, other studies have found that aerobic exercise therapy improves the rate of symptom resolution compared to placebo (passive stretching is commonly utilized) or standard care [15,16,17,20,37,38]. Additionally, early aerobic exercise therapy after a concussion may reduce the risk of adolescents developing PPCS [29]. One possible factor that may contribute to these contrasting findings is participant compliance, where participants who are more compliant and complete a higher volume of their prescribed aerobic exercise intervention report greater improvements in symptom severity compared to those who are not compliant [32,34].
3.3. Changes in Patient-Reported Quality of Life with Aerobic Exercise Therapy
The search resulted in six studies that evaluated patient-reported quality of life over time and in response to aerobic exercise therapy in individuals with persistent concussion symptoms [14,19,23,30,33,35]. These studies suggest that participants who perform aerobic exercise report an improved health-related quality of life, but to no different extent than individuals who do not receive aerobic exercise therapy [23,30,33] or receive delayed aerobic exercise therapy [35]. However, one study by Mercier et al. (2025) found that a six-week aerobic exercise therapy program resulted in improved quality of life compared to a stretching protocol with per-protocol analysis, but not with intention-to-treat analysis [14]. However, the mean change of 7.72 points on the Quality Of Life After Brain Injury scale (QOLIBRI) with aerobic exercise therapy [14] did not reach the minimally important clinical difference of 12 points previously identified following brain injury [40]. This suggests that patient compliance may contribute to the previously observed outcomes.
3.4. Changes in Patient-Reported Depression and Anxiety with Aerobic Exercise Therapy
Several of the identified studies investigated patient-reported depressive symptoms as an outcome measure. Over a six-week intervention period in individuals with persistent concussion symptoms, depression improves throughout the recovery of a concussion, but it is unclear if it is influenced by aerobic exercise compared to standard care [13,14,19,22] or delayed aerobic exercise [35]. Shorter durations of intervention (i.e., seven days) do not result in improved reporting of depression in either standard care or aerobic exercise interventions for individuals around 19 days post-injury [21].
Similar to patient-reported depression, few studies investigated patient-reported anxiety. The identified studies show that over a seven-day intervention period, symptoms of trait anxiety, but not state anxiety (evaluated with STAI), can improve in participants with concussions approximately 19 days post-injury [21], while a six-week intervention can improve symptoms of anxiety for individuals with persistent concussion symptoms [19], but possibly to no greater extent than stretching exercise [14]. The change in anxiety symptoms over seven days was no greater than standard care [21], and it is not known whether there is a difference compared to standard care over the longer six-week time period [19]. Additionally, aerobic exercise interventions implemented early after a concussion do not improve patient-reported anxiety to a greater extent compared to the placebo condition (stretching) [31], usual care [13], or delayed aerobic exercise [35].
3.5. Other Patient-Reported Outcomes Measured in Association with Aerobic Exercise Therapy
Several additional PROMs have been investigated, but are all limited to being included in only two studies each. The effects of aerobic exercise interventions on sleep have been investigated [19,21]. Based on the limited literature, over a six-week aerobic exercise intervention period, individuals with persistent concussion symptoms (~75 days post-injury) show improved sleep compared to baseline sleep quality [19]. However, the meaningfulness of the 7.67 point improvement on the Adolescent Sleep–Wake Scale (ASWS) is unknown [19], as an MCID for a concussion or TBI population could not be found. Additionally, a seven-day intervention is insufficient to alter sleep in individuals with more acute (~19 days post-injury) concussions, and there was no standard care or placebo condition, with no difference between individuals undergoing aerobic exercise therapy and those receiving standard care [21]. The functional impact of headache, fatigue, daytime sleepiness, and dizziness has been investigated in two studies by the same research group [14,35]. A six-week aerobic exercise intervention resulted in improved functional impact of headache and fatigue, but these improvements were not different from patients who completed a six-week stretching protocol [14]. Similarly, a 12-week aerobic exercise intervention resulted in improved impact of headache, fatigue, and dizziness [35]. However, Mercier et al. (2024) found that the immediate initiation of a 12-week aerobic exercise program improves the impact of headaches, fatigue, and dizziness to a greater extent than in individuals who delayed the aerobic exercise for six weeks [35].
4. Discussion
The purpose of this scoping review was to identify the effects of aerobic exercise on patient-reported outcomes and to identify the current gaps in the literature. This study identified a limited number of PROMs reported in association with prescribed exercise-based interventions following concussions. The most common PROM evaluated in the literature was a symptom severity score, with fewer studies reporting on patient-reported quality of life, anxiety, depression, and sleep quality. The available literature used a variety of methods to prescribe the exercise intervention, with varying durations, mixed-age patients, differences in time since injury, and different tools to evaluate the same PROMs. Additional research is needed to establish the role prescribed aerobic exercise could play in the response of PROMs.
Patient-reported symptom severity was the most frequently evaluated PROM [13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,34,35,36,37,38,39]. The literature supports that an aerobic exercise intervention improves patient-reported symptoms in patients with persistent post-concussion symptoms (>4 weeks post-injury) [19,22,23,24,25,27,28,36,39]. However, the benefits of aerobic exercise therapy on patient-reported symptoms in patients <4 weeks post-injury are mixed, with some studies finding no benefit [13,18,21,26,31,34] and others finding beneficial outcomes compared to standard care or placebo [15,16,17,20,37,38]. One possible explanation for the differing findings could be compliance, where individuals who performed a greater volume of exercise and complied with their exercise prescription showed beneficial outcomes compared to individuals who did not comply with their prescription [14,32,34].
Compared to patient-reported symptom severity, there were far fewer studies that evaluated other PROMs. Patient-reported quality of life was evaluated in six studies and showed improvement over time, similar to standard care [14,19,23,30,33,35]. However, all but one of these studies [30] were conducted in individuals with persistent post-concussion symptoms for >4 weeks. Further studies on the effects of aerobic exercise initiated early post-concussion on patient-reported quality of life are needed. Also, additional studies that utilize comparable exercise interventions across different ages and time since injury are needed to draw a more complete picture of how aerobic exercise therapy may impact patient-reported quality of life.
Patient-reported depressive symptoms were evaluated in six studies [13,14,19,21,22,35], while patient-reported anxiety was examined in six studies [13,14,19,21,31,35] and sleep in two studies [19,21]. Due to the few number of studies and the use of differing patient populations, four studies were in patients with persistent post-concussion symptoms [14,19,22,35] and one in patients <4 weeks post-injury [21], it is not possible to draw conclusions on the effects of aerobic exercise therapy on patient-reported depression, anxiety, and sleep compared to standard care.
The results of this scoping review identified that few studies investigate PROMs in association with aerobic exercise-based therapy, and that patient-reported symptoms are the main measurement. Future research should evaluate an array of PROMs to develop a further understanding of the holistic patient. The inclusion of PROMs evaluating social aspects, sleep, quality of life, psychological, vestibular, neuromotor function, mood, global outcomes, and family and environmental outcomes post-concussion would provide a more inclusive understanding of the role aerobic exercise could play in a patient’s treatment plan.
One consideration not investigated in the identified literature is the potential role that genetic makeup could play in patient response to exercise therapy following concussion. An individual’s genetic composition could greatly impact their exercise performance and trainability [41,42,43]. Genetic variations may contribute to the heterogeneity of functional adaptations in older adults [44] and cardiovascular and metabolic adaptations to physical activity and exercise [43]. Therefore, certain individuals with a favorable genetic makeup may respond better to a given exercise therapy than others [43]. Symptomology and outcomes following concussion and mTBI are highly variable between individuals [45], which is possibly due to genetic factors [46]. Therefore, the influence of genetic makeup could greatly influence individual outcomes of exercise-based therapy following concussion.
4.1. Limitations of the Literature
The primary limitation of the literature is that most studies only investigated patient-reported symptom severity, and few studies investigated other PROMs. Additionally, the identified studies utilized different exercise interventions, including using different methods for prescribing exercise intensity, implemented the exercise intervention for different durations, and initiated the aerobic exercise at different time points post-concussion.
4.2. Limitations of This Review
A limitation of this review is that only studies published in English, or with an English translation available, were included in this scoping review due to the authors’ abilities. Also, it is not possible or appropriate to draw meaningful conclusions from this review for many of the assessed PROMs due to the limited volume of studies which assessed them, as well as the varying methodologies and demographics in the studies. Another limitation of the literature is that some studies did not report the specific patient-reported symptom severity and instead included the return of symptoms to baseline or reporting of no symptoms as a criterion for medical clearance. It was therefore assumed that, unless otherwise noted in the study, the patient’s medical clearance corresponded with the resolution of symptoms.
4.3. Future Directions
Future research aimed at understanding the effects of aerobic exercise therapy on PROMs beyond symptom severity is needed to fully understand the impact on the holistic patient. Also, future studies should investigate the influence of sex and gender on PROMs in relation to aerobic exercise therapy, since both sex and gender are known to sway injury presentation and recovery time [47,48,49,50]. Finally, in association with aerobic exercise therapy, future research should utilize serial collection of multiple data sources to try and elucidate the relationship between patient demographics, medical history, biological and physiological markers (i.e., biomarkers of injury and neurotrophic factors, cerebral physiologic measures, and quantified tractography and connectivity assessments with neuroimaging), and short- and long-term clinical outcomes and PROMs. Understanding the association of the numerous outcomes could assist in the development of personalized exercise treatment plans to best benefit specific patient populations. The development of a curated polygenic score repository would assist in understanding the genetic influence aerobic exercise may or may not have on an individual following a concussion [51,52].
5. Conclusions
This scoping review highlights the limited available literature that investigates the influence of aerobic exercise therapy on PROMs. Aerobic exercise therapy appears to be beneficial in improving patient-reported symptom severity in patients with persistent post-concussion symptoms and possibly beneficial in patients with more acute concussions as well. The literature investigating patient-reported quality of life, depression, anxiety, and sleep was too limited to draw conclusions due to the few studies, varying exercise interventions, and different initiation times of the interventions. Expanding our understanding of the effects of aerobic exercise therapy after concussion on a broader range of PROMs would assist in understanding the full scope of the role exercise therapy could play after brain injury.
Author Contributions
Conceptualization, D.M.C. and F.A.Z.; methodology, D.M.C. and F.A.Z.; investigation, D.M.C., S.C.L.B. and I.M.; writing—original draft preparation, D.M.C.; writing—review and editing, D.M.C., F.A.Z., S.C.L.B. and I.M. All authors have read and agreed to the published version of the manuscript.
Funding
This work was directly supported through the Pan Am Clinic Foundation and the Endowed Manitoba Public Insurance (MPI) Chair in Neuroscience. FAZ is supported through the Endowed Manitoba Public Insurance (MPI) Chair in Neuroscience/TBI Research Endowment, Natural Sciences and Engineering Research Council of Canada (NSERC) ((DGECR-2022-00260, RGPIN-2022-03621, ALLRP-578524-22, ALLRP-576386-22, I2IPJ-586104–23, ALLRP 586244-23, and ALLRP-597442-24), Canadian Institutes of Health Research (CIHR) (Grant #: 507377, 505116, 472286), the MPI Neuroscience Research Operating Fund, the Health Sciences Center Foundation Winnipeg, the Pan Am Clinic Foundation (Winnipeg, MB), the Canada Foundation for Innovation (CFI) (Project #: 38583), and Research Manitoba (Grant #: 3906, 5429, 5914).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created for the purpose of this study.
Conflicts of Interest
All authors report no conflicts of interest related to this publication. The Pan Am Clinic Foundation receives general education and research support from ConMed Linvatec, Ossur, Zimmer Biomet, and Arthrex.
Abbreviations
The following abbreviations are used in this manuscript:
| GCS | Glasgow Coma Scale |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| PROMs | Patient-Reported Outcome Measures |
| TBI | Traumatic Brain Injury |
Appendix A. Search Terms and Conditions
(Mild traumatic brain injury OR Mild TBI OR Brain injury OR Head injury OR Head trauma OR Cerebral trauma OR Brain trauma OR Cerebral Injury OR Concussion OR Closed brain injury OR Acute brain injury OR Brain injuries OR Cerebrovascular trauma OR Mild concussion OR Cerebral Concussion OR Brain Injuries, Traumatic) AND (Exercise OR Physical activit* OR Aerobic exercise OR Light intensity exercise OR Moderate intensity exercise OR Exercise training OR Acute exercise OR Leisure Activit* OR Recreation OR Exercise Therapy OR Rehabilitation Exercise* OR Exercise Therapies) AND (Post Concussion Syndrome*OR Post-Concussion Syndrome* OR Post-concussive Symptom* OR Post concussive Symptom*OR Post-concussion Symptom* OR Post concussion Symptom* OR Post-Concussion Symptom* OR Chronic post-concussive syndrome* OR Chronic post concussive syndrome* OR Function Recoveries OR Function Recovery OR Recovery of Function* OR Patient-Relevant Outcome* OR Patient Relevant Outcome* OR Clinical Effectiveness OR Treatment Effectiveness OR Rehabilitation Outcome* OR Treatment Outcome* OR Treatment Efficacy OR Clinical Efficacy OR Quality of life OR Life Quality OR Health-related quality of life OR Health Related Quality of Life OR HRQOL OR Cognition OR Cognitive function* OR Memory OR Mental Recall OR Retention OR Spatial Memory OR Short-term memory OR Long-term memory OR Return to Sport* OR Return to Play OR Return to Sporting Activit* OR Resumption of Sporting Activit* OR Sporting Activity Resumption* OR Activities Resumption* OR Return to Recreational Activit* OR Recreational Activities Resumption* OR Return to School* OR Return to Work)
Appendix B. PRISMA-ScR Checklist
Table A1.
Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for scoping reviews (PRISMA-ScR) Checklist.
Appendix C
Table A2.
Study characteristics.
Table A3.
Study results and conclusions.
References
- Pedersen, B.K.; Saltin, B. Exercise as Medicine—Evidence for Prescribing Exercise as Therapy in 26 Different Chronic Diseases. Scand. J. Med. Sci. Sports 2015, 25, 1–72. [Google Scholar] [CrossRef] [Scilit]
- Leddy, J.J.; Haider, M.N.; Ellis, M.; Willer, B.S. Exercise Is Medicine for Concussion. Curr. Sports Med. Rep. 2018, 17, 262–270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giza, C.C.; Hovda, D.A. The Neurometabolic Cascade of Concussion. J. Athl. Train. 2001, 36, 228–235. [Google Scholar] [CrossRef] [Scilit]
- Griesbach, G.S.; Hovda, D.A.; Molteni, R.; Wu, A.; Gomez-Pinilla, F. Voluntary Exercise Following Traumatic Brain Injury: Brain-Derived Neurotrophic Factor Upregulation and Recovery of Function. Neuroscience 2004, 125, 129–139. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.M.; Wong, M.D.; Samii, A.; Hovda, D.A. Evidence for Energy Failure Following Irreversible Traumatic Brain Injury. Ann. N. Y. Acad. Sci. 1999, 893, 337–340. [Google Scholar] [CrossRef] [Scilit]
- Griesbach, G.S.; Gomez-Pinilla, F.; Hovda, D.A. The Upregulation of Plasticity-Related Proteins Following TBI Is Disrupted with Acute Voluntary Exercise. Brain Res. 2004, 1016, 154–162. [Google Scholar] [CrossRef] [Scilit]
- Silverberg, N.D.; Otamendi, T. Advice to Rest for More Than 2 Days After Mild Traumatic Brain Injury Is Associated with Delayed Return to Productivity: A Case-Control Study. Front. Neurol. 2019, 10, 362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cordingley, D.M.; Gomez, A.; Ellis, M.; Zeiler, F.A. Identifying the Cerebral Physiologic Response to Aerobic Exercise Following Concussion: A Scoping Review. J. Head Trauma Rehabil. 2024, 39, E407–E418. [Google Scholar] [CrossRef] [Scilit]
- Cordingley, D.M.; Marquez, I.; Buchwald, S.C.L.; Zeiler, F.A. Response of Central Nervous System Biomolecules and Systemic Biomarkers to Aerobic Exercise Following Concussion: A Scoping Review of Human and Animal Research. Neurotrauma Rep. 2024, 5, 708–720. [Google Scholar] [CrossRef] [Scilit]
- Hunt, C.; Michalak, A.; Ouchterlony, D.; Marshall, S.; Masanic, C.; Vaidyanath, C.; Bhalerao, S.; Cusimano, M.D.; Quon, D.; Fischer, L.K.; et al. Common Data Elements for Concussion in Tertiary Care: Phase One in Ontario. Can. J. Neurol. Sci. 2017, 44, 676–683. [Google Scholar] [CrossRef] [Scilit]
- National Institute of Neurological Disorders and Stroke NINDS Common Data Elements Harmonizing Information. Streamlining Research. Available online: https://www.commondataelements.ninds.nih.gov/ (accessed on 8 October 2024).
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Thomas, D.G.; Erpenbach, H.; Smith, C.N.; Hickey, R.W.; Waltzman, D.; Haarbauer-Krupa, J.; Nelson, L.D.; Patterson, C.G.; McCrea, M.; Collins, M.W.; et al. Impact of Early Activity and Behavioral Management on Acute Concussion Recovery: A Randomized Controlled Trial. J. Pediatr. 2025, 283, 114596. [Google Scholar] [CrossRef] [Scilit]
- Mercier, L.J.; McIntosh, S.J.; Boucher, C.; Joyce, J.M.; Batycky, J.; Galarneau, J.-M.; Esser, M.J.; Schneider, K.J.; Dukelow, S.P.; Harris, A.D.; et al. Effect of Aerobic Exercise on Symptom Burden and Quality of Life in Adults with Persisting Post-Concussive Symptoms: The ACTBI Randomized Controlled Trial. Arch. Phys. Med. Rehabil. 2025, 106, 195–205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leddy, J.J.; Master, C.L.; Mannix, R.; Wiebe, D.J.; Grady, M.F.; Meehan, W.P.; Storey, E.P.; Vernau, B.T.; Brown, N.J.; Hunt, D.; et al. Early Targeted Heart Rate Aerobic Exercise versus Placebo Stretching for Sport-Related Concussion in Adolescents: A Randomised Controlled Trial. Lancet Child Adolesc. Health 2021, 5, 792–799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hutchison, M.G.; Di Battista, A.P.; Lawrence, D.W.; Pyndiura, K.; Corallo, D.; Richards, D. Randomized Controlled Trial of Early Aerobic Exercise Following Sport-Related Concussion: Progressive Percentage of Age-Predicted Maximal Heart Rate versus Usual Care. PLoS ONE 2022, 17, e0276336. [Google Scholar] [CrossRef] [Scilit]
- Leddy, J.J.; Haider, M.N.; Ellis, M.J.; Mannix, R.; Darling, S.R.; Freitas, M.S.; Suffoletto, H.N.; Leiter, J.; Cordingley, D.M.; Willer, B. Early Subthreshold Aerobic Exercise for Sport-Related Concussion: A Randomized Clinical Trial. JAMA Pediatr. 2019, 173, 319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Howell, D.R.; Wingerson, M.J.; Kirkwood, M.W.; Grubenhoff, J.A.; Wilson, J.C. Early Aerobic Exercise among Adolescents at Moderate/High Risk for Persistent Post-Concussion Symptoms: A Pilot Randomized Clinical Trial. Phys. Ther. Sport 2022, 55, 196–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chrisman, S.P.D.; Mendoza, J.A.; Zhou, C.; Palermo, T.M.; Gogue-Garcia, T.; Janz, K.F.; Rivara, F.P. Pilot Study of Telehealth Delivered Rehabilitative Exercise for Youth with Concussion: The Mobile Subthreshold Exercise Program (MSTEP). Front. Pediatr. 2021, 9, 645814. [Google Scholar] [CrossRef] [Scilit]
- Micay, R.; Richards, D.; Hutchison, M.G. Feasibility of a Postacute Structured Aerobic Exercise Intervention Following Sport Concussion in Symptomatic Adolescents: A Randomised Controlled Study. BMJ Open Sport Exerc. Med. 2018, 4, e000404. [Google Scholar] [CrossRef] [Scilit]
- Snyder, A.R.; Greif, S.M.; Clugston, J.R.; FitzGerald, D.B.; Yarrow, J.F.; Babikian, T.; Giza, C.C.; Thompson, F.J.; Bauer, R.M. The Effect of Aerobic Exercise on Concussion Recovery: A Pilot Clinical Trial. J. Int. Neuropsychol. Soc. 2021, 27, 790–804. [Google Scholar] [CrossRef] [Scilit]
- Bailey, C.; Meyer, J.; Briskin, S.; Tangen, C.; Hoffer, S.A.; Dundr, J.; Brennan, B.; Smith, P. Multidisciplinary Concussion Management: A Model for Outpatient Concussion Management in the Acute and Post-Acute Settings. J. Head Trauma Rehabil. 2019, 34, 375–384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chrisman, S.P.D.; Whitlock, K.B.; Mendoza, J.A.; Burton, M.S.; Somers, E.; Hsu, A.; Fay, L.; Palermo, T.M.; Rivara, F.P. Pilot Randomized Controlled Trial of an Exercise Program Requiring Minimal In-Person Visits for Youth with Persistent Sport-Related Concussion. Front. Neurol. 2019, 10, 623. [Google Scholar] [CrossRef] [Scilit]
- Leddy, J.J.; Cox, J.L.; Baker, J.G.; Wack, D.S.; Pendergast, D.R.; Zivadinov, R.; Willer, B. Exercise Treatment for Postconcussion Syndrome: A Pilot Study of Changes in Functional Magnetic Resonance Imaging Activation, Physiology, and Symptoms. J. Head Trauma Rehabil. 2013, 28, 241–249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kurowski, B.G.; Hugentobler, J.; Quatman-Yates, C.; Taylor, J.; Gubanich, P.J.; Altaye, M.; Wade, S.L. Aerobic Exercise for Adolescents with Prolonged Symptoms After Mild Traumatic Brain Injury: An Exploratory Randomized Clinical Trial. J. Head Trauma Rehabil. 2017, 32, 79–89. [Google Scholar] [CrossRef] [Scilit]
- Maerlender, A.; Rieman, W.; Lichtenstein, J.; Condiracci, C. Programmed Physical Exertion in Recovery from Sports-Related Concussion: A Randomized Pilot Study. Dev. Neuropsychol. 2015, 40, 273–278. [Google Scholar] [CrossRef] [Scilit]
- Chrisman, S.P.D.; Whitlock, K.B.; Somers, E.; Burton, M.S.; Herring, S.A.; Rowhani-Rahbar, A.; Rivara, F.P. Pilot Study of the Sub-Symptom Threshold Exercise Program (SSTEP) for Persistent Concussion Symptoms in Youth. NRE 2017, 40, 493–499. [Google Scholar] [CrossRef] [Scilit]
- McGeown, J.P.; Zerpa, C.; Lees, S.; Niccoli, S.; Sanzo, P. Implementing a Structured Exercise Program for Persistent Concussion Symptoms: A Pilot Study on the Effects on Salivary Brain-Derived Neurotrophic Factor, Cognition, Static Balance, and Symptom Scores. Brain Inj. 2018, 32, 1556–1565. [Google Scholar] [CrossRef] [Scilit]
- Castellana, M.C.; Burnett, G.J.; Gasper, A.; Nazir, M.S.Z.; Leddy, J.J.; Master, C.L.; Mannix, R.C.; Meehan, W.P.; Willer, B.S.; Haider, M.N. Adolescents with a High Burden of New-Onset Mood Symptoms After Sport-Related Concussion Benefit from Prescribed Aerobic Exercise, a Secondary Analysis of 2 Randomized Controlled Trials. Clin. J. Sport Med. 2025, 35, 29–36. [Google Scholar] [CrossRef] [Scilit]
- Bogdanowicz, I.; Plante, K.; Leddy, J.; Master, C.; Haider, M. Quality of Life in Adolescent Athletes with Sport-Related Concussion Prescribed Heart Rate-Targeted Aerobic Exercise Within 10 Days of Injury. Clin. Pediatr. 2025, 64, 631–641. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Alonzo, B.A.; Wiebe, D.J.; Master, C.L.; Castellana, M.C.; Willer, B.S.; Leddy, J.J. Relationship between Anxiety and Concussion Symptoms among Adolescents Enrolled in a Randomized Controlled Trial of Aerobic Exercise. NRE 2023, 53, 187–198. [Google Scholar] [CrossRef] [Scilit]
- Chizuk, H.M.; Willer, B.S.; Cunningham, A.; Bezherano, I.; Storey, E.; Master, C.; Mannix, R.; Wiebe, D.J.; Grady, M.F.; Meehan, W.P.; et al. Adolescents with Sport-Related Concussion Who Adhere to Aerobic Exercise Prescriptions Recover Faster. Med. Sci. Sports Exerc. 2022, 54, 1410–1416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gladstone, E.; Narad, M.E.; Hussain, F.; Quatman-Yates, C.C.; Hugentobler, J.; Wade, S.L.; Gubanich, P.J.; Kurowski, B.G. Neurocognitive and Quality of Life Improvements Associated with Aerobic Training for Individuals with Persistent Symptoms After Mild Traumatic Brain Injury: Secondary Outcome Analysis of a Pilot Randomized Clinical Trial. Front. Neurol. 2019, 10, 1002. [Google Scholar] [CrossRef] [Scilit]
- Howell, D.R.; Hunt, D.L.; Aaron, S.E.; Meehan, W.P.; Tan, C.O. Influence of Aerobic Exercise Volume on Postconcussion Symptoms. Am. J. Sports Med. 2021, 49, 1912–1920. [Google Scholar] [CrossRef] [Scilit]
- Mercier, L.J.; McIntosh, S.J.; Boucher, C.; Joyce, J.M.; Batycky, J.; Galarneau, J.-M.; Burma, J.S.; Smirl, J.D.; Esser, M.J.; Schneider, K.J.; et al. Evaluating a 12-Week Aerobic Exercise Intervention in Adults with Persisting Post-Concussive Symptoms. Front. Neurol. 2024, 15, 1482266. [Google Scholar] [CrossRef] [Scilit]
- Leddy, J.J.; Kozlowski, K.; Donnelly, J.P.; Pendergast, D.R.; Epstein, L.H.; Willer, B. A Preliminary Study of Subsymptom Threshold Exercise Training for Refractory Post-Concussion Syndrome. Clin. J. Sport Med. 2010, 20, 21–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Willer, B.S.; Haider, M.N.; Bezherano, I.; Wilber, C.G.; Mannix, R.; Kozlowski, K.; Leddy, J.J. Comparison of Rest to Aerobic Exercise and Placebo-like Treatment of Acute Sport-Related Concussion in Male and Female Adolescents. Arch. Phys. Med. Rehabil. 2019, 100, 2267–2275. [Google Scholar] [CrossRef] [Scilit]
- Leddy, J.J.; Haider, M.N.; Hinds, A.L.; Darling, S.; Willer, B.S. A Preliminary Study of the Effect of Early Aerobic Exercise Treatment for Sport-Related Concussion in Males. Clin. J. Sport Med. 2019, 29, 353–360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yuan, W.; Wade, S.L.; Quatman-Yates, C.; Hugentobler, J.A.; Gubanich, P.J.; Kurowski, B.G. Structural Connectivity Related to Persistent Symptoms After Mild TBI in Adolescents and Response to Aerobic Training: Preliminary Investigation. J. Head Trauma Rehabil. 2017, 32, 378–384. [Google Scholar] [CrossRef] [Scilit]
- Heiberg, G.; Friborg, O.; Pedersen, S.; Thrane, G.; Stabel, H.; Feldbæk Nielsen, J.; Anke, A. Post-Stroke Health-Related Quality of Life at 3 and 12 Months and Predictors of Change in a Danish and Arctic Norwegian Region. J. Rehabil. Med. 2020, 52, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Furrer, R.; Hawley, J.A.; Handschin, C. The Molecular Athlete: Exercise Physiology from Mechanisms to Medals. Physiol. Rev. 2023, 103, 1693–1787. [Google Scholar] [CrossRef] [Scilit]
- Bouchard, C.; An, P.; Rice, T.; Skinner, J.S.; Wilmore, J.H.; Gagnon, J.; Pérusse, L.; Leon, A.S.; Rao, D.C. Familial Aggregation ofV˙ o 2 max Response to Exercise Training: Results from the HERITAGE Family Study. J. Appl. Physiol. 1999, 87, 1003–1008. [Google Scholar] [CrossRef] [Scilit]
- Bouchard, C.; Rankinen, T.; Timmons, J.A. Genomics and Genetics in the Biology of Adaptation to Exercise. Compr. Physiol. 2011, 1, 1603–1648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, G.C.; Mavros, Y.; Tajouri, L.; Singh, M.F. The Role of Genetic Profile in Functional Performance Adaptations to Exercise Training or Physical Activity: A Systematic Review of the Literature. J. Aging Phys. Act. 2019, 27, 594–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kenzie, E.S.; Parks, E.L.; Bigler, E.D.; Lim, M.M.; Chesnutt, J.C.; Wakeland, W. Concussion as a Multi-Scale Complex System: An Interdisciplinary Synthesis of Current Knowledge. Front. Neurol. 2017, 8, 513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davidson, J.; Cusimano, M.D.; Bendena, W.G. Post-Traumatic Brain Injury: Genetic Susceptibility to Outcome. Neuroscientist 2015, 21, 424–441. [Google Scholar] [CrossRef] [Scilit]
- Mollayeva, T.; El-Khechen-Richandi, G.; Colantonio, A. Sex & Gender Considerations in Concussion Research. Concussion 2018, 3, CNC51. [Google Scholar] [CrossRef] [Scilit]
- Koerte, I.K.; Schultz, V.; Sydnor, V.J.; Howell, D.R.; Guenette, J.P.; Dennis, E.; Kochsiek, J.; Kaufmann, D.; Sollmann, N.; Mondello, S.; et al. Sex-Related Differences in the Effects of Sports-Related Concussion: A Review. J. Neuroimaging 2020, 30, 387–409. [Google Scholar] [CrossRef] [Scilit]
- Bretzin, A.C.; Esopenko, C.; D’Alonzo, B.A.; Wiebe, D.J. Clinical Recovery Timelines Following Sport-Related Concussion in Men’s and Women’s Collegiate Sports. J. Athl. Train. 2021, 57, 678–687. [Google Scholar] [CrossRef] [Scilit]
- Bretzin, A.C.; Covassin, T.; Wiebe, D.J.; Stewart, W. Association of Sex with Adolescent Soccer Concussion Incidence and Characteristics. JAMA Netw. Open 2021, 4, e218191. [Google Scholar] [CrossRef] [Scilit]
- Lambert, S.A.; Gil, L.; Jupp, S.; Ritchie, S.C.; Xu, Y.; Buniello, A.; McMahon, A.; Abraham, G.; Chapman, M.; Parkinson, H.; et al. The Polygenic Score Catalog as an Open Database for Reproducibility and Systematic Evaluation. Nat. Genet. 2021, 53, 420–425. [Google Scholar] [CrossRef] [Scilit]
- Yang, S.; Ye, X.; Ji, X.; Li, Z.; Tian, M.; Huang, P.; Cao, C. PGSFusion Streamlines Polygenic Score Construction and Epidemiological Applications in Biobank-Scale Cohorts. Genome Med. 2025, 17, 77. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).