


Abstract
Background/Objectives: Although antimicrobial resistance (AMR) is recognized as a critical global health threat across human, animal, and environmental domains, evidence from AMR economic evaluations remains limited. This study systematically reviewed available studies, emphasizing existing evidence and reported limitations in AMR-related economic evaluations. Methods: A comprehensive review of peer-reviewed empirical studies was conducted, including publications up to July 2023 without temporal restrictions, but limited to English-language articles. Literature searches were undertaken in PubMed and Cochrane using a search strategy centered on the terms “economic evaluations” and “antimicrobial resistance.” Screening and data extraction were performed by two reviewers independently, with disagreements resolved through consensus or consultation with a third reviewer. Findings were synthesized narratively. Results: Of the 3682 records screened, 93 studies were included. Evidence gaps were identified across income and geographic regions, particularly in low- and middle-income countries (LMICs) and the African, Southeast Asian, and Eastern Mediterranean regions. Studies were comparatively more numerous in high-income countries (HICs) and the European and Americas regions. Substantial gaps also existed in one health approach and community-based evaluations. Nine major study limitations were identified, with many interlinked. The most frequent issues included limited generalizability primarily due to inadequate sampling approaches (n = 16), and single-center studies (n = 11), alongside errors in cost estimation (n = 4), and lack of consideration for essential features or information (n = 3). Conclusions: The review highlights persistent evidence gaps and recurring methodological shortcomings in AMR economic evaluations. Addressing these limitations, particularly in LMICs, will strengthen the evidence base and better inform policy implementation to combat AMR effectively.
1. Background
Antimicrobial drugs, which include antibiotics, antivirals, antifungals, and antiparasitics, serve as essential medicines for preventing and treating infectious diseases in humans, animals, and plants [1]. Despite these agents’ life-saving impact over the years, antimicrobial resistance (AMR) is a significant global health challenge and is defined as the ability of microorganisms to counteract the action of antimicrobial agents, particularly when antibiotics lose their effectiveness in inhibiting bacterial growth [2]. The major drivers of AMR are excessive use and inappropriate prescription practices, including incorrect drug selection, duration, and frequency [3].
The World Health Organization (WHO) projected that the unrelenting overuse of antibiotics could result in 10 million global deaths by 2050 and may lead to 24 million people experiencing extreme poverty by 2030 [4]. Additionally, the World Bank (WB) estimated that AMR could result in USD 1 trillion in additional healthcare costs by 2050 and up to USD 3.4 trillion in gross domestic product losses per year by 2030 [5]. Furthermore, a total annual health sector cost of USD 28.2 million for methicillin-resistant Staphylococcus aureus in Canada was reported in 1998 [6], and a total annual hospital cost of USD 5.2 million for Ceftriaxone-resistant Escherichia coli bloodstream infections in Australia was reported in 2014 [7]. AMR has become a primary health concern globally because of its life-threatening impact and substantial economic burden. A recent systematic review reported that the global burden of AMR was due mainly to the pathogens Escherichia coli, Acinetobacter baumannii, Klebsiella pneumoniae, Salmonella spp. and Staphylococcus aureus [8]. This has elevated AMR to a critical global policy issue, and the current focus is to reduce its use, even though antibiotics are indispensable for human, animal, and plant health [9,10].
In this context, AMR evaluation studies are critical for addressing this policy issue by generating evidence on the burden of AMR and highlighting its severity. However, a review article highlighted that the prevailing studies are generally inadequate because of methodological gaps, including narrow perspectives of the analysis and problems associated with the input-cost data [11]. Good-quality research, including economic evaluations and comprehensive modeling, is needed to determine the most effective strategies to combat AMR and to find ways to address these methodological difficulties. More importantly, the number of economic evaluations of AMR is limited globally; moreover, existing evidence is disproportionately lower in LMICs.
With this background, it is critical to understand what evidence is currently available, and a review reporting the economic evidence and limitations of each published study of AMR-related economic evaluations would aid in designing and implementing policy interventions, ultimately helping combat AMR. Therefore, the main aim of this review is to report existing evidence and limitations in published AMR-related economic evaluations worldwide.
2. Methods
2.1. Study Design
We employed the methodology of systematic literature review, following the principles of the ‘Preferred Reporting Items for Systematic Reviews and Meta-Analyses’ (PRISMA) guidelines. The PRISMA Abstract Checklist and the full PRISMA Checklist are presented in Supplementary File S1 and Supplementary File S2, respectively.
2.2. Eligibility Criteria
All peer-reviewed primary empirical studies on economic evaluations of AMR were assessed. There were no temporal restrictions for publications; studies published up to July 2023 were considered. The searches were limited only to the English-language publications.
2.3. Search Strategy
Data sources: The electronic search included bibliographic database searches via PubMed and Cochrane Library. The search was performed on 1 July 2023.
Search terms: The search strategy consisted of two high-level categories, namely, ‘economic evaluations’ and ‘antimicrobial resistance,’ which are searched via medical subject headings (MeSH) and text words. Each of the high-level categories included specific search terms, and the two high-level categories were combined as shown below:
[(“antimicrobial*” OR “antibiotic*” OR “antibacterial*” OR “antiviral*” OR “antifungal*” OR “antiparasitic*”) AND (“resistan*” OR “overus*” OR “misus*”) AND (“economic evaluation” OR “economic burden” OR “cost effective*” OR “cost utility” OR “cost benefit” OR “cost of illness” OR “cost minimization” OR “incremental cost-effectiveness ratio” OR “QALY*” OR “quality adjusted life year*” OR “DALY*” OR “disability adjusted life year*”)]
2.4. Selecting Studies
The outcomes of the searches in each database were exported and deduplicated using Mendeley Desktop 1.19.8 reference management software. Each study’s eligibility was determined based on the basis of the respective study title and abstract (and keywords where applicable) screening. Two independent reviewers assessed and further screened the full-text articles of the potentially eligible studies. A third reviewer resolved any disagreements regarding the inclusion of studies at both stages. The outcomes of this screening process are presented in a PRISMA flow diagram.
2.5. Data Extraction
We extracted data using a systematically developed form in Microsoft Excel that included all the necessary fields to achieve the review’s objectives. The data extraction table template is available in Supplementary File S3.
The key indicators that we prioritized were infection-related data (type of infection, resistant pathogen, and intervention), economic evaluation-related information (type of economic evaluation, main outcome interest, and reported outcomes), and limitations/challenges reported in the studies. This review focused on six economic evaluation types, defined in the section ‘Definition of economic evaluations’ below. Two impartial reviewers meticulously extracted information on study attributes, economic assessments, and any limitations documented in the eligible research studies.
2.6. Definitions of Economic Evaluations
Cost-effectiveness analysis (CEA): CEA refers to a full economic evaluation that considers both the cost and effectiveness of each alternative intervention, and enables the combination of relevant outcome measures with costs, allowing alternatives to be ranked based on their effectiveness relative to resource utilization [12].
Cost-benefit analysis (CBA): CBA is a full economic evaluation that systematically compares the costs and benefits of an intervention to assess its economic profitability. In health economics, CBA compares the expected costs of healthcare interventions with their benefits to determine the most efficient use of resources. It is crucial for making well-informed decisions that enhance patient outcomes and optimize healthcare expenditures [13].
Cost-utility analysis (CUA): CUA is a full economic evaluation and that is considered an essential tool for evaluating and comparing the costs and effects of alternative interventions. CUA involves comparing the additional cost of a program from a specific perspective with the incremental health improvement expressed in terms of quality-adjusted life years (QALYs). CUA is a valuable tool for decision-makers aiming to maximize population health within budget constraints [14].
Cost minimization analysis (CMA): CMA is a full economic evaluation that evaluates and compares the costs of alternative interventions, helping to assess the value for money of an intervention. It is advantageous when both quantity (life years) and quality of life matter, as it measures health effects in terms of both by combining them into a single measure of health: QALYs. CMA is also a valuable tool for decision-makers aiming to maximize population health within a budget constraint [15].
Cost of illness (COI): COI is a partial economic evaluation that is commonly used to measure the economic burden of a specific disease or condition. It aims to identify and measure all costs associated with a particular disease, including direct, indirect, and intangible costs. Direct costs include medical costs, such as diagnostic tests, physician visits, medications, and nonmedical costs, including (but not limited to) travel expenses incurred when obtaining care. Indirect costs encompass productivity losses, such as work or leisure time missed due to the disease. Intangible costs are more challenging to quantify but may include factors such as reduced quality of life. The result of a cost of illness analysis is expressed in monetary terms, providing an estimate of the total economic burden of the disease on society. Decision-makers can use this information to understand the economic impact of a disease and prioritize interventions [16,17].
Disease burden studies: The burden of disease refers to the total and cumulative consequences of a specific disease or a range of harmful diseases within a community. These consequences encompass various aspects, including health impacts, social implications, and societal costs. The concept highlights the gap between an ideal scenario where everyone lives free of disease and disability and the current health status, thereby quantifying the overall burden. One widely used method to quantify the global disease burden is the measure of disability-adjusted life years (DALYs). These studies are crucial for understanding health priorities and informing public health interventions [18,19].
2.7. Quality Assessment
Considering the heterogeneity of the study designs of the selected studies, the Mixed-Methods Appraisal Tool (MMAT) was adapted for the quality appraisal of the eligible studies. The MMAT is a critical appraisal tool used in systematic reviews and meta-analyses that is designed to assess the methodological quality of included studies. It covers five study types: qualitative research, randomized and nonrandomized trials, quantitative descriptive studies, and mixed-methods studies [20]. The evaluation was performed by assigning a score of 1 if the criteria were fully met, 0.5 if the requirements were partially fulfilled, and a score of zero if the criteria were not met or if there was insufficient evidence to draw a conclusion. The sum of the scores for each study was then converted into percentages. A study with a score of more than 75.0% was classified as high quality, 50.0–74.0% as average quality, and less than 50.0% as poor quality. Two reviewers independently appraised the quality of each study, and a third reviewer was engaged when any disagreement occurred during the initial assessments.
2.8. Data Synthesis
An overview of the selected studies was presented, including the study citations, study year, country, income status according to the WB income classification, geographical distribution according to the WHO region classification, and type of economic evaluation. The primary outcome interests of this review, the available evidence and the study limitations of economic evaluations of AMR, were presented according to the type of economic evaluation.
3. Results
3.1. Search Results
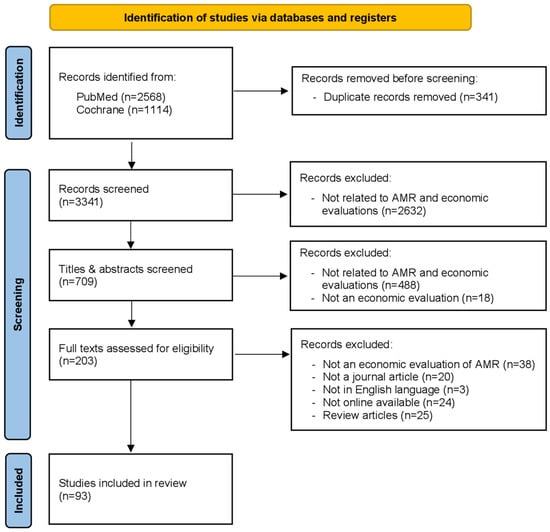
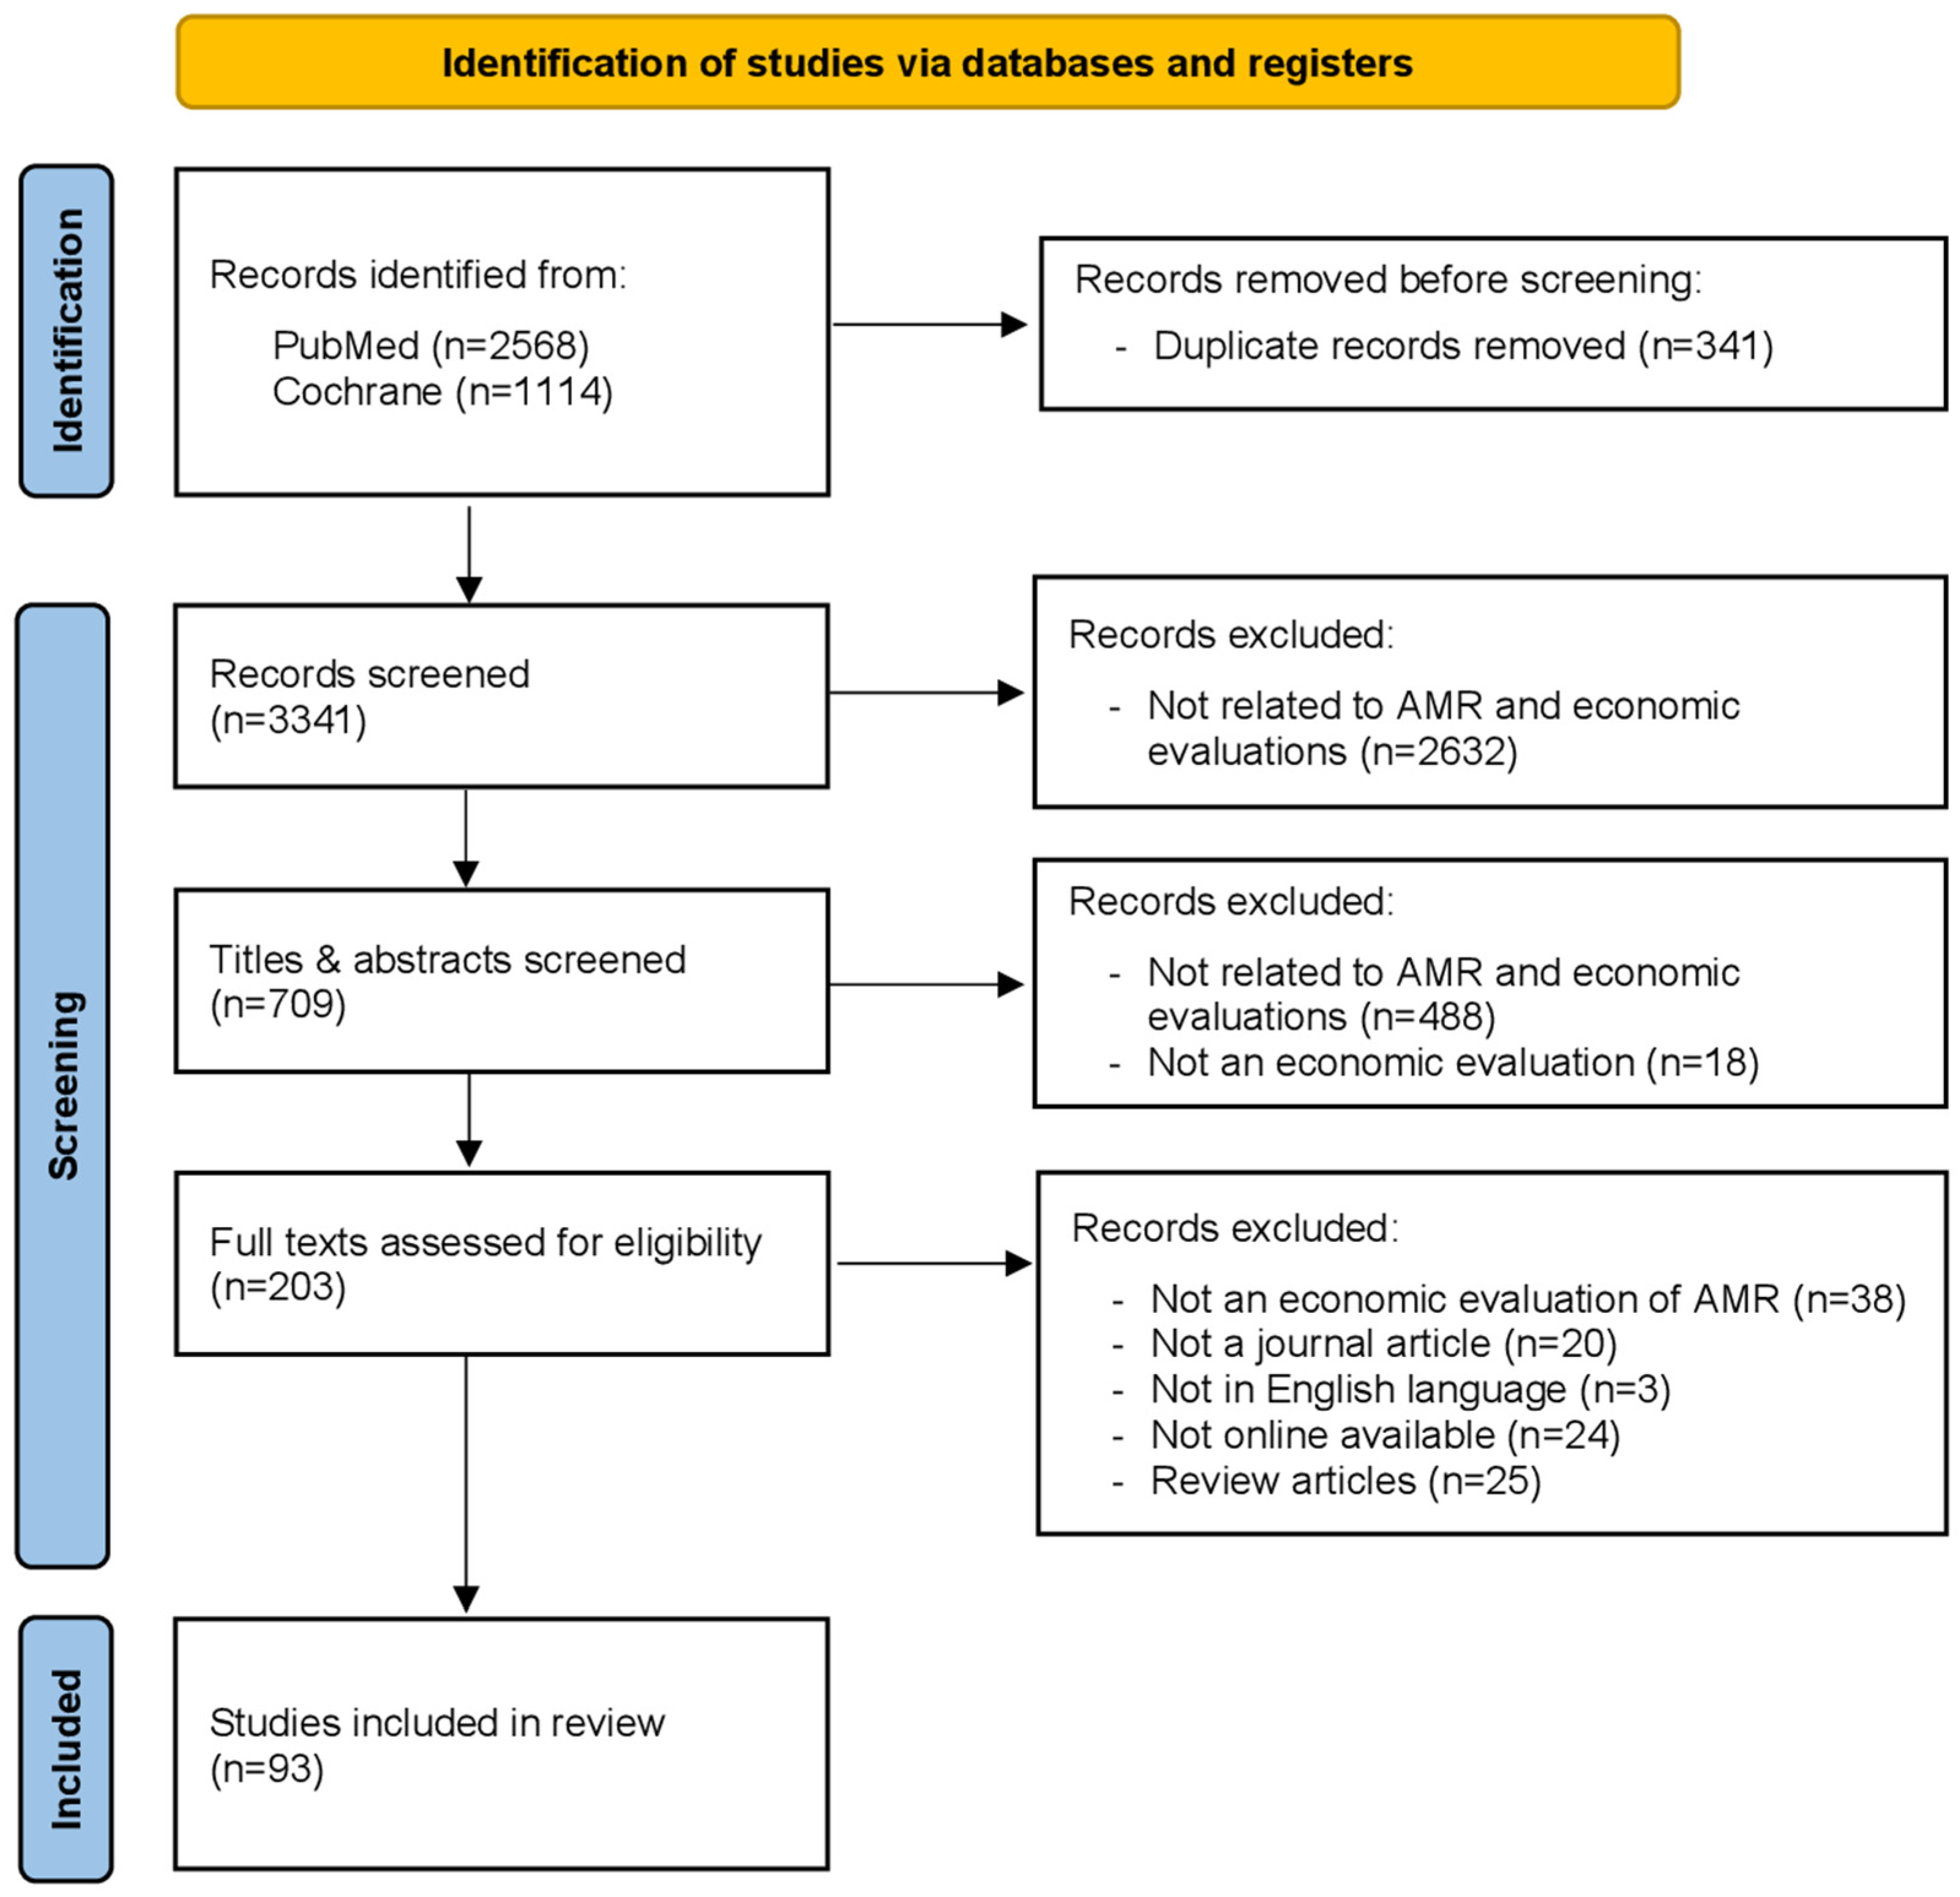
A total of 3682 records were retrieved during the record identification stage by searching the electronic databases PubMed (n = 2568) and Cochrane (n = 1114) (Table 1). After the title, abstract, and full-text screening, 93 articles met the criteria for inclusion in the review (Figure 1).
Table 1.
Database-specific search strategy and number of results per database.
Figure 1.
PRISMA flow diagram.
3.2. Quality Appraisal of Eligible Studies
Among the five study designs considered in the MMAT, this review included only three types of studies, including quantitative randomized controlled trials (n = 30, 32.3%), quantitative nonrandomized studies (n = 29, 31.2%), and quantitative descriptive studies (n = 34, 36.5%).
Among the quantitative randomized controlled trials, the majority (n = 24, 80.0%) were high-quality studies, five (16.7%) trials were of average quality, and one (3.3%) was rated as poor quality. However, among the quantitative nonrandomized studies, most of the studies (n = 15, 51.7%) were average-quality studies, followed by 12 (41.4%) high-quality studies and two (6.9%) poor-quality studies. Most of the quantitative descriptive studies were also high-quality studies (n = 21, 61.8%), followed by 10 (29.4%) average-quality studies and three (8.8%) poor-quality studies.
Overall, this review included 57 (61.3%) high-quality studies, 30 (32.3%) average-quality studies and six (6.5%) poor-quality studies (Supplementary File S4).
3.3. Overview of AMR Economic Evaluations
Among the selected studies (n = 93), 25 (26.2%) either did not report the type of economic evaluation or reported in a way that did not match our classification criteria. Therefore, we reclassified these into six types of economic evaluations (CEA, COI, CBA, CUA, CMA, or disease burden studies) based on their primary outcome of interest. The original and revised classifications are presented in Supplementary File S5.
Most studies were single-country analyses (n = 84, 90.3%) while 8 (8.6%) involved multiple countries, and one (1.1%) study did not specify the study location. Considering both single- and multiple country studies (n = 93), the total amounted to 162 distinct evaluations conducted across 58 countries.
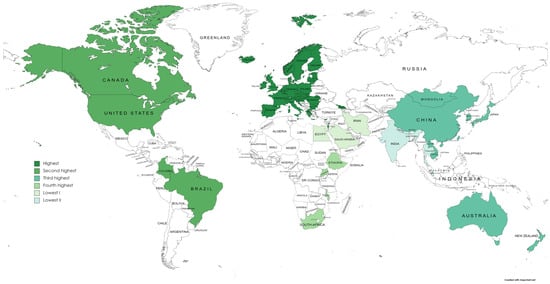
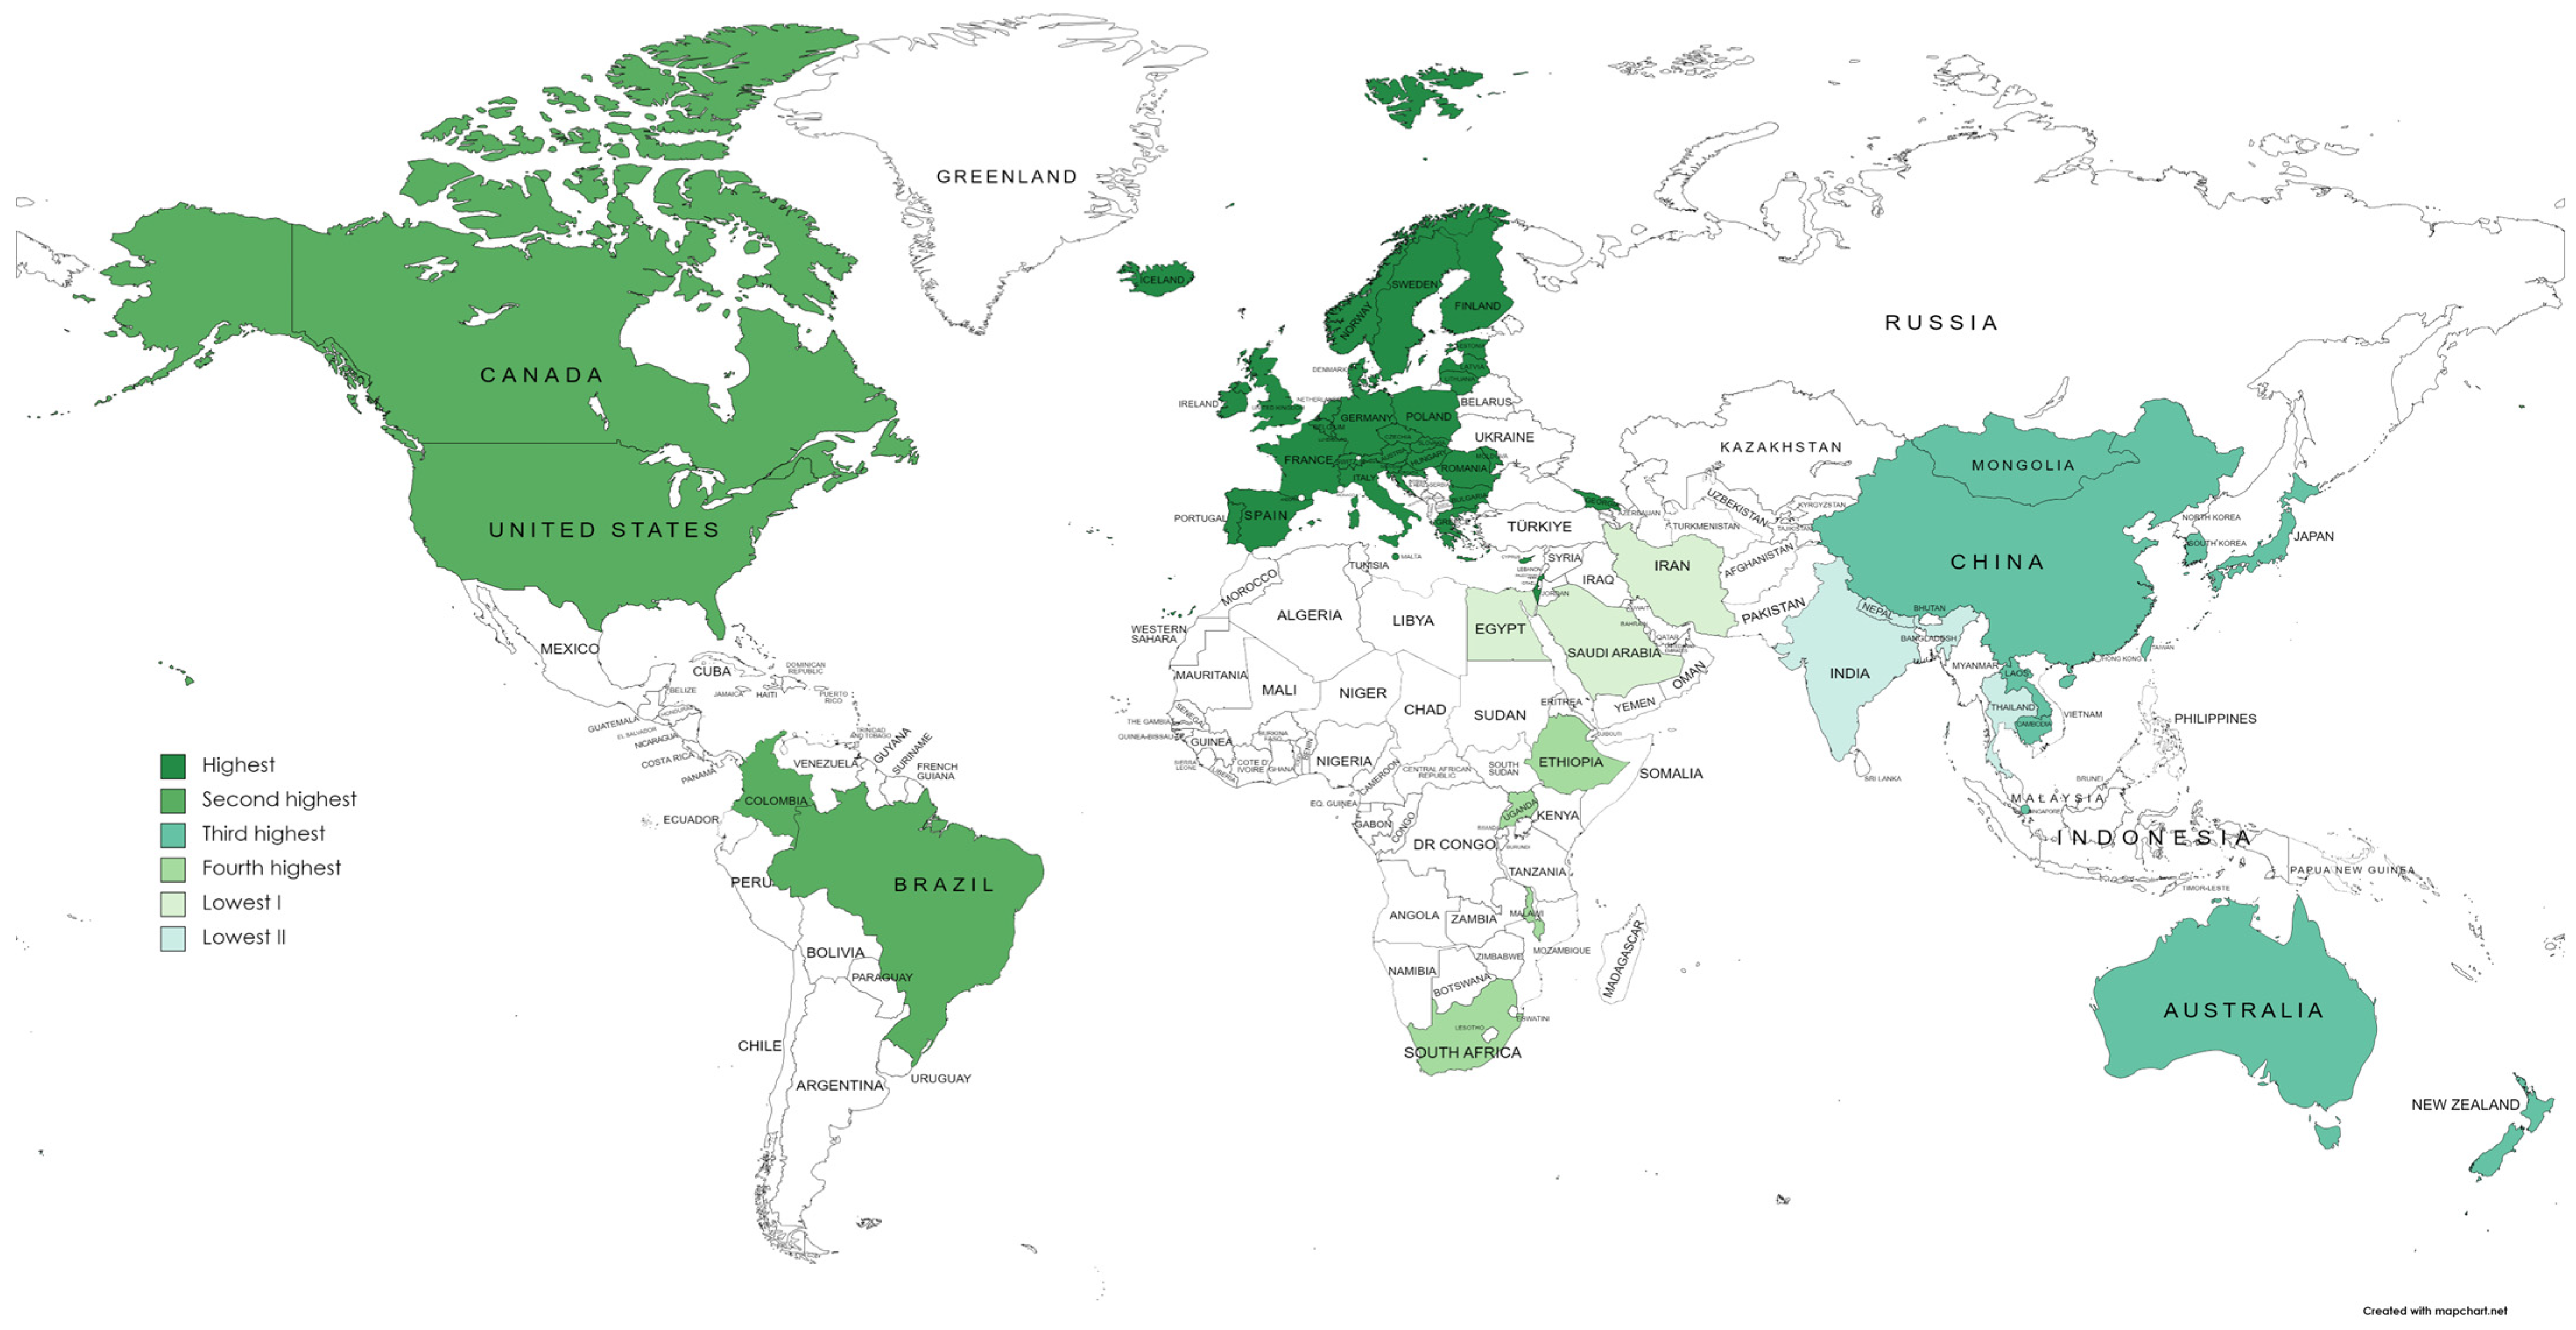
Considering the geographical distribution, Figure 2 presents the spread of AMR economic evaluations across regions based on the WHO regional classification. Across all 162 analyses from 93 studies in 58 countries, the European region accounted for the largest share (52.5%, 85 analysis across 34 countries), followed by the Americas (21.6%, 35 analysis across 4 countries), the Western Pacific region (17.9%, 29 analysis across 10 countries), the African region (4.3%, 7 analysis across 7 countries), the Eastern Mediterranean region (1.9%, 3 analysis across 3 countries), and the South-East Asia region (1.9%, 3 analysis across 3 countries) (Figure 2). Moreover, overview of the studies, including country and income classifications, is provided in Supplementary Files S6–S8.
Figure 2.
Countries reported AMR economic evaluations according to WHO region classification. Note: Highest: 85 analyses (52.5%) in 34 European countries (the UK, Netherlands, Germany, France, Greece, Belgium, Italy, Spain, Switzerland, Austria, Poland, Portugal, Slovakia, Slovenia, Bulgaria, Croatia, Cyprus, Czech Republic, Denmark, Estonia, Finland, Hungary, Iceland, Ireland, Israel, Latvia, Lithuania, Luxembourg, Malta, Norway, Romania, and Georgia, and Moldova); second highest: 35 analyses (21.6%) in four regions of the Americas (USA, Canada, Brazil, and Colombia); third highest: 29 analyses (17.9%) in 10 Western Pacific countries (Japan, Australia, Singapore, Republic of Korea, New Zealand, Taiwan, Cambodia, Lao PDR, Mongolia, and China); fourth highest: seven analyses (4.3%) in seven African countries (Malawi, Ethiopia, Uganda, and South Africa); lowest I: three analyses (1.9%) in three Eastern Mediterranean countries (Saudi Arabia, Egypt, and Iran); lowest II: three analyses (1.9%) in three South East Asian countries.
Most of the studies were CEAs (n = 50, 53.7%), followed by COIs (n = 33, 35.4%), disease burden studies (n = 5, 5.4%), CBAs (n = 2, 2.2%), CUAs (n = 2, 2.2%), and a CMA (n = 1, 1.1%). The distribution of economic evaluations according to the WB income classification of countries is presented in Table 2.
Table 2.
AMR economic evaluations according to the WB income classification.
3.4. Available Evidence of Economic Evaluations of AMR
All the studies were human-centered studies, and no animal- or environmental-related studies were found during this review. With respect to the study setting of all eligible studies, most studies were hospital-based (n = 74, 79.6%), including tertiary-care hospital-based studies (n = 9, 9.7%), followed by community-based (n = 8, 8.6%) and combined hospital- and community-based (n = 4, 4.3%) studies. Furthermore, seven studies (7.5%) did not reveal information related to the study setting. All the human center economic evaluations of AMR involved various infections, interventions, and resistant pathogens, which are presented according to the value type, unit of measurement and reported values in Appendix A.
3.5. Limitations Reported in Studies of AMR-Related Economic Evaluations
3.5.1. Cost-Effectiveness Analysis
Among the 50 CEAs, the most common limitations reported were overestimation of results [21,22,23,24], underestimation of results [23,25,26,27,28,29,30,31], absence of primary data [21,28,32,33,34,35,36,37,38,39,40], lack of consideration of essential features or information [21,26,28,31,32,35,38,41,42,43,44,45,46,47,48,49,50], uncertainty [25,31,34,39,44,51,52,53], inadequate sampling approaches [21,22,29,35,41,44,54,55], assumption errors [23,30,32,47,55,56,57,58], errors in cost estimation [25,26,31,35,42,44,45,49,56,59,60,61,62,63,64], lack of generalizability/standardization of study results to the population [22,26,29,34,35,42,43,44,45,53,62], and other limitations [24,36,48,55,57,58,63]. More details are shown in Table 3. Three CEA studies out of 47 studies did not report limitations.
Table 3.
Limitations associated with AMR-related CEA.
3.5.2. Cost of Illness Studies
Among the 33 COI studies, the most common limitations reported were the underestimation of results [65,66], absence of primary data [66,67,68,69], no consideration of essential features or information [70,71,72,73,74], uncertainty [75,76], inadequate sampling approaches [6,66,73,77,78,79,80], assumption errors [75], errors in cost estimation [6,7,67,68,70,71,72,76,78,81,82,83,84,85,86], lack of generalizability/standardization of study results to the population [66,67,69,70,73,79,81,84,85,86,87,88], and other limitations [65,68,71,73,77,79,89], as shown in Table 4. However, study limitations were not reported in one COI study.
Table 4.
Limitations associated with AMR-related COI.
3.5.3. Other Economic Evaluations: Disease Burden Studies, Cost-Benefit Analysis, Cost-Utility Analysis, and Cost Minimization Analysis
Among the disease burden studies, the absence of primary data [90,91,92,93] and the lack of consideration of essential features or data/information [90,93,94] were the significant limitations reported. The lack of generalizability/standardization of study results to the population was the most common limitation noted in the cost-benefit analysis [95,96], cost-utility analysis [97,98], and cost minimization analysis [99]. Further details are presented in Table 5.
Table 5.
Limitations associated with other economic evaluations of AMR.
3.6. Causes and Consequences of Study Limitations
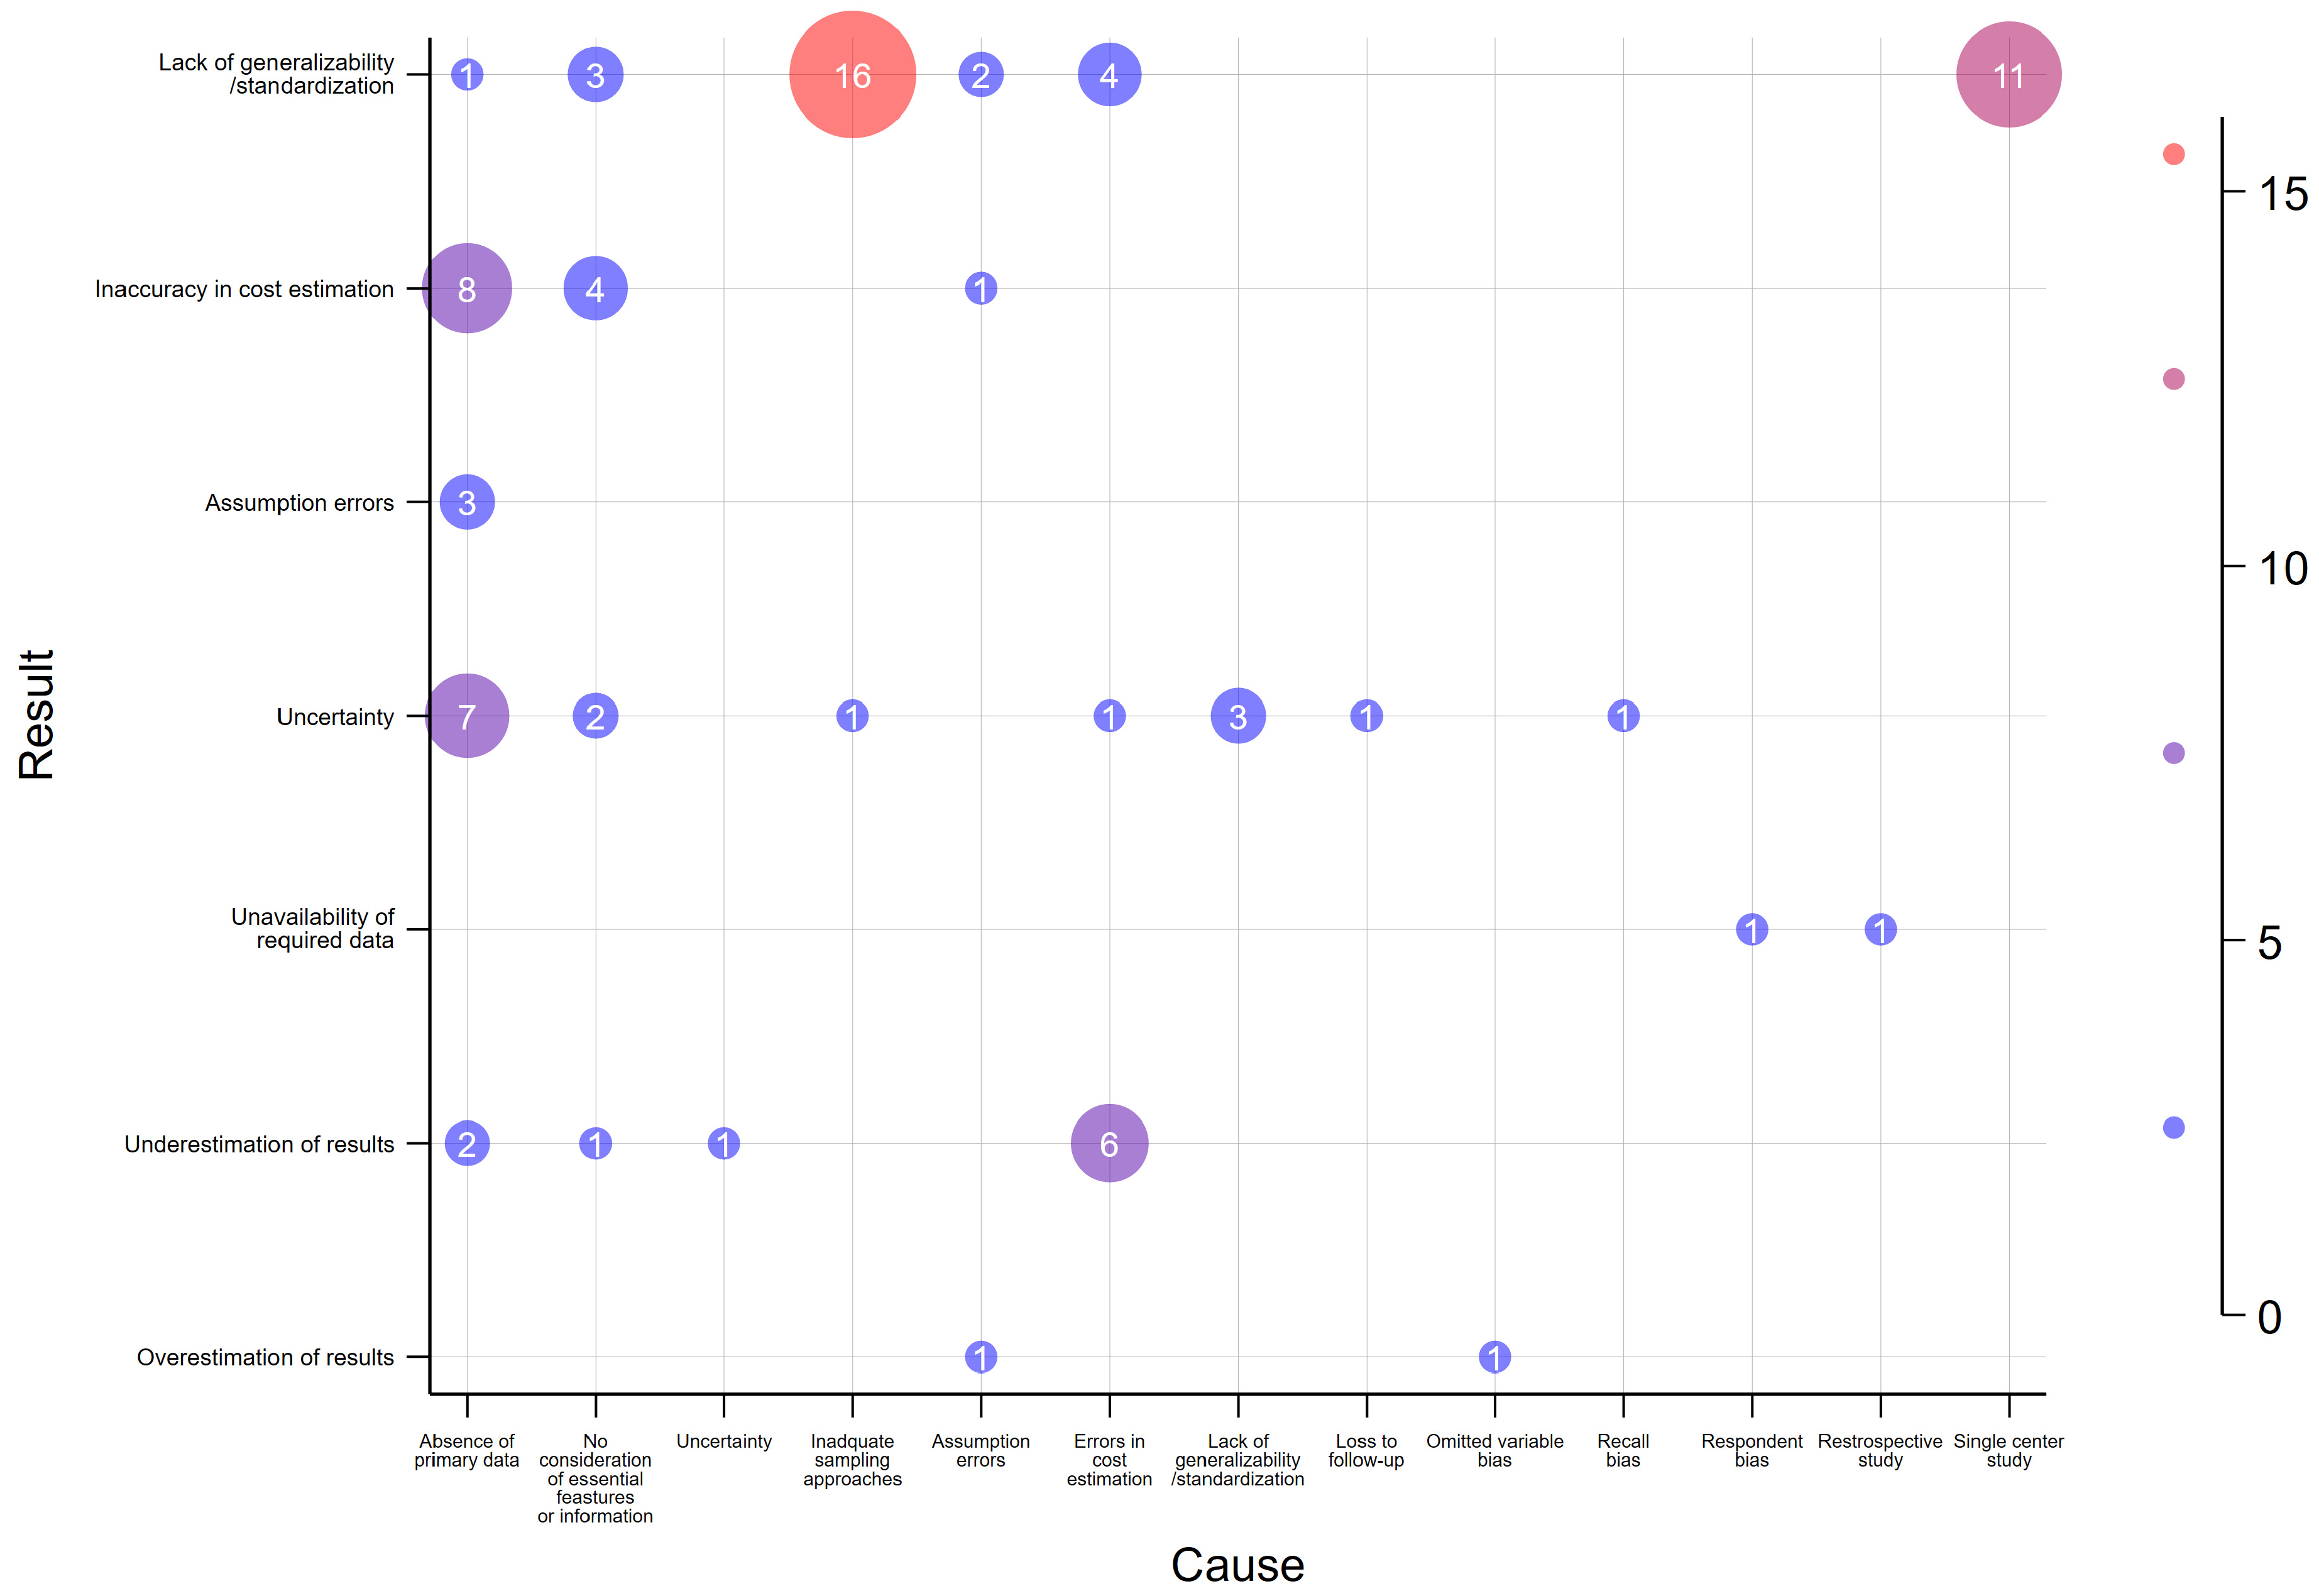
Figure 3 shows the interactions of limitations, showing how one limitation leads to another. The most common limitation interactions were the lack of generalizability/standardization of the study results to the population due to inadequate sampling approaches (reported in 16 studies) [6,21,29,35,41,42,44,54,55,66,67,77,78,79,92,99], single-center studies (reported in 11 studies) [22,41,44,55,73,78,79,80,84,96,98], errors in cost estimation (reported in 4 studies) [70,73,81,87], and no consideration of essential features or information [69,85,88] (reported in 3 studies). Additionally, the absence of primary data led to errors in cost estimation in 8 studies [35,40,45,47,52,60,67,85] and to the uncertainty of the study findings in 7 studies [21,25,31,34,39,52,53]. Furthermore, errors in cost estimation led to underestimations of results in 6 studies [25,27,28,29,31,66]. Further interactions are also presented in Figure 3.
Figure 3.
Causes and consequences of study limitations.
4. Discussion
We conducted a systematic review of published literature up to July 2023, to synthesize all available evidence from economic evaluations related to AMR. Among the 3682 records identified, 93 eligible articles were included in our review. These articles included 50 CEAs, 33 COIs, five disease burden studies, two CBAs, two CUAs, and one CMA.
4.1. Available Evidence and the Evidence Gap in AMR Economic Evaluations
Nearly 75% of the studies originated from HICs, highlighting the disparity in evidence across varying income contexts. The absence of sufficient evidence in LMICs is particularly concerning, given that patients in these regions may require more potent medications, prolonged hospital stays, and additional medical interventions to treat AMR-related diseases. In resource-constrained settings, managing antibiotic-resistant infections poses greater challenges and incurs higher costs [100]. Conducting economic evaluations related to AMR can aid in allocating resources effectively in such resource-limited contexts. The significance of evidence in LMICs becomes apparent when considering the substantial 76% increase in antibiotic usage between 2000 and 2018, while HICs maintained relatively stable consumption during the same period [101]. Furthermore, in contrast to HICs, LMICs and LICs exhibit higher rates of antibiotic misuse due to overuse and self-prescription [102]. Given these challenges, strengthening the global evidence concerning AMR in LMICs is imperative.
Studies are more abundant in the region of Americas, the Western Pacific and European regions. However, only 2–3 articles were published for each African, Southeast Asian, and Eastern Mediterranean region. This pattern suggests that while numerous studies originate from HICs, they predominantly focus on the Americas, Western Pacific, and European regions rather than HICs in other regions. Nevertheless, expanding the evidence base for economic evaluations in other regions is crucial. A recent systematic review revealed that countries in the African region reported 18% higher rates of antibiotic misuse than other nations did [102]. Additionally, the World Health Organization has highlighted the substantial challenges faced by the African region due to inadequate enforcement and rapid proliferation of antibiotic-resistant strains resulting from misuse and overuse of antibiotics. These issues pose a significant threat to Africa’s public health and healthcare system, leading to increased morbidity, mortality, and healthcare expenses [103,104,105,106]. Furthermore, the Southeast Asia region faces significant challenges, as it is at risk of the emergence and spread of AMR in humans. Factors contributing to this risk include poverty, inadequate sanitation, and the overuse of antibiotics [107]. Moreover, a study conducted across 139 hospitals in seven Eastern Mediterranean countries revealed high overall hospital antimicrobial usage [108]. Considering the above findings, strengthening the global evidence concerning AMR in other regions where evidence is lacking is imperative.
Furthermore, despite the high importance and necessity of the One Health Approach for understanding and mitigating AMR, all the available economic evaluations have focused on human health. No studies were found in the Animal or Environmental related fields. This represents a limitation of the one health approach, which aims to sustainably balance the health of people, animals, and ecosystems [109]. A recent systematic review emphasized the importance of one health approach in AMR research, particularly for informing AMR policy decisions [110]. However, achieving these goals remains uncertain due to the lack of evidence related to animal and environmental health.
Additionally, community-based health studies play a crucial role in contextual learning within real-world settings, allowing us to understand health issues, observe health behaviors, and explore social determinants [111]. Unfortunately, the review revealed that most of the studies were conducted in hospital settings, leaving a gap in evidence for community-based evidence.
4.2. Limitations Reported in AMR Economic Evaluations and Their Interactions
We identified nine significant limitations associated with AMR economic evaluations: overestimation of results, underestimation of results, absence of primary data, no consideration of essential features or information, uncertainty, inadequate sampling approaches, assumption errors, errors in cost estimation, lack of generalizability/standardization of study results to the population, etc. When reviewing the limitations of AMR economic evaluations, we found that one limitation often leads to another, creating interconnected links among these limitations. The most common interaction occurs with the lack of generalizability/standardization of study results to the population. This limitation is influenced by other limitations, such as inadequate sampling approaches, reliance on single-center studies, errors in cost estimation, and no consideration of essential features or information.
Inadequate sampling approaches occur because a sample may not exhibit precisely the same behavior as the larger population from which it was selected. It may either underrepresent or overrepresent the study population, especially due to the non-random nature of the sample. For these reasons, inadequate sampling approaches are often recognized as one of the major reasons for the uncertainty and limited generalizability of the study findings [112,113]. On the other hand, single-center studies (a type of sampling error), which are conducted in a single hospital, clinic, or research institution, often involve a homogeneous sample due to limited diversity, as all data collection, participant recruitment, and intervention occur within this location. Therefore, the findings of these studies are generated under context-specific factors and geographical bias, which ultimately affect their generalizability [114,115].
Moreover, we identified the presence of a lack of applicability, and the uncertainty of the study results due to errors in cost estimations [25,27,28,29,31,66]. Errors in the data analysis could affect the applicability of the study findings, as inaccurate measurements or misclassification undermine the validity of the study results. According to this review, one of the reasons for errors in cost estimations is the absence of primary data required for the analysis, which is an uncontrollable limitation, as evidenced by 14 studies [21,25,31,34,35,39,40,45,47,52,53,60,67,85]. Furthermore, the lack of consideration of essential data/information, which could be due to a lack of data/information, also affects the generalizability and standardization of the study results to the population [69,85,88].
Consequently, considering the potential drawbacks and limitations, several critical factors should receive greater attention while addressing existing gaps in evidence. These factors include sample characteristics (such as the representativeness of the sample), the study context (for example, whether it occurs in a controlled laboratory environment), the relevance of the study over time (given societal, technological, and environmental changes), measurement tools, research design, and cultural and geographical considerations, which could impact the generalizability or standardization of study outcomes [113,116,117].
5. Strengths and Limitations
The key advantage of this review lies in our utilization of a comprehensive and sensitive search strategy to capture all published articles related to economic evaluations of AMR. Additionally, we deliberately avoided restricting the search time frame, ensuring that all relevant publications, regardless of their publication date, were included in our analysis up to July 2023.
However, several limitations are associated with this review. First, our search was confined to two research databases. Second, we did not consult the reference lists of eligible studies. Third, we focused exclusively on peer-reviewed journal articles, excluding gray literature, which might have restricted the inclusion of relevant information from published or unpublished sources. Fourth, our search was limited to English-language content, potentially introducing language bias. Fifth, we excluded articles that were not available online and did not contact corresponding authors for access to relevant publications. Finally, we categorized other types of economic evaluations into six predefined categories, which could introduce misclassification bias.
6. Conclusions and Recommendations
This review sheds light on the existing evidence gaps in LMICs, with a particular focus on the African, Southeast Asian, and Eastern Mediterranean regions. These gaps extend to the community-based approach, whereas the One Health Approach suffers from a complete lack of studies related to animal and environmental aspects. Additionally, the review identifies a chain of interrelated limitations, where one limitation often leads to another. The most common limitation lies in the lack of generalizability or standardization of the study outcomes to the population.
It is imperative that future studies address the identified evidence gaps more effectively. Specifically, researchers must focus on tackling the root causes of the most common limitations. These limitations, if left unaddressed, could significantly impact the validity of the study findings. Moreover, addressing these gaps would contribute to evidence-informed policy development aimed at combating AMR.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/antibiotics14111072/s1, Supplementary File S1: PRISMA 2020 for Abstracts Checklist [118]; Supplementary File S2: PRISMA 2020 Checklist [118]; Supplementary File S3: Data extraction template; Supplementary File S4: Quality appraisal of eligible studies; Supplementary File S5: Revised types of economic evaluations; Supplementary File S6: AMR Economic evaluation by income classification; Supplementary File S7: AMR Economic evaluation by countries; Supplementary File S8: Characteristics of selected studies.
Author Contributions
S.G.: carried out the literature review, extracted the data, and prepared the manuscript; Y.H. served as a second reviewer and verified the extracted information; J.-S.L. conceptualized the study and provided overall supervision. All authors have read and agreed to the published version of the manuscript.
Funding
This study was funded by the Fleming Fund (Grant number: FF133/539), a global initiative established by the United Kingdom’s Department of Health and Social Care (DHSC) to combat the growing threat of antimicrobial resistance.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Patients and/or the public were not involved in developing the outcome measures and study design or in conducting, reporting, or disseminating plans for this research at any stage. All authors approved this version for publication. Institutional clearance was obtained for publication.
Data Availability Statement
All the data are included in the manuscript and in the public domain.
Acknowledgments
We acknowledge the generous funding provided by the Fleming Fund, the United Kingdom’s Department of Health and Social Care (DHSC).
Conflicts of Interest
The authors declare that they have no competing interest.
Correction Statement
This article has been republished with a minor correction to the correspondence contact information. This change does not affect the scientific content of the article.
Abbreviations
| AMR | Antimicrobial resistance |
| CBA | Cost–benefit analysis |
| CEA | Cost-effectiveness analysis |
| CMA | Cost minimization analysis |
| COI | Cost of illness |
| CUA | Cost–utility analysis |
| DALYs | Disability-Adjusted Life Years |
| DHSC | Department of Health and Social Care |
| HICs | High-income countries |
| Lao PDR | Lao People’s Democratic Republic |
| LICs | Low-income countries |
| LMICs | Lower- and middle-income countries |
| MeSH | Medical subject headings |
| MMAT | Mixed-methods appraisal tool |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| QALYs | Quality-adjusted life years |
| UK | United Kingdom |
| USA | United States of America |
| WB | World Bank |
| WHO | World Health Organization |
Appendix A
Table A1.
Available evidence from economic evaluations of AMR.
References
- World Health Organization. An Update on the Fight Against Antimicrobial Resistance. 2020. Available online: https://www.who.int/news-room/feature-stories/detail/an-update-on-the-fight-against-antimicrobial-resistance (accessed on 12 April 2024).
- World Health Organization. Antimicrobial Resistance. 2023. Available online: https://www.who.int/news-room/fact-sheets/detail/antimicrobial-resistance (accessed on 15 April 2024).
- Sathyapalan, D.T.; James, J.; Sudhir, S.; Nampoothiri, V.; Bhaskaran, P.N.; Shashindran, N.; Thomas, J.; Prasanna, P.; Mohamed, Z.U.; Edathadathil, F.; et al. Antimicrobial Stewardship and Its Impact on the Changing Epidemiology of Polymyxin Use in a South Indian Healthcare Setting. Antibiotics 2021, 10, 470. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. New Report Calls for Urgent Action to Avert Antimicrobial Resistance Crisis. 2019. Available online: https://www.who.int/news/item/29-04-2019-new-report-calls-for-urgent-action-to-avert-antimicrobial-resistance-crisis (accessed on 12 April 2024).
- World Bank. Drug-Resistant Infections: A Threat to Our Economic Future. n.d. Available online: https://www.worldbank.org/en/topic/health/publication/drug-resistant-infections-a-threat-to-our-economic-future (accessed on 16 April 2024).
- Kim, T.; Oh, P.I.; Simor, A.E. The Economic Impact of Methicillin-Resistant Staphylococcus aureus in Canadian Hospitals. Infect. Control Hosp. Epidemiol. 2001, 22, 99–104. [Google Scholar] [CrossRef] [Scilit]
- Wozniak, T.M.; Bailey, E.J.; Graves, N. Health and economic burden of antimicrobial-resistant infections in Australian hospitals: A population-based model. Infect. Control Hosp. Epidemiol. 2019, 40, 320–327. [Google Scholar] [CrossRef] [Scilit]
- Pulingam, T.; Parumasivam, T.; Gazzali, A.M.; Sulaiman, A.M.; Chee, J.Y.; Lakshmanan, M.; Chin, C.F.; Sudesh, K. Antimicrobial resistance: Prevalence, economic burden, mechanisms of resistance and strategies to overcome. Eur. J. Pharm. Sci. 2022, 170, 106103. [Google Scholar] [CrossRef] [Scilit]
- Pokharel, S.; Shrestha, P.; Adhikari, B. Antimicrobial use in food animals and human health: Time to implement ‘One Health’ approach. Antimicrob. Resist. Infect. Control 2020, 9, 181. [Google Scholar] [CrossRef] [Scilit]
- O’neill, J. Tackling Drug-Resistant Infctions Globally: Final Report and Recommendations. 2016. Available online: https://amr-review.org/sites/default/files/160518_Final%20paper_with%20cover.pdf (accessed on 16 April 2024).
- Coast, J.; Smith, R.D. Antimicrobial resistance: Cost and containment. Expert. Rev. Anti Infect. Ther. 2003, 1, 241–251. [Google Scholar] [CrossRef] [Scilit]
- Levin, H.M.; McEwan, P.J. Cost-Effectiveness Analysis: Methods and Applications, 2nd ed.; Sage: Thousand Oaks, CA, USA, 2001; Volume 4, 308p. [Google Scholar]
- Mishan, E.J.; Quah, E. Cost-Benefit Analysis, 6th ed.; Routledge-Taylor & Francis Group: Oxfordshire, UK, 2021; 404p. [Google Scholar]
- Dernovsek, M.Z.; Rupel, V.P.; Tavcar, R. Cost-Utility Analysis. In Quality of Life Impairment in Schizophrenia, Mood and Anxiety Disorders-New Perspectives on Research and Treatment; Ritsner, M.S., Awad, A.G., Eds.; Springer: Berlin/Heidelberg, Germany, 2022; pp. 373–384. [Google Scholar]
- Duenas, A. Cost-Minimization Analysis. In Encyclopedia of Behavioral Medicine; Gellman, M.D., Turner, J.R., Eds.; Springer: New York, NY, USA, 2013. [Google Scholar]
- Hodgson, T.A. Costs of illness in cost-effectiveness analysis. A review of the methodology. Pharmacoeconomics 1994, 6, 536–552. [Google Scholar] [CrossRef] [Scilit]
- Byford, S.; Torgerson, D.J.; Raftery, J. Economic note: Cost of illness studies. BMJ 2000, 320, 1335. [Google Scholar] [CrossRef] [Scilit]
- Mukherjee, J.S. Global Health and the Global Burden of Disease. In An Introduction to Global Health Delivery; Mukherjee, J.S., Ed.; Oxford Academic: New York, NY, USA, 2017. [Google Scholar]
- Hessel, F. Burden of Disease. In Encyclopedia of Public Health; Kirch, W., Ed.; Springer: Dordrecht, The Netherlands, 2008. [Google Scholar]
- Hong, Q.N.; Pluye, P.; Fàbregues, S.; Bartlett, G.; Boardman, F.; Cargo, M.; Dagenais, P.; Gagnon, M.-P.; Griffiths, F.; Nicolau, B.; et al. Improving the content validity of the mixed methods appraisal tool: A modified e-Delphi study. J. Clin. Epidemiol. 2018, 111, 49–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jansen, J.P.; Kumar, R.; Carmeli, Y. Accounting for the Development of Antibacterial Resistance in the Cost Effectiveness of Ertapenem versus Piperacillin/Tazobactam in the Treatment of Diabetic Foot Infections in the UK. Pharmacoeconomics 2009, 27, 1045–1056. [Google Scholar]
- Wassenberg, M.W.; De Wit, G.A.; Van Hout, B.A.; Bonten, M.J.M. Quantifying cost-effectiveness of controlling nosocomial spread of antibiotic-resistant bacteria: The case of MRSA. PLoS ONE 2010, 5, e11562. [Google Scholar] [CrossRef] [Scilit]
- Weinstein, M.C.; Goldie, S.J.; Losina, E.; Cohen, C.J.; Baxter, J.D.; Zhang, H.; Kimmel, A.D.; Freedberg, K.A. Use of Genotypic Resistance Testing To Guide HIV Therapy: Clinical Impact and Cost-Effectiveness. Ann. Intern. Med. 2001, 134, 440–450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Cock, E.; Krueger, W.A.; Sorensen, S.; Baker, T.; Hardewig, J.; Duttagupta, S.; Müller, E.; Piecyk, A.; Reisinger, E.; Resch, A. Cost-effectiveness of linezolid vs vancomycin in suspected methicillin-resistant Staphylococcus aureus nosocomial pneumonia in Germany. Infection 2009, 37, 123–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Larsson, S.; Edlund, C.; Nauclér, P.; Svensson, M.; Ternhag, A. Cost-Effectiveness Analysis of Temocillin Treatment in Patients with Febrile UTI Accounting for the Emergence of Antibiotic Resistance. Appl. Health Econ. Health Policy 2022, 20, 835–843. [Google Scholar] [CrossRef] [Scilit]
- Xiridou, M.; Lugnér, A.; de Vries, H.J.; van Bergen, J.E.; Götz, H.M.; van Benthem, B.H.; Wallinga, J.; van der Sande, M.A. Cost-Effectiveness of Dual Antimicrobial Therapy for Gonococcal Infections Among Men Who Have Sex With Men in the Netherlands. Sex. Transm. Dis. 2016, 43, 542–548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wan, Y.; Li, Q.; Chen, Y.; Haider, S.; Liu, S.; Gao, X. Economic evaluation among Chinese patients with nosocomial pneumonia caused by methicillin-resistant Staphylococcus aureus and treated with linezolid or vancomycin: A secondary, post-hoc analysis based on a Phase 4 clinical trial study. J. Med. Econ. 2016, 19, 53–62. [Google Scholar] [CrossRef] [Scilit]
- Kirwin, E.; Varughese, M.; Waldner, D.; Simmonds, K.; Joffe, A.M.; Smith, S. Comparing methods to estimate incremental inpatient costs and length of stay due to methicillin-resistant Staphylococcus aureus in Alberta, Canada. BMC Health Serv. Res. 2019, 19, 743. [Google Scholar] [CrossRef] [Scilit]
- Niederman, M.S.; Chastre, J.; Solem, C.T.; Wan, Y.; Gao, X.; Myers, D.E.; Haider, S.; Li, J.Z.; Stephens, J.M. Health economic evaluation of patients treated for nosocomial pneumonia caused by methicillin-resistant Staphylococcus aureus: Secondary analysis of a multicenter randomized clinical trial of vancomycin and linezolid. Clin. Ther. 2014, 36, 1233–1243.e1. [Google Scholar] [CrossRef] [Scilit]
- Jansen, J.P.; Kumar, R.; Carmeli, Y. Cost-effectiveness evaluation of ertapenem versus piperacillin/tazobactam in the treatment of complicated intraabdominal infections accounting for antibiotic resistance. Value Health 2009, 12, 234–244. [Google Scholar] [CrossRef] [Scilit]
- Matsumoto, T.; Darlington, O.; Miller, R.; Gordon, J.; McEwan, P.; Ohashi, T.; Taie, A.; Yuasa, A. Estimating the Economic and Clinical Value of Reducing Antimicrobial Resistance to Three Gram-negative Pathogens in Japan. J. Health Econ. Outcomes Res. 2021, 8, 64–75. [Google Scholar] [CrossRef] [Scilit]
- Oppong, R.; Smith, R.D.; Little, P.; Verheij, T.; Butler, C.C.; Goossens, H.; Coenen, S.; Moore, M.; Coast, J. Cost effectiveness of amoxicillin for lower respiratory tract infections in primary care: An economic evaluation accounting for the cost of antimicrobial resistance. Br. J. Gen. Pract. 2016, 66, e633-9. [Google Scholar] [CrossRef] [Scilit]
- Wysham, W.Z.; Schaffer, E.M.; Coles, T.; Roque, D.R.; Wheeler, S.B.; Kim, K.H. Adding bevacizumab to single agent chemotherapy for the treatment of platinum-resistant recurrent ovarian cancer: A cost effectiveness analysis of the AURELIA trial. Gynecol. Oncol. 2017, 145, 340–345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tringale, K.R.; Carroll, K.T.; Zakeri, K.; Sacco, A.G.; Barnachea, L.; Murphy, J.D. Cost-effectiveness Analysis of Nivolumab for Treatment of Platinum-Resistant Recurrent or Metastatic Squamous Cell Carcinoma of the Head and Neck. J. Natl. Cancer Inst. 2018, 110, 479–485. [Google Scholar] [CrossRef] [Scilit]
- Kong, W.; Yang, X.; Shu, Y.; Li, S.; Song, B.; Yang, K. Cost-effectiveness analysis of ceftazidime-avibactam as definitive treatment for treatment of carbapenem-resistant Klebsiella pneumoniae bloodstream infection. Front. Public Health 2023, 11, 1118307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daniel Mullins, C.; Kuznik, A.; Shaya, F.T.; Obeidat, N.A.; Levine, A.R.; Liu, L.Z.; Wong, W. Cost-effectiveness analysis of linezolid compared with vancomycin for the treatment of nosocomial pneumonia caused by methicillin-resistant Staphylococcus aureus. Clin. Ther. 2006, 28, 1184–1198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fawsitt, C.G.; Vickerman, P.; Cooke, G.S.; Welton, N.J.; Barnes, E.; Ball, J.; Brainard, D.; Burgess, G.; Dillon, J.; Foster, G.; et al. Cost-Effectiveness Analysis of Baseline Testing for Resistance-Associated Polymorphisms to Optimize Treatment Outcome in Genotype 1 Noncirrhotic Treatment-Naive Patients with Chronic Hepatitis C Virus. Value Health 2020, 23, 180–190. [Google Scholar] [CrossRef] [Scilit]
- Martin, M.; Quilici, S.; File, T.; Garau, J.; Kureishi, A.; Kubin, M. Cost-effectiveness of empirical prescribing of antimicrobials in community-acquired pneumonia in three countries in the presence of resistance. J. Antimicrob. Chemother. 2007, 59, 977–989. [Google Scholar] [CrossRef] [Scilit]
- Hollinghurst, S.; Carroll, F.E.; Abel, A.; Campbell, J.; Garland, A.; Jerrom, B.; Kessler, D.; Kuyken, W.; Morrison, J.; Ridgway, N.; et al. Cost-effectiveness of cognitive-behavioural therapy as an adjunct to pharmacotherapy for treatment-resistant depression in primary care: Economic evaluation of the CoBalT Trial. Br. J. Psychiatry 2014, 204, 69–76. [Google Scholar] [CrossRef] [Scilit]
- Ross, E.L.; Soeteman, D.I. Cost-Effectiveness of Esketamine Nasal Spray for Patients with Treatment-Resistant Depression in the United States. Psychiatr. Serv. 2020, 71, 988–997. [Google Scholar] [CrossRef] [Scilit]
- Yi, D.M.; Yang, T.-T.; Chao, S.-H.; Li, Y.-X.; Zhou, Y.-L.; Zhang, H.-H.; Lan, L.; Zhang, Y.-W.; Wang, X.-M.; Zhang, Y.-R.; et al. Comparison the cost-efficacy of furazolidone-based versus clarithromycin-based quadruple therapy in initial treatment of Helicobacter pylori infection in a variable clarithromycin drug-resistant region, a single-center, prospective, randomized, open-label study. Medicine 2019, 98, e14408. [Google Scholar]
- Martin, M.; Moore, L.; Quilici, S.; Decramer, M.; Simoens, S. A cost-effectiveness analysis of antimicrobial treatment of community-acquired pneumonia taking into account resistance in Belgium. Curr. Med. Res. Opin. 2008, 24, 737–751. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harding-Esch, E.M.; Huntington, S.; Harvey, M.J.; Weston, G.; Broad, C.E.; Adams, E.J.; Sadiq, S.T. Antimicrobial resistance point-of-care testing for gonorrhoea treatment regimens: Cost-effectiveness and impact on ceftriaxone use of five hypothetical strategies compared with standard care in England sexual health clinics. Eurosurveillance 2020, 25, 1900402. [Google Scholar] [CrossRef] [Scilit]
- Sado, M.; Koreki, A.; Ninomiya, A.; Kurata, C.; Mitsuda, D.; Sato, Y.; Kikuchi, T.; Fujisawa, D.; Ono, Y.; Mimura, M.; et al. Cost-effectiveness analyses of augmented cognitive behavioral therapy for pharmacotherapy-resistant depression at secondary mental health care settings. Psychiatry Clin. Neurosci. 2021, 75, 341–350. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Zhang, Y.; Wu, B.; Wang, S.; Wu, D.B.-C.; You, R. Cost-Effectiveness of Testing for NS5A Resistance to Optimize Treatment of Elbasvir/Grazoprevir for Chronic Hepatitis C in China. Front. Pharmacol. 2021, 12, 717504. [Google Scholar] [CrossRef] [Scilit]
- Marseille, E.; Kahn, J.G.; Yazar-Klosinski, B.; Doblin, R. The cost-effectiveness of MDMA-assisted psychotherapy for the treatment of chronic, treatment-resistant PTSD. PLoS ONE 2020, 15, e0239997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mac, S.; Fitzpatrick, T.; Johnstone, J.; Sander, B. Vancomycin-resistant enterococci (VRE) screening and isolation in the general medicine ward: A cost-effectiveness analysis. Antimicrob. Resist. Infect. Control 2019, 8, 168. [Google Scholar] [CrossRef] [Scilit]
- Evans, H.L.; Lefrak, S.N.; Lyman, J.; Smith, R.L.; Chong, T.W.; McElearney, S.T.; Schulman, A.R.; Hughes, M.G.; Raymond, D.P.; Pruett, T.L.; et al. Cost of Gram-negative resistance. Crit. Care Med. 2007, 35, 89–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gordon, J.P.; Al Taie, A.; Miller, R.L.; Dennis, J.W.; Blaskovich, M.A.T.; Iredell, J.R.; Turnidge, J.D.; Coombs, G.W.; Grolman, D.C.; Youssef, J. Quantifying the Economic and Clinical Value of Reducing Antimicrobial Resistance in Gram-negative Pathogens Causing Hospital-Acquired Infections in Australia. Infect. Dis. Ther. 2023, 12, 1875–1889. [Google Scholar] [CrossRef] [Scilit]
- Rosu, L.; Madan, J.J.; Tomeny, E.M.; Muniyandi, M.; Nidoi, J.; Girma, M.; Vilc, V.; Bindroo, P.; Dhandhukiya, R.; Bayissa, A.K.; et al. Economic evaluation of shortened, bedaquiline-containing treatment regimens for rifampicin-resistant tuberculosis (STREAM stage 2): A within-trial analysis of a randomised controlled trial. Lancet Glob. Health 2023, 11, e265–e277. [Google Scholar] [CrossRef] [Scilit]
- Liao, M.; Jiang, Q.; Hu, H.; Han, J.; She, L.; Yao, L.; Ding, D.; Huang, J. Cost-effectiveness analysis of utidelone plus capecitabine for metastatic breast cancer in China. J. Med. Econ. 2019, 22, 584–592. [Google Scholar] [CrossRef] [Scilit]
- Reed, S.D.; Li, Y.; Anstrom, K.J.; Schulman, K.A. Cost effectiveness of ixabepilone plus capecitabine for metastatic breast cancer progressing after anthracycline and taxane treatment. J. Clin. Oncol. 2009, 27, 2185–2191. [Google Scholar] [CrossRef] [Scilit]
- Phillips, M.T.; Antillon, M.; Bilcke, J.; Bar-Zeev, N.; Limani, F.; Debellut, F.; Pecenka, C.; Neuzil, K.M.; Gordon, M.A.; Thindwa, D.; et al. Cost-effectiveness analysis of typhoid conjugate vaccines in an outbreak setting: A modeling study. BMC Infect. Dis. 2023, 23, 143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tu, M.M.; Clemons, M.; Stober, C.; Jeong, A.; Vandermeer, L.; Mates, M.; Blanchette, P.; Joy, A.A.; Aseyev, O.; Pond, G.; et al. Cost-Effectiveness Analysis of 12-Versus 4-Weekly Administration of Bone-Targeted Agents in Patients with Bone Metastases from Breast and Castration-Resistant Prostate Cancer. Curr. Oncol. 2021, 28, 1847–1856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cara, A.K.S.; Szaidi, T.R.; Suleman, F. Cost-effectiveness analysis of low versus high dose colistin in the treatment of multi-drug resistant pneumonia in Saudi Arabia. Int. J. Clin. Pharm. 2018, 40, 1051–1058. [Google Scholar] [CrossRef] [Scilit]
- Pollard, M.E.; Moskowitz, A.J.; Diefenbach, M.A.; Hall, S.J. Cost-effectiveness analysis of treatments for metastatic castration resistant prostate cancer. Asian J. Urol. 2017, 4, 37–43. [Google Scholar] [CrossRef] [Scilit]
- Wolfson, L.J.; Walker, A.; Hettle, R.; Lu, X.; Kambili, C.; Murungi, A.; Knerer, G. Cost-effectiveness of adding bedaquiline to drug regimens for the treatment of multidrug-resistant tuberculosis in the UK. PLoS ONE 2015, 10, e0120763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xin, W.; Ding, H.; Fang, Q.; Zheng, X.; Tong, Y.; Xu, G.; Yang, G. Cost-effectiveness of pembrolizumab for treatment of platinum-resistant recurrent or metastatic head and neck squamous cell carcinoma in China: An economic analysis based on a randomised, open-label, phase III trial. BMJ Open 2020, 10, e038867. [Google Scholar] [CrossRef] [Scilit]
- Simpson, K.N.; Welch, M.J.; Kozel, F.A.; Demitrack, M.A.; Nahas, Z. Cost-effectiveness of transcranial magnetic stimulation in the treatment of major depression: A health economics analysis. Adv. Ther. 2009, 26, 346–368. [Google Scholar] [CrossRef] [Scilit]
- Machado, A.R.L.; Arns, C.d.C.; Follador, W.; Guerra, A. Cost-Effectiveness of Linezolid versus Vancomycin in Mechanical Ventilation Associated Nosocomial Pneumonia Caused by Methicillin-Resistant Staphylococcus aureus. Braz. J. Infect. Dis. 2005, 9, 191–200. [Google Scholar] [CrossRef] [Scilit]
- Breuer, T.; Graham, D.Y. Costs of Diagnosis and Treatment of Helicobacter pylori Infection: When Does Choosing the Treatment Regimen Based on Susceptibility Testing Become Cost Effective? Am. J. Gastroenterol. 1999, 94, 725–729. [Google Scholar] [CrossRef] [Scilit]
- Morgans, A.K.; Hutson, T.; Guan, A.K.D.; Garcia, D.; Zhou, A.; Drea, E.; Vogelzang, N.J. An economic evaluation of cabazitaxel versus a second androgen receptor-targeted agent (ARTA) for patients with metastatic castration-resistant prostate cancer previously treated with docetaxel and an ARTA: The United States payer perspective. BMC Health Serv. Res. 2022, 22, 916. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papaefthymiou, A.; Liatsos, C.; Georgopoulos, S.D.; Apostolopoulos, P.; Doulberis, M.; Kyriakos, N.; Giakoumis, M.; Papadomichelakis, M.; Galanopoulos, M.; Katsinelos, P.; et al. Helicobacter pylori eradication regimens in an antibiotic high-resistance European area: A cost-effectiveness analysis. Helicobacter 2020, 25, e12666. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lynch, F.L.; Dickerson, J.F.; Clarke, G.; Vitiello, B.; Porta, G.; Wagner, K.D.; Emslie, G.; Asarnow, J.R.; Keller, M.B.; Birmaher, B.; et al. Incremental Cost-effectiveness of Combined Therapy vs Medication Only for Youth with Selective Serotonin Reuptake Inhibitor–Resistant Depression. Arch. Gen. Psychiatry 2011, 68, 253–262. [Google Scholar] [CrossRef] [Scilit]
- Zhen, X.; Lundborg, C.S.; Sun, X.; Gu, S.; Dong, H. Clinical and Economic Burden of Carbapenem-Resistant Infection or Colonization Caused by Klebsiella pneumoniae, Pseudomonas aeruginosa, Acinetobacter baumannii: A Multicenter Study in China. Antibiotics 2020, 9, 514. [Google Scholar] [CrossRef] [Scilit]
- Uematsu, H.; Stålsby Lundborg, C.; Sun, X.; Gu, S.; Dong, H. The economic burden of methicillin-resistant Staphylococcus aureus in community-onset pneumonia inpatients. Am. J. Infect. Control 2016, 44, 1628–1633. [Google Scholar] [CrossRef] [Scilit]
- Naylor, N.R.; Yamashita, K.; Iwami, M.; Kunisawa, S.; Mizuno, S.; Castro-Sánchez, E.; Imanaka, Y.; Ahmad, R.; Holmes, A. Code-Sharing in Cost-of-Illness Calculations: An Application to Antibiotic-Resistant Bloodstream Infections. Front. Public Health 2020, 8, 562427. [Google Scholar] [CrossRef] [Scilit]
- Browne, C.; Muszbek, N.; Chapman, R.; Marsh, K.; Gould, I.M.; Seaton, R.A.; Allen, M. Comparative healthcare-associated costs of methicillin-resistant Staphylococcus aureus bacteraemia-infective endocarditis treated with either daptomycin or vancomycin. Int. J. Antimicrob. Agents 2016, 47, 357–361. [Google Scholar] [CrossRef] [Scilit]
- Madan, J.J.; Rosu, L.; Tefera, M.G.; van Rensburg, C.; Evans, D.; Langley, I.; Tomeny, E.M.; Nunn, A.; Phillips, P.P.; Rusen, I.D.; et al. Economic evaluation of short treatment for multidrug-resistant tuberculosis, Ethiopia and South Africa: The STREAM trial. Bull. World Health Organ. 2020, 98, 306–314. [Google Scholar] [CrossRef] [Scilit]
- McCollum, M.; Sorensen, S.V.; Liu, L.Z. A Comparison of Costs and Hospital Length of Stay Associated with Intravenous/Oral Linezolid or Intravenous Vancomycin Treatment of Complicated Skin and Soft-Tissue Infections Caused by Suspected or Confirmed Methicillin Resistant Staphylococcus aureus in Elderly US Patients. Clin. Ther. 2007, 29, 469–477. [Google Scholar]
- Zhen, X.; Li, Y.; Chen, Y.; Dong, P.; Liu, S.; Dong, H. Effect of multiple drug resistance on total medical costs among patients with intra-abdominal infections in China. PLoS ONE 2018, 13, e0193977. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, K.H.; Kim, C.-J.; Choi, N.-K.; Ahn, J.; Choe, P.G.; Park, W.B.; Kim, N.J.; Choi, H.J.; Bae, J.Y.; Kim, E.S.; et al. Clinical and economic burden of bacteremia due to multidrug-resistant organisms in Korea: A prospective case control study. J. Glob. Antimicrob. Resist. 2022, 31, 379–385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roberts, R.R.; Hota, B.; Ahmad, I.; Scott, R.D., II; Foster, S.D.; Abbasi, F.; Schabowski, S.; Kampe, L.M.; Ciavarella, G.G.; Supino, M.; et al. Hospital and societal costs of antimicrobial-resistant infections in a Chicago teaching hospital: Implications for antibiotic stewardship. Clin. Infect. Dis. 2009, 49, 1175–1184. [Google Scholar] [CrossRef] [Scilit]
- Stewardson, A.J.; Allignol, A.; Beyersmann, J.; Graves, N.; Schumacher, M.; Meyer, R.; Tacconelli, E.; De Angelis, G.; Farina, C.; Pezzoli, F.; et al. The health and economic burden of bloodstream infections caused by antimicrobial-susceptible and non-susceptible Enterobacteriaceae and Staphylococcus aureus in European hospitals, 2010 and 2011: A multicentre retrospective cohort study. Eurosurveillance 2016, 21, 30319. [Google Scholar] [CrossRef] [Scilit]
- Desai, U.; Kirson, N.Y.; Guglielmo, A.; Le, H.H.; Spittle, T.; Tseng-Tham, J.; Shawi, M.; Sheehan, J.J. Cost-per-remitter with esketamine nasal spray versus standard of care for treatment-resistant depression. J. Comp. Eff. Res. 2021, 10, 393–407. [Google Scholar] [CrossRef] [Scilit]
- Touat, M.; Opatowski, M.; Brun-Buisson, C.; Cosker, K.; Guillemot, D.; Salomon, J.; Tuppin, P.; de Lagasnerie, G.; Watier, L. A Payer Perspective of the Hospital Inpatient Additional Care Costs of Antimicrobial Resistance in France: A Matched Case-Control Study. Appl. Health Econ. Health Policy 2019, 17, 381–389. [Google Scholar] [CrossRef] [Scilit]
- van Rijt, A.M.; Dik, J.H.; Lokate, M.; Postma, M.J.; Friedrich, A.W. Cost analysis of outbreaks with Methicillin-resistant Staphylococcus aureus (MRSA) in Dutch long-term care facilities (LTCF). PLoS ONE 2018, 13, e0208092. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vasudevan, A.; Memon, B.I.; Mukhopadhyay, A.; Li, J.; Tambyah, P.A. The costs of nosocomial resistant gram negative intensive care unit infections among patients with the systemic inflammatory response syndrome- a propensity matched case control study. Antimicrob. Resist. Infect. Control 2015, 4, 3. [Google Scholar] [CrossRef] [Scilit]
- Labreche, M.J.; Lee, G.C.; Attridge, R.T.; Mortensen, E.M.; Koeller, J.; Du, L.C.; Nyren, N.R.; Treviño, L.B.; Treviño, S.B.; Peña, J.; et al. Treatment failure and costs in patients with methicillin-resistant Staphylococcus aureus (MRSA) skin and soft tissue infections: A South Texas Ambulatory Research Network (STARNet) study. J. Am. Board. Fam. Med. 2013, 26, 508–517. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahmoudi, L.; Sepasian, A.; Firouzabadi, D.; Akbari, A. The Impact of an Antibiotic Stewardship Program on the Consumption of Specific Antimicrobials and Their Cost Burden: A Hospital-wide Intervention. Risk Manag. Healthc. Policy 2020, 13, 1701–1709. [Google Scholar] [CrossRef] [Scilit]
- Roberts, T.; Luangasanatip, N.; Ling, C.L.; Hopkins, J.; Jaksuwan, R.; Lubell, Y.; Vongsouvath, M.; van Doorn, H.R.; Ashley, E.A.; Turner, P. Antimicrobial resistance detection in Southeast Asian hospitals is critically important from both patient and societal perspectives, but what is its cost? PLoS Glob. Public Health 2021, 1, e0000018. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.; Shrestha, R.; Koju, P.; Maharjan, B.; Shah, P.; Thapa, P.; Li, H. The direct medical economic burden of healthcare-associated infections and antimicrobial resistance: A preliminary study in a teaching hospital of Nepal. J. Glob. Antimicrob. Resist. 2022, 29, 299–303. [Google Scholar] [CrossRef] [Scilit]
- Janis, J.E.; Hatef, D.A.; Reece, E.M.; Wong, C. Does empiric antibiotic therapy change MRSA [corrected] hand infection outcomes? Cost analysis of a randomized prospective trial in a county hospital. Plast. Reconstr. Surg. 2014, 133, 511e–518e. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ng, E.; Earnest, A.; Lye, D.C.; Ling, M.L.; Ding, Y.; Hsu, L.Y. The Excess Financial Burden of Multidrug Resistance in Severe Gram-negative Infections in Singaporean Hospitals. Ann. Acad. Med. Singap. 2012, 41, 189–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szukis, H.; Joshi, K.; Huang, A.; Amos, T.B.; Wang, L.; Benson, C.J. Economic burden of treatment-resistant depression among veterans in the United States. Curr. Med. Res. Opin. 2021, 37, 1393–1401. [Google Scholar] [CrossRef] [Scilit]
- Patel, D.A.; Patel, D.; Michel, A.; Weber, B.; Petrik, C.; Charbonneau, C. An economic model to compare linezolid and vancomycin for the treatment of confirmed methicillin-resistant Staphylococcus aureus nosocomial pneumonia in Germany. Infect. Drug Resist. 2014, 7, 273–280. [Google Scholar] [CrossRef] [Scilit]
- van Wely, M.; Bayram, N.; van der Veen, F.; Bossuyt, P.M. An economic comparison of a laparoscopic electrocautery strategy and ovulation induction with recombinant FSH in women with clomiphene citrate-resistant polycystic ovary syndrome. Hum. Reprod. 2004, 19, 1741–1745. [Google Scholar] [CrossRef] [Scilit]
- Zhen, X.; Lundborg, C.S.; Sun, X.; Zhu, N.; Gu, S.; Dong, H. Economic burden of antibiotic resistance in China: A national level estimate for inpatients. Antimicrob. Resist. Infect. Control 2021, 10, 5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhen, X.; Lundborg, C.S.; Sun, X.; Hu, X.; Dong, H. Clinical and Economic Impact of Third-Generation Cephalosporin-Resistant Infection or Colonization Caused by Escherichia coli and Klebsiella pneumoniae: A Multicenter Study in China. Int. J. Environ. Res. Public Health 2020, 17, 9285. [Google Scholar] [CrossRef] [Scilit]
- Kritsotakis, E.I.; Kontopidou, F.; Astrinaki, E.; Roumbelaki, M.; Ioannidou, E.; Gikas, A. Prevalence, incidence burden, and clinical impact of healthcare-associated infections and antimicrobial resistance: A national prevalent cohort study in acute care hospitals in Greece. Infect. Drug Resist. 2017, 10, 317–328. [Google Scholar] [CrossRef] [Scilit]
- Tsuzuki, S.; Matsunaga, N.; Yahara, K.; Shibayama, K.; Sugai, M.; Ohmagari, N. Disease burden of bloodstream infections caused by antimicrobial-resistant bacteria: A population-level study, Japan, 2015–2018. Int. J. Infect. Dis. 2021, 108, 119–124. [Google Scholar] [CrossRef] [Scilit]
- Wozniak, T.M.; Dyda, A.; Merlo, G.; Hall, L. Disease burden, associated mortality and economic impact of antimicrobial resistant infections in Australia. Lancet Reg. Health West. Pac. 2022, 27, 100521. [Google Scholar] [CrossRef] [Scilit]
- Le, T.P.; Miller, L.G. Empirical Therapy for Uncomplicated Urinary Tract Infections in an Era of Increasing Antimicrobial Resistance: A Decision and Cost Analysis. Clin. Infect. Dis. 2001, 33, 615–621. [Google Scholar] [CrossRef] [Scilit]
- Cassini, A.; Högberg, L.D.; Plachouras, D.; Quattrocchi, A.; Hoxha, A.; Simonsen, G.S.; Colomb-Cotinat, M.; Kretzschmar, M.E.; Devleesschauwer, B.; Cecchini, M.; et al. Attributable deaths and disability-adjusted life-years caused by infections with antibiotic-resistant bacteria in the EU and the European Economic Area in 2015: A population-level modelling analysis. Lancet Infect. Dis. 2019, 19, 56–66. [Google Scholar] [CrossRef] [Scilit]
- Puzniak, L.A.; Gillespie, K.N.; Leet, T.; Kollef, M.; Mundy, L.M. A Cost-Benefit Analysis of Gown Use in Controlling Vancomycin-Resistant Enterococcus Transmission: Is It Worth the Price? Infect. Control Hosp. Epidemiol. 2004, 25, 418–424. [Google Scholar] [CrossRef] [Scilit]
- Simoens, S.; Ophals, E.; Schuermans, A. Search and destroy policy for methicillin-resistant Staphylococcus aureus: Cost-benefit analysis. J. Adv. Nurs. 2009, 65, 1853–1859. [Google Scholar] [CrossRef] [Scilit]
- Varon-Vega, F.A.; Lemos, E.; Castaño, G.N.; Reyes, J. Cost-utility analysis of ceftazidime-avibactam versus colistin-meropenem in the treatment of infections due to Carbapenem-resistant Klebsiella pneumoniae in Colombia. Expert. Rev. Pharmacoecon Outcomes Res. 2022, 22, 235–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, G.J.; Pan, S.-C.; Foo, J.; Morel, C.; Chen, W.-T.; Wang, J.-T. Comparing ceftolozane/tazobactam versus piperacillin/tazobactam as empiric therapy for complicated urinary tract infection in Taiwan: A cost-utility model focusing on gram-negative bacteria. J. Microbiol. Immunol. Infect. 2019, 52, 807–815. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Farquhar, C.M.; Williamson, K.; Brown, P.M.; Garland, J. An economic evaluation of laparoscopic ovarian diathermy versus gonadotrophin therapy for women with clomiphene citrate resistant polycystic ovary syndrome. Hum. Reprod. 2004, 19, 1110–1115. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Antibiotic Resistance: Why Vaccination Is Important. 2016. Available online: https://www.who.int/news-room/questions-and-answers/item/antibiotic-resistance-why-vaccination-is-important (accessed on 5 March 2024).
- The University of Oxford. Global Antibiotic Consumption Rates Increased by 46 Percent Since 2000. 2021. Available online: https://www.ox.ac.uk/news/2021-11-16-global-antibiotic-consumption-rates-increased-46-percent-2000 (accessed on 5 March 2024).
- Mallah, N.; Orsini, N.; Figueiras, A.; Takkouche, B. Income level and antibiotic misuse: A systematic review and dose–response meta-analysis. Eur. J. Health Econ. 2022, 23, 1015–1035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ndihokubwayo, J.B.; Yahaya, A.A.; Dest, A.T.; Ki-Zerbo, G.; Odei, E.M.; Keita, B.; Pana, A.P.; Nkhoma, W. Antimicrobial resistance in the African Region: Issues, challenges and actions proposed. In Key determinants for Health in the African Region; Regional Office of Africa, World Health Organization: Brazzaville, Congo, 2013. [Google Scholar]
- World Health Organization. WHO Ethiopia Hosts a High-Level Summit on Appropriate Use of Antimicrobials in Africa. 2023. Available online: https://www.afro.who.int/countries/ethiopia/news/who-ethiopia-hosts-high-level-summit-appropriate-use-antimicrobials-africa (accessed on 4 March 2024).
- World Health Organization: Regional Office for Africa. Antimicrobial Resistance in the WHO African Region: A Systematic Literature Review. 2021. Available online: https://www.afro.who.int/sites/default/files/2021-11/Antimicrobial%20Resistance%20in%20the%20WHO%20African%20region%20a%20systematic%20literature%20review.pdf (accessed on 15 September 2025).
- World Health Organization: Regional Office for Africa. African Health Ministers Mobilize Against Dangerous Threat of Antimicrobial Resistance. 2023. Available online: https://www.afro.who.int/news/african-health-ministers-mobilize-against-dangerous-threat-antimicrobial-resistance (accessed on 10 March 2024).
- Chereau, F.; Opatowski, L.; Tourdjman, M.; Vong, S. Risk assessment for antibiotic resistance in South East Asia. BMJ 2017, 358, j3393. [Google Scholar] [CrossRef] [Scilit]
- Talaat, M.; Tolba, S.; Abdou, E.; Sarhan, M.; Gomaa, M.; Hutin, Y.J.-F. Over-Prescription and Overuse of Antimicrobials in the Eastern Mediterranean Region: The Urgent Need for Antimicrobial Stewardship Programs with Access, Watch, and Reserve Adoption. Antibiotics 2022, 11, 1773. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. One Health. n.d. Available online: https://www.who.int/health-topics/one-health#tab=tab_1 (accessed on 7 March 2024).
- McCubbin, K.D.; Anholt, R.M.; de Jong, E.; Ida, J.A.; Nóbrega, D.B.; Kastelic, J.P.; Conly, J.M.; Götte, M.; McAllister, T.A.; Orsel, K.; et al. Knowledge Gaps in the Understanding of Antimicrobial Resistance in Canada. Front. Public Health 2021, 20, 726484. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Community-Based Health Care, Including Outreach and Campaigns, in the Context of the COVID-19 Pandemic-Interim Guidance. 2020. Available online: https://www.who.int/publications/i/item/WHO-2019-nCoV-Comm_health_care-2020.1 (accessed on 6 March 2024).
- Altman, D.G.; Bland, J.M. Uncertainty and sampling error. BMJ 2014, 349, g7064. [Google Scholar] [CrossRef] [Scilit]
- Nikolopoulou, K. What Is Generalizability? Definition & Examples. 2022. Available online: https://www.scribbr.com/research-bias/generalizability/ (accessed on 3 May 2024).
- Bafeta, A.; Dechartres, A.; Trinquart, L.; Yavchitz, A.; Boutron, I.; Ravaud, P. Impact of single centre status on estimates of intervention effects in trials with continuous outcomes: Meta-epidemiological study. BMJ 2012, 344, e813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walker, S.G.; Carr, J.E. Generality of Findings from Single-Case Designs: It’s Not All About the “N”. Behav. Anal. Pract. 2021, 14, 991–995. [Google Scholar] [CrossRef] [Scilit]
- Kamper, S.J. Generalizability: Linking Evidence to Practice. J. Orthop. Sports Phys. Ther. 2020, 50, 45–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eisend, M.; Kuss, A. Generalizability of Research Results. In Research Methodology in Marketing; Springer: Berlin/Heidelberg, Germany, 2019. [Google Scholar]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Rao, N.; Jacobs, S.; Joyce, L. Cost-Effective Eradication of an Outbreak of Methicillin-Resistant Staphylococcus aureus in a Community Teaching Hospital. Infect. Control Hosp. Epidemiol. 1988, 9, 255–260. [Google Scholar] [CrossRef]
- Wang, G.; Liu, Y.; Qiu, P.; Xu, L.; Wen, P.; Wen, J.; Xiao, X.; Zhou, S.-F. Cost-effectiveness analysis of lamivudine, telbivudine, and entecavir in treatment of chronic hepatitis B with adefovir dipivoxil resistance. Drug Des. Dev. Ther. 2015, 9, 2839–2846. [Google Scholar] [CrossRef] [Scilit]
- Barbieri, M.; Wong, J.B.; Drummond, M. The Cost Effectiveness of Infliximab for Severe Treatment-Resistant Rheumatoid Arthritis in the UK. Pharmacoeconomics 2005, 23, 607–618. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhavnani, S.M.; Prakhya, A.; Hammel, J.P.; Ambrose, P.G. Cost-Effectiveness of daptomycin versus vancomycin and gentamicin for patients with methicillin-resistant Staphylococcus aureus bacteremia and/or endocarditis. Clin. Infect. Dis. 2009, 49, 691–698. [Google Scholar] [CrossRef] [Scilit]
- Lowery, W.J.; Lowery, A.W.; Barnett, J.C.; Lopez-Acevedo, M.; Lee, P.S.; Secord, A.A.; Havrilesky, L. Cost-effectiveness of early palliative care intervention in recurrent platinum-resistant ovarian cancer. Gynecol. Oncol. 2013, 130, 426–430. [Google Scholar] [CrossRef] [Scilit]
- Chappell, N.P.; Miller, C.R.; Fielden, A.D.; Barnett, J.C. Is FDA-Approved Bevacizumab Cost-Effective When Included in the Treatment of Platinum-Resistant Recurrent Ovarian Cancer? J. Oncol. Pract. 2016, 12, e775-83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Girgis, N.I.; Sultan, Y.; Hammad, O.; Farid, Z. Comparission of the efficacy, safety and cost of cefixime, ceftriaxone and aztreonam in the treatment of multidrug-resistant Salmonella typhi septicemia in children. Pediatr. Infect. Dis. J. 1995, 14, 603–605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nahuis, M.J.; Lohuis, E.O.; Kose, N.; Bayram, N.; Hompes, P.; Oosterhuis, G.J.E.; Kaaijk, E.M.; Cohlen, B.J.; Bossuyt, P.P.M.; van der Veen, F.; et al. Long-term follow-up of laparoscopic electrocautery of the ovaries versus ovulation induction with recombinant FSH in clomiphene citrate-resistant women with polycystic ovary syndrome: An economic evaluation. Hum. Reprod. 2012, 27, 3577–3582. [Google Scholar] [CrossRef] [Scilit]
- Young, L.S.; Sabel, A.L.; Price, C.S. Epidemiologic, clinical, and economic evaluation of an outbreak of clonal multidrug-resistant Acinetobacter baumannii infection in a surgical intensive care unit. Infect. Control Hosp. Epidemiol. 2007, 28, 1247–1254. [Google Scholar] [CrossRef] [Scilit]
- Lester, R.; Mango, J.; Mallewa, J.; Jewell, C.P.; Lalloo, D.A.; Feasey, N.A.; Maheswaran, H. Individual and population level costs and health-related quality of life outcomes of third-generation cephalosporin resistant bloodstream infection in Blantyre, Malawi. PLOS Glob. Public Health 2023, 3, e0001589. [Google Scholar] [CrossRef] [Scilit]
- Lu, E.Y.; Chen, H.-H.; Zhao, H.; Ozawa, S. Health and economic impact of the pneumococcal conjugate vaccine in hindering antimicrobial resistance in China. Proc. Natl. Acad. Sci. USA 2021, 118, e2004933118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Imai, S.; Inoue, N.; Nagai, H. Economic and clinical burden from carbapenem-resistant bacterial infections and factors contributing: A retrospective study using electronic medical records in Japan. BMC Infect. Dis. 2022, 22, 581. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).