


Abstract
Background/Objectives: Postoperative analgesia is important for reducing biologically invasive reactions to surgery. In Japan, postoperative analgesia, including indices of analgesia, has not been adequately addressed. This study aimed to determine the relationship between postoperative pain and postoperative course and the importance of analgesia for early recovery. Methods: Patients who underwent any of seven surgical procedures in gastrointestinal, thoracic, and cardiac surgery were enrolled. The primary endpoint was a median Prince Henry Pain Scale score from postoperative days 1 to 3. Secondary endpoints were the quality of recovery on postoperative day 7 (Quality of Recovery-15 [QoR-15]) and the length of postoperative hospital stay. Results: Median postoperative pain levels among surgeries were 3 on day 1, 2 on days 2 and 3, 1 on day 7, and 1 at discharge. In both univariate and multivariate analyses, the use of postoperative epidural analgesia and intravenous patient-controlled analgesia (IV-PCA) were significant predictors of early postoperative pain. Only early postoperative pain was a significant predictor of QoR-15 score. Regular use of acetaminophen, early postoperative pain, no appetite, and postoperative complications were significant in affecting the length of postoperative hospital stay. In the comparison of early postoperative pain according to whether epidural analgesia and IV-PCA were used, the group that used both methods had the least pain. Conclusions: In Japan, early postoperative pain persists after major surgical procedures and affects postoperative quality of recovery and length of hospital stay. The use of epidural analgesia, IV-PCA, or both appeared to be effective in overcoming early postoperative pain, thereby enhancing early postoperative recovery.
1. Introduction
The Enhanced Recovery After Surgery (ERAS®) protocol developed in Northern Europe [1] will soon be implemented globally as a standardized approach for perioperative management [2,3,4]. However, simply adding this protocol to daily clinical practice will not guarantee success. Surgical staff must give careful consideration to post-surgical metabolic fluctuations in patients. Above all, perioperative management must be acceptable to the patient. In response to challenges in implementing ERAS, the Japanese Society for Surgical Metabolism and Nutrition (JSSMN) developed the Essential Strategy for Early Normalization after Surgery with Patient’s Excellent Satisfaction (ESSENSE) program in 2012 [5]. ESSENSE and ERAS have similar goals, but ESSENSE offers a more contextually appropriate approach for Japan, based on four key concepts: (1) the modulation of biological responses to surgical insults; (2) the early restoration of physical activity; (3) the early recovery of normal nutritional intake; and (4) the mitigation of perioperative anxiety and encouragement of enhancement of the motivation to recover. The ESSENSE program has been introduced across several types of gastroenterological surgery in Japan [5], and despite initial challenges, has been adopted in many institutions [6,7]. When used in specific gastroenterological surgeries, it aims to eliminate unnecessary and potentially harmful conventional perioperative management practices, reduce postoperative pain, and promote rapid recovery of daily activities and return to work. Achieving these goals requires pain management to serve as an essential link connecting the objectives of the ESSENSE protocol. Postoperative analgesia is an important measure to reduce biologically invasive reactions to surgery, thereby supporting the other elements of the protocol and enhancing early recovery [8]. We hypothesized that a well-structured postoperative pain management strategy, particularly for early postoperative pain, will contribute significantly to both the quality and speed of patient recovery. However, in Japan, postoperative analgesia, including indices of analgesia, has not yet been adequately addressed. As part of the ESSENSE project aimed at early postoperative recovery, the JSSMN conducted a multi-institutional prospective observational study to evaluate postoperative analgesia methods and changes in pain after various surgical procedures. In this clinical study, we aimed to examine the relationship between the degree of postoperative pain and the postoperative course and to clarify the significance of analgesia for early postoperative recovery.
2. Materials and Methods
2.1. Population
This was a multi-institutional, prospective, observational study conducted from January 2021 to December 2023. The subjects were patients who underwent gastrointestinal, thoracic, and cardiac surgery. The following surgical procedures were included in gastrointestinal surgery: (1) Esophagectomy, (2) Total gastrectomy and gastrectomy, (3) Colectomy and rectal resection, (4) Hepatectomy, (5) Pancreaticoduodenectomy. Pulmonary resection was included in thoracic surgery. The following surgical procedures were included in cardiac surgery: (1) Cardiothoracic large vessel surgery (valvular disease, ischemic heart disease, thoracic aortic surgery, congenital, etc.), (2) Abdominal large vessel surgery (aortic aneurysm, arteriosclerosis obliterans, etc.).
The inclusion criteria were as follows: (1) Patients of any gender, (2) Patients who provided their own voluntary consent after receiving and understanding a full explanation of the study, and (3) Patients treated at facilities that are members of the council of the JSSMN that perform more than 30 surgeries of the same category per year within the defined categories.
The exclusion criteria were as follows: (1) Patients undergoing surgical procedures not listed in the inclusion criteria, (2) Patients treated at facilities that did not meet the qualification standards (performing fewer than 30 surgeries of the same category per year), and (3) Patients who did not provide voluntary informed consent to participate.
The number of participating cases was about 500 in total from facilities that were members of the council of JSSMN and agreed to participate.
2.2. Outcomes
The primary endpoint was the median Prince Henry Pain Scale score [9,10,11] from postoperative days 1 to 3. The Prince Henry Pain Scale was used to assess pain and was divided into five stages: 0: No pain when coughing, 1: Pain when coughing, but not when taking a deep breath, 2: Pain when taking a deep breath, but no pain at rest, 3: Pain at rest, but no painkillers needed, 4: Pain at rest, and painkillers needed. The Prince Henry Pain Scale is an activity-based pain assessment scale that is well-suited for evaluating postoperative patients and adjusting analgesic dosing, especially for those who need to resume activities early as part of the ERAS protocol. Pain assessments were conducted on the 1st, 2nd, 3rd, and 7th days after surgery and at the time of discharge. Pain was defined as the worst pain, including at the drain insertion site, and the worst pain on any given day was recorded through patient interview. Physicians at each facility explained the differences between these stages before and after surgery so that they were understood by the patients.
Secondary endpoints were quality of postoperative recovery on the 7th day after surgery (Quality of Recovery-15 [QoR-15]) [12,13] and length of postoperative hospital stay (days).
The survey items were as follows: (1) patient information, (2) method of general anesthesia, (3) postoperative analgesic measures, (4) other evaluation items that directly or indirectly impact postoperative recovery or serve as indicators of the recovery process, including time to start eating, degree of appetite and ambulation, presence or absence of postoperative complications, presence or absence of postoperative nausea/vomiting within 2 days after surgery, presence or absence of postoperative intestinal paralysis from the 3rd day after surgery onwards, length of postoperative hospital stay, time of first flatus, time of first defecation, and perioperative measurements of total lymphocyte count, neutrophil count, serum albumin, and serum C-reactive protein (CRP) levels. Postoperative complications were defined as those of Clavien–Dindo classification grade III or higher [14]. The study protocol was approved by the institutional ethics committee of Kansai Medical University (reference number: KMU 2021102). Ethics applications were also submitted and approved at each participating institution. Informed consent for this study was obtained from each participating institution.
2.3. Statistical Analysis
Quantitative variables were expressed as medians (interquartile ranges), and qualitative variables were expressed as frequencies and percentages. Correlations between the Prince Henry Pain Scale score, QoR-15 score, length of postoperative hospital stay, and clinical factors were evaluated using Spearman’s rank correlation coefficient. Comparisons of qualitative clinical factors related to the Prince Henry Pain Scale score, QoR-15 score, and length of postoperative hospital stay were performed using the Wilcoxon rank sum test. In addition, the Prince Henry Pain Scale score, QoR-15 score, and length of postoperative hospital stay were dichotomized at the median, and associated risk factors were examined using univariate and multivariate logistic regression analyses. Group comparisons of clinical characteristics selected from the multivariate analysis were performed using the Wilcoxon rank sum test, while the Steel–Dwass test was used for multiple comparisons. p values less than 0.05 were considered significant. All data analyses were conducted using the R statistical package (version 4.3.3, R Foundation for Statistical Computing, Vienna, Austria).
3. Results
3.1. Patient Background for Seven Organ Surgeries
A total of 593 patients underwent surgery on one of seven organs, and 25 facilities participated in this study (Table 1). The median age was 72, and there were more males than females in each organ surgery group. There were no surgeries for malignant tumors in the cardiovascular surgery group. Of the 593 total surgeries, 366 were laparoscopic, thoracoscopic, or robot-assisted surgeries.
Table 1.
Patient background for seven organ surgeries.
3.2. Changes in Postoperative Pain Following Seven Organ Surgeries
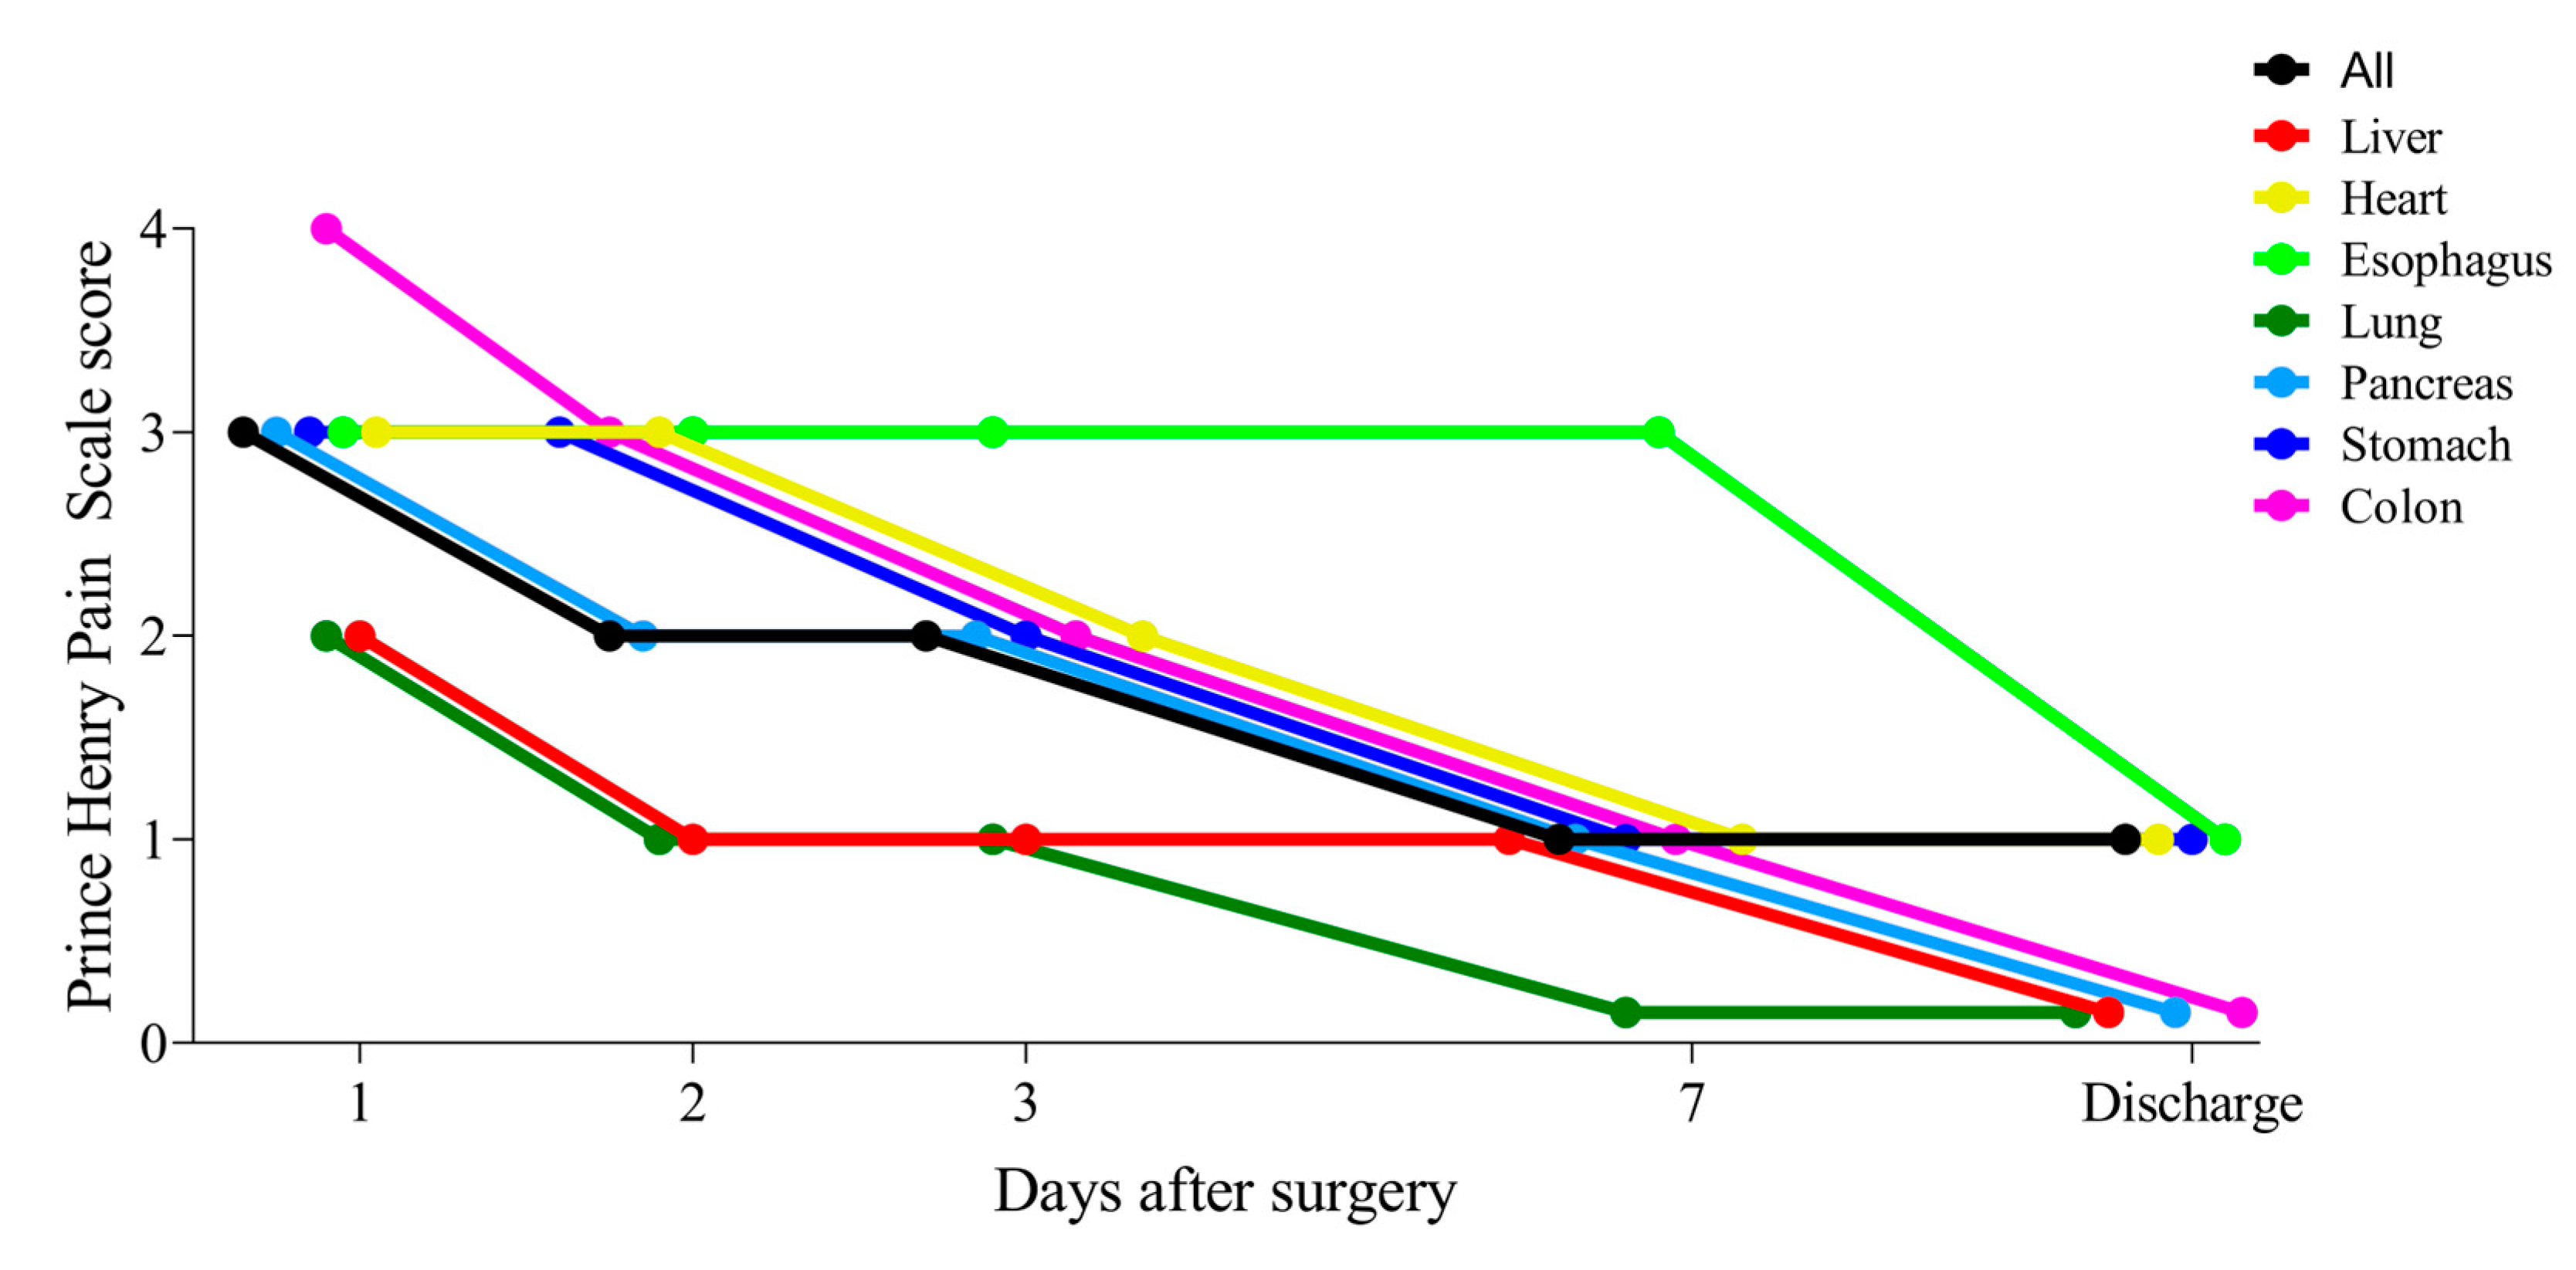
The median (interquartile range) postoperative pain level according to the Prince Henry Pain Scale score in the seven organ surgeries was as follows: 3 (2–4) on the first day, 2 (1–3) on the second day; 2 (1–3) on the third day; 1 (1–1) on the seventh day; and 1 (0–1) at the time of discharge (Figure 1). The postoperative hospital stay in seven organ surgeries was 11 (8–15) days. The pain intensity was highest during the first three postoperative days and gradually decreased by the seventh day, with nearly minimal levels at discharge across all surgical groups. Pain after colon surgery was severe on the first postoperative day, but from the second postoperative day onwards, it showed a similar progression to heart, esophagus, pancreas, and stomach surgeries. In contrast, pain after lung and liver surgeries was relatively low up to the third postoperative day.
Figure 1.
Changes in postoperative pain following seven organ surgeries. Postoperative pain level was assessed using the Prince Henry Pain Scale score on postoperative days 1, 2, 3, 7, and at discharge, with five levels: 0: No pain when coughing, 1: Pain when coughing, but not when taking a deep breath, 2: Pain when taking a deep breath, but no pain at rest, 3: Pain at rest, but no painkillers needed, 4: Pain at rest, and painkillers needed.
3.3. Correlations Between Clinical Factors and the Three Endpoints
Factors strongly correlated with the median pain level on postoperative days 1–3 were food intake ratio throughout the entire postoperative course, QoR-15 score on the 7th day after surgery, postoperative hospital stay, and perioperative neutrophil count (Table 2). The following eight factors were strongly correlated with the QoR-15 score on the seventh postoperative day: amount of blood loss during surgery, operation time, length of wound, pain on postoperative days 1–3, food intake ratio and five-level appetite throughout the entire postoperative course, postoperative hospital stay, and perioperative neutrophil count. The following 13 factors were strongly correlated with postoperative hospital stay: blood loss during surgery, operation time, length of wound, urinary volume during surgery, pain on postoperative days 1–3, onset of eating, food intake ratio, five-level appetite and 10 levels of bed exit throughout the entire postoperative course, QoR-15 score on postoperative day 7, and perioperative neutrophil count, and serum albumin and CRP levels.
Table 2.
Correlations between Prince Henry Pain Scale score, QoR-15 score, postoperative hospital stay, and clinical factors a.
3.4. Comparison of Clinical Factors on the Three Endpoints
When comparing clinical factors on the Prince Henry Pain Scale score, QoR-15 score, and postoperative hospital stay, significant differences were found on all three endpoints: American Society of Anesthesiologists Physical Status (ASA-PS) classification (I, II, and III), the presence or absence of intestinal paralysis, and the presence or absence of postoperative epidural analgesia (Table 3).
Table 3.
Comparison of effects of clinical factors on the Prince Henry Pain Scale score, QoR-15 score, and postoperative hospital stay a.
3.5. Univariate and Multivariate Logistic Regression Analyses of Risk Factors for the Three Endpoints
Results of the logistic regression analysis examining risk factors for Prince Henry Pain Scale score are presented in Table 4A. The use of postoperative epidural analgesia and IV-PCA were identified as significant predictors in both the univariate and multivariate analyses. Regarding the investigation of risk factors for the QoR-15 score (Table 4B), only a Prince Henry Pain Scale score ≥ 2.33 was identified as a significant predictor in both the univariate and multivariate analyses. The following four factors were found to be significant in affecting the length of postoperative hospital stay: regular use of acetaminophen, Prince Henry Pain Scale score ≥ 2.33, Five levels of appetite ≥ 2.75, and the occurrence of postoperative complications (Table 4C).
Table 4.
Univariate and multivariate logistic regression analyses of risk factors for Prince Henry Pain Scale score, QoR-15 score, and postoperative hospital stay in various organ surgeries.
3.6. Effects of Risk Factors Selected from Multivariate Analyses on Each Endpoint
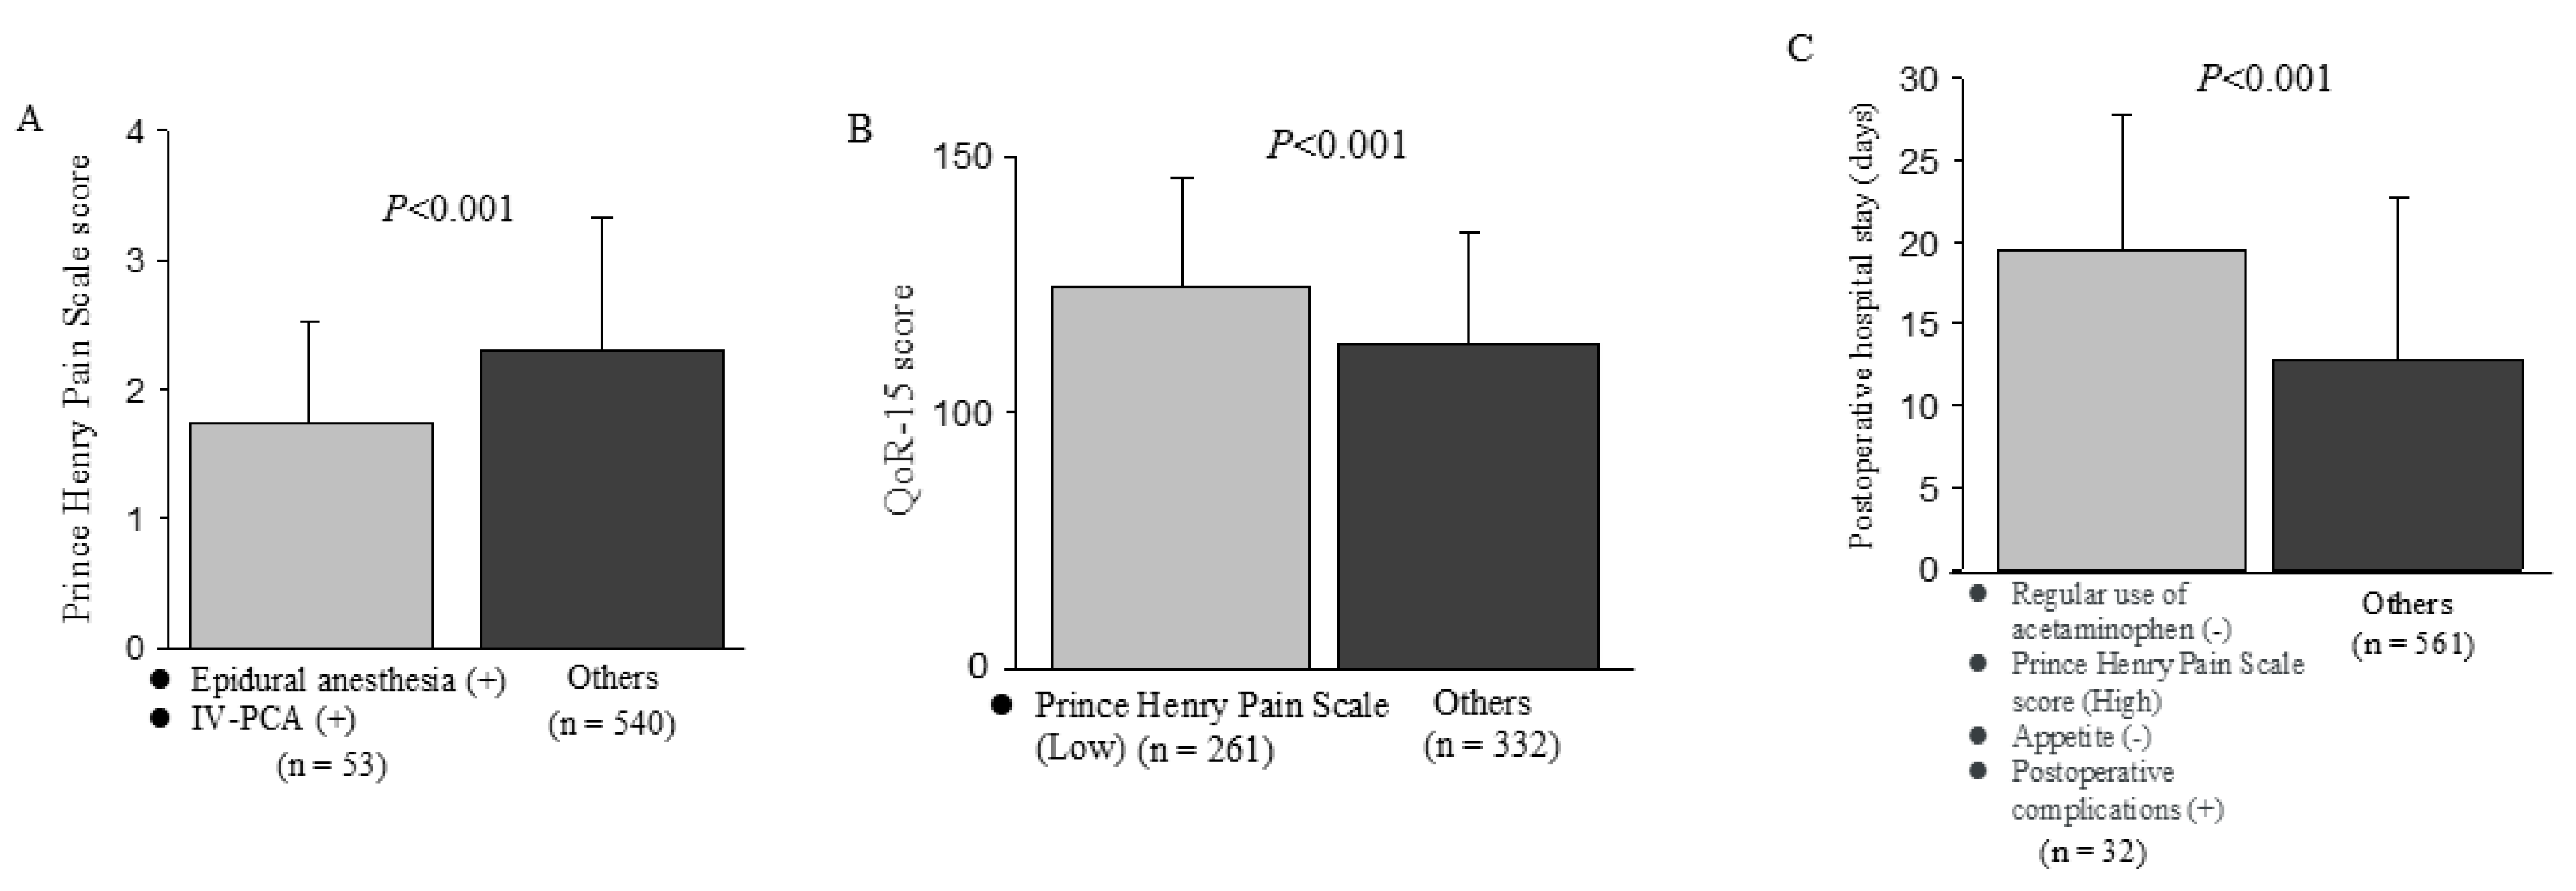
Patients who received both epidural analgesia and IV-PCA after surgery had significantly less early postoperative pain than those who did not (Figure 2A). The group with low early postoperative pain showed higher QoR-15 scores on the seventh day after surgery compared with the other groups (Figure 2B). The 32 patients who did not take acetaminophen regularly had early postoperative pain and no appetite after surgery, and developed postoperative complications had a significantly longer hospital stay than the other 561 patients (Figure 2C).
Figure 2.
Effects of risk factors selected from multivariate analyses on each endpoint: (A) Prince-Henry Pain Scale score, (B) QOR-15 score, (C) Postoperative hospital stay. p values were calculated using the Wilcoxon rank sum test.
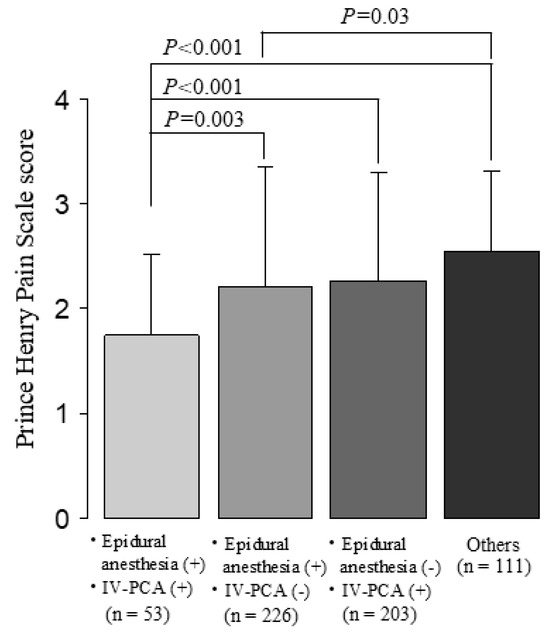
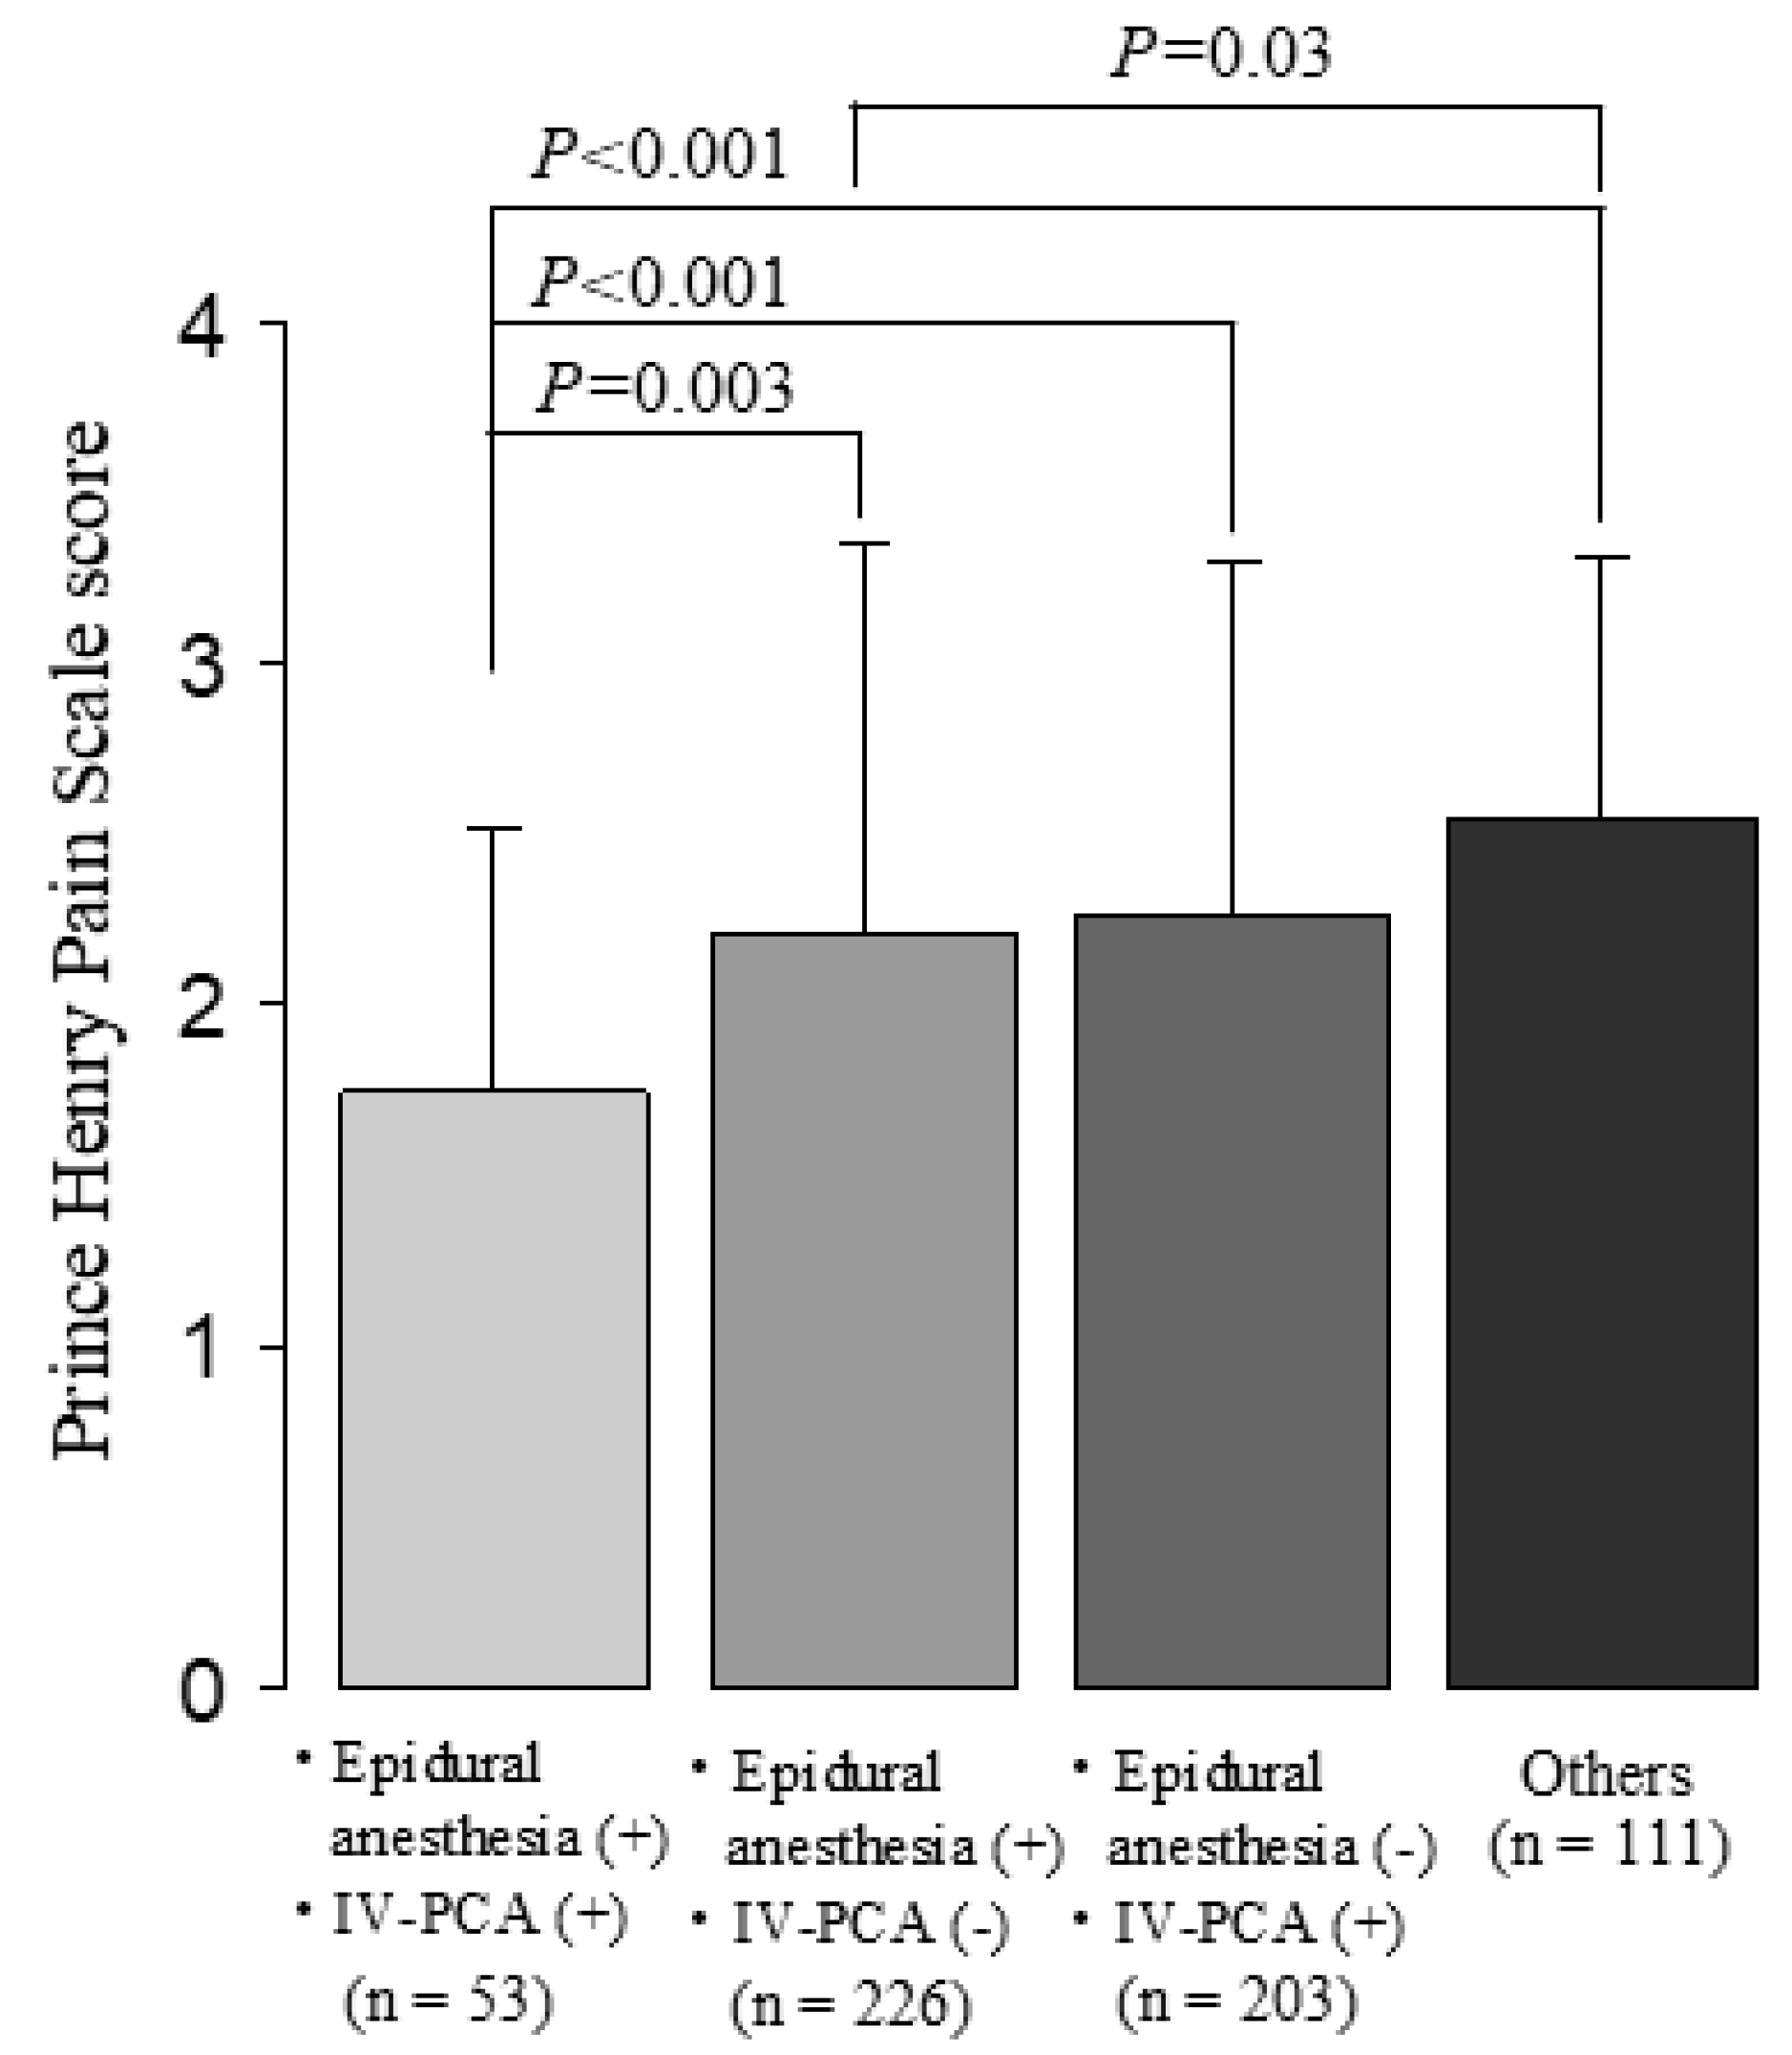
We investigated the degree of early postoperative pain according to whether postoperative epidural analgesia and/or IV-PCA were used. The group using both methods had the least amount of pain in the early postoperative period, while the group not using either method had the most severe pain (Figure 3). These 53 patients who were provided with both epidural analgesia and IV-PCA had the most reduced early postoperative pain. Both methods are not generally used at the same time, and it is presumed that IV-PCA was initiated as a support when the effect of epidural anesthesia was insufficient. In the group not using either method, 64 of 111 patients used acetaminophen alone, 39 used acetaminophens in combination with NSAIDs, and 8 used NSAIDs alone.
Figure 3.
Degree of early postoperative pain with or without postoperative epidural anesthesia and/or IV-PCA. The table below shows the number of patients who used epidural analgesia and/or IV-PCA for each organ surgery. IV-PCA; intravenous patient-controlled analgesia. p values were calculated using the Steel–Dwass test for multiple comparisons.
4. Discussion
The four core concepts of ESSENSE, the Japanese version of ERAS, are the following: (1) the modulation of biological responses to surgical insults; (2) the early restoration of physical activity; (3) the early recovery of normal nutritional intake; and (4) the mitigation of perioperative anxiety and encouragement of enhancement of the motivation to recover [5]. The underlying element “modulation of biological responses to surgical insults” informs the other elements, all of which are directed toward quick postoperative recovery. The most important and central item among these four concepts is the suppression and prevention of postoperative pain. In other words, if the patient’s pain is suppressed, it is assumed that they will be able to walk, have an appetite, eat better, have bowel movements, and feel more positive [8]. In our study, we investigated perioperative outcomes focusing on postoperative pain at representative facilities for various surgeries in Japan. This highlighted the fact that postoperative pain in various surgeries still occurs frequently in the early postoperative period (Figure 1), a situation that has not been overcome with our perioperative management. It was found that the use of epidural analgesia, IV-PCA, or both, was effective in suppressing this early postoperative pain (Figure 3). On the other hand, early postoperative pain significantly affected patients’ satisfaction with their hospital stay in the first week after surgery and their length of postoperative hospital stay (Table 4). QOR-15, an indicator of postoperative patient satisfaction, is a sensitive reflection of the patient’s postoperative condition and correlates with the occurrence of postoperative complications, making it an important screening tool for observing the “quality” of the postoperative course [13]. In our study, Table 2 shows the correlations between the Prince Henry Pain Scale score, QoR-15 score, postoperative hospital stays, and clinical factors. Among these, the factor that most influenced QOR-15 was early postoperative pain, highlighting that effective pain management strategies can significantly improve recovery quality. This conclusion is further supported by the finding that a Prince Henry Pain Scale score ≥ 2.33 was identified as a significant predictor in both the univariate and multivariate analyses (Table 4B). Correlations between QoR-15 scores and surgical variables, including operative blood loss, operation time, and length of wound, indicate that use of perioperative management strategies, such as minimizing blood loss and optimizing surgical techniques, could enhance recovery quality. In addition, shortening the postoperative hospital stay by achieving early recovery is an important issue in hospital management in terms of increasing the efficiency of bed utilization. Japan has a system where all citizens can receive medical insurance, which is different from the insurance systems in the U.S. and Europe. This study revealed that to shorten postoperative hospital stay, it is important to reduce early postoperative pain, that regular administration of acetaminophen and/or NSAIDs after surgery is recommended [15,16,17], that these efforts increase appetite, and early mobilization, and, naturally, that the occurrence of postoperative complications is decreased.
The results of our study suggest that because early postoperative pain is clearly present, it will be important to provide more thorough postoperative pain management in the near future to ensure early postoperative recovery. Pain and anxiety are two of the most common factors influencing recovery from surgery [18]. When inappropriately treated, pain can cause immunosuppression, tachycardia, increased oxygen consumption, and increased catecholamine production [19]. To hasten discharge and recovery, postoperative treatments should minimize physiological and psychological stress [20]. Postoperative analgesia has been reported to be a key contributor to the postoperative management of patients who have undergone gastrointestinal surgery in ERAS programs [21]. Epidural analgesia and IV-PCA are key strategies for perioperative management of patients who undergo abdominal surgery, especially surgeries involving an upper abdominal incision [22,23]. Epidural analgesia has been recognized for many years to be superior to intravenous opioid analgesia, as it provides better pain relief at movement and early intestinal movement, and it is associated with a lower incidence of postoperative pulmonary complications [22,23]. However, the results of recent clinical studies using multimodal analgesia consisting of regional anesthesia, non-opioid analgesics, and opioids have called this superiority into question [24,25,26]. Epidural analgesia will be replaced by multimodal analgesia using peripheral regional analgesia, non-opioids, and rescue opioids for laparoscopic surgery and lower laparotomy. However, its clinical utility will not wane for pain relief after major upper abdominal laparotomy. On the other hand, IV-PCA has the advantage that the administration route is easy to establish, and it can be used in cases where epidural analgesia is not applicable. However, compared to epidural analgesia, it has disadvantages such as inferior analgesic effect during body movement, high incidence of respiratory complications, and slow recovery of gastrointestinal motility [27,28,29,30,31]. In addition, if analgesia is achieved only with IV-PCA with opioids, the side effects of the opioids may hinder postoperative recovery [30,31]. Therefore, when using IV-PCA, it is necessary to devise a method to enhance the analgesic effect while avoiding the adverse effects of opioids by combining it with other analgesic methods, multimodal analgesia. Figure 2A and Figure 3 show that the combination of epidural analgesia and IV-PCA as multimodal analgesia provided pain relief superior to that obtained with either method alone. This combination was not initially implemented; instead, IV-PCA was added in cases where epidural analgesia alone was insufficient. This addition offers the advantage of rapid onset and broader pain coverage, which may improve efficacy. Although this combination improved pain relief, careful consideration must be given to the potential side effects associated with increased opioid doses. A recent clinical trial showed that combining short-term thoracic epidural analgesia with IV-PCA on the first two postoperative days and applying IV-PCA alone on the two subsequent days resulted in superior pain relief compared to thoracic epidural analgesia alone, with no significant increase in opioid-related side effects [32].
The present study has some limitations. (1) Limited case numbers per surgical procedure: the small sample size for each procedure suggests that additional data per technique would improve the clinical relevance of findings. Analyzing postoperative pain for each surgical method independently might provide greater insight. An increased number of cases for each procedure, adoption of a standardized pain management protocol, and pain assessments for individual procedures are warranted in future studies. (2) It is necessary to clarify the rationale for selecting cases in which epidural analgesia or IV-PCA was administered, as well as the impact of the analgesic drug doses of each method on the level of pain. In the present study, it was presumed that anesthesiologists at each institution followed their own institution’s practice. (3) The Prince Henry Pain Scale was used in this study. It is suitable for evaluating postoperative pain related to physical activity; however, it is less commonly used than the Numeric Rating Scale. This limits its comparability with other studies. In addition, this scale offers only five levels and does not consider the psychological or emotional aspects of pain, making it less sensitive for comprehensive pain assessment, especially in studies that require higher-resolution data. To address this, other pain assessments should have been performed simultaneously, as this scale may not be sufficient to capture comprehensive pain results.
5. Conclusions
It was clear that early postoperative pain persists after major surgical procedures in Japan. Early postoperative pain affected the postoperative quality of recovery and length of hospital stay. The use of epidural analgesia, IV-PCA, or both appeared to be effective in overcoming early postoperative pain, thereby enhancing early postoperative recovery.
Author Contributions
Conceptualization, M.K., Y.N. (Yoshihiro Nabey), K.F. and G.M.; methodology, M.K. and H.M.; investigation, M.K.; resources, M.K.; data curation, T.T.L., W.T., R.I., Y.M., K.K., M.A., K.T. (Keitaro Tanaka), H.S., T.Y., T.M., Y.H., R.M., K.T. (Kazuhiro Takehara), S.K., I.Y., N.W., H.T., Y.K., N.I., Y.A., N.H., T.H., T.S., T.K. (Takashi Kamei), H.O., Y.N. (Yuichi Nagakawa), C.T., T.K. (Takayuki Kohri) and K.M.; writing—original draft preparation, M.K.; writing—review and editing, M.K., K.Y., T.T.L., H.M., W.T., R.I., Y.M., K.K., M.A., K.T. (Keitaro Tanaka), H.S., T.Y., T.M., Y.H., R.M., K.T. (Kazuhiro Takehara), S.K., I.Y., N.W., H.T., Y.K., N.I., Y.A., N.H., T.H., T.S., T.K. (Takashi Kamei), H.O., Y.N. (Yuichi Nagakawa), C.T., T.K. (Takayuki Kohri), K.M., Y.N. (Yoshihiro Nabey), K.F. and G.M.; visualization, M.K. and K.Y.; Formal analysis, K.Y.; project administration, M.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study protocol was approved by the institutional ethics committee of Kansai Medical University on 12 December 2022 (reference number: KMU 2021102). Informed consent for this study was obtained at each institution. After receiving official approval, this study was conducted as a prospective analysis of database records based on the Guidelines for Clinical Research issued by the Ministry of Health and Welfare of Japan. All procedures were performed in accordance with the Declaration of Helsinki. The data were made anonymous before analysis to protect patient privacy.
Informed Consent Statement
All patients provided written informed consent to participate in this study.
Data Availability Statement
Due to the nature of this research, participants in this study could not be contacted regarding whether the findings could be shared publicly; thus, supporting data are not available. The datasets generated and/or analyzed for the current study are not publicly available due to the nature of the research, as noted above. Further enquiries can be directed to the corresponding author.
Conflicts of Interest
None of the authors have a potential conflict of interest to declare.
Abbreviations
The following abbreviations are used in this manuscript:
| ERAS | Enhanced Recovery After Surgery |
| ESSENSE | Essential Strategy for Early Normalization after Surgery with Patient’s Excellent satisfaction |
| JSSMN | Japanese Society for Surgical Metabolism and Nutrition |
| QoR-15 | Quality of Recovery-15 |
| CRP | C-reactive Protein |
| ASA-PS | American Society of Anesthesiologists Physical Status |
| IV-PCA | Intravenous Patient-Controlled Analgesia |
References
- Fearon, K.C.H.; Ljungqvist, O.; Von Meyenfeldt, M.; Revhaug, A.; Dejong, C.H.C.; Lassen, K.; Nygren, J.; Hausel, J.; Soop, M.; Andersen, J.; et al. Enhanced Recovery after Surgery: A Consensus Review of Clinical Care for Patients Undergoing Colonic Resection. Clin. Nutr. 2005, 24, 466–477. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weimann, A.; Braga, M.; Carli, F.; Higashiguchi, T.; Hübner, M.; Klek, S.; Laviano, A.; Ljungqvist, O.; Lobo, D.N.; Martindale, R.; et al. ESPEN Guideline: Clinical Nutrition in Surgery. Clin. Nutr. 2017, 36, 623–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Visioni, A.; Shah, R.; Gabriel, E.; Attwood, K.; Kukar, M.; Nurkin, S. Enhanced Recovery After Surgery for Noncolorectal Surgery?: A Systematic Review and Meta-Analysis of Major Abdominal Surgery. Ann. Surg. 2018, 267, 57. [Google Scholar] [CrossRef] [Scilit]
- Makaryus, R.; Miller, T.E.; Gan, T.J. Current Concepts of Fluid Management in Enhanced Recovery Pathways. Br. J. Anaesth. 2018, 120, 376–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaibori, M.; Miyata, G.; Yoshii, K.; Fukushima, R. Perioperative Management for Gastrointestinal Surgery after Instituting Interventions Initiated by the Japanese Society of Surgical Metabolism and Nutrition. Asian J. Surg. 2020, 43, 124–129. [Google Scholar] [CrossRef] [Scilit]
- Yamagata, Y.; Yoshikawa, T.; Yura, M.; Otsuki, S.; Morita, S.; Katai, H.; Nishida, T. Current Status of the “Enhanced Recovery after Surgery” Program in Gastric Cancer Surgery. Ann. Gastroenterol. Surg. 2019, 3, 231–238. [Google Scholar] [CrossRef] [Scilit]
- Taniguchi, H.; Sasaki, T.; Fujita, H.; Kobayashi, H.; Kawasaki, R.; Goloubev, M.; Ishikawa, T.; Takano, O.; Ogata, T.; Cho, H.; et al. Modified ERAS Protocol Using Preoperative Oral Rehydration Therapy: Outcomes and Issues. J. Anesth. 2014, 28, 143–147. [Google Scholar] [CrossRef] [Scilit]
- Kehlet, H. Postoperative pain, analgesia, and recovery—Bedfellows that cannot be ignored. Pain 2018, 159, S11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doi, K.; Yamanaka, M.; Shono, A.; Fukuda, N.; Saito, Y. Preoperative Epidural Fentanyl Reduces Postoperative Pain after Upper Abdominal Surgery. J. Anesth. 2007, 21, 439–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamashita, S.; Yokouchi, T.; Tanaka, M. Effects of Intraoperative High-Dose vs Low-Dose Remifentanil for Postoperative Epidural Analgesia after Gynecological Abdominal Surgery: A Randomized Clinical Trial. J. Clin. Anesth. 2016, 32, 153–158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, M.; Shi, J.; Gao, T.; Shen, J.; Zhao, C.; Xi, F.; Li, W.; Li, Q.; Yu, W. The Addition of Dexmedetomidine to Analgesia for Patients After Abdominal Operations: A Prospective Randomized Clinical Trial. World J. Surg. 2017, 41, 39–46. [Google Scholar] [CrossRef] [Scilit]
- Stark, P.A.; Myles, P.S.; Burke, J.A. Development and Psychometric Evaluation of a Postoperative Quality of Recovery Score: The QoR-15. Anesthesiology 2013, 118, 1332–1340. [Google Scholar] [CrossRef] [Scilit]
- Campfort, M.; Cayla, C.; Lasocki, S.; Rineau, E.; Léger, M. Early Quality of Recovery According to QoR-15 Score Is Associated with One-Month Postoperative Complications after Elective Surgery. J. Clin. Anesth. 2022, 78, 110638. [Google Scholar] [CrossRef] [Scilit]
- Clavien, P.A.; Barkun, J.; de Oliveira, M.L.; Vauthey, J.N.; Dindo, D.; Schulick, R.D.; de Santibañes, E.; Pekolj, J.; Slankamenac, K.; Bassi, C.; et al. The Clavien-Dindo Classification of Surgical Complications: Five-Year Experience. Ann. Surg. 2009, 250, 187–196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buvanendran, A.; Kroin, J.S. Multimodal Analgesia for Controlling Acute Postoperative Pain. Curr. Opin. Anesthesiol. 2009, 22, 588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chou, R.; Gordon, D.B.; de Leon-Casasola, O.A.; Rosenberg, J.M.; Bickler, S.; Brennan, T.; Carter, T.; Cassidy, C.L.; Chittenden, E.H.; Degenhardt, E.; et al. Management of Postoperative Pain: A Clinical Practice Guideline From the American Pain Society, the American Society of Regional Anesthesia and Pain Medicine, and the American Society of Anesthesiologists’ Committee on Regional Anesthesia, Executive Committee, and Administrative Council. J. Pain 2016, 17, 131–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American Society of Anesthesiologists Task Force on Acute Pain Management. Practice Guidelines for Acute Pain Management in the Perioperative Setting: An Updated Report by the American Society of Anesthesiologists Task Force on Acute Pain Management. Anesthesiology 2012, 116, 248–273. [Google Scholar] [CrossRef] [Scilit]
- Sinatra, R. Causes and Consequences of Inadequate Management of Acute Pain. Pain Med. 2010, 11, 1859–1871. [Google Scholar] [CrossRef] [Scilit]
- Guo, T.Z.; Jiang, J.Y.; Buttermann, A.E.; Maze, M. Dexmedetomidine Injection into the Locus Ceruleus Produces Antinociception. Anesthesiology 1996, 84, 873–881. [Google Scholar] [CrossRef] [Scilit]
- Meiser, A.; Sirtl, C.; Bellgardt, M.; Lohmann, S.; Garthoff, A.; Kaiser, J.; Hügler, P.; Laubenthal, H.J. Desflurane Compared with Propofol for Postoperative Sedation in the Intensive Care Unit. Br. J. Anaesth. 2003, 90, 273–280. [Google Scholar] [CrossRef] [Scilit]
- Gustafsson, U.O.; Scott, M.J.; Schwenk, W.; Demartines, N.; Roulin, D.; Francis, N.; McNaught, C.E.; Macfie, J.; Liberman, A.S.; Soop, M.; et al. Guidelines for Perioperative Care in Elective Colonic Surgery: Enhanced Recovery After Surgery (ERAS(®)) Society Recommendations. World J. Surg. 2013, 37, 259–284. [Google Scholar] [CrossRef] [Scilit]
- Hughes, M.; Yim, I.; Deans, D.A.C.; Couper, G.W.; Lamb, P.J.; Skipworth, R.J.E. Systematic Review and Meta-Analysis of Epidural Analgesia Versus Different Analgesic Regimes Following Oesophagogastric Resection. World J. Surg. 2018, 42, 1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, W.; Li, Y.; Huang, Q.; Ye, S.; Rong, T. Short and Long-Term Outcomes of Epidural or Intravenous Analgesia after Esophagectomy: A Propensity-Matched Cohort Study. PLoS ONE 2016, 11, e0154380. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hausken, J.; Fretland, Å.A.; Edwin, B.; Andersen, M.H.; Dagenborg, V.J.; Bjørnelv, G.M.W.; Kristiansen, R.; Røysland, K.; Kvarstein, G.; Tønnessen, T.I. Intravenous Patient-Controlled Analgesia Versus Thoracic Epidural Analgesia After Open Liver Surgery: A Prospective, Randomized, Controlled, Noninferiority Trial. Ann. Surg. 2019, 270, 193. [Google Scholar] [CrossRef] [Scilit]
- Pirrera, B.; Alagna, V.; Lucchi, A.; Berti, P.; Gabbianelli, C.; Martorelli, G.; Mozzoni, L.; Ruggeri, F.; Ingardia, A.; Nardi, G.; et al. Transversus Abdominis Plane (TAP) Block versus Thoracic Epidural Analgesia (TEA) in Laparoscopic Colon Surgery in the ERAS Program. Surg. Endosc. 2018, 32, 376–382. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sondekoppam, R.V.; Uppal, V.; Brookes, J.; Ganapathy, S. Bilateral Thoracic Paravertebral Blocks Compared to Thoracic Epidural Analgesia After Midline Laparotomy: A Pragmatic Noninferiority Clinical Trial. Anesth. Analg. 2019, 129, 855. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hübner, M.; Blanc, C.; Roulin, D.; Winiker, M.; Gander, S.; Demartines, N. Randomized Clinical Trial on Epidural Versus Patient-Controlled Analgesia for Laparoscopic Colorectal Surgery Within an Enhanced Recovery Pathway. Ann. Surg. 2015, 261, 648. [Google Scholar] [CrossRef] [Scilit]
- Mann, C.; Pouzeratte, Y.; Boccara, G.; Peccoux, C.; Vergne, C.; Brunat, G.; Domergue, J.; Millat, B.; Colson, P. Comparison of Intravenous or Epidural Patient-Controlled Analgesia in the Elderly after Major Abdominal Surgery. Anesthesiology 2000, 92, 433–441. [Google Scholar] [CrossRef] [Scilit]
- Ferguson, S.E.; Malhotra, T.; Seshan, V.E.; Levine, D.A.; Sonoda, Y.; Chi, D.S.; Barakat, R.R.; Abu-Rustum, N.R. A Prospective Randomized Trial Comparing Patient-Controlled Epidural Analgesia to Patient-Controlled Intravenous Analgesia on Postoperative Pain Control and Recovery after Major Open Gynecologic Cancer Surgery. Gynecol. Oncol. 2009, 114, 111–116. [Google Scholar] [CrossRef] [Scilit]
- Nishimori, M.; Low, J.H.; Zheng, H.; Ballantyne, J.C. Epidural Pain Relief versus Systemic Opioid-based Pain Relief for Abdominal Aortic Surgery—Nishimori, M—2012|Cochrane Library. Cochrane Database Syst. Rev. 2016, CD005059. [Google Scholar] [CrossRef] [Scilit]
- Jørgensen, H.; Wetterslev, J.; Møiniche, S.; Dahl, J.B. Epidural Local Anaesthetics versus Opioid-Based Analgesic Regimens on Postoperative Gastrointestinal Paralysis, PONV and Pain after Abdominal Surgery. Cochrane Database Syst. Rev. 2000, CD001893. [Google Scholar] [CrossRef] [Scilit]
- Xu, W.; Li, Y.; Li, N.; Sun, Y.; Wang, C.; An, K. Combination of Thoracic Epidural Analgesia with Patient-Controlled Intravenous Analgesia versus Traditional Thoracic Epidural Analgesia for Postoperative Analgesia and Early Recovery of Laparotomy: A Prospective Single-Centre, Randomized Controlled Trial. BMC Anesthesiol. 2022, 22, 341. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).