


Abstract
Post-operative atrial fibrillation (POAF) is the most common arrhythmia in the post-operative period after cardiac surgery. We aim to investigate the main clinical, local, and/or peripheral biochemical and molecular predictors for POAF in patients undergoing coronary and/or valve surgery. Between August 2020 and September 2022, consecutive patients undergoing cardiac surgery without previous history of AF were studied. Clinical variables, plasma, and biological tissues (epicardial and subcutaneous fat) were obtained before surgery. Pre-operative markers associated with inflammation, adiposity, atrial stretch, and fibrosis were analyzed on peripheral and local samples with multiplex assay and real-time PCR. Univariate and multivariate logistic regression analyses were performed in order to identify the main predictors for POAF. Patients were followed-up until hospital discharge. Out of 123 consecutive patients without prior AF, 43 (34.9%) developed POAF during hospitalization. The main predictors were cardiopulmonary bypass time (odds ratio (OR) 1.008 (95% confidence interval (CI), 1.002–1.013), p = 0.005), and plasma pre-operative orosomucoid levels (OR 1.008 (1.206–5.761). After studying differences regarding sex, orosomucoid was the best predictor for POAF in women (OR 2.639 (95% CI, 1.455–4.788), p = 0.027) but not in men. The results support the pre-operative inflammation pathway as a factor involved in the risk of POAF, mainly in women.
1. Introduction
In the post-operative cardiac surgical setting, new-onset atrial fibrillation (AF) is not a benign entity, as it is known to increase the risk of all-cause mortality, stroke and critical care unit, and overall hospital length of stay. This complication is estimated to occur in nearly one-third of the patients undergoing open heart surgery [1,2]. Some pre-operative and peri-operative strategies were recommended in order to decrease the risk of post-operative atrial fibrillation (POAF) with mixed results [3]. This is the case of pretreatment with drugs (beta blockers, amiodarone), electrolyte infusions, and different anesthetic or surgical techniques (systemic temperature control, coated circuits, posterior pericardiotomy, and off-pump bypass grafting) among others. Meanwhile, other studies focused their attention on the cellular and molecular level, such as modulation of the neutrophils and inflammatory pathways or modulation of the nervous system through botulin toxin on epicardial fat [4,5]. Many triggers and substrates can promote acute AF during procedures and personalized management may be required for reducing its incidence and recurrence [6].
Relevantly, predisposing conditions and long-term management of this arrhythmia may differ between the medical and the surgical patients, as the evidence in the latter is significantly scarcer. Particularities of POAF following cardiac surgery and its differences with other types of AF are not completely clarified yet, but the direct surgical trauma to the heart, inflammation following cardiopulmonary bypass, and increased sympathetic stimuli may be involved [7]. As such, a better understanding of the pathways involved in POAF might help to improve its management.
On top of that, there is a growing interest in the study of internal signaling pathways that can alter tissue homeostasis. Inflammatory and pro-thrombotic response mechanisms, metabolic or hormonal disarrangements, and fibrosis promote ventricular and atrial remodeling. Thus, some circulating markers of atrial strain and function [8], adiposity [9], cytokine-induced stress [10], and inflammation [11] were found to be associated with AF.
The aim of our study was to investigate the association of local and peripheral markers involved in inflammation, strain, adiposity, and fibrosis with the development of POAF in the post-operative period. We studied clinical and echocardiographic parameters, and biochemical and molecular markers on local tissues (subcutaneous and epicardial fat), peripheral cells, and blood.
2. Materials and Methods
2.1. Study Design and Population
This is a prospective, observational, and single-center cohort study conducted at the University Hospital of Santiago de Compostela (a university-affiliated tertiary center in Santiago de Compostela, Spain). Between August 2020 and September 2022, consecutive patients undergoing cardiac surgery (coronary, valve, or mixed surgery) under informed consent were eligible for inclusion. The exclusion criteria were prior open-heart surgery, prior history of AF or severe active infective disease, or cardiogenic shock at hospitalization.
The protocol was approved by Galician Clinical Ethics Committee and followed the Declaration of Helsinki’s rules. As per protocol, all patients undergo routine evaluation before cardiac surgery. This includes a minimum of medical history assessment, clinical examination, electrocardiography, laboratory blood sampling, and echocardiography performed by cardiologists specifically dedicated to cardiac imaging and anesthetic evaluation.
At the operating room, after sternotomy, epicardial and subcutaneous fat biopsies (0.2–0.5 g) were obtained and stored at −80 °C for RNA expression levels. Blood samples into tubes with heparin or EDTA were obtained before starting the surgical procedure.
After the operation, the patients were transferred to the intensive care unit (ICU) for recovery. From there, when deemed suitable, discharged to the standard cardiac surgical ward or cardiology intermediate care unit. Patients were monitored via continuous ECG telemetry while in the intensive or intermediate care unit. Daily 12-lead ECGs were recorded routinely until the day of discharge. Further ECGs could be requested physician in charge if considered necessary as per usual clinical practice. The follow up period for this study finished after hospital discharge.
2.2. Study Primary End-Point
The primary end-point was the development of AF as defined by the European Society of Cardiology guidelines [12] (a cardiac rhythm with the absence of distinct p waves and irregularly irregular RR intervals). This could be documented either in the continuous ECG monitoring, in a 12-lead ECG, or both, depending on whether the patient was under cardiac telemetry or not during the event.
2.3. Clinical, Echocardiography, and Biochemical Variables (Pre- and Peri-Operative)
2.3.1. Clinical Variables
Demographic and anthropometric variables, previous clinical diagnoses, and chronic medications were recorded after medical history taking and reviewing the electronic history records.
2.3.2. Echocardiography
Transthoracic echocardiography was routinely performed during hospitalization (or in the outpatients’ clinic for scheduled procedures) by trained clinicians in a comprehensive way, initially during the pre-operative evaluation and again after heart surgery. Measured parameters included left ventricular dimensions, ejection fraction (as calculated by the international Simpson’s method), left and right atrial dimensions, right ventricular dimensions, contractility (TAPSE, S’), pulmonary pressures, and valvular heart diseases (significant stenosis or regurgitation).
2.3.3. Pre-Operative Clinical Laboratory Variables
Blood cell count, renal and liver function tests, electrolytes, coagulation, and metabolic profile (HbA1C, total cholesterol, and LDL-c), as well as NTproBNP levels, were determined as per routine practice.
2.3.4. Pre-Operative Circulating Blood Biomarkers
Fasting blood samples were collected in EDTA tubes in the operating room before the surgical incision. After being centrifuged at 1800× g for 10 min, plasma was stored at −80 °C. Selected circulating markers of atrial strain (atrial natriuretic peptide), adiposity (fatty acid binding protein (FABP4) and leptin), cytokine-induced stress (growth differentiation factor 15 (GDF15)), complement (C5a), and matrix extracellular (Thrombospondin-2) were analyzed by magnetic Luminex multiplex test kit (R&D Systems, Minneapolis, MN, USA). The manufacturer’s instructions were followed and the plasma was diluted twice.
Alpha1-acid glycoprotein, also known as orosomucoid (ORM), was measured as a marker of inflammatory activity [13]. ORM levels were determined by enzyme-linked immunoassay (ELISA) with a detection limit of 59 ng/mL (SEA816Hu, Cloud Clone). Diluted plasma 1:1000 was used for this determination.
2.3.5. Pre-Operative Neutrophils Migratory Activity
Fasting blood samples were also collected into lithium heparin-coated vacutainers transferred and processed in the laboratory within the first hours. Neutrophils were isolated by single-step centrifugation of whole blood onto Polymorphprep (Proteogenix, Schiltigheim, France) following the manufacturer’s recommendation. Blood was pipetted on Polymorphprep (1:3) and centrifuged at 500× g for 35 min without brake. Granulocytes, mainly neutrophils were carefully taken and resuspended in RPMI 1640 media supplemented with 25 mM HEPES (Lonza Biologics, Porriño, Spain). After washing, the neutrophils number was determined by Scepter™ 2.0 Cell Counter (Millipore®, Merck Life Science S.L.U., Madrid, Spain). Four hundred thousand neutrophils between 9–12 µm were used for migration assays. They were seeded into transwells with 3 µm in size (Merck Life Science S.L.U., Madrid, Spain). Migrated cells were determined after treatment with or without complement component 5a (C5a) at 11 nM for 90 min. Migrated cells were detached with EDTA (0.05M) for 15 min at 4 °C. Afterward, migrated and non-migrated neutrophils were collected and centrifuged at 500× g for 5 min and lysed for DNA quantifying using CyQUANT® GR dye (Thermo Fisher Scientific, Waltham, MA, USA), according to the manufacturer’s protocol. After that, fluorescence that represents also migrated and no migrated neutrophils, was recorded at an excitation/emission wavelength (485/525 nm) with (FLUOstar OPTIMA, BMG Labtech, Allmendgrün, Germany). Results were expressed as a percentage of migrated total cells in relative fluorescence units (RFU) as it was described before [14].
2.3.6. Pre-Operative Neutrophils, Monocytes, Epicardial Fat, and Subcutaneous Fat mRNA Expression Analysis
Isolated neutrophils and monocytes from blood, epicardial fat, and subcutaneous fat biopsies were lysed and RNA was isolated by AllPrep DNA/RNA/Protein Mini Kit (Qiagen, Hilden, Germany). After retro-transcription, using the Maxima First Strand cDNA Synthesis Kit (Thermo Fisher Scientific, Waltham, MA, USA), 1 μL of cDNA was used for amplifying the enzymes (MPO, DEFA3, MPO, NGAL, LF), and adhesion molecules (CXCR2, CD11B, SELL, CXCR4) from neutrophils and monocytes or adiposity (FABP4, CD36), inflammatory cells (CD14, CD16, CD3, CD68), fibroblasts (COL1A2, PREF-1), and myofibroblasts (a-SMA) markers in epicardial and subcutaneous fat as it was previously described [15].
2.3.7. Peri-Operative Clinical Laboratory Variables
Cardiopulmonary bypass (CPB) time during surgery was measured in all patients. After surgery, daily blood tests with blood cell count, renal and liver function tests, electrolytes, and coagulation profiles were obtained. Additionally, and according to the patient’s clinical situation, arterial and mixed venous blood gases could be ordered to measure pH, lactate, and SvO2.
2.3.8. Peri-Operative Clinical Variables
Time on mechanical ventilation, the requirement of vasopressors or inotropes and days of support, length of stay in the ICU, and complications during the hospitalization were recorded.
2.4. Statistical Analysis
Continuous variables were reported as numbers and categorical variables as percentages. To check the normal distribution of variables, Kolmogorov–Smirnov tests were performed. Normal variables are presented as mean ± standard deviation (SD). Scattered variables are represented as interquartile ranges. Differences in continuous variables between patients with and without POAF were determined by the Student’s t-test or Mann–Whitney according to the normality of data. Categorical variables were compared using χ2 test.
Univariate and multivariate logistic regression analyses were performed. We selected EUROSCORE II, CPB duration, and preoperative ORM values as independent variables: EuroSCORE II is a surgical risk model created to predict surgical mortality and is commonly used worldwide as a pre-operative evaluation tool. It includes important clinical, echocardiography, and laboratory parameters and surgical variables. CPB duration and preoperative ORM values are associated with the inflammatory hypothesis, which is being investigated as a contributor to POAF. The left atrial area was not included as differences between both groups were not clinically significant. Finally, some of the biomarkers were not considered appropriate for the multivariate model as their values were not available for all the patients.
Hosmer–Lemeshow test was used for testing the goodness of fit for regression. Cut-off values were determined by the area under the curve (AUC).
All statistical analyses were performed by SPSS Statistics 26 (IBM, Armonk, NY, USA).
3. Results
Overall, 123 consecutive patients with no prior history of AF undergoing heart surgery were included. The general baseline characteristics of the population are described in Table 1. Of note, a significant number of patients were pre-treated with anti-platelet agents, beta-blockers, ACE-I/ARB, and statins. During the post-operative period, 43 patients (34.9%) developed POAF. Details about complications during the peri-operative course are displayed in Table 2.
Table 1.
Baseline characteristics of the overall cohort.
Table 2.
Post-operative course.
Regarding clinical variables between those who developed and those who did not develop POAF, there were statistically significant differences in predicted surgical risk (as in EuroSCORE II), left atrial dimensions, and CPB time during surgery.
Differences in biomarkers were as follows: the local epicardial fat analysis showed higher expression of fatty acid binding protein 4 (FABP4) mRNA levels in those who developed POAF (p < 0.05). These differences were not found in subcutaneous fat biopsies.
Peripheral neutrophils also showed higher expression levels of CD16, a marker of mature neutrophils (p < 0.01) in those patients who developed POAF. There were no changes in its migratory activity. Monocyte transcriptome did not differ between these two groups of patients.
Plasma circulating markers of adiposity, stretch, or fibrosis were not different between patients with and without POAF. However, ORM was higher in those who developed POAF (p < 0.05). Although insulin levels did not reach the statistical difference between patients (p = 0.098), they were also higher in those who suffered POAF. Table 3 shows the differences in terms of clinical variables and biomarkers between patients who developed POAF or not, whereas Table 4 shows the same information specified by sex.
Table 3.
Differences between patients who developed POAF or not.
Table 4.
Sex differences between patients who developed POAF or not.
Our results showed in the univariate and multivariate models that the main risk variables for POAF were CPB and preoperative ORM levels (Table 5).
Table 5.
Logistic regression analyses. (a) Univariate logistic regression analysis. (b) Multivariate logistic regression analysis. (c) Multivariate logistic regression analyses (Women only).
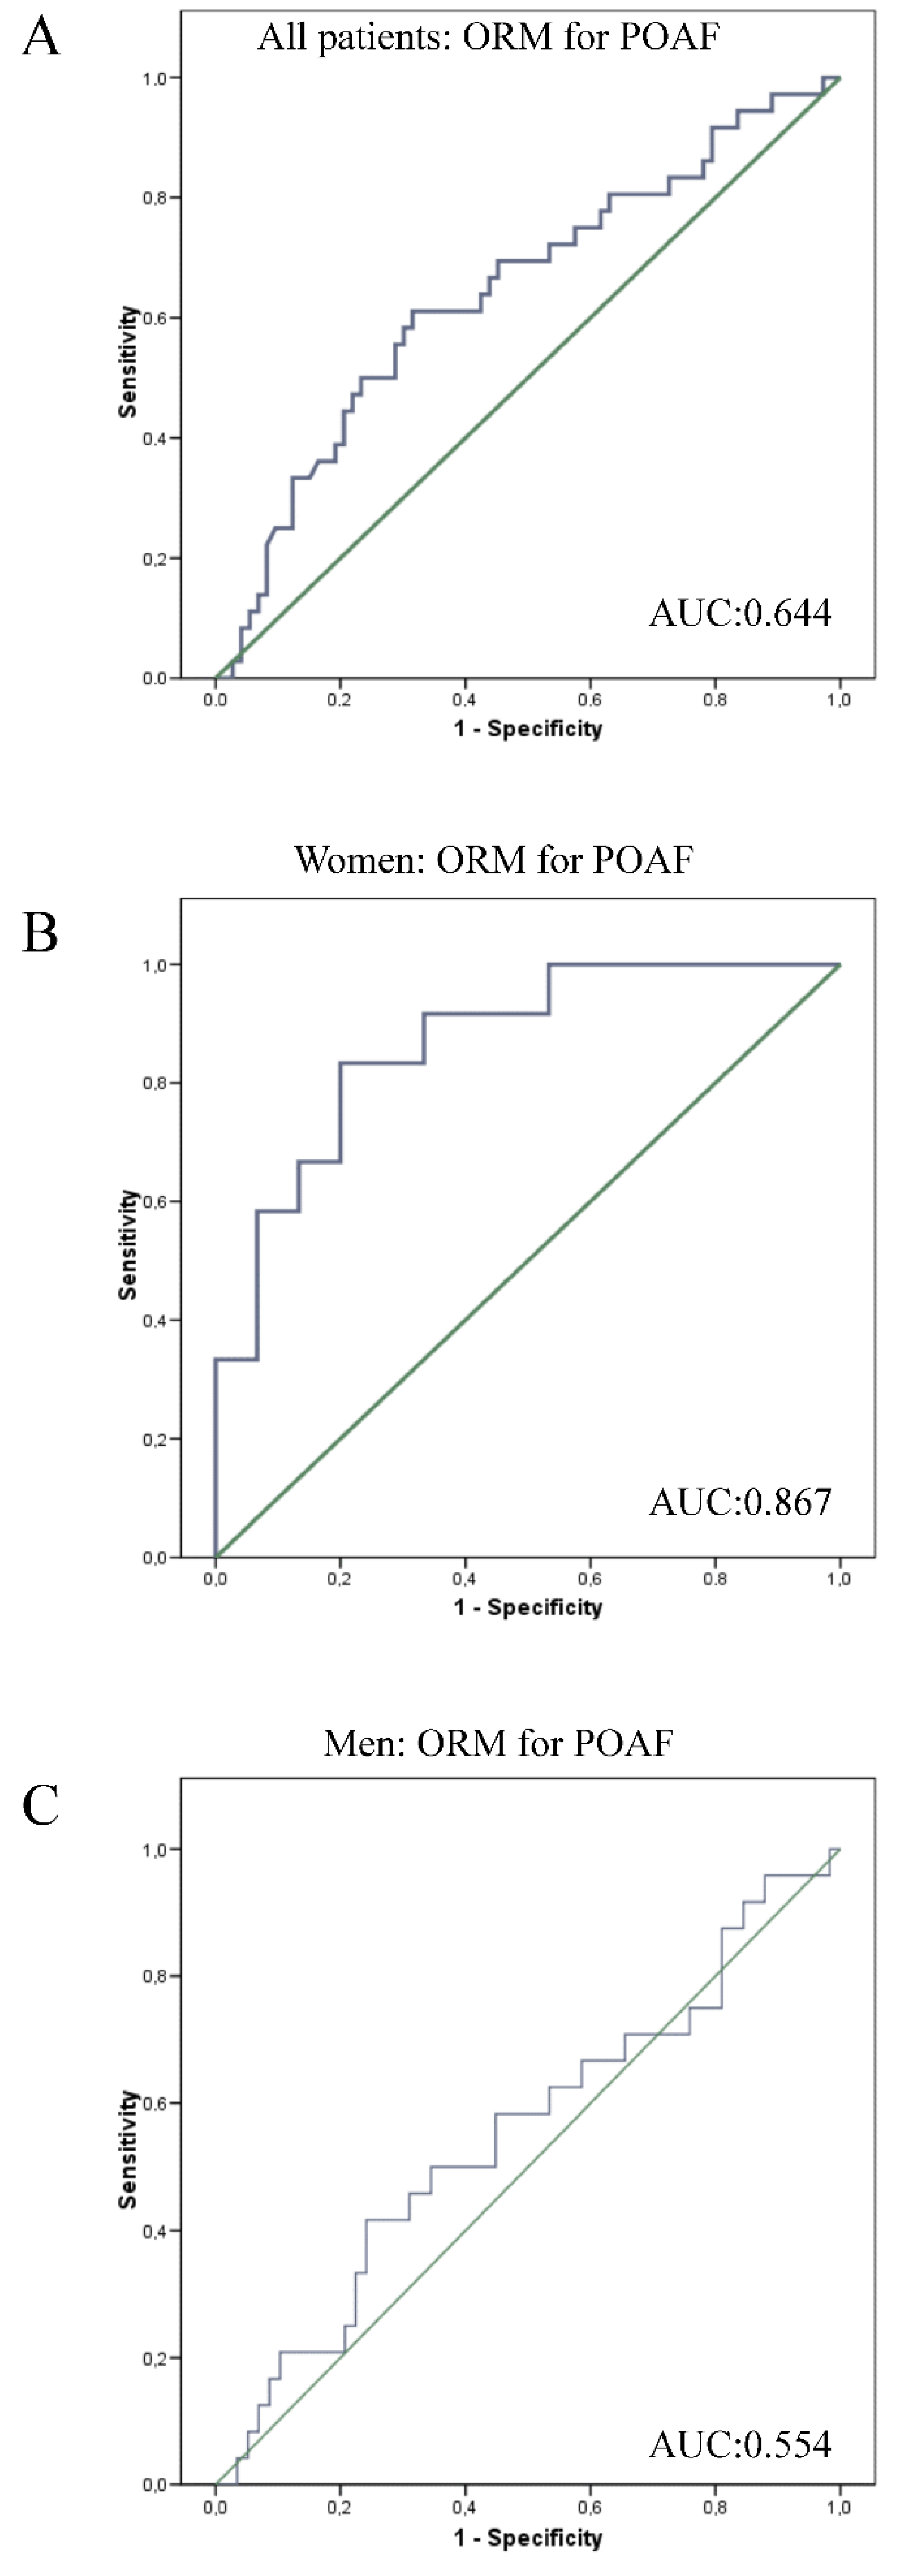
We also performed an area under the curve (AUC) for analyzing the degree of separability between the two groups (with and without POAF) in terms of some of the previously mentioned markers. We found the best AUC for ORM (0.644, 95% CI 0.542–0.756, p = 0.009) (Figure 1A).
Figure 1.
(A). ROC curves, ORM for POAF in all patients. (B). ROC curves, ORM for POAF in women. (C). ROC curves. ORM for POAF in men.
Sexual Dimorphism and Markers
Although the population was limited and the statistical power might be affected, we tried to define the markers for POAF in women and men. Out of 30 female patients, 14 (46.6%) developed POAF as compared to 29 out of 93 (31%) in men. None of the clinical characteristics differed between both groups. Regarding biomarkers, significant differences were observed for circulating (FABP4 and leptin) and epicardial fat adiposity markers (FABP4 and CD36). In women, the main clinical differences between those developing POAF were CPB time and previous admission due to heart failure. ORM plasma levels were also significantly higher whereas the local inflammatory cells on epicardial fat were reduced. AUC for ORM was 0.844 (95% CI 0.668–1.021; p = 0.01) (Figure 1B). Multivariate logistic regression analyses on the female population showed that high ORM was the strongest independent variable for POAF risk (OR 2.639, 95% CI 1.455–4.788, p < 0.05) (Table 5). This was not the case in men where ORM was not associated with POAF occurrence.
4. Discussion
In our cohort of post-operative cardiac surgical patients without previous AF, a significant association was found between the onset of POAF, CPB time, and plasmatic ORM levels measured in the operating theatre before surgical incision. Specifically, the addition of ORM to the predictive model significantly improved the ability to predict POAF during hospitalization after heart surgery. These results could be of help for a better understanding of POAF pathophysiology, adding valuable information to the inflammatory hypothesis, which is particularly associated with cardiac surgery. This information could be of use for the development of future targeted or personalized therapies. Patients with higher inflammatory status at baseline could have a lower threshold for the development of POAF during the post-operative period after cardiac surgery, making them more vulnerable to this condition.
4.1. Clinical and Biomarker Predictors of POAF
Among all the variables studied, advanced age has been one of the most consistent predictors of POAF according to previous data. Aging entails the accumulation of oxidative stress and reactive species leading to a progressive decline in the efficiency of tissues and organs [16]. In the human heart, the atria suffer from changes in their substrate such as alterations affecting the connective tissue, progressive dilatation, and electrical remodeling of atrial myocytes [17].
Several metabolic and humoral pathways are believed to act as intervening factors in the occurrence of AF. Such is the case of the autonomic nervous system, the renin-angiotensin-aldosterone system, and other less acknowledged routes, namely fibrosis or heart strain, and stretching. Nevertheless, pharmacological intervention with beta-blockers, ACE inhibitors, and mineralocorticoid receptor antagonists have been extensively studied for POAF prevention with mixed results [18].
Carbohydrate metabolism has been another intensive area of research for its relationship with AF. Lee et al. found a significant association between insulin resistance and AF risk, regardless of diabetes mellitus [19]. Moreover, in a population of patients with drug-refractory AF episodes who underwent pulmonary vein isolation, it was found to be a predictor of AF recurrence-inducing delays in left atrial conduction [20]. In our study, we could not find an association between insulin levels and POAF development, although higher insulin levels were more frequently found in the POAF group.
Epicardial fat is contemplated as an endocrine organ. Its secretome and differential expression of inflammatory and modulatory proteins was described as a possible substrate of POAF in patients undergoing coronary artery bypass surgery [21]. It has been shown that cholinergic activity can regulate the inflammatory secretome of this tissue [22]. This might explain the POAF reduction rate after botulin toxin injection on the epicardial fat pad from patients with paroxysmal AF found by Romanov et al. [23]. Local inflammatory cell infiltration and higher neutrophil or monocyte migration activity might be part of this mechanism [24]. In our study population, higher levels of adiposity marker (FABP4) were found in epicardial fat from patients who developed POAF. In the same line, our group has demonstrated higher adiposity in the epicardial stroma of patients with long-standing persistent AF [25] and the association of plasmatic FABP4 levels with atrial adiposity and recurrence of AF after catheter ablation.
A strong component of inflammation after cardiac surgery might be likely. Supporting this hypothesis, posterior left pericardiotomy has recently been shown to be effective for the reduction of POAF after coronary, valvular, or aortic surgery [26]. Surgical trauma, blood loss, and transfusion can contribute to the systemic inflammatory response. The beneficial effect of this technique is believed to be related to less mechanical compression and inflammation around the atria as the pericardiotomy allows the evacuation of fluid or thrombi to the left pleural space.
We studied alpha1-acid glycoprotein, also known as ORM. This is an acute-phase protein synthesized in the liver. It is related to a significant number of physiological functions, including binding and transporting molecules in the blood, modulating the immune system, regulating inflammation, and maintaining tissue homeostasis. Its concentration increases in response to tissue injury, infection, or systemic inflammation. This protein has been studied in other cardiac conditions, specifically in acute and chronic heart failure. Higher concentrations of ORM have been linked to worse outcomes in this population, even independently of NT-proBNP levels [27].
Moreover, the CPB is often employed to provide circulatory and respiratory support to the patient’s organs while the surgeons can perform their operation on a bloodless field. CPB induces an ischemia-reperfusion type injury and a complex inflammatory response. This may influence the post-operative course in the form of systemic and local tissue irritation [28], which may be dependent on how long the CPB and cross-clamp times are.
Patients undergoing open heart surgery face the consequences of not only their structural heart disease but also of surgical trauma and peri-operative care. Depending on their baseline inflammatory status, some patients may trigger POAF with insults of lesser intensity than others.
4.2. Clinical Relevance
Our findings complement other studies in the field of biomarkers and cardiac surgery. Although it is still premature for its implementation in routine clinical practice, there are promising data on the usefulness of serum biomarkers as tools for enhanced and personalized POAF risk stratification. We describe for the first time the predictive value of ORM as a risk factor for the development of POAF. This might have important implications for a better understanding of the physiopathology surrounding the inflammatory hypothesis, which is believed to have an important role in the field of cardiac surgery. ORM was not a predictor of POAF in this subset of male patients. However, those who developed POAF and those who did not have similar levels of ORM were physiological. We cannot rule out its additive predictive value in those patients with higher, and pathological levels, as we demonstrated in women. A larger study would help us to clarify this point.
Moreover, the results of the present study could also be of help for a tailored follow-up of patients at higher risk. Potentially, this subgroup of patients may benefit from preventive strategies such as pharmacological interventions that blunt the sympathetic response after cardiac surgery (preoperative prescription of anti-arrhythmic drugs or beta-blockers) or bi-atrial temporary pacing, which is believed to suppress automatic foci and reduce the dispersion of atrial refractory periods [29,30].
5. Limitations
The observational nature of the study may be subject to inherent bias. We included a small number of patients. Nevertheless, it is comparable to other studies performed in this setting, especially including some biomarkers. Although it was performed in a single center, several surgeons and anesthetists participated in the surgical process, so it is possible that some differences in the surgical technique or anesthetist regimes could have existed. Importantly, as patients are not under continuous ECG monitoring at the time of discharge to the surgical ward, exists the possibility that asymptomatic or subclinical episodes of AF (especially paroxysmal) might have been missed and therefore not included in our analyses. Nevertheless, all patients undergo daily ECG plus vital signs assessment up to at least three times per day.
Our study included a mixed population of patients with coronary and valvular heart disease. While valvular patients with extensive pre-operative structural changes were a minority (those requiring mitral intervention), we acknowledge that the specific characteristics of our patient population may limit the generalizability of our findings.
Although we studied other biomarkers and some of them were statistically significant in the univariate regression analysis, we finally did not include them in the multivariate model. This would have reduced significantly the number of subjects used to generate the regression model and therefore compromised the statistical significance of the rest of the predictor variables. Adipocyte and leukocyte biomarkers are less accessible and more costly than plasmatic biomarkers and they were not available for all patients, nevertheless, we consider that they could be of interest for further mechanistic studies.
6. Conclusions
In cardiac surgical patients, higher ORM at the moment of the surgical procedure was an independent risk factor for the development of POAF and its addition to EuroSCORE II and CPB time showed a significant improvement in risk stratification.
Author Contributions
Conceptualization, D.I.-Á., M.R.-M. and S.E.; methodology, M.R.-M., X.F. and S.E.; writing—original draft preparation, D.I.-Á.; writing—review and editing, J.M.M.-C., S.V.-D.R., S.S.-C., M.V.R.-M., M.E.-M., A.M.-S., L.R.-L., S.S., J.G.-C., Á.L.F.-G., B.A.-N., S.E., M.R.-M., M.T.-M., R.M.A.-B. and J.R.G.-J.; tissue and blood sample collection: J.M.M.-C., S.V.-D.R., S.S.-C., M.V.R.-M., M.E.-M., A.M.-S., L.R.-L., S.S., J.G.-C., Á.L.F.-G. and B.A.-N. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by Fondo de Investigaciones Sanitarias (PI16/01282 and PI19/01330) from Plan Estatal de I+D+I and cofounded by ISCIII-Subdirección general de evaluación y fomento de la investigación del fondo europeo de desarrollo regional (FEDER), Grupos de potencial crecemento, Xunta de Galicia (IN607B 2022/04). X.F. has a predoctoral PFIS fellowship by ISCIII-Subdirección general de evaluación y fomento de la investigación del fondo europeo de desarrollo regional (FEDER).
Informed Consent Statement
The patients of this study provided informed written consent for the publication of their study data.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author, upon reasonable request.
Conflicts of Interest
The authors declare no conflict of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
References
- Eikelboom, R.; Sanjanwala, R.; Le, M.-L.; Yamashita, M.H.; Arora, R.C. Postoperative Atrial Fibrillation After Cardiac Surgery: A Systematic Review and Meta-Analysis. Ann. Thorac. Surg. 2021, 111, 544–554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, M.-H.; Kamel, H.; Singer, D.E.; Wu, Y.-L.; Lee, M.; Ovbiagele, B. Perioperative/Postoperative Atrial Fibrillation and Risk of Subsequent Stroke and/or Mortality. Stroke 2019, 50, 1364–1371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Creswell, L.L.; Alexander, J.C.; Ferguson, T.B.; Lisbon, A.; Fleisher, L.A. Intraoperative Interventions. Chest 2005, 128, 28S–35S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chyou, J.Y.; Barkoudah, E.; Dukes, J.W.; Goldstein, L.B.; Joglar, J.A.; Lee, A.M.; Lubitz, S.A.; Marill, K.A.; Sneed, K.B.; Streur, M.M.; et al. Atrial Fibrillation Occurring During Acute Hospitalization: A Scientific Statement from the American Heart Association. Circulation 2023, 147, e676–e698. [Google Scholar] [CrossRef] [Scilit]
- Gaudino, M.; Di Franco, A.; Rong, L.Q.; Piccini, J.; Mack, M. Postoperative atrial fibrillation: From mechanisms to treatment. Eur. Heart J. 2023, 44, 1020–1039. [Google Scholar] [CrossRef] [Scilit]
- Abdelmoneim, S.S.; Rosenberg, E.; Meykler, M.; Patel, B.; Reddy, B.; Ho, J.; Klem, I.; Singh, J.; Worku, B.; Tranbaugh, R.F.; et al. The Incidence and Natural Progression of New-Onset Postoperative Atrial Fibrillation. JACC Clin. Electrophysiol. 2021, 7, 1134–1144. [Google Scholar] [CrossRef] [Scilit]
- Aljure, O.D.; Fabbro, M. Cardiopulmonary Bypass and Inflammation: The Hidden Enemy. J. Cardiothorac. Vasc. Anesthesia 2019, 33, 346–347. [Google Scholar] [CrossRef] [Scilit]
- Hofer, F.; Hammer, A.; Steininger, M.; Kazem, N.; Koller, L.; Steinlechner, B.; Laufer, G.; Andreas, M.; Marculescu, R.; Hengstenberg, C.; et al. The Prognostic Potential of Atrial Natriuretic Peptide on the Development of Postoperative Atrial Fibrillation after Cardiac Surgery. Thromb. Haemost. 2021, 121, 1523–1529. [Google Scholar] [CrossRef] [Scilit]
- Lopez-Canoa, J.N.; Baluja, A.; Couselo-Seijas, M.; Naveira, A.B.; Gonzalez-Melchor, L.; Rozados, A.; Martínez-Sande, L.; García-Seara, J.; Fernandez-Lopez, X.A.; Fernandez, A.; et al. Plasma FABP4 levels are associated with left atrial fat volume in persistent atrial fibrillation and predict recurrence after catheter ablation. Int. J. Cardiol. 2019, 292, 131–135. [Google Scholar] [CrossRef] [Scilit]
- Rienstra, M.; Yin, X.; Larson, M.G.; Fontes, J.D.; Magnani, J.W.; McManus, D.D.; McCabe, E.L.; Coglianese, E.E.; Amponsah, M.; Ho, J.E.; et al. Relation between soluble ST2, growth differentiation factor-15, and high-sensitivity troponin I and incident atrial fibrillation. Am. Heart J. 2014, 167, 109–115.e2. [Google Scholar] [CrossRef] [Scilit]
- Guo, Y.; Lip, G.Y.; Apostolakis, S. Inflammation in Atrial Fibrillation. J. Am. Coll. Cardiol. 2012, 60, 2263–2270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hindricks, G.; Potpara, T.; Dagres, N.; Arbelo, E.; Bax, J.J.; Blomström-Lundqvist, C.; Boriani, G.; Castella, M.; Dan, G.-A.; Dilaveris, P.E.; et al. 2020 ESC Guidelines for the diagnosis and management of atrial fibrillation developed in collaboration with the European Association for Cardio-Thoracic Surgery (EACTS): The Task Force for the diagnosis and management of atrial fibrillation of the European Society of Cardiology (ESC) Developed with the special contribution of the European Heart Rhythm Association (EHRA) of the ESC. Eur. Heart J. 2021, 42, 373–498. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luo, Z.; Lei, H.; Sun, Y.; Liu, X.; Su, D.-F. Orosomucoid, an acute response protein with multiple modulating activities. J. Physiol. Biochem. 2015, 71, 329–340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almengló, C.; Fu, X.; Flores-Arias, M.T.; Fernández, L.; Viñuela, J.E.; Martínez-Cereijo, J.M.; Durán, D.; Rodríguez-Mañero, M.; González-Juanatey, J.R.; Eiras, S. Synergism between obesity andHFpEFon neutrophils phenotype and its regulation by adipose tissue-molecules andSGLT2idapagliflozin. J. Cell. Mol. Med. 2022, 26, 4416–4427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fu, X.; Almenglo, C.; Fernandez, L.; Martínez-Cereijo, J.M.; Iglesias-Alvarez, D.; Duran-Muñoz, D.; García-Caballero, T.; Gonzalez-Juanatey, J.R.; Rodriguez-Mañero, M.; Eiras, S. The Effect of Mineralocorticoid Receptor 3 Antagonists on Anti-Inflammatory and Anti-Fatty Acid Transport Profile in Patients with Heart Failure. Cells 2022, 11, 1264. [Google Scholar] [CrossRef] [Scilit]
- Bhave, P.; Passman, R. Age as a Risk factor for Atrial Fibrillation and Flutter after Coronary Artery Bypass Grafting. J. Atr. Fibrillation 2012, 4, 482. [Google Scholar]
- Kawczynski, M.J.; Gilbers, M.; Van De Walle, S.; Schalla, S.; Crijns, H.J.; Maessen, J.G.; Schotten, U.; Maesen, B.; Bidar, E. Role of pre-operative transthoracic echocardiography in predicting post-operative atrial fibrillation after cardiac surgery: A systematic review of the literature and meta-analysis. EP Eur. 2021, 23, 1731–1743. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.H.; Jang, M.-J.; Hwang, H.Y. Perioperative Beta-Blocker for Atrial Fibrillation after Cardiac Surgery: A Meta-Analysis. Thorac. Cardiovasc. Surg. 2021, 69, 133–140. [Google Scholar] [CrossRef] [Scilit]
- Lee, Y.; Cha, S.J.; Park, J.-H.; Shin, J.-H.; Lim, Y.-H.; Park, H.-C.; Shin, J.; Kim, C.K.; Park, J.-K. Association between insulin resistance and risk of atrial fibrillation in non-diabetics. Eur. J. Prev. Cardiol. 2020, 27, 1934–1941. [Google Scholar] [CrossRef] [Scilit]
- Wang, Z.; Wang, Y.-J.; Liu, Z.-Y.; Li, Q.; Kong, Y.-W.; Chen, Y.-W.; Sun, Y.-H.; Dong, J.-Z. Effect of Insulin Resistance on Recurrence after Radiofrequency Catheter Ablation in Patients with Atrial Fibrillation. Cardiovasc. Drugs Ther. 2022, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Viviano, A.; Yin, X.; Zampetaki, A.; Fava, M.; Gallagher, M.; Mayr, M.; Jahangiri, M. Proteomics of the epicardial fat secretome and its role in post-operative atrial fibrillation. EP Eur. 2018, 20, 1201–1208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Couselo-Seijas, M.; Lopez-Canoa, J.N.; Fernandez, L.; González-Melchor, L.; Seoane, L.M.; Duran-Muñoz, D.; Rozados-Luis, A.; González-Juanatey, J.R.; Rodríguez-Mañero, M.; Eiras, S. Inflammatory and lipid regulation by cholinergic activity in epicardial stromal cells from patients who underwent open-heart surgery. J. Cell. Mol. Med. 2020, 24, 10958–10969. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romanov, A.; Pokushalov, E.; Ponomarev, D.; Bayramova, S.; Shabanov, V.; Losik, D.; Stenin, I.; Elesin, D.; Mikheenko, I.; Strelnikov, A.; et al. Long-term suppression of atrial fibrillation by botulinum toxin injection into epicardial fat pads in patients undergoing cardiac surgery: Three-year follow-up of a randomized study. Heart Rhythm. 2019, 16, 172–177. [Google Scholar] [CrossRef] [Scilit]
- Liu, Z.; Khuong, J.N.; Caruana, C.B.; Jackson, S.M.; Campbell, R.; Ramson, D.M.; Penny-Dimri, J.C.; Kluger, M.; Segal, R.; Perry, L.A. The Prognostic Value of Elevated Perioperative Neutrophil-Lymphocyte Ratio in Predicting Postoperative Atrial Fibrillation after Cardiac Surgery: A Systematic Review and Meta-Analysis. Heart Lung Circ. 2020, 29, 1015–1024. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Canoa, J.N.; Couselo-Seijas, M.; Baluja, A.; González-Melchor, L.; Rozados, A.; Llorente-Cortés, V.; de Gonzalo-Calvo, D.; Guerra, J.M.; Vilades, D.; Leta, R.; et al. Sex-related differences of fatty acid-binding protein 4 and leptin levels in atrial fibrillation. EP Eur. 2021, 23, 682–690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gaudino, M.; Sanna, T.; Ballman, K.V.; Robinson, N.B.; Hameed, I.; Audisio, K.; Rahouma, M.; Di Franco, A.; Soletti, G.J.; Lau, C.; et al. Posterior left pericardiotomy for the prevention of atrial fibrillation after cardiac surgery: An adaptive, single-centre, single-blind, randomised, controlled trial. Lancet 2021, 398, 2075–2083. [Google Scholar] [CrossRef] [Scilit]
- Agra-Bermejo, R.M.; Cacho-Antonio, C.; Gonzalez-Babarro, E.; Rozados-Luis, A.; Couselo-Seijas, M.; Gómez-Otero, I.; Varela-Román, A.; López-Canoa, J.N.; Gómez-Rodríguez, I.; Pata, M.; et al. A New Biomarker Tool for Risk Stratification in “de novo” Acute Heart Failure (OROME). Front. Physiol. 2022, 12, 2438. [Google Scholar] [CrossRef] [Scilit]
- Zakkar, M.; Ascione, R.; James, A.; Angelini, G.; Suleiman, M. Inflammation, oxidative stress and postoperative atrial fibrillation in cardiac surgery. Pharmacol. Ther. 2015, 154, 13–20. [Google Scholar] [CrossRef] [Scilit]
- Arsenault, K.A.; Yusuf, A.M.; Crystal, E.; Healey, J.S.; Morillo, C.A.; Nair, G.M.; Whitlock, R.P. Interventions for preventing post-operative atrial fibrillation in patients undergoing heart surgery. Cochrane Database Syst. Rev. 2013, 2021, CD003611. [Google Scholar] [CrossRef] [Scilit]
- Dunning, J.; Treasure, T.; Versteegh, M.; Nashef, S.A. Guidelines on the prevention and management of de novo atrial fibrillation after cardiac and thoracic surgery. Eur. J. Cardio-Thorac. Surg. 2006, 30, 852–872. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).