


Simple Summary
Circulating tumor DNA (ctDNA) is emerging as a diagnostic and surveillance tool in cancer and recurrence. The recurrence rates after liver transplant for cancer are significant, highlighting the need for early detection and treatment. We report a cohort of patients who underwent liver transplant for hepatocellular carcinoma, cholangiocarcinoma, or colorectal cancer liver metastasis and received ctDNA testing pre- and/or post-transplant. We aim to show how ctDNA testing can be incorporated into pre-transplant work-up and post-transplant surveillance and discuss the benefits of this testing modality in the identification of genetic targets and surveillance of recurrence.
Abstract
Introduction: Circulating tumor DNA (ctDNA) is emerging as a promising, non-invasive diagnostic and surveillance biomarker in solid organ malignancy. However, its utility before and after liver transplant (LT) for patients with primary and secondary liver cancers is still underexplored. Methods: Patients undergoing LT for hepatocellular carcinoma (HCC), cholangiocarcinoma (CCA), and colorectal liver metastases (CRLM) with ctDNA testing were included. CtDNA testing was conducted pre-transplant, post-transplant, or both (sequential) from 11/2019 to 09/2023 using Guardant360, Guardant Reveal, and Guardant360 CDx. Results: 21 patients with HCC (n = 9, 43%), CRLM (n = 8, 38%), CCA (n = 3, 14%), and mixed HCC/CCA (n = 1, 5%) were included in the study. The median follow-up time was 15 months (range: 1–124). The median time from pre-operative testing to surgery was 3 months (IQR: 1–4; range: 0–5), and from surgery to post-operative testing, it was 9 months (IQR: 2–22; range: 0.4–112). A total of 13 (62%) patients had pre-transplant testing, with 8 (62%) having ctDNA detected (ctDNA+) and 5 (32%) not having ctDNA detected (ctDNA-). A total of 18 (86%) patients had post-transplant testing, 11 (61%) of whom were ctDNA+ and 7 (33%) of whom were ctDNA-. The absolute recurrence rates were 50% (n = 5) in those who were ctDNA+ vs. 25% (n = 1) in those who were ctDNA- in the post-transplant setting, though this difference was not statistically significant (p = 0.367). Six (29%) patients (HCC = 3, CCA = 1, CRLM = 2) experienced recurrence with a median recurrence-free survival of 14 (IQR: 6–40) months. Four of these patients had positive post-transplant ctDNA collected following diagnosis of recurrence, while one patient had positive post-transplant ctDNA collected preceding recurrence. A total of 10 (48%) patients had sequential ctDNA testing, of whom n = 5 (50%) achieved ctDNA clearance (+/−). The remainder were ctDNA+/+ (n = 3, 30%), ctDNA−/− (n = 1, 10%), and ctDNA−/+ (n = 1, 11%). Three (30%) patients showed the acquisition of new genomic alterations following transplant, all without recurrence. Overall, the median tumor mutation burden (TMB) decreased from 1.23 mut/Mb pre-transplant to 0.00 mut/Mb post-transplant. Conclusions: Patients with ctDNA positivity experienced recurrence at a higher rate than the ctDNA- patients, indicating the potential role of ctDNA in predicting recurrence after curative-intent transplant. Based on sequential testing, LT has the potential to clear ctDNA, demonstrating the capability of LT in the treatment of systemic disease. Transplant providers should be aware of the potential of donor-derived cell-free DNA and improved approaches are necessary to address such concerns.
1. Introduction
Liver transplant is the only curative-intent treatment option for patients with unresectable hepatocellular carcinoma, cholangiocarcinoma, and colorectal liver metastasis [1,2,3,4,5,6]. However, the recurrence rates may be as high as 20–50% in certain conditions, highlighting the need for thorough and frequent post-transplant monitoring [3,4,7,8,9]. Traditional surveillance relies on cross-sectional imaging and serum biomarkers such as alpha-fetoprotein (AFP), carbohydrate/cancer antigen 19-9 (CA19-9), or carcinoembryonic antigen (CEA) depending on the disease. However, post-transplant recurrence remains a challenge in terms of diagnostics and treatment due to the limited sensitivity and specificity of current tools for cancer detection [10,11,12,13,14].
To address this issue, ctDNA-based liquid biopsy has emerged as a non-invasive approach that allows for the real-time monitoring of tumor dynamics, detection of minimal residual disease, and identification of actionable mutations [15,16,17,18,19]. In patients undergoing liver transplant, the use of cell-free DNA has also been applied to detecting rejection [20]. We have previously reported the use of ctDNA in patients undergoing liver transplant for CRLM [21]. However, its use as a predictive tool of recurrence in liver transplant remains to be fully explored.
Herein, we present a cohort of patients who underwent liver transplant for HCC, CCA, or CRLM and ctDNA testing at pre-transplant and/or post-transplant time points, demonstrating a proof of concept for ctDNA in this setting.
2. Methods
Patients who underwent liver transplantation for CRLM, HCC, or CCA with pre-transplant and/or post-transplant ctDNA assessment between November 2019 and September 2023 at a single quaternary care academic institution were included in this study. All the patients were evaluated by a multidisciplinary liver tumor board and liver transplant review committee. The demographic and clinical variables, including on imaging, laboratory values, and treatment courses, were collected via a retrospective review of the patients’ health charts, as approved by the Institutional Review Board (IRB).
The ctDNA was assessed using Guardant360, Guardant360 CDx, and Guardant Reveal assays (Guardant Health, Redwood City, CA, USA). Guardant360 uses next-generation sequencing (NGS) to detect clinically relevant genomic alterations in the circulating tumor DNA in plasma collected via the peripheral blood. NGS testing was performed as part of the standard clinical care in a CLIA-certified and College of American Pathologists-accredited laboratory. The blood was collected in two to four 10 mL Streck tubes, and the processed plasma was evaluated for single-nucleotide variants (SNVs), insertions–deletions (indels), gene fusions/rearrangements, and copy number variants (CNVs) across 83 genes. Mutations were annotated using OncoKB to define pathogenic variants. The blood tumor mutational burden (bTMB) was determined by analyzing the somatic SNVs and indels across a 1.0 Mb genomic backbone. For the TMB algorithm, common cancer drivers and resistance alterations, as well as putative CHIP alterations, were filtered from the analysis. Guardant Reveal uses NGS to determine the presence of ctDNA by assessing somatic alterations (SNVs, insertion–deletion alterations) and epigenomic signatures (methylation status). Guardant Reveal was used for the portion of patients with CRLM, while Guardant360 CDx was used for the portion of patients with HCC. Guardant360 was used for all cancer types.
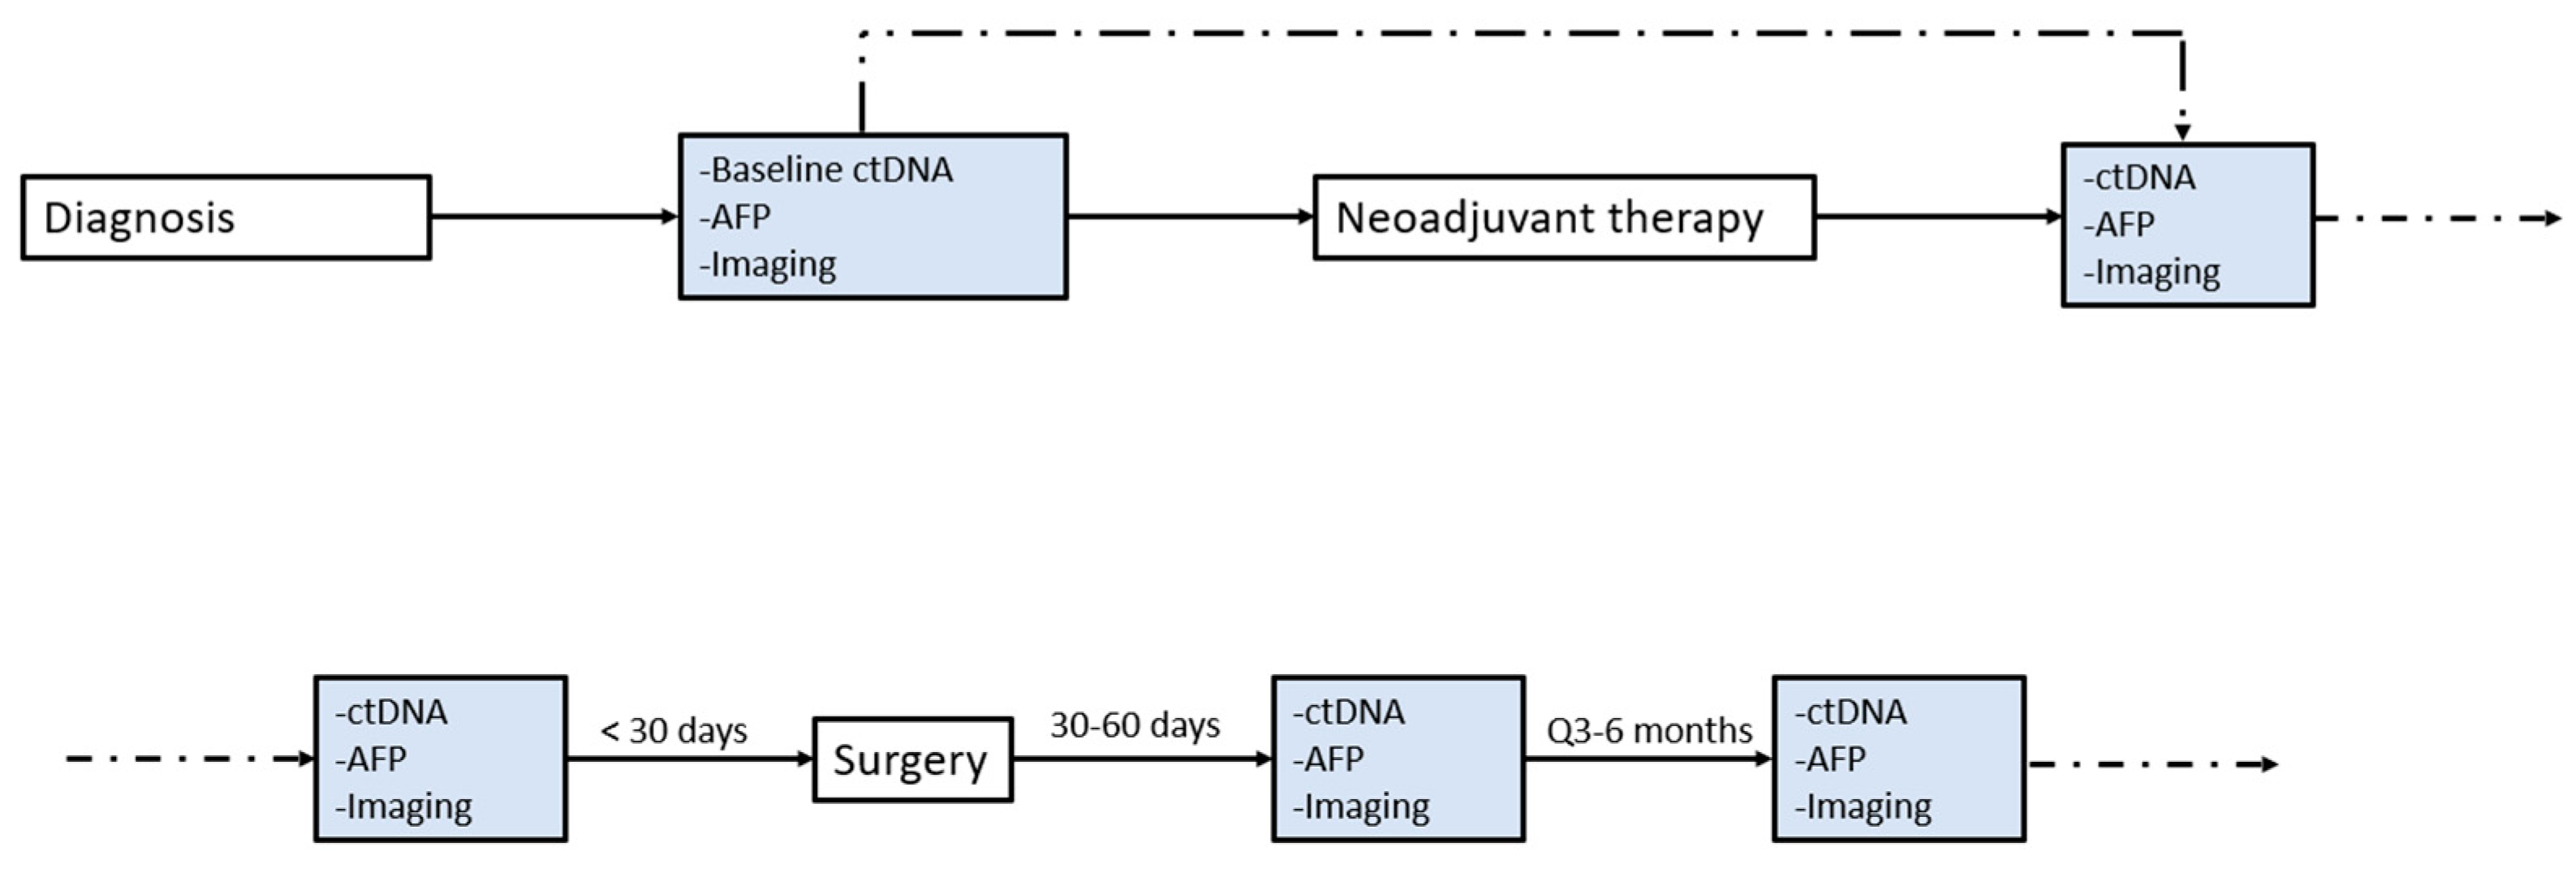
Prior to January 2021, the ctDNA was collected and evaluated at the discretion of the treating surgeon. From January 2021 onward, attempts were made to collect the ctDNA at times outlined by the current institutional protocol of within 30 days pre-operatively, 30–60 days post-operatively, and every 3–6 months afterward (Figure 1). Synonymous mutations were excluded from the analysis.
Figure 1.
Timeline for ctDNA testing, cancer work-up, and surveillance as per institutional protocol. Note the example tumor marker shown is AFP for HCC; for other cancer types, the corresponding serum tumor marker (CCA: CA19-9, CRLM: CA19-9) is used for assessment.
Discrete variables were presented as frequency and percentages, and continuous variables were presented as medians with interquartile ranges due to non-normal distributions. Statistical analysis was performed using IBM SPSS Statistics Version 29.0 (Armonk, New York, NY, USA). A two-sided p-value < 0.05 was considered significant for all tests.
3. Results
A total of 21 patients underwent ctDNA testing and LT for HCC (n = 9, 43%), CRLM (n = 8, 38%), CCA (n = 3, 14%), and mixed HCC/CCA (n = 1, 5%) (Table 1). Nine (43%) patients underwent living donor liver transplant (LDLT), seven (33%) underwent orthotopic liver transplant (OLT) with grafts from donation after brain death (DBD), and five (24%) had OLT with grafts from donation after cardiac death (DCD) (Table 1). Most patients had cirrhosis (n = 19, 90%), with a median MELD score of 15 at the time of transplant. NASH (n = 6, 30%) was the most frequent cause of cirrhosis. The median tumor marker levels at the time of liver cancer diagnosis were AFP = 8 ng/mL (HCC), CA19-9 = 23 U/mL (CCA), and CEA = 31 ng/mL (CRLM). (Table 1). Prior to transplant, most patients (n = 18, 86%) received treatment, the most common being chemotherapy (n = 10, 48%), radiation (n = 6, 29%), TACE (n = 6, 29%), and TARE (n = 5, 24%). The post-transplant tumor marker levels were 3 ng/mL, 13 U/mL, and 1.8 ng/mL for AFP, CA19-9, and CEA, respectively (Table 1). Six (29%) patients (HCC = 3, CCA = 1, CRLM = 2) experienced recurrence with a median recurrence-free survival of 14 (IQR: 6-40) months. Two (10%) patients experienced cancer-related death, both with a diagnosis of HCC (Table 1). Overall, four (19%) patients experienced mortality, with a median overall survival of 16 (IQR: 8–40) months. The median and maximum follow-up times were 15 and 124 months, respectively (Table 1).
Table 1.
Summary of demographic and pre-transplant variables and post-transplant outcomes.
In terms of transplant, most patients (n = 18, 86%) underwent the piggyback technique (Table 2). The median warm ischemia time was 43 (IQR: 39–46) minutes, with a median LT duration of 589 (IQR: 471–702) minutes. Post-operatively, most patients underwent induction immunosuppression with basiliximab (n = 12, 57%) and initial immunosuppression with glucocorticoids, mycophenolate mofetil, and tacrolimus (n = 19, 90%) (Table 3). Five (24%) patients experienced bile leaks, requiring ERCP and/or PTHC, while three (14%) patients experienced biliary strictures requiring ERCP (Table 3). One patient had ischemic cholangiopathy and hepatic artery stenosis in addition to their biliary leak, requiring HJ reconstruction, PTHC, re-transplant, and stent placement (Table 3). Two patients experienced mild acute rejection, which was treated with IV steroids. No patients experienced chronic rejection (Table 3).
Table 2.
Transplant variables.
Table 3.
Post-transplant variables.
A total of 18 (86%) patients had post-transplant ctDNA, with 11 having ctDNA detected and 7 not having ctDNA detected (Table 4). The absolute recurrence rates were higher in patients with detected ctDNA (n = 5, 50%) compared to patients without ctDNA detected (n = 1, 25%), although this difference was not found to be statistically significant (p = 0.367).
Table 4.
Tumor marker correlation with ctDNA testing at times prior to and following transplant, along with time of recurrence.
Of the six (29%) patients with recurrence, five patients had post-transplant ctDNA detected. The remaining patient (#20) did not have post-transplant ctDNA detected during or after treatment of their recurrence with metastasectomy and chemotherapy (Table 4 and Table 5). Of the post-transplant ctDNA+ patients, 4/5 had ctDNA detected following radiologic detection of recurrence, while 1/5 (#7) had ctDNA detected prior to recurrence, without elevated tumor markers. Overall, only 3/6 patients (#3, 12, 21) had elevated serum tumor markers preceding recurrence, while 3/6 (#6, 7, 20) patients lacked elevation of the traditionally used tumor markers prior to recurrence.
Table 5.
Oncologic variables including treatment before and after liver transplant as well as with recurrence.
Of all 21 patients, 10 (48%) patients had sequential ctDNA testing, with half (n = 5, 50%) having ctDNA clearance (+/−). The remainder were ctDNA+/+ (n = 3, 30%), ctDNA−/− (n = 1, 10%), and ctDNA−/+ (n = 1, 10%). More specifically, patients #9, 11, 15, 16, and 18 were ctDNA+/−; patients #2, 17, and 21 were ctDNA +/+; patient #13 was ctDNA−/−; and patient #14 was ctDNA−/+. Of note, patient #21 experienced recurrence. Three (30%) patients showed the acquisition of new genomic alterations in post-transplant ctDNA (#2, 14, 17) (Table 6). Patients #14 and 17 had no evidence of histopathologic viable tumors on explant (Table 7), suggesting potential alternate sources of these ctDNA findings. No signs of acute rejection were noticed for these patients (#14, #17, Table 6).
Table 6.
Pre- vs. post-transplant mutational profiles of patients who underwent sequential ctDNA testing by cancer type.
Table 7.
Tumor details from diagnostic radiologic imaging and explant pathology.
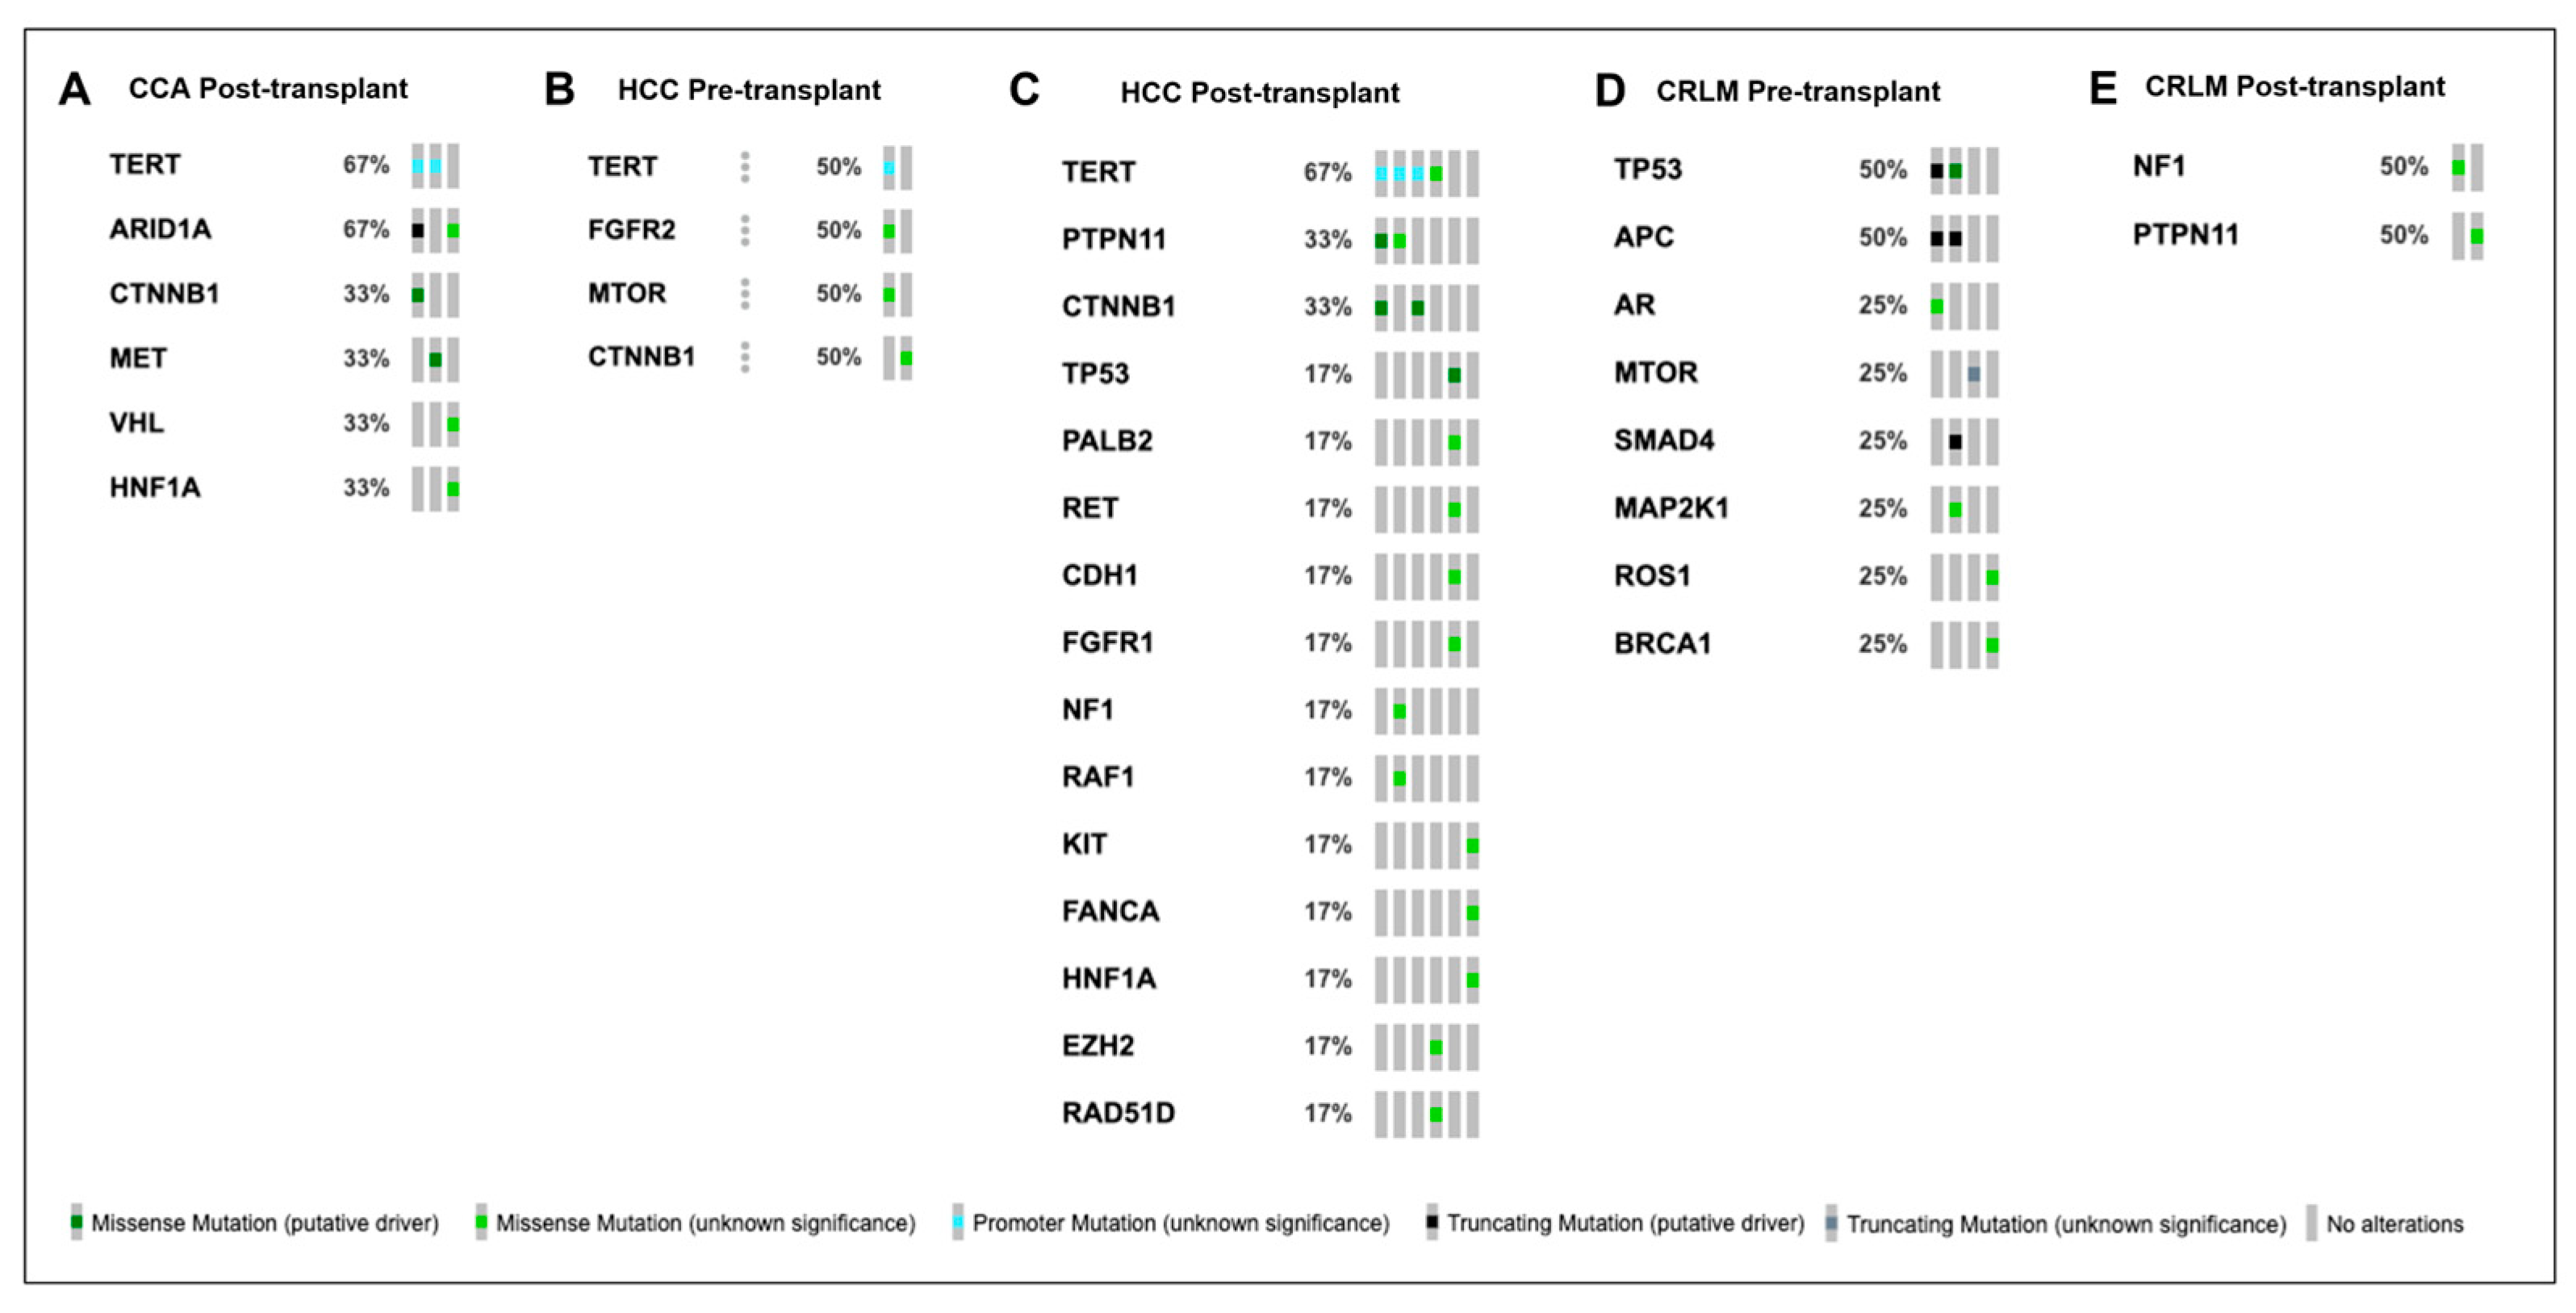
Overall, the median TMB decreased from 1.23 mut/Mb pre-transplant (n = 9) to 0.00 mut/Mb post-transplant (n = 11). For HCC, a TERT promoter mutation was the most common genomic alteration both pre-transplant and post-transplant (Figure 2). For CRLM, TP53 and APC mutations were the most common alterations observed pre-transplant, compared to NF1 and PTPN11 post-transplant (Figure 2).
Figure 2.
Oncoprints of genomic alterations detected using Guardant 360 available for CCA post-transplant (A), HCC pre-transplant (B), HCC post-transplant (C), CRLM pre-transplant (D), and CRLM post-transplant (E). Type of genomic alteration represented by color with key at bottom of figure.
4. Discussion
Liver transplant as a treatment for primary and secondary liver malignancy has grown in volume, with expansion from HCC to CCA and, more recently, to CRLM [6]. However, recurrence after LT remains a concern [22]. CtDNA has emerged as a non-invasive surveillance tool in predicting and detecting recurrence after the treatment of hepatic malignancies [23]. Compared to traditionally used tumor markers (e.g., CA19-9) which are notorious for their limited sensitivity and specificity, ctDNA offers a more individualized testing modality that can be used to predict recurrence-free survival at earlier time points, leading to guided decision-making for treatment selection [24,25].
This study demonstrates proof-of-concept for ctDNA testing in patients undergoing LT for primary and secondary liver cancers. We found a higher absolute recurrence rate in patients with positive post-transplant ctDNA. In patients who experienced recurrence, ctDNA was detected in all patients with active disease. Conversely, ctDNA was not detected in the one patient who achieved remission after recurrence. When comparing pre- vs. post-transplant ctDNA, clearance of ctDNA was observed in half of the patients who underwent sequential testing. An overall reduction in the TMB was also noted after LT. Interestingly, 30% of patients with sequential testing acquired new genomic alterations in post-transplant ctDNA, which may induce caution toward recurrent malignancy and/or the introduction of confounding genomic material that influences the interpretation of the results.
Our group previously published on the use of ctDNA in the context of hepatic resection for CRLM, showing how the detection of post-operative ctDNA was associated with an increased likelihood of disease recurrence [21]. Similarly, Tie et al. (2023) [24], Liu et al. (2023) [26], and Nishioka et al. (2022) [27] showed that post-operative ctDNA positivity predicts a reduced recurrence-free (RFS) and overall survival (OS) in patients undergoing hepatectomy for CRLM. The results of the GALAXY study further demonstrate the association of post-operative ctDNA with an increased recurrence risk and the ability to identify patients who derived benefits from adjuvant chemotherapy in patients with stage II or III CRC [28]. In patients with resected CCA, the preliminary results from Yoo at al. (2023) similarly show positive ctDNA status is predictive of a poor RFS [29]. In HCC, Wang et al. (2020) showed a reduced RFS with post-operative ctDNA assessed according to a panel of four hotspot genomic mutations in TP53 (G747T), CTNNB1 (A121G, C133T), and TERT (c.-124C>T) [30]. In the setting of liver transplant for unresectable primary liver cancer, larger scale studies by Huang et al. (2023) [23] and Jiang et al. (2022) [31] again display higher recurrence rates in patients with positive post-transplant ctDNA and decreased disease-free survival.
The widely known limitations of tumor serum biomarkers are additionally observed in our study. Of the six patients in our study who experienced recurrence, three (#6, 7, 20) had normal serum levels of traditionally used biomarkers at time of recurrence. However, ctDNA was detected post-transplant in two of these patients (#6, 7), demonstrating a potential set of patients in whom the recurrence of HCC following LT may be predicted or detected with ctDNA. To this end, expanding the enrollment of patients undergoing post-transplant ctDNA testing and conducting serial testing at earlier time points following LT may help elucidate whether the detection of ctDNA correlates with or predicts recurrence. If shown to be of prognostic utility, ctDNA could be used to stratify patients based on their risk of recurrence and determine more targeted, individualized selection of adjuvant therapy.
In addition, we report the acquisition of new mutations post-transplant in several patients who underwent sequential tumor-agnostic ctDNA testing. Although the exact source of the ctDNA is unknown, the absence of viable tumors in the explant histopathology for at least two patients may lead us to postulate that these mutations may be of donor origin. Alternatively, they may represent somatic mutations in the setting of immunosuppression post-transplant or clonal evolution. To address this concern, tumor-informed genetic testing may be considered due to its ability to differentiate ctDNA from germline-derived variants, clonal hematopoiesis of indeterminate potential, and dd-cfDNA. Such tumor-informed tools have been developed and are actively being explored in clinical studies and trials [32]. However, these methods do have limitations in patients who have received extensive pre-LT locoregional and systemic therapy, as adequate viable tumor is necessary for tissue-informed testing. Given the uncertain origin of the novel post-LT genomic alterations, making ctDNA-based treatment decisions may be challenging in this subset. At a minimum, pre- and post-LT testing should be pursued when using tissue-agnostic testing in order to obtain a pre-transplant comparison. With expanding evidence supporting the use of ctDNA testing in liver cancers [24,25,26,27,28,29,30,31], the optimization of protocols effective at addressing the concerns regarding donor-derived alterations is warranted in future studies.
In addition to assessing for the presence of ctDNA, liquid biopsy can identify specific genes that predict patient outcomes based on cancer. For example, in HCC, CTNNB1 and TERT have been shown to be two of the most commonly mutated genes and were present frequently in our cohort [33]. The presence of these two mutations, along with a mutation in TP53, in post-operative ctDNA has been associated with a decreased recurrence-free survival [30]. In CCA, the mutations are thought to be more heterogeneous, though mutations in KRAS, IDH1/2, FGFR, ERBB2, and BRAF have been noted to be more frequently mutated [34]. In colorectal cancer, mutations in APC and TP53 are known to drive the transition from adenoma to adenocarcinoma [35,36,37,38]. In patient #21, the presence of these mutations post-transplant, although at lower variant allele frequencies, was detected prior to diagnosis of recurrence (Table 8). While our study was not aimed at addressing the prognostic or therapeutic implications of specific genes, the correlation between our findings in solid organ transplant patients and the published findings in the non-transplant population is encouraging for the application of liquid biopsy to this new set of patients. Tissue-agnostic ctDNA testing could theoretically provide such analysis before transplant, allowing for pre-transplant prognostication. One example of potential utility is the detection of mutations that are contraindications to transplant, such as BRAF V600E, which represents a contraindication to LT for CRLM in our center. As detection of such a mutation pre-LT may preclude transplant due to high risk of recurrence, the use of ctDNA in the transplant population warrants further investigation for optimization of protocols and interpretation.
Table 8.
ctDNA profiles for patients who experienced recurrence.
The limitations of this study include a small sample size, which is insufficient for determining causal relationships between ctDNA clearance and liver transplant. Furthermore, a low number of patients had sequential testing, which interferes with the evaluation of donor-derived cell-free DNA. Inconsistency in the ctDNA sampling and timing may have arisen due to challenges in clinical practice and logistics. To address these issues, a large-scale multi-institutional study is being conducted to increase the patient volume, and new institutional protocols have been implemented to ensure adequate sampling. Furthermore, the impact of neoadjuvant and adjuvant chemo, immune, and radiation therapy on the ctDNA results is still unknown. Lastly, the correlation of ctDNA with tissue-based mutational profiles was not assessed in the present study, although concurrent tissue testing is now ongoing.
5. Conclusions
Circulating tumor DNA can help us to identify recurrence after liver transplant for hepatic malignancy. Transplantation was also associated with clearance of the ctDNA burden in half of the patients with sequential testing. We report a subset of patients with non-viable tumors and novel post-transplant genomic profiles, raising concern about donor-derived sources; improved approaches are necessary to address the potential of such findings confounding treatment decisions. Larger-scale studies and serial monitoring should be conducted to confirm the utility of ctDNA as a surveillance tool for MRD post-transplant and optimize the timing of the screening protocols.
Author Contributions
Conceptualization, H.H., C.J.W. and F.A.; methodology, H.H. and C.J.W.; software, H.H. and C.J.W.; validation, H.H., C.J.W. and F.A.; formal analysis, H.H. and C.J.W.; investigation, H.H., M.Z., S.F., H.S. and D.G.; resources, F.A., D.C.H.K., K.H., C.M., R.M.W., J.K., A.S., A.P. and M.K.; data curation, H.H., C.J.W., F.A., M.Z., B.E., S.K. (Suneel Kamath), S.K. (Smitha Krishnamurthi), W.W.M., T.K., E.A., E.Y., J.M.E., M.W.L., M.K., A.P., A.S. and J.K.; writing—original draft preparation, H.H., C.J.W. and F.A.; writing—review and editing, all authors; visualization, all authors; supervision, F.A.; project administration, F.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
IRB approval was obtained under Cleveland Clinic’s IRB, 09-096.
Informed Consent Statement
Consent was waived due to the retrospective nature of the review.
Data Availability Statement
The data presented in the study are available in the paper.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Hagness, M.; Foss, A.; Line, P.-D.; Scholz, T.; Jørgensen, P.F.; Fosby, B.; Boberg, K.M.; Mathisen, O.; Gladhaug, I.P.; Egge, T.S.; et al. Liver Transplantation for Nonresectable Liver Metastases from Colorectal Cancer. Ann. Surg. 2013, 257, 800–806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dueland, S.; Guren, T.K.; Hagness, M.; Glimelius, B.; Line, P.-D.; Pfeiffer, P.; Foss, A.; Tveit, K.M. Chemotherapy or Liver Transplantation for Nonresectable Liver Metastases from Colorectal Cancer? Ann. Surg. 2015, 261, 956–960. [Google Scholar] [CrossRef] [Scilit]
- Dueland, S.; Syversveen, T.; Solheim, J.M.; Solberg, S.; Grut, H.; Bjørnbeth, B.A.; Hagness, M.; Line, P.-D. Survival Following Liver Transplantation for Patients with Nonresectable Liver-Only Colorectal Metastases. Ann. Surg. 2020, 271, 212–218. [Google Scholar] [CrossRef] [Scilit]
- Tabrizian, P.; Holzner, M.L.; Mehta, N.; Halazun, K.; Agopian, V.G.; Yao, F.; Busuttil, R.W.; Roberts, J.; Emond, J.C.; Samstein, B.; et al. Ten-Year Outcomes of Liver Transplant and Downstaging for Hepatocellular Carcinoma. JAMA Surg. 2022, 157, 779–788. [Google Scholar] [CrossRef] [Scilit]
- Twohig, P.; Peeraphatdit, T.B.; Mukherjee, S. Current Status of Liver Transplantation for Cholangiocarcinoma. World J. Gastrointest. Surg. 2022, 14, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Gorji, L.; Brown, Z.J.; Limkemann, A.; Schenk, A.D.; Pawlik, T.M. Liver Transplant as a Treatment of Primary and Secondary Liver Neoplasms. JAMA Surg. 2024, 159, 211–218. [Google Scholar] [CrossRef] [Scilit]
- Agarwal, P.D.; Lucey, M.R. Management of Hepatocellular Carcinoma Recurrence after Liver Transplantation. Ann. Hepatol. 2022, 27, 100654. [Google Scholar] [CrossRef] [Scilit]
- Wu, T.C.; Smith, C.P.; Li, J.S.; Burton, J.; Jackson, N.J.; Tao, R.; Ludmir, E.B.; Raldow, A.C. A Systematic Review and Meta-Analysis of Pathologic Complete Response Rates for Patients with Cholangiocarcinoma Treated on Liver Transplant Protocols. J. Surg. Oncol. 2023, 129, 574–583. [Google Scholar] [CrossRef] [Scilit]
- Solheim, J.M.; Dueland, S.; Line, P.-D.; Hagness, M. Transplantation for Nonresectable Colorectal Liver Metastases: Long-Term Follow-Up of the First Prospective Pilot Study. Ann. Surg. 2023, 278, 239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berenguer, M.; Burra, P.; Ghobrial, M.; Hibi, T.; Metselaar, H.; Sapisochin, G.; Bhoori, S.; Kwan Man, N.; Mas, V.; Ohira, M.; et al. Posttransplant Management of Recipients Undergoing Liver Transplantation for Hepatocellular Carcinoma. Working Group Report From the ILTS Transplant Oncology Consensus Conference. Transplantation 2020, 104, 1143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanif, H.; Ali, M.J.; Susheela, A.T.; Khan, I.W.; Luna-Cuadros, M.A.; Khan, M.M.; Lau, D.T.-Y. Update on the Applications and Limitations of Alpha-Fetoprotein for Hepatocellular Carcinoma. World J. Gastroenterol. 2022, 28, 216–229. [Google Scholar] [CrossRef] [Scilit]
- Lin, M.-S.; Huang, J.-X.; Yu, H. Elevated Serum Level of Carbohydrate Antigen 19-9 in Benign Biliary Stricture Diseases Can Reduce Its Value as a Tumor Marker. Int. J. Clin. Exp. Med. 2014, 7, 744–750. [Google Scholar] [PubMed]
- Roles of Serum and Biliary CEA, CA19-9, VEGFR3, and TAC in Differentiating between Malignant and Benign Biliary Obstructions. Available online: http://turkjgastroenterol.org/en/roles-of-serum-and-biliary-cea-ca19-9-vegfr3-and-tac-in-differentiating-between-malignant-and-benign-biliary-obstructions-134337 (accessed on 25 January 2024).
- Sekiguchi, M.; Matsuda, T. Limited Usefulness of Serum Carcinoembryonic Antigen and Carbohydrate Antigen 19-9 Levels for Gastrointestinal and Whole-Body Cancer Screening. Sci. Rep. 2020, 10, 18202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liquid Biopsy at the Frontier of Detection, Prognosis and Progression Monitoring in Colorectal Cancer—PMC. Available online: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8951719/ (accessed on 25 January 2024).
- Bent, A.; Raghavan, S.; Dasari, A.; Kopetz, S. The Future of ctDNA-Defined Minimal Residual Disease: Personalizing Adjuvant Therapy in Colorectal Cancer. Clin. Color. Cancer 2022, 21, 89–95. [Google Scholar] [CrossRef] [Scilit]
- Kopystecka, A.; Patryn, R.; Leśniewska, M.; Budzyńska, J.; Kozioł, I. The Use of ctDNA in the Diagnosis and Monitoring of Hepatocellular Carcinoma—Literature Review. Int. J. Mol. Sci. 2023, 24, 9342. [Google Scholar] [CrossRef] [Scilit]
- Cabel, L.; Proudhon, C.; Buecher, B.; Pierga, J.-Y.; Bidard, F.-C. Circulating Tumor DNA Detection in Hepatocellular Carcinoma. Ann. Oncol. 2018, 29, 1094–1096. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Zheng, Y.; Wu, L.; Li, J.; Ji, J.; Yu, Q.; Dai, W.; Feng, J.; Wu, J.; Guo, C. Current Status of ctDNA in Precision Oncology for Hepatocellular Carcinoma. J. Exp. Clin. Cancer Res. 2021, 40, 140. [Google Scholar] [CrossRef] [Scilit]
- Levitsky, J.; Kandpal, M.; Guo, K.; Kleiboeker, S.; Sinha, R.; Abecassis, M. Donor-Derived Cell-Free DNA Levels Predict Graft Injury in Liver Transplant Recipients. Am. J. Transplant. 2022, 22, 532–540. [Google Scholar] [CrossRef] [Scilit]
- Wehrle, C.J.; Raj, R.; Aykun, N.; Orabi, D.; Estfan, B.; Kamath, S.; Krishnamurthi, S.; Fujiki, M.; Hashimoto, K.; Quintini, C.; et al. Liquid Biopsy by ctDNA in Liver Transplantation for Colorectal Cancer Liver Metastasis. J. Gastrointest. Surg. Off. J. Soc. Surg. Aliment. Tract 2023, 27, 1498–1509. [Google Scholar] [CrossRef] [Scilit]
- Halazun, K.J.; Najjar, M.; Abdelmessih, R.M.; Samstein, B.; Griesemer, A.D.; Guarrera, J.V.; Kato, T.; Verna, E.C.; Emond, J.C.; Brown, R.S. Recurrence After Liver Transplantation for Hepatocellular Carcinoma. Ann. Surg. 2017, 265, 557–564. [Google Scholar] [CrossRef] [Scilit]
- Huang, A.; Guo, D.-Z.; Zhang, X.; Sun, Y.; Zhang, S.-Y.; Zhang, X.; Fu, X.-T.; Wang, Y.-P.; Yang, G.-H.; Sun, Q.-M.; et al. Serial Circulating Tumor DNA Profiling Predicts Tumor Recurrence after Liver Transplantation for Liver Cancer. Hepatol. Int. 2023, 18, 254–264. [Google Scholar] [CrossRef] [Scilit]
- Tie, J.; Cohen, J.D.; Lahouel, K.; Lo, S.N.; Wang, Y.; Kosmider, S.; Wong, R.; Shapiro, J.; Lee, M.; Harris, S.; et al. Circulating Tumor DNA Analysis Guiding Adjuvant Therapy in Stage II Colon Cancer. N. Engl. J. Med. 2022, 386, 2261–2272. [Google Scholar] [CrossRef] [Scilit]
- Powles, T.; Assaf, Z.J.; Davarpanah, N.; Banchereau, R.; Szabados, B.E.; Yuen, K.C.; Grivas, P.; Hussain, M.; Oudard, S.; Gschwend, J.E.; et al. ctDNA Guiding Adjuvant Immunotherapy in Urothelial Carcinoma. Nature 2021, 595, 432–437. [Google Scholar] [CrossRef] [Scilit]
- Liu, W.; Jin, K.-M.; Zhang, M.-H.; Bao, Q.; Liu, M.; Xu, D.; Wang, K.; Xing, B.-C. Recurrence Prediction by Circulating Tumor DNA in the Patient with Colorectal Liver Metastases After Hepatectomy: A Prospective Biomarker Study. Ann. Surg. Oncol. 2023, 30, 4916–4926. [Google Scholar] [CrossRef] [Scilit]
- Nishioka, Y.; Chun, Y.S.; Overman, M.J.; Cao, H.S.T.; Tzeng, C.-W.D.; Mason, M.C.; Kopetz, S.W.; Bauer, T.W.; Vauthey, J.-N.; Newhook, T.E.; et al. Effect of Co-Mutation of RAS and TP53 on Postoperative ctDNA Detection and Early Recurrence after Hepatectomy for Colorectal Liver Metastases. J. Am. Coll. Surg. 2022, 234, 474. [Google Scholar] [CrossRef] [Scilit]
- Kotani, D.; Oki, E.; Nakamura, Y.; Yukami, H.; Mishima, S.; Bando, H.; Shirasu, H.; Yamazaki, K.; Watanabe, J.; Kotaka, M.; et al. Molecular Residual Disease and Efficacy of Adjuvant Chemotherapy in Patients with Colorectal Cancer. Nat. Med. 2023, 29, 127–134. [Google Scholar] [CrossRef] [Scilit]
- Yoo, C.; Laliotis, G.; Jeong, H.; Jeong, J.H.; Kim, K.-P.; Lee, S.; Ryoo, B.-Y.; Sharma, S.; Dutta, P.; Malhotra, M.; et al. Utility of Circulating Tumor DNA (ctDNA) as a Predictive Biomarker for Disease Monitoring in Patients (Pts) with Cholangiocarcinoma (CCA) before and during Adjuvant Chemotherapy (ACT): Sub-Analysis of the Randomized Phase 2 STAMP Trial. J. Clin. Oncol. 2023, 41 (Suppl. S16), 4123. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Huang, A.; Wang, Y.-P.; Yin, Y.; Fu, P.-Y.; Zhang, X.; Zhou, J. Circulating Tumor DNA Correlates with Microvascular Invasion and Predicts Tumor Recurrence of Hepatocellular Carcinoma. Ann. Transl. Med. 2020, 8, 237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, N.; Zeng, X.; Tang, J.; Liang, Z.; Qi, X.; Huang, L.; Pang, F. Circulating Tumor DNA Is a Potential Prognostic Risk Factor of Recurrence in Patients with Hepatocellular Carcinoma Treated by Liver Transplantation. J. Clin. Oncol. 2022, 40 (Suppl. S16), e16196. [Google Scholar] [CrossRef] [Scilit]
- Chan, H.T.; Nagayama, S.; Otaki, M.; Chin, Y.M.; Fukunaga, Y.; Ueno, M.; Nakamura, Y.; Low, S.-K. Tumor-Informed or Tumor-Agnostic Circulating Tumor DNA as a Biomarker for Risk of Recurrence in Resected Colorectal Cancer Patients. Front. Oncol. 2023, 12, 1055968. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ambrozkiewicz, F.; Trailin, A.; Červenková, L.; Vaclavikova, R.; Hanicinec, V.; Allah, M.A.O.; Palek, R.; Třeška, V.; Daum, O.; Tonar, Z.; et al. CTNNB1 Mutations, TERT Polymorphism and CD8+ Cell Densities in Resected Hepatocellular Carcinoma Are Associated with Longer Time to Recurrence. BMC Cancer 2022, 22, 884. [Google Scholar] [CrossRef] [Scilit]
- Tavolari, S.; Brandi, G. Mutational Landscape of Cholangiocarcinoma According to Different Etiologies: A Review. Cells 2023, 12, 1216. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Shay, J.W. Multiple Roles of APC and Its Therapeutic Implications in Colorectal Cancer. JNCI J. Natl. Cancer Inst. 2017, 109, djw332. [Google Scholar] [CrossRef] [Scilit]
- Lamlum, H.; Ilyas, M.; Rowan, A.; Clark, S.; Johnson, V.; Bell, J.; Frayling, I.; Efstathiou, J.; Pack, K.; Payne, S.; et al. The Type of Somatic Mutation at APC in Familial Adenomatous Polyposis Is Determined by the Site of the Germline Mutation: A New Facet to Knudson’s “two-Hit” Hypothesis. Nat. Med. 1999, 5, 1071–1075. [Google Scholar] [CrossRef] [Scilit]
- Wang, R.; Li, J.; Zhou, X.; Mao, Y.; Wang, W.; Gao, S.; Wang, W.; Gao, Y.; Chen, K.; Yu, S.; et al. Single-Cell Genomic and Transcriptomic Landscapes of Primary and Metastatic Colorectal Cancer Tumors. Genome Med. 2022, 14, 93. [Google Scholar] [CrossRef] [Scilit]
- Michel, M.; Kaps, L.; Maderer, A.; Galle, P.R.; Moehler, M. The Role of P53 Dysfunction in Colorectal Cancer and Its Implication for Therapy. Cancers 2021, 13, 2296. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).