


Abstract
Little is known about the impact of school-based nutrition interventions on parents and other family members. This systematic review aims to explore the impact of school-based nutrition interventions on different parental/family outcomes, mainly dietary intake, nutrition knowledge, and health outcomes. PubMed, Web of Science, PsycINFO, EconLit, Cochrane Reviews, and Google Scholar were systematically searched for controlled trials or natural experiments measuring the impact of school-based nutrition interventions, with or without parental involvement, on parents/families of school children. Twenty-two studies met the inclusion criteria. Of which, 15 studies assessed the impact of school-based nutrition interventions on parental/family dietary intake, 10 on parental/family nutrition knowledge, and 2 on parental/family health outcomes. Inconsistent results were found for parental dietary intake with six studies reporting favorable effects. Most studies found improved parental nutrition knowledge. Positive impacts were seen by both studies that assessed the impact on a parental health outcome. Overall, we found that there is potential for school-based nutrition interventions to result in positive effects for parents, in particular for nutrition knowledge. More research is needed to assess the impacts of school-based nutrition interventions on parents and other family members and to assess important intervention characteristics in creating a positive impact.
1. Introduction
The prevalence of non-communicable diseases (NCDs) such as diabetes, cardiovascular diseases, and cancer is continuing to increase worldwide. NCDs already account for 41 million deaths annually, representing 71% of the global deaths [1]. According to the World Health Organization (WHO), NCDs can be controlled by reducing associated risk factors including tobacco use, excessive alcohol use, physical inactivity, and unhealthy diet [1].
The role of diet in the development and control of NCDs is well established [2,3]. Dietary risk factors including low intake of whole grains, fruits, and vegetables as well as high intake of sodium, trans fats, and sugar-sweetened beverages (SSBs) were estimated to account for 11 million deaths and 255 million disability-adjusted life years (DALYs) in 2017—with high sodium and low fruit and whole grain consumption as the leading dietary risk factors [2]. Therefore, interventions aiming to promote healthy diets are essential for the prevention and control of NCDs and their associated morbidities and mortality [4].
The exposure to many NCD risk factors starts often early in life, with severe consequences in later life [5,6]. For example, childhood overweight and obesity were found to be associated with a higher risk of premature mortality and physical morbidity during adulthood [7]. It is therefore important that preventive health interventions target children and adolescents [8]. Schools are one of the key settings through which nutrition and other health interventions can be delivered. This setting has been recognized as an efficient and effective channel for reaching a wider population [9]. There have been several meta-analyses and systematic reviews exploring the effectiveness of school-based health interventions among children and adolescents. Some reviews have demonstrated promising results on children’s and adolescents’ anthropometry [10,11,12], dietary intake [10], and physical activity [12]. In addition to children, school-based health interventions may also have impacts on parents. For example, a systematic review on school-based stroke education suggested that children might be able to convey information about strokes to their parents [13]. Another study reported evidence of a positive effect from health education at primary school on parents engaging in light physical activity [14].
A large segment of the population, including parents and other family members, can benefit from interventions conducted in a school setting. However, the impact of school-based nutrition interventions on parents has not been systematically reviewed. Given the potential effect of these interventions on parents, we sought to conduct a systematic review to explore whether school-based nutrition interventions on school children, with or without parental involvement, have an impact on dietary intake, nutrition knowledge, and health outcomes of their parents and/or other household family members.
2. Materials and Methods
This systematic literature review followed the reporting guidelines of Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) (see Table S3) [15]. This review is not registered in any protocol registry.
2.1. Search Strategy and Eligibility Criteria
A systematic literature search was performed in the following databases: PubMed, Web of Science, PsycINFO, EconLit, Google Scholar, and Cochrane Reviews. The search strategy was developed based on the following three categories: (i) setting, (ii) intervention, and (iii) target population. It was then adapted according to the different structures of the databases (see Table S1 for the search strategy of each database). No date or language restrictions were applied. Additionally, the reference list of each included article was screened for potentially eligible studies. We searched Google Scholar for grey literature by screening stepwise packages of 50 hits until a package did not contain relevant results. All searches were last updated in June 2021.
Each study had to meet the following criteria to be included in this review: (1) be a controlled trial, with or without random assignment, or natural experiment; (2) target school-age children and/or adolescents (5–18 years), with or without parental involvement; (3) evaluate school-based interventions with nutrition as the primary component; and (4) report the impact of interventions on at least one of the following parental/family outcomes: (a) dietary intake, (b) nutrition knowledge, or (c) health outcome. Studies targeting parents only, preschoolers, or children with specific health issues (e.g., overweight or obesity) were excluded. We also excluded interventions related to eating disorders and oral health.
2.2. Study Selection and Data Extraction
All studies retrieved from the literature search were imported into EndNote X9 software to eliminate duplicates. The remaining unique studies were then imported to Rayyan QCRI [16]. Two reviewers (E.A. and M.R.M.) independently screened the titles and abstracts. Afterwards, the full texts of the remaining articles were screened for eligibility by the same reviewers. Any uncertainty in the decisions was addressed by a second opinion from a member of the author team (V.W. and A.S.W.). When the full texts of potentially eligible articles were not available, the authors were contacted. For the data extraction, a pre-designed and piloted extraction form was used. This form included information on the following: authors, country, study design, study participants, intervention components, theoretical framework, intervention duration, outcome measures, and findings.
2.3. Quality Assessment
The quality assessment was done based on parental data. Two reviewers (E.A. and M.R.M.) independently assessed the quality of included studies using the Quality Assessment Tool for Quantitative Studies [17]. This tool was selected for this review because it can be used to assess the methodological quality of a wide range of study designs in public health. It assesses the quality of studies based on the following components: selection bias, study design, confounders, blinding, data collection methods, and withdrawals and dropouts. Each of these components was rated as “strong”, “moderate”, or “weak” based on predefined criteria as described in the tool’s dictionary. The overall quality rating of each study was then determined based on the ratings of the above six components as “strong” (no component with a weak rating), “moderate” (one component with a weak rating), or “weak” (two or more components with weak ratings). The discrepancies between reviewers were resolved through discussion until consensus was reached.
3. Results
3.1. Literature Search Results
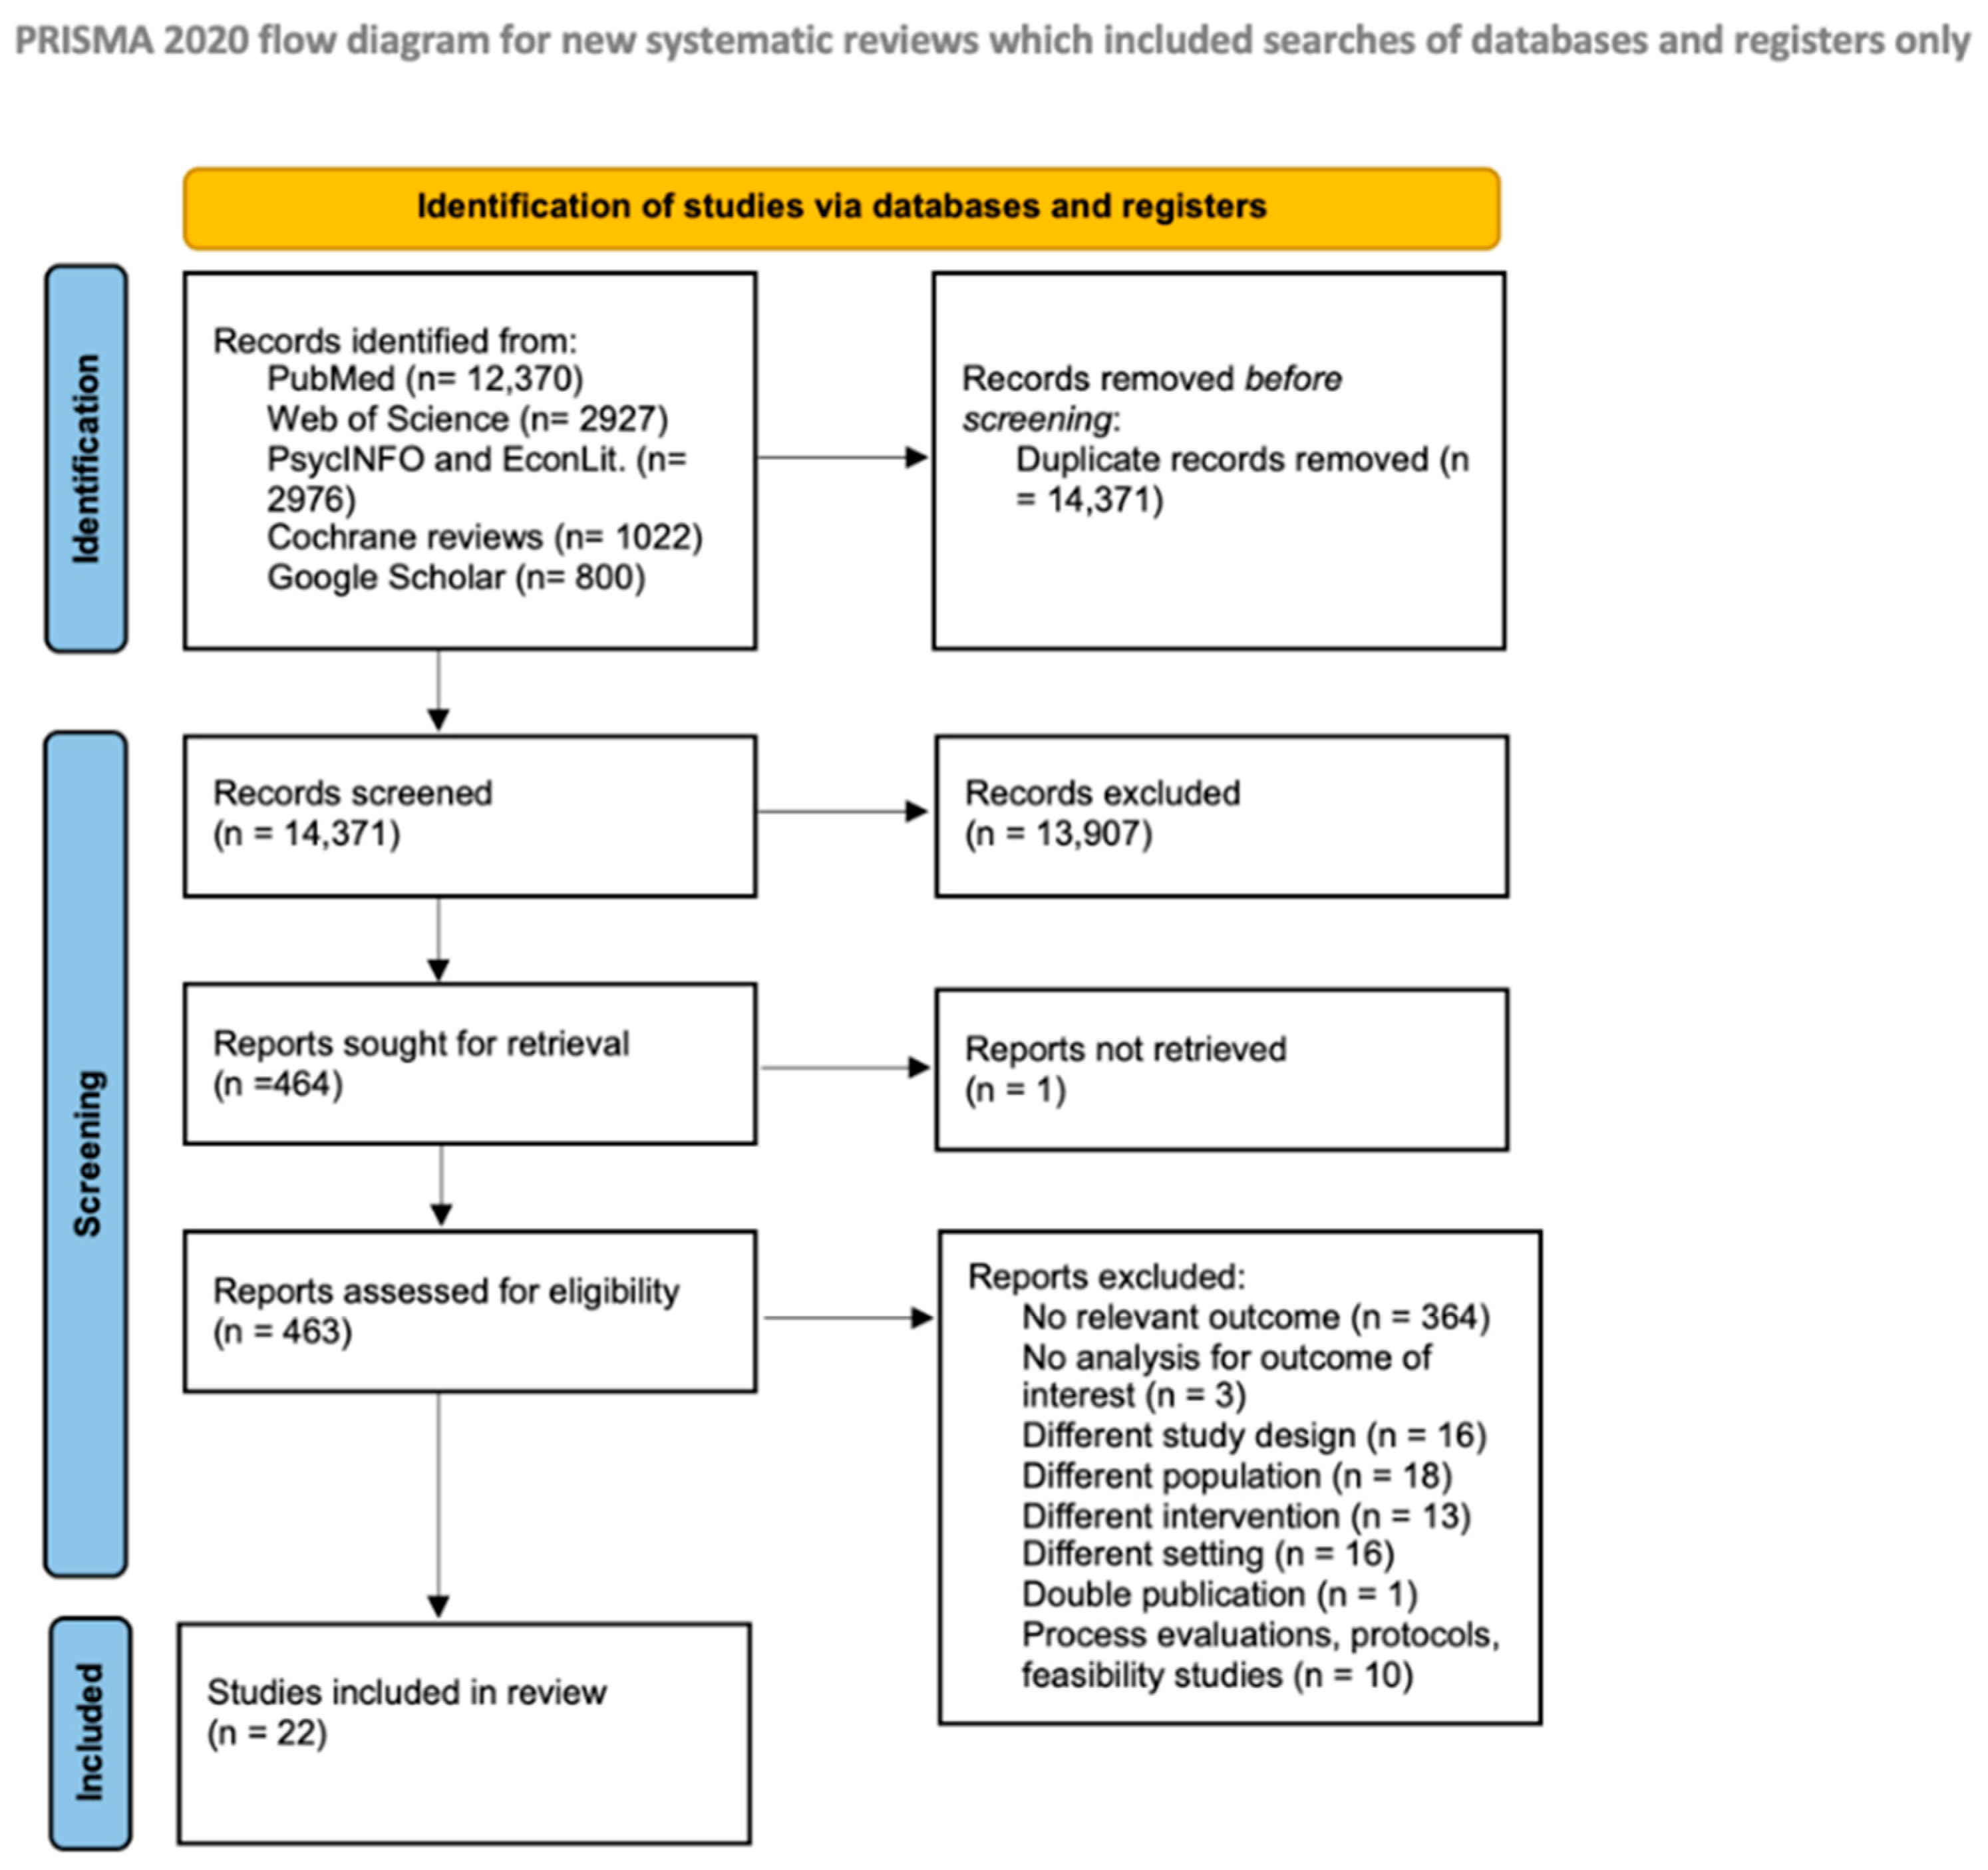
Our literature search retrieved 20,095 articles. After removal of duplicates, a total of 14,371 articles remained for the title and abstract screening, which yielded 464 articles for the full text assessment. Finally, 22 articles met our inclusion criteria and were thus included in our review. Only one non-English study (Chinese) met the inclusion criteria and was included in our review [18]. Two of the included studies had the same sample, but different outcomes were reported [19,20]. Additionally, one study [21] reported the long-term impact of another included study [22]. Figure 1 shows the results of the search strategy and reasons for exclusion.
Figure 1.
PRISMA flow diagram of study selection.
3.2. Study Characteristics
The study characteristics and quality rating of the included studies are presented in Table 1.
Table 1.
General characteristics and quality ratings of included studies.
3.3. Countries and Study Design
Of the 22 included studies, seven were conducted in the United States [24,25,26,29,33,34,35], five in China [18,19,20,36,38], and five in Europe (two in Norway [23,32], two in the Netherlands [21,22] and one study included samples from Spain, Norway, and the Netherlands [37]). The remaining studies were conducted in the following countries: Kenya [27], Sri Lanka [28], Jamaica [30], Australia [31], and the UK [39]. Regarding study designs, ten of the included studies were RCTs [18,20,23,27,28,29,33,34,37,38], ten were non-RCTs, of which nine utilized pre-post-test study designs [21,22,24,25,26,30,35,36,39], and one used a post-test study design [31]. Finally, one study had a natural experimental study design [32].
3.4. Participant Characteristics
All of the included studies recruited students from first through eighth grade. One study included a mixed sample of kindergarten and primary school students [24]. Most of the studies (n = 15) included both parents. Three studies included only mothers [28,30,37] and two studies included one adult family member [19,20]. Finally, one study included parents and siblings [27]. The sample size of parents/families varied largely, ranging from 47 [39] to 1698 participants [34].
3.5. Intervention Characteristics
Most of the interventions (n = 16) had multiple components and involved more than one domain, including the classroom, school-wide, family, and community outreach. The remaining interventions were based on a single component, including the daily distribution of snacks [27], free or subsidized fruits and vegetables [32], and providing lessons and/or training for school children [28,30].
Most of the interventions (n = 15) included parent/family components. Different approaches were used to involve parents, including sending messages to parents through mail, newsletters, text-messages, pamphlets, handouts, and/or other educational materials; collaborative homework and activities for children to complete with their parents; and parent meetings, events, lectures, and workshops.
The intervention duration varied greatly, ranging from five weeks [26] to two years [27,31]. Only six interventions were guided by theoretical frameworks, including Social Cognitive Theory (SCT) [25,34,35], Social Learning Theory (SLT) [26,33], Theory of Planned Behavior (TPB) [35], and the Social-Ecological Model [29].
3.6. Quality Assessment
Eleven of the included studies had an overall “weak” quality rating [18,21,22,23,24,27,29,30,31,36,39], five had a “moderate” quality rating [25,32,33,35,37], and six had a “strong” quality rating [19,20,26,28,34,38]. Table S2 summarizes the quality assessment for each included study. For the selection bias component, five studies were rated as “weak” [24,25,31,35,39], mainly due to the lack of representativeness of samples to the target population, and low or unreported participation rate. Four studies did not explicitly report the study design and thus were rated as “weak” [24,30,36,39]. One study had a natural experiment design and thus was rated as “moderate” [32]. Regarding the confounder component, six studies were rated as “weak” [18,24,29,31,36,39] mainly due to a lack of reporting about controlling of potential confounders. With respect to blinding, one study was not blinded to the outcome assessors nor to the study participants and thus was rated as “weak” [27]. The remaining studies were rated as “moderate” primarily due to a lack of reporting about the blinding status of outcome assessors and/or study participants. For the data collection method component, ten studies were rated as “weak” mainly due to a lack of reporting about the validity and reliability of the data collection measures. Finally, nine studies were rated as “weak” for the withdrawal and dropout component, due to a high [21,22,23,24,31,37] or unreported attrition rate [29,36,39].
3.7. Parental/Family Outcomes
The impact of school-based nutrition interventions on parental/family outcomes along with the outcome measures are presented in Table 2. Additionally, Table S4 and Figure S1 in the Supplementary Materials present a summary of the findings.
Table 2.
Parental involvement, outcomes of interest, outcome measures, and findings on parental/family outcomes of interest.
3.7.1. Dietary Intake
Mixed results were seen among the 15 studies that evaluated the impact of interventions on parental dietary intake. Of these 15 studies, 7 found no significant intervention effects on dietary intake outcomes [23,26,28,29,33,37,38]. One other study reported a general decline in dietary quantity and quality among all study groups of parents of children receiving supplementary snacks at schools and in the control group. The decline in food quantity was only significant for the parents of the vegetarian group. Significant declines in at least one of the markers of dietary quality were also seen among parents of the vegetarian, meat, and control groups [27]. Nevertheless, as reported in the study, this decline could be attributed to crop failure caused by a failed rainy season. In this study the impact of the intervention was also assessed for siblings of school children. However, we did not consider the results on siblings since it was combined with the results of school children.
The remaining seven studies reported significant intervention effects in the intervention groups. Of these, four measured parents’ change in fruit and vegetable intake. One study found a significant increase in the consumption of fruits, vegetables, and fruits and vegetables combined at the first follow-up (8 weeks post-baseline) compared to the baseline and control group. However, post-intervention, a significant increase was only found for fruit consumption in the intervention group [35]. The second study found a significant difference in vegetable consumption but not for fruits or fruits and vegetables combined immediately post-intervention. No significant differences were found for parental fruit and vegetable consumption at 1-year post intervention [34]. The third study reported a significant increase in fruit and vegetable consumption by parents in the intervention group at the first follow-up (15 months post-baseline). At 20 months post-baseline follow-up, the average fruits and vegetables consumed by parents/guardians of the pilot schools was not significantly different from either the baseline or the comparison school [39]. Finally, one study found that the parents of children who received the intervention had a significantly higher consumption of fruits than parents of children without the intervention. No significant differences in vegetable intake between groups were seen [32].
For the three remaining studies that assessed the dietary intake outcome, one study (two papers) reported a significant reduction in salt intake among family members of the intervention group compared to those of the control group [20], which led to a decrease in iodine consumption [19]. However, the iodine intake remained adequate despite this decrease in salt intake.
Finally, one study reported a significant reduction in parents’ self-reported intake of refined grains, but no significant differences were observed between groups for whole grain intake [25].
Most of the studies collected data via self-reporting, including Food Frequency Questionnaires (FFQs), 24-h recall, and questionnaire items, to assess dietary intake. The recall periods of FFQs varied between studies and were not reported in all studies. Biological markers were used to measure food intake in two studies. In these studies, 24-h urinary sodium [20] and iodine [19] excretion were used to measure salt and iodine intake.
Only three studies reported the guidelines used to estimate the serving size of food items, including the 2005 Dietary Guidelines for Americans [25,40], National Cancer Institute (5 a day guideline) [34,41], and USDA 2010 Dietary Guidelines [35,42].
3.7.2. Nutrition Knowledge
Ten studies assessed the impacts of interventions on nutrition knowledge of parents [18,21,22,24,26,30,31,34,36,38], of which seven reported significant positive intervention effects. For the remaining three studies, one found a positive effect on the knowledge of five a day serving but not on low-fat preparation knowledge at the first follow-up. No significant intervention effect on nutrition knowledge was observed at the second follow-up [34]. Finally, one study (two papers) found no significant differences between the intervention and control groups at the first [22] and second follow-ups [21].
All ten studies used questionnaires to measure nutrition knowledge. Seven of the questionnaires were self-administered [18,21,22,26,31,34,38] and two were interviewer-administered [24,30]. One study did not report the questionnaire’s mode of delivery [36].
3.7.3. Health Outcomes
Only two studies assessed the impacts of nutrition interventions on parental/family health. One study observed a significant reduction in weight and body mass index among intervention group mothers as opposed to the controls [28]. In this study, weight and height were measured at baseline and immediately post-intervention by trained study team members. The second study evaluated the differences between intervention and control groups in blood pressure using a validated automatic blood pressure monitor by trained researchers [20]. At the end of the intervention, both groups showed an increase in the systolic and diastolic blood pressure as compared to baseline. Nevertheless, the increase in systolic blood pressure was smaller in the intervention group than that observed among the control group. The mean effect on systolic blood pressure for the intervention group versus the control group was −2.3 mm Hg (95% confidence interval −4.5 to −0.04 mm Hg). No significant differences were observed in diastolic blood pressure between the groups.
4. Discussion
This systematic review sought to explore the impact of school-based nutrition interventions on three parental/family outcomes: dietary intake, nutrition knowledge, and health outcomes.
For the dietary intake, mixed results were reported across studies, with only 42% of the studies reporting positive impacts. A previous systematic review found that school-based nutrition interventions with durations between six weeks and five months were most effective in modifying the dietary behaviors of pre-adolescents and adolescents. It was also found that interventions with durations that are shorter than six weeks or longer than five months were less likely to result in positive effects [43]. Here, we observed a similar trend. Most of the interventions that were ineffective in changing parental dietary intake had a duration longer than five months. We did not find differences between effective and ineffective interventions in terms of intervention components (i.e., single component, multi-component) and parental involvement.
Most of the included studies that assessed the impact of interventions on dietary intake have focused on fruit and vegetable intake, either combined or separately. In our systematic review, the evidence on whether interventions were more effective for fruit or vegetable intake was equivocal. In contrast, a previous systematic review and meta-analysis found that school-based nutrition interventions were effective in improving the fruit intake of children with minimal impact on vegetable intake [44].
Due to the limited number of included studies that assessed the long-term impact of school-based nutrition interventions on the dietary intake of the parents, we were unable to determine the sustainability of the impacts of these interventions over time. Similarly, a previous systematic review reported a lack of evidence on the long-term impact of interventions to increase vegetable intake among children [45].
With regard to nutrition knowledge, most studies reported a statistically significant favourable impact from school-based nutrition interventions on parental nutritional knowledge. Different aspects of nutrition knowledge were studied, such as knowledge about daily recommendations for fruits, vegetables, fat, and salt intake; knowledge about diet and its relationship to diseases; and general nutrition knowledge. However, different nutrition knowledge assessment tools were used across studies. Additionally, some of these assessment methods were not validated. This may limit the comparability between studies. However, results suggest an improved nutrition knowledge among parents as a result of school-based interventions.
Only two studies included in this review assessed the impact of a nutrition intervention on parental health outcomes. These two studies had a strong methodological quality and demonstrated some promising results. Gunawardena et al. [28] reported a significant reduction in the weight of mothers of the intervention group children as compared to the control group. He et al. [20] reported that the family of the intervention group had a significantly smaller increase in systolic blood pressure compared to the control group. The small number of studies makes it difficult to draw a conclusion about this outcome. Interestingly, although these two studies had no direct parental involvement, they demonstrated positive results.
Previous systematic reviews were inconclusive about whether interventions with parental involvement improved child outcomes. One systematic review suggested that the higher involvement of parents in school-based nutrition interventions resulted in better dietary changes among children in comparison with interventions with lower parental involvement [46]. However, interventions without parental involvement were effective in improving dietary intake when they included repeated fruit and vegetable exposure. Another review reported inconsistent evidence on the effect of parental involvement on child health behaviors [47]. The differences in results between the two reviews could be explained by the different natures of the studies included in each review. The first review compared studies with high parental involvement to studies with low or no parental involvement. The second review, however, only included studies that compared the outcomes of the same intervention with and without parental involvement. Additionally, only a limited number of studies were included in the second review. Given the above evidence, parental involvement may influence the impact of school interventions on parents and/or other family members. However, there was insufficient evidence to assess this association in our review. More comprehensive studies are needed to assess the impact of parental involvement in school-based nutrition interventions on parents themselves or other family members. It is noteworthy that only two included studies assessed the impact of school-based nutrition interventions on family members other than parents.
The findings of this review emphasize the potential for school-based interventions in improving certain parental/family outcomes (i.e., parental nutrition knowledge). The findings also show a lack of systematic assessment of the effects of school-based interventions on the family, and it highlights to public health professionals that more research is needed to explore the potential impacts of school-based nutrition interventions beyond children.
Our systematic review has several strengths. First, to our knowledge, this is the first systematic review on the impact of school-based nutrition interventions on parents and other household family members. Second, despite the importance of studying the impact of school-based nutrition interventions on parents and other family members, it is often reported as a secondary outcome. For this reason, we used a broad search strategy that yielded a large number of studies that were screened for eligibility. Additionally, our search was not restricted by date, language, or geographical location. This systematic review has limitations as well. The high variability between studies, especially in terms of intervention components, assessment tools, intervention durations, and follow-up periods, made it difficult to compare results across studies. Furthermore, only six of the included studies had a strong quality rating. The remaining studies had moderate to weak ratings.
5. Conclusions
Overall, we found that there is potential for school-based nutrition interventions to result in positive effects for parents, in particular for nutrition knowledge, with less evidence for dietary intake or health outcome impacts. More research is needed to assess the impacts of school-based nutrition interventions on parents and other family members and to assess which intervention characteristics are important for positive impacts.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu14122399/s1, Table S1: Full search strategy for all databases, Table S2: Quality assess- ment of included studies using the EPHPP tool, Table S3: PRISMA 2020 Checklist, Table S4: Summary table of the impact of school-based nutrition interventions on parental outcomes, Figure S1: Summary of school-based nutrition intervention impacts on parental outcomes.
Author Contributions
Conceptualization, E.A., A.S.W. and V.W., methodology, E.A., M.R.M., A.D., K.A., N.A., P.D., S.K., O.H., V.W. and A.S.W.; formal analysis, E.A. and M.R.M.; writing—original draft preparation, E.A.; writing—review and editing, M.R.M., A.D., K.A., N.A., P.D., S.K., O.H., V.W. and A.S.W.; supervision, A.S.W. and V.W.; funding acquisition, E.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Saudi Arabian Ministry of Education.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
All literature reviewed in the study was publicly available.
Acknowledgments
For the publication fee we acknowledge financial support by Deutsche Forschungsgemeinschaft within the funding programme “Open Access Publikationskosten” as well as by Heidelberg University.
Conflicts of Interest
The authors declare no conflict of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript, or in the decision to publish the results.
References
- World Health Organization. Noncommunicable Diseases, Fact Sheets 2021; WHO: Geneva, Switzerland, 2021. [Google Scholar]
- Afshin, A.; Sur, P.J.; Fay, K.A.; Cornaby, L.; Ferrara, G.; Salama, J.S.; Mullany, E.C.; Abate, K.H.; Abbafati, C.; Abebe, Z.; et al. Health effects of dietary risks in 195 countries, 1990–2017: A systematic analysis for the Global Burden of Disease Study 2017. Lancet 2019, 393, 1958–1972. [Google Scholar] [CrossRef] [Scilit]
- Iriti, M.; Varoni, E.M.; Vitalini, S. Healthy Diets and Modifiable Risk Factors for Non-Communicable Diseases-The European Perspective. Foods 2020, 9, 940. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Daniele, N. The Role of Preventive Nutrition in Chronic Non-Communicable Diseases. Nutrients 2019, 11, 1074. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saraf, D.S.; Nongkynrih, B.; Pandav, C.S.; Gupta, S.K.; Shah, B.; Kapoor, S.K.; Krishnan, A. A systematic review of school-based interventions to prevent risk factors associated with noncommunicable diseases. Asia Pac. J. Public Health 2012, 24, 733–752. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akseer, N.; Mehta, S.; Wigle, J.; Chera, R.; Brickman, Z.J.; Al-Gashm, S.; Sorichetti, B.; Vandermorris, A.; Hipgrave, D.B.; Schwalbe, N.; et al. Non-communicable diseases among adolescents: Current status, determinants, interventions and policies. BMC Public Health 2020, 20, 1908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reilly, J.J.; Kelly, J. Long-term impact of overweight and obesity in childhood and adolescence on morbidity and premature mortality in adulthood: Systematic review. Int. J. Obes. 2011, 35, 891–898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selvan, M.S.; Kurpad, A.V. Primary prevention: Why focus on children & young adolescents? Indian J. Med. Res. 2004, 120, 511–518. [Google Scholar]
- World Health Organization. Global Standards for Health Promoting Schools; WHO: Geneva, Switzerland, 2018. [Google Scholar]
- Silveira, J.A.; Taddei, J.A.; Guerra, P.H.; Nobre, M.R. Effectiveness of school-based nutrition education interventions to prevent and reduce excessive weight gain in children and adolescents: A systematic review. J. Pediatr. 2011, 87, 382–392. [Google Scholar] [CrossRef] [Scilit]
- Jacob, C.M.; Hardy-Johnson, P.L.; Inskip, H.M.; Morris, T.; Parsons, C.M.; Barrett, M.; Hanson, M.; Woods-Townsend, K.; Baird, J. A systematic review and meta-analysis of school-based interventions with health education to reduce body mass index in adolescents aged 10 to 19 years. Int. J. Behav. Nutr. Phys. Act. 2021, 18, 1–22. [Google Scholar] [CrossRef] [Scilit]
- Verjans-Janssen, S.R.B.; van de Kolk, I.; Van Kann, D.H.H.; Kremers, S.P.J.; Gerards, S. Effectiveness of school-based physical activity and nutrition interventions with direct parental involvement on children’s BMI and energy balance-related behaviors—A systematic review. PLoS ONE 2018, 13, e0204560. [Google Scholar] [CrossRef] [Scilit]
- Beal, C.C.; Flanders, S.A.; Bader, S.G. Can Children Reduce Delayed Hospital Arrival for Ischemic Stroke?: A Systematic Review of School-Based Stroke Education. J. Neurosci. Nurs. 2016, 48, e2–e13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berniell, L.; de la Mata, D.; Valdés, N. Spillovers of health education at school on parents’ physical activity. Health Econ. 2013, 22, 1004–1020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; Moher, D.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. PRISMA 2020 explanation and elaboration: Updated guidance and exemplars for reporting systematic reviews. BMJ 2021, 372, n160. [Google Scholar] [CrossRef] [PubMed]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan—A web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Effective Public Health Practice Project. Quality Assessment Tool for Quantitative Studies. Available online: http://www.ephpp.ca/tools.html (accessed on 15 January 2021).
- Dong, J.; Gao, C.C.; Xu, C.X.; Tang, J.L.; Ren, J.; Zhang, J.Y.; Chen, X.; Shi, W.H.; Zhao, Y.F.; Guo, X.L.; et al. Evaluation on the effect of salt reduction intervention among fourth-grade primary school students and their parents in Shandong Province. Chin. J. Prev. Med. 2019, 53, 519–522. [Google Scholar]
- He, F.J.; Ma, Y.; Feng, X.; Zhang, W.; Lin, L.; Guo, X.; Zhang, J.; Noi, W.; Wu, Y.; MacGregor, G.A. Effect of salt reduction on iodine status assessed by 24 hour urinary iodine excretion in children and their families in northern China: A substudy of a cluster randomised controlled trial. BMJ Open 2016, 6, e011168. [Google Scholar] [CrossRef] [Scilit]
- He, F.J.; Wu, Y.; Feng, X.X.; Ma, J.; Ma, Y.; Wang, H.; Zhang, J.; Yuan, J.; Lin, C.P.; Nowson, C.; et al. School based education programme to reduce salt intake in children and their families (School-EduSalt): Cluster randomised controlled trial. BMJ 2015, 350, h770. [Google Scholar] [CrossRef] [Scilit]
- Tak, N.I.; Te Velde, S.J.; Brug, J. Long-term effects of the Dutch Schoolgruiten Project—Promoting fruit and vegetable consumption among primary-school children. Public Health Nutr. 2009, 12, 1213–1223. [Google Scholar] [CrossRef] [Scilit]
- Tak, N.I.; Te Velde, S.J.; Brug, J. Ethnic differences in 1-year follow-up effect of the Dutch Schoolgruiten Project—Promoting fruit and vegetable consumption among primary-school children. Public Health Nutr. 2007, 10, 1497–1507. [Google Scholar] [CrossRef] [Scilit]
- Bjelland, M.; Hausken, S.E.S.; Bergh, I.H.; Grydeland, M.; Klepp, K.-I.; Andersen, L.F.; Totland, T.H.; Lien, N. Changes in adolescents’ and parents’ intakes of sugar-sweetened beverages, fruit and vegetables after 20 months: Results from the HEIA study—A comprehensive, multi-component school-based randomized trial. Food Nutr. Res. 2015, 59, 25932. [Google Scholar] [CrossRef] [Scilit]
- Blom-Hoffman, J.; Wilcox, K.R.; Dunn, L.; Leff, S.S.; Power, T.J. Family Involvement in School-Based Health Promotion: Bringing Nutrition Information Home. Sch. Psych. Rev. 2008, 37, 567–577. [Google Scholar] [CrossRef] [Scilit]
- Burgess-Champoux, T.L.; Chan, H.W.; Rosen, R.; Marquart, L.; Reicks, M. Healthy whole-grain choices for children and parents: A multi-component school-based pilot intervention. Public Health Nutr. 2008, 11, 849–859. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crockett, S.J.; Mullis, R.; Perry, C.L.; Luepker, R.V. Parent education in youth-directed nutrition interventions. Prev. Med. 1989, 18, 475–491. [Google Scholar] [CrossRef] [Scilit]
- Gewa, C.A.; Murphy, S.P.; Weiss, R.E.; Neumann, C.G. A school-based supplementary food programme in rural Kenya did not reduce children’s intake at home. Public Health Nutr. 2013, 16, 713–720. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gunawardena, N.; Kurotani, K.; Indrawansa, S.; Nonaka, D.; Mizoue, T.; Samarasinghe, D. School-based intervention to enable school children to act as change agents on weight, physical activity and diet of their mothers: A cluster randomized controlled trial. Int. J. Behav. Nutr. Phys. Act. 2016, 13, 45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katz, D.L.; Katz, C.S.; Treu, J.A.; Reynolds, J.; Njike, V.; Walker, J.; Smith, E.; Michael, J. Teaching healthful food choices to elementary school students and their parents: The Nutrition DetectivesTM program. J. Sch. Health 2011, 81, 21–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knight, J.; Grantham-McGregor, S.; Ismail, S.; Ashley, D. A child-to-child programme in rural Jamaica. Child Care Health Dev. 1991, 17, 49–58. [Google Scholar] [CrossRef] [Scilit]
- Newell, S.A.; Huddy, A.D.; Adams, J.K.; Miller, M.; Holden, L.; Dietrich, U.C. The tooty fruity vegie project: Changing knowledge and attitudes about fruits and vegetables. Aust. N. Z. J. Public Health 2004, 28, 288–295. [Google Scholar] [CrossRef] [Scilit]
- Øvrum, A.; Bere, E. Evaluating free school fruit: Results from a natural experiment in Norway with representative data. Public Health Nutr. 2014, 17, 1224–1231. [Google Scholar] [CrossRef] [Scilit]
- Perry, C.L.; Bishop, D.B.; Taylor, G.; Murray, D.M.; Mays, R.W.; Dudovitz, B.S.; Smyth, M.; Story, M. Changing fruit and vegetable consumption among children: The 5-a-Day Power Plus program in St. Paul, Minnesota. Am. J. Public Health 1998, 88, 603–609. [Google Scholar] [CrossRef] [Scilit]
- Reynolds, K.D.; Franklin, F.A.; Binkley, D.; Raczynski, J.M.; Harrington, K.F.; Kirk, K.A.; Person, S. Increasing the fruit and vegetable consumption of fourth-graders: Results from the high 5 project. Prev. Med. 2000, 30, 309–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, S.V.; Markham, C.; Chow, J.; Ranjit, N.; Pomeroy, M.; Raber, M. Evaluating a school-based fruit and vegetable co-op in low-income children: A quasi-experimental study. Prev. Med. 2016, 91, 8–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shi-Chang, X.; Xin-Wei, Z.; Shui-Yang, X.; Shu-Ming, T.; Sen-Hai, Y.; Aldinger, C.; Glasauer, P. Creating health-promoting schools in China with a focus on nutrition. Health Promot. Int. 2004, 19, 409–418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Te Velde, S.J.; Wind, M.; Perez-Rodrigo, C.; Klepp, K.I.; Brug, J. Mothers’ involvement in a school-based fruit and vegetable promotion intervention is associated with increased fruit and vegetable intakes—Tthe Pro Children study. Int. J. Behav. Nutr. Phys. Act. 2008, 5, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, D.; Stewart, D.; Chang, C. School-based intervention for nutrition promotion in Mi Yun County, Beijing, China: Does a health-promoting school approach improve parents’ knowledge, attitudes and behaviour? Health Educ. 2016, 116, 310–319. [Google Scholar] [CrossRef] [Scilit]
- Woodhouse, L.; Bussell, P.; Jones, S.; Lloyd, H.; Macdowall, W.; Merritt, R. Bostin value: An intervention to increase fruit and vegetable consumption in a deprived neighborhood of dudley, United Kingdom. Soc. Mark. Q. 2012, 18, 221–233. [Google Scholar] [CrossRef] [Scilit]
- US Department of Health and Human Services and US Department of Agriculture. Dietary Guidelines for Americans, 2005, 6th ed.; US Government Printing Office: Washington, DC, USA, 2005.
- National Cancer Institute. 5 a Day for Better Health Program Guidebook; National Cancer Institute: Washington, DC, USA, 1991.
- U.S. Department of Agriculture; U.S. Department of Health and Human Services. Dietary Guidelines for Americans, 2010, 7th ed.; U.S. Government Printing Office: Washington, DC, USA, 20 December 2010.
- Racey, M.; O’Brien, C.; Douglas, S.; Marquez, O.; Hendrie, G.; Newton, G. Systematic Review of School-Based Interventions to Modify Dietary Behavior: Does Intervention Intensity Impact Effectiveness? J. Sch. Health 2016, 86, 452–463. [Google Scholar] [CrossRef] [Scilit]
- Evans, C.E.; Christian, M.S.; Cleghorn, C.L.; Greenwood, D.C.; Cade, J.E. Systematic review and meta-analysis of school-based interventions to improve daily fruit and vegetable intake in children aged 5 to 12 y. Am. J. Clin. Nutr. 2012, 96, 889–901. [Google Scholar] [CrossRef] [Scilit]
- Appleton, K.M.; Hemingway, A.; Saulais, L.; Dinnella, C.; Monteleone, E.; Depezay, L.; Morizet, D.; Perez-Cueto, F.J.A.; Bevan, A.; Hartwell, H. Increasing vegetable intakes: Rationale and systematic review of published interventions. Eur. J. Nutr. 2016, 55, 869–896. [Google Scholar] [CrossRef] [Scilit]
- Muzaffar, H.; DiFilippo, K.N.; Fitzgerald, N.; Tidwell, D.K.; Idris, R.; Kurzynske, J.S.; Chapman-Novakofski, K. A Systematic Review of Interventions to Improve Diet Quality of Children that Included Parents Versus Those Without Parental Involvement. Curr. Dev. Nutr. 2020, 4 (Suppl. S2), 1336. [Google Scholar] [CrossRef] [Scilit]
- Van Lippevelde, W.; Verloigne, M.; De Bourdeaudhuij, I.; Brug, J.; Bjelland, M.; Lien, N.; Maes, L. Does parental involvement make a difference in school-based nutrition and physical activity interventions? A systematic review of randomized controlled trials. Int. J. Public Health 2012, 57, 673–678. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).