


Abstract
Recombinant human insulin plays an important role in the gut maturation of preterm infants. This meta-analysis was carried out to assess the efficacy and safety of enteral recombinant human insulin in decreasing the time to full enteral feeding in preterm infants. The pooling of data from four clinical trials yielded a significant decrease in the time to full enteral feeding in preterm infants under both low (Mean difference [MD] −3.43 days; 95% CI: −6.18 to −0.69 days; I2 = 48%) and high doses of insulin (MD −7.10 days; 95% CI: −10.02 to −4.18 days; I2 = 0%). These findings require confirmation by further large trials that evaluate the efficacy and safety of enteral insulin, especially at supraphysiological doses.
1. Introduction
A preterm birth is categorized as the birth of a baby before 37 weeks of gestation [1]. Around 15 million children are born prematurely every year, representing a worldwide rate of 11% [2,3]. Preterm infants often have low birth weight and feeding problems associated with immaturity of the gastrointestinal system. The full development of the gastrointestinal tract, including motor development and lactase activity, typically occurs in the third trimester of pregnancy [4]. As a result, preterm infants may require enteral feeding via naso- or orogastric tubes to support their nutritional needs; however, gut immaturity makes enteral feedings difficult to tolerate. Feeding intolerance may include clinical manifestations such as vomiting, abdominal distension, and gastric residuals [5]. The consequence of feeding intolerance is increased dependency on total parenteral nutrition (TPN) and an increased risk of associated complications such as intestinal-associated liver disease and late-onset sepsis [6,7,8]. Therefore, interventions that improve feeding intolerance and enhance a quick transition to full enteral feeding in preterm infants are crucial.
Studies on animal models suggest that maternal milk contains factors that stimulate the development of the gastrointestinal tract [9]. These intestinal-enhancing effects of maternal milk are attributed to a multitude of non-nutritive, biologically active factors, including the peptide hormone insulin [10]. During the early puerperal period, insulin levels peak and then decline to a basal level within 3 days of postpartum [11]. Unfortunately, insulin is not yet available in formula powders.
Some clinical trials have been conducted on this topic, but they have not been systematically evaluated. In this study, we aim to evaluate the efficacy and safety of enteral human recombinant insulin in reducing the time to full enteral feeding in preterm infants. Our meta-analysis will help to determine if this intervention can prevent feeding intolerance and associated complications in this vulnerable population.
2. Methods
This meta-analysis was conducted according to the guidelines of the Preferred Reporting Items for Systematic Review (PRISMA) [12]. The PRISMA guidelines checklist has been submitted as Supplementary Materials for this journal article. We thoroughly searched all relevant articles on PubMed and Embase from inception until 20 December 2022 using the following search terms: (“Insulin”) AND (“preterm” OR “LBW” OR “Low birth weight” OR “birth weight” OR “infants”) AND (“Feeding intolerance” OR “Maturation” OR “full enteral feed” OR “enteral feed”). We applied no language restrictions.
We initially screened articles based on titles and abstracts and then screened them by reading the full text of the research articles. Two separate authors (FQ and MA) conducted the screening, and any conflicts and discrepancies were resolved through discussion with the third author (MA). We included controlled clinical trials that enrolled preterm infants and compared the efficacy of recombinant human insulin concentration with placebo or no treatment. Our outcomes of interest were the reduction in the time to full enteral feeding and the incidence of serious adverse events.
We pooled the data using RevMan 5.4 software under a random-effects model using mean differences (MDs) and risk ratios (RRs) with their 95% confidence intervals (CIs). Heterogeneity was assessed by the I2 statistic. We evaluated the efficacy of enteral insulin in two doses: (a) the physiological dose (400 µIU/mL milk) present in human colostrum (low dose) and (b) a supraphysiological dose (2000 µIU/mL milk) (high dose) [11].
3. Results
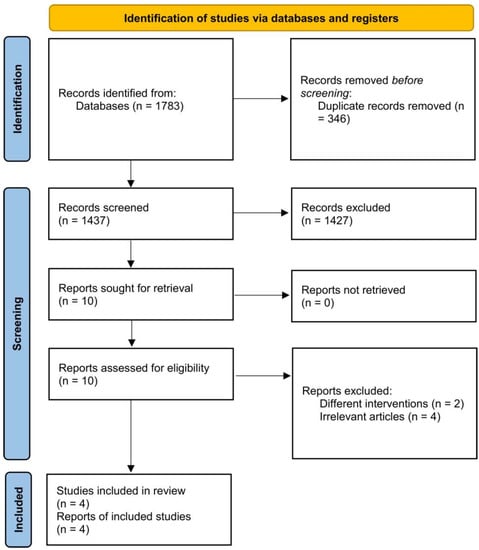
The screening process identified four trials meeting the inclusion criteria that contributed five comparisons to the meta-analysis with a total of 388 participants (204 receiving enteral recombinant insulin, 184 receiving placebo) [13,14,15,16]. The detailed screening process is depicted in Figure 1. Three studies were randomized controlled trials (RCTs) [13,14,16] while the remaining trial was a pilot study that used a matched historical cohort as the comparator [15]. Two studies used a low dose of insulin [13,14], one study evaluated a supraphysiological dose of insulin [15], and the remaining RCT assessed both low and high doses [16]. The characteristics of each study are summarized in Table 1.
Figure 1.
PRISMA 2020 flowchart.
Table 1.
Characteristics of the included studies.
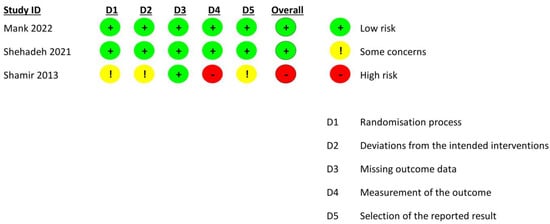
The quality assessment of RCTs was carried out using the revised Cochrane Risk of Bias (RoB 2.0) tool [17]. One trial was at a high risk of bias while the other two were judged to have a low risk of bias (Figure 2). The pilot study was rated as fair using the National Institute of Health’s (NIH) quality assessment tool (Table 2) [18].
Figure 2.
Quality assessment of included trials [13,14,16].
Table 2.
Quality assessment of the pilot study.
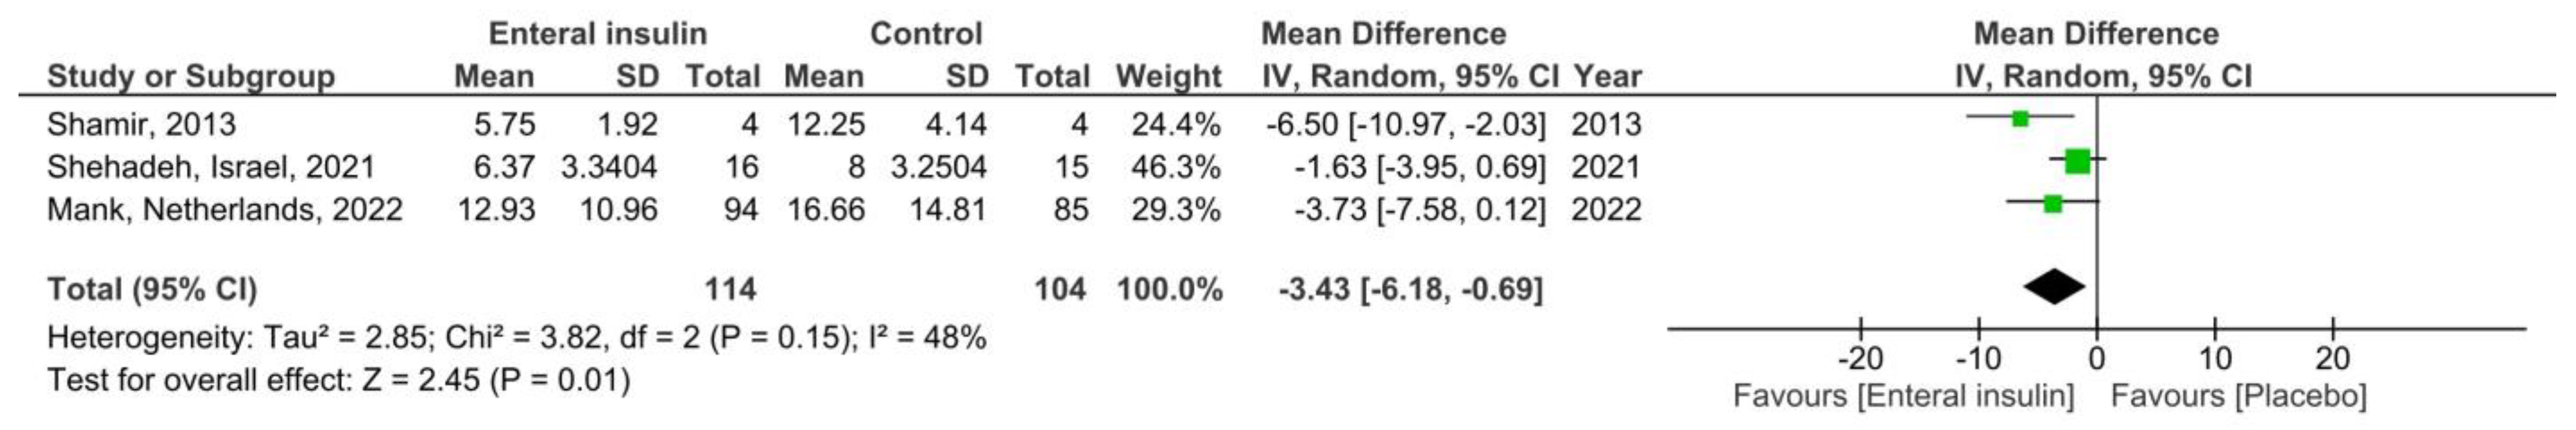
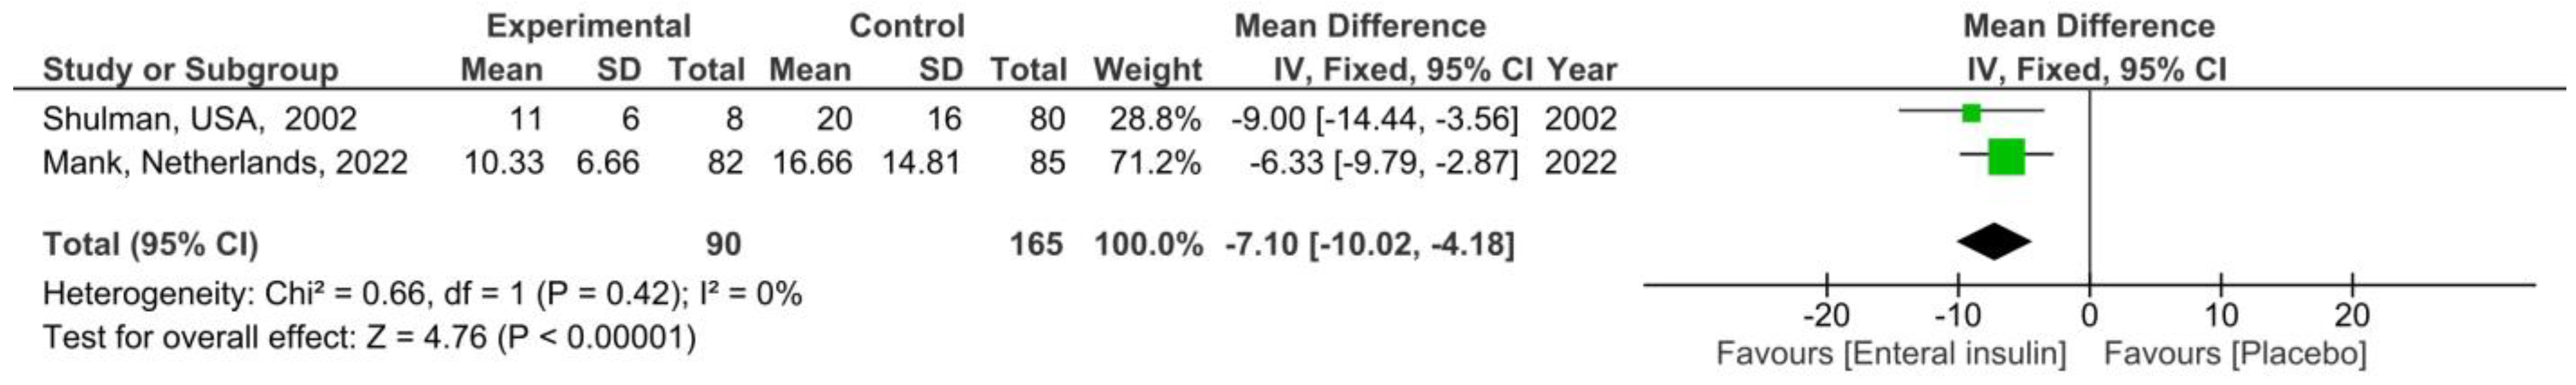
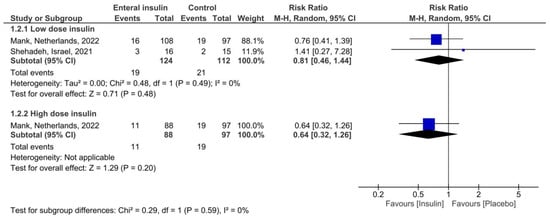
The results of our meta-analysis show that the use of enteral recombinant human insulin significantly decreased the time to full enteral feeding in preterm infants at both low (MD −3.43 days; 95% CI: −6.18 to −0.69 days; I2 = 48%; Figure 3) and high doses (MD −7.10 days; 95% CI: −10.02 to −4.18 days; I2 = 0%; Figure 4). Upon sensitivity analysis after excluding the study by Shamir et al. in the low-dose group, the heterogeneity decreased to 0% potentially due to the study’s small sample size. Because only one study reported serious adverse events in the high-dose group, indicating that high-dose insulin was safe (RR 0.64; 95% CI: 0.32 to 1.26), adverse events were meta-analyzed in the low-dose insulin group only. Low-dose insulin did not increase the number of serious adverse events (RR 0.81; 95% CI: 0.46 to 1.44; I² = 0%; Figure 5).
Figure 3.
Effect of low-dose insulin on time to full enteral feeding [13,14,16].
Figure 4.
Effect of high-dose insulin on time to full enteral feeding [13,16].
Figure 5.
Incidence of adverse events with enteral insulin [13,16].
4. Discussion
To the best of our knowledge, this is the first meta-analysis that focuses on the use of enteral recombinant insulin in preterm infants. Our results indicate that the use of enteral insulin in preterm infants promotes gut maturation and increases enteral feeding intake. Our findings demonstrate that both low- and high-dose insulin significantly reduce the time to achieve full enteral feeding. There was no significant difference in the incidence of serious adverse events between the insulin and control groups. The occurrence of adverse events was largely attributed to the preterm birth of infants.
Managing preterm infants is challenging because it involves preventing sepsis and necrotizing enterocolitis, which are common in these infants. Preterm infants may need to receive their nutrition through nasogastric or orogastric tubes due to an inability to feed orally resulting from neurological immaturity [19]. However, feeding intolerance is a common condition in this population. The development of the gastrointestinal tract, including the ability to move and digest lactose, usually happens entirely during the third trimester of pregnancy. Gut immaturity and decreased lactase activity contribute to feeding intolerance [5]. To address this, factors that promote lactase activity can be used. Human milk contains various bioactive factors, hormones, and nutrients that protect infants. However, preterm infants who cannot tolerate full enteral feeding should have their nutritional requirements covered parenterally. This can increase the length of hospitalization, and subsequently, the risk of hospital-acquired infections, especially in developing countries. Hence, any intervention that decreases the time to full enteral feeding can directly reduce the duration of hospital stay and decrease the complications associated with parenteral feeding.
Some limitations of our meta-analysis need to be considered. Most of our included trials were small with only one study involving more than 80 participants in each group. Furthermore, one of the pooled studies was a pilot study that used a historical cohort as the comparator. There are limited data about the safety of enteral insulin, especially with high doses of insulin.
In summary, our study supports the use of insulin in preterm infants as it reduces the time to full enteral feeding. This provides a new direction for the management of preterm neonates, contributing to a decreased duration of hospital stay and the prevention of short-term and long-term consequences of hospitalization. However, further larger studies are required to evaluate the efficacy and safety of insulin, especially at supraphysiological doses. Furthermore, the effect of this intervention on other clinical outcomes reflecting reduced morbidity should be evaluated. Additionally, the efficacy of enteral recombinant human insulin in extremely preterm infants (born at gestational ages of less than 28 weeks) should be evaluated.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/pediatric15020033/s1.
Author Contributions
F.Q.: Conceptualization, Methodology, Formal analysis, Resources, Writing—Review & Editing, Project Administration; M.A. (Muhammad Adil): Methodology, Formal analysis, Resources, Writing—Original draft preparation; M.K.: Formal analysis, Data curation, Writing—Original draft preparation; M.A. (Muhammad Azam): Formal analysis, Investigation, Writing—Original draft preparation; H.A.C.: Writing—Review & Editing, Supervision, Validation, Project administration; A.S.: Conceptualization, Investigation, Writing—Review & Editing; I.C.-O.: Methodology, Writing—Reviewing and Editing, Visualization. All authors agree to be accountable for all aspects of the work. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not required.
Informed Consent Statement
Not required.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Quinn, J.-A.; Munoz, F.M.; Gonik, B.; Frau, L.; Cutland, C.; Mallett-Moore, T.; Kissou, A.; Wittke, F.; Das, M.; Nunes, T.; et al. Preterm Birth: Case Definition & Guidelines for Data Collection, Analysis, and Presentation of Immunisation Safety Data. Vaccine 2016, 34, 6047–6056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization (WHO). Preterm Birth Fact Sheet. Available online: https://www.who.int/news-room/fact-sheets/detail/preterm-birth (accessed on 19 February 2023).
- Walani, S.R. Global Burden of Preterm Birth. Int. J. Gynaecol. Obstet. 2020, 150, 31–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berseth, C.L.; Nordyke, C. Enteral Nutrients Promote Postnatal Maturation of Intestinal Motor Activity in Preterm Infants. Am. J. Physiol. 1993, 264, G1046–G1051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fanaro, S. Feeding Intolerance in the Preterm Infant. Early Hum. Dev. 2013, 89 (Suppl. S2), S13–S20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- El Manouni El Hassani, S.; Berkhout, D.J.C.; Niemarkt, H.J.; Mann, S.; de Boode, W.P.; Cossey, V.; Hulzebos, C.V.; van Kaam, A.H.; Kramer, B.W.; van Lingen, R.A.; et al. Risk Factors for Late-Onset Sepsis in Preterm Infants: A Multicenter Case-Control Study. Neonatology 2019, 116, 42–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, J.; Jefferies, A.L.; Yoon, E.W.; Lee, S.K.; Shah, P.S. Risk Factors and Outcomes of Late-Onset Bacterial Sepsis in Preterm Neonates Born at < 32 Weeks’ Gestation. Am. J. Perinatol. 2015, 32, 675–682. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kelly, D.A. Intestinal Failure-Associated Liver Disease: What Do We Know Today? Gastroenterology 2006, 130, S70–S77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koldovský, O.; Thornburg, W. Hormones in Milk. J. Pediatr. Gastroenterol. Nutr. 1987, 6, 172–196. [Google Scholar] [PubMed]
- Shehadeh, N.; Gelertner, L.; Blazer, S.; Perlman, R.; Solovachik, L.; Etzioni, A. Importance of Insulin Content in Infant Diet: Suggestion for a New Infant Formula. Acta Paediatr. 2001, 90, 93–95. [Google Scholar] [CrossRef] [PubMed]
- Mank, E.; van Toledo, L.; Heijboer, A.C.; van den Akker, C.H.P.; van Goudoever, J.B. Insulin Concentration in Human Milk in the First Ten Days Postpartum: Course and Associated Factors. J. Pediatr. Gastroenterol. Nutr. 2021, 73, e115–e119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shehadeh, N.; Simmonds, A.; Zangen, S.; Riskin, A.; Shamir, R. Efficacy and Safety of Enteral Recombinant Human Insulin for Reduction of Time-to-Full Enteral Feeding in Preterm Infants: A Randomized, Double-Blind, Placebo-Controlled Trial. Isr. Med. Assoc. J. 2021, 23, 563–568. [Google Scholar] [PubMed]
- Shamir, R.; Shehadeh, N. Insulin in Human Milk and the Use of Hormones in Infant Formulas. In Nestlé Nutrition Institute Workshop Series; Karger Publishers: Basel, Switzerland, 2013; Volume 77, pp. 57–64. ISBN 1664-2147. [Google Scholar]
- Shulman, R.J. Effect of Enteral Administration of Insulin on Intestinal Development and Feeding Tolerance in Preterm Infants: A Pilot Study. Arch. Dis. Child. Fetal Neonatal Ed. 2002, 86, F131–F133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mank, E.; Sáenz de Pipaón, M.; Lapillonne, A.; Carnielli, V.P.; Senterre, T.; Shamir, R.; van Toledo, L.; van Goudoever, J.B.; van Goudoever, J.B.; Mank, E.; et al. Efficacy and Safety of Enteral Recombinant Human Insulin in Preterm Infants: A Randomized Clinical Trial. JAMA Pediatr. 2022, 176, 452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.-Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A Revised Tool for Assessing Risk of Bias in Randomised Trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- NHLBI Study Quality Assessment Tools. Available online: https://www.nhlbi.nih.gov/health-topics/study-quality-assessment-tools (accessed on 19 February 2023).
- McGuire, W.; Henderson, G.; Fowlie, P.W. Feeding the Preterm Infant. BMJ 2004, 329, 1227–1230. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).