


Abstract
Exosomes are extracellular vesicles within the nanosized range that play roles in intercellular communication and thus have certain biological activities. The secretory signaling communication mechanism is an efficient way of exchanging information between cells and has been investigated as nature’s therapeutic drug carriers. This review will summarize the potential of exosomes as therapeutic tools and drug delivery vehicles for corneal pathologies. The cornea is an avascular ocular tissue, and its healing is a complex process including cell death and migration, cell proliferation and differentiation, and extracellular matrix remodeling. Here, we discussed the structure, barrier, phases, and healing cascade of cornea. We briefly reviewed the immunogenicity and toxicity of exosomes and role of exosomes in preserving cornea. Additionally, we provided combining exosome strategies with hydrogels, gene and stem cells therapy focused on corneal treatment, repair, and regeneration.
1. Introduction
Vision impairment occurs when an eye condition affects the visual systems and functions. According to the WHO 2019 global report, 2.2 billion people are experiencing some ocular issues. Among ocular diseases, corneal defects and illnesses are the third leading cause of vision impairment worldwide. Disorders like corneal scarring, haze, dry eye, keratitis, keratoconus, corneal dystrophies, herpes infection, cicatrizing conjunctivitis, Surfer’s eye, fibrosis, Stevens–Johnson syndrome, and iridocorneal endothelial syndrome are common corneal conditions that affect normal vision [1]. Corneal opacities, which can be caused by a range of factors like trauma, infections, hereditary conditions, and previous surgeries, contribute significantly to visual impairment. The global burden of corneal opacities was responsible for 1.9 million cases of moderate to severe visual impairment in 2019, and they were reported as the primary cause of blindness [2]. It has been established physiologically that corneal healing involves complex pathways. Thus, varying mechanisms of actions are often involved to support corneal recovery, repair, and regeneration. Particularly, for the corneal wound-healing mechanism, several approaches have been identified, including gene therapy and biologic therapeutics, and there is a plethora of drug classes employed by ophthalmologists to control eye pain, combat inflammation, and treat ocular surface disease. However, the complexity of five-layered corneal tissue still needs patient-friendly and effective treatments. Thus, we explored the potential of exosomes as therapeutics for repair, regeneration, and treatment of cornea.
Exosomes, a class of tiny extracellular vesicles (EVs), have been used as a suitable delivery vehicle owing to their inherent function in intracellular communication and biocompatibility [3]. EVs are lipid-bound, small cellular containers secreted by nearly all cell types. Subcategories of EVs include apoptotic bodies, microvesicles, and exosomes, which are differentiated based on size and pathway of origin [4,5]. Exosomes, being the smallest subtype of EVs, range in diameter from only 30 to 150 nanometers (nm) [6]. Despite their small size, the nanovesicles contain fundamental building blocks of cells, including nucleic acids, proteins, and lipids from their derived parent cell. Their main feature and most understood function to date is their role as signaling molecules through the transfer of stored genetic information, serving as a biomarker for disease, as well as being proposed therapeutics by themselves (non-drug- or gene-loaded) [7]. Due to those described roles of exosomes, they have shown promise as a non-invasive treatment for corneal disease. In this article, we will review the use of exosomes to rescue cornea, which includes the source of exosomes, therapeutic effects, and limitations to clinical use. Overall, this succinct review will provide concise summaries of cornea anatomy, physiology, wound-healing mechanism, biogenesis, and immunogenicity of exosomes and exosome-based approaches for corneal repair, regeneration, and treatment.
2. Cornea Structure and Barrier
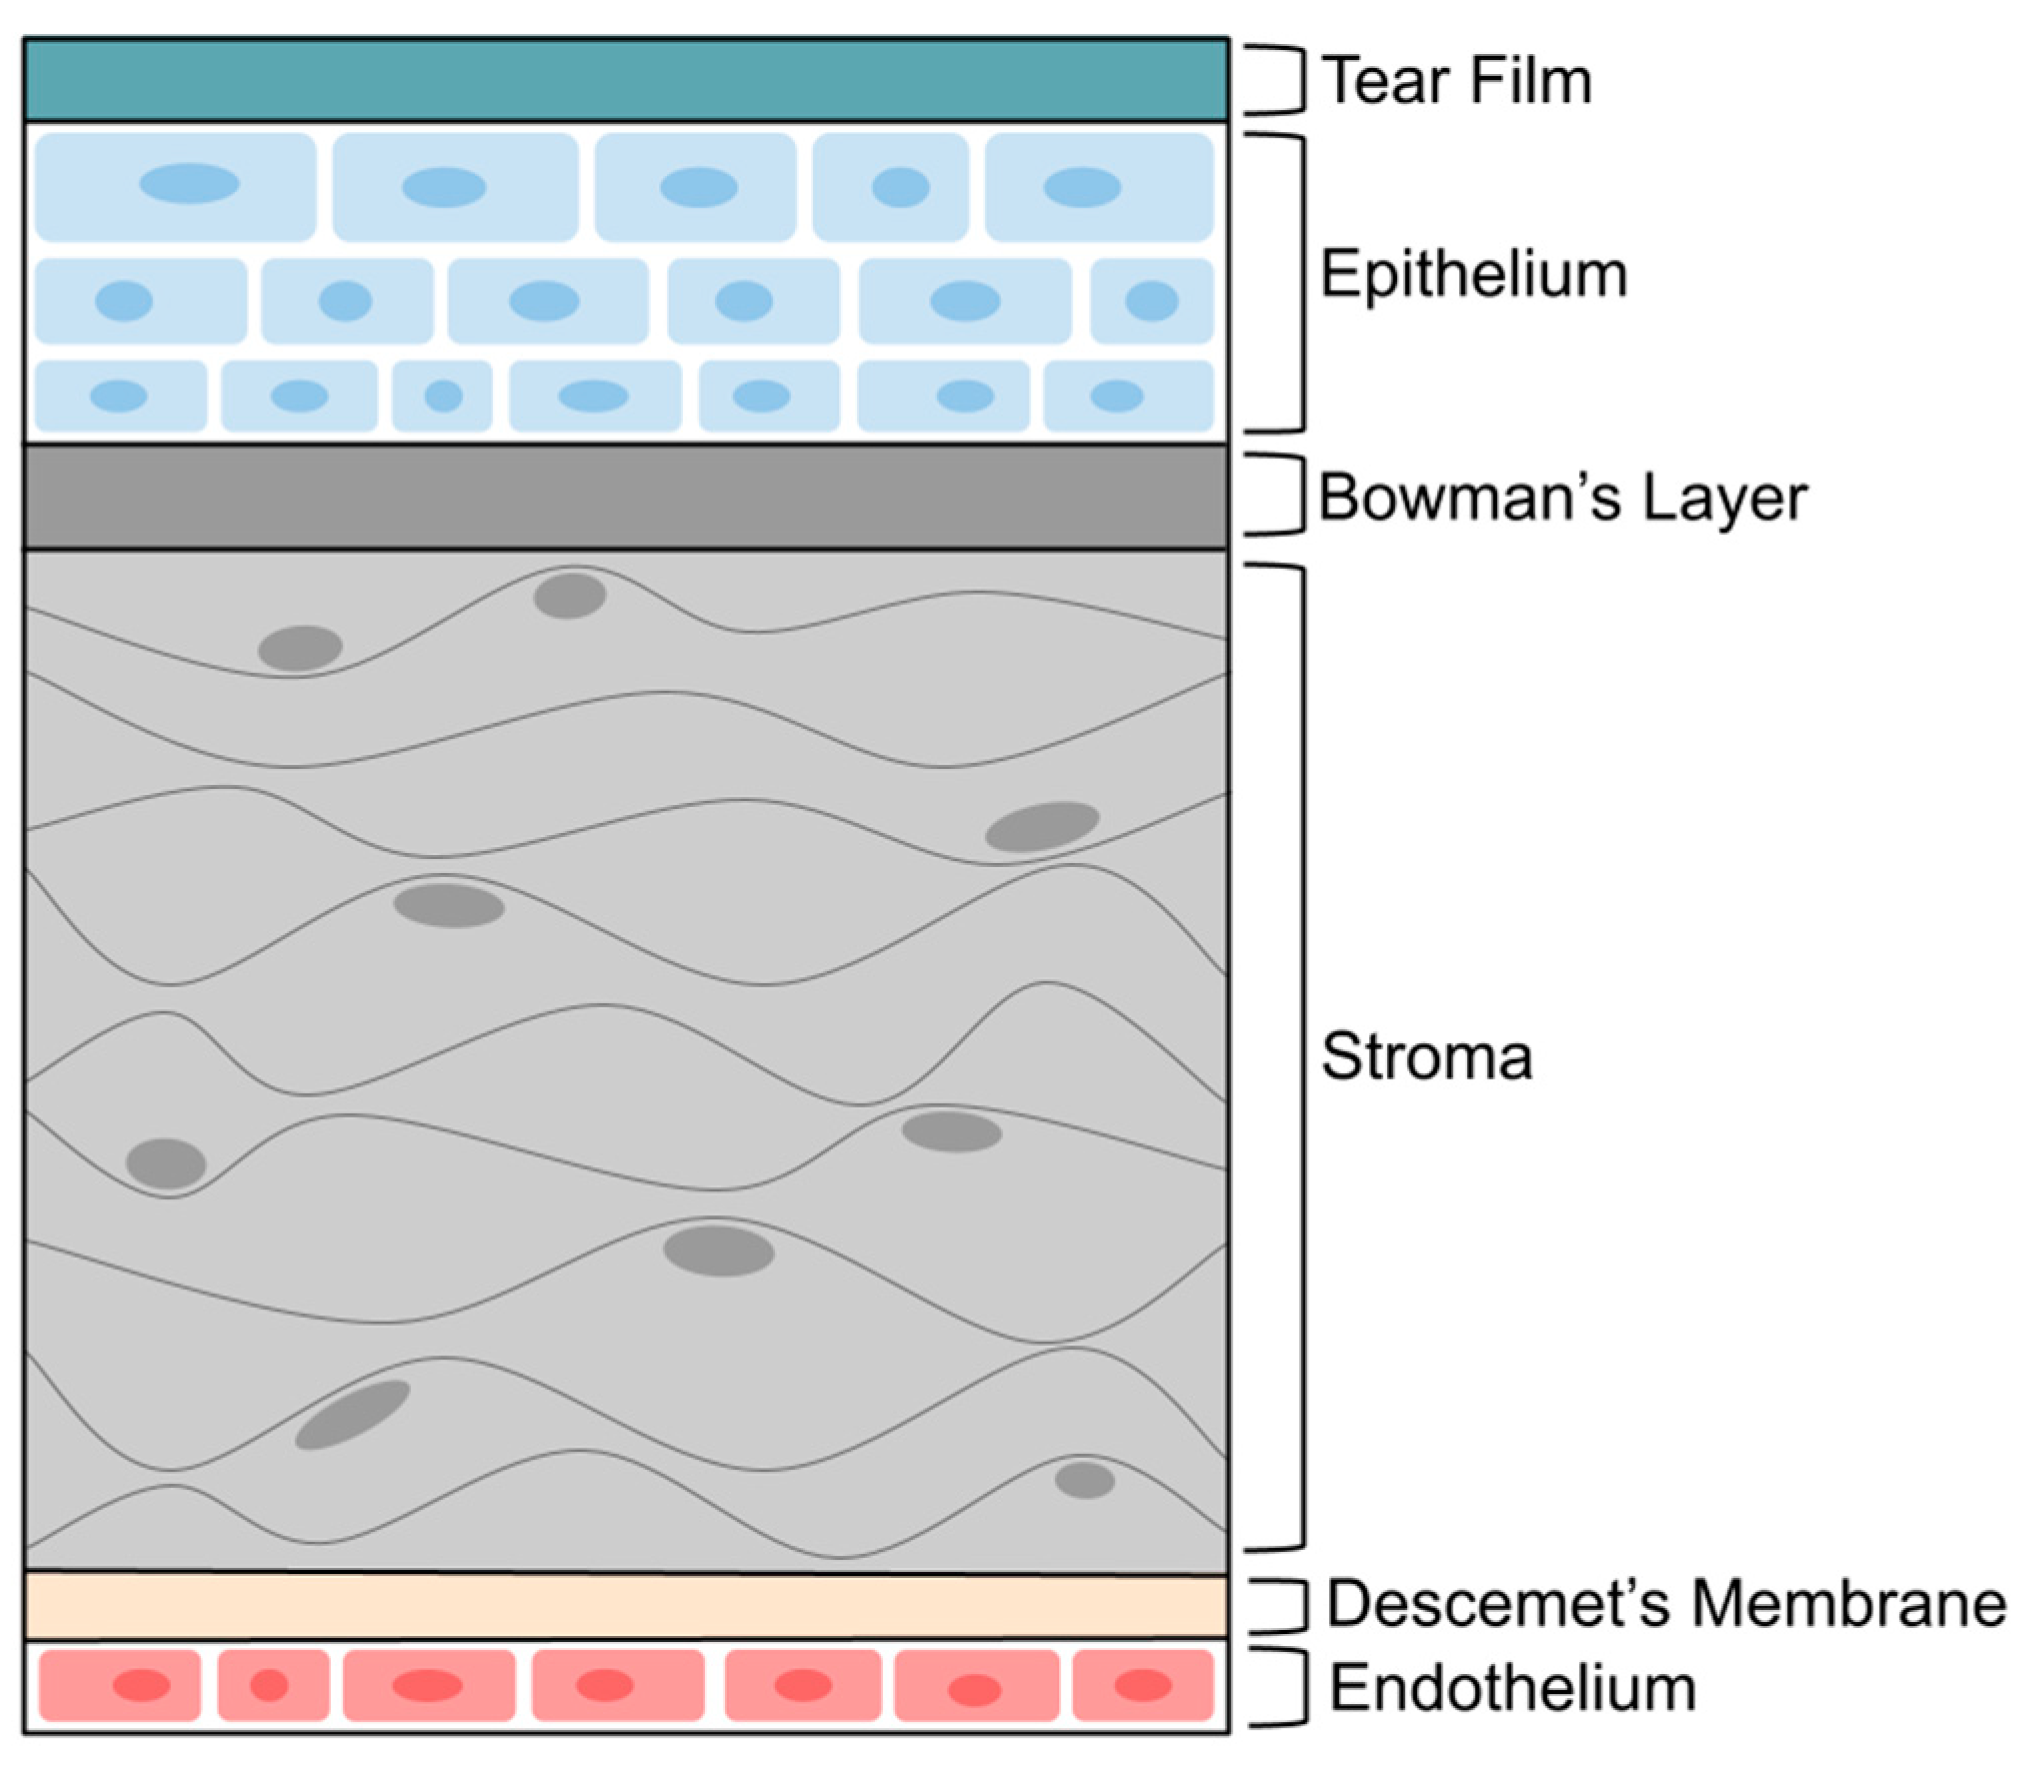
In recent years, ophthalmic drug delivery research has focused on improving the ability of drugs to penetrate the many biological barriers present in the eye [8]. These barriers, the most notable of which are the tear film and corneal barrier, represent a special challenge for topically administered ophthalmic drugs [9]. The tear film is the first barrier encountered by any drug applied topically to the eye; blinking and tear dilution cause rapid clearance and reduced bioavailability of drugs administered via this route. The tear film is composed of three layers: lipid, aqueous, and mucin; the mucin layer is the deepest and is most closely located to both the cornea and the conjunctiva [4]. As illustrated in Figure 1, the cornea itself is composed of an epithelial layer, the Bowman membrane, the corneal stroma, the Descemet membrane, and the corneal endothelium [10]. Each layer provides some type of anatomical or physiological support that is necessary to the function of the cornea; together, all these layers form a mechanical barrier that hinders microbial and foreign body penetration into the eye. Cornea protects the internal eye structures and is responsible for two-thirds of the refractive power of the eye by focusing light correctly on the retina. The corneal composition can be broken down into the cellular components: epithelial cells, keratocytes, and endothelial cells and the acellular components: collagen and proteoglycans. The permeability barriers of the cornea are the epithelium and stroma. The corneal structure is critically dependent on the dynamic maintenance of corneal hydrostasis to ensure proper hydration.
Figure 1.
Layers of cornea (prepared using Google drawings).
Starting at the outermost layer of the cornea, the corneal epithelium is transparent; non-keratinized; stratified; and is comprised of layers of squamous, basal, and wing cells [11]. These epithelial cells are connected to one another via tight junctions that prevent the entry of foreign materials or organisms into the cornea [10]. The epithelial layer is also the most anteriorly located layer of the cornea and is similar to the Descemet membrane in its ability to regenerate after disease, trauma, or desquamation. Structurally, the epithelial layer forms the outermost surface of the eye but is limited in its ability to grow or expand into deeper parts due to the basement membrane [11]. The main functions of the corneal epithelium include physical protection, refraction, radiation protection, tear stabilization, barrier protection, and mucous production [12]. Bowman’s layer is located on the posterior side of the basement membrane; the posterior side of the basement membrane projects collagen fibrils that interact with the surface of the stroma [13]. This layer does not act as a barrier to foreign objects, microbes, or drugs and does not regenerate post-injury. The function of Bowman’s membrane has often been a topic of debate, with many suggesting that it possesses some sort of barrier function; however, it is not clear what its main function is based upon the available literature. It is likely that Bowman’s layer is involved in or maintained by epithelial–stromal interactions [13]. The stroma is the largest layer of the cornea and is characterized by its transparency, avascularity, and other physical properties; it is responsible for providing the cornea with structural support. Keratocytes, which are most localized to the stroma, are responsible for the secretion of the extracellular matrix (ECM) [14]. The ECM is used to maintain hydration in the eye, modulate angiogenesis, and regulate intraocular pressure [15]. Keratocytes also cause a backscatter reduction of light, reducing the transparency of the cornea and producing soluble protein “crystallins”, which reduce the backscatter of light and maintain corneal transparency [16]. The Descemet membrane is the basement membrane of the corneal endothelium and anchors the endothelium to connective tissues. It is comprised of collagen and glycoproteins and lacks elasticity despite being mostly resistant to trauma, damage, or disease [4]. The Descemet membrane is involved in physiologic activities that maintain the corneal structure and homeostasis; it allows for molecular and nutrient transport, regulates corneal hydration, and maintains transparency [17]. The endothelium, which secretes the ECM forming the Descemet membrane, is comprised of a single cell layer, all of which are hexagonal in shape. The endothelium is responsible for maintaining the dehydrated state of the stroma that is necessary for transparency and unobstructed vision; this dehydrated state is maintained through ionic pumps on the endothelium’s basolateral plasma membranes [12].
3. Corneal Wound-Healing Processes
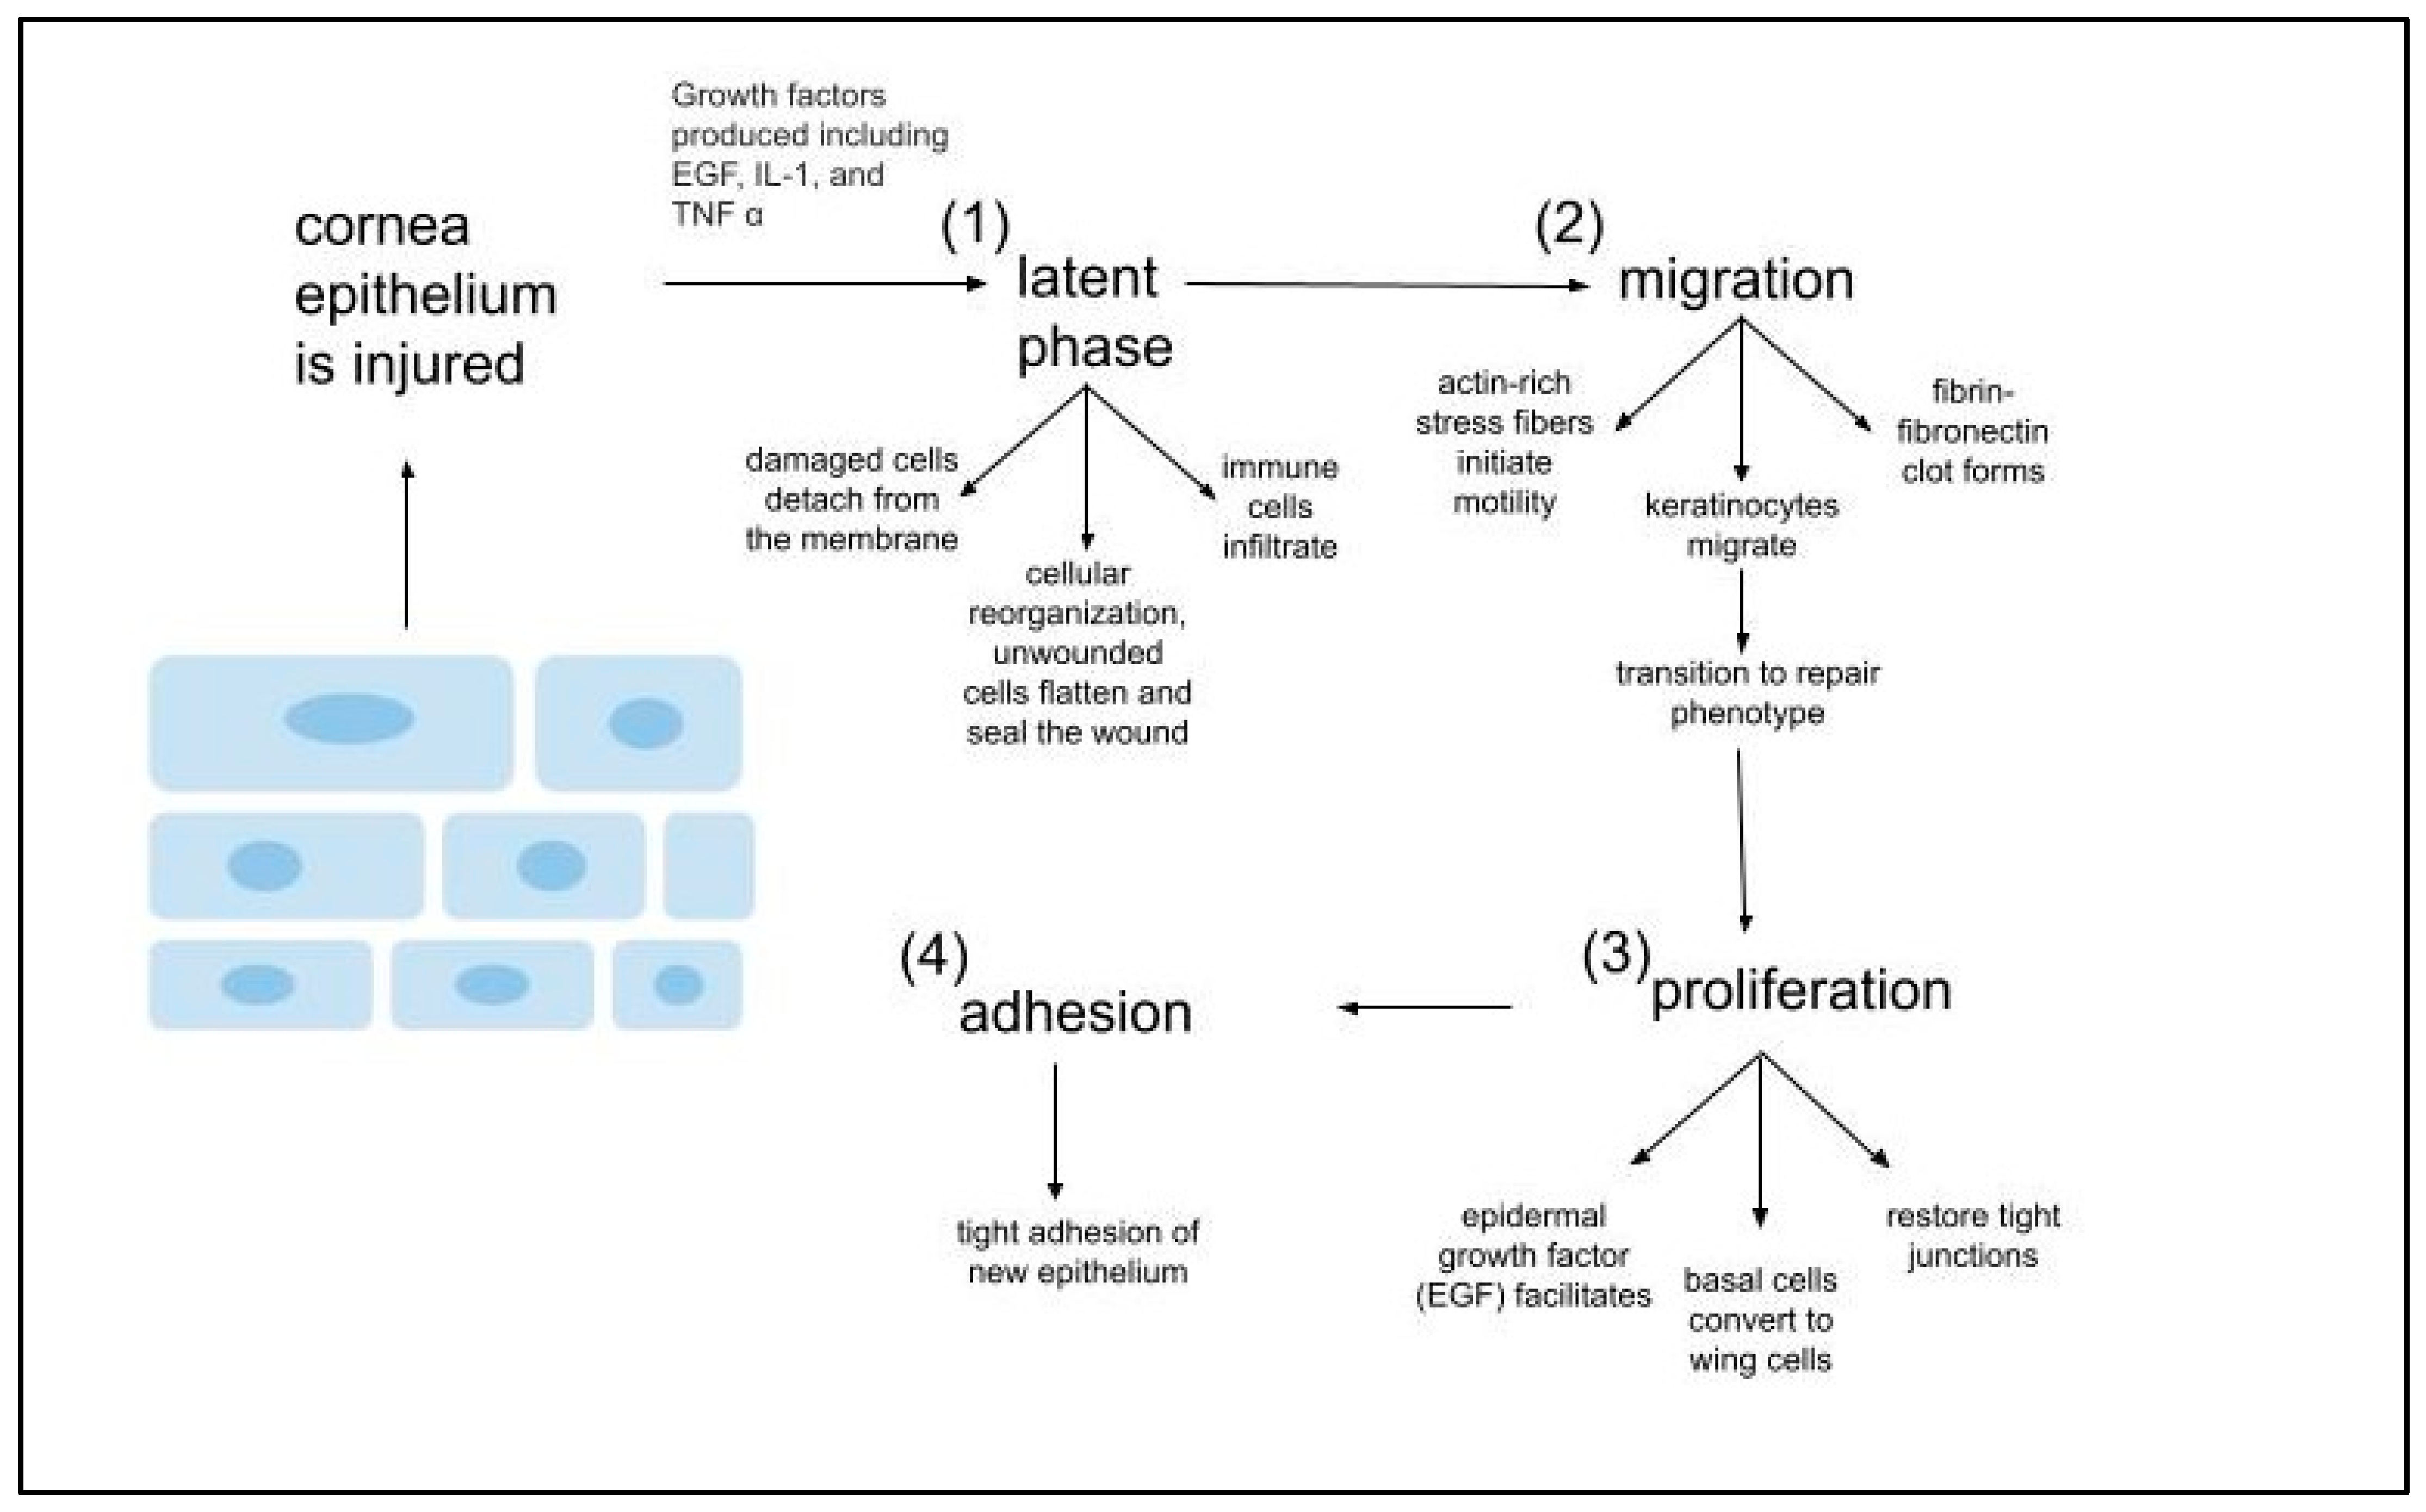
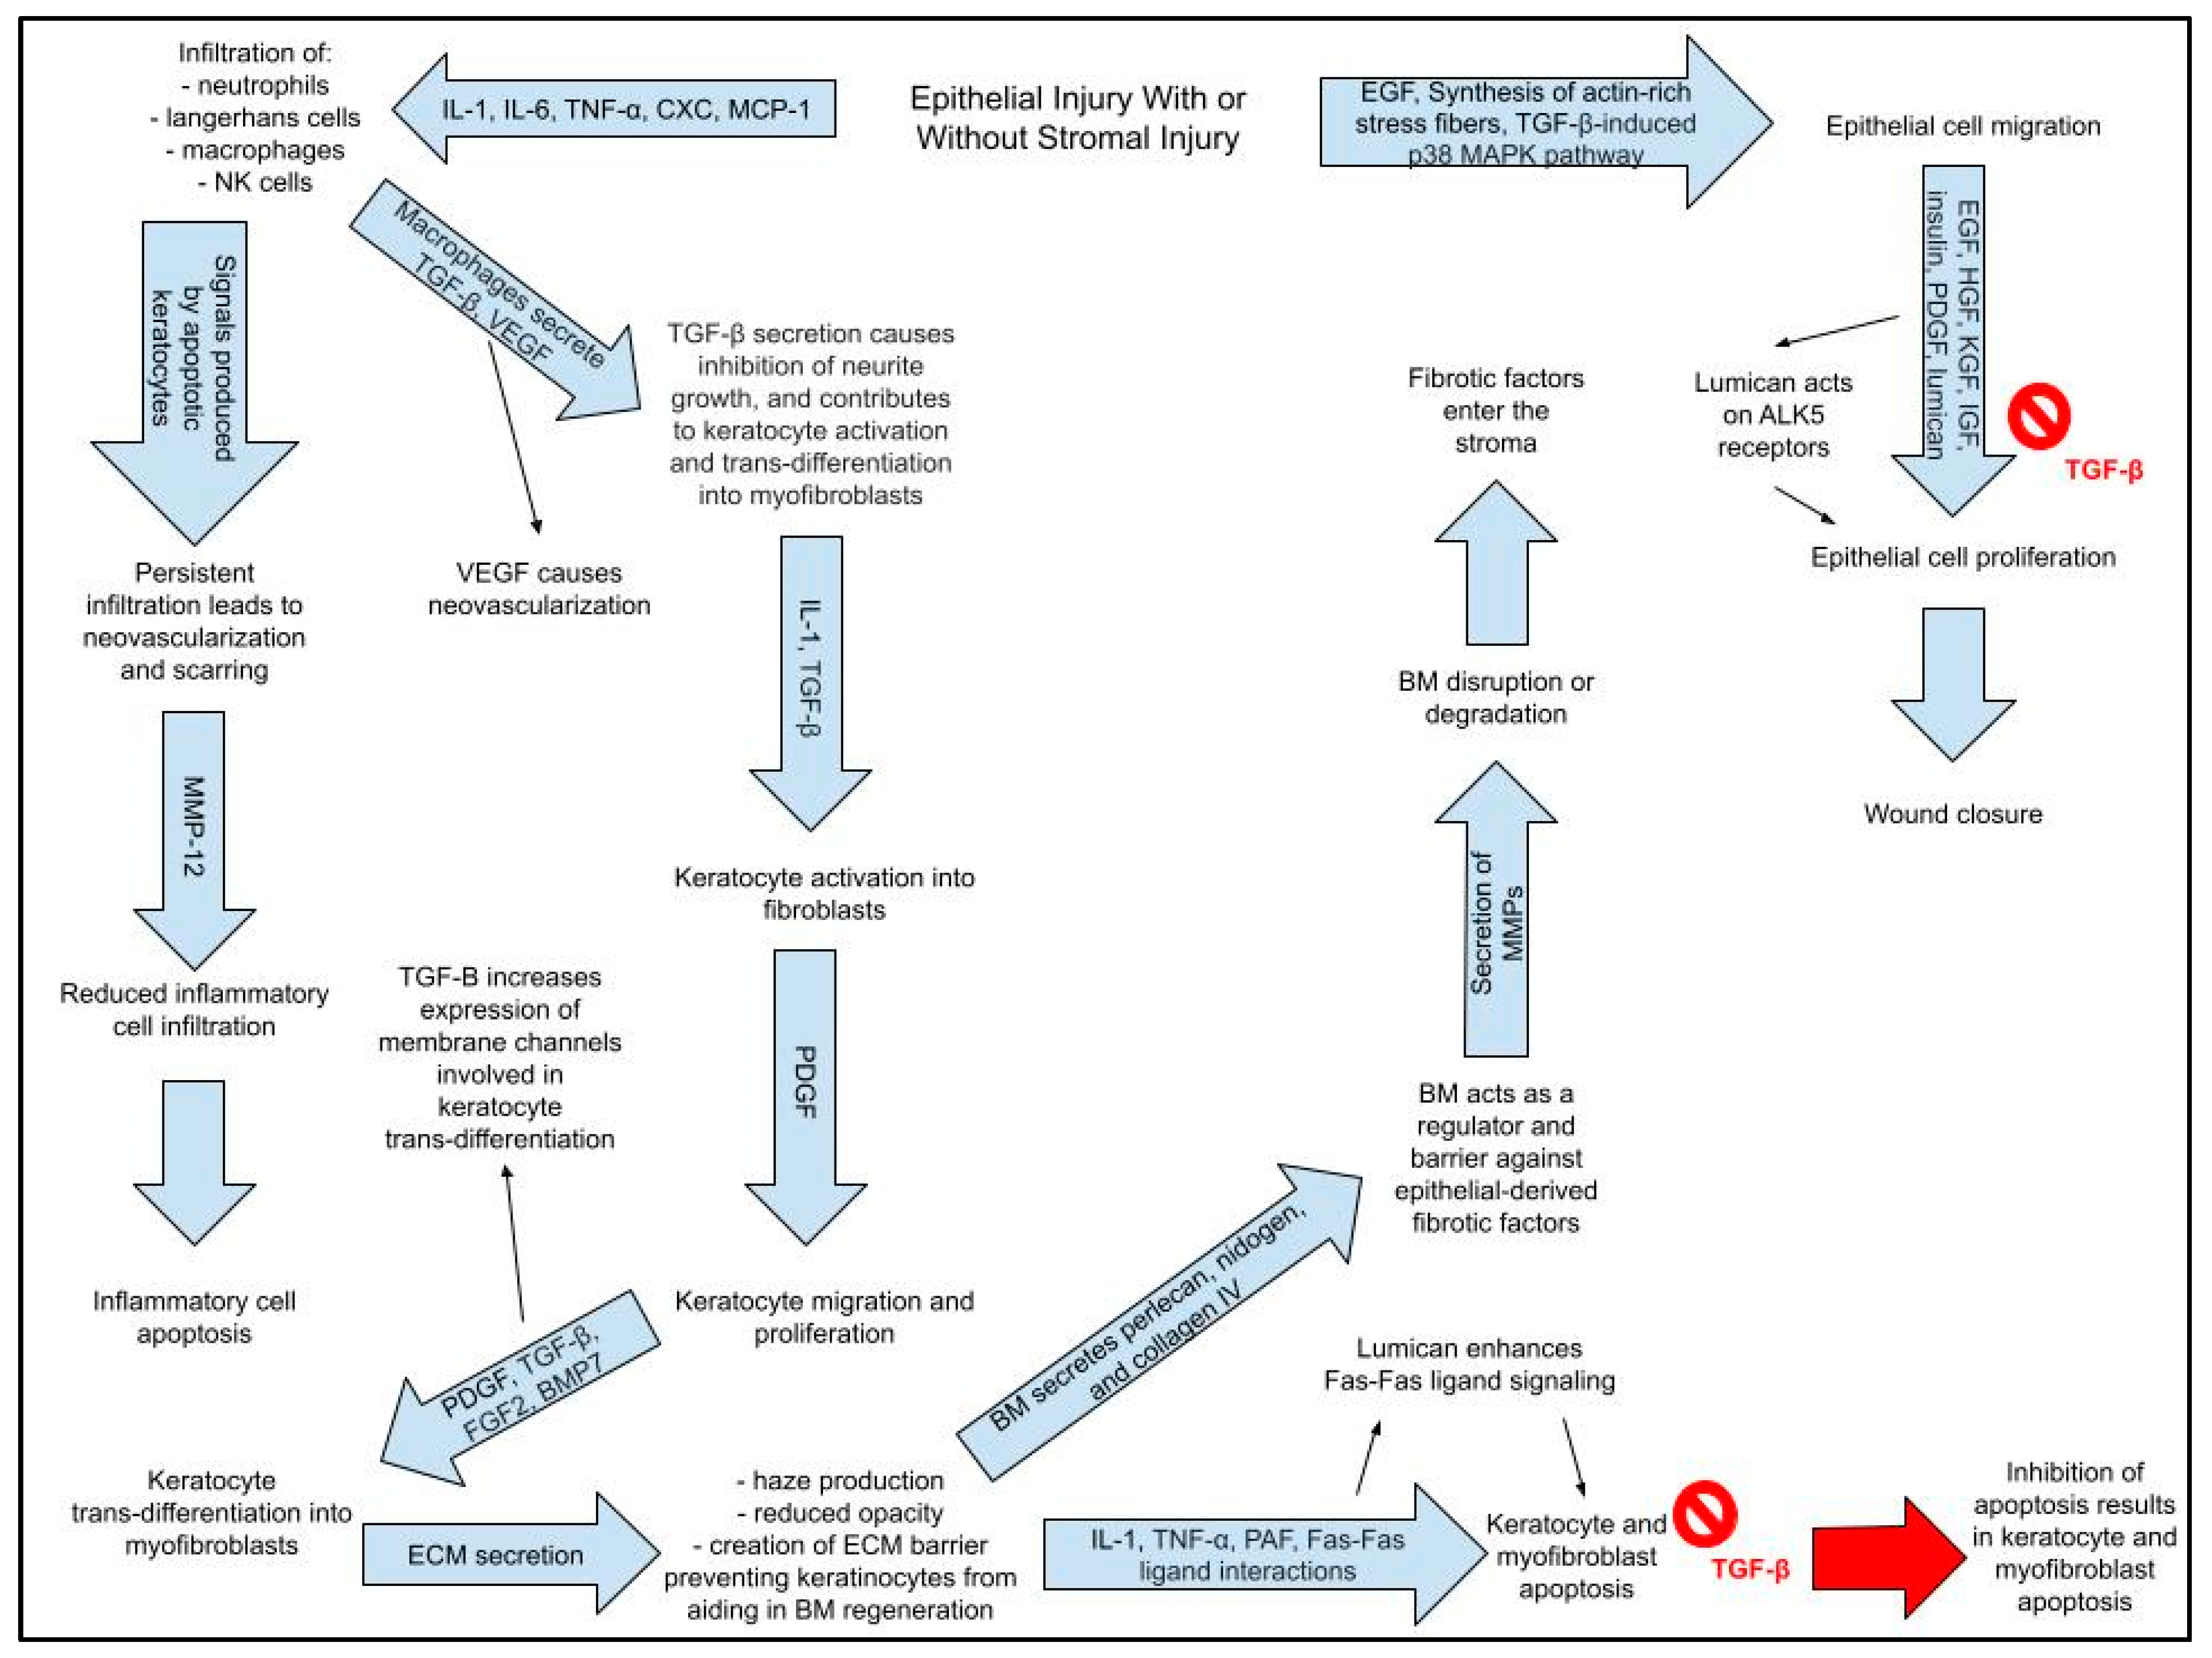
Corneal wound-healing is a critical process for restoring corneal integrity and maintaining vision after corneal injury/trauma. The aggressive inflammatory responses following ocular injuries and bacterial invasion often tend to impair corneal re-epithelization, which results in the loss of corneal transparency and impairment of vision [18]. When the cornea sustains an injury due to trauma, chemical attack, environmental damage, or infection to the eye, a wound-healing cascade is initiated to rapidly address the damage [1]. Most corneal injuries are superficial and occur at the most anteriorly located layers of the cornea: the epithelium and its basement membrane. The epithelium is the only layer of the cornea that possesses regenerative ability for both normal maintenance and injury. Corneal epithelium wound-healing is a multi-stage process described in Figure 2, which is separated into four phases: the lag or latent phase, the migratory, proliferation, and assembly of adhesion structures [19]. The phases occur chronologically but may overlap in time and cascade of inflammatory responses after cornel integrity is broken, described in Figure 3 and discussed in this section.
Figure 2.
Four phases of epithelial wound-healing (prepared using Google drawings).
Figure 3.
Cascade during corneal injury and inflammatory responses (prepared using Google drawings).
The latent phase of corneal epithelial wound-healing is responsible for conducting cellular reorganization. The cellular reorganization increases cellular motility and initiates the migratory phase so that re-epithelialization may take place [19]. During the migration phase, cell layers extend over the wound to maintain the cornea’s integrity; the migration of these corneal epithelial cells to the wound site is dependent on the synthesis of actin-stress fibers [20]. The purpose of the proliferative phase is to repopulate the wound site with corneal epithelial cells; both limbal and peripheral epithelial cells exhibit enhanced proliferation rates during this period [21]. The last phase of corneal epithelial wound-healing involves the formation of adhesion structures; cells on the epithelium’s basement membrane form hemidesmosomal attachments that secure epithelial structures to underlying connective tissues [20]. The formation of these adhesion structures results in wound closure. During the early phases of corneal epithelial wound-healing, many types of growth factors and/or cytokines are produced, such as epidermal growth factor (EGF), keratinocyte growth factor 1 (KGF-1), and hepatocyte growth factor (HGF) [19,22]. Stromal injury almost always coincides with injuries to the epithelium and basement membrane because of the stroma’s more posterior location. Within a few minutes of stromal injury taking place, keratocytes undergo apoptosis and/or necrosis that is triggered by an influx of interleukin-1 (IL-1) and tumor necrosis factor-alpha (TNF-α); the keratocytes adjacent to the injury proliferate and migrate [18,23]. These keratocytes will later be activated to become fibroblasts and will eventually transform into myofibroblasts [18,24]. Transforming growth factor (TGF)-β1, TGF-β2, and platelet-derived growth factor (PDGF) are responsible for the development of mature, alpha-smooth muscle actin (SMA)+ myofibroblasts; this myofibroblast phenotype secretes disordered ECM that contributes to corneal scarring, corneal opacity, stromal fibrosis, visual field defects and/or loss of visual acuity [24]. The ECM also acts as a physical barrier to keratocytes, preventing them from assisting in regeneration of the epithelial basement membrane. Myofibroblasts may also be responsible for the inhibition of neurite outgrowth; TGF-β contributes to sensory dysfunction via involvement in a pathway that inhibits nerve regeneration [18,25].
The Descemet membrane is similar to the stroma in that it lacks the ability to regenerate; because of this, keratoplasty is the only available method for healing wounds to the Descemet membrane and the corneal endothelium. It is thought that the endothelium’s reduced ability to self-heal can be contributed to lower rates of cell proliferation; thus, the endothelium relies on cellular migration and cell spreading to address any injuries [21]. Cell migration is stimulated by several ECM proteins, growth factors, and cytokines. As endothelial cells migrate, they begin to exhibit a fibroblastic phenotype through the expression of alpha-smooth muscle actin and the loss of tight junction proteins; the fibrotic changes produced by this transition can contribute to the formation of a retrocorneal fibrous membrane [21].
Why stromal regeneration and EBM restoration are important: ultrastructural studies have demonstrated that defective epithelial basement membrane (EBM) regeneration after injury to the cornea underlies the development of myofibroblasts that become established in the anterior stroma. These myofibroblasts often persist for months or years after the injury and are responsible for opacity. Therefore, full regeneration of the stroma is essential to maintain the transparency and to restore the EBM [18]. Since the corneal stroma is avascular and has a low keratocyte density, it could be healed by the exosomes, while subjected to in-depth investigations. The steps of a stromal wound-healing cascade are explained separately in Box 1 and explained with help of nine steps.
Box 1. Steps of a stromal wound healing cascade.
- (1)
- Stromal injury
- (a)
- Stromal injury involves epithelial injury.
- (b)
- Epithelial injury + damage to basement membrane → stromal haze
- (i)
- Stromal haze → scarring, opacity → reduced transparency
- (c)
- Epithelial Healing Cascade
- (i)
- Upon injury, epithelial cells proliferate.
- (ii)
- Actin-rich stress fibers initiate migration to the wound
- (iii)
- Generation of adhesion structures that anchor the regenerated epithelium to the underlying connective tissue.
- (d)
- Epithelial healing cascade is regulated by GFs and cytokines, which primary function is to mediate interactions corneal epithelium and stroma via the basement membrane. These interactions lead to keratocyte apoptosis, keratocyte activation, and keratocyte trans-differentiation into myofibroblasts.
- (2)
- IL-1, TNF-α, PAF, and Fas–Fas ligand interactions cause immediate apoptosis of keratocytes beneath corneal epithelium within the zone of injury.
- (a)
- Apoptosis causes infiltration of inflammatory cells via release of IL-1, IL-6, TNF-α, CXC chemokines, and MCP-1 (macrophage chemotactic protein-1) released from epithelial and stromal cells
- (3)
- Some keratocytes undergo necrosis.
- (4)
- Other keratocytes near the area of necrosis/apoptosis proliferate, migrate, and undergo activation into fibroblasts.
- (5)
- Fibroblasts have the potential to transform into myofibroblasts.
- (6)
- Fibroblasts and myofibroblasts secrete a provisional matrix scaffold.
- (7)
- Epithelial and stromal cells secrete chemokines, which triggers an influx of inflammatory cells;
- (a)
- Inflammatory cells clear apoptotic and necrotic (#2 and #3) debris.
- (8)
- Epithelial cells, inflammatory cells, fibroblasts, and myofibroblasts secrete collagenolytic metalloproteinases that cause stromal repair and remodeling
- (9)
- Resorption of abnormal ECM and apoptosis or reversal of myofibroblast phenotype restores normal form and function of the stroma.
4. Exosomes for Preserving Cornea
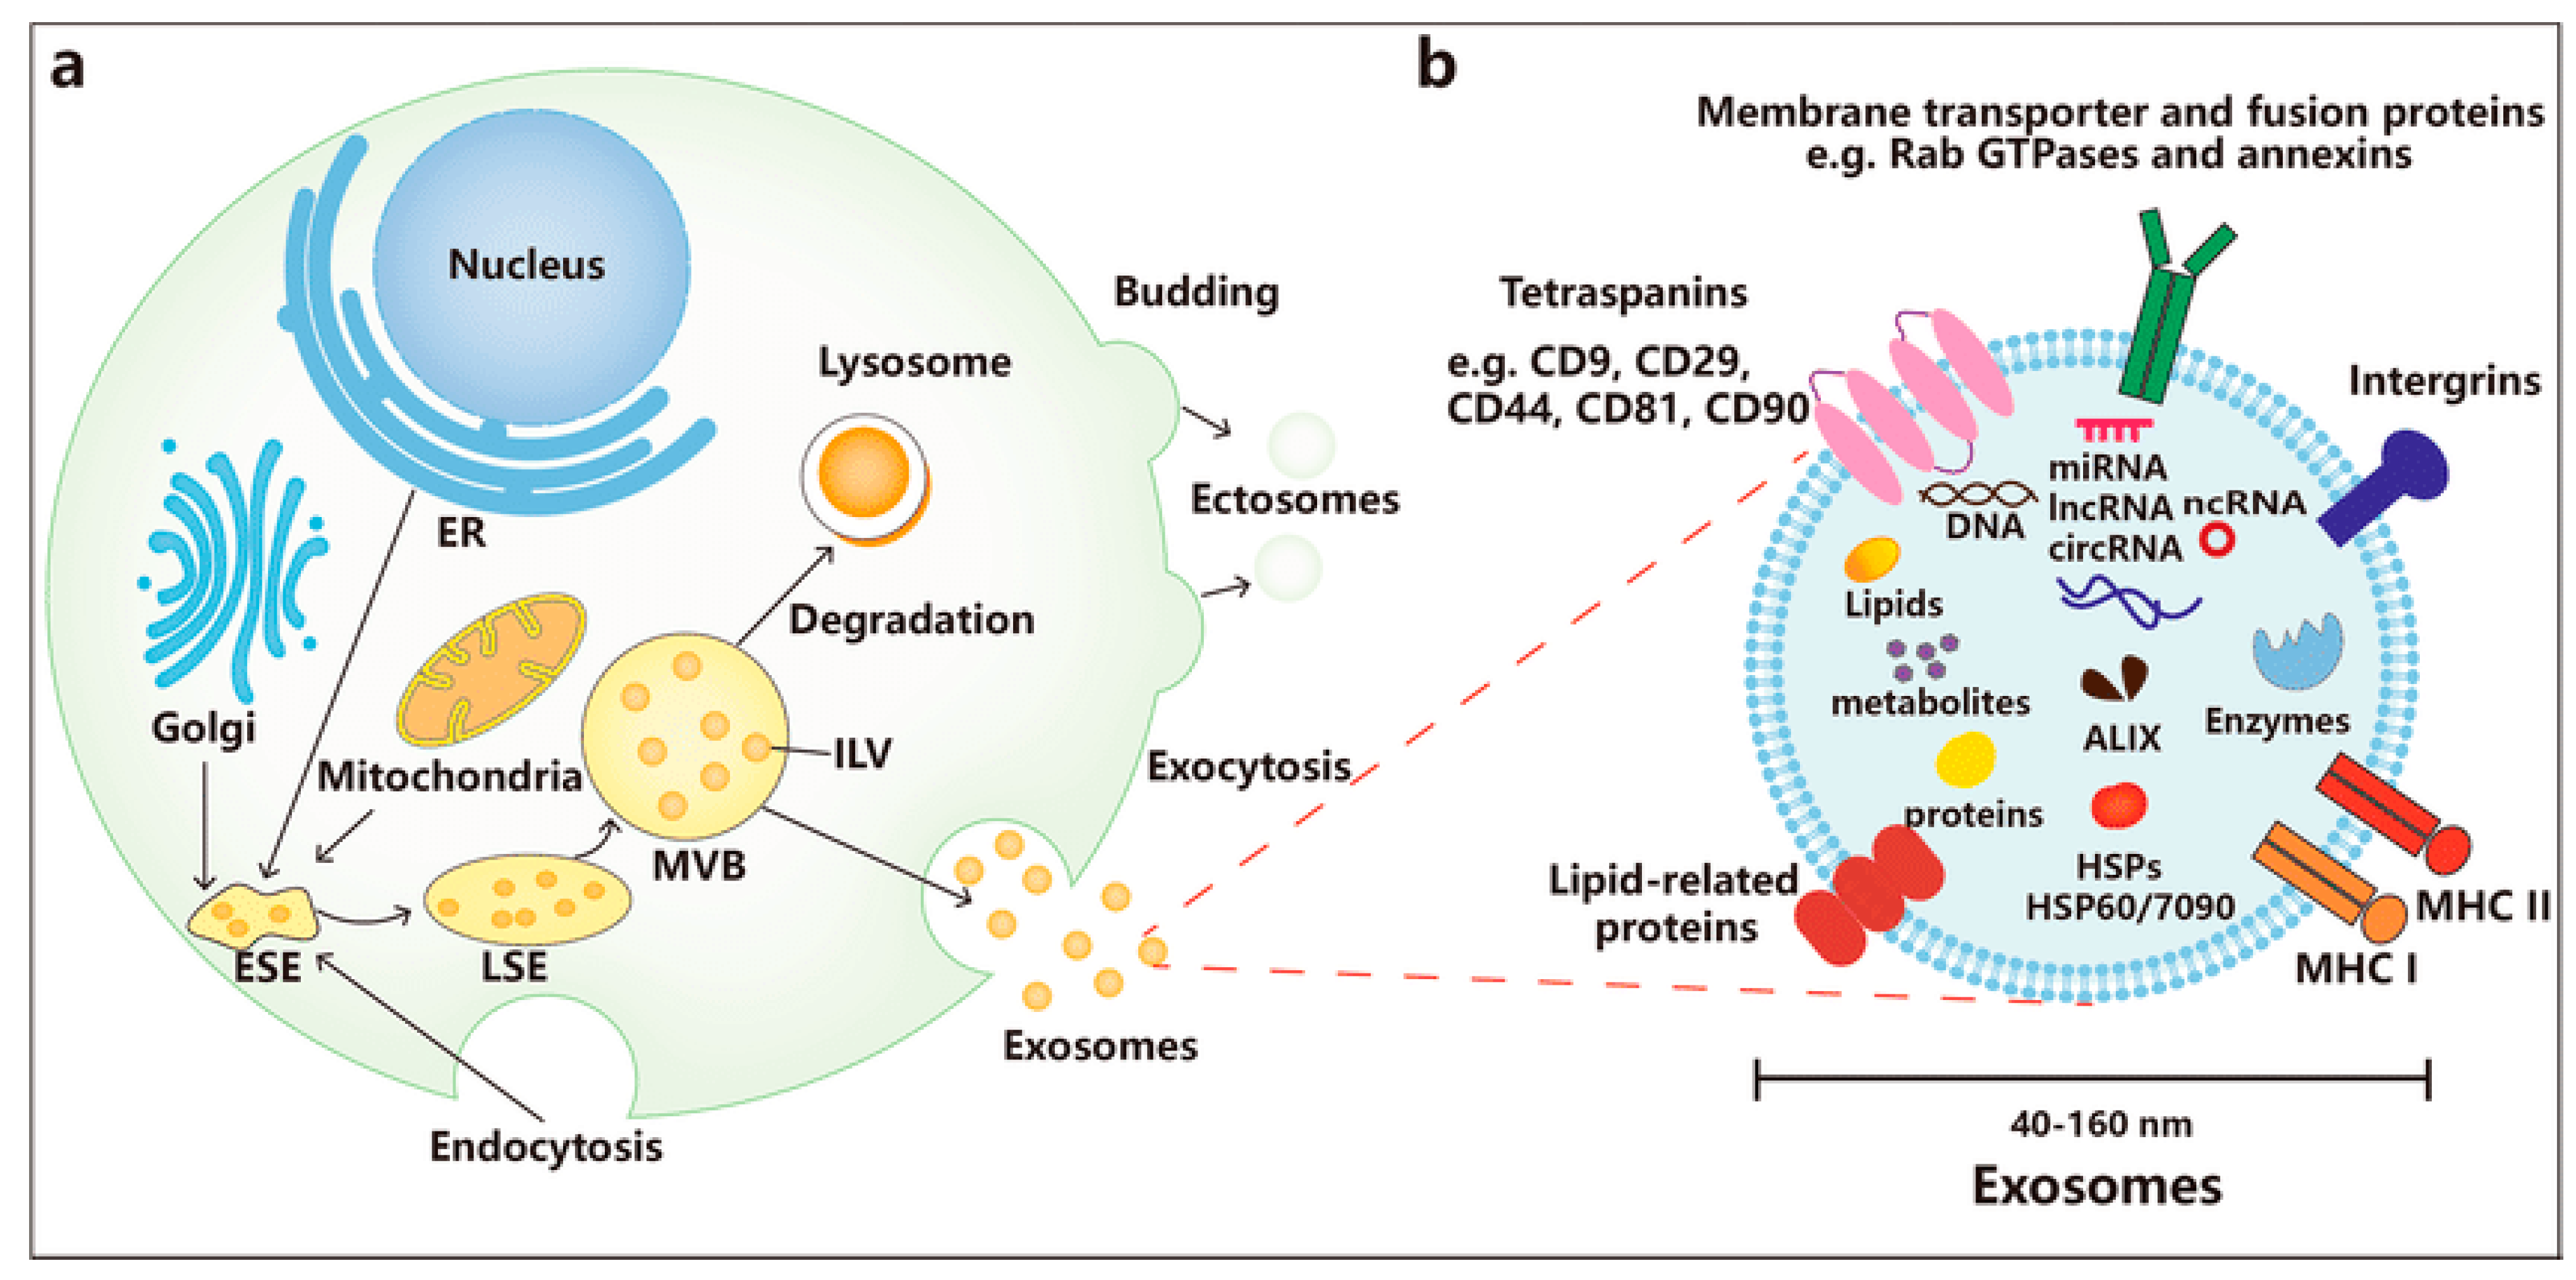
The vast majority of cells constantly discharge EVs to the extracellular environment to engage in different biological functions. There are two distinct biogenesis processes for EVs: (1) created naturally by breaking from the plasma membrane; (2) generated when the multivesicular body (MVB) fuses with the plasma membrane. Exosome biosynthesis is a continuous, endosomal-dependent cytological process [26], illustrated in Figure 4. While the initial endosomes created by cellular membrane invagination develop into late endosomes, intraluminal vesicles (ILVs) gather in the lumen. Specific-sorted ILVs, including lipids, proteins, and cytosol, are produced by internal splitting of the initial endosomal membrane. Multivesicular endosomes (MVEs), often called MVBs, are the terms used to describe late endosomes that include ILVs. The MVB in cells has two possible outcomes. These include MVB fusions with lysosomes, which destroy what they carry, and MVB fusions with the membrane of the plasma cell, which discharge ILVs into the external milieu as exosomes [7,26]. Chiefly, they are mediators of cell-to-cell communication through the transport of signaling molecules. Pertaining to the cornea, exosomes are being studied as non-invasive, natural drug delivery systems for cornea wound-healing, repair, and stromal regeneration. Currently, exosome drug delivery systems have been investigated as alternatives to surgical corneal transplants. In cornea, exosomes mediate communication between the epithelium, stroma, and endothelium. A study analyzed and characterized the production of exosomes by different cell types in the human cornea using exosome biomarkers: CD9, CD63, and CD81, where CD63 is the most used biomarker. The uptake of exosomes enriched with Human corneal epithelial cells (hCECs), corneal fibroblasts (hCFs), corneal endothelial cells (hCEnCs) was monitored [27].
Figure 4.
Biogenesis of MSC-derived exosomes. (a) comprises of endocytosis, MVB formation, and exosomes secretion into the extracellular environment through merging with the plasma membrane. (b) represents contents and characteristics of exosomes carrying a variety of substances such as proteins, lipids, nucleic acids, metabolites [26].
5. Immunogenicity and Toxicity of Exosomes
The eye, an immune-privileged organ, can typically withstand the introduction of antigens or other foreign materials without incurring a compensatory immune response. This evolutionary adaptation protects the eye from damage caused by inflammation, scarring, etc. The role exosomes play in immunologic responses has been studied extensively; although, much of this research has focused on the immunomodulatory effects they may exert in cancer. Little research has been conducted regarding the potential toxic effects of exosomes on ocular tissues [28,29]. Exosomes derived from human sources are natural, nanosized, intercellular communication systems and are normally non-immunogenic and do not typically illicit a direct immune response. Most studies examining the effects of exosomes as a potential treatment for corneal disease and injury have found that they tend to inhibit undesirable immune responses, such as inflammation, scarring, fibrosis, and so on. However, this does not mean that exosomes have no immunogenic potential. Research has shown that exosomes sourced from human sources can elicit inflammatory responses in animal models [30]. This finding suggests a need for further research on the immunogenicity of exosomes when used in cross-species models. However, it has long been assumed that, due to exosomes’ inability to accumulate for long-term periods in tissues and organs, they exhibit minimal toxic effects [31]. This characteristic can be attributed to exosomes’ lack of systemic toxicity, but that does not mean that they are not able to exert local toxic effects. The local toxic effects, however, seem to only be exerted by exosomes that have been modified to encapsulate a potentially toxic substance or biologic molecule, by exosomes with modified protein content or cellular surface proteins, or by exosomes that are secreted from damaged or diseased cells [32]. The encouraging results from kidney allograft survival [33] and improved islet transplantation [34] suggest that exosomes from specific immunosuppressive cell populations serve as a potentially effective tool to promote immune tolerance in corneal graft survivals.
6. Exosomes Combined with Other Therapeutic Approaches
Exosomes are being recognized for their potential as delivery vehicles for a wide array of therapeutics, including hydrogels, gene delivery, biologic drugs, secretome from stem cells, etc. Table 1 summarizes several investigations on exosomes-based cornea treatment.
6.1. Exosomes with Hydrogels
Hydrogels are crosslinked polymeric networks exhibiting hydrophilic interactions with water molecules. Their hydrophilic and flexible properties make them an ideal drug delivery system and have been used to administer exosomes both in vitro and in vivo to ocular tissues [35]. Hydrogels offer several advantages, including adjustable mechanical behavior, cytocompatibility, and optical characteristics that make them suited for corneal regeneration and restoration [36]. Various kinds of biological and synthetic hydrogels, such as collagen/gelatin/alginate [37], collagen/hyaluronic acid [38] chitosan [39], and collagen/polyethylene glycol [40,41], have been used for corneal wound-healing [42]. There are three main strategies to incorporate exosomes into hydrogels [43]: (a) incorporate exosomes into the polymer solution before adding crosslinkers to the gel composite; (b) using a swelling/“breathing” approach, physically insert exosomes into pre-formed hydrogels; (c) combine exosomes and polymers, along with crosslinkers in real time for in situ gelation. Hydrogels are designed to dissolve when epithelial cells glue over the exposed stroma, preventing vision from being obstructed for an extended length of time. If the undamaged corneal epithelium needs to be protected from the start of medication, the exosome-loaded film/hydrogel shall be inserted intrastromally [44]. Tang et al. [45] developed an exosome-loaded thermosensitive hydrogel to regenerate the corneal epithelium and stroma. The exosomes used were derived from induced pluripotent stem cell-derived mesenchymal stem cells (iPSC-MSCs) and were combined with a chitosan-based, thermosensitive hydrogel that exhibited matrix-type release kinetics. The group’s in vivo study determined that the exosome-loaded thermosensitive hydrogel downregulates expression of the mRNA encoding collagens produced in the stroma, thus preventing ECM deposition during or after corneal injury. Through this mechanism, the hydrogel effectively reduces scarring, leading to corneal opacity, and accelerates the overall healing process. Additionally, the exosomes derived from iPSC-MSCs contained miR-432-5p, which is involved in the suppression of a modulator involved in the biosynthesis of collagen, further reducing ECM deposition and the risk for corneal opacity in their in vivo rat model [45]. Sun et al. [46] recently demonstrated that a miRNA-rich exosome-loaded thermosensitive hyaluronic acid-based hydrogel can promote corneal epithelial cell (CEC) migration and repair both in vitro and in vivo. Exosomes from adipose-derived mesenchymal stem cells were loaded into a functionalized, DEGMA [di(ethylene glycol) monomethyl ether methacrylate]-modified hyaluronic acid hydrogel and studied for ocular chemical alkali burn. In vivo, exosomes were used as a carrier for miRNA 24-3p and applied topically to rabbit corneal epithelial wounds. The formulation promoted corneal epithelial wound-healing, as well as the inhibition of corneal fibrosis and keratitis. The ocu-miRNA 24-3p (miRNA 24-3p)-rich exosome-loaded hydrogel showed novel effects in promoting corneal wound closure in vivo in rabbit corneal epithelial cells [46].
6.2. Exosomes with Gene Therapy
Gene delivery has been viewed as an emerging therapy to treat corneal opacity by delivering genes of interest via low immunogenic EVs. Zhao et al. observed that exosomes loaded with c-Rel-specific siRNA, a siRNA targeting the c-Rel member of the NF-KB family involved in the regulation of inflammatory responses, can effectively accelerate the healing of both regular and diabetic corneal wounds in vivo [47].
A study conducted by Shojaati et al. examined the effects of MSCs from corneal stromal stem cells (CSSCs) and their secreted EVs/exosomes on corneal fibrosis and inflammation. CSSCs produced EVs 130–150 nm in diameter, which expressed surface proteins used to classify EVs (CD63, CD81, and CD9). However, the EVs themselves produced similar effects to the CSSCs, in regard to reducing visual scarring in murine models. This effect was achieved by decreasing the expression of the fibrotic genes Col3al and Acta2, reduced neutrophil infiltration, and restoration of the corneal tissue morphology. This study also examined the importance of the PDCD6IP (Alix) gene in upregulating regenerative function and reducing corneal scarring, which was discerned by utilizing siRNA to knock down the mRNA encoding for Alix. The group’s in vivo studies determined that CSSC-derived EVs reduced corneal scarring, preserved the cornea’s morphology, and reduced early neutrophil infiltration [48].
6.3. Stem Cell-Derived Exosomes for Corneal-Related Investigations
Currently, the majority of exosomes incorporated into ophthalmic drug delivery systems are produced from mesenchymal stem cells (MSCs). These hematological cells, often sourced from bone marrow and birth-associated tissue types, differentiate into many types of connective tissues in the body, including cartilage, bone, skeletal muscle, and adipose tissue [21]. MSCs are a widely studied source of exosomes due to their simple isolation, abundance, and ability to be easily biochemically modified, as well as their ability to produce enormous amounts of exosomes [21]. In vitro and in vivo studies on the eye have shown that MSCs are able to differentiate into keratocytes and other corneal stromal cells. Keratocytes, mesenchymal-derived cells of the corneal stroma, can revert to their repair phenotype and respond to ocular injury. Unlike stem cells, using only the exosomes from stem cells for regenerative medicine eliminates some of the biosafety risk that is associated with stem cell therapy [49]. Carter et al. examined the effects of the bone marrow-derived MSC paracrine factors on corneal fibroblast cells in vitro and ex vivo. One of the experimental groups included MSCs co-cultured with electrospun fibers, which displayed a faster wound closure rate than other experimental groups in vitro. In an ex vivo study, MSCs alone and the MSC-electrospun fiber co-culture exhibited similar rates of wound closure and reduced corneal opacity but still surpassed that of the control group. However, the MSC-electrospun fiber co-culture did exhibit higher cell viability [50].
Exosomes are also recognized as a vital player within every cell’s secretome, which is a term used to describe the whole of a cell’s secreted messenger substances. Secretomes include a wide array of EVs, such as microvesicles, membrane particles, peptides, and small proteins, like cytokines [51]. The secretomes of MSCs have been widely studied, with many promising results regarding their anti-inflammatory and anti-angiogenic properties. A study conducted by Kyung-Sun et al. [41] examined the effects of the MSC secretome by utilizing topically applied MSC-loaded PEG–collagen hydrogels on alkali-burned rabbit corneas in an ex vivo model. The groups containing MSCs alone and MSCs encapsulated in hydrogel both accelerated wound closure, reduced stromal haze formation, reduced corneal opacity, and facilitated epithelial healing. However, the group containing the MSCs encapsulated in hydrogel produced slightly more remarkable results regarding reductions in corneal haze. The delivery of MSCs and their secreted paracrine factors alongside novel biomaterials describes the effects of a lyophilized MSC secretome delivered via a viscoelastic gel carrier on both mechanical injury and alkali burn injury to the cornea both in vitro and in vivo. The in vitro study determined that the formulation increased HCEC proliferation, which was exemplified by increases in cell metabolic activity and DNA concentration. For an in vivo study utilizing a mechanical wound model in rat corneas, the MSC secretome viscoelastic gel increased the rate of re-epithelialization. However, in the in vivo studies utilizing a corneal alkali burn model, the gel enhanced re-epithelialization while also reducing scar formation and hemorrhage. For both the in vitro and in vivo studies, upregulation of the CD44 receptor was observed, suggesting that the effects of the formulation may be dependent upon interactions with the receptor [52]. Another study examining the effects of secretome derived from TNF-a stimulated MSCs in an in vivo mouse model designed to replicate corneal limbal stem cell deficiency (LSCD) induced by an alkali burn injury. LSCD is a condition characterized by corneal conjunctivalization, vascularization, recurrent corneal erosions, and corneal opacity and/or blindness. By pre-treating the MSCs with TNF-a prior to administration, the group stimulated the MSC’s immunosuppressive function involving a variety of soluble factors. A concentrated, conditioned medium containing the MSC secretome was applied topically to the eye for 4 weeks and suppressed alkali-induced epithelial cell damage, as well as corneal neovascularization and inflammation [53]. An et al. examined the effects of the MSC secretome and the specific role of exosomes in induced wound-healing effects. This study emphasized the importance of a MSC’s secreted cellular messengers in their overall wound-healing effect. When two experimental groups were compared, one including MSC EVs and one considered to be EV-depleted, the group still possessing the ability to secrete paracrine factors had an increased rate of cell proliferation and a dose-dependent promotion of wound-healing in vitro. Upon conducting the in vivo studies, this same dose-dependent promotion of wound-healing was observed in the EV-proficient group, which was determined to be dependent upon the EV fraction utilized [54].
Table 1.
Exosome-based cornea-related investigations.
7. Clinical Trials
Human-derived exosomes have more detailed findings in clinical trials compared to plant-based exosomes, though both types of investigation have been documented in clinical studies. A prospective clinical trial on dry eye was conducted to determine if miR-204-loaded exosomes may relieve graft-versus-host disease-associated (GVHD) dry eye disease, utilizing exosomes derived from MSCs. The results showed 28 eyes with refractory GVHD dry eye disease exhibited substantial relief after MSC-exo treatment, showing reduced fluorescein scores, longer tear film breakup time, increased tear secretion, and lower OSDI scores. These exosomes were administered as eye drops and suppressed inflammation while also improving epithelial recovery in both mice and humans. A miRNA called miR-204 is the main immunomodulatory cargo in MSC-exo. MiR-204 specifically targeted the interleukin-6 receptor (IL-6R) to inhibit the expression of the IL-6/IL-6R/Stat3 process, causing inflammatory M1 macrophages to change to the immunosuppressive M2 phenotype on the corneal surface [74].
NCT04213248 aims to determine whether umbilical mesenchymal stem cell (UMSC)derived exosomes could alleviate dry eye symptoms in patients with chronic graft-versus-host disease. In this study, the effect of UC-MSC-Exo will be tested on 27 participants between the ages of 18 to 70 years. Participants will be administered artificial tears for 2 weeks, followed by UC-MSC-Exo at 10 μg/drop four times a day for 2 weeks. Participants will be followed up on for 12 weeks to measure the dry eye progression. The primary endpoint will be a change in Ocular Surface Disease Index (OSDI) score, and secondary endpoints include tear secretion, tear break time, areas stained by fluorescent, ocular redness, tear meniscus, and best-corrected visual acuity post-treatment [75].
In a phase II clinical trial (NCT03687632), the effects of a multi-cytokine-containing, novel secretome formulation were evaluated for the treatment of persistent corneal epithelial defects caused by a wide array of underlying diagnoses. The secretome itself was derived from amnion-derived multipotent progenitor (AMP) cells and was administered via an ophthalmic drop formulation. All 12 patients evaluated in the study showed re-epithelialization and, for 41.7% of the patient population, total wound closure by the end of a 28-day treatment. Preclinical in vitro and in vivo studies of the formulation, dubbed ST266, also examined the anti-inflammatory and neuroprotective properties of the formulation [76].
8. Future Perspective, Opportunities, and Challenges
With continued advancements in exosome investigations, it may assume a pivotal role in corneal disorders and injuries and in the future of regenerative ophthalmology. Here, we summarize the recent, ongoing, and continued perspectives on ocular-based exosomes drug delivery in multiple directions. Advanced exosome engineering and customization: Molecular engineering is expected to enable the exact tailoring of exosome cargo to target specific ocular tissues. Methods such as surface modification or functionalization may allow exosomes to transport elevated levels of anti-fibrotic drugs, growth factors, or particularly miRNAs, thus amplifying their healing effects [77,78,79]. Integration with stem cell and gene therapy: Exosome-based delivery systems offer a precise and efficient method for gene modulation, enhancing regenerative outcomes in corneal and other ocular tissues. These engineered exosomes encapsulate gene-editing tools, like CRISPR-Cas9 [80] and siRNAs, facilitating targeted delivery and overcoming traditional bioavailability issues [81]. Exosomes functionalized with RNA-binding proteins or hybridized with liposomes further improve the delivery of genetic material, enabling effective gene silencing and editing [82]. This approach highlights exosomes’ potential as powerful carriers for targeted gene therapy in regenerative medicine. Personalized exosome therapies: Exosome-based therapy holds promise for personalized medicine based on each patient’s distinct profile. Thus, analyze each corneal condition individually and tailoring exosome therapy for diverse patient needs to advance personalized medicine in ophthalmology [83,84]. Investigation of alternative exosome sources: Increasing studies on exosomes derived from different cell types, such as plant-based or non-human animal sources, may reveal novel characteristics or improve therapeutic outcomes. Accordingly, adequate investigations are required to ensure compatibility and safety, immune responses, and lowering inflammation in the eye from distinct sources [85]. Clinical translation and immunogenicity: In lieu of encouraging preclinical findings, exosomes’ immunogenic profiles for corneal applications are under investigation, and future studies ought to concentrate on the safety of exosomes in the immune-privileged ocular environment, specifically regarding the exosomes’ origin (e.g., human versus non-human sources) and possible long-term immunological reactions [83,86]. Regulatory challenges in exosome and EV therapy approval: The existing regulatory framework for exosomes and EV therapeutics encounters obstacles due to the absence of standardized rules, resulting in uncertainty in classification and assessment by organizations such as the FDA and EMA [87]. EVs fall between categories like biological products and cell therapies and can be mingled with drug delivery systems, delaying the regulatory guidelines [88]. Moreover, the intrinsic variability of EVs, arising from diverse cell origins, sizes, and cargo compositions presents further challenges in complying with regulatory requirements for product characterization and batch uniformity [89]. The variability in EV preparations can affect treatment efficacy and reproducibility, underscoring the requirement for generally agreed on protocols establishing practical standards for EV characterization, safety, and efficacy assessment [87].
9. Concluding Remarks
Exosomes are promising nanovesicles and can act as therapeutic active components alongside drugs. Their capacity to administer bioactive chemicals directly to specific corneal cells provides a non-invasive and biocompatible alternative to conventional treatments, particularly for diseases where the existing therapies are inadequate. Thus, they are recognized as promising next-generation therapeutics due to demonstrated safety and efficacy in preclinical models and early-stage clinical trials. Similarly, exosomes have the potential to serve as novel carriers for cornea-targeted drug delivery because of their low toxicity, ability to carry materials from one cell to another, adaptability with biological tissues, non-immunogenicity, and specific targeting of different cells. Here, we have highlighted some of the key advances of EVs in corneal treatment, repair, and regeneration, such as exosomes facilitate corneal healing, including controlling inflammation, encouraging cell proliferation, and inhibiting scarring. Given the complexity of the corneal healing cascade and immunogenicity of the eye, there will be many future EV-related discoveries together, unveiling the exciting benefits of exosomes-based therapeutic platforms, and further investigations are required for clinical translational challenges.
Author Contributions
Conceptualization, V.A. and P.K.; writing—original draft preparation, B.T.R. and K.A.M.; writing—review and revision, B.T.R., K.A.M., N.K., P.K. and V.A.; visualization, B.T.R. and K.A.M.; supervision, V.A.; project administration, V.A. and P.K.; funding acquisition, V.A. All authors have read and agreed to the published version of the manuscript.
Funding
Part of research was funded by the American Association Colleges of Pharmacy (AACP), New Investigator Award 2023 to V.A.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data sharing is not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Mohan, R.R.; Kempuraj, D.; D’Souza, S.; Ghosh, A. Corneal stromal repair and regeneration. Prog. Retin. Eye Res. 2022, 91, 101090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tidke, S.C.; Tidake, P. A Review of Corneal Blindness: Causes and Management. Cureus 2022, 14, e30097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burnouf, T.; Agrahari, V.; Agrahari, V. Extracellular Vesicles As Nanomedicine: Hopes And Hurdles In Clinical Translation. Int. J. Nanomed. 2019, 14, 8847–8859. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mofidfar, M.; Abdi, B.; Ahadian, S.; Mostafavi, E.; Desai, T.A.; Abbasi, F.; Sun, Y.; Manche, E.E.; Ta, C.N.; Flowers, C.W. Drug delivery to the anterior segment of the eye: A review of current and future treatment strategies. Int. J. Pharm. 2021, 607, 120924. [Google Scholar] [CrossRef] [Scilit]
- Agrahari, V.; Agrahari, V.; Burnouf, P.A.; Chew, C.H.; Burnouf, T. Extracellular Microvesicles as New Industrial Therapeutic Frontiers. Trends Biotechnol. 2019, 37, 707–729. [Google Scholar] [CrossRef] [Scilit]
- Miron, R.J.; Zhang, Y. Understanding exosomes: Part 1-Characterization, quantification and isolation techniques. Periodontol. 2000 2024, 94, 231–256. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Jiang, F.; Jiang, Y.; Wang, Y.; Li, Z.; Shi, X.; Zhu, Y.; Wang, H.; Zhang, Z. Roles of Exosomes in Ocular Diseases. Int. J. Nanomedicine 2020, 15, 10519–10538. [Google Scholar] [CrossRef] [Scilit]
- Agrahari, V.; Agrahari, V.; Mandal, A.; Pal, D.; Mitra, A.K. How are we improving the delivery to back of the eye? Advances and challenges of novel therapeutic approaches. Expert. Opin. Drug Deliv. 2017, 14, 1145–1162. [Google Scholar] [CrossRef] [Scilit]
- Agrahari, V.; Mandal, A.; Agrahari, V.; Trinh, H.M.; Joseph, M.; Ray, A.; Hadji, H.; Mitra, R.; Pal, D.; Mitra, A.K. A comprehensive insight on ocular pharmacokinetics. Drug Deliv. Transl. Res. 2016, 6, 735–754. [Google Scholar] [CrossRef] [Scilit]
- Dosmar, E.; Walsh, J.; Doyel, M.; Bussett, K.; Oladipupo, A.; Amer, S.; Goebel, K. Targeting Ocular Drug Delivery: An Examination of Local Anatomy and Current Approaches. Bioengineering 2022, 9, 41. [Google Scholar] [CrossRef] [Scilit]
- Downie, L.E.; Bandlitz, S.; Bergmanson, J.P.G.; Craig, J.P.; Dutta, D.; Maldonado-Codina, C.; Ngo, W.; Siddireddy, J.S.; Wolffsohn, J.S. CLEAR—Anatomy and physiology of the anterior eye. Cont. Lens Anterior Eye 2021, 44, 132–156. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eghrari, A.O.; Riazuddin, S.A.; Gottsch, J.D. Overview of the Cornea: Structure, Function, and Development. Prog. Mol. Biol. Transl. Sci. 2015, 134, 7–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, S.E. Bowman’s layer in the cornea- structure and function and regeneration. Exp. Eye Res. 2020, 195, 108033. [Google Scholar] [CrossRef] [Scilit]
- Espana, E.M.; Birk, D.E. Composition, structure and function of the corneal stroma. Exp. Eye Res. 2020, 198, 108137. [Google Scholar] [CrossRef] [Scilit]
- Pouw, A.E.; Greiner, M.A.; Coussa, R.G.; Jiao, C.; Han, I.C.; Skeie, J.M.; Fingert, J.H.; Mullins, R.F.; Sohn, E.H. Cell-Matrix Interactions in the Eye: From Cornea to Choroid. Cells 2021, 10, 687. [Google Scholar] [CrossRef] [Scilit]
- DelMonte, D.W.; Kim, T. Anatomy and physiology of the cornea. J. Cataract. Refract. Surg. 2011, 37, 588–598. [Google Scholar] [CrossRef] [Scilit]
- de Oliveira, R.C.; Wilson, S.E. Descemet’s membrane development, structure, function and regeneration. Exp. Eye Res. 2020, 197, 108090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kamil, S.; Mohan, R.R. Corneal stromal wound healing: Major regulators and therapeutic targets. Ocul. Surf. 2021, 19, 290–306. [Google Scholar] [CrossRef] [Scilit]
- Fortingo, N.; Melnyk, S.; Sutton, S.H.; Watsky, M.A.; Bollag, W.B. Innate Immune System Activation, Inflammation and Corneal Wound Healing. Int. J. Mol. Sci. 2022, 23, 14933. [Google Scholar] [CrossRef] [Scilit]
- Liu, C.Y.; Kao, W.W. Corneal Epithelial Wound Healing. Prog. Mol. Biol. Transl. Sci. 2015, 134, 61–71. [Google Scholar] [CrossRef] [Scilit]
- Ljubimov, A.V.; Saghizadeh, M. Progress in corneal wound healing. Prog. Retin. Eye Res. 2015, 49, 17–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, S.L.; El Haj, A.J.; Yang, Y. Control of scar tissue formation in the cornea: Strategies in clinical and corneal tissue engineering. J. Funct. Biomater. 2012, 3, 642–687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, S.E.; Mohan, R.R.; Mohan, R.R.; Ambrosio, R., Jr.; Hong, J.; Lee, J. The corneal wound healing response: Cytokine-mediated interaction of the epithelium, stroma, and inflammatory cells. Prog. Retin. Eye Res. 2001, 20, 625–637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilson, S.E. Corneal wound healing. Exp. Eye Res. 2020, 197, 108089. [Google Scholar] [CrossRef] [Scilit]
- Jeon, K.I.; Hindman, H.B.; Bubel, T.; McDaniel, T.; DeMagistris, M.; Callan, C.; Huxlin, K.R. Corneal myofibroblasts inhibit regenerating nerves during wound healing. Sci. Rep. 2018, 8, 12945. [Google Scholar] [CrossRef] [Scilit]
- Lin, Z.; Wu, Y.; Xu, Y.; Li, G.; Li, Z.; Liu, T. Mesenchymal stem cell-derived exosomes in cancer therapy resistance: Recent advances and therapeutic potential. Mol. Cancer 2022, 21, 179. [Google Scholar] [CrossRef] [Scilit]
- Desjardins, P.; Berthiaume, R.; Couture, C.; Le-Bel, G.; Roy, V.; Gros-Louis, F.; Moulin, V.J.; Proulx, S.; Chemtob, S.; Germain, L.; et al. Impact of Exosomes Released by Different Corneal Cell Types on the Wound Healing Properties of Human Corneal Epithelial Cells. Int. J. Mol. Sci. 2022, 23, 12201. [Google Scholar] [CrossRef] [Scilit]
- Li, S.F.; Han, Y.; Wang, F.; Su, Y. Progress in exosomes and their potential use in ocular diseases. Int. J. Ophthalmol. 2020, 13, 1493–1498. [Google Scholar] [CrossRef] [Scilit]
- Li, N.; Zhao, L.; Wei, Y.; Ea, V.L.; Nian, H.; Wei, R. Recent advances of exosomes in immune-mediated eye diseases. Stem Cell Res. Ther. 2019, 10, 278. [Google Scholar] [CrossRef] [Scilit]
- Zhu, X.; Badawi, M.; Pomeroy, S.; Sutaria, D.S.; Xie, Z.; Baek, A.; Jiang, J.; Elgamal, O.A.; Mo, X.; Perle, K.; et al. Comprehensive toxicity and immunogenicity studies reveal minimal effects in mice following sustained dosing of extracellular vesicles derived from HEK293T cells. J. Extracell. Vesicles 2017, 6, 1324730. [Google Scholar] [CrossRef] [Scilit]
- Sanghani, A.; Andriesei, P.; Kafetzis, K.N.; Tagalakis, A.D.; Yu-Wai-Man, C. Advances in exosome therapies in ophthalmology-From bench to clinical trial. Acta Ophthalmol. 2022, 100, 243–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, K.; Sheng, M.; Zhang, J.; Yan, G.; Li, B. Plasma exosomal proteomic studies of corneal epithelial injury in diabetic and non-diabetic group. Exp. Eye Res. 2021, 212, 108794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aiello, S.; Rocchetta, F.; Longaretti, L.; Faravelli, S.; Todeschini, M.; Cassis, L.; Pezzuto, F.; Tomasoni, S.; Azzollini, N.; Mister, M.; et al. Extracellular vesicles derived from T regulatory cells suppress T cell proliferation and prolong allograft survival. Sci. Rep. 2017, 7, 11518. [Google Scholar] [CrossRef] [Scilit]
- Wen, D.; Peng, Y.; Liu, D.; Weizmann, Y.; Mahato, R.I. Mesenchymal stem cell and derived exosome as small RNA carrier and Immunomodulator to improve islet transplantation. J. Control Release 2016, 238, 166–175. [Google Scholar] [CrossRef] [Scilit]
- Fathi, M.; Barar, J.; Aghanejad, A.; Omidi, Y. Hydrogels for ocular drug delivery and tissue engineering. Bioimpacts 2015, 5, 159–164. [Google Scholar] [CrossRef] [Scilit]
- Meng, S.; Hu, H.; Qiao, Y.; Wang, F.; Zhang, B.N.; Sun, D.; Zhou, L.; Zhao, L.; Xie, L.; Zhang, H.; et al. A Versatile Hydrogel with Antibacterial and Sequential Drug-Releasing Capability for the Programmable Healing of Infectious Keratitis. ACS Nano 2023, 17, 24055–24069. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, M.C.; Kuo, Y.J.; Hung, K.H.; Peng, C.L.; Chen, K.Y.; Yeh, L.K. Liposomal dexamethasone-moxifloxacin nanoparticle combinations with collagen/gelatin/alginate hydrogel for corneal infection treatment and wound healing. Biomed. Mater. 2020, 15, 055022. [Google Scholar] [CrossRef] [Scilit]
- Chen, F.; Mundy, D.C.; Le, P.; Seo, Y.A.; Logan, C.M.; Fernandes-Cunha, G.M.; Basco, C.A.; Myung, D. In Situ-Forming Collagen-Hyaluronate Semi-Interpenetrating Network Hydrogel Enhances Corneal Defect Repair. Transl. Vis. Sci. Technol. 2022, 11, 22. [Google Scholar] [CrossRef] [Scilit]
- Feng, L.; Liu, R.; Zhang, X.; Li, J.; Zhu, L.; Li, Z.; Li, W.; Zhang, A. Thermo-Gelling Dendronized Chitosans as Biomimetic Scaffolds for Corneal Tissue Engineering. ACS Appl. Mater. Interfaces 2021, 13, 49369–49379. [Google Scholar] [CrossRef] [Scilit]
- Logan, C.M.; Fernandes-Cunha, G.M.; Chen, F.; Le, P.; Mundy, D.; Na, K.S.; Myung, D. In Situ-forming Collagen Hydrogels Crosslinked by Multifunctional Polyethylene Glycol as a Matrix Therapy for Corneal Defects: 2-Month Follow-up In Vivo. Cornea 2023, 42, 97–104. [Google Scholar] [CrossRef] [Scilit]
- Na, K.S.; Fernandes-Cunha, G.M.; Varela, I.B.; Lee, H.J.; Seo, Y.A.; Myung, D. Effect of mesenchymal stromal cells encapsulated within polyethylene glycol-collagen hydrogels formed in situ on alkali-burned corneas in an ex vivo organ culture model. Cytotherapy 2021, 23, 500–509. [Google Scholar] [CrossRef] [Scilit]
- Khosravimelal, S.; Mobaraki, M.; Eftekhari, S.; Ahearne, M.; Seifalian, A.M.; Gholipourmalekabadi, M. Hydrogels as Emerging Materials for Cornea Wound Healing. Small 2021, 17, e2006335. [Google Scholar] [CrossRef] [Scilit]
- Riau, A.K.; Ong, H.S.; Yam, G.H.F.; Mehta, J.S. Sustained Delivery System for Stem Cell-Derived Exosomes. Front. Pharmacol. 2019, 10, 1368. [Google Scholar] [CrossRef] [Scilit]
- Mansoor, H.; Ong, H.S.; Riau, A.K.; Stanzel, T.P.; Mehta, J.S.; Yam, G.H. Current Trends and Future Perspective of Mesenchymal Stem Cells and Exosomes in Corneal Diseases. Int. J. Mol. Sci. 2019, 20, 2853. [Google Scholar] [CrossRef] [Scilit]
- Tang, Q.; Lu, B.; He, J.; Chen, X.; Fu, Q.; Han, H.; Luo, C.; Yin, H.; Qin, Z.; Lyu, D.; et al. Exosomes-loaded thermosensitive hydrogels for corneal epithelium and stroma regeneration. Biomaterials 2022, 280, 121320. [Google Scholar] [CrossRef] [Scilit]
- Sun, X.; Song, W.; Teng, L.; Huang, Y.; Liu, J.; Peng, Y.; Lu, X.; Yuan, J.; Zhao, X.; Zhao, Q.; et al. MiRNA 24-3p-rich exosomes functionalized DEGMA-modified hyaluronic acid hydrogels for corneal epithelial healing. Bioact. Mater. 2023, 25, 640–656. [Google Scholar] [CrossRef] [Scilit]
- Zhao, W.; He, X.; Liu, R.; Ruan, Q. Accelerating corneal wound healing using exosome-mediated targeting of NF-kappaB c-Rel. Inflamm. Regen. 2023, 43, 6. [Google Scholar] [CrossRef] [Scilit]
- Shojaati, G.; Khandaker, I.; Funderburgh, M.L.; Mann, M.M.; Basu, R.; Stolz, D.B.; Geary, M.L.; Dos Santos, A.; Deng, S.X.; Funderburgh, J.L. Mesenchymal Stem Cells Reduce Corneal Fibrosis and Inflammation via Extracellular Vesicle-Mediated Delivery of miRNA. Stem Cells Transl. Med. 2019, 8, 1192–1201. [Google Scholar] [CrossRef] [Scilit]
- Imanishi, J.; Kamiyama, K.; Iguchi, I.; Kita, M.; Sotozono, C.; Kinoshita, S. Growth factors: Importance in wound healing and maintenance of transparency of the cornea. Prog. Retin. Eye Res. 2000, 19, 113–129. [Google Scholar] [CrossRef] [Scilit]
- Carter, K.; Lee, H.J.; Na, K.S.; Fernandes-Cunha, G.M.; Blanco, I.J.; Djalilian, A.; Myung, D. Characterizing the impact of 2D and 3D culture conditions on the therapeutic effects of human mesenchymal stem cell secretome on corneal wound healing in vitro and ex vivo. Acta Biomater. 2019, 99, 247–257. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.J.; Kim, G.; Lee, J.; Lee, Y.; Kim, J.H. Secretome of Stem Cells: Roles of Extracellular Vesicles in Diseases, Stemness, Differentiation, and Reprogramming. Tissue Eng. Regen. Med. 2022, 19, 19–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fernandes-Cunha, G.M.; Na, K.S.; Putra, I.; Lee, H.J.; Hull, S.; Cheng, Y.C.; Blanco, I.J.; Eslani, M.; Djalilian, A.R.; Myung, D. Corneal Wound Healing Effects of Mesenchymal Stem Cell Secretome Delivered Within a Viscoelastic Gel Carrier. Stem Cells Transl. Med. 2019, 8, 478–489. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di, G.H.; Qi, X.; Xu, J.; Yu, C.Q.; Cao, Q.L.; Xing, Z.J.; Li, Z.C. Therapeutic effect of secretome from TNF-alpha stimulated mesenchymal stem cells in an experimental model of corneal limbal stem cell deficiency. Int. J. Ophthalmol. 2021, 14, 179–185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- An, S.; Anwar, K.; Ashraf, M.; Lee, H.; Jung, R.; Koganti, R.; Ghassemi, M.; Djalilian, A.R. Wound-Healing Effects of Mesenchymal Stromal Cell Secretome in the Cornea and the Role of Exosomes. Pharmaceutics 2023, 15, 1486. [Google Scholar] [CrossRef] [Scilit]
- Samaeekia, R.; Rabiee, B.; Putra, I.; Shen, X.; Park, Y.J.; Hematti, P.; Eslani, M.; Djalilian, A.R. Effect of Human Corneal Mesenchymal Stromal Cell-derived Exosomes on Corneal Epithelial Wound Healing. Investig. Ophthalmol. Vis. Sci. 2018, 59, 5194–5200. [Google Scholar] [CrossRef] [Scilit]
- Escandon, P.; Liu, A.; Nicholas, S.E.; Khan, A.; Riaz, K.M.; Karamichos, D. Unravelling Novel Roles of Salivary Exosomes in the Regulation of Human Corneal Stromal Cell Migration and Wound Healing. Int. J. Mol. Sci. 2022, 23, 4330. [Google Scholar] [CrossRef] [Scilit]
- Wu, W.; Zhou, J.; Zhu, D.; Ma, S. Effect of PKH-26-labeled exosomes derived from bone marrow mesenchymal stem cells on corneal epithelium regeneration in diabetic mice. Ann. Transl. Med. 2023, 11, 167. [Google Scholar] [CrossRef] [Scilit]
- Altug, B.; Soykan, M.N.; Eyubova, S.; Eker Sariboyaci, A.; Dogan, C.; Ozalp, O.; Atalay, E. Crosstalk among miR-29, alpha-SMA, and TGFbeta1/beta3 in melatonin-induced exosome (Mel-prExo) treated human limbal mesenchymal stem cells (hLMSCs): An insight into scarless healing of the cornea. Biofactors 2024. [Google Scholar] [CrossRef] [Scilit]
- Erkoc-Biradli, F.Z.; Erenay, B.; Ozgun, A.; Oztatli, H.; Isik, F.; Ates, U.; Rasier, R.; Garipcan, B. Mesenchymal stem cells derived-exosomes enhanced amniotic membrane extract promotes corneal keratocyte proliferation. Biotechnol. Prog. 2024, 40, e3465. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.J.; Lee, S.H.; Koh, A.; Kim, K.W. EGF-conditioned M1 macrophages Convey reduced inflammation into corneal endothelial cells through exosomes. Heliyon 2024, 10, e26800. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Gao, J.; Lu, P.; Wang, Y.; Xing, S.; Yan, Y.; Han, R.; Hao, P.; Li, X. Mesenchymal Stem Cell-Derived Exosomes as Drug Carriers for Delivering miRNA-29b to Ameliorate Inflammation in Corneal Injury Via Activating Autophagy. Investig. Ophthalmol. Vis. Sci. 2024, 65, 16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, C.; Sun, Y.; Zeng, F.; Chen, X.; Ma, L.; Liu, X.; Qi, X.; Shi, W.; Gao, H. Exosomal miR-181d-5p Derived from Rapamycin-Conditioned MDSC Alleviated Allograft Rejection by Targeting KLF6. Adv Sci (Weinh) 2023, 10, e2304922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ryu, Y.; Hwang, J.S.; Bo Noh, K.; Park, S.H.; Seo, J.H.; Shin, Y.J. Adipose Mesenchymal Stem Cell-Derived Exosomes Promote the Regeneration of Corneal Endothelium Through Ameliorating Senescence. Investig. Ophthalmol. Vis. Sci. 2023, 64, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ong, H.S.; Riau, A.K.; Yam, G.H.; Yusoff, N.; Han, E.J.Y.; Goh, T.W.; Lai, R.C.; Lim, S.K.; Mehta, J.S. Mesenchymal Stem Cell Exosomes as Immunomodulatory Therapy for Corneal Scarring. Int. J. Mol. Sci. 2023, 24, 7456. [Google Scholar] [CrossRef] [Scilit]
- Zhou, J.; Ding, Y.; Zhang, Y.; Zheng, D.; Yan, L.; Guo, M.; Mao, Y.; Yang, L. Exosomes from bone marrow-derived mesenchymal stem cells facilitate corneal wound healing via regulating the p44/42 MAPK pathway. Graefes Arch. Clin. Exp. Ophthalmol. 2023, 261, 723–734. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.; Li, X.; Wu, G.; Qi, P.; Zhang, Y.; Liu, Z.; Li, X.; Yu, Y.; Ye, X.; Li, Y.; et al. Umbilical Cord Mesenchymal Stem Cell-Derived Small Extracellular Vesicles Deliver miR-21 to Promote Corneal Epithelial Wound Healing through PTEN/PI3K/Akt Pathway. Stem Cells Int. 2022, 2022, 1252557. [Google Scholar] [CrossRef] [Scilit]
- Ma, S.; Yin, J.; Hao, L.; Liu, X.; Shi, Q.; Diao, Y.; Yu, G.; Liu, L.; Chen, J.; Zhong, J. Exosomes From Human Umbilical Cord Mesenchymal Stem Cells Treat Corneal Injury via Autophagy Activation. Front. Bioeng. Biotechnol. 2022, 10, 879192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, Z.; Lv, Y.; Zhang, W.; Zhang, X.; Li, F.; Lu, X.; Zhao, S. Mesenchymal stem cell derived exosomes-based immunological signature in a rat model of corneal allograft rejection therapy. Front. Biosci. 2022, 27, 86. [Google Scholar] [CrossRef] [Scilit]
- Buono, L.; Scalabrin, S.; De Iuliis, M.; Tanzi, A.; Grange, C.; Tapparo, M.; Nuzzi, R.; Bussolati, B. Mesenchymal Stem Cell-Derived Extracellular Vesicles Protect Human Corneal Endothelial Cells from Endoplasmic Reticulum Stress-Mediated Apoptosis. Int. J. Mol. Sci. 2021, 22, 4930. [Google Scholar] [CrossRef] [Scilit]
- Wang, S.; Hou, Y.; Li, X.; Song, Z.; Sun, B.; Li, X.; Zhang, H. Comparison of exosomes derived from induced pluripotent stem cells and mesenchymal stem cells as therapeutic nanoparticles for treatment of corneal epithelial defects. Aging 2020, 12, 19546–19562. [Google Scholar] [CrossRef] [Scilit]
- Shen, T.; Zheng, Q.; Luo, H.; Li, X.; Chen, Z.; Song, Z.; Zhou, G.; Hong, C. Exosomal miR-19a from adipose-derived stem cells suppresses differentiation of corneal keratocytes into myofibroblasts. Aging 2020, 12, 4093–4110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verta, R.; Saccu, G.; Tanzi, A.; Grange, C.; Buono, L.; Fagoonee, S.; Deregibus, M.C.; Camussi, G.; Scalabrin, S.; Nuzzi, R.; et al. Phenotypic and functional characterization of aqueous humor derived extracellular vesicles. Exp. Eye Res. 2023, 228, 109393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lyu, N.; Knight, R.; Robertson, S.Y.T.; Dos Santos, A.; Zhang, C.; Ma, C.; Xu, J.; Zheng, J.; Deng, S.X. Stability and Function of Extracellular Vesicles Derived from Immortalized Human Corneal Stromal Stem Cells: A Proof of Concept Study. AAPS J. 2022, 25, 8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, T.; He, C.; Lai, P.; Yang, Z.; Liu, Y.; Xu, H.; Lin, X.; Ni, B.; Ju, R.; Yi, W.; et al. miR-204-containing exosomes ameliorate GVHD-associated dry eye disease. Sci. Adv. 2022, 8, eabj9617. [Google Scholar] [CrossRef] [Scilit]
- Lotfy, A.; AboQuella, N.M.; Wang, H. Mesenchymal stromal/stem cell (MSC)-derived exosomes in clinical trials. Stem Cell Res. Ther. 2023, 14, 66. [Google Scholar] [CrossRef] [Scilit]
- Jeng, B.H.; Hamrah, P.; Kirshner, Z.Z.; Mendez, B.C.; Wessel, H.C.; Brown, L.R.; Steed, D.L. Exploratory Phase II Multicenter, Open-Label, Clinical Trial of ST266, a Novel Secretome for Treatment of Persistent Corneal Epithelial Defects. Transl. Vis. Sci. Technol. 2022, 11, 8. [Google Scholar] [CrossRef] [Scilit]
- Lee, C.S.; Fan, J.; Hwang, H.S.; Kim, S.; Chen, C.; Kang, M.; Aghaloo, T.; James, A.W.; Lee, M. Bone-Targeting Exosome Mimetics Engineered by Bioorthogonal Surface Functionalization for Bone Tissue Engineering. Nano Lett. 2023, 23, 1202–1210. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Li, W.; Lu, Z.; Zhang, L.; Hu, Y.; Li, Q.; Du, W.; Feng, X.; Jia, H.; Liu, B.F. The use of RGD-engineered exosomes for enhanced targeting ability and synergistic therapy toward angiogenesis. Nanoscale 2017, 9, 15598–15605. [Google Scholar] [CrossRef] [Scilit]
- Jafari, D.; Shajari, S.; Jafari, R.; Mardi, N.; Gomari, H.; Ganji, F.; Forouzandeh Moghadam, M.; Samadikuchaksaraei, A. Designer Exosomes: A New Platform for Biotechnology Therapeutics. BioDrugs 2020, 34, 567–586. [Google Scholar] [CrossRef] [Scilit]
- Ye, Y.; Zhang, X.; Xie, F.; Xu, B.; Xie, P.; Yang, T.; Shi, Q.; Zhang, C.Y.; Zhang, Y.; Chen, J.; et al. An engineered exosome for delivering sgRNA:Cas9 ribonucleoprotein complex and genome editing in recipient cells. Biomater. Sci. 2020, 8, 2966–2976. [Google Scholar] [CrossRef] [Scilit]
- El-Andaloussi, S.; Lee, Y.; Lakhal-Littleton, S.; Li, J.; Seow, Y.; Gardiner, C.; Alvarez-Erviti, L.; Sargent, I.L.; Wood, M.J. Exosome-mediated delivery of siRNA in vitro and in vivo. Nat. Protoc. 2012, 7, 2112–2126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, Y.; Wu, J.; Gu, W.; Huang, Y.; Tong, Z.; Huang, L.; Tan, J. Exosome-Liposome Hybrid Nanoparticles Deliver CRISPR/Cas9 System in MSCs. Adv. Sci. 2018, 5, 1700611. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tiwari, A.; Singh, A.; Verma, S.; Stephenson, S.; Bhowmick, T.; Sangwan, V.S. Mini Review: Current Trends and Understanding of Exosome Therapeutic Potential in Corneal Diseases. Front. Pharmacol. 2021, 12, 684712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, X.; Peng, Z.; Yuan, L.; Jin, M.; Hu, H.; Peng, X.; Wang, Y.; Zhang, C.; Luo, Z.; Liao, H. Research progress of exosomes in pathogenesis, diagnosis, and treatment of ocular diseases. Front. Bioeng. Biotechnol. 2023, 11, 1100310. [Google Scholar] [CrossRef] [Scilit]
- Sarasati, A.; Syahruddin, M.H.; Nuryanti, A.; Ana, I.D.; Barlian, A.; Wijaya, C.H.; Ratnadewi, D.; Wungu, T.D.K.; Takemori, H. Plant-Derived Exosome-like Nanoparticles for Biomedical Applications and Regenerative Therapy. Biomedicines 2023, 11, 1053. [Google Scholar] [CrossRef] [Scilit]
- Perocheau, D.; Touramanidou, L.; Gurung, S.; Gissen, P.; Baruteau, J. Clinical applications for exosomes: Are we there yet? Br. J. Pharmacol. 2021, 178, 2375–2392. [Google Scholar] [CrossRef] [Scilit]
- Lener, T.; Gimona, M.; Aigner, L.; Borger, V.; Buzas, E.; Camussi, G.; Chaput, N.; Chatterjee, D.; Court, F.A.; Del Portillo, H.A.; et al. Applying extracellular vesicles based therapeutics in clinical trials—An ISEV position paper. J. Extracell. Vesicles 2015, 4, 30087. [Google Scholar] [CrossRef] [Scilit]
- Meng, W.; He, C.; Hao, Y.; Wang, L.; Li, L.; Zhu, G. Prospects and challenges of extracellular vesicle-based drug delivery system: Considering cell source. Drug Deliv. 2020, 27, 585–598. [Google Scholar] [CrossRef] [Scilit]
- Nelson, B.C.; Maragh, S.; Ghiran, I.C.; Jones, J.C.; DeRose, P.C.; Elsheikh, E.; Vreeland, W.N.; Wang, L. Measurement and standardization challenges for extracellular vesicle therapeutic delivery vectors. Nanomedicine 2020, 15, 2149–2170. [Google Scholar] [CrossRef] [Scilit]




Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).