


We present the case of a young woman who was resuscitated on an aircraft shortly before take-off. The initial ECG showed a prolonged QT-interval along with a complete atrioventricular block.
Case presentation
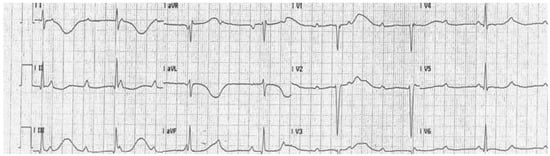
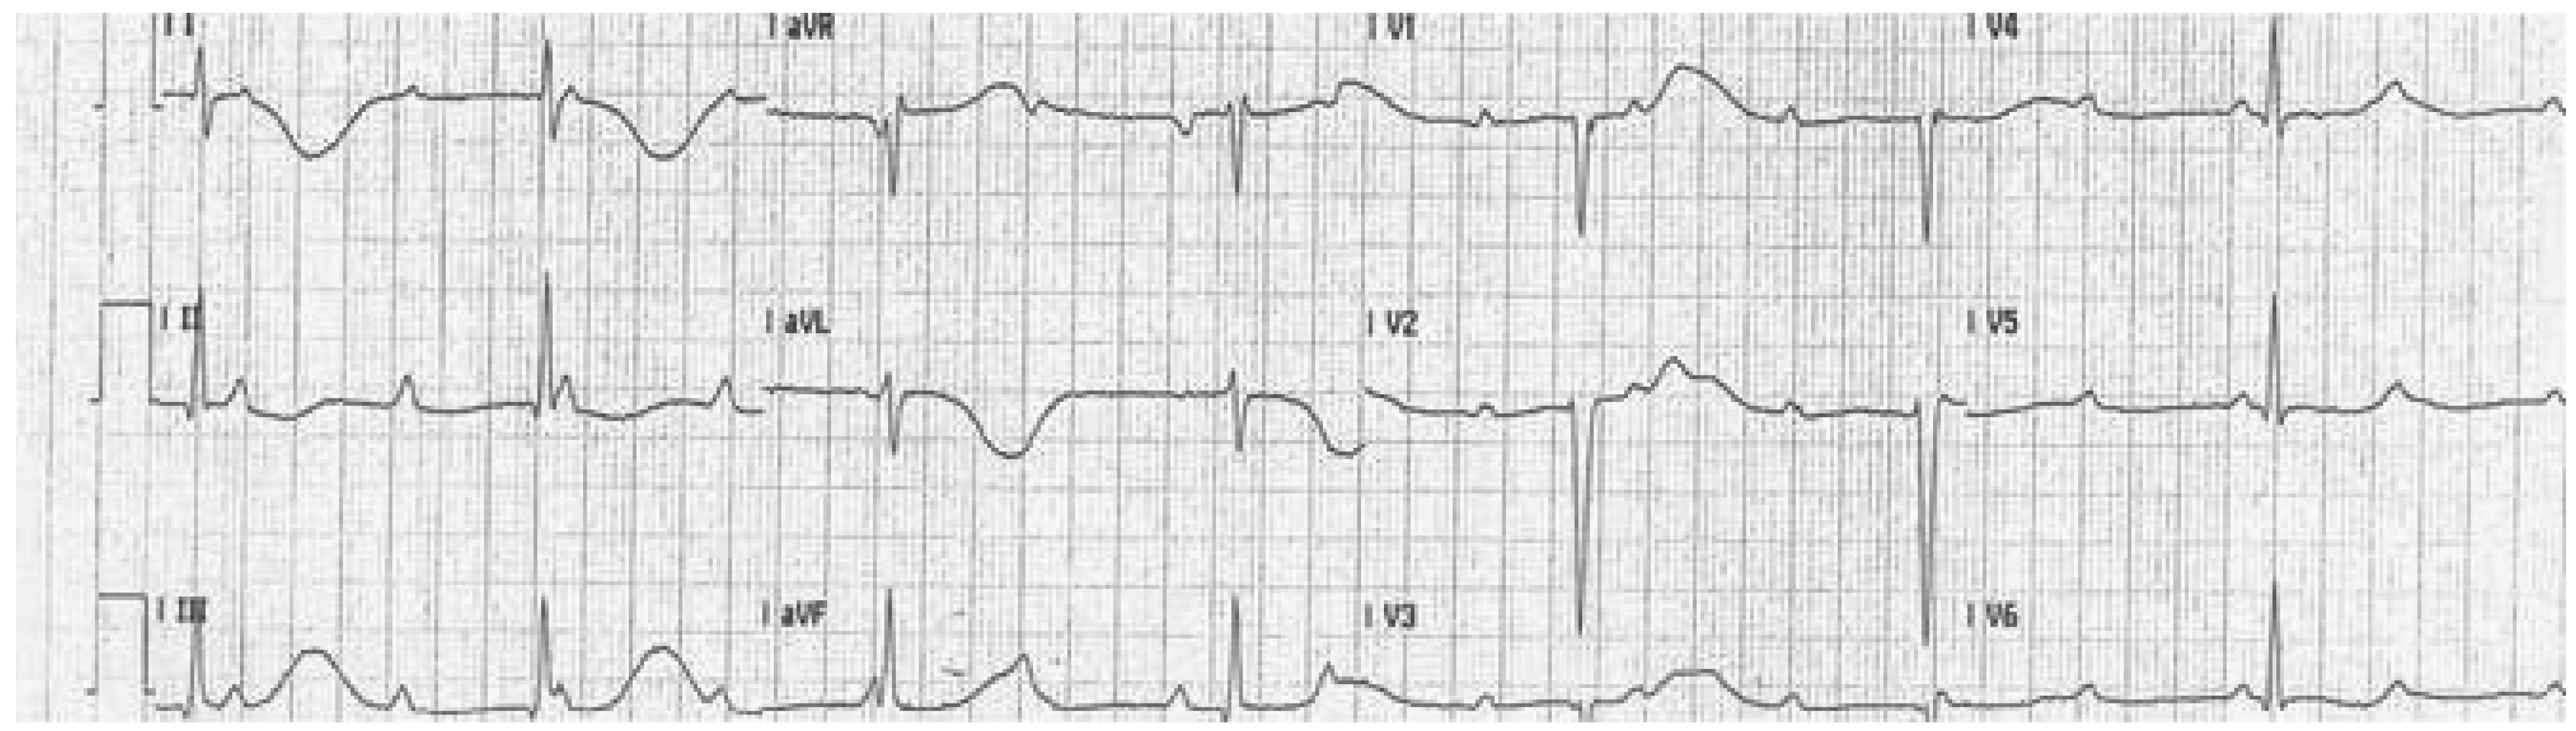
A 22-year-old student was admitted to our hospital after she had been resuscitated in an airplane at the local airport. According to the emergency personnel, the patient was found unconscious shortly before takeoff. Upon arrival, the paramedics initiated cardiopulmonary resuscitation. Figure 1 shows the initial rhythm documentation. The patient had no known diseases or family history of sudden cardiac death (SCD) and had never had an ECG taken before. She took no medications and used no illicit drugs.
Figure 1.
Initial ECG on arrival of emergency medical services (25 mm/sec).
Coronary angiography was performed, due to initially reduced left ventricular ejection fraction (LVEF 35%), and revealed normal coronary arteries. Cardiac MRI showed no signs of myocarditis.
Questions
- Which pathology is displayed on the ECG?
- Are there any ECG clues for the cause of the cardiac arrest?
Commentary
Firstly, a third degree atrioventricular block (AVB) with a junctional escape rhythm of 44 bpm and a sinus rate of 90 bpm was present. Secondly, the QT-interval was markedly prolonged (QT 800 ms, QTc 653 ms). In the absence of acquired causes for QT prolongation, the diagnosis was therefore congenital long QT syndrome (LQTS) along with complete AVB.
LQTS is the most common genetic arrhythmia syndrome. To date, 12 LQTS phenotypes are known, of which LQTS 1–3 are most common. The T-wave pattern with a long ST-segment interval before a late onset of the T-wave and the circumstances of the arrest during physical rest are indicative for the LQTS3 phenotype [1]. The complete AVB with prolonged ventricular cycle length in association with LQTS made bradycardia induced Torsade de Pointes (TdP) tachycardia with spontaneous termination the most likely reason for syncope in our patient [2]. Coexistence of LQTS with inherited cardiac conduction system defects have been reported [3], especially in patients with mutations in the SCN5A gene encoding the cardiac sodium channel. In our patient, we could not find a mutation in the SCN5A gene. However, a genetic disorder cannot be excluded since only in up to 60% of patients with a clear LQTS phenotype, mutations in the target genes can be identified. After neurological recovery, complete recovery of the LVEF and discussion with the family, our patient opted for a dual chamber ICD for secondary prevention after presumed survived SCD. During a fiveyear follow-up, the complete AVB persisted and no ventricular arrhythmias occurred.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Schwartz, P.J.; et al. Genotype-phenotype correlation in the long QT syndrome: gene-specific triggers for life-threatening arrhythmias. Circulation. 2001, 103(1), 89–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viskin, S.; et al. Arrhythmias in the congenital long QT syndrome: how often is torsade de pointes pause dependent? Heart. 2000, 83(6), 661–666. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolf, C.M.; Berul, C.I. Inherited conduction system abnormalities – one group of diseases, many genes. J Cardiovasc Electrophysiol. 2006, 17(4), 446–455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2010 by the author. Attribution - Non-Commercial - NoDerivatives 4.0.