


Abstract
The COVID-19 evolution depends on immunological capacity. The global hospital mortality rate is 15–20%, but in México it is 46%. There are several therapeutic protocols, however, integral nutrition is not considered. In this study, a Nutritional Support System (NSS) was employed to increase survival and reduce mortality in patients with stage III COVID-19. A randomized, blinded, controlled clinical trial was performed. Eighty patients (aged 30 to 75 years, both sexes) were assigned to (1) “Control Group” (CG) hospital diet and medical treatment or (2) “Intervention Group” (IG) hospital diet, medical treatment, and the NSS (vitamins, minerals, fiber, omega-3, amino acids, B-complex, and probiotics). IG significantly increased survival and reduced mortality compared to CG (p = 0.027). IG decreased progression to Mechanical Ventilation Assistance (MVA) by 10%, reduced the intubation period by 15 days, and increased survival in intubated patients by 38% compared to CG. IG showed improvement compared to CG in decrease in supplemental oxygen (p = 0.014), the qSOFA test (p = 0.040), constipation (p = 0.014), the PHQ-9 test (p = 0.003), and in the follow-up, saturation with oxygen (p = 0.030). The NSS increases survival and decreases mortality in patients with stage III COVID-19.
Keywords:
COVID-19; SARS-CoV-2; nutritional support; NSS; nutrition; supplementation; probiotics; pneumonia; survival; mortality 1. Introduction
The SARS-CoV-2 disease was first identified in Wuhan, China, in December 2019 [1] and was declared a global pandemic on March 11, 2020, by the World Health Organization [2]. Epidemiologically, according to the WHO until December 2021, there are a total of 270,155,054 confirmed cases with a total of 5,305,991 deaths, with a 2.18% mortality rate and a hospital mortality rate between 15% and 20% [3]. In Mexico the number of deaths amounts to 296,984. The mortality rate is 9.07% [4,5] with hospital mortality of 46% and 75% among intubated patients [6,7]. Comorbidities such as obesity, systemic arterial hypertension (SAH), and type 2 diabetes mellitus (DM 2) have been associated with more severe disease symptoms [8]. Treatment is not specific; international guidelines recommend analgesia, retroviral, steroids, anticoagulation, and the occasional use of monoclonal antibodies, depending on the stage, the thrombotic risk, and renal and liver function [9].
Regarding nutritional support, the European Society for Parenteral and Enteral Nutrition (ESPEN) Guidelines recommend an energy calculation of 27–30 kcal/kg/day, proteins up to 1.5 g/kg/day, carbohydrates, and lipids with a proportion of 30:70 and 50:50 in patients with respiratory failure [10]. The evidence of nutrients, probiotics, minerals, and certain vitamins for therapeutic use is limited, although some are studied to improve the prognosis of patients [11]. It is known that patients with COVID-19 are catabolic and decrease their protein reserve together with cachexia and hyporexia, provoking nutritional deficit and dysbiosis [12,13]. If malnutrition prevails, it compromises immunity and inflammatory response, so a Nutritional Support System (NSS) may be necessary to reduce complications due to SARS-CoV-2, the progression to MVA, and even death [14]. The aim of this study was to investigate the effect of the NSS to increase survival and reduce mortality in patients with stage III COVID-19 and comorbidities.
2. Materials and Methods
2.1. Subject Selection
Inclusion criteria: hospitalized COVID-19 patients aged 30 and 75 years of both sexes, with oxygen saturation < 90%, use of supplemental oxygen, tolerance to the oral route, comorbidities (DM 2, SAH, and Body Mass Index (BMI) 25–40) were interviewed.
Non-inclusion criteria: respiratory frequency (BR) > 30 bpm, glycemia > 250 mg/dL, severe gastroesophageal reflux and/or dysphagia, a neurological condition, surgery < 3 months, allergy to any component of the NSS, sepsis, cancer, or chronic degenerative diseases that increase the metabolism.
2.2. Trial Design and Supervision
A randomized, blinded, controlled clinical trial was conducted at Centro Medico ISSEMyM Toluca (CMI), State of Mexico. The clinical phase started in September 2020. At discharge, each patient was followed for 40 days or until death. Recruitment ended in February 2021 and follow-up ended in April 2021.
Sampling and group assignment: Consecutive cases. Randomization was performed in blocks of 10 patients, assigned by a sequence of random numbers obtained from the Excel program and divided into two groups.
A triple blinding was planned: 1. Participants had no contact with each other because they were isolated, and when collecting informed consent, they were made aware that nutritional support might or might not be included with their meals as well as being part of regular medication or not; 2. The evaluators (treating physicians, care, and laboratory personnel) were unaware of the patient’s allocation; 3. Outcomes Assessors.
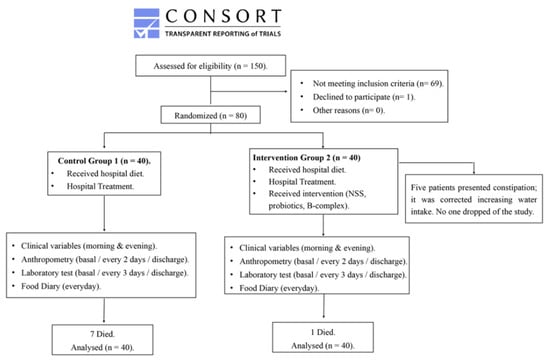
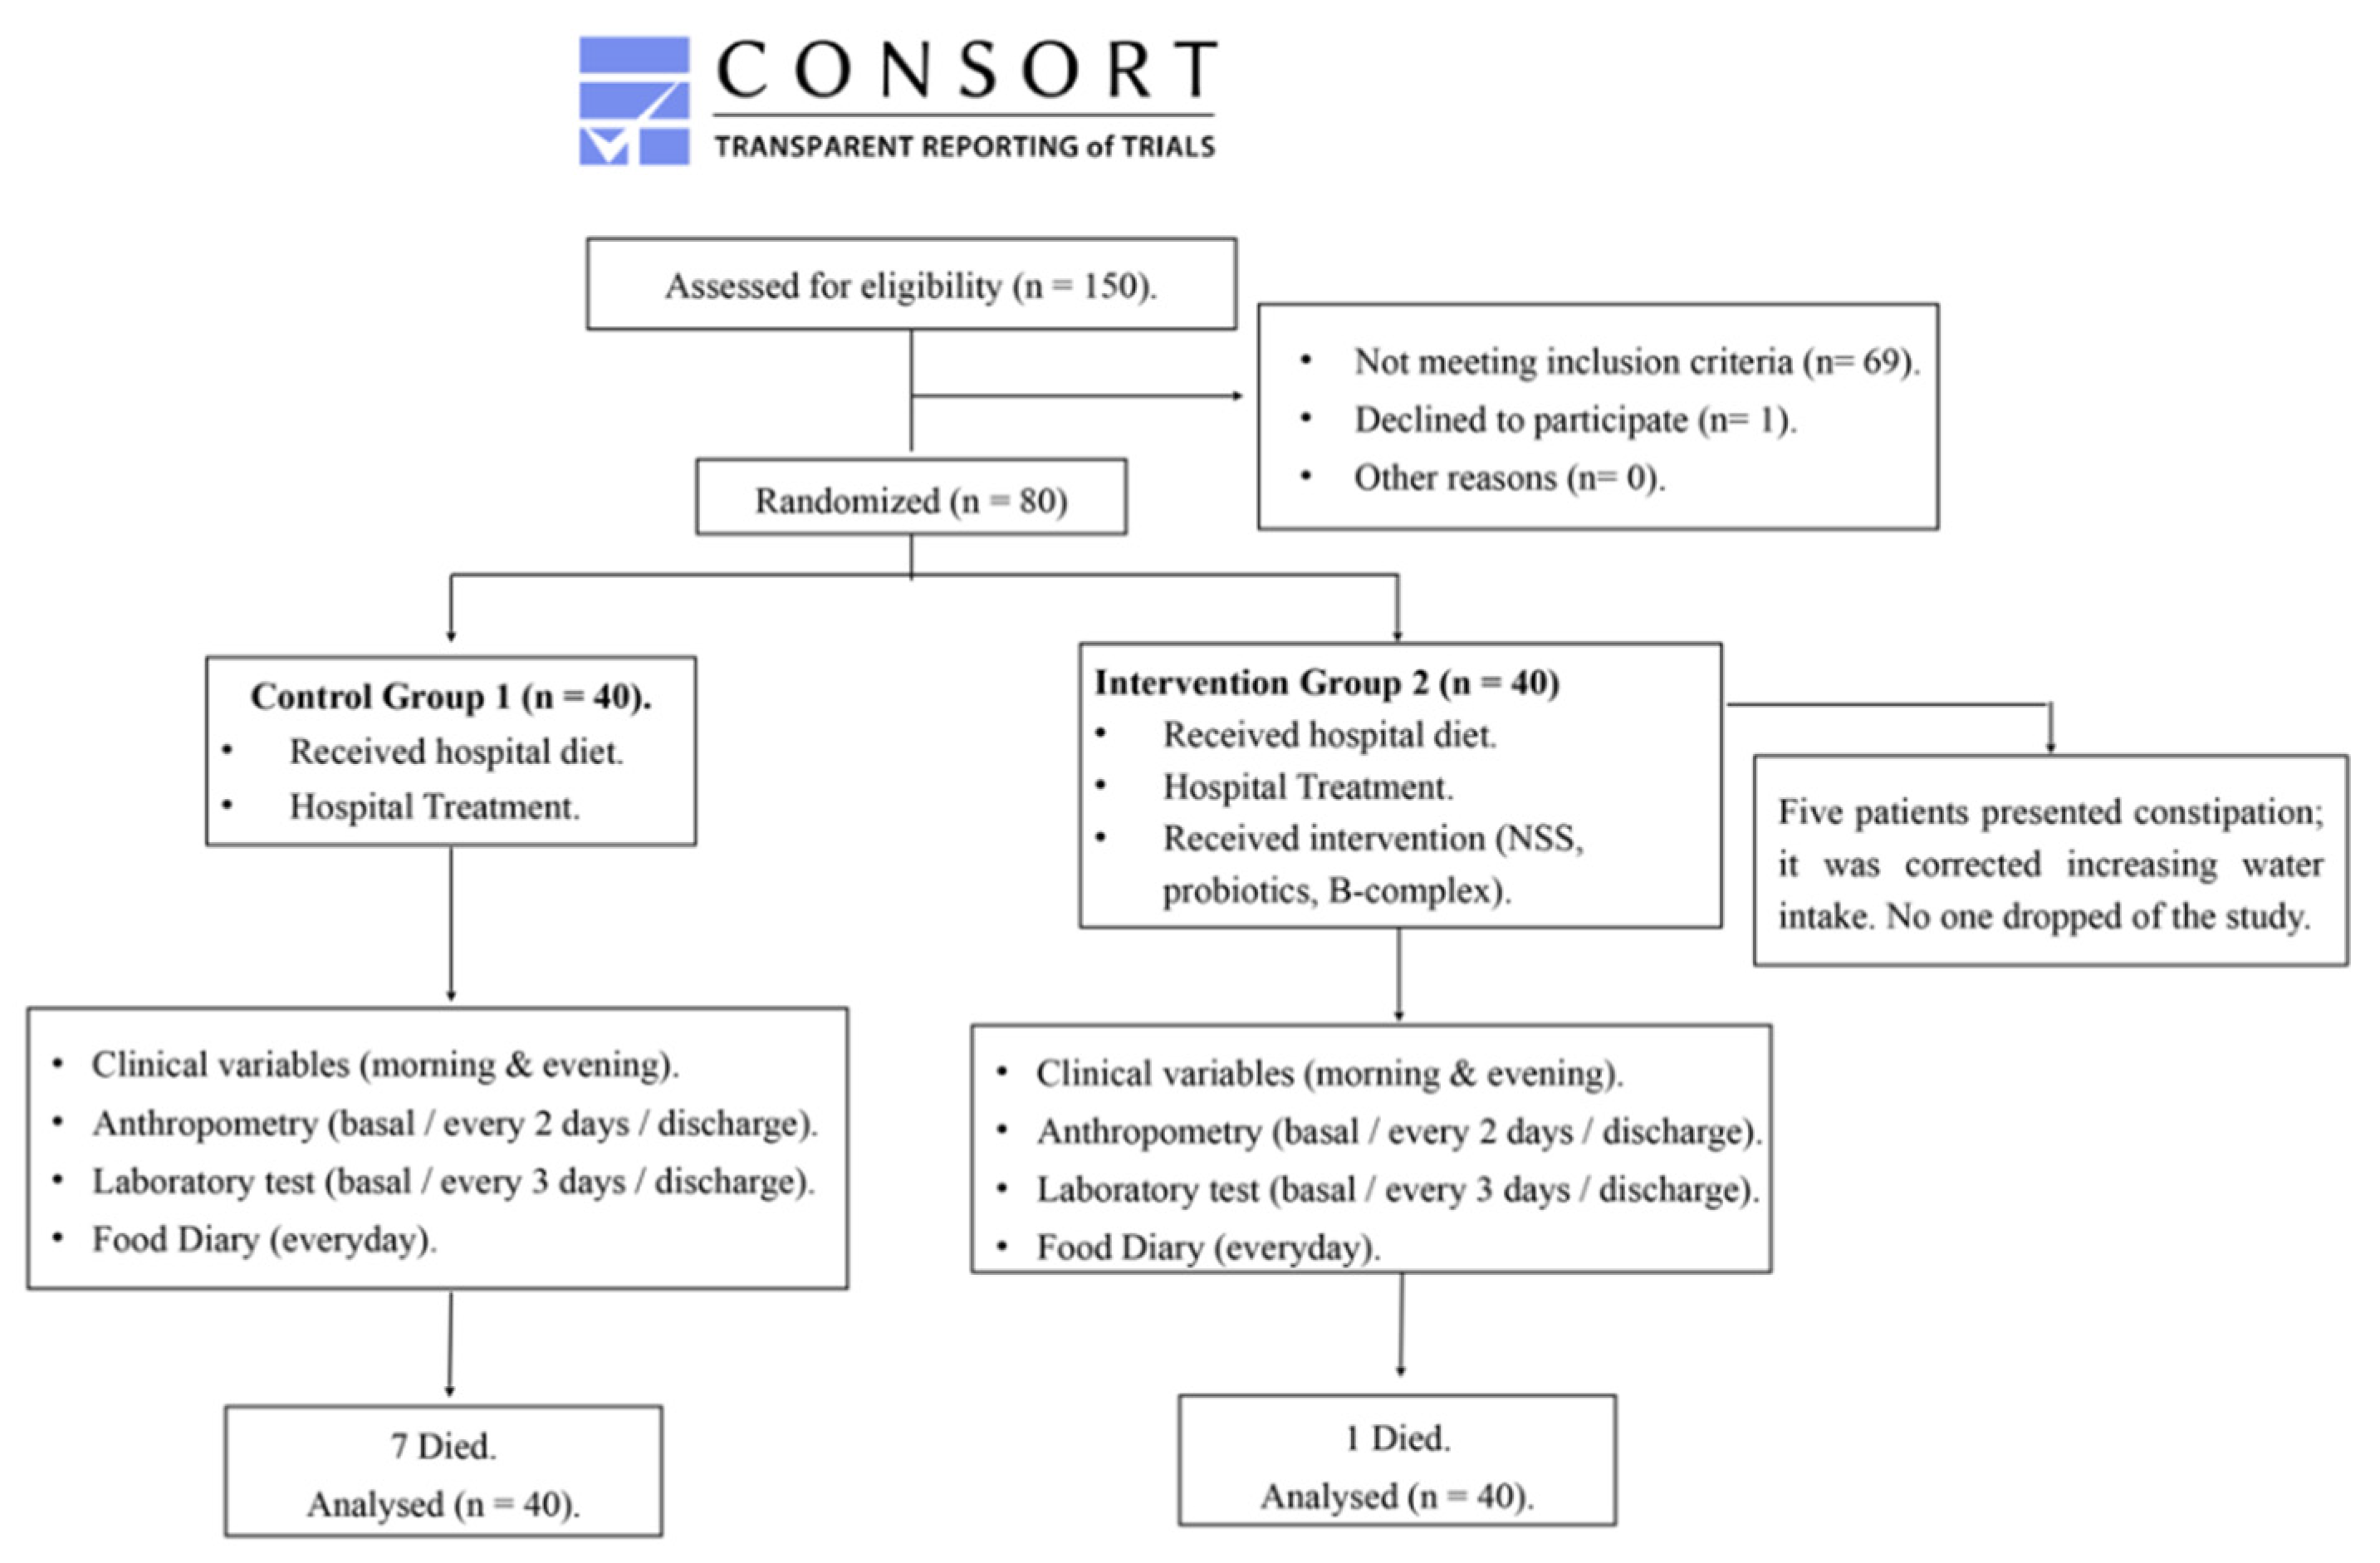
One hundred and fifty patients were interviewed, 80 were chosen and randomized, and 40 patients were assigned to each group. The two groups were: 1. Control Group (CG); and 2. Intervention Group (IG) (Figure 1).
Figure 1.
Consort. Transparent reporting trials.
After deaths, there were 33 patients in the CG and 39 patients in the IG who completed the follow-up on day 40. The nutritional adequacy and calculation of all the patients in the study were performed by the hospital nutrition department before they were enrolled in the study; this department did not know the assignment of the patients. The nutritional intake in the baseline was assessed by food diary analysis. Food diaries were applied and collected by the research team; each patient was followed up from the initial interview until hospital discharge.
The IG received the NSS, which consists in:
- (1)
- B-complex: 10 mg of cyanocobalamin, 100 mg of thiamin, and 100 mg of pyridoxine administered intramuscularly every 24 h for the first 5 days.
- (2)
- NSS powder: one envelope orally after morning meals and another after evening meals, diluted in 400 mL of water each, during the whole intervention for a maximum of 21 days. Each envelope contained: Spirulina Maxima 2.5 g, folic acid 5 mg, glutamine 5 g, vegetable protein 10 g, constituted by two foods without processing or fragmenting in amino acids, brewer’s yeast, and amaranth, ascorbic acid 1 g, zinc 20 mg, selenium 100 mcg, cholecalciferol 2000 IU, resveratrol 200 mg, Omega-3 fatty acids 1 g, L-Arginine 750 mg, inulin 20 g, and magnesium 400 mg.
- (3)
- Probiotics: Saccharomyces boulardii (SB) 500 mg daily for 6 days orally.
Table 1 summarize the effects of the nutrients contained in the NSS.
Table 1.
Biological functions of NSS components.
The clinical staff, evaluators, and patients were unaware of the treatment assignments. The research team was responsible for the administration of the NSS without any other patient or treating physician in the study being aware of it.
Discharge criteria were: spO2 > 90% with a minimum of 2 L of supplemental oxygen, BR < 20 bpm, T° < 37 °C, with no data of sepsis.
2.3. Clinical and Laboratory Monitoring
Patients were evaluated before starting the study and during their hospital stay by physical examination, vital signs (spO2, HR, BR, BP, and T°), food diary, lipid profile, glucose, serum electrolytes, liver function tests, renal function, hematic biometry, procalcitonin, ferritin, CPR, fibrinogen, and D-dimer every third day. Clinical tests were applied such as: MNA, PHQ-9, Bristol scale, and q-SOFA.
2.4. Statistical Analysis
Data distribution in numerical variables was analyzed using Shapiro–Wilk normality test. For the analysis of overall survival and mortality, progression to ventilation, and survival and mortality in intubated patients, Kaplan–Meier curves and significant difference by Log-Rank were used.
For the intergroup comparison analysis of the numerical variables, a t-test or Mann–Whitney test was used. For the intragroup analysis, paired t-test or Wilcoxon test was used.
For the analysis of qualitative variables, the Fisher’s exact test (one-sided) was used; p values ≤ 0.05 were considered indicative of statistical significance. The programs used were Prism 6 and SPSS Statistics version 25.
2.5. Sample Size
The sample size was calculated using the following formula: n = , where: confidence level 95% (z = 1.96), p = 0.975, q = 0.025, with a margin of error of 5% (e = 0.05), obtaining 38 patients per group.
2.6. Ethical Aspects
Informed consent was obtained from all participants. The Declaration of Helsinki, the Nuremberg Code, and the Mexican Standard NOM-012-SSA3-2012 were considered. The research was approved by the research committee of the Faculty of Health Sciences of the Universidad Anáhuac México Norte, registration number: 202062, CONBIOETICA-15-CEI-004-20160729, the research committee of the CMI Toluca, registration number: 207C0401010201S/JIC/155/2020, and Clinical Trials registration code: NCT04507867.
3. Results
Eighty patients were chosen and randomized, and 40 were assigned to each group. After the deaths, 33 CG patients and 39 IG patients completed follow-up at day 40.
3.1. Baseline Results
Clinical, demographic, and biochemical characteristics were compared in both groups at baseline and the results are shown in Table 2A,B. No significant difference was found in any item.
Table 2.
(A) Demographic and clinical characteristics at baseline of CG and IG. (B) Clinical and biochemical characteristics at baseline of CG and IG.
Adherence to the treatment was strictly supervised by the research team, and more than 95% of the participants complied with the treatment. A food diary was kept for each patient, estimating their caloric intake. The average kcal consumed at the beginning of the study in the CG was 1411 kcal/day, and in the IG, 1376 kcal/day. On the third day the consumption in the CG was 1597 kcal/day, and in the IG, 1773 kcal/day, with a 23% difference in caloric intake in favor of the IG.
3.2. Survival and Mortality of the Studied Patients
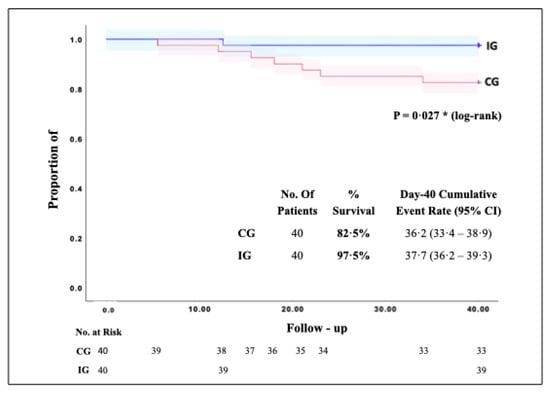
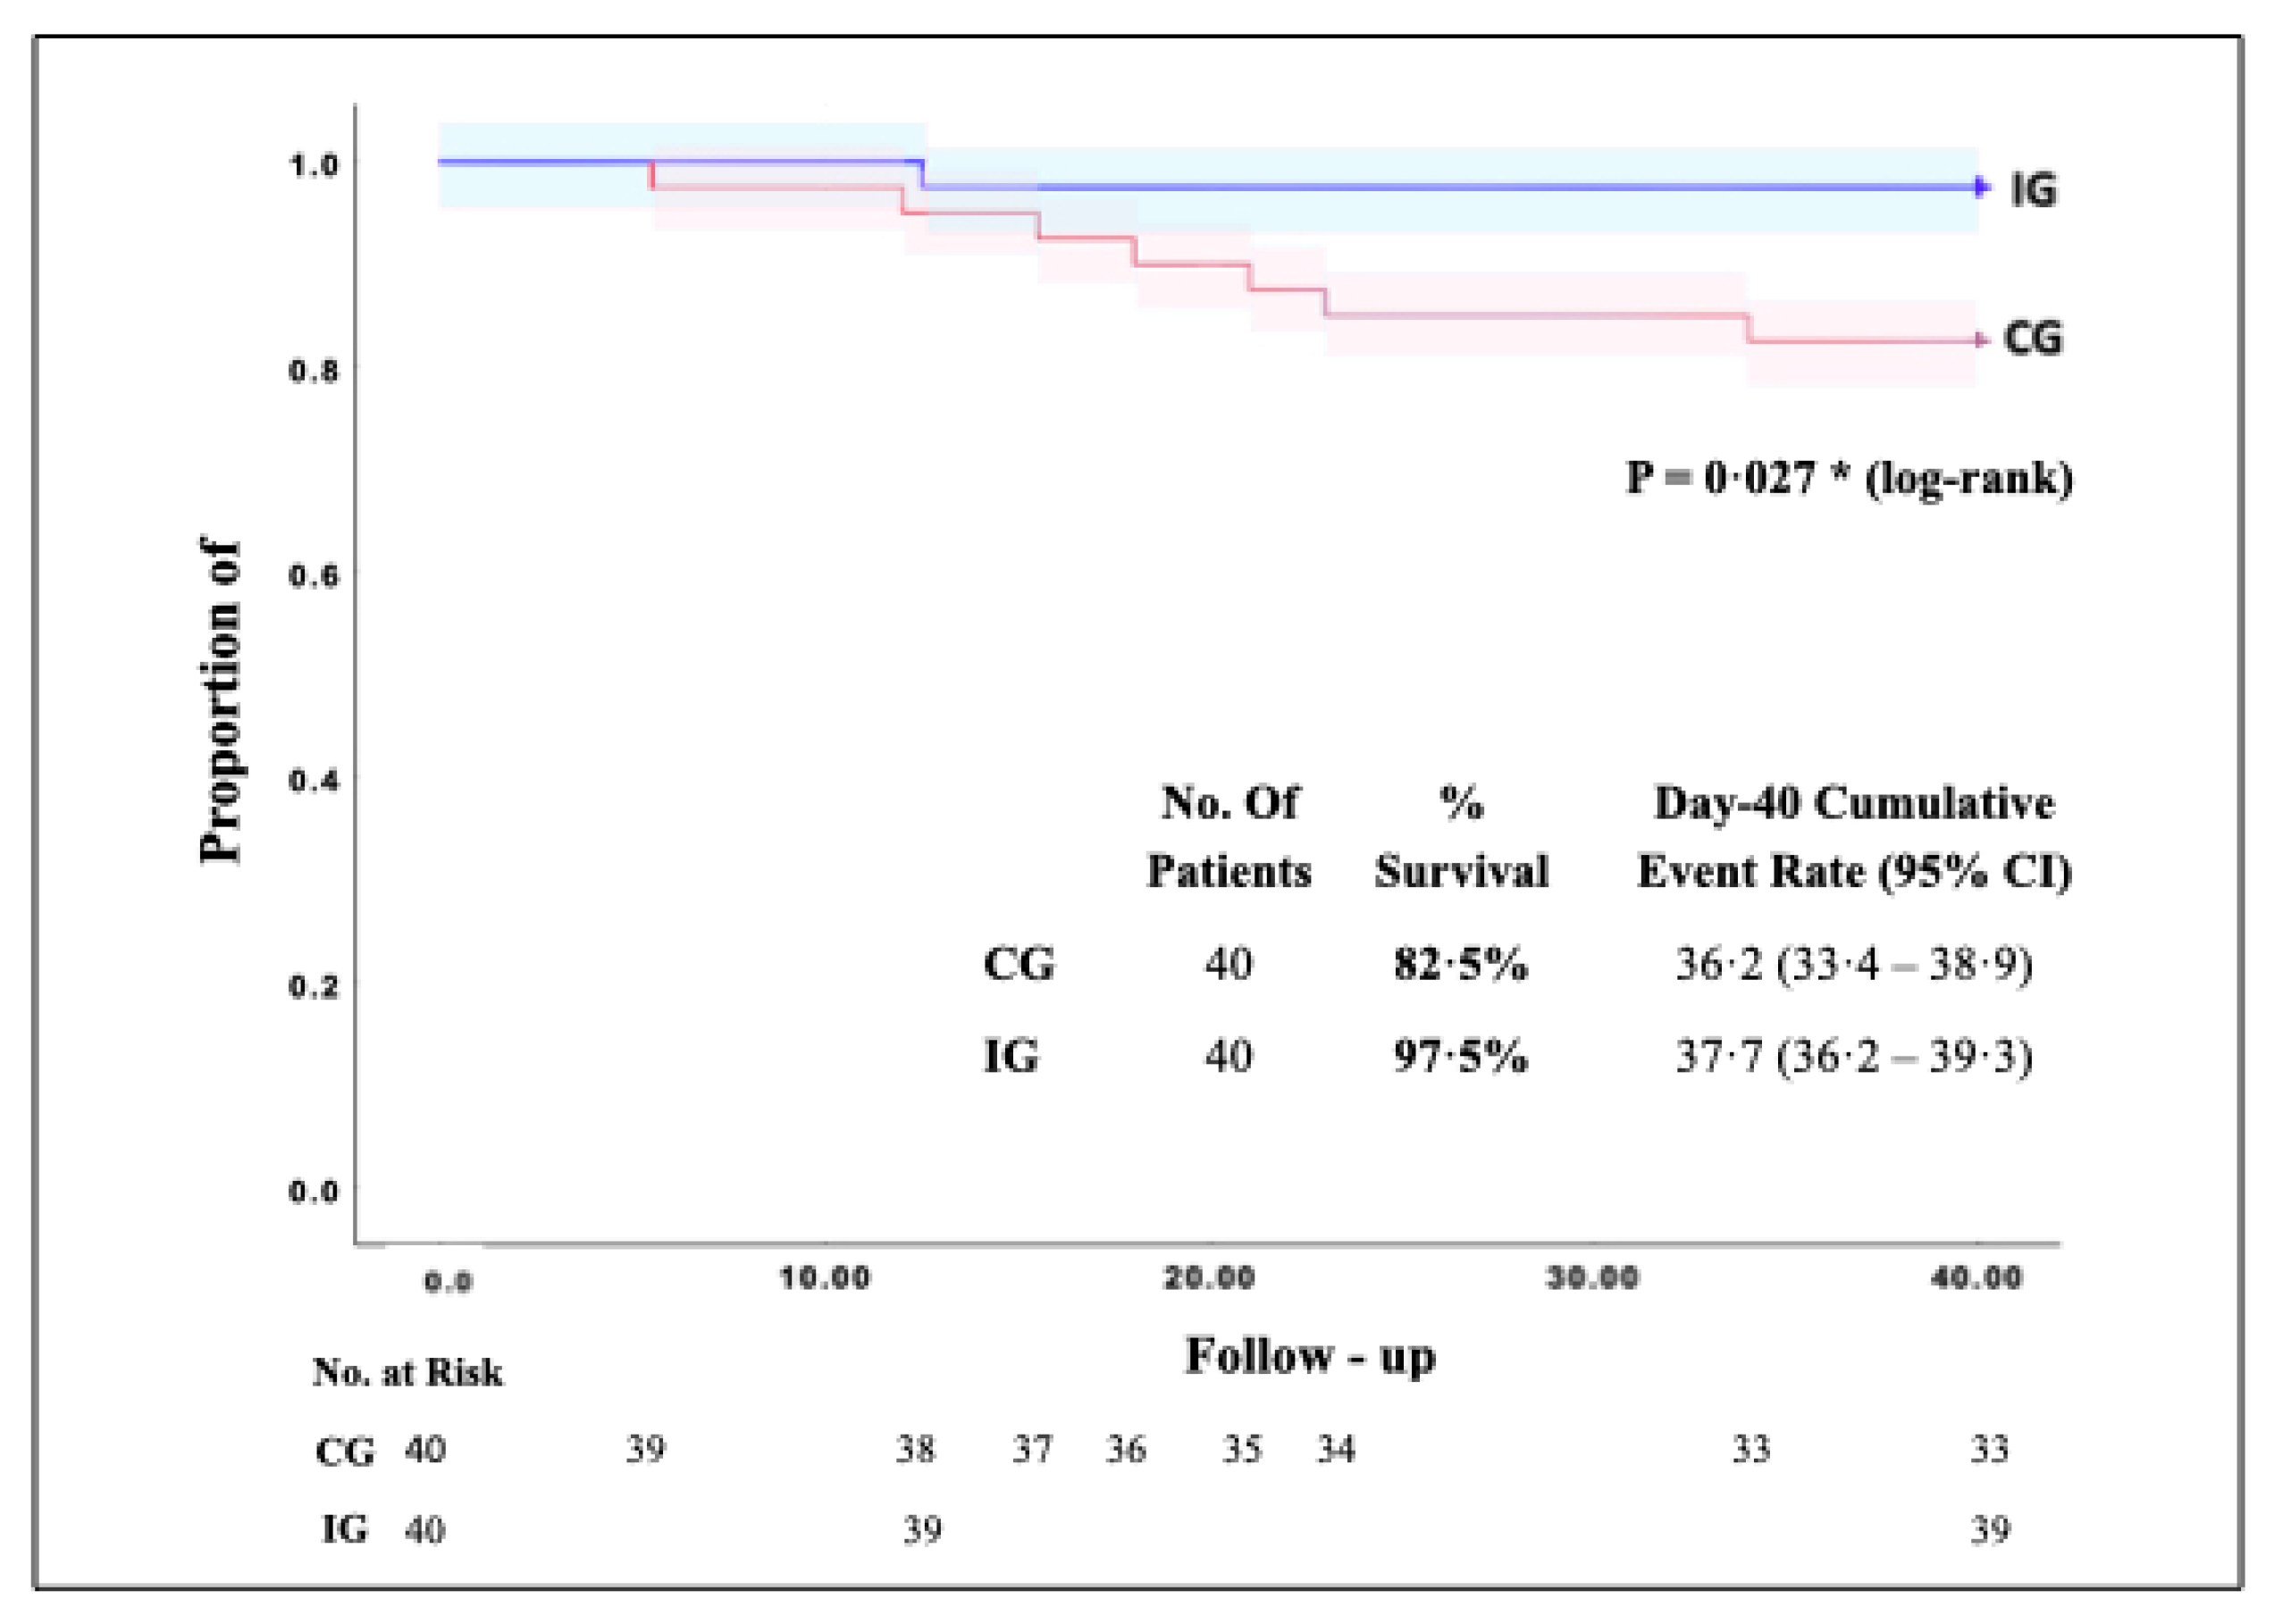
Overall survival and mortality at day 40 are shown in Figure 2. Seven of 40 patients died in the CG (survival 82.5%, mortality 17.5%, median survival 36.22 days, 95% confidence interval (CI), 33.46 to 38.98 days), while one of 40 patients died in the IG (survival 97.5%, mortality 2.5%, median survival 39.31 days, 95% (CI), 37.98 to 40.64 days). In the IG (survival increased and mortality decreased compared to the CG) p = 0.027 (Log Rank). All the deceased patients were male.
Figure 2.
Kaplan–Meier general survival curve from CG and IG patients. The proportion of patients in the IG (blue line) and the CG (red line) included in the study and completed a 40-day follow-up from September to April 2021. The cumulative proportion of surviving patients was estimated with the Kaplan–Meier method and compared in both groups, from the CG died seven of 40 patients (surveillance 97.5%, mean 39.31%, 95% of (CI), 37.98 to 40.64). This showed a significant difference of IG compared to CG * p = 0.027 (Log Rank test, 95% of (CI).
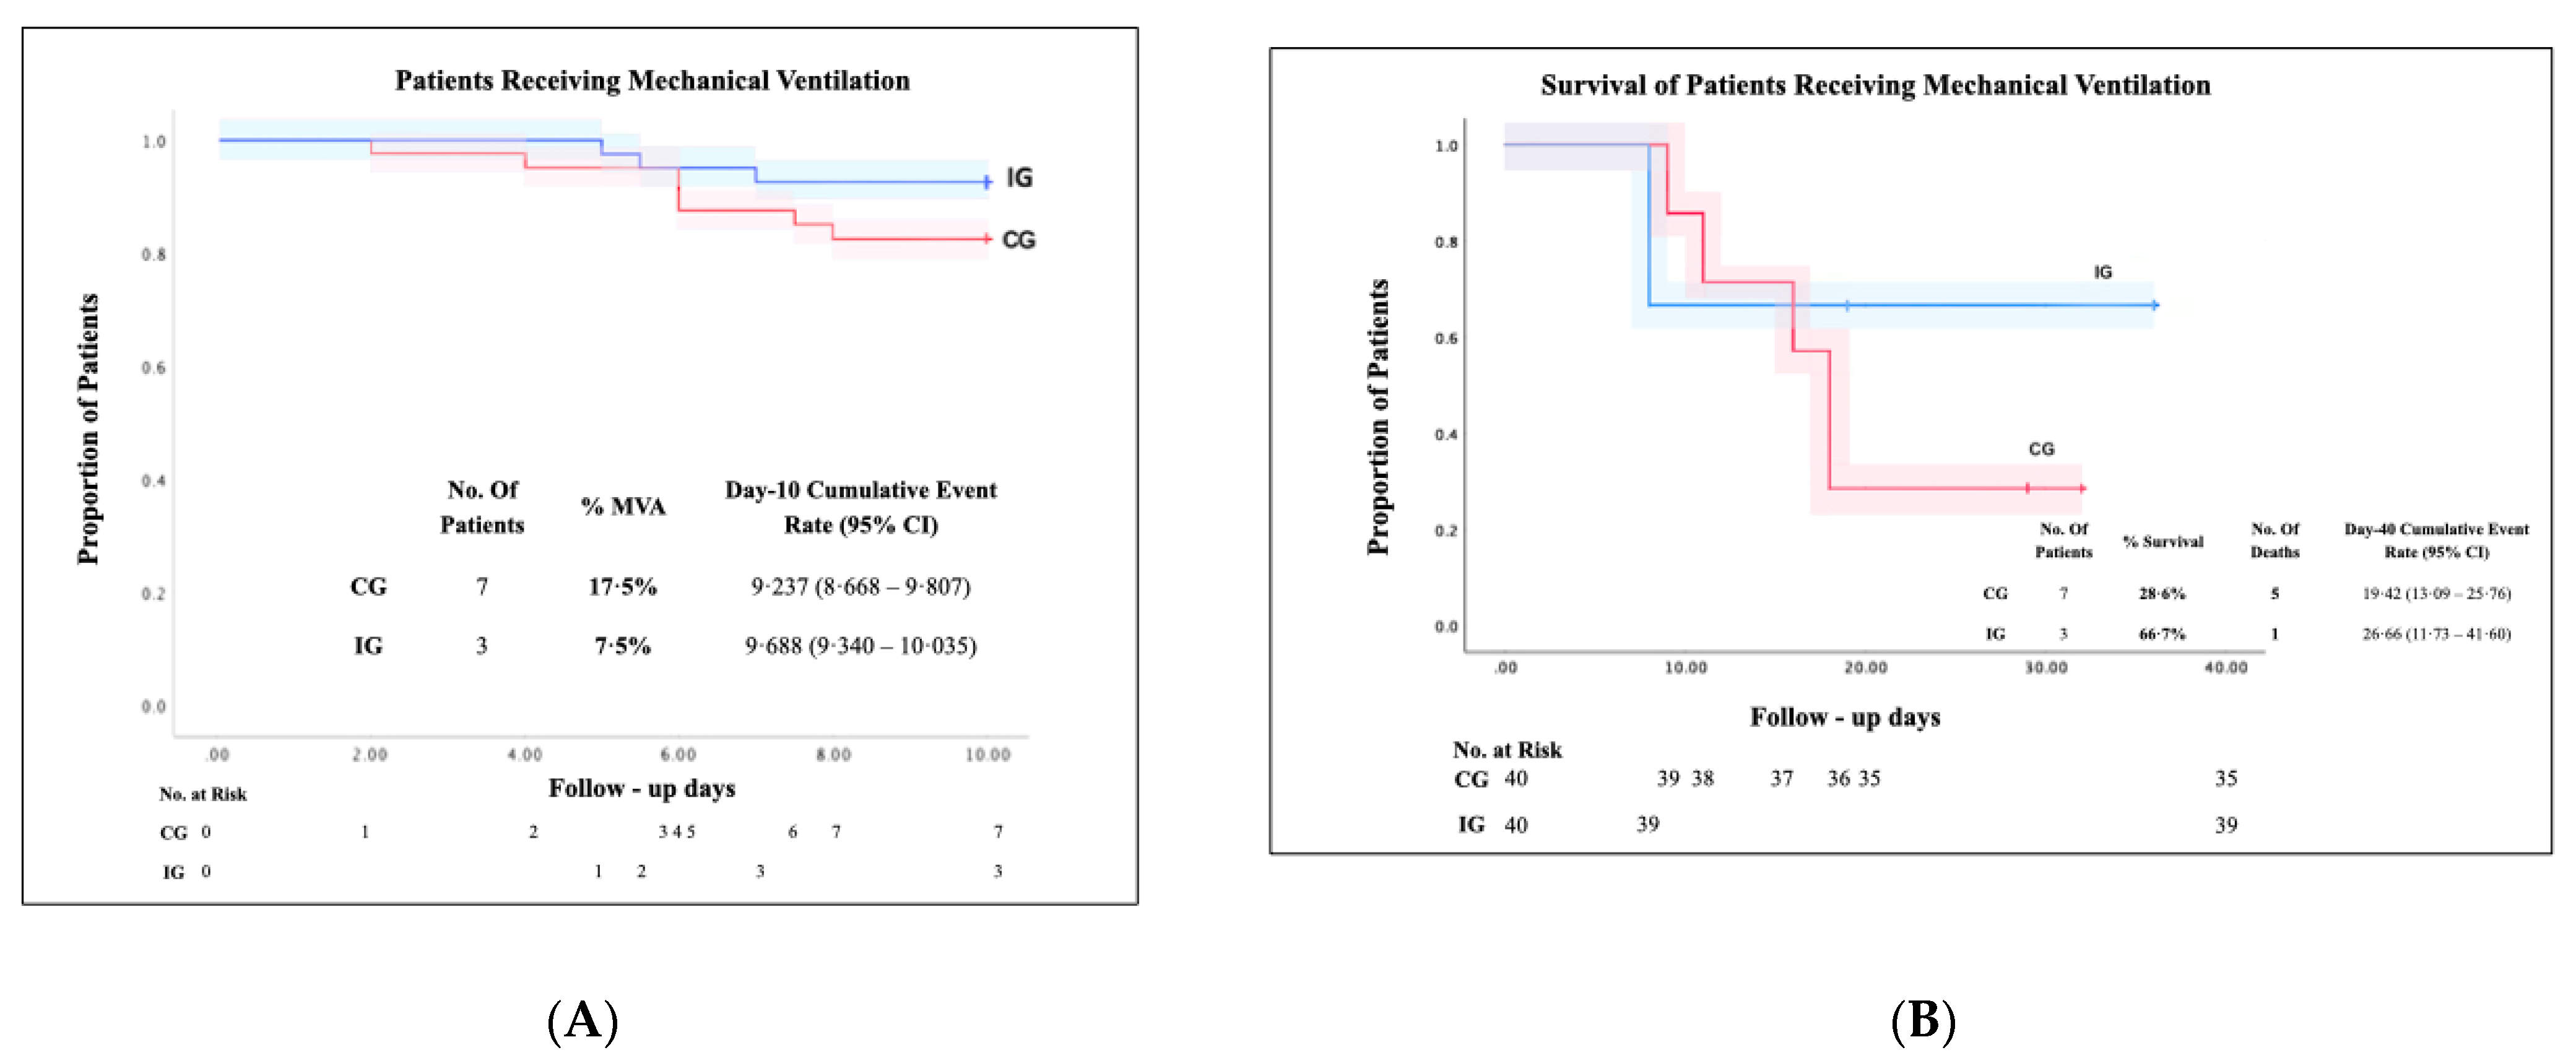
Of the patients who progressed to MVA, seven were from CG (17.5%) and three from IG (7.5%), representing a 10% decrease in IG compared to CG (Figure 3A). Survival in CG corresponded to two of seven patients (28.6%), while in IG two of three patients (66.7%) survived, increasing survival in IG by 38.1% compared to CG, and decreasing mortality to 33.3% of patients with MVA in IG compared to 71.4% in CG (Figure 3B).
Figure 3.
The proportion of patients with MVA from CG and the IG were included in the study and completed 40-day follow-up from September 2020 to April 2021. (A): IG and CG were analyzed with the Kaplan–Meier method comparing both groups to MVA progression, from CG seven patients progressed to MVA (17.5%, mean 9.68%, (CI) of 95%, 8.66 to 9.80); meanwhile, MVA progression of IG in comparison with CG. (B): In overall survival and mortality with MVA, five out of seven patients died in CG) 71.4%, mean 19.42, (CI) of 95%, 13.09 to 25.76). One out of three patients died in IG (33.5%, mean 26.66, (CI) of 95% 11.73 to 41.6), this represents the 38.1% decrease in mortality with MVA in IG compared to CG.
In the analysis of the days with MVA of the patients who survived, the CG presented a mean of 26 days ± 2.83 while the IG presented 11 days ± 0, decreasing 15 days with MVA in favor of the IG.
The oxygen flow administered to maintain spO2 > 90% from baseline to day three was analyzed in both groups. In the CG a mean of 5.9 L (±3.8) was found in the baseline in 6 L (±4.4) at day three, while the IG presented a mean of 6 L (±3.2) in the baseline and 4.5 L (±3.5) at day three, which represents a significant difference in the decrease in oxygen flow in the IG (p = 0.014, Wilcoxon test). In addition, the presence of spO2 > 90% at day three was analyzed between both groups after oxygen supplementation. In the CG, 85% of the patients showed progress as did 92.5% in the IG, with a difference of 7.5% in favor of the IG.
To evaluate prognosis, the qSOFA scale was applied and the baseline was analyzed and compared to day three in both groups. The CG presented a mean of 0.425 points (±0.594) at baseline and a mean of 0.512 points (±0.571) at day three, while the IG presented a mean of 0.65 points (±0.62 at baseline and 0.43 points (±0.496) at day three, representing an improvement in the prognosis of the IG (p = 0.040, Wilcoxon test).
The gastrointestinal function was analyzed through average bowel movements, abdominal distention, and the Bristol scale, reflecting a clinical improvement in IG (Table 2A).
The depressive state was assessed using the PHQ-9 questionnaire at baseline and hospital discharge. In the CG a mean of 3.66 points (±2.5) was obtained at baseline and 1.9 points (±1.4) at day three, presenting a significant difference in the improvement of mood in the IG patients (p = 0.003, Mann–Whitney test). The above results are shown in Table 3A. Table 3B shows laboratory data that were associated with overall mortality.
Table 3.
(A) Clinical evolution and 40-day follow-up. (B) Association of baseline laboratory parameters and general mortality.
3.3. Follow-Up
Patients who survived had a follow-up on day 40. Analysis of spO2 without supplemental oxygen was performed. In the CG, a mean of 90.30% (±3.4) was presented while the IG presented a mean of 92.08% (±2.5), which implies greater progression in spO2 in favor of the IG (p = 0.03, Mann–Whitney test).
At discharge, 85.2% of the CG and 66.7% of the IG required the use of home oxygen use, the CG presented a mean of 57.6 days (±24.6), while the IG presented a mean of 43.8 days (±16.2), a 13.8-day average reduction favoring the IG (Table 3A).
Post-COVID syndrome was analyzed and present in 37.5% of the patients in the CG and 23.5% of the IG (Table 3A). The decrease in body weight was present in 72.2% of the patients in the CG and 44.4% in the IG (Table 3A).
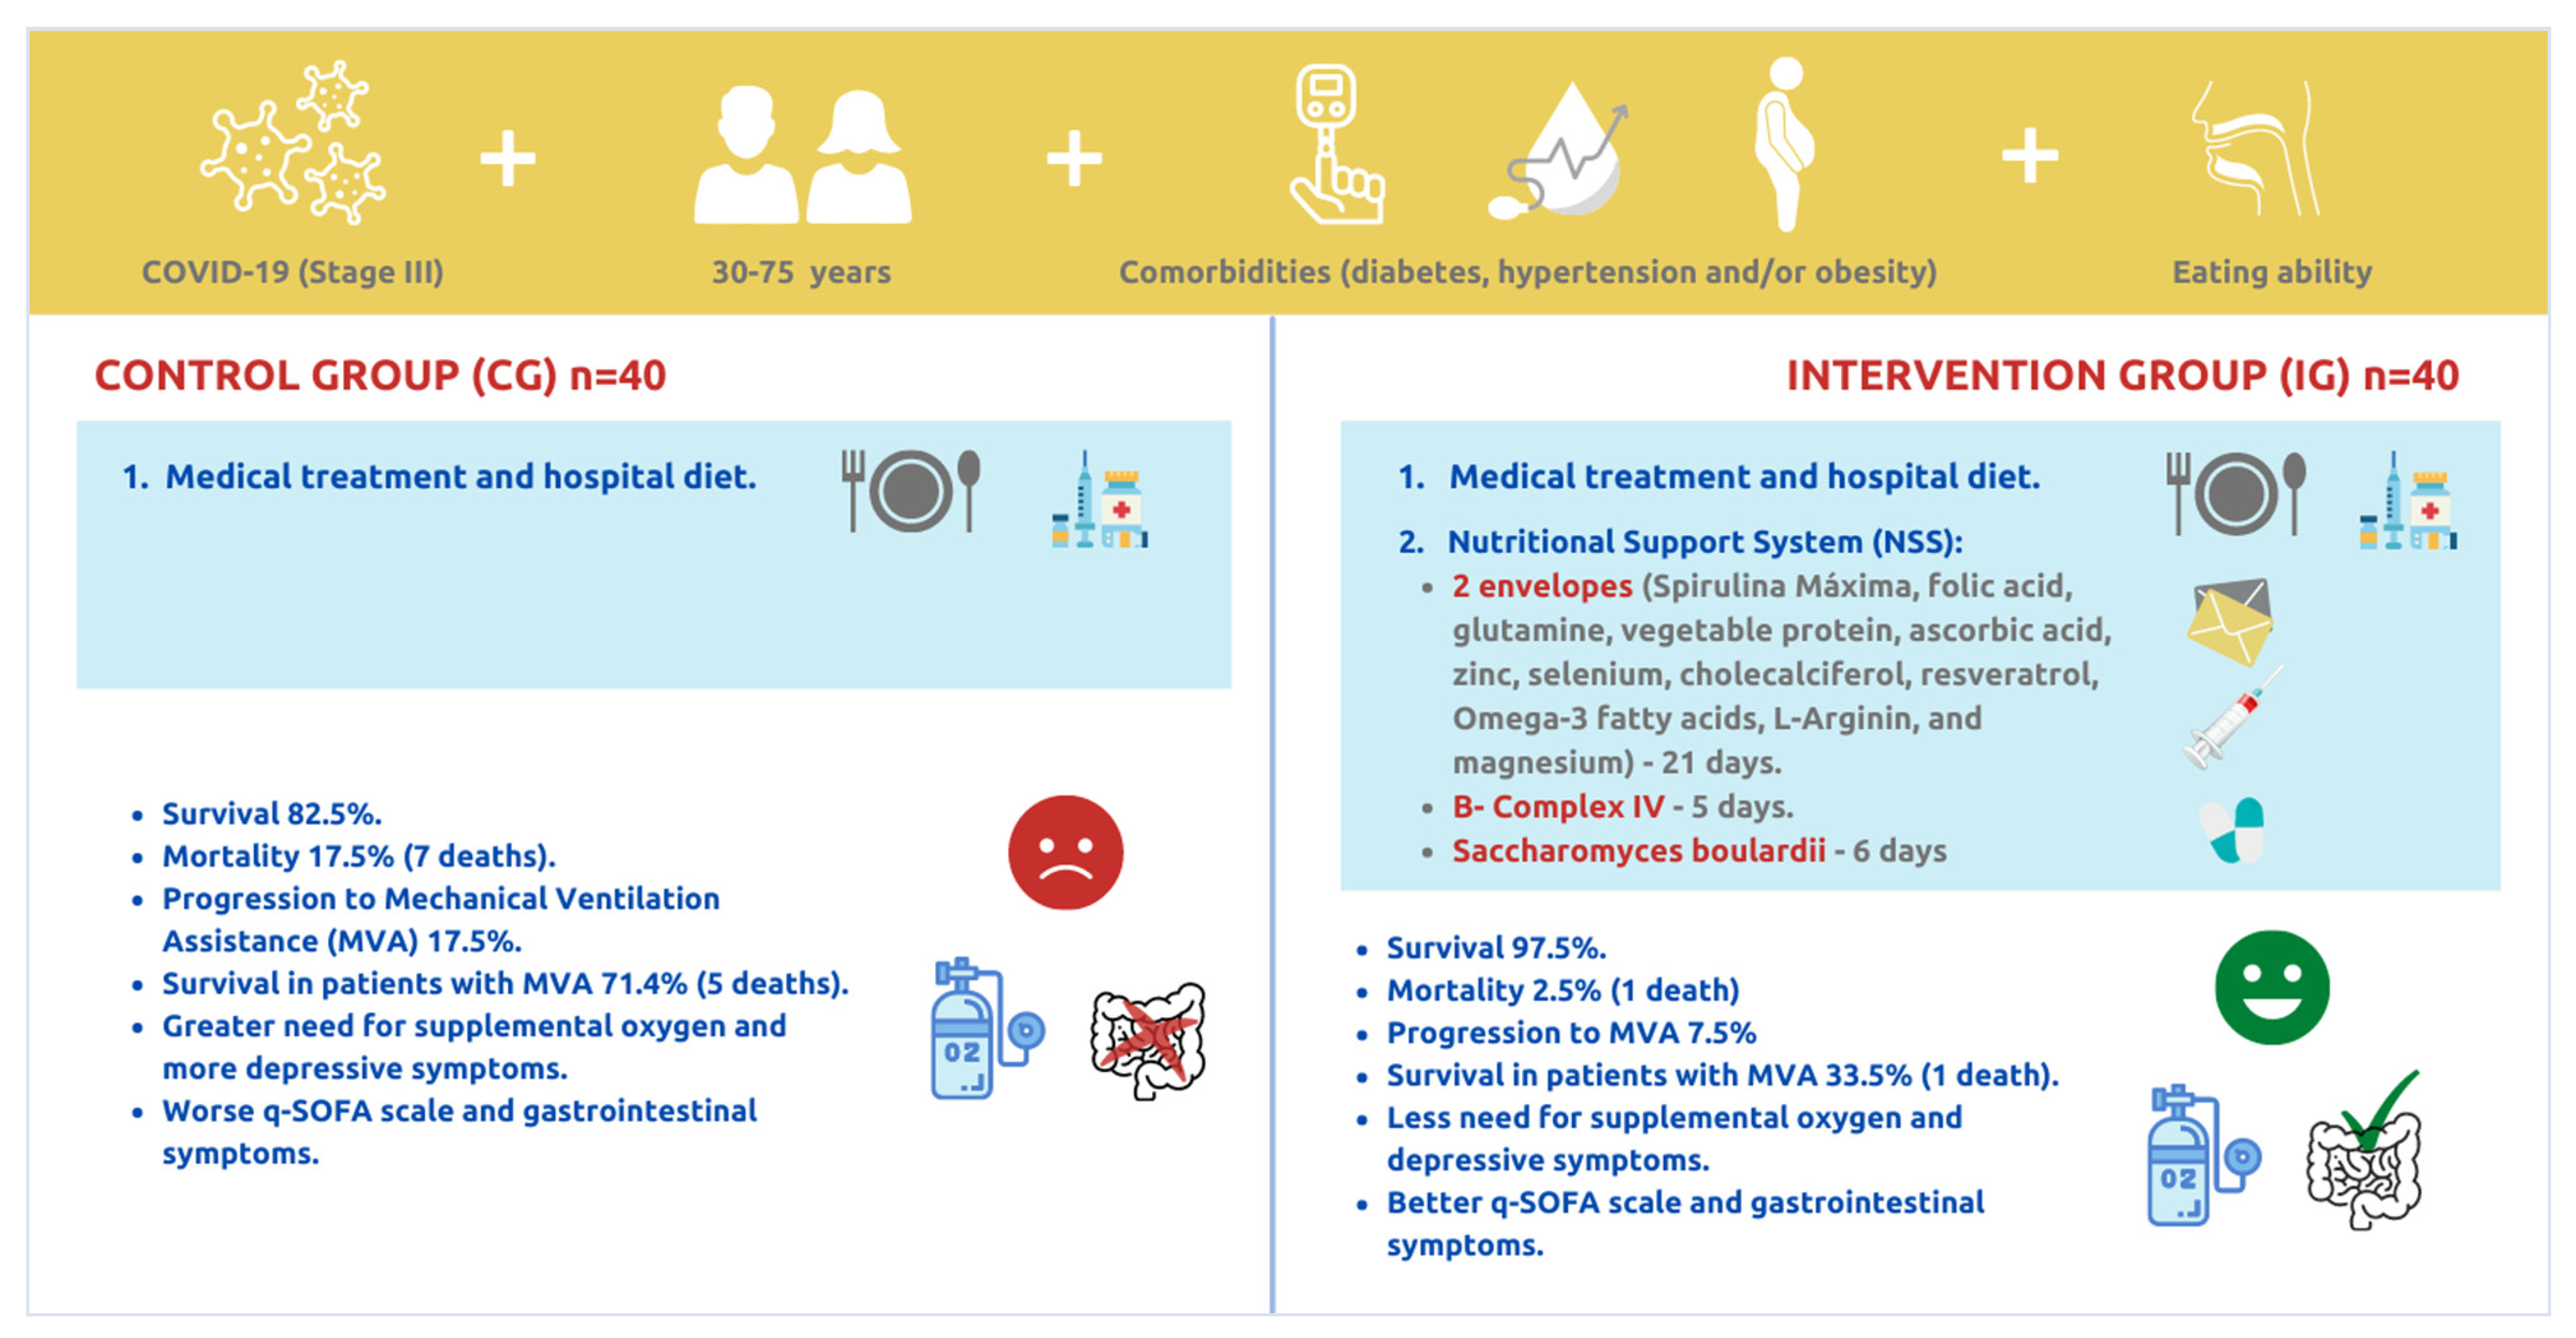
The schematization of the study groups and the primary results are shown in Figure 4.
Figure 4.
Characteristics of the study groups and primary outcomes.
4. Discussion
SARS-CoV-2 is a challenge for researchers due to current therapeutic limitations. Some drugs that have achieved positive results are Tocilizumab, reducing progression to MVA 12% [14], and Remdesivir, decreasing mortality 6.7% at the hospital level. The use of these two drugs in therapy, however, is limited by their side effects [45].
Altered nutritional status is known to be associated with decreased immunity and increased mortality in patients with COVID-19 [46]. It has been reported that decreased appetite and caloric intake are associated with increased synthesis of pro-inflammatory interleukins, mainly TNF-alpha, leading to cachexia [47]. Cachexia is associated with the reduction in glutamine and arginine reserves and the pool of amino acids, this generates alteration of the immune and ventilatory response in COVID-19 [21,48]. It is expected that providing nutritional support to these patients may improve their prognosis.
The MATH+ Hospital Treatment Protocol for COVID-19 guidelines recommend the use of Vitamin D, Zinc, and melatonin, although their evidence on mortality and survival is limited [49]. It is known that the state of mind and the ability to sleep in patients with COVID-19 is associated with survival and mortality [50], it is also known that the consumption of probiotics, amino acids such as tryptophan and glutamine, and B complex, increase the production of neurotransmitters that regulate sleep and state of mind. [51]
In this research, it was observed that NSS in the IG increased survival by 97.5% and reduced mortality by 2.5% compared to CG (p = 0.027). These results are significant, especially considering that hospital mortality worldwide in these patients is 15–20% [52]. The most evident results associated with clinical improvement were observed from day 3, a crucial moment to know the patient’s prognosis and which coincides with the increase in the cytokine storm [53]. At this point, spO2, abdominal distension, stool consistency, appetite, and water intake improved in the IG.
SARS-CoV-2 viral replication is directly associated with mortality [54]. The use of various nutrients in the regulation of different molecular pathways in viral processes has been demonstrated. Masuda et al. described that C-phycocyanin, an extract of Spirulina Maxima, blocks in vitro hemagglutination of viruses such as influenza, and the use of B complex and minerals such as zinc have been studied for their binding to the active site of the nsp 12 and 3C-like protein of SARS-CoV-2, blocking viral RNA transcription [55]. Folic acid (FA) inhibits the furin protease that SARS-CoV-2 needs to enter the host cell and its components (histidine and lepidine) block SARS-CoV-2 transcription and replication by forming hydrogen bonds with the SARS-CoV-2 enzyme 3CL hydrolase, counteracting 3CLpro (Mpro) which counteracts the host innate immune response [19]. It has been seen that when 200 µg/day of selenium is administered, it decreases SARS-CoV-2 transcription and replication, inhibiting the major protease (Mpro) [36].
It is known that dysbiosis is recurrent in SARS-CoV-2 [56] and that clinical improvement is associated with its correction. A microbiota–gut–lung axis has been described that coordinates inflammation and immunity mediated by T lymphocytes, it is dependent on eubiosis and the use of probiotics. Saccharomyces boulardii and Saccharomyces cerevisiae are one of the most studied probiotics due to their immunological effect [26,41]. These activate the Th1 andTh2 response, endocrine regulation, orexigenic factors, endothelial repair, and chemotaxis [37]. According to Youseff et al., the latter is also regulated by vitamin D, decreasing the expression of proinflammatory cytokines (IL-6) and the activation of TNF-alpha [57]. Zhang et al. point out that correcting dysbiosis decreases proinflammatory cytokines (IL-12, IL-6) and neutrophil infiltration in the lungs [58]. In addition, remote effects of this axis, mediated by Short Chain Fatty Acids (SCFA), are known [32,41,59]. One of the components of NSS is inulin. The positive effects of dietary fiber and inulin are known to promote the production of SCFAs by fermentation in the intestine and together with omega-3 PUFAs regulate TNF-alpha which is directly related to the inflammatory cascade and cachexia, two physiological processes related to mortality in patients with COVID-19 [27], especially in overweight, obese, and DM2 patients (Birkeland and Van der Beek) [60,61].
Amino acids such as glutamine and arginine have been used to increment the ventilatory response and they are currently being used to increase alveolar exchange in lung cancer and asthma [21,42] and are also necessary to produce collagen in pulmonary fibroblasts [23]. In SARS-CoV-2; specifically, the viral spike protein is responsible for the entry of SARS-CoV-2 into host cells and harbors arginine residues that modulate the binding of the receptor to the virus membrane [41,62]. Other nutrients such as selenium, and Omega-3 PUFAs participate in alveolar distention together with the surfactant factor [35] and Zinc that inhibits SARS-CoV-2 replication in vitro through inhibition of RNA-dependent RNA polymerase [32].
Patients who did not progress satisfactorily in the present study required MVA; upon admission to intensive care, catabolism, and oxidative stress increase, affecting prognosis; in Mexico, 75% of patients with COVID-19 and MVA die [7]. Related to this, it is known that arginine and glutamine interact in the homeostasis of reactive oxygen species (ROS) regulating oxidative stress. In recent studies, it was demonstrated that the use of 10 g of glutamine three times a day improves saturation and reduces progression to MVA and admission to the Intensive Care Unit (ICU) [47]. On the other hand, thiamine inhibits carbonic anhydrase isoenzymes in vitro and could limit hypoxia and decrease hospitalization in early stages of COVID-19 [63,64].
Progression among intubated patients to MVA was reduced to 10%, while mortality was reduced to 33% in this study. Associated with the result of the qSOFA where the prognosis favored the IG group. Associated with this, the progression of the patients at discharge was favorable for the IG, where the amount of home supplemental oxygen was reduced by 18.5% and 13.8 days less use in contrast to CG patients.
Folic acid, ascorbic acid, and resveratrol are associated with the survival and improvement of patients after infection, which regulate cell apoptosis induced by MERS-CoV-2 due to their anti-inflammatory and metabolic effects [19,32,40]. It is also known that the lymphopenia observed in most SARS-CoV-2 patients is associated with decreased levels of ascorbic acid and arginine. During SARS-CoV-2 infection, ascorbic acid modulates ROS production, decreases glyceraldehyde 3-phosphate dehydrogenase (GAPDH) enzyme activity, preventing cell death, regulation of lymphoid cell production [29] and pneumocyte preservation [32].
Improved mood and melatonin upregulation have been reported to be linked to prognosis in patients with COVID-19. When analyzing PHQ-9, there was a difference in favor of IG patients, which may be related to the gut–brain–microbiota axis [60]. The latter regulates human behavior and the circadian cycle through neurotransmitters such as serotonin, 95% of which is produced in the gut, and dopamine and melatonin, which are generated from microbiota and nutrients such as tryptophan, pyridoxine, nicotinic acid, and cobalamin [16]. It is known that the state of mind and the ability to sleep in patients with COVID-19 is associated with survival and mortality, it is also known that the consumption of probiotics, amino acids such as tryptophan and glutamine, and B complex, the increase the production of neurotransmitters that regulate sleep and state of mind [65].
5. Conclusions
Our study provides important results on the positive effect of NSS on survival and decreased mortality in these hospitalized patients with COVID-19, associating that the use of different nutrients together, in addition to the adequate regulation of the microbiota, is determinant for the clinical improvement, prognosis, and evolution of the disease.
Although more multicenter studies are needed to corroborate the impact of these findings and to replicate the results obtained to recommend their use, this study leaves a precedent of a significant effect in a small sample that may serve other researchers to consider complementing new therapeutic lines.
Author Contributions
Conceptualization: F.L.-M.; data curation: L.A.-B., A.G.-P., D.G.-T. and G.C.-C.; formal analysis: F.L.-M., A.I., G.C.-C. and L.A.-B.; funding acquisition: F.L.-M. and A.I.; investigation: F.L.-M., L.A.-B., A.G.-P., D.G.-T. and G.C.-C.; methodology: F.L.-M., L.A.-B., A.G.-P., D.G.-T. and G.C.-C.; project administration: F.L.-M., L.A.-B., A.G.-P. and D.G.-T.; resources: L.A.-B., A.G.-P., D.G.-T. and M.M.-G.; supervision: F.L.-M.; writing—review, and editing: F.L.-M., A.I., L.A.-B., A.G.-P., D.G.-T. and G.C.-C. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by Centro de Investigación en Ciencias de la Salud (CICSA), Universidad Anáhuac México Campus Norte, authorization number 202062. The funders had no role in study design, data collection, analysis, publication decisions, or preparation of the manuscript.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki, the Nuremberg Code, and the Mexican Standard NOM-012-SSA3-2012. The research was approved by the research committee of the Faculty of Health Sciences of the Universidad Anáhuac México Norte, registration number: 202062, CONBIOETICA-15-CEI-004-20160729, the research committee of the CMI Toluca, registration number: 207C0401010201S/JIC/155/2020, and Clinical Trials registration code: NCT04507867.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Data supporting the reported results can be obtained by contacting the corresponding author.
Acknowledgments
We would like to thank the authorities of Centro Medico ISSEMyM Toluca for providing us with their facilities and equipment as well as the execution of laboratory studies, Alimentos Esenciales para la Humanidad, Telomer Lab SA de CV, and Jesse Adams for supporting us with the review of this article.
Conflicts of Interest
The authors declare that they have no conflict of interest.
References
- Tian, S.; Hu, N.; Lou, J.; Chen, K.; Kang, X.; Xiang, Z.; Chen, H.; Wang, D.; Liu, N.; Liu, D.; et al. Characteristics of COVID-19 infection in Beijing. J. Infect. 2020, 80, 401–406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leguía Valentín, E.D.; Niño Montero, J.S.; Quino Florentini, M.G. Coronavirus causante del síndrome respiratorio de Oriente Medio (MERS-CoV). Rev. Med. Carrion. 2019, 1, 1–15. Available online: http://cuerpomedico.hdosdemayo.gob.pe/index.php/revistamedicacarrionica/article/view/300/208 (accessed on 2 September 2021).
- Covid19.who.int. WHO Coronavirus (COVID-19) Dashboard. 2021. Available online: https://covid19.who.int/ (accessed on 2 September 2021).
- Salud, S. Coronavirus COVID19 Comunicado Técnico Diario. 2021. Available online: https://www.gob.mx/salud/documentos/coronavirus-covid-19-comunicado-tecnico-diario-238449 (accessed on 2 September 2021).
- COVID-19 Tablero México. COVID-19 Tablero México. 2021. Available online: https://datos.covid-19.conacyt.mx/ (accessed on 2 September 2021).
- Salud.edomex.gob.mx. Estadísticas COVID-19|Centro Estatal de Vigilancia Epidemiológica y Control de Enfermedades. 2021. Available online: https://salud.edomex.gob.mx/cevece/estadisticas_covid19 (accessed on 2 September 2021).
- Talanquer, M. La Letalidad Hospitalaria por COVID-19 en México: Desigualdades Institucionales. 2021. Available online: https://datos.nexos.com.mx/la-letalidad-hospitalaria-por-covid-19-en-mexico-desigualdades-institucionales/ (accessed on 2 September 2021).
- Wang, Y.; Liu, Y.; Liu, L.; Wang, X.; Luo, N.; Li, L. Clinical Outcomes in 55 Patients with Severe Acute Respiratory Syndrome Coronavirus 2 Who Were Asymptomatic at Hospital Admission in Shenzhen, China. J. Infect. Dis. 2020, 221, 1770–1774. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhimraj, A.; Morgan, R.L.; Shumaker, A.H.; Lavergne, V.; Baden, L.; Cheng, V.C.-C.; Edwards, K.M.; Gandhi, R.; Muller, W.J.; O’Horo, J.C.; et al. Infectious Diseases Society of America Guidelines on the Treatment and Management of Patients with (COVID-19). IDSA 2021, 1–44. [Google Scholar] [CrossRef] [Scilit]
- Barazzoni, R.; Bischoff, S.C.; Breda, J.; Wickramasinghe, K.; Krznaric, Z.; Nitzan, D.; Pirlich, M.; Singer, P.; endorsed by the ESPEN Council. ESPEN expert statements and practical guidance for nutritional management of individuals with SARS-CoV-2 infection. Clin. Nutr. 2020, 39, 1631–1638. [Google Scholar] [CrossRef] [Scilit]
- Louca, P.; Murray, B.; Klaser, K.; Graham, M.S.; Mazidi, M.; Leeming, E.R.; Thompson, E.; Bowyer, R.; Drew, D.A.; Nguyen, L.H.; et al. Modest effects of dietary supplements during the COVID-19 pandemic: Insights from 445 850 users of the COVID-19 Symptom Study app. BMJ Nutr. Prev. Health 2021, 4, 149–157. [Google Scholar] [CrossRef] [Scilit]
- Castro, M.; Rodríguez, F. Levaduras: Probióticos y prebióticos para mejorar la producción animal. Ciencia y Tecnología Agropecuaria 2005, 6, 26–38. [Google Scholar] [CrossRef] [Scilit]
- Anand, S.; Mande, S.S. Diet, Microbiota and Gut-Lung Connection. Front. Microbiol. 2018, 9, 2147. [Google Scholar] [CrossRef] [Scilit]
- Chen, N.; Zhou, M.; Dong, X.; Qu, J.; Gong, F.; Han, Y.; Qiu, Y.; Wang, J.; Liu, Y.; Wei, Y.; et al. Epidemiological and clinical characteristics of 99 cases of 2019 novel coronavirus pneumonia in Wuhan, China: A descriptive study. Lancet 2020, 395, 507–513. [Google Scholar] [CrossRef] [Scilit]
- Pujadas, E.; Chaudhry, F.; McBride, R.; Richter, F.; Zhao, S.; Wajnberg, A.; Nadkarni, G.; Glicksberg, B.S.; Houldsworth, J.; Cordon-Cardo, C. SARS-CoV-2 viral load predicts COVID-19 mortality. Lancet Respir. Med. 2020, 8, e70. [Google Scholar] [CrossRef] [Scilit]
- Al Sulaiman, K.; Aljuhani, O.; Al Dossari, M.; Alshahrani, A.; Alharbi, A.; Algarni, R.; Al Jeraisy, M.; Al Harbi, S.; Al Katheri, A.; Al Eidan, F.; et al. Evaluation of thiamine as adjunctive therapy in COVID-19 critically ill patients: A two-center propensity score matched study. Crit. Care 2021, 25, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Shakoor, H.; Feehan, J.; Mikkelsen, K.; Al Dhaheri, A.S.; Ali, H.I.; Platat, C.; Ismail, L.C.; Stojanovska, L.; Apostolopoulos, V. Be well: A potential role for vitamin B in COVID-19. Maturitas 2021, 144, 108–111. [Google Scholar] [CrossRef] [Scilit]
- Ratha, S.K.; Renuka, N.; Rawat, I.; Bux, F. Prospective options of algae-derived nutraceuticals as supplements to combat COVID-19 and human coronavirus diseases. Nutrition 2021, 83, 111089. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Acosta-Elias, J.; Espinosa-Tanguma, R. The Folate Concentration and/or Folic Acid Metabolites in Plasma as Factor for COVID-19 Infection. Front. Pharmacol. 2020, 11, 1062. [Google Scholar] [CrossRef] [Scilit]
- Serseg, T.; Benarous, K.; Yousfi, M. Hispidin and Lepidine E: Two Natural Compounds and Folic Acid as Potential Inhibitors of 2019-novel Coronavirus Main Protease (2019-nCoVMpro), Molecular Docking and SAR Study. Curr. Comput. Aided Drug Des. 2021, 17, 469–479. [Google Scholar] [CrossRef] [Scilit]
- Cengiz, M.; Uysal, B.B.; Ikitimur, H.; Ozcan, E.; Islamoğlu, M.S.; Aktepe, E.; Yavuzer, H.; Yavuzer, S. Effect of oral l-Glutamine supplementation on Covid-19 treatment. Clin. Nutr. Exp. 2020, 33, 24–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bharadwaj, S.; Singh, M.; Kirtipal, N.; Kang, S.G. SARS-CoV-2 and Glutamine: SARS-CoV-2 Triggered Pathogenesis via Metabolic Reprograming of Glutamine in Host Cells. Front. Mol. Biosci. 2021, 7, 627842. [Google Scholar] [CrossRef] [Scilit]
- Vanhove, K.; Derveaux, E.; Graulus, G.-J.; Mesotten, L.; Thomeer, M.; Noben, J.-P.; Guedens, W.; Adriaensens, P. Glutamine Addiction and Therapeutic Strategies in Lung Cancer. Int. J. Mol. Sci. 2019, 20, 252. [Google Scholar] [CrossRef] [Scilit]
- Dy, A.B.C.; Tanyaratsrisakul, S.; Voelker, D.R.; Ledford, J.G. The Emerging Roles of Surfactant Protein-A in Asthma. J. Clin. Cell. Immunol. 2018, 9, 553. [Google Scholar] [CrossRef]
- Hamanaka, R.B.; O’Leary, E.M.; Witt, L.J.; Tian, Y.; Gökalp, G.A.; Meliton, A.Y.; Dulin, N.O.; Mutlu, G.M. Glutamine Metabolism Is Required for Collagen Protein Synthesis in Lung Fibroblasts. Am. J. Respir. Cell Mol. Biol. 2019, 61, 597–606. [Google Scholar] [CrossRef] [Scilit]
- Iddir, M.; Brito, A.; Dingeo, G.; Del Campo, S.S.F.; Samouda, H.; La Frano, M.R.; Bohn, T. Strengthening the Immune System and Reducing Inflammation and Oxidative Stress through Diet and Nutrition: Considerations during the COVID-19 Crisis. Nutrients 2020, 12, 1562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maneira, C.; Bermejo, P.M.; Pereira, G.A.G.; de Mello, F.D.S.B. Exploring G protein-coupled receptors and yeast surface display strategies for viral detection in baker’s yeast: SARS-CoV-2 as a case study. FEMS Yeast Res. 2021, 21, foab004. [Google Scholar] [CrossRef] [Scilit]
- De Sousa Cavalcante, L.; Costa-Silva, T.A.; Souza, T.A.; Ienne, S.; Monteiro, G. Chemogenomic study of gemcitabine using Saccharomyces cerevisiae as model cell—Molecular insights about chemoresistance. Braz. J. Microbiol. 2020, 51, 489–496. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fowler, A.A., III; Truwit, J.D.; Hite, R.D.; Morris, P.E.; Dewilde, C.; Priday, A.; Fisher, B.; Thacker, L.R., 2nd; Natarajan, R.; Brophy, D.F.; et al. Effect of Vitamin C Infusion on Organ Failure and Biomarkers of Inflammation and Vascular Injury in Patients with Sepsis and Severe Acute Respiratory Failure. JAMA 2019, 322, 1261. [Google Scholar] [CrossRef] [Scilit]
- Mejia, L.; Alvarado, A. Vitamina C como antioxidante en el manejo del SARS-CoV-2. Rev. Colomb. Endocrinol. Diabetes Metab. 2020, 7, 99–101. [Google Scholar] [CrossRef] [Scilit]
- Vollbracht, C.; Kraft, K. Feasibility of Vitamin C in the Treatment of Post Viral Fatigue with Focus on Long COVID, Based on a Systematic Review of IV Vitamin C on Fatigue. Nutrients 2021, 13, 1154. [Google Scholar] [CrossRef] [Scilit]
- Pormohammad, A.; Monych, N.K.; Turner, R.J. Zinc and SARS-CoV-2: A molecular modeling study of Zn interactions with RNA-dependent RNA-polymerase and 3C-like proteinase enzymes. Int. J. Mol. Med. 2020, 47, 326–334. [Google Scholar] [CrossRef] [Scilit]
- Doboszewska, U.; Wlaź, P.; Nowak, G.; Młyniec, K. Targeting zinc metalloenzymes in COVID-19. Br. J. Pharmacol. 2020, 177, 4887–4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bermano, G.; Méplan, C.; Mercer, D.K.; Hesketh, J.E. Selenium and viral infection: Are there lessons for COVID-19? Br. J. Nutr. 2021, 125, 618–627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rakib, A.; Nain, Z.; Sami, S.A.; Mahmud, S.; Islam, A.; Ahmed, S.; Siddiqui, A.B.F.; Babu, S.M.O.F.; Hossain, P.; Shahriar, A.; et al. A molecular modelling approach for identifying antiviral selenium-containing heterocyclic compounds that inhibit the main protease of SARS-CoV-2: An in-silico investigation. Brief. Bioinform. 2021, 22, 1476–1498. [Google Scholar] [CrossRef] [Scilit]
- Staples, S.; Wall, S.B.; Li, R.; Tipple, T.E. Selenium-independent antioxidant and anti-inflammatory effects of thioredoxin reductase inhibition in alveolar macrophages. Life Sci. 2020, 259, 118285. [Google Scholar] [CrossRef] [Scilit]
- Malik, M.; Suboc, T.M.; Tyagi, S.; Salzman, N.; Wang, J.; Ying, R.; Tanner, M.J.; Kakarla, M.; Baker, J.E.; Widlansky, M.E. Lactobacillus plantarum 299v Supplementation Improves Vascular Endothelial Function and Reduces Inflammatory Biomarkers in Men with Stable Coronary Artery Disease. Circ. Res. 2018, 123, 1091–1102. [Google Scholar] [CrossRef] [Scilit]
- Ling, S.F.; Broad, E.; Murphy, R.; Pappachan, J.M.; Pardesi-Newton, S.; Kong, M.F.; Jude, E.B. High-Dose Cholecalciferol Booster Therapy is Associated with a Reduced Risk of Mortality in Patients with COVID-19: A Cross-Sectional Multi-Centre Observational Study. Nutrients 2020, 12, 3799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdrabbo, M.; Birch, C.M.; Brandt, M.; Cicigoi, K.A.; Coffey, S.J.; Dolan, C.C.; Dvorak, H.; Gehrke, A.C.; Gerzema, A.E.L.; Hansen, A.; et al. Vitamin D and COVID-19: A review on the role of vitamin D in preventing and reducing the severity of COVID-19 infection. Protein Sci. 2021, 30, 2206–2220. [Google Scholar] [CrossRef] [Scilit]
- Ramdani, L.H.; Bachari, K. Potential therapeutic effects of Resveratrol against SARS-CoV-2. Acta Virol. 2020, 64, 276–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weill, P.; Plissonneau, C.; Legrand, P.; Rioux, V.; Thibault, R. May omega-3 fatty acid dietary supplementation help reduce severe complications in Covid-19 patients? Biochimie 2020, 179, 275–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reizine, F.; Lesouhaitier, M.; Gregoire, M.; Pinceaux, K.; Gacouin, A.; Maamar, A.; Painvin, B.; Camus, C.; Le Tulzo, Y.; Tattevin, P.; et al. SARS-CoV-2-Induced ARDS Associates with MDSC Expansion, Lymphocyte Dysfunction, and Arginine Shortage. J. Clin. Immunol. 2021, 41, 515–525. [Google Scholar] [CrossRef] [Scilit]
- Van Kempen, T.A.T.G.; Deixler, E. SARS-CoV-2: Influence of phosphate and magnesium, moderated by vitamin D, on energy (ATP) metabolism and on severity of COVID-19. Am. J. Physiol. Endocrinol. Metab. 2021, 320, E2–E6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaźmierczak-Siedlecka, K.; Ruszkowski, J.; Fic, M.; Folwarski, M.; Makarewicz, W. Saccharomyces boulardii CNCM I-745: A Non-bacterial Microorganism Used as Probiotic Agent in Supporting Treatment of Selected Diseases. Curr. Microbiol. 2020, 77, 1987–1996. [Google Scholar] [CrossRef] [Scilit]
- Salama, C.; Han, J.; Yau, L.; Reiss, W.G.; Kramer, B.; Neidhart, J.D.; Criner, G.J.; Kaplan-Lewis, E.; Baden, R.; Pandit, L.; et al. Tocilizumab in Patients Hospitalized with Covid-19 Pneumonia. N. Engl. J. Med. 2021, 384, 20–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beigel, J.H.; Tomashek, K.M.; Dodd, L.E.; Mehta, A.K.; Zingman, B.S.; Kalil, A.C.; Hohmann, E.; Chu, H.Y.; Luetkemeyer, A.; Kline, S.; et al. Remdesivir for the Treatment of COVID-19—preliminary report. N. Engl. J. Med. 2020, 383, 1813–1826. [Google Scholar] [CrossRef] [Scilit]
- Zhao, X.; Li, Y.; Ge, Y.; Shi, Y.; Lv, P.; Zhang, J.; Fu, G.; Zhou, Y.; Jiang, K.; Lin, N.; et al. Evaluation of Nutrition Risk and Its Association With Mortality Risk in Severely and Critically Ill COVID-19 Patients. JPEN J. Parenter. Enter. Nutr. 2021, 45, 32–42. [Google Scholar] [CrossRef] [Scilit]
- Adebayo, A.; Varzideh, F.; Wilson, S.; Gambardella, J.; Eacobacci, M.; Jankauskas, S.S.; Donkor, K.; Kansakar, U.; Trimarco, V.; Mone, P.; et al. l-Arginine y COVID-19: An Update. Nutrients 2021, 13, 3951. [Google Scholar] [CrossRef] [Scilit]
- Kory, P.; Meduri, G.U.; Iglesias, J.; Varon, J.; Marik, P.E. Clinical and Scientific Rationale for the “MATH+” Hospital Treatment Protocol for COVID-19. J. Intensiv. Care Med. 2021, 36, 135–156. [Google Scholar] [CrossRef] [Scilit]
- Anker, M.S.; Landmesser, U.; von Haehling, S.; Butler, J.; Coats, A.J.; Anker, S.D. Weight loss, malnutrition, and cachexia in COVID-19: Facts and numbers. J. Cachexia Sarcopenia Muscle 2021, 12, 9–13. [Google Scholar] [CrossRef] [Scilit]
- Djokic, G.; Vojvodic, P.; Korcok, D.; Agic, A.; Rankovic, A.; Djordjevic, V.; Vojvodic, A.; Vlaskovic-Jovicevic, T.; Peric-Hajzler, Z.; Vojvodic, J.; et al. The Effects of Magnesium—Melatonin—Vit B Complex Supplementation in Treatment of Insomnia. Open Access Maced. J. Med. Sci. 2019, 7, 3101–3105. [Google Scholar] [CrossRef] [Scilit]
- Sidawi, T.; Garau, J.; COVID-19 Mortality. Trends in the evolution of the pandemic. J. Health Sci. 2021, 36, 42–49, p-ISSN: 1579-5853; e-ISSN: 2255-0569. [Google Scholar] [CrossRef] [Scilit]
- Zhu, Z.; Cai, T.; Fan, L.; Lou, K.; Hua, X.; Huang, Z.; Gao, G. Clinical value of immune-inflammatory parameters to assess the severity of coronavirus disease 2019. Int. J. Infect. Dis. 2020, 95, 332–339. [Google Scholar] [CrossRef] [Scilit]
- Zuo, T.; Zhang, F.; Lui, G.C.Y.; Yeoh, Y.K.; Li, A.Y.L.; Zhan, H.; Wan, Y.; Chung, A.C.K.; Cheung, C.P.; Chen, N.; et al. Alterations in Gut Microbiota of Patients With COVID-19 During Time of Hospitalization. Gastroenterology 2020, 159, 944–955. [Google Scholar] [CrossRef] [Scilit]
- Hao, Q.; Dong, B.R.; Wu, T. Probiotics for preventing acute upper respiratory tract infections. Cochrane Database Syst. Rev. 2015, CD006895. [Google Scholar] [CrossRef] [PubMed]
- Infusino, F.; Marazzato, M.; Mancone, M.; Fedele, F.; Mastroianni, C.M.; Severino, P.; Ceccarelli, G.; Santinelli, L.; Cavarretta, E.; Marullo, A.G.M.; et al. Diet Supplementation, Probiotics, and Nutraceuticals in SARS-CoV-2 Infection: A Scoping Review. Nutrients 2020, 12, 1718. [Google Scholar] [CrossRef] [Scilit]
- Munshi, R.; Hussein, M.H.; Toraih, E.A.; Elshazli, R.M.; Jardak, C.; Sultana, N.; Youssef, M.R.; Omar, M.; Attia, A.S.; Fawzy, M.S.; et al. Vitamin D insufficiency as a potential culprit in critical COVID-19 patients. J. Med. Virol. 2021, 93, 733–740. [Google Scholar] [CrossRef] [Scilit]
- Zhang, D.; Guo, R.; Lei, L.; Liu, H.; Wang, Y.; Wang, Y.; Qian, H.; Dai, T.; Zhang, T.; Lai, Y.; et al. Frontline Science: COVID-19 infection induces readily detectable morphologic and inflammation-related phenotypic changes in peripheral blood monocytes. J. Leukoc. Biol. 2021, 109, 13–22. [Google Scholar] [CrossRef] [Scilit]
- Rogero, M.M.; Leão, M.D.C.; Santana, T.M.; Pimentel, M.V.D.M.; Carlini, G.C.; da Silveira, T.F.; Gonçalves, R.C.; Castro, I.A. Potential benefits and risks of omega-3 fatty acids supplementation to patients with COVID-19. Free Radic. Biol. Med. 2020, 156, 190–199. [Google Scholar] [CrossRef] [Scilit]
- Van der Beek, C.M.; Canfora, E.E.; Kip, A.M.; Gorissen, S.H.M.; Olde Damink, S.W.M.; van Eijk, H.M.; Holst, J.J.; Blaak, E.E.; Dejong, C.H.C.; Lenaerts, K. The prebiotic inulin improves substrate metabolism and promotes short-chain fatty acid production in overweight to obese men. Metabolism 2018, 87, 25–35. [Google Scholar] [CrossRef] [Scilit]
- Birkeland, E.; Gharagozlian, S.; Birkeland, K.I.; Valeur, J.; Måge, I.; Rud, I.; Aas, A.M. Prebiotic effect of inulin-type fructans on faecal microbiota and short-chain fatty acids in type 2 diabetes: A randomized controlled trial. Eur. J. Nutr. 2020, 59, 3325–3338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Narayanan, N.; Nair, D.T. Vitamin B12 may inhibit RNA-dependent-RNA polymerase activity of nsp12 from the SARS-CoV-2 virus. IUBMB Life 2020, 72, 2112–2120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Virgens, I.P.A.; Santana, N.M.; Lima, S.C.V.C.; Fayh, A.P.T. Can COVID-19 be a risk for cachexia for patients during intensive care? Narrative review and nutritional recommendations. Br. J. Nutr. 2020, 126, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cardinali, D.P.; Brown, G.M.; Pandi-Perumal, S.R. Can Melatonin Be a Potential “Silver Bullet” in Treating COVID-19 Patients? Diseases 2020, 8, 44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gheorghe, C.E.; Martin, J.A.; Manriquez, F.V.; Dinan, T.G.; Cryan, J.F.; Clarke, G. Focus on the essentials: Tryptophan metabolism and the microbiome-gut-brain axis. Curr. Opin. Pharmacol. 2019, 48, 137–145. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).