


Abstract
Emergency peripartum hysterectomy (EPH) is performed for massive postpartum hemorrhage following a cesarean delivery or vaginal delivery, in order to save the patient’s life. The current study was performed on a sample of 13.162 patients, which underwent cesarean or vaginal delivery during a period of 6 years, from 2010 to 2015, in Bucur Maternity Hospital. There were two subsequential groups consisting in: 6593 patients with cesarean operations and 6569 patients with vaginal delivery. In 12 cases occurred one or more of the risk factors that lead to EPH, divided equally across the two groups above. The main two types of surgery are a more frequent subtotal hysterectomy, which is the preferred type of EPH as it takes less time and is associated with fewer complications, and a total hysterectomy. The majority of procedures were performed at patients over 35 years old (9 of 12), with a median age of 31,16 (ranging from 21 to 44 years old). The most important risk factor present across the lot was multiparity (11 from 12), with cicatricial uterus being the second one (4 of 12). ICU median time was 4,5 days (ranging from 3 to 15 days), with a median blood transfusion necessity of around 2,4 I.U per patient. There were no mother or newborn reported deaths, neither PTSD following EPH.EPH is a procedure performed as last-resort, life-saving surgery, leaving no time for mental preparation. This may predispose to negative psychological outcomes, especially because they are not part of decision-making process due to the emergency character of hysterectomy.
Introduction
Emergency peripartum hysterectomy (EPH) is performed for massive postpartum hemorrhage following a cesarean delivery or vaginal delivery, in order to save the patient’s life. Some studies show that the incidence of peripartum hysterectomy ranges from 13.1 cases per 10,000 births to 4.1 cases per 10,000 births [1,2,3].
The most important risk factors that lead to EPH are: uterine atony, abnormal placental implantation (accreta, previa, etc.), uteroplacental apoplexy, uterine rupture due to cicatricial uterus, advanced maternal age, increased parity, birth weight ≥ 4,000 gr and previous uterine surgery [2,3,4]. Interesting studies related to the northern countries found Finland with the highest (5.1) and Norway with the lowest (2.9) prevalence, the delivery mode being cesarean section in nearly 80% of cases [3].
A special category is represented by patients whose current delivery was vaginal, and had a cesarean section (CS) in their history: they can have a six-fold risk for EPH [5]. The median maternal age is reported to be from 31 years to 35.5 years [2,6].The average blood transfusion can be as high as 4.79 (1–14) units [6]. Maternal mortality can be as much as 4.5 %in some studies [7,8]. The main complications of EPH are often described as febrile morbidity: 12 (21%), wound infection: 8 (14%) and bladder or ureteric injury: 8 (14%). A difference in the incidence of EPH is noted following vaginal delivery and cesarean section, sometimes up to ten fold more for the latter. The incidence by parity increased from 1/143 deliveries in nulliparous women with placenta previa to 1/4 deliveries in multiparous women with placenta previa [9,10].
Table 1.
Estimated Risk of Needing a Peripartum Hysterectomy in Different Categories of Women [1].

Nowadays, protocols can provide a standardized approach to evaluating and monitoring the patient, how to notify a multidisciplinary team, and adequate treatment [9,11].
Materials and methods
This study aims to estimate the occurrence of emergency peripartum hysterectomy (EPH) and to quantify its risk factors in connection with the mode of delivery as well as psychological impact over patients at the Bucur Maternity Hospital, Bucharest, Romania.
The study was made on a sample of 13162 patients, which underwent cesarean or vaginal delivery during a period of 6 years, from 2010 to 2015, in Bucur Maternity Hospital. There were two subsequential groups consisting in: 6593 patients with cesarean operations and 6569 patients with assisted vaginal delivery. In 12 cases occurred one or more of the risk factors that lead to EPH, divided equally across the two groups above.
The EPH was performed from 2 to 6 hours after vaginal delivery and at the same time in for cesarean ones. The main two types of surgery are a more frequent subtotal hysterectomy, which is the preferred type of EPH as it takes less time and is associated with fewer complications, and a less used total hysterectomy. Either type performed may or may not involve bilateral adnexectomy. For each patient was necessary some degree of blood transfusion, and also a variable number of days of ICU admission. Each patient underwent a repetitive psychological evaluation during the whole period of admission.
Results
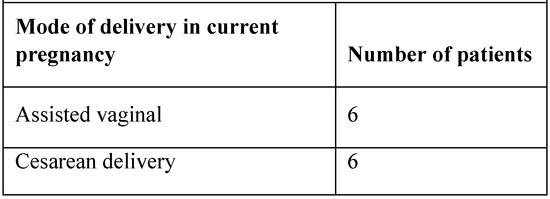
The majority procedures were performed at patients over 35 years old (9 of 12), with a median age of 31,16 (ranging from 21 to 44 years old). These data are consistent with data from literature [2,6]. The most important risk factor present across the lot was multiparity (11/12), with cicatricial uterus being the second one (4 of 12). There was a balance between the two ways of delivery, as shown in Table 2 below.
Table 2.
Mode of delivery in current pregnancy.
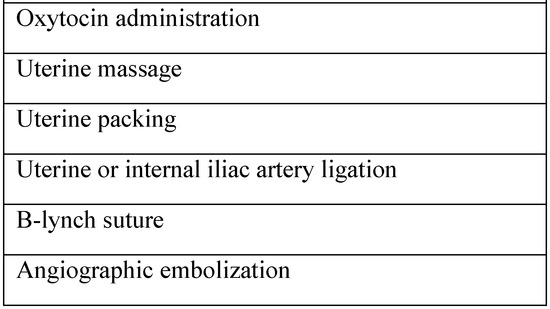
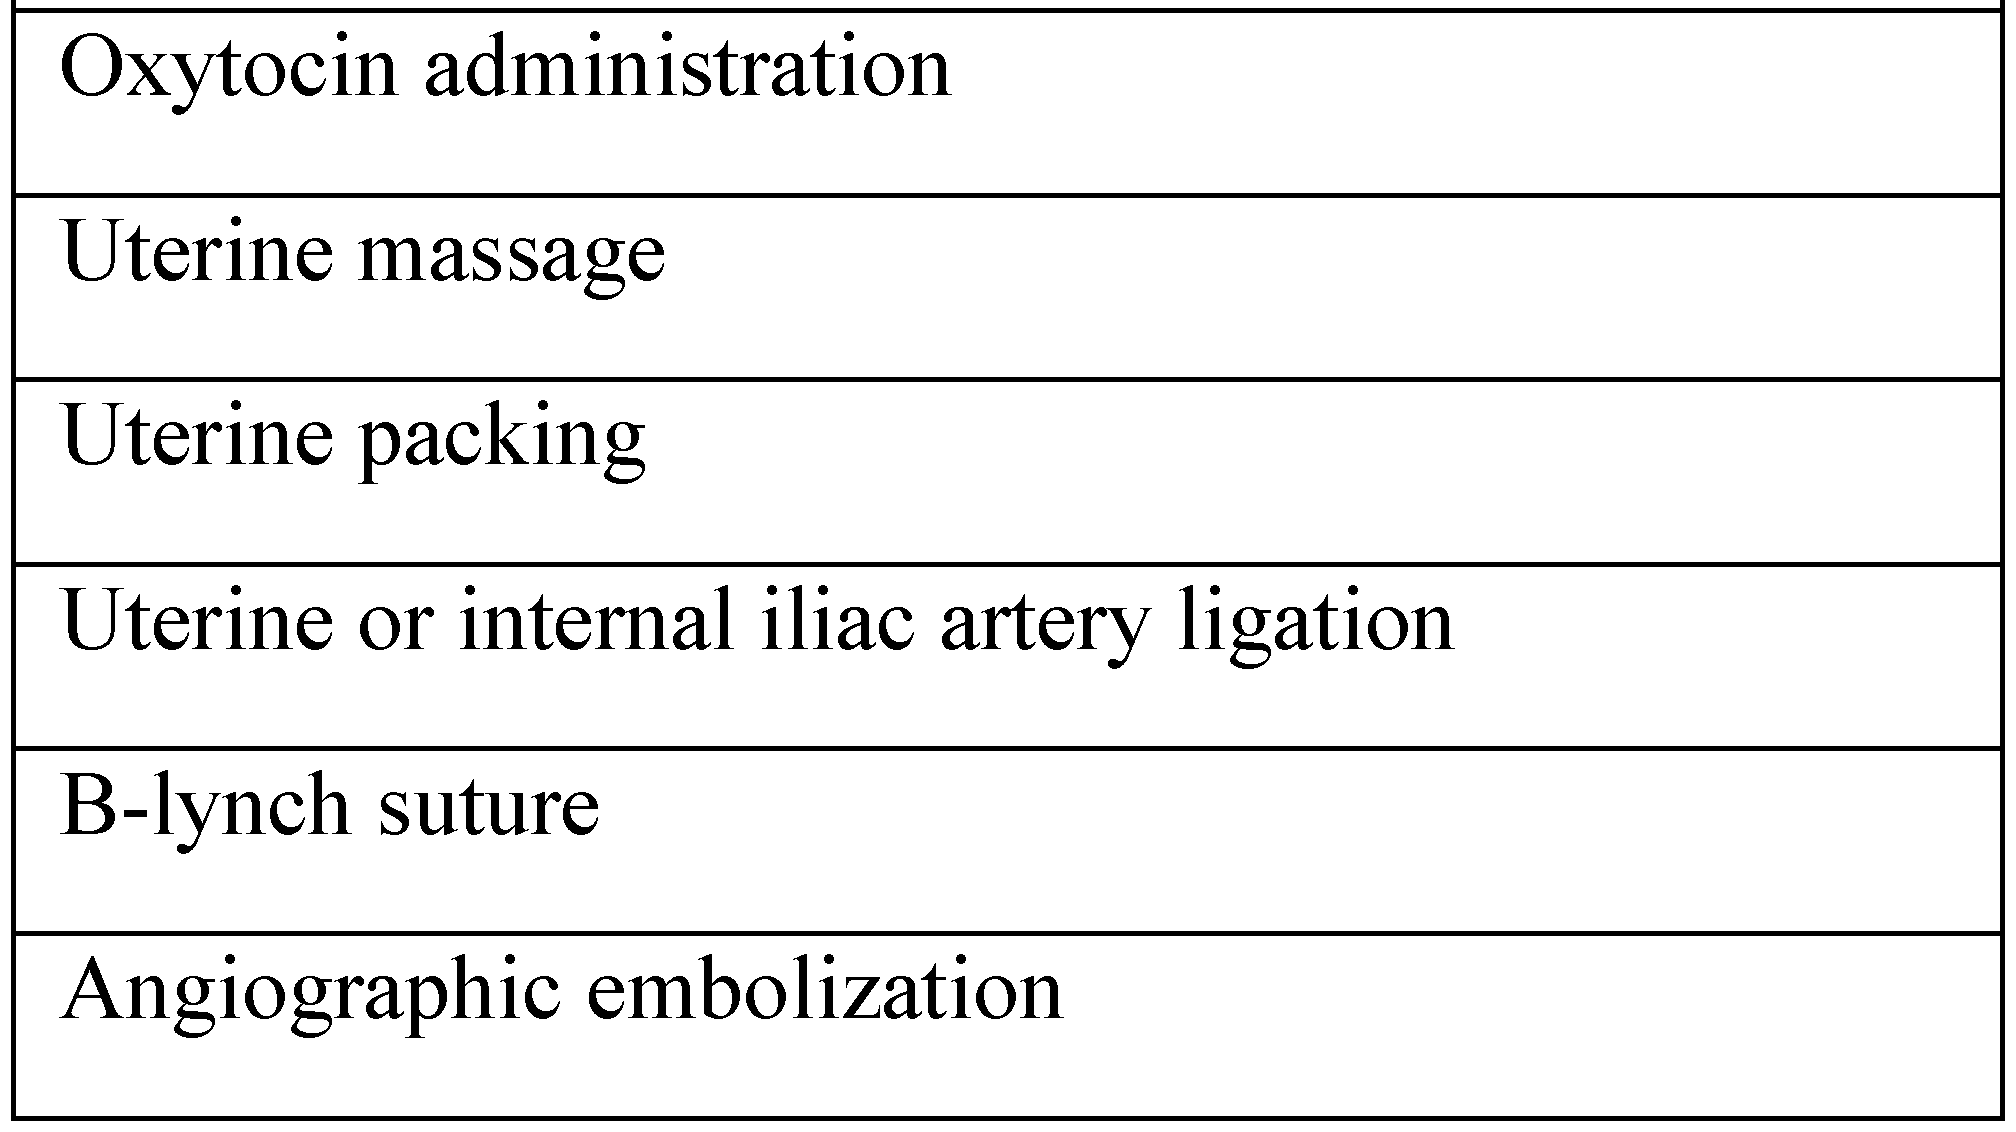
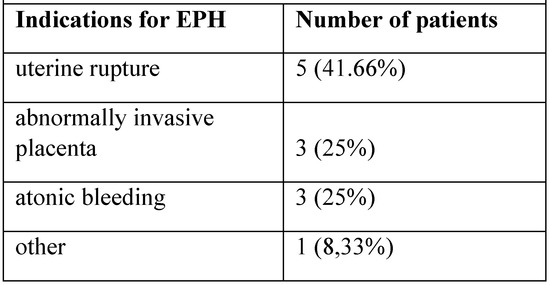
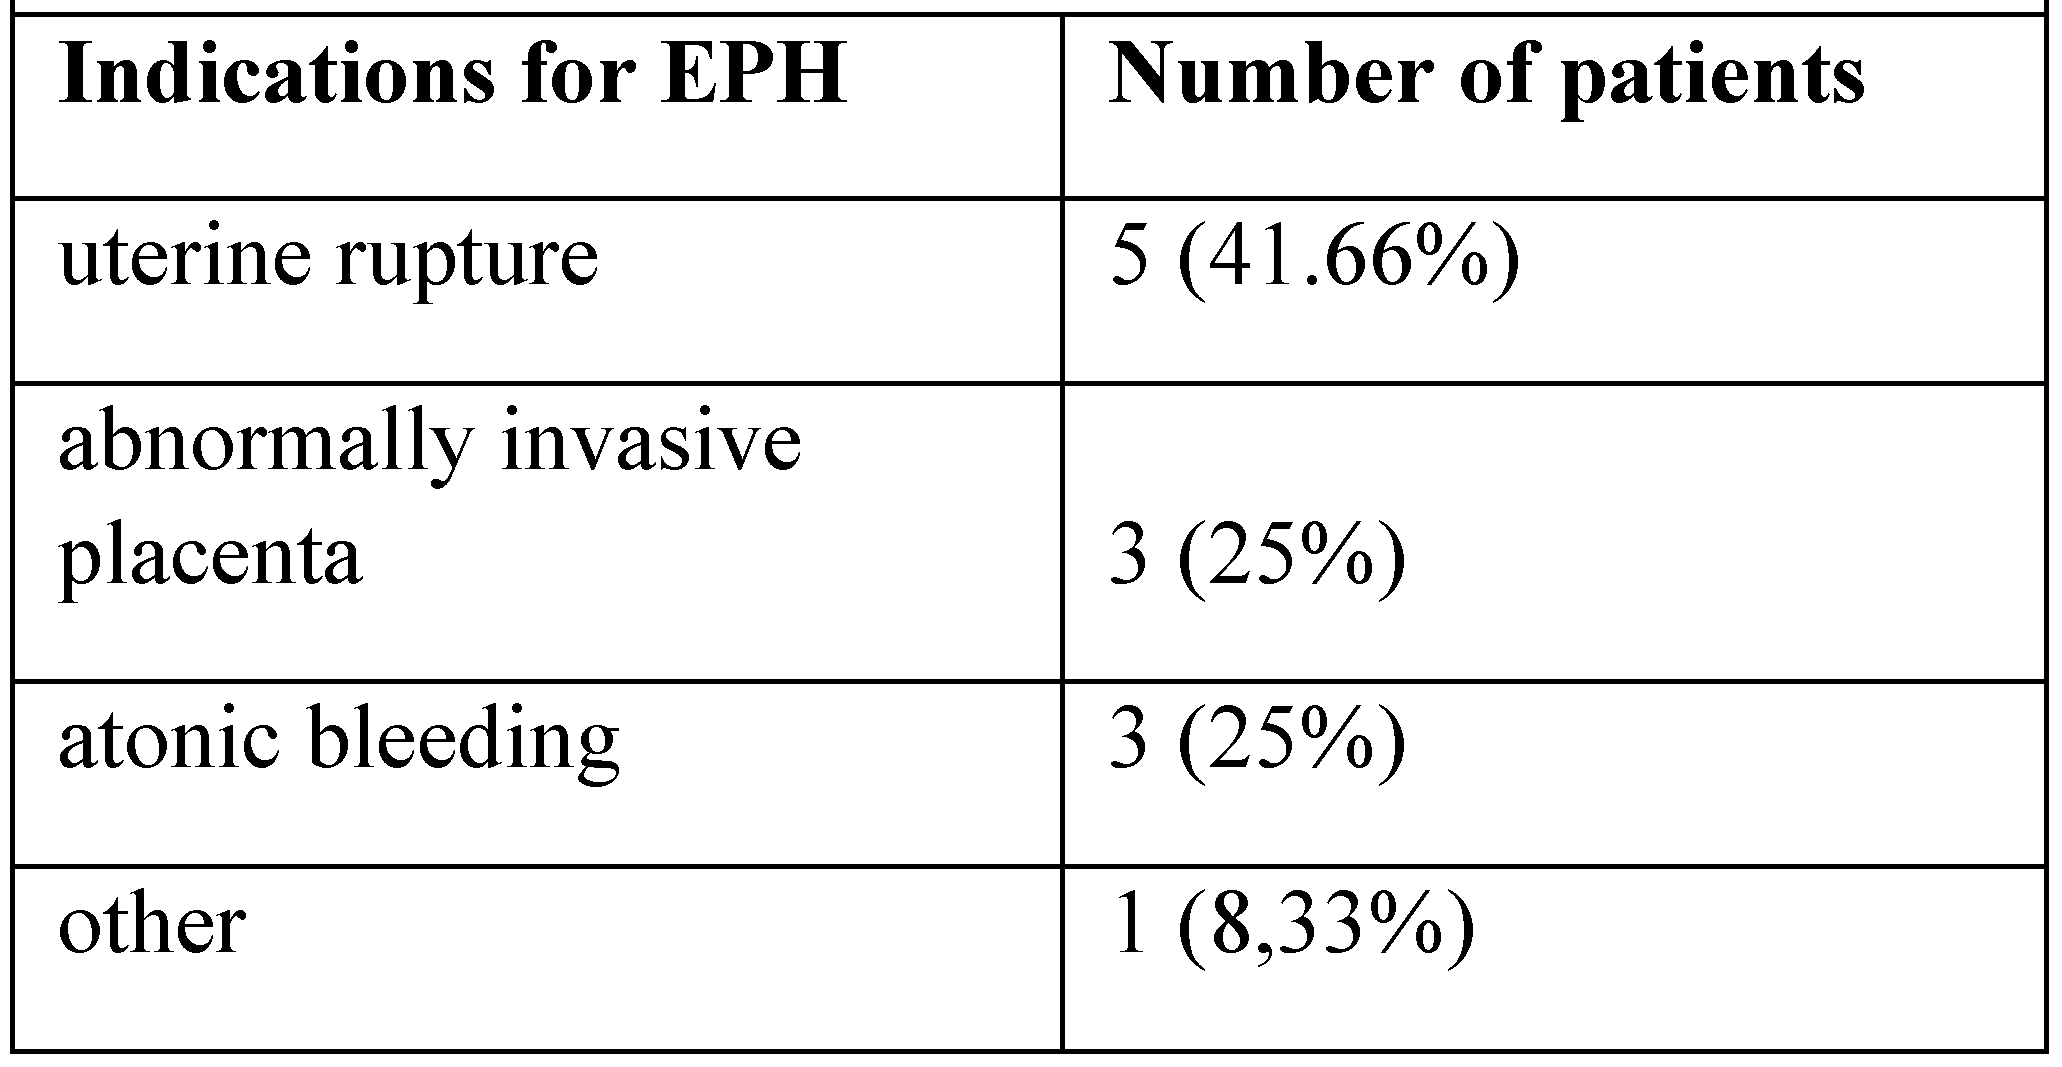
Primary indications included uterine rupture (n = 5, 41.66%), an abnormally invasive placenta (n = 3, 25%), atonic bleeding (n = 3, 25%), and others (n = 1, 8,33%). The delivery mode was cesarean section in nearly 50% of cases. In Table 3 are presented the principal techniques used to control bleeding prior to perform EPH, as the last resort (Table 4). The parity between assisted vaginal delivery and cesarean delivery has been translated to the group that underwent EPH.
Table 3.
Techniques used to control bleeding postpartum.
Table 4.
Indications for EPH.
ICU median time was 4,5 days (ranging from 3 to 15 days), with a great variability from case to case because of subsequent complication. The median blood transfusion necessity was around 2,4 I.U per patient, significant lower than in other studies [5]. There were no mother or newborn reported deaths, neither PTSD following EPH, although literature data reveal a maternal mortality ranging from 0,16 to 4%. There were no postoperative complications, too.
Discussions
EPH is a procedure performed as last-resort, life-saving surgery, leaving no time for mental preparation of the patients. This may predispose them to negative psychological outcomes, especially because they are not part of decision- making process due to the emergency character of hysterectomy.
The current study suggests that the most common indications for EPH are uterine atony, uterine rupture and abnormal placentation. This is probably due to previous scars on the uterus (cesarean delivery, myomectomy), advanced age of the mother and multiparity (large placenta).
In order to reduce the prevalence of EPH some measure should be taken prior to delivery. First of all, risk factors associated with emergency peripartum hysterectomy should be identified. Women included in this high risk group of should be delivered only by trained and experience team and following all the standard protocols that should be established in any delivery department. These measures, along with skilled ICU care can contribute to reduce the maternal morbidity and mortality associated to EPH. Although no research studies look at PTSD following EPH, the events during and after traumatic birth are similar to those of EPH. In the end, it all resumes to the perception of the mother on how traumatic was the procedure and the understanding of the long-term consequences. Nevertheless, psychological modifications in pregnancy coupled with longer surgical recovery (and possible complication after surgery) can put mother to a risk, if her psychological defence mechanism are overcome, and could result in PTSD.
Conclusions
EPH is a procedure performed as last-resort, life-saving surgery, leaving no time for mental preparation of the patients. This may predispose them to negative psychological outcomes, especially because they are not part of decision- making process due to the emergency character of hysterectomy. There are not enough studies to make a clear statement concerning the link between PTSD and EPH.
Obstetric emergency training and guidelines for massive hemorrhage should be established in any delivery department. Besides that, anticipation of such complication by classifying those patients in the risk group, along with protocols that can provide a standardized approach to evaluating and monitoring the patient, notifying a multidisciplinary team, and treatment, will greatly improve the final outcome. The last but not the least, each patient should undergo a repetitive psychological evaluation during the whole period of admission.
References
- Knight, M.; Kurinczuk, J.J.; Spark, P.; Brocklehurst, P. Cesarean Delivery and Peripartum Hysterectomy. Obstet Gynecol. 2008, 111, 97–105. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chanterm, T.; Chittacharoen, A.; Ayudhya, N.I.N. Risk factors of emergency peripartum hysterectomy. Thai Journal of Obstetrics and Gynaecology 2015, 23, 96–103. [Google Scholar]
- Jakobsson, M.; Tapper, A.M.; Colmorn, A.M.; Lindqvist, P.G.; Klungsøyr, K.; Krebs, L.; Børdahl, P.E.; Gottvall, K.E.; Källén, K.; Bjarnadóttir, R.I.; Langhoff-Roos, J.; Gissle, M. Emergency peripartum hysterectomy: results from the prospective nordic obstetric surveillance study (noss). Acta Obstet Gynecol Scand 2015, 94, 745–54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Macharey, G.; Ulander, V.M.; Kostev, K.; Väisänen- Tommiska, M.; Ziller, V. Emergency peripartum hysterectomy and risk factors by mode of delivery and obstetric history: a 10-year review from Helsinki University Central Hospital. Journal of Perinatal Medicine 2015, 43, 721–8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yalinkaya, A.Q.; Güzel, A.I.; Kangal, K. Emergency Peripartum Hysterectomy: 16-year Experience of a Medical Hospital. J Chin Med Assoc 2010, 73, 360–3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, T.Y. Emergency Peripartum Hysterectomy, a 10-year review in a tertiary obstetric hospital. The New Zeeland Medical Journal 2011, 124, 34–9. [Google Scholar]
- Sahin, S.; Guzin, K.; Eroğlu, M.; Kayabasoglu, F.; Yaşartekin, M.S. Emergency peripartum hysterectomy: our 12-year experience. Archives of Gynecology and Obstetrics 2014, 289, 953–958. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chibber, R.; Al-Hijji Fouda, M.; Al-Saleh, E.; Al- Adwani, A.R.; Mohammed, A.T. A 26-Year Review of Emergency Peripartum Hysterectomy in a Tertiary Teaching Hospital in Kuwait – Years 1983–2011. Med Princ Pract 2012, 21, 217–222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fawad, A.; Islam, A.; Naz, H.; Nelofar, T.; Abbasi, U.N. Emergency peripartum hysterectomy- a life saving procedure. J Ayub Med Coll Abbottabad. 2015, 27, 143–5. [Google Scholar] [PubMed]
- Zelop, C.M.; Harlow, B.L.; Frigoletto Jr, F.D.; Safon, L.E.; Saltzman, D.H. Emergency peripartum hysterectomy. American journal of Ostetrics and Gynecology 1993, 168, 1443–1448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balalau, C.; Popa, F.; Negrei, C.; Andreianu, P. Therapeutic attitude in perforated stress ulcer. Rev Med Chir Soc Med Nat Iasi. 2011, 115, 1119–23. [Google Scholar] [PubMed]

© 2016 by the authors. 2016 Denisa-Oana Bălălău, Romina Marina Sima, Nicolae Bacalbașa, Liana Pleș, Anca Daniela Stănescu. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).