


Abstract
Background: Frailty is a syndrome characterised by increased vulnerability to negative outcomes. Interstitial lung disease (ILD), asthma, and pleural disease are leading causes of morbidity and mortality. We aimed to investigate the prevalence and impact of frailty in adult patients with these diseases. Methods: We conducted a systematic review and meta-analysis, searching PubMed, Web of Science, The Cochrane Library, and EMBASE for studies reporting on frailty in ILD, asthma, and pleural disease. MeSH terms including interstitial lung disease, Idiopathic Pulmonary Fibrosis, Non-specific Interstitial Pneumonia, Chronic Hypersensitivity Pneumonitis, systemic sclerosis-associated ILD, connective tissue disease-associated ILD, and frailty were used as key words. The primary outcome was prevalence of frailty. Where enough contextually homogeneous studies were included, a pooled random-effects meta-analysis was performed with mortality and hospitalisation as the outcomes. Results: The review found three studies relating to frailty in asthma. No studies relating to pleural disease and frailty were identified. The median prevalence in asthma was 9.5% (IQR, 7.8–11.3). Six relevant studies incorporating 1471 ILD patients (age 68.3 ± SD2.38; 50% male) were identified, which were either cohort or cross-sectional design rated either good or fair. The median prevalence of frailty was 48% (IQR, 25–50). There was a positive association between frail ILD patients and increased risk of long-term mortality (pooled OR, 2.33 95%CI 1.31–4.15, I2 9%). One study reported a hospitalization rate of HR = 1.97(1.32–3.06) within 6 months in frail ILD patients. Conclusions: Frailty is very common and associated with increased mortality in patients with ILD. There are still minimal data regarding the prevalence of frailty and its influence on the risk in this population.
1. Introduction
Frailty is a syndrome characterised by a decline in physiological reserves and functions resulting in a greater vulnerability to negative health outcomes following acute stressors [1,2]. Chronic diseases, including lung diseases, are known risk factors for the development of frailty [1,2,3].
The prevalence of frailty varies according to the criteria or model used to identify it and the setting in which a population is studied [4]. Its prevalence increases with age, although it is also seen in younger populations, especially those affected by chronic conditions [5,6,7]. Commonly, frailty is measured using a Phenotype model [2] or by an accumulation of deficits [8]. These models have been developed according to a different underlying concept of frailty. The frailty index is a quantification of the cumulative burden of health deficits and widely based on chronic diseases. Conversely, the Phenotype model is based on domains such as weakness, slowness, and low physical activity. This model includes an assessment of physical function that, when impaired, can cause disability independently of diseases. Some of the clinical manifestations of frailty are due to sarcopenia that is directly related to low physical performance [9].
Prevalence of frailty may vary according to the model used (deficit or phenotype) and prevalence rates vary according to the setting, for example in a younger community-based population, such as the UK Biobank, it was as low as 3% [10] but in a large hospital population with COVID-19, with an average age of 74 years, the prevalence was 49.4% [7]. Increased frailty has been shown to consistently correlate with worse outcomes across a wide range of medical specialities and populations [11]. If chronic diseases are considered the cause of frailty, it becomes extremely important to assess frailty in patients with long-term conditions. More personalised medicine should be beneficial following evaluation of the role of frailty in disease course and intensive treatments [12].
The term interstitial lung disease (ILD) includes a heterogeneous group of diffuse parenchymal pulmonary disorders, with varying degrees of inflammation or fibrosis [13,14]. The literature on frailty in ILD has been evolving in recent years but there remains a paucity of knowledge in the area of frailty, despite frailty being a common risk factor for higher morbidity and early mortality in patients with ILD, independent of age [15].
Asthma is an important global health problem affecting millions of people and all age groups, with a rising burden on health care systems and on society through loss of productivity in the workplace [16,17]. The evidence for the effect of frailty in patients with asthma has not been explored to any significant extent.
Pleural disease remains common, affecting 360 per 100,000 people each year [18]. Pleural disease is the result of a range of different pathologies and includes malignancy, organ failure, infection, and pneumothorax. Collectively, it represents a significant burden in clinical practice [18].
The literature of frailty in Chronic Obstructive Pulmonary Disease (COPD) is evolving. This topic was the subject of another systematic review [Verduri A et al. Manuscript under review], therefore COPD has been excluded in the present review.
The aim of this study was to perform a systematic review and meta-analysis of observational studies to explore the role of frailty in adult patients with ILD, asthma, and pleural disease. The specific aims were (1) to identify the prevalence of frailty in people with ILD, asthma, or pleural disease; and (2) to assess the association between frailty and mortality, between frailty and morbidity such as exacerbation rates, and the number of hospitalisations.
2. Materials and Methods
The systematic review and meta-analysis were conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Metanalyses (PRISMA) recommendations. The protocol was registered through the PROSPERO database (registration number: CRD42022328511).
2.1. Search Strategy and Study Selection
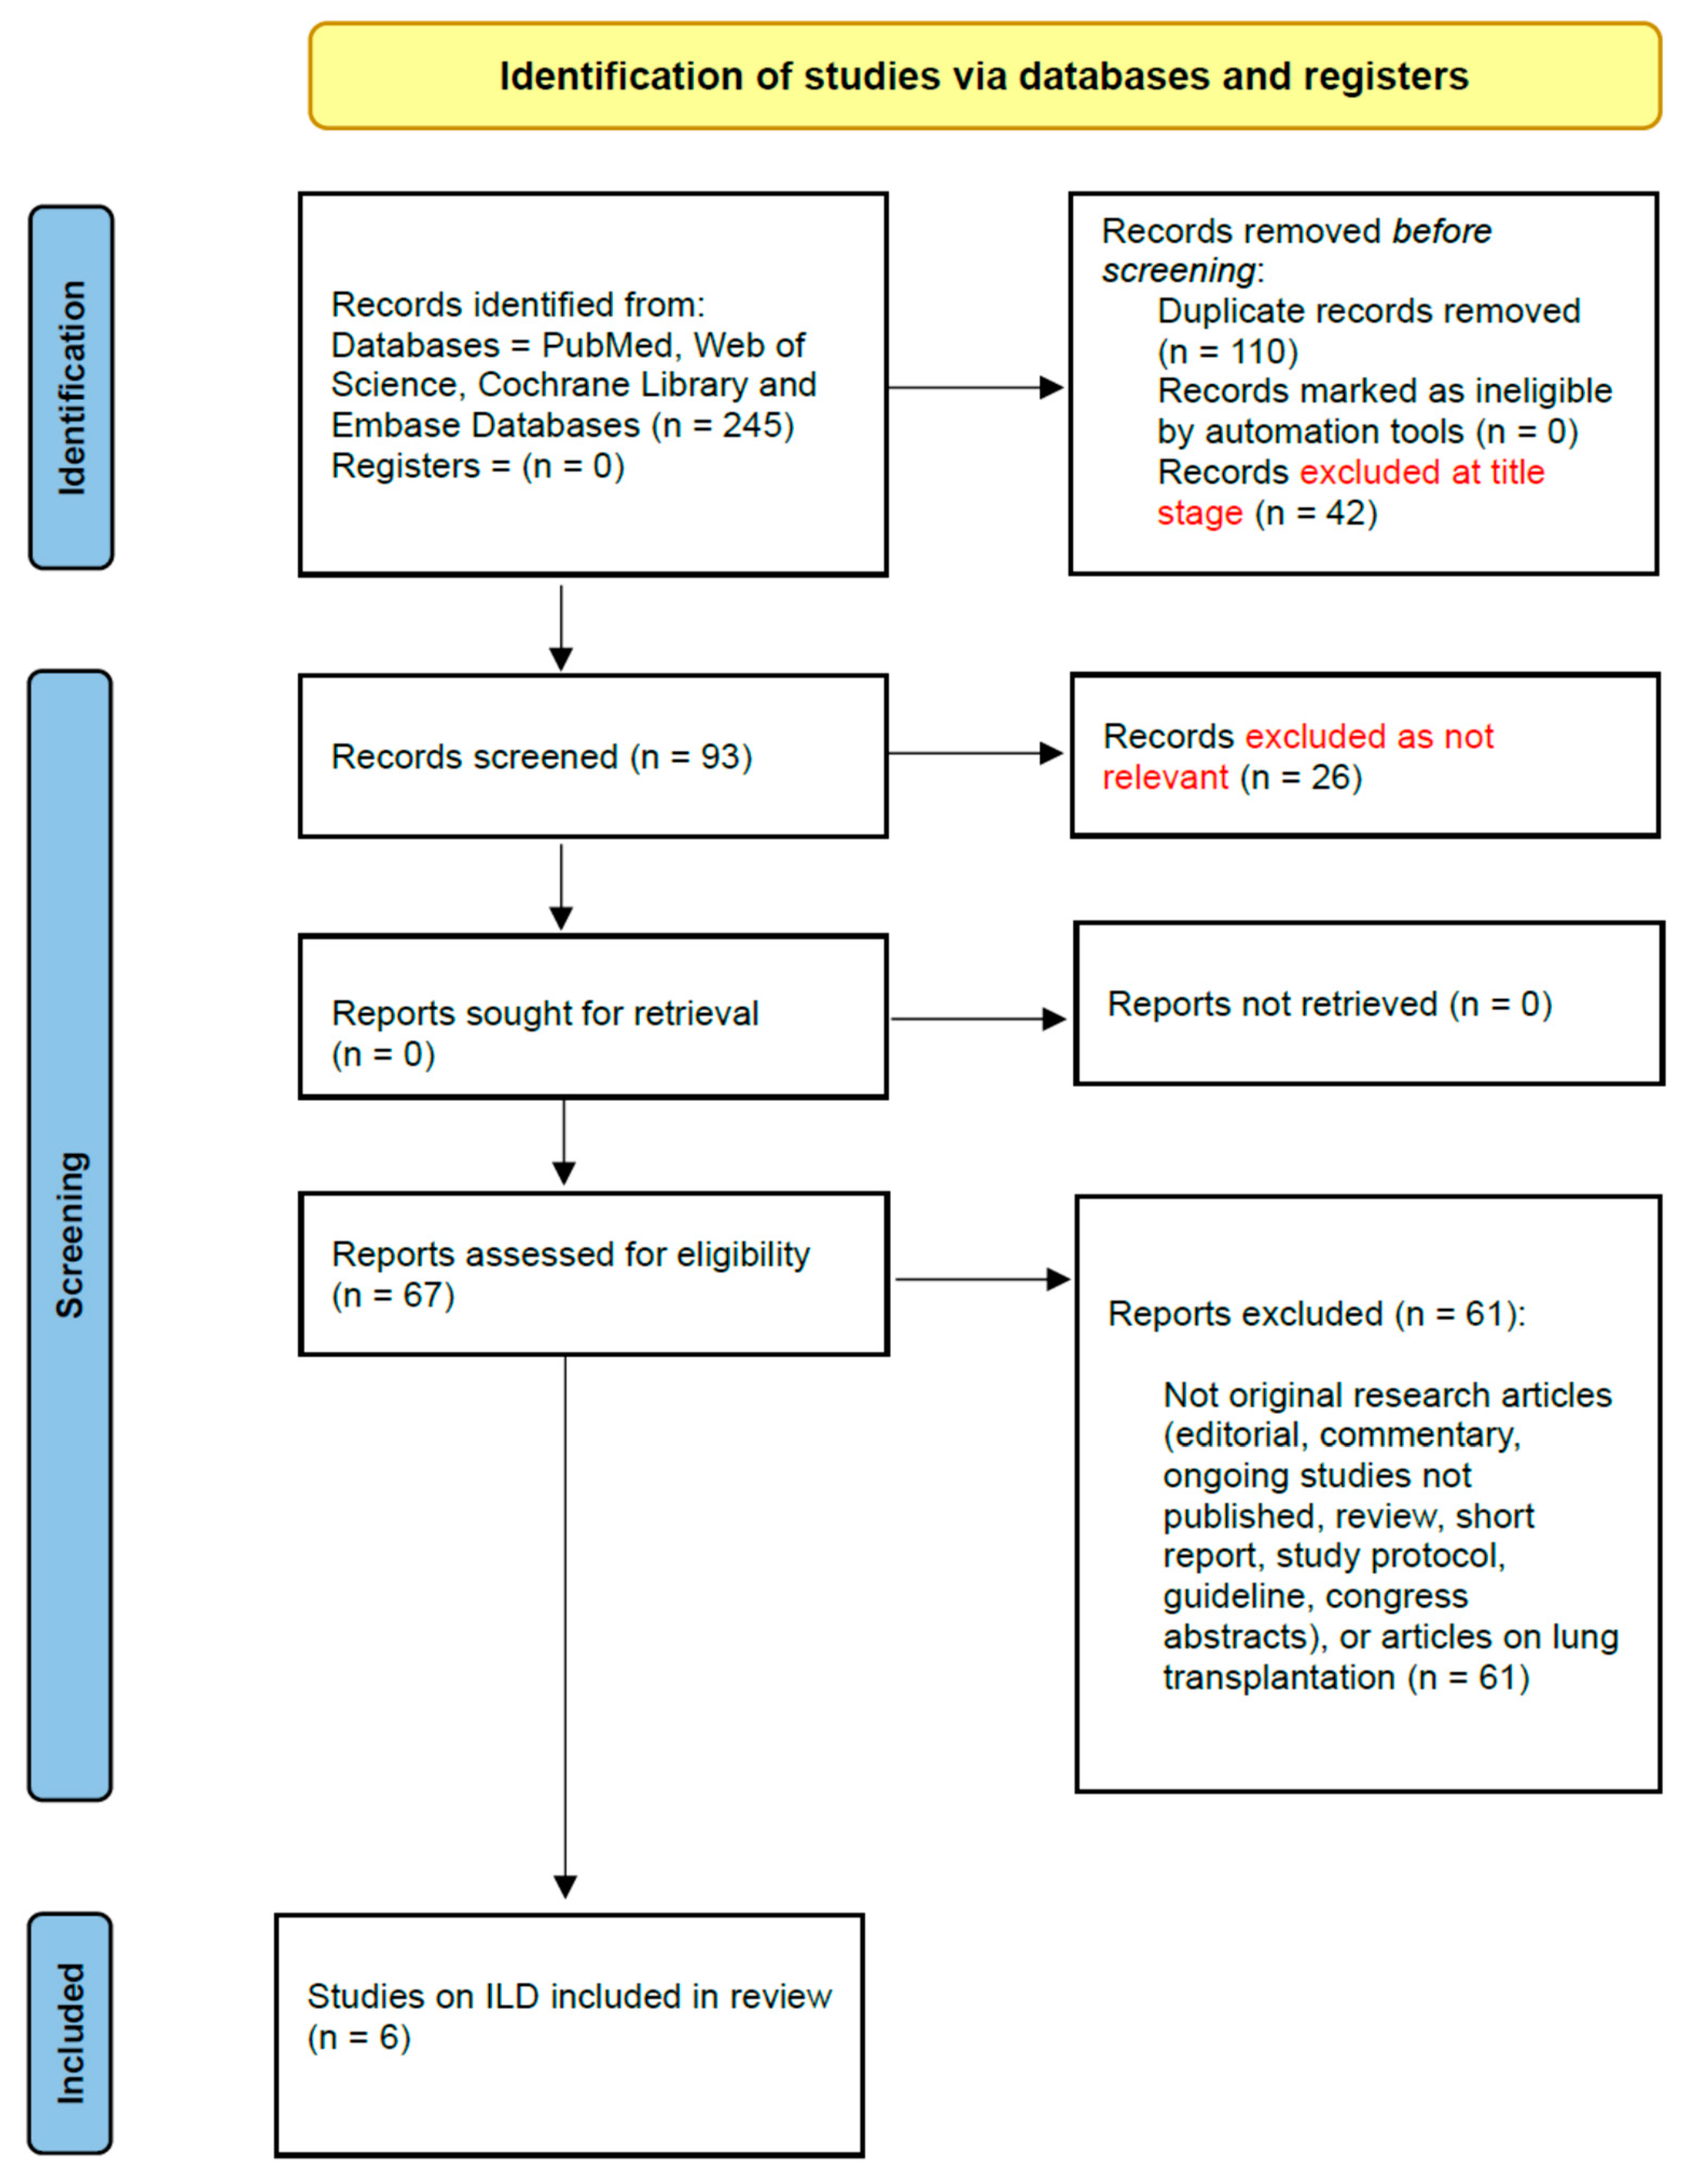
The search strategy was developed with a specialist librarian. Two researchers (AV, CR) independently searched four electronic databases (PubMed, Web of Science, The Cochrane Library, and EMBASE) for manuscripts published from inception to 25 October 2022. The search terms were based on Medical Subject Headings (MeSH). MeSH terms referring to frailty and Interstitial Lung Disease were used as key words, including the following: Idiopathic Pulmonary Fibrosis, Non-specific Interstitial Pneumonia, Chronic Hypersensitivity Pneumonitis, systemic sclerosis-associated ILD, connective tissue disease-associated ILD, and frailty. MeSH terms referring to frailty and asthma were used as key words. The review process for ILD is summarised in a PRISMA flow diagram (Figure 1). The search strategy is outlined in Supplementary Materials (File S1). The PRISMA flow diagrams for asthma and pleural disease are shown in File S1 (Figure S1A,B). Studies reporting information on frailty assessment and interstitial lung disease, asthma, and pleural disease in titles and abstracts were included. Any disagreement on study eligibility was resolved through discussion with a third reviewer (JH). A hand search of the reference list of all relevant articles was performed to identify any articles not captured by the electronic search. Only full-text reports in English and Italian were considered.
Figure 1.
PRISMA Flowchart of the included studies on ILD. From: Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ 2021;372:n71.
The Inclusion criteria were (1) study participants (≥18 years) who were diagnosed with ILD, asthma, or pleural disease who were assessed for frailty; (2) only studies using a validated method of frailty identification were included; (3) primary outcome measure was the prevalence of frailty in adults with ILD, asthma, or pleural disease; (4) cross-sectional, longitudinal, prospective or retrospective cohort, and case–control study designs.
Articles based solely on editorial, commentary, symposium, expert opinion, congress abstract, ongoing studies not published, short reports, and reviews were excluded.
Exclusion criteria were ILD patients listed for or referred for lung transplantation.
2.2. Data Extraction and Quality Assessment
Study characteristics, demographic information, frailty tool, frailty prevalence, and outcomes data were independently extracted from the included studies. Study authors were contacted to clarify or provide additional data where it was missing or unclear.
For included studies, the quality assessment was conducted by the two reviewers independently (AV, CR) and arbitrated by a third (JH) using the Newcastle–Ottawa Scale (NOS), [19] which assesses the risk of bias of observational studies. Each domain examined was classified as good, fair, or poor corresponding to low, moderate, and high risk of bias, respectively. Studies were considered to be of good quality where they scored good for all domains, fair if they scored fair in one or more domain, and poor if they scored poorly in any domain.
2.3. Outcomes
The primary outcome was prevalence of frailty in ILD, asthma, and pleural disease. Secondary outcomes were mortality; exacerbation rate; or number of hospitalizations in patients with ILD, asthma, or pleural disease. A priori, long-term mortality was defined as ≥1-year mortality.
2.4. Key Exposure of Frailty
Studies were included if they measured frailty using any validated instrument [20]. The following were examples of those included: Fried Frailty Phenotype [2], Frailty Index [8,21], and Kihon Checklist [22]. Frailty was measured as a binary variable as frail or not frail using the thresholds presented for the individual instruments. Where frailty measures included pre-frailty, this variable was also included. For example, in the Fried Frailty Phenotype, pre-frailty is defined as the presence of one or two of the following factors: unintentional weight loss, self-reported exhaustion, slowness, weakness, and low physical activity [2]. We summarized each frailty instrument in File S1.
2.5. Data Analysis
The primary outcome of the prevalence of frailty was estimated as the median study level prevalence, presented alongside the range.
Secondary outcomes were narratively described, and where study characteristics were deemed as contextually homogeneous, they were associated with frailty as a binary variable. Data were analysed in a pooled random-effects meta-analysis using the Mantel-Haenszel method. Pooled estimates were presented as OR with the associated 95% CIs, p values, and I2 summary data. RevMan V5.4. was used as statistical software.
2.6. Assessment of Subgroups and Statistical Heterogeneity
Statistical heterogeneity was measured using the I2 statistic. Heterogeneity exceeding 80% was explored using subgroup analyses. Pre-specified subgroups to explore heterogeneity included quality assessment.
3. Results
3.1. Interstitial Lung Disease
3.1.1. Search Results and Quality Assessment on ILD Studies
After removal of duplicates, 135 records were identified. Sixty-seven (67) full texts were reviewed, and 61 of these were excluded with reasons. The six studies included in the analysis are shown in the PRISMA flowchart (Figure 1). Three studies were determined as good quality [23,24,25] and three were categorized as fair quality [26,27,28]. The qualitative synthesis is summarised in File S1 (Table S1A,B).
3.1.2. Characteristics of Studies on ILD Included
A summary of the characteristics of included studies is presented in Table 1. The included studies were published between 2017 and 2022. Included studies were conducted in Canada (n = 5) [23,24,25,27,28] and the USA (n = 1) [26]. From the six studies, 1471 patients were included, 50% of which were male (735/1471). There was a range of frailty assessment tools used in the included studies, of which all were deemed suitable for inclusion in the frailty prevalence estimation. The mean age was 68.3 (±SD 2.38) and the age ranged between 48 and 79 years (Table 1).
Table 1.
Included studies on interstitial lung disease.
3.1.3. Frailty Prevalence in ILD
Prevalence was assessed using two different frailty scales: the Fried Frailty Phenotype [2] and the Frailty Index (File S1, Table S1C) [8,21]. Of the six included studies, the median prevalence of frailty in ILD patients was 48% (25–50 IQR), ranging from 25% [25] to 52.5% [27]. The presence of pre-frailty ranged between 20% [27] and 56%, [23] with a median of 40% (IQR, 23–55). The included studies on ILD and the prevalence estimate are shown in Table 1.
3.1.4. Frailty Score as a Predictor of Morbidity and Mortality in Patients with ILD
Long-Term Mortality
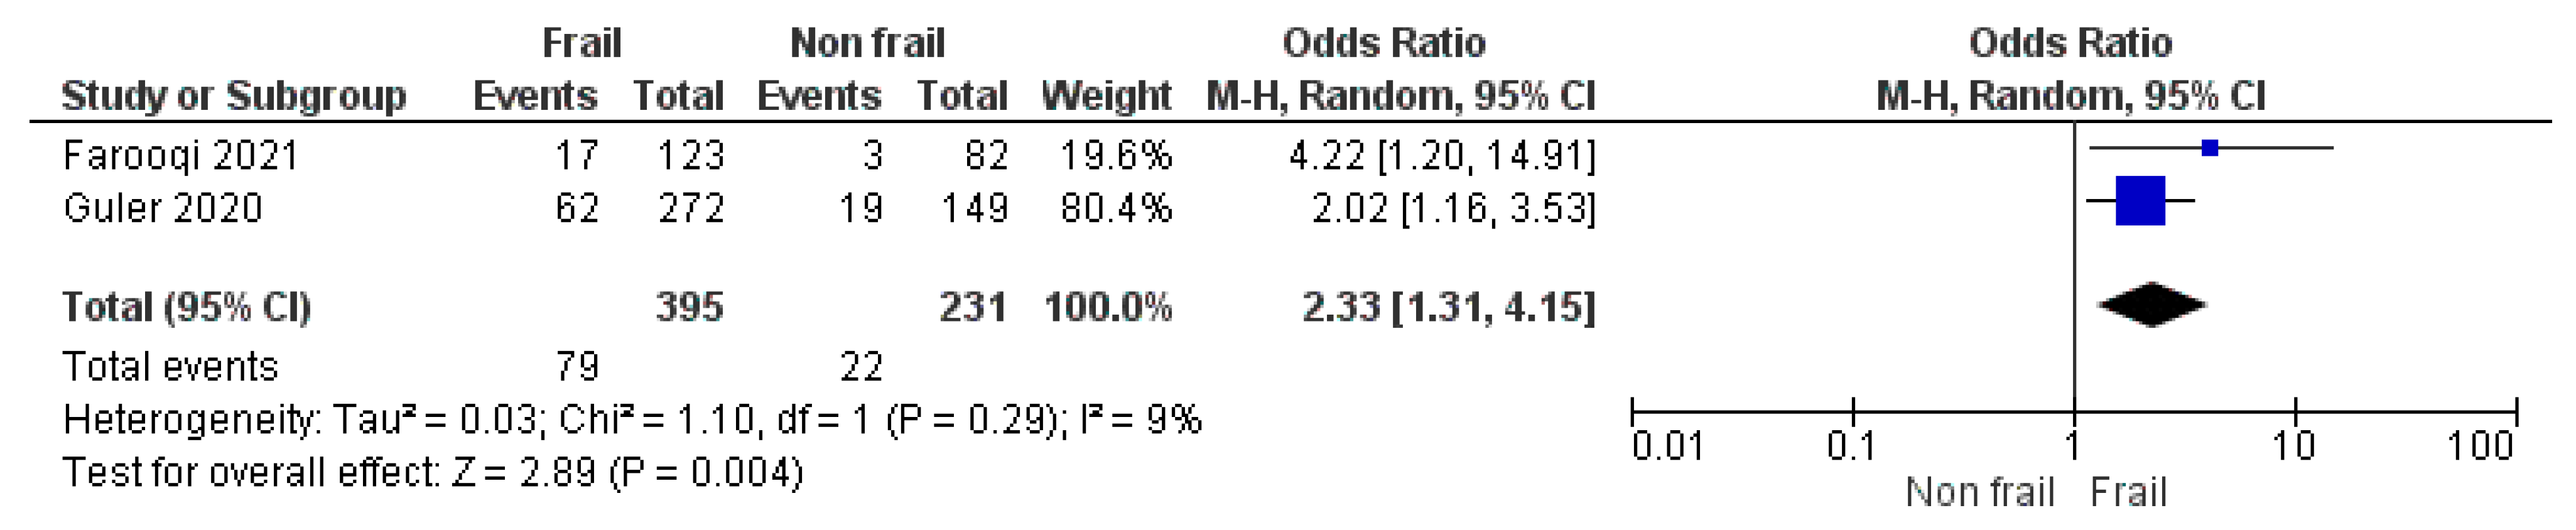
Two studies [23,24] explored frailty, pre-frailty, and mortality in the long term, including 1003 patients. Both studies found a positive association over a median time ranging between 17 months and 3 years. The pooled analysis showed a positive association between ILD patients living with frailty and increased risk of long-term mortality compared to non-frail ILD patients (pooled OR, 2.33 95% CI 1.31–4.15, I2 9%) (Figure 2). When frailty and pre-frailty were compared against non-frailty and frailty was compared against pre- and non-frailty, the results showed a trend towards worsening mortality for the frailer people (File S1, Figure S3).
Figure 2.
A meta-analysis of frailty and mortality in ILD. Forest plot describing effect of frailty on all-cause mortality. The mortality of ILD patients living with or without frailty were compared across two studies. Frailty vs. non-frailty and long-term mortality in ILD patients [23,24].
Due to the low number of included studies on ILDs, no sensitivity analyses were carried out.
Number of Hospitalizations
One study [24] reported a nearly double rate of all-cause hospitalisations (HR = 1.97, 1.32–3.06, p = 0.002) within 6 months after frailty assessment in ILD patients living with frailty.
3.2. Asthma
3.2.1. Search Results and Quality Assessment on Asthma Studies
We identified three studies regarding frailty in asthma (Table 2; File S1, Figure S1A) that were reviewed and quality assessed. Two studies were categorized as fair quality, [29,30] and one study as good quality (File S1, Tables S1B and S2A) [10]. Due to the low numbers of included studies, meta-analyses were not performed.
Table 2.
Included studies on asthma.
3.2.2. Characteristics of Included Studies on Asthma
A summary of the characteristics of included studies is presented in Table 2. The included studies were published between 2018 and 2021. Included studies were conducted in France, [29] Japan, [30] and the UK (Table 2) [10]. From the three studies, 57,610 participants with asthma were included. The mean age was 69.6 and the age ranged between 37 and 80 years. Data from the UK Biobank [10] did not describe prevalence of sex and age range in the group of participants with asthma. There were two frailty assessment tools (Fried Frailty Phenotype and Kihon Checklist) [2,22] used in the included studies (File S1, Table S1C), and all studies were deemed suitable for inclusion in the frailty prevalence estimation. The three studies identified did not examine the impact of frailty on clinical outcomes in asthma.
3.2.3. Frailty Prevalence in Asthma
Of the included studies, all [10,29,30] reported the prevalence of frailty in patients with asthma and the median prevalence was 9.5% (IQR, 7.8–11.3), ranging from 6% [10] to 14.5% [30]. The overall prevalence of pre-frailty ranged between 30.4% [30] and 42.1% [10], with a median of 38% (IQR, 30.4–42.1). The included studies on asthma and the prevalence estimate are shown in Table 2.
3.3. Pleural Disease
Search Results on Pleural Disease Studies
We did not find any studies relating to frailty in pleural disease.
4. Discussion
4.1. ILD
This study is the first review that systematically characterises frailty in ILD. The results showed that the prevalence of frailty or pre-frailty was present in nearly 50% of the study participants and that there was an association between frailty and increased mortality.
The study identified six studies on ILD, which included 1471 patients [23,24,25,26,27,28]. Three studies were good quality [23,24,25], and three were fair quality [26,27,28]. The included studies covered a range of interstitial lung diseases, including Idiopathic Pulmonary Fibrosis (IPF), Chronic Hypersensitivity Pneumonitis, systemic sclerosis-associated ILD, Non-specific Interstitial Pneumonia, connective tissue disease-associated ILD (CTD-ILD), and other unclassifiable ILDs.
Frailty was found in 50% of patients with ILD aged 60 years and over, confirming that age alone represents a narrow field of view in patient management and showing a potential relationship between interstitial lung disease and ageing. The high proportion of ILD outpatients living with frailty and assessed in stable condition is likely related to a degree of physical inactivity that widely contributes to sarcopenia and progressively to more severe frailty [9]. ILD patients living with frailty can have higher vulnerability and dramatically be affected by even small acute stressors that shorten their survival [15].
Two prospective cohort studies [23,24] reported a positive association between frailty and long-term mortality in patients with ILD in stable conditions, with a more than double chance of dying in frail people. Similarly, other lung diseases such as Chronic Obstructive Pulmonary Disease (COPD) showed an increased risk of mortality in patients with COPD living with frailty [Verduri A et al. Manuscript under review]. The type of ILD patients varied between the studies. Guler et al., [24] included 18.5% patients with IPF and 42% patients with SSc-ILD and other connective-tissue disease ILD, and the study of Farooqi et al. [23] involved 39.5% patients with IPF and 17% patients with CTD-ILD. These different patient groups may have introduced some bias. However, it is well known that systemic sclerosis and IPF are associated with other age-related comorbidities that can facilitate the development of frailty. Both studies considered the comorbidities associated with ILD. Farooqi et al. [23] did not find any difference in the number of comorbidities between frail and non-frail patients, while Guler et al. [24] suggested that the co-occurring diseases influence the frailty score in non-connective tissue disease-ILD. Further investigations on frailty measurement including comorbidities in ILD are required.
Only one study [24] reported all-cause hospitalisations, with a nearly double rate in ILD patients living with frailty within 6 months.
While these findings confirm the role of frailty in worse clinical outcomes of patients with ILD, other studies on frailty and a broader range of relevant clinical outcomes are required.
A strength of this systematic review is that it included the Fried Frailty model [2] and the accumulation of deficits model (Frailty Index) [8,21] that are the two of the most commonly employed frailty instruments, both valid and frequently applied to research and used in clinical practice. The populations considered were North American, which may limit generalisation and the comparatively low numbers of studies did not allow meta-analyses across a wide range of outcomes and this must be noted as a limitation. Further, these data are observational and reverse causality is possible, if unlikely.
Increasing evidence has emerged on progressive fibrosis in patients with IPF and also with different underlying interstitial lung disease. The progressive-fibrosing phenotype can be characterised by worsening respiratory symptoms and early mortality [14]. Prevalence of frailty may vary in fibrotic ILD and non-fibrotic ILD. Whilst this can be a potential limitation of the study, it also suggests that future studies on frailty and clinical outcomes in ILD should take the phenotype into account.
Recently, Saketkoo et al. [31] focused on patients with ILD in advanced age and in people with late-in-life onset ILD, proposing prevention of frailty in ILD at any age for well-being of this group of patients.
4.2. Asthma
The review identified only three studies on asthma and frailty, which involved 57,610 individuals [10,29,30]. Whilst older age was prevalent in two studies [29,30], one study [10], that included 57,169 people with asthma, reported 81% of all the individuals recruited were aged <65 years. All studies were found to be of fair quality, [29,30] except one of good quality [10]. The studies included in this review showed a prevalence of frailty in asthma of 9.5% and pre-frailty of 38%.
Although all included studies were reliable and used validated frailty tools, one study [30] assessed outpatients with diagnosis of asthma according to the GINA guidelines [17] and the two other studies [10,29] through questionnaires, meaning that the majority of participants had a mostly self-reported asthma diagnosis. Further, there was little specific evidence regarding the severity of the asthma and the disease in older populations. Particularly, in older patients, the asthma prevalence does not decrease with ageing and the disease has specific clinical presentation in advanced age, such as asthma-COPD overlap syndrome as an example. The recognition of asthma in ageing is frequently delayed and the treatment postponed due to difficulties that clinicians have in the approach in older asthmatic patient. Recently, a study protocol on the role of frailty in older patients with diagnosis of moderate-to-severe asthma according to guidelines [17] has been published by a group of researchers from Brazil, which may help characterise this group of patients [32]. A greater number of future studies and a multidisciplinary management of asthma in older adults are still needed.
4.3. Pleural Disease
This study did not find any articles regarding pleural disease and frailty. The measurement of frailty in patients with pleural disease has not been considered until now, this is therefore a clear gap in clinical practice and research.
5. Conclusions
This work included a limited number of studies on ILD but those that are reported provided consistent and plausible findings. The study found that frailty is common in patients with ILD. Although frailty has been recently recognised as an important aspect for patients with ILD, there is still paucity of data regarding the prevalence of frailty and mainly its influence on clinical outcomes in this population. Despite only two studies included in the meta-analysis, this review showed that frailty was associated with increased long-term mortality in this population. However, additional studies are required to determine whether frailty can be used to predict disease progression and worse health outcomes. These studies will clarify how the frailty status can be reversed, and potentially identify therapeutic targets for improved outcomes. Dyspnea, cough, and fatigue are frequent in ILD before dying and contribute to physical inactivity, deconditioning, and further worsening of symptoms that can lead to high degree of frailty in these patients. This systematic review outlines the challenges facing ILD clinicians in making an early identification of frailty with resulting non-pharmacological approaches in the care of patients.
In conclusion, the study provided a scientific summary of the currently available literature regarding frailty and ILD, asthma, and pleural disease and identified gaps that can be used for future research. Frailty is evolving as an important measure in chronic lung disease such that may enhance the clinical management of respiratory patients at risk. Areas such as severe asthma, asthma in older populations, and pleural disease have not been well described or considered and require further investigation. These future directions of research and clinical practice on frailty could potentially improve patient outcomes.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/geriatrics8040082/s1, (File S1), Figure S1A: PRISMA flowchart of the included studies on asthma; Figure S1B: PRISMA flowchart of the included studies on Pleural Disease; Table S1A: Newcastle–Ottawa Score for the included studies on ILD; Table S1B: Newcastle–Ottawa Score (NOS) domain description; Table S1C: Frailty instruments used in the included studies on ILD and asthma; Table S2A: Newcastle–Ottawa Score for the included studies on asthma; Figure S3: Forest plot demonstrating effect of frailty, pre-frailty, and non-frailty on all-cause mortality in ILD; Table S3: Search strategy; Table S4: PRISMA 2020 Checklist.
Author Contributions
A.V. and J.H. conceived the study, searched the literature, extracted the data, and drafted the manuscript. A.V. and C.R. searched the literature, extracted the data, and reviewed the manuscript. B.C. and J.H. developed the methods, arbitrated differences in data extraction, carried out the analysis, interpreted the analysis, and drafted the manuscript. N.A.M. advised on the methods for the study, and drafted and reviewed the manuscript. J.L., E.B. and E.C. reviewed the manuscript. J.H. is the guarantor of this review. All authors have read and agreed to the published version of the manuscript.
Funding
There was no direct funding was received for this study. This paper represents independent research part funded by the National Institute for Health Research (NIHR) Biomedical Research Centre at South London and Maudsley NHS Foundation Trust and King’s College London. The views expressed are those of the author(s) and not necessarily those of the NIHR or the Department of Health and Social Care (BC). A.V. was supported by a research fellowship at Cardiff University (UK) funded by CHIESI Italy. The sponsor had no role in study design, analysis, interpretation, or writing of the manuscript.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
All data sharing and collaboration requests should be directed to the corresponding author. The data underlying this article are available in the article and in its online Supplementary Materials (File S1).
Conflicts of Interest
The authors declare no conflict of interest.
References
- Clegg, A.; Young, J.; Iliffe, S.; Rikkert, M.O.; Rockwood, K. Frailty in elderly people. Lancet 2013, 381, 752–762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fried, L.P.; Tangen, C.M.; Walston, J.; Newman, A.B.; Hirsch, C.; Gottdiener, J.; Seeman, T.; Tracy, R.; Kop, W.J.; Burke, G.; et al. Frailty in older adults: Evidence for a phenotype. J. Gerontol. A Biol. Sci. Med. Sci. 2001, 56, M146–M156. [Google Scholar] [CrossRef] [Scilit]
- Morley, J.E.; Vellas, B.; van Kan, G.A.; Anker, S.D.; Bauer, J.M.; Bernabei, R.; Cesari, M.; Chumlea, W.; Doehner, W.; Evans, J.; et al. Frailty consensus: A call to action. J. Am. Med. Dir. Assoc. 2013, 14, 392–397. [Google Scholar] [CrossRef] [Scilit]
- Buta, B.J.; Walston, J.D.; Godino, J.G.; Park, M.; Kalyani, R.R.; Xue, Q.-L.; Bandeen-Roche, K.; Varadhan, R. Frailty assessment instruments: Systematic characterization of the uses and contexts of highly-cited instruments. Ageing Res. Rev. 2016, 26, 53–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rockwood, K.; Song, X.; Mitnitski, A. Changes in relative fitness and frailty across the adult lifespan: Evidence from the Canadian National Population Health Survey. CMAJ 2011, 183, E487–E494. [Google Scholar] [CrossRef] [Scilit]
- Smart, R.; Carter, B.; McGovern, J.; Luckman, S.; Connelly, A.; Hewitt, J.; Quasim, T.; Moug, S. Frailty exists in younger adults admitted as surgical emergency leading to adverse outcomes. J. Frailty Aging 2017, 6, 219–223. [Google Scholar] [CrossRef] [Scilit]
- Hewitt, J.; Carter, B.; Vilches-Moraga, A.; Quinn, T.J.; Braude, P.; Verduri, A.; Pearce, L.; Stechman, M.; Short, R.; Price, A.; et al. The effect of frailty on survival in patients with COVID-19 (COPE): A multicentre, European, observational cohort study. Lancet Public Health 2020, 5, e444–e451. [Google Scholar] [CrossRef] [Scilit]
- Mitnitski, A.; Mogilner, A.J.; Rockwood, K. Accumulation of deficit as a proxy measure of aging. Sci. World J. 2001, 1, 323–336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Angulo, J.; El Assar, M.; Rodriguez-Manas, L. Frailty and sarcopenia as the basis for the phenotypic manifestation of chronic diseases in older adults. Mol. Asp. Med. 2016, 50, 1–32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanlon, P.; Nicholl, B.I.; Jani, B.D.; Lee, D.; McQueenie, R.; Mair, F.S. Frailty and pre-frailty in middle-aged and older adults and its association with multimorbidity and mortality: A prospective analysis of 493 737 UK Biobank participants. Lancet Public Health 2018, 3, e323–e332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kojima, G.; Iliffe, S.; Walters, K. Frailty index as a predictor of mortality: A systematic review and meta-analysis. Age Ageing 2018, 47, 193–200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onder, G.; Vetrano, D.L.; Marengoni, A.; Bell, J.S.; Johnell, K.; Palmer, K. Optimising Pharmacotherapy through Pharmacoepidemiology Network (OPPEN). Accounting for frailty when treating chronic diseases. Eur. J. Intern. Med. 2018, 56, 49–52. [Google Scholar] [CrossRef] [Scilit]
- Wijsenbeek, M.; Cottin, V. Spectrum of fibrotic lung diseases. New Engl. J. Med. 2020, 383, 958–968. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raghu, G.; Remy-Jardin, M.; Richeldi, L.; Thomson, C.C.; Inoue, Y.; Johkoh, T.; Kreuter, M.; Lynch, D.A.; Maher, T.M.; Martinez, F.J.; et al. Idiopathic Pulmonary Fibrosis (an update) and Progressive Pulmonary Fibrosis in adults. An official ATS/ERS/JRS/ALAT Clinical Practice Guideline. Am. J. Respir. Crit. Care Med. 2022, 205, e18–e47. [Google Scholar] [CrossRef] [Scilit]
- Guler, S.A.; Ryerson, C.J. Frailty in patients with interstitial lung disease. Curr. Opin. Pulm. Med. 2020, 26, 449–456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reddel, H.K.; Bacharier, L.B.; Bateman, E.D.; Brightling, C.E.; Brusselle, G.G.; Buhl, R.; Cruz, A.A.; Duijts, L.; Drazen, J.M.; FitzGerald, J.M.; et al. Global Initiative for Asthma Strategy 2021: Executive summary and rationale for key changes. Eur. Respir. J. 2021, 59, 2102730. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Global Initiative for Asthma. Available online: https://ginasthma.org/ (accessed on 18 July 2023).
- Bodtger, U.; Hallifax, R.J. Epidemiology: Why is pleural disease becoming more common? In Pleural Disease; Maskell, N.A., Laursen, C.B., Lee, Y.C.G., Rahman, N.M., Eds.; European Respiratory Society: Sheffield, UK, 2020; pp. 1–12. [Google Scholar]
- Stang, A. Critical evaluation of the Newcastle-Ottawa scale for the assessment of the quality of nonrandomized studies in meta-analyses. Eur. J. Epidemiol. 2010, 25, 603–605. [Google Scholar] [CrossRef] [Scilit]
- Aguayo, G.A.; Donneau, A.-F.; Vaillant, M.T.; Schritz, A.; Franco, O.H.; Stranges, S.; Malisoux, L.; Guillaume, M.; Witte, D.R. Agreement between 35 published frailty scores in the general population. Am. J. Epidemiol. 2017, 186, 420–434. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rockwood, K.; Song, X.; MacKnight, C.; Bergman, H.; Hogan, D.B.; McDowell, I.; Mitnitski, A. A global clinical measure of fitness and frailty in elderly people. CMAJ 2005, 173, 489–495. [Google Scholar] [CrossRef] [Scilit]
- Ogawa, K.; Fujiwara, Y.; Yoshida, H.; Nishi, M.; Fukaya, T.; Kim, M.; Amano, H.; Lee, S.; Watanabe, N.; Shinkai, S. The validity of the “Kihon Check-list” as an index of frailty and its biomarkers and inflammatory markers in elderly people. Nihon Ronen Igakkai Zasshi Jpn. J. Geriatr. 2011, 48, 545–552. [Google Scholar] [CrossRef] [Scilit]
- Farooqi, M.A.M.; O’Hoski, S.; Goodwin, S.; Makhdami, N.; Aziz, A.; Cox, G.; Wald, J.; Ryerson, C.J.; Beauchamp, M.K.; Hambly, N.; et al. Prevalence and prognostic impact of physical frailty in interstitial lung disease: A prospective cohort study. Respirology 2021, 26, 683–689. [Google Scholar] [CrossRef] [Scilit]
- Guler, S.A.; Kwan, J.M.; Leung, J.M.; Khalil, N.; Wilcox, P.G.; Ryerson, C.J. Functional ageing in fibrotic interstitial lung disease: The impact of frailty on adverse health outcomes. Eur. Respir. J. 2020, 55, 1900647. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Labrecque, P.-F.; Dion, G.; Saey, D. Functional clinical impairments and frailty in interstitial lung disease patients. ERJ Open Res. 2022, 8, 00144–2022. [Google Scholar]
- Sheth, J.S.; Xia, M.; Murray, S.; Martinez, C.H.; Meldrum, C.A.; Belloli, E.A.; Salisbury, M.L.; White, E.S.; Holtze, C.H.; Flaherty, K.R. Frailty and geriatric conditions in older patients with idiopathic pulmonary fibrosis. Respir. Med. 2019, 148, 6–12. [Google Scholar] [CrossRef] [Scilit]
- Guler, S.A.; Kwan, J.M.; Winstone, T.A.; Milne, K.M.; Dunne, J.V.; Wilcox, P.G.; Ryerson, C.J. Severity and features of frailty in systemic sclerosis-associated interstitial lung disease. Respir. Med. 2017, 129, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Milne, K.M.; Kwan, J.M.; Guler, S.; Winstone, T.A.; Le, A.; Khalil, N.; Camp, P.G.; Wilcox, P.G.; Ryerson, C.J. Frailty is common and strongly associated with dyspnea severity in fibrotic interstitial lung disease. Respirology 2017, 22, 728–734. [Google Scholar] [CrossRef] [Scilit]
- Landré, B.; Nadif, R.; Goldberg, M.; Gourmelen, J.; Zins, M.; Ankri, J.; Herr, M. Asthma is associated with frailty among community-dwelling adults: The GAZEL cohort. BMJ Open Respir. Res. 2020, 7, e000526. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kusunose, M.; Sanda, R.; Mori, M.; Narita, A.; Nishimura, K. Are frailty and patient-reported outcomes independent in subjects with asthma? A cross-sectional observational study. Clin. Respir. J. 2021, 15, 216–224. [Google Scholar] [CrossRef] [Scilit]
- Saketkoo, L.A.; Obi, O.N.; Patterson, K.C.; Russell, A.-M. Ageing with Interstitial Lung Disease: Preserving health and well being. Curr. Opin. Pulm. Med. 2022, 28, 321–336. [Google Scholar] [CrossRef] [Scilit]
- Figueiredo, R.G.; Pinheiro, G.P.; Arata, V.; Leal, M.F.M.; Santana, C.V.N.; Tiraboschi, T.L.; Bessa, J., Jr.; Cruz, A. Impact of frailty in elderly patients with moderate to severe asthma. PLoS ONE 2022, 17, e0270921. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).