


Highlights
Main findings
- Clozapine shown to improve Parkinson’s disease psychosis (PDP) with a large effect size despite low doses and does not appear to worsen motor function.
- Quetiapine has a poor evidence base for treatment of PDP, despite widespread use.
Implications
- Clozapine could be considered as a first line antipsychotic (AP) for the management of PDP if standard reductions in dopaminergic medications fail to achieve resolution of symptoms.
- APs with low Dopamine receptor 2 (D2) affinity may not appreciably worsen motor symptoms of Parkinson’s Disease.
Abstract
Background: Psychosis is a common neuropsychiatric symptom associated with Parkinson’s disease (PD), with prevalence rates of up to 75% over the course of the disease. Parkinson’s disease psychosis (PDP) is associated with increased morbidity, caregiver burden, depression, poorer quality of life and progression of dementia. It has also been shown to be a strong predictive factor for long-term care placement, and results in up to 71% increase in risk of mortality compared with PD patients free from psychotic symptoms. Use of APs for PDP is common, with up to 35% of PD patients prescribed at least one AP within 7 years of PD diagnosis. Methods: Four electronic databases (Ovid MEDLINE, Embase, PsycINFO, PubMed) were systematically searched for double-blind, randomised, placebo-controlled clinical trials for the use of APs in the treatment of PDP and their effects on PD motor symptoms, according to PRISMA guidelines. Results: Eleven studies from ten publications were identified and included in this review. Four studies investigated quetiapine, three investigated olanzapine, two investigated clozapine and a further two investigated pimavanserin. Quetiapine showed no significant improvement for PDP over placebo in three of the four studies, with both olanzapine studies also showing no improvement. Olanzapine studies also showed significant motor worsening compared to placebo. Clozapine significantly improved psychosis compared with placebo in both studies, with large effect sizes in primary outcome measures; (−0.82, 95% CI −1.37 to −0.26), −0.89 (95% CI −1.42 to −0.36). Pimavanserin also showed significant improvement (−0.48, 95% CI −0.77 to −0.18). Quetiapine, clozapine and pimavanserin showed no significant worsening in motor scores compared with placebo groups. Conclusions: Data from the studies included in this review suggest that the use of quetiapine for the management of PDP may not be evidence based. Clozapine may improve PDP symptoms with low doses however significant side-effects may limit usability. The findings from this review support the use of clozapine as an alternative AP for the management of PDP when clinically appropriate.
1. Introduction
Parkinson’s Disease (PD) is a progressive, neurodegenerative disorder characterised by bradykinesia, rigidity, resting tremor and postural instability, resulting from neuronal cell loss within the Substantia Nigra Pars Compacta and subsequent dopamine (DA) depletion [1]. It is the second most common neurodegenerative disorder globally, affecting over 6 million individuals [2], with the fastest growing prevalence; incident cases exceeding one million annually as of 2017 [3,4]. Although diagnostic criteria focus on motor dysfunction, PD also presents with other non-motor symptoms, which may occur up to 20 years prior to clinical motor manifestation [5]. This prodromal phase of PD can be characterised by autonomic disturbance, olfactory dysfunction, sleep disorders and psychiatric symptoms [6,7,8,9,10].
Psychotic symptoms may occur in up to 75% of PD patients during the course of the disease process, depending on psychosis definitions and rating scales [11,12,13,14], and are a significant burden of disease. Parkinson’s disease psychosis (PDP) is associated with increased morbidity, depression, poorer quality of life [15], caregiver burden [16], development and progression of dementia [17,18] and has been shown to be a strong predictive factor for long-term care placement [19]. Recent studies show those diagnosed with PDP at an increased risk of hospitalisation [20] and up to 71% increase in risk of mortality compared with PD patients free from psychotic symptoms [21].
Dopaminergic medications have long been suggested as the main causative factor leading to PDP [22,23], with all PD medication types associated with psychotic symptoms [24]. Changes in dopaminergic therapy have been observed to precipitate PDP, with improvements in psychosis seen following reduction or cessation [25], however psychotic symptoms have been reported in up to 42% of drug-naive PD patients [26,27], suggesting that their occurrence may be intrinsically linked with the disease process itself rather than solely attributable to dopaminergic therapy used to manage motor dysfunction.
When psychotic symptoms are distressing, intolerable or fail to improve with adjustment of dopaminergic therapy, AP treatment may be required [28]. The use of AP medications in patients with PD is widespread, with 12% of patients prescribed an AP within the first 12 months of PD diagnosis and 35% of patients within seven years [29,30], and has been associated with worsened motor symptoms of PD and increased mortality [31].
Currently, only clozapine has a UK licence for the treatment of PDP, however accounts for <2% of AP prescribing. Quetiapine accounts for 49–66% of AP prescriptions in PDP [29,32], despite no clear advantage over placebo in a previous meta-analysis of double-blind, randomised placebo-controlled trials [33].
Previous systematic reviews and meta-analyses investigating APs in PDP have been completed, with a number limited to atypical class [34,35,36,37,38,39] or single drug reviews [33,40]. A single meta-analysis [34] completed in 2015 includes wide search terms for APs, and specifies only double blind, randomised, placebo-controlled trials for inclusion, and further systematic reviews and network meta-analyses have been completed including any APs whilst also including comparator [37] and open label studies [36,39]. Details of relevant studies are summarised on Table 1.
Table 1.
Previous reviews of Antipsychotic treatment for PDP.
This review aims to provide an up-to-date analysis of double-blind, randomised, placebo-controlled trials investigating the treatment of PDP with no restriction by AP class, searching all AP medications that are in use or have been used, worldwide. The most recent systematic review with these strict inclusion criteria was published in 2015 [34] and this review serves as an appropriate update to the current body of literature. Preliminary findings from this review were presented in abstract and poster form at the Royal College of Psychiatrists International Congress, 2024. This manuscript has been substantially expanded and updated with recent literature searches, detailed methodology including risk of bias assessment, reporting of dose titration schedules and how these may have impacted outcomes, with a focus on detailed narrative synthesis to help inform readers of the strengths and weaknesses of the included studies. A limited pooled meta-analysis was also performed to provide supporting quantitative evidence. This review aims to further inform clinical decision-making regarding AP choice, dosing and titration schedules in PDP, given ongoing uncertainty about the relative roles of commonly used agents in routine practice, where quetiapine often remains a first-line treatment.
2. Materials and Methods
2.1. Study Design
This systematic review was conducted with reference to the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) 2020 statement guidelines (for PRISMA flow diagram, see Appendix A, Figure A1) [41]. The review protocol was developed a priori, however was not registered.
2.2. Objectives
The aims of this review are to identify, appraise and synthesise evidence from published, peer-reviewed double-blind, randomised, placebo-controlled trials investigating the efficacy and tolerability of APs in the management of PDP, with particular focus on motor outcomes.
2.3. Search Strategy
Searches were restricted to fully published and peer-reviewed papers: Electronic database searches were conducted via Ovid, including MEDLINE (1946 to 7 November 2025), Embase (1974 to 2025 Week 45), APA PsycINFO (1806 to Nov 2025 Week 1). Additional searches were performed in PubMed and Google Scholar to identify further relevant references (Nov 2025). Clinical trial registries, unpublished and non-peer reviewed sources were not systematically searched or included. Peer-review was considered an essential criterion for study inclusion, to ensure methodological scrutiny. The list of APs was derived by searching available literature and the online resources [42,43,44]. To maximise yield of relevant papers, selected keywords were truncated to account for differences in spelling and pluralisation and to cover a broader range of relevant related terms. Search strategy for each database can be found in Appendix A, Figure A2a,b.
2.4. Eligibility
Inclusion Criteria:
- Double-blind, randomised, placebo-controlled trials.
- Treatment arm using recognised AP medication.
- Participants with a clinical diagnosis of idiopathic PD and psychotic symptoms
- Studies reporting quantified measures of psychosis and motor outcomes using validated rating scales as either primary or secondary outcome measure.
- English-language, peer reviewed publications.
Exclusion Criteria:
- Comparator or open-label studies.
- Reviews, case reports, conference abstracts without full data or unpublished data.
- Studies including patients with diagnosed dementias such as dementia with Lewy bodies, unless data could be separated.
2.5. Outcomes of Interest
- Primary Outcome: Change in psychotic symptoms in PD, measured by validated instruments.
- Secondary outcome: Change in Motor symptoms, measured using validated instruments
- Adverse events and discontinuations reported.
2.6. Study Selection and Data Extraction
Titles and abstracts were screened independently by both authors. Full texts of potentially eligible publications were reviewed independently by both authors against inclusion criteria, with discrepancies resolved by discussion. Data were extracted from eligible publications by the lead author, using a modified Cochrane Data Collection Tool and are tabulated in Table 2 (trial characteristics; participant demographics, psychotic symptoms, entry criteria, PD diagnostic criteria, measures used, titration schedule) and Table 3 (descriptive results; psychosis outcomes, motor outcomes, dropouts and adverse events). Raw numerical data for included publications are included in Supplementary Materials.
Table 2.
Characteristics of Included Studies.
2.7. Quality Assessment
Risk of Bias was assessed by the lead author using RoB 1 (integrated in RevMan 5.4 software) provided by the Cochrane collaboration [55]. Inclusion of studies was not dependent on outcome of risk of bias assessment. Assessment included reviews of selection bias (random sequence generation and allocation concealment), performance bias, detection bias, attrition bias and reporting bias. Domains were assessed as low, high or unclear risk of bias Results are summarised in Appendix A, Figure A3. Domains were judged following guidance in the Cochrane Handbook for Systematic Reviews of Interventions [56].
2.8. Data Synthesis
Due to the anticipated small number and heterogeneity of trials, a full pooled meta-analysis for all APs was not planned a priori. However, where trials of the same AP were comparable in outcome measures and appropriate data were available, limited inverse-variance random-effects meta-analyses were performed using RevMan 5.4 statistical software, provided by the Cochrane Collaboration [55]. A random-effects model was utilised for pooling of estimates to account for clinical and methodological heterogeneity, including differences in study duration and dosing strategies. Statistical heterogeneity was assessed using the I2 statistic. Where pooling was not appropriate due to heterogeneity in outcome measures or insufficient data, findings have been synthesised descriptively and grouped by AP to allow comparison of efficacy, motor effects and tolerability, as well as direction and magnitude of effect. Effect sizes were calculated where adequate data were available.
2.9. Reference Management
All references were managed in Mendeley Cite, and data extraction tables were prepared in Microsoft Word. Database search results were managed in Rayyan [57] for further deduplication and completion of manual screening.
3. Results
A total of 1048 publications were returned from database searches. Following initial deduplication “abstract” and “randomised controlled trial” filters were applied as part of the structured a priori search strategy. 124 papers remained and were manually screened to assess eligibility for inclusion. 113 were excluded (reasons provided in PRISMA flow diagram Appendix A, Figure A1). Full text review of eleven publications was completed. One included patients with Dementia with Lewy Bodies and was disregarded [58]. One lacked a control group and was also disregarded [59] as per pre-defined inclusion criteria. Reference lists of included publications were screened for further relevant papers, yielding one further study that met criteria for inclusion [49]. Ten papers comprising a total of eleven individual clinical studies fulfilled the criteria for inclusion, with a total of 645 patients: 129 from the four quetiapine studies, 137 from the two olanzapine studies, 120 from the two clozapine studies and 259 from the two pimavanserin studies. All included studies utilised single active intervention arm versus placebo; no adjustment for multi-armed designs was required. Where a publication reported two distinct randomised trials, these were extracted and analysed as two separate studies. Four investigated quetiapine [45,46,47,48], two olanzapine [49,50], two clozapine [51,52] and two pimavanserin [53,54]. Cognitive exclusion criteria varied between studies. One excluded patient with dementia [54], although no definition of dementia was provided. Unified Parkinson Disease Rating Scale (UPDRS) Part 1 “intellectual impairment” is however recorded in the results. Two excluded patients with either “significant cognitive impairment” or dementia, if unable to complete testing [48,51] without specifying how these patients were assessed.
Table 3.
Description of Study Results.
Formalised cognitive assessment using Mini-Mental State Examination (MMSE) [60] was undertaken in four papers as part of their exclusion criteria screening. Three used an inclusion cut off score of >20 [49,52,53] and one used a score of >21 [47]. The remaining three papers did not exclude patients on the basis of cognitive impairment or diagnosis of dementia, however, did complete MMSE testing [45,46,50].
Psychosis inclusion criteria differed between the included studies with regards to severity and instruments used to screen participants. One paper [54] utilised criteria developed for diagnosis of PDP, however the remaining nine used standard definitions of psychosis, not specific to PD. Three focused exclusively on hallucinations [47,48,49], with the remainder investigating both hallucinations and delusions.
Diagnostic criteria for Parkinson’s disease was not consistent for the included papers: five citing UK Brain Bank Criteria [45,46,48,52,53]; one utilising Diagnostic and Statistical Manual of Mental Disorders-IV criteria [50]; two papers diagnosed PD on either two or three “cardinal features” with no obvious exclusionary criteria for other parkinsonian presentations [49,51], and two did not report diagnostic criteria [47,54].
Risk of Bias assessment of the included studies found that both blinding of participants and personnel as well as blinding of outcome assessment were all considered to be low risk, however many studies did not describe how allocation concealment was maintained, leading to unclear risk of selection bias in eight of the included papers. Of particular note was the overall high risk of attrition bias in the papers, with no included study considered to be low risk. This may reduce confidence in the interpretation of treatment effects.
Evidence Synthesis
Where pooling of data was undertaken for individual agents, a random-effects model was used to account for anticipated clinical and methodological heterogeneity. Due to the small number of included studies, statistical heterogeneity, as assessed by the I2 statistic, was interpreted cautiously.
Of the four quetiapine trials, three found that there was no statistically significant improvement in psychosis of any measure [45,46,47], with one paper showing significant improvements in Brief Psychiatric Rating Scale (BPRS) item II (hallucinations) and Clinical Global Impression-Severity (CGI-S) [48]. No significant worsening of motor symptoms was seen between groups. Meta-analysis was not undertaken for quetiapine due to incomplete data, omitting mean change difference (MD) ± Standard Deviation (SD) or Standard Error (SE).
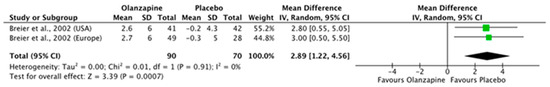
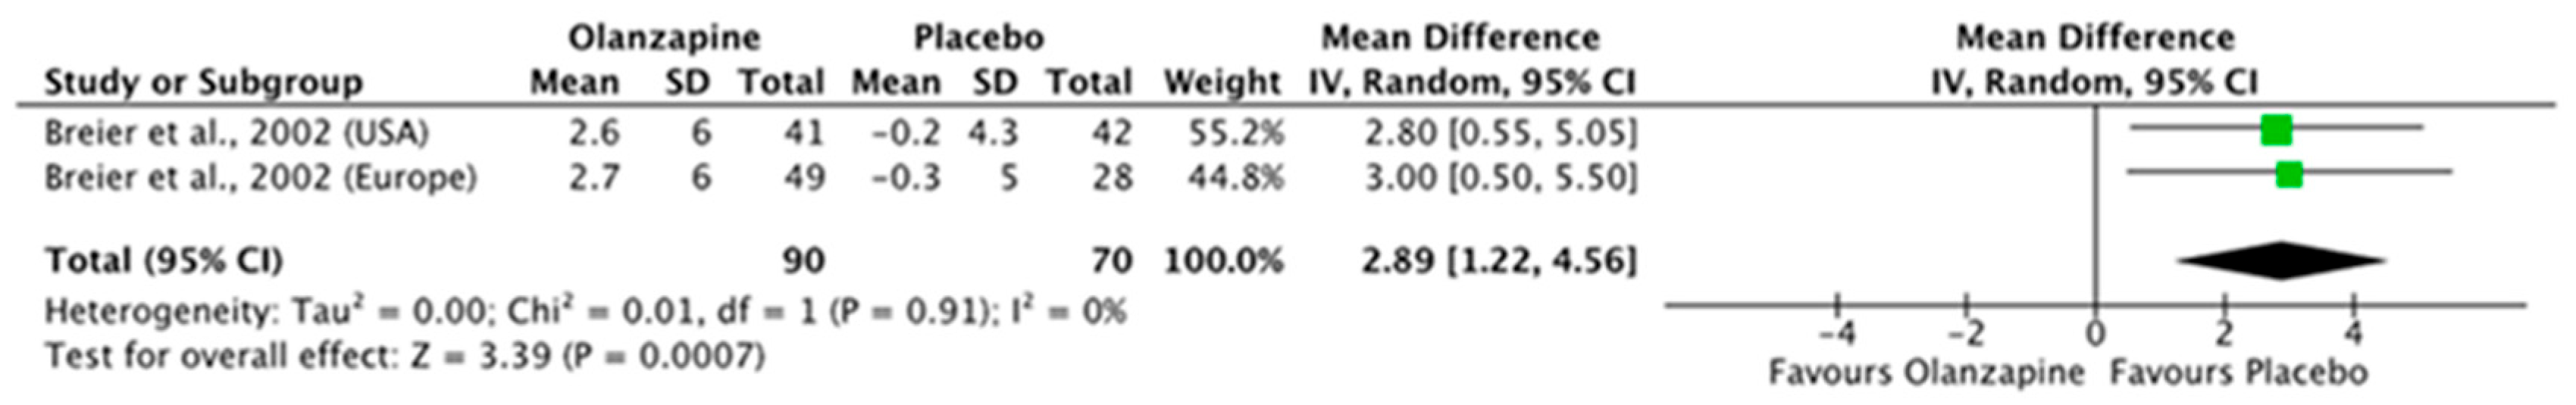
Both olanzapine studies [49,50], demonstrated no statistically significant improvement in psychosis compared with placebo and showed significant worsening of motor function. Pooled analyses for psychosis and motor symptoms were completed for two olanzapine trials from one paper [50], with statistically significant worsening of motor symptoms observed on UPDRS mean change difference (Figure 1).
Figure 1.
Random-effects model meta-analysis, olanzapine, motor (UPDRS) mean change difference [50].
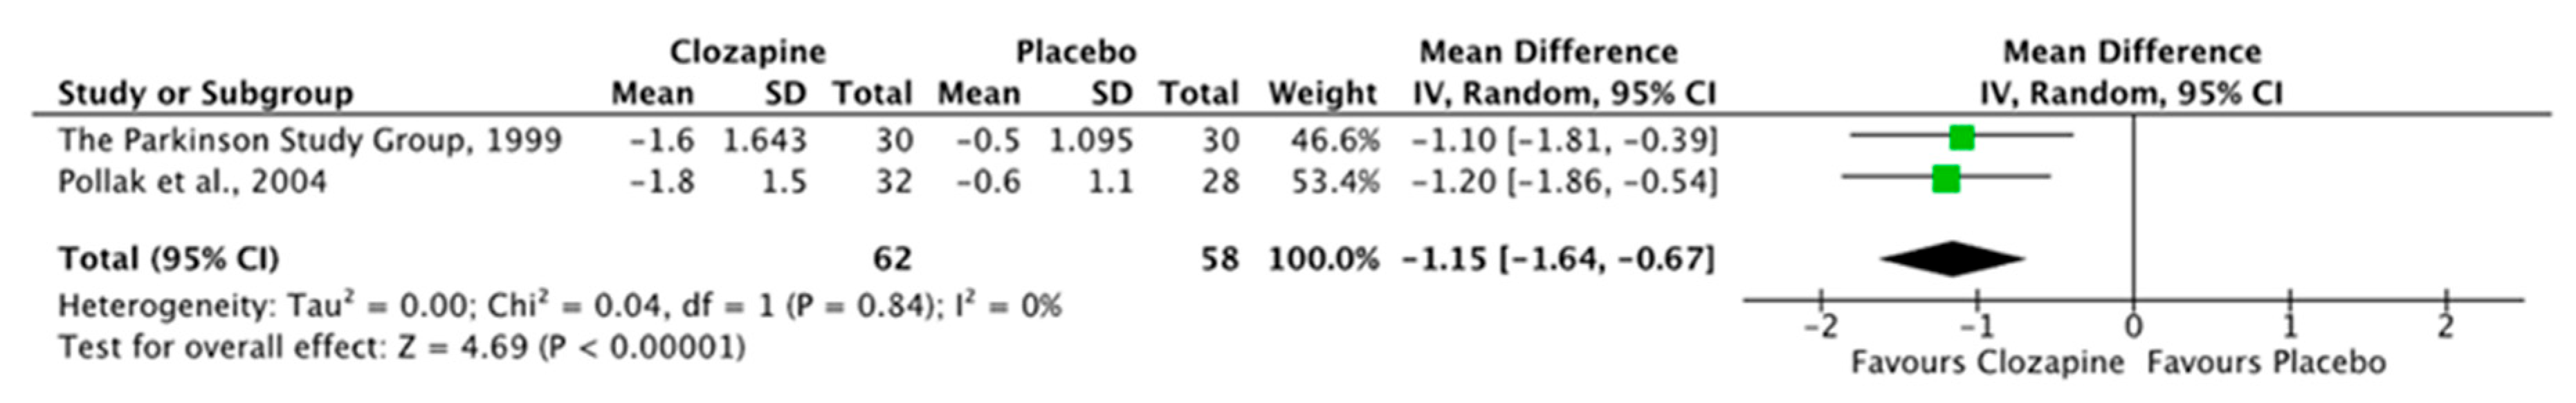
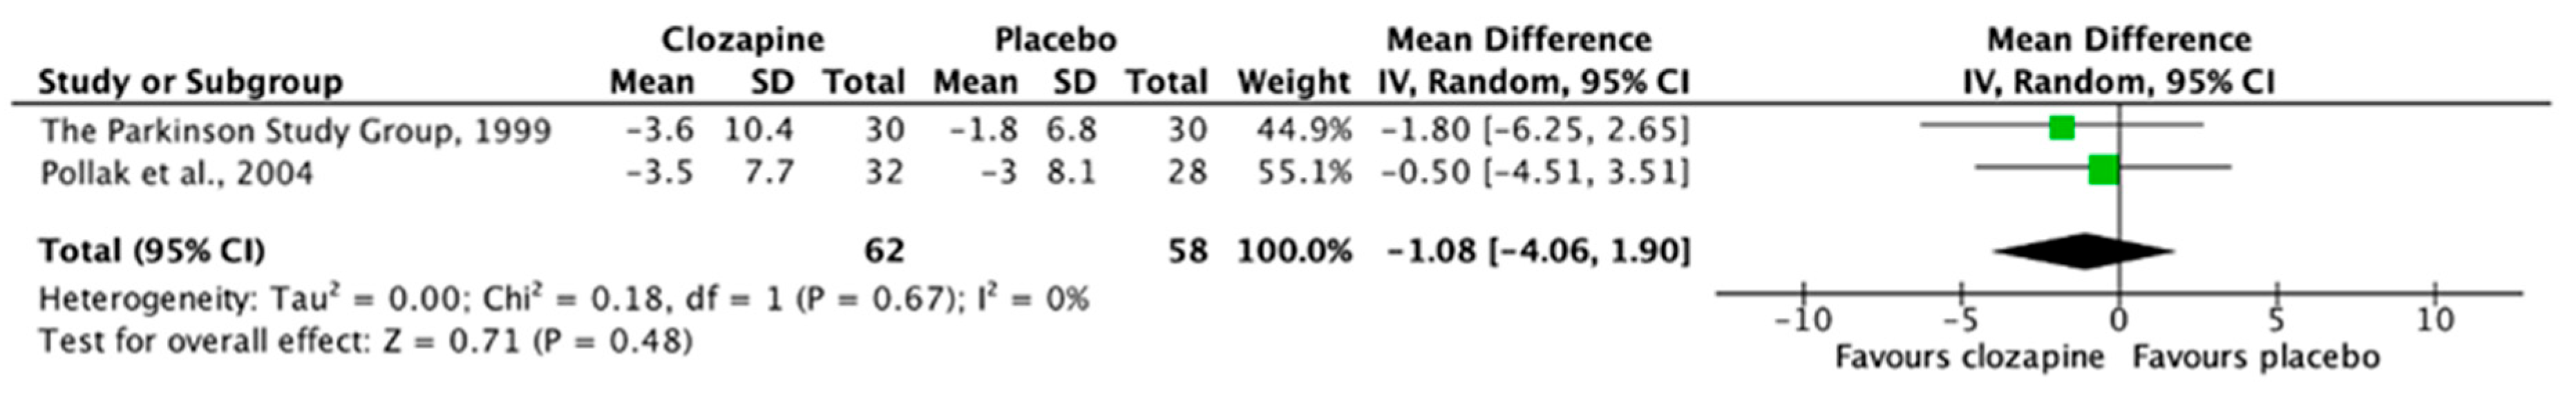
Both publications investigating clozapine [51,52] found significant improvements in measures of psychosis with a large effect size, and no statistically significant worsening of motor symptoms compared with placebo. These studies were sufficiently homogeneous in design and outcome measures to allow for pooling of data. Random-effects meta-analysis demonstrated a significant improvement in psychotic symptoms as measured by CGI-S scale mean change difference (Figure 2), with no statistically significant worsening of motor scores as measured by UPDRS (Figure 3).
Figure 2.
Random-effects model meta-analysis, clozapine, psychosis (CGI-S) mean change difference [51,52].
Figure 3.
Random-effects model meta-analysis, clozapine, motor (UPDRS) mean change difference [51,52].
Statistical heterogeneity within the analyses in this review was low, which may indicate consistent effects between pooled studies; however, this must be interpreted cautiously due to the small number of trials included for each agent.
Pimavanserin studies found no statistically significant worsening of motor symptoms, however differed in improvements in psychosis. One paper did not reach significance in primary efficacy outcome measures but found global rater-assessed measure of hallucinations and delusions to have improved significantly when compared with placebo [54]. One paper found significant improvement in psychosis using both primary and secondary efficacy measures when compared with placebo [53], however failed to reach a previously specified threshold for meaningful clinical relevance. Due to differences in the reporting of data between the two pimavanserin studies (one providing MD ± SE for both psychosis and motor symptoms, and one paper providing baseline and post treatment means ± SD, with no MD ± SD/SE), pooled analysis was not performed.
4. Discussion
Across the included studies, clozapine demonstrated the most consistent efficacy for treatment of PDP showing a large effect size in most measures of psychosis utilised by the papers, with only a single measure marginally missing the large effect threshold value of 0.8. Effect sizes are presented in Appendix A, Table A1, calculated using data provided by the included papers where available. Both studies’ CGI-S measure has shown a robust clinician rated treatment effect for PDP, which supports the significant treatment effect seen in both patient-rated BPRS and Positive and Negative Syndrome Scale (PANSS) positive.
UPDRS motor scores were not significantly different between groups in either paper, however a trend towards improvement was seen in those treated with clozapine. The Parkinson Study Group noted that there was an improvement in tremor in the clozapine group, not reported in Pollak et al., (2014) [52], which may account for this. Pollak et al. [52], report seven AEs of worsening Parkinsonism, however these did not require cessation of medication and were not reflected in overall motor scoring. Pollak et al., [52] also reported a high frequency of somnolence in the active group, which may reflect the relatively rapid titration of treatment when compared with the Parkinson Study Group, (1999) [51] paper. Both clozapine studies experienced at least one instance of neutropenia (NP) or leukopenia, which highlights the potential risk of inducing haematological abnormalities despite the low doses used. These findings broadly support the conclusions from the previous meta-analyses in Table 1, all of which showed consistent improvements in measures of psychosis from their included trials.
The studies using pimavanserin show a mixed picture with regards to efficacy, which is at odds with results from previous meta-analyses possibly due to the exclusion of two unpublished trials that are frequently included, as well as other trials including comparator studies that were not included in this review due to a priori inclusion/exclusion criteria. Both included pimavanserin studies in this review utilise the Scale for the Assessment of Positive Symptoms, Hallucinations and Delusions subsections (SAPS H + D) as a measure of psychosis, however Cummings et al., [53] showed a significant improvement, whilst Meltzer et al. [54], efficacy results fell short of significance. Mean SAPS H + D score reductions for pimavanserin groups in both studies appear similar, as do the mean score reductions in placebo groups. Considering the greater treatment effect seen by Meltzer [54], the lack of significance may be the result of a type 2 error, potentially due to relatively small sample size. Cummings et al., [53] utilised the Scale for the Assessment of Positive Symptoms—Parkinson’s Disease (SAPS-PD) as their primary outcome measure for psychosis, which is unique to this paper. It is unclear if this measure has been robustly validated as a measure of PDP, however the effect size seen is consistent with other measures of psychosis used in the study, which would suggest that this may be a valid measure of PDP. The authors have stated that an improvement of 1 on Clinical Global impression—Improvement (CGI-I) would be deemed to be a clinically meaningful improvement in PDP, which was associated with a change of 2.33 in SAPS-PD during its development [61]. Cummings et al., [53] did not observe an improvement of 1 on CGI-I, the benchmark for meaningful clinical improvement, despite SAPS-PD mean reduction of 3.06. Statistical significance of individual reported rates side effects for both studies have not been reported, however both studies appear to show an increased risk of peripheral oedema. Data from both studies show no statistically significant worsening of motor symptoms, which is consistent with pimavanserin’s very low D2 binding affinity (detailed in Table 4) resulting in negligible nigrostriatal DA blockade.
BPRS, CGI-S and UPDRS outcomes for the Breier et al., [50] studies support the findings of Ondo et al., (2002) [49] with olanzapine’s lack of efficacy for the treatment of PDP, as well as its negative impact on motor symptoms of PD. The AEs reported in the Ondo et al., USA study [47,49] add weight to the results, with significantly higher reported rates of extrapyramidal symptoms, hallucinations and increased salivation in the active group, however these differences were not seen in the European study. These results are in keeping with olanzapine’s comparatively high D2 receptor binding affinity, with previous studies [62] showing significant D2 receptor occupancy at low doses of olanzapine, comparable to mean dosages used in the included studies. This may explain PD patients’ particular sensitivity due to depleted nigrostriatal DA being subject to further blockade, worsening motor and extrapyramidal symptoms.
Three of the four studies utilising quetiapine included in this review showed no significant improvement in psychosis over placebo, however Fernandez et al., (2009) [48] reported significant improvement in two measures, with improvements in BPRS item 12 demonstrating a large effect size. The reasons for these significant results are unclear but may represent a type 1 error due to small sample size and method used for intention-to-treat analysis. All quetiapine studies showed no significant worsening of motor scores, again possibly due to quetiapine’s low D2 receptor binding affinity, again broadly supporting the findings of previously published literature.
Table 4.
Receptor binding affinities (Ki, nM) of antipsychotics in this review.
The studies that have been included in this review suffered several methodological limitations that may affect their reliability. Power calculations were provided in only five of the eleven included studies [45,46,51,53,54], with only two of these recruiting the required numbers of participants [51,54]. A further significant limitation of the literature included in this review was incomplete outcome data, which limited statistical analysis, with only six studies providing adequate data required to calculate effect size appropriately (Appendix A, Table A1). Study design heterogeneity, including duration, dosages of medications, and titration schedules further complicates direct comparison, as does the use of differing scales for the assessment of psychosis. Entry criteria were also not consistent for all studies, with differing inclusion and exclusion thresholds for both cognitive function and psychosis. PDP has no formalised diagnostic criteria, however a National Institute of Neurological Disorders and Stroke/National Institute for Mental Health work group developed suggested criteria [65] which have been utilised by two of the included publications. Other publications in this review either conducted their studies prior to the publication or have used an alternative definition of PDP. This introduces further participant heterogeneity between the papers. Five studies were deemed to have an unclear risk of attrition bias, four of which utilised Last Observation Carried Forward for missing data. This method assumes stability of symptoms after dropout, and may introduce bias if attrition differs between groups. A further six studies were deemed high risk of attrition bias (see Appendix A, Figure A3). Incomplete follow up and potential bias reduce confidence in the reliability of calculated treatment effect estimates across studies.
The findings of this review are broadly consistent with the current body of evidence for the AP management of PDP (see Table 1), with clozapine demonstrating the most consistent efficacy signal and olanzapine showing poor efficacy alongside a propensity to worsen motor scores. Most recent reviews similarly find that although quetiapine does not appear to exacerbate motor symptoms in PD patients, its antipsychotic effect is comparable to placebo. The quetiapine trial demonstrating statistically significant improvements in CGI-S and the hallucinations subsection of BPRS (item 12) was associated with a 50% attrition rate in the active intervention arm, with non-completer data imputed using a linear model of completers. High attrition and small sample size reduces confidence in the robustness and reliability of these findings [48]. Pimavanserin is widely reported to produce statistically significant improvements in psychosis scores and remains a potential alternative to clozapine; however, the effect sizes observed for the included studies in this review were small to medium, and clinically meaningful improvements were not achieved in one of the two trials. This highlights that statistical significance within trial data does not necessarily translate into clinically meaningful benefit for patients.
5. Conclusions
Recent publications examining AP prescribing patterns indicate quetiapine accounts for approximately half of all prescriptions for the treatment of PDP. National Institute for Health and Care Excellence (NICE) guidelines recommend considering quetiapine in patients without cognitive impairment and offering clozapine where standard management is ineffective [28]. The findings from this systematic review suggest that, despite quetiapine’s low risk of worsening motor symptoms in PD, it has not demonstrated benefit over placebo for the treatment PDP in double-blind, randomised, placebo-controlled trials. Given the increased risk of mortality in patients prescribed APs, a clear therapeutic benefit should be seen to justify their use.
Currently available evidence does not support the use of quetiapine as a first-line AP for the treatment of PDP, particularly when other agents have demonstrated superiority to placebo, without appreciable worsening of motor scores. Notably, although efficacious for PDP, clozapine continues to carry a risk of significant adverse effects including NP even with the low dosages utilised in PDP trials. Owing to the potential for significant and life-threatening adverse effects, stringent haematological monitoring has historically been required for patients receiving clozapine. Perceived risk and monitoring burden may impact clinicians’ willingness to prescribe clozapine for PDP, potentially contributing to its relatively low utilisation despite evidence of efficacy and overall tolerability. This may in turn result in some patients’ psychosis remaining inadequately managed.
More recently, clozapine monitoring guidance in the European Union has changed to 12-weekly blood tests from the previous four-weekly if the patient has not developed NP within the first year of treatment, and then moving to yearly testing if no evidence of NP in the first two years. This is based upon large meta-analyses [66], retrospective cohort studies [67] and registry-based analyses [68,69], which have found NP to be most common in early treatment, with incidence decreasing after 18 weeks. These evolving guidelines may reduce the burden of haematological monitoring and may improve the utilisation of clozapine for the treatment of PDP due to changing perspectives on risk, and improved capacity in dedicated clozapine clinics from these reduced monitoring requirements.
A collaborative, multidisciplinary approach involving both movement disorder and mental health specialists is advised when managing PDP, due to its impact on quality of life, morbidity and mortality. Dedicated PDP clozapine services and early involvement of community mental health teams to robustly monitor for PDP may improve long-term outcomes for PD patients.
The strengths of this review include its scope; completing a systematic search for publications investigating the efficacy and tolerability of APs in the treatment of PDP over four scientific databases, including all currently available APs worldwide to reduce the likelihood of arbitrarily disregarding studies completed with APs not available in the UK. Only primary data has been utilised; double-blind, randomised, placebo-controlled studies that have been published in a peer reviewed journal have been included, providing the highest level of evidence for treatment effect.
The limitations of this review include: its restriction of eligible studies to published, peer reviewed double-blind, randomised, placebo-controlled trials, which excluded double-blind comparator studies that may have provided comparative effectiveness data for a wider range of APs. This limits the number of trials and agents included in this review, which may impact its clinical utility. Limiting papers to English language may have also resulted in relevant papers being omitted. Use of automated database search limits may arbitrarily disregard relevant studies, and a lack of preregistration limits the verifiability of a priori review protocol. However, narrowly defined inclusion criteria, restricted to published, peer reviewed double-blind placebo-controlled trials mitigates the risk of selective inclusion exclusion of relevant studies. The exclusion of unpublished trials which may be listed on clinical trial registries may also contribute to publication bias, potentially resulting in data synthesis supporting favourable efficacy or tolerability.
Despite the high prevalence of PDP, there is a paucity of high-quality double-blind, randomised placebo-controlled clinical trials that inform national guidelines, with only four AP medications investigated to this standard of evidence. Among these, inter-study design heterogeneity, as well as limited number of included studies render statistical analysis of provided data more difficult to interpret. Further clinical trials of AP medications, particularly those with low D2 binding affinity, may help to improve the evidence base that is currently used to inform national prescribing guidelines. Direct head-to-head pimavanserin clozapine studies may more clearly demonstrate comparative efficacy and tolerability, as well as comparator studies between pimavanserin and quetiapine—the most commonly prescribed AP medication for PDP in the UK [29,32]. Tolerability and long-term safety studies for newer agents such as pimavanserin, as well as the currently NICE recommended clozapine in PD cohorts would be of significant benefit for clinicians to better understand balance of risk when prescribing for their patients.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/healthcare14050698/s1, Table S1: Quantitative results data for change in psychosis as reported by included clinical studies; Table S2: Quantitative results data for change in motor symptoms as reported by publications.
Author Contributions
C.J.M.—Conceptualisation, Methodology, Formal Analysis, Investigation, Writing—Original Draft, Writing—Review and Editing, Visualisation. A.S. Methodology, Investigation, Writing—Original Draft, Writing—Review and Editing, Supervision, Project Administration. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding. The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.
Institutional Review Board Statement
Ethical review and approval were waived for this study; it is a systematic review based upon previously published data, and does not involve human participants or identifiable personal data.
Informed Consent Statement
Informed consent was not applicable for this study as analysis was based upon data from previously published research.
Data Availability Statement
Data analysed were obtained from previously published studies that have been cited in the reference list and main body text. Extracted data and calculated effect sizes are included within the manuscript Supplementary Materials.
Acknowledgments
The authors used ChatGPT 5.4 (OpenAI) to assist with language refinement and typography checking. All content has been critically reviewed and verified by the authors, who take full responsibility for the integrity of the work.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| α1A | Adrenergic Alpha Receptor Type 1A |
| α2A | Adrenergic Alpha Receptor Type 2A |
| α2C | Adrenergic Alpha Receptor Type 2C |
| ADL | Activities of Daily Living |
| AE | Adverse Event |
| AP | Antipsychotic |
| BD | Bis in Die |
| BPRS | Brief Psychiatric Rating Scale |
| CGI-I | Clinical Global Impression—Improvement |
| CGI-S | Clinical Global Impression—Severity |
| CLO | Clozapine |
| COMP | Comparator Trial |
| D2 | Dopamine Receptor Type 2 |
| D3 | Dopamine Receptor Type 3 |
| DA | Dopamine |
| DBRPCT | Double Blind, Randomised Placebo Controlled Trial |
| DLB | Dementia with Lewy Bodies |
| F | Female |
| GDRS | Goetz Dyskinesia Rating Scale |
| H1 | Histamine Receptor Type 1 |
| Ki | Equilibrium Inhibitor Constant |
| M | Male |
| M1 | Muscarinic Receptor Type 1 |
| mg | Milligram |
| MMSE | Mini Metal State Examination |
| NICE | National Institute for Health and Care Excellence |
| nM | Nanomolar |
| NP | Neutropenia |
| NPI | Neuropsychiatric Inventory |
| nr | No Response |
| NR | Not Reported |
| OD | Omne in Die |
| OL | Open Label |
| OLZ | Olanzapine |
| PANSS | Positive and Negative Syndrome Scale |
| PPRS | Parkinson Psychosis Rating Scale |
| PD | Parkinson’s Disease |
| PDP | Parkinson’s Disease Psychosis |
| PIM | Pimavanserin |
| PLA | Placebo |
| QTP | Quetiapine |
| RCT | Randomised Controlled Trial |
| SAPS | Scale for the Assessment of Positive Symptoms |
| SAPS H + D | SAPS total Hallucinations and Delusions domain score |
| SAPS-PD | Scale for the Assessment of Positive Symptoms in Parkinson’s Disease |
| SD | Standard Deviation |
| SE | Standard Error |
| UPDRS | Unified Parkinson’s Disease Rating Scale |
| 5-HT1A | Serotonin Receptor Type 1A |
| 5-HT2A | Serotonin Receptor Type 2A |
| 5-HT2C | Serotonin Receptor Type 2C |
| 5-HT6 | Serotonin Receptor Type 6 |
| 5-HT7 | Serotonin Receptor Type 7 |
Appendix A
Figure A1.
PRISMA 2020 flow diagram for database searches.
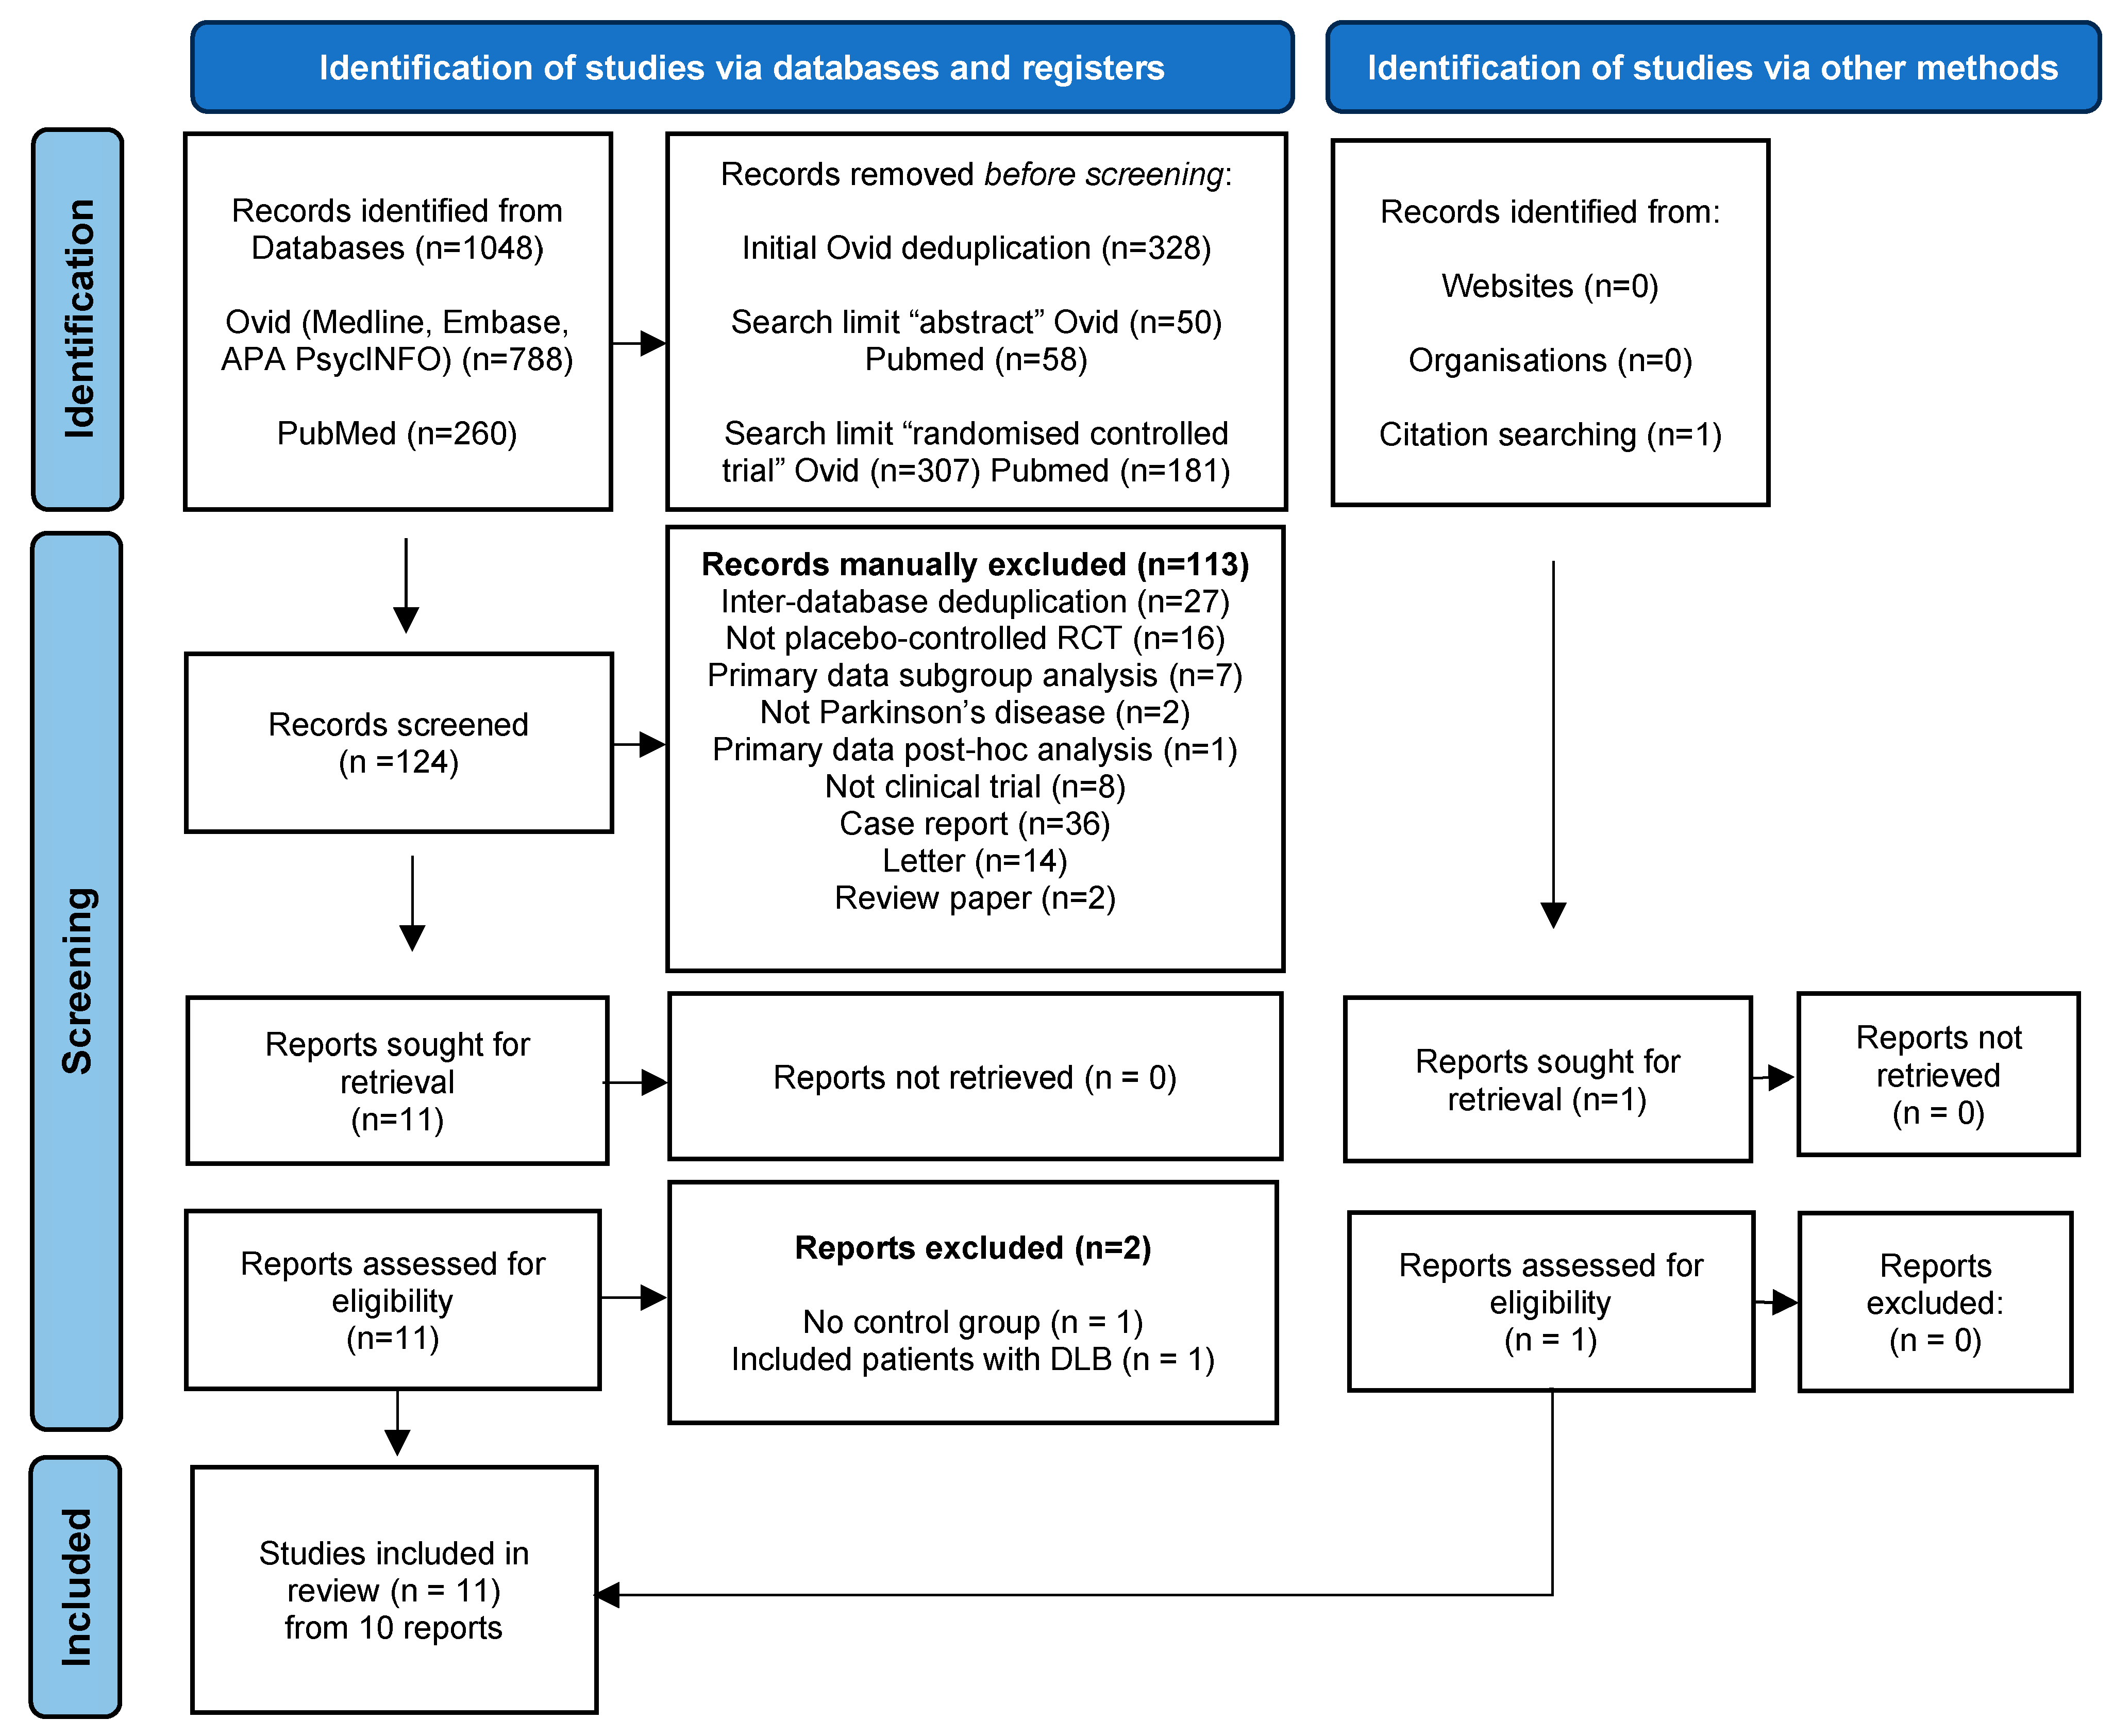
Figure A2.
(a), Search strategy for Ovid (MEDLINE, Embase, PsycINFO). Search Limits “Abstract” and “Randomised Controlled Trial” applied to results following automated deduplication. (b), Search strategy for Pubmed. Search limits “Abstract” and Randomised Controlled Trial” applied to results. * is used for truncation in the search criteria-standard for electronic databases.
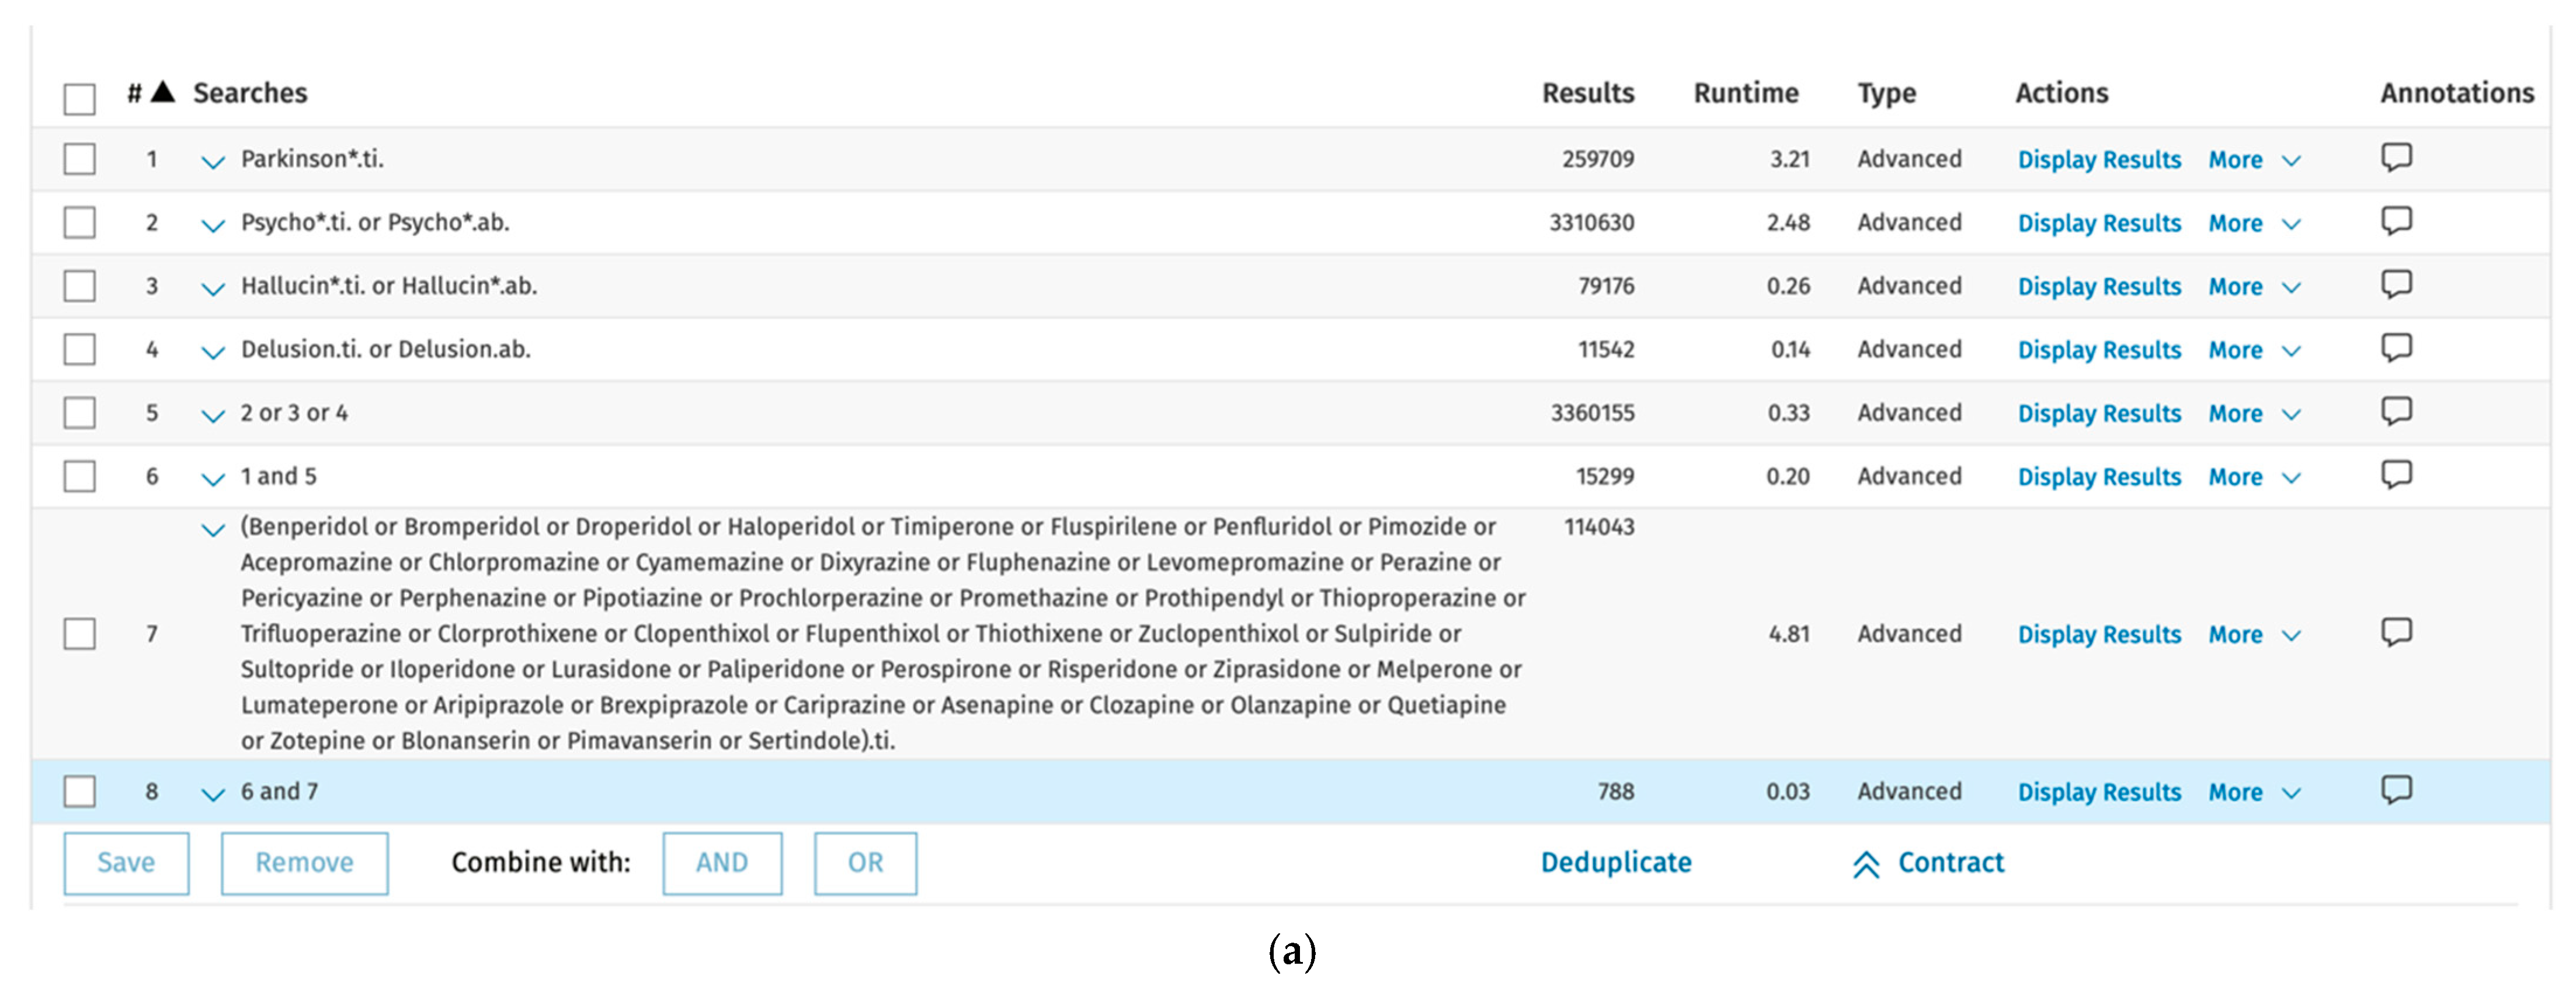

Figure A3.
Risk of Bias assessment Summary Table [45,46,47,48,49,50,51,52,53,54].
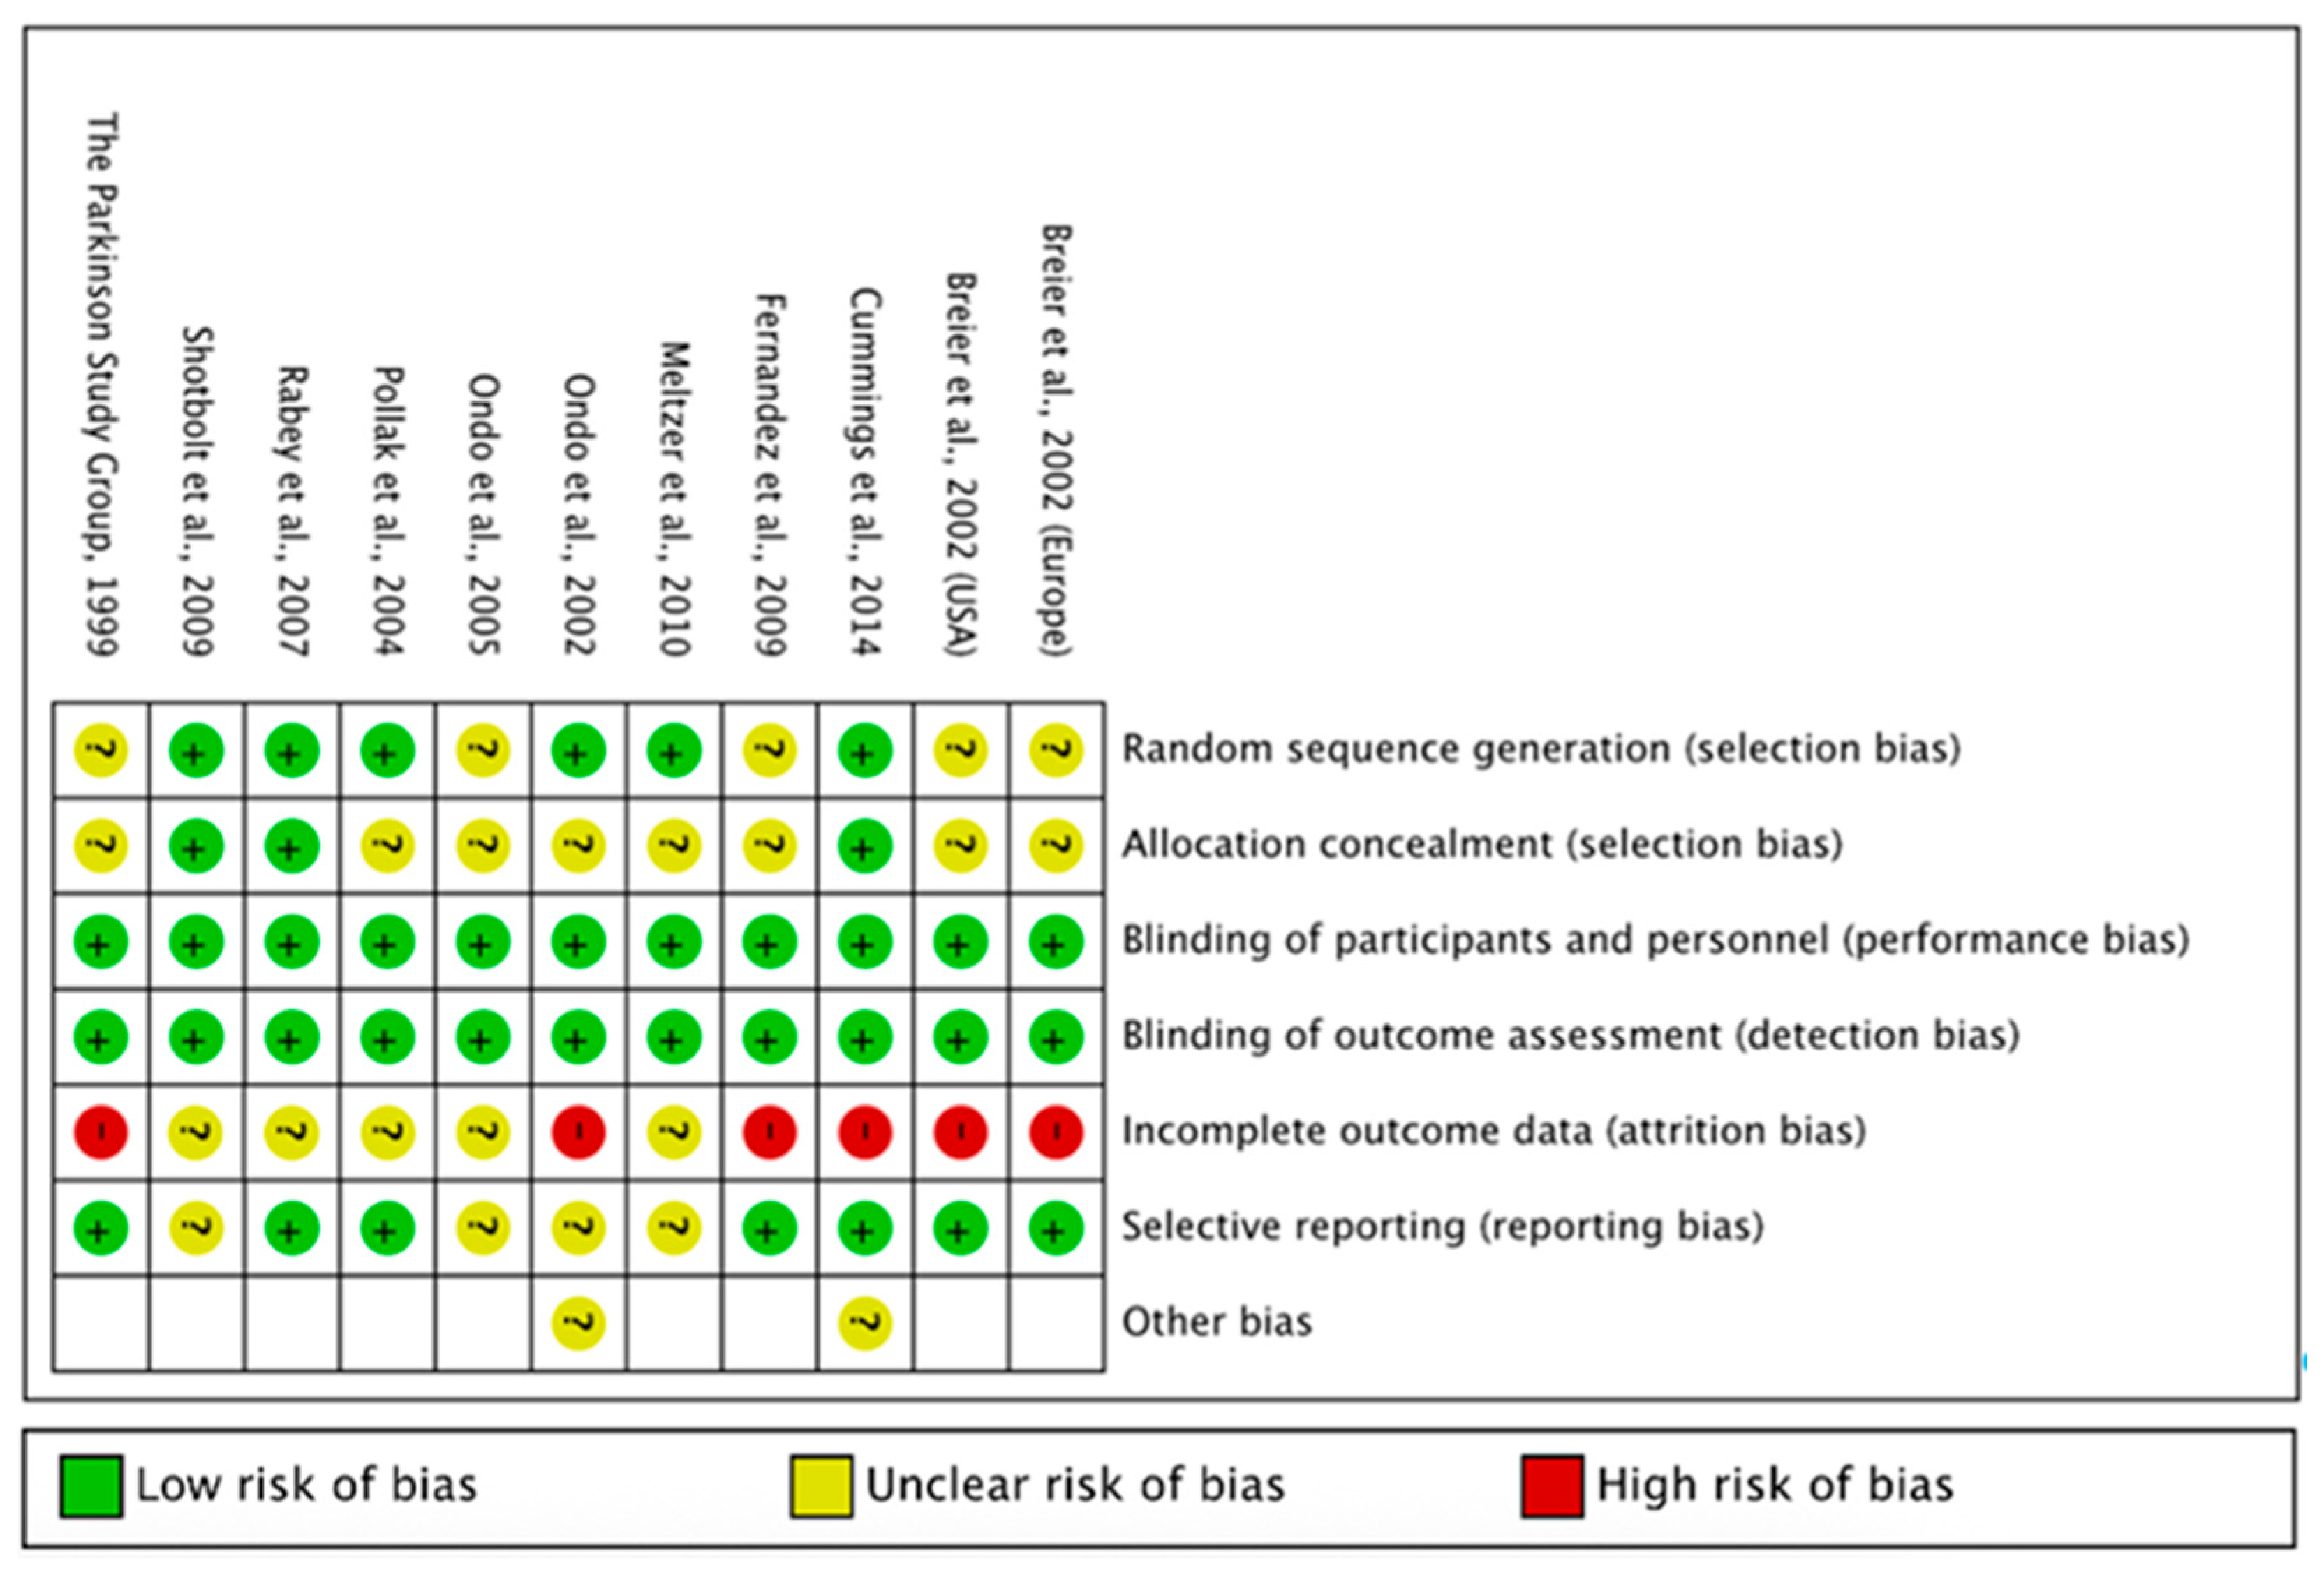
Table A1.
Effect sizes calculated for studies that provided adequate data.
References
- Giguère, N.; Nanni, S.B.; Trudeau, L.E. On cell loss and selective vulnerability of neuronal populations in Parkinson’s disease. Front. Neurol. 2018, 9, 455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dorsey, E.R.; Elbaz, A.; Nichols, E.; Abbasi, N.; Abd-Allah, F.; Abdelalim, A.; Adsuar, J.C.; Ansha, M.G.; Brayne, C.; Choi, J.-Y.J.; et al. Global, regional, and national burden of Parkinson’s disease, 1990–2016: A systematic analysis for the Global Burden of Disease Study 2016. Lancet Neurol. 2018, 17, 939–953. [Google Scholar] [CrossRef] [Scilit]
- GBD 2015 Neurological Disorders Collaborator Group. Global, regional, and national burden of neurological disorders during 1990–2015: A systematic analysis for the Global Burden of Disease Study 2015. Lancet Neurol. 2017, 16, 877–897. [Google Scholar] [CrossRef] [Scilit]
- Okunoye, O.; Marston, L.; Walters, K.; Schrag, A. Change in the incidence of Parkinson’s disease in a large UK primary care database. NPJ Park. Dis. 2022, 8, 23. [Google Scholar] [CrossRef] [Scilit]
- Postuma, R.B.; Berg, D. Advances in markers of prodromal Parkinson disease. Nat. Rev. Neurol. 2016, 12, 622–634. [Google Scholar] [CrossRef] [Scilit]
- Pellicano, C.; Dario, B.; Pisani, V.; Buttarelli, F.; Giovannelli, M.; Pontieri, F.E. Prodromal non-motor symptoms of Parkinson’s disease. Neuropsychiatr. Dis. Treat. 2007, 3, 145–151. [Google Scholar] [CrossRef] [Scilit]
- Poewe, W. Non-motor symptoms in Parkinson’s disease. Eur. J. Neurol. 2008, 15, 14–20. [Google Scholar] [CrossRef] [Scilit]
- Marsili, L.; Rizzo, G.; Colosimo, C. Diagnostic criteria for Parkinson’s disease: From James Parkinson to the concept of prodromal disease. Front. Neurol. 2018, 9, 156. [Google Scholar] [CrossRef] [Scilit]
- Tibar, H.; El Bayad, K.; Bouhouche, A.; Ben Haddou, E.H.A.; Benomar, A.; Yahyaoui, M.; Benazzouz, A.; Regragui, W. Non-motor symptoms of Parkinson’s Disease and their impact on quality of life in a cohort of Moroccan patients. Front. Neurol. 2018, 9, 170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rodriguez-Blazquez, C.; Schrag, A.; Rizos, A.; Chaudhuri, K.R.; Martinez-Martin, P.; Weintraub, D. Prevalence of Non-Motor Symptoms and Non-Motor Fluctuations in Parkinson’s Disease Using the MDS-NMS. Mov. Disord. Clin. Pract. 2020, 8, 231–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fénelon, G.; Mahieux, F.; Huon, R.; Ziégler, M. Hallucinations in Parkinson’s disease Prevalence, phenomenology and risk factors. Brain 2000, 123, 733–745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barnes, J.; David, A.S. Visual hallucinations in Parkinson’s disease: A review and phenomenological survey. J. Neurol. Neurosurg. Psychiatry 2001, 70, 727–733. [Google Scholar] [CrossRef] [Scilit]
- Williams, D.R.; Warren, J.D.; Lees, A.J. Using the presence of visual hallucinations to differentiate Parkinson’s disease from atypical parkinsonism. J. Neurol. Neurosurg. Psychiatry 2008, 79, 652–655. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riedel, O.; Klotsche, J.; Spottke, A.; Deuschl, G.; Förstl, H.; Henn, F.; Heuser, I.; Oertel, W.; Reichmann, H.; Riederer, P.; et al. Frequency of dementia, depression, and other neuropsychiatric symptoms in 1449 outpatients with Parkinson’s disease. J. Neurol. 2010, 257, 1073–1082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mack, J.; Rabins, P.; Anderson, K.; Goldstein, S.; Grill, S.; Hirsch, E.S.; Lehmann, S.; Little, J.T.; Margolis, R.L.; Palanci, J.; et al. Prevalence of psychotic symptoms in a community-based parkinson disease sample. Am. J. Geriatr. Psychiatry 2012, 20, 123–132. [Google Scholar] [CrossRef] [Scilit]
- Schrag, A.; Hovris, A.; Morley, D.; Quinn, N.; Jahanshahi, M. Caregiver-burden in parkinson’s disease is closely associated with psychiatric symptoms, falls, and disability. Park. Relat. Disord. 2006, 12, 35–41. [Google Scholar] [CrossRef] [Scilit]
- Factor, S.A.; Feustel, P.J.; Friedman, J.H.; Comella, C.L.; Goetz, C.G.; Kurlan, R.; Parsa, M.; Pfeiffer, R. The Parkinson Study Group. Longitudinal outcome of Parkinson’s disease patients with psychosis. Neurology 2003, 60, 1756–1761. [Google Scholar] [CrossRef] [Scilit]
- Aarsland, D.; Andersen, K.; Larsen, J.P.; Lolk, A.; Kragh-Sørensen, P. Prevalence and Characteristics of Dementia in Parkinson Disease An 8-Year Prospective Study. Arch. Neurol. 2003, 60, 387–392. [Google Scholar] [CrossRef] [Scilit]
- Aarsland, D.; Larsen, J.P.; Tandberg, E.; Laake, K. Predictors of nursing home placement in Parkinson’s disease: A population-based, prospective study. J. Am. Geriatr. Soc. 2000, 48, 938–942. [Google Scholar] [CrossRef] [Scilit]
- Okunoye, O.; Kojima, G.; Marston, L.; Walters, K.; Schrag, A. Factors associated with hospitalisation among people with Parkinson’s disease—A systematic review and meta-analysis. Park. Relat. Disord. 2020, 71, 66–72. [Google Scholar] [CrossRef] [Scilit]
- Stang, C.D.; Mullan, A.F.; Camerucci, E.; Hajeb, M.; Turcano, P.; Martin, P.; Mielke, M.M.; Josephs, K.A.; Splett, M.; Abler, V.; et al. Incidence, Prevalence, and Mortality of Psychosis Associated with Parkinson’s Disease (1991–2010). J. Park. Dis. 2022, 12, 1319–1327. [Google Scholar] [CrossRef] [Scilit]
- Friedman, J.H. The Management of the Levodopa Psychoses. Clin. Neuropharmacol. 1991, 14, 283–295. [Google Scholar] [CrossRef] [Scilit]
- Ecker, D.; Unrath, A.; Kassubek, J.; Sabolek, M. Dopamine Agonists and their risk to induce psychotic episodes in Parkinson’s disease: A case-control study. BMC Neurol. 2009, 9, 23. [Google Scholar] [CrossRef] [Scilit]
- Papapetropoulos, S.; Mash, D.C. Psychotic symptoms in Parkinson’s disease: From description to etiology. J. Neurol. 2005, 254, 753–764. [Google Scholar] [CrossRef] [Scilit]
- Beaulieu-Boire, I.; Lang, A.E. Behavioral effects of levodopa. Mov. Disord. 2015, 30, 90–102. [Google Scholar] [CrossRef] [Scilit]
- Fénelon, G.; Alves, G. Epidemiology of psychosis in Parkinson’s disease. J. Neurol. Sci. 2010, 289, 12–17. [Google Scholar] [CrossRef] [Scilit]
- Pagonabarraga, J.; Martinez-Horta, S.; de Bobadilla, R.F.; Pérez, J.; Ribosa-Nogué, R.; Marín, J.; Pascual-Sedano, B.; García, C.; Gironell, A.; Kulisevsky, J. Minor hallucinations occur in drug-naive Parkinson’s disease patients, even from the premotor phase. Mov. Disord. 2016, 31, 45–52. [Google Scholar] [CrossRef] [Scilit]
- NICE (National Institute for Health and Care Excellence). Parkinson’s Disease in Adults. NG71. 2017. Available online: https://www.nice.org.uk/guidance/ng71 (accessed on 23 August 2022).
- Orayj, K. Trends and contributing factors for prescribing antipsychotics in newly diagnosed parkinson’s disease patients: A population-based study. Risk Manag. Healthc. Policy 2021, 14, 2443–2452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marras, C.; Kopp, A.; Qiu, F.; Lang, A.E.; Sykora, K.; Shulman, K.I.; Rochon, P.A. Antipsychotic use in older adults with Parkinson’s disease. Mov. Disord. 2007, 22, 319–323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weintraub, D.; Chiang, C.; Kim, H.M.; Wilkinson, J.; Marras, C.; Stanislawski, B.; Mamikonyan, E.; Kales, H.C. Association of antipsychotic use with mortality risk in patients with Parkinson disease. JAMA Neurol. 2016, 73, 535–541. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weintraub, D.; Chen, P.; Ignacio, R.V.; Mamikonyan, E.; Kales, H.C. Patterns and trends in antipsychotic prescribing for Parkinson disease psychosis. Arch. Neurol. 2011, 68, 899–904. [Google Scholar] [CrossRef] [Scilit]
- Shotbolt, P.; Samuel, M.; David, A. Quetiapine in the treatment of psychosis in Parkinson’s disease. Ther. Adv. Neurol. Disord. 2010, 3, 339–350. [Google Scholar] [CrossRef] [Scilit]
- Jethwa, K.D.; Onalaja, O.A. Antipsychotics for the management of psychosis in Parkinson’s disease: Systematic review and meta-analysis. BJPsych Open 2015, 1, 27–33. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, H.; Wang, L.; Fan, Y.; Yang, L.; Wen, X.; Liu, Y.; Liu, Z. Atypical antipsychotics for Parkinson’s disease psychosis: A systematic review and meta-analysis. Neuropsychiatr. Dis. Treat. 2019, 15, 2137–2149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iketani, R.; Furushima, D.; Imai, S.; Yamada, H. Efficacy and safety of atypical antipsychotics for psychosis in Parkinson’s disease: A systematic review and Bayesian network meta-analysis. Park. Relat. Disord. 2020, 78, 82–90. [Google Scholar] [CrossRef] [Scilit]
- Srisurapanont, M.; Suradom, C.; Suttajit, S.; Kongsaengdao, S.; Maneeton, B. Second-generation antipsychotics for Parkinson’s disease psychosis: A systematic review and network meta-analysis. Gen. Hosp. Psychiatry 2024, 87, 124–133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iketani, R.; Kawasaki, Y.; Yamada, H. Comparative Utility of Atypical Antipsychotics for the Treatment of Psychosis in Parkinson’s Disease: A Systematic Review and Bayesian Network Meta-analysis. Biol. Pharm. Bull. 2017, 40, 1976–1982. [Google Scholar] [CrossRef] [Scilit]
- Yunusa, I.; Rashid, N.; Seyedin, R.; Paratane, D.; Rajagopalan, K. Comparative Efficacy, Safety, and Acceptability of Pimavanserin and Other Atypical Antipsychotics for Parkinson’s Disease Psychosis: Systematic Review and Network Meta-Analysis. J. Geriatr. Psychiatry Neurol. 2023, 36, 417–432. [Google Scholar] [CrossRef] [Scilit]
- Mansuri, Z.; Reddy, A.; Vadukapuram, R.; Trivedi, C.; Amara, A. Pimavanserin in the Treatment of Parkinson’s Disease Psychosis: Meta-analysis and Meta-regression of Randomized Clinical Trials. Innov. Clin. Neurosci. 2022, 19, 46–51. [Google Scholar]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Hálfdánarson, Ó.; Zoëga, H.; Aagaard, L.; Bernardo, M.; Brandt, L.; Fusté, A.C.; Furu, K.; Garuoliené, K.; Hoffmann, F.; Huybrechts, K.F.; et al. International trends in antipsychotic use: A study in 16 countries, 2005–2014. Eur. Neuropsychopharmacol. 2017, 27, 1064–1076. [Google Scholar] [CrossRef] [Scilit]
- Wishart, D.S.; Feunang, Y.D.; Guo, A.C.; Lo, E.J.; Marcu, A.; Grant, J.R.; Sajed, T.; Johnson, D.; Li, C.; Sayeeda, Z.; et al. DrugBank 5.0: A major update to the DrugBank database for 2018. Nucleic Acids Res. 2018, 46, D1074–D1082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- WHO (World Health Organisation). ATC/DDD Index; N05A Antipsychotics. Available online: https://www.whocc.no/atc_ddd_index/?code=N05A (accessed on 26 May 2022).
- Shotbolt, P.; Samuel, M.; Fox, C.; David, A.S. A randomized controlled trial of quetiapine for psychosis in Parkinson’s disease. Neuropsychiatr. Dis. Treat. 2009, 5, 327–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rabey, J.M.; Prokhorov, T.; Miniovitz, A.; Dobronevsky, E.; Klein, C. Effect of quetiapine in psychotic Parkinson’s disease patients: A double-blind labeled study of 3 months’ duration. Mov. Disord. 2007, 22, 313–318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ondo, W.G.; Tintner, R.; Voung, K.D.; Lai, D.; Ringholz, G. Double-blind, placebo-controlled, unforced titration parallel trial of quetiapine for dopaminergic-induced hallucinations in Parkinson’s disease. Mov. Disord. 2005, 20, 958–963. [Google Scholar] [CrossRef] [Scilit]
- Fernandez, H.H.; Okun, M.S.; Rodriguez, R.L.; Malaty, I.A.; Romrell, J.; Sun, A.; Wu, S.S.; Pillarisetty, S.; Nyathappa, A.; Eisenschenk, S. Quetiapine improves visual hallucinations in parkinson disease but not through normalization of sleep architecture: Results from a double-blind clinical-polysomnography study. Int. J. Neurosci. 2009, 119, 2196–2205. [Google Scholar] [CrossRef] [Scilit]
- Ondo, W.G.; Levy, J.K.; Vuong, K.D.; Hunter, C.; Jankovic, J. Olanzapine treatment for dopaminergic-induced hallucinations. Mov. Disord. 2002, 17, 1031–1035. [Google Scholar] [CrossRef] [Scilit]
- Breier, A.; Sutton, V.K.; Feldman, P.D.; Kadam, D.L.; Ferchland, I.; Wright, P.; Friedman, J.H. Olanzapine in the Treatment of Dopamimetic-Induced Psychosis in Patients with Parkinson’s Disease. Biol. Psychiatry 2002, 52, 438–445. [Google Scholar] [CrossRef] [Scilit]
- Parkinson Study Group. Low-Dose Clozapine for the Treatment of Drug-Induced Psychosis in Parkinson’s Disease. N. Engl. J. Med. 1999, 340, 757–763. [Google Scholar] [CrossRef] [Scilit]
- Pollak, P.; Tison, F.; Rascol, O.; Destée, A.; Péré, J.J.; Senard, J.M.; Durif, F.; Bourdeix, I. Clozapine in drug induced psychosis in Parkinson’s disease: A randomised, placebo controlled study with open follow up. J. Neurol. Neurosurg. Psychiatry 2004, 75, 689–695. [Google Scholar] [CrossRef] [Scilit]
- Cummings, J.; Isaacson, S.; Mills, R.; Williams, H.; Chi-Burris, K.; Corbett, A.; Dhall, R.; Ballard, C. Pimavanserin for patients with Parkinson’s disease psychosis: A randomised, placebo-controlled phase 3 trial. Lancet 2014, 383, 533–540. [Google Scholar] [CrossRef] [Scilit]
- Meltzer, H.Y.; Mills, R.; Revell, S.; Williams, H.; Johnson, A.; Bahr, D.; Friedman, J.H. Pimavanserin, a serotonin 2A receptor inverse agonist, for the treatment of Parkinson’s disease psychosis. Neuropsychopharmacology 2010, 35, 881–892. [Google Scholar] [CrossRef] [Scilit]
- The Cochrane Collaboration. Review Manager (RevMan), version 5.4; The Cochrane Collaboration: Copenhagen, Denmark, 2020.
- Higgins, J.P.T.; Churchill, R.; Chandler, J.; Cumpston, M.S. Chapter 8: Assessing risk of bias in included studies. In Cochrane Handbook for Systematic Reviews of Interventions; Version 5.2.0; Higgins, J.P.T., Altman, D.G., Sterne, J.A.C., Eds.; Cochrane: London, UK, 2017; Chapter 8. [Google Scholar]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan—A web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit]
- Kurlan, R.; Cummings, J.; Raman, R.; Thal, L. Quetiapine for agitation or psychosis in patients with dementia and parkinsonism. Neurology 2007, 68, 1356–1363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolters, E.C.; Hurwitz, T.A.; Mak, E.; Teal, P.; Peppard, F.R.; Remick, R.; Calne, S.; Calne, D.B. Clozapine in the treatment of parkinsonian patients with dopaminomimetic psychosis. Neurology 1990, 40, 832–834. [Google Scholar] [CrossRef] [Scilit]
- Folstein, M.F.; Folstein, S.E.; Mchugh, P.R. “Mini-mental state”: A practical method for grading the cognitive state of patients for the clinician. J. Psychiatr. Res. 1975, 12, 189–198. [Google Scholar] [CrossRef] [Scilit]
- Voss, T.; Bahr, D.; Cummings, J.; Mills, R.; Ravina, B.; Williams, H. Performance of a shortened Scale for Assessment of Positive Symptoms for Parkinson’s disease psychosis. Park. Relat. Disord. 2013, 19, 295–299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raedler, T.J.; Knable, M.B.; Lafargue, T.; Urbina, R.A.; Egan, M.F.; Pickar, D.; Weinberger, D.R. In vivo determination of striatal dopamine D2 receptor occupancy in patients treated with olanzapine. Psychiatry Res. Neuroimaging 1999, 90, 81–90. [Google Scholar] [CrossRef] [Scilit]
- Lippi, M.; Fanelli, G.; Fabbri, C.; De Ronchi, D.; Serretti, A. The dilemma of polypharmacy in psychosis: Is it worth combining partial and full dopamine modulation? Int. Clin. Psychopharmacol. 2022, 37, 263–275. [Google Scholar] [CrossRef] [Scilit]
- Hacksell, U.; Burstein, E.S.; McFarland, K.; Mills, R.G.; Williams, H. On the Discovery and Development of Pimavanserin: A Novel Drug Candidate for Parkinson’s Psychosis. Neurochem. Res. 2014, 39, 2008–2017. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ravina, B.; Marder, K.; Fernandez, H.H.; Friedman, J.H.; McDonald, W.; Murphy, D.; Aarsland, D.; Babcock, D.; Cummings, J.; Endicott, J.; et al. Diagnostic criteria for psychosis in Parkinson’s disease: Report of an NINDS, NIMH Work Group. Mov. Disord. 2007, 22, 1061–1068. [Google Scholar] [CrossRef] [Scilit]
- Myles, N.; Myles, H.; Xia, S.; Large, M.; Kisely, S.; Galletly, C.; Bird, R.; Siskind, D. Meta-analysis examining the epidemiology of clozapine-associated neutropenia. Acta Psychiatr. Scand. 2018, 138, 101–109. [Google Scholar] [CrossRef] [Scilit]
- Northwood, K.; Myles, N.; Clark, S.R.; Every-Palmer, S.; Myles, H.; Kisely, S.; Warren, N.; Siskind, D. Evaluating the epidemiology of clozapine-associated neutropenia among people on clozapine across Australia and Aotearoa New Zealand: A retrospective cohort study. Lancet Psychiatry 2024, 11, 27–35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Atkin, K.; Kendall, F.; Gould, D.; Freeman, H.; Lieberman, J.; O’Sullivan, D.; Liberman, J. Neutropenia and agranulocytosis in patients receiving clozapine in the UK and Ireland. Br. J. Psychiatry 1996, 169, 483–488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mena, C.I.; Nachar, R.A.; Crossley, N.A.; Gonzalez-Valderrama, A.A. Clozapine-associated neutropenia in Latin America: Incidence report of 5380 Chilean users. Int. Clin. Psychopharmacol. 2019, 34, 257–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.