


Abstract
Burnout can affect nurses’ sleep quality. The aim of this study was to analyze the relationship between burnout syndrome and sleep problems in nurses. A systematic review with meta-analysis was performed. PubMed, CINAHL and Scopus databases were used. Some of the inclusion criteria were quantitative studies, in which the levels of burnout and sleep disorders were investigated in a sample of nurses using validated scales. A total of 12 studies were included. Sociodemographic variables did not influence the relation between burnout and sleep problems, except for being female. The environment and workplace violence, together with psychological traits and shifts, affect the probability of developing burnout and insomnia. The meta-analysis sample was n = 1127 nurses. The effect size of the correlation between burnout and sleep disorders was r = 0.39 (95% CI 0.29–0.48) with p < 0.001, indicating that the higher the level of burnout in nurses, the greater the presence of sleep disorders. The positive correlation between burnout and sleep disorders is a problem that must be addressed to improve the health of nurses. Developing turnicity strategies, using warmer lights in hospital units during night shifts and eliminating the fixed night shift could improve nurses’ working conditions.
1. Introduction
Burnout syndrome has been studied throughout history by many researchers. Authors have defined burnout as a psychological phenomenon [1] or as a clinical pathology [2]. However, the most used conceptualization describes burnout as an emotional response to chronic work stress with three dimensions [3]. Burnout is characterized by the appearance of emotional exhaustion (EE), understood as a progressive loss of energy; depersonalization (D), expressed as hostility towards the work environment; and feelings of low professional accomplishment (PA) or loss of self-confidence and demotivation [3,4,5].
This syndrome has a high prevalence among professionals who base their daily work on interpersonal relationships, either with coworkers or with clients [6,7]. Health sector employees are among the most affected by this problem, with nursing professionals being one of the most vulnerable populations to chronic work stress due to the high degree of relationship between nurses and patients and the strong emotional involvement that this requires [8]. Nurses also usually suffer from work overload [9] and difficulties reconciling work and family life [10].
These personal conflicts in the work environment lead to the appearance of occupational stress and burnout [11]. On the other hand, the consequences that arise from nurse burnout are numerous, such as absenteeism; lack of motivation; impaired work performance and communication between colleagues [12]; concentration difficulty; poor organization; increased errors; decreased patient safety; lack of energy; and feelings of frustration, anxiety, depression and insomnia [8]. These symptoms are often underestimated by professionals, who self-medicate instead of asking for help in medical or psychological consultation [13]. Furthermore, it has a strong impact on the quality of care [6].
Burnout can influence nurses’ sleep quality, and it has been identified as a cause of insomnia [8]. It is important to analyze the relation between burnout and sleep problems in nurses. Furthermore, the work of nurses has some characteristics that can increase sleep problems and generate an increased release of adrenaline [14]. Nurses work rotating shifts and extended hours, which can change the circadian rhythm, occasionally leading to abuse of caffeine and benzodiazepines, [13,15], resulting in nurses needing to use their days off and free time to recover lost sleep hours [16]. All these factors can lead to an increase in sleep onset and maintenance insomnia, along with alterations in sleep architecture and a decrease in the quality and quantity of sleep hours [17].
This scenario leads to insufficient sleep quality, which plays an essential role in emotional regulation and mental wellbeing [18], creating a cyclical problem underlying nursing work [19]. Burnout syndrome, among other problems, leads to the appearance of insomnia, which is caused by the presence of chronic stress [20].
Sleep plays a fundamental role in learning, memory consolidation and motor learning, as well as in the immune system and cardiovascular and liver metabolism [21]. Insufficient sleep or circadian alteration can trigger a decrease in cognitive function and mental performance [22], psychiatric morbidity [23], physical fatigue, decreased levels of attention and concentration, increased risk of accidents, slow complex coordination and a weakening of the cardiovascular autonomic response system [24]. Female nurses are also at higher risk of metabolic disorders and disrupted circadian rhythms, which can lead to diseases such as diabetes mellitus, obesity and important cardiovascular diseases, such as coronary artery disease or hypertension [25].
Due to the negative repercussions of burnout and sleep disorders in nurses (decreasing quality of care and patient satisfaction, as well as increasing mistakes in healthcare, among others) and in order to avoid such problems, it is important to analyze the relationship between these phenomena to establish possible interventions to improve both parameters and achieve better health for nurses. To the best of our knowledge, there is no similar study reviewing the literature about burnout and sleep problems in nurses or other healthcare professionals. Thus, the aim of the present study was to analyze the relationship between burnout syndrome and sleep problems in nurses. A meta-analysis was performed to clarify the direction and the real effect size of the correlation between these variables with a larger sample of nurses with a higher level of evidence.
2. Materials and Methods
A systematic review of the literature was performed following PRISMA recommendations (preferred reporting items for systematic reviews and meta-analyses) [26,27].
2.1. Search Strategy
CINAHL, PubMed and Scopus databases were consulted. The search equation, based on MeSH terms, was: “burnout AND nurs* AND sleep disorders”. The search was performed in September 2021. There were no restrictions on the date of publication.
2.2. Inclusion and Exclusion Criteria
The inclusion criteria were the following: quantitative studies investigating the levels of burnout and sleep disorders in a sample of nurses and studies using validated scales written in English or Spanish. The exclusion criteria were studies employing a mixed sample of professionals that did not provide independent data for nurses.
2.3. Study Selection Process
Two members of the team [details omitted for double-anonymized peer review] performed the search and study selection independently. In case of disagreement, a third researcher [details omitted for double-anonymized peer review] was consulted. For the selection, a reading of the title and abstract was executed first, followed by a full-text reading and, finally, a reverse search within the references of the included studies.
2.4. Data Extraction and Synthesis
A data collection table was prepared in Microsoft Word. The variables collected from the studies were: (a) authors; (b) year and country of publication; (c) characteristics of the sample, such as number of subjects included, age and sex; (d) study design; (e) aim of the study; (f) scores on the burnout and sleep scales; (g) relation between burnout and sleep disorders; and (h) level of evidence and degree of recommendation.
2.5. Critical Reading and Level of Evidence
A critical reading of the included studies was conducted using the STROBE checklist for observational studies [28] and the TREND checklist for quasi-experimental studies [29]. The levels of evidence and grade of recommendation proposed by the Levels of Evidence Working Group of the Oxford Centre for Evidence-Based Medicine (OCEBM) [30] were used.
2.6. Data Analysis
A descriptive analysis of the information from the included studies was performed for the systematic review. StatsDirect software was used for the meta-analysis. A random-effect meta-analysis based on the correlation (r) effect size between burnout and sleep disorders was performed. For calculation of the correlation effect size, the sample size and the correlation between burnout and sleep were used. The correlation meta-analysis package in StatsDirect was used. A sensitivity analysis was performed, and publication bias was assessed with Egger’s linear regression. The I2 index was used as a measure of heterogeneity. Information related to the research materials can be accessed through the meta-analysis research data file.
3. Results
3.1. Search Results
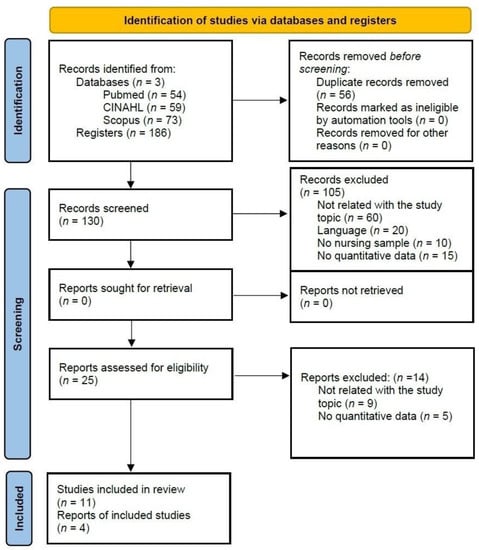
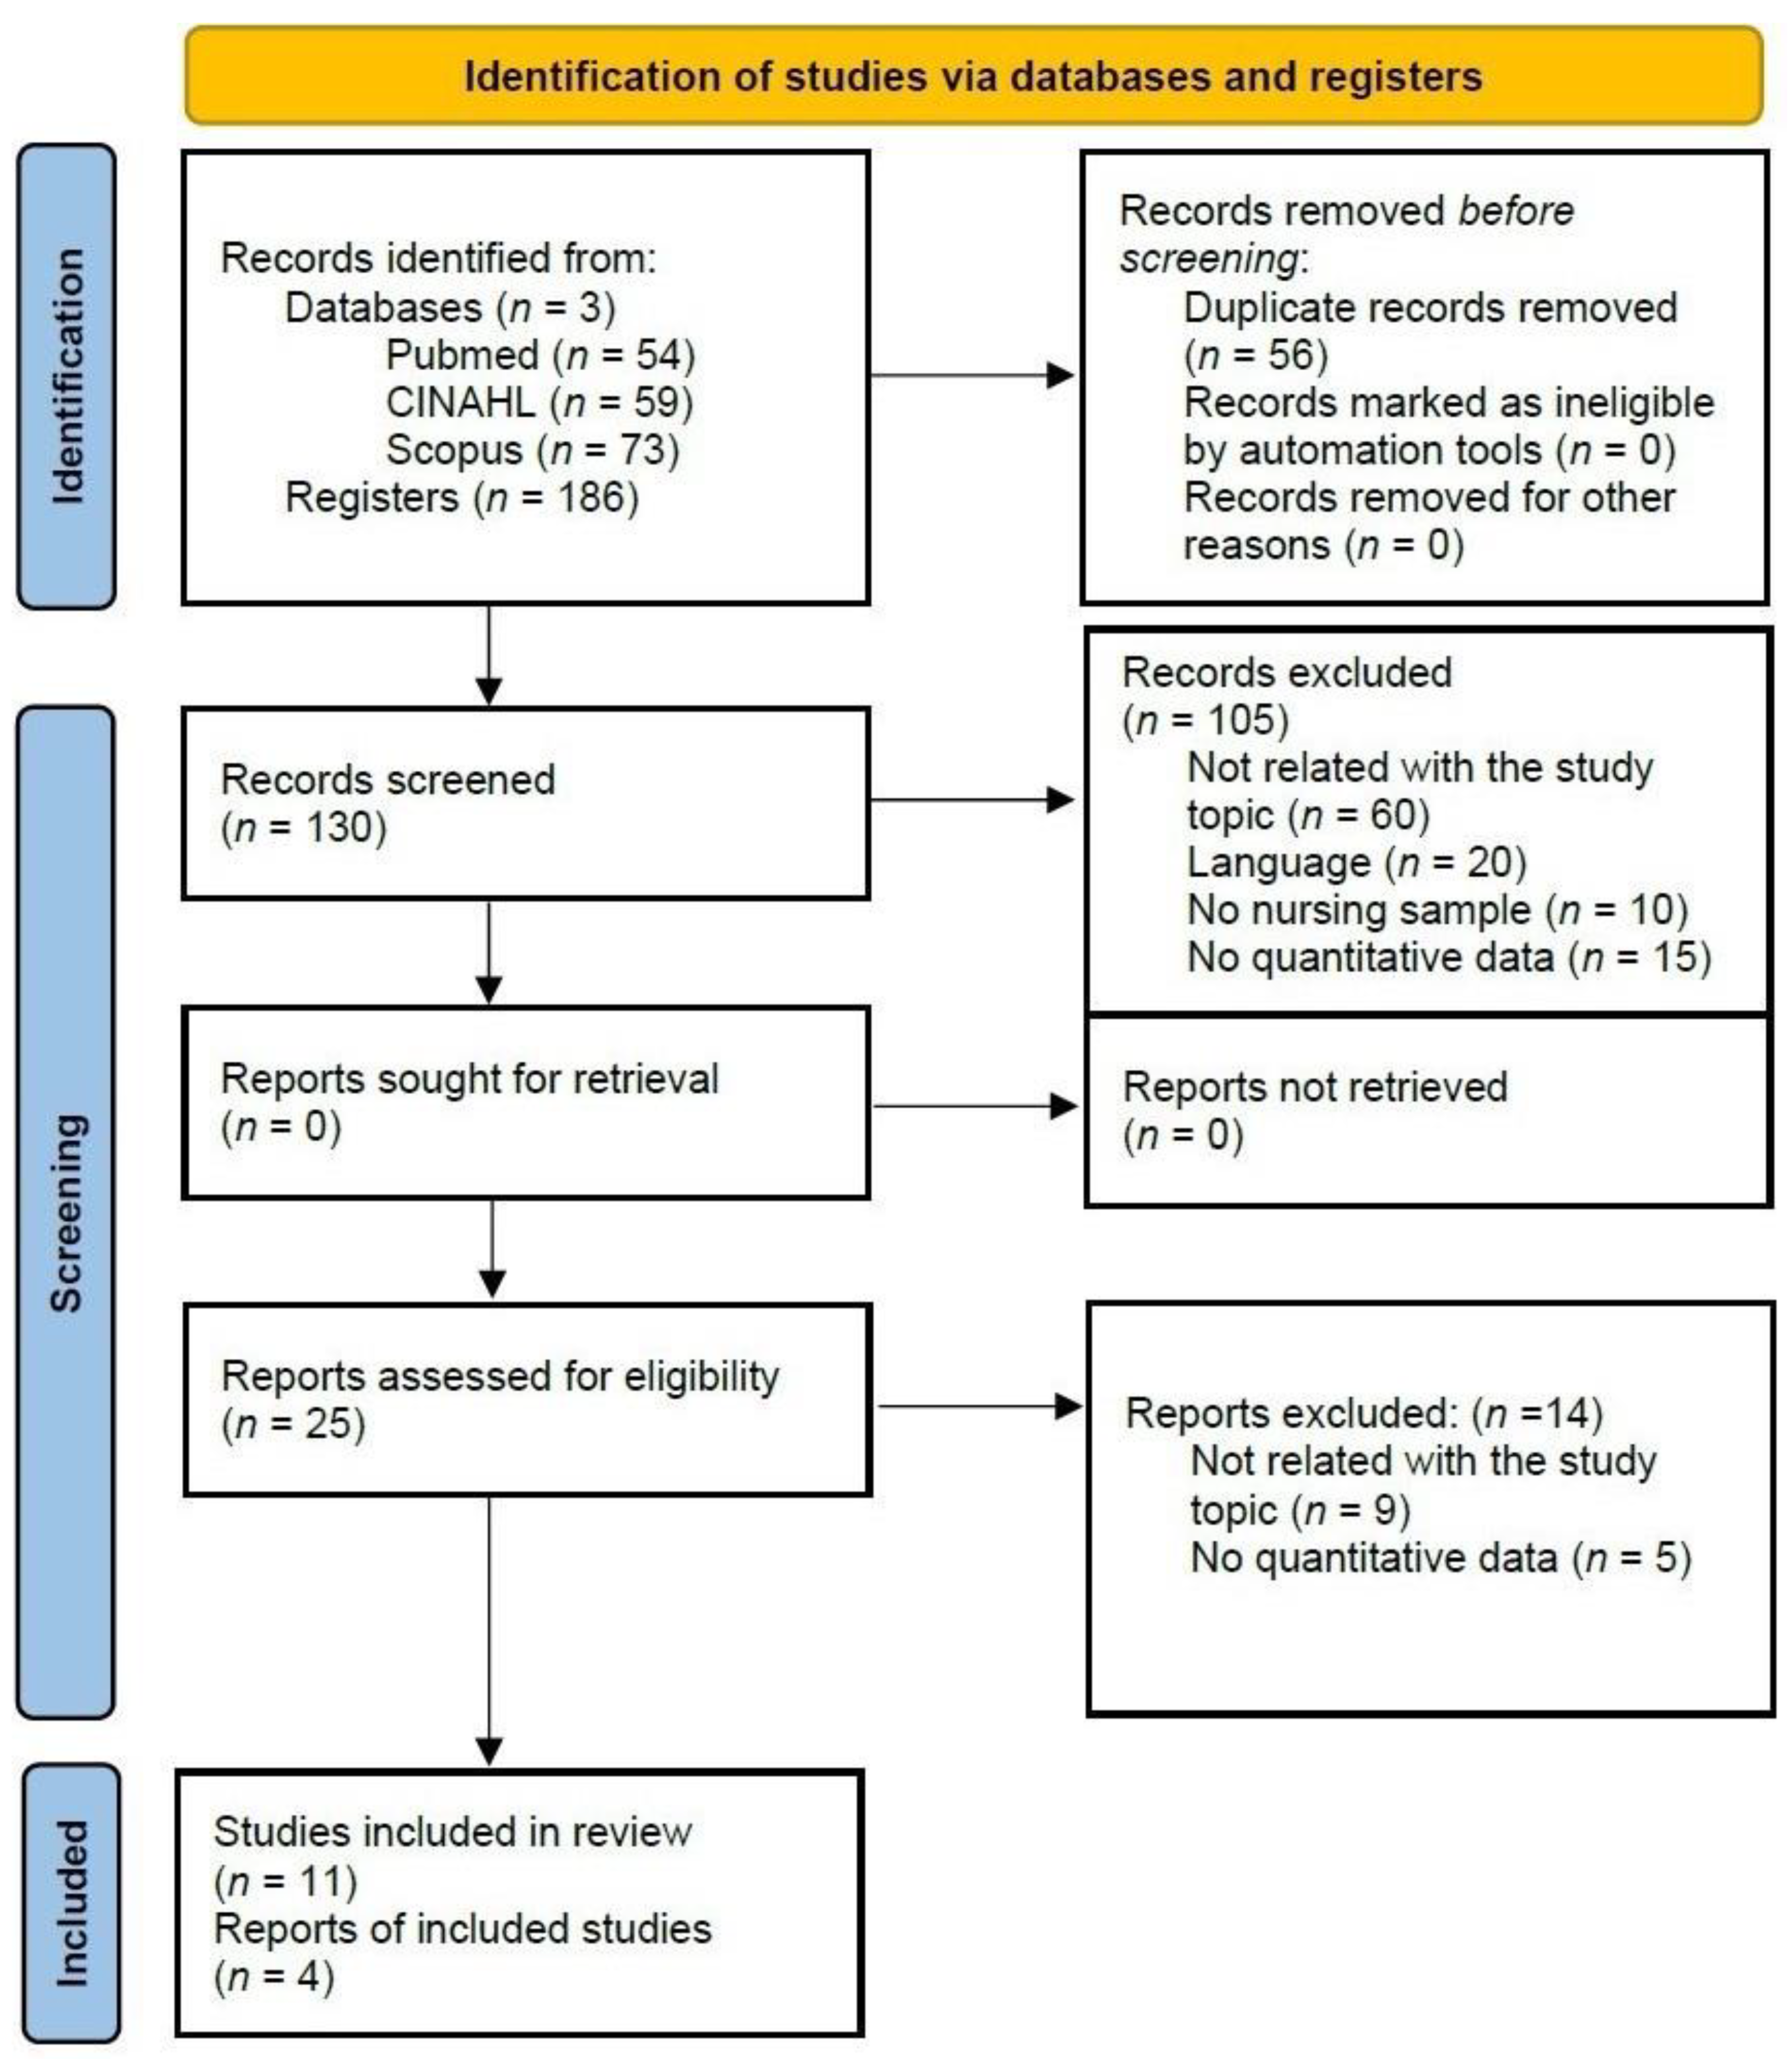
A total of 186 articles were identified in the databases. After eliminating duplicates, 130 studies remained. Once the inclusion criteria were applied, n = 12 articles were selected for the systematic review, and 4 studies included the necessary information for meta-analysis. The search and selection process are shown in Figure 1.
Figure 1.
Flow diagram of search process.
3.2. Study and Participant Characteristics
The total combined sample of all included studies was 26,509 subjects. Of the 12 included studies, two were quasi-experimental [31,32], and the rest were descriptive and cross-sectional studies [33,34,35,36,37,38,39,40,41,42]. Of the included studies, 70% were published between 2015 and 2020 [32,33,34,35,37,39,40,41]. Regarding the geographic location of the included studies, four were conducted in Europe [31,34,36,39], four in Asia [32,37,38,41], two in North America [35,40] and two in Muslim countries [33,42]. The average age of the nurses who participated in the selected studies was between 29 and 55 years old, and all the samples had a higher percentage of women (more than 60% in most cases). The most used scale to measure burnout was the MBI (n = 8) [32,33,35,36,38,39,40,42], and the most used scale to measure sleep disorders was the Pittsburgh Sleep Quality Index (n = 6) [32,34,36,37,39,42]; two studies additionally used the Epworth Scale [32,39]. The characteristics of the studies are summarized in Table 1.
Table 1.
Main results included in the review.
3.3. Burnout Syndrome and Sleep Problems in Nurses
A proportion of 15% of the nurses who participated in the analyzed studies had high levels of burnout [33], which is similar to data reported in other studies [39,41]. Some studies [34,42] found a positive and significant correlation between nurses who suffered from high levels of burnout and those who presented daytime sleepiness, together with low subjective quality of sleep [34]. Additionally, these sleep problems were predominantly correlated with the EE dimension [34,42]. It was found that 9.2% of the nurses were classified within the “withdrawing/burned out” profile [40]. This group, as well as the “frustrated/burning up” profile, presented significantly higher probabilities of suffering from sleep disorders.
3.4. Sociodemographic Variables and Probability of Suffering from Burnout and Sleep Disorders
Most of the sociodemographic variables studied did not affect sleep quality [42]. On the other hand, it was found in other studies that men presented lower levels than women, in terms of suffering from burnout and work problems [33]. Being female and suffering from burnout were significantly associated with deterioration of sleep quality [34].
3.5. Sleep Problems, Burnout Syndrome and the Organization of Nursing Work
Regarding the cycles of discontinuous work shifts or poorly organized overtime, an association was found with the risk of suffering from higher levels of burnout [33]. On the other hand, other types of nursing shift schedules were studied in [36]. The authors showed that when comparing 12-h and 8-h shift workers, those with the longer shift had worse health, wellbeing and sleep quality, as well as a higher level of burnout.
3.6. Other Risk Factors: Work Environment, Workplace Violence and Psychological Factors
Numerous studies found abundant predictive factors for suffering from burnout, which were positively correlated with the health environment [41] exposure to workplace violence, self-efficacy, sleep disorders and mild transient ailments, such as headaches, low back pain, odynophagia, etc. [38]. The risk factors found in nurses’ work environment were habitually witnessing the death of patients, especially in the emergency department [41], the multiple psychological demands of the patients and the lack of support from coworkers [33].
Nurses who had experienced an incident in their work environment in the last month (p < 0.001) or suffered a biological accident, such as a puncture (p = 0.010), presented worse sleep quality [42]. Likewise, other authors found that suffering from burnout was a strong mediator of the association between sleep disorders and violence in the workplace.
Therefore, nurses who worked in healthier work environments had higher levels of burnout and sleep disorders when they witnessed a violent incident at work [35]. On the other hand, psychological factors, such as self-criticism, personality traits with a strong temperament, fear of making mistakes [41] and compassion fatigue, were defined as mediators of the cyclical relationship between suffering from burnout and insomnia [37].
3.7. Psychological Interventions to Improve Sleep and Burnout
Regarding the experimental studies, a rehabilitation program based on psychoeducation for stress management strongly improved physiology, together with the quality of sleep, and allowed for a reduction in burnout, in addition to a consequent decrease in physical daytime fatigue [31]. On the other hand, a personal self-care program based on changing night-time habits and stress management improved the global score on the PSQI scale [32], in particular the subjective sleep quality item, as well as a significant reduction in latency and sleep disorders. However, this intervention only achieved significant results for sleep problems and not for symptoms of depression, burnout or the quality of life perceived by nurses [32].
3.8. Meta-Analysis of the Relationship between Burnout and Sleep Problems
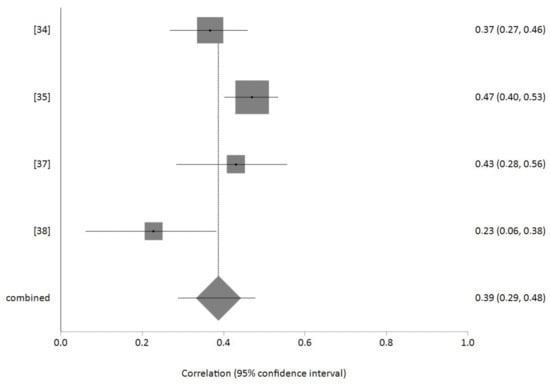
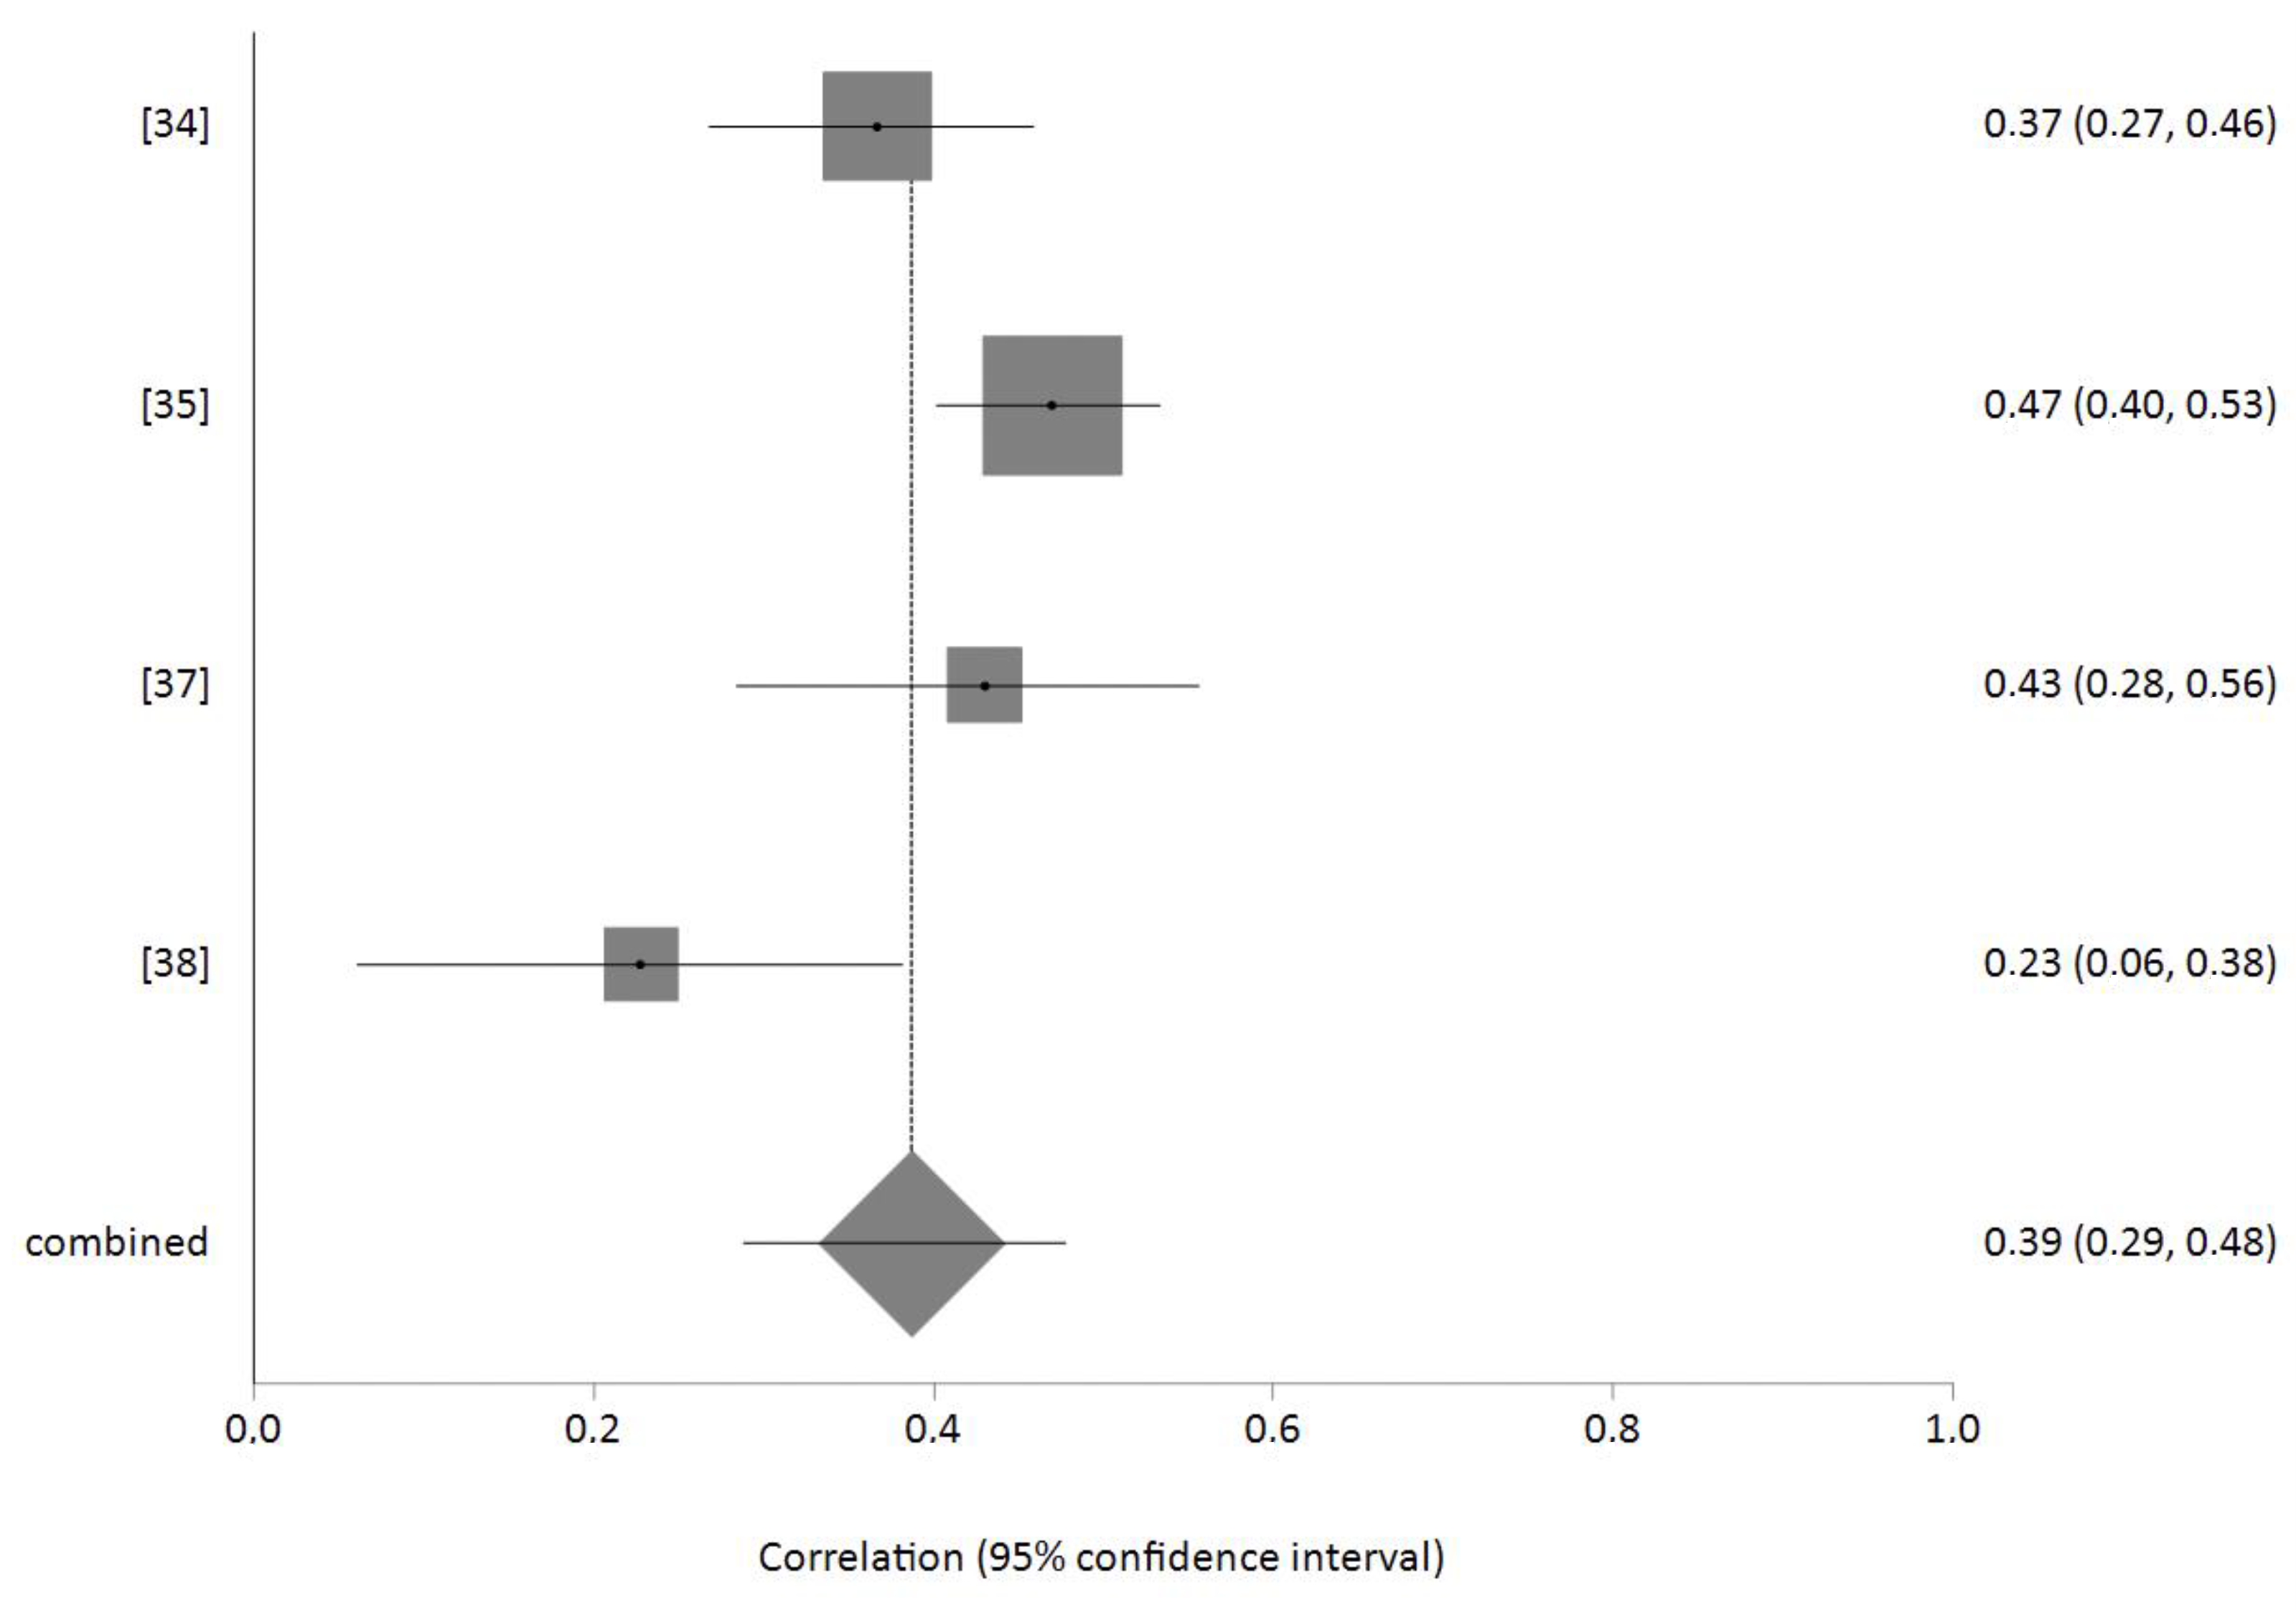
Of the studies included in the systematic review, four included the necessary data for a meta-analysis of the effect size of the correlation between burnout and sleep problems. The total meta-analysis sample was n = 1127 nurses. The effect size was r = 0.39 (95% CI 0.29–0.48) with p < 0.001, indicating that the higher the level of burnout among nurses, the greater the presence of sleep problems. Egger’s test showed no publication bias, and the value of heterogeneity was I2 = 67.8%. A forest plot is shown in Figure 2.
Figure 2.
Forest plot of the relation between burnout and sleep problems.
4. Discussion
The aim of the study was to analyze the relation between burnout and sleep problems in nurses. With this study, we found a positive correlation between burnout and sleep problems, as well as some variables that may mediate this relation. Several studies included in the review established a positive correlation between nurses suffering from high levels of burnout, especially in terms of EE and low PA, with suffering from daytime sleepiness and low subjective sleep quality [34,39,40,42]. On the other hand, we identified an association between the different patterns of the circadian rhythm and the possibility of developing burnout based on stress tolerance and adaptation to the different shifts of each worker [33].
In the scientific literature, we find similar results, which explain the cause of this association. A chronic depletion of energy reserves, influenced by a constant activation of the hypothalamic–pituitary–adrenal axis and increasing levels of body stress, can generate burnout after a while, in addition to difficulty falling asleep and maintaining sleep [20]. Regarding the low personal accomplishment (PA) presented by nurses, there are multiple risk factors, both from the work environment and from the worker themself, with lack of training being one of the most influential factors [43], along with lack of support of the work team [44]. However, it has been shown that a good organization of resources in the work environment leads to greater job satisfaction, which acts as a protective factor against developing EE and increases workers’ PA [45,46].
Regarding the studies that analyzed the mediation of sociodemographic variables in the relationship between burnout and sleep disturbances [33,34,42], we found that the female sex is the main variable related to the probability of suffering from sleep disorders and burnout [34,42]. There are discrepancies in the scientific literature regarding this result. On the one hand, some authors have shown that women have greater difficulties in combining working hours in health centers, especially night shifts, with family life and motherhood, which contributes to greater stress in women, consequently affecting their quality of sleep, which was previously affected by raising children [47,48]. On the other hand, some authors state that male health professionals have a higher risk of developing burnout compared to women [49]. These data can be justified by the higher probability of men facing more responsibilities and conflicts on a daily basis at work [50,51].
Nursing professionals are subject to a specific work organization based on teamwork and distributed in shifts so that care for patients is covered 24 h a day, 7 days a week. This implies a cyclical, continuous or discontinuous rhythm of shifts with specific schedules [52]. In addition to the 8-, 10- and 12-h shifts, there is the possibility of performing extended shifts or additional physical hours due to service needs, increasing the daily work shift to a total of 24 h, with subsequent rest [53]. Different studies reflect the association between shifts of 12 h or more [36] and discontinuous or poorly organized work shifts with the presence of burnout [33], daytime sleepiness and sleep pattern disturbances [39]. The fixed night shift affects these variables the most, followed by the rotating shift [39]. Nurses who have rotating and night shifts sleep fewer hours per week than other fixed-shift workers who work during the day [19,54]. In addition, nurses who work night shifts and rotating shifts can suffer other health problems, such as varicose veins in the lower limbs, appetite disorder, alteration of leisure time [54] and stress, triggering greater professional burnout [55]. On the other hand, shifts longer than 8 h and with work overload strongly influence the probability of suffering high levels of EE, depersonalization and neuroticism [53].
In addition to developing sleep disorders [24,56] and daytime sleepiness, in many cases, days off could be considered insufficient to recover from such a high exposure to work stressors during extended shifts [36]. In many cases, it is impossible to change the work team’s organization; thus, it is necessary for these professionals to adopt measures to reduce variations in the sleep-watch rhythm [19], using a system of daily naps and adjusting their personal and family rhythms to their varying work schedules and days of payment [57]. Likewise, if the possibility exists, nurses can structure night shifts in a way that allows patients to be given quality care, including micro-naps lasting more than one hour, with the aim of presenting a greater recovery after the work shift [58].
The predictive factors of burnout and some sleep disturbances are closely related to the type of work performed by nurses in terms of the work environment, suffering workplace violence or the psychological factors of each worker. Thus, factors associated with the work environment, whether due to working with dying patients, psychological demands, lack of support from colleagues or having experienced a biological accident, are classified as potentially stressful events for workers and have somatic repercussions [33,39,41,42]; these data are corroborated in the scientific literature. The impact of the physical environment, workload and ambiguity of nursing care, were shown to be the main risk factors for severe stress, which, in turn, is associated with sleep disorders and digestive problems [59]. Other authors found caring for dying patients and seriously injured children to be the most stressful events, with somatic repercussions for nurses [60].
Regarding workplace violence, nurses who work in healthier work environments present higher levels of burnout and sleep disorders when they witness violent incidents at work compared to nurses who work in more hostile environments [35,38], which can be explained according to the theory that nurses who work in more violent environments are used to suffering stressful incidents throughout their working hours and face such incidents without suffering repercussions in sleep patterns or additional stress [61].
Regarding the psychological factors that enhance the cyclical relationship between suffering from burnout and insomnia [37,41], we found other studies with similar results. In other research, sleep quality and daytime sleepiness were identified as the variables most related to anxiety/insomnia and somatic symptoms [62]. On the other hand, some studies corroborate the association between burnout and personality traits. EE and D dimensions are positively correlated with neuroticism, anxiety and depression but negatively correlated with agreeableness, conscientiousness, extraversion and openness. The PA dimension has a negative correlation with neuroticism, kindness, conscience and extraversion [6,63].
Another finding is the inclusion of psychoeducational interventions for managing stress and daytime fatigue in nurses, thus improving physiology and quality of sleep [32], in addition to mediating recovery from chronic burnout [31]. Previously, cognitive behavioral therapy was used to treat problems of severe insomnia, sleep efficiency, the number of awakenings and waking time after the onset of sleep [64], as well as interventions with calming music before going to bed, combined with brisk walks [65]. At present, there is an increase in research that includes, in burnout prevention therapies, the management of somatic symptoms entailed by chronic stress through education in mindfulness and resilience, presenting a more protective effect in conditions of work stress [22,66].
Regarding the limitations of this study, there are numerous articles that reported on the relationship between anxiety and depression with sleep disorders but did not include burnout measurements. Almost all the studies included in the review were cross-sectional, and most employed convenience sampling, which makes it difficult to establish causal relationships and increases in the risk of bias, making it difficult to extrapolate the obtained data. Finally, it is important to indicate that some of the studies did not include information about the duration of the sleep problems, and the age of the participants varied (which can influence burnout and sleep quality), which could influence the results. This fact, coupled with the considerable heterogeneity in the measurement questionnaires used to study sleep problems and their subjective quality, means that the results should be interpreted with caution. Future research should analyze how some interventions that work for reducing burnout in nurses, such as mindfulness, may also improve sleep quality by reducing burnout.
Implications for Practice
The relationship between sleep and burnout must be taken into account to improve nurses’ working conditions. Developing turnicity strategies that limit alterations in circadian rhythm and improve sleep quality could be positive. Using warmer lights in hospital units during night shifts could also be valued, as white light seems to be an important factor for sleep quality. In addition, where possible, elimination of the fixed night shift should be considered due to its impact on circadian rhythm.
5. Conclusions
The results of this study and meta-analysis provide information about the relationship between burnout and sleep problems. High burnout levels are correlated with higher levels of sleep problems in nurses. Some variables can influence these problems, such as gender, shift type, work environment and workplace violence. Improving burnout in nurses should be a priority for nurse managers because doing so may help to improve sleep quality and the quality of care. The importance of healthcare workers was made clear during the COVID−19 pandemic; therefore ensuring the health or nurses is important in the future.
Author Contributions
Conceptualization, J.L.G.-U., T.A., G.A.C.-D.l.F. and E.I.D.l.F.-S.; methodology, J.L.G.-U., T.A. and E.I.D.l.F.-S.; software, J.L.G.-U.; validation, J.L.G.-U., T.A. and E.I.D.l.F.-S.; formal analysis, M.J.M.-J., J.L.G.-U. and N.S.-M.; investigation, M.J.M.-J., J.L.G.-U. and N.S.-M.; resources, M.J.M.-J., J.L.G.-U. and N.S.-M.; data curation, M.J.M.-J., J.L.G.-U. and A.V.-S.; writing—original draft preparation, M.J.M.-J. and A.V.-S.; writing—review and editing, J.L.G.-U., N.S.-M., T.A. and G.A.C.-D.l.F.; visualization, M.J.M.-J., J.L.G.-U., N.S.-M., A.V.-S., T.A., G.A.C.-D.l.F. and E.I.D.l.F.-S.; supervision, M.J.M.-J., J.L.G.-U., N.S.-M., A.V.-S., T.A., G.A.C.-D.l.F. and E.I.D.l.F.-S.; project administration, E.I.D.l.F.-S.; funding acquisition, E.I.D.l.F.-S. All authors have read and agreed to the published version of the manuscript.
Funding
The research was carried out within the framework of Research Project P11 HUM-7771, directed by Emilia I. De la Fuente and funded by the Regional Government of Andalusia (Spain).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study is available by contacting the corresponding author.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Bradley, H.B. Community-based treatment for young adult offenders. Crime Delinq. 1969, 15, 359–370. [Google Scholar] [CrossRef] [Scilit]
- Freudenberger, H.J. Staff burn-out. J. Soc. Issues 1974, 30, 159–165. [Google Scholar] [CrossRef] [Scilit]
- Maslach, C.; Jackson, S.E. Maslach Burnout Inventory; Consulting Psychologists Press: Palo Alto, CA, USA, 1981. [Google Scholar]
- Maslach, C.; Jackson, S.E. Maslach Burnout Inventory, 2nd ed.; Consulting Psychologists Press: Palo Alto, CA, USA, 1986. [Google Scholar]
- Maslach, C.; Jackson, S.E.; Leiter, M.P. The Maslach Burnout Inventory, 3rd ed.; Consulting Psychologists Press: Palo Alto, CA, USA, 1996. [Google Scholar]
- De la Fuente, G.A.C.; Vargas, C.; San Luis, C.; García, I.; Cañadas, G.R.; de la Fuente, E.I. Risk factors and prevalence of burnout syndrome in the nursing profession. Int. J. Nurs. Stud. 2015, 52, 240–249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Molina-Praena, J.; Ramírez-Baena, L.; Gómez-Urquiza, J.L.; Cañadas, G.R.; de la Fuente, E.I.; Cañadas-De la Fuente, G.A. Levels of burnout and risk factors in medical area nurses: A meta-analytic study. Int. J. Environ. Res. 2018, 15, 2800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parada, M.E.; Moreno, R.; Mejías, M.Z.; Rivas, F.A.; Rivas, F.F.; Cerrada, S.J.; Rivas, P.F. Job satisfaction and burnout syndrome in the nursing staff of the Instituto Autónomo Hospital Universitario Los Andes, Mérida, Venezuela. Rev. Fac. Nac. 2005, 23, 33–45. [Google Scholar]
- Gómez-Urquiza, J.L.; Monsalve-Reyes, C.S.; San Luis-Costas, C.; Fernández-Castillo, R.; Aguayo-Estremera, R.; Cañadas-de la Fuente, G.A. Factores de riesgo y niveles de burnout en enfermeras de atención primaria: Una revisión sistemática. Aten. Primaria 2017, 49, 77–85. [Google Scholar] [CrossRef] [Scilit]
- Gallagher, R.M.; Gormley, D.K. Perceptions of stress, burnout, and support systems in pediatric bone marrow transplantation nursing. Clin. J. Oncol. Nurs. 2009, 13, 681–685. [Google Scholar] [CrossRef] [Scilit]
- Karasek, R.; Theorell, T. Healthy Work: Stress, Productivity, and the Reconstruction of Working Life; Basic Books: New York, NY, USA, 1990. [Google Scholar]
- Adriaenssens, J.; Hamelink, A.; van Bogaert, P. Predictors of occupational stress and well-being in first-line nurse managers: A cross-sectional survey study. Int. J. Nurs. Stud. 2017, 73, 85–92. [Google Scholar] [CrossRef] [Scilit]
- Hsieh, M.L.; Li, Y.M.; Chang, E.T.; Lai, H.L.; Wang, W.H.; Wang, S.C. Sleep disorder in Taiwanese nurses: A random sample survey. Nurs. Health Sci. 2011, 13, 468–474. [Google Scholar] [CrossRef] [Scilit]
- Huang, C.L.C.; Wu, M.P.; Ho, C.; Wang, J.J. Risks of treated anxiety, depression, and insomnia among nurses: A nationwide longitudinal cohort study. PLoS ONE 2018, 13, e0204224. [Google Scholar] [CrossRef] [Scilit]
- Yazdanshenas, M.; Kavian, M.; Ahmadloo, M.; Jarchi, A.; Golchin, S.; Latifi, S.; Hossein, S.A.; Ghajarzadeh, M. The association between life satisfaction and the extent of depression, anxiety and stress among Iranian nurses: A multicenter survey. Iran J. Psychiatry 2016, 11, 120–127. [Google Scholar]
- Jacobsen, H.B.; Reme, S.E.; Sembajwe, G.; Hopcia, K.; Stoddard, A.M.; Kenwood, C.; Buxton, O.M. Work- family conflict, psychological distress, and sleep deficiency among patient care workers. Workplace Health Saf. 2014, 62, 282–291. [Google Scholar]
- Geiger-Brown, J.; Rogers, V.E.; Trinkoff, A.M.; Kane, R.L.; Bausell, R.B.; Scharf, S.M. Sleep, sleepiness, fatigue, and performance of 12-hour-shift nurses. Chronobiol. Int. 2012, 29, 211–219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sarrais, F.; de Castro, P. El insomnio. An. Sist. Sanit. Navar. 2007, 30, 121–134. [Google Scholar] [CrossRef] [Scilit]
- Sánchez-Sánchez, A.M.; Vega-Escaño, J. Abordaje del insomnio en salud laboral. Enferm. Trab. 2019, 9, 11–20. [Google Scholar]
- Stewart, N.H.; Arora, V.M. The impact of sleep and circadian disorders on physician burnout. Chest 2019, 156, 1022–1030. [Google Scholar] [CrossRef] [Scilit]
- Bautista, S.; Balanza, J.; Torres, L. Trastornos del Sueño. In Guía de Manejo de los Trastornos Mentales; Chamorro, L., Ed.; Ars Medica: Barcelona, Spain, 2004; pp. 141–158. [Google Scholar]
- Kemper, K.J.; Mo, X.; Khayat, R. Are mindfulness and self-compassion associated with sleep and resilience in health professionals? J. Altern. Complement. Med. 2015, 21, 496–503. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Duffy, J.F.; Ronan, E. Do sleep disturbances mediate the association between work-family conflict and depressive symptoms among nurses? A cross-sectional study. J. Psychiatr. Ment. Health Nurs. 2017, 24, 620–628. [Google Scholar] [CrossRef] [Scilit]
- Eanes, L. CE: The potential effects of sleep loss on a nurse’s health. Am. J. Nurs. Sci. 2015, 115, 34–40. [Google Scholar] [CrossRef] [Scilit]
- Zhang, C.; Tait, C.; Minacapelli, C.D.; Bhurwal, A.; Gupta, K.; Amin, R.; Rustgi, V.K. The role of race, sex and age in circadian disruption and metabolic disorders. Gastro Hep Adv. 2022, 1, 471–479. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 88, 105906. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; Moher, D.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. PRISMA 2020 explanation and elaboration: Updated guidance and exemplars for reporting systematic reviews. BMJ 2021, 372, 160. [Google Scholar] [CrossRef] [PubMed]
- von Elm, E.; Altman, D.G.; Egger, M.; Pocock, S.J.; Gøtzsche, P.C.; Vandenbroucke, J.P.; STROBE Iniciative. The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: Guidelines for reporting observational studies. J. Clin. Epidemiol. 2008, 61, 344–349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- des Jarlais, D.C.; Lyles, C.; Crepaz, N. Trend Group: Improving the reporting quality of nonrandomized evaluations of behavioral and public health interventions: The TREND statement. Am. J. Public. Health 2004, 94, 361–366. [Google Scholar] [CrossRef] [Scilit]
- Howick, J.; Chalmers, I.; Glasziou, P.; Greenhalgh, T.; Heneghan, C.; Liberati, A.; Moschetti, I.; Phillips, B.; Thornton, H. Explanation of the 2011 Oxford Centre for Evidence-Based Medicine (OCEBM) Levels of Evidence (Background Document). Available online: https://www.cebm.ox.ac.uk/resources/levels-of-evidence/ocebm-levels-of-evidence (accessed on 30 October 2021).
- Ekstedt, M.; Söderström, M.; Akerstedt, T. Sleep physiology in recovery from burnout. Biol. Psychol. 2009, 82, 267–273. [Google Scholar] [CrossRef] [Scilit]
- Morimoto, H.; Tanaka, H.; Ohkubo, R.; Mimura, M.; Ooe, N.; Ichikawa, A.; Yukitoshi, H. Self-help therapy for sleep problems in hospital nurses in Japan: A controlled pilot study. Sleep Biol. Rhythm. 2015, 14, 177–185. [Google Scholar] [CrossRef] [Scilit]
- Bagheri, M.; Ebrahimi, M.H.; Khanjani, N.; Biganeh, J.; Mohammadi, S.; Abdolahfard, M. The effects of amplitude and stability of circadian rhythm and occupational stress on burnout syndrome and job dissatisfaction among irregular shift working nurses. J. Clin. Nurs. 2019, 28, 1868–1878. [Google Scholar] [CrossRef] [Scilit]
- Giorgi, F.; Mattei, A.; Notarnicola, I.; Petrucci, C.; Lancia, L. Can sleep quality and burnout affect the job performance of shift-work nurses? A hospital cross-sectional study. J. Adv. Nurs. 2018, 74, 698–708. [Google Scholar] [CrossRef] [Scilit]
- Havaei, F.; Astivia, O.L.; MacPhee, M. The impact of workplace violence on medical-surgical nurses’ health outcome: A moderated mediation model of work environment conditions and burnout using secondary data. Int. J. Nurs. Stud. 2020, 109, 103666. [Google Scholar] [CrossRef] [Scilit]
- Iskera-Golec, I.; Folkard, S.; Marek, T.; Noworol, C. Health, well-being and burnout of ICU nurses on 12- and 8-h shifts. Work Stress 1996, 10, 251–256. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.J.; Na, H. A study of the relationships between compassion fatigue, compassion satisfaction, depression, anxiety, and sleep disorders among oncology nurses. Asian Oncol. Nurs. 2017, 2, 116–123. [Google Scholar] [CrossRef] [Scilit]
- Lu, J.L. Multiple interactions of hazard exposures, role stressors and situational factors, and burnout among nurses. Int. J. Occup. Saf. Ergon. 2007, 13, 73–82. [Google Scholar] [CrossRef] [PubMed]
- Moreno-Casbas, M.T.; Alonso-Poncelas, E.; Gómez-García, T.; Martínez-Madrid, M.J.; Escobar-Aguilar, G. Percepción sobre la calidad de los cuidados, entorno laboral y características del sueño de las enfermeras que trabajan en el Sistema Nacional de Salud. Enferm. Clin. 2018, 28, 230–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schult, T.M.; Mohr, D.C.; Osatuke, K. Examining burnout profiles in relation to health and well-being in the Veterans Health Administration employee population. Stress Health 2018, 34, 490–499. [Google Scholar] [CrossRef] [Scilit]
- Wilson, W.; Raj, J.P.; Narayan, G.; Ghiya, M.; Murty, S.; Joseph, B. Quantifying Burnout among Emergency Medicine Professionals. J. Emerg. Trauma Shock 2017, 10, 199–204. [Google Scholar] [CrossRef] [Scilit]
- Zencirci, A.D.; Arslan, S. Morning-evening type and burnout level as factors influencing sleep quality of shift nurses: A questionnaire study. Croat. Med. J. 2011, 52, 527–537. [Google Scholar] [CrossRef] [Scilit]
- Alba-Martín, R. Burnout in nursing: Prevalence and related factors in a hospital environment. Rev. Cient. Soc. Esp. Enferm. Neurol. 2015, 41, 9–14. [Google Scholar]
- Blanca-Gutiérrez, J.J.; Arias-Herrera, A. Síndrome de burnout en personal de enfermería: Asociación con estresores del entorno hospitalario, Andalucía, España. Enferm. Univ. 2018, 15, 30–44. [Google Scholar] [CrossRef] [Scilit]
- Gómez, M.C.; Álamo, M.C.; Amador, M.; Ceacero, F.; Mayor, A.; Muñoz, A.; Izquierdo, M. Estudio de seguimiento del desgaste profesional en relación con factores organizativos en el personal de enfermería de medicina interna. Med. Segur. Trab. 2009, 55, 52–62. [Google Scholar]
- Paris, L. Estrategias de afrontamiento del estrés asistencial y satisfacción laboral-personal en médicos y enfermeros. Rev. Interam. Psicol. Ocup. 2007, 26, 7–21. [Google Scholar]
- Camerino, D.; Sandri, M.; Sartori, S.; Conway, P.M.; Campanini, P.; Costa, G. Shiftwork, work-family conflict among italian nurses and prevention efficacy. Chronobiol. Int. 2010, 27, 1105–1123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Estryn-Behar, M.; Fry, C.; Guetarni, K.; Machet, G.; Doppia, M.A.; Lassaunière, J.M.; Muster, D.; Pelloux, P.; Prudhomme, C. Work week duration, work-family balance and difficulties encountered by female and male physicians: Results from the French SESMAT study. Work 2011, 40, 83–100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alqahtani, A.M.; Awadalla, N.J.; Alsaleem, S.A.; Alsamghan, A.S.; Alsaleem, M.A. Burnout syndrome among emergency physicians and nurses in Abha and Khamis Mushait Cities, Aseer Region, Southwestern Saudi Arabia. Sci. World J. 2019, 2019, 4515972. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, Q.H.; Jiang, C.Q.; Lam, T.H. The relationship between occupational stress, burnout, and turnover intention among managerial staff from a Sino-Japanese joint venture in Guangzhou. J. Occup. Health 2013, 55, 458–467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ríos, M.I.; Godoy, C.; Peñalver, F.; Alonso, A.R.; López, F.; López, A.; Garnés, S.; Salmerón, E.; López, M.D.; Ruiz, R.; et al. Estudio comparativo del burnout en personal de enfermería de Cuidados Intensivos y Urgencias. Enferm. Intensiva 2008, 19, 2–13. [Google Scholar] [CrossRef] [Scilit]
- Nogareda, C.; Nogareda, S. NTP 455. Trabajo a Turnos y Nocturnos: Aspectos Organizativos [Ministerio de Trabajo y Asuntos Sociales, España Web Site]. Available online: https://www.insst.es/documents///ntp_455.pdf/–21f3–419a-b356–1f2ddb9e2766 (accessed on 20 October 2021).
- Cañadas-de la Fuente, G.A.; Albendín-García, L.; de la Fuente, E.I.; San Luis, C.; Gómez-Urquiza, J.L.; Cañadas, G.R. Síndrome de burnout en profesionales de enfermería que realizan jornada física complementaria en servicios de cuidados críticos y urgencias. Rev. Esp. Salud Publica 2016, 90, e1–e9. [Google Scholar] [PubMed]
- Bonet-Porqueras, R.; Moliné-Pallarés, A.; Olona-Cabases, M.; Gil-Mateu, E.; Bonet-Notario, P.; Les-Morell, E.; Iza-Maiza, M.; Bonet-Porqueras, M. Turno nocturno: Un factor de riesgo en la salud y calidad de vida del personal de enfermería. Enferm. Clin. 2009, 19, 76–82. [Google Scholar] [CrossRef] [Scilit]
- García, A. Enfermería y turno de noche: Trabajar contra corriente. Inferm. Ponent 2003, 8, 1–7. [Google Scholar]
- Chiu, H.Y.; Tsai, P.S. The impact of various work schedules on sleep complaints and minor accidents during work or leisure time: Evidence from a national survey. J. Occup. Environ. Med. 2013, 55, 325–330. [Google Scholar] [CrossRef] [Scilit]
- Deschamps, A.; Olivares, S.B.; de la Rosa, K.L.; Asunsolo, A. Influencia de los turnos de trabajo y las guardias nocturnas en la aparición del Síndrome de Burnout en médicos y enfermeras. Med. Segur. Trab. 2011, 57, 224–241. [Google Scholar] [CrossRef] [Scilit]
- Palermo, T.A.C.; Rotenberg, L.; Zeitoune, R.C.G.; Silva-Costa, A.; Souto, E.P.; Griep, R.H. Siesta durante la guardia nocturna y la recuperación tras el trabajo entre enfermeros de hospitales. Rev. Lat. Am. Enferm. 2015, 23, 114–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poursadeghiyan, M.; Moghimian, M.; Nabiamjad, R.; Baneshi, M.M.; Yari, A.; Noroozi, M.; Hami, M.; Khammar, A.; Farrokhi, M. Effects on job stress on Iranian clinical nurses. Ann. Trop. Med. Public Health 2017, 10, 985–988. [Google Scholar] [CrossRef] [Scilit]
- Adriaenssens, J.; de Gucht, V.; Maes, S. The impact of traumatic events on emergency room nurses: Findings from a questionnaire survey. Int. J. Nurs. Stud. 2012, 49, 1411–1422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roche, M.A.; Diers, D.; Duffield, C.; Catling-Paull, C. Violence toward nurses, the work environment, and patient outcomes. J. Nurs. Scholarsh. 2010, 42, 13–22. [Google Scholar] [CrossRef] [Scilit]
- Díaz-Ramiro, E.M.; Rubio-Valdehita, S.; López-Núñez, M.I.; Aparicio-García, M.E. Los hábitos de sueño como predictores de la salud psicológica en profesionales sanitarios. An. Psicol. 2020, 36, 242–246. [Google Scholar] [CrossRef] [Scilit]
- de la Fuente-Solana, E.I.; Gómez-Urquiza, J.L.; Cañadas, G.R.; Albendín-García, L.; Ortega-Campos, E.; Cañadas-de la Fuente, G.A. Burnout and its relationship with personality factors in oncology nurses. Eur. J. Oncol. Nurs. 2017, 30, 91–96. [Google Scholar] [CrossRef] [Scilit]
- Pigeon, W.R.; Funderburk, J.; Bishop, T.M.; Crean, H.F. Brief cognitive behavioral therapy for insomnia delivered to depressed veterans receiving primary care services: A pilot study. J. Affect. Disord. 2017, 217, 105–111. [Google Scholar] [CrossRef] [Scilit]
- Huang, C.Y.; Chang, E.T.; Lai, H.L. Comparing the effects of music and exercise with music for older adults with insomnia. Appl. Nurs. Res. 2016, 32, 104–110. [Google Scholar] [CrossRef] [Scilit]
- Shatté, A.; Perlman, A.; Smith, B.; Lynch, W.D. The positive effect of resilience on stress and business outcomes in difficult work environments. J. Occup. Environ. Med. 2017, 59, 135–140. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).