


Abstract
Influenza vaccination can benefit most populations, including adults ≥ 65 years of age, who are at greater risk of influenza-related complications. In many countries, enhanced vaccines, such as adjuvanted, high-dose, and recombinant trivalent/quadrivalent influenza vaccines (aTIV/aQIV, HD-TIV/HD-QIV, and QIVr, respectively), are recommended in older populations to provide higher immunogenicity and increased relative vaccine efficacy/effectiveness (rVE) than standard-dose vaccines. This review explores how efficacy and effectiveness data from randomized controlled trials and real-world evidence (RWE) are used in economic evaluations. Findings from published cost-effectiveness analyses (CEA) on enhanced influenza vaccines for older adults are summarized, and the assumptions and approaches used in these CEA are assessed alongside discussion of the importance of RWE in CEA. Results from many CEA showed that adjuvanted and high-dose enhanced vaccines were cost-effective compared with standard vaccines, and that differences in rVE estimates and acquisition price may drive differences in cost-effectiveness estimates between enhanced vaccines. Overall, RWE and CEA provide clinical and economic rationale for enhanced vaccine use in people ≥ 65 years of age, an at-risk population with substantial burden of disease. Countries that consider RWE when making vaccine recommendations have preferentially recommended aTIV/aQIV, as well as HD-TIV/HD-QIV and QIVr, to protect older individuals.
1. Introduction
Each year, seasonal influenza is associated with substantial global disease burden experienced by patients, caregivers, and communities. In the United States, the cost of influenza burden is estimated at $11.2 billion annually (2015 US dollars), comprising direct medical costs, such as healthcare visits (estimated at around $3 billion), and indirect costs, such as lost days at work (estimated at around $8 billion) [1]. Preventative vaccination is a key strategy by which societies can minimize influenza-related disease burden and economic cost. The US Centers for Disease Control and Prevention (CDC) estimated that 3.7 million medical visits, 105,000 hospitalizations, and 6300 deaths related to influenza were prevented by vaccination during the 2019–2020 influenza season [2]. The overall value of influenza vaccination may be underestimated [3].
National advisory bodies, such as the US Advisory Committee on Immunization Practices (ACIP), recommend that all individuals ≥ 6 months of age receive an annual vaccine for protection against seasonal influenza [4]. The need for annual vaccination is driven by ongoing evolution of the influenza virus, owing to a segmented RNA genome, which is subject to mutation and genome reassortment [5,6]. Each year, the World Health Organization (WHO) reviews influenza surveillance data and presents recommendations to regulators and vaccine manufacturers for the composition of influenza vaccines [7]. The ongoing potential for antigenic drift and resulting mismatch between vaccine and virus necessitates continual monitoring and data collection on vaccine performance in the real world [8].
All populations can benefit from influenza vaccination, although certain groups, including older adults ≥ 65 years of age, are at greater risk of influenza-related complications [1,3]. Older individuals, who show age-related declines in immune system function [9], have disproportionately high rates of seasonal influenza-related hospitalizations and deaths [2,10]. For this population, enhanced vaccines have been designed to mitigate the effects of age-related immunosenescence by providing higher immunogenicity and increased relative vaccine efficacy/effectiveness (rVE) compared with standard vaccines [10,11,12].
Enhanced vaccines use different strategies to augment immune responses and have been available for varying lengths of time in different countries (Table 1). High-dose trivalent/quadrivalent influenza vaccines (HD-TIV/HD-QIV) contain four-times more hemagglutinin antigen than standard-dose vaccines, an approach demonstrated to increase the magnitude of the immune response [10]. Adjuvanted trivalent/quadrivalent influenza vaccines (aTIV/aQIV) contain the adjuvant MF59, an oil-in-water emulsion of squalene oil, which has been demonstrated to increase the magnitude and breadth of immune responses [13,14,15]. Recombinant quadrivalent influenza vaccines (QIVr) use a higher antigen content and recombinant technology for synthetic (non-egg, non-cell) manufacture that eliminate the risk of viral mutations, an approach that may limit antigenic mismatch [16].
Adult vaccination against seasonal influenza is recommended in many countries and some, such as several countries in Europe, provide influenza vaccination free-of-charge at the point of delivery to older individuals [17]. Many European countries recommend that older individuals receive an enhanced influenza vaccine [11]. Outside Europe, in many countries, including the United States, the United Kingdom, Australia, and Argentina, enhanced vaccines are preferentially recommended over other influenza vaccines in older populations [18,19,20,21,22]. To make recommendations, national vaccine policymakers consider many factors, such as vaccine evidence, public health priorities, cost, and the ability to implement new interventions in a timely, feasible, and sustainable manner. The findings of cost-effectiveness analyses (CEA) may also be considered when making recommendations [23], with the United Kingdom Joint Committee on Vaccination and Immunization (JCVI) stating that analysis of cost-effectiveness is the “cornerstone of decision-making” related to universal vaccination decision-making and implementation [24].
The robustness of conclusions from economic models depends on the quality, accuracy, and appropriateness of a large range of data inputs and assumptions. Randomized controlled trials (RCTs) provide a gold-standard methodology to answer specific clinical research questions [25]. However, evidence that is of interest to vaccine advisory bodies, payers, and health economists, such as effectiveness data sets from multiple seasons describing patient-centric outcomes, may exceed what can be achieved practically with RCTs, which may take years to plan, implement, and analyze, and may not produce broadly generalizable findings across influenza seasons and patient populations [25,26,27]. To supplement efficacy data from RCTs, real-world evidence (RWE) provides timely and expanding datasets to monitor and evaluate vaccine effectiveness [27,28], which is important given the dynamics of a continuously changing influenza virus [5,6]. The use of RWE is increasing over time as familiarity and acceptance of data from well-constructed studies with non-randomized designs grow, especially for evaluating vaccines [29,30].
The objective of this review is to improve understanding of how efficacy and effectiveness data from RCT and RWE sources, and other parameters, are used in economic evaluations by providing an overview of published CEA on enhanced vaccines for influenza in older adults. This paper aims to critically assess assumptions and approaches in these CEA and to discuss the importance of RWE in evaluating vaccine effectiveness (VE) against influenza, with a particular focus on rVE inputs. Expert opinion on the importance, challenges, and future directions of RWE and CEA related to influenza vaccines is provided.
This paper adds to the contributions of prior articles reviewing CEA of enhanced vaccines in older adults [31,32,33,34]. In line with best practices, meta-analysis techniques are inappropriate for summarizing the outputs of economic modeling studies [35]; however, differences between economic models, including how investigators select inputs, are of interest to discuss.
Table 1.
Currently available enhanced vaccines for older adults.
2. Methods
2.1. Targeted Literature Search
A targeted literature review was performed to identify economic evaluations of enhanced influenza vaccines (aTIV/aQIV, HD-TIV/HD-QIV, and QIVr) in older individuals. MEDLINE (PubMed) was searched for publications using the following strings in October 2022, limited to studies from the past 10 years and prioritizing English-language publications. Additional articles published through March 2023 were included based on follow up searches.
- (“Adjuvanted quadrivalent influenza vaccine” OR “Fluad” OR “aIIV4” OR “aQIV”) AND (“economic” OR “cost” OR “cost effectiveness” OR “cost utility” OR “budget impact”)
- (“Adjuvanted trivalent influenza vaccine” OR “Fluad” OR “aIIV3” OR “aTIV”) AND (“economic” OR “cost” OR “cost effectiveness” OR “cost utility” OR “budget impact”)
- (“High dose quadrivalent influenza vaccine” OR “IIV4 HD” OR “QIV HD” OR “Fluzone HD”) AND (“economic” OR “cost” OR “cost effectiveness” OR “cost utility” OR “budget impact”)
- (“High dose trivalent influenza vaccine” OR “IIV3 HD” OR “TIV HD” OR “Fluzone HD”) AND (“economic” OR “cost” OR “cost effectiveness” OR “cost utility” OR “budget impact”)
- (“Quadrivalent recombinant influenza vaccine” OR “QIVr” OR “Flublok”) AND (“economic” OR “cost” OR “cost-effectiveness” OR “cost-utility” OR “budget impact”).
2.2. Supplemental Searches
The reference lists of retrieved primary studies, systematic reviews, and meta-analyses were searched to capture additional studies. Congress presentations that included CEA or cost-utility analysis (CUA; hereafter referred to simply as CEA for convenience) were included based on expert knowledge and ability to retrieve poster and oral presentations.
2.3. Included Studies
Identified papers describing CEA from any world region were prioritized for inclusion. Included papers regarded enhanced vaccines in populations ≥ 65 years of age (or >50 years of age in models regarding QIVr). To be included, studies reported multiple parameters from the following: model type, country setting, vaccine strategy, study perspective, time horizon, selected costs, currency, rVE and/or VE, discounting strategies, and use of uncertainty analyses. Included studies could use VE and rVE inputs generated from RCTs and/or RWE.
3. Cost-Effectiveness Studies with Enhanced Influenza Vaccines
3.1. Comparison between CEA for Enhanced and Standard Vaccines
In many countries, CEA have estimated the economic value of enhanced vaccines for older populations. Thirty-one CEA comparing enhanced vaccines to standard-dose vaccines were analyzed, 17 comparing aTIV/aQIV with TIV/QIV (Table 2A) and 14 comparing HD-TIV/HD-QIV with TIV/QIV (Table 2B). Studies included static and dynamic designs, and perspectives included healthcare system, societal, and third-party payer. Most studies included probabilistic and/or deterministic sensitivity analyses. Time horizons varied from one influenza season or year, although some models took a multi-year or lifetime approach. Discounting ranged from 0–5% for outcomes and costs. Most studies had an industry sponsor.
Inputted rVE values varied across studies. In studies of adjuvanted versus standard-dose vaccines, estimates of rVE for aTIV/aQIV versus TIV/QIV ranged from 13.7% to 34.6%, which represents RWE estimates of rVE against laboratory-confirmed influenza (LCI), hospitalization/healthcare visits, or other measures (Table 2A; Figure 1). The rVE of aTIV/aQIV versus TIV/QIV was also captured as reported in studies that used a common comparator of TIV/QIV to indirectly compare rVE of HD-TIV/HD-QIV versus aTIV/aQIV. Interestingly, in this case, much lower estimates of rVE, ranging from 0% to 6% for aTIV/aQIV versus TIV, were input into CEA models (Table 3B; Figure 2). The rVE estimate of 24.2% for HD-TIV/HD-QIV versus TIV/QIV for LCI cases, based on results from the FIM12 RCT [50], was consistently used in CEA comparing HD-TIV/HD-QIV versus TIV/QIV, and used in CEA that indirectly compared the rVE of HD-TIV/HD-QIV versus aTIV/aQIV (Table 2B and Table 3B; Figure 2).
Figure 1.
rVE as used in base-case analyses of aTIV/aQIV compared with TIV/QIV and/or HD-TIV/HD-QIV [51,52,53,54,55,56,57,58,59,60,61,62,63,64]. aQIV, adjuvanted quadrivalent influenza vaccine; aTIV, adjuvanted trivalent influenza vaccine; CEA, cost-effectiveness analysis; HD-QIV, high-dose quadrivalent influenza vaccine; HD-TIV, high-dose trivalent influenza vaccine; QIV, quadrivalent influenza vaccine; RCT, randomized controlled trial; rVE, relative vaccine effectiveness; RWE, real-world evidence; TIV, trivalent influenza vaccine.
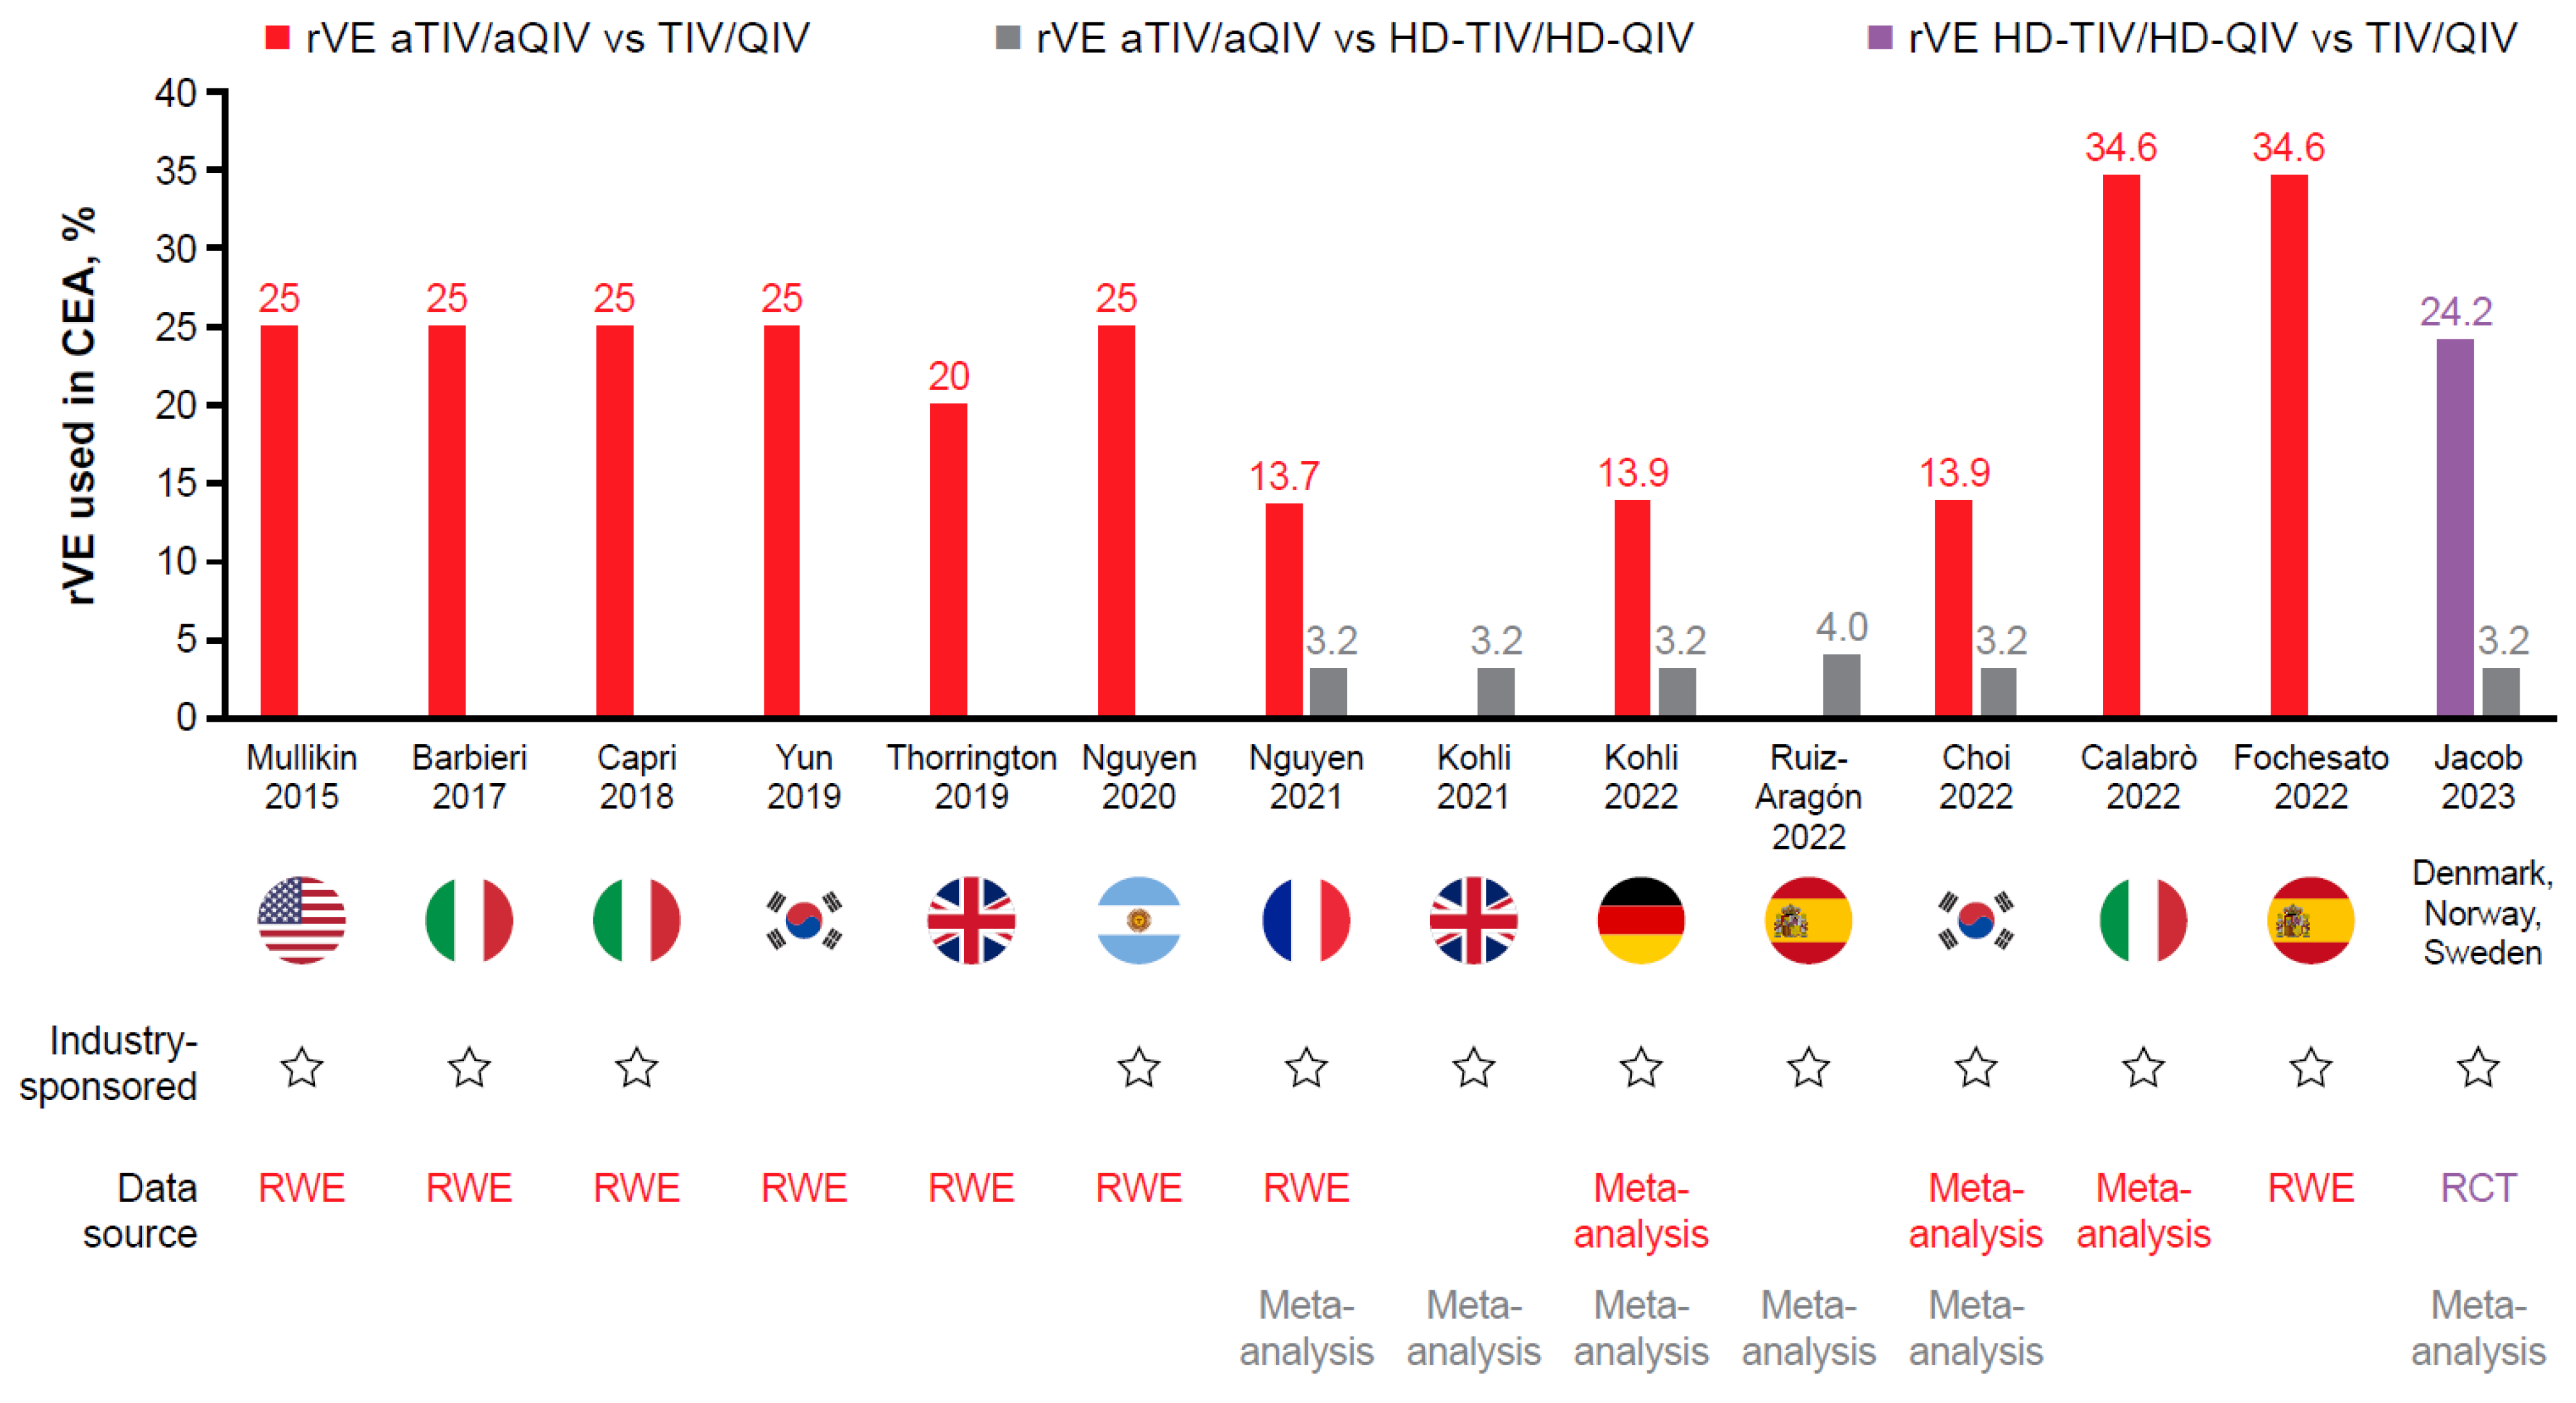
Figure 2.
rVE as used in base-case analyses of HD-TIV/HD-QIV compared with TIV/QIV or aTIV/aQIV [65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81]. Note: no value indicates that a comparison was not evaluated. 0 indicates a rVE of 0% in base-case analysis. Note: rVE aTIV/aQIV versus TIV/QIV is captured as reported in studies that use a common comparator of TIV/QIV to indirectly compare rVE of HD-TIV/HD-QIV versus aTIV/aQIV. aQIV, adjuvanted quadrivalent influenza vaccine; aTIV, adjuvanted trivalent influenza vaccine; CEA, cost-effectiveness analysis; HD-QIV, high-dose quadrivalent influenza vaccine; HD-TIV, high-dose trivalent influenza vaccine; QIV, quadrivalent influenza vaccine; RCT, randomized controlled trial; rVE, relative vaccine effectiveness; RWE, real-world evidence; TIV, trivalent influenza vaccine.
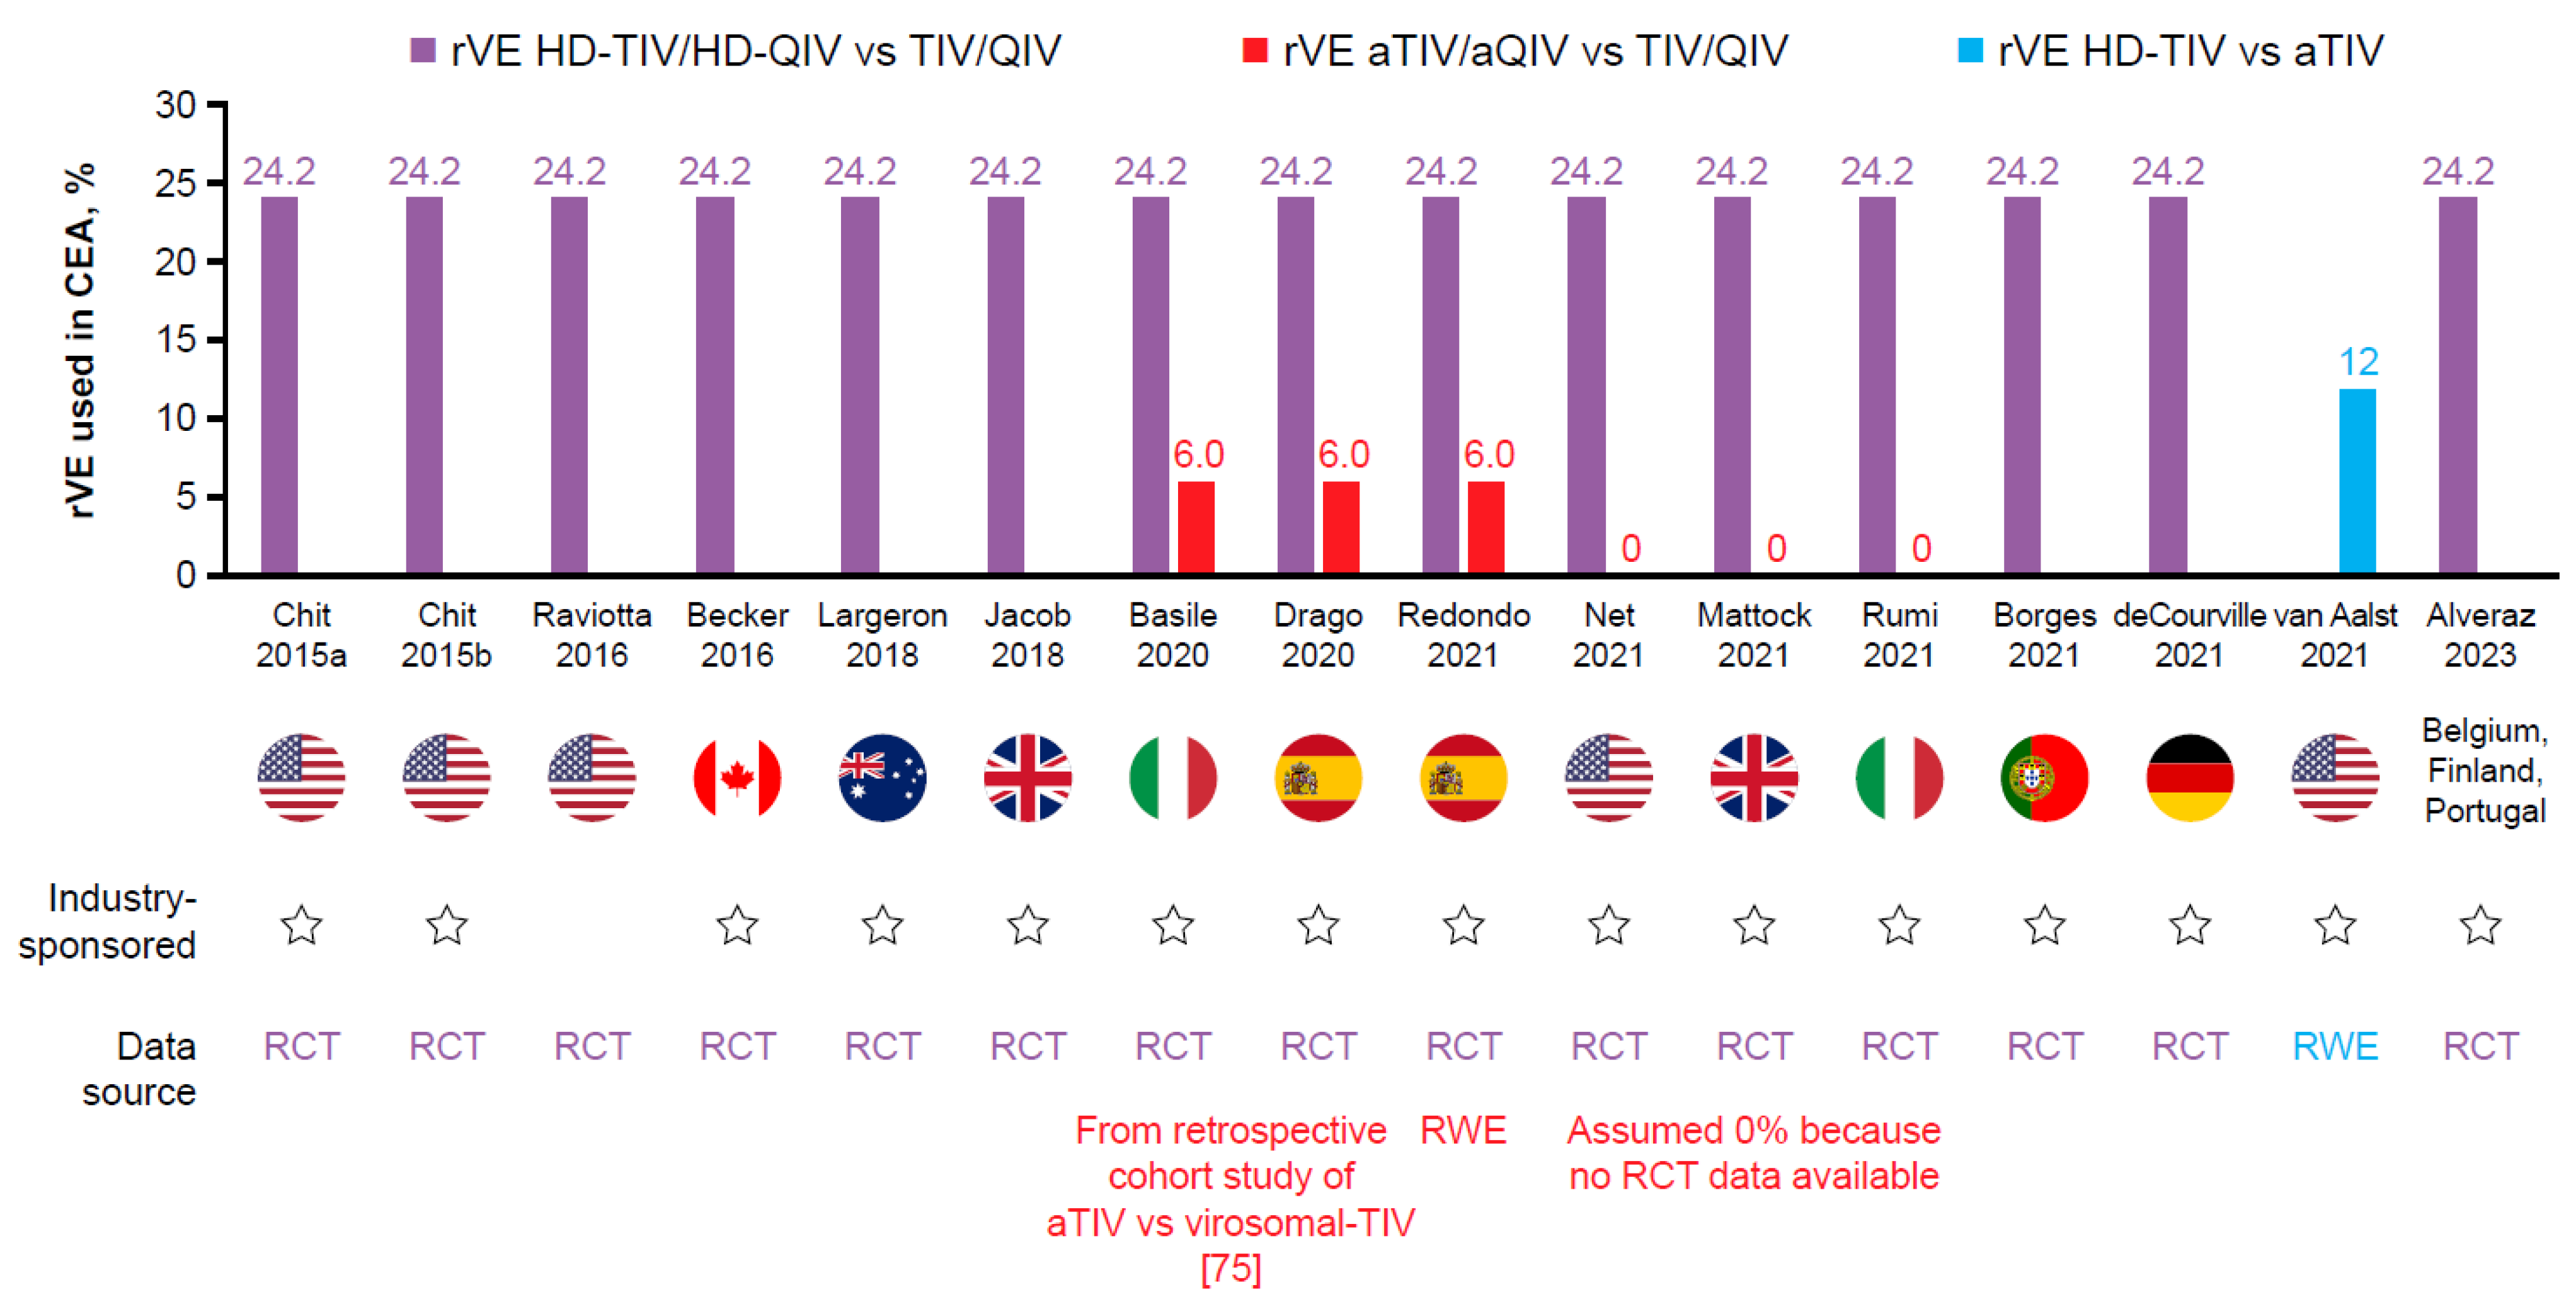
Table 2.
Cost-effectiveness studies of adjuvanted vaccines (A) or high-dose vaccines (B), compared with TIV/QIV.
CEA comparing enhanced vaccines with standard-dose vaccines estimated that enhanced vaccines were cost-effective in individuals ≥ 65 years of age. aTIV/aQIV and HD-TIV/HD-QIV were cost-effective compared with TIV/QIV, independent of setting, model design, perspective, rVE estimate, or acquisition cost difference (Table 2A,B).
3.2. Comparison between Enhanced Vaccines in CEA
CEA results were inconsistent when enhanced vaccines were compared with each other. Six studies compared aTIV/aQIV with HD-TIV/HD-QIV (mostly Seqirus-sponsored), ten studies compared HD-TIV/HD-QIV with aTIV/aQIV (mostly Sanofi-sponsored), and two studies compared QIVr with aQIV. Studies included static and dynamic designs, and perspectives ranged between healthcare system, societal, and third-party payer. Time horizons varied between one and multiple seasons. Discounting ranged from 0–5% for outcomes and costs. Most studies included deterministic and probabilistic sensitivity analyses. Findings remained robust across sensitivity analyses. Rate of hospitalization, rVE, and vaccine acquisition price were drivers of cost-effectiveness (CE) in many models (Table 3).
rVE inputs varied across studies. Most CEA comparing aTIV/aQIV versus HD-TIV/HD-QIV included direct estimates of rVE based on meta-analyses findings (Table 3A). On the other hand, CEA comparing HD-TIV/HD-QIV versus aTIV/aQIV often took an indirect approach, wherein a common comparator of TIV/QIV was used. The rVE estimate of 24.2% was commonly used for HD-TIV/HD-QIV versus TIV/QIV, based on findings from the FIM12 RCT [50] (Figure 1), whereas rVE ranging from 0% to 6% were used for aTIV/aQIV versus TIV/QIV (Table 3B; Figure 2).
Two CEA studies of interest were identified for QIVr (Table 3C). The first estimated the effect of switching from QIV/aQIV to QIVr in two age cohorts (≥18 years of age and ≥65 years of age) in the Spanish population using a static decision tree model [104]. The study estimated that mortality, hospitalizations, general practitioner visits, and emergency room services would decrease by 12%, 13%, 11%, and 12%, respectively, should the switch from QIV/aQIV to QIVr be implemented [104]. The second study did not find QIVr cost-effective compared with aQIV for individuals ≥ 65 years of age living in Spain. To achieve an incremental cost-effectiveness ratio (ICER) within the willingness-to-pay threshold, the rVE of QIVr versus aQIV would need to reach 34.1% [105].
Table 3.
Cost-effectiveness studies evaluating adjuvanted vaccines versus high-dose vaccines (A), high-dose vaccines versus adjuvanted vaccines (B), and recombinant vaccine versus other enhanced vaccines (C).
3.3. Systematic Reviews of CEA
Further to primary CEA studies, several systematic reviews of CEA for enhanced vaccines in older adults have been published [31,32,33,34]. A systematic review of the cost-effectiveness of HD-TIV in individuals ≥ 65 years of age identified that HD-TIV was either cost-effective or cost-saving across multiple analyses [33], and that the prevention of cardiorespiratory complications was a potential driver of economic benefits [33]. Many of the studies included in this systematic review were also included in our analysis (such as [65,66,67,68,101], which are included in Table 2B). A comprehensive review from Canada suggested that aTIV, HD-TIV, and QIV were cost-effective compared with TIV for individuals ≥ 65 years of age, but noted a lack of head-to-head comparisons between QIV, HD-TIV, and aTIV [31]. The authors suggested that future studies should include real-world evaluations, and that methodological, structural, and parameter uncertainty should be assessed in CEA [31]. Similarly, a systematic review of seasonal influenza vaccine economic evaluations in individuals ≥ 60 or ≥65 years of age from the European Union recommended linking economic evaluations to observational cohort studies, RCTs, or other long-term, prospective, controlled studies [32]. The authors pointed out the need for data over multiple seasons, owing to influenza virus mutations and the potential for vaccine mismatch [32]. Finally, a review of economic analyses of aTIV in older adults identified aTIV as cost-effective or cost-saving compared with no vaccination or non-adjuvanted vaccines [34].
4. Critical Assessment of CEA Inputs and Approaches
CEA is a robust process that involves a variety of inputs, including, but not limited to, price, effectiveness, and utility, which supports decision analysis and is amenable to sensitivity testing [115]. Many economic analyses are performed to a high standard in accordance with gold-standard reporting guidelines for CEA, such as Consolidated Health Economic Evaluation Reporting Standards (CHEERS) 2022 [116]. Selection of robust inputs is of critical importance to the usability of findings from CEA models.
4.1. Effectiveness Input
4.1.1. Importance of RWE for Influenza
It is important for public health officials to closely monitor circulating virus strains and for annual influenza vaccines to be adjusted and assessed on a seasonal basis [7]. Although vaccinated individuals achieve a level of cross-protection during mismatched seasons, VE usually decreases during mismatched seasons [90], and other factors, such as prior exposure, timing of vaccination, and waning immunity, may affect VE. The ability to assess vaccine performance in real time over multiple seasons, including those characterized by antigenic mismatch [8], is of high value for influenza.
Whereas RCTs aim to answer a focused research question by minimizing bias and confounders through randomization, blinding, and patient selection criteria, observational studies better reflect real-world conditions and are more easily performed over multiple influenza seasons with different circulating strains. Studies of real-world data sources may evaluate larger, more diverse, and more representative study populations than RCTs, potentially leading to more generalizable and clinically relevant results [27,28]. RWE may be used more often for influenza vaccine recommendations than for other vaccines or decisions in other disease areas [117,118], owing to timeline, cost, ethical, and enrollment difficulties of conducting RCTs to evaluate influenza vaccines in older individuals [28,119]. However, RWE may be subject to bias and similar studies may return conflicting results. For example, as assessed by Gärtner et al., 2022, of the seven retrospective cohort studies included in a systematic review discussing RWE of enhanced vaccines for older adults, three were found to have serious risk of bias owing to ‘inadequate control for important confounders’, ‘selection of reported outcome’, and ‘selection of participants’, and four were at moderate risk of bias [11]. RCTs themselves may also be subject to selection and/or informational bias, and new ways of defining ‘high-quality evidence’ have been proposed [120].
Multiple tools are used to assess and describe the risk of bias in non-randomized studies, and these approaches are very important for assessing the quality of RWE. Meta-analyses and systematic reviews may assess the risk of bias between studies (e.g., using Egger’s test to assess potential positive publication bias) or within studies (e.g., using the GRACE, Cochrane Risk of Bias, ROBINS-I, or AMSTAR 2 tools) to rank study design, conduct, and evidence against several parameters to determine an overall risk of bias for individual studies [11,92,121,122]. To support the transparent communication of findings, the structured template and reporting tool for real-world evidence (STaRT-RWE) provides guidance endorsed by the International Society of Pharmacoepidemiology and the Transparency Initiative [123]. STaRT-RWE aims to support researchers by setting clear reporting expectations, leading to reduced misinterpretation and improved validity assessment [123]. A review of RWE studies published using this template shows that STaRT-RWE has the potential to improve the reporting standards for RWE studies [124].
From a public health perspective, policymakers should understand epidemiological methods and have familiarity with seasonal influenza patterns to utilize RWE studies appropriately for decision-making. Confounding factors, such as comorbidities, health status, or previous history of vaccination, can alter estimates of effectiveness in studies without randomized designs [119]. In observational studies, different methods to identify and adjust for confounding factors can be used, including multivariate sensitivity analysis, restriction, matching, and stratification [119]. Early enhanced vaccine RWE studies in Italy, including Mannino et al., 2012, determined that aTIV reduces the risk of influenza- or pneumonia-related hospitalization by 25% compared with TIV in older adults [85]. This study used a prospective, observational design to capture evidence from multiple influenza seasons between 2006–2009, and stratification and statistical procedures to control for confounding, such as propensity-score-based multivariate analysis [85]. In this case, bias inherent in the non-randomized design may have diminished the impact of effectiveness findings (i.e., bias towards the null, as the authors suggest that their estimate may have under-reported the number of influenza- or pneumonia-related hospitalizations prevented by aTIV compared with TIV [85]. Bias towards the null arising from misclassification of outcomes has been mentioned in this and other studies of enhanced vaccines [85,125].
Use of real-world inputs in CEA is increasing as regulators and payers recognize the value of diverse measures and high-quality RWE in informing healthcare decision-making [30,126]. When selecting effectiveness inputs for use in CEA, there is a need for practicality, to ‘do the best with the available data’, and to continue to prioritize analyses of patient-centric endpoints (e.g., hospitalization) in the real-world setting. For example, a Dutch study found that a major driver of cost savings with enhanced vaccines compared with standard vaccines in older adults was the prevention of cardiovascular-related hospital admissions [103], a real-world endpoint that may not be practical to study in a RCT setting. Furthermore, the practical real-time use of RWE has been demonstrated during the coronavirus disease 2019 (COVID-19) pandemic, a setting in which rapid policy decisions were required to save lives [120,127,128]. RWE aided the characterization of COVID-19 natural history, symptoms, and identification of clinical features associated with increased disease severity [127,128]. Real-world data provided confidence in the effectiveness and safety of COVID-19 vaccination in special populations, such as pregnant women, who were excluded from vaccine clinical trials [129]. Although the authors pointed out that most of the RWE reviewed had some risk of bias, the available data were sufficient to be highly reassuring to patients and providers who had to make decisions based on available data at the time [129].
With increased influenza rates in 2022–2023 compared with pandemic years [130], and risk of co-infection with influenza in patients with COVID-19 [131], there is a clear need to prevent extra hospitalizations to maintain hospital bed capacity; adequate protection of older individuals from influenza with enhanced vaccines supports this goal.
4.1.2. Importance of RWE Meta-Analysis
Although several systematic reviews of enhanced vaccines support the comparable effectiveness of aTIV/aQIV and HD-TIV/HD-QIV for older adults [11,92,132], in the absence of RCT data and head-to-head comparisons between enhanced vaccines, different approaches to model assumptions and evidence strength grading may explain some variation in CEA findings across studies and industry sponsors. The European Centre for Disease Prevention and Control (ECDC) 2020 technical report on the efficacy, effectiveness, and safety of newer and enhanced seasonal influenza vaccines determined that the evidence base for the efficacy/effectiveness of enhanced influenza vaccines is ‘limited’ and comparability of enhanced vaccines with traditional seasonal influenza vaccines is ‘uncertain’ because of a lack of literature and because of clinical and statistical heterogeneity [133]. In the report, using GRADE criteria, relative efficacy data with HD-TIV versus TIV from one RCT (rVE 24.2%) and relative efficacy data with QIVr versus QIV from another RCT (rVE 30%) were classified as moderate-strength evidence. Conversely, VE data from five observational studies across three seasons (2011–2012, 2017–2018, and 2018–2019; VE 44.9%) were graded as low-strength evidence, because the data were generated from non-randomized sources and subject to risk of bias and imprecision [133]. In this context, different rVE estimates have been used by different researchers in CEA to model the economic benefits of aTIV/aQIV compared with other options (Figure 1 and Figure 2).
Other systematic reviews highlight the limitations of available RCTs that evaluate enhanced vaccines [134] and the potential value in using rVE estimates from RWE (as well as from RCTs) for HD-TIV [135]. After publication of the ECDC report, Gärtner et al., 2022 found similar effectiveness between aTIV and HD-TIV in seven RWE studies, whereas aTIV was more effective than HD-TIV in three studies [11]. From a policy perspective, countries considering RWE when making vaccine recommendations have recommended aTIV/aQIV, alongside other enhanced vaccines, such as HD-TIV/HD-QIV, in individuals ≥ 65 years of age [18,19,20].
Best-available estimates of rVE may include those arising from systematic reviews, meta-analysis, and network meta-analyses [31], which enable comparison of three or more interventions simultaneously [136,137]. Meta-analyses of real-world data may provide more robust estimates of effectiveness based on pooled sources of evidence compared with those provided by single studies. Among composite studies of enhanced vaccines in older adults, meta-analyses by Domnich et al., 2022 and Coleman et al., 2021 showed that aTIV and HD-TIV provide comparable effectiveness, which is supported by the Gärtner et al., 2022 systematic review; Lee et al., 2021 showed that HD-TIV is more effective than TIV [11,92,132,135]. These analyses were performed across large patient populations with data from multiple influenza seasons. rVE estimates from meta-analysis sources have been used in several CEA models assessing enhanced vaccines (Figure 1) [57,58,59,60,62,63,64], and some studies have produced novel meta-analysis estimates for use as part of a CEA [60,64].
When head-to-head trials are not available and comparisons are needed across multiple vaccines, network meta-analysis (also known as mixed treatment comparisons or multiple treatments meta-analysis) is an additional methodological option that enables the effectiveness of three or more vaccines to be compared in a single statistical analysis to aid decision-making [136,137]. Existing studies of rVE between vaccine pairs are organized into a network linked by direct and indirect comparisons [136,137]. This approach enables comparative ranking between vaccines and, similar to traditional meta-analysis methods, may produce a more precise estimate of relative effectiveness than that estimated from single studies [136,137]. The utility of network meta-analyses to assess relative effectiveness has also been established for COVID-19 vaccines [138,139]; one network meta-analysis analyzing the relative effectiveness and safety of approved seasonal influenza vaccines in different age and patient risk groups has been published [140].
4.1.3. Limitations of Currently Available Influenza RCT Evidence
The HD-TIV versus TIV rVE point estimate from the FIM12 RCT is used consistently in CEA of HD-TIV (Figure 1 and Figure 2). Although an important and well-designed study, the use of a single rVE estimate across multiple CEA may not reflect the reality of influenza, of which VE estimates may change seasonally because of virus mutations [32]. Use of the same efficacy or effectiveness data in multiple CEA may also over-represent a limited evidence base [32]. Variation in VE reflects the reality of changing vaccine performance across seasons and emphasizes the importance of continuous and current effectiveness data collection to underpin influenza vaccine policy.
A systematic review and meta-analysis of high-dose versus standard-dose influenza vaccine RCTs in adults ≥ 65 years of age illustrated the importance of understanding vaccine effects on influenza-associated hospitalizations and deaths, and these outcomes cannot be assessed from the high-dose influenza vaccine RCT evidence base [134]. Data from immunocompromised individuals were also lacking [134]; exclusion of high-risk populations has been identified as a general limitation of influenza vaccine RCTs [141]. The authors concluded that, even with RCT data comparing HD-TIV versus TIV, there is limited evidence confirming a reduction in LCI cases with HD-TIV, and limited evidence regarding clinically relevant outcomes [134]. The authors stated that longer-term pragmatic trials are needed to demonstrate impact in real-world settings [134].
More broadly, the limitations of RCT evidence have been highlighted by the pressing need for current evidence describing real-world endpoints during the COVID-19 pandemic [120]. RCTs may have practical, ethical, and timeline concerns; meta-analyses may also be affected by the inclusion of flawed individual RCTs that require subjective assessment of certain methodologies of constituent studies [120]. Conceptual proposals, such as next-generation evidence-based medicine (EBM), or EBM plus (EBM+), contend that taking a broader approach to defining clinically actionable evidence is necessary in certain situations, such as when information is needed for rapid and urgent decision-making [120,142]. Research groups have proposed new frameworks for evidence appraisal using interdisciplinary, pluralistic, patient-centric, and/or complex system paradigms to complement traditional hierarchical study design-driven approaches [120,142]. The COVID-19 pandemic has taught us that even without RCT evidence ‘we cannot do nothing’ [143].
4.2. Vaccine Acquisition Price
In CEA in which rVE estimates for aTIV/aQIV and HD-TIV/HD-QIV are comparable, vaccine acquisition price can be the major driver of CE estimates (Table 3). However, determining the price paid for vaccines is challenging, because vaccines are purchased from manufacturers with pricing subject to proprietary negotiation and rebates; some studies use adjustment methods to estimate vaccine acquisition and administration costs [62,144,145]. Furthermore, specific vaccine prices, or type of price (e.g., list, reimbursed price, etc.) are not always disclosed in CEA, which prevents robust comparative assessment.
4.3. Sensitivity/Scenario Analyses
Best practices in CEA call for interrogating model inputs and assumptions through one-way, multivariate, and probabilistic sensitivity and scenario analyses [30,146]. Varying model assumptions in a one-way or multivariate manner assists in identifying which parameters drive ICERs; these are often illustrated within tornado plots. Estimates from composite probabilistic sensitivity findings indicate how often ICERs may sit within willingness-to-pay thresholds; for example, when multiple parameters are randomly varied simultaneously across pre-set ranges, often illustrated on a cost-effectiveness plane. As public health authorities make recommendations that often remain in place for years before re-appraisal, decision-making incorporating assessment of the most extreme scenarios from CEA is of sound public interest. Furthermore, for infectious disease modeling, such as influenza, more methodologically complex dynamic models are valuable [31] because they are able to incorporate varying disease state disutility inputs, the likelihood of transition between different disease states, and the likely duration of disease states for a hypothetical cohort of individuals.
Many CEA of enhanced influenza vaccines account for aspects of parameter uncertainty (e.g., variance of rVE), although measures taken to assess methodological uncertainty (e.g., discount rates and time horizon) and structural certainty (e.g., static or dynamic models) were more difficult to assess. rVE is often varied in sensitivity/scenario analyses and identified as a key driver influencing cost-effectiveness estimates. Other CEA vary parameters not limited to vaccine coverage rate, VE at baseline, hospitalization rates, case fatality rates, outpatient complications, baseline utility, vaccine acquisition price, human capital costs, and discount rates for costs and/or outcomes.
4.4. Interpretation of ICERs
It is difficult to compare ICERs across studies, particularly from analyses performed in different markets/countries; however, aTIV/aQIV and HD-TIV/HD-QIV are estimated as consistently cost-effective compared with TIV/QIV across countries (Table 2 and Table 3). Between CEA studies, estimated ICER estimates may differ. Not overlooking variations between markets, including differences in vaccines prices, costs of disease management, and opportunity costs, current thinking is that variations in ICERs are generally determined by two core drivers: vaccine acquisition price and rVE. From a practical perspective, despite differences in the rVE inputted into models, comparable rVE has been seen between enhanced vaccines from RWE [11,92,132]; thus, the fundamental driver of ICER differences may be vaccine acquisition price. Currently, adjuvanted vaccines are often priced less than high-dose vaccines.
5. Future Directions and Conclusions
5.1. Future Directions
As novel vaccine technologies become available, including nucleoside-modified messenger RNA vaccines [147], RWE-driven CEA for comparative assessment may become even more important. ‘Big data’ may be a valuable source of RWE as datasets become more analyzable, particularly when these data allow for alignment with patient-centric EMB+ approaches [120,142]. RCTs will not be replaced, but there is a need to rely more on RWE obtained from high-quality studies; as such, developing frameworks to define and/or rank RWE may have merit [29].
The continuous development of CEA models that account for the uncertainty of influenza in future seasons relies on updated RWE and robust use of sensitivity analyses. Effectiveness values from across multiple seasons allow for policymakers to consider more realistic and representative estimates accrued over time. In traditional evidence hierarchies, RWE may be graded as lower strength than RCT data because retrospective and observational studies contain bias [120]; however, RWE is particularly important to assess for influenza. Recent lessons from COVID-19 pandemic responses have illustrated how RWE can guide rapid public health action [120]. Network meta-analyses, especially those with value-of-information analysis, may become best practice sources for effectiveness inputs. Increased understanding of methods to control bias in real-world studies, and frameworks to enhance transparency in RWE publications, may make RWE an increasingly more acceptable contributing data source for vaccine policymakers.
Influenza B, a more genetically stable virus than influenza A, becomes the predominant strain compared with influenza A approximately every 4–5 years and is generally perceived to lead to milder disease than influenza A [148]. Outcomes data have challenged this perception, with some studies finding similar or excess mortality associated with influenza B as compared with influenza A [148]. QIVs that protect against influenza B have achieved lower effectiveness rates than anticipated, suggesting that more study of influenza B is required [148]. Future RWE studies may support preparedness against future changes in the relative prevalence and impact of influenza A and B.
Secondary bacterial infections may account for a substantial proportion of influenza-related mortality during pandemics [149]. The most common co-infection pathogens include Streptococcus pneumoniae, Staphylococcus aureus, Streptococcus pyogenes, and Haemophilus influenzae [149]. The impact of influenza vaccination against secondary bacterial infections, or even in full, has not been widely studied clinically, but evidence suggests a protective effect against mortality outcomes related to invasive secondary disease [149]. Devising methods to identify and capture the value of potential protection against invasive bacterial disease within influenza vaccine CEA may allow for a more accurate representation of the value of influenza vaccines.
5.2. Conclusions
Across many studies, aTIV/aQIV and HD-TIV/HD-QIV demonstrate cost-effectiveness against TIV/QIV, despite diversity in model type, vaccine acquisition price, rVE estimate, and study perspective in individuals ≥ 65 years of age. aTIV demonstrates similar rVE compared with other enhanced vaccines across multiple influenza-related outcomes in older adults based on RWE.
Despite the bias inherent in their design, RWE studies provide crucial information needed in CEA. Sensitivity analyses within CEA are important to identify which parameters present greatest uncertainty, while probabilistic sensitivity analyses can provide an overall view of the robustness of output estimates. Well-constructed meta-analyses may reduce uncertainty regarding individual rVE point estimates and provide the best estimates of rVE. Although many variables are included in influenza vaccine CEA, rVE and vaccine acquisition price are key drivers of ICERs. In most markets, adjuvanted vaccines are priced lower than high-dose vaccines.
Overall, data from RWE and CEA provide clinical and economic rationales for the use of enhanced vaccines, such as aTIV/aQIV, in people ≥ 65 years of age. In addition to price considerations, countries that consider RWE when making vaccine recommendations have preferentially recommended aTIV/aQIV, HD-TIV/HD-QIV, and/or QIVr, in individuals ≥ 65 years of age [18,19,20,21,22].
Author Contributions
All authors made substantial contributions to the conception, analysis, and interpretation of literature review findings; critically reviewed draft manuscripts for important intellectual content and provided input into draft manuscripts; and provided final approval of the version to be published. All authors have read and agreed to the published version of the manuscript.
Funding
Seqirus provided funding to the medical communications agency Scion for medical writing support.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Acknowledgments
Medical writing support was provided by Helene Wellington, of Scion, London, UK, supported by Seqirus according to Good Publication Practice guidelines (https://www.acpjournals.org/doi/10.7326/M22-1460) (accessed on 30 May 2023).
Conflicts of Interest
M.P. has received honoraria from Seqirus for taking part in advisory boards. D.F. has received honoraria for participating in advisory boards with Merck, Sanofi-Pasteur, Seqirus, Pfizer, and AstraZeneca related to influenza, SARS-CoV-2, and pneumococcal vaccines. J.R.-A. has received honoraria from Seqirus for taking part in advisory boards. J.M.-Q. is an employee of CSL Seqirus. A.U. received institution funding for investigator-led studies from GSK, MSD, Seqirus, Takeda, and Sanofi-Pasteur. A.U. has also received honoraria from Seqirus and Takeda for acting as a speaker in congresses, and from GSK, Takeda, and Seqirus for taking part in advisory boards. She is a member of the Directory board of Sociedad Argentina de Vacunología y Epidemiologia (SAVE). N.G. received funding for investigator-led studies from GSK, MSD, Seqirus, Takeda, and Sanofi-Pasteur and GVDN. N.G. has received honoraria from Seqirus, Takeda, and Pfizer for acting as a speaker in congresses, and from GSK, Takeda, and Seqirus for taking part in advisory boards. S.M.P. has received honoraria from Seqirus for taking part in advisory boards. A.P. has received honoraria from Seqirus for taking part in advisory boards. V.H.N. received funding for conducting RWE and CEA on vaccines from Takeda, Seqirus, Pfizer, and Moderna.
References
- Putri, W.; Muscatello, D.J.; Stockwell, M.S.; Newall, A.T. Economic burden of seasonal influenza in the United States. Vaccine 2018, 36, 3960–3966. [Google Scholar] [CrossRef] [Scilit]
- Near, A.M.; Tse, J.; Young-Xu, Y.; Hong, D.K.; Reyes, C.M. Burden of influenza hospitalization among high-risk groups in the United States. BMC Health Serv. Res. 2022, 22, 1209. [Google Scholar] [CrossRef] [Scilit]
- Calabro, G.E.; D’Ambrosio, F.; Fallani, E.; Ricciardi, W. Influenza Vaccination Assessment according to a Value-Based Health Care Approach. Vaccines 2022, 10, 1675. [Google Scholar] [CrossRef] [Scilit]
- Grohskopf, L.A.; Blanton, L.H.; Ferdinands, J.M.; Chung, J.R.; Broder, K.R.; Talbot, H.K.; Morgan, R.L.; Fry, A.M. Prevention and Control of Seasonal Influenza with Vaccines: Recommendations of the Advisory Committee on Immunization Practices—United States, 2022–2023 Influenza Season. MMWR Recomm. Rep. 2022, 71, 1–28. [Google Scholar] [CrossRef] [Scilit]
- Bouvier, N.M.; Palese, P. The biology of influenza viruses. Vaccine 2008, 26 (Suppl. S4), D49–D53. [Google Scholar] [CrossRef] [Scilit]
- Petrova, V.N.; Russell, C.A. The evolution of seasonal influenza viruses. Nat. Rev. Microbiol. 2018, 16, 60. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization (WHO). Recommendations Announced for Influenza Vaccine Composition for the 2022–2023 Northern Hemisphere Influenza Season. Available online: https://www.who.int/news/item/25-02-2022-recommendations-announced-for-influenza-vaccine-composition-for-the-2022-2023-northern-hemisphere-influenza-season (accessed on 13 February 2023).
- Tenforde, M.W.; Kondor, R.J.G.; Chung, J.R.; Zimmerman, R.K.; Nowalk, M.P.; Jackson, M.L.; Jackson, L.A.; Monto, A.S.; Martin, E.T.; Belongia, E.A.; et al. Effect of Antigenic Drift on Influenza Vaccine Effectiveness in the United States-2019–2020. Clin. Infect. Dis. 2021, 73, e4244–e4250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crooke, S.N.; Ovsyannikova, I.G.; Poland, G.A.; Kennedy, R.B. Immunosenescence and human vaccine immune responses. Immun. Ageing 2019, 16, 25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haq, K.; McElhaney, J.E. Immunosenescence: Influenza vaccination and the elderly. Curr. Opin. Immunol. 2014, 29, 38–42. [Google Scholar] [CrossRef] [Scilit]
- Gartner, B.C.; Weinke, T.; Wahle, K.; Kwetkat, A.; Beier, D.; Schmidt, K.J.; Schwarz, T.F. Importance and value of adjuvanted influenza vaccine in the care of older adults from a European perspective—A systematic review of recently published literature on real-world data. Vaccine 2022, 40, 2999–3008. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ciabattini, A.; Nardini, C.; Santoro, F.; Garagnani, P.; Franceschi, C.; Medaglini, D. Vaccination in the elderly: The challenge of immune changes with aging. Semin. Immunol. 2018, 40, 83–94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calabro, S.; Tortoli, M.; Baudner, B.C.; Pacitto, A.; Cortese, M.; O’Hagan, D.T.; De Gregorio, E.; Seubert, A.; Wack, A. Vaccine adjuvants alum and MF59 induce rapid recruitment of neutrophils and monocytes that participate in antigen transport to draining lymph nodes. Vaccine 2011, 29, 1812–1823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khurana, S.; Verma, N.; Yewdell, J.W.; Hilbert, A.K.; Castellino, F.; Lattanzi, M.; Del Giudice, G.; Rappuoli, R.; Golding, H. MF59 adjuvant enhances diversity and affinity of antibody-mediated immune response to pandemic influenza vaccines. Sci. Transl. Med. 2011, 3, 85ra48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seqirus. FLUAD TETRA Summary of Product Characteristics. Available online: https://www.ema.europa.eu/en/documents/product-information/fluad-tetra-epar-product-information_en.pdf (accessed on 12 April 2021).
- Arunachalam, A.B.; Post, P.; Rudin, D. Unique features of a recombinant haemagglutinin influenza vaccine that influence vaccine performance. NPJ Vaccines 2021, 6, 144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Observatory on Health Systems and Policies. The Organization and Delivery of Vaccination Services in the European Union. Available online: https://health.ec.europa.eu/system/files/2018-11/2018_vaccine_services_en_0.pdf (accessed on 13 February 2023).
- National Center for Immunization & Respiratory Diseases (US) Influenza Division; Advisory Committee on Immunization Practices. Influenza Vaccines for Older Adults: GRADE Summary. Available online: https://stacks.cdc.gov/view/cdc/114834 (accessed on 13 October 2022).
- Joint Committee on Vaccination and Immunisation. Advice on Influenza Vaccines for 2021/22. Available online: https://app.box.com/s/t5ockz9bb6xw6t2mrrzb144njplimfo0/file/737845224649 (accessed on 31 January 2022).
- Australia Government Department of Health and Aged Care. 2022 Seasonal Influenza Vaccines. Available online: https://www.tga.gov.au/news/media-releases/2022-seasonal-influenza-vaccines (accessed on 6 November 2022).
- Advisory Committee on Immunization Practices. Prevention and Control of Seasonal Influenza with Vaccines: Recommendations of the Advisory Committee on Immunization Practices (ACIP)—United States, 2022–2023. Available online: https://www.cdc.gov/flu/professionals/acip/summary/summary-recommendations.htm (accessed on 13 February 2023).
- Ministerio de Salud Argentina. II Reunión Ordinaria de la Comisión Nacional de Inmunizaciones, 22 de Octubre de 2020. Available online: https://www.argentina.gob.ar/sites/default/files/2020-10-22_acta-conain.pdf (accessed on 4 May 2023).
- Ultsch, B.; Damm, O.; Beutels, P.; Bilcke, J.; Brüggenjürgen, B.; Gerber-Grote, A.; Greiner, W.; Hanquet, G.; Hutubessy, R.; Jit, M.; et al. Methods for Health Economic Evaluation of Vaccines and Immunization Decision Frameworks: A Consensus Framework from a European Vaccine Economics Community. Pharmacoeconomics 2016, 34, 227–244. [Google Scholar] [CrossRef] [Scilit]
- Hall, A.J. The United Kingdom Joint Committee on Vaccination and Immunisation. Vaccine 2010, 28 (Suppl. S1), A54–A57. [Google Scholar] [CrossRef] [Scilit]
- Jones, D.S.; Podolsky, S.H. The history and fate of the gold standard. Lancet 2015, 385, 1502–1503. [Google Scholar] [CrossRef] [Scilit]
- Schad, F.; Thronicke, A. Real-World Evidence-Current Developments and Perspectives. Int. J. Environ. Res. Public Health 2022, 19, 159. [Google Scholar] [CrossRef] [Scilit]
- Frieden, T.R. Evidence for health decision making—Beyond randomized, controlled trials. N. Engl. J. Med. 2017, 377, 465–475. [Google Scholar] [CrossRef] [Scilit]
- Katkade, V.B.; Sanders, K.N.; Zou, K.H. Real world data: An opportunity to supplement existing evidence for the use of long-established medicines in health care decision making. J. Multidiscip. Healthc. 2018, 11, 295–304. [Google Scholar] [CrossRef] [Scilit]
- Burns, L.; Roux, N.L.; Kalesnik-Orszulak, R.; Christian, J.; Hukkelhoven, M.; Rockhold, F.; O’Donnell, J. Real-world evidence for regulatory decision-making: Guidance from around the world. Clin. Ther. 2022, 44, 420–437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bowrin, K.; Briere, J.B.; Levy, P.; Millier, A.; Clay, E.; Toumi, M. Cost-effectiveness analyses using real-world data: An overview of the literature. J. Med. Econ. 2019, 22, 545–553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loong, D.; Pham, B.; Amiri, M.; Saunders, H.; Mishra, S.; Radhakrishnan, A.; Rodrigues, M.; Yeung, M.W.; Muller, M.P.; Straus, S.E.; et al. Systematic Review on the Cost-Effectiveness of Seasonal Influenza Vaccines in Older Adults. Value Health 2022, 25, 1439–1458. [Google Scholar] [CrossRef] [Scilit]
- Shields, G.E.; Elvidge, J.; Davies, L.M. A systematic review of economic evaluations of seasonal influenza vaccination for the elderly population in the European Union. BMJ Open 2017, 7, e014847. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Colrat, F.; Thommes, E.; Largeron, N.; Alvarez, F.P. Economic evaluation of high-dose inactivated influenza vaccine in adults aged >/=65 years: A systematic literature review. Vaccine 2021, 39 (Suppl. S1), A42–A50. [Google Scholar] [CrossRef] [Scilit]
- Loperto, I.; Simonetti, A.; Nardone, A.; Triassi, M. Use of adjuvanted trivalent influenza vaccine in older-age adults: A systematic review of economic evidence. Hum. Vaccin. Immunother. 2019, 15, 1035–1047. [Google Scholar] [CrossRef] [Scilit]
- Walker, D.G.; Wilson, R.F.; Sharma, R.; Bridges, J.; Niessen, L.; Bass, E.B.; Frick, K. AHRQ Methods for Effective Health Care. In Best Practices for Conducting Economic Evaluations in Health Care: A Systematic Review of Quality Assessment Tools; Agency for Healthcare Research and Quality (US): Rockville, MD, USA, 2012. [Google Scholar]
- Bragazzi, N.L.; Orsi, A.; Ansaldi, F.; Gasparini, R.; Icardi, G. Fluzone® intra-dermal (Intanza®/Istivac® Intra-dermal): An updated overview. Hum. Vaccin. Immunother. 2016, 12, 2616–2627. [Google Scholar] [CrossRef] [Scilit]
- Public Health Agency of Canada. Canada Communicable Disease Report. Available online: https://www.canada.ca/content/dam/phac-aspc/migration/phac-aspc/publicat/ccdr-rmtc/11vol37/acs-dcc-6/assets/pdf/acs-dcc-6-eng.pdf (accessed on 27 March 2023).
- Sanofi Pasteur. FLUZONE® High-Dose. Influenza Virus Vaccine Trivalent Types A and B (Split Virion). Product Monograph. Available online: https://products.sanofi.ca/en/fluzone-hd.pdf (accessed on 8 May 2023).
- Sanofi Pasteur. SupemtekTM Quadrivalent Recombinant Influenza Vaccine. Product Monograph. Available online: https://pdf.hres.ca/dpd_pm/00059645.PDF (accessed on 8 May 2023).
- Food and Drug Administration. FLUAD® Seqirus Inc US Package Insert. Available online: https://www.fda.gov/media/94583/download (accessed on 1 June 2021).
- Seqirus. FLUAD QUADRIVALENT (Influenza Vaccine, Adjuvanted). Available online: https://www.fda.gov/media/135432/download (accessed on 2 June 2021).
- Sanofi Pasteur. Fluzone® High-Dose Quadrivalent. Available online: www.fda.gov/media/132238/download (accessed on 19 August 2021).
- Protein Sciences Corporation. Flublok Quadrivalent (Influenza Vaccine, Recombinant). Available online: https://www.fda.gov/media/123144/download (accessed on 23 March 2023).
- NHS England. Update on Use of Adjuvanted Trivalent Flu Vaccine for 2018–19 Flu Season. Available online: https://www.england.nhs.uk/wp-content/uploads/2017/12/2018-19-aTIV-vaccine.pdf (accessed on 8 May 2023).
- UK Health Security Agency. The National Influenza Immunisation Programme 2022 to 2023: Information for Healthcare Practitioners. Available online: https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/1105068/Flu-information-for-HCPs-2022-to-2023-20Sept22.pdf (accessed on 8 May 2023).
- UK Medicines and Healthcare products Regulatory Agency. Innovation: MHRA’s Speedy Approval of High Dose Flu Vaccine Demonstrates Flexibilities in National Applications. Available online: https://www.gov.uk/government/case-studies/innovation-mhras-speedy-approval-of-high-dose-flu-vaccine-demonstrates-flexibilities-in-national-applications (accessed on 8 May 2023).
- Sanofi Pasteur. Press Release: Sanofi to Build New Facility in Canada to Increase Global Availability of High-Dose Influenza Vaccine. Available online: https://ml-eu.globenewswire.com/Resource/Download/22550b60-1c00-4977-a2e7-7e43f2e59050 (accessed on 8 May 2023).
- Seqirus. Fluad, Suspension for Injection in Pre-Filled Syringe. Available online: https://www.medicines.org.uk/emc/product/9223/smpc (accessed on 2 June 2021).
- Sanofi Pasteur. Supemtek Quadrivalent Influenza Vaccine (Recombinant, Prepared in Cell Culture). Available online: https://www.ema.europa.eu/en/medicines/human/EPAR/supemtek (accessed on 23 March 2023).
- DiazGranados, C.A.; Dunning, A.J.; Kimmel, M.; Kirby, D.; Treanor, J.; Collins, A.; Pollak, R.; Christoff, J.; Earl, J.; Landolfi, V.; et al. Efficacy of high-dose versus standard-dose influenza vaccine in older adults. N. Engl. J. Med. 2014, 371, 635–645. [Google Scholar] [CrossRef] [Scilit]
- Mullikin, M.; Tan, L.; Jansen, J.P.; Van Ranst, M.; Farkas, N.; Petri, E. A Novel Dynamic Model for Health Economic Analysis of Influenza Vaccination in the Elderly. Infect. Dis. Ther. 2015, 4, 459–487. [Google Scholar] [CrossRef] [Scilit]
- Barbieri, M.; Capri, S. Analisi Di Costo-Efficacia Della Vaccinazione Antinfluenzale Nella Popolazione Anziana In Italia: Confronto Tra Vaccino Inattivato Trivalente Adiuvato Con Mf59® E Altri Tipi Di Vaccini. QIJPH 2017, 6, 69–82. [Google Scholar]
- Capri, S.; Barbieri, M.; de Waure, C.; Boccalini, S.; Panatto, D. Cost-effectiveness analysis of different seasonal influenza vaccines in the elderly Italian population. Hum. Vaccin. Immunother. 2018, 14, 1331–1341. [Google Scholar] [CrossRef] [Scilit]
- Yun, J.W.; Choi, M.J.; Shin, G.S.; Lim, J.O.; Noh, J.Y.; Kim, Y.K.; Song, J.Y.; Kim, W.J.; Choi, S.E.; Cheong, H.J. Cost-effectiveness of influenza vaccine strategies for the elderly in South Korea. PLoS ONE 2019, 14, e0209643. [Google Scholar] [CrossRef] [Scilit]
- Thorrington, D.; van Leeuwen, E.; Ramsay, M.; Pebody, R.; Baguelin, M. Assessing optimal use of the standard dose adjuvanted trivalent seasonal influenza vaccine in the elderly. Vaccine 2019, 37, 2051–2056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, V.H.; Vizzotti, C.; Uruena, A.; Giglio, N.; Magneres, C.; Richmond, H. Cost-effectiveness of introducing an MF59-adjuvanted trivalent influenza vaccine for older adults in Argentina. Vaccine 2020, 38, 3682–3689. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, V.H.; D’Agostino, P.; Phalippon, N.; McCracken, A.; Mould-Quevedo, J. Budget Impact Analysis of the MF59-Adjuvanted Quadrivalent Influenza Vaccine in the Older Adult French Population. In Proceedings of the 8th European Scientific Working Group on Influenza (ESWI), Online, 4–7 December 2021. [Google Scholar]
- Kohli, M.A.; Maschio, M.; Cartier, S.; Mould-Quevedo, J.; Fricke, F.U. The cost-effectiveness of vaccination of older adults with an MF59-adjuvanted quadrivalent influenza vaccine compared to other available quadrivalent vaccines in Germany. Vaccines 2022, 10, 1386. [Google Scholar] [CrossRef] [Scilit]
- Choi, M.J.; Yun, J.W.; Song, J.Y.; Ko, K.; Mould, J.F.; Cheong, H.J. A Comparative Analysis of Influenza-Associated Disease Burden with Different Influenza Vaccination Strategies for the Elderly Population in South Korea. Vaccines 2022, 10, 1387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calabro, G.E.; Boccalini, S.; Panatto, D.; Rizzo, C.; Di Pietro, M.L.; Abreha, F.M.; Ajelli, M.; Amicizia, D.; Bechini, A.; Giacchetta, I.; et al. The New Quadrivalent Adjuvanted Influenza Vaccine for the Italian Elderly: A Health Technology Assessment. Int. J. Environ. Res. Public Health 2022, 19, 4166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fochesato, A.; Sottile, S.; Pugliese, A.; Marquez-Pelaez, S.; Toro-Diaz, H.; Gani, R.; Alvarez, P.; Ruiz-Aragon, J. An Economic Evaluation of the Adjuvanted Quadrivalent Influenza Vaccine Compared with Standard-Dose Quadrivalent Influenza Vaccine in the Spanish Older Adult Population. Vaccines 2022, 10, 1360. [Google Scholar] [CrossRef] [Scilit]
- Jacob, J.; Biering-Sørensen, T.; Holger Ehlers, L.; Edwards, C.H.; Mohn, K.G.-I.; Nilsson, A.; Hjelmgren, J.; Ma, W.; Sharma, Y.; Ciglia, E.; et al. Cost-Effectiveness of Vaccination of Older Adults with an MF59®-Adjuvanted Quadrivalent Influenza Vaccine Compared to Standard-Dose and High-Dose Vaccines in Denmark, Norway, and Sweden. Vaccines 2023, 11, 753. [Google Scholar] [CrossRef] [Scilit]
- Kohli, M.A.; Maschio, M.; Mould-Quevedo, J.F.; Drummond, M.; Weinstein, M.C. The cost-effectiveness of an adjuvanted quadrivalent influenza vaccine in the United Kingdom. Hum. Vaccin. Immunother. 2021, 17, 4603–4610. [Google Scholar] [CrossRef] [Scilit]
- Ruiz-Aragon, J.; Marquez-Pelaez, S.; Gani, R.; Alvarez, P.; Guerrero-Luduena, R. Cost-Effectiveness and Burden of Disease for Adjuvanted Quadrivalent Influenza Vaccines Compared to High-Dose Quadrivalent Influenza Vaccines in Elderly Patients in Spain. Vaccines 2022, 10, 176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chit, A.; Becker, D.L.; DiazGranados, C.A.; Maschio, M.; Yau, E.; Drummond, M. Cost-effectiveness of high-dose versus standard-dose inactivated influenza vaccine in adults aged 65 years and older: An economic evaluation of data from a randomised controlled trial. Lancet Infect. Dis. 2015, 15, 1459–1466. [Google Scholar] [CrossRef] [Scilit]
- Chit, A.; Roiz, J.; Briquet, B.; Greenberg, D.P. Expected cost effectiveness of high-dose trivalent influenza vaccine in US seniors. Vaccine 2015, 33, 734–741. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Becker, D.L.; Chit, A.; DiazGranados, C.A.; Maschio, M.; Yau, E.; Drummond, M. High-dose inactivated influenza vaccine is associated with cost savings and better outcomes compared to standard-dose inactivated influenza vaccine in Canadian seniors. Hum. Vaccin. Immunother. 2016, 12, 3036–3042. [Google Scholar] [CrossRef] [Scilit]
- Raviotta, J.M.; Smith, K.J.; DePasse, J.; Brown, S.T.; Shim, E.; Nowalk, M.P.; Zimmerman, R.K. Cost-Effectiveness and Public Health Effect of Influenza Vaccine Strategies for U.S. Elderly Adults. J. Am. Geriatr. Soc. 2016, 64, 2126–2131. [Google Scholar] [CrossRef] [Scilit]
- Skinner, L.; Jacob, J.; Bianic, F.; Carroll, S.; Bricout, H.; Largeron, N.; Alvarez, F.P.; Clark-Wright, J. PIN30—An Economic Model to Estimate the Cost-Effectiveness of Trivalent Influenza Vaccine High Dose for the Elderly Population in England And Wales. Value Health 2018, 21, S225. [Google Scholar] [CrossRef] [Scilit]
- Largeron, N.; Manton, A.; Net, P.; Choi, S.; Becker, D.L.; Bianic, F.; Jacob, J.; Maschio, M. PIN22—An Economic Model To Estimate The Public Health Impact and Cost-Effectiveness of Vaccination of Seniors with Fluzone High Dose Influenza Vaccine in Australia. Value Health 2018, 21, S65. [Google Scholar] [CrossRef] [Scilit]
- Basile, M.; Rumi, F.; Cicchetti, A.; Nascimento Costa, M.; Bianic, F.; Noelle, H.; Alvarez, F.; Muzii, B. Cost-Effectiveness of Quadrivalent Influenza Vaccine High Dose Versus Standard Dose Quadrivalent Influenza Vaccine in Italy. In Proceedings of the 7th European Scientific Working Group on Influenza (ESWI), Virtual, 6–9 December 2021. [Google Scholar]
- Borges, M.; Lopes, R.; Bricout, H.; Martins, M.; de Courville, C.; Miguel, L.S. Public Health Benefit of Switching to High Dose Quadrivalent Vaccine for Influenza Seasonal Vaccination in Portuguese Elderly Population. In Proceedings of the Professional Society for Health Economics and Outcomes Research (ISPOR), Online, 17–20 May 2020. [Google Scholar]
- De Courville, C.; Chevalier, P.; Borms, M.; Bricout, H.; Petit, C.; Alvarez, F. Costs-Effectiveness of Influenza Vaccination with a High Dose Quadrivalent Vaccine of the Belgian Elderly Population. In Proceedings of the 8th European Scientific Working Group on Influenza (ESWI), Online, 4–7 December 2021. [Google Scholar]
- Alvarez, F.P.; Chevalier, P.; Borms, M.; Bricout, H.; Marques, C.; Soininen, A.; Sainio, T.; Petit, C.; de Courville, C. Cost-effectiveness of influenza vaccination with a high dose quadrivalent vaccine of the elderly population in Belgium, Finland, and Portugal. J. Med. Econ. 2023, 26, 710–719. [Google Scholar] [CrossRef] [Scilit]
- Puig-Barberà, J.; Natividad-Sancho, A.; Calabuig-Pérez, J.; Lluch-Rodrigo, J.A.; Pastor-Villalba, E.; Martínez-Úbeda, S.; Pérez-Vilar, S.; Díez-Domingo, J. MF59-adjuvanted and virosomal influenza vaccines for preventing influenza hospitalization in older people: Comparative effectiveness using the Valencia health care information system. Vaccine 2013, 31, 3995–4002. [Google Scholar] [CrossRef] [Scilit]
- Net, P.; Colrat, F.; Nascimento Costa, M.; Bianic, F.; Thommes, E.; Alvarez, F.P. Estimating public health and economic benefits along 10 years of Fluzone® High Dose in the United States. Vaccine 2021, 39 (Suppl. S1), A56–A69. [Google Scholar] [CrossRef] [Scilit]
- Rumi, F.; Basile, M.; Cicchetti, A.; Alvarez, F.P.; Muzii, B.; Azzi, M.V. Cost Effectiveness of High Dose Quadrivalent Influenza Vaccine (HD-QIV) Versus Adjuvanted Quadrivalent Influenza Vaccine (aQIV) in the Italian Elderly Population. In Proceedings of the 8th European Scientific Working Group on Influenza (ESWI), Online, 4–7 December 2021. [Google Scholar]
- Redondo, E.; Drago, G.; Lopez-Belmonte, J.L.; Guillen, J.M.; Bricout, H.; Alvarez, F.P.; Callejo, D.; Gil de Miguel, A. Cost-utility analysis of influenza vaccination in a population aged 65 years or older in Spain with a high-dose vaccine versus an adjuvanted vaccine. Vaccine 2021, 39, 5138–5145. [Google Scholar] [CrossRef] [Scilit]
- Mattock, R.; Gibbons, I.; Moss, J.; Mealing, S.; Largeron, N.; Carroll, S.; Alvarez, F.P. Cost-effectiveness of high dose versus adjuvanted trivalent influenza vaccines in England and Wales. J. Med. Econ. 2021, 24, 1261–1271. [Google Scholar] [CrossRef] [Scilit]
- Drago, G.R.E.; Gil de Miguel, A.; Alvarex, F.; Costa, M.; Bianic, F.; Noelle, H.; Velasco, D.; Lopez-Belmonte, J.L. Cost-Effectiveness of Quadrivalent Influenza Vaccine High Dose Versus Adjuvanted Trivalent Influenza Vaccine in Spain. In Proceedings of the ESWI Conference, Online, 6–9 December 2020. [Google Scholar]
- van Aalst, R.; Gravenstein, S.; Mor, V.; Mahmud, S.M.; Wilschut, J.; Postma, M.; Chit, A. Economic Assessment of High-Dose Versus Adjuvanted Influenza Vaccine: An Evaluation of Hospitalization Costs Based on a Cohort Study. Vaccines 2021, 9, 1065. [Google Scholar] [CrossRef] [Scilit]
- Lee, B.Y.; Ercius, A.K.; Smith, K.J. A predictive model of the economic effects of an influenza vaccine adjuvant for the older adult (age 65 and over) population. Vaccine 2009, 27, 2251–2257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fisman, D.N.; Tuite, A.R. Estimation of the health impact and cost-effectiveness of influenza vaccination with enhanced effectiveness in Canada. PLoS ONE 2011, 6, e27420. [Google Scholar] [CrossRef] [Scilit]
- Jefferson, T.; Di Pietrantonj, C.; Al-Ansary, L.A.; Ferroni, E.; Thorning, S.; Thomas, R.E. Vaccines for preventing influenza in the elderly. Cochrane Database Syst. Rev. 2010, CD004876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mannino, S.; Villa, M.; Apolone, G.; Weiss, N.S.; Groth, N.; Aquino, I.; Boldori, L.; Caramaschi, F.; Gattinoni, A.; Malchiodi, G.; et al. Effectiveness of adjuvanted influenza vaccination in elderly subjects in northern Italy. Am. J. Epidemiol. 2012, 176, 527–533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruiz-Aragón, J.; Grande Tejada, A.M.; Márquez-Peláez, S.; García-Cenoz, M. Estimación del impacto de la vacunación antigripal con adyuvante MF59 en población mayor de 64 años para el Sistema Nacional de Salud: Efectos y costes. Vacunas 2015, 16, 6–11. [Google Scholar] [CrossRef] [Scilit]
- Coudeville, L.; Andre, P.; Bailleux, F.; Weber, F.; Plotkin, S. A new approach to estimate vaccine efficacy based on immunogenicity data applied to influenza vaccines administered by the intradermal or intramuscular routes. Hum. Vaccin. 2010, 6, 841–848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perez-Rubio, A.; Eiros, J.M. Economic and Health impact of influenza vaccination with adjuvant MF59 in population over 64 years in Spain. Rev. Esp. Quimioter. 2018, 31, 43–52. [Google Scholar]
- Jefferson, T.; Di Pietrantonj, C.; Rivetti, A.; Bawazeer, G.A.; Al-Ansary, L.A.; Ferroni, E. Vaccines for preventing influenza in healthy adults. Cochrane Database Syst Rev 2010, CD001269. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Chit, A.; Soobiah, C.; Hallett, D.; Meier, G.; Chen, M.H.; Tashkandi, M.; Bauch, C.T.; Loeb, M. Comparing influenza vaccine efficacy against mismatched and matched strains: A systematic review and meta-analysis. BMC Med. 2013, 11, 153. [Google Scholar] [CrossRef] [Scilit]
- Van Buynder, P.G.; Konrad, S.; Van Buynder, J.L.; Brodkin, E.; Krajden, M.; Ramler, G.; Bigham, M. The comparative effectiveness of adjuvanted and unadjuvanted trivalent inactivated influenza vaccine (TIV) in the elderly. Vaccine 2013, 31, 6122–6128. [Google Scholar] [CrossRef] [Scilit]
- Coleman, B.L.; Sanderson, R.; Haag, M.D.M.; McGovern, I. Effectiveness of the MF59-adjuvanted trivalent or quadrivalent seasonal influenza vaccine among adults 65 years of age or older, a systematic review and meta-analysis. Influenza Other Respir. Viruses 2021, 15, 813–823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Angerami, R.; Pires, B.; Mould-Quevedo, J.F.; Magneres, C.; Kfouri, R. Cost-Effectiveness of Introducing an Mf59-Adjuvanted Trivalent Influenza Vaccine for Older Adults in Brazil. In Proceedings of the 15th Vaccine Congress, Online, 19 April 2021. [Google Scholar]
- Belongia, E.A.; Simpson, M.D.; King, J.P.; Sundaram, M.E.; Kelley, N.S.; Osterholm, M.T.; McLean, H.Q. Variable influenza vaccine effectiveness by subtype: A systematic review and meta-analysis of test-negative design studies. Lancet Infect. Dis. 2016, 16, 942–951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boccalini, S.; Pariani, E.; Calabrò, G.E.; De Waure, C.; Panatto, D.; Amicizia, D.; Lai, P.L.; Rizzo, C.; Amodio, E.; Vitale, F.; et al. Health Technology Assessment (HTA) of the introduction of influenza vaccination for Italian children with Fluenz Tetra®. J. Prev. Med. Hyg. 2021, 62, E1–E118. [Google Scholar] [CrossRef]
- Beyer, W.E.; McElhaney, J.; Smith, D.J.; Monto, A.S.; Nguyen-Van-Tam, J.S.; Osterhaus, A.D. Cochrane re-arranged: Support for policies to vaccinate elderly people against influenza. Vaccine 2013, 31, 6030–6033. [Google Scholar] [CrossRef] [Scilit]
- Cheng, X.; Roïz, J. PIN34—Cost-Utility analysis of three types of Influenza Vaccines (Trivalent, Trivalent High dose and quadrivalent) in adults aged 65 and Older Under Universal Influenza Immunization Program (UIIP) In Ontario, Canada. Value Health 2015, 18, A233–A234. [Google Scholar] [CrossRef] [Scilit]
- Molinari, N.A.; Ortega-Sanchez, I.R.; Messonnier, M.L.; Thompson, W.W.; Wortley, P.M.; Weintraub, E.; Bridges, C.B. The annual impact of seasonal influenza in the US: Measuring disease burden and costs. Vaccine 2007, 25, 5086–5096. [Google Scholar] [CrossRef] [Scilit]
- Crépey, P.; Skinner, L.; Carroll, S.; Bricout, H.; Jacob, J.; Largeron, N.; Alvarez, F.P.; Clark-Wright, J. PIN33—A Dynamic Transmission Model to Estimate the Public Health Impact and Cost-Effectiveness of Trivalent Influenza Vaccine High Dose for the Elderly Population in England and Wales. Value Health 2018, 21, S226. [Google Scholar] [CrossRef] [Scilit]
- Clements, K.M.; Meier, G.; McGarry, L.J.; Pruttivarasin, N.; Misurski, D.A. Cost-effectiveness analysis of universal influenza vaccination with quadrivalent inactivated vaccine in the United States. Hum. Vaccin. Immunother. 2014, 10, 1171–1180. [Google Scholar] [CrossRef] [Scilit]
- Shireman, T.I.; Ogarek, J.; Gozalo, P.; Zhang, T.; Mor, V.; Davidson, H.E.; Han, L.; Taljaard, M.; Gravenstein, S. Cost Benefit of High-Dose vs. Standard-Dose Influenza Vaccine in a Long-Term Care Population During an A/H1N1-Predominant Influenza Season. J. Am. Med. Dir. Assoc. 2019, 20, 874–878. [Google Scholar] [CrossRef] [Scilit]
- Govaert, T.M.; Thijs, C.T.; Masurel, N.; Sprenger, M.J.; Dinant, G.J.; Knottnerus, J.A. The efficacy of influenza vaccination in elderly individuals. A randomized double-blind placebo-controlled trial. JAMA 1994, 272, 1661–1665. [Google Scholar] [CrossRef] [Scilit]
- Zeevat, F.; Wilschut, J.C.; Boersma, C.; Postma, M.J. Reducing Hospital Capacity Needs for Seasonal Respiratory Infections: The case of switching to High-Dose influenza vaccine for Dutch older adults. Value Health 2023, 26, 461–464. [Google Scholar] [CrossRef] [Scilit]
- Drago Manchón, G.; López-Belmonte, J.L.; Bricout, H.; de Courville, C. Public Health Benefits of Switching into a Recombinant Quadrivalent Vaccine in the Spanish Murcia and Valencia Regions the Recommended Adult Population (18+) for Influenza Seasonal Vaccination. Proceedings of 8th European Scientific Working Group on Influenza (ESWI), Online, 4–7 December 2021. [Google Scholar]
- Ruiz-Aragón, J.; Márquez-Peláez, S. An Economic Comparison in the Elderly of Adjuvanted Quadrivalent Influenza Vaccine with Recombinant Quadrivalent Influenza Vaccine in Spain. Vaccines 2023, 11, 427. [Google Scholar] [CrossRef] [Scilit]
- Skinner, L.; Chit, A.; Bianic, F.; Largeron, N.; Alvarez, F.P.; Carroll, S. PIN20 Expected Cost-Effectiveness of High Dose Versus Adjuvanted Standard Dose Trivalent Influenza Vaccines in England and Wales: Assessments Using Direct and Indirect Comparative Effectiveness Data. Value Health 2019, 22, S643. [Google Scholar] [CrossRef] [Scilit]
- Gibbons, I.; Davidson, C.; Clark-Wright, J.; Miller, C.; Carroll, S.; Costa, M.; Bricout, H.; Alvarez, F.P. PIN60 Cost-Effectiveness of Quadrivalent Influenza Vaccine High Dose Versus Adjuvanted Standard Dose Trivalent Influenza Vaccine in England. Value Health 2020, 23, S555. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.K.H.; Lam, G.K.L.; Shin, T.; Kim, J.; Krishnan, A.; Greenberg, D.P.; Chit, A. Efficacy and effectiveness of high-dose versus standard-dose influenza vaccination for older adults: A systematic review and meta-analysis. Expert Rev. Vaccines 2018, 17, 435–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, V.H.; Roy, B. Modelling the Economic Impact of lnfluenza Vaccine Programs with the Cell-Based Quadrivalent Influenza Vaccine and Adjuvanted Trivalent Influenza Vaccine in Canada. Vaccines 2022, 10, 1257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, V.H.; Hilsky, Y.; Mould-Quevedo, J. The Epidemiological and Economic Impact of a Cell-Based Quadrivalent Influenza Vaccine in Adults in the US: A Dynamic Modeling Approach. Vaccines 2021, 9, 1095. [Google Scholar] [CrossRef] [Scilit]
- Van Aalst, R.; Gravenstein, S.; Mor, V.; Mahmud, S.M.; Wilschut, J.; Postma, M.; Chit, A. Comparative effectiveness of high dose versus adjuvanted influenza vaccine: A retrospective cohort study. Vaccine 2020, 38, 372–379. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rondy, M.; El Omeiri, N.; Thompson, M.G.; Levêque, A.; Moren, A.; Sullivan, S.G. Effectiveness of influenza vaccines in preventing severe influenza illness among adults: A systematic review and meta-analysis of test-negative design case-control studies. J. Infect. 2017, 75, 381–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dunkle, L.M.; Izikson, R.; Patriarca, P.; Goldenthal, K.L.; Muse, D.; Callahan, J.; Cox, M.M.J. Efficacy of Recombinant Influenza Vaccine in Adults 50 Years of Age or Older. N. Engl. J. Med. 2017, 376, 2427–2436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Izurieta, H.S.; Lu, M.; Kelman, J.; Lu, Y.; Lindaas, A.; Loc, J.; Pratt, D.; Wei, Y.; Chillarige, Y.; Wernecke, M.; et al. Comparative Effectiveness of Influenza Vaccines Among US Medicare Beneficiaries Ages 65 Years and Older during the 2019–2020 Season. Clin. Infect. Dis. 2021, 73, e4251–e4259. [Google Scholar] [CrossRef] [Scilit]
- Jayawardana, S.; Mossialos, E. How should economic evaluation be used to measure value and set priorities in health care? AMA J. Ethics 2021, 23, E613–E618. [Google Scholar] [CrossRef] [Scilit]
- Husereau, D.; Drummond, M.; Augustovski, F.; de Bekker-Grob, E.; Briggs, A.H.; Carswell, C.; Caulley, L.; Chaiyakunapruk, N.; Greenberg, D.; Loder, E.; et al. Consolidated Health Economic Evaluation Reporting Standards (CHEERS) 2022 Explanation and Elaboration: A Report of the ISPOR CHEERS II Good Practices Task Force. Value Health 2022, 25, 10–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Evaluation of Influenza Vaccine Effectiveness: A Guide to the Design and Interpretation of Observational Studies. Available online: https://apps.who.int/iris/bitstream/handle/10665/255203/9789241512121-eng.pdf (accessed on 13 February 2023).
- World Health Organization (WHO). Guidance on the Economic Evaluation of Influenza Vaccination. Available online: https://apps.who.int/iris/bitstream/handle/10665/250086/WHO-IVB-16.05-eng.pdf (accessed on 6 March 2023).
- Mori, M.; Oura, A.; Ohnishi, H.; Washio, M. Confounding in evaluating the effectiveness of influenza vaccine. Vaccine 2008, 26, 6459–6461. [Google Scholar] [CrossRef] [Scilit]
- Greenhalgh, T.; Fisman, D.; Cane, D.J.; Oliver, M.; Macintyre, C.R. Adapt or die: How the pandemic made the shift from EBM to EBM+ more urgent. BMJ Evid. Based Med. 2022, 27, 253–260. [Google Scholar] [CrossRef] [Scilit]
- Domnich, A.; Panatto, D.; Pariani, E.; Napoli, C.; Chironna, M.; Manini, I.; Rizzo, C.; Orsi, A.; Icardi, G.; IT-BIVE-HOSP Network Study Group. Relative effectiveness of the adjuvanted vs non-adjuvanted seasonal influenza vaccines against severe laboratory-confirmed influenza among hospitalized Italian older adults. Int. J. Infect. Dis. 2022, 125, 164–169. [Google Scholar] [CrossRef] [Scilit]
- Ma, L.-L.; Wang, Y.-Y.; Yang, Z.-H.; Huang, D.; Weng, H.; Zeng, X.-T. Methodological quality (risk of bias) assessment tools for primary and secondary medical studies: What are they and which is better? Mil. Med. Res. 2020, 7, 7. [Google Scholar] [CrossRef] [Scilit]
- Wang, S.V.; Pinheiro, S.; Hua, W.; Arlett, P.; Uyama, Y.; Berlin, J.A.; Bartels, D.B.; Kahler, K.H.; Bessette, L.G.; Schneeweiss, S. STaRT-RWE: Structured template for planning and reporting on the implementation of real world evidence studies. BMJ 2021, 372, m4856. [Google Scholar] [CrossRef] [Scilit]
- Khambholja, K.; Gehani, M. Use of Structured Template and Reporting Tool for Real-World Evidence Template for Critical Appraisal of the Quality of Reporting of Real-World Evidence Studies: A Systematic Review. Value Health 2023, 26, 427–434. [Google Scholar] [CrossRef] [Scilit]
- Pelton, S.; Divino, V.; Shah, D.; Mould-Quevedo, J.; DeKoven, M.; Krishnarajah, G.; Postma, M. Evaluating the relative vaccine effectiveness of adjuvanted trivalent influenza vaccine compared to high-dose trivalent and other egg-based influenza vaccines among older adults in the US during the 2017–2018 influenza season. Vaccines 2020, 8, 446. [Google Scholar] [CrossRef] [Scilit]
- Postma, M.; Biundo, E.; Chicoye, A.; Devlin, N.; Mark Doherty, T.; Garcia-Ruiz, A.J.; Jaros, P.; Sheikh, S.; Toumi, M.; Wasem, J.; et al. Capturing the value of vaccination within health technology assessment and health economics: Country analysis and priority value concepts. Vaccine 2022, 40, 3999–4007. [Google Scholar] [CrossRef] [Scilit]
- Franklin, J.M.; Lin, K.J.; Gatto, N.M.; Rassen, J.A.; Glynn, R.J.; Schneeweiss, S. Real-World Evidence for Assessing Pharmaceutical Treatments in the Context of COVID-19. Clin. Pharmacol. Ther. 2021, 109, 816–828. [Google Scholar] [CrossRef] [Scilit]
- Li, J.; Huang, D.Q.; Zou, B.; Yang, H.; Hui, W.Z.; Rui, F.; Yee, N.T.S.; Liu, C.; Nerurkar, S.N.; Kai, J.C.Y.; et al. Epidemiology of COVID-19: A systematic review and meta-analysis of clinical characteristics, risk factors, and outcomes. J. Med. Virol. 2021, 93, 1449–1458. [Google Scholar] [CrossRef] [Scilit]
- Prasad, S.; Kalafat, E.; Blakeway, H.; Townsend, R.; O’Brien, P.; Morris, E.; Draycott, T.; Thangaratinam, S.; Le Doare, K.; Ladhani, S.; et al. Systematic review and meta-analysis of the effectiveness and perinatal outcomes of COVID-19 vaccination in pregnancy. Nat. Commun. 2022, 13, 2414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- UK Health Security Agency. Weekly National Influenza and COVID-19 Surveillance Report Week 2 Report (up to Week 1 Data), 12 January 2023. Available online: https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/1129894/Weekly_Flu_and_COVID-19_report_w2.pdf (accessed on 11 January 2023).
- Musuuza, J.S.; Watson, L.; Parmasad, V.; Putman-Buehler, N.; Christensen, L.; Safdar, N. Prevalence and outcomes of co-infection and superinfection with SARS-CoV-2 and other pathogens: A systematic review and meta-analysis. PLoS ONE 2021, 16, e0251170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Domnich, A.; de Waure, C. Comparative effectiveness of adjuvanted versus high-dose seasonal influenza vaccines for older adults: A systematic review and meta-analysis. Int. J. Infect. Dis. 2022, 122, 855–863. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Centre for Disease Prevention and Control. Systematic Review of the Efficacy, Effectiveness and Safety of Newer and Enhanced Seasonal Influenza Vaccines for the Prevention of Laboratory-Confirmed Influenza in Individuals Aged 18 Years and Over. Available online: https://www.ecdc.europa.eu/sites/default/files/documents/seasonal-influenza-vaccines-systematic-review-efficacy.pdf (accessed on 6 November 2022).
- Wilkinson, K.; Wei, Y.; Szwajcer, A.; Rabbani, R.; Zarychanski, R.; Abou-Setta, A.M.; Mahmud, S.M. Efficacy and safety of high-dose influenza vaccine in elderly adults: A systematic review and meta-analysis. Vaccine 2017, 35, 2775–2780. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.K.H.; Lam, G.K.L.; Shin, T.; Samson, S.I.; Greenberg, D.P.; Chit, A. Efficacy and effectiveness of high-dose influenza vaccine in older adults by circulating strain and antigenic match: An updated systematic review and meta-analysis. Vaccine 2021, 39 (Suppl. S1), A24–A35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rouse, B.; Chaimani, A.; Li, T. Network meta-analysis: An introduction for clinicians. Intern. Emerg. Med. 2017, 12, 103–111. [Google Scholar] [CrossRef] [Scilit]
- Chaimani, A.; Caldwell, D.M.; Li, T.; Higgins, J.P.T.; Salanti, G. Chapter 11: Undertaking network meta-analyses. In Cochrane Handbook for Systematic Reviews of Interventions Version 6.3 (updated February 2022); Higgins, J.P.T., Thomas, J., Chandler, J., Cumpston, M., Li, T., Page, M.J., Welch, V.A., Eds.; Cochrane: London, UK, 2022; Available online: www.training.cochrane.org/handbook (accessed on 30 May 2023).
- Rotshild, V.; Hirsh-Raccah, B.; Miskin, I.; Muszkat, M.; Matok, I. Comparing the clinical efficacy of COVID-19 vaccines: A systematic review and network meta-analysis. Sci. Rep. 2021, 11, 22777. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Diallo, A.; Carlos-Bolumbu, M.; Diallo, M.H.; Makinson, A.; Galtier, F. Efficacy of approved vaccines to prevent COVID-19: A systematic review and network meta-analysis of reconstructed individual patient data from randomized trials. Z. Gesundh. Wiss. 2022, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Minozzi, S.; Lytras, T.; Gianola, S.; Gonzalez-Lorenzo, M.; Castellini, G.; Galli, C.; Cereda, D.; Bonovas, S.; Pariani, E.; Moja, L. Comparative efficacy and safety of vaccines to prevent seasonal influenza: A systematic review and network meta-analysis. EClinicalMedicine 2022, 46, 101331. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, P.; Mantovani, L.G. The importance of real-world evidence in understanding influenza vaccine effectiveness. Farmeconomia. Health Econ. Ther. Pathw. 2022, 23, 29–32. [Google Scholar] [CrossRef] [Scilit]
- Subbiah, V. The next generation of evidence-based medicine. Nat. Med. 2023, 29, 49–58. [Google Scholar] [CrossRef] [Scilit]
- Greenhalgh, T. Will COVID-19 be evidence-based medicine’s nemesis? PLoS Med. 2020, 17, e1003266. [Google Scholar] [CrossRef] [Scilit]
- O’Reilly, D.J.; Blackhouse, G.; Burns, S.; Bowen, J.M.; Burke, N.; Mehltretter, J.; Waite, N.M.; Houle, S.K. Economic analysis of pharmacist-administered influenza vaccines in Ontario, Canada. Clinicoecon. Outcomes Res. 2018, 10, 655–663. [Google Scholar] [CrossRef] [Scilit]
- Centers for Disease Control and Prevention. Seasonal Influenza Vaccines Pricing. Available online: https://www.cms.gov/Medicare/Medicare-Fee-for-Service-Part-B-Drugs/McrPartBDrugAvgSalesPrice/VaccinesPricing (accessed on 8 May 2023).
- Mauskopf, J.; Standaert, B.; Connolly, M.P.; Culyer, A.J.; Garrison, L.P.; Hutubessy, R.; Jit, M.; Pitman, R.; Revill, P.; Severens, J.L. Economic Analysis of Vaccination Programs: An ISPOR Good Practices for Outcomes Research Task Force Report. Value Health 2018, 21, 1133–1149. [Google Scholar] [CrossRef] [Scilit]
- Arevalo, C.P.; Bolton, M.J.; Le Sage, V.; Ye, N.; Furey, C.; Muramatsu, H.; Alameh, M.G.; Pardi, N.; Drapeau, E.M.; Parkhouse, K.; et al. A multivalent nucleoside-modified mRNA vaccine against all known influenza virus subtypes. Science 2022, 378, 899–904. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, L.; Rebaza, A.; Dela Cruz, C.S. When “B” becomes “A”: The emerging threat of influenza B virus. Eur. Respir. J. 2019, 54, 159–173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, A.M.; Huber, V.C. The Unexpected Impact of Vaccines on Secondary Bacterial Infections Following Influenza. Viral Immunol. 2018, 31, 159–173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).