


Abstract
The purpose of this systematic review and network meta-analysis was to determine the analgesic effectiveness of peripheral nerve blocks (PNBs), including each anatomical approach, with or without intrathecal morphine (ITMP) in cesarean delivery (CD). All relevant randomized controlled trials comparing the analgesic effectiveness of PNBs with or without ITMP after CD until July 2021. The two co-primary outcomes were designated as (1) pain at rest 6 h after surgery and (2) postoperative cumulative 24-h morphine equivalent consumption. Secondary outcomes were the time to first analgesic request, pain at rest 24 h, and dynamic pain 6 and 24 h after surgery. Seventy-six studies (6278 women) were analyzed. The combined ilioinguinal nerve and anterior transversus abdominis plane (II-aTAP) block in conjunction with ITMP had the highest SUCRA (surface under the cumulative ranking curve) values for postoperative rest pain at 6 h (88.4%) and 24-h morphine consumption (99.4%). Additionally, ITMP, ilioinguinal-iliohypogastric nerve block in conjunction with ITMP, lateral TAP block, and wound infiltration (WI) or continuous infusion (WC) below the fascia also showed a significant reduction in two co-primary outcomes. Only the II-aTAP block had a statistically significant additional analgesic effect compared to ITMP alone on rest pain at 6 h after surgery (−7.60 (−12.49, −2.70)). In conclusion, combined II-aTAP block in conjunction with ITMP is the most effective post-cesarean analgesic strategy with lower rest pain at 6 h and cumulative 24-h morphine consumption. Using the six described analgesic strategies for postoperative pain management after CD is considered reasonable. Lateral TAP block, WI, and WC below the fascia may be useful alternatives in patients with a history of sensitivity or severe adverse effects to opioids or when the CD is conducted under general anesthesia.
1. Introduction
Cesarean sections cause moderate-to-severe acute postoperative pain. Furthermore, more than 10% of mothers may experience persistent post-cesarean delivery (CD) pain, which may persist for more than 3–6 months after surgery [1,2]. Inadequately controlled postoperative pain may delay the mother’s recovery, disturb breastfeeding, and interfere with maternal-neonatal bonding [3]. Therefore, optimal postoperative analgesia is a major concern for both parturients and obstetric anesthesiologists.
Low-dose intrathecal morphine (ITMP) is considered the gold standard for postoperative analgesia after a cesarean section under spinal anesthesia [4]. However, it has the potential for unwanted opioid-related adverse effects, such as pruritus, nausea, vomiting, urinary retention, and sedation, which could increase the requirement for additional medications.
Currently, multimodal analgesic strategies are widely used after cesarean section to reduce opioid consumption and provide synergistic or additive analgesia [5]. Several peripheral nerve block (PNB) techniques have been investigated to assess their potential analgesic benefit for post-CD pain: erector spinae plane (ESP) block, quadratus lumborum (QL) block, ilioinguinal-iliohypogastric (II-IH) nerve block, transversus abdominis plane (TAP) block, rectus sheath (RS) block, and surgical wound infiltration (WI) [6]. To date, more than 10 published meta-analyses have compared the analgesic effect of these abdominal wall fascial plane blocks. However, most of them concluded that there was no further improvement in analgesic outcomes when intrathecal morphine was combined [7,8,9,10]. Conversely, there are several different approaches for each block technique, and the spread of the local anesthetic may vary depending on the anatomical location of each approach. Resultantly, analgesic outcomes may differ depending on the approach [6]. Consequently, previously published meta-analyses that were not classified according to each approach may have some limitations in the interpretability of their results and may provide incorrect information to clinicians.
This systematic review and network meta-analysis (NMA) aimed to compare the analgesic effectiveness of all types of PNBs to decrease postoperative pain and opioid consumption after cesarean section. Specifically, in this study, we analyzed the results by considering each anatomical approach of the PNB method and whether intrathecal morphine was used in combination during spinal anesthesia as an individual comparator. Ultimately, we sought to answer the following conclusions: (1) Is ITMP still sufficient as the gold standard, (2) which method is the most effective strategy for post-CD analgesia, and (3) which PNB methods have additional analgesic effects when combined with ITMP?
2. Materials and Methods
This systematic review and NMA on multimodal post-CD pain was conducted in accordance with the protocol recommended by the Cochrane Collaboration [11] and reported according to the PRISMA extension for NMA guidelines [12]. We used a pre-designed protocol to review and specifically evaluate the results of randomized controlled trials (RCTs) that compared the postoperative analgesic outcomes of all types of PNB methods and ITMP after CD. The protocol was registered with the PROSPERO network (registration number: CRD42021264372; https://www.crd.york.ac.uk/prospero, accessed on 1 December 2021).
2.1. Eligibility Criteria
We included full reports of RCTs that investigated the postoperative analgesic effects of all types of PNB methods and intrathecal or epidural morphine in CD. A detailed description of the inclusion and exclusion criteria is provided in the Supplementary Materials-Methods.
2.2. Search Strategy and Study Selection
We searched MEDLINE, EMBASE, the Cochrane Central Register of Controlled Trials (CENTRAL), and Google Scholar using search terms related to PNB and ITMP for the management of post-CD pain from inception until July 2021. Two investigators (C.W.B. and C.K.C.) independently selected the studies.
A detailed description of the literature search strategy and study selection is provided in Supplementary Materials-Methods.
2.3. Data Extraction and Management
Using standardized extraction, the following data were extracted by two independent investigators (C.R. and H.K.): (1) title; (2) name of the first author; (3) name of the journal; (4) year of publication; (5) country; (6) language; (7) primary anesthesia details and regimen (general versus. neuraxial); (8) block technique and approach used; (9) number of subjects; (10) the type and dose of drug used; (11) nature of primary and secondary outcomes investigated; (12) supplemental postoperative analgesia regimen. A detailed description of the data extraction and data management is provided in Supplementary Materials-Methods.
2.4. Quality Assessment
The quality of all included studies was independently assessed by two investigators (C.R. and H.K.), using version 2 of the Cochrane RoB tool for randomized trials. RoB 2 was evaluated by considering the following five potential sources of bias: (1) bias arising from the randomization process, (2) bias due to deviations from intended interventions, (3) bias due to missing outcome data, (4) bias in outcome measurements, and (5) bias in the selection of the reported results. We judged all five domains in each article according to a series of questions, “signaling questions,” presented in the Cochrane RoB 2 to elicit information about features of the trial that are relevant to the risk of bias.
Thereafter, we evaluated the overall risk of biased judgment according to domain-level judgments. The methodology for each domain was assigned as “high risk of bias,” “some concerns,” or “low risk of bias” to reflect the risk of bias [13].
2.5. Quality of the Evidence
Evidence grade was determined using the Grading of Recommendations Assessment, Development, and Evaluation (GRADE) system, which uses a sequential assessment of evidence quality, followed by an assessment of the risk-benefit balance and a subsequent judgment on the strength of the recommendations.
2.6. Statistical Analysis
A frequentist NMA was performed using STATA software (version 15; StataCorp LP, College Station, TX, USA) based on mvmeta with NMA graphical tools developed by Chaimani et al. [14]. Additionally, to test the robustness of the results of the frequentist random NMA, we also conducted Bayesian NMA using fixed and random effects models and with Markov Chain Monte Carlo methods using the R statistical package gemtc [15]. We evaluated the similarity, transitivity, and consistency assumptions for the NMA. We also performed a network meta-regression analysis to test the possible causes of heterogeneity. A detailed description of the statistical analysis is provided in Supplementary Materials-Methods.
3. Results
3.1. Study Selection
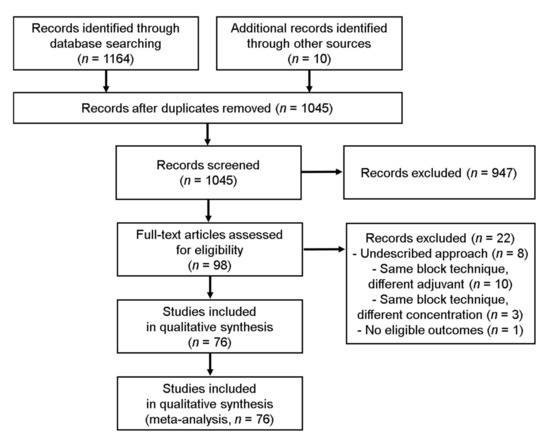
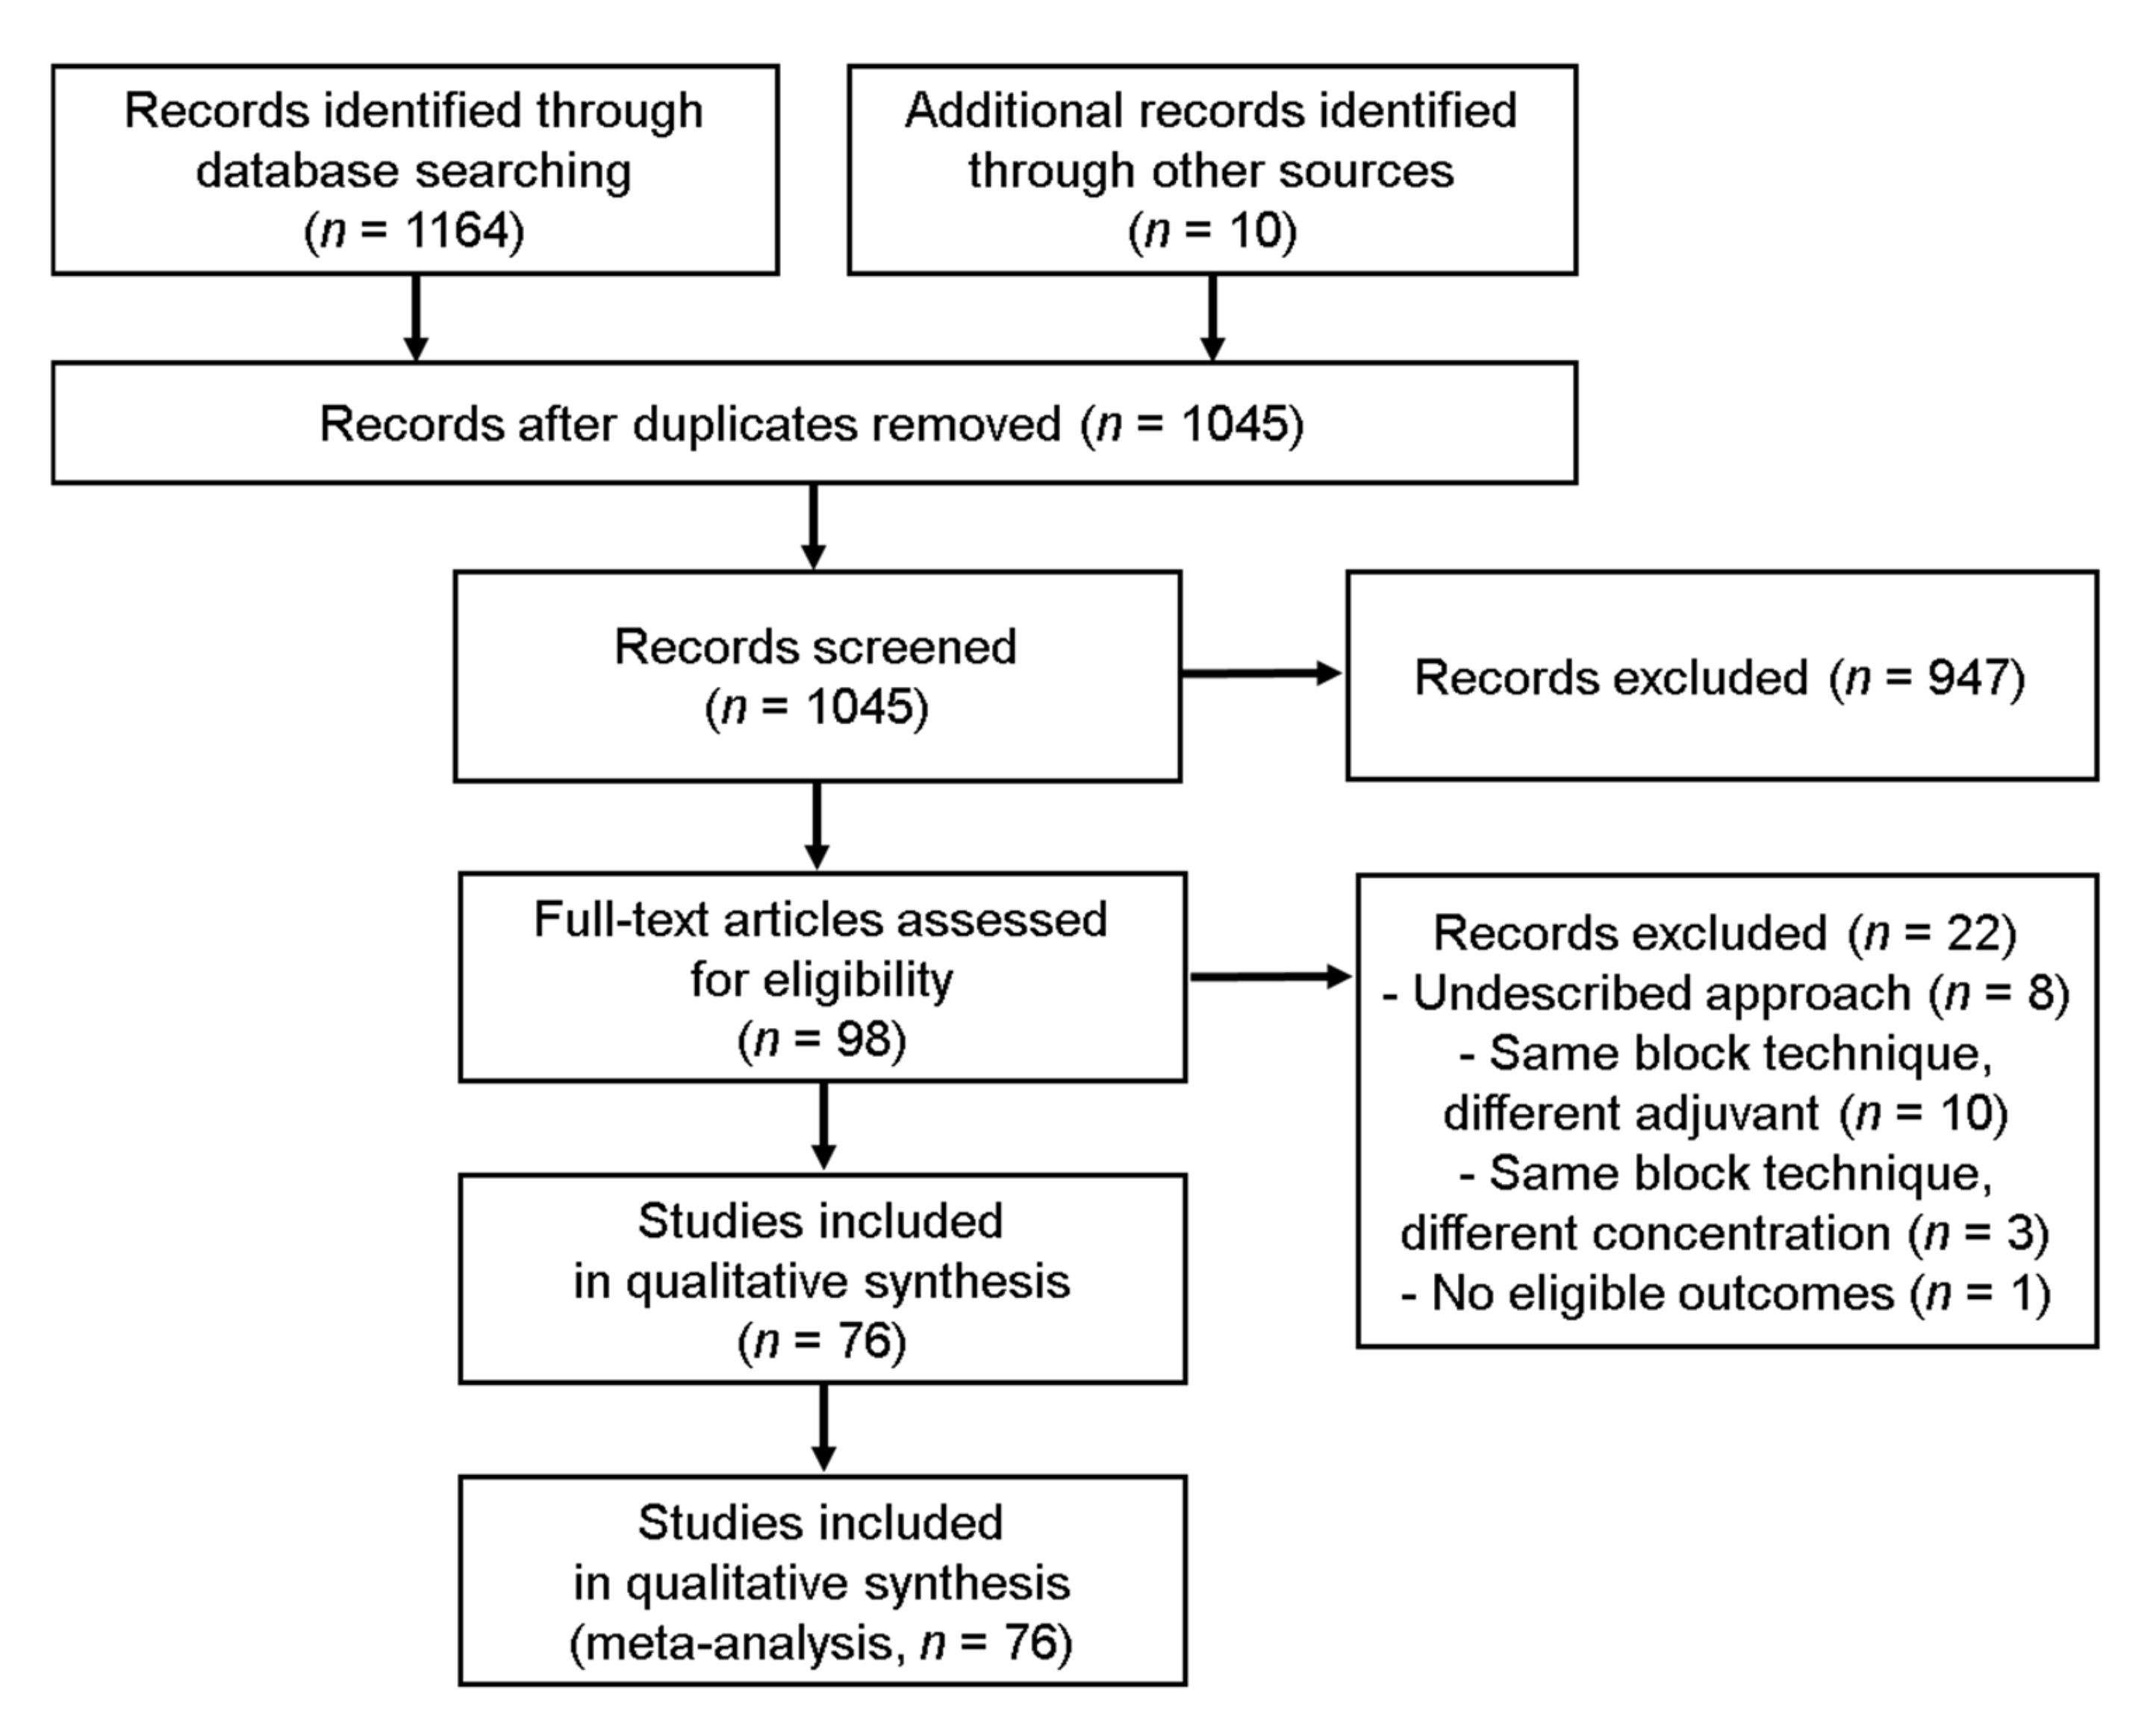
We initially identified 1164 unique citations from MEDLINE, EMBASE, the Cochrane Central Register of Controlled Trials, and Google Scholar database. Additionally, we retrieved 10 more articles from the reference lists of related meta-analyses. A PRISMA flow chart of the study selection is shown in. After the removal of duplicates (129 studies), we conducted extensive screening of the individual titles and abstracts of 1045 studies. In the first stage of study selection, the kappa value between the two investigators was 0.768. A total of 98 studies that met the predefined definitions of PICO-SD (population, intervention, comparator, outcome and study design) remained, whose eligibility we evaluated via full-text reviews. Among these, 22 additional studies were excluded for the reasons described in Figure 1 and Supplementary Materials-Methods. Finally, we included 76 RCTs in this systematic review and the NMA [16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87,88,89,90,91]. In the second stage of study selection, the kappa value between the two investigators was 0.939.
Figure 1.
PRISMA flow diagram of literature search and selection.
3.2. Study Characteristics
The characteristics of included studies are presented in Table 1. In papers published since 1991, we identified seven types of PNB methods: ESP block, transverse fascial plane (TFP) block, QL block, II-IH nerve block, TAP block, RS block, and surgical WI. Although there are several specific approach techniques for each block, only the following approach techniques were included in this study through data extraction: QL block (anterior, aQL; posterior, pQL, combined anterior and posterior; apQL, and lateral approach; lQL), TAP block (anterior; aTAP, lateral; lTAP, combined subcostal and lateral; slTAP, posterior approach; pTAP), continuous wound infusion (catheter insertion above or below the fascia; WC_above or WC_below, respectively). Consequently, we identified 28 different postoperative analgesia strategies (164 directly compared group), except for the non-active control group (no intervention), either alone or in various combinations. Except for non-active controls (45 studies, 27.4%, 1835 patients), ITMP (active control, 24 studies, 14.6%, 891 patients), lTAP block (20 studies, 12.2%, 650 patients), and WI, 15 studies, 9.1%, 662 patients) were compared the most. A detailed description is provided in Supplementary Materials-Methods.
Table 1.
Summary of study characteristics in included studies.
3.3. Study Quality Assessment
The risk of bias assessment in the included studies using the Cochrane RoB 2 is presented in Table S1). When judging the overall risk of bias, only 13 studies had a low risk of bias in all domains. A detailed description of the study quality assessment is provided in Supplementary Materials-Methods.
3.4. Synthesis of Results
3.4.1. Primary Outcomes
Pain at Rest 6 h after Surgery
Although a total of 60 studies (4672 patients) measured the pain at rest 6 h after surgery, as one study was separated from the loops [72], we performed the NMA excluding that study. Therefore, 59 studies (4622 patients) were analyzed.
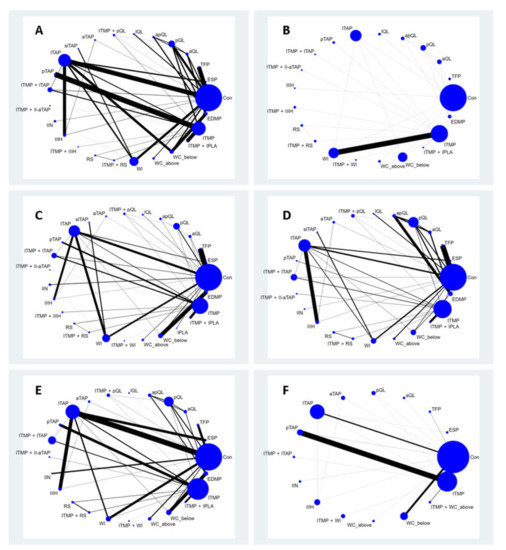
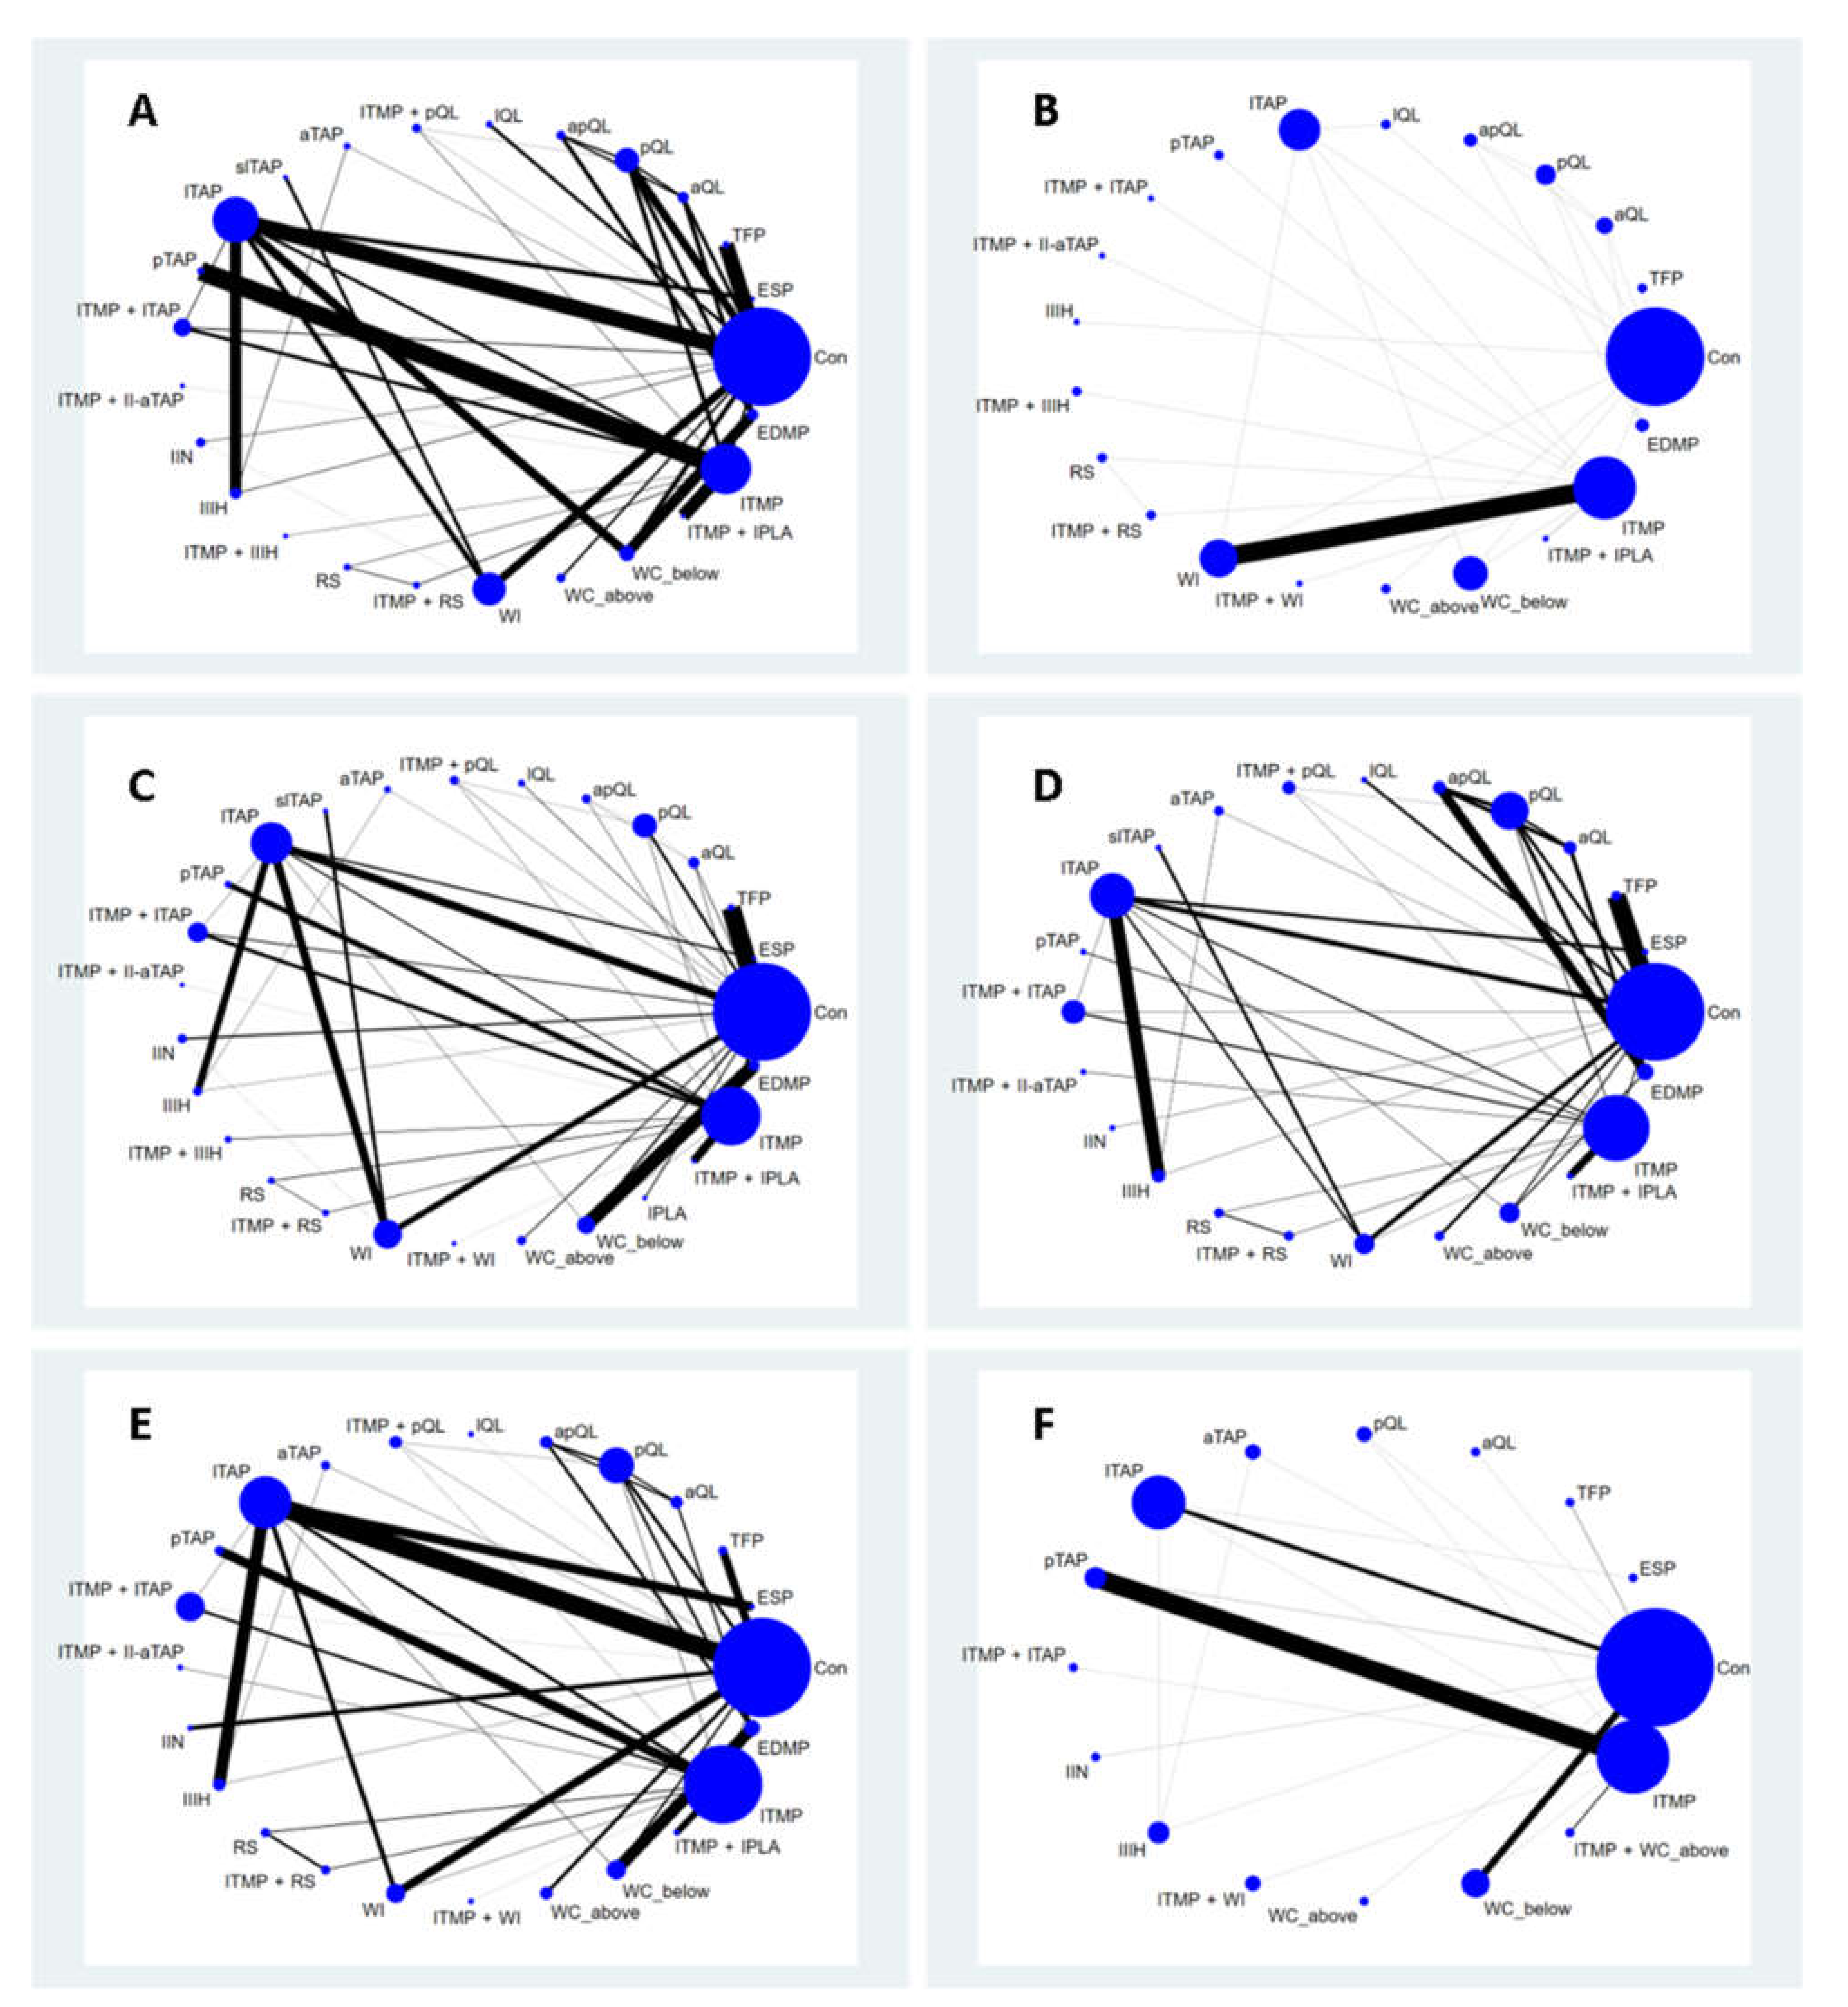
The network plot of all eligible comparisons for this endpoint is shown in Figure 2. Although all 25 analgesic management strategies (nodes) were connected to the network, two comparisons (control and lTAP block) were more directly comparable than the other 23 nodes. There was no evidence of network inconsistency (χ2 (14) = 17.29, p = 0.241). There were 19 triangular loops, and two quadratic loops closed in the network from the comparison of pain at rest 6 h after surgery. Triangular loops are formed by three interventions all compared with each other, and quadratic loops are formed by four interventions, each of which is compared exactly with two other interventions in the loop.
Figure 2.
Network plots of direct comparisons for all included studies for outcomes. Each postoperative analgesia strategy is depicted by a node that is weighed based on the number of subjects who were randomized to that intervention. Edges between the nodes show the eligible direct comparisons among those interventions, and their width is weighed based on an inverse of the standard error of effect. (A) Pain at rest 6 h after surgery; (B) Postoperative cumulative 24 h morphine equivalent consumption; (C) Pain at rest 24 h after surgery; (D) Dynamic pain at 6 h after surgery; (E) Dynamic pain at 24 h after surgery; (F) The time to first analgesic request.
Five loops (aQL/pQL/apQL [50], aQL/pQL/EDMP [50], aQL/apQL/EDMP [50], pQL/apQL/EDMP [50], and RS/ITMP + RS/ITMP [60]) were formed only by multi-arm trials. Although almost all loops showed no significance in the local inconsistency between the direct and indirect point estimates, five loops (Control/aQL/WC_below/EDMP, Control/pQL/WC_below/EDMP, pQL/ITMP + pQL/ITMP, Control/pQL/lTMP + pQL, and Control/aTAP/II-IH) showed significant inconsistency (Supplementary Figure S1A).
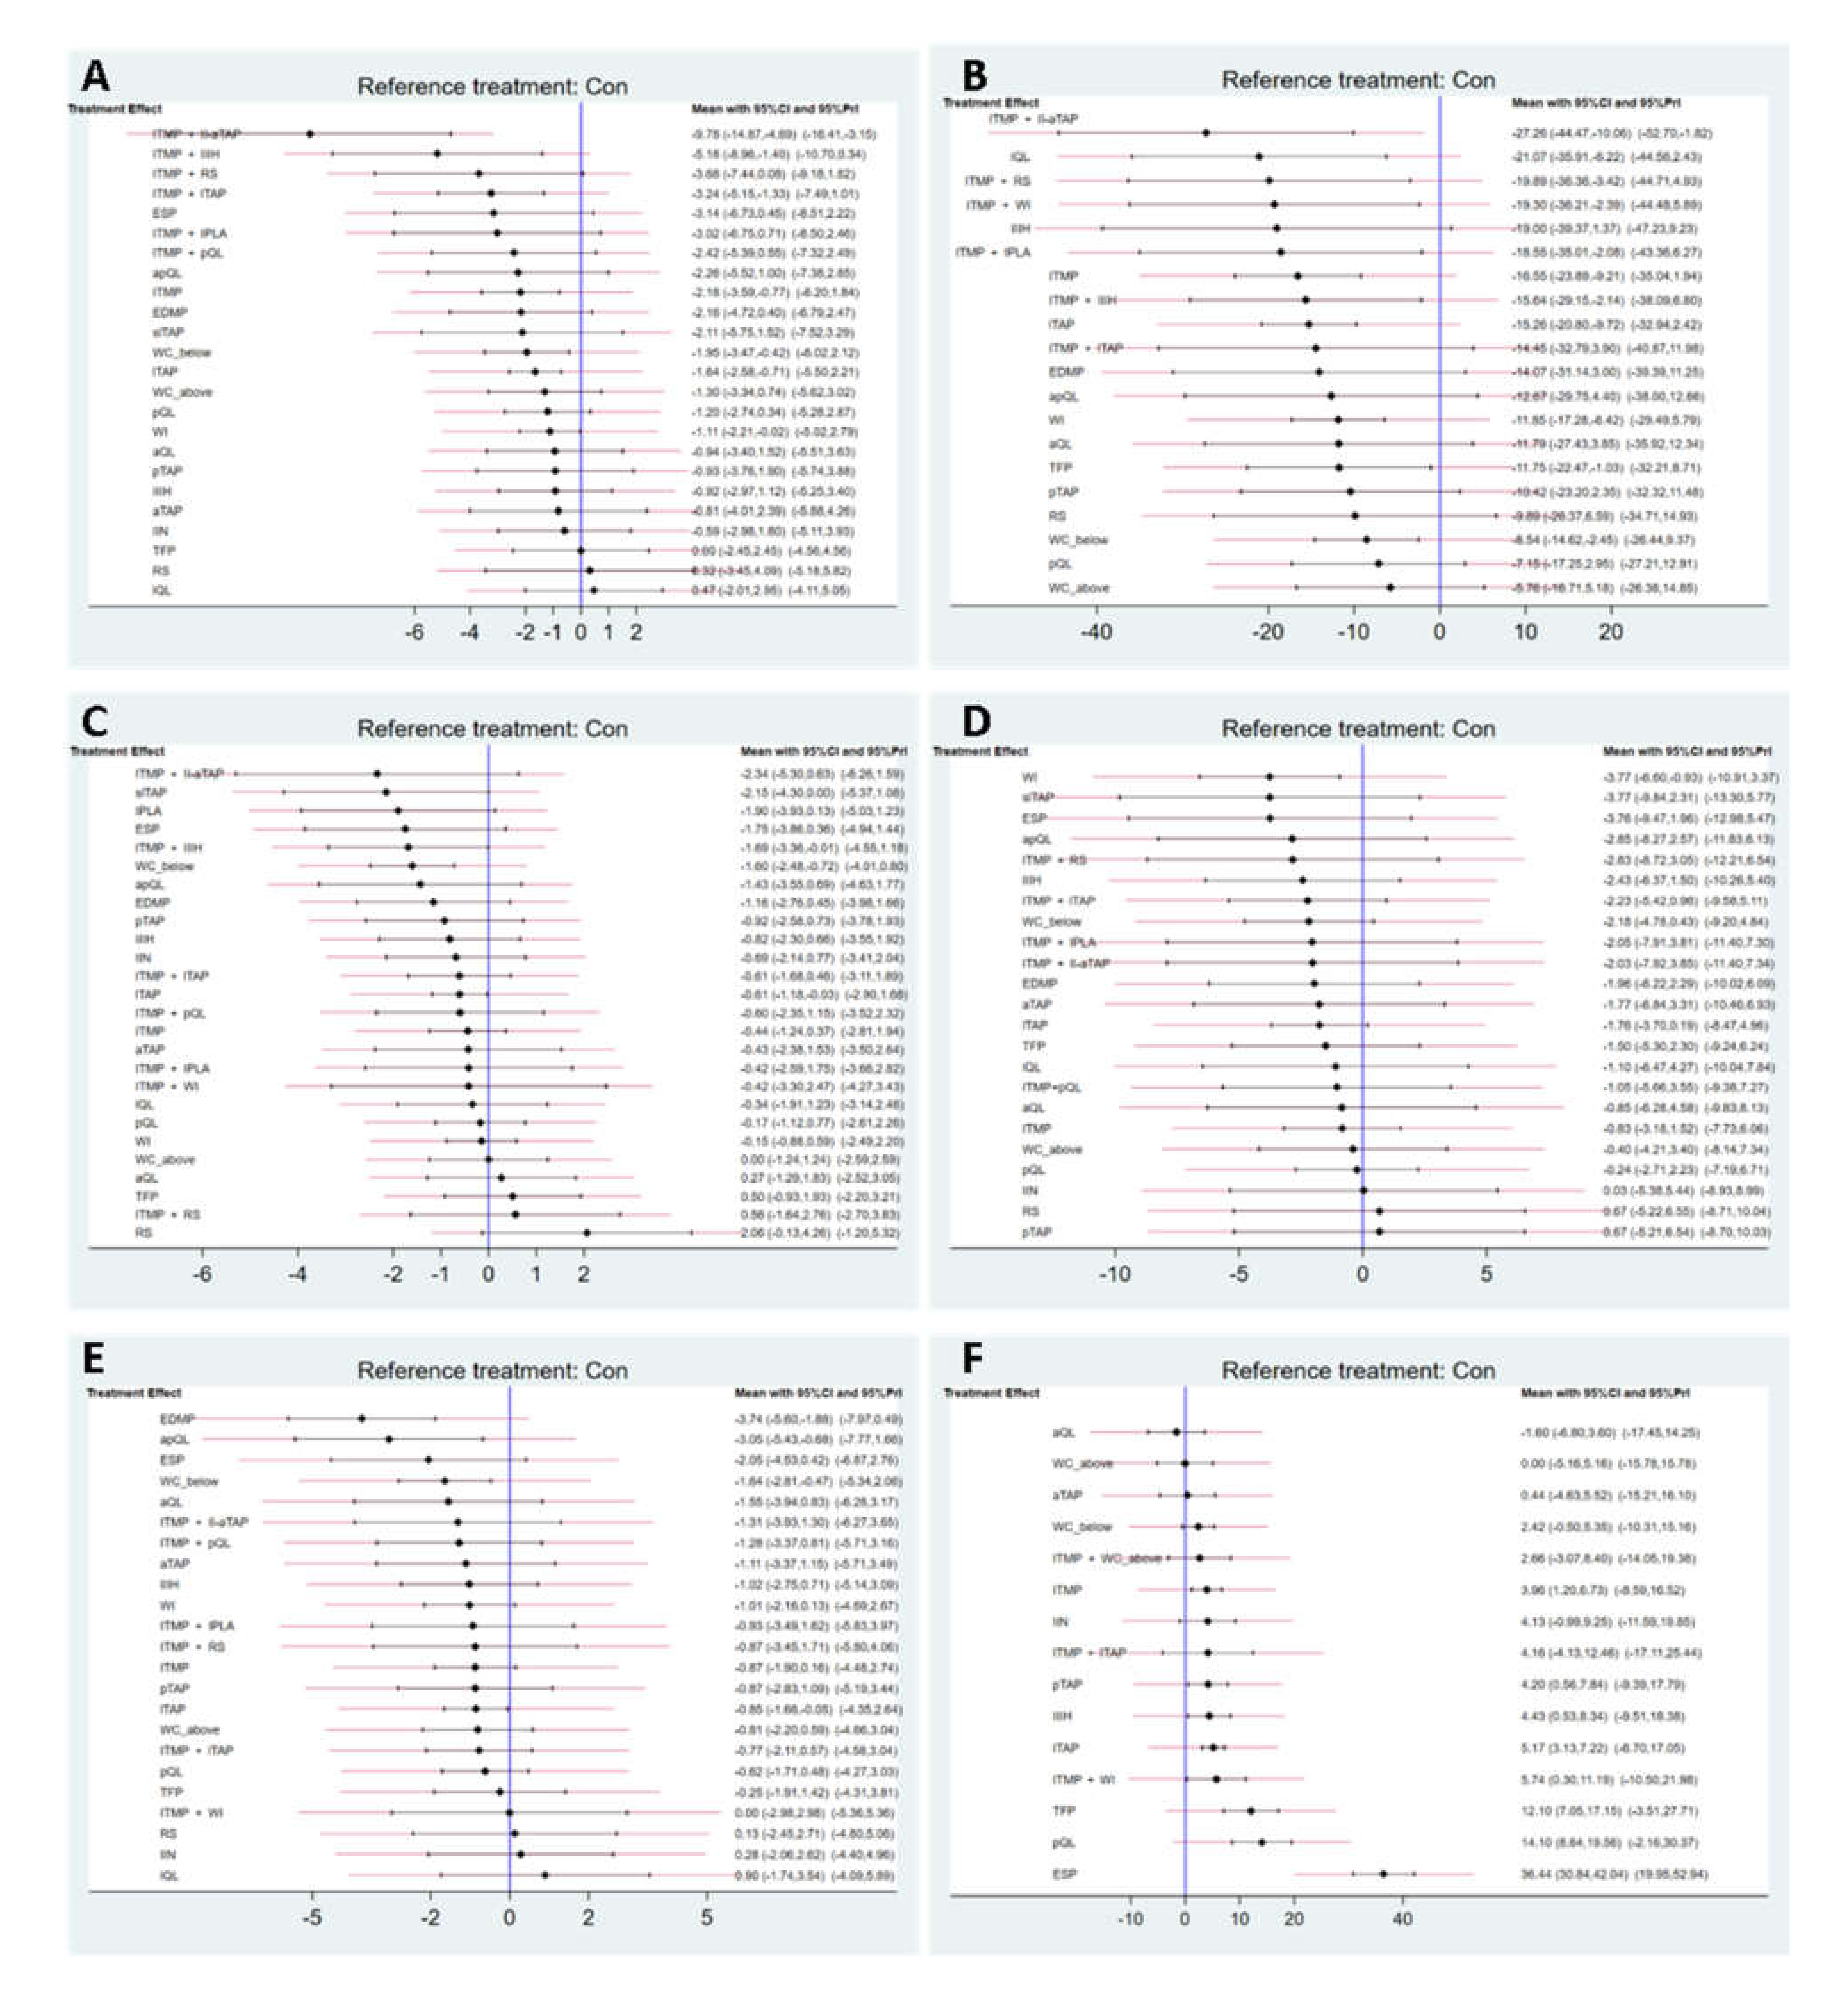
ITMP in conjunction with the ilioinguinal nerve and aTAP block (ITMP + II-aTAP) showed a lower pain at rest 6 h after surgery than the non-active control group (no intervention) in terms of 95% CI (−14.87, −4.69) and PrI (−16.41, −3.15). Conversely, ITMP + II-IH, ITMP + lTAP, ITMP, WC_below, lTAP, and WI showed lower pain than the controls only in terms of the 95% CI (Figure 3). Insignificance in the 95% PrIs suggests that any future RCTs could change the significance of the efficacy of these comparisons.
Figure 3.
The confidence intervals (CI) and predictive intervals (PrI) of all outcomes. Each solid black line represents the CI for each comparison, and the red one shows the respective PrI. The blue line is the line of no effect (odds ratio = 1). (A) Pain at rest 6 h after surgery; (B) Postoperative cumulative 24 h morphine equivalent consumption; (C) Pain at rest 24 h after surgery; (D) Dynamic pain at 6 h after surgery; (E) Dynamic pain at 24 h after surgery; (F) The time to first analgesic request.
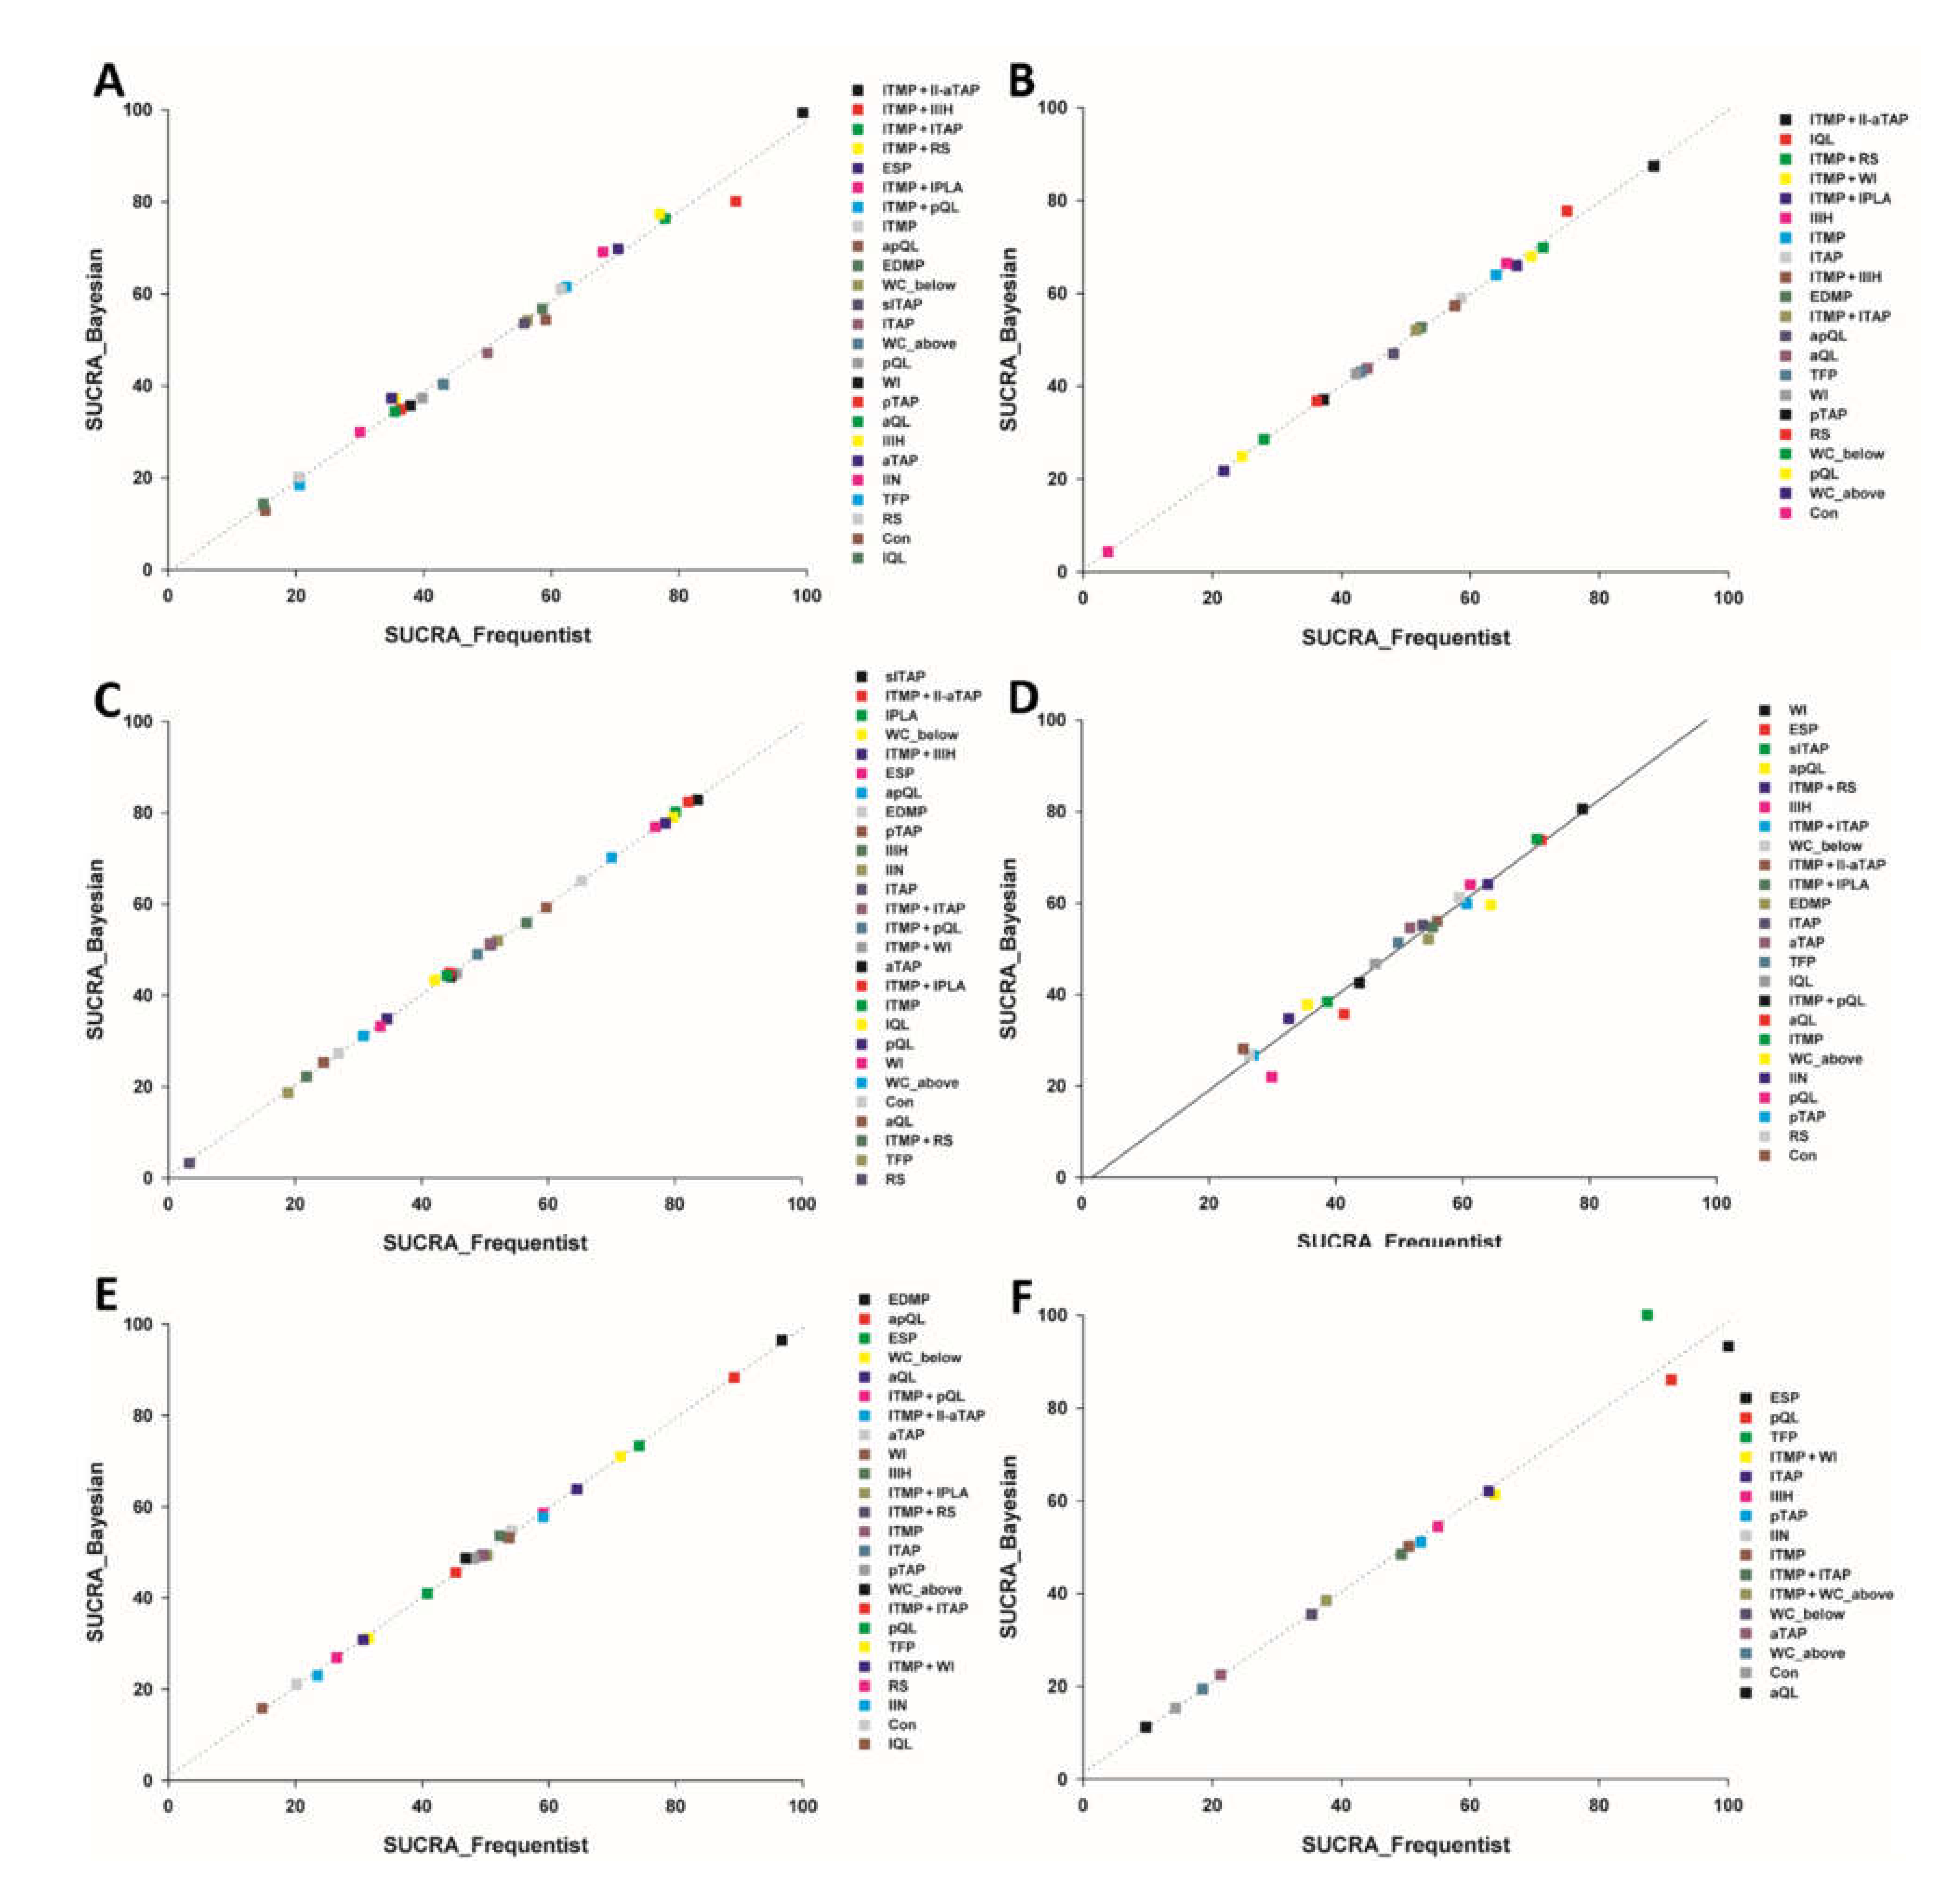
The rankogram shows the distribution of the estimated probability for each intervention to achieve each of the possible ranks. Figure S2A shows that ITMP + II-aTAP followed by ITMP + II-IH, ITMP + lTAP and ITMP + RS had the lowest pain at rest 6 h after surgery. A cumulative ranking plot was drawn, and the SUCRA probabilities of the different interventions for this outcome were calculated (Figure S3A). The expected mean rankings and SUCRA values for each intervention are presented in Figure 4. According to the SUCRA value, the pain at rest 6 h after surgery was lower in the order of ITMP + II-aTAP (99.4%), followed by ITMP + II-IH (88.9%), ITMP + lTAP (77.8%), and ITMP + RS (77.0%). The SUCRA values from the Bayesian model are like those from the frequentist model, which demonstrates the robustness of our analysis. The comparison-adjusted funnel plots showed that the funnel plots were symmetrical around the zero line, which suggested a less likely publication bias (Figure S4A).
Figure 4.
The expected mean ranking and surface under the cumulative ranking curve (SUCRA) values from a frequentist and Bayesian model of all outcomes. SUCRA is a numeric presentation of the overall ranking. The higher the SUCRA value and the closer to 100%, the better the rank of the intervention. (A) Pain at rest 6 h after surgery; (B) Postoperative cumulative 24 h morphine equivalent consumption; (C) Pain at rest 24 h after surgery; (D) Dynamic pain at 6 h after surgery; (E) Dynamic pain at 24 h after surgery; (F) The time to first analgesic request.
The network diagnostics using trace and density plots showed that the model convergence was valid in both models (Figure S5A,B). However, the Gelman–Rubin–Brooks method with a potential scale reduction factor (PSRF) and DIC showed that the random effect model was a better fit for the data (Figure S5C,D; Table S2). Thus, we analyzed the data using a random effect model.
Forest plots, node splitting plots, and rankograms generated by the Bayesian model were also generated (Figure S5E–G), which shows results like those of the frequentist model.
Postoperative Cumulative 24 h Morphine Equivalent Consumption (mg)
A total of 44 studies (3360 patients) presented postoperative cumulative 24 h morphine equivalent consumption. In most studies, opioids were administered using an intravenous patient-controlled analgesia (PCA) device, and in some cases, intermittent IV bolus injection was performed according to the patient’s pain scale. In all studies in which IV morphine was administered through a PCA device after the surgery, basal infusion was not performed, but a bolus dose and lockout time were set up.
The network plot of all eligible comparisons for this endpoint is shown in Figure 2B. Although all 21 analgesic management strategies (nodes) were connected to the network, three comparisons (Control, ITMP, and lTAP) were more directly comparable to the other 18 nodes. There was no evidence of network inconsistency (χ2 (7) = 7.59, p = 0.371). There were 14 triangular loops closed in the network based on the comparison of this outcome.
Five loops (aQL/pQL/apQL [50], aQL/pQL/EDMP [50], aQL/apQL/EDMP [50], pQL/apQL/EDMP [50], and RS/ITMP + RS/ITMP [60]) were formed only by multi-arm trials. There was no evidence of local inconsistency between the direct and indirect point estimates (Figure S1B).
ITMP + II-aTAP showed a lower morphine consumption at 24 h than the control in terms of 95% CI (−44.47, −10.06) and PrI (−52.70, −1.82) at the same time. LQL, ITMP + RS, ITMP + WI, ITMP + IPLA (intraperitoneal local anesthetic instillation), ITMP, ITMP + II-IH, lTAP, WI, TFP, and WC_below showed a lower morphine consumption than the control only in terms of the 95% CI (Figure 3B).
The rankograms showed that ITMP + II-aTAP followed by lQL and ITMP + RS had the lowest postoperative cumulative 24 h morphine equivalent consumption (Figure S2B). A cumulative ranking plot was drawn, and the SUCRA probabilities of the different interventions for this endpoint were calculated (Figure S3B). The expected mean rankings and SUCRA values for each intervention are presented in Figure 4B. According to the SUCRA value, the postoperative cumulative 24 h morphine equivalent consumption was lower in the ITMP + II-aTAP (88.4%), followed by lQL (75.0%), ITMP + RS (71.3%), and ITMP + WI (69.4%). The comparison-adjusted funnel plots showed that the funnel plots were symmetrical around the zero line, which suggested a less likely publication bias (Figure S4B).
The network diagnostics using trace and density plots showed that model convergence was valid in both models (Figure S6A,B). However, the Gelman-Rubin-Brooks methods with PSRF and DIC showed that the random effect model was a better fit for the data (Figure S6C,D; Table S2). Thus, we analyzed the data using a random effect model.
Forest plot, node splitting plot, rankogram, and SUCRA values from the Bayesian model showed similar results to those from the frequentist model, which showed the robustness of our analysis (Figure S6E–G; Figure 4B).
3.4.2. Secondary Outcomes
Pain at Rest 24 h after Surgery
The network plot of all eligible comparisons for this outcome is shown in Figure 2C. Continuous wound infusion below the fascia (WC_below) showed lower pain than the control only in terms of the 95% confidence interval (Figure 3C). According to the SUCRA value, the pain at rest 24 h after surgery was lower in the order of the slTAP (83.6%), followed by ITMP + II-aTAP (82.1%), IPLA (80.1%), and WC_below (79.8%) (Figures S2C and S3C; Figure 4C). Inconsistency and publication bias were checked (Figures S1C and S4C). The network diagnostics showed that the random effect model was a better fit for the data (Figure S7A–D; Table S2). Forest plot, node splitting plot, rankogram, and SUCRA values from the Bayesian model showed similar results to those from the frequentist model, which showed the robustness of our analysis (Figure S7E–G; Figure 4C).
Dynamic Pain 6 h after Surgery
The network plot of all eligible comparisons for this endpoint is shown in Figure 2D. WI showed lower pain than the control only in terms of 95% CI (Figure 3D). According to the SUCRA value, the dynamic pain at 6 h after surgery was lower in the order of WI (78.9%), followed by ESP (72.4%), slTAP (71.7%), and apQL (64.4%) (Figures S2D and S3D, and Figure 4D). The comparison-adjusted funnel plots showed that the funnel plots were symmetrical around the zero line, which suggested a less likely publication bias (Figure S4D). Inconsistency and publication bias were checked (Figures S1D and S4D).
The network diagnostics showed that the random effect model was a better fit for the data (Figure S8A–D; Table S2). Forest plot, node splitting plot, rankogram, and SUCRA values from the Bayesian model showed similar results to those from the frequentist model, which showed the robustness of our analysis (Figure S8E–G and Figure 4D).
Dynamic Pain 24 h after Surgery
The network plot of all eligible comparisons for this endpoint is shown in Figure 2E. EDMP, apQL, WC_below, and lTAP showed lower pain than the control in terms of the 95% CI only (Figure 3E). According to the SUCRA value, the dynamic pain at 24 h after surgery was lower in the order of EDMP (96.7%), followed by apQL (89.2%), ESP (74.2%), and WC_below (71.3%) (Figures S2E and S3E, and Figure 4E). Inconsistency and publication bias were checked (Figures S1E and S4E).
The network diagnostics showed that the random effect model was a better fit for the data (Figure S9A–D; Table S2). Forest plot, node splitting plot, rankogram, and SUCRA values from the Bayesian model showed similar results to those from the frequentist model, which showed the robustness of our analysis (Figure S9E–G and Figure 4E).
Time to First Analgesic Request (h)
The network plot of all eligible comparisons for this endpoint is shown in Figure 2F. ESP showed a longer time to first analgesic request than controls in terms of the 95% CI (30.84, 42.04) and PrI (19.95, 52.94) at the same time. Additionally, ITMP, pTAP, II-IH, lTAP, ITMP + WI, TFP, and pQL showed a longer time to first analgesic request than controls only in terms of the 95% CI (Figure 3F). According to the SUCRA value, the time to first analgesic request was longer in the order of the ESP (100.0%), followed by pQL (91.2%), TFP (87.5%), ITMP + WI (63.8%), and lTAP (62.9%) (Figures S2F and S3F and Figure 4F). Inconsistency and publication bias were checked (Figures S1F and S4F).
The network diagnostics showed that the random effect model was a better fit for the data (Figure S10A–D; Table S2). The forest plot, node splitting plot, rankogram, and SUCRA values from the Bayesian model showed similar results to those from the frequentist model, which showed the robustness of our analysis (Figure S10E and Figure 4F).
Detailed descriptions of the results of secondary outcomes are provided in Supplementary Materials-Methods.
3.5. Quality of the Evidence
Six outcomes were evaluated using the GRADE system. The evidence quality was moderate for pain at rest 6 h after surgery, postoperative cumulative 24 h morphine equivalent consumption, and the time to first analgesic request, and low for pain at rest 24 h after surgery, dynamic pain at 6 h after surgery, and dynamic pain at 24 h after surgery. A detailed description of the quality of the evidence assessment is provided in Supplementary Materials-Methods and Table 2.
Table 2.
The GRADE evidence quality for each outcome.
4. Discussion
Our systematic review and NMA showed the potential analgesic role of combined II-aTAP block in conjunction with ITMP in providing post-cesarean analgesia. It is the most effective analgesic strategy with lower rest pain at 6 h and morphine consumption at 24 h after surgery compared to the non-active control group (no intervention) in terms of the 95% CI and PrI at the same time. Additionally, ITMP, ITMP+ II-IH, lTAP, WI, and WC_below showed a significant reduction in both co-primary outcomes compared to the non-active control in terms of the 95% CI only. On the other hand, in terms of the additional effect of using PNB with ITMP, only II-aTAP had a statistically significant additional effect compared to ITMP alone on pain at rest 6 h after surgery (mean difference (95% CI) (−7.60 (−12.49, −2.70)) (Table S3A,B).
NMA is a useful tool for comparative effectiveness research. We compared the analgesic effects of all kinds of post-cesarean analgesic strategies extracted from all included RCTs; therefore, through this NMA, we will be able to explore the answers to the following questions.
First, is ITMP monotherapy still sufficient as the gold standard for post-cesarean analgesia? It is known to provide long-lasting analgesic effects up to 14–36 h [92]. Regarding the duration of action, a meta-analysis designed to determine the analgesic effect according to the difference in ITMP dose after CD concluded that higher doses (>100 μg) of ITMP prolonged analgesia compared with lower doses (50–100 μg) [93]. The range of mean times to first analgesic request was 13.8 h to 39.5 h and 9.7 h to 26.6 h in the higher and lower doses groups, respectively. In our study, a total of 24 included studies (n = 891, 133.8 ± 56.1 μg) administered ITMP, of which 15 used lower doses, and nine used higher doses of morphine. Despite the use of relatively higher doses of morphine, ITMP showed no statistically significant differences compared with non-active controls in the three secondary outcomes. It prolongs the time to first analgesic request (mean difference (95% CI); 3.96 (1.20, 6.73)), reduces cumulative 24-h morphine consumption (−16.55 (−23.89, −9.21)), and relieves rest pain at 6 h after surgery (−2.18 (−3.59, −0.77)) compared to the non-active control. Although none of the PNB was superior to ITMP in all the three outcomes described above, when PNBs were used together with ITMP, many strategies had greater mean differences and SUCRA values than ITMP monotherapy. Additionally, considering the mean difference in the time to first analgesic request (3.96 h), the analgesic duration of ITMP is thought to be shorter than the result derived from a previous meta-analysis, which was analyzed in fewer studies than ours [93]. Consequently, although ITMP is still simple and effective, it is not the best method in terms of SUCRA values, and it cannot be an option for general anesthesia.
Then, what is the most effective post-cesarean analgesic strategy? PNBs are increasingly used as an important component of postoperative multimodal analgesia, and many RCTs and meta-analyses have been conducted to compare their post-cesarean analgesic effect. As described in the Supplementary Materials-Methods, the analgesic outcomes of PNBs may differ depending on the anatomical approach, and the results that do not distinguish each approach are likely to provide misinformation to clinicians. Therefore, we designed each approach technique as an individual comparator for a more accurate comparison of the post-cesarean analgesic effects of PNBs.
Based on the SUCRA value, ITMP + II-aTAP was ranked as the most effective strategy, with the lowest 24-h morphine consumption (88.4%) and the lowest rest pain at 6 h (99.4%). It also had a statistically significant mean difference compared with non-active controls in terms of the 95% CI and PrI. In particular, it significantly reduced rest pain at 6 h compared to all types of included analgesic strategies, except one (Table S3A). Additionally, it has an opioid-sparing effect (mean difference in 24-h morphine consumption: 27.26 mg, Figure 3B). Reducing the use of opioids improves postoperative recovery and minimizes the risk of opioid-related adverse events. A description of why this combined PNB was most effective is provided in the Supplementary Materials-Methods.
Additionally, considering analgesic duration, ESP block was most effective in prolonging the time to the first analgesic request in terms of both 95% CI and PrI. The SUCRA value was determined to be 100%. The ESP block is a relatively new paraspinal regional anesthesia technique described for the first time in 2016 [94]. It aims to disperse local anesthetics between the transverse process of the vertebra and erector spinae muscle and then spread it into the paravertebral space of 3 or 4 vertebral levels cranially and caudally [62]. Therefore, it can offer both somatic and visceral analgesia.
Most PNBs, including ITMP, were ineffective in late postoperative pain at 24 h in our study (Figure 3C,E). Only WC_below (−1.60 (−2.48, −0.72), −1.64 (−2.81, −0.47)) and lTAP (−0.61 (−1.18, −0.03), −0.85 (−1.66, −0.05)) showed statistically significant lower pain scores in both rest and dynamic pain at 24 h, respectively (Figure 3C,E). WC_below was much more effective than lTAP in terms of the mean difference and SUCRA value. Therefore, for late post-cesarean pain after 24 h, continuous wound infusion of local anesthetics via a catheter below the fascia is recommended.
Third, which PNB methods have an additional analgesic effect when used with ITMP? In our study, only II-aTAP had a statistically significant additional analgesic effect in pain at rest 6 h after surgery (−7.60 (−12.49, −2.70), Table S3A). In any other included intervention, there was no statistically significant difference in terms of the 95% CI.
Finally, through this study, in addition to the predefined questions, we obtained the following additional information.
First, synthetically, six analgesic strategies are written in the first paragraph of the Discussion section that significantly reduced both the rest pain at 6 h after surgery and 24-h morphine consumption at the same time. Therefore, it is reasonable to use these strategies for post-cesarean analgesia. In addition, lTAP, WI, and WC_below showed favorable results, even in the absence of ITMP (Figure 3A,B). Therefore, these three PNB techniques may be useful alternatives if the patient reports a history of sensitivity or severe adverse effects to opioids or when the CD is conducted under general anesthesia.
Second, among the articles finally included in this meta-analysis, the PNB method with the most comparisons was lTAP (20 studies, 650 patients). Abdallah et al. [95] reported that pTAP appeared to lower not only rest and dynamic pain but also morphine consumption for up to 48 h compared to the controls in their meta-analysis. On the contrary, lTAP showed notably more favorable results in our study, except for dynamic pain at 6 h after surgery, compared with pTAP. We believe that the results have changed because 21 articles published after this meta-analysis were retrieved and analyzed in our study.
The QL block is known to have additional effects on visceral pain compared to TAP, which is expected to show better results, but not in our study. LQL was ranked as the second most effective strategy to reduce 24-h morphine consumption (SUCRA value 75.0%), apQL was the second most effective strategy to lower dynamic pain at 24 h after surgery (89.2%), and pQL was also the second most effective strategy to prolong the time to first analgesic request (91.2%) compared to non-active controls in the absence of ITMP. However, there were no statistically significant differences with any approach to the TAP block in terms of mean difference and 95% CI.
Our study has several limitations. First, as with all meta-analyses, there were inevitable heterogeneities, especially in methodologies among the finally included 76 RCTs, which may be attributed to variability in the doses of short-acting opioids such as fentanyl or sufentanil as adjuvants for spinal anesthesia, doses of intrathecal or epidural morphine, doses of local anesthetics for spinal anesthesia and PNBs as described in the results section, and a wide variety of combinations of analgesics used for postoperative multimodal analgesic regimens such as opioids, acetaminophen, and non-steroidal anti-inflammatory drugs. Second, as most of the trials were conducted in a single center using a small scale, there was a possibility of a lack of evidence on some interventions. Third, although II-aTAP in conjunction with ITMP was the most effective postoperative analgesic strategy after CD, it was compared in only one trial with a small sample size (n = 50 patients); therefore, there is a risk of overestimation of effect size. Fourth, many of the included trials had a risk of bias, as described in the results section. Specifically, in performance bias, the studies that compared different PNB methods were unable to blind the investigator who performed the intervention. However, all PNBs were performed in the operating room or post-anesthesia care unit (PACU), and all our primary and secondary outcomes were measured after discharge from the PACU. Additionally, among those studies, there was no case in which the domain of ‘bias in the measurement of the outcome’ was judged as high risk at the same time.
Despite these limitations, the current NMA has several strengths. First, this is the first NMA to compare and quantify the rank order of the relative effect of various strategies for post-CD pain, which may help patients, anesthesiologists, obstetricians, and policy makers in making evidence-based decisions. Second, a rigorous methodology based on a pre-planned protocol was applied. Specifically, we performed both frequentist and Bayesian NMA to test the robustness of the results and network meta-regression analysis to test the possible cause of heterogeneity.
5. Conclusions
This NMA shows that ITMP monotherapy is still simple and effective for post-cesarean analgesia. However, it is not the best method in terms of SUCRA values, and it cannot be an option for general anesthesia. Combined II-aTAP block in conjunction with ITMP for spinal anesthesia is the most effective analgesic strategy with lower rest pain at 6 h and morphine consumption at 24 h after surgery compared with non-active controls. Additionally, ITMP, II-IH nerve block in conjunction with ITMP, lTAP block, and WI or WC_below showed a significant reduction in the two co-primary outcomes as well. Therefore, it is reasonable to use PNBs for postoperative pain management after CD. In particular, lTAP block, WI, and WC_below may be useful alternatives if the patient reports a history of sensitivity or severe adverse effects to opioids or when the CD is conducted under general anesthesia. Finally, only the II-aTAP block had a statistically significant additional effect compared to ITMP alone on rest pain at 6 h after surgery.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/jpm12040634/s1, Figure S1: Inconsistency plots of direct and indirect comparisons for the entire network ((A) Pain at rest 6 h after surgery, (B) Postoperative cumulative 24 h morphine equivalent consumption, (C) Pain at rest 24 h after surgery, (D) Dynamic pain at 6 h after surgery, (E) Dynamic pain at 24 h after surgery, and (F) The time to first analgesic request); Figure S2: The rankograms of all outcomes ((A) Pain at rest 6 h after surgery, (B) Postoperative cumulative 24 h morphine equivalent consumption, (C) Pain at rest 24 h after surgery, (D) Dynamic pain at 6 h after surgery, (E) Dynamic pain at 24 h after surgery, and (F) The time to first analgesic request); Figure S3: The cumulative ranking curves of all outcomes ((A) Pain at rest 6 h after surgery, (B) Postoperative cumulative 24 h morphine equivalent consumption, (C) Pain at rest 24 h after surgery, (D) Dynamic pain at 6 h after surgery, (E) Dynamic pain at 24 h after surgery, and (F) The time to first analgesic request); Figure S4: Comparison-adjusted funnel plots ((A) Pain at rest 6 h after surgery, (B) Postoperative cumulative 24 h morphine equivalent consumption, (C) Pain at rest 24 h after surgery, (D) Dynamic pain at 6 h after surgery, (E) Dynamic pain at 24 h after surgery, and (F) The time to first analgesic request); Figure S5: Pain at rest 6h after surgery ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model, (F) Node splitting plot in random effect model, and (G) Rankogram in random effect model); Figure S6: Postoperative cumulative 24 h morphine equivalent consumption ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model, (F) Node splitting plot in random effect model, and (G) Rankogram in random effect model); Figure S7: Pain at rest 24 h after surgery ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model, (F) Node splitting plot in random effect model, and (G) Rankogram in random effect model); Figure S8: Dynamic pain at 6 h after surgery ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model, (F) Node splitting plot in random effect model, and (G) Rankogram in random effect model); Figure S9; Dynamic pain at 24 h after surgery ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model, (F) Node splitting plot in random effect model, and (G) Rankogram in random effect model); Figure S10: The time to first analgesic request ((A) Trace plot and density plot in fixed effect model, (B) Trace plot and density plot in random effect model, (C) Gelman-Rubin-Brooks plot in fixed effect model, (D) Gelman-Rubin-Brooks plot in random effect model, (E) Forest plot comparing with control in random effect model); Table S1: Summary of risk of bias assessment (RoB 2); Table S2: Network diagnostic for Bayesian analysis; Table S3: Network league tables for all the postcesarean analgesic strategies regarding ((A) Pain at 6 h after surgery and (B) Postoperative cumulative 24 h morphine equivalent consumption); Supplementary Materials-Methods (S1: Materials and Methods; S2: Results; S3: Discussion; S4: Search Terms). References [96,97,98,99,100,101,102,103,104,105,106,107,108,109,110,111,112,113,114,115,116,117,118,119,120,121,122,123,124,125,126,127,128,129] are cited in the Supplementary Materials.
Author Contributions
Conceptualization, C.R. and H.K.; methodology, G.J.C. and H.K.; software, H.K.; validation, G.J.C., Y.H.J., C.W.B., and C.K.C.; formal analysis, H.K.; investigation, C.R., G.J.C., and H.K.; resources, C.R. and G.J.C.; data curation, Y.H.J., C.W.B., C.K.C., and H.K.; writing—original draft preparation, C.R. and H.K.; writing—review and editing, G.J.C., Y.H.J., C.W.B., and C.K.C.; visualization, G.J.C. and H.K.; supervision, H.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The datasets used and analyzed during the current study are available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflict of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript, or in the decision to publish the results.
References
- Nikolajsen, L.; Sørensen, H.C.; Jensen, T.S.; Kehlet, H. Chronic pain following Caesarean section. Acta Anaesthesiol. Scand. 2004, 48, 111–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kehlet, H.; Jensen, T.S.; Woolf, C.J. Persistent postsurgical pain: Risk factors and prevention. Lancet 2006, 367, 1618–1625. [Google Scholar] [CrossRef] [Scilit]
- Gadsden, J.; Hart, S.; Santos, A.C. Post-cesarean delivery analgesia. Anesth. Analg. 2005, 101 (Suppl. S5), S62–S69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dahl, J.B.; Jeppesen, I.S.; Jørgensen, H.; Wetterslev, J.; Møiniche, S. Intraoperative and postoperative analgesic efficacy and adverse effects of intrathecal opioids in patients undergoing cesarean section with spinal anesthesia: A qualitative and quantitative systematic review of randomized controlled trials. Anesthesiology 1999, 91, 1919–1927. [Google Scholar] [CrossRef] [Scilit]
- Arroyo-Fernández, F.J.; Calderón Seoane, J.E.; Torres Morera, L.M. Strategies of analgesic treatment after cesarean delivery. Current state and new alternatives. Rev. Esp. Anestesiol. Reanim. 2020, 67, 167–175. [Google Scholar] [CrossRef] [Scilit]
- Mitchell, K.D.; Smith, C.T.; Mechling, C.; Wessel, C.B.; Orebaugh, S.; Lim, G. A review of peripheral nerve blocks for cesarean delivery analgesia. Reg. Anesth. Pain Med. 2020, 45, 52–62. [Google Scholar] [CrossRef] [Scilit]
- Mishriky, B.M.; George, R.B.; Habib, A.S. Transversus abdominis plane block for analgesia after Cesarean delivery: A systematic review and meta-analysis. Can. J. Anaesth. 2012, 59, 766–778. [Google Scholar] [CrossRef] [Scilit]
- Sultan, P.; Patel, S.D.; Jadin, S.; Carvalho, B.; Halpern, S.H. Transversus abdominis plane block compared with wound infiltration for postoperative analgesia following Cesarean delivery: A systematic review and network meta-analysis. Can. J. Anaesth. 2020, 67, 1710–1727. [Google Scholar] [CrossRef] [Scilit]
- Xu, M.; Tang, Y.; Wang, J.; Yang, J. Quadratus lumborum block for postoperative analgesia after cesarean delivery: A systematic review and meta-analysis. Int. J. Obstet. Anesth. 2020, 42, 87–98. [Google Scholar] [CrossRef] [Scilit]
- Hussain, N.; Brull, R.; Weaver, T.; Zhou, M.; Essandoh, M.; Abdallah, F.W. Postoperative Analgesic Effectiveness of Quadratus Lumborum Block for Cesarean Delivery under Spinal Anesthesia. Anesthesiology 2021, 134, 72–87. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T. Cochrane Handbook for Systematic Reviews of Interventions; Wiley-Blackwell: Chichester, UK, 2008. [Google Scholar]
- Cornell, J.E. The PRISMA extension for network meta-analysis: Bringing clarity and guidance to the reporting of systematic reviews incorporating network meta-analyses. Ann. Intern. Med. 2015, 162, 797–798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaimani, A.; Higgins, J.P.; Mavridis, D.; Spyridonos, P.; Salanti, G. Graphical tools for network meta-analysis in STATA. PLoS ONE 2013, 8, e76654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Valkenhoef, G.; Lu, G.; de Brock, B.; Hillege, H.; Ades, A.E.; Welton, N.J. Automating network meta-analysis. Res. Synth. Methods 2012, 3, 285–299. [Google Scholar] [CrossRef] [Scilit]
- Aydin, M.E.; Bedir, Z.; Yayik, A.M.; Celik, E.C.; Ates, I.; Ahiskalioglu, E.O.; Ahiskalioglu, A. Subarachnoid block and ultrasound-guided transversalis fascia plane block for caesarean section: A randomised, double-blind, placebo-controlled trial. Eur. J. Anaesthesiol. 2020, 37, 765–772. [Google Scholar] [CrossRef] [Scilit]
- Aydogmus, M.; Sinikoglu, S.; Naki, M.; Ocak, N.; Sanlı, N.; Alagol, A. Comparison of analgesic efficiency between wound site infiltration and ultra-sound-guided transversus abdominis plane block after cesarean delivery under spinal anaesthesia. Hippokratia 2014, 18, 28–31. [Google Scholar]
- Baaj, J.M.; Alsatli, R.A.; Majaj, H.A.; Babay, Z.A.; Thallaj, A.K. Efficacy of ultrasound-guided transversus abdominis plane (TAP) block for postcesarean section delivery analgesia—A double-blind, placebo-controlled, randomized study. Middle East J. Anaesthesiol. 2010, 20, 821–826. [Google Scholar]
- Bamigboye, A.A.; Justus, H.G. Ropivacaine abdominal wound infiltration and peritoneal spraying at cesarean delivery for preemptive analgesia. Int. J. Gynaecol. Obstet. 2008, 102, 160–164. [Google Scholar] [CrossRef] [Scilit]
- Barney, E.Z.; Pedro, C.D.; Gamez, B.H.; Fuller, M.E.; Dominguez, J.E.; Habib, A.S. Ropivacaine and Ketorolac Wound Infusion for Post-Cesarean Delivery Analgesia: A Randomized Controlled Trial. Obstet. Gynecol. 2020, 135, 427–435. [Google Scholar] [CrossRef] [Scilit]
- Belavy, D.; Cowlishaw, P.J.; Howes, M.; Phillips, F. Ultrasound-guided transversus abdominis plane block for analgesia after Caesarean delivery. Br. J. Anaesth. 2009, 103, 726–730. [Google Scholar] [CrossRef] [Scilit]
- Bell, E.A.; Jones, B.P.; Olufolabi, A.J.; Dexter, F.; Phillips-Bute, B.; Greengrass, R.A.; Penning, D.H.; Reynolds, J.D. Iliohypogastric-ilioinguinal peripheral nerve block for post-Cesarean delivery analgesia decreases morphine use but not opioid-related side effects. Can. J. Anaesth. 2002, 49, 694–700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bensghir, M.; Elwali, A.; Miller, C.; Azendour, H.; Drissi, M.; Bakkali, H.; Belyamani, L.; Atmani, M.; Drissi Kamili, N. Effects of skin infiltration with ropivacaine 0.75% on postoperative pain after caesarean section. Gynecol. Obstet. Fertil. 2008, 36, 516–520. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bessmertnyj, A.E.; Antipin, E.E.; Uvarov, D.N.; Sedyh, S.V.; Nedashkovsky, E.V. Comparison of the Effectiveness of Ilioinguinal-Iliohypogastric Blockade and Transversus Abdominis Plane Block for Analgesia after Cesarean Section. Anesteziol. Reanimatol. 2015, 60, 51–54. [Google Scholar]
- Bollag, R.; Ansari, T.; Girgis, E. Quadratus lumborum block for postoperative pain after caesarean section: A randomised controlled trial. Eur. J. Anaesthesiol. 2015, 32, 812–818. [Google Scholar]
- Blanco, R.; Ansari, T.; Riad, W.; Shetty, N. Quadratus Lumborum Block Versus Transversus Abdominis Plane Block for Postoperative Pain After Cesarean Delivery: A Randomized Controlled Trial. Reg. Anesth. Pain Med. 2016, 41, 757–762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bollag, L.; Richebe, P.; Siaulys, M.; Ortner, C.M.; Gofeld, M.; Landau, R. Effect of transversus abdominis plane block with and without clonidine on post-cesarean delivery wound hyperalgesia and pain. Reg. Anesth. Pain Med. 2012, 37, 508–514. [Google Scholar] [CrossRef] [Scilit]
- Canakci, E.; Gultekin, A.; Cebeci, Z.; Hanedan, B.; Kilinc, A. The Analgesic Efficacy of Transverse Abdominis Plane Block versus Epidural Block after Caesarean Delivery: Which One Is Effective? TAP Block? Epidural Block? Pain Res. Manag. 2018, 2018, 3562701. [Google Scholar] [CrossRef] [Scilit]
- Canovas, L.; Lopez, C.; Castro, M.; Rodriguez, A.B.; Perez, L. Contribution to post-caesarean analgesia of ultrasound-guided transversus abdominis plane block. Rev. Esp. Anestesiol. Reanim. 2013, 60, 124–128. [Google Scholar] [CrossRef] [Scilit]
- Chandon, M.; Bonnet, A.; Burg, Y.; Barnichon, C.; DesMesnards-Smaja, V.; Sitbon, B.; Foiret, C.; Dreyfus, J.F.; Rahmani, J.; Laloe, P.A.; et al. Ultrasound-guided Transversus Abdominis plane block versus continuous wound infusion for post-caesarean analgesia: A randomized trial. PLoS ONE 2014, 9, e103971. [Google Scholar]
- Corsini, T.; Cuvillon, P.; Forgeot, A.; Chapelle, C.; Seffert, P.; Chauleur, C. Single-dose intraincisional levobupivacaine infiltration in caesarean postoperative analgesia: A placebo-controlled double-blind randomized trial. Ann. Fr. Anesth. Reanim. 2013, 32, 25–30. [Google Scholar] [CrossRef] [Scilit]
- Costello, J.F.; Moore, A.R.; Wieczorek, P.M.; Macarthur, A.J.; Balki, M.; Carvalho, J.C. The transversus abdominis plane block, when used as part of a multimodal regimen inclusive of intrathecal morphine, does not improve analgesia after cesarean delivery. Reg. Anesth. Pain Med. 2009, 34, 586–589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Demiraran, Y.; Albayrak, M.; Yorulmaz, I.S.; Ozdemir, I. Tramadol and levobupivacaine wound infiltration at cesarean delivery for postoperative analgesia. J. Anesth. 2013, 27, 175–179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dereu, D.; Savoldelli, G.L.; Mercier, Y.; Combescure, C.; Mathivon, S.; Rehberg, B. The impact of a transversus abdominis plane block including clonidine vs. intrathecal morphine on nausea and vomiting after caesarean section: A randomised controlled trial. Eur. J. Anaesthesiol. 2019, 36, 575–582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ducarme, G.; Sillou, S.; Wernet, A.; Davitian, C.; Poujade, O.; Ceccaldi, P.F.; Bougeois, B.; Luton, D. Single-shot ropivacaine wound infiltration during cesarean section for postoperative pain relief. Gynecol. Obstet. Fertil. 2012, 40, 10–13. [Google Scholar] [CrossRef] [Scilit]
- Eldaba, A.A.; Amr, Y.M.; Sobhy, R.A. Effect of wound infiltration with bupivacaine or lower dose bupivacaine/magnesium versus placebo for postoperative analgesia after cesarean section. Anesth. Essays Res. 2013, 7, 336–340. [Google Scholar]
- Eslamian, L.; Jalili, Z.; Jamal, A.; Marsoosi, V.; Movafegh, A. Transversus abdominis plane block reduces postoperative pain intensity and analgesic consumption in elective cesarean delivery under general anesthesia. J. Anesth. 2012, 26, 334–338. [Google Scholar] [CrossRef] [Scilit]
- Fakor, F.; Farzi, F.; Abdollahzadeh, M.; Golrizan, F.; Kazemnejad, E. The Effect of Transversus Abdominis Plane (TAP) Block with Bupivacaine 25% on Post Cesarean Pain. J. Guilan Univ. Med. Sci. 2014, 23, 53–60. [Google Scholar]
- Fusco, P.; Cofini, V.; Petrucci, E.; Scimia, P.; Pozone, T.; Paladini, G.; Carta, G.; Necozione, S.; Borghi, B.; Marinangeli, F. Transversus Abdominis Plane Block in the Management of Acute Postoperative Pain Syndrome after Caesarean Section: A Randomized Controlled Clinical Trial. Pain Physician 2016, 19, 583–591. [Google Scholar]
- Ganta, R.; Samra, S.K.; Maddineni, V.R.; Furness, G. Comparison of the effectiveness of bilateral ilioinguinal nerve block and wound infiltration for postoperative analgesia after caesarean section. Br. J. Anaesth. 1994, 72, 229–230. [Google Scholar] [CrossRef] [Scilit]
- Gao, Y.; Guo, M.; Du, C.; Zhang, H.; Zhang, H. Clinical study of ultrasound-guided transversus abdominis plane block for analgesia after cesarean section. Medicine 2019, 98, e17542. [Google Scholar] [CrossRef] [Scilit]
- Givens, V.A.; Lipscomb, G.H.; Meyer, N.L. A randomized trial of postoperative wound irrigation with local anesthetic for pain after cesarean delivery. Am. J. Obstet. Gynecol. 2002, 186, 1188–1191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hansen, C.K.; Dam, M.; Steingrimsdottir, G.E.; Laier, G.H.; Lebech, M.; Poulsen, T.D.; Chan, V.W.S.; Wolmarans, M.; Bendtsen, T.F.; Borglum, J. Ultrasound-guided transmuscular quadratus lumborum block for elective cesarean section significantly reduces postoperative opioid consumption and prolongs time to first opioid request: A double-blind randomized trial. Reg. Anesth. Pain Med. 2019, 44, 896–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Irwin, R.; Stanescu, S.; Buzaianu, C.; Rademan, M.; Roddy, J.; Gormley, C.; Tan, T. Quadratus lumborum block for analgesia after caesarean section: A randomised controlled trial. Anaesthesia 2020, 75, 89–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jadon, A.; Jain, P.; Chakraborty, S.; Motaka, M.; Parida, S.S.; Sinha, N.; Agrawal, A.; Pati, A.K. Role of ultrasound guided transversus abdominis plane block as a component of multimodal analgesic regimen for lower segment caesarean section: A randomized double blind clinical study. BMC Anesthesiol. 2018, 18, 53. [Google Scholar] [CrossRef] [Scilit]
- Jolly, C.; Jathieres, F.; Keita, H.; Jaouen, E.; Guyot, B.; Torre, A. Cesarean analgesia using levobupivacaine continuous wound infiltration: A randomized trial. Eur. J. Obstet. Gynecol. Reprod. Biol. 2015, 194, 125–130. [Google Scholar] [CrossRef] [Scilit]
- Kagwa, S.; Hoeft, M.A.; Firth, P.G.; Ttendo, S.; Modest, V.E. Ultrasound guided transversus abdominis plane versus sham blocks after caesarean section in an Ugandan village hospital: A prospective, randomised, double-blinded, single-centre study. Lancet 2015, 385, S36. [Google Scholar] [CrossRef] [Scilit]
- Kainu, J.P.; Sarvela, J.; Halonen, P.; Puro, H.; Toivonen, H.J.; Halmesmaki, E.; Korttila, K.T. Continuous wound infusion with ropivacaine fails to provide adequate analgesia after caesarean section. Int. J. Obstet. Anesth. 2012, 21, 119–124. [Google Scholar] [CrossRef] [Scilit]
- Kanazi, G.E.; Aouad, M.T.; Abdallah, F.W.; Khatib, M.I.; Adham, A.M.; Harfoush, D.W.; Siddik-Sayyid, S.M. The analgesic efficacy of subarachnoid morphine in comparison with ultrasound-guided transversus abdominis plane block after cesarean delivery: A randomized controlled trial. Anesth. Analg. 2010, 111, 475–481. [Google Scholar] [CrossRef] [Scilit]
- Kang, W.; Lu, D.; Yang, X.; Zhou, Z.; Chen, X.; Chen, K.; Zhou, X.; Feng, X. Postoperative analgesic effects of various quadratus lumborum block approaches following cesarean section: A randomized controlled trial. J. Pain Res. 2019, 12, 2305–2312. [Google Scholar] [CrossRef] [Scilit]
- Kessous, R.; Wiznitzer, A.; Polachek, H.; Weintraub, A.Y.; Zlotnik, A.; Pariente, G.; Aricha-Tamir, B.; Press, F.; Leizerovich, A.; Sheiner, E. Preoperative analgesia with local lidocaine infiltration for post cesarean delivery pain management. J. Matern. Fetal Neonatal Med. 2012, 25, 1131–1134. [Google Scholar] [CrossRef] [Scilit]
- Kiran, L.V.; Sivashanmugam, T.; Kumar, V.R.H.; Krishnaveni, N.; Parthasarathy, S. Relative Efficacy of Ultrasound-guided Ilioinguinal-iliohypogastric Nerve Block versus Transverse Abdominis Plane Block for Postoperative Analgesia following Lower Segment Cesarean Section: A Prospective, Randomized Observer-blinded Trial. Anesth. Essays Res. 2017, 11, 713–717. [Google Scholar] [PubMed]
- Klasen, F.; Bourgoin, A.; Antonini, F.; Dazeas, E.; Bretelle, F.; Martin, C.; Baumstarck, K.; Leone, M. Postoperative analgesia after caesarean section with transversus abdominis plane block or continuous infiltration wound catheter: A randomized clinical trial. TAP vs. infiltration after caesarean section. Anaesth. Crit. Care Pain Med. 2016, 35, 401–406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krohg, A.; Ullensvang, K.; Rosseland, L.A.; Langesaeter, E.; Sauter, A.R. The Analgesic Effect of Ultrasound-Guided Quadratus Lumborum Block After Cesarean Delivery: A Randomized Clinical Trial. Anesth. Analg. 2018, 126, 559–565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kwikiriza, A.; Kiwanuka, J.K.; Firth, P.G.; Hoeft, M.A.; Modest, V.E.; Ttendo, S.S. The analgesic effects of intrathecal morphine in comparison with ultrasound-guided transversus abdominis plane block after caesarean section: A randomised controlled trial at a Ugandan regional referral hospital. Anaesthesia 2019, 74, 167–173. [Google Scholar]
- Lalmand, M.; Wilwerth, M.; Fils, J.F.; Van der Linden, P. Continuous Ropivacaine Subfascial Wound Infusion Compared with Intrathecal Morphine for Postcesarean Analgesia: A Prospective, Randomized Controlled, Double-Blind Study. Anesth. Analg. 2017, 125, 907–912. [Google Scholar] [CrossRef] [Scilit]
- Lavand’homme, P.M.; Roelants, F.; Waterloos, H.; De Kock, M.F. Postoperative analgesic effects of continuous wound infiltration with diclofenac after elective cesarean delivery. Anesthesiology 2007, 106, 1220–1225. [Google Scholar] [CrossRef] [Scilit]
- Lee, A.J.; Palte, H.D.; Chehade, J.M.; Arheart, K.L.; Ranasinghe, J.S.; Penning, D.H. Ultrasound-guided bilateral transversus abdominis plane blocks in conjunction with intrathecal morphine for postcesarean analgesia. J. Clin. Anesth. 2013, 25, 475–482. [Google Scholar] [CrossRef] [Scilit]
- Loane, H.; Preston, R.; Douglas, M.J.; Massey, S.; Papsdorf, M.; Tyler, J. A randomized controlled trial comparing intrathecal morphine with transversus abdominis plane block for post-cesarean delivery analgesia. Int. J. Obstet. Anesth. 2012, 21, 112–118. [Google Scholar] [CrossRef] [Scilit]
- Lui, M.W.; Li, T.K.T.; Lui, F.; Ong, C.Y.T. A randomised, controlled trial of rectus sheath bupivacaine and intrathecal bupivacaine, without or with intrathecal morphine, vs. intrathecal bupivacaine and morphine after caesarean section. Anaesthesia 2017, 72, 1225–1229. [Google Scholar] [CrossRef] [Scilit]
- Magnani, E.; Corosu, R.; Mancino, P.; Borgia, M.L. Postoperative analgesia after cesarean section by continued administration of levobupivacaine with the On-Q Painbuster system over the fascia vs ketorolac + morphine i.v. Clin. Exp. Obstet. Gynecol. 2006, 33, 223–225. [Google Scholar]
- Malawat, A.; Verma, K.; Jethava, D.; Jethava, D.D. Erector spinae plane block and transversus abdominis plane block for postoperative analgesia in cesarean section: A prospective randomized comparative study. J. Anaesthesiol. Clin. Pharmacol. 2020, 36, 201–206. [Google Scholar] [PubMed]
- Mankikar, M.G.; Sardesai, S.P.; Ghodki, P.S. Ultrasound-guided transversus abdominis plane block for post-operative analgesia in patients undergoing caesarean section. Indian J. Anaesth. 2016, 60, 253–257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McKeen, D.M.; George, R.B.; Boyd, J.C.; Allen, V.M.; Pink, A. Transversus abdominis plane block does not improve early or late pain outcomes after Cesarean delivery: A randomized controlled trial. Can. J. Anaesth. 2014, 61, 631–640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McMorrow, R.C.; Ni Mhuircheartaigh, R.J.; Ahmed, K.A.; Aslani, A.; Ng, S.C.; Conrick-Martin, I.; Dowling, J.J.; Gaffney, A.; Loughrey, J.P.; McCaul, C.L. Comparison of transversus abdominis plane block vs spinal morphine for pain relief after Caesarean section. Br. J. Anaesth. 2011, 106, 706–712. [Google Scholar] [CrossRef] [Scilit]
- Mecklem, D.W.; Humphrey, M.D.; Hicks, R.W. Efficacy of bupivacaine delivered by wound catheter for post-Caesarean section analgesia. Aust. N. Z. J. Obstet. Gynaecol. 1995, 35, 416–421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mieszkowski, M.M.; Mayzner-Zawadzka, E.; Tuyakov, B.; Mieszkowska, M.; Zukowski, M.; Wasniewski, T.; Onichimowski, D. Evaluation of the effectiveness of the Quadratus Lumborum Block type I using ropivacaine in postoperative analgesia after a cesarean section—A controlled clinical study. Ginekol. Pol. 2018, 89, 89–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naghshineh, E.; Shiari, S.; Jabalameli, M. Preventive effect of ilioinguinal nerve block on postoperative pain after cesarean section. Adv. Biomed. Res. 2015, 4, 229. [Google Scholar]
- Niklasson, B.; Borjesson, A.; Carmnes, U.B.; Segerdahl, M.; Ohman, S.G.; Blanck, A. Intraoperative injection of bupivacaine-adrenaline close to the fascia reduces morphine requirements after cesarean section: A randomized controlled trial. Acta Obstet. Gynecol. Scand. 2012, 91, 1433–1439. [Google Scholar] [CrossRef] [Scilit]
- O’Neill, P.; Duarte, F.; Ribeiro, I.; Centeno, M.J.; Moreira, J. Ropivacaine continuous wound infusion versus epidural morphine for postoperative analgesia after cesarean delivery: A randomized controlled trial. Anesth. Analg. 2012, 114, 179–185. [Google Scholar] [CrossRef] [Scilit]
- Patel, R.; Carvalho, J.C.; Downey, K.; Kanczuk, M.; Bernstein, P.; Siddiqui, N. Intraperitoneal Instillation of Lidocaine Improves Postoperative Analgesia at Cesarean Delivery: A Randomized, Double-Blind, Placebo-Controlled Trial. Anesth. Analg. 2017, 124, 554–559. [Google Scholar] [CrossRef] [Scilit]
- Rackelboom, T.; Strat, S.L.; Silvera, S.; Schmitz, T.; Bassot, A.; Goffinet, F.; Ozier, Y.; Beaussier, M.; Mignon, A. Improving continuous wound infusion effectiveness for postoperative analgesia after cesarean delivery: A randomized controlled trial. Obstet. Gynecol. 2010, 116, 893–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reinikainen, M.; Syvaoja, S.; Hara, K. Continuous wound infiltration with ropivacaine for analgesia after caesarean section: A randomised, placebo-controlled trial. Acta Anaesthesiol. Scand. 2014, 58, 973–979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salama, E.R. Ultrasound-guided bilateral quadratus lumborum block vs. intrathecal morphine for postoperative analgesia after cesarean section: A randomized controlled trial. Korean J. Anesthesiol. 2020, 73, 121–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sekhavat, L.; Behdad, S. Preoperative analgesia with local lidocaine for cesarean delivery pain relief. J. Matern. Fetal Neonatal Med. 2011, 24, 891–893. [Google Scholar] [CrossRef] [Scilit]
- Serifsoy, T.E.; Tulgar, S.; Selvi, O.; Senturk, O.; Ilter, E.; Peker, B.H.; Ozer, Z. Evaluation of ultrasound-guided transversalis fascia plane block for postoperative analgesia in cesarean section: A prospective, randomized, controlled clinical trial. J. Clin. Anesth. 2020, 59, 56–60. [Google Scholar] [CrossRef] [Scilit]
- Shahin, A.Y.; Osman, A.M. Intraperitoneal lidocaine instillation and postcesarean pain after parietal peritoneal closure: A randomized double-blind placebo-controlled trial. Clin. J. Pain 2010, 26, 121–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, S.; Dhir, S.; Marmai, K.; Rehou, S.; Silva, M.; Bradbury, C. Efficacy of ultrasound-guided transversus abdominis plane blocks for post-cesarean delivery analgesia: A double-blind, dose-comparison, placebo-controlled randomized trial. Int. J. Obstet. Anesth. 2013, 22, 188–193. [Google Scholar] [CrossRef] [Scilit]
- Srivastava, U.; Verma, S.; Singh, T.K.; Gupta, A.; Saxsena, A.; Jagar, K.D.; Gupta, M. Efficacy of trans abdominis plane block for post cesarean delivery analgesia: A double-blind, randomized trial. Saudi J. Anaesth. 2015, 9, 298–302. [Google Scholar]
- Staker, J.J.; Liu, D.; Church, R.; Carlson, D.J.; Panahkhahi, M.; Lim, A.; LeCong, T. A triple-blind, placebo-controlled randomised trial of the ilioinguinal-transversus abdominis plane (I-TAP) nerve block for elective caesarean section. Anaesthesia 2018, 73, 594–602. [Google Scholar] [CrossRef] [Scilit]
- Svirskiǐ, D.A.; Antipin, E.E.; Uvarov, D.N.; Nedashkovskiǐ, E.V. Abdominal cross section space blockade as a component of the multimodal postoperative analgesia in patients after cesarean section: Blockade efficiency analysis. Anesteziol. Reanimatol. 2012, 6, 33–35. [Google Scholar]
- Pavy, T.; Gambling, D.; Kliffer, P.; Munro, A.; Merrick, P.M.; Douglas, J. Effect of preoperative skin infiltration with 0.5% bupivacaine on postoperative pain following cesarean section under spinal anesthesia. Int. J. Obstet. Anesth. 1994, 3, 199–202. [Google Scholar] [CrossRef] [Scilit]
- Tamura, T.; Yokota, S.; Ando, M.; Kubo, Y.; Nishiwaki, K. A triple-blinded randomized trial comparing spinal morphine with posterior quadratus lumborum block after cesarean section. Int. J. Obstet. Anesth. 2019, 40, 32–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tan, T.T.; Teoh, W.H.; Woo, D.C.; Ocampo, C.E.; Shah, M.K.; Sia, A.T. A randomised trial of the analgesic efficacy of ultrasound-guided transversus abdominis plane block after caesarean delivery under general anaesthesia. Eur. J. Anaesthesiol. 2012, 29, 88–94. [Google Scholar] [CrossRef] [Scilit]
- Tawfik, M.M.; Mohamed, Y.M.; Elbadrawi, R.E.; Abdelkhalek, M.; Mogahed, M.M.; Ezz, H.M. Transversus Abdominis Plane Block Versus Wound Infiltration for Analgesia After Cesarean Delivery: A Randomized Controlled Trial. Anesth. Analg. 2017, 124, 1291–1297. [Google Scholar] [CrossRef] [Scilit]
- Telnes, A.; Skogvoll, E.; Lonnee, H. Transversus abdominis plane block vs. wound infiltration in Caesarean section: A randomised controlled trial. Acta Anaesthesiol. Scand. 2015, 59, 496–504. [Google Scholar] [CrossRef] [Scilit]
- Triyasunant, N.; Chinachoti, T.; Duangburong, S. Direct Field Block with 40 ML of 0.125% Bupivacaine in Conjunction with Intrathecal Morphine for Analgesia after Cesarean Section: A Randomized Controlled Trial. J. Med. Assoc. Thai. 2015, 98, 1001–1009. [Google Scholar] [PubMed]
- Trotter, T.N.; Hayes-Gregson, P.; Robinson, S.; Cole, L.; Coley, S.; Fell, D. Wound infiltration of local anaesthetic after lower segment caesarean section. Anaesthesia 1991, 46, 404–407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vallejo, M.C.; Steen, T.L.; Cobb, B.T.; Phelps, A.L.; Pomerantz, J.M.; Orebaugh, S.L.; Chelly, J.E. Efficacy of the bilateral ilioinguinal-iliohypogastric block with intrathecal morphine for postoperative cesarean delivery analgesia. Sci. World J. 2012, 2012, 107316. [Google Scholar] [CrossRef] [Scilit]
- Wagner-Kovacec, J.; Povalej-Brzan, P.; Mekis, D. Efficacy of continuous in-wound infusion of levobupivacaine and ketorolac for post-caesarean section analgesia: A prospective, randomised, double-blind, placebo-controlled trial. BMC Anesthesiol. 2018, 18, 165. [Google Scholar] [CrossRef] [Scilit]
- Wolfson, A.; Lee, A.J.; Wong, R.P.; Arheart, K.L.; Penning, D.H. Bilateral multi-injection iliohypogastric-ilioinguinal nerve block in conjunction with neuraxial morphine is superior to neuraxial morphine alone for postcesarean analgesia. J. Clin. Anesth. 2012, 24, 298–303. [Google Scholar] [CrossRef] [Scilit]
- Sutton, C.D.; Carvalho, B. Optimal Pain Management After Cesarean Delivery. Anesthesiol. Clin. 2017, 35, 107–124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sultan, P.; Halpern, S.H.; Pushpanathan, E.; Patel, S.; Carvalho, B. The Effect of Intrathecal Morphine Dose on Outcomes After Elective Cesarean Delivery: A Meta-Analysis. Anesth. Analg. 2016, 123, 154–164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forero, M.; Adhikary, S.D.; Lopez, H.; Tsui, C.; Chin, K.J. The Erector Spinae Plane Block: A Novel Analgesic Technique in Thoracic Neuropathic Pain. Reg. Anesth. Pain Med. 2016, 41, 621–627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdallah, F.W.; Laffey, J.G.; Halpern, S.H.; Brull, R. Duration of analgesic effectiveness after the posterior and lateral transversus abdominis plane block techniques for transverse lower abdominal incisions: A meta-analysis. Br. J. Anaesth. 2013, 111, 721–735. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jarraya, A.; Zghal, J.; Abidi, S.; Smaoui, M.; Kolsi, K. Subarachnoid morphine versus TAP blocks for enhanced recovery after caesarean section delivery: A randomized controlled trial. Anaesth. Crit. Care Pain Med. 2016, 35, 391–393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kupiec, A.; Zwierzchowski, J.; Kowal-Janicka, J.; Goździk, W.; Fuchs, T.; Pomorski, M.; Zimmer, M.; Kübler, A. The analgesic efficiency of transversus abdominis plane (TAP) block after caesarean delivery. Ginekol. Polska 2018, 89, 421–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sriramka, B.; Sahoo, N.; Panigrahi, S. Analgesic Efficacy of Ultrasound-guided Transversus Abdominis Plane Block following Caesarean Section. Int. J. Perioper. Ultrasound Appl. Technol. 2012, 1, 5–8. [Google Scholar] [CrossRef] [Scilit]
- Tuncer, S.; Aysolmaz, G.; Reisli, R.; Erol, A.; Yalçin, N.; Yosunkaya, A. The effects of the administration of subfacial levobupivacaine infusion with the ON-Q pain pump system on postoperative analgesia and tramadol consumption in cesarean operations. Agri 2010, 22, 73–78. [Google Scholar]
- Qian, H.; Zhang, Q.; Zhu, P.; Zhang, X.; Tian, L.; Feng, J.; Wu, Y.; Zhao, Z.; Luan, H. Ultrasound-guided transversus abdominis plane block using ropivacaine and dexmedetomidine in patients undergoing caesarian sections to relieve post-operative analgesia: A randomized controlled clinical trial. Exp. Ther. Med. 2020, 20, 1163–1168. [Google Scholar] [CrossRef] [Scilit]
- Buluc, H.; Ar, A.Y.; Turan, G.; Karadogan, F.; Sargin, M.A.; Akgun, N. The efficacy of transversus abdominis plane block for post-operative analgesia after the cesarean section performed under general anesthesia. North. Clin. Istanb. 2019, 6, 368–373. [Google Scholar] [CrossRef] [Scilit]
- Akkaya, A.; Yildiz, I.; Tekelioglu, U.Y.; Demirhan, A.; Bayir, H.; Ozlu, T.; Bilgi, M.; Kocoglu, H. Dexamethasone added to levobupivacaine in ultrasound-guided tranversus abdominis plain block increased the duration of postoperative analgesia after caesarean section: A randomized, double blind, controlled trial. Eur. Rev. Med. Pharmacol. Sci. 2014, 18, 717–722. [Google Scholar] [PubMed]
- Behdad, S.; Sekhavat, L.; Ayatollahi, V.; Meshkat, F.; Mortazavi, A. Comparison of postoperative analgesic effect of tramadol and bupivacaine subcutaneous infiltration in patients undergoing cesarean section. Acta Clin. Croat. 2013, 52. [Google Scholar]
- Eslamian, L.; Kabiri-Nasab, M.; Agha-Husseini, M.; Azimaraghi, O.; Barzin, G.; Movafegh, A. Adding Sufentanil to TAP Block Hyperbaric Bupivacaine Decreases Post-Cesarean Delivery Morphine Consumption. Acta Med. Iran. 2016, 54, 185–190. [Google Scholar] [PubMed]
- Gupta, A.; Gupta, A.; Yadav, N. Effect of dexamethasone as an adjuvant to ropivacaine on duration and quality of analgesia in ultrasound-guided transversus abdominis plane block in patients undergoing lower segment cesarean section—A prospective, randomised, single-blinded study. Indian J. Anaesth. 2019, 63, 469–474. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haliloglu, M.; Bilgen, S.; Menda, F.; Ozcan, P.; Ozbay, L.; Tatar, S.; Unal, D.O.; Koner, O. Analgesic efficacy of wound infiltration with tramadol after cesarean delivery under general anesthesia: Randomized trial. J. Obstet. Gynaecol. Res. 2016, 42, 816–821. [Google Scholar] [CrossRef] [Scilit]
- Ranjan, R.; John, R.; Ramachandran, T.; George, S.K. Analgesic efficacy of transverse abdominal plane block after elective cesarean delivery—Bupivacaine with fentanyl versus bupivacaine alone: A randomized, double-blind controlled clinical trial. Anesth. Essays Res. 2017, 11, 181–184. [Google Scholar] [CrossRef] [Scilit]
- Zachariah, S.K.; Joseph, B.; Abraham, S.P. The comparison of effects of fentanyl and dexmedetomidine as adjuvants to ropivacaine for ultrasound-guided transversus abdominis plane block for postoperative pain in cesarean section under spinal anesthesia –A randomized controlled trial. J. Anaesthesiol. Clin. Pharmacol. 2020, 36, 377–380. [Google Scholar] [CrossRef] [Scilit]
- Tharwat, A.A.; Yehia, A.H.; Wahba, K.A.; Ali, A.-E.G. Efficacy and safety of post-cesarean section incisional infiltration with lidocaine and epinephrine versus lidocaine alone in reducing postoperative pain: A randomized controlled double-blinded clinical trial. J. Turk. Gynecol. Assoc. 2016, 17, 1–5. [Google Scholar] [CrossRef] [Scilit]
- Katz, D.; Hamburger, J.; Gutman, D.; Wang, R.; Lin, H.; Marotta, M.; Zahn, J.; Beilin, Y. The Effect of Adding Subarachnoid Epinephrine to Hyperbaric Bupivacaine and Morphine for Repeat Cesarean Delivery: A Double-blind Prospective Randomized Control Trial. Obstet. Anesth. Dig. 2019, 39, 51–52. [Google Scholar] [CrossRef] [Scilit]
- Onishi, Y.; Kato, R.; Okutomi, T.; Tabata, K.-I.; Amano, K.; Unno, N. Transversus abdominis plane block provides postoperative analgesic effects after cesarean section: Additional analgesia to epidural morphine alone. J. Obstet. Gynaecol. Res. 2013, 39, 1397–1405. [Google Scholar] [CrossRef] [Scilit]
- Ekmekçi, P.; Çağlar, G.S.; Yilmaz, H.; Kazbek, B.K.; Gursoy, A.Y.; Kiseli, M.; Tüzüner, F.; Yılmaz, H.; Gursoy, A.Y. Effects of different doses of tramadol added to levobupivacaine in continuous wound infusion for postoperative pain treatment following cesarean section. J. Matern. Neonatal Med. 2016, 30, 343–346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohamed, A.Z.E.A. Assessment of the analgesic potency of ropivacaine 0.2% versus ropivacaine 0.5% in transversus abdominis plane block after cesarean delivery. Egypt. J. Anaesth. 2016, 32, 385–390. [Google Scholar] [CrossRef] [Scilit]
- Aly, M.; Ibrahim, A.; Farrag, W.; Abdelsalam, K.; Mohamed, H.; Tawfik, A. Pruritus after intrathecal morphine for cesarean delivery: Incidence, severity and its relation to serum serotonin level. Int. J. Obstet. Anesthesia 2018, 35, 52–56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kintu, A.; Abdulla, S.; Lubikire, A.; Nabukenya, M.T.; Igaga, E.; Bulamba, F.; Semakula, D.; Olufolabi, A.J. Postoperative pain after cesarean section: Assessment and management in a tertiary hospital in a low-income country. BMC Health Serv. Res. 2019, 19, 68. [Google Scholar] [CrossRef] [Scilit]
- Joshi, G.; Gandhi, K.; Shah, N.; Gadsden, J.; Corman, S.L. Peripheral nerve blocks in the management of postoperative pain: Challenges and opportunities. J. Clin. Anesth. 2016, 35, 524–529. [Google Scholar] [CrossRef] [Scilit]
- Viera, A.J.; Garrett, J.M. Understanding interobserver agreement: The kappa statistic. Fam. Med. 2005, 37, 360–363. [Google Scholar]
- Hozo, S.P.; Djulbegovic, B.; Hozo, I. Estimating the mean and variance from the median, range, and the size of a sample. BMC Med. Res. Methodol. 2005, 5, 13. [Google Scholar] [CrossRef] [Scilit]
- Wan, X.; Wang, W.; Liu, J.; Tong, T. Estimating the sample mean and standard deviation from the sample size, median, range and/or interquartile range. BMC Med Res. Methodol. 2014, 14, 135. [Google Scholar] [CrossRef] [Scilit]
- White, I.R.; Barrett, J.K.; Jackson, D.; Higgins, J.P.T. Consistency and inconsistency in network meta-analysis: Model estimation using multivariate meta-regression. Res. Synth. Methods 2012, 3, 111–125. [Google Scholar] [CrossRef] [Scilit]
- Salanti, G.; Ades, A.; Ioannidis, J.P. Graphical methods and numerical summaries for presenting results from multiple-treatment meta-analysis: An overview and tutorial. J. Clin. Epidemiol. 2011, 64, 163–171. [Google Scholar] [CrossRef] [Scilit]
- Riley, R.D.; Higgins, J.; Deeks, J. Interpretation of random effects meta-analyses. BMJ 2011, 342, d549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rackelboom, T.; Le Strat, S.; Silvera, S.; Schmitz, T.; Bassot, A.; Goffinet, F.; Ozier, Y.; Beaussier, M.; Mignon, A. Improving Continuous Wound Infusion Effectiveness for Postoperative Analgesia After Cesarean Delivery. Obstet. Gynecol. 2010, 116, 893–900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Milan, Z.; Tabor, D.; McConnell, P.; Pickering, J.; Kocarev, M.; Du Feu, F.; Barton, S. Three different approaches to Transversus abdominis planeblock: A cadaveric study. Med. Glas. 2011, 8, 181–184. [Google Scholar]
- Hansen, C.K.; Dam, M.; Bendtsen, T.F.; Børglum, J. Ultrasound-Guided Quadratus Lumborum Blocks. Astron. Astrophys. 2016, 6, 39. [Google Scholar] [CrossRef] [Scilit]
- Elsharkawy, H.; El-Boghdadly, K.; Barrington, M. Quadratus Lumborum Block. Anesthesiol. 2019, 130, 322–335. [Google Scholar] [CrossRef] [Scilit]
- Patel, S.; El Sharawi, N.; Sultan, P. Local anaesthetic techniques for post-caesarean delivery analgesia. Int. J. Obstet. Anesthesia 2019, 40, 62–77. [Google Scholar] [CrossRef] [Scilit]
- Lee, T.H.W.; Barrington, M.J.; Tran, T.M.N.; Wong, D.; Hebbard, P.D. Comparison of Extent of Sensory Block following Posterior and Subcostal Approaches to Ultrasound-Guided Transversus Abdominis Plane Block. Anaesth. Intensiv. Care 2010, 38, 452–460. [Google Scholar] [CrossRef] [Scilit]
- Moore, K.L.; Dalley, A.F.; Agur, A.M.R. Clinically Oriented Anatomy, 8th ed.; Wolters Kluwer Health/Lippincott Williams & Wilkins: Philadelphia, PA, USA, 2010. [Google Scholar]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).