


Abstract
Research on healthy aging commonly concerns problems related to loneliness and food intake. These are not independent aspects of health since eating, beyond its biological necessity, is a central part of social life. This scoping review aimed to map scientific articles on eating alone or together among community-living older people, and to identify relevant research gaps. Four databases were searched, 989 articles were identified and 98 fulfilled the inclusion criteria. In the first theme, eating alone or together are treated as central topics of interest, isolated from adjoining, broader concepts such as social participation. In the second, eating alone or together are one aspect of the findings, e.g., one of several risk factors for malnutrition. Findings confirm the significance of commensality in older peoples’ life. We recommend future research designs allowing identification of causal relationships, using refined ways of measuring meals alone or together, and qualitative methods adding complexity.
1. Introduction
Research on health and aging commonly concerns problems related to loneliness [1] and food intake [2]. The prevalence of perceived loneliness and food-related problems increases with age and often has a multifactorial origin, due to common age-related physiological, socio-economic, and psychological changes [2,3]. Furthermore, loneliness and food-related problems are not independent aspects of health since eating, beyond its biological necessity, is a central part of social life [4]. In fact, the practice of sharing a meal—commensality—has been identified as one key social influence on eating behavior in later life, which can stimulate greater pleasure from food and may improve nutritional status [5].
The number of older people is growing [6] and so is the requirement to stay in community-living and independently for long periods of time. Nevertheless, reviews on food in later life that illuminate the role of eating alone or with others have primarily focused on institutionalized people [7,8], thus overlooking a large community-living population. Consequently, the aim of this article was to map the currently available scientific articles on eating alone or together with others among community-living older people. The research question was: which topics, methods, and main results are dominating the literature? Additionally, we aimed to identify research gaps relevant for future studies. With this aim, of searching broadly across disciplines, methodological approaches, outcomes (sociocultural, psychological, dietary, etc.), and geographical locations, a scoping review was chosen as our method.
2. Materials and Methods
This scoping review followed the framework established by Arksey and O′Malley [9] and enhanced by Levac et al. [10].
2.1. Search Strategy
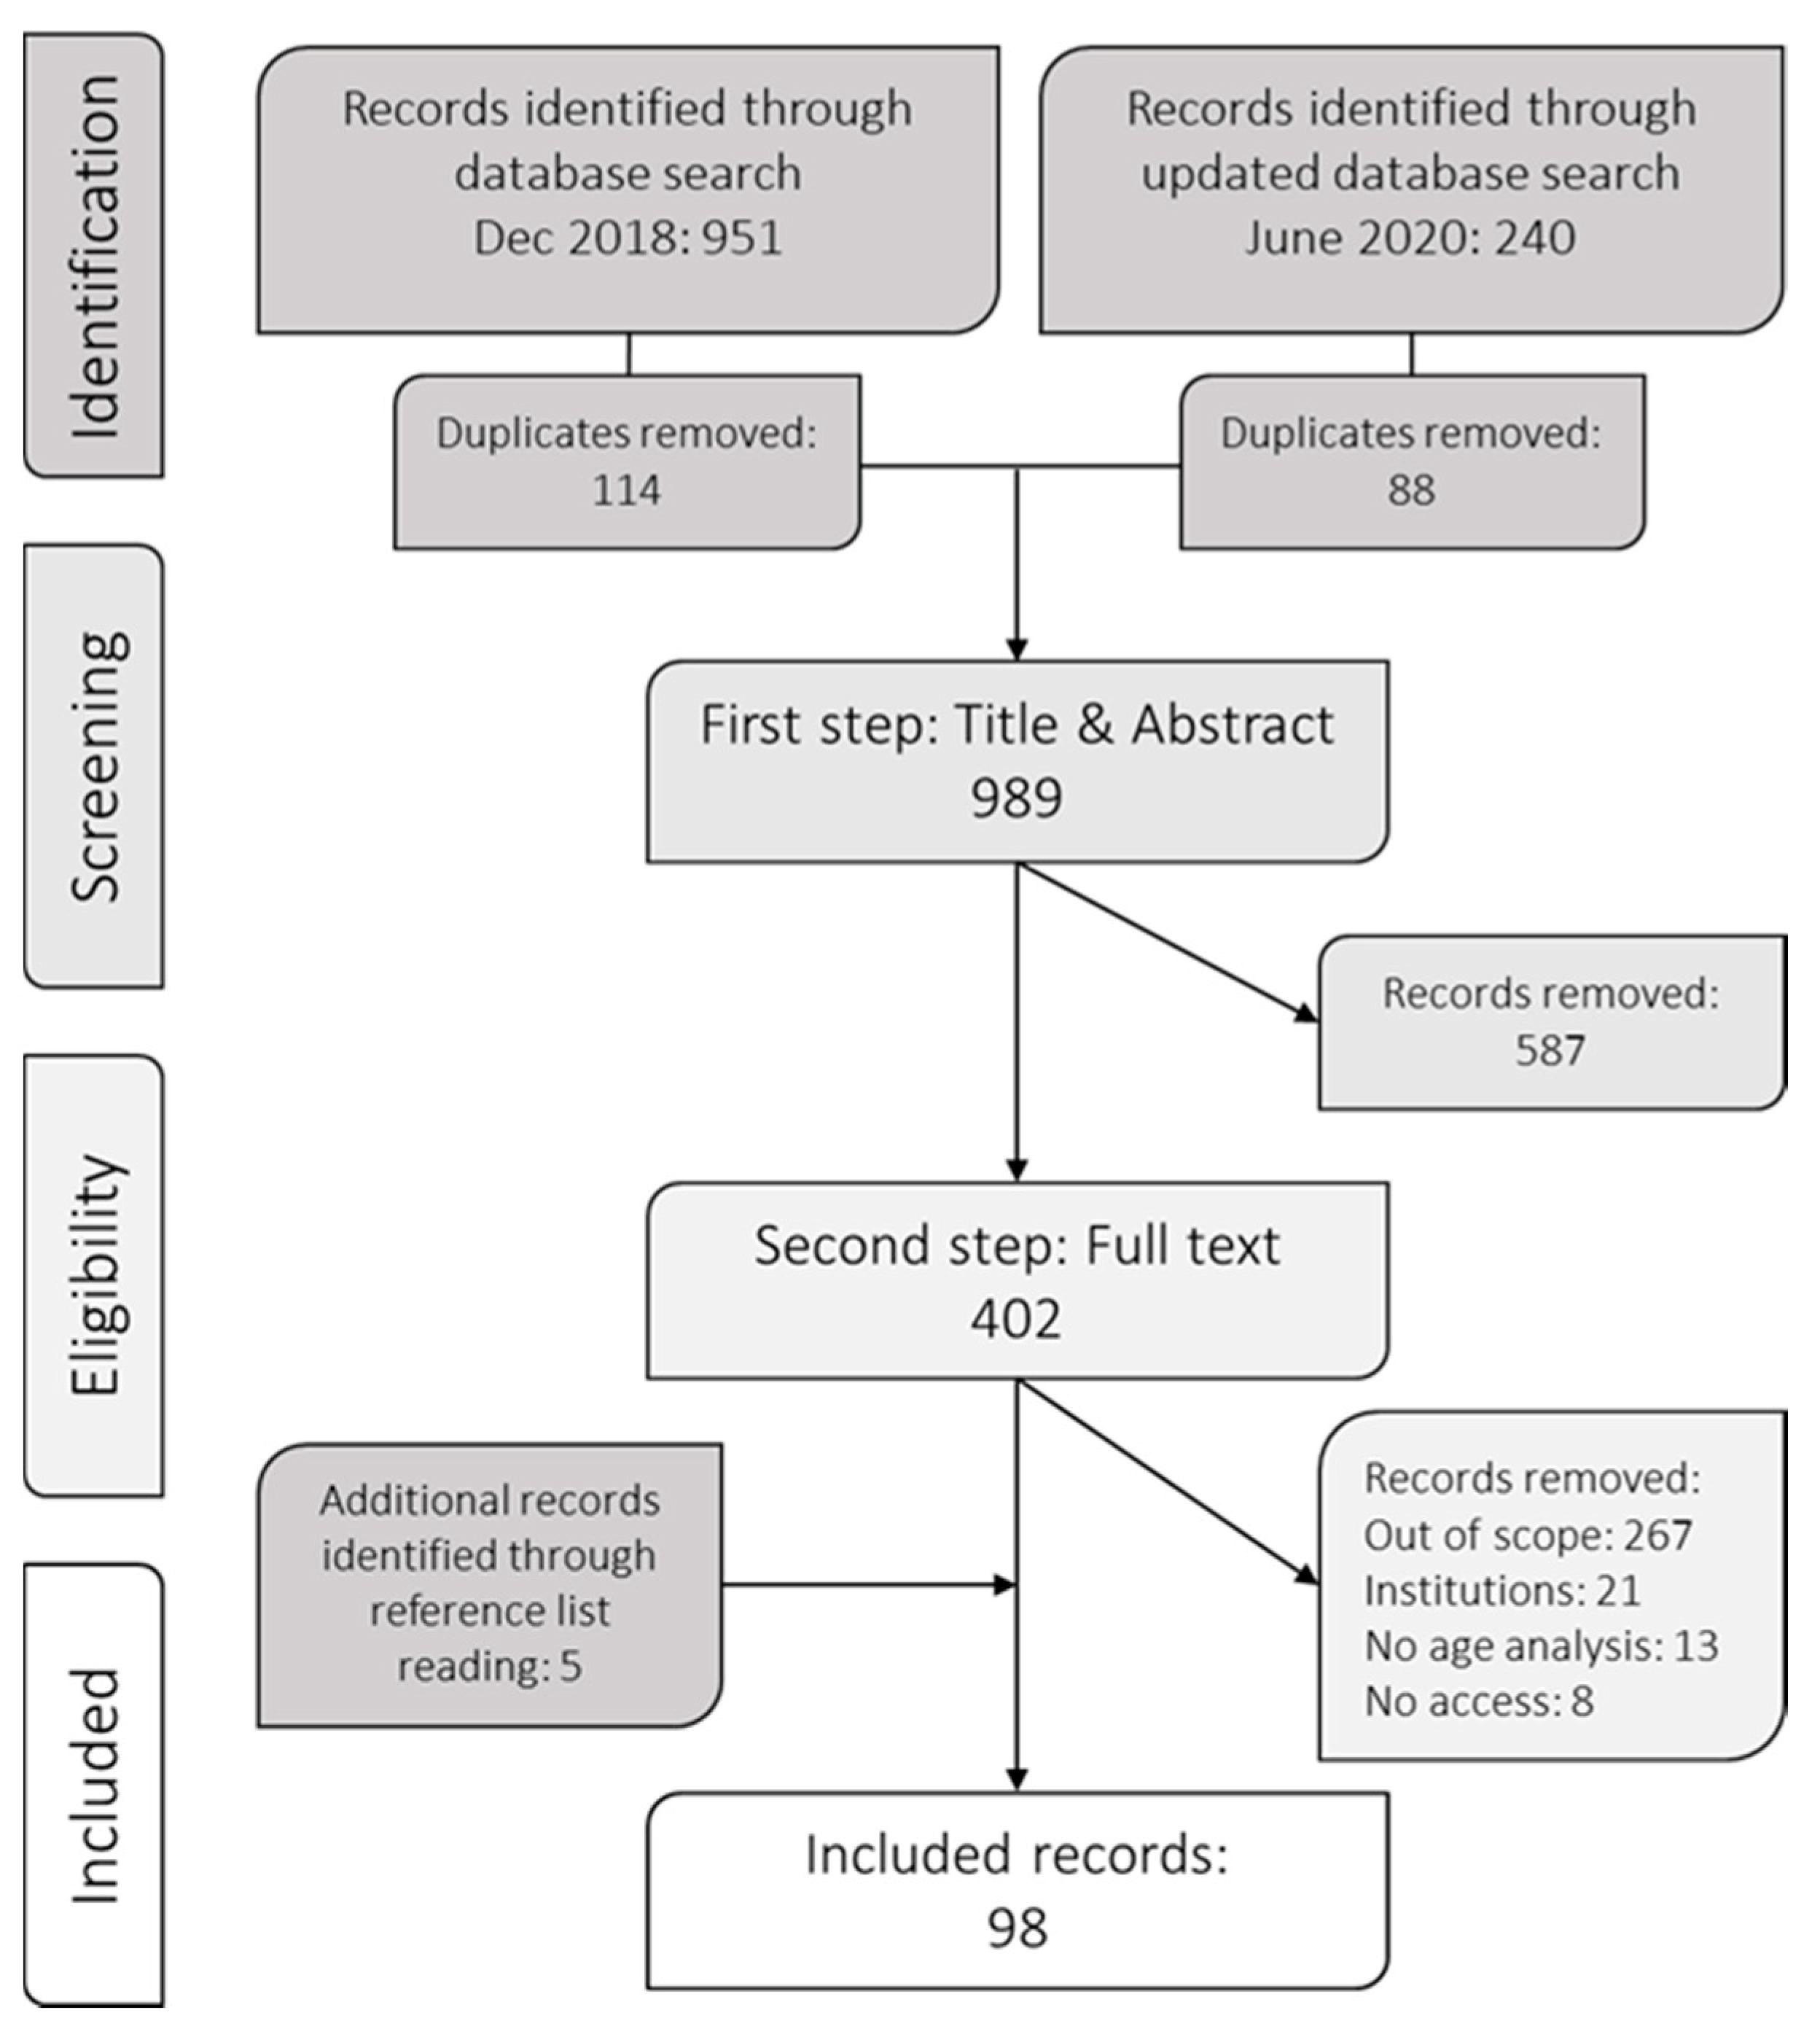
To find relevant studies a block search method was used, including three blocks: target group, meals and social aspects. In order for an article to be identified in the list of results, it was necessary to have a hit of one or more search terms in each of the three blocks. Databases and search terms were established by first consulting with a librarian who was experienced in literature searches in public health sciences, and then by carrying out several test runs to calibrate the search. Databases used were PubMed, Web of Science, Cinahl, and PsycInfo (search terms in Appendix A). To enable a broad search, no limits were set regarding the time of publication (see full electronic search strategy in Appendix B). The literature search was conducted in December 2018 and updated in June 2020. The list of results was managed in a bibliographic software (EndNote X8; Clarivate, Philadelphia, PA, USA); after manual removal of duplicates (by software and manually), the total number of unique hits were 989.
2.2. Study Selection Process
Title and abstract for all the hits were screened by two independent readers and were either included for further review or excluded. Inclusion criteria for the first step of screening were: English or Swedish language; human studies; no study protocols; older people as target group, or a part of target group (e.g., 18 and above) and including social aspects of the meal. The screening process is summarized in Figure 1. During the first step, all abstracts indicating that social aspects of meals could have potentially been studied were included. Examples of such terms were “social participation,” “social support,” and “social isolation.” Moreover, “older” means different things in the literature. We therefore followed the definitions used by the respective authors. In other words, if the author(s) of an article wrote that the study included older people, or if the age range of a study was wide with no explicit exclusion of older people, it was included in this review. Disagreements and uncertainties were resolved after deliberation by A.B. and N.N.
Figure 1.
Flowchart of screening process.
In the second step, full texts of the articles were collected and read. The terms indicating social aspects were scanned and all studies not including eating alone or eating together with others were excluded. To reduce the risk of studies being included more than once in the results, review articles were excluded. Only the articles including community-living older adults were included for further review compared to living institutionalized (e.g., long-term care, hospital, etc.). “Community-living” was defined as living independently, and studies were included when this was made explicit or unless another living situation was described. Several articles lacked analyses or discussions related to age, even though older people were included in the study sample. These articles were therefore excluded, since the lack of any detail about older people meant that it did not reveal any information corresponding to the aim. Lastly, as in the first step, disagreements and uncertainties were resolved after deliberation by A.B. and N.N.
2.3. Data Analysis
When charting the data, three main categories were created to get an overview of the results that were most central to our research question. The first category included articles where eating alone or together was the central topic, meaning that it was clear from the build-up of the articles, the methodology sections, the results, and the discussions that the role of eating alone or not was at the core of the research. In the second category, eating alone or together was included as one aspect in a larger context, where eating alone was discussed but not dominant in the results or discussions. In other words, these aspects were formulated as relevant for the research, but not at the core. The third category included articles where eating alone or together was peripheral although it occurred in the method or as a minor part of the results.
In the next section, we present the findings from the first and second categories. Since articles in the third category did not contribute substantially to the aim, they are presented in Appendix C and Table A3. Our findings are not synthesized or weighed together [9,10]. Nonetheless, the large body of material included are collated and an overview is presented with relevant examples highlighted.
3. Results
3.1. Study Characteristics
After the screening, 98 articles were included. The majority used quantitative methods and consist of cross-sectional surveys (n = 45), longitudinal surveys (n = 9), and experimental studies (n = 4). About one-third used qualitative methods, most commonly individual interviews (n = 17), focus group interviews (n = 7), other study designs or a combination of qualitative study designs (n = 7). Nine articles, combining quantitative and qualitative methodologies were included. Most articles came from Northern America (40%), Northern Europe (24%), and Eastern Asia (16%). The most prevalent countries among all studies were USA (n = 33), UK (n = 14) and Japan (n = 9), followed by a wide spread of countries contributing with five or less (Appendix D).
3.2. Eating Alone as Central Topic
Eating alone is the central topic in one-third of the articles (n = 30), consisting of both quantitative and qualitative studies with several different aims and methods. Prominent topics examined were: dietary behavior, depressive symptoms, household eating arrangements, loneliness, and coping with grief. The most relevant examples for our study aim are described below, and all articles included are presented in Table 1.
3.2.1. Quantitative Studies
In most quantitative studies, different health variables in relation to eating alone were surveyed, such as dietary behavior [11,12], subjective well-being [13], metabolic syndrome [14], or mortality [15,16]. One example was a longitudinal study (n = 2584), testing the combined effect of nutritional status and eating alone, a variable based on the question “Are there others present during your meals?” on cognitive changes [17]. Nutritional status was found as one salient predictor of cognitive decline, and women who had a compromised nutritional status at baseline and ate alone had a greater cognitive decline than those eating together. The authors conclude that nutritional programs for older people should focus on what they eat as well as with whom. A study using a cross-sectional design (n = 2196), examined subjective well-being among older people living alone [13]. Those who ate together less than once a month had lower rates of subjective health, food diversity, and food intake frequency than those who ate together more often. Another study, with a similar topic and design (n = 83,364) examined dietary behavior and body weight status in relation to eating alone and found that men who exclusively ate alone were more likely to skip meals than men who ate with others [11]. The authors concluded that among men, eating and living alone may be jointly associated with a higher prevalence of both obesity and underweight, as well as unhealthy food habits.
Eating alone was examined in relation to depressive symptoms and, compared to eating together, it was associated with higher rates [18,19,20,21,22]. One of the studies had a longitudinal design (n = 37,130); apart from a generally increased risk of depressive symptoms, the authors argued that among men, the negative effects ascribed to eating alone could be amplified when living alone [20]. Eating together with company was studied by asking “Who do you usually have meals with?” with the response alternatives: “no one”/“spouse”/“children”/“grandchildren”/“friends”/“other.” Furthermore, in three of the articles, it was suggested that those who ate alone, yet lived with their families, seemed to be at a particular risk [19,21,22]. This category, also used in Torres et al. [23], was only represented by small proportions of the samples (around 5%).
Another set of studies looked at eating arrangements, without any outcomes on health and well-being. Yates and Warde [24] used an online survey to look at eating alone and living arrangements among adults in British households (n = 2784). They found that older respondents were more likely than younger to eat with companions if they lived with others, whereas the oldest respondents living alone were least likely to eat with others. Jacobson et al. [25] used questionnaires (n = 625) in combination with qualitative interviews (n = 9) in the Cyprus context to examine households′ food expenditure as well as “food as a shared meal in the sociological sense” (p. 677). They found that there was a relatively high expenditure on food for home consumption by older couples, which may be explained by older people providing food when younger family members (i.e., children and grandchildren) frequently come to their homes for shared meals. Furthermore, a Japanese study examining the frequencies of family commensality, comparing differences between people under and over 60 (n = 242), found that those older than 60 had the highest commensal frequency; moreover, it was the only age group exceeding the national average rate of commensal meals [26].
Lastly, three experimental studies were included in this category. One randomized controlled pilot study examined the effects of a mealtime intervention in older participants (n = 50 control group; n = 50 intervention group) living alone and in self-reported risk of social isolation [27]. During the intervention the participants met a volunteer to cook and share a meal together, once a week for eight weeks. Improvements were evident within the treatment group, but also relative to participants in the control group regarding food enjoyment. The authors concluded that there was a gap in the current services offered to older adults and suggested that a combination of social and nutritional support would be of importance for older people living alone. However, they were also conscious about the study being underpowered due to the low sample size.
The other two experimental studies examined the social facilitation of eating. Oral nutritional supplements were tested in the first study [28], where the participants (n = 21) were their own controls, attending one individual session and one group session in which participants brought two friends. Eating together resulted in a 60 percent increase in the total energy intake, compared to eating alone. The other study tested whether the social facilitation of eating occurred even in the absence of other people, when eating in front of a mirror (n = 16) or a picture of oneself (n = 12) [29]. The participants ate more and rated that the snacks had better taste when eating in front of a mirror or a picture than when eating in front of a wall. However, these studies also have low sample sizes.
3.2.2. Qualitative Studies
When examining different aspects of older peoples′ lives or situations, eating alone or together with others became a central topic in several qualitative studies. Eating alone was mainly described as a negative experience by participants in the interview studies [30,31,32]. Older people of low weight described eating alone, social isolation, and stressors as the main influences on their eating patterns [30]. Respondents who experienced social isolation and were living with others, yet eating alone, also expressed feelings of being a burden. In an article on the role of the meal for retired women, both cohabiting and single-living, the meal was expressed as a gift [31]. However, for the widowers, the meaning of cooking and eating was expressed as lost, and the authors warned that this group was at nutritional risk. In an article focusing specifically on widowers, Vesnaver et al. [32] explored loss of commensality and found that eating alone led to fewer regular meals and less time spent on food. However, participants also said that even if mealtimes were negatively affected by being alone at the table, cooking and eating could still be pleasurable [32].
In contrast to these studies, meals eaten alone at home was described as being enjoyable by single-living older people, in a qualitative study on domestic and communal meals [33]. For example, dining in alone was linked with feelings of contentment and peacefulness. Additionally, freshness and variety of foods were considered of higher priority than commensality. The author writes:
“Therefore, whilst dining in was, for the main part, experienced alone it was not described by participants as a lonely event. By contrast, dining in alone was perceived in practical terms and, at times, symbolic of independence, competence and control” [33].(p. 38)
A study by Keller et al. [34] explored the meaning and experiences of mealtimes, and the article illuminates perspectives of persons with dementia and their primary family partners in care. Participants described strategies used to support social engagement during mealtimes, such as making the meals an important ritual and not a task, using conversation aids during meals, or eating together in a calm environment without distractions. Even though it could be more challenging as the dementia progressed, families enjoyed socializing by eating out, or getting together with other social groups.
One article, which stood out in its methodology, presented a formative evaluation study of mixed-reality solitary meals in virtual environments among older adults with mobility impairments [35]. The participants had a meal alone, using a head-mounted display showing two different virtual environments: a kitchen and a park. The interviews revealed that the preferred eating environments were dependent on which meals the participants were served, but the kitchen, where they usually ate alone, was reported as the perfect eating-alone environment.
Table 1.
Articles in the first category: central topic.
3.3. Eating Alone as One Aspect
This category has the largest number of articles (n = 50) and covers a wide range of topics and aims, where eating alone or together with others constitute one aspect of the study, for example, in broader discussions about food habits, social isolation, widowhood, loneliness or the social context of eating. The most relevant examples for our study aim are described below, and all articles included are presented in Table 2.
3.3.1. Quantitative Studies
The majority of articles in this category are based on quantitative studies, and half of these studies examine food-related problems in different ways. Whether eating alone was associated with lower food intake or higher nutritional risk varied in the different studies. For example, two studies used a questionnaire where eating alone, measured as “Do you eat one or more meals a day with someone?” was included and categorized as one risk factor for food intake [41,42]. They found that participants at high nutritional risk more often ate alone compared with those of lower nutritional risk. Similarly, participants categorized as being at nutritional risk (18%) were more likely to report eating alone (among other risk factors), as found in a study using a nutritional risk screening checklist on members of a congregate meal program (n = 8892) [43]. However, Posner et al. [44] did not find a significant association between eating alone and nutritional risk when they developed and tested the same checklist (n = 749). The checklist included the statement “I eat alone most of the time,” with the possible answers “Yes/No.” The last example is a study looking at dietary intake and eating patterns among older people in Israel [45]. The study found eating alone to be associated with lower food intake in men (n = 172) but not in women (n = 205), when the number of meals alone per week was included as a continuous variable.
Questionnaires including eating meals alone or together were also used in studies on social isolation and loneliness in relation to food-related problems [46,47]. One found that social isolation and loneliness were independently associated with higher nutritional risk, among 1200 randomly selected older people [46]. However, no association was found between frequency of sharing meals (“Do you share meals with others?” with response alternatives “most of the time”/“about half the time”/“infrequently”/“never”) and nutritional risk. Ferry et al. [47] conducted a mixed method study on a similar topic with older people, who lived alone and reported no more than five “emotionally meaningful” contacts per month (n = 150). One-third (32%) never shared a meal with family or friends and two-fifths (42%) reported inadequate food intake to cover nutritional needs. In both articles, the authors express concerns about loneliness and social isolation among older people and its effects on nutritional status.
The following four articles are presented to illustrate the variety of methods and topics touched upon in this category. The first example is an article that explored the benefits of active social engagement by evaluating different kinds of relationships [48]. The 133 participants were 60 years or older and generated 1506 social relationships in which interactions occurred at least once a month, of which 35 percent included regularly shared meals together. Social relationships that involved co-engagement in social and daily activities, such as shared meals, conveyed more social support, companionship, and positive social influence compared to the relationships that did not.
The second example is presented because it is the only included article with a single-blinded cluster controlled study design. The study aimed to understand whether older adults’ involvement in their own meals, as part of a rehabilitation program, could improve the health-related quality of life, muscle strength, and nutritional status [49]. From baseline to follow-up, a significant improvement was found in the intervention group compared to the control group in their health-related quality of life.
The third is a prospective population-based survey conducted in Botswana, with “eating meals alone” used as an indicator of diminished social support [50]. The study aimed to assess diminished function and lack of social support as indicators of short-term mortality (n = 372). Respondents who reported that they “usually eat meals alone” were assumed to have diminished social support, and this was found to be one of several significant discriminators for survival.
3.3.2. Qualitative Studies
In the qualitative studies in this category, eating with others or alone seems to have been an inductive finding, meaning that nowhere is it stated in the method description (or in supplementary files, when such were available) that this was part of the original design. The majority aimed to examine a food-related topic such as food habits or food practices, although two studies considered mealtimes alone or with others when studying widowhood [51] and loneliness [52].
In two articles, the meal was described as an opportunity to meet other people and became a coping strategy toward loneliness [52,53]. Eating together represented one aspect of “social engagement,” which was identified as impacting diet quality among participants in a focus group study. The authors suggest that eating out with friends or family may be a key social activity [53]. Similarly, in a study examining loneliness in later life, food and beverage rituals were identified as aspects that maintain interactions with family and friends [52].
Being alone at the table was described as lonely and leading to having less motivation for cooking and eating in several studies [51,54,55,56]. The participant groups and topics of interest differed, such as food choice in later life among British households [54], food practices among Lesbian, Gay, Bisexual, and Transgender seniors [55] and newly bereaved older people coping with grief [51,56]. While all of the articles acknowledge the importance of the social context of food practices and meals to enhance nutritional status and well-being, the need to address dietary issues for grieving older adults was emphasized in particular in an interview study by Hegge [51] and a mixed method study by Johnson [56].
Loneliness in relation to mealtimes also emerged as a problem in two studies focusing on self-management of type 2 diabetes [57,58]. Not being able to eat the same food as the rest of the family and therefore eating separately was expressed as a problem, creating social isolation among participants in both studies. Another study, about life with type 2 diabetes, explored different views regarding a healthy diet among ethnic minorities in the Netherlands and found that all their participants were eating with their families [59]. Here, shared eating was described both as a support and a hindrance for changes in lifestyles and eating habits.
Overall, within this category qualitative findings tend to diverge in two different directions. In one, the meal is described as an opportunity to meet other people. In the other, lonely meals are said to result in less time spent on food practices and less regular meals. In one study with British older adults, the authors found both perspectives described by different participants relating to food practices and identity maintenance [60]. The participants were categorized into groups, based on their findings—“food lovers” and “nonfoodies”—and stated that “‘[b]eing alone at the table’ was the greatest threat to food activities and identity, especially for the food lovers who gained pleasure from the social aspect of their food activities” [60] (p. 5). The food lovers coped with being alone by cooking for friends and family, while the nonfoodies had different experiences, describing eating alone as difficult.
Table 2.
Articles in the second category: one aspect.
4. Discussion
Having mapped out scientific articles presently available on eating alone or with others among community-living older people, we found a wide range of topics and methods. Research on nutritional status, depression, household eating arrangements, loneliness, and coping with grief are common topics. Furthermore, the studies consisted of both quantitative and qualitative study designs, such as cross-sectional surveys, experimental studies, qualitative interviews, and participant observations. In about one-third of the articles, eating alone or together are treated as central topics of interest, isolated from adjoining and broader concepts such as social participation, social activities, or social isolation. In about half, eating alone or together are one aspect of the findings, for example, treated as one of several variables in a regression model, one of several identified risk factors for malnutrition or depression, or as one of several significant aspects of social life in general. Summarized, our findings confirm the significance of commensality in community-living older peoples’ lives—in several cultural and geographical contexts, with different household compositions, and with diverse health conditions. Aspects that were highlighted less than one might anticipate from a public health perspective were socioeconomic factors and gender. A few studies highlight income as a relevant variable [13,23,64,80] and gender differences of eating alone are specifically examined in four studies included [15,21,53,74]. Moreover, some studies show associations between eating alone and negative health outcomes in men but not in women, regarding depressive symptoms [21], metabolic syndrome [14], and mortality [15,16]. These are aspects that could benefit from further analyses. However, based on our findings, we argue that the main gaps identified in the literature are two of a different kind: study designs for finding causal relationships and an improved differentiation in the measurements of eating alone or with others.
First, even though our method provides no information about methodological quality of individual studies, or combined effects of the strength of the evidence for any given relationship, we can see that the main results of quantitative studies tend to point in one direction—eating alone is suggested to have negative effects on the target population—and they are dominated by cross-sectional studies. High-quality randomized controlled trials are lacking and longitudinal studies are few; thus, no claims of causality can be made. For example, a cross-sectional study cannot rule out if meals eaten alone is a common feature of a person’s life before or after feelings of loneliness or depressive symptoms occur. Nor can we say, for example, that malnutrition is caused by the lack of meal company, or if the causality is reversed (e.g., people with eating problems avoiding shared meals). In contrast, qualitative studies provide richness and nuances to large-scale statistical patterns. Talk about reasons for low weight [30] or changes in food behaviors due to the loss of commensality [32], for example, rely on subjective recollections from small groups of people. Such studies are indeed important but must be interpreted with their methodological limitations in mind. Moreover, different forms of mealtime interventions have previously targeted institutionalized older people [8,91] but are clearly lacking for the community-living population. Institutionalized older people might be easier to include in an intervention, simply because it is possible to target a specific hospital or care home, and this is no doubt a relevant target group. However, as both quantitative and qualitative studies included in this article suggest, some community-living older people could possibly benefit from mealtime interventions as well, for example to improve nutritional status or prevent feelings of loneliness. The pilot study by McHugh Power et al. [27] is an example of a design that could inspire further RCTs, as does the cluster-controlled study by Husted et al. [49]. Such studies should be pre-registered and designed with the ambition of identifying, for example, whether sharing meals may have clear causal effects on health outcomes (e.g., nutritional status, general well-being, social isolation, etc.) and, if so, whether this is fundamentally different from the effects of other social activities. Regarding the scarcity of longitudinal data, prospective cohort studies could add questions pertaining to eating alone or with others, but this must be done with caution, which brings us to our next point.
Second, as the results show, measurements of eating alone or with others are often created in similar ways, with people responding if they eat alone, how often, and possibly with whom. This is a stark contrast to the literature on loneliness, in which significant work has been put into classification and measurement in order to capture the nuances of what it means to be “alone”, e.g., [92,93]. This literature conveys that questions about how many people one is sharing a household with, or how many friends one has—objective loneliness—are inadequate to capture the subjective dynamics of loneliness. We suggest that researchers trying to measure commensality search for inspiration in this literature. We also suggest that measurements of commensality should be informed by qualitative findings, since these, as our results show, may add complexity and nuances from stories of older people who are neutral about having eating companions, or actually prefer eating alone.
Strengths and Limitations
One important advantage of a scoping review, including this one, is its comprehensive mapping of a very broad range of studies on a given topic, providing a summary view of what has been done and where important gaps may be. This strength of the comprehensiveness must, however, be weighed against the limitations of not evaluating the quality of individual studies or make qualitative judgments about the strength of the evidence of a relationship between a given exposure and outcome, as in systematic reviews [94]. Nor can we draw any combined statistical conclusions from the quantitative studies, which we could have done with a meta-analysis. However, this is not the aim of a scoping review. Our general mapping of the literature can hopefully stimulate such future endeavors.
A strength of this particular scoping review is that it covers a wide range of research from geographical regions, academic disciplines, and methodologies. Two reviewers checked all of the abstracts independently; moreover, the screening of full-texts was a collaborative effort of continuous author deliberation, with generous criteria for inclusion. Furthermore, we added publications found in reference lists of relevant publications. We therefore see it as unlikely that publications that could substantially alter our findings were overlooked.
The broadness of our findings provides us with an understanding of both the scientific breadth of the questions as well as the cross-cultural significance in peoples’ lives. However, this also makes it difficult to collate them and abstract key concepts from the findings. Moreover, although the findings are broad, our review only includes studies focused on eating. This means, for example, that the social aspects of cooking, also acknowledged as meaningful in sociological research, e.g., [95,96], were excluded. The search method also means that some commensality research on social sciences and humanities not connected to such databases may have been overlooked (e.g., book chapters or articles in non-indexed journals). Lastly, scoping reviews may include “gray literature” [10], and our findings could perhaps have been more informative had we done the same. Our aim, nevertheless, was explicitly to map out scientific publications for the purposes of scientific research; hence, gray literature was considered redundant.
5. Conclusions
Findings from this scoping review demonstrate that social aspects of eating are acknowledged by several researchers and research teams, from a variety of research fields and countries. However, how close this question is to the core of a given study varies, and the majority of articles do not have eating alone or together as its central topic. We show a wide range of topics and methods, with relatively similar patterns regarding the main results, but also with scientifically important exceptions. Based on our findings we recommend future research designs that allow for the identification of causal relationships, use more refined ways of measuring meals alone or together, as well as qualitative methods that add complexity and nuances to the explored phenomena.
Supplementary Materials
The following are available online at https://www.mdpi.com/article/10.3390/ijerph18073495/s1, Table S1: Databases and search terms; Table S2: Documentation of full electronic search strategy; Table S3: Articles in the third category: peripheral; Table S4: Geographical spread of included articles.
Author Contributions
Conceptualization, A.B., Y.M.S., and N.N.; methodology, A.B., Y.M.S., and N.N.; validation, A.B., Y.M.S., A.K., and N.N.; formal analysis, A.B., and N.N.; investigation A.B., and N.N.; data curation, A.B.; writing—original draft preparation, A.B., and N.N.; writing—review and editing A.B., Y.M.S., A.K., and N.N.; visualization, A.B., and N.N.; supervision, N.N.; project administration, A.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research was partially funded by Stiftelsen Kronprinsessan Margarets Minne. The publication fee of this paper was funded by a generous contribution from the Centre for Integrated Research on Culture and Society (CIRCUS), Uppsala University.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
We would like to thank Professor emeritus Agneta Yngve for important contributions in the beginning of this study.
Conflicts of Interest
The authors declare no conflict of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript, or in the decision to publish the results.
Appendix A
Table A1.
Databases and search terms.
Appendix B
Table A2.
Documentation of full electronic search strategy (Example from PubMed).
Appendix C
Appendix C.1. The Third Category: Eating Alone is Peripheral
This category has the smallest number of articles (n = 18). Due to the peripheral nature of the studies, these are not described in depth, although some examples are mentioned in order to clarify how they are “peripheral” and still included (Table A3).
Appendix C.2. Quantitative Studies
Three studies focusing on cancer patients used a questionnaire, in combination with a cancer specific scale or module [97,98,99]. Looking into the cancer specific scale, the “Eating in public subscale” was found to include a question about eating with others [97,98]. Another cancer specific module included seven multi-item symptom scales where one was mentioned as “social eating” [99]. The results of the Eating in public subscale and the symptom scale for social eating is peripheral in the articles. In other words, eating alone or with others has a minor part of the design but is neither analyzed nor touched upon in the articles.
In other studies, questions were asked about eating with others but not mentioned in the article [100,101] or only indirectly touched upon through a variable of “going out to eat” [102] or with “social interaction” as a mentioned reason for older people to participate in congregate meal programs [103].
Appendix C.3. Qualitative Studies
As a qualitative example, a focus group interview study explored built and social environmental facilitators of, and barriers to, engagement in eating a healthy diet, physical activity, and regular contact with other people, among older Chinese immigrants in Australia [104]. One part of their findings was that lack of social support from family members was a barrier to a healthy diet, further the participants mention eating in restaurants or community centers but did not describe the eating company or lack thereof.
Table A3.
Articles included in the third category: peripheral.
Appendix D
Table A4.
Geographical spread of included articles (n = 72), also distributed in respective categories. The geographical origin of articles was divided in accordance with the regional classification of the United Nations [115].
References
- Courtin, E.; Knapp, M. Social isolation, loneliness and health in old age: A scoping review. Health Soc. Care Commun. 2017, 25, 799–812. [Google Scholar] [CrossRef] [Scilit]
- Keller, H.H. Promoting food intake in older adults living in the community: A review. Appl. Physiol. Nutr. Metab. 2007, 32, 991–1000. [Google Scholar] [CrossRef] [Scilit]
- Hawkley, L.C.; Capitanio, J.P. Perceived social isolation, evolutionary fitness and health outcomes: A lifespan approach. Philos. Trans. R. Soc. B Biol. Sci. 2015, 370. [Google Scholar] [CrossRef] [Scilit]
- Warde, A. The Practice of Eating; Polity Press: Cambridge, UK, 2016. [Google Scholar]
- Vesnaver, E.; Keller, H.H. Social influences and eating behavior in later life: A review. J. Nutr. Gerontol. Geriatr. 2011, 30, 2–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. World Report on Ageing and Health. Available online: https://apps.who.int/iris/bitstream/handle/10665/186463/9789240694811_eng.pdf;jsessionid=574F13482630EAACA3B27638854F0100?sequence=1 (accessed on 15 May 2020).
- Jonsson, A.-S.; Nyberg, M.; Jonsson, I.M.; Öström, Å. Older patients’ perspectives on mealtimes in hospitals: A scoping review of qualitative studies. Scand. J. Caring Sci. 2020. [Google Scholar] [CrossRef] [Scilit]
- Vucea, V.; Keller, H.H.; Ducak, K. Interventions for Improving Mealtime Experiences in Long-Term Care. J. Nutr. Gerontol. Geriatr. 2014, 33, 249–324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Levac, D.; Colquhoun, H.; O’Brien, K.K. Scoping studies: Advancing the methodology. Implement. Sci. 2010, 5. [Google Scholar] [CrossRef] [Scilit]
- Tani, Y.; Kondo, N.; Takagi, D.; Saito, M.; Hikichi, H.; Ojima, T.; Kondo, K. Combined effects of eating alone and living alone on unhealthy dietary behaviors, obesity and underweight in older Japanese adults: Results of the JAGES. Appetite 2015, 95, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Locher, J.L.; Robinson, C.O.; Roth, D.L.; Ritchie, C.S.; Burgio, K.L. The effect of the presence of others on caloric intake in homebound older adults. J. Gerontol. Ser. Biol. Sci. Med. Sci. 2005, 60, 1475–1478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ishikawa, M.; Takemi, Y.; Yokoyama, T.; Kusama, K.; Fukuda, Y.; Nakaya, T.; Nozue, M.; Yoshiike, N.; Yoshiba, K.; Hayashi, F.; et al. “Eating together” is associated with food behaviors and demographic factors of older Japanese people who live alone. J. Nutr. Health Aging 2017, 21, 662–672. [Google Scholar] [CrossRef] [Scilit]
- Kwon, A.R.; Yoon, Y.S.; Min, K.P.; Lee, Y.K.; Jeon, J.H. Eating alone and metabolic syndrome: A population-based Korean National Health and Nutrition Examination Survey 2013–2014. Obes. Res. Clin. Pract. 2018, 12, 146–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Y.C.; Cheng, H.L.; Wahlqvist, M.L.; Lo, Y.C.; Lee, M.S. Gender differences in longevity in free-living older adults who eat-with-others: A prospective study in Taiwan. BMJ Open 2017, 7, e016575. [Google Scholar] [CrossRef] [Scilit]
- Tani, Y.; Kondo, N.; Noma, H.; Miyaguni, Y.; Saito, M.; Kondo, K. Eating Alone Yet Living With Others Is Associated With Mortality in Older Men: The JAGES Cohort Survey. J. Gerontol. Ser. B Psychol. Sci. Soc. Sci. 2018, 73, 1330–1334. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, C.L.; Tung, H.J.; Yeh, M.C. Combined effect of eating alone and a poor nutritional status on cognitive decline among older adults in Taiwan. Asia Pac. J. Clin. Nutr. 2018, 27, 686–694. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kimura, Y.; Wada, T.; Okumiya, K.; Ishimoto, Y.; Fukutomi, E.; Kasahara, Y.; Chen, W.; Sakamoto, R.; Fujisawa, M.; Otsuka, K.; et al. Eating alone among community-dwelling Japanese elderly: Association with depression and food diversity. J. Nutr. Health Aging 2012, 16, 728–731. [Google Scholar] [CrossRef] [Scilit]
- Kuroda, A.; Tanaka, T.; Hirano, H.; Ohara, Y.; Kikutani, T.; Furuya, H.; Obuchi, S.P.; Kawai, H.; Ishii, S.; Akishita, M.; et al. Eating Alone as Social Disengagement is Strongly Associated With Depressive Symptoms in Japanese Community-Dwelling Older Adults. J. Am. Med. Dir. Assoc. 2015, 16, 578–585. [Google Scholar] [CrossRef] [Scilit]
- Tani, Y.; Sasaki, Y.; Haseda, M.; Kondo, K.; Kondo, N. Eating alone and depression in older men and women by cohabitation status: The JAGES longitudinal survey. Age Ageing 2015, 44, 1019–1026. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.A.; Park, E.C.; Ju, Y.J.; Nam, J.Y.; Kim, T.H. Is one’s usual dinner companion associated with greater odds of depression? Using data from the 2014 Korean National Health and Nutrition Examination Survey. Int. J. Soc. Psychiatry 2016, 62, 560–568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Shen, W.; Wang, C.; Zhang, X.; Xiao, Y.; He, F.; Zhai, Y.; Li, F.; Shang, X.; Lin, J. Association between eating alone and depressive symptom in elders: A cross-sectional study. BMC Geriatr. 2016, 16, 19. [Google Scholar] [CrossRef] [Scilit]
- Torres, C.C.; McIntosh, W.A.; Kubena, K.S. Social network and social background characteristics of elderly who live and eat alone. J. Aging Health 1992, 4, 564–578. [Google Scholar] [CrossRef] [Scilit]
- Yates, L.; Warde, A. Eating together and eating alone: Meal arrangements in British households. Br. J. Sociol. 2017, 68, 97–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jacobson, D.S.; McMullan, C.; Minas, C. Engel and Simmel: Sharing meals at home in Cyprus. Br. Food J. 2015, 117, 677–687. [Google Scholar] [CrossRef] [Scilit]
- Takeda, W.; Melby, M.K.; Ishikawa, Y. Who eats with family and how often? Household members and work styles influence frequency of family meals in urban Japan. Appetite 2018, 125, 160–171. [Google Scholar] [CrossRef] [Scilit]
- McHugh Power, J.E.; Lee, O.; Aspell, N.; McCormack, E.; Loftus, M.; Connolly, L.; Lawlor, B.; Brennan, S. RelAte: Pilot study of the effects of a mealtime intervention on social cognitive factors and energy intake among older adults living alone. Br. J. Nutr. 2016, 116, 1573–1581. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McAlpine, S.J.; Harper, J.; McMurd, M.E.T.; Bolton-Smith, C.; Hetherington, M.M. Nutritional supplementation in older adults: Pleasantness, preference and selection of sip-feeds. Br. J. Health Psychol. 2003, 8, 57–66. [Google Scholar] [CrossRef] [Scilit]
- Nakata, R.; Kawai, N. The ‘social’ facilitation of eating without the presence of others: Self-reflection on eating makes food taste better and people eat more. Physiol. Behav. 2017, 179, 23–29. [Google Scholar] [CrossRef] [Scilit]
- Martin, C.T.; Kayser-Jones, J.; Stotts, N.A.; Porter, C.; Froelicher, E.S. Factors contributing to low weight in community-living older adults. J. Am. Acad. Nurse Pract. 2005, 17, 425–431. [Google Scholar] [CrossRef] [Scilit]
- Sidenvall, B.; Nydahl, M.; Fjellstrom, C. The meal as a gift—The meaning of cooking among retired women. J. Appl. Gerontol. 2000, 19, 405–423. [Google Scholar] [CrossRef] [Scilit]
- Vesnaver, E.; Keller, H.H.; Sutherland, O.; Maitland, S.B.; Locher, J.L. Alone at the Table: Food Behavior and the Loss of Commensality in Widowhood. J. Gerontol. B Psychol. Sci. Soc. Sci. 2016, 71, 1059–1069. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thomas, N.; Emond, R. Living alone but eating together: Exploring lunch clubs as a dining out experience. Appetite 2017, 119, 34–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Keller, H.H.; Martin, L.S.; Dupuis, S.; Reimer, H.; Genoe, R. Strategies to support engagement and continuity of activity during mealtimes for families living with dementia; a qualitative study. BMC Geriatr. 2015, 15, 119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Korsgaard, D.; Bjoner, T.; Nilsson, N.C. Where would you like to eat? A formative evaluation of mixed-reality solitary meals in virtual environments for older adults with mobility impairments who live alone. Food Res. Int. 2019, 117, 30–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, M.A.; Murphy, S.P.; Neuhaus, J.M. Living arrangements and eating behaviors of older adults in the United States. J. Gerontol. 1988, 43, S96–S98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Motteli, S.; Siegrist, M.; Keller, C. Women’s social eating environment and its associations with dietary behavior and weight management. Appetite 2017, 110, 86–93. [Google Scholar] [CrossRef] [Scilit]
- Boyer, K.; Orpin, P.; King, A.C. ‘I come for the friendship’: Why social eating matters. Australas. J. Ageing 2016, 35, E29–E31. [Google Scholar] [CrossRef] [Scilit]
- McHugh, J.; Lee, O.; Lawlor, B.; Brennan, S. The meaning of mealtimes: Social and nutritional needs identified among older adults attending day services and by healthcare professionals. Int. J. Geriatr. Psychiatry 2015, 30, 325–329. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saeed, A.; Fisher, J.; Mitchell-Smith, Z.; Brown, L.J.E. “You’ve Got to Be Old to Go There”: Psychosocial Barriers and Facilitators to Social Eating in Older Adults. Gerontologist 2020, 60, 628–637. [Google Scholar] [CrossRef] [Scilit]
- Lengyel, C.O.; Jiang, D.; Tate, R.B. Trajectories of nutritional risk: The Manitoba follow-up study. J. Nutr. Health Aging 2017, 21, 604–609. [Google Scholar] [CrossRef] [Scilit]
- Wham, C.; Carr, R.; Heller, F. Country of origin predicts nutrition risk among community living older people. J. Nutr. Health Aging 2011, 15, 253–258. [Google Scholar] [CrossRef] [Scilit]
- Quigley, K.K.; Hermann, J.R.; Warde, W.D. Nutritional risk among Oklahoma congregate meal participants. J. Nutr. Educ. Behav. 2008, 40, 89–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Posner, B.M.; Jette, A.M.; Smith, K.W.; Miller, D.R. Nutrition and health risks in the elderly: The nutrition screening initiative. Am. J. Public Health 1993, 83, 972–978. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahar, D.; Shai, I.; Vardi, H.; Fraser, D. Dietary intake and eating patterns of elderly people in Israel: Who is at nutritional risk? Eur. J. Clin. Nutr. 2003, 57, 18–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boulos, C.; Salameh, P.; Barberger-Gateau, P. Social isolation and risk for malnutrition among older people. Geriatr. Gerontol. Int. 2017, 17, 286–294. [Google Scholar] [CrossRef] [Scilit]
- Ferry, M.; Sidobre, B.; Lambertin, A.; Barberger-Gateau, P. The SOLINUT study: Analysis of the interaction between nutrition and loneliness in persons aged over 70 years. J. Nutr. Health Aging 2005, 9, 261–268. [Google Scholar]
- Ashida, S.; Sewell, D.K.; Schafer, E.J.; Schroer, A.; Friberg, J. Social network members who engage in activities with older adults: Do they bring more social benefits than other members? Ageing Soc. 2019, 39, 1050–1069. [Google Scholar] [CrossRef] [Scilit]
- Husted, M.M.; Beck, A.M.; Ulrikkeholm, L.K. Involving community-dwelling older adults in activities related to meals as part of a rehabilitation program: A single-blinded cluster-controlled study. Clin. Rehabil. 2019, 33, 1185–1196. [Google Scholar] [CrossRef] [Scilit]
- Clausen, T.; Wilson, A.O.; Molebatsi, R.M.; Holmboe-Ottesen, G. Diminished mental- and physical function and lack of social support are associated with shorter survival in community dwelling older persons of Botswana. BMC Public Health 2007, 7. [Google Scholar] [CrossRef] [Scilit]
- Hegge, M. A qualitative retrospective study of coping strategies of newly widowed elderly: Effects of anticipatory grieving on the caregiver. Am. J. Hosp. Palliat. Care 1991, 8, 28–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pettigrew, S.; Roberts, M. Addressing loneliness in later life. Aging Ment. Health 2008, 12, 302–309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bloom, I.; Lawrence, W.; Barker, M.; Baird, J.; Dennison, E.; Sayer, A.A.; Cooper, C.; Robinson, S. What influences diet quality in older people? A qualitative study among community-dwelling older adults from the Hertfordshire Cohort Study, UK. Public Health Nutr. 2017, 20, 2685–2693. [Google Scholar] [CrossRef] [Scilit]
- Whitelock, E.; Ensaff, H. On Your Own: Older Adults’ Food Choice and Dietary Habits. Nutrients 2018, 10, 413. [Google Scholar] [CrossRef] [Scilit]
- Cohen, N.; Cribbs, K. The everyday food practices of community-dwelling Lesbian, Gay, Bisexual, and Transgender (LGBT) older adults. J. Aging Stud. 2017, 41, 75–83. [Google Scholar] [CrossRef] [Scilit]
- Johnson, C.S. Nutritional considerations for bereavement and coping with grief. J. Nutr. Health Aging 2002, 6, 171–176. [Google Scholar]
- Foley, E.; BeLue, R. Identifying Barriers and Enablers in the Dietary Management of Type 2 Diabetes in M’Bour, Senegal. J. Transcult. Nurs. 2017, 28, 348–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knutsen, I.R.; Foss, I.C.; Todorova, E.; Roukova, P.; Kennedy, A.; Portillo, M.C.; Regaira, E.; Serrano-Gil, M.; Lionis, C.; Angelaki, A.; et al. Negotiating Diet in Networks: A Cross-European Study of the Experiences of Managing Type 2 Diabetes. Qual. Health Res. 2017, 27, 299–310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jager, M.J.; van der Sande, R.; Essink-Bot, M.L.; van den Muijsenbergh, M. Views and experiences of ethnic minority diabetes patients on dietetic care in the Netherlands—A qualitative study. Eur. J. Public Health 2019, 29, 208–213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Plastow, N.A.; Atwal, A.; Gilhooly, M. Food Activities and Identity Maintenance Among Community-Living Older Adults: A Grounded Theory Study. Am. J. Occup. Ther. Off. Publ. Am. Occup. Ther. Assoc. 2015, 69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alberti Fidanza, A. Nutritional status of the elderly. IV. Nutritional knowledge, food preferences and life styles connected with the nutritional process. Int. J. Vitam. Nutr. Res. 1984, 54, 361–369. [Google Scholar]
- De Castro, J.M. Age-related-changes in spontaneous food-intake and hunger in humans. Appetite 1993, 21, 255–272. [Google Scholar] [CrossRef] [Scilit]
- De Castro, J.M. Age-related changes in the social, psychological, and temporal influences on food intake in free-living, healthy, adult humans. J. Gerontol. Ser. A Biol. Sci. Med. Sci. 2002, 57, M368–M377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dean, W.R.; Sharkey, J.R.; Nalty, C.C.; Xu, J. Government Capital, Intimate and Community Social Capital, and Food Security Status in Older Adults with Different Income Levels. Rural Sociol. 2014, 79, 505–531. [Google Scholar] [CrossRef] [Scilit]
- Getty, M.D.; Mueller, M.; Amella, E.J.; Fraser, A.M. Differences in Medical and Life-style Risk Factors for Malnutrition in Limited-Resource Older Adults in a Rural U.S. State: A Descriptive Study. J. Nutr. Health Aging 2016, 20, 121–127. [Google Scholar] [CrossRef] [Scilit]
- Holm, L.; Lauridsen, D.; Lund, T.B.; Gronow, J.; Niva, M.; Makela, J. Changes in the social context and conduct of eating in four Nordic countries between 1997 and 2012. Appetite 2016, 103, 358–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Holmes, B.A.; Roberts, C.L. Diet quality and the influence of social and physical factors on food consumption and nutrient intake in materially deprived older people. Eur. J. Clin. Nutr. 2011, 65, 538–545. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Holmes, B.A.; Roberts, C.L.; Nelson, M. How access, isolation and other factors may influence food consumption and nutrient intake in materially deprived older men in the UK. Nutr. Bull. 2008, 33, 212–220. [Google Scholar] [CrossRef] [Scilit]
- Ishikawa, M.; Yokoyama, T.; Hayashi, F.; Takemi, Y.; Nakaya, T.; Fukuda, Y.; Kusama, K.; Nozue, M.; Yoshiike, N.; Murayama, N. Subjective Well-Being Is Associated with Food Behavior and Demographic Factors in Chronically Ill Older Japanese People Living Alone. J. Nutr. Health Aging 2018, 22, 341–353. [Google Scholar] [CrossRef] [Scilit]
- Keller, H.H.; Goy, R.; Kane, S.L. Validity and reliability of SCREEN II (Seniors in the Community: Risk evaluation for eating and nutrition, Version II). Eur. J. Clin. Nutr. 2005, 59, 1149–1157. [Google Scholar] [CrossRef] [Scilit]
- Nicholas, M.; Jennelle, L.; Connor, L.T.; Haynes, C.; Zipse, L. Do caregiver proxy reports and congruence of client-proxy activity participation goals relate to quality of life in people with aphasia? Int. J. Lang. Commun. Disord. 2020, 55, 373–386. [Google Scholar] [CrossRef] [Scilit]
- Porter, K.; Keary, S.; VanWagenen, A.; Bradford, J. Social Network and Nutritional Value of Congregate Meal Programs: Differences by Sexual Orientation. J. Appl. Gerontol. 2016, 35, 960–981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosenbloom, C.A.; Whittington, F.J. The effects of bereavement on eating behaviors and nutrient intakes in elderly widowed persons. J. Gerontol. 1993, 48, S223–S229. [Google Scholar] [CrossRef] [Scilit]
- Rugel, E.J.; Carpiano, R.M. Gender differences in the roles for social support in ensuring adequate fruit and vegetable consumption among older adult Canadians. Appetite 2015, 92, 102–109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Swan, J.H.; Severance, J.J.; Turner, K. Senior Centers and Nutritional Outcomes: A Texas Example. Soc. Work Public Health 2016, 31, 439–452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toner, H.; Morris, J. A Social-Psychological Perspective of Dietary Quality in Later Adulthood. J. Nutr. Elder. 1993, 11, 35–53. [Google Scholar] [CrossRef] [Scilit]
- Waring, M.L.; Kosberg, J.I. Morale and the differential use among the Black elderly of social welfare services delivered by volunteers. J. Gerontol. Soc. Work 1984, 6, 81–94. [Google Scholar] [CrossRef] [Scilit]
- Asamane, E.A.; Greig, C.A.; Aunger, J.A.; Thompson, J.L. Perceptions and Factors Influencing Eating Behaviours and Physical Function in Community-Dwelling Ethnically Diverse Older Adults: A Longitudinal Qualitative Study. Nutrients 2019, 11, 1224. [Google Scholar] [CrossRef] [Scilit]
- Byker Shanks, C.; Haack, S.; Tarabochia, D.; Bates, K.; Christenson, L. Factors Influencing Food Choices Among Older Adults in the Rural Western USA. J. Community Health 2017, 42, 511–521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falciglia, G.; Wahlbrink, D.; Suszkiw, D. Factors of change in elderly eating-related behaviors: An anthropological perspective. J. Nutr. Elder. 1985, 5, 67–77. [Google Scholar] [CrossRef] [Scilit]
- Falk, L.W.; Bisogni, C.A.; Sobal, J. Food choice processes of older adults: A qualitative investigation. J. Nutr. Educ. 1996, 28, 257–265. [Google Scholar] [CrossRef] [Scilit]
- Howell, B.M.; Bardach, S.H. “It’s a Social Thing”: Sociocultural Experiences with Nutrition and Exercise in Anchorage, Alaska. Arct. Anthrop. 2018, 55, 1–16. [Google Scholar] [CrossRef] [Scilit]
- Sriram, U.; Morgan, E.H.; Graham, M.L.; Folta, S.C.; Seguin, R.A. Support and Sabotage: A Qualitative Study of Social Influences on Health Behaviors Among Rural Adults. J. Rural Health 2018, 34, 88–97. [Google Scholar] [CrossRef] [Scilit]
- Tessier, S.; Gerber, M. Comparison between Sardinia and Malta: The Mediterranean diet revisited. Appetite 2005, 45, 121–126. [Google Scholar] [CrossRef] [Scilit]
- Thompson, J.; Tod, A.; Bissell, P.; Bond, M. Understanding food vulnerability and health literacy in older bereaved men: A qualitative study. Health Expect. 2017, 20, 1342–1349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uribe, A.C.R. “I Go Upstairs and Eat in Front of the Television”: The Cooking and Eating Behaviors of Mexican Older Women Living Alone. J. Cross. Cult. Gerontol. 2019, 34, 171–186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gustafsson, K.; Sidenvall, B. Food-related health perceptions and food habits among older women. J. Adv. Nurs. 2002, 39, 164–173. [Google Scholar] [CrossRef] [Scilit]
- Hughes, G.; Bennett, K.M.; Hetherington, M.M. Old and alone: Barriers to healthy eating in older men living on their own. Appetite 2004, 43, 269–276. [Google Scholar] [CrossRef] [Scilit]
- Shifflett, P.A. Future time perspective, past experiences, and negotiation of food use patterns among the aged. Gerontologist 1987, 27, 611–615. [Google Scholar] [CrossRef] [Scilit]
- Zelig, R.; Jones, V.M.; Touger-Decker, R.; Hoskin, E.R.; Singer, S.R.; Byham-Gray, L.; Radler, D.R.; Rothpletz-Puglia, P. The Eating Experience: Adaptive and Maladaptive Strategies of Older Adults with Tooth Loss. JDR Clin. Transl. Res. 2019, 4, 217–228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Porter, J.; Ottrey, E.; Huggins, C.E. Protected Mealtimes in Hospitals and Nutritional Intake: Systematic Review and Meta-Analyses; Elsevier Ltd.: London, UK, 2017; Volume 65, pp. 62–69. [Google Scholar]
- Valtorta, N.K.; Kanaan, M.; Gilbody, S.; Hanratty, B. Loneliness, social isolation and social relationships: What are we measuring? A novel framework for classifying and comparing tools. BMJ Open 2016, 6, e010799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Victor, C.; Grenade, L.; Boldy, D. Measuring loneliness in later life: A comparison of differing measures. Rev. Clin. Gerontol. 2006, 15, 63–70. [Google Scholar] [CrossRef] [Scilit]
- Munn, Z.; Peters, M.D.J.; Stern, C.; Tufanaru, C.; McArthur, A.; Aromataris, E. Systematic review or scoping review? Guidance for authors when choosing between a systematic or scoping review approach. BMC Med. Res. Methodol. 2018, 18, 143. [Google Scholar] [CrossRef] [PubMed]
- Daniels, S.; Glorieux, I.; Minnen, J.; van Tienoven, T.P. More than preparing a meal? Concerning the meanings of home cooking. Appetite 2012, 58, 1050–1056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neuman, N.; Gottzén, L.; Fjellström, C. Masculinity and the sociality of cooking in men’s everyday lives. Sociol. Rev. 2017, 65, 816–831. [Google Scholar] [CrossRef] [Scilit]
- Allal, A.S.; Dulguerov, P.; Bieri, S.; Lehmann, W.; Kurtz, J.M. Assessment of quality of life in patients treated with accelerated radiotherapy for laryngeal and hypopharyngeal carcinomas. Head Neck 2000, 22, 288–293. [Google Scholar] [CrossRef]
- Allal, A.S.; Nicoucar, K.; Mach, N.; Dulguerov, P. Quality of life in patients with oropharynx carcinomas: Assessment after accelerated radiotherapy with or without chemotherapy versus radical surgery and postoperative radiotherapy. Head Neck 2003, 25, 833–839. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kjær, T.K.; Johansen, C.; Andersen, E.; Karlsen, R.; Nielsen, A.L.; Frederiksen, K.; Rorth, M.; Ibfelt, E.; Dalton, S.O. Influence of social factors on patient-reported late symptoms: Report from a controlled trial among long-term head and neck cancer survivors in Denmark. Head Neck 2016, 38 (Suppl. 1), E1713–E1721. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoerster, K.D.; Wilson, S.; Nelson, K.M.; Reiber, G.E.; Masheb, R.M. Diet quality is associated with mental health, social support, and neighborhood factors among Veterans. Eat. Behav. 2016, 23, 168–173. [Google Scholar] [CrossRef] [Scilit]
- Wham, C.A.; Teh, R.; Moyes, S.; Dyall, L.; Kepa, M.; Hayman, K.; Kerse, N. Health and social factors associated with nutrition risk: Results from life and living in advanced age: A cohort study in New Zealand (LILACS NZ). J. Nutr. Health Aging 2015, 19, 637–645. [Google Scholar] [CrossRef] [Scilit]
- Ang, S. Social Participation and Mortality Among Older Adults in Singapore: Does Ethnicity Explain Gender Differences? J. Gerontol. Ser. B Psychol. Sci. Soc. Sci. 2018, 73, 1470–1479. [Google Scholar] [CrossRef] [Scilit]
- Lee, K.-I. Using the Theory of Planned Behavior to Assess Participation in Congregate Meal Programs; ProQuest Information & Learning: Ann Arbor, MI, USA, 2009. [Google Scholar]
- Cerin, E.; Nathan, A.; Choi, W.K.; Ngan, W.; Yin, S.; Thornton, L.; Barnett, A. Built and social environmental factors influencing healthy behaviours in older Chinese immigrants to Australia: A qualitative study. Int. J. Behav. Nutr. Phys. Act. 2019, 16. [Google Scholar] [CrossRef] [Scilit]
- Byeon, H. Predicting the Swallow-Related Quality of Life of the Elderly Living in a Local Community Using Support Vector Machine. Int. J. Environ. Res. Public Health 2019, 16, 4269. [Google Scholar] [CrossRef] [Scilit]
- Lai, X.J.; Lam, W.H.K.; Su, J.B.; Fu, H. Modelling intra-household interactions in time-use and activity patterns of retired and dual-earner couples. Transp. Res. Part A Policy Pract. 2019, 126, 172–194. [Google Scholar] [CrossRef] [Scilit]
- Quandt, S.A.; Rao, P. Hunger and food security among older adults in a rural community. Hum. Organ. 1999, 58, 28–35. [Google Scholar] [CrossRef] [Scilit]
- Arcury, T.A.; Grzywacz, J.G.; Ip, E.H.; Saldana, S.; Nguyen, H.T.; Bell, R.A.; Kirk, J.K.; Quandt, S.A. Social integration and diabetes management among rural older adults. J. Aging Health 2012, 24, 899–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mamalaki, E.; Anastasiou, C.A.; Kosmidis, M.H.; Dardiotis, E.; Hadjigeorgiou, G.M.; Sakka, P.; Scarmeas, N.; Yannakoulia, M. Social life characteristics in relation to adherence to the Mediterranean diet in older adults: Findings from the Hellenic Longitudinal Investigation of Aging and Diet (HELIAD) study. Public Health Nutr. 2020, 23, 439–445. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van den Heuvel, E.; Murphy, J.L.; Appleton, K.M. Could Eggs Help Increase Dietary Protein Intake in Older Adults?—Exploring Reasons for the Consumption and Non-Consumption of Eggs in People over 55 years old. J. Nutr. Gerontol. Geriatr. 2018, 37, 292–309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zou, P. Facilitators and Barriers to Healthy Eating in Aged Chinese Canadians with Hypertension: A Qualitative Exploration. Nutrients 2019, 11, 111. [Google Scholar] [CrossRef] [Scilit]
- Glover, L.; Dyson, J.; Cowdell, F.; Kinsey, D. Healthy ageing in a deprived northern UK city: A co-creation study. Health Soc. Care Commun. 2020. [Google Scholar] [CrossRef] [Scilit]
- Howell, B.M. Interactions between Diet, Physical Activity, and the Sociocultural Environment for Older Adult Health in the Urban Subarctic. J. Commun. Health 2020, 45, 252–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nogueira, D.; Reis, E.; Ferreira, P.; Schindler, A. Measuring Quality of Life in the Speaker with Dysarthria: Reliability and Validity of the European Portuguese Version of the QoL-DyS. Folia Phoniatr. Logop. 2019, 71, 176–190. [Google Scholar] [CrossRef] [Scilit]
- United Nations. Methodology: Geographic Regions. Available online: https://unstats.un.org/unsd/methodology/m49/ (accessed on 15 May 2020).
Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).