


Abstract
Inhalation of asbestos resulting from living with and handling the clothing of workers directly exposed to asbestos has been established as a possible contributor to disease. This review evaluates epidemiologic studies of asbestos-related disease or conditions (mesothelioma, lung cancer, and pleural and interstitial abnormalities) among domestically exposed individuals and exposure studies that provide either direct exposure measurements or surrogate measures of asbestos exposure. A meta-analysis of studies providing relative risk estimates (n = 12) of mesothelioma was performed, resulting in a summary relative risk estimate (SRRE) of 5.02 (95% confidence interval [CI]: 2.48–10.13). This SRRE pertains to persons domestically exposed via workers involved in occupations with a traditionally high risk of disease from exposure to asbestos (i.e., asbestos product manufacturing workers, insulators, shipyard workers, and asbestos miners). The epidemiologic studies also show an elevated risk of interstitial, but more likely pleural, abnormalities (n = 6), though only half accounted for confounding exposures. The studies are limited with regard to lung cancer (n = 2). Several exposure-related studies describe results from airborne samples collected within the home (n = 3), during laundering of contaminated clothing (n = 1) or in controlled exposure simulations (n = 5) of domestic exposures, the latter of which were generally associated with low-level chrysotile-exposed workers. Lung burden studies (n = 6) were also evaluated as a surrogate of exposure. In general, available results for domestic exposures are lower than the workers’ exposures. Recent simulations of low-level chrysotile-exposed workers indicate asbestos levels commensurate with background concentrations in those exposed domestically.
1. Introduction
The potential exposure scenarios for individuals who are non-occupationally exposed to asbestos vary, but may include: (1) neighborhood exposure due to asbestos emissions from nearby asbestos-product manufacturing facilities, asbestos mines, construction work involving asbestos, or naturally occurring asbestos; (2) household exposure from the use of asbestos-containing materials (e.g., use of tremolite/erionite whitewash on the exterior of homes); and (3) household contamination resulting from asbestos fibers brought into the home on workers’ clothing or bodies, and domestic activities such as handling or laundering workers’ contaminated clothing. In this review, we discuss the third scenario, which can be referred to as secondary, para-occupational or take-home exposure, and herein is termed “domestic exposure”.
Early Reports of Domestic Exposure
In 1960, a seminal case series reported by Wagner [1] was not only one of the first to associate asbestos exposure, specifically to crocidolite, with the development of malignant pleural mesothelioma in 33 persons, but was also the first to identify exposure pathways via non-occupational domestic and neighborhood asbestos exposure. Wagner’s study was followed shortly by a case-control study by Newhouse and Thompson [2,3], which identified seven cases of pleural mesothelioma and two cases of peritoneal mesothelioma in patients whose relatives worked with asbestos, including chrysotile, amosite, and crocidolite. These workers’ occupations included spinners, an engine-room worker, a boiler coverer, an asbestos factory foreman, a docker handling asbestos cargo, a railway carriage builder, and an asbestos factory worker. Later studies involving domestically exposed persons followed (e.g., [4,5]).
The review of indirect exposures in bystanders in the workplace and at home by Grandjean and Bach [6] provided a relatively early evaluation of indirect exposures to lead, beryllium, asbestos, and other substances, including bystander exposures and exposure to substances carried home from work by family members. The authors addressed early case reports, case series, and cross-sectional studies that documented cases of mesothelioma, lung cancer, asbestosis, and pleural plaques in persons believed to be exposed domestically through family members who worked mostly in shipyards or asbestos factories. No specific data on the number of persons included in their evaluation were provided, nor was information on fiber type provided.
In conjunction with the Workers’ Family Protection Act of 1992, the U.S. National Institute for Occupational Safety and Health (NIOSH) produced the Report to Congress on Workers’ Home Contamination Study Conducted under the Workers’ Family Protection Act [7]. The authors of this report evaluated “the potential for, prevalence of, and issues related to the contamination of workers’ homes with hazardous chemicals and substances...transported from the workplaces of such workers”. In their report, NIOSH indicated that they included four cohort studies, one community study, seven case-control studies, and “numerous” case reports and case series. This report is the most comprehensive by NIOSH to date on this topic—it provides a summary of cohort studies, case-control studies, case reports, and case series, as well as an overview of studies that describe contaminated clothing. The report concluded that domestic asbestos exposures may pose an increased risk of disease, but did not provide analyses regarding the type of exposure (including fiber type), level, frequency, or duration needed to produce disease. As a follow-up to this report, NIOSH published a research agenda focused on protecting workers’ families [8]. This agenda included characterizing the extent of home contamination, identifying populations at greatest risk of known and suspected take-home exposures, assessing the adverse health effects from take-home exposures, and assessing the effectiveness of prevention and remediation methods. To date, NIOSH has not published any results from this agenda.
An often-cited French report by the National Institute of Health and Medical Research (INSERM) [9] concluded that the risk of mesothelioma in persons exposed in a non-occupational and domestic setting was “established” in the literature, indicating that the source of the asbestos was typically dirty work clothes; however, this report does not provide any quantitative domestic exposure estimates, and it specifically states that good exposure data do not exist in the literature to feasibly evaluate the extent of domestic exposures. In addition, the authors lump non-occupational (termed “para-occupational” by the original authors) exposures together, which include domestic and direct exposures from the use of home products potentially containing asbestos (e.g., ironing boards and insulating gloves), thereby making it difficult to understand those exposures that resulted solely from domestic exposure. No specific data on the number of persons included in their evaluation were provided.
In 2000, Bourdès et al. [10] conducted a study focused solely on pleural mesothelioma based on five published studies, and the reported meta-relative risk included a study of household use of asbestos (e.g., whitewash, stucco) in Turkey in which 23 mesotheliomas were reported; however, a number of studies have been published since its culmination date of 1998. Three of the remaining four included studies provided information on the number of domestically-exposed persons with mesothelioma, reporting on a combined 21 cases of mesothelioma; the fifth included study did not provide information by exposure type, but noted that 17 persons (9%) likely or possibly had para-occupational exposure. In all but one of the included studies, the exposure was to amosite or mixed fibers (i.e., amphibole and chrysotile fibers). Bourdès et al. also presented a review of non-occupational exposure measurements, which largely included environmental exposures (ambient exposures due to nearby sources) and indoor exposures due to specific asbestos-containing products used in the home or business (e.g., schools with sprayed asbestos, use of asbestos-containing whitewash in the home).
The purpose of our current paper has two specific aims: (1) to provide an up-to-date and comprehensive review of epidemiologic (cohort, case-control, and case reports and series) and exposure data regarding domestic exposure and mesothelioma, lung cancer, and interstitial and pleural abnormalities and (2) to conduct a quantitative assessment using a meta-analysis approach to estimate the risk of mesothelioma among individuals domestically exposed vs. those not exposed. The issue of domestic exposures remains an important question because of potential ongoing uses of potentially hazardous materials. For asbestos, the issue becomes important because of ongoing litigation matters and the need to understand historical exposures to asbestos and the associations with asbestos-related diseases. During the time of writing this paper, another paper has been published which also provides a review of epidemiologic and exposure data regarding domestic exposures [11]; however, this paper does not provide a meta-analysis or quantitative evaluation of risk, excludes several studies that are included in the present paper, and uses different methods of evaluation.
2. Methods
The published literature from the 1960s to 2012 was searched using MEDLINE, accessed via PubMed (the U.S. National Library of Medicine). Key words included domestic, household, laundry, para-occupational, or take-home and asbestos (and specific fiber types, including crocidolite, amosite, and chrysotile), mesothelioma, lung cancer, asbestosis, or pleural changes. No specific restrictions were imposed on the literature search, although the review was restricted to the most recent update of a study population. The reference lists of articles were reviewed to identify studies that might not have been detected in the literature search. Each article was reviewed by at least two scientists for inclusion. In an attempt to be as comprehensive as possible, all studies that provided some primary epidemiologic or exposure information were included. Some studies were written in a foreign language; for these, the English abstract was relied upon for relevant information.
2.1. Epidemiology Review and Analysis
Analytical and descriptive epidemiologic studies were considered in the qualitative review, including cohort, case-control, cross-sectional studies, case reports, and case series. The medical conditions of interest were mesothelioma, lung cancer, and interstitial and pleural abnormalities.
In addition to a qualitative review of the published epidemiologic studies, we also performed a quantitative meta-analysis of the studies reporting mesothelioma in domestically exposed persons. Only mesothelioma studies were included in the meta-analysis, because there were too few studies of lung cancer and interstitial and pleural abnormalities to perform meta-analyses for those endpoints. Epidemiologic studies were included in the meta-analysis if the original study reported relative risk estimates, or provided the information necessary to calculate a relative risk estimate, and a measure of variance (e.g., confidence intervals). Random-effects meta-analysis models were used to calculate summary relative risk estimates (SRREs), 95% confidence intervals (CIs), and corresponding p-values for heterogeneity (p-H). Statistical significance was identified when the 95% CI did not include 1.0. The random-effects model assumes that the study-specific effect sizes come from a random distribution of effect sizes according to a specific mean and variance. A p-H < 0.1 suggests significant “between-study” statistical variability in a meta-analysis model [12]. The relative risk estimates of the individual studies were weighted based on the inverse of the variance, which is related to the sizes of the study populations. Tests for heterogeneity were conducted, and subgroup analyses (specifically, case-control vs. cohort, modification by occupational exposure) were performed to discern any potential sources of between-study variability. “One study removed” sensitivity analyses were conducted to evaluate the relative influence of each study on the model-specific SRRE. This was performed by generating an SRRE based on all studies in a particular model, followed by the removal of one study at a time to compare the overall SRRE with SRREs from models that had one study removed. Separate models were created to estimate the effects of occupational vs. neighborhood exposures. Potential confounding from occupational or neighborhood exposures was assessed by the methods described in each paper, as well as suggestions from the original authors’ discussion of limitations. Analyses were conducted using Comprehensive Meta-Analysis (version 2.2.045; Biostat, Englewood, NJ, USA), STATA (version 1.0; StataCorp, College Station, TX, USA), and Episheet [13].
2.2. Exposure Review
The exposure studies reviewed included a variety of study types that provided some direct asbestos exposure data or surrogate of asbestos exposure, and were categorized into four distinct groups: (1) studies describing results of airborne or settled dust samples collected within the homes of domestically exposed persons, (2) studies describing exposures during laundering or other handling of contaminated clothing, (3) studies describing controlled simulations of take-home exposures, and (4) lung burden studies. Due to the different in potency among asbestos fiber types, wherever possible, the type of asbestos fiber from which the exposure occurred is noted.
3. Results
In total 143 published articles were identified for inclusion in the review, and of these, 108 were evaluated for relevant information. Many of the studies were subsequently excluded after initial review. Specific reasons for exclusion included lack of quantitative data regarding risk and/or exposure (e.g., review articles with no original data) and studies that did not report specifically on domestically-exposed persons or that lumped those domestically-exposed with other types of asbestos exposures. The remaining articles are discussed below. Wherever possible, the asbestos fiber type to which the population was exposed was reported (Table 1, Table 2 and Table 3).
3.1. Review of Domestic Epidemiologic Studies
Studies of mesothelioma, lung cancer, and pleural and interstitial abnormalities with information regarding domestic exposure are discussed below by disease type.
3.1.1. Mesothelioma
Table 1 provides a list of 32 case reports and case series of mesothelioma in asbestos-exposed domestic populations, beginning with Wagner and colleagues’ case series of pleural mesothelioma in 1960. The case reports and series are provided for comprehensiveness, not to address the question of whether or not there is an association between domestic exposure to asbestos and mesothelioma, or the magnitude of that association.
Table 1.
Case reports and series of mesothelioma in domestically exposed populations.
Table 2.
Cohort and case-control studies of mesothelioma in domestically exposed populations.
Table 3.
Epidemiologic studies of interstitial and pleural abnormalities in domestically exposed populations.
The case reports and case series include pleural and peritoneal mesothelioma in wives, children, mothers, and siblings of asbestos workers such as miners, asbestos factory workers, pipefitters, laggers/insulators, and shipyard workers. Unfortunately, these published case reports rarely identified the type of asbestos to which the case was exposed [1,14,23,38], with a few exceptions, all of which reported exposure to amphibole asbestos (amosite or crocidolite) (Table 1). None of the case reports provided information on the level of asbestos exposure experienced in each case, although a limited number of studies reported results of lung-burden analyses [28,36,41]. Two of these studies reported finding asbestos bodies in 20% to 35% of persons examined [36,41]. Several of the case reports specifically noted clothes washing as the source of exposure via the inhalation pathway [15,16,17,21,24,29,31,32,33,34,35,36,37,38,40,41,44].
Among studies of the association between domestic exposure and asbestos-related disease, mesothelioma was the most common disease reported. Several cohort (n = 3) and case-control (n = 14) studies of mesothelioma evaluated domestically exposed populations or identified cases of mesothelioma in domestically exposed individuals (Table 2). One meta-analysis was also identified. The occupations of the workers included in the studies were primarily those associated with traditional high-risk trades: asbestos miners, asbestos factory workers, shipyard/dock workers, textile workers, furnace/engine/boiler room workers, railway carriage builders, pipefitters, and insulators. Our review included 14 case-control studies, of which 10 reported relative risk estimates or provided enough information to calculate a crude relative risk estimate [2,3,4,5,49,50,51,52,53,54,56], ranging from 1.4 [54] to 16.75 [2,3]. Two of the three cohort studies reported relative risk values [63,65]. In the first cohort study, a statistically significant standardized incidence ratio (SIR) of 25.19 (95% CI: 12.57–45.07) was reported for wives of Italian cement workers [63], although results were not adjusted for potential confounding by neighborhood or occupational exposure. In the second cohort study, a non-statistically significant hazard ratio (HR) of 2.61 (95% CI: 0.85–7.99) was reported in household members of workers of the Australian Blue Asbestos Company [65]. In this study, potential neighborhood exposures were also not evaluated in the estimation of relative risk.
The cohort and case-control studies evaluated both pleural and peritoneal mesotheliomas, with some studies not discerning between the two sites. In many studies, asbestos fiber type was also not reported. The fiber type to which the study participants were exposed is an important factor, as amphibole fibers (crocidolite, amosite or tremolite) are generally more potent then chrysotile fibers [72,73,74,75]. When reported, the workers via whom the individuals were domestically exposed were nearly always exposed to amphiboles. This fiber-type issue is further complicated by the fact that some chrysotile deposits have different degrees of co-occurrence of tremolite. One case-control study evaluated exposure to chrysotile in 10 female co-habitants of Quebec chrysotile miners, although the miners worked in the Thetford area, which the authors described has having the highest tremolite content of the Canadian mining sites. This study resulted in a non-significant increase in the risk of mesothelioma (odds ratio [OR] = 4.92, 95% CI: 0.65–219.54) among co-habitants [51].
Meta-analysis of all 12 cohort and case-control studies with reported relative risk estimates resulted in an SRRE of 5.02 (95% CI: 2.48–10.13; Figure 1). This SRRE indicates a statistically significant increase in the risk of mesothelioma for those domestically exposed, although heterogeneity was evident (p-H < 0.0001). The lower bound of the confidence interval in the Ferrante et al. study [63] is greater than the upper bound of the confidence interval from the overall summary effect. Removal of this study in a sensitivity analysis resulted in an attenuation, albeit still statistically significant, of the overall effect (SRRE = 3.34, 95% CI: 2.15–5.19), and the model became more homogeneous (p-H = 0.126).
Figure 1.
Meta-analysis of cohort and case-control studies of mesothelioma in domestically exposed populations.
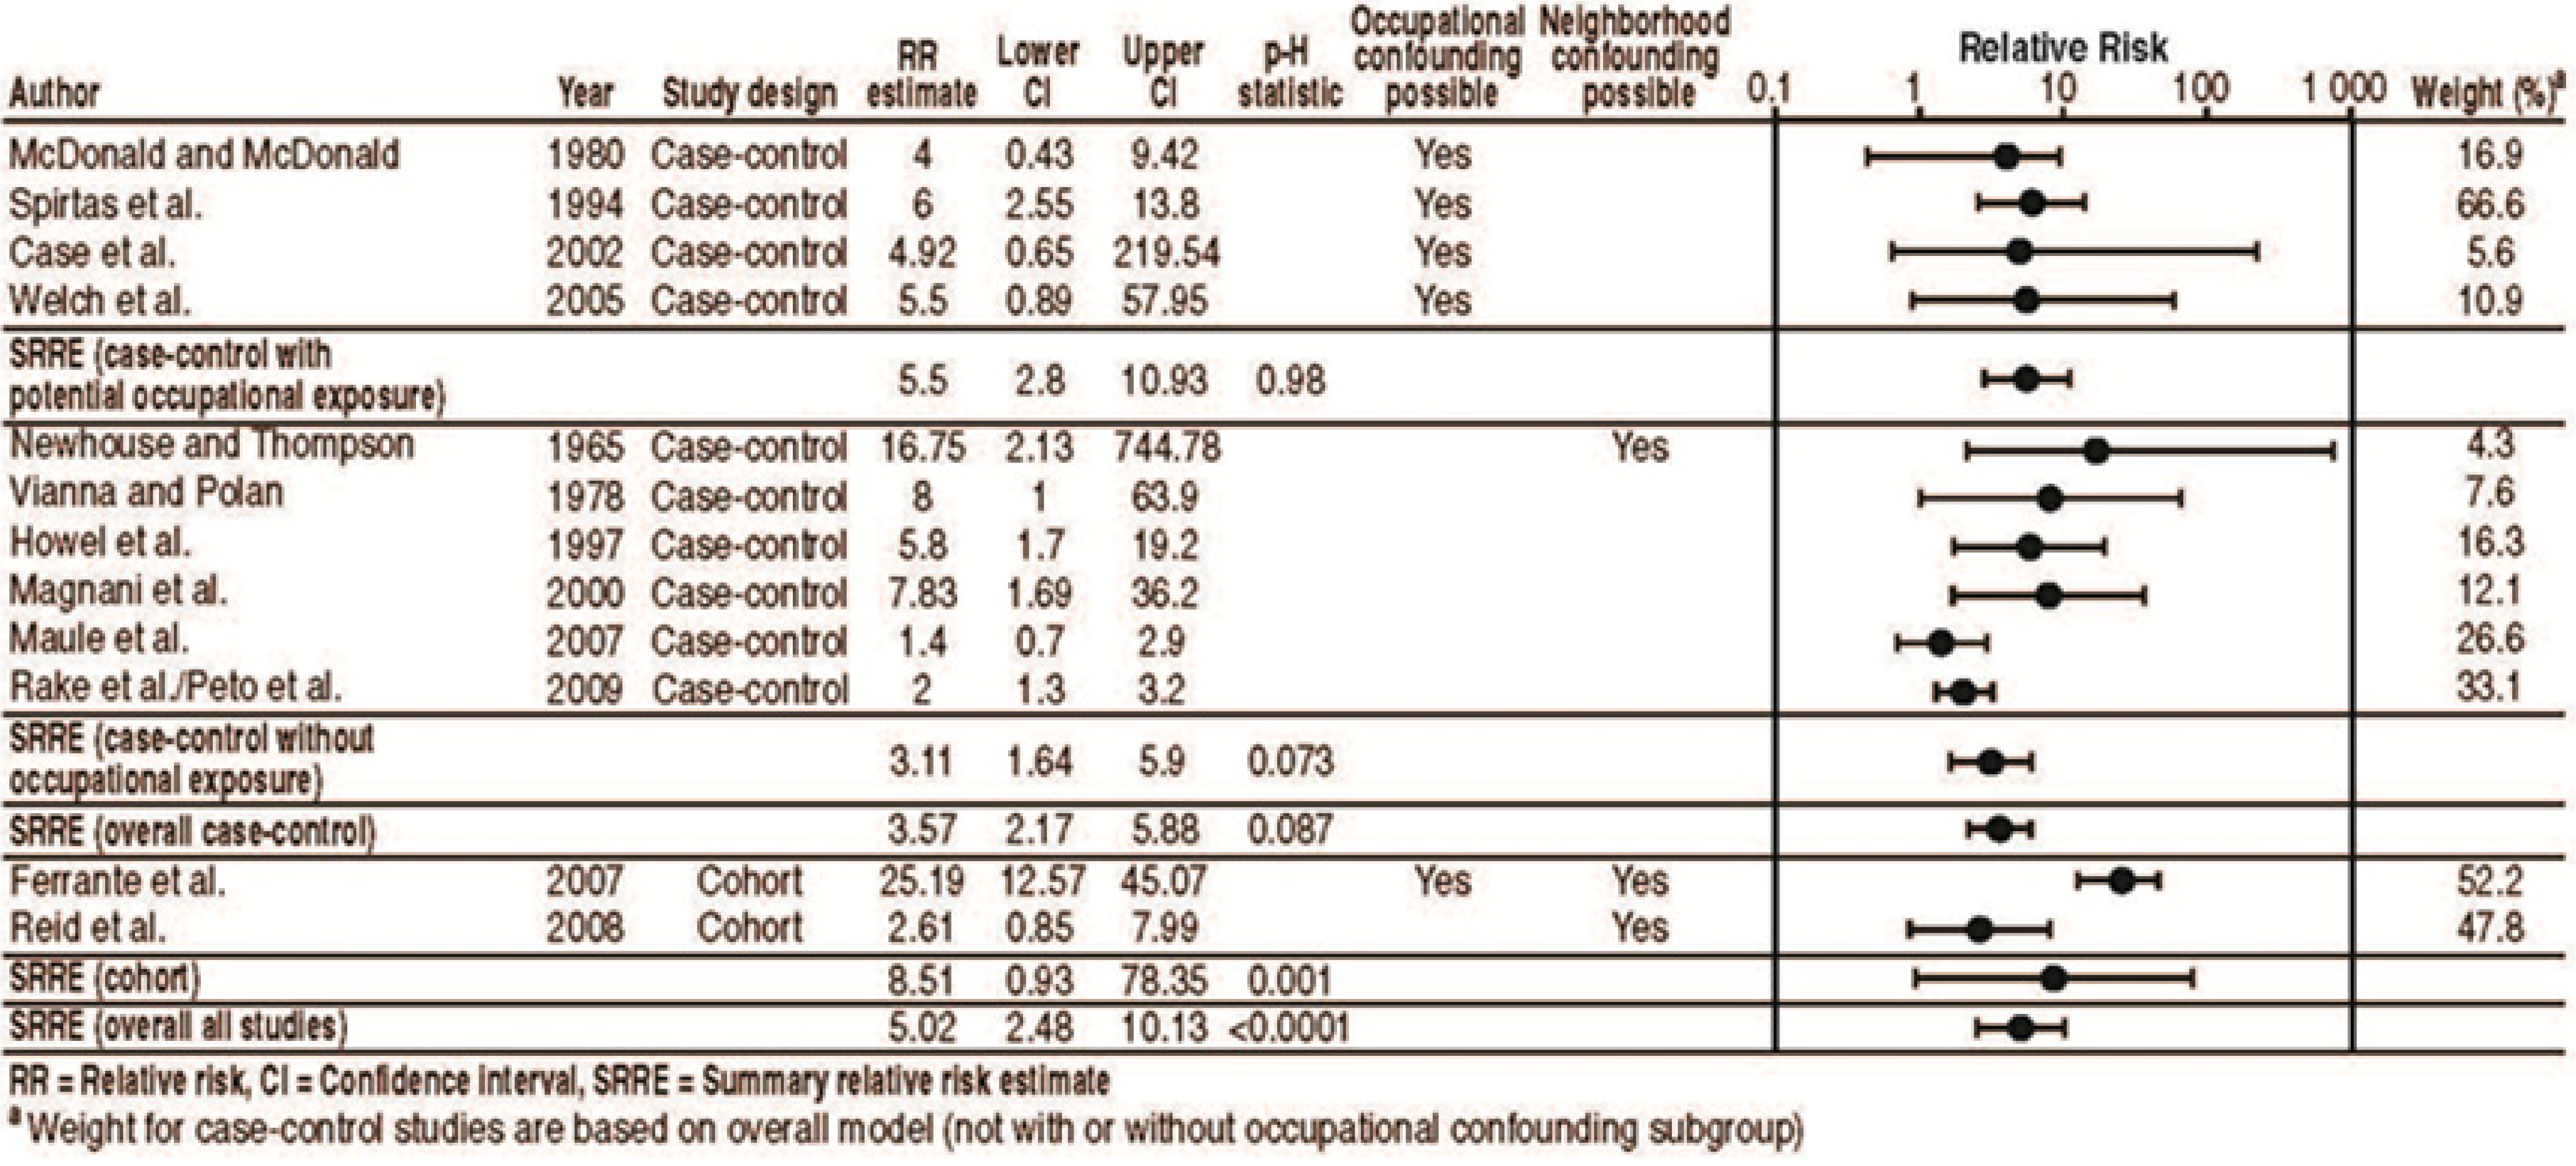
A further sub-analysis by study type (cohort vs. case-control) was performed. The SRRE for the two cohort studies together [63,65] was elevated, but was not statistically significant (SRRE = 8.51, 95% CI: 0.93–78.35; p-H = 0.001). There is considerable heterogeneity between these two cohort studies; the disparity in risk estimates is likely due to potential confounding by occupational exposures (e.g., [63]) and neighborhood exposures (e.g., [63,65]). In contrast, the SRRE for the 10 case-control studies was elevated and statistically significant (SRRE = 3.57, 95% CI: 2.17–5.88; p-H = 0.087). Significant heterogeneity was present in both study design models. The case-control studies were further divided by whether the results could have been modified by the cases being occupationally exposed to asbestos themselves. The SRREs for the case-control studies, with and without potential modification by occupational exposure, were both statistically significantly increased, and the model of studies with potential occupational exposure was homogeneous (SRRE = 5.5, 95% CI: 2.8–10.93, p-H = 0.980 and SRRE = 3.11, 95% CI: 1.64–5.9, p-H = 0.073, respectively). Additionally, in the group of case-control studies without potential for occupational exposure, the highest relative risk value was from a study with increased likelihood of neighborhood exposure (16.75) [2,3]. As a sensitivity analysis, the cohort study by Reid et al. [65], which did not have potential occupational confounding, was analyzed with the six case-control studies that also did not have occupational confounding. The resulting SRRE is 2.87 (95% CI: 1.69–4.88). This value is not much different from the overall SRRE based on the six case-control studies alone, indicating that this study does not have a large effect on the analysis. As an additional sensitivity analysis, the case-control study by Newhouse and Thompson [2,3] was omitted from the six case-control studies that did not have potential occupational confounding. The relative risk estimate for this study is considerably greater than those for the other five. A point of deviation for Newhouse and Thompson [2,3] appears to be study date, which may be a proxy for increased exposure or for less accurate categorization of exposure compared to the more recent studies. As noted earlier, the Newhouse and Thompson studies included persons exposed to various fiber types, including chrysotile, amosite, and crocidolite. The resulting SRRE based on five case-control studies is 2.83 (95% CI: 1.51–5.31). This value is also not much different from the overall SRRE based on the six case-control studies, including Newhouse and Thompson [2,3], indicating that this study does not have a large effect on the analysis.
3.1.2. Lung Cancer
The epidemiologic studies of domestic exposure rarely evaluated the risk of lung cancer. Only two studies with results for lung cancer were identified [58,63]. In the first study, a cohort of 2,218 family contacts of amosite asbestos factory workers in New Jersey first employed between 1941 and 1945 was studied [58]. The authors reported a slight statistically significant increase in cancer of the respiratory system for male family contacts of the factory workers with more than 20 years latency (observed vs. expected = 1.97), but not for female contacts (observed vs. expected = 1.70). In the second study of 1,780 wives of asbestos cement workers in Casale Monferrato, Italy, no significant increase in lung cancer was reported (SMR = 1.17; 95% CI: 0.60–2.04) [63]. Although the fiber potency gradient is less pronounced for lung cancer than it is for mesothelioma, fiber type is an important factor in determining disease. The study by Ferrante et al. included persons exposed to chrysotile and crocidolite, while the Andersen study included amosite workers.
3.1.3. Pleural and Interstitial Abnormalities
Case reports of pleural and interstitial abnormalities in domestically exposed individuals date back to the 1960s [7,76,77,78,79,80] and focus primarily on pleural plaques. Epidemiologic studies of pleural (i.e., plaques and diffuse pleural thickening) and interstitial abnormalities were gathered and reviewed (Table 3). As with the studies of asbestos-related malignancy, information on fiber type was either not reported or indicated a mixed fiber exposure. Six cohort and cross-sectional studies were identified [58,63,68,69,70,71], half of which accounted for potential confounding by occupational exposure [58,69,70,71]. Sider et al. [70] collected chest radiographs of the male workers and their wives, reporting that the majority (82%) of the husbands, who worked in the insulation trades, demonstrated more severe radiographic changes than their wives. Likewise, Kilburn et al. [69] reported that 75% of the wives with pleural and/or parenchymal abnormalities had husbands who worked in shipyards and exhibited abnormalities. One of these studies [58] also reported a statistically significant relationship between the duration of domestic exposure and year of first exposure with pleural thickening, calcification, or both abnormalities combined, but not small opacities alone. Sider et al. [70] reported that only the year of initial domestic exposure was statistically different from the comparison group.
3.2. Review of Domestic Exposure Studies
Unfortunately, none of the epidemiologic studies reported the level of asbestos exposures experienced by the domestic cases themselves. This was expected, given the findings of previous review articles, and the difficulty of characterizing exposures in a domestic setting in an epidemiologic study. At best, the epidemiologic studies characterized exposure by intensity (low, medium, high) or probability of exposure. In our review of household exposure studies, nineteen separate exposure studies were identified, although some reported on overlapping populations. These studies, in each of the four categories of interest, are shown in Table 4. As with the epidemiology studies, most exposures were to mixed fibers.
3.2.1. Exposures in the Home Environment
Three of the studies reviewed provided results of sampling within the homes of asbestos workers [81,82,83]. Two of the three studies [81,83] reported airborne asbestos concentrations, while the third [82] summarized reports of fibers found in the settled dust. These three studies were primarily reviews or articles that reported exposure concentrations indirectly and did not provide sufficient information to attribute concentrations directly to worker clothing. For example, in their book, Selikoff and Lee [82] described a study performed by Mount Sinai regarding asbestos workers’ homes, wherein workers were employed at asbestos factories during 1941 to 1954, and “small amounts” of amosite were identified in settled dust in the workers’ homes and in neighboring homes of non-asbestos workers up to 400 yards downwind of factories. The authors attributed these amosite fibers found in workers’ homes to the clothing workers brought home from the workplace. The amosite fibers identified in the homes of non-asbestos workers were attributed to atmospheric contamination and deposition; however, because samples were collected 20 to 25 years after the fact, it is difficult to attribute concentrations directly to a take-home source such as clothing. In addition, these samples involved settled dust from surfaces in the homes, rather than airborne asbestos concentrations. The observed dust concentrations are not representative of the air inhaled by household members.
In 1986, the World Health Organization (WHO) reported a mean concentration of 0.006 f/cc (range, 0.002–0.011 f/cc) in the homes of South African asbestos miners and estimated a range of 0.01–1 f/cc for “paraoccupational” exposures [83]. Although described as an environmental study, Nicholson et al. [81] found levels ranging from 100 to up to 5,000 ng/m3 by weight (approximately 0.003–0.15 f/cc based on the conversion factor presented by the National Research Council [84]) in the homes of chrysotile miners in California and Newfoundland, where homes were described as having visible fibers and dust in living areas and laundry facilities.
3.2.2. Exposures from Clothing
Our literature review identified only one study that provided airborne asbestos levels measured during laundering of workers’ clothing [85]. This study evaluated concentrations associated with laundering clothes contaminated during an asbestos removal operation, reporting an average airborne concentration of 0.4 ± 0.1 f/cc (duration not specified) resulting from picking up contaminated clothing and loading it into the washer. No information was provided regarding specific sample duration; however, earlier evaluations performed at the same building reported mean fiber counts that were typically associated with one-hour sampling duration. The exposure levels “dropped to zero” following a single wash cycle (Table 4). A maximum personal sample of 1.2 f/cc (corresponding mean = 0.4 f/cc, sample duration unknown) was measured during the complete laundry operation, and all asbestos fibers detected were chrysotile. This study was not conducted in a home laundry setting, but focused primarily on the sufficiency of the decontamination procedures used by 40 workers after the removal of an asbestos-containing ceiling. Although not reported specifically as 8-hour time-weighted averages, these exposure levels are clearly low.
Two studies regarding bulk samples of dust on workers’ clothing performed by NIOSH at friction product manufacturing plants were also reviewed. Unfortunately, these studies did not discuss airborne exposures resulting from this dust [86,87]. One of these studies reported that asbestos was present in 85% of samples obtained from clothing and car seats of friction workers, but did not describe the fiber type.
Table 4.
Domestic exposure studies.
3.2.3. Exposure Modeling and Simulation
Five exposure simulation studies were identified (Table 4). Four of these involved an evaluation of simulated domestic exposures resulting from those working with friction products, such as brakes and clutches [88,89,90,92], three of which were performed by the same group of investigators. The fifth study characterized exposures from roofers’ clothing [91]. Phase contrast microscopy (PCM) was used in all simulations; transmission electron microscopy (TEM) was also used in all except the Weir et al. study [92] to analyze fiber type in clothing-related samples. In studies employing TEM, PCM-equivalent (PCM-E) concentrations were also reported.
The simulations of friction-product-related exposures involved laundering activities by agitating a brake mechanic’s coveralls [92] and simulated clean-up of countertops and clothes-handling tasks, such as shaking and folding clothes worn by an operator, whose work activities involved packing and re-packing boxes of brakes and clutches [88,89] or performing repair work on heavy equipment [90]. All of these studies involved exposures only to chrysotile asbestos of unknown origin, because this was the fiber type used in the formulation of asbestos-containing friction materials [101]. Estimated 30 min PCM-E mean values were reported as 0.002 ± 0.002 f/cc (8 h time-weighted average [TWA] = 0.0001 f/cc) and 0.002–0.015 f/cc (mean = 0.011 f/cc) during clothes handling following unpacking and re-packing of clutches and brakes, respectively [88,89]. Similar asbestos levels were reported by Mowat et al. [91] in the simulation of potential exposures from asphalt-based roofing materials from scraping or picking dried material from laundered coveralls, with a 30 min exposure value of 0.0017 f/cc (range, non-detect [ND]–0.011 f/cc). For mechanics performing brake repair on heavy equipment, equivalent 30 min mean values following clothes handling were 0.036 f/cc and 0.010 f/cc for primary workers and bystanders, respectively [90]. During agitation of a brake mechanic’s coveralls following brake work, the 30 min concentration was 0.72 f/cc [92].
3.2.4. Lung-Burden Studies
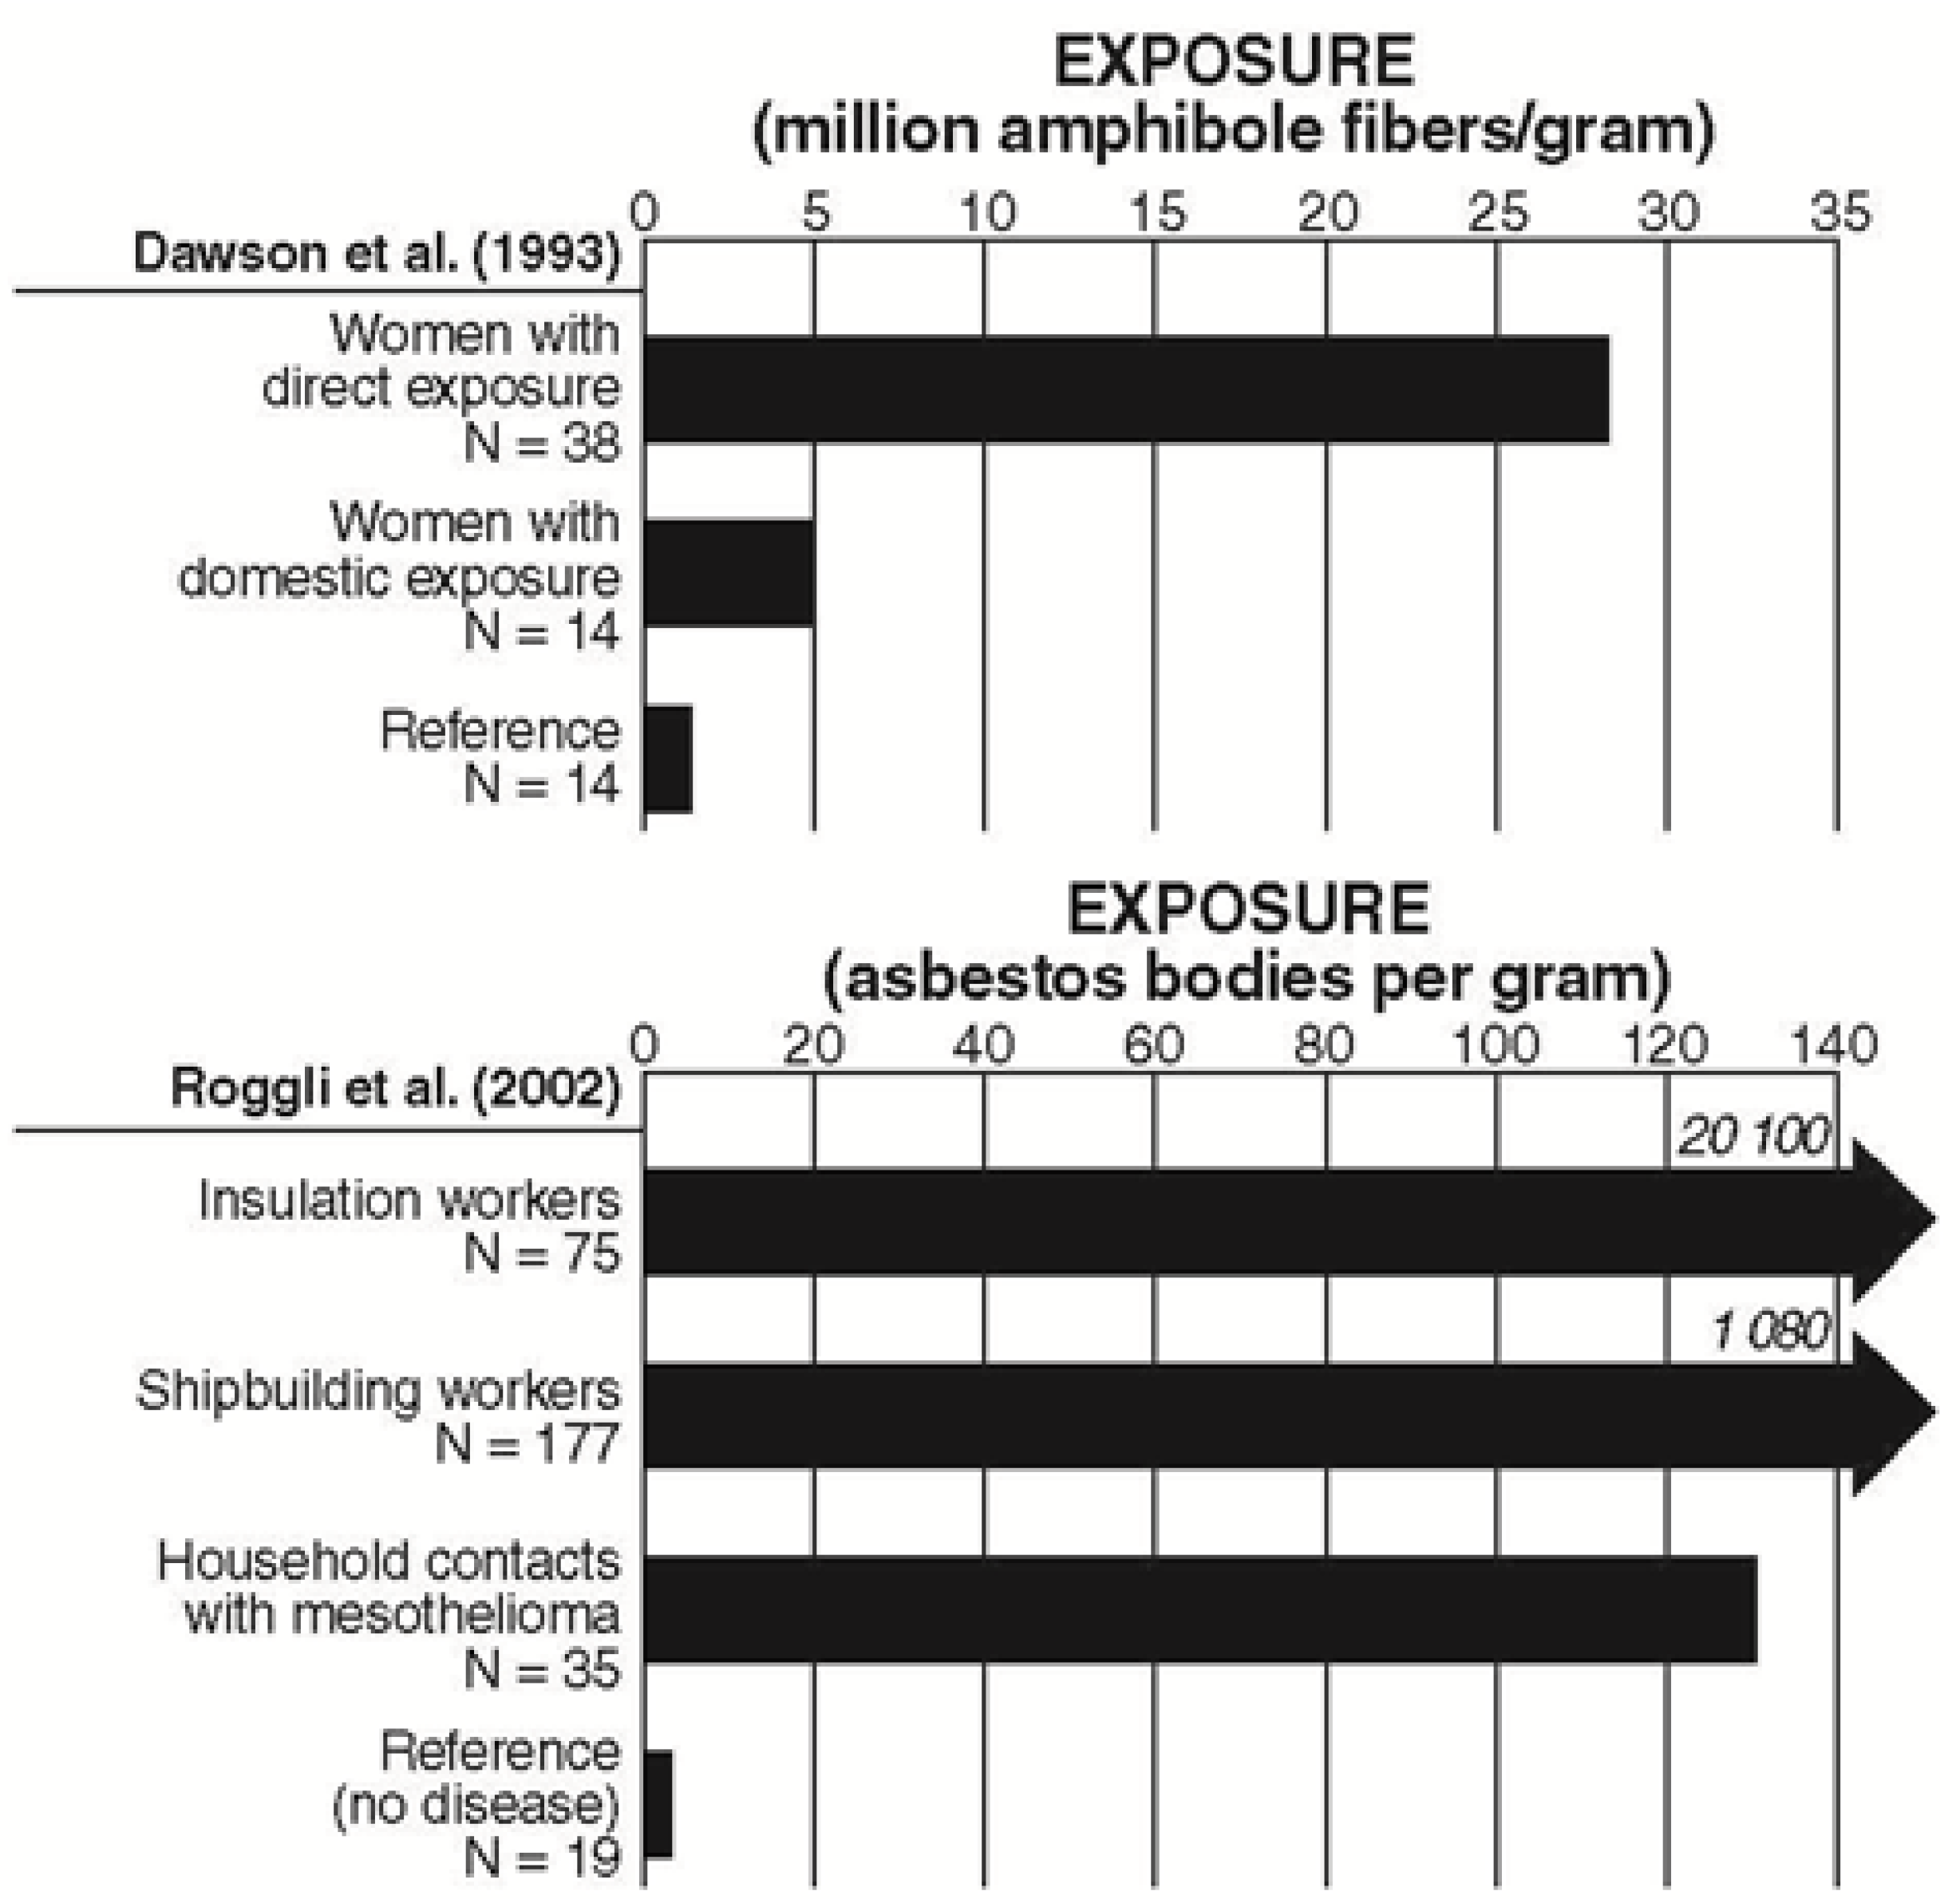
Six unique lung-burden studies were identified that provide results related to domestic exposure, generally reporting fiber concentrations either as fibers × 106/g dry lung (f/g) or asbestos bodies per gram of lung tissue analyzed (AB/g). Gibbs and colleagues [95,96] and Roggli and colleagues [102] reported multiple times on overlapping populations. Asbestos bodies are indicative of amphibole exposures, because asbestos bodies form primarily on amphibole fibers [102]. Of the studies identified, most reported that the domestically exposed persons were typically wives or daughters of insulators, boilermakers, or shipyard workers [36,93,94,96,97,98,99,100]. All six studies identified the fiber type detected in the lung tissue examined and found amphibole asbestos fibers, such as crocidolite and amosite, in the lungs of domestically exposed persons (Table 4). Only two studies [93,100] presented lung-burden data for domestic contacts compared to a reference group (Figure 2). Both studies indicated significantly higher concentrations of amphibole asbestos and/or AB/g of lung tissue in domestically exposed cases compared to the reference group, and even higher concentrations of amphibole asbestos in directly exposed insulation or shipyard workers, although the domestically exposed persons and directly exposed workers were not linked. No study compared the lung burdens of workers with those of their spouses.
In the series of studies by Roggli and colleagues, all of the asbestos workers were diagnosed with asbestosis, and three with lung cancer; all of the household contacts were diagnosed with either mesothelioma or lung cancer. In an update to their analyses involving 1,445 cases of mesothelioma, Roggli and colleagues reported that, in the household contacts identified, 57% were found to have pleural plaques, and 7.9% had asbestosis [100]. Of the four domestically exposed cases evaluated in their study, Dodson et al. [94] found ferruginous bodies in lung tissue of two of the four women, uncoated commercial amphibole asbestos fibers in another woman, uncoated non-commercial amphibole asbestos fibers in a third woman, and chrysotile fibers in another. Not surprisingly, high concentrations of crocidolite fibers were identified in lung tissue of the spouse of the crocidolite cement worker.
Figure 2.
Lung-burden studies.
Some of the studies provided exposure estimates of those domestically exposed, but generally, the objectives for these studies were not related to an evaluation of domestic exposure, and no explanation of exposure-level estimation or quantitative analysis was performed. For example, Camus et al. [103] analyzed lung cancer risk among women living in asbestos mining areas wherein indoor household concentrations were estimated by extrapolation from fiber burden results in ten autopsied women who had lived with asbestos workers. Indoor asbestos concentrations associated with these observed fiber burdens were reported as being approximately 0.03 f/cc higher than existing outdoor levels, although the method by which this result was obtained was not described. These authors also reported an estimated cumulative exposure of 7.8 f/cc-years in household contacts using their approach.
4. Discussion and Conclusions
Overall, the results indicate a consistent elevated risk of mesothelioma in the domestically exposed populations, and summary results suggest that the association may be modified by the potential for additional occupational exposure. The SRRE for all cohort and case-control studies indicated a five-fold greater risk of mesothelioma for persons domestically exposed. For persons domestically exposed, the results of the meta-analysis indicated a three- to five-fold increased risk for case-control studies and 8.5-fold risk of mesothelioma for cohort studies, although the cohort studies suffered from heterogeneity (and there were only two studies). Comparatively, the Bourdès et al. [10] meta-analysis of pleural mesothelioma found an eight-fold greater risk. Our finding of increased risk applies to domestically exposed populations in which the associated workers were employed in traditionally high-risk occupations involving exposure to asbestos, where in many cases, possible confounding due to direct asbestos exposures was not taken into account. For most of the included studies, exposures were to amphibole or mixed fiber exposures associated with traditionally high-risk occupations.
The domestic exposure studies of lung cancer were extremely limited and not supportive of an association between domestic exposure and lung cancer. In addition, both identified studies suffered from potential confounding by other occupational exposures and lack of consideration of smoking history. Fiber type was also not considered in these studies, though the two identified studies specifically included those exposed to amphibole asbestos. For the studies of pleural and interstitial abnormalities, results of pleural and interstitial abnormalities were often combined, despite them being two separate and distinct disease types, with reported exposures primarily being to mixed fibers. Even within pleural abnormalities themselves, the disease types differ (i.e., pleural plaques vs. diffuse pleural thickening) in terms of their health impact and level of exposure required to cause the abnormality [104]. The studies supported an association between abnormalities and domestic exposure, but the association is largely due to pleural abnormalities. Similar to the mesothelioma studies, the workers themselves were likely highly exposed populations with exposure to amphiboles (e.g., asbestos product plant, amosite factory, and shipyard workers, insulators, and miners). These studies are unique, in that they provide linked data on husbands and wives (i.e., data were collected on husbands and their wives, rather than workers in general and wives in general).
The findings of the lung-burden studies are consistent with the epidemiologic studies, in that they concluded that accumulated fiber burdens in persons exposed domestically might suggest a significant risk of mesothelioma, although the directly exposed workers in these studies were in traditional high-risk occupations, such as insulators, shipyard workers, and those in the building trades. All nine lung-burden studies (six unique studies total) detected amphibole fibers in the lungs of domestically exposed persons and, when compared to an appropriate reference group, were found to be present at significantly higher concentrations (Figure 2). In the Roggli series of studies, the lungs of household contacts were found to contain commercial amphiboles (defined as amosite and crocidolite) in 48% of cases, non-commercial amphiboles in 10.5% of cases, and chrysotile in 4.2% of the cases. Other studies also reported elevated amphibole fiber burdens [93,95,97]. These concentrations were reported as similar to those found in construction workers (190 AB/g), with higher lung fiber burdens reported in wives than children of these workers [100].
Ideally, airborne exposure estimates including asbestos fiber type information for the participants in the epidemiologic studies would exist in the peer-reviewed literature to allow for better evaluation of risk; however, this is not the case for epidemiologic studies of domestically exposed individuals. Instead, there are review articles with limited discussion of airborne measurements in asbestos miners’ homes, one study of airborne monitoring during laundering the clothes of asbestos abatement workers exposed to chrysotile, and more recent controlled simulation studies of airborne concentrations during the handling of the clothes of workers who traditionally have low chrysotile exposures. Thus, the experiences of the domestically exposed populations in the epidemiologic studies (exposed via workers in high-risk occupations, with high levels of exposure to amphibole asbestos) do not correspond to the exposures characterized by the available airborne data (generally for low-level chrysotile exposures).
As noted above, the existing relevant airborne exposure data pertain to populations occupationally exposed to low-level chrysotile asbestos. Given the absence of epidemiologic studies of populations exposed domestically by family members who were exposed occupationally to low-level chrysotile, alternative methods must be used to estimate the exposures and risk of mesothelioma for these populations.
First, it is logical that, if the worker is exposed to low levels of asbestos occupationally, then their co-habitants would experience even lower exposure concentrations. Automobile mechanics are a good population in which to test this hypothesis, because brake mechanics are exposed to low concentrations of solely chrysotile asbestos (e.g., [105,106]). For example, Paustenbach et al. [105] reported a typical 8-hour TWA exposure of 0.04 f/cc for automobile mechanics, based on review of numerous historical studies. When 8 h TWAs are calculated for the four simulation studies that involve clothing manipulation or potential take-home exposure from friction products [89,90,92], the exposure levels reported are approximately two orders of magnitude lower than the 8-hour TWA for automobile mechanics (0.0001 f/cc vs. 0.04 f/cc). In fact, the daily exposures resulting from clothing activities were indistinguishable from background concentrations of asbestos, reported as ranging between 0.00001 f/cc and 0.0001 f/cc [107].
The results of the simulation studies are based on a small sample size in some studies (n = 1 in Jiang et al. [88]) or involved a short period of time (45 seconds in Jiang et al. [88], to 2 min in Madl et al. [89]); however, in all four studies, the results were consistently low, well below current and historical occupational exposure limits and, in some cases, within ambient concentrations. The anomaly of higher concentrations reported in the Weir et al. [92] study can be explained, because the majority of the fibers present in the sample were non-asbestiform, such as cotton fibers. Although this comparison has limitations due to the small sample sizes and exposure durations attributed to clothing manipulation activities and differences in methods used to analyze for asbestos fibers, the comparison nonetheless indicates that, at a minimum, domestic asbestos exposures to persons derived from domestic relationships with automobile mechanics are likely to be lower than those observed in occupationally exposed career automobile mechanics. This is consistent with the lung-burden studies showing a gradation of fiber burden from occupationally exposed to domestically exposed persons [93,100].
In our review, only one study [48] identified a domestically exposed case of mesothelioma reportedly due to chrysotile exposure in a woman whose husband was an automobile mechanic. Although fiber type was not specifically reported, chrysotile was the only fiber type used in the manufacture of brake and clutch parts [101]. This study, and therefore this case, was not included in the meta-analysis, because it lacked the information to calculate an estimate of relative risk, namely a comparison group. Vianna and Polan [4], Spirtas et al. [49], and Welch et al. [53] combine the activity of brake lining work/repair with traditionally highly exposed asbestos activities (e.g., insulation, shipyard work); thus, any observed increase in risk cannot be attributed to automobile mechanic work or solely to chrysotile exposure, and instead is highly likely attributable to the other activities (e.g., [108]).
Second, if workers whose occupation involving low-level chrysotile exposure is not associated with an increased risk of mesothelioma, it follows that co-habitants of these workers also would not have an increased risk of mesothelioma. The existing epidemiologic studies of domestically exposed populations support this hypothesis, and demonstrate that the risk for the domestically exposed individual is remarkably less than that of the worker. While the exposure data is not complete in many of these studies with respect to both exposure level and fiber type, at least for one group—mechanics—the epidemiology shows that career workers exposed to low levels of chrysotile asbestos are not at risk and, therefore, it follows that the families of these workers would also not be at increased risk for developing asbestos-related disease. This has also been demonstrated in other industries, where higher exposures have been reported. Maule et al. [54] provided risk estimates for those occupationally exposed during asbestos cement manufacturing, and their relatives, with the OR for the workers being remarkably greater than for those domestically exposed (27.5 vs. 1.4, non-significant). Likewise, the radiographic studies showed that the majority of the workers demonstrated more severe radiographic changes than their wives, and alternatively, if the wives showed radiographic abnormalities, so did their husbands [69,70]. Thus, if the existing studies of domestically exposed populations show trends of lower risk and disease than the worker population, it follows that if the worker population does not have increased risk, then the domestically exposed co-habitant would not either.
In conclusion, the epidemiologic and lung burden studies, as a surrogate of past exposure, support an increased risk of mesothelioma and interstitial, but more likely pleural, abnormalities in domestically exposed individuals whose associated worker was employed in traditionally high-risk occupations involving exposure to amphibole asbestos. Quantifiable exposure concentrations do not exist for these domestically exposed cohorts; however, some data exist for manipulation of worker clothing after low-level chrysotile exposure, mostly in the form of recent exposure simulations. These simulation data show that results for domestic exposures are lower than the workers’ exposures and are commensurate with background concentrations.
Acknowledgements
The authors thank Meghan Mitchell of Exponent for her aid in reviewing the epidemiologic studies.
Conflicts of Interest
No funding was obtained to prepare this manuscript. Two of the authors (David L. Dahlstrom and Fionna Mowat) have been designated as experts in litigation matters related to asbestos, and all authors have been retained as consultants in asbestos-related litigation matters.
References
- Wagner, J.C.; Sleggs, C.A.; Marchand, P. Diffuse pleural mesothelioma and asbestos exposure in the north western Cape Province. Brit. J. Ind. Med. 1960, 17, 260–271. [Google Scholar]
- Newhouse, M.L.; Thompson, H. Epidemiology of mesothelial tumors in the London area. Ann. N. Y. Acad. Sci. 1965, 132, 579–588. [Google Scholar]
- Newhouse, M.L.; Thompson, H. Mesothelioma of pleura and peritoneum following exposure to asbestos in the London area. Brit. J. Ind. Med. 1965, 22, 261–269. [Google Scholar]
- Vianna, N.J.; Polan, A.K. Non-occupational exposure to asbestos and malignant mesothelioma in females. Lancet 1978, 1, 1061–1063. [Google Scholar] [CrossRef]
- McDonald, A.D.; McDonald, J.C. Malignant mesothelioma in North America. Cancer 1980, 46, 1650–1656. [Google Scholar]
- Grandjean, P.; Bach, E. Indirect exposures: The significance of bystanders at work and at home. Amer. Ind. Hyg. Assn. J. 1986, 47, 819–824. [Google Scholar]
- National Institute for Occupational Safety and Health (NIOSH). Report to Congress on Workers’ Home Contamination Study Conducted under the Workers’ Family Protection Act; United States; Department of Health and Human Services, Centers for Disease Control and Prevention: Cincinnati, OH, USA, 1995.
- National Institute for Occupational Safety and Health (NIOSH). Protecting Workers’ Families: A Research Agenda; United States Department of Health and Human Services, Centers for Disease Control and Prevention: Cincinnati, OH, USA, 2002.
- Institut National de la Santé de la Recherche Médicale (INSERM). Effets sur la santé des principaux types d’exposition à l’amiante. INSERM: Paris, France, 1997. [Google Scholar]
- Bourdès, V.; Boffetta, P.; Pisani, P. Environmental exposure to asbestos and risk of pleural mesothelioma: Review and meta-analysis. Eur. J. Epidemiol. 2000, 16, 411–417. [Google Scholar]
- Donovan, E.P.; Donovan, B.L.; McKinley, M.A.; Cowan, D.M.; Paustenbach, D.P. Evaluation of take home (para-occupational) exposure to asbestos and disease: A review of the literature. Crit. Rev. Toxicol. 2012, 42, 703–731. [Google Scholar]
- Sutton, A.J.; Jones, D.R.; Abrams, K.R.; Sheldon, T.A.; Song, F. Systematic reviews and meta-analysis: A structured review of the methodological literature. J. Health. Serv. Res. Policy 1999, 4, 49–55. [Google Scholar]
- Andersson, T.; Ahlbom, A. Episheet software: Spreadsheets for the analysis of epidemiologic data. 2004. Available online: http://www.google.com/url?sa=t&rct=j&q=&esrc=s&frm=1&source=web&cd=1&ved=0CC0QFjAA&url=http%3A%2F%2Fkrothman.hostbyet2.com%2FEpisheet.xls&ei=SeTyUZrgPOSqiALi2IDwDQ&usg=AFQjCNHeAwcg2RhXfkGM_b8RdX498JSs9A&sig2=U6MjH7LGvrV4FIowPto19g&bvm=bv.49784469,d.cGE (accessed on 23 October 2013).
- Lieben, J.; Pistawka, H. Mesothelioma and asbestos exposure. Arch. Environ. Health 1967, 14, 559–563. [Google Scholar]
- Rusby, N.L. Pleural manifestations following the inhalation of asbestos in relation to malignant change. J. Roy. Nav. Med. Serv. 1968, 54, 142–148. [Google Scholar]
- Heller, R.M.; Janower, M.L.; Weber, A.L. The radiological manifestations of malignant pleural mesothelioma. Amer. J. Roentgenol. 1970, 108, 53–59. [Google Scholar] [CrossRef]
- Bittersohl, G.; Ose, H. The epidemiology of pleural mesotheliomas. (in German). Z. Gesante Hyg. 1971, 17, 861–864. [Google Scholar]
- Champion, P. Two cases of malignant mesothelioma after exposure to asbestos. Amer. Rev. Resp. Dis. 1971, 103, 821–826. [Google Scholar]
- Knappmann, J. Observations made at post mortem examination of 251 cases of mesothelioma in Hamburg (1958–1968). (in German). Pneumonology 1972, 148, 60–65. [Google Scholar] [CrossRef]
- Greenberg, M.; Davies, T.A.L. Mesothelioma register 1967−1968. Br. J. Ind. Med. 1974, 34, 91–104. [Google Scholar]
- Lillington, G.A.; Jamplis, R.W.; Differding, J.R. Conjugal malignant mesothelioma. N. Engl. J. Med. 1974, 291, 583–584. [Google Scholar]
- Milne, J.E.H. Thirty-two cases of mesothelioma in Victoria, Australia: A retrospective survey related to occupational asbestos exposure. Br. J. Ind. Med. 1976, 33, 115–122. [Google Scholar]
- Edge, J.R.; Choudhury, S.L. Malignant mesothelioma of the pleura in Barrow-in-Furness. Thorax 1978, 33, 26–30. [Google Scholar]
- Li, F.P.; Lokich, J.; Lapey, J.; Neptune, W.B.; Wilkins, E.W. Familial mesothelioma after intense asbestos exposure at home. J. Amer. Med. Assn. 1978, 240. [Google Scholar] [CrossRef]
- Epler, G.R.; Gerald, M.X.; Gaensler, E.A.; Carrington, C.B. Asbestos-related disease from household exposure. Respiration 1980, 39, 229–240. [Google Scholar]
- Vianna, N.J.; Maslowsky, J.; Roberts, S.; Spellman, G.; Patton, R.B. Malignant mesothelioma: Epidemiologic patterns in New York State. N. Y. State J. Med. 1981, 81, 735–738. [Google Scholar]
- Martensson, G.; Larsson, S.; Zettergren, L. Malignant mesothelioma in two pairs of siblings: Is there a hereditary predisposing factor? Eur. J. Resp. Dis. 1984, 65, 179–184. [Google Scholar]
- Krousel, T.; Garcas, N.; Rothschild, H. Familial clustering of mesothelioma: A report on three affected persons in one family. Amer. J. Prev. Med. 1986, 2, 186–188. [Google Scholar]
- Li, F.P.; Drefus, M.G.; Antman, K.H. Asbestos-contaminated nappies and familial mesothelioma. Lancet 1989, 1, 909–910. [Google Scholar]
- Kane, M.J.; Chahinian, A.P.; Holland, J.F. Malignant mesothelioma in young adults. Cancer 1990, 65, 1449–1455. [Google Scholar]
- Konetzke, G.W.; Beck, B.; Mehnert, W.H. Uber berufliche und auberberufliche asbestwirkungen—Remarks on occupational and non-occupational effects of asbestos. Pneumologie 1990, 44, 858–861. [Google Scholar]
- Oern, S.; Odden, S.; Osnes, M. Familial clustering of asbestos-related disease. (in Norwegian). Tidssker Nor Laegeforen 1991, 111, 1099–1101. [Google Scholar]
- Chellini, E.; Fornaciai, G.; Merler, E.; Paci, E.; Costantini, A.S.; Silvestri, S.; Zappa, M.; Buiatti, E. Pleural malignant mesothelioma in Tuscany, Italy (1970−1988): II. Identification of occupational exposure to asbestos. Amer. J. Ind. Med. 1997, 21, 577–585. [Google Scholar]
- Seniori-Costantini, A.; Chellini, E. The experience of the mesothelioma registry of Tuscany in assessing health hazard associated with asbestos exposure. Med. Lav. 1997, 88, 310–315. [Google Scholar]
- Dodoli, D.; del Nevo, M.; Fiumalbi, C.; Iaia, T.E.; Cristaudo, A.; Comba, P.; Viti, C.; Battista, G. Environmental household exposures to asbestos and occurrence of pleural mesothelioma. Amer. J. Ind. Med. 1992, 21, 681–687. [Google Scholar]
- Giarelli, L.; Bianchi, C.; Grandi, G. Malignant mesothelioma of the pleura in Trieste, Italy. Amer. J. Prev. Med. 1992, 22, 521–530. [Google Scholar]
- Schneider, J.; Straif, K.; Woitowitz, H.J. Pleural mesothelioma and household asbestos exposure. Rev. Environ. Health 1966, 11, 65–70. [Google Scholar]
- Rees, D.; Goodman, K.; Fourie, E.; Chapman, R.; Blignaut, C.; Bachmann, M.O.; Myers, J. Asbestos exposure and mesothelioma in South Africa. S. Afr. Med. J. 1990, 89, 627–634. [Google Scholar]
- Ascoli, V.; Fantini, F.; Carnovale, S.C.; Blasetti, F.; Bruno, C.; di Domenicantonio, R.; lo Presti, E.; Pasetto, R.; Nardi, F.; Comba, P. Malignant mesothelioma in the industrial area of Colleferro. Med. Lav. 2000, 91, 547–564. [Google Scholar]
- Barbieri, P.G.; Lombardi, S.; Candela, A.; Pezzotti, C.; Binda, I. Incidence of malignant mesothelioma (1980–1999) and asbestos exposure in 190 cases diagnosed in the population of the Province of Brescia. Med. Lav. 2001, 92, 249–262. [Google Scholar]
- Bianchi, C.; Brollo, A.; Ramani, L.; Bianchi, T.; Giarelli, L. Asbestos exposure in malignant mesothelioma of the pleura: A survey of 557 cases. Ind. Health 2001, 39, 161–167. [Google Scholar]
- Mangone, L.; Romanelli, A.; Campari, C.; Candela, S. Malignant mesothelioma in Emilia-Romagna: Incidence and asbestos exposure. Epidemiol. Prev. 2002, 26, 124–129. [Google Scholar]
- Miller, A. Mesothelioma in household members of asbestos-exposed workers: 32 United States cases since 1990. Amer. J. Ind. Med. 2005, 47, 458–462. [Google Scholar] [CrossRef]
- Bianchi, C.; Bianchi, T.; Tommasi, M. Mesothelioma of the pleura in the province of Trieste. Med. Lav. 2007, 98, 374–380. [Google Scholar]
- Ashcroft, T.; Heppelston, A.G. Mesothelioma and asbestos on tyneside. In Pneumoconiosis: Proceedings of the International Conference, Johannesburg 1969; Shapiro, H.A., Ed.; Oxford University Press: Cape Town, South Africa, 1970; pp. 177–179. [Google Scholar]
- McEwen, J.; Finlayson, A.; Mair, A.; Gibson, A.A. Asbestos and mesothelioma in Scotland: An epidemiological study. Int. Arch. Arbeitsmed. 1971, 28, 301–311. [Google Scholar]
- Rubino, G.F.; Scansetti, G.; Donna, A.; Palestro, G. Epidmilogy of pleural mesotheioma in north-western Italy (Piedmont). Br. J. Ind. Med. 1972, 29, 436–442. [Google Scholar]
- Muscat, J.E.; Wynder, E.L. Cigarette smoking, asbestos exposure, and malignant mesothelioma. Cancer Res. 1991, 51, 2263–2267. [Google Scholar]
- Spirtas, R.; Heineman, E.F.; Bernstein, L.; Beebe, G.W.; Keehn, R.J.; Stark, A.; Harlow, B.L.; Benichou, J. Malignant mesothelioma: Attributable risk of asbestos exposure. Occup. Environ. Med. 1994, 51, 804–811. [Google Scholar]
- Howel, D.; Arblaster, L.; Sinburne, L.; Schweiger, M.; Renvoize, E.; Hatton, P. Routes of asbestos exposure and the development of mesothelioma in an English region. Occup. Environ. Med. 1997, 54, 403–409. [Google Scholar]
- Case, B.W.; Camus, M.; Richardson, L.; Parent, M.E.; Desy, M.; Siemiatycki, J. Preliminary findings for pleural mesothelioma among women in the Quebec chrysotile mining regions. Ann. Occup. Hyg. 2002, 46, S128–S131. [Google Scholar]
- Magnani, C.; Agudo, A.; Gonzalez, C.A.; Andrion, A.; Calleja, A.; Chellini, E.; Dalmasso, P.; Escolar, A.; Hernandez, S.; Lvaldi, C.; et al. Multicentric study on malignant pleural mesothelioma and non-occupational exposure to asbestos. Br. J. Cancer 2000, 83, 104–111. [Google Scholar]
- Welch, L.S.; Acherman, Y.I.Z.; Haile, E.; Sokas, R.K.; Sugarbaker, P.H. Asbestos and peritoneal mesothelioma among college-educated men. Int. J. Occup. Environ. Health 2005, 11, 254–258. [Google Scholar]
- Maule, M.M.; Magnani, C.; Dalmasso, P.; Mirabelli, D.; Merletti, F.; Biggeri, A. Modeling mesothelioma risk associated with environmental asbestos exposure. Environ. Health Perspect. 2007, 115, 1066–1071. [Google Scholar]
- Magnani, C.; Dalmasso, P.; Biggeri, A.; Ivaldi, C.; Mirabelli, D.; Terracini, B. Increased risk of malignant mesothelioma of the pleura after residential or domestic exposure to asbestos: A case-control study in Casale Monferrato, Italy. Environ. Health Perspect. 2001, 109, 915–919. [Google Scholar]
- Rake, C.; Gilham, C.; Hatch, J.; Darnson, A.; Hodgson, J.; Peto, J. Occupational, domestic and environmental mesothelioma risks in the British population: A case-control study. Br. J. Cancer 2009, 100, 1175–1183. [Google Scholar]
- Peto, J.; Rake, C.; Gilham, C.; Hatch, J. Occupational, Domestic and Environmental Mesothelioma Risks in Britain: A Case-Control Study; Health and Safety Executive: Norwich, UK, 2009.
- Anderson, H.A. Family contact exposure. In Proceedings of the World Symposium on Asbestos; Canadian Asbestos Information Centre: Montreal, Canada, 1982; pp. 349–362. [Google Scholar]
- Joubert, L.; Seidman, H.; Selikoff, I.J. Mortality experience of family contacts of asbestos factory workers. Ann. N. Y. Acad. Sci. 1991, 643, 416–418. [Google Scholar]
- Anderson, H.A.; Lilis, R.; Daum, S.M.; Selikoff, I.J. Asbestosis among household contacts of asbestos factory workers. Ann. N. Y. Acad. Sci. 1979, 330, 387–399. [Google Scholar]
- Anderson, H.A.; Lilis, R.; Daum, S.M.; Fischbein, A.S.; Selikoff, I.J. Household-contact asbestos neoplastic risk. Ann. N. Y. Acad. Sci. 1976, 271, 311–323. [Google Scholar]
- Selikoff, I.J. Household risks with inorganic fibers. Bull. N. Y. Acad. Med. 1981, 57, 947–961. [Google Scholar]
- Ferrante, D.; Bertolotti, M.; Todesco, A.; Mirabelli, D.; Terracini, B.; Magnani, C. Cancer mortality and incidence of mesothelioma in a cohort of wives of asbestos workers in Casale Monferrato, Italy. Environ. Health Perspect. 2007, 115, 1401–1405. [Google Scholar]
- Magnani, C.; Terracini, B.; Ivaldi, C.; Botta, M.; Budel, P.; Mancini, A.; Zanetti, R. A cohort study on mortality among wives of workers in the asbestos cement industry in Casale Monferrato, Italy. Br. J. Ind. Med. 1993, 50, 779–784. [Google Scholar]
- Reid, A.; Heyworth, J.; de Klerk, N.H.; Musk, B. Cancer incidence among women and girls environmentally and occupationally exposed to blue asbestos at Wittenoom, Western Australia. Int. J. Cancer 2008, 122, 2337–2344. [Google Scholar]
- Hansen, J.; de Klerk, N.H.; Eccles, J.L.; Musk, A.W.; Hobbs, M.S. Malignant mesothelioma after environmental exposure to blue asbestos. Int. J. Cancer 1993, 54, 578–581. [Google Scholar]
- Yazicioglu, S.; Ilcayto, R.; Balci, K.; Sayli, B.S.; Yorulmaz, B. Pleural calcification, pleural mesotheliomas, and bronchial cancers caused by tremolite dust. Thorax 1980, 35, 564–569. [Google Scholar]
- Navratil, M.; Trippe, F. Prevalence of pleural calcification in persons exposed to asbestos dust, and in the general population in the same district. Environ. Res. 1972, 5, 210–216. [Google Scholar]
- Kilburn, K.H.; Warshaw, R.; Thornton, J.C. Asbestos diseases and pulmonary symptoms and signs in shipyard workers and their families in Los Angeles. Arch. Int. Med. 1986, 146, 2213–2220. [Google Scholar]
- Sider, L.; Holland, E.A.; Davis, T.M.; Cugell, D.W. Changes on radiographs of wives of workers exposed to asbestos. Radiology 1987, 164, 723–726. [Google Scholar]
- Peipins, L.A.; Lewin, M.; Campolucci, S.; Lybarger, J.A.; Miller, A.; Middleton, D.; Weis, C.; Spence, M.; Black, B.; Kapil, V. Radiographic abnormalities and exposure to asbestos-contaminated vermiculite in the community of Libby, Montana, USA. Environ. Health Perspect. 2003, 111, 1753–1759. [Google Scholar]
- Hodgson, J.T.; Darnton, A. The quantitative risks of mesothelioma and lung cancer in relation to asbestos exposure. Ann. Occup. Hyg. 2000, 44, 565–601. [Google Scholar]
- Yarborough, C.M. Chrysotile as a cause of mesothelioma: An assessment based on epidemiology. Crit. Rev. Toxicol. 2006, 36, 165–187. [Google Scholar]
- Berman, W.D.; Crump, K.S. A meta-analysis of asbestos-related cancer risk that addresses fiber size and mineral type. Crit. Rev. Toxicol. 2008, 38, S49–S73. [Google Scholar]
- Berman, W.D.; Crump, K.S. Update of potency factors for asbestos-related lung cancer and mesothelioma. Crit. Rev. Toxicol. 2008, 38, S1–S47. [Google Scholar]
- Kiviluoto, T. Pleural plaques and asbestos: Further observations on endemic and other nonoccupational asbestosis. Ann. N. Y. Acad. Sci. 1965, 132, 235–239. [Google Scholar]
- Dalquen, P.; Hinz, I.; Dabbert, A.F. Pleural plaques, asbestosis and exposure to asbestos: An epidemiological study from the Hamburg Area. Pneumonologie 1970, 143, 23–42. [Google Scholar]
- Ebihara, I. Asbestos related pulmonary disorders in Japan: Occupational exposure, contact in the home and air pollutional exposure to asbestos in Japanese urban districts. Rodo Kagaku (Journal of Science of Labour—Japanese Edition) 1981, 57, 363–396. [Google Scholar]
- Lander, F.; Viskum, B. The occurrence of benign pulmonary changes in the spouses of previously employed asbestos workers. Ugeskr. Laeg. 1985, 147, 1805–1806. [Google Scholar]
- Bianchi, C.; Brollo, A.; Ramani, L.; Berte, R. Exposure to asbestos in Monfalcone, Italy. A necropsy-based study. In Autopsy in Epidemiology and Medical Research; Ribloi, E., Delendi, M., Eds.; International Agency for Research on Cancer (IARC): Lyon, France, 1991; pp. 127–140. [Google Scholar]
- Nicholson, W.J.; Rohl, A.N.; Weisman, I.; Selikoff, I.J. Environmental asbestos concentrations in the United States. In Biological Effects of Mineral Fibres; Wagner, J.C., Ed.; International Agency for Research on Cancer (IARC): Lyon, France, 1980; Volume 2, pp. 823–827. [Google Scholar]
- Selikoff, I.J.; Lee, D.H.K. Asbestos and Disease; Academic Press: New York, NY, USA, 1978. [Google Scholar]
- World Health Organization (WHO). Asbestos and Other Natural Mineral Fibres; World Health Organisation: Geneva, Swizerland, 1986.
- Committee on Nonoccupational Health Risks of Asbestiform Fibers; Board on Toxicology and Environmental Health Hazards; Commission on Life Sciences; National Research Council (NRC). Asbestiform. Fibers: Nonoccupational Health Risks; National Academy Press: Washington, DC, USA, 1984.
- Sawyer, R.N. Asbestos exposure in a Yale building. Environ. Res. 1977, 13, 146–169. [Google Scholar]
- Seixas, N.; Ordin, D. Health Hazard Evaluation Report; National Institute for Occupational Safety and Health (NIOSH): Cincinnati, OH, USA, 1986.
- Driscoll, R.J.; Elliott, L.J. Health Hazard Evaluation Report; National Institute for Occupational Safety and Health (NIOSH): Trenton, MI, USA, 1990.
- Jiang, G.C.T.; Madl, A.K.; Ingmundson, K.J.; Murbach, D.M.; Fehling, K.A.; Paustenbach, D.J.; Finley, B.L. A study of airborne chrysotile concentrations associated with handling, unpacking, and repacking boxes of automobile clutch discs. Regul. Toxicol. Pharmacol. 2008, 51, 87–97. [Google Scholar]
- Madl, A.K.; Scott, L.L.; Murbach, D.M.; Fehling, K.A.; Finley, B.L.; Paustenbach, D.J. Exposure to chrysotile asbestos associated with unpacking and repacking boxes of automobile brake pads and shoes. Ann. Occup. Hyg. 2008, 52, 463–479. [Google Scholar]
- Madl, A.K.; Gaffney, S.H.; Balzer, J.L.; Paustenbach, D.J. Airborne asbestos concentrations associated with heavy equipment brake removal. Ann. Occup. Hyg. 2009, 53, 839–857. [Google Scholar]
- Mowat, F.; Weidling, R.; Sheehan, P. Simulation tests to assess occupational exposure to airborne asbestos from asphalt-based roofing products. Ann. Occup. Hyg. 2007, 51, 451–462. [Google Scholar]
- Weir, F.W.; Tolar, G.; Meraz, L.B. Characterization of vehicular brake service personnel exposure to airborne asbestos and particulate. Appl. Occup. Environ. Hyg. 2001, 16, 1139–1146. [Google Scholar]
- Dawson, A.; Gibbs, A.R.; Pooley, F.D.; Griffiths, D.M.; Hoy, J. Malignant mesothelioma in women. Thorax 1993, 48, 269–274. [Google Scholar]
- Dodson, R.F.; O'Sullivan, M.; Brooks, D.R.; Hammar, S.P. Quantitative analysis of asbestos burden in women with mesothelioma. Amer. J. Ind. Med. 2003, 43, 188–195. [Google Scholar]
- Gibbs, A.R.; Jones, J.S.P.; Pooley, F.D.; Griffiths, D.M.; Wagner, J.C. Non-occupational malignant mesotheliomas. In Non-Occupational Exposure to Mineral Fibres; Bignon, J., Peto, J., Saracci, R., Eds.; International Agency for Research on Cancer: Lyon, France, 1989; pp. 219–228. [Google Scholar]
- Gibbs, A.R.; Griffiths, D.M.; Pooley, F.D.; Jones, J.S.P. Comparisons of fibre types and size distributions in lung tissues of paraoccupational and occupational cases of malignant mesothelioma. Br. J. Ind. Med. 1990, 47, 621–626. [Google Scholar]
- Huncharek, M.; Capotorto, J.V.; Muscat, J. Domestic asbestos exposure, lung fibre burden, and pleural mesothelioma in a housewife. Br. J. Ind. Med. 1989, 46, 354–355. [Google Scholar]
- Roggli, V.L.; Longo, W.E. Mineral fiber content of lung tissue in patients with environmental exposures: Household contacts vs. building occupants. Ann. N. Y. Acad. Sci. 1991, 643, 511–518. [Google Scholar]
- Roggli, V.L. Mineral fiber content of lung tissue in patients with malignant mesothelioma. In Malignant Mesothelioma; Henderson, D.W., Shilkin, K.B., Langlois, S.L., Witaker, D, Eds.; Hemisphere Publishing Corp.: New York, NY, USA, 1992; pp. 201–222. [Google Scholar]
- Roggli, V.L.; Sharma, A.; Butnor, K.J.; Sporn, T.; Vollmer, R.T. Malignant mesothelioma and occupational exposure to asbestos: A clinicopathological correlation of 1445 cases. Ultrastruct. Pathol. 2002, 26, 55–65. [Google Scholar]
- Sheehy, J.W.; Cooper, T.C.; O’Brien, D.M.; McGlothlin, J.D.; Froehlich, P.A. Control. of Asbestos Exposure During Brake Drum Service; U.S. National Institute for Occupational Safety and Health: Cincinnati, OH, USA, 1989.
- Roggli, V.L. Asbestos bodies and nonasbestos ferruginous bodies. In Pathology of Asbestos-associated Diseases, 2nd ed.; Oury, T.D., Sporn, T.A., Eds.; Springer-Verlag: New York, NY, USA, 2004; pp. 34–70. [Google Scholar]
- Camus, M.; Siemiatycki, J.; Meek, B. Nonoccupational exposure to chrysotile asbestos and the risk of lung cancer. N. Engl. J. Med. 1998, 338, 1565–1571. [Google Scholar] [CrossRef]
- American Thoracic Society (ATS). Diagnosis and initial management of nonmalignant diseases related to asbestos. Amer. J. Respir. Crit. Care Med. 2004, 170, 691–715. [Google Scholar]
- Paustenbach, D.J.; Richter, R.O.; Finley, B.L.; Sheehan, P.J. An evaluation of the historical exposures of mechanics to asbestos in brake dust. Appl. Occup. Environ. Hyg. 2003, 18, 786–804. [Google Scholar]
- Finley, B.L.; Richter, R.O.; Mowat, F.S.; Mlynarek, S.; Paustenbach, D.J.; Warmerdam, J.M.; Sheehan, P.J. Cumulative asbestos exposure for US automobile mechanics involved in brake repair (circa 1950s−2000). J. Expo. Sci. Enviro. Epidemiol. 2007, 17, 644–655. [Google Scholar]
- Agency for Toxic Substances and Disease Registry (ATSDR). Toxicological Profile for Asbestos; Agency for Toxic Substances and Disease Registry: Atlanta, GA, USA, 2001.
- Hessel, P.A.; Teta, M.J.; Goodman, M.; Lau, E. Mesothelioma among brake mechanics: An expanded analysis of a case-control study. Risk Anal. 2004, 24, 547–552. [Google Scholar]
© 2013 by the authors; licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution license (http://creativecommons.org/licenses/by/3.0/).