Article

Current Experiences and Practices of Surveilling and Managing Ebola Virus Disease Outbreaks in the Democratic Republic of Congo by Involving the Community in a “One Health” Approach


by
Dieudonné K. Mwamba
1,2,3,
Pierre Z. Akilimali
2,3,*,
Célestin Manianga
4,
Serge Kapanga
4,
Nadège K. Ngombe
5,6,
Jean Shonganye
3,
Karl B. Angendu
3,7,
Gregory Moullec
1 and
Christina Zarowsky
1
1
Department of Social and Preventive Medicine, School of Public Health, University of Montreal, Montreal, QC H3C 3J7, Canada
2
Kinshasa School of Public Health, University of Kinshasa, Kinshasa P.O. Box 11850, Democratic Republic of the Congo
3
Democratic Republic of Congo National Public Health Institute, Kinshasa P.O. Box 3243, Democratic Republic of the Congo
4
Department of Anthropology, University of Kinshasa, Kinshasa P.O. Box 0243, Democratic Republic of the Congo
5
Centre de Recherche en Nanotechnologies Appliquées aux Produits Naturels (CReNAPN), Department of Medicinal Chemistry and Pharmacognosy, Faculty of Pharmaceutical Sciences, University of Kinshasa, Kinshasa P.O. Box 212, Democratic Republic of the Congo
6
Centre d’Etudes des Substances Naturelles d’Origine Végétale (CESNOV), Faculty of Pharmaceutical Sciences, University of Kinshasa, Kinshasa P.O. Box 212, Democratic Republic of the Congo
7
Inserm U1094, IRD UMR270, CHU Limoges, EpiMaCT-Epidemiology of Chronic Diseases in Tropical Zone, Institute of Epidemiology and Tropical Neurology, OmegaHealth, University of Limoges, 87000 Limoges, France
*
Author to whom correspondence should be addressed.
Pandemics 2026, 1(1), 3; https://doi.org/10.3390/pandemics1010003
Submission received: 15 December 2025 / Revised: 2 February 2026 / Accepted: 26 February 2026 / Published: 6 March 2026

Abstract

This study examines the community integration and One Health strategies employed to combat Ebola virus disease in the Democratic Republic of Congo from 2007 to 2022. We synthesized 12 outbreak reports, conducted qualitative interviews with 36 managers, organized three focus groups, and adapted an analytical framework (MATCH) to evaluate three essential dimensions: the integration of the One Health approach, community involvement, and bottom-up approaches. This study evidences progressive improvement in all domains. The first outbreaks (2007–2009) were marked by moderate community engagement and a One Health approach that was largely limited to the human health sector, deemed suboptimal. The 10th outbreak represented an era of transformation, when the Incident Management System (IMS) was adopted to better manage the response to the virus. The latest outbreaks (13th to 15th) demonstrate an “optimal” implementation of the “One Health” approach through effective collaboration between those in charge of ensuring human, animal, and environmental health and that of the community. This study demonstrates that success is largely dependent on bottom-up initiatives in which local populations, their leaders (both traditional and religious), community liaisons, and specific groups (women and youth) are involved in the design and implementation of such measures. The inclusion of anthropologists and psychologists in addressing the psychosocial dimensions—fear, stigma, and distress—has been critical in ensuring the success of these initiatives and the degree to which the public trusts and accepts them. However, many issues still need to be addressed, including poor coordination among sectoral ministries and the partial implementation of IMS at the grassroots level. In summary, the authors of this study propose that these integrated and participatory models are sustainable and imperative to building the resilience of the Congolese health system to future outbreaks.

1. Introduction

Pandemics and disease outbreaks are increasingly prevalent worldwide, resulting in significant loss of life despite various preventive measures [1]. In Africa, the trajectory of these health emergencies underscores the necessity for health systems to adopt integrated, participatory approaches that prioritize community involvement in disease management and prevention. The “One Health” framework—recognizing the interconnectedness of human, animal, and environmental health—has emerged as a crucial strategy for enhancing surveillance and response to zoonotic crises such as Ebola virus disease (EVD) [2]. This collaborative, multisectoral, and transdisciplinary approach must be implemented at local, regional, national, and global levels to achieve optimal health outcomes [3].
The Democratic Republic of Congo (DRC) has confronted numerous public health emergencies, including the COVID-19 pandemic and multiple EVD outbreaks. Initially, these outbreaks were misdiagnosed as Salmonella infections or other viral hemorrhagic fevers, delaying appropriate responses [4]. Community resistance and unhealthy behaviors often exacerbate the spread of disease, complicating outbreak management efforts [5]. Community trust is vital for effective response strategies; however, engagement often lags, and affected populations may resist medical interventions due to inadequate involvement in the early stages of a crisis.
To address these challenges, the DRC healthcare system has focused on building community trust through risk communication and outreach initiatives, aiming to reduce disease transmission and swiftly control outbreaks. Recognizing this, the World Health Organization (WHO), the World Organisation for Animal Health, the Food and Agriculture Organization (FAO), and the United Nations Environment Programme advocate for a “One Health” approach that emphasizes local participation in all surveillance and response activities [6]. Effective community engagement strategies are essential; although top-down approaches may be implemented more quickly, they tend to be less effective than bottom-up strategies that empower local stakeholders and field actors [7].
This study aims to investigate the effectiveness of community engagement strategies in managing EVD outbreaks in the DRC, with a particular emphasis on the need for a longitudinal analysis of these strategies from 2007 to 2022. While previous studies have explored community engagement, they often focus on short-term interventions and lack a comprehensive understanding of how these strategies evolve over time. A longitudinal analysis is crucial for identifying patterns, successes, and challenges in community involvement, thereby providing a deeper understanding of its impact on outbreak management across different phases.
The primary research question guiding this study is, “How do community engagement strategies influence the response to EVD outbreaks, and what lessons can be drawn to enhance public health interventions for future viral outbreaks?” By integrating the “One Health” framework, this work contributes to existing knowledge by highlighting the critical role of community involvement in shaping public health responses, particularly in resource-limited contexts. Through case studies and community feedback analysis, we aim to provide evidence-based recommendations for improving outbreak management strategies, informing policy and practice at local, national, and international levels. Ultimately, this research seeks to bridge the gap between theoretical knowledge and practical application by demonstrating how effective community engagement can improve health outcomes during viral outbreaks. This study not only advances our understanding of EVD management but also offers valuable insights applicable to other emerging infectious diseases.

2. Materials and Methods

Through documentary and qualitative analysis, this study examines the modalities of implementing community engagement and the “One Health” approach in the management of Ebola outbreaks in the DRC.

2.1. Documentary Sources

We carried out an analysis of 12 formal documents on the management of the Ebola outbreak in the DRC from 2007 to 2022, that is, from the 4th to the 15th outbreaks [8,9,10,11,12,13,14]. These reports were produced by the Ministry of Public Health, the WHO, and partner organizations involved in the successive responses [15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45]. All of the official reports described the coordination measures, community interventions, results achieved, and recommendations made following each crisis. Documents were identified through systematic searches of official health organization websites, government publications, and academic databases, focusing on Ebola outbreaks in the DRC. Only documents published during the relevant outbreak periods were selected. Criteria for selection included the credibility of the issuer (e.g., the WHO, government health ministries, and international health organizations) and relevance to the research objectives (Table A1). Each document was appraised for methodological rigor, relevance, and credibility. This involved reviewing the publication processes of the organizations involved and ensuring that the documents were peer-reviewed or produced by recognized public health authorities.

2.2. Analytical Framework

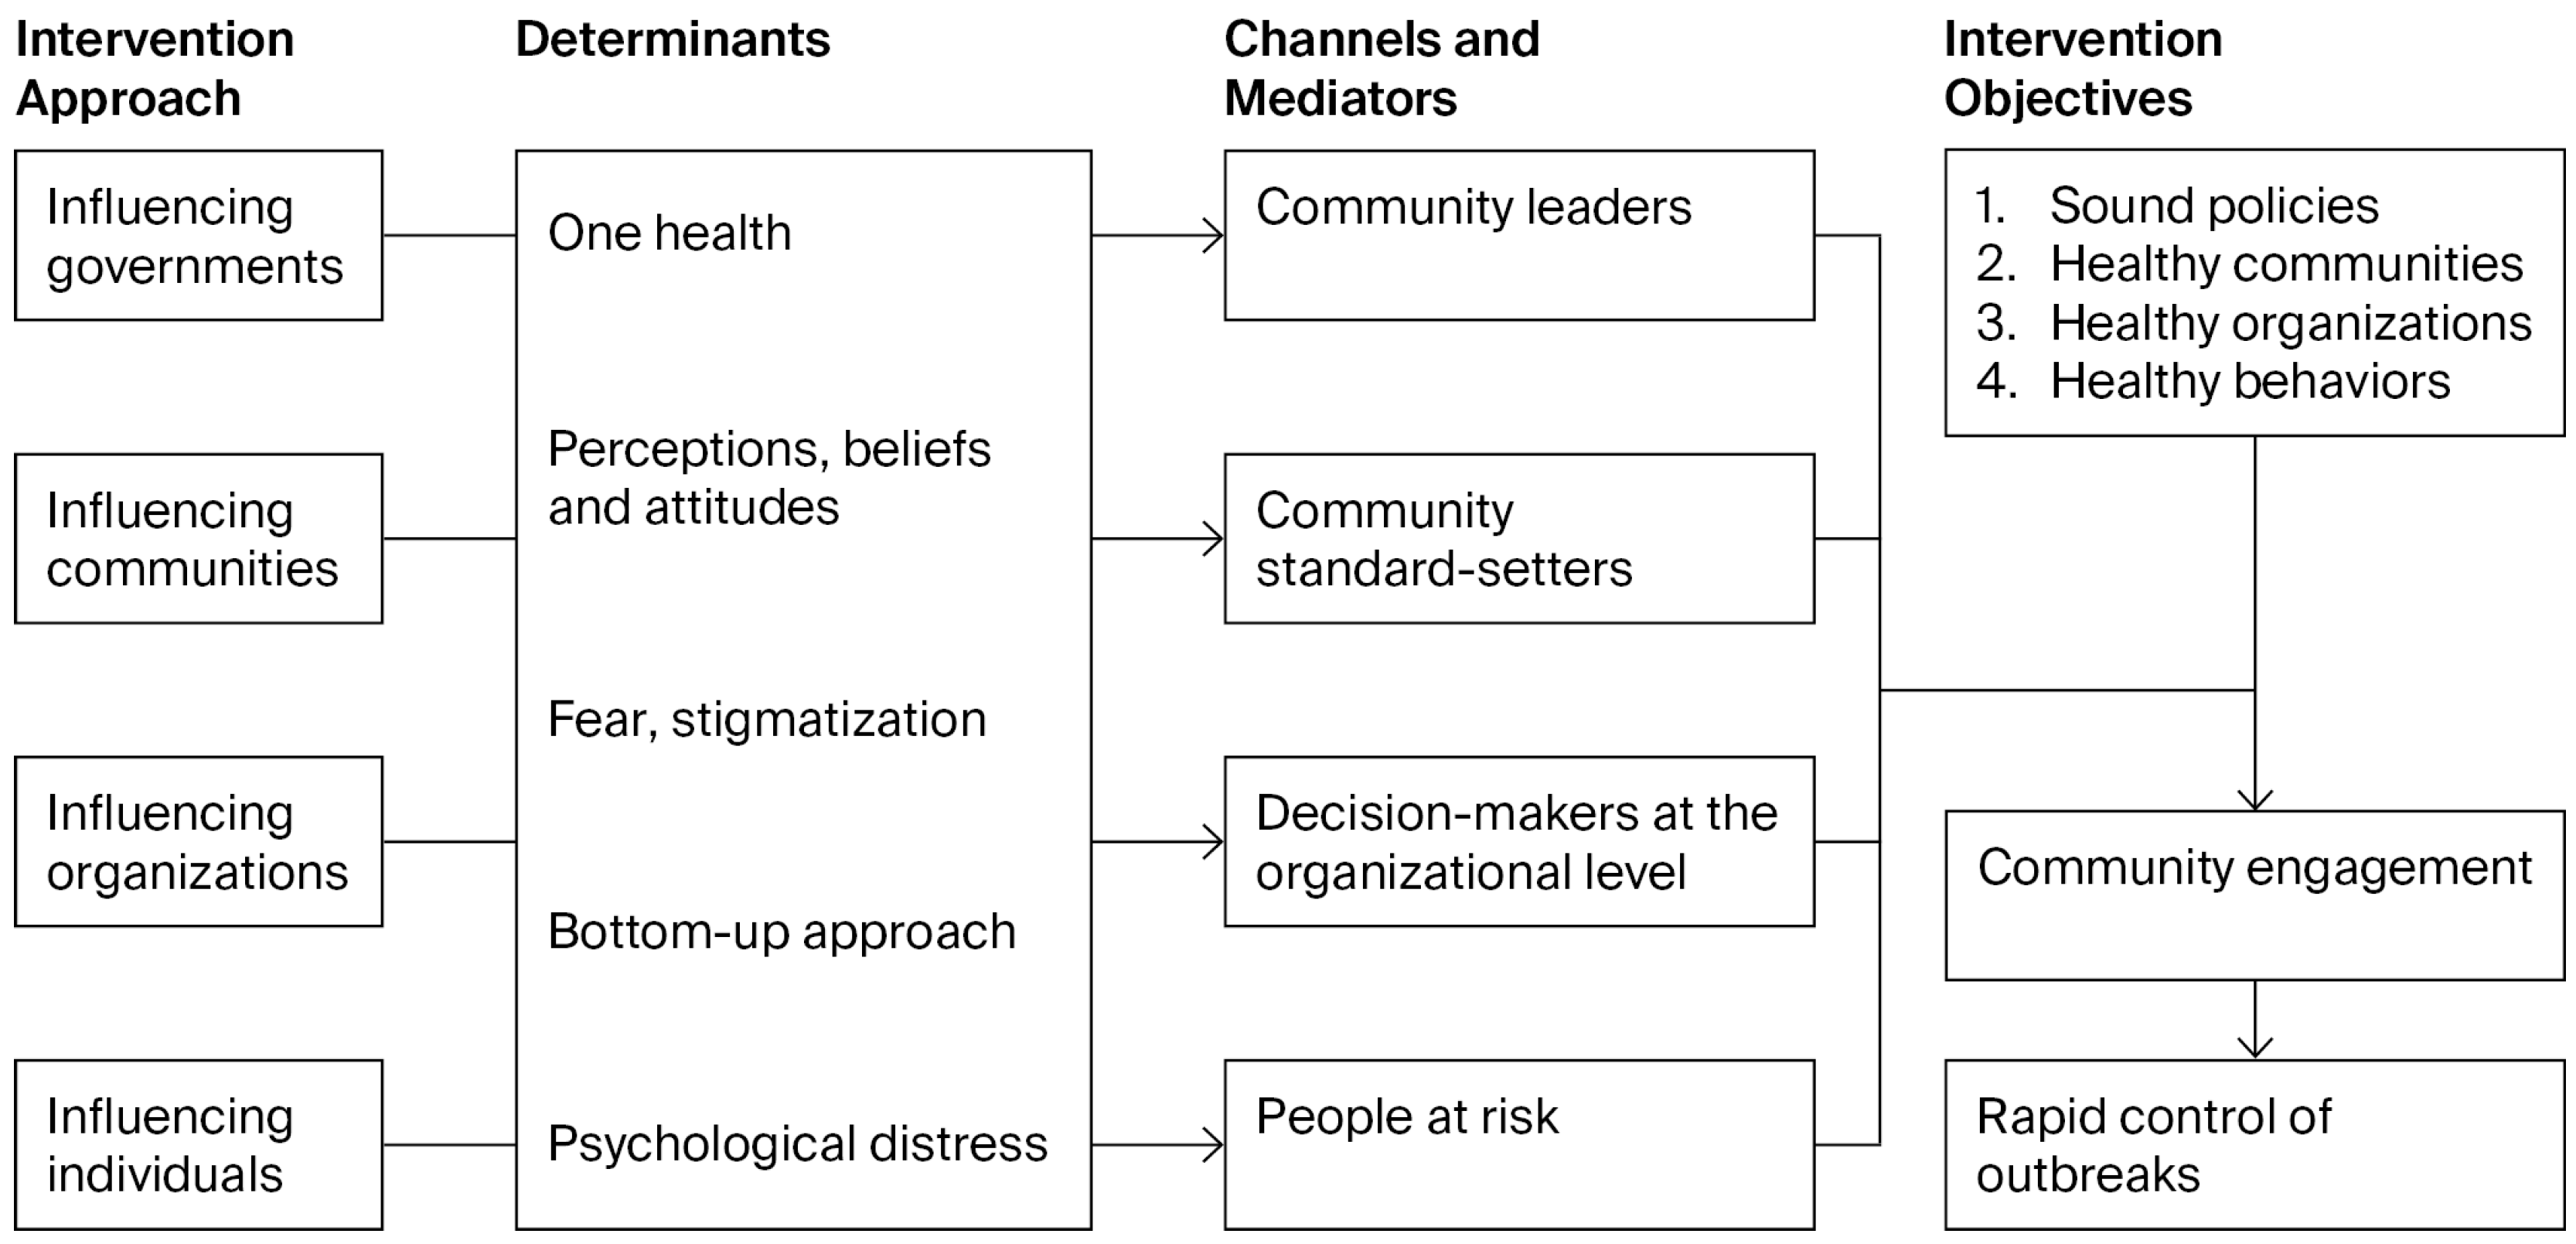
To gain an insight into the recent experiences and practices of surveilling and treating Ebola by involving the community in a “One Health” approach (Table 1), a literature review was conducted, using an adaptation of Simons’ (Appendix A: Table A2) [46,47] Multi-Level Approach to Community Health (MATCH) conceptual model as an intervention model [48]. This framework was adjusted to assess three key dimensions (Figure 1):
o
The integration of the “One Health” approach: Whether the human, animal, and environmental health sectors are integrated into the response or not.
o
Community involvement: The degree of participation of local communities in actions to prevent, monitor, and manage outbreaks.
o
Techniques applied from the bottom up: Community involvement in designing and implementing strategies.

The ratings were assigned using an adaptation of Simons’ MATCH framework, which involved a qualitative assessment of three key dimensions: One Health integration, community involvement, and bottom-up techniques for each Ebola epidemic. The analysis covered the 10th through 15th outbreaks, allowing for a chronological comparison, as detailed in Table 1. This comparison revealed a notable progression in community mobilization efforts, even in the presence of intersectoral weaknesses that affected overall response [47].
Community involvement or engagement refers to the active participation of local populations in health interventions, decision-making processes, and response strategies. In the context of Ebola outbreaks, community involvement in epidemic management is characterized by the active participation of local communities through volunteers, leaders, and health workers. It encompasses collaboration between health authorities and communities to foster trust, enhance communication, and empower local stakeholders in disease prevention and control efforts. Effective community engagement is characterized by transparency, mutual respect, and a genuine commitment to incorporating community perspectives into health initiatives. Their roles in surveillance, prevention, and response efforts enhance vaccine acceptance and diminish distrust during health crises.
The assessment of community involvement during the Ebola outbreaks utilized both qualitative and quantitative measures. Feedback mechanisms were established to understand community perceptions and pinpoint areas for improvement. Participation rates in health initiatives, such as vaccination campaigns, were monitored to gauge the effectiveness of engagement. The impact on health outcomes was evaluated by analyzing disease transmission rates and compliance with health measures, showing a positive correlation between community engagement and health outcomes. Surveys and interviews helped researchers grasp the perceived value of community involvement and its influence on health behaviors through IMS’s research pillar.
Table 1. Analytical framework.
No.Qualitative Indicators Drawn from the MATCH FrameworkObservation of the Evaluation of Indicators
1.One Health approach
  • Optimal: Three sectors (human health, animal health, and environmental health) work together in response. These three sectors also share valuable information and exhibit multisectoral cooperation.
  • Suboptimal *: Two sectors are involved in the response.
  • Not optimal **: Only one sector is involved in the response.
2.Community involvement/
engagement
  • Good involvement: The community actively collaborates with community health workers in response activities.
  • Moderate involvement: The community participates to a moderate degree.
  • Low involvement: The community does not participate or there is low community participation.
3.Bottom-up approach
  • Applied: The higher-level decision-makers include the community in coming up with ideas and in design and implementation committees.
  • Not applied: The higher-level decision-makers impose rules with no community involvement.
*: Two of the three following sectors: (human health, animal health, and environmental health; **: One of the three following sectors: (human health, animal health, and environmental health.
A qualitative analysis grid was developed based on these dimensions to methodically inspect each outbreak management report. Integration levels were coded according to qualitative parameters (optimal to suboptimal; good to low involvement; and applied to non-applied).
Figure 1. Adapted conceptual MATCH model.
Pandemics 01 00003 g001

2.3. Qualitative Data

In addition to analyzing the documents, we conducted a qualitative case study to explore community engagement during the Ebola epidemics that occurred from 2018 to 2020 in North Kivu Province, eastern Democratic Republic of Congo. We specifically selected two health zones, Goma and Butembo, due to their significantly high number of Ebola virus disease (EVD) cases during this period. The study was conducted between October and December 2020, using the COREQ checklist for the collection and reporting of qualitative data. A total of 36 key informants were interviewed, comprising young people, women, community leaders, health staff, and traditional healers, all chosen for their relevant experience in managing EVD. Additionally, we organized three focus group discussions, each consisting of 6 to 10 participants (n = 28). These mixed-gender focus groups included young individuals from associations involved in response, arts and crafts students, and Ebola survivors, representing various professions. In total, 64 participants contributed to the study. All interviews were conducted in French or Swahili by a socio-anthropologist with extensive qualitative research experience, assisted by an interpreter. Audio recordings were captured using a dictaphone, and detailed notes, including observations of non-verbal expressions, were taken during each interview, which lasted an average of 50 min. The French audio recordings were transcribed, while the Swahili recordings were translated into French during transcription by two bilingual members of the research team. The transcripts were reviewed multiple times alongside the recordings to ensure the accuracy of both transcription and translation and to familiarize the team with the content.
To enrich our data on community perspectives, we conducted interviews with three focus groups, each with 28 participants. The criteria for being included in the research, the method of data collection, and the sociodemographic profiles of the interviewees are summarized in Table 2 and discussed in a separate article [1]. Given the significance of psychological distress, fear, and stigma in determining the effectiveness of community engagement [49], these factors were also assessed to gauge the extent to which they should be considered when establishing practical approaches to managing health emergencies such as Ebola outbreaks. The integration of qualitative data into our coding framework was essential in deriving our findings.
Participants were selected using a purposive sampling strategy to ensure representation from key sectors involved in outbreak management, including public health officials, community leaders, and healthcare workers. This approach allowed for the inclusion of diverse perspectives relevant to the One Health framework. Data collection involved semi-structured interviews conducted by trained researchers fluent in the local language. Each interview lasted approximately 45 to 60 min, allowing for in-depth exploration of participants’ experiences and perspectives. All interviews were audio-recorded with participants’ consent and subsequently transcribed for analysis.
The research team used Atlas.ti 22 for data management, coding, and analysis. The study team initially examined all interview transcripts in French and produced memos for each transcript, documenting significant ideas, enquiries, or pertinent observations on the transcript and/or participant. A trio of researchers subsequently created a unified codebook via open coding methods—specifically, extracting candidate codes from three transcripts, followed by deliberations among the study team to develop a preliminary codebook. The coding methodology adhered to a framework established by Strauss and Corbin (1990) to delineate terminology and definitions for coding subcategories (e.g., phenomenon, causal circumstances, tactics, consequences, context, and intervention conditions pertaining to abortion information seeking) [50]. Subsequently, we performed axial coding, which involved creating a coding framework and a definitive codebook for the remaining transcripts. Upon establishment of the final codebook, each researcher coded about 10 transcripts, which another team member subsequently reviewed to ensure coder uniformity and code completeness. Memos were documented during the coding phase to investigate any developing research issues or concepts. Coders documented any discrepancies in participants’ narratives of their abortion experiences to facilitate the examination of divergent aspects of care.
Upon finalizing the coding, we performed an inductive theme analysis and generated a coding report in Atlas.ti, exporting a comprehensive list of coded quotations along with their corresponding codes for our analysis. Subsequently, we constructed a matrix to delineate and characterize the principal themes and subthemes. The matrix had pertinent quotations exemplifying each topic or subtheme, along with participant characteristics for each quotation. Inductive thematic saturation methods were employed to attain saturation of themes and sub-themes. During each study team meeting, members concentrated on detecting newly emergent codes and themes rather than assessing the completeness of existing ones, continuing this process until no new codes or themes were identified [51]. Rigor was upheld during the research process via weekly team meetings to address issues, interpret quotes, and explore conceptual connections among important themes, ultimately contributing to the development of the final thematic matrix.

2.4. Ethical Considerations

The protocol was approved by the Ethics Committee of the University of Montreal and the University of Kinshasa. Informed consent was obtained from each participant after explaining the study objectives and their right to refuse or withdraw without consequences. Confidentiality was maintained by anonymizing data and storing it securely on a protected computer accessible only to the research team.

3. Results

3.1. Evaluation of Indicators from the 4th to the 15th Ebola Outbreak in the DRC

The results of the documentary analysis of reports from the 4th to the 15th Ebola outbreaks in the DRC are presented in Table 2. We also describe the models of Ebola outbreak management before and after 2017, followed by an analysis of the implementation of the One Health approach and the significance of fear and stigma as key elements in the effectiveness of community involvement under the “bottom-up” model.

3.2. The Response to Ebola Virus Disease: An Overview

The response to EVD outbreaks in the DRC is multisectoral and community-based, aimed at controlling and limiting their spread. The strategies employed include strengthened epidemiological surveillance capacities, rigorous contact tracing, coordination between national and international health authorities, and the promotion of social mobilization and local community engagement. It is important to involve community leaders, women’s groups, and other influential local groups to promote adherence to prevention measures and health interventions, particularly in high-risk areas, given the weak security in some contexts.
A “good” or “optimal” response to an outbreak such as EVD in the DRC is defined by several essential criteria (as articulated in national and international strategic response plans): early detection and enhanced surveillance, multisectoral and logistical coordination, strong community engagement, targeted vaccination, adaptability and operational flexibility, and integration of survivor care. An “optimal” Ebola response is based on guidelines and frameworks established by the WHO and by national strategic response plans. Specifically, we reference the WHO’s “Ebola Response Roadmap” and the national response plans of the DRC to support our definition [52].

3.3. Transformation of Intervention Models in the Management of Ebola

(A)
Outbreak management framework up to 2017
From the third outbreak in Kikwit in 1995 until 2017, the management of outbreaks, including EVD, was based on a tripartite structure comprising a National Coordination Committee, a Provincial Coordination Committee, and an International Scientific and Technical Coordination Committee (ICST) at the epicenter level [53]. At the national level, the National Coordination Committee, under the responsibility of the national Minister of Health, ensures communication between stakeholders and coordinates interventions to guarantee a coherent and effective response. This committee is composed of seven subcommittees: care, surveillance, laboratory and research, water, hygiene and sanitation, social communication, logistics, and psychosocial support.
At the intermediate level, the Provincial Ministry of Health, under the Provincial Minister’s coordination, chairs the Provincial Coordination Committee. This committee is responsible for the smooth implementation of all activities related to the EVD outbreak response. It coordinates interventions at the provincial level and is also subdivided into seven subcommittees.
At the epicenter of outbreaks, there is a coordinator for the CICST, which is also subdivided into seven subcommittees. This model, although organized, struggled to empower local actors in decision-making, with power limited to experts at the central level, as demonstrated by the content of the epidemiological surveillance subcommittee during the outbreaks from 2007 to 2017 (Table 3) [12].
(B)
New WHO outbreak management model adopted in DRC: Incident Management System (IMS)
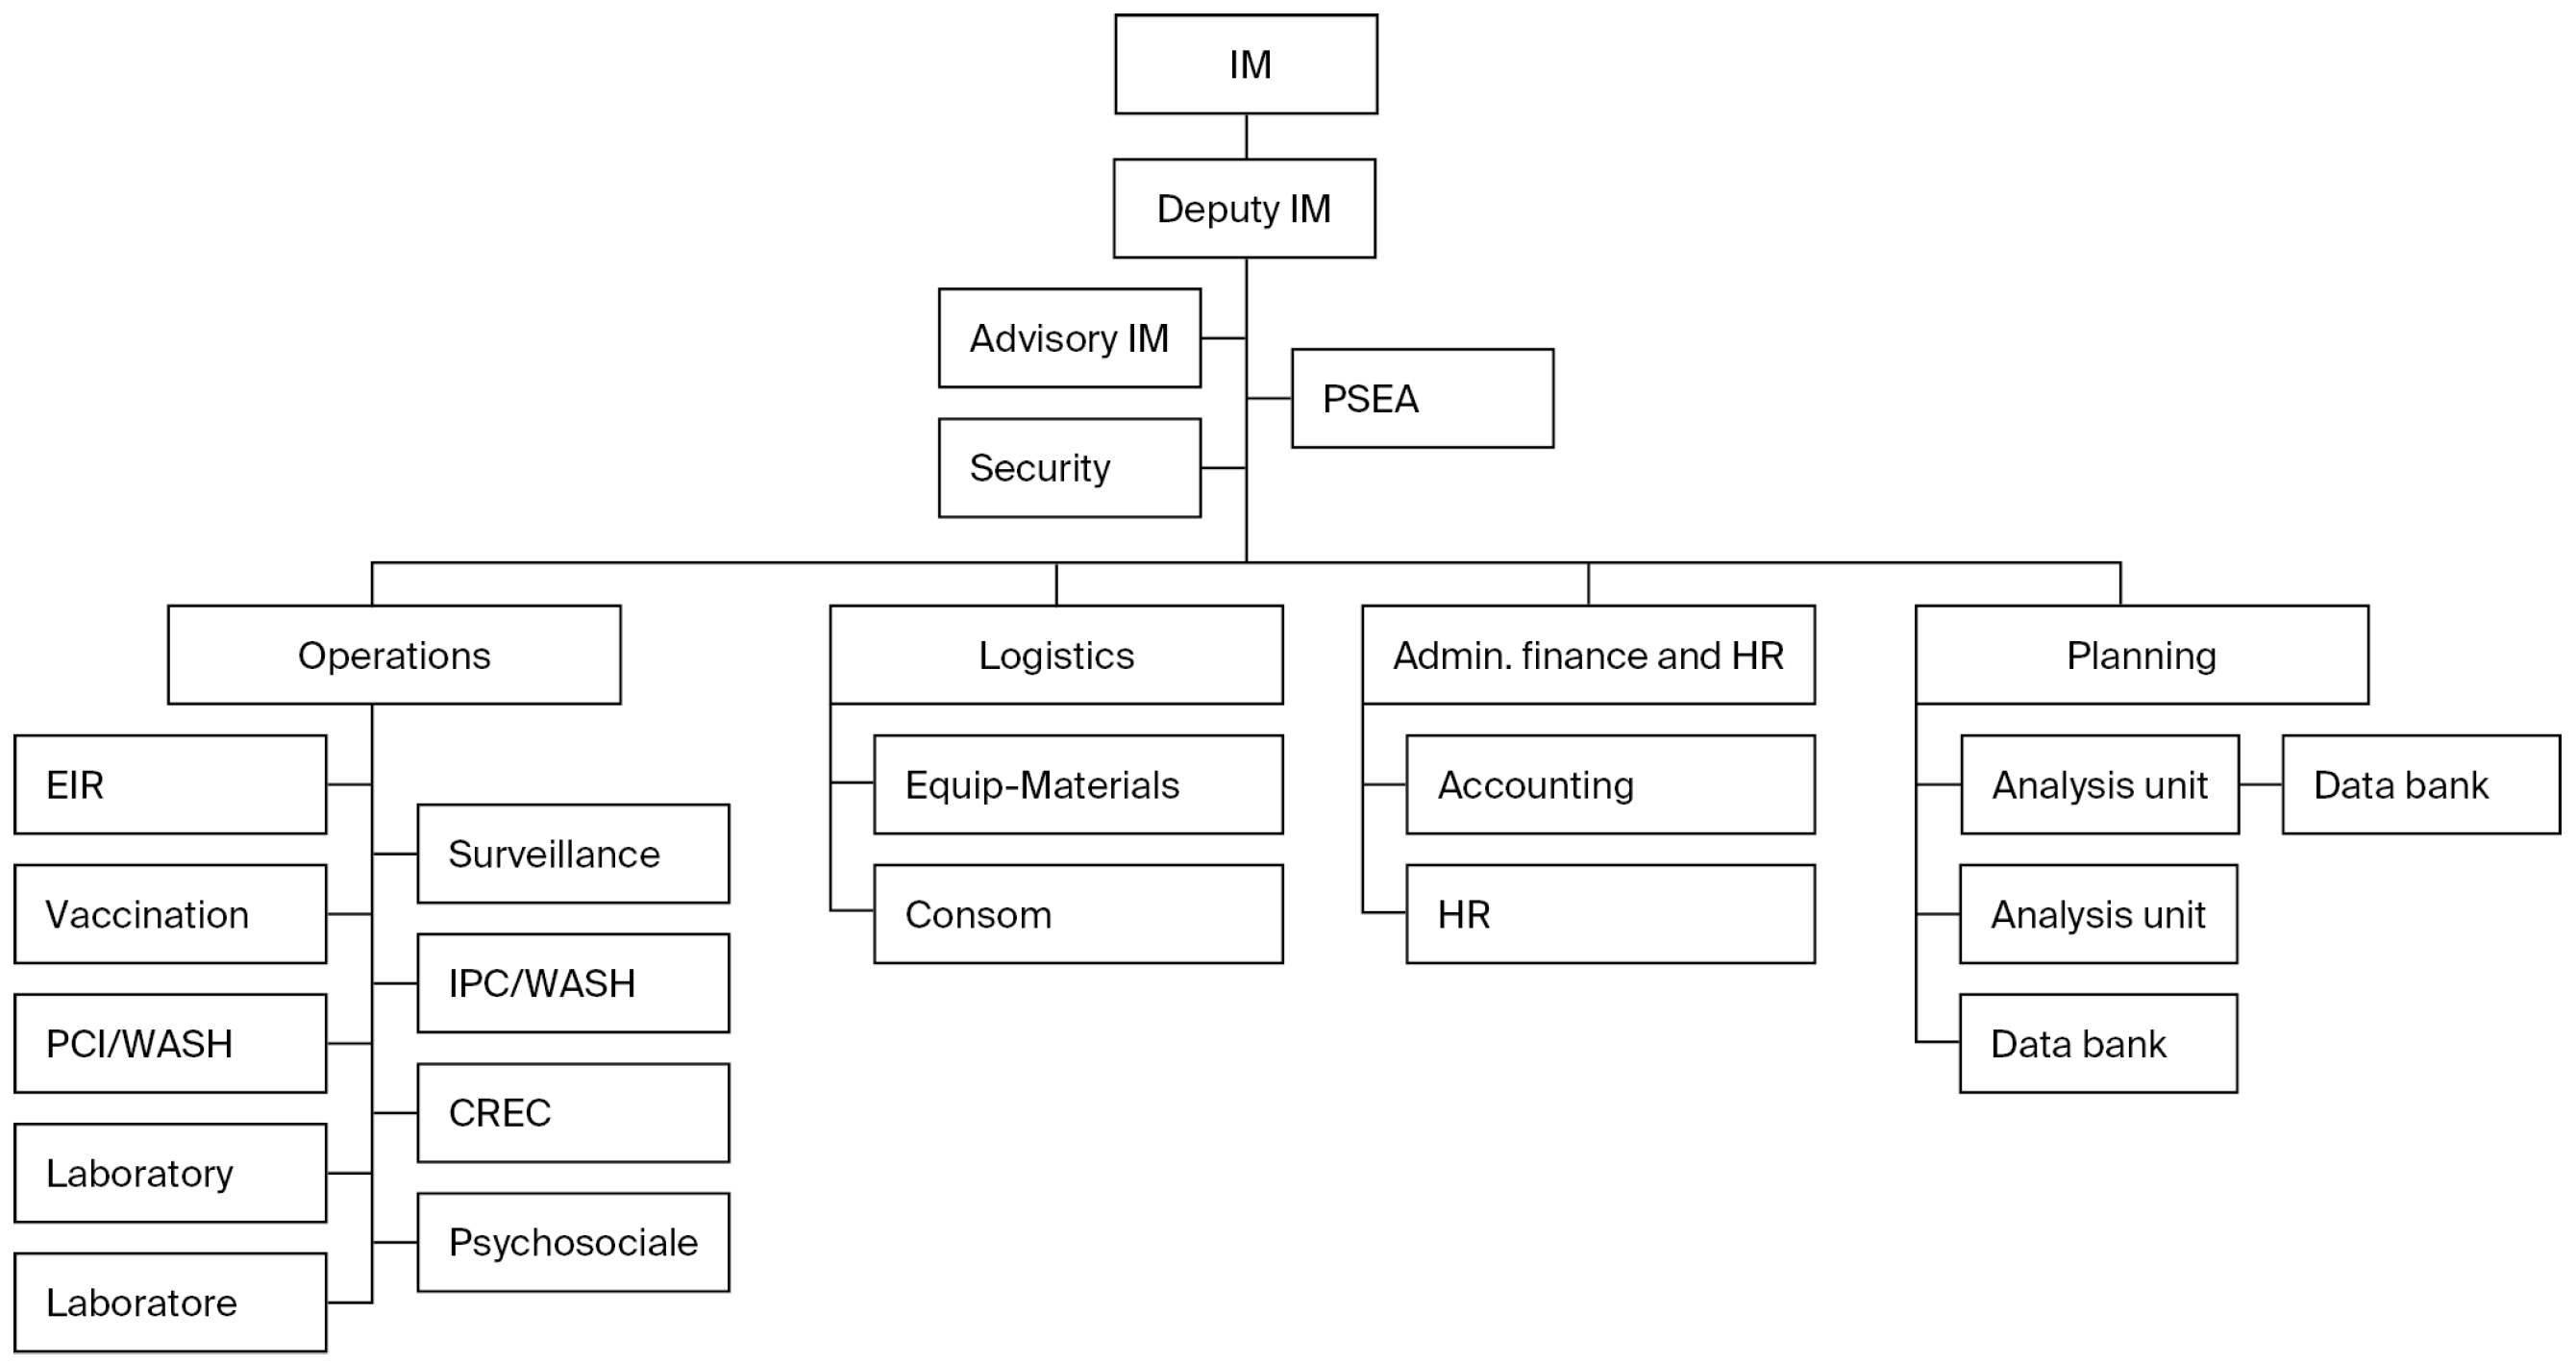
The 10th outbreak (the longest, lasting nearly 18 months) was considered a watershed, as the DRC adopted the IMS (Figure 2) as recommended by the WHO [54]. This model states that, in the case of an event (e.g., outbreak), an Incident Manager (IM) should be appointed by the relevant authorities and that four sectors should be established (operations, logistics, administration and finance, and planning). This led to a more standardized and responsive approach now used to manage other health emergencies, such as MPOX outbreaks. However, effectively implementing this system at the local level remains challenging, particularly in the most remote health zones. Many questionnaire respondents highlighted the need for stronger local integration to enable operation of the Integrated Health System (IHS) in low-resource settings.

3.4. Evolution of Community Integration

The Ebola response in the DRC has shifted from a biomedicine-only framework to a successful community-integration approach that involves the local population. Initially, mistrust and resistance from within the community hindered public acceptance of measures to improve health (such as vaccination and medical interventions). However, public perception has shifted recently due to systematic inclusivity, including the engagement of community leaders, women’s groups, and other influential groups. Community feedback mechanisms are in place to permit local adaptation of interventions to cultural and social customs, making community ownership of interventions more credible. In addition, policy responses to such actions have been strategically designed to include both psychosocial and humanitarian elements, which is key to sustaining community engagement moving forward by providing better living conditions and addressing community issues.
This evolution has allowed the community to play an active role instead of being a passive recipient, making the public active partners in the response process. Community health workers in Beni and other disease hotspots are a key component in early detection, awareness-raising, and psychosocial support, thereby improving the success of the fight against outbreaks. The trends of community engagement during Ebola outbreaks (in the DRC), which have evolved over time, are as follows (Table A3):
Early outbreaks (2007–2009): First-wave community engagement was, in general, “moderate”, and the adopted approach was “suboptimal”. There were efforts to engage the community, but they were insufficient to optimize the effectiveness of the health intervention.
Intermediate outbreaks (2012–2018): After the sixth outbreak (2012), there was a lot of improvement in community engagement, with multiple events showing “good involvement.” [10,12]. This is often associated with the better implementation of public health interventions.
Recent outbreaks (2018–2022): In a case study of recent outbreaks, namely those between 2018 and 2022, community engagement was reported to be “optimal” in some instances, suggesting enhanced community participation and learning [14]. The impacts of the actions taken were also found to be much stronger, leading to higher community engagement and stronger community support in the response process.

3.5. Application/Implementation of the “One Health” Approach

Hunting and forestry are major sources of income in many rural areas. As a result, selling game in local markets is an essential activity; however, it contributes to the spread of EVD within the community [55]. In response to repeated outbreaks, several tactics have been used to fight the disease, such as working with local leaders to encourage adherence to prevention and treatment measures, as well as forming local volunteer organizations tasked with raising awareness of the disease and tracing contacts (report on the 12th outbreak) [56]. The perceptions of the interviewees indicated that community mobilization is as important as biomedical devices in ensuring the effectiveness of response activities [1].
The decision-makers interviewed in this study recognized the importance of the “One Health” approach in countering zoonotic diseases, stating that this approach integrates the efforts of human, animal, and environmental health professionals. The Ministry of Health officials interviewed cited some strengths of intersectoral collaboration, specifically with regard to case detection, risk communication, and field coordination. However, this approach does still have substantial governance-related weaknesses. A number of respondents complained about the relatively slow reactions of certain partner ministries, notably the Environment and the Agriculture and Livestock ministries, which, the evidence suggests, did not take timely action. In addition, a key respondent at the Ministry of Agriculture and Livestock stated that “The lethargy in the functioning of services in other ministries (Environment, Fisheries and Livestock, and Agriculture), is a formidable threat to public health. It undermines the implementation of preventive measures, disease detection, effective treatment, and epidemiological monitoring, both for individuals and animals (livestock). This has a bottleneck to the real-life execution of the One Health approach in our country.”
Intersectoral epidemiological surveillance is thus complex and represents an issue at the national level. Some obstacles include operational coordination, information sharing, and the absence of sustainable mechanisms for consultation between sectors. As stated by another respondent from the Ministry of Environment and Sustainable Development, “The effectiveness of epidemiological surveillance depends to a great extent on the readiness of various state agencies and institutions to work together on the joint pursuit of common goals in each specific local context, and on the concrete application of the One Health approach.” Here are some concrete examples of how the One Health approach was optimally implemented during the 13th to 15th outbreaks [57,58,59,60]: (1) Multisectoral teams used sequencing to quickly determine if the virus originated from an animal reservoir (zoonotic spillover) or a human persistent infection, which informed different response strategies. (2) In the 13th outbreak (Beni), veterinary teams conducted ecological investigations of local bat and primate populations alongside human contact tracing. (3) Agencies such as UNICEF integrated WASH (Water, Sanitation, and Hygiene) with environmental monitoring to reduce the risk of virus persistence in shared water or soil sources. (4) The Ervebo vaccine was deployed within days of the index case in the 14th and 15th outbreaks, a speed attributed to the pre-coordinated One Health infrastructure. (5) The 13th to 15th outbreaks saw “optimal” implementation where animal health officers and human health workers shared data in real time to track potential zoonotic triggers.

3.6. Community Involvement and Addressing Fear and Stigmatization

During the Ebola outbreaks in the DRC, community involvement varied and faced significant challenges, including security issues due to armed conflict, political mistrust between communities and health authorities, and perceptions of top-down approaches to health responses. Despite these barriers, some communities showed resilience and engaged proactively when they recognized tangible benefits from their participation.
The outcomes of the reports and interviews confirm the slow progression of community involvement in Ebola management in the DRC. Nevertheless, this development has led to heightened engagement of public health community partners in sharing information, monitoring disease, and working together with other sectors, and even sub-sectors, to promote health, particularly in affected health zones. The One Health approach in the DRC emphasizes collaborative efforts among multiple sectors—human, animal, and environmental health—to tackle health challenges. Key human health actors include the Ministry of Public Health, the National Institute of Biomedical Research (INRB), the WHO, Médecins Sans Frontières (MSF), and Ebola experts. The animal health sector involves the Ministry of Agriculture and Livestock, the Ministry of Fisheries, the Food and Agriculture Organization (FAO), and the Office of the Veterinary Services (OMSA). The environmental sector comprises the Ministry of Environment, the Directorate General for Nature Conservation, and wildlife experts. These institutions work together to foster a comprehensive understanding of health, acknowledging the interconnections between human, animal, and environmental factors. In the One Health approach, “working together” signifies collaboration among the human, animal, and environmental health sectors to enhance health outcomes. This collaboration includes joint planning and interdisciplinary teams that utilize each sector’s expertise. “Data sharing” is critical for exchanging health information, improving situational awareness, and making informed decisions. Optimal integration is indicated by formal communication channels, case studies of successful interventions, and metrics of improved health outcomes. Additionally, joint training programs and shared databases demonstrate effective integration across these sectors, fostering a resilient One Health framework for enhanced preparedness and response to health crises. In fact, several practices established in this context have been mentioned in the 13th Ebola Report in the province of North Kivu/Beni. Campaigns to mobilize youth and women and increase awareness allowed information to be distributed to many populations [61]. Good practices were promoted regarding animal health and the environment, including the cessation of hunting, bushmeat consumption, and game collection, as well as the monitoring of parks and domestic animals. Respect for local cultural norms, for instance, through the provision of respectful and safe burial practices, also contributed to reducing social hostilities. This demonstrates that all levels of society worked together to achieve an efficient collective response [62].
Teams led by anthropologists and psychologists helped to “demystify” the disease and minimize fear and stigma surrounding ill and sick people or survivors, helping them to reintegrate into the community [63].
In addition, feedback loops have enabled interventions to be adjusted to accommodate the needs of populations. However, response success has been largely attributed to the provision of psychosocial and material support to affected families in certain settings, such as in Likati. A key respondent from the Ministry of Public Health stated, “It is hard to address this rigorously and successfully without community involvement”. Community involvement enables the whole community to be integrated into plans to curb the spread of the virus; thus, community and religious leaders, as well as traditional healers, have provided psychological and material support to families affected by Ebola.
However, tensions have also arisen, especially in places where engagement mechanisms are not deeply rooted in the local environment, as illustrated by the report on the 11th Ebola outbreak in Equateur/Mbandaka Province [13]. The use of external community relays (that is, relays not from the affected regions) has at times weakened the response, and in some instances has led to protests, strikes, and even killings, thereby increasing the risk of outbreaks returning. Based on the analysis of the 11th to 15th reports, local governments play an important role as donors, with the revitalization of community outreach units and the payment of local liaisons being crucial for restoring trust and improving the effectiveness of interventions [13,14,55,61]. This is demonstrated by the 10th outbreak in Butembo, North Kivu, in which a series of mediations between response actors and community leaders reduced tensions and allowed cooperation to recover [64].
In addition, while our analysis validates that the One Health initiative is gaining traction in the DRC, it does not provide much clarity as to the roles of the health actors involved. Despite growing representation of the human, animal, and environmental health sectors, collaboration is frequently hindered by ambiguous governance and leadership constraints. This results in on-the-ground frustration, despite the fact that well-organized multisectoral teams are widely acknowledged to be capable of monitoring and controlling outbreaks. Finally, findings from the reports and interviews indicate that information on community concerns (including the need to work with community members to change their perceptions) has increasingly been integrated across successive outbreaks to enhance community engagement. These advances are related not only to systematic communication channels but also to institutions’ willingness to listen to communities and adapt their strategies to their knowledge, ways of working, and local dynamics.

3.7. Bottom-Up Approach to Community Engagement Within the Framework of the “One Health” Strategy

The bottom-up approach naturally leads to better integration of communities into the “One Health” strategy, as it increases community involvement in multisectoral and systemic decision-making and health-related actions. According to Dieudonné K. Mwamba et al. (2024), such local mobilization is key to managing health emergencies using a “One Health” approach (integrating human, animal, and environmental health) [1]. The WHO also adopts an enabling role in the participatory approach to improve the implementation of this global framework, as it localizes interventions and encourages the intersectoral collaborative process [6]. Additionally, the University of Montreal’s One Health initiative fosters collaboration through co-construction, inclusion, and reciprocity, with a focus on the essential role of communities in the success of these actions.
The One Health approach is based, among other things, on the logic of multisectoral collaboration. However, its successful application also depends on a bottom-up form of execution; this means that initiatives must be established by community actors so that lessons and knowledge can be drawn from communities and local practices. The bottom-up approach was not adopted in the early outbreaks, as shown by management reports. About half of the studies examined were interventions implemented in a top-down manner, with little to no community participation in the design or adjustment of strategies. Only in recent outbreaks have remarkable advances been made, with increased community engagement in the development and on-the-ground implementation of activities.
This transition to a has highlighted the central role of certain local actors in disease response [7,65]. The practices documented are as follows (Table A4):
  • Participation of traditional and religious authorities: These individuals were the pivotal factor in the adoption of Ebola prevention and management interventions.
  • Mobilization of youth and women’s groups: As active participants in programs established to spread awareness of Ebola, these groups have engaged a wide range of populations and extended the reach of community discourse.

4. Discussion

The findings underscore the critical importance of community engagement in managing EVD outbreaks and have significant implications for public health policy and practice. The results indicate that when communities are actively involved in outbreak response efforts, not only do health outcomes improve, but also the overall resilience of health systems is enhanced. This examination of the 12 EVD outbreaks in DRC between 2007 and 2022 demonstrates slow development of coordination models and community engagement mechanisms. Until the ninth outbreak, the country had largely depended on a tripartite structure, including national coordination at the central level supported by the national commission structure, provincial coordination, and an international scientific committee at the center. This model was effective and enabled early control of EVD health crises within a reasonable time frame of around three to four months. Peripheral health workers, the first to be affected by the health crisis, were left without sufficient power to manage the outbreak [12]. Consequently, response leadership rested exclusively with authorities at the center of government—the coordinator of the International Scientific and Technical Coordination Committee—and this might have weakened internal control over response measures at the health zone level.
Since the 10th outbreak, following the WHO’s recommendations, the DRC has adopted the IMS model of outbreak management [54]. This approach, inspired by the military’s crisis management model, involves appointing an Incident Manager with support from operational leaders across four areas: operations, planning, administration, and finance and logistics. This model has already been implemented within the Emergency Operations Center of the National Institute of Public Health, an organization established for preparing and addressing health emergencies and outbreaks; it is a common approach to outbreak management because it does not create ad hoc structures that interfere with the normal activity of already-existing structures and that are therefore ineffective for reinforcing resilience against recurring health crises, such as in the DRC.
The bottom-up approach to community involvement, combined with the “One Health” approach, is being adopted to solve the Mpox outbreak in the DRC, which was identified as the global epicenter for this disease for 2024–2025. Official reports by the DRC Ministry of Health, the WHO, and the National Public Health Institute’s in-country teams have confirmed its use for Mpox outbreak surveillance, prevention, and response. However, its involvement of the local community is insufficient. Within numerous health zones, public health officials face a range of emergencies without access to integrated coordination tools, which hampers their ability to respond in a timely, coordinated manner. Moreover, recent experiences and practices highlight the importance of well-coordinated community partnerships in preventing the spread of outbreaks, especially EVD [48]. The 10th Ebola outbreak (2018–2020) in the eastern Democratic Republic of Congo exemplifies the significant challenges posed by external factors that exacerbated its severity. This outbreak was uniquely characterized by a confluence of active armed conflict, entrenched political mistrust, and a response strategy perceived by local communities as militarized and top-down. Despite the stated goal of community involvement, the actual implementation was severely restricted by security threats and a public health approach that prioritized enforcement over collaboration. The presence of armed groups such as the Allied Democratic Forces created “red zones” that restricted health workers’ access, necessitating armed escorts and complicating efforts to engage with affected populations. This “securitization” of the response often incited fear and resentment, leading to community pushbacks against health interventions [40,58]. Ultimately, while the IMS framework included plans for community engagement, the unprecedented security crisis rendered these efforts ineffective. The outbreak’s severity was not merely a result of flaws in the response strategy, but rather a reflection of a broader environmental context marked by conflict, urban density, and pervasive misinformation, which undermined the potential benefits of community involvement and bottom-up approaches.
However, obstacles remain, including fear, stigma, and mental and emotional pain, which can affect the public’s willingness to collaborate, despite the advancement of community interventions and the widespread adoption of the One Health approach [1]. The need to include a strong psychosocial dimension in the management of outbreaks is not confined to medical or logistical issues. In this context, the “One Health” approach, while increasingly embedded in national strategies, is not yet functioning practically on the ground [2]. The effectiveness of the “One Health” response requires the participation and engagement of communities through bottom-up strategies, where action is initiated from the bottom up and takes place across all parts of the community, as well as the provision of policy support by local authorities—both provincial and national. Despite achieved advances in community integration, the interview respondents noted that the bottom-up approach alone does not fully address these issues when a multisectoral consultative framework and other measures are in place. This includes calling on all members of the community to participate in public health responses to outbreaks and other public health emergencies. Structured collaboration is essential for supplementing and strengthening skills related to human, animal, and environmental health. It involves stakeholders from various sectors, such as local civil society, farmer and livestock breeder organizations, and agricultural associations.
Community- and event-based surveillance to quickly identify Ebola cases within a given area requires community health workers to improve their knowledge, thereby helping minimize unreported cases and maximize outbreak tracking effectiveness. A further dimension that has been investigated is risk communication and the creation of more local community relays. According to Ryan et al. [66], trust between health authorities and communities is crucial during Ebola outbreaks, and communication strategies that account for local fears and beliefs are helpful. If messages are adapted to the local culture, they create greater awareness of the dangers and promote precautionary action. In addition, Frimpong et al. argue that mobilizing local resources to prevent outbreaks is of paramount importance [67].
The participation of community leaders and local Non-Governmental Organizations (NGOs) has also led to the establishment of networks that support disease surveillance and management in the region. Because conventional treatment and isolation methods are applied during outbreaks, they are subject to more appropriate localization. Regarding the One Health working environment, we need to encourage practical collaborations between all actors, from local organizations to research centers, anthropologists, sociologists, government representatives, and international organizations, and establish platforms that facilitate such collaborations to enable the sharing of information and practices that will support One Health [65]. Donors and financiers will undoubtedly play an important role in advancing One Health approaches when setting development priorities, making policy decisions, and allocating resources. Several different factors and sectors need to come together to accommodate the complexity of EVD outbreaks in the context of people and animals and the widespread ecological degradation caused by EVD in the region. A multisectoral and multidisciplinary approach is the only way to address this challenge, taking into account the participation of institutions and the community, all with different missions, priorities, funding, levels, training, and outlooks [68].
Implications for public health policy emphasize the importance of community engagement, tailored communication strategies, and the integration of a One Health approach. Community engagement during EVD outbreaks provides valuable insights that can enhance future outbreak responses. Evidence suggests that public health policies should prioritize community involvement in outbreak response, promoting trust and relationships between health authorities and communities to enhance cooperation during health crises. Developing communication strategies that are culturally relevant and actionable is crucial; public health messages must align with local beliefs and practices, supported by training for community health workers in effective communication. Additionally, incorporating the One Health approach—recognizing the interconnectedness of human, animal, and environmental health—into public health strategies can help mitigate factors contributing to viral outbreaks, including environmental changes and zoonotic transmission. Data-driven decision-making can lead to tailored interventions, improving acceptance and effectiveness. Empowering communities builds health system resilience, ensuring sustained health practices beyond outbreaks. Additionally, establishing feedback mechanisms encourages continuous dialog, allowing public health agencies to adapt strategies based on community experiences and challenges.
In this study, interpretations are robustly supported by a comprehensive analysis of documentary sources and qualitative data derived from interviews with key stakeholders, including health managers and community members. The findings align with the existing literature, which emphasizes the importance of community engagement and the One Health approach in managing Ebola outbreaks. However, limitations such as potential biases in qualitative interviews and the reliance on retrospective data may affect the generalizability of the conclusions. For several outbreaks, our analysis relied on a single source of information without incorporating independent or external sources to corroborate the official reports. This limitation may impact on the comprehensiveness and reliability of our findings. Future research should consider integrating multiple perspectives and diverse data sources to strengthen the robustness of the analysis. Additionally, alternative explanations for the observed outcomes could include socio-political dynamics and environmental factors not fully captured in the study. The scoring process, while guided by predefined criteria, is subject to inherent limitations stemming from its reliance on qualitative assessments by a single researcher, which may introduce bias and compromise the reliability of the ratings. We acknowledge that the dynamics of armed conflict in North Kivu may differ from those in other regions of the DRC, and we have framed our claims accordingly. Despite these limitations, the practical implications of this research are significant; it underscores the need to integrate community perspectives into health interventions to enhance trust and cooperation, particularly in conflict-affected areas. These insights can inform future public health strategies and policies, emphasizing a collaborative approach to disease management that considers local contexts and fosters community ownership of health initiatives.

5. Conclusions

The study’s findings advocate for a paradigm shift in public health policy toward a more inclusive, community-centered approach. By recognizing the pivotal role of community engagement in enhancing health outcomes and building resilience, public health agencies can better prepare for and respond to future outbreaks. This study serves as a call to action for policymakers to invest in community engagement as an essential element of public health strategy, ultimately leading to healthier and more resilient populations. Effective management of EVD outbreaks and other health crises in the DRC must be grounded in community engagement and the concrete implementation of a One Health approach. The data from this study, based on the analysis of 12 outbreak reports and interviews with stakeholders at various levels, suggest the need for holistic responses, locally calibrated strategies, and a trust- and collaboration-based platform to guide action and response approaches. Nonetheless, it is necessary to continue analyzing and readjusting response strategies in the face of future crises, while considering changing socio-cultural contexts and community movements. When fear, stigma, and psychological distress are addressed and when communities are meaningfully involved, prevention and control efforts become reliable and effective.
These reflections on Ebola management in the Congolese setting can inform interventions worldwide in populations affected by disease outbreaks, highlighting the applicability of the “One Health” approach. An intersectoral, participatory strategy rooted in trust, proximity, and shared knowledge represents a powerful tool for strengthening health systems’ resilience to future challenges.

Author Contributions

D.K.M., P.Z.A., S.K., N.K.N., J.S. and K.B.A. produced the first draft of the article. All of the other authors contributed to enhancing the quality of the article. D.K.M., C.M., G.M., P.Z.A., S.K., N.K.N., J.S., K.B.A. and C.Z. guided the writing of the article. All authors revised this article and approved its submission. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

This study has been approved by the ethics committee of the University of Montreal (UdeM), Projet # 2020-890 on 29 January 2024. Privacy and confidentiality were maintained throughout the study.

Informed Consent Statement

The study was conducted in accordance with the Declaration of Helsinki and approved by the University of Montreal (UdeM), Projet # 2020-890 on 29 January 2024. Informed consent was obtained from all subjects involved in the study.

Data Availability Statement

The collected data is available and can be shared anonymously.

Acknowledgments

We thank everyone who directly or indirectly contributed to the completion of this work. We offer special thanks to the technical experts from the government, the technical government partners, and the financial partners of the DRC who helped respond to the Ebola outbreak.

Conflicts of Interest

The authors declare no conflicts of interest.

Appendix A. Qualitative Indicators of the MATCH Framework

Table A1. Summary table of documentary sources.
OutbreakDocument Type and SourcesReferences
4th (1995): Kikwit (Bandundu Province)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[15,16,17]
5th (2007): Kasai OccidentalEpidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,18,19,20]
6th (2008–2009): Mweka/Luebo (Kasai Occidental)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,21,22]
7th (2012): Isiro (Orientale Province)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,23,24]
8th (2014): Boende (Équateur Province)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,25,26,27,28]
9th (2017): Likati (Bas-Uélé Province)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,29,30]
10th (2018): Bikoro/Mbandaka (Équateur).Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,31,32]
11th (2018–2020): North Kivu/IturiEpidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,33,34,35,36]
12th (2020): Équateur ProvinceEpidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,37,38,39]
13th (2021): North Kivu (Beni).Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,40,41]
14th (2022): Équateur Province (Mbandaka)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,42,43]
15th (2022): North Kivu (Beni)Epidemiological Situation Report (Ministry of Health—DRC), WHO, Published papers, CDC[17,44,45]
Table A2. “One Health” approach.
Analysis CriteriaObservation:
Involvement
of Sectors
Outbreak
Code
YearProvince/Health ZonesStrainMultisectoral
Coordination
Data SharingIntersectoral
Collaboration
Actors InvolvedLevel of
Integration:
E12007Western Kasai—Mweka, Luebo, BulapeEbola ZaireLimited coordination, led by the Ministry of Health (MS) alone Fragmented data, limited disseminationMinimal collaboration with Non-Governmental Organizations (NGOs)MS, World Health Organization (WHO), National Institute of Biomedical Research (INRB), UNICEF, Doctors Without Borders (MSF), Red Cross: (Technical and Scientific Committee)Suboptimal
E22008Western Kasai—Mweka, Luebo, BulapeEbola ZaireCoordination similar to 2007Non-harmonized dataLimited collaborationMS, WHO, INRB, UNICEF, MSF, Red Cross: (Technical and Scientific Committee)Suboptimal
E32012Orientale Province—Isiro, Haut-Uélé, ViadanaEbola ZaireEnhanced coordination with the WHOData shared via radio/NGOCollaboration with church/schoolsHuman health (National Coordinating Committee and International Scientific and Technical Coordinating Committee (ICST))Not optimal
E42014Equator Province (Boende) Increased multisectoral coordinationLimited but real sharingNGO and authority collaborationHuman health (Ministry of Health, Red Cross, local authorities)Suboptimal
E52017Bas-Uele—LikatiEbola ZaireImproved coordination, local involvementSharing via village committeesIncreased collaboration with community liaisons (RECO) and survivorsMS, WHO, INRB, UNICEF, MSF, Food and Agriculture Organization (FAO), Red Cross (multidisciplinary team from the Ministry of Health and the National Coordination Committee)Suboptimal
E62018Ecuador—Bikoro, Iboko, WangataEbola ZaireEnhanced WHO/MS CoordinationStructured sharingNGO collaboration, traditional leadersMS, WHO, INRB, UNICEF, MSF, FAO, Red Cross (multidisciplinary team from the Ministry of Health and the National Coordination Committee)Suboptimal
E72018North Kivu, Ituri, South Kivu—MabalakoEbola ZaireComplex multisectoral coordinationData shared via platformsStrong multisectoral collaborationMultisectoral Committee for the Ebola Response (CMRE) and Ministry of HealthSuboptimal
E82020Ecuador—Bikoro, Iboko, WangataEbola ZairePartial coordinationLimited sharingLimited collaborationCMRE and Ministry of HealthSuboptimal
E92021North Kivu—Biena, Butembo, Katwa, MusienneEbola ZaireImproved coordination, leadership involvementStructured sharingGood collaboration between survivors and NGOsNational Coordination Committee (NCC) and Incident Management System: MS, WHO, INRB, UNICEF, MSF, Red CrossSuboptimal
E102021North Kivu—BeniEbola ZaireFragile coordinationLimited dataWeak collaborationCNC and SGI: MS, WHO, INRB, UNICEF, MSF, Red CrossSuboptimal
E112022Ecuador—Mbandaka, Wangata, BolengeEbola ZaireConsolidated coordinationRegular sharingNGO and authority collaborationCNC and SGI: MS, WHO, INRB, UNICEF, MSF, Red CrossSuboptimal
E122022North Kivu—BeniEbola ZaireReduced coordination, local tensionsLow sharingWeak collaborationCNC and SGI: MS, WHO, INRB, UNICEF, MSF, Red CrossSuboptimal
Outbreak codes (E1–E12) refer to Ebola outbreaks in the DRC from 2007 to 2022. Not optimal: involvement of a single sector (e.g., human health). Suboptimal: involvement of 2 sectors (e.g., human and animal health).
Table A3. Community engagement.
Analysis CriteriaObservation
Community
Involvement:
Outbreak
Code
YearProvince/Health ZonesStrainAwarenessAccountabilityCommunity Stakeholders InvolvedSpecific GroupsLevel of
Involvement
E12007Western Kasai—Mweka, Luebo, BulapeEbola ZaireLocal campaigns through community relays (RECO), rural radio (local authorities and community leaders)Low accountability, limited mobilization of local authoritiesRECO, Red Cross, CACReligious leaders, local authorities, local radio stations, orchestras (general population)Low
E22008Western Kasai—Mweka, Luebo, BulapeEbola ZaireIncreased use of community radio, local postersGreater accountability with the involvement of local health authoritiesRECO, Red Cross, Community Coordination Unit (CAC)General population, affected familiesModerate
E32012Orientale Province—Isiro, Haut-Uélé, ViadanaEbola ZaireAwareness sessions in villages, involvement of local NGOsBeginning of participatory approaches (community consultations)RECO, Red Cross, local Non-Governmental Organizations (NGOs), youth associationsReligious leaders, hunters, game sellers, Indigenous People, charcoal burners, women’s and youth associationsModerate
E42014Ecuador (Bikoro)Ebola ZaireLarge-scale radio and church campaigns; survivor involvementPartial empowerment (associated traditional leaders)RECO, religious denominations, survivorsGeneral population (women, youth, survivors)Good
E52017Bas-Uele—LikatiEbola ZaireLocal communication, community theaterStrong empowerment (community leaders active in the response)CAC, Red CrossCommunity leaders, hunters, traditional healers, driver associations (general population, affected families)Good
E62018Ecuador—Bikoro, Iboko, WangataEbola ZaireExtensive radio campaign, involvement of schoolsProgressive empowerment with role sharingRECO, teachers, health authoritiesCommunity leaders, hunters, traditional healers, driving associationsGood
E72018North Kivu, Ituri, South Kivu—MabalakoEbola ZaireIntensive campaigns, local radio, TV spots, WhatsApp (development of a map of RECOs, local supervisors and Health Area supervisors)Strong empowerment but polarized by a climate of mistrust (training of RECOs; village/neighborhood/group leaders; and opinions of leaders on the procedure for prevention, identification of cases, collection and transmission of Ebola-related community information to health centers)CACCommunity leaders, youth, women, schoolchildren, traditional healersModerate to Good
E82020Ecuador Targeted communication in the affected areasPartial responsibility, dependent on health authoritiesRECO, churches, traditional leadersGeneral populationModerate
E92021North Kivu—Biena, Butembo, Katwa, MusienneEbola ZaireRapid mobilization via radio and local leadersStrong accountability through vigilance committees (capacity building for community leaders: mayors, neighborhood and street chiefs) regarding Ebola virus diseaseCAC, RECO, local authorities, youth associationsCommunity leaders (youth, affected families)Good
E102021North Kivu—BeniEbola ZaireGoodGood capacity building for community leaders (mayors, neighborhood and street chiefs) in fight against EVDCACCommunity leadersGood
E112022Ecuador—Mbandaka, Wangata, BolengeEbola ZaireAwareness-raising via community radio, local campaignsCapacity building for community leaders (mayors, neighborhood and street chiefs) in fight against EbolaCAC, RECO, local NGOs, religious denominationsCommunity leaders, familiesModerate
E122022North Kivu—BeniEbola ZaireTargeted awareness-raising with crisis communicationAccountability consolidated by authorities and survivors (capacity building of community leaders: mayors, neighborhood and street chiefs) in fight against EbolaCAC, RECO, survivors, NGOs, churchesCommunity leaders (affected communities, bereaved families)Moderate to Good
E1–E12 = numbering of the Ebola virus disease outbreaks in the DRC (from 2007 to 2022). The following denote the level of involvement: Low: Occasional, unstructured involvement; Moderate: Partial participation, but not systematic; Good: Regular and structured community engagement.
Table A4. Bottom-up approach.
Analysis CriteriaObservation
Outbreak CodeYearProvince/Health ZonesStrainLocal Information
Collection
Community
Involvement
Strategic
Adaptation
Local System
Strengthening
Key PlayersApplication of
the Approach
E12007Western Kasai—Mweka, Luebo, BulapeEbola ZaireAd hoc reports via community relays (RECO)Low demand, fear/rumorsLimited adjustments to local customs (involvement of non-medical stakeholders)No permanent system (involvement of the community facilitator of the Mweka Health Zone (HZ) in the management of emergency activities to address the outbreak)Community facilitator ZS/Mweka, RECO, traditional leaders Not applied
E22008Western Kasai—Mweka, Luebo, BulapeEbola ZaireSame setup as in 2007Limited participation, little consideration given to feedbackLittle adaptation to expressed needsNo emergency structural improvement in response to the outbreakRECO, local leaders Not applied
E32012Orientale Province—Isiro, Haut-Uélé, ViadanaEbola ZaireLocal radio stations, parish meetingsParticipation of religious leaders/teachersPartial adjustments based on feedbackLocal dialog strengthened on occasionRECO, priests, teachersApplied: Moderate
E42014BoendeEbola ZaireCommunity meetings, radio stationsIncreased mobilization around funeral practicesPartial adjustments to funeral ritualsLimited structural reinforcementRECO, Red Cross, local authoritiesApplied: Moderate
E52017Bas-Uele—LikatiEbola ZaireWord of mouth, village committeesInvolvement of survivors and familiesCommunication to encourage behavior changeStart of functional committeesRECO, survivors, Red CrossApplied: Good
E62018Ecuador—Bikoro, Iboko, WangataEbola ZaireCommunity radio stations, structured meetingsActive customary leadershipThe village-by-village and household-by-household strategy is one of the strategies that has been used to control the diseaseStructuring of local mechanismsRECO, Non-Governmental Organization (NGO), traditional leadersApplied: Good
E72018North Kivu, Ituri, South Kivu—MabalakoEbola ZaireMonitoring committees, platforms, feedback pointsPresentInvitations to all village chiefs, neighborhood chiefs, group chiefs, leaders, and registered nurses (RNs) of the targeted Health Areas (HAs) to participate in operational meetingsHealth personnel, managers from other sectors, administrative staff, and social organizations within the health zone are the main actors in the responseVillage chiefs, community leaders, registered nursesApplied: Optimal
E82020EcuadorEbola ZaireLocal radio stations, community relaysPartial involvementLimited adjustmentsLow durabilityRECO, local NGOsApplied: Moderate
E92021North Kivu—Biena, Butembo, Katwa, MusienneEbola ZaireRegular community dialogStrong involvement of survivors/young peopleInvitations to all village chiefs, neighborhood chiefs, group leaders, and IT staff of the targeted AS to participate in operational meetingsHealth personnel, managers from other sectors, administrative staff, and social organizations within the health zone are the main actors in the responseCommunity leaders and local influencersApplied: Good
E102021North Kivu—BeniEbola ZaireAd hoc meetingsLimited involvement, persistent mistrustMinor adjustmentsWeak local reinforcementRECO, local NGOsApplied: Moderate
E112022Ecuador—Mbandaka, Wangata, BolengeEbola ZaireRadio and meetings reinforcedGood community participationAdjustments to local practicesStrengthened community relaysRECO, NGO, Red CrossApplied: Good
E122022North Kivu—BeniEbola ZaireInformal, unsystematic collectionReduced involvementWeak adjustmentsNo reinforcement observedCommunity leaders and local influential groupsApplied: Low
The following denote the level of application of the approach: Not applied; Low: Occasional, unstructured involvement; Moderate: Partial participation, but not systematic; Good: Regular and structured community engagement; Optimal: Central and active involvement, with clear local ownership.

References

  1. Mwamba, D.K.; Zarowsky, C.; Manianga, C.D.; Kapanga, S.; Moullec, G. Engagement communautaire et prise en compte de la détresse psychologique, de la peur et de la stigmatisation dans la surveillance et la gestion des épidémies de la maladie à virus Ebola dans l’approche «Une seule santé» en RD. Glob. Health Promot. 2024, 32, 75–84. [Google Scholar] [CrossRef] [Scilit]
  2. Olive, M.M.; Angot, J.L.; Binot, A.; Desclaux, A.; Dombreval, L.; Lefrancois, T.; Lury, A.; Paul, M.; Peyre, M.; Simard, F.; et al. Plan d’action conjoint «Une seule santé» (2022–2026). In Travailler Ensemble Pour des Êtres Humains, des Animaux, des Végétaux et un Environnement en Bonne Santé; World Health Organization: Geneva, Switzerland, 2022; Volume 30, pp. 72–81. [Google Scholar]
  3. Olive, M.M.; Angot, J.L.; Binot, A.; Desclaux, A.; Dombreval, L.; Lefrancois, T.; Lury, A.; Paul, M.; Peyre, M.; Simard, F.; et al. Les approches One Health pour faire face aux emergences: Un necessaire dialogue A tat-sciences-societes. Nat. Sci. Soc. 2022, 30, 72–81. [Google Scholar] [CrossRef] [Scilit]
  4. Rosello, A.; Mossoko, M.; Flasche, S.; Van Hoek, A.J.; Mbala, P.; Camacho, A.; Funk, S.; Kucharski, A.; Ilunga, B.K.; Edmunds, W.J.; et al. Ebola virus disease in the Democratic Republic of the Congo, 1976–2014. eLife 2015, 4, e09015. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Vinck, P.; Pham, P.N.; Bindu, K.K.; Bedford, J.; Nilles, E.J. Institutional trust and misinformation in the response to the 2018–2019 Ebola outbreak in North Kivu. Lancet Infect. Dis. 2019, 19, 529–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. World Health Organization. One Health High Level Expert Panel Annual Report 2021; World Health Organization: Geneva, Switzerland, 2021; pp. 1–35. Available online: https://cdn.who.int/media/docs/default-source/one-health/ohhlep/ohhlep-annual-report-2021.pdf?sfvrsn=f2d61e40_10&download=true (accessed on 1 December 2025).
  7. Voltz, R.; Meesters, S.; Ohler, K.; Weihrauch, B.; Kreische, A.; Niessen, J.; Heller, A.; Strupp, J.; Kremeike, K. Top-down and bottom-up or participation through action? How to build a compassionate community—The experience of Caring Community Cologne. Palliat. Care Soc. Pract. 2024, 18, 26323524241238230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Ministère de la Santé Publique (Direction de la Lutte contre la Maladie), Democratic Republic of the Congo. Rapport de la Gestion de l’Epidémie de Fièvre Hémorragique Virale Ebola dans la Zone de Santé de Mweka, Province du Kasai Occidental; Ministère de la Santé Publique (Direction de la Lutte contre la Maladie), Democratic Republic of the Congo: Kinshasa, Democratic Republic of the Congo, 2007; pp. 1–73.
  9. Ministère de la Santé Publique (Direction de la Lutte Contre la Maladie). Rapport de la Gestion de l’Epidémie de Fièvre Hémorragique Virale Ebola dans la Zone de Santé de Mweka, Province du Kasai Occidental; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2009.
  10. Ministère de la Santé Publique (Direction de la Lutte Contre la Maladie). Gestion de l’Epidémie de la Fièvre Hémorragique a Virus Ebola a Isiro; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2012.
  11. Ministère de la Santé Publique; Hygiène et Prévention de la République. Rapport de Gestion de l’ Épidemie de la Maladie à Virus Ébola; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2014; pp. 1–62.
  12. Ministère de la Santé Publique; Hygiène et Prévention de la République. Brève Situation de la Riposte à L’épidémie de la Maladie à Virus Ebola (MVE) dans la Province de l’Equateur, République Démocratique du Congo au 30e Jour; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2018.
  13. Ministère de la Santé Publique; Hygiène et Prévention de la République. Rapport de Gestion de la 11 Ième Épidemie de la Maladie à Virus Ébola_Boende Direction de la Surveillance Epidémiologique, Direction Generale de Lutte Contre la Maladie Rapport de la 11ème Épidemie de la Maladie à Virus Ébola (MVE) Dans la Province de L’équateur; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2020.
  14. Ministère de la Santé Publique; Hygiène et Prévention de la République. Rapport de la 14 Ème Épidemie de la Maladie à Virus Ébola (MVE) Dans la Province de L’équateur Juillet; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2022.
  15. Muyembe-Tamfum, J.J.; Kipasa, M.; Kiyungu, C.; Colebunders, R. Ebola outbreak in Kikwit, Democratic Republic of the Congo: Discovery and control measures. J. Infect. Dis. 1999, 179, S259–S262. [Google Scholar] [CrossRef] [Scilit]
  16. WHO. Ebola Haemorrhagic Fever. Available online: https://iris.who.int/server/api/core/bitstreams/45a1a7ab-16e5-479a-8117-9d6238300a99/content (accessed on 15 November 2025).
  17. CDC. Outbreak History: Ebola Disease Outbreaks by Species and Size, Since 1976. Available online: https://www.cdc.gov/ebola/outbreaks/index.html (accessed on 15 November 2025).
  18. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2007_09_27-en (accessed on 15 November 2025).
  19. Grard, G.; Biek, R.; Tamfum, J.J.; Fair, J.; Wolfe, N.; Formenty, P.; Paweska, J.; Leroy, E. Emergence of divergent Zaire ebola virus strains in Democratic Republic of the Congo in 2007 and 2008. J. Infect. Dis. 2011, 204, S776–S784. [Google Scholar] [CrossRef] [Scilit]
  20. Leroy, E.M.; Epelboin, A.; Mondonge, V.; Pourrut, X.; Gonzalez, J.P.; Muyembe-Tamfum, J.J.; Formenty, P. Human Ebola outbreak resulting from direct exposure to fruit bats in Luebo, Democratic Republic of Congo, 2007. Vector-Borne Zoonotic Dis. 2009, 9, 723–728. [Google Scholar] [CrossRef] [Scilit]
  21. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2009_02_17-en (accessed on 15 November 2025).
  22. Muyembe-Tamfum, J.J.; Mulangu, S.; Masumu, J.; Kayembe, J.M.; Kemp, A.; Paweska, J.T. Ebola virus outbreaks in Africa: Past and present. Onderstepoort J. Vet. Res. 2012, 79, 451. [Google Scholar] [CrossRef] [Scilit]
  23. Kratz, T.; Roddy, P.; Tshomba Oloma, A.; Jeffs, B.; Pou Ciruelo, D.; de la Rosa, O.; Borchert, M. Ebola Virus Disease Outbreak in Isiro, Democratic Republic of the Congo, 2012: Signs and Symptoms, Management and Outcomes. PLoS ONE 2015, 10, e0129333. [Google Scholar] [CrossRef] [Scilit]
  24. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2012_10_08a-en (accessed on 15 November 2025).
  25. European Centre for Disease Prevention and Control. Outbreak of Ebola Virus Disease in Equateur Province, Democratic Republic of the Congo; ECDC: Stockholm, Sweden, 2014. Available online: https://www.ecdc.europa.eu/sites/default/files/media/en/publications/Publications/rapid-risk-asseessment-Ebola-DRCongo-9-Sept-2014.pdf (accessed on 15 November 2025).
  26. Maganga, G.D.; Kapetshi, J.; Berthet, N.; Kebela Ilunga, B.; Kabange, F.; Mbala Kingebeni, P.; Mondonge, V.; Muyembe, J.J.; Bertherat, E.; Briand, S.; et al. Ebola virus disease in the Democratic Republic of Congo. N. Engl. J. Med. 2014, 371, 2083–2091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Nanclares, C.; Kapetshi, J.; Lionetto, F.; de la Rosa, O.; Tamfun, J.J.; Alia, M.; Kobinger, G.; Bernasconi, A. Ebola Virus Disease, Democratic Republic of the Congo, 2014. Emerg. Infect. Dis. 2016, 22, 1579–1586. [Google Scholar] [CrossRef] [Scilit]
  28. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2014_08_27_ebola-en (accessed on 15 November 2025).
  29. Hemingway-Foday, J.J.; Ngoyi, B.F.; Tunda, C.; Stolka, K.B.; Grimes, K.E.L.; Lubula, L.; Mossoko, M.; Kebela, B.I.; Brown, L.M.; MacDonald, P.D.M. Lessons Learned from Reinforcing Epidemiologic Surveillance During the 2017 Ebola Outbreak in the Likati District, Democratic Republic of the Congo. Health Secur. 2020, 18, S81–S91. [Google Scholar] [CrossRef] [Scilit]
  30. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/13-may-2017-ebola-drc-en (accessed on 15 November 2025).
  31. Mbala-Kingebeni, P.; Pratt, C.B.; Wiley, M.R.; Diagne, M.M.; Makiala-Mandanda, S.; Aziza, A.; Di Paola, N.; Chitty, J.A.; Diop, M.; Ayouba, A.; et al. 2018 Ebola virus disease outbreak in Équateur Province, Democratic Republic of the Congo: A retrospective genomic characterisation. Lancet Infect. Dis. 2019, 19, 641–647. [Google Scholar] [CrossRef] [Scilit]
  32. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/13-june-2018-ebola-drc-en (accessed on 15 November 2025).
  33. Vossler, H.; Akilimali, P.; Pan, Y.; KhudaBukhsh, W.R.; Kenah, E.; Rempała, G.A. Analysis of individual-level data from 2018–2020 Ebola outbreak in Democratic Republic of the Congo. Sci. Rep. 2022, 12, 5534. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Mbala-Kingebeni, P.; Aziza, A.; Di Paola, N.; Wiley, M.R.; Makiala-Mandanda, S.; Caviness, K.; Pratt, C.B.; Ladner, J.T.; Kugelman, J.R.; Prieto, K.; et al. Medical countermeasures during the 2018 Ebola virus disease outbreak in the North Kivu and Ituri Provinces of the Democratic Republic of the Congo: A rapid genomic assessment. Lancet Infect. Dis. 2019, 19, 648–657. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Sah, R.; Mohanty, A.; Mehta, V.; Satapathy, P.; Padhi, B.K.; Rodriguez-Morales, A.J. The Ebola Resurgence in Democratic Republic of Congo. Ann. Med. Surg. 2022, 82, 104616. [Google Scholar] [CrossRef] [Scilit]
  36. WHO. Ebola Outbreak 2018–2020-North Kivu-Ituri. Available online: https://www.who.int/emergencies/situations/Ebola-2019-drc- (accessed on 15 November 2025).
  37. Kinganda-Lusamaki, E.; Whitmer, S.; Lokilo-Lofiko, E.; Amuri-Aziza, A.; Muyembe-Mawete, F.; Makangara-Cigolo, J.C.; Makaya, G.; Mbuyi, F.; Whitesell, A.; Kallay, R.; et al. 2020 Ebola virus disease outbreak in Équateur Province, Democratic Republic of the Congo: A retrospective genomic characterisation. Lancet Microbe 2024, 5, e109–e118. [Google Scholar] [CrossRef] [Scilit]
  38. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2020-DON277 (accessed on 15 November 2025).
  39. Lenhardt, A. Lessons Learned from Ebola Outbreak 9 in Equateur, Democratic Republic of the Congo; K4D Helpdesk Report 845; Institute of Development Studies: Brighton, UK, 2020; Available online: https://www.rcce-collective.net/wp-content/documents-repo/Evaluation_Learning/Research_Evidence_%26_Lessons_Learned/845_Lessons_learned_from_Ebola_outbreak9_in_Equateur_Province_DRC.pdf (accessed on 15 November 2025).
  40. Diarra, T.; Okeibunor, J.; Diallo, A.B.; Onyeneho, N.; Rodrigue, B.; N’da Konan Yao, M.; Yoti, Z.; Djingarey, M.H.; Fall, I.S.; Gueye, A.S. Epidemic Response amidst Insecurity: Addressing the Ebola Virus Epidemic in the Provinces of North Kivu and Ituri. J. Immunol. Sci. 2023, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
  41. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2021-DON351 (accessed on 15 November 2025).
  42. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2022-DON398 (accessed on 15 November 2025).
  43. Sun, J.; Uwishema, O.; Kassem, H.; Abbass, M.; Uweis, L.; Rai, A.; El Saleh, R.; Adanur, I.; Onyeaka, H. Ebola virus outbreak returns to the Democratic Republic of Congo: An urgent rising concern. Ann. Med. Surg. 2022, 79, 103958. [Google Scholar] [CrossRef] [Scilit]
  44. WHO. Disease Outbreak News. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2025-DON580 (accessed on 15 November 2025).
  45. Kikwango, E.M.; Akilimali, P.Z.; Tran, N.T. Impact of most promising Ebola therapies on survival: A secondary analysis during the tenth outbreak in the Democratic Republic of Congo. Virol. J. 2025, 22, 144. [Google Scholar] [CrossRef] [Scilit]
  46. Bunker, B.S.-M. Parcel Influencing Personal and Environnemental Conditions for Community Health_A Multilevel Intervention Model; Aspen Publishers, Inc.: New York, NY, USA, 1988; pp. 25–35. [Google Scholar]
  47. Simons-Morton, B.; McLeroy, K.; Wendel, M. Behavior Theory in Health Promotion Practice and Research; Jones & Bartlett Learning: Burlington, MA, USA, 2011. [Google Scholar]
  48. Lawrence, R.S.; Bibbins-Domingo, K.; Brennan, L.K.; Daniels, N.; Gaskin, D.J.; Green, L.W.; Haveman, R.; Jenson, J.; Nieto, F.J.; Polsky, D.; et al. An Integrated Framework for Assessing the Value of Community-Based; National Academies Press: Washington, DC, USA, 2012. [Google Scholar]
  49. Desclaux, A.; Sow, K. «Humaniser» les soins dans l’épidémie d’Ebola? Les tensions dans la gestion du care et de la biosécurité dans le suivi des sujets contacts au Sénégal. Anthropol. Santé 2015, 11, 2–17. [Google Scholar]
  50. Strauss, A.; Corbin, J. Basics of Qualitative Research; Sage Publications: Thousand Oaks, CA, USA, 1990. [Google Scholar]
  51. Saunders, B.; Sim, J.; Kingstone, T.; Baker, S.; Waterfield, J.; Bartlam, B.; Burroughs, H.; Jinks, C. Saturation in qualitative research: Exploring its conceptualization and operationalization. Qual. Quant. 2018, 52, 1893–1907. [Google Scholar] [CrossRef] [Scilit]
  52. WHO; Ministère de la Santé-RDC. Strategic Response Plan for the Ebola Virus DISEASE Outbreak in the Provinces of North Kivu and Ituri Democratic Republic of the Congo. 2019. Available online: https://www.who.int/docs/default-source/documents/drc-srp4-9august2019.pdf (accessed on 15 November 2025).
  53. Frieden, T.R.; Damon, I.; Bell, B.P.; Kenyon, T.; Nichol, S. Ebola 2014—New Challenges, New Global Response and Responsibility. N. Engl. J. Med. 2014, 371, 1177–1180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  54. Wadoum, R.E.G.; Sevalie, S.; Minutolo, A.; Clarke, A.; Russo, G.; Colizzi, V.; Mattei, M.; Montesano, C. The 2018–2020 Ebola Outbreak in the Democratic Republic of Congo: A Better Response Had Been Achieved Through Inter-State Coordination in Africa. Risk Manag. Healthc. Policy 2021, 14, 4923–4930. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  55. Fa, J.E.; Nasi, R.; Van Vliet, N. Bushmeat, human impacts and human health in tropical rainforests: The Ebola virus case. Sante Publique 2019, 31, 107–114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Ministère de la Santé Publique. Rapport de Gestion de la 12ième Épidemie de la Maladie à Virus Ébola Ministère de la Santé, Hygiène et Prévention, Direction Surveillance Epidé Miologique Direction Génèrale de Lutte Contre la Maladie Rapport se la 12 Ème Épidemie de la Maladie à Virus Ébpola (MVE) Dans la Province du Nord Kivu; Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2021.
  57. Kavulikirwa, O.K.; Sikakulya, F.K. Recurrent Ebola outbreaks in the eastern Democratic Republic of the Congo: A wake-up call to scale up the integrated disease surveillance and response strategy. One Health 2022, 14, 100379. [Google Scholar] [CrossRef] [Scilit]
  58. Sikakulya, F.K.; Mulisya, O.; Munyambalu, D.K.; Bunduki, G.K. Ebola in the Eastern Democratic Republic of Congo: One Health approach to infectious disease control. One Health 2019, 9, 100117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Soke, G.N.; Fonjungo, P.; Mbuyi, G.; Luce, R.; Klena, J.; Choi, M.; Kombe, J.; Makaya, G.; Mbuyi, F.; Bulambo, H.; et al. Continuous Community Engagement Is Needed to Improve Adherence to Ebola Response Activities and Survivorship During Ebola Outbreaks. Glob. Health Sci. Pract. 2024, 12, e2300006. [Google Scholar] [CrossRef] [Scilit]
  60. Ryan, C.S.; Belizaire, M.D.; Nanyunja, M.; Olu, O.O.; Ahmed, Y.A.; Latt, A.; Kol, M.T.; Bamuleke, B.; Tusiime, J.; Nsabimbona, N.; et al. Sustainable strategies for Ebola virus disease outbreak preparedness in Africa: A case study on lessons learnt in countries neighbouring the Democratic Republic of the Congo. Infect. Dis. Poverty 2022, 11, 118. [Google Scholar] [CrossRef] [Scilit]
  61. Ministère de la Santé Publique; Hygiène et Prévention de la République Démocratique du Congo; Direction de la Surveillance Épidémiologique. Rapport de la 13 Ème Épidémie de la Maladie à Virus Ebola (MVE); Ministère de la Santé Publique, République Démocratique du Congo: Kinshasa, Democratic Republic of the Congo, 2021.
  62. Fotso, A.S.; Wright, C.G.; Low, A. How does HIV-related stigma correlate with HIV prevalence in African countries? Distinct perspectives from individuals living with and living without HIV. BMC Public Health 2023, 23, 1720. [Google Scholar] [CrossRef] [Scilit]
  63. Rabelo, I.; Lee, V.; Fallah, M.P.; Massaquoi, M.; Evlampidou, I.; Crestani, R.; Decroo, T.; Van den Bergh, R.; Severy, N. Psychological Distress among Ebola Survivors Discharged from an Ebola Treatment Unit in Monrovia, Liberia—A Qualitative Study. Front. Public Health 2016, 4, 142. [Google Scholar] [CrossRef] [Scilit]
  64. Crawford, N.; Holloway, K.; Baker, J.; Dewulf, A.; Kaboy, P.; Musema, E.K. The Democratic Republic of Congo’s 10th Ebola Title Response Subtitle; Humanitarian Policy Group: London, UK, 2021. [Google Scholar]
  65. Metta, E.; Mohamed, H.; Kusena, P.; Nyamhanga, T.; Bahuguna, S.; Kakoko, D.; Siril, N.; Araya, A.; Mwiru, A.; Magesa, S.; et al. Community perspectives of Ebola Viral Disease in high-risk transmission border regions of Tanzania: A qualitative inquiry. BMC Public Health 2024, 24, 2766. [Google Scholar] [CrossRef] [Scilit]
  66. Ryan, M.J.; Giles-vernick, T.; Graham, J.E. Technologies of trust in outbreak response: Openness, reflexivity and accountability during the 2014–2016 Ebola outbreak in West Africa. BMJ Glob. Health 2019, 4, e001272. [Google Scholar] [CrossRef] [Scilit]
  67. Frimpong, S.O.; Paintsil, E. Community engagement in Ebola outbreaks in sub-Saharan Africa and implications for COVID-19 control: A scoping review. Int. J. Infect. Dis. 2023, 126, 182–192. [Google Scholar] [CrossRef] [Scilit]
  68. Meseko, C.A.; Egbetade, A.O.; Fagbo, S. Ebola virus disease control in West Africa: An ecological, one health approach. Pan Afr. Med. J. 2015, 21, 6. [Google Scholar] [CrossRef] [Scilit]
Figure 2. Model of an Incident Management System. Source: WHO [54].
Pandemics 01 00003 g002
Table 2. Evaluation of indicators from the 4th to the 15th Ebola outbreaks in the DRC.
Period and LocationStrainImpactOne HealthLevel of Community
Involvement/Engagement
Bottom-Up Approach
2007—Luebo (Western Kasai):
4th outbreak
of Ebola, also known as the
Kaluamba outbreak.
EBOV 264 suspected cases, including 187 deaths (case fatality rate of 71%). Not applied Moderate involvement Not applied
2008–2009—Mweka (Western
Kasai):
5th outbreak, occurring in the same region as the 2007 outbreak.
EBOV 32 cases, including 15 deaths (case fatality rate of 47%). Not applied Moderate involvement Not applied
2012—Isiro (Oriental
Province/Haut-Uélé):
Sixth Ebola virus disease (EVD) outbreak, mainly occurring in the city of Isiro.
EBOV 77 cases, including 36 deaths (case fatality rate of 47%). Suboptimal Moderate involvement Applied
Report on the 7th EVD outbreak,
Isiro (Orientale Province), DRC, 2012.
EBOV 38 cases, including 13 deaths (case fatality rate of 34%). Suboptimal Moderate involvement Applied
Report on the 8th EVD outbreak,
Likati Health Zone (Bas-Uele Province), DRC, 2017.
EBOV 8 cases and 4 deaths (case fatality rate of 50%). SuboptimalGood involvementApplied
Report on the response to the 9th
Ebola virus disease outbreak in Equateur/Bikoro Province, 2018.
EBOV From 8 May to 28 June 2018, 53 cases were recorded, including 29 deaths, of which 38 were confirmed and 15 were probable. The case fatality rate was 61%. Suboptimal Good involvement Not applied
Report on the 10th EVD outbreak in the provinces of North Kivu, South Kivu, and Ituri (Declared on 1 August 2018, and ended on 25 June 2020, lasting roughly 22 months.) EBOV 2852 confirmed cases, including 1155 recoveries and 1111 deaths. Women were more affected, representing 55.9% of cases, with a case fatality rate of 66%. Suboptimal Good involvement Applied
Report on the 11th EVD outbreak in Equateur/Mbandaka (Occurred from 1 June 2020 to 18 November 2020, with a duration of approximately 6 months). EBOV 130 confirmed cases, including 55 deaths (case fatality rate of 42%). Suboptimal Good involvement Applied
Report on the 12th EVD outbreak in the North Kivu/Beni and Butembo provinces (Lasted from 7 February 2021 to 3 May 2021, spanning about 3 months). EBOV 12 confirmed cases, including 6 deaths (case fatality rate of 50%). Suboptimal Good involvement Applied
Report on the 13th EVD outbreak in North Kivu/Beni Province (Emerged on 8 October 2021, and was declared over on 16 December 2021, lasting just over 2 months). EBOV 11 confirmed cases, including 9 deaths (case fatality rate of 82%). Optimal Good involvement Applied
Report on the 14th EVD outbreak in Equateur/Mbandaka Province (Ran from 23 April 2022 to 4 July 2022, a duration of approximately 2.5 months). EBOV 5 confirmed cases, including 5 deaths (100% case fatality rate). Optimal Good involvement Applied
Report on the 15th EVD outbreak in North Kivu/Beni Province (The shortest in this series, lasting from 21 August 2022 to 27 September 2022, about 1 month). EBOV 1 confirmed case, including 1 death (100% case fatality rate). Optimal Good involvement Applied
Table 3. Epidemiological surveillance subcommittee.
SubcommitteeMembersObjectivesActivities Carried Out
Epidemiological surveillanceThe subcommittee was made up of several members, including:
-
Experts from the Ministry of Health;
-
Clinicians;
-
Epidemiologists (MSF, WHO, etc.).
-
Make the case definitions available in all health facilities across all health zones.
-
Provide health zones, transporters, and hygiene services at border points that display posters on VHFs (viral hemorrhagic fevers).
-
Strengthen active and passive surveillance activities in all health zones.
-
Investigation: Alerts detected by the mobile surveillance team.
-
Retrospective study through document review and field visits within the community.
-
A 21-day follow-up of all identified contacts.
-
Identification of active cases in health facilities and communities.
-
Database management based on investigation forms.
-
Reconstruction of the transmission chain.
-
Data analysis: Description of the outbreak in terms of times, places, and people affected.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.