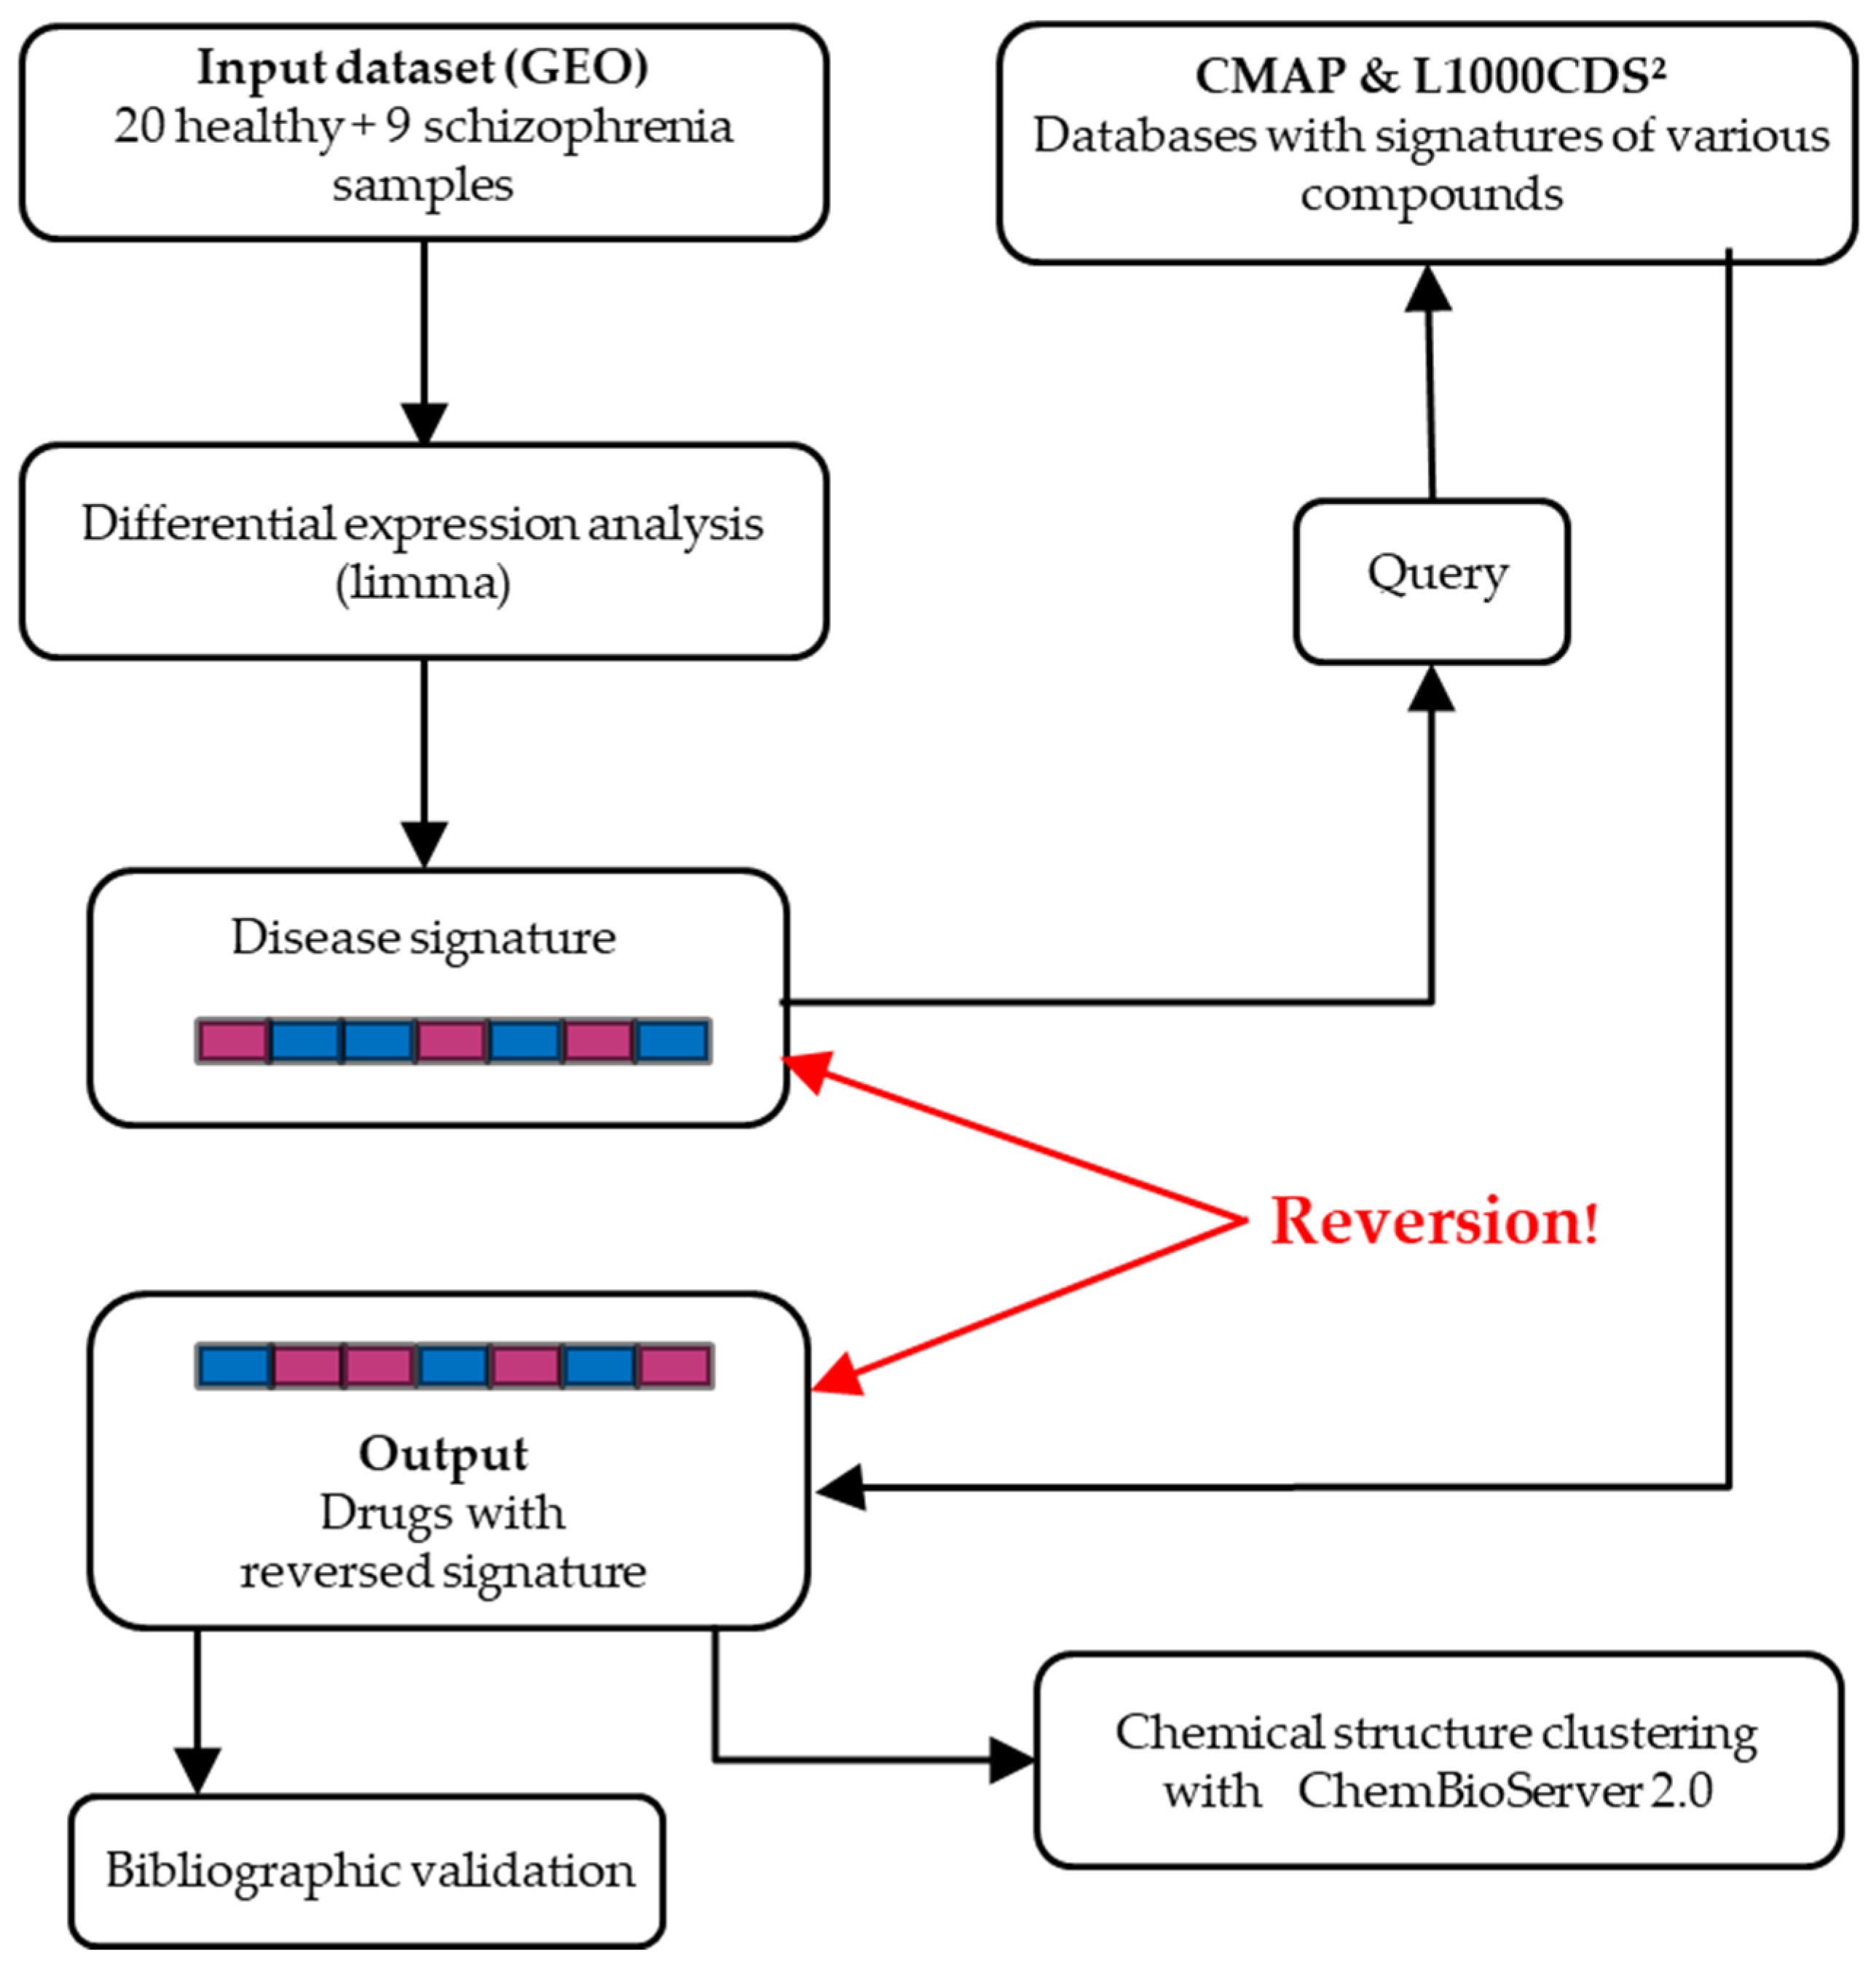
Leveraging Gene Expression Data for Drug Repurposing in Schizophrenia: A Signature Reversion Approach



 and

Abstract
1. Introduction
2. Results
2.1. Schizophrenia’s Signature
2.2. Query Results
2.2.1. CMap Tool
2.2.2. L1000CD2
2.3. Prescreening of Results
2.4. Clustering Drug List
2.5. Predicted Mechanisms of Actions
3. Discussion
4. Materials and Methods
4.1. Dataset
4.2. Differential Gene Expression Analysis
- Upregulated Genes: Genes with adjusted p-value < 0.05 and log2FC > 0 (FC refers to fold-change)
- Downregulated Genes: Genes with adjusted p-value < 0.05 and log2FC < 0
- Genes with adjusted p-value exceeding 0.05 and absolute log2FC below 1 were removed.
- Duplicate genes were filtered out.
- Genes classified as both upregulated and downregulated were excluded.
- Genes that are invalid or cannot be used by CMap were also removed.
4.3. Drug Repurposing Tools
4.3.1. CMap Tool
4.3.2. L1000CDS2
4.4. Clustering with ChemBioServer 2.0
4.5. Predicting MOAs Using L1000FWD
Author Contributions
Funding
Data Availability Statement
Conflicts of Interest
Appendix A

| Upregulated Genes | |||||||
|---|---|---|---|---|---|---|---|
| Symbol | logFC | p.Value | adj.P.Val | Symbol | logFC | p.Value | adj.P.Val |
| MGST1 | 1.196 | 0 | 0 | DUSP1 | 1.023 | 0.001 | 0.004 |
| HEBP1 | 1.271 | 0 | 0.001 | ETF1 | 1.045 | 0 | 0 |
| SLC38A5 | 1.326 | 0.001 | 0.003 | EGR1 | 2.009 | 0.002 | 0.009 |
| EHD2 | 1.517 | 0.004 | 0.014 | GJB6 | 3.558 | 0 | 0 |
| HMGB3 | 1.044 | 0.001 | 0.006 | SPINK4 | 1.216 | 0.012 | 0.036 |
| TG | 1.003 | 0.001 | 0.003 | PLAU | 2.572 | 0 | 0.001 |
| HSPA5 | 1.404 | 0 | 0 | G0S2 | 3.038 | 0.002 | 0.009 |
| DKK3 | 1.19 | 0.002 | 0.008 | SLPI | 1.598 | 0 | 0 |
| RRP12 | 1.178 | 0 | 0 | SNAI1 | 1.529 | 0.003 | 0.01 |
| PSD | 1.041 | 0 | 0.001 | STX16 | 1.375 | 0 | 0 |
| SPAG4 | 1.021 | 0.001 | 0.004 | SEMG1 | 1.789 | 0 | 0.001 |
| GLTSCR1 | 1.099 | 0 | 0 | TREM1 | 1.091 | 0.002 | 0.008 |
| GSTO2 | 1.365 | 0 | 0 | SOX4 | 1.206 | 0 | 0 |
| KLF6 | 1.131 | 0 | 0 | FOSB | 1.712 | 0.004 | 0.014 |
| LAPTM4A | 1.389 | 0 | 0 | TGM3 | 1.494 | 0.001 | 0.005 |
| BCL3 | 1.1 | 0 | 0 | GZF1 | 1.022 | 0 | 0.001 |
| MAOB | 1.643 | 0.002 | 0.009 | ID1 | 4.194 | 0 | 0 |
| JMJD6 | 1.249 | 0 | 0 | SBDS | 1.047 | 0 | 0 |
| PABPC1 | 1.249 | 0 | 0 | HSPA2 | 1.15 | 0.013 | 0.037 |
| P4HA2 | 1.431 | 0 | 0 | HRASLS | 1.094 | 0.003 | 0.012 |
| RAB7A | 1.142 | 0 | 0 | EMC6 | 1.025 | 0 | 0.001 |
| RAP1GAP | 1.243 | 0.016 | 0.043 | LRFN1 | 1.207 | 0 | 0 |
| EDN1 | 1.068 | 0.01 | 0.03 | ZFP36 | 1.254 | 0 | 0 |
| TP53INP2 | 1.376 | 0 | 0 | ADORA2A | 1.632 | 0 | 0.002 |
| CD82 | 1.038 | 0 | 0 | DNAJB9 | 1.3 | 0 | 0 |
| IGSF9 | 1.04 | 0.005 | 0.016 | ALDH1A2 | 1.217 | 0 | 0 |
| B4GALT1 | 1.027 | 0 | 0 | LOXL1 | 1.727 | 0 | 0.001 |
| PPP1R15A | 1.207 | 0 | 0 | FGF13 | 1.149 | 0.009 | 0.029 |
| ADAMTS2 | 3.645 | 0 | 0 | KLF16 | 1.025 | 0 | 0 |
| RFX2 | 1.04 | 0 | 0.001 | LPPR3 | 1.933 | 0 | 0 |
| RPH3A | 1.724 | 0 | 0.001 | CBFA2T3 | 1.337 | 0 | 0 |
| FUS | 1.503 | 0 | 0 | PVRL2 | 1.123 | 0.001 | 0.004 |
| CCNK | 1.313 | 0 | 0 | GADD45G | 1.489 | 0 | 0.002 |
| TREM2 | 1.572 | 0 | 0.001 | TNNT3 | 1.443 | 0 | 0 |
| HNRNPH3 | 1.023 | 0 | 0 | COL5A1 | 1.279 | 0.008 | 0.026 |
| GADD45B | 1.009 | 0 | 0 | PDLIM4 | 2.101 | 0 | 0 |
| DDT | 1.373 | 0 | 0.001 | RPL27 | 1.288 | 0 | 0 |
| SEC14L3 | 1.07 | 0.007 | 0.022 | LGALS3 | 1.05 | 0 | 0.001 |
| UPB1 | 1.051 | 0 | 0 | EIF5A | 1.12 | 0 | 0 |
| NFKBIA | 1.626 | 0 | 0 | KDM6B | 1.562 | 0 | 0 |
| SIRPB1 | 1.021 | 0 | 0.001 | MTSS1L | 1.06 | 0 | 0.001 |
| CHMP4B | 1.158 | 0 | 0 | NXT1 | 1.136 | 0 | 0.001 |
| EMD | 1.159 | 0 | 0 | CCDC59 | 1.091 | 0 | 0 |
| USB1 | 1.191 | 0 | 0 | PTGFRN | 1.242 | 0 | 0 |
| TULP2 | 2.028 | 0 | 0 | ECHDC3 | 1.934 | 0 | 0 |
| RPS16 | 1.658 | 0 | 0 | AKIRIN2 | 1.175 | 0 | 0 |
| CCDC9 | 1.194 | 0 | 0 | CD63 | 1.228 | 0 | 0 |
| SCN1B | 1.03 | 0 | 0 | CKAP4 | 1.104 | 0 | 0 |
| ERF | 1.085 | 0 | 0 | NACAD | 1.056 | 0.002 | 0.009 |
| NAMPT | 1.251 | 0 | 0 | SCN2A | 1.327 | 0.005 | 0.018 |
| UBE2R2 | 1.098 | 0 | 0 | ANP32B | 1.273 | 0 | 0 |
| UBE2S | 1.02 | 0 | 0 | HIST1H2AB | 1.442 | 0 | 0.001 |
| RPL28 | 1.252 | 0 | 0 | GCM1 | 1.347 | 0 | 0 |
| AREG | 2.226 | 0.006 | 0.019 | SLCO5A1 | 1.134 | 0 | 0.001 |
| MAPK10 | 1.294 | 0.001 | 0.004 | SDCBP | 1.031 | 0 | 0 |
| SH3D19 | 1.612 | 0 | 0.001 | RPLP1 | 1.066 | 0 | 0 |
| SLC1A2 | 3.11 | 0 | 0 | SMAD6 | 1.561 | 0.016 | 0.043 |
| POU2AF1 | 1.137 | 0 | 0.001 | HNRNPD | 1.079 | 0 | 0 |
| MGP | 1.468 | 0.001 | 0.006 | CCNG2 | 1.042 | 0 | 0 |
| PHACTR1 | 1.488 | 0 | 0 | ANXA3 | 1.072 | 0.001 | 0.006 |
| CD83 | 1.465 | 0.001 | 0.004 | GPR84 | 1.414 | 0.013 | 0.037 |
| PTP4A1 | 1.409 | 0 | 0 | RAB20 | 1.17 | 0.002 | 0.008 |
| VNN1 | 1.018 | 0 | 0.001 | REM2 | 1.083 | 0 | 0 |
| CCR6 | 1 | 0.007 | 0.023 | BCL2A1 | 1.039 | 0.005 | 0.018 |
| HBEGF | 1.507 | 0.005 | 0.018 | RLBP1 | 1.572 | 0 | 0.001 |
| BCL6 | 1.059 | 0 | 0.001 | MAP1LC3B | 1.041 | 0 | 0 |
| EIF1B | 1.51 | 0 | 0 | OSGIN1 | 1.031 | 0.003 | 0.012 |
| IL1R2 | 1.354 | 0 | 0 | TOB1 | 1.633 | 0 | 0 |
| IL1RL2 | 2.118 | 0.002 | 0.007 | ZMYND15 | 1.707 | 0 | 0 |
| PAPPA2 | 1.611 | 0.007 | 0.022 | CSNK1D | 1.674 | 0 | 0 |
| TNFAIP3 | 1.21 | 0.005 | 0.018 | NFIC | 1.07 | 0 | 0 |
| UBE2B | 1.039 | 0 | 0 | CTD-3222D19.2 | 1.07 | 0.006 | 0.021 |
| KLF9 | 1.095 | 0 | 0 | DMRTC2 | 1.92 | 0 | 0.001 |
| NR4A3 | 2.491 | 0.001 | 0.003 | SIK1 | 1.304 | 0.006 | 0.02 |
| YPEL5 | 1.041 | 0 | 0 | NR1I3 | 1.226 | 0 | 0 |
| Downregulated Genes | |||||||
|---|---|---|---|---|---|---|---|
| Symbol | logFC | p.Value | adj.P.Val | Symbol | logFC | p.Value | adj.P.Val |
| PDK4 | −1.099 | 0.002 | 0.007 | WNT3 | −1.191 | 0.001 | 0.003 |
| ZMYND10 | −1.673 | 0 | 0 | CCL2 | −2.109 | 0.017 | 0.045 |
| MEOX1 | −1.301 | 0.006 | 0.021 | CACNG1 | −1.88 | 0.002 | 0.009 |
| TTC22 | −1.172 | 0 | 0 | GNRHR | −1.511 | 0.001 | 0.005 |
| CACNA2D2 | −1.031 | 0 | 0.001 | B3GAT1 | −1.682 | 0 | 0 |
| OSBPL5 | −1.213 | 0 | 0 | SNX15 | −2.006 | 0 | 0 |
| CPS1 | −1.322 | 0.007 | 0.024 | UPK2 | −1.117 | 0.007 | 0.023 |
| HSD17B6 | −1.319 | 0.017 | 0.046 | CALCA | −1.538 | 0.01 | 0.03 |
| INSRR | −1.333 | 0.015 | 0.041 | ENDOU | −1.119 | 0.006 | 0.02 |
| SLC18A1 | −2.203 | 0.002 | 0.007 | FANCE | −1.257 | 0 | 0 |
| RTN4R | −1.629 | 0 | 0.002 | ENPP5 | −1.74 | 0 | 0 |
| USP28 | −1.127 | 0 | 0 | NUDT12 | −1.076 | 0.003 | 0.011 |
| EPN3 | −1.135 | 0.007 | 0.022 | KIF20A | −1.144 | 0.001 | 0.003 |
| SLC4A8 | −1.014 | 0 | 0 | PDGFRB | −2.167 | 0 | 0 |
| LAMC3 | −2.011 | 0.005 | 0.017 | SERPINI2 | −1.274 | 0.001 | 0.003 |
| TNIP3 | −1.042 | 0.016 | 0.044 | HHLA2 | −1.723 | 0.001 | 0.004 |
| MCOLN3 | −1.568 | 0 | 0 | C3orf52 | −1.319 | 0.001 | 0.004 |
| PCGF2 | −1.287 | 0.003 | 0.013 | RTKN | −1.459 | 0 | 0 |
| ZNF112 | −2.017 | 0.004 | 0.014 | ZAP70 | −1.003 | 0 | 0 |
| TSPAN32 | −1.138 | 0 | 0 | PCSK4 | −1.039 | 0.001 | 0.006 |
| NGFR | −1.833 | 0.002 | 0.007 | GNLY | −1.433 | 0 | 0 |
| CDON | −1.2 | 0.007 | 0.023 | LCT | −1.212 | 0.007 | 0.022 |
| FGFR2 | −1.078 | 0.018 | 0.05 | GRIN3B | −1.005 | 0.006 | 0.02 |
| LLGL2 | −1.343 | 0 | 0 | DHCR24 | −1.176 | 0 | 0 |
| TBX21 | −1.247 | 0 | 0 | C1orf21 | −1.194 | 0 | 0 |
| TTC38 | −1.139 | 0 | 0 | OLFML3 | −1.526 | 0.001 | 0.003 |
| UBE2T | −1.676 | 0 | 0 | CD160 | −1.149 | 0 | 0.001 |
| AMPH | −1.657 | 0 | 0 | TSPAN1 | −1.697 | 0 | 0.001 |
| DDX43 | −1.211 | 0.008 | 0.024 | FASLG | −1.941 | 0 | 0 |
| JMJD4 | −1.006 | 0 | 0 | ATP10B | −1.61 | 0 | 0.001 |
| ATP8B1 | −1.103 | 0.017 | 0.046 | FILIP1 | −1.379 | 0.01 | 0.031 |
| FAT1 | −1.056 | 0.013 | 0.038 | RARRES1 | −1.353 | 0 | 0.001 |
| CETP | −1.042 | 0.001 | 0.005 | PROX2 | −1.202 | 0 | 0.001 |
| C3orf18 | −1.205 | 0 | 0 | C10orf95 | −1.431 | 0.016 | 0.044 |
| SIRT4 | −2.144 | 0 | 0 | HOXB3 | −1.367 | 0 | 0 |
| FLT3LG | −1.098 | 0 | 0.002 | SMAD9 | −2.201 | 0.001 | 0.006 |
| SLC26A3 | −1.95 | 0.002 | 0.008 | EPX | −1.061 | 0.007 | 0.023 |
| IL5RA | −1.305 | 0.001 | 0.003 | TAS2R10 | −1.203 | 0.017 | 0.045 |
| TF | −1.533 | 0.016 | 0.044 | PRB2 | −1.329 | 0.01 | 0.03 |
| RGS17 | −1.456 | 0.002 | 0.009 | FABP3 | −1.111 | 0 | 0 |
| ANGPT2 | −1.032 | 0.001 | 0.005 | ZSCAN20 | −1.293 | 0 | 0 |
| TGM1 | −1.081 | 0 | 0 | WIPF3 | −1.792 | 0.002 | 0.007 |
| SEMA4G | −1.509 | 0 | 0 | SLC12A5 | −1.556 | 0 | 0.001 |
| ARVCF | −1.791 | 0 | 0 | BTN1A1 | −1.719 | 0.006 | 0.019 |
| MMP11 | −1.461 | 0.009 | 0.028 | BFSP1 | −2.255 | 0 | 0 |
| P2RX6 | −1.23 | 0.007 | 0.024 | LRRN4 | −1.638 | 0.001 | 0.006 |
| SOX10 | −1.171 | 0.008 | 0.026 | TMEM74B | −1.452 | 0.001 | 0.005 |
| APOL4 | −1.35 | 0.005 | 0.018 | PROZ | −2.243 | 0 | 0.002 |
| MLC1 | −1.435 | 0 | 0 | TAS2R3 | −2.058 | 0 | 0.001 |
| GZMH | −1.4 | 0 | 0 | TAS2R4 | −2.196 | 0.002 | 0.009 |
| GZMB | −1.507 | 0 | 0 | TAS2R5 | −1.047 | 0.007 | 0.024 |
| ASB2 | −1.102 | 0.001 | 0.004 | CRYGN | −2.107 | 0.001 | 0.005 |
| NINL | −1.862 | 0.001 | 0.004 | ZNF835 | −1.669 | 0 | 0.002 |
| TSNAXIP1 | −1.596 | 0.001 | 0.005 | CDHR3 | −1.231 | 0 | 0 |
| SMPD3 | −1.116 | 0.001 | 0.004 | USP6 | −1.127 | 0.004 | 0.016 |
| METRN | −1.041 | 0 | 0 | MRM1 | −1.213 | 0 | 0 |
| SYT17 | −1.054 | 0.012 | 0.034 | ZSCAN10 | −1.528 | 0.016 | 0.043 |
| SCG3 | −1.555 | 0.005 | 0.017 | USHBP1 | −1.135 | 0.004 | 0.015 |
| TRPA1 | −1.639 | 0 | 0.002 | ACSBG2 | −1.941 | 0 | 0 |
| CALB1 | −1.14 | 0.018 | 0.049 | PKDREJ | −1.142 | 0.001 | 0.006 |
| POP1 | −1.077 | 0 | 0 | ULBP3 | −1.701 | 0.002 | 0.007 |
| PYCRL | −1.046 | 0 | 0 | IDO1 | −2.434 | 0 | 0.001 |
| LHB | −1.933 | 0 | 0.001 | CA6 | −1.099 | 0.01 | 0.03 |
| SARS2 | −1.027 | 0.003 | 0.012 | CKMT2 | −1.889 | 0 | 0.001 |
| OLFM2 | −1.003 | 0.007 | 0.023 | ZNF132 | −1.328 | 0 | 0 |
| FSD1 | −1.76 | 0 | 0.002 | SLC52A1 | −1.598 | 0.007 | 0.022 |
| SIGLEC8 | −1.726 | 0.001 | 0.004 | GUCY2D | −1.66 | 0 | 0.002 |
| LIM2 | −1.644 | 0.001 | 0.005 | ACY3 | −1.629 | 0.003 | 0.012 |
| NKG7 | −1.106 | 0 | 0 | MMACHC | −1.222 | 0 | 0 |
| ZNF175 | −1.023 | 0 | 0 | ZSWIM3 | −1.261 | 0 | 0.001 |
| DFNA5 | −1.091 | 0.001 | 0.003 | LGR6 | −1.323 | 0 | 0.001 |
| AGFG2 | −1.047 | 0 | 0 | SFTPD | −1.996 | 0 | 0.002 |
| SFRP4 | −1.687 | 0.002 | 0.007 | ADAM20 | −1.173 | 0.003 | 0.01 |
| PTGDS | −1.377 | 0 | 0 | KLRD1 | −1.178 | 0 | 0 |
| RGS9 | −1.186 | 0 | 0.002 | HNF1A | −1.419 | 0 | 0 |
| Drug Name | Connectivity Score | Drug Name | Connectivity Score |
|---|---|---|---|
| PIK-75 | −96.86 | PD-166793 | −72.03 |
| triptolide | −94.35 | AT-7519 | −71.73 |
| ZG-10 | −94 | staurosporine | −71.51 |
| ascorbic-acid | −93.85 | myriocin | −71.48 |
| PI-103 | −93.67 | bisindolylmaleimide-ix | −71.44 |
| chromomycin-a3 | −93.52 | PPT | −70.78 |
| dactinomycin | −93.15 | flufenamic-acid | −70.32 |
| KIN001-242 | −92.87 | carbetocin | −70.27 |
| idarubicin | −92.68 | azithromycin | −70.23 |
| CS-110266 | −92.62 | MEK1-2-inhibitor | −70.17 |
| TWS-119 | −92.57 | chloramphenicol | −69.88 |
| pirarubicin | −91.86 | parbendazole | −69.79 |
| daunorubicin | −90.64 | selumetinib | −69.46 |
| ER-27319 | −90.61 | L-655240 | −69.31 |
| tivozanib | −90.52 | 5-iodotubercidin | −69.13 |
| pazopanib | −90.29 | minoxidil | −69.12 |
| pidorubicine | −89.47 | hexylcaine | −69.03 |
| 9-methyl-5H-6-thia-4,5-diaza-chrysene-6,6-dioxide | −88.83 | byssochlamic-acid | −68.83 |
| saracatinib | −88.72 | methoxsalen | −68.82 |
| H-7 | −88.6 | rifampicin | −68.07 |
| alvocidib | −87.49 | metformin | −67.58 |
| CGP-60474 | −85.21 | BRL-37344 | −67.57 |
| veliparib | −84.65 | kavain | −67.5 |
| GDC-0941 | −83.94 | ampicillin | −66.96 |
| PP-2 | −82.97 | FR-122047 | −66.61 |
| AZD-7762 | −82.58 | mestranol | −66.44 |
| tofacitinib | −82.49 | ochratoxin-a | −66.43 |
| nornicotine | −82.4 | fluoxetine | −66.41 |
| tianeptine | −82.13 | KU-0063794 | −66.29 |
| tramadol | −81.78 | cobalt(II)-chloride | −65.87 |
| erismodegib | −81.69 | maackiain | −65.43 |
| fasudil | −80.93 | amitriptyline | −65.12 |
| fostamatinib | −80.81 | doxorubicin | −64.92 |
| benproperine | −80.22 | aminogenistein | −64.54 |
| WH-4023 | −79.94 | tenofovir | −64.24 |
| acamprosate | −79.27 | PP-30 | −64.09 |
| etilefrine | −78.89 | mofezolac | −63.55 |
| cosmosiin | −78.71 | dictamnine | −63.5 |
| DCPIB | −78.71 | ML-7 | −63.4 |
| fluspirilene | −77.9 | AS-601245 | −63.39 |
| W-12 | −77.66 | AM-580 | −63.24 |
| RO-90-7501 | −77.6 | bifemelane | −62.92 |
| cefoxitin | −77.59 | OSI-027 | −62.89 |
| lestaurtinib | −77.35 | benzatropine | −62.73 |
| MLN-8054 | −77.14 | n-formylmethionylalanine | −62.41 |
| dasatinib | −76.83 | caffeine | −62.15 |
| solanine | −76.15 | LY-364947 | −61.91 |
| erythrosine | −75.66 | canrenoic-acid | −61.84 |
| clopidogrel | −75.19 | SB-205607 | −61.71 |
| lamivudine | −75.11 | tipifarnib | −61.56 |
| AZ-628 | −73.85 | amoxicillin | −61.28 |
| bongkrek-acid | −73.81 | nitrofural | −61.08 |
| didanosine | −73.69 | JNJ-38877605 | −60.83 |
| carbidopa | −73.57 | olopatadine | −60.81 |
| EI-231 | −73.47 | mitoxantrone | −60.73 |
| MK-2206 | −73.33 | piretanide | −60.61 |
| TAK-715 | −73.06 | SB-202190 | −60.01 |
| ENMD-2076 | −72.41 |
| Drug Name | Overlap Score |
|---|---|
| CGP-60474 | 0.0729 |
| alvocidib | 0.0648 |
| BMS-387032 | 0.0567 |
| A443654 | 0.0526 |
| radicicol | 0.0486 |
| PHA-793887 | 0.0486 |
| daunorubicin | 0.0445 |
| epirubicin | 0.0445 |
| triptolide | 0.0445 |
| geldanamycin | 0.0445 |
| ER 27319 maleate | 0.0405 |
| KN-93 | 0.0405 |
| 16-hydroxytriptolide | 0.0405 |
| evodiamine | 0.0405 |
| parbendazole | 0.0405 |
| 656402-250MG | 0.0405 |
| linifanib | 0.0405 |
| AT-7519 | 0.0405 |
| mitoxantrone | 0.0405 |
| JNK-9L | 0.0405 |
References
- Keshavan, M.S.; Song, S.H. Neuroscience in Pictures: 3. Schizophrenia. Asian J. Psychiatry 2024, 102, 104278. [Google Scholar] [CrossRef] [Scilit]
- Velligan, D.I.; Rao, S. The epidemiology and global burden of schizophrenia. J. Clin. Psychiatry 2023, 84, 45094. [Google Scholar] [CrossRef] [Scilit]
- Lago, S.G.; Bahn, S. The druggable schizophrenia genome: From repurposing opportunities to unexplored drug targets. NPJ Genom. Med. 2022, 7, 25. [Google Scholar] [CrossRef] [Scilit]
- Giliberto, S.; Shishodia, R.; Nastruz, M.; Brar, C.; Bulathsinhala, S.; Terry, J.; Pemminati, S.; Shenoy, S.K. A Comprehensive Review of Novel FDA-Approved Psychiatric Medications (2018–2022). Cureus 2024, 16, C207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hasan, A.H.; Abid, M.A. Cobenfy (Xanomeline-Trospium Chloride): A New Frontier in Schizophrenia Management. Cureus 2024, 16, e71131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Truong, T.T.T.; Liu, Z.S.J.; Panizzutti, B.; Kim, J.H.; Dean, O.M.; Berk, M.; Walder, K. Network-based drug repurposing for schizophrenia. Neuropsychopharmacology 2024, 49, 983–992. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, S.; Roy, V. Repurposing drugs: An empowering approach to drug discovery and development. Drug Res. 2023, 73, 481–490. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, M.; Shen, W.; Li, W.; Xue, Y.; Zou, S.; Xu, D.; Wang, W. Topoisomerase 3β is the major topoisomerase for mRNAs and linked to neurodevelopment and mental dysfunction. Nucleic Acids Res. 2017, 45, 2704–2713. [Google Scholar] [CrossRef] [Scilit]
- Meera, M.; Sekar, S.; Mahatao, R. A novel approach for drug discovery-drug repurposing. Natl. J. Physiol. Pharm. Pharmacol. 2022, 12, 546–551. [Google Scholar] [CrossRef] [Scilit]
- Khan, S.; Agnihotri, J.; Patil, S.; Khan, N. Drug repurposing: A futuristic approach in drug discovery. J. Pharm. Biol. Sci. 2023, 11, 66–69. [Google Scholar] [CrossRef] [Scilit]
- Biswal, S.; Mallick, B. Unlocking the potential of signature-based drug repurposing for anticancer drug discovery. Arch. Biochem. Biophys. 2024, 761, 110150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sahay, S.; Henkel, N.D.; Vargas, C.F.-A.; McCullumsmith, R.E.; O’Donovan, S.M. Activity of protein kinase a in the frontal cortex in schizophrenia. Brain Sci. 2023, 14, 13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takase, S.; Liao, J.; Liu, Y.; Tanaka, R.; Miyagawa, Y.; Sawahata, M.; Sobue, A.; Mizoguchi, H.; Nagai, T.; Kaibuchi, K.; et al. Antipsychotic-like effects of fasudil, a Rho-kinase inhibitor, in a pharmacologic animal model of schizophrenia. Eur. J. Pharmacol. 2022, 931, 175207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Banerjee, A.; Wang, H.-Y.; E Borgmann-Winter, K.; MacDonald, M.L.; Kaprielian, H.; Stucky, A.; Kvasic, J.; Egbujo, C.; Ray, R.; Talbot, K.; et al. Src kinase as a mediator of convergent molecular abnormalities leading to NMDAR hypoactivity in schizophrenia. Mol. Psychiatry 2014, 20, 1091–1100. [Google Scholar] [CrossRef] [Scilit]
- Feng, Y.; Shen, J.; He, J.; Lu, M. Schizophrenia and cell senescence candidate genes screening, machine learning, diagnostic models, and drug prediction. Front. Psychiatry 2023, 14, 1105987. [Google Scholar] [CrossRef] [Scilit]
- Fond, G.; Lançon, C.; Korchia, T.; Auquier, P.; Boyer, L. The role of inflammation in the treatment of schizophrenia. Front. Psychiatry 2020, 11, 160. [Google Scholar] [CrossRef] [Scilit]
- Schweiger, A.; Diniz, B.; Nicol, G.; Schweiger, J.; Dasklakis-Perez, A.E.; Lenze, E.J. Protocol for a pilot clinical trial of the senolytic drug combination Dasatinib Plus Quercetin to mitigate age-related health and cognitive decline in mental disorders. F1000Research 2025, 13, 1072. [Google Scholar] [CrossRef] [Scilit]
- Huang, L.; Sperlágh, B. Caffeine consumption and schizophrenia: A highlight on adenosine receptor–independent mechanisms. Curr. Opin. Pharmacol. 2021, 61, 106–113. [Google Scholar] [CrossRef] [Scilit]
- Gao, L.; Gao, S.; Shan, H.; Wu, Y.; Zhou, Q. GSK-3β inhibitor TWS119 promotes neuronal differentiation after hypoxic-ischemic brain damage in neonatal rats. NeuroReport 2024, 35, 200–207. [Google Scholar] [CrossRef] [Scilit]
- Kwon, J.-T.; Jung, K. Tianeptine Affects the Improvement of Behavioral Defects, such as Schizophrenia, Caused by Maternal Immune Activation in the Mice Offspring. Central Nerv. Syst. Agents Med. Chem. 2023, 23, 157–166. [Google Scholar] [CrossRef] [Scilit]
- Rawas, R.E.; Amaral, I.M.; Hofer, A. The Anti-social Brain in Schizophrenia: A role of CAMKII? Front. Psychiatry 2022, 13, 868244. [Google Scholar] [CrossRef] [Scilit]
- Enriquez-Barreto, L.; Morales, M. The PI3K signaling pathway as a pharmacological target in Autism related disorders and Schizophrenia. Mol. Cell. Ther. 2016, 4, 2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chua, H.C.; Christensen, E.T.; Hoestgaard-Jensen, K.; Hartiadi, L.Y.; Ramzan, I.; Jensen, A.A.; Absalom, N.L.; Chebib, M. Kavain, the major constituent of the anxiolytic kava extract, potentiates GABAA receptors: Functional characteristics and molecular mechanism. PLoS ONE 2016, 11, e0157700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Puranen, A.; Koponen, M.; Lähteenvuo, M.; Tanskanen, A.; Tiihonen, J.; Taipale, H. Real-world effectiveness of antidepressant use in persons with schizophrenia: Within-individual study of 61,889 subjects. Schizophrenia 2023, 9, 34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kjoe, P.R.L.M.; van der Wall, E.; Schagen, S.B. Endocrine Therapy with or Without CDK4/6 Inhibitors in Women with Hormone-receptor Positive Breast Cancer: What do we Know About the Effects on Cognition? Clin. Breast Cancer 2021, 22, 191–199. [Google Scholar] [CrossRef] [Scilit]
- Yang, L.; Liu, F.; Yuan, Q.; Zhu, J.; Wang, W.; Li, X.; He, J. Fluoxetine attenuates prepulse inhibition deficit induced by neonatal administration of MK-801 in mice. NeuroReport 2020, 31, 1128–1133. [Google Scholar] [CrossRef] [Scilit]
- Feng, T.; Tripathi, A.; Pillai, A. Inflammatory Pathways in Psychiatric Disorders: The Case of Schizophrenia and Depression. Curr. Behav. Neurosci. Rep. 2020, 7, 128–138. [Google Scholar] [CrossRef] [Scilit]
- Alijevic, O.; McHugh, D.; Rufener, L.; Mazurov, A.; Hoeng, J.; Peitsch, M. An electrophysiological characterization of naturally occurring tobacco alkaloids and their action on human α4β2 and α7 nicotinic acetylcholine receptors. Phytochemistry 2019, 170, 112187. [Google Scholar] [CrossRef] [Scilit]
- Abhijnhan, A.; E Adams, C.; David, A.; Ozbilen, M. Depot fluspirilene for schizophrenia. Cochrane Database Syst. Rev. 2007, 2012, CD001718. [Google Scholar] [CrossRef] [Scilit]
- Battini, V.; Cirnigliaro, G.; Leuzzi, R.; Rissotto, E.; Mosini, G.; Benatti, B.; Pozzi, M.; Nobile, M.; Radice, S.; Carnovale, C.; et al. The potential effect of metformin on cognitive and other symptom dimensions in patients with schizophrenia and antipsychotic-induced weight gain: A systematic review, meta-analysis, and meta-regression. Front. Psychiatry 2023, 14, 1215807. [Google Scholar] [CrossRef] [Scilit]
- Piłat, P.; Nikel, K.; Smolarczyk, J.; Piegza, M. The use of ascorbic acid in adjunctive treatment for Schizophrenia—Current state of knowledge. Life 2024, 14, 828. [Google Scholar] [CrossRef] [Scilit]
- Saranaruk, P.; Kariya, R.; Sittithumcharee, G.; Boueroy, P.; Boonmars, T.; Sawanyawisuth, K.; Wongkham, C.; Wongkham, S.; Okada, S.; Vaeteewoottacharn, K. Chromomycin A3 suppresses cholangiocarcinoma growth by induction of S phase cell cycle arrest and suppression of Sp1-related anti-apoptotic proteins. Int. J. Mol. Med. 2020, 45, 1005–1016. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kesby, J.P.; Eyles, D.W.; McGrath, J.J.; Scott, J.G. Dopamine, psychosis and schizophrenia: The widening gap between basic and clinical neuroscience. Transl. Psychiatry 2018, 8, 30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gangadhar, N.N.; Rao, N.P. Action of antipsychotics. In Brain Mapping; Toga, A.W., Ed.; Academic Press: Amsterdam, The Netherlands, 2015; pp. 937–941. [Google Scholar] [CrossRef] [Scilit]
- Kellendonk, C. Modeling excess striatal D2 receptors in mice. Prog. Brain Res. 2009, 179, 59–65. [Google Scholar] [PubMed]
- Peng, A.; Chai, J.; Wu, H.; Bai, B.; Yang, H.; He, W.; Zhao, Y. New therapeutic targets and drugs for schizophrenia beyond dopamine D2 receptor antagonists. Neuropsychiatr. Dis. Treat. 2024, 20, 607–620. [Google Scholar] [CrossRef] [Scilit]
- Sun, N.; Zhang, X.; Guo, S.; Le, H.T.; Zhang, X.; Kim, K.-M. Molecular mechanisms involved in epidermal growth factor receptor-mediated inhibition of dopamine D3 receptor signaling. Biochim. Et Biophys. Acta (BBA)-Mol. Cell Res. 2018, 1865, 1187–1200. [Google Scholar] [CrossRef] [Scilit]
- Sotoyama, H.; Namba, H.; Tohmi, M.; Nawa, H. Schizophrenia animal modeling with epidermal growth factor and its homologs: Their connections to the inflammatory pathway and the dopamine system. Biomolecules 2023, 13, 372. [Google Scholar] [CrossRef] [Scilit]
- Perrone, M.G.; Centonze, A.; Miciaccia, M.; Ferorelli, S.; Scilimati, A. Cyclooxygenase inhibition safety and efficacy in inflammation-based psychiatric disorders. Molecules 2020, 25, 5388. [Google Scholar] [CrossRef] [Scilit]
- Müller, N. COX-2 Inhibitors, aspirin, and other potential anti-inflammatory treatments for psychiatric disorders. Front. Psychiatry 2019, 10, 375. [Google Scholar] [CrossRef] [Scilit]
- McKinnon, P.J. Topoisomerases and the regulation of neural function. Nat. Rev. Neurosci. 2016, 17, 673–679. [Google Scholar] [CrossRef] [Scilit]
- Cheng, L.; Liu, J.; Chen, Z. The histaminergic system in neuropsychiatric disorders. Biomolecules 2021, 11, 1345. [Google Scholar] [CrossRef] [Scilit]
- de Sousa, T.R.; Ribeiro, M.; Novais, F. Assessment of Innovative Pharmacological Targets in Schizophrenia. Curr. Treat. Options Psychiatry 2024, 11, 203–217. [Google Scholar] [CrossRef] [Scilit]
- Liu, Z.; Fang, H.; Reagan, K.; Xu, X.; Mendrick, D.L.; Slikker, W., Jr.; Tong, W. In silico drug repositioning–what we need to know. Drug Discov. Today 2013, 18, 110–115. [Google Scholar] [CrossRef] [Scilit]
- Souri, E.A.; Chenoweth, A.; Karagiannis, S.N.; Tsoka, S. Drug repurposing and prediction of multiple interaction types via graph embedding. BMC Bioinform. 2023, 24, 202. [Google Scholar] [CrossRef] [Scilit]
- Papikinos, T.; Krokidis, M.G.; Vrahatis, A.; Vlamos, P.; Exarchos, T.P. Signature-Based Computational Drug Repurposing for Amyotrophic Lateral Sclerosis. In Worldwide Congress on “Genetics, Geriatrics and Neurodegenerative Diseases Research”; Springer International Publishing: Cham, Switzerland, 2022; pp. 201–211. [Google Scholar]
- Karatzas, E.; Kolios, G.; Spyrou, G.M. An application of computational drug repurposing based on transcriptomic signatures. In Computational Methods for Drug Repurposing; Springer: New York, NY, USA, 2019; pp. 149–177. [Google Scholar]
- Barrett, T.; Wilhite, S.E.; Ledoux, P.; Evangelista, C.; Kim, I.F.; Tomashevsky, M.; Marshall, K.A.; Phillippy, K.H.; Sherman, P.M.; Holko, M.; et al. NCBI GEO: Archive for functional genomics data sets—Update. Nucleic Acids Res. 2012, 41, D991–D995. [Google Scholar] [CrossRef] [Scilit]
- Wang, F.; Fan, Y.; Li, Y.; Zhou, Y.; Wang, X.; Zhu, M.; Chen, X.; Xue, Y.; Shen, C. Identification of differentially expressed genes of blood leukocytes for Schizophrenia. Front. Genet. 2024, 15, 1398240. [Google Scholar] [CrossRef] [Scilit]
- Song, X.; Liu, Y.; Pu, J.; Gui, S.; Zhong, X.; Chen, X.; Chen, W.; Chen, X.; Chen, Y.; Wang, H.; et al. Transcriptomics analysis reveals shared pathways in peripheral blood mononuclear cells and brain tissues of patients with schizophrenia. Front. Psychiatry 2021, 12, 716722. [Google Scholar] [CrossRef] [Scilit]
- Love, M.I.; Huber, W.; Anders, S. Moderated estimation of fold change and dispersion for RNA-seq data with DESeq2. Genome Biol. 2014, 15, 550. [Google Scholar] [CrossRef] [Scilit]
- Subramanian, A.; Narayan, R.; Corsello, S.M.; Peck, D.D.; Natoli, T.E.; Lu, X.; Gould, J.; Davis, J.F.; Tubelli, A.A.; Asiedu, J.K.; et al. A next generation connectivity map: L1000 platform and the first 1,000,000 profiles. Cell 2017, 171, 1437–1452.e17. [Google Scholar] [CrossRef] [Scilit]
- Duan, Q.; Reid, S.P.; Clark, N.R.; Wang, Z.; Fernandez, N.F.; Rouillard, A.D.; Readhead, B.; Tritsch, S.R.; Hodos, R.; Hafner, M.; et al. L1000CDS2: LINCS L1000 characteristic direction signatures search engine. NPJ Syst. Biol. Appl. 2016, 2, 16015. [Google Scholar] [CrossRef] [Scilit]
- Lim, N.; Pavlidis, P. Evaluation of connectivity map shows limited reproducibility in drug repositioning. Sci. Rep. 2021, 11, 17624. [Google Scholar] [CrossRef] [Scilit]
- Lee, B.K.B.; Cheong, S.C.; Tan, A.C. Expanding the Connectivity Map Concept as the Functional Look-Up Table for Systems Biology. Adv. Mol. Pathol. 2019, 2, 201–213. [Google Scholar] [CrossRef] [Scilit]
- CONNECTOPEDIA. (n.d.). Available online: https://clue.io/connectopedia/connectivity_scores (accessed on 15 March 2025).
- Karatzas, E.; Zamora, J.E.; Athanasiadis, E.; Dellis, D.; Cournia, Z.; Spyrou, G.M. ChemBioServer 2.0: An advanced web server for filtering, clustering and networking of chemical compounds facilitating both drug discovery and repurposing. Bioinformatics 2020, 36, 2602–2604. [Google Scholar] [CrossRef] [Scilit]
- Wang, Z.; Lachmann, A.; Keenan, A.B.; Ma’ayan, A. L1000FWD: Fireworks visualization of drug-induced transcriptomic signatures. Bioinformatics 2018, 34, 2150–2152. [Google Scholar] [CrossRef] [Scilit]

| Group 1 | Group 2 | Group 3 | Group 4 | Group 5 | Group 6 |
|---|---|---|---|---|---|
| H-7 | saracatinib | tianeptine | kavain | metformin | ascorbic acid |
| fasudil | fostamatinib | KN-93 | amitriptyline | chromomycin-a3 | |
| tofacitinib | PIK-75 | alvocidib | |||
| dasatinib | fluoxetine | ||||
| caffeine | ampicillin | ||||
| TWS-119 | nornicotine | ||||
| PP-2 | fluspirilene |
| Drug Name | Predicted MOA | Probability |
|---|---|---|
| H-7 | Dopamine receptor antagonist | 0.6717 |
| fasudil | Dopamine receptor antagonist | 0.7290 |
| saracatinib | EGFR inhibitor | 0.9684 |
| fostamatinib | EGFR inhibitor | 0.3228 |
| dasatinib | Aurora kinase inhibitor | 0.3754 |
| TWS-119 | Dopamine receptor antagonist | 0.4940 |
| PP-2 | Cyclooxygenase inhibitor | 0.2409 |
| KN-93 | EGFR inhibitor | 0.2617 |
| PIK-75 | Cyclooxygenase inhibitor | 0.2910 |
| kavain | Cyclooxygenase inhibitor | 0.4005 |
| amitriptyline | Histamine receptor antagonist | 0.9347 |
| alvocidib | Topoisomerase inhibitor | 0.4321 |
| fluoxetine | Histamine receptor antagonist | 0.5377 |
| fluspirilene | Dopamine receptor antagonist | 0.9649 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).
Share and Cite
Chalkioti, M.; Papikinos, T.; Krokidis, M.G.; Vlamos, P.; Exarchos, T.P. Leveraging Gene Expression Data for Drug Repurposing in Schizophrenia: A Signature Reversion Approach. Drugs Drug Candidates 2025, 4, 49. https://doi.org/10.3390/ddc4040049
Chalkioti M, Papikinos T, Krokidis MG, Vlamos P, Exarchos TP. Leveraging Gene Expression Data for Drug Repurposing in Schizophrenia: A Signature Reversion Approach. Drugs and Drug Candidates. 2025; 4(4):49. https://doi.org/10.3390/ddc4040049
Chicago/Turabian StyleChalkioti, Maria, Thomas Papikinos, Marios G. Krokidis, Panagiotis Vlamos, and Themis P. Exarchos. 2025. "Leveraging Gene Expression Data for Drug Repurposing in Schizophrenia: A Signature Reversion Approach" Drugs and Drug Candidates 4, no. 4: 49. https://doi.org/10.3390/ddc4040049
APA StyleChalkioti, M., Papikinos, T., Krokidis, M. G., Vlamos, P., & Exarchos, T. P. (2025). Leveraging Gene Expression Data for Drug Repurposing in Schizophrenia: A Signature Reversion Approach. Drugs and Drug Candidates, 4(4), 49. https://doi.org/10.3390/ddc4040049