Article

The Preclinical-to-Clinical Empathy Dip: Early Findings from a Longitudinal Study of Medical Students


by
Angelina Van Dyne
1,2,*,
Nicole P. Mirabadi
2,3,4,*,
Federica Klaus
2,4 and
Lisa T. Eyler
2,3,4
1
Joint Doctoral Program in Clinical Psychology, San Diego State University/University of California, San Diego, CA 92120, USA
2
T. Denny Sanford Institute for Empathy and Compassion, University of California, San Diego, CA 92037, USA
3
University of California San Diego School of Medicine, La Jolla, CA 92093, USA
4
Department of Psychiatry, University of California, San Diego, CA 92121, USA
*
Authors to whom correspondence should be addressed.
Int. Med. Educ. 2026, 5(2), 56; https://doi.org/10.3390/ime5020056
Submission received: 12 May 2026 / Revised: 12 June 2026 / Accepted: 16 June 2026 / Published: 18 June 2026

Abstract

Background: Empathy, compassion, self-compassion, and resilience are essential to medical practice and education. While some evidence shows that these traits may decline during medical school, few studies have examined all these capacities in the same cohorts or trends within an academic year. This study examines first-year longitudinal findings on cohort and within-year changes in these constructs among medical students. Methods: 98 students (58.2% female; Mage = 26.34 (2.86); 37.8% White; MS1 25.5%, MS2 25.5%, MS3 20.4%, MS4 26.5%) from a large US school participated in at least one wave of an online survey distributed 4 times during the 2023–2024 academic year. Validated measures assessed empathy (IRI), compassion (SCBCS), self-compassion (Neff SCS), and resilience (CD-RISC-10). Linear mixed models analyzed between-cohort differences over time with gender and race/ethnicity as covariates. Results: Compared to MS4 students, MS2 and MS3 students had significantly lower cognitive empathy and self-compassion, with marginally lower compassion and higher resilience (p = 0.06). Women reported higher compassion toward others but lower self-compassion and resilience than men. Conclusions: Lower empathy and compassion were observed as early as the second year of medical school, suggesting erosion factors, such as academic pressure and standardized testing, may impact trainees earlier than previously reported.

1. Introduction

Empathy is the ability to perceive, feel, and understand another person’s emotions, while compassion is the emotional response to the individual’s pain or suffering and involves a genuine desire to help [1]. Empathy and compassion are essential to the practice of medicine and providing high-quality patient care [2,3]. As such, empathy and compassion are part of the core competencies for medical students outlined by the Association of American Medical Colleges (AAMC) [4]. Specifically, AAMC guidelines describe the expectations for students to develop skills in recognizing and acknowledging others’ distress, feelings, and perspectives, as well as exhibiting a motivation to help and reduce others’ suffering [4].
In clinical settings, there is empirical evidence to suggest that empathic and compassionate care is associated with improved outcomes for patients [1,5]. Even for health care providers themselves, exhibiting empathy and compassion towards their patients has been shown to protect against burnout and increase resilience [6]. Despite copious research supporting the importance of empathy, compassion, self-compassion, and resilience in patient care and provider well-being, there is evidence to suggest that health care is experiencing a compassion crisis as doctors are missing the majority of opportunities to show compassion in patient encounters [1].
There is evidence to suggest that empathy decline may occur during medical training. Among medical students, studies have demonstrated that empathy tends to be lower in the clinical years when compared to the preclinical years [7]. According to Chen et al., empathy levels in medical students increased from the beginning of medical school through the end of the preclinical years. This observation was followed by a steep drop in empathy during the third year of medical school (i.e., first year of clinical rotations) and continued to decline up through graduation [7]. It is postulated that empathy and compassion decline in medical students during high-stress periods, especially in the third year of medical education, due to high academic and clinical demands [8]. However, much of the research remains cross-sectional, and longitudinal trends remain understudied [9]. Thus, there is a need for more longitudinal studies, which would follow the same cohort of medical students throughout their medical education and observe changes in their empathy levels at each stage [8,10]. Additionally, there is great variability not only between academic years and medical school stages, but also within each year due to different stressors. Therefore, designs that implement multiple measurements throughout the year may yield more representative data for the medical student experience.
There has been much research interest in preserving empathy and compassion among healthcare providers and medical students. Several protective factors against empathy fatigue have been identified. Among them, self-compassion and resilience have been found to be related to reduced emotional overwhelm and better well-being among physicians [11,12]. To our knowledge, none of the previous cross-sectional or longitudinal studies examined differences across the years of medical school in self-compassion or resilience. Examining how these variables may or may not change in concert with each other is important for understanding how to intervene and design curricula aimed at mitigating any declines. Additionally, a systematic review showed that there is growing incorporation of empathy and compassion curricula in medical education [13]. However, the outcomes were heterogeneous, likely reflecting the lack of standardization of empathy and compassion training in healthcare. One important need, therefore, is to understand the nature of changes in empathy and compassion across years of medical school in order to best target curricula aimed at them for the time periods when they could be most impactful. It can also provide the necessary evidence base for creating effective curricula aimed at increasing these attributes among medical learners.
Given the reported decline in empathy and compassion during medical school and the potential deleterious consequences of this decline for both patients and providers, understanding factors that contribute to this trend remains an important issue that has not been sufficiently addressed. We aim to contribute to existing literature by undertaking a longitudinal cohort study at a medical school on the West Coast of the US with multiple measurements each year to examine cohort differences and, eventually, to allow for measurement of within-person changes across the 4 years of medical school in empathy, compassion, self-compassion, and resilience. This study has the potential to uncover developmental empathy and compassion trends while controlling for potential cohort effects, which can identify critical points in medical training when interventions are most appropriate. We also plan to investigate protective factors such as dedicated empathy and compassion curricula and attributes such as resilience and self-compassion. In this preliminary analysis of the first year of data from the ongoing study, we examined cohort differences between first-, second-, third- and fourth-year medical students in their self-reported levels of these attitudes measured four times across one academic year. These early results present an opportunity to establish a foundation for and provide early insights into empathy and compassion changes. We hypothesized that third-year students would have lower levels of empathy, compassion, self-compassion, and resilience compared to other cohorts throughout the academic year.

2. Materials and Methods

2.1. Setting

The institutional setting was a four-year university-affiliated MD-granting medical school with an integrated health system on the West Coast of the United States. The cohort sizes were as follows: MS1–107, MS2–107, MS3–108, and MS4–80, with a total of 402 students across 4 cohorts. The school follows the standard U.S. graduate-entry medical school model, wherein the first two years of training (MS1, MS2) are largely devoted to preclinical training and fulfilling core academic training requirements, and in the remaining two years (MS3, MS4), students complete clinical clerkships in affiliated medical centers and clinics.

2.2. Recruitment and Retention

The target population for this study was U.S. medical students. The accessible population consisted of students enrolled at a single medical school during the 2023–2024 academic year. The student list was provided by the registrar’s office of a West Coast medical school. Eligible students included those enrolled in any of the four cohorts of the medical school. Exclusion criteria were students on a gap year and those enrolled in joint MD/PhD and MD/MPH programs due to differences in curricula and clinical practice. An initial sample of 35 students per cohort was generated using a random number generator, and the recruitment email was sent to selected students. Recruitment continued until a target enrollment of at least 25 participants per cohort was achieved. If fewer than 25 participants per cohort were enrolled during the initial recruitment phase, an additional round of randomization and recruitment was performed. This sample size was determined by feasibility and is comparable to those of other similar published studies based in the U.S. [14], with the expectation that the sample size will increase over time with additional years of follow-up. A total of 202 recruitment emails were sent, and 103 students (MS1–MS4) consented to participate in the study, resulting in a 51.0% response rate. Online surveys were distributed during four (4) rounds of measurement during the 2023–2024 academic year (approximately once every quarter, in September, December, March, and May). Participation rates were as follows: 78 (79.6%) students completed the first survey, 83 (84.7%) completed the second, 80 (81.6%) completed the third, and 77 (78.6%) completed the fourth round. Surveys were administered via Qualtrics. Each round, a reminder email containing a link to complete the survey was sent to participating students, with up to three reminders. Every participant was assigned a code to track their responses longitudinally and protect their confidentiality. Participants were asked to provide their code at the beginning of each survey. Data were stored in a secure university server. Each student received a $25 gift card for each round of participation, with a maximum earning of $100 for participating in all four rounds. The study was deemed exempt from approval by the UC San Diego Institutional Review Board (IRB).

2.3. Participants

A total of 103 students consented to participate in the study, and 98 completed at least one survey round.

2.4. Measures

In addition to the above-reported demographic questions, the survey contained four validated questionnaires assessing empathy, compassion, self-compassion, and resilience. No pilot testing occurred prior to primary data collection. McDonald’s Omega was used to calculate the internal consistency of the scales used in the study [15]. The omega coefficient is calculated based on factor loadings of the items in a scale and is a preferred method of calculating internal consistency when the assumption of tau-equivalence is not supported [16].

2.5. Cognitive Empathy/Perspective Taking

The Interpersonal Reactivity Index (IRI) is a 28-item measure of empathy that consists of four subscales: Perspective-Taking, Empathic Concern, Personal Distress, and Fantasy [17]. For this study, we utilized the Perspective-Taking subscale to measure cognitive empathy [17]. The subscale consists of 7 items rated on a 5-point Likert scale (0 (does not describe me very well) to 4 (describes me very well)), with a total score ranging from 0 to 28. A sample item includes “I try to look at everybody’s side of a disagreement before I make a decision.” Higher scores on this subscale indicate greater cognitive empathy and adoption of others’ perspectives [17]. The internal consistency of the subscale in the present study ranged from w = 0.78 to w = 0.88 across data waves. The use of IRI was validated among medical students with adequate reliability and validity [18].

2.6. Compassion

Compassion was measured using the Santa Clara Brief Compassion Scale (SCBCS), a 5-item measure assessing an individual’s compassion toward others [19]. SCBCS measures different dimensions of compassion, such as tender feelings toward others and compassionate love [19]. A sample item of the measure is “When I hear about someone (a stranger) going through a difficult time, I feel a great deal of compassion for him or her.” Each of the scale’s items is scored on a Likert-type scale from 1 to 7, resulting in a total score ranging from 1 to 35 [19]. The scale has demonstrated robust internal consistency, as well as convergent and divergent validity [19]. The internal consistency of SCBCS in the present sample ranged from w = 0.87 to 0.94 across waves of data. The use of SCBCS was shown to have good convergent validity in medical settings [20].

2.7. Self-Compassion

To measure self-compassion, we used the Neff Self-Compassion Scale (SCS) [21]. The SCS is a widely used self-report measure of self-compassion validated in multiple populations [22]. It consists of 26 items rated on a 5-point Likert scale (1 (almost never) to 5 (almost always)), indicating how often responders engage in self-compassion-related behaviors. The items comprise six subscales that reflect positive and negative dimensions of self-compassion: Self-Kindness, Self-Judgment, Common Humanity, Isolation, Mindfulness, and Overidentification. Both subscale and global scores are calculated, with higher scores reflecting higher levels of self-compassion. To calculate the total score, first, the mean of each subscale is computed. Then the average of all six subscales is derived to represent the total score. Therefore, the scores range from 1 to 5. The psychometric properties of the scale are strong, with high internal consistency, validity, and test–retest reliability reported [22]. In the present study, the internal consistency of the scale ranged from w = 0.94 to w = 0.96 across waves of data. The use of the scale has been validated among medical students with good internal consistency and acceptable structural validity [23].

2.8. Resilience

Resilience was measured using the Connor-Davidson Resilience Scale, a 10-item version (CD-RISC-10) [24]. Items reflect an individual’s ability to cope with adversity and stress, with items such as “I can deal with whatever comes my way.” The scale has demonstrated good internal consistency, construct, and convergent validity in general and clinical samples [25]. Each item is rated on a 5-point Likert scale from 0 (Not true at all) to 4 (True nearly all the time). The total score ranges from 0 to 40. The internal consistency of the scale ranged from w = 0.88 to w = 0.93 across data waves. The use of the scale among healthcare learners was validated with good internal consistency and adequate structural validity [26].

2.9. Statistical Analysis

To estimate the trajectories of empathy and compassion over time (within the first year of observation) and compare these across different cohorts, we used linear mixed-effects models (LMM) with a random intercept for each participant to account for repeated measures. These models are particularly appropriate for longitudinal data with repeated measures due to their ability to accommodate missing data under the missing at random (MAR) assumption, while using all available data points, and to incorporate a realistic correlation and variance structures for within-person observations in a longitudinal design [27]. Four separate analyses were performed with self-compassion, compassion, cognitive empathy, and resilience as outcome variables and cohort (MS1, MS2, MS3, or MS4) as the main independent variable. Total scale scores were used for all outcome variables. All models also included fixed effects for the covariates of gender, race/ethnicity, and a time variable of survey round. These covariates were chosen because of previous literature showing gender and racial/ethnic differences in empathy, self-compassion, and resilience, as well as an association between these constructs and academic load, which changes throughout the year [28,29,30,31,32]. Visual inspection of residual and Q-Q plots of the models did not reveal any significant deviations from normality, and no evidence of heteroscedasticity was detected. Full information maximum likelihood (FIML) was used to handle missing data in our analysis, which allowed us to incorporate all available data points to estimate parameters.
Due to an error, the Santa Clara Brief Compassion Scale was administered on a 1–5 Likert scale instead of a 1–7 scale during Round 1. Therefore, the Round 1 data was rescaled using the following formula: New   Score = Old   Score 1 6 4 + 1 . Sensitivity analysis was performed with Rounds 2–4 data, confirming the results of the rescaling.
LMM and descriptive analyses were performed using RStudio (Version 2024.12.1+563). LMM analyses were performed using the lme4 package. Pairwise comparisons between cohorts were performed using estimated marginal means derived via the emmeans package. Effect size was estimated via partial η2 using the effectsize package. Tukey’s adjustment was used for all pairwise comparisons. Statistical significance was set at p ≤ 0.05, while results between 0.05 < p < 0.10 were considered marginally significant after the adjustment for multiple comparisons. The following benchmarks were used for effect size interpretations: 0.01—small; 0.06—medium; 0.14—large [33].

3. Results

3.1. Descriptive Characteristics

We present the cohort distribution and demographic characteristics of the sample in Table 1.

3.2. Cognitive Empathy/Perspective Taking

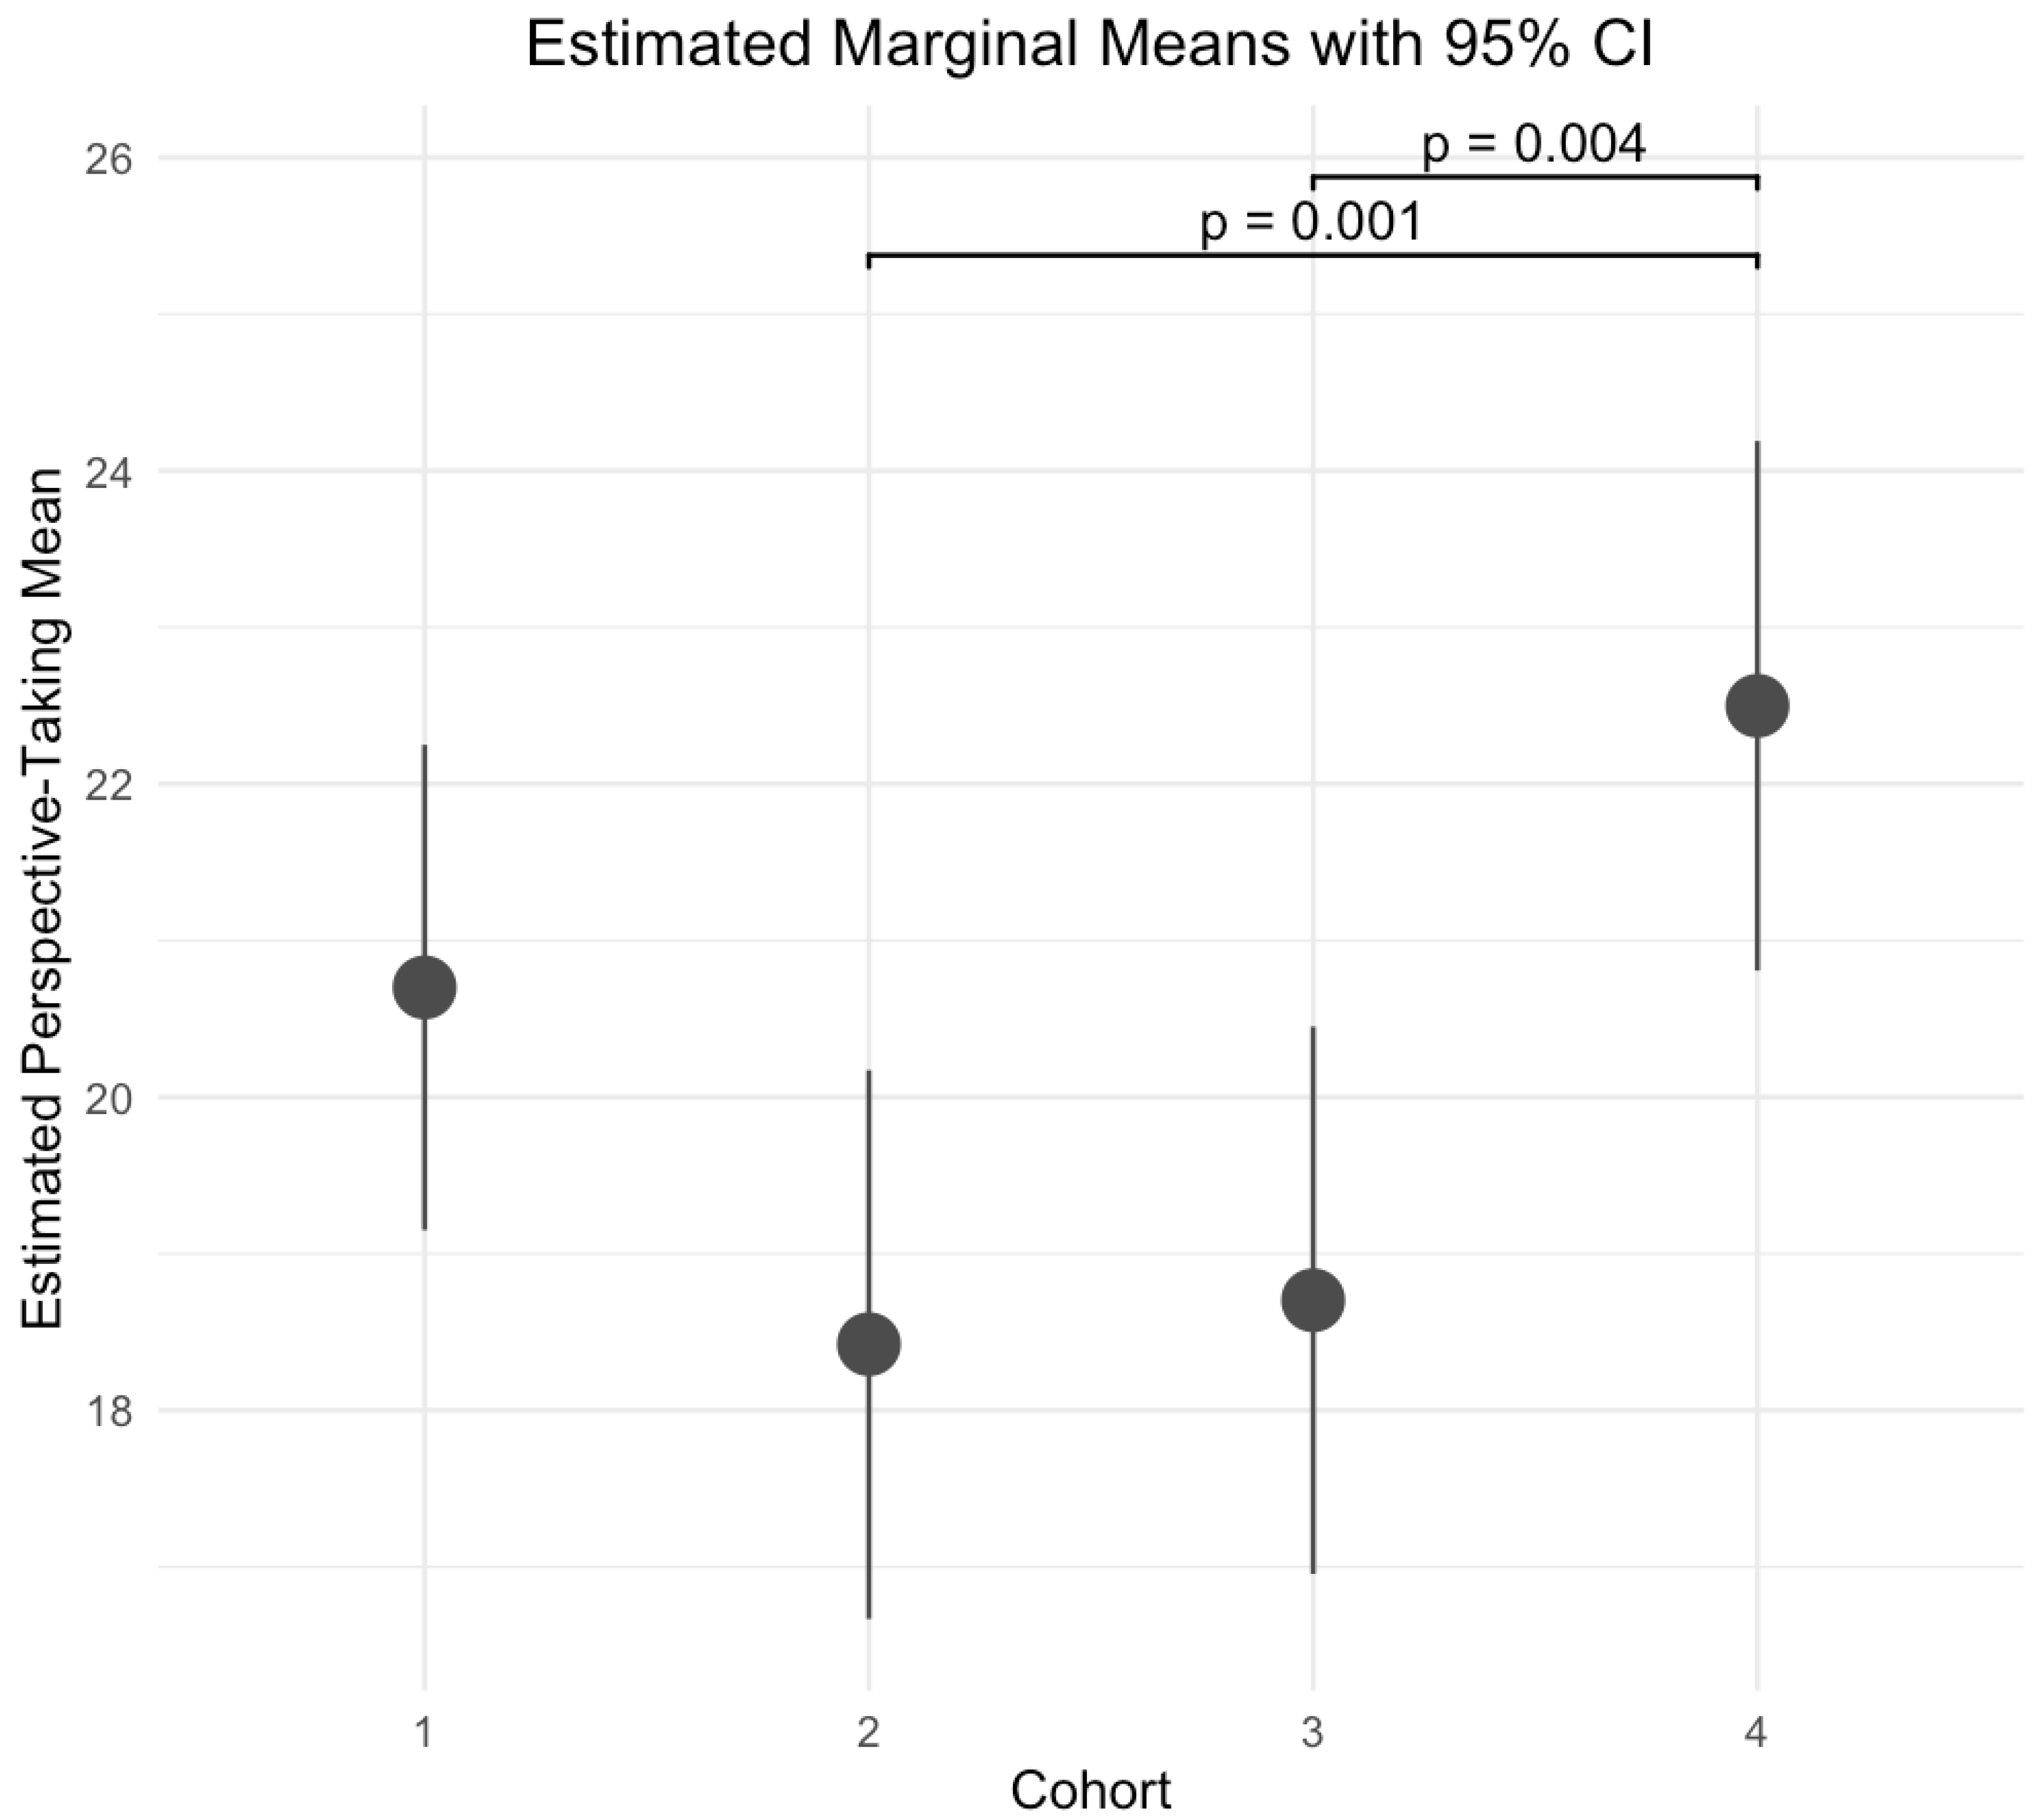
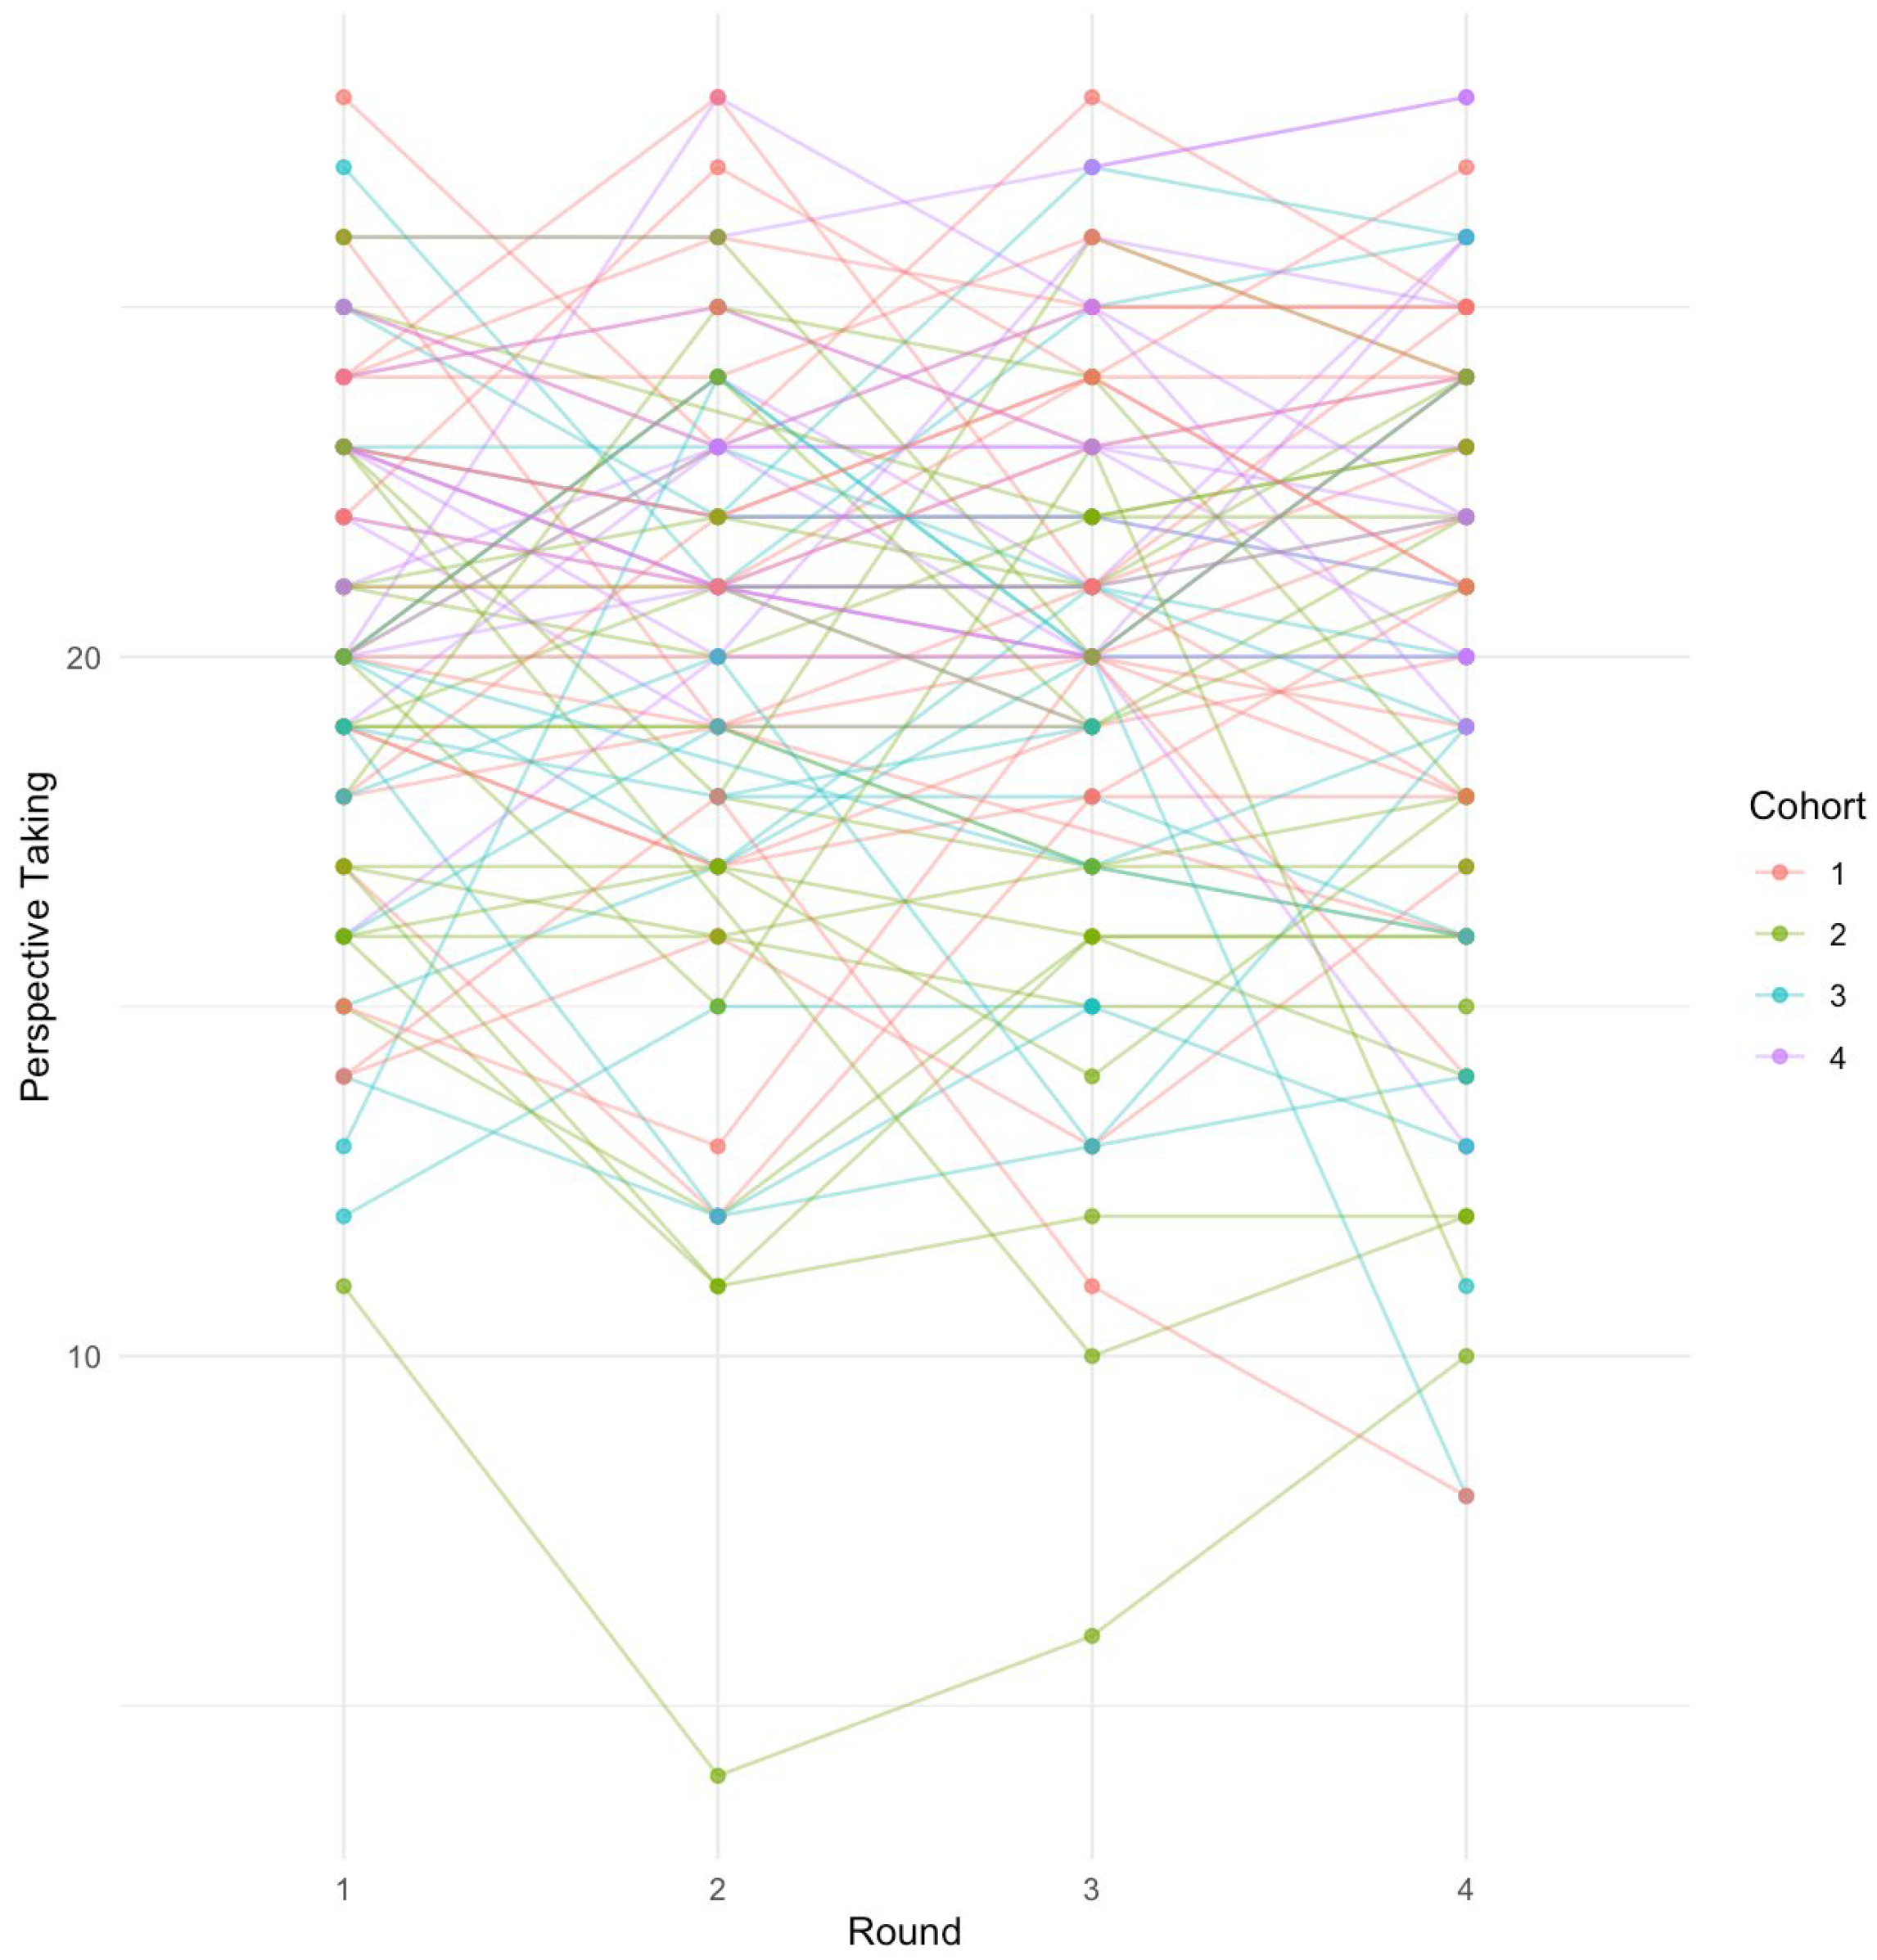
The individual trajectories of the cognitive empathy scores are presented in Figure A1. There was no significant relationship of gender (F (1, 87.47) = 0.18, p = 0.68, η2 = 0.002), race/ethnicity (F (4, 86.72) = 0.35, p = 0.88, η2 = 0.02), or measurement round (F (3, 222.96) = 0.20, p = 0.90, η2 = 0.003) with cognitive empathy. Cohort was significantly associated (F (3, 87.33) = 6.52, p = 0.0005; η2 = 0.18). Figure 1 shows that cognitive empathy was significantly lower among MS2 (M = 18.4, 95% CI [16.7; 20.2], t (86.8) = −3.93, adjusted p = 0.001) and MS3 students (M = 18.7, 95% CI [17.0; 20.5], t (88.3) = −3.50, adjusted p = 0.004) compared to MS4 students (M = 22.5, 95% CI [20.8; 24.2]).

3.3. Compassion

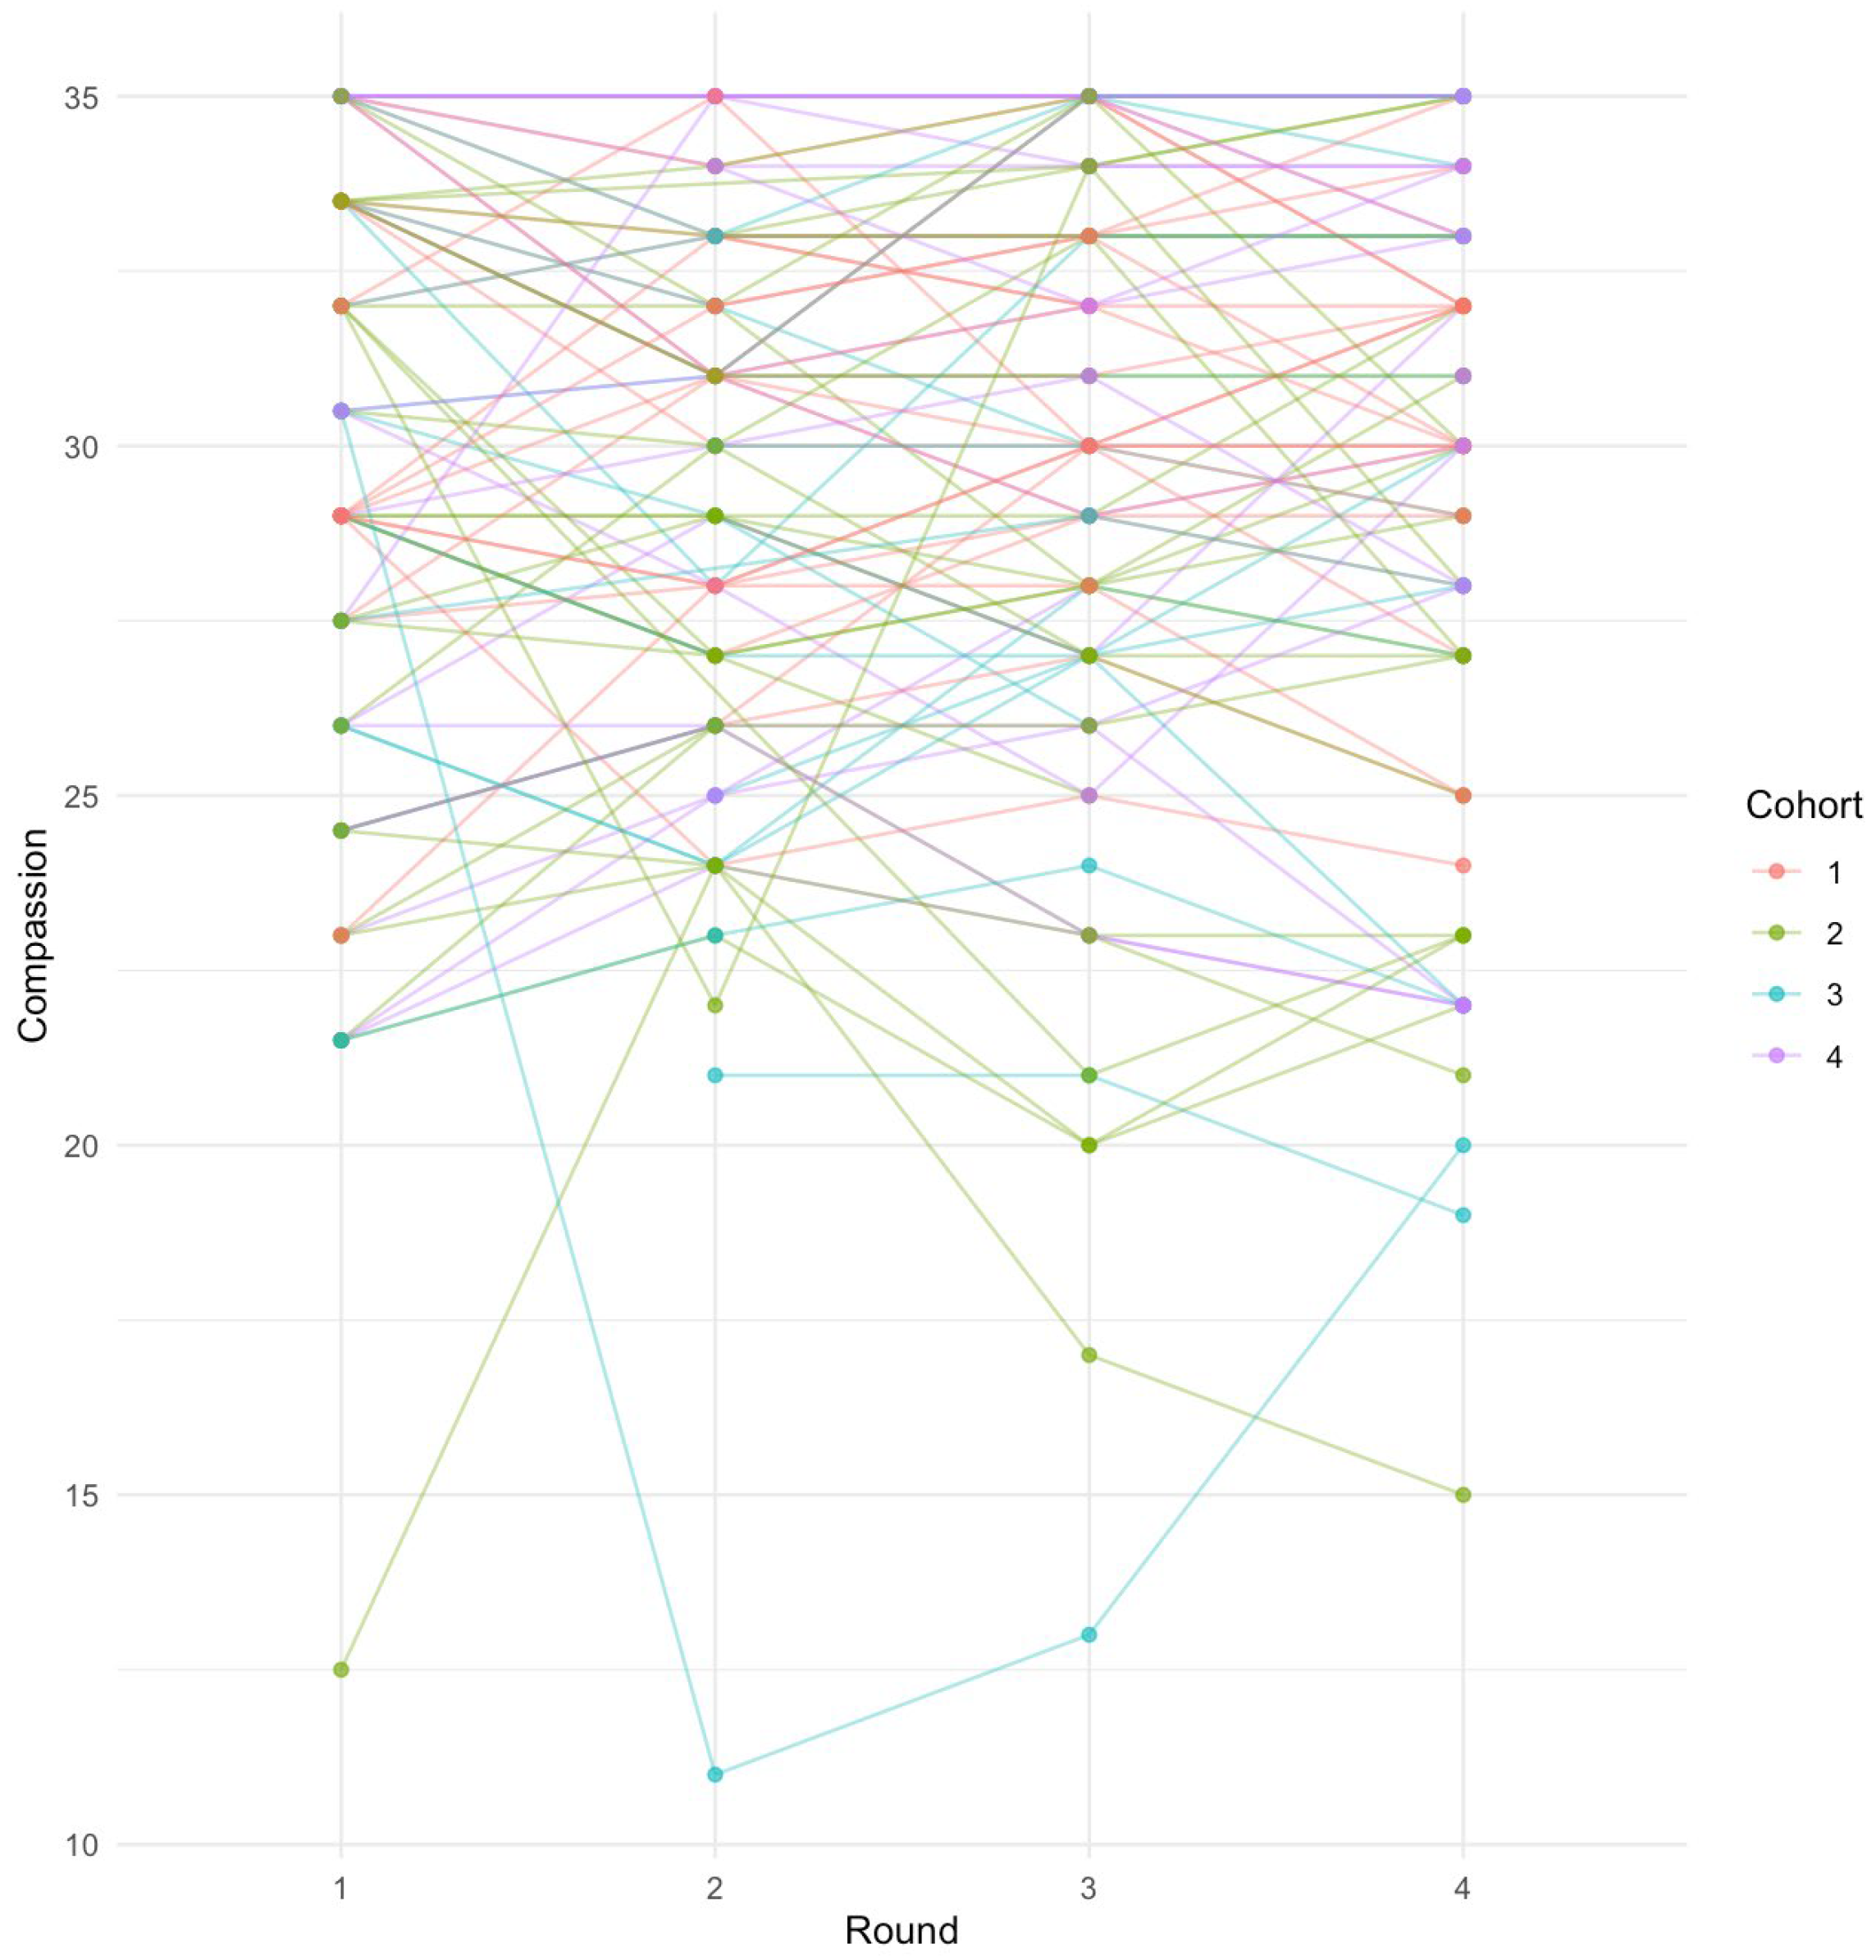
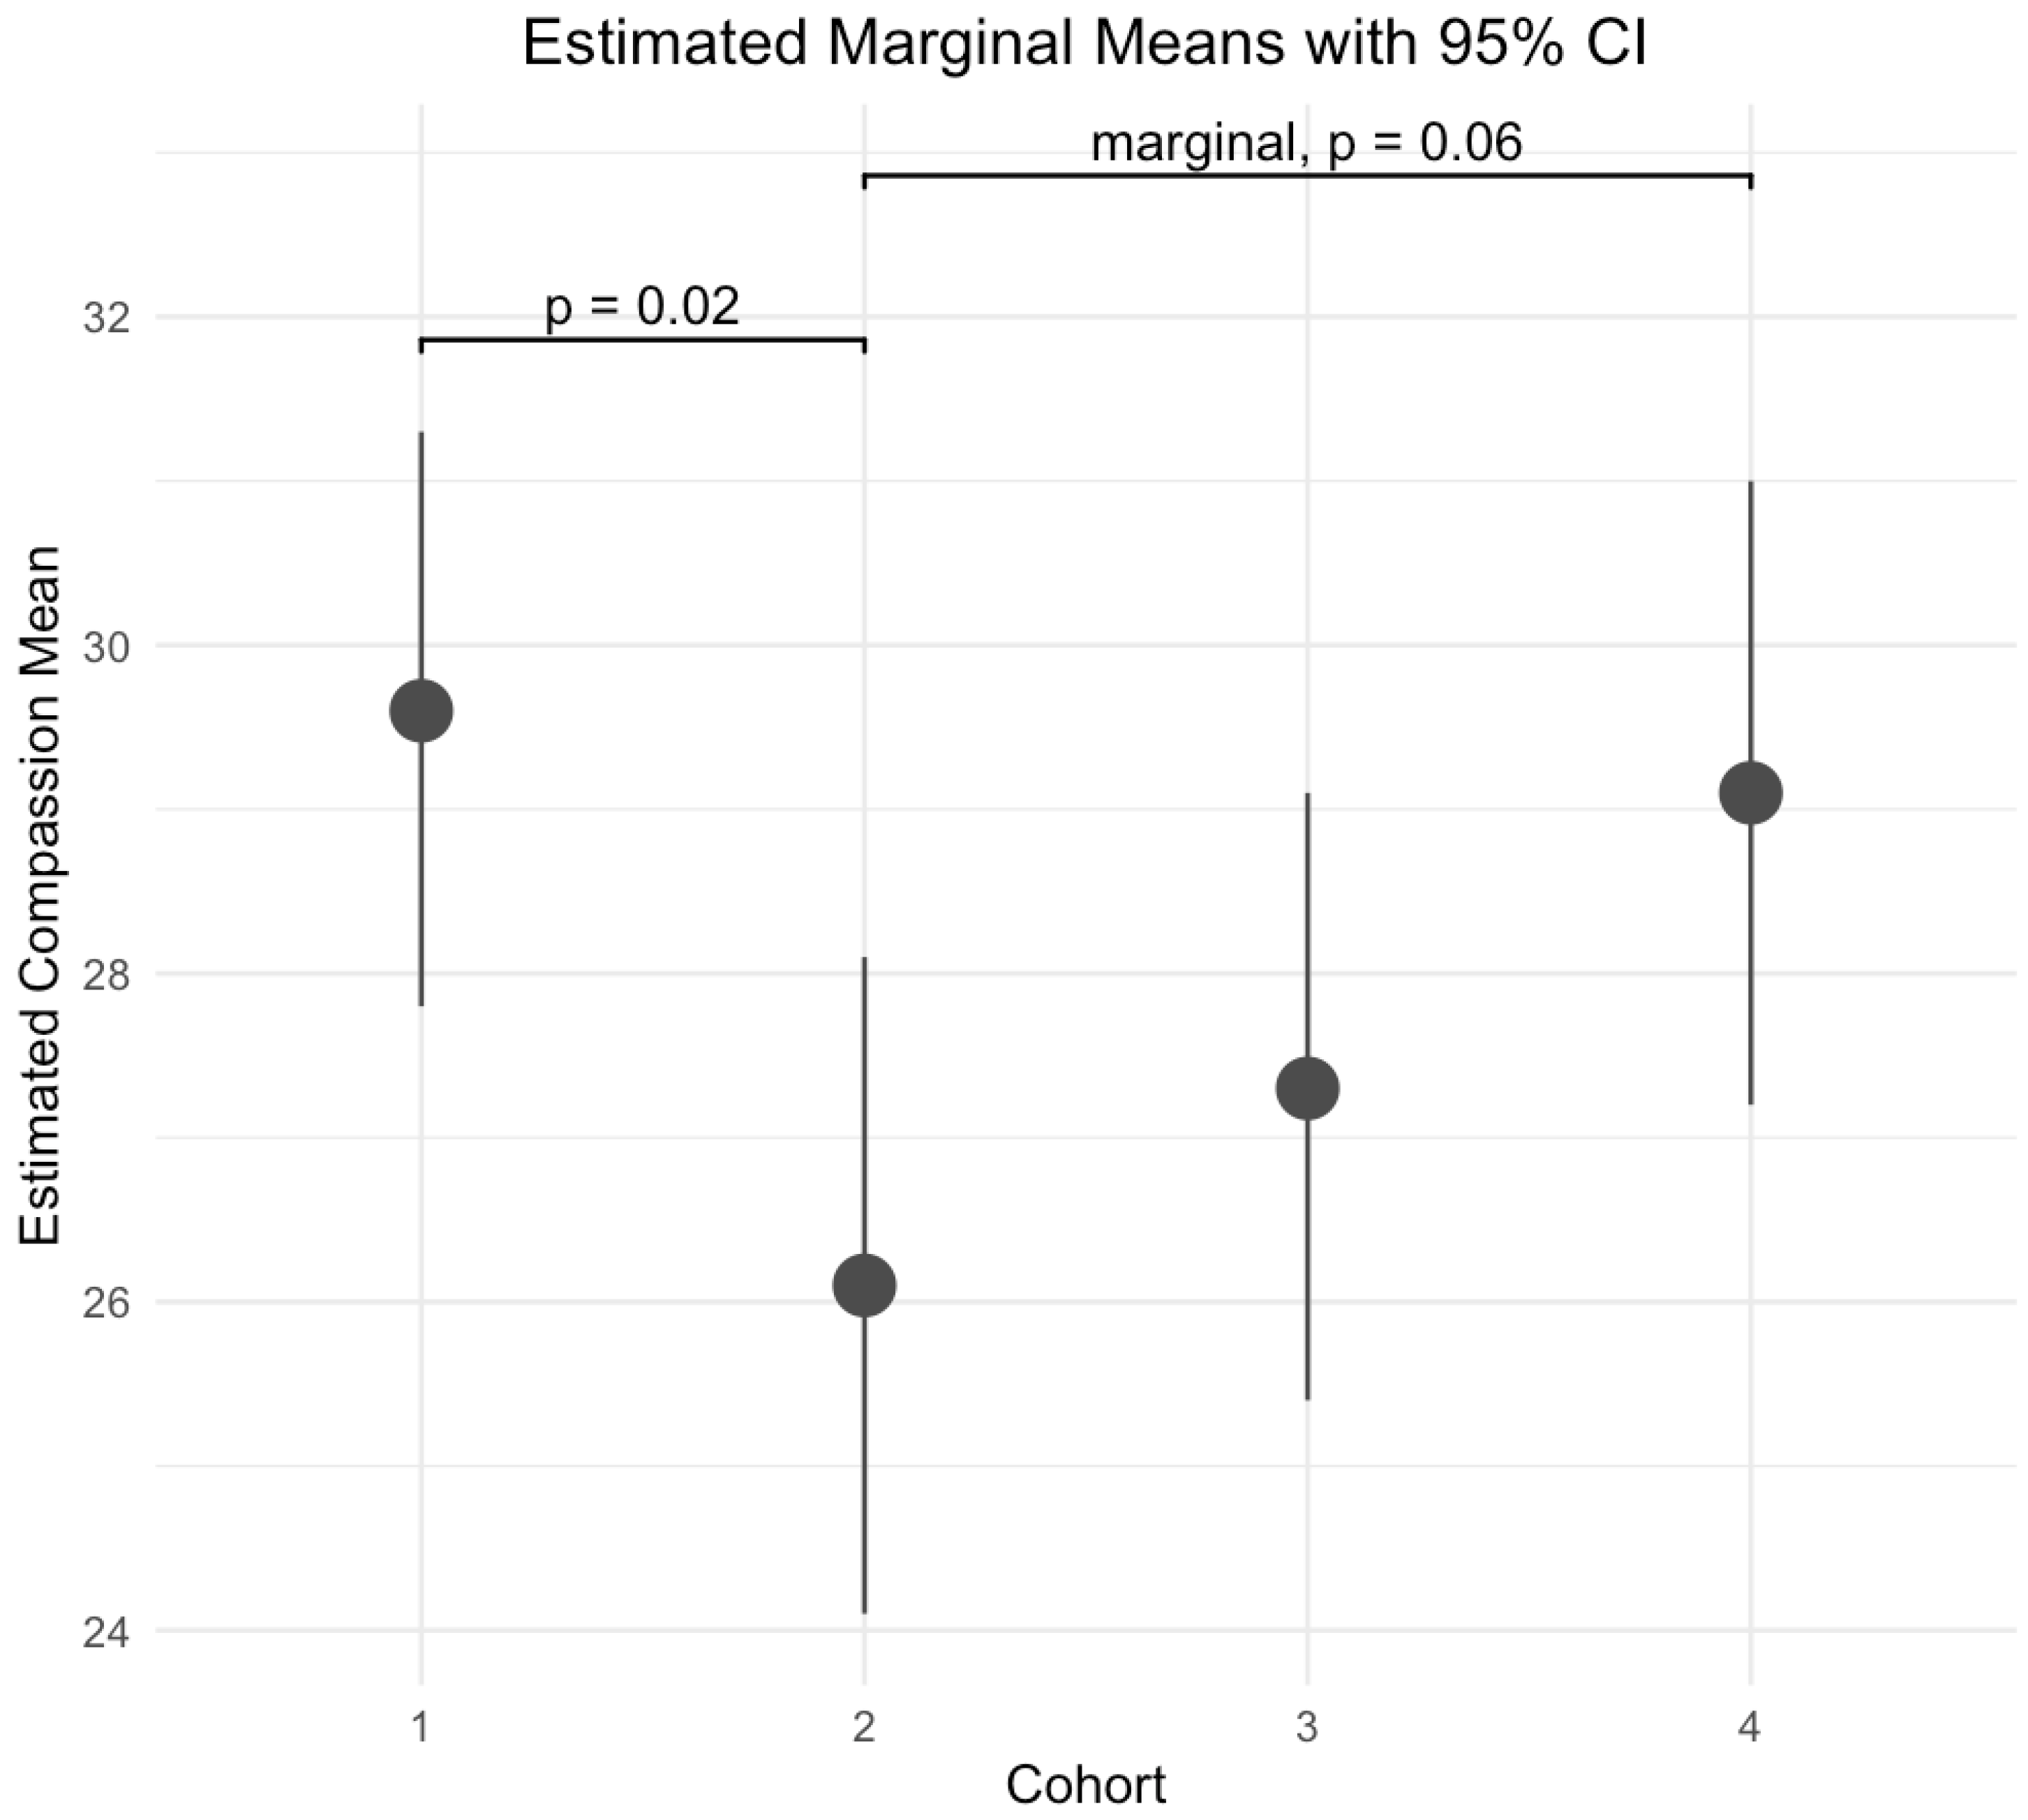
The individual trajectories of the compassion scores are presented in Figure A2. There was a significant relationship of gender with compassion (F (1, 86.31) = 5.04, p = 0.03, η2 = 0.06); women reported higher compassion than men (M = 29.0, 95% CI [27.6; 30.3] vs. M = 27.0, 95% CI [25.4; 28.7]). There was no significant relationship between race/ethnicity and compassion (F(4, 85.82) = 1.92, p = 0.11, η2 = 0.08). There was no significant association between measurement round and compassion (F (3, 222.51) = 1.30, p = 0.28; η2 = 0.02). There were significant cohort differences (F (3, 86.33) = 3.72, p = 0.01, η2 = 0.11): Compassion scores were significantly lower among MS2 students (M = 26.1, 95% CI [24.1; 28.1]) compared to MS1 students (M = 29.6; 95% CI [27.8; 31.3], t (81.9) = 2.94, adjusted p = 0.02) (Figure 2). The differences between MS2 and MS4 students, with MS2 showing numerically lower compassion, were marginally significant (M = 26.1, 95% CI [24.1; 28.1] vs. M = 29.1, 95% CI [27.2; 31.0], t (86.8) = −2.55, adjusted p = 0.06).

3.4. Self-Compassion

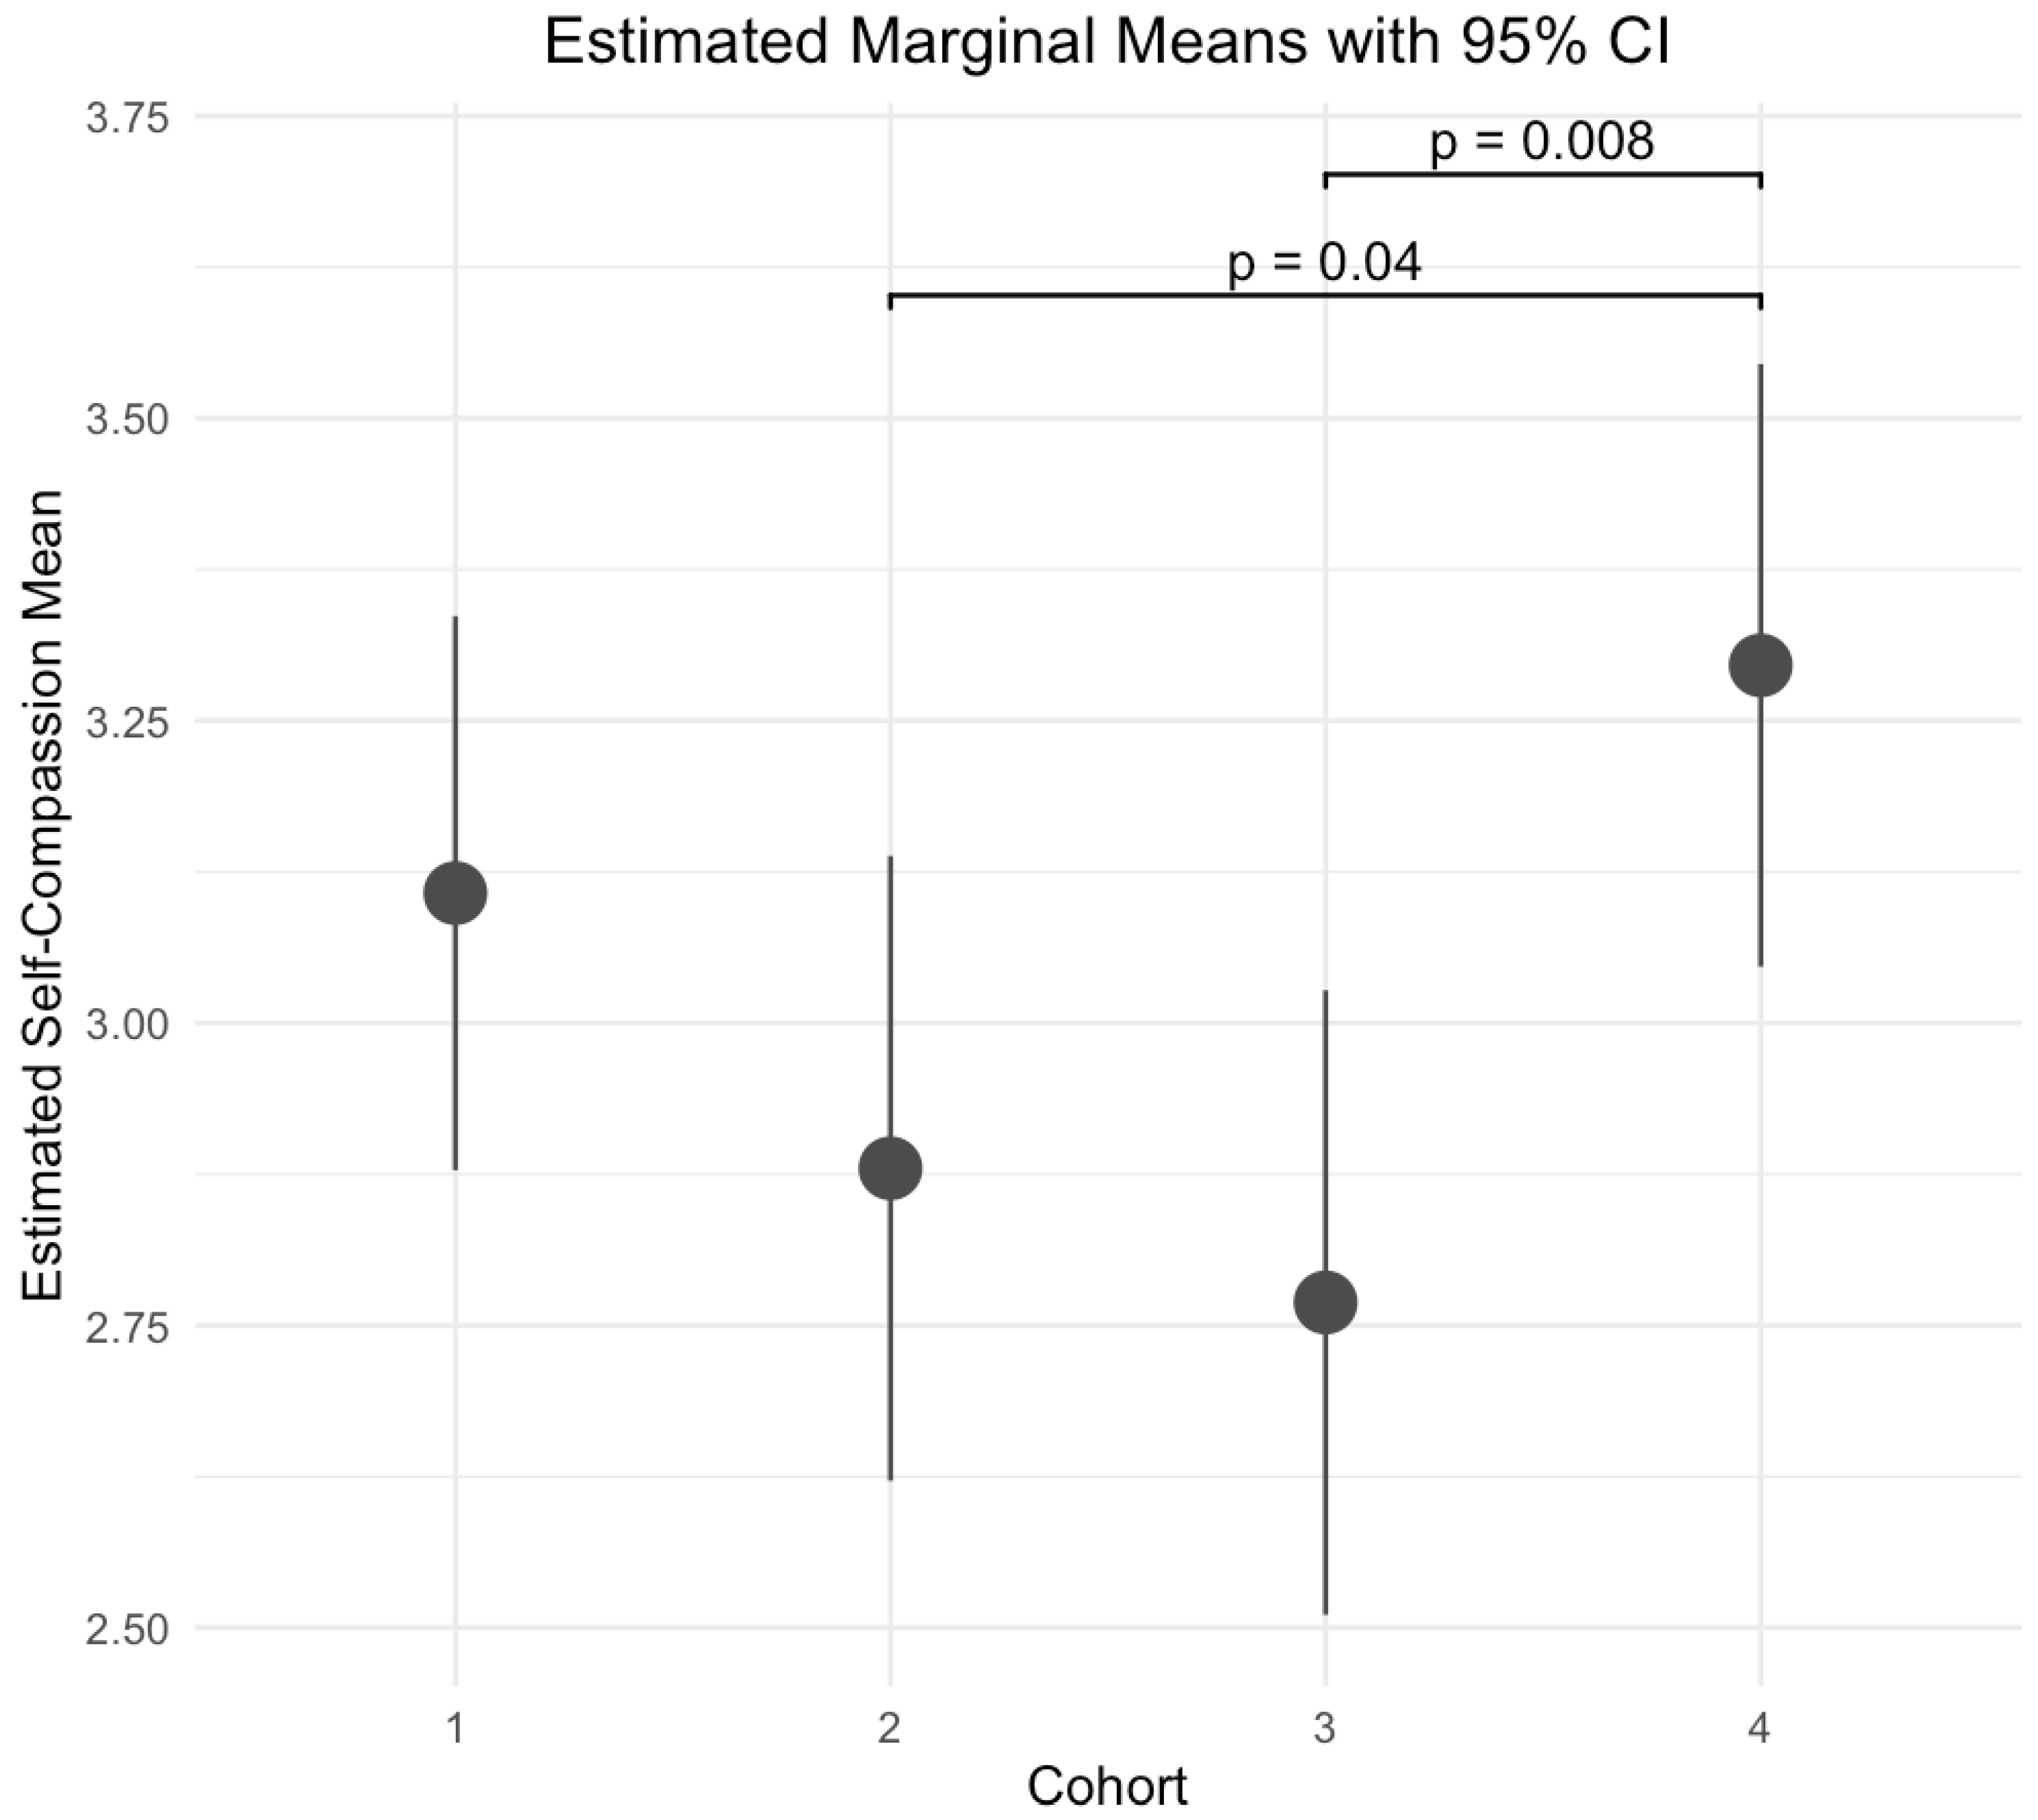
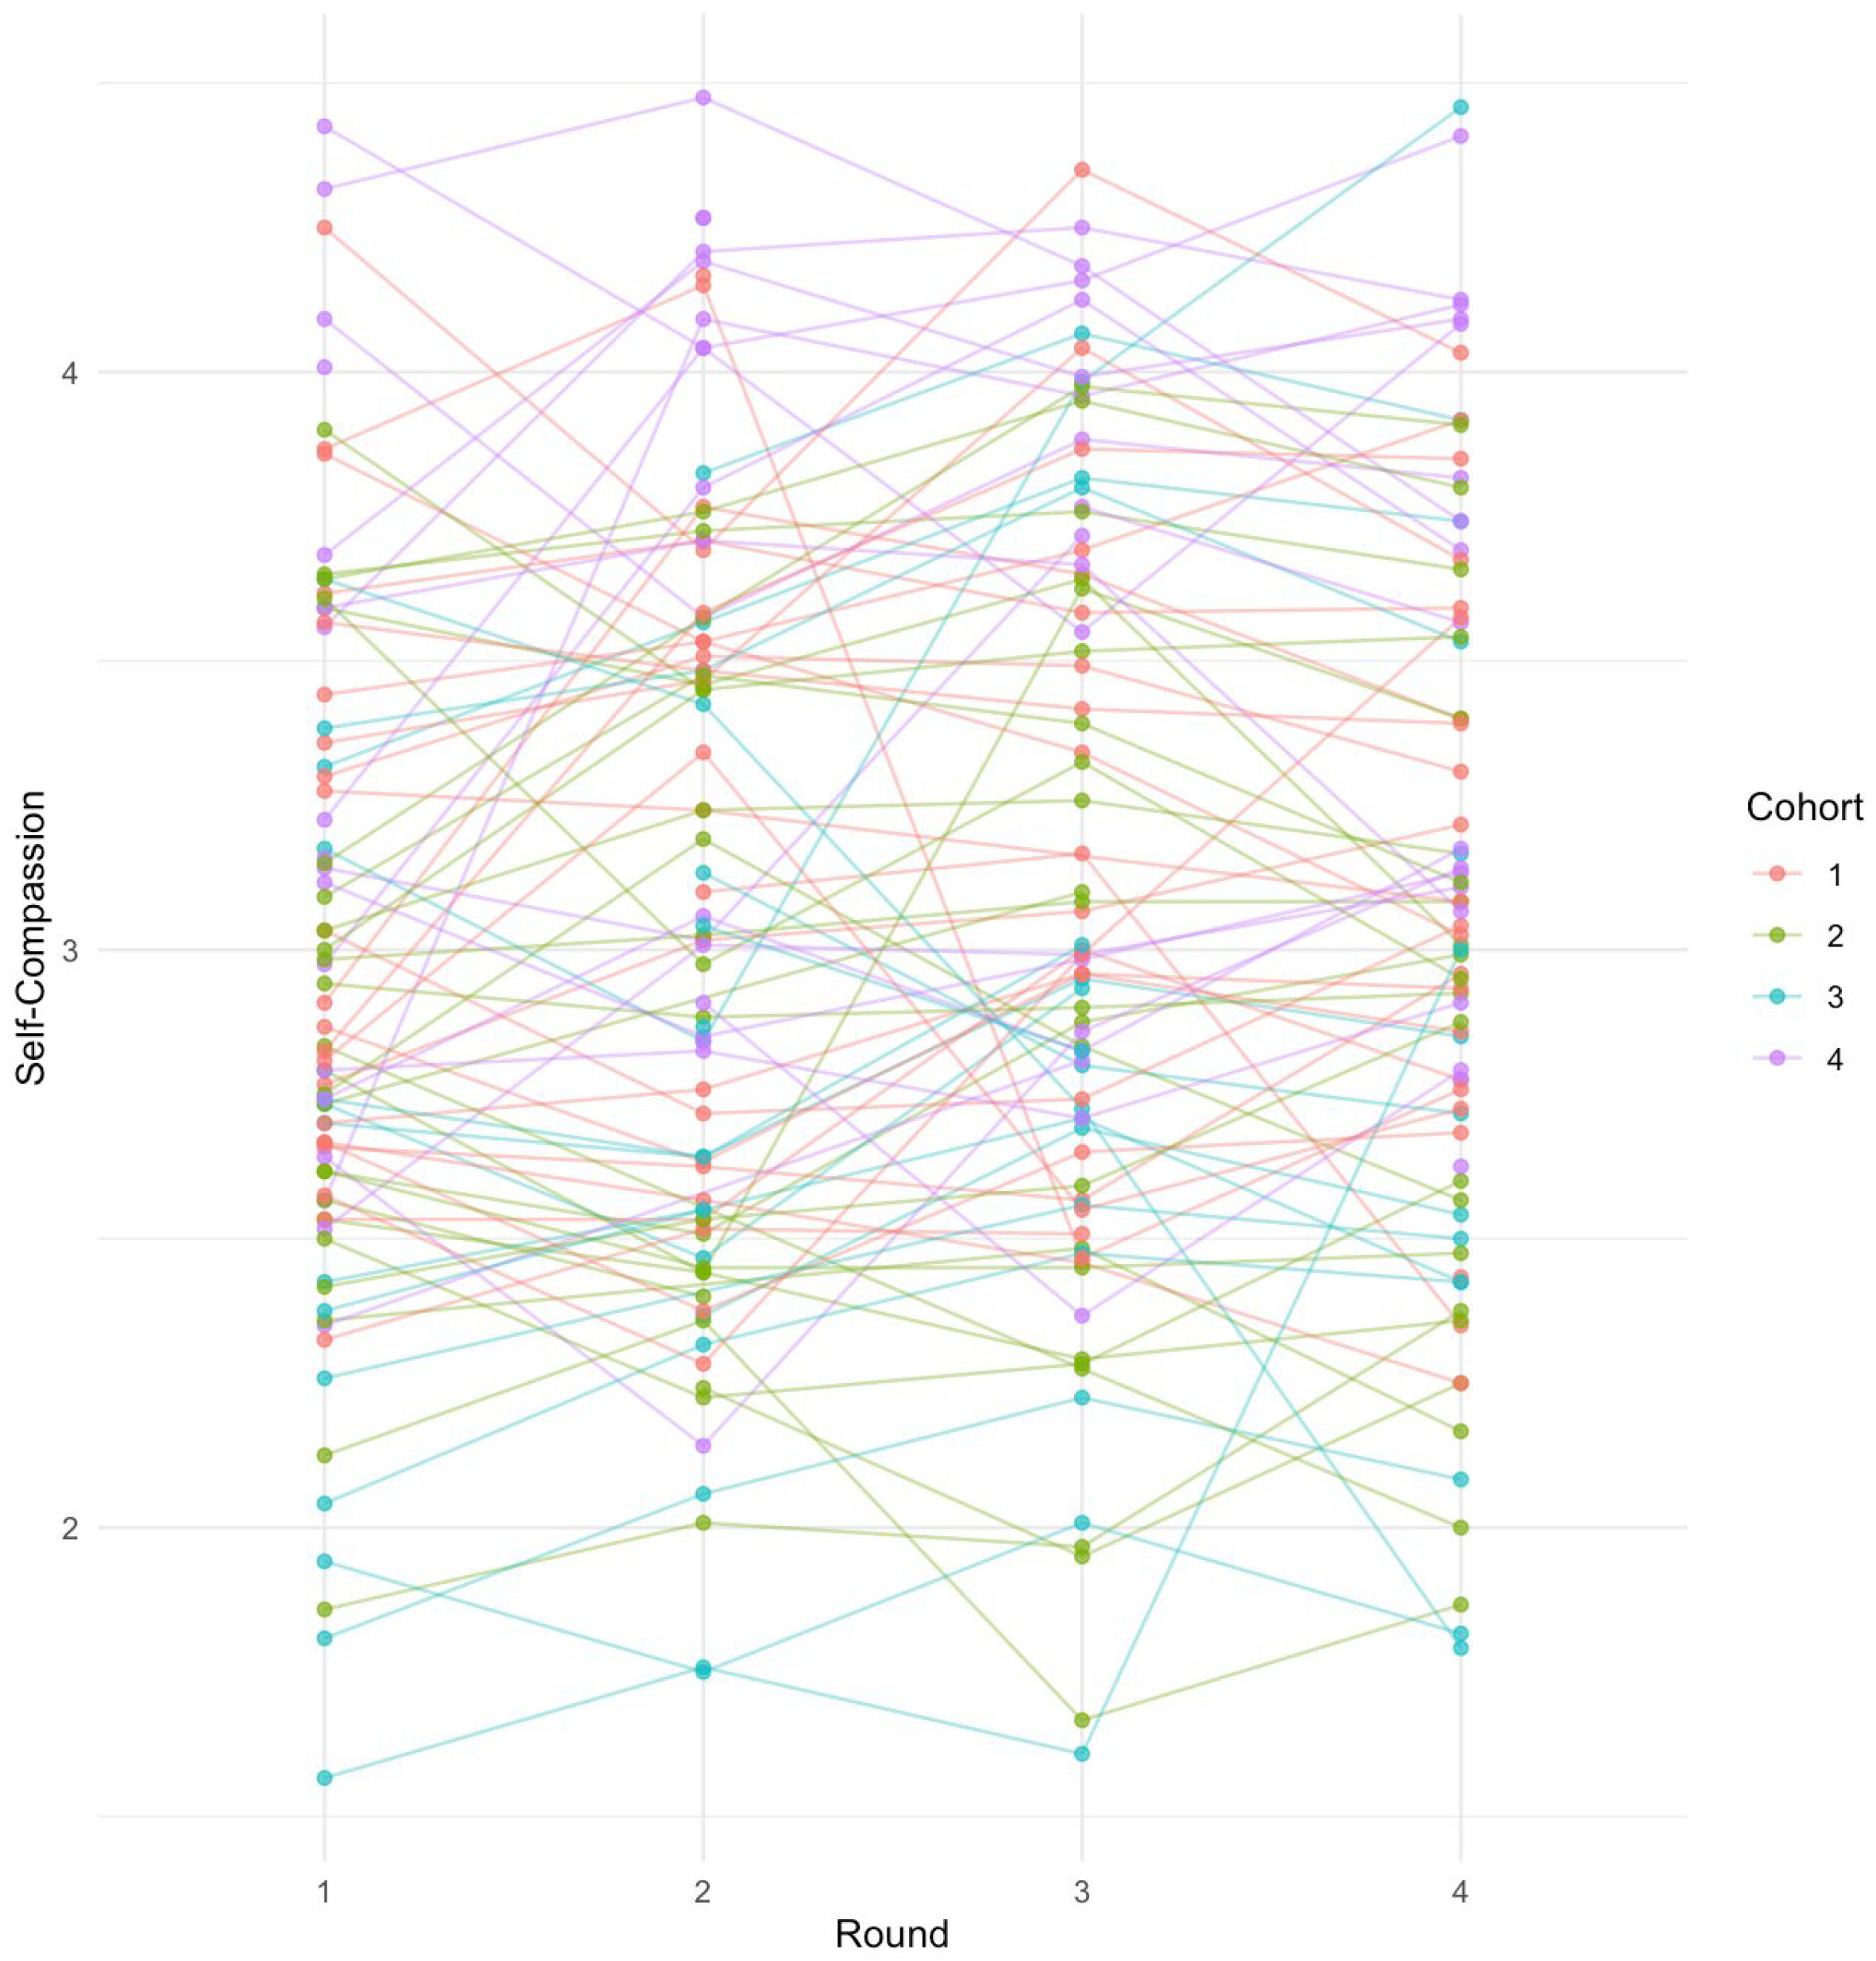
The individual trajectories of the self-compassion scores are presented in Figure A3. There was a significant relationship with gender (F (1, 85.19) = 7.21, p = 0.009; η2 = 0.08); men had significantly higher self-compassion than women (M = 3.16 vs. M = 2.86). There was no significant relationship of race/ethnicity with self-compassion (F (4, 84.74) = 0.76, p = 0.55; η2 = 0.03). Additionally, there was a significant association between round and self-compassion (F (3, 220.58) = 2.75, p = 0.04; η2 = 0.04): after adjusting for multiple comparisons, self-compassion was significantly lower during Round 1 (beginning of the academic year) compared to Round 3 (early spring of the academic year) (M = 2.93, 95% CI [2.76; 3.11] vs. M = 3.08, 95% CI [2.91; 3.25]; t(218) = −2.80, adjusted p = 0.03). There were significant cohort differences (F (3, 85.22) = 4.44, p = 0.006; η2 = 0.14) in self-compassion. Figure 3 shows that self-compassion scores, compared to MS4 students (M = 3.30, 95% CI [3.05; 3.54]), were significantly lower among MS2 (M = 2.88, 95% CI [2.62; 3.14], t(86.8) = −2.72, adjusted p = 0.04) and MS3 students (M = 2.77, 95% CI [2.51; 3.03], t(88.3) = −3.29, adjusted p = 0.008).

3.5. Resilience

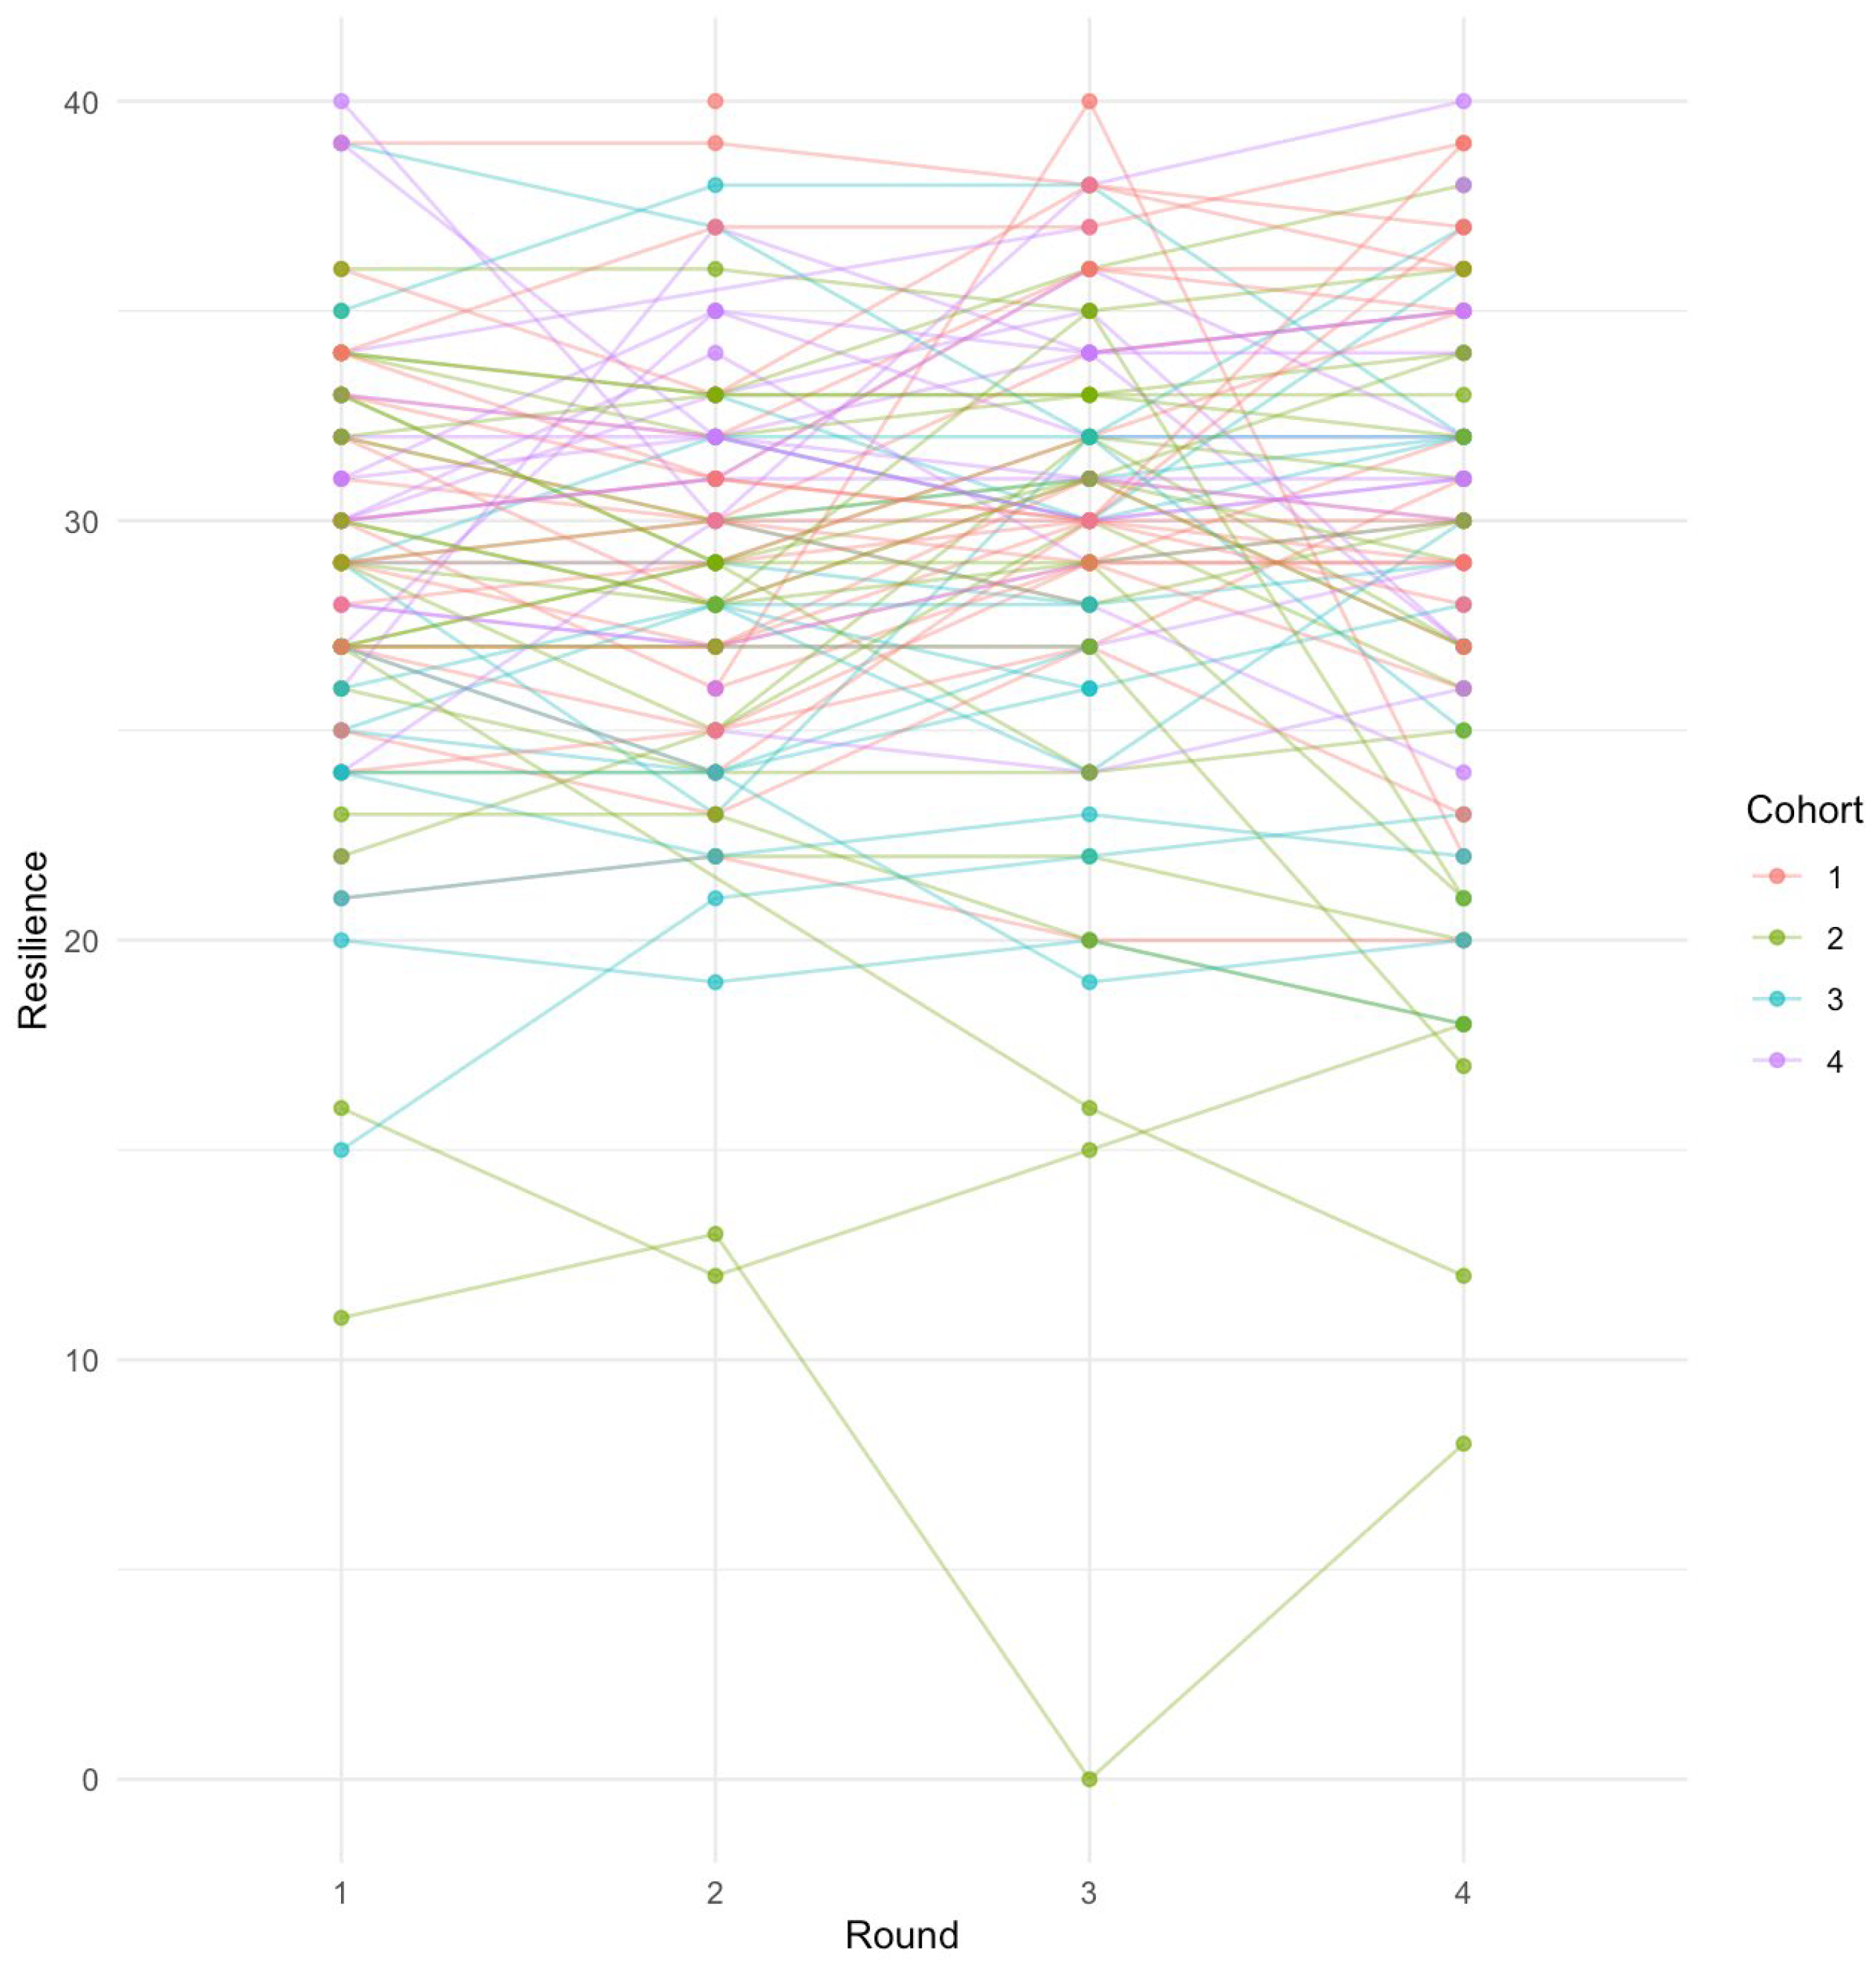
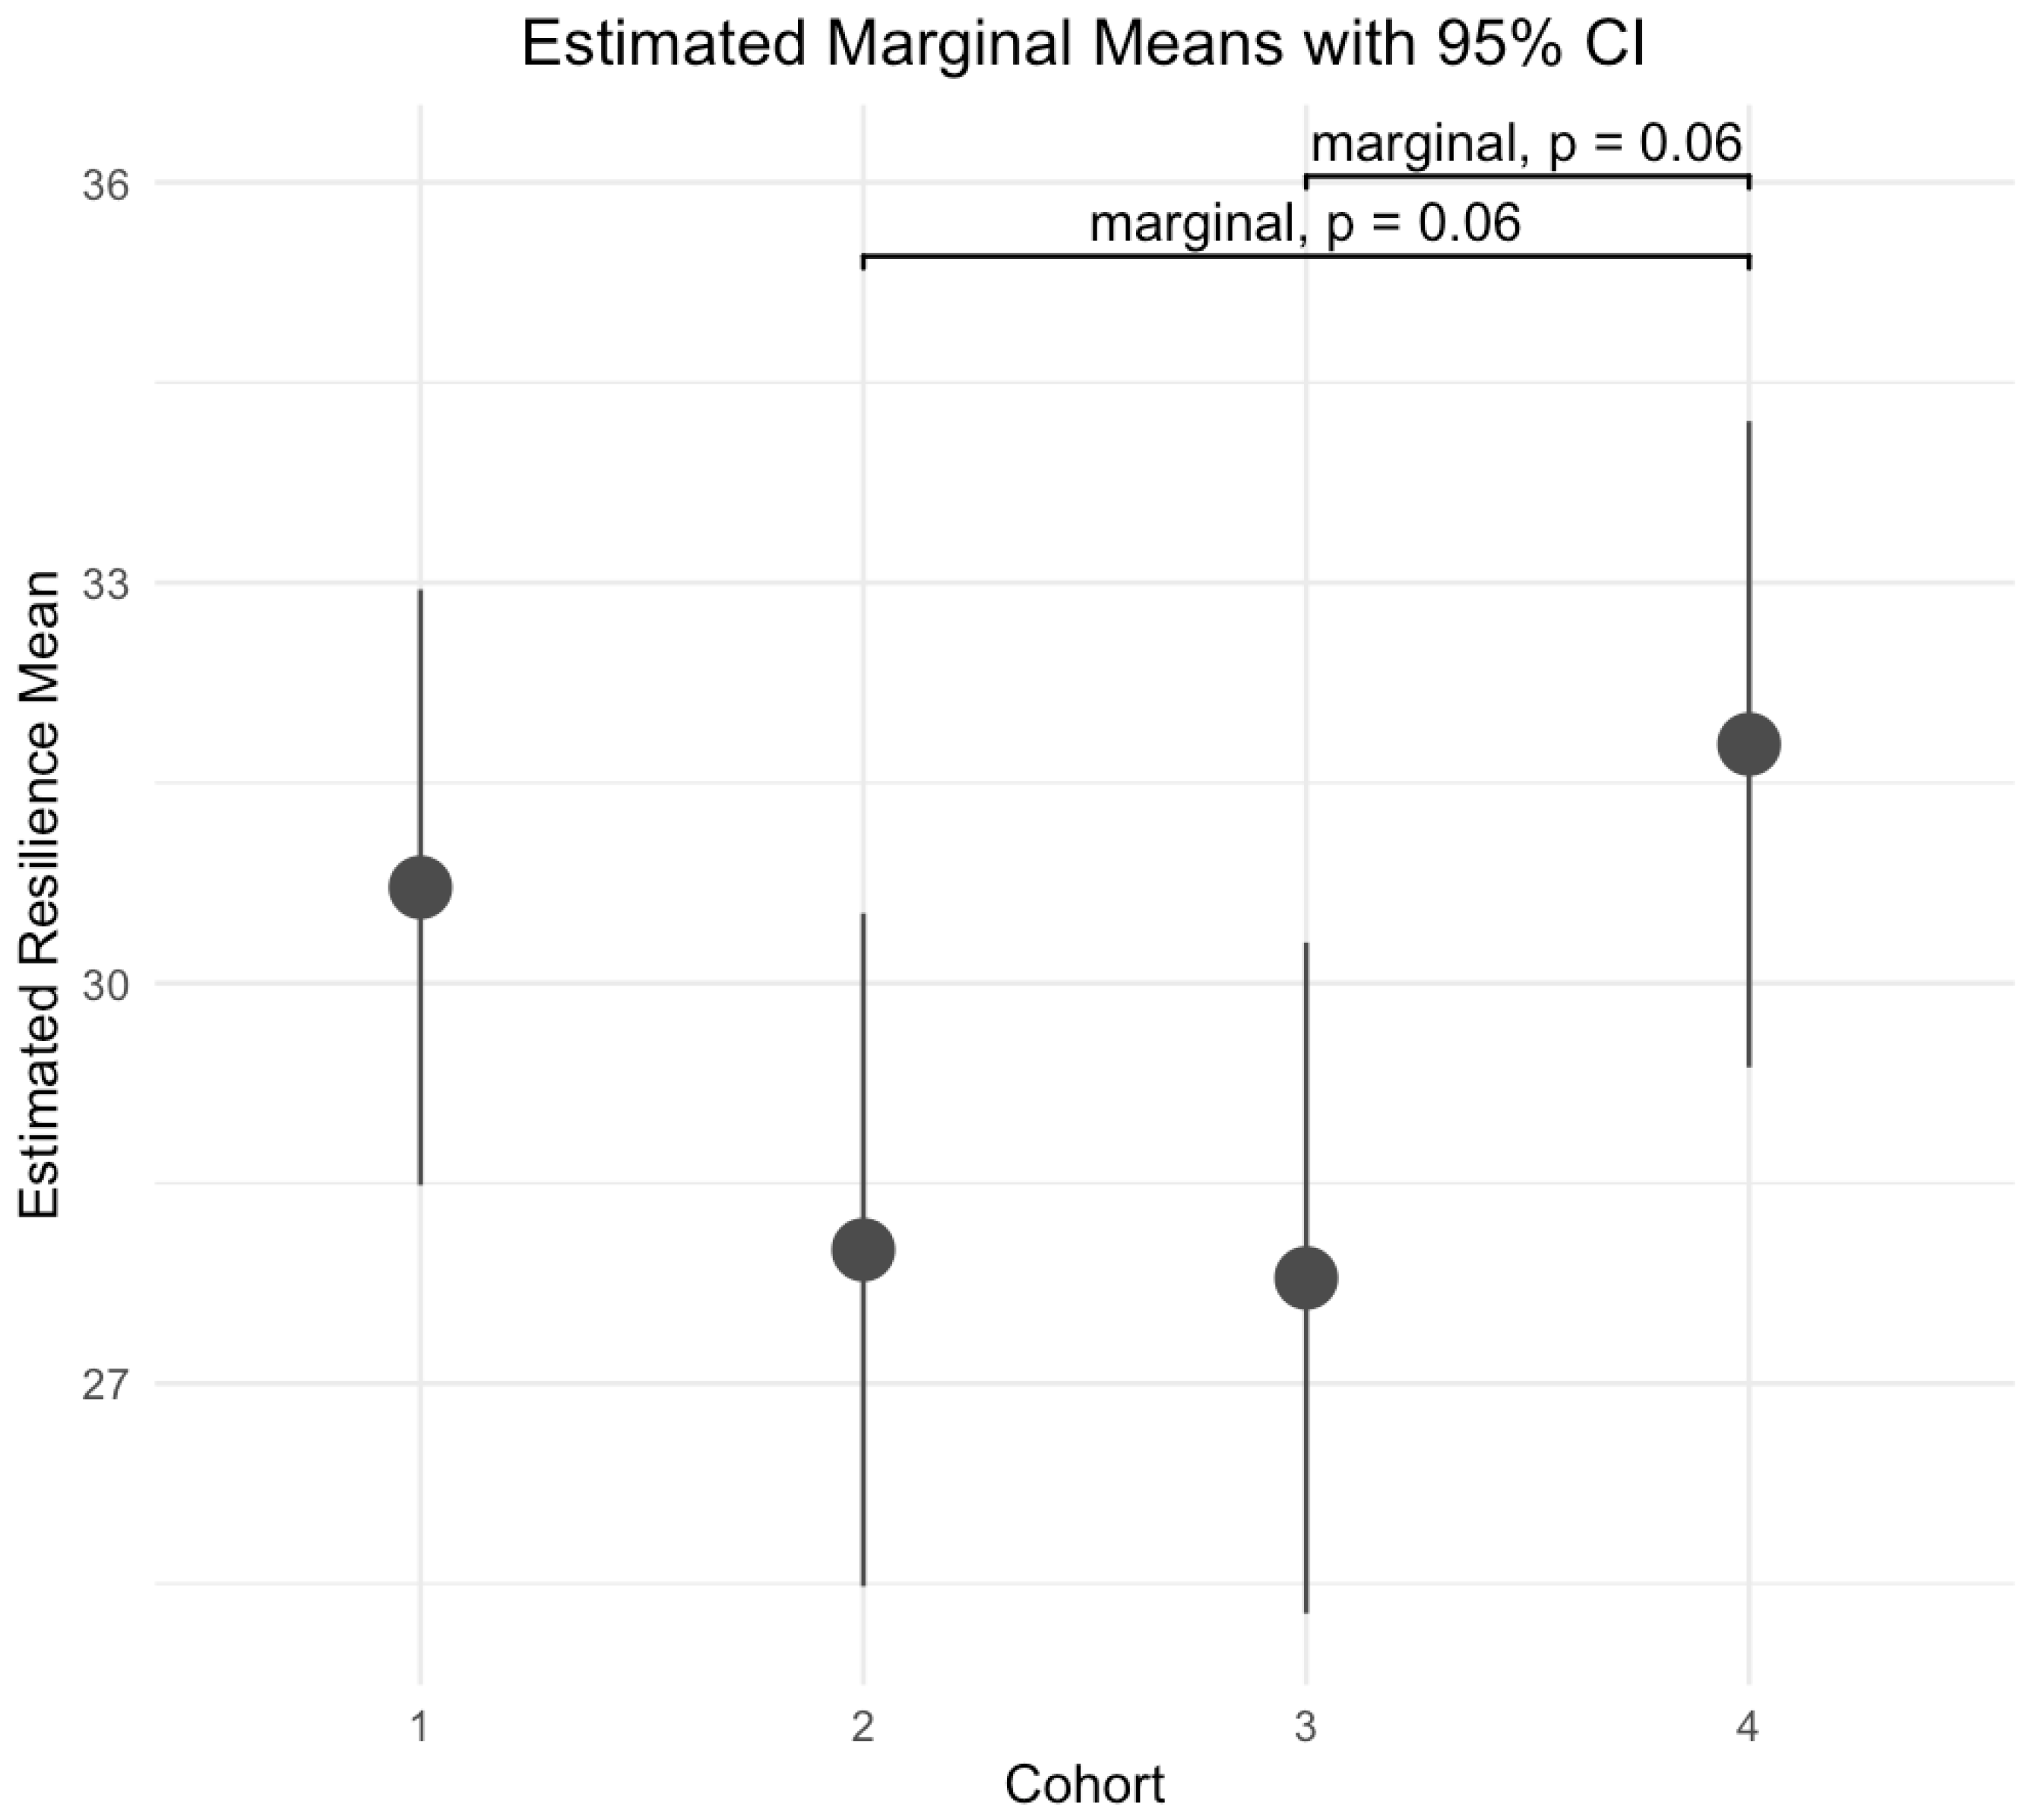
The individual trajectories of the resilience scores are presented in Figure A4. There was a significant relationship of gender (F (1, 84.41) = 5.09, p = 0.03; η2 = 0.06) with resilience; men had significantly higher resilience than women (M = 30.8, 95% CI [28.7; 32.9] vs. M = 28.3, 95% CI [26.6; 30.0]). There was no significant association between race/ethnicity and resilience (F (4, 83.76) = 0.51, p = 0.73; η2 = 0.02). Additionally, there was no significant association between measurement round and resilience (F (3, 218.07) = 1.15, p = 0.33; η2 = 0.02). Cohort differences were significant (F (3, 84.29) = 3.41, p = 0.02; η2 = 0.11). However, after the adjustment for multiple comparisons, the differences were marginally significant. A trend toward significance was noted: compared to MS4 (M = 31.8, 95% CI [29.4; 34.2]) students, MS2 (M = 28.0, 95% CI [25.5; 30.5], t (86.7) = −2.55, adjusted p = 0.06) and MS3 (M = 27.8, 95% CI [25.3; 30.3], t (87.9) = −2.57, adjusted p = 0.06) students had marginally lower resilience scores (Figure A5).

4. Discussion

The present study sought to report early findings from a longitudinal cohort study of medical students’ empathy, compassion, self-compassion, and resilience. Our preliminary findings suggest that second and third-year students had significantly lower cognitive empathy and self-compassion and marginally lower compassion and resilience compared to fourth-year students. Additionally, second-year students had lower compassion than first-year students. Specific gender patterns also emerged. We observed significant differences between men and women in compassion, self-compassion, and resilience, such that women reported higher compassion towards others but lower self-compassion and resilience than men.
The literature on medical students’ empathy and compassion has often observed lower levels of these traits during the third year of education that persist until graduation and into residency [8]. However, upon closer examination, a more nuanced picture emerges. Smith et al. [34] found that while medical students’ clinical empathy had declined over the three years of the study’s duration, there was an increase in overall cognitive and affective empathy, as well as an improvement in accuracy on objective behavioral tasks assessing empathy and compassion. Another study did not observe a statistically significant change in empathy and compassion among third-year students exposed to a course on humanism in medicine [35]. Similarly, our study’s preliminary findings suggest a more complex pattern. While students in our sample reported lower cognitive empathy, self-compassion, and compassion as early as the second (pre-clinical) year, as well as in the third (clinical) year, levels of these traits were higher again in the fourth year. This is a promising early finding suggesting that despite earlier reductions in empathy and compassion, medical students may regain these qualities later in training. If these preliminary results are supported in future longitudinal analyses and with larger sample sizes, several contextual factors may help explain this finding. Although unique stressors such as residency interviews and the matching process are present during the fourth year of education, many students note an improvement in their experience due to activities that are more related to their clinical interests [36]. Moreover, in a qualitative study, fourth-year medical students noted that additional available time during the fourth year allowed them to pursue personal interests and have more academic and personal flexibility, allowing them to feel more relaxed and fulfilled in other areas of life [36]. This additional time resource may help create more self-perceived capacity for empathy and compassion. This pattern should be further explored in future studies and supported by qualitative and additional quantitative results. Of note, MS4 students in our study entered medical school in 2020 during the COVID-19 pandemic. Although during the height of the pandemic, this cohort of students had limited exposure to direct patient care, being in healthcare during the time of global emergency and increased public suffering may have impacted this cohort’s empathy ratings [37]. Studies showed that COVID-19 cohorts in other medical schools reported greater empathy compared to pre-pandemic cohorts, potentially representing transient cohort effects [37]. We aim to disentangle the influences of cohort and stage of training effects by conducting additional surveys across three additional academic years.
We also observed lower levels of empathy and compassion as early as the second year of education in our initial cohort comparison, contrary to existing literature that reports an erosion of these qualities starting in the third year. It has been hypothesized that this decline occurs due to challenges associated with clinical rotations, such as increased time pressures, high-stakes evaluative environments, negative role models, and exposure to patient suffering [8]. However, our results, if verified with longer longitudinal follow-up, suggest that decline may begin earlier, which may be associated with overall academic demands and medical school culture rather than clinical practice alone. This observation is echoed in the qualitative findings of Ahrweiler et al. [38], who found that patient encounters during medical school increase the physician’s ability for empathy. In contrast, the demands of medical school were identified as the most significant barriers to this quality [38].
Another explanation for the preliminary finding of lower empathy and compassion during the second year is the possible role of standardized testing. The second year of medical school is the time of the United States Medical Licensing Examination (USMLE) Step 1, which was converted into a pass/fail format in 2022. Hence, students participating in our survey were among the first to experience the shift in this evaluation. Designed to alleviate students’ stress, the new system appeared to have produced mixed results. While many students approved of the new pass/fail format, others reported feeling uncertain or skeptical about the implications of the new approach [39]. For instance, according to one study, approximately half of medical students perceived that the new pass/fail criteria would make the application to already competitive specialties (e.g., orthopedic surgery, urology, dermatology) even more competitive due to a higher number of applicants [39]. The students hypothesized that the new pass/fail criteria may encourage the students who, under previous criteria, would have selected less competitive specialties due to lower Step 1 scores, to apply for more selective residencies, broadening the pool of applicants for already limited positions. In response, students reported a higher likelihood of devoting more time to research or taking a gap year to conduct research full-time in order to make their application more competitive, potentially increasing academic stress and reducing social mobility [39]. This competitive environment may also impact students’ empathy and compassion, as their focus may shift to personal achievement and away from patient-centered care. These interpretations, however, should be considered as hypothesis-generating, and future studies should explore the potential association between Step 1, empathy, compassion, and stress.
The stress and high academic demands of Step 1 are not the only things that may be contributing to the results observed in our study. As part of our team’s yearly focus groups with fourth-year (MS 4) students, a preliminary thematic analysis suggested that Step 1 exams were perceived as being associated with students’ empathy and compassion through content-specific mechanisms. In focus groups, students shared that repeated exposure to standardized case stems may have been negatively associated with empathy and compassion towards patients, which they attributed to stereotypical patient presentations and, consequently, the emergence of anchoring bias. Thus, the impersonal and formulaic presentation of Step 1 and Step 2 questions may be related to the perceived reduction in empathy and compassion during the examination preparation period. At the same time, fourth-year students noted that patient and family panels during the pre-clinical years were among the most memorable and influential activities, which students perceived as fostering empathy and compassion. In sum, while the value of standardized examinations in assessing knowledge across large student populations is significant, incorporating more patient-centered activities during the preclinical years may help offset their potential unintended consequences. Furthermore, it may be important to reinforce a growth mindset among students and convey that an out-sized focus on personal achievement can be detrimental to the ultimate goal of becoming a compassionate physician. As part of our ongoing research, we plan to further explore students’ experiences with standardized testing and its possible association with a decline in empathy and compassion.
We have similarly observed that self-compassion was significantly higher in MS4 students compared to MS2 and MS3 students. This aligns with evidence that self-compassion is associated with higher self-efficacy (i.e., self-perceived confidence and competence), suggesting that increased experience gained through medical education may contribute to higher self-compassion [40]. Additionally, in medical students, self-compassion has been associated with gain-maximizing learning goals (e.g., striving to master educational content) compared to loss-minimizing learning goals (e.g., not failing in a class) [41]. During their final year in medical school, MS4 students are more likely to engage in elective and self-paced learning that helps them prepare for their specialty of choice, placing them in the gain-maximizing mindset. This additional resource may then increase self-compassion during the fourth year of education. We also found that self-compassion was significantly lower for the first wave of the surveys conducted at the beginning of the academic year, compared to the third wave of surveys conducted in the spring. This finding may reflect increased self-efficacy through academic and clinical exposure [40].
After adjustment for multiple comparisons, there were no significant differences among medical students in resilience. Although marginal differences (p’s = 0.06) were noted, with MS4 students reporting higher resilience than MS2 and MS3 students. One study of 1321 U.S. medical students similarly did not observe a difference in self-reported resilience between students in different years of study [42]. However, of note, only 5 students in that study were MS4 students, suggesting a need for further investigations, as our results demonstrated marginally higher levels in that population.
Our findings on gender differences in self-compassion, compassion, and resilience align with extant literature, as higher compassion and lower self-compassion and resilience among women have been consistently demonstrated [42,43]. Studies have shown consistent differences in these constructs in both general and healthcare worker samples [44]. Multiple and conflicting explanations for these differences exist, including evolutionary and social models. However, it is of note that while the differences are significant, the reported effect sizes are frequently small, as was the case in our sample [43].
Our findings have implications for the design of medical school curricula. At the policy level, our qualitative and quantitative findings suggest the need for further investigation into the potential relationship between standardized testing and its mental health consequences. At educational and practical levels, our results suggest that comprehensive programs integrated throughout education, rather than only during the preclinical years, are better equipped to address the dynamic changes in empathy and compassion that occur throughout medical education. As the decline in empathy and compassion may be emerging as early as the second year of schooling, longitudinal approaches should be used when designing empathy and compassion curricula to better address developmental challenges associated with both pre-clinical and clinical years. Many efforts to foster empathy and compassion are frequently limited in time, such as workshops and brief courses, and may be insufficient to mitigate chronic stressors and barriers to empathic and compassionate care [13]. Importantly, educational efforts in empathy and compassion have been found to be especially effective when didactic courses are supplemented with practical application under the supervision of other physicians [1]. Additionally, the importance of teaching sustainable empathy, which involves the acknowledgment and understanding of patients’ emotions without their internalization, is increasingly recognized [13]. Sustainable empathy can help maintain positive regard toward patients and support compassionate care while protecting against empathy fatigue associated with emotional responses to patients’ suffering [13]. To foster sustainable empathy in medical trainees, holistic educational approaches, involving practice of adjacent capacities such as resilience and self-compassion, shown to protect against empathy fatigue and burnout, should be incorporated into empathy and compassion curricula in medical schools [45]. This holistic approach may allow trainees to develop skills that are effective and sustainable over long periods of time, even in high-stress environments. Together, these findings suggest that empathy and compassion curricula integrated throughout medical education that incorporates hands-on practice of learned skills and fostering of resilience and self-compassion may be beneficial for fostering these qualities.
There are a few limitations worth noting. First, despite the longitudinal design and four waves of data, our study only spanned one academic year, and the observed differences may be attributable to cohort differences rather than to developmental trajectories. Therefore, the findings of our study are preliminary, and future studies would better elucidate both cohort and longitudinal differences. Second, our study was conducted in a single U.S. institution and had a limited number of participants from Hispanic/Latinx and Black backgrounds, limiting generalizability. Another limitation is associated with the self-report bias and student monetary incentivization, and students may have responded to questionnaires in a socially desirable way [46]. Our team plans to address this limitation through third-person rating of the recorded encounters between participating students and simulated patients during the Objective Structured Clinical Examination (OSCE). This approach will not only provide a more objective evaluation of students’ empathy and compassion skills but also offer an opportunity to examine a possible discrepancy between empathy and compassion self-report data and clinical skills. Furthermore, empathy and compassion measures used in this study were developed for the general population and are not tailored for the medical student population; however, the scales used in our study were validated among medical learners [18,20,23,26]. Additionally, future studies by our group plan to incorporate qualitative and observer-rated measures of empathy and compassion to offset this limitation.
Despite limitations, our study has several notable strengths. First, we measured empathy and compassion four times during the academic year, capturing changes at different stages of the academic calendar and increasing the power to detect between-cohort differences due to more reliable measurement of each individual’s scores. Finally, the inclusion of additional constructs related to empathy and compassion, such as self-compassion and resilience, offers a more nuanced insight into differences between stages of medical education.

5. Conclusions

In conclusion, our study provided preliminary insights into empathy and compassion differences between four cohorts of medical students during the 2023–2024 academic year. While lower levels of empathy and related constructs were noted during both preclinical and clinical stages, levels were higher during the fourth year. These preliminary findings contribute to the growing body of literature on empathy and compassion among medical students. Additional waves of data will provide a more comprehensive examination of both cohort differences and the longitudinal progression of students from different cohorts over time. Our future research will also investigate the effects of mandatory and elective curricula focused on enhancing empathy and compassion by comparing outcomes across different levels of curricular exposure in order to examine a potential dose–response effect.

Author Contributions

Conceptualization, A.V.D., N.P.M. and F.K.; methodology, A.V.D.; formal analysis, A.V.D.; data curation, A.V.D.; writing—original draft preparation, A.V.D. and N.P.M.; writing—review and editing, N.P.M., F.K. and L.T.E.; supervision, F.K. and L.T.E.; project administration, A.V.D. and L.T.E.; funding acquisition, L.T.E. All authors have read and agreed to the published version of the manuscript.

Funding

This research was funded by the T. Denny Sanford Institute for Empathy and Compassion, University of California, San Diego.

Institutional Review Board Statement

The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of the University of California, San Diego (protocol code 808836). Ethical approval was reviewed and waived as the study posed minimal risk to human subjects.

Informed Consent Statement

Informed consent was obtained from all subjects involved in the study.

Data Availability Statement

The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request.

Acknowledgments

We thank the medical students who participated in our study.

Conflicts of Interest

The authors declare no conflicts of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.

Abbreviations

The following abbreviations are used in this manuscript:
MS1Medical Students in year 1
MS2Medical Students in year 2
MS3Medical Students in year 3
MS4Medical Students in year 4

Appendix A

Appendix A.1

Figure A1. Individual trajectories of cognitive empathy across measurement rounds.
Ime 05 00056 g0a1

Appendix A.2

Figure A2. Individual trajectories of compassion across measurement rounds.
Ime 05 00056 g0a2

Appendix A.3

Figure A3. Individual trajectories of self-compassion across measurement rounds.
Ime 05 00056 g0a3

Appendix A.4

Figure A4. Individual trajectories of resilience across measurement rounds.
Ime 05 00056 g0a4

Appendix A.5

Figure A5. Resilience differences across medical school cohorts.
Ime 05 00056 g0a5

References

  1. Patel, S.; Pelletier-Bui, A.; Smith, S.; Roberts, M.B.; Kilgannon, H.; Trzeciak, S.; Roberts, B.W. Curricula for empathy and compassion training in medical education: A systematic review. PLoS ONE 2019, 14, e0221412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Neumann, M.; Wirtz, M.; Bollschweiler, E.; Mercer, S.W.; Warm, M.; Wolf, J.; Pfaff, H. Determinants and patient-reported long-term outcomes of physician empathy in oncology: A structural equation modelling approach. Patient Educ. Couns. 2007, 69, 63–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Epstein, R.M.; Franks, P.; Shields, C.G.; Meldrum, S.C.; Miller, K.N.; Campbell, T.L.; Fiscella, K. Patient-centered communication and diagnostic testing. Ann. Fam. Med. 2005, 3, 415–421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. The Premed Competencies for Entering Medical Students. Students & Residents. Available online: https://students-residents.aamc.org/real-stories-demonstrating-premed-competencies/premed-competencies-entering-medical-students (accessed on 25 March 2026).
  5. Kim, S.S.; Kaplowitz, S.; Johnston, M.V. The effects of physician empathy on patient satisfaction and compliance. Eval. Health Prof. 2004, 27, 237–251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Thomas, M.R.; Dyrbye, L.N.; Huntington, J.L.; Lawson, K.L.; Novotny, P.J.; Sloan, J.A.; Shanafelt, T.D. How do distress and well-being relate to medical student empathy? A multicenter study. J. Gen. Intern Med. 2007, 22, 177–183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Chen, D.C.R.; Kirshenbaum, D.S.; Yan, J.; Kirshenbaum, E.; Aseltine, R.H. Characterizing changes in student empathy throughout medical school. Med. Teach. 2012, 34, 305–311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Hojat, M.; Vergare, M.J.; Maxwell, K.; Brainard, G.; Herrine, S.K.; Isenberg, G.A.; Veloski, J.; Gonnella, J.S. The Devil is in the Third Year: A Longitudinal Study of Erosion of Empathy in Medical School. Acad. Med. 2009, 84, 1182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Andersen, F.A.; Johansen, A.-S.B.; Søndergaard, J.; Andersen, C.M.; Assing Hvidt, E. Revisiting the trajectory of medical students’ empathy, and impact of gender, specialty preferences and nationality: A systematic review. BMC Med. Educ. 2020, 20, 52. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Caruana, E.J.; Roman, M.; Hernández-Sánchez, J.; Solli, P. Longitudinal studies. J. Thorac. Dis. 2015, 7, E537–E540. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Román-Calderón, J.P.; Krikorian, A.; Ruiz, E.; Romero, A.M.; Lemos, M. Compassion and Self-Compassion: Counterfactors of Burnout in Medical Students and Physicians. Psychol. Rep. 2024, 127, 1032–1049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Roslan, N.S.; Yusoff, M.S.B.; Morgan, K.; Ab Razak, A.; Ahmad Shauki, N.I. What Are the Common Themes of Physician Resilience? A Meta-Synthesis of Qualitative Studies. Int. J. Environ. Res. Public Health 2022, 19, 469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Byrne, M.; Campos, C.; Daly, S.; Lok, B.; Miles, A. The current state of empathy, compassion and person-centred communication training in healthcare: An umbrella review. Patient Educ. Couns. 2024, 119, 108063. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Wang, C.X.Y.; Pavlova, A.; Boggiss, A.L.; O’Callaghan, A.; Consedine, N.S. Predictors of Medical Students’ Compassion and Related Constructs: A Systematic Review. Teach. Learn. Med. 2023, 35, 502–513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. McDonald, R.P. Test Theory: A Unified Treatment; Psychology Press: New York, NY, USA, 2013. [Google Scholar] [CrossRef] [Scilit]
  16. Padilla, M.A.; Divers, J. A Comparison of Composite Reliability Estimators. Educ. Psychol. Meas. 2016, 76, 436–453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Davis, M.H. Interpersonal reactivity index. JSAS Cat. Sel. Doc. Psychol. 1980, 10, 85. [Google Scholar]
  18. Lee, Y.-M.; Park, H.; Shin, H.S.; Huh, S. Validation of a Modified Version of Interpersonal Reactivity Index for Medical Students Using Rasch Analysis. Teach. Learn. Med. 2023, 35, 346–355. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Plante, T.G. Santa Clara Brief Compassion Scale (SCBCS). In Handbook of Assessment in Mindfulness Research; Medvedev, O.N., Krägeloh, C.U., Siegert, R.J., Singh, N.N., Eds.; Springer International Publishing: Cham, Switzerland, 2022; pp. 1–7. [Google Scholar] [CrossRef] [Scilit]
  20. Sinclair, S.; Russell, L.B.; Hack, T.F.; Kondejewski, J.; Sawatzky, R. Measuring Compassion in Healthcare: A Comprehensive and Critical Review. Patient 2017, 10, 389–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Neff, K.D. Self-Compassion Scale; American Psychological Association: Washington, DC, USA, 2003. [Google Scholar] [CrossRef] [Scilit]
  22. Neff, K.D.; Tóth-Király, I.; Yarnell, L.M.; Arimitsu, K.; Castilho, P.; Ghorbani, N.; Guo, H.X.; Hirsch, J.K.; Hupfeld, J.; Hutz, C.S.; et al. Examining the factor structure of the Self-Compassion Scale in 20 diverse samples: Support for use of a total score and six subscale scores. Psychol. Assess. 2019, 31, 27–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Babenko, O.; Guo, Q. Measuring Self-Compassion in Medical Students: Factorial Validation of the Self-Compassion Scale–Short Form (SCS-SF). Acad. Psychiatry 2019, 43, 590–594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Connor, K.M.; Davidson, J.R.T. Development of a new resilience scale: The Connor-Davidson Resilience Scale (CD-RISC). Depress. Anxiety 2003, 18, 76–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Campbell-Sills, L.; Stein, M.B. Psychometric analysis and refinement of the Connor–Davidson resilience scale (CD-RISC): Validation of a 10-item measure of resilience. J. Trauma. Stress 2007, 20, 1019–1028. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Almanasef, M.; Bajis, D.; Al-Haqan, A.; Alnahar, S.; Bates, I. Assessing the psychometric properties of Connor-Davidson Resilience Scale 25 (CD-RISC 25) in pharmacy students and academics in the Eastern Mediterranean Region. Explor. Res. Clin. Soc. Pharm. 2024, 16, 100515. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Gueorguieva, R.; Krystal, J.H. Move over ANOVA: Progress in analyzing repeated-measures data and its reflection in papers published in the Archives of General Psychiatry. Arch. Gen. Psychiatry 2004, 61, 310–317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Helminen, E.C.; Scheer, J.R.; Felver, J.C. Gender Differences in the Associations Between Mindfulness, Self-Compassion, and Perceived Stress Reactivity. Mindfulness 2021, 12, 2173–2183. [Google Scholar] [CrossRef] [Scilit]
  29. Lee, E.E.; Govind, T.; Ramsey, M.; Wu, T.C.; Daly, R.; Liu, J.; Tu, X.M.; Paulus, M.P.; Thomas, M.L.; Jeste, D.V. Compassion toward others and self-compassion predict mental and physical well-being: A 5-year longitudinal study of 1090 community-dwelling adults across the lifespan. Transl. Psychiatry 2021, 11, 397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Simmons, A.; Ferry, M.; Christopher, M. Relative Impact of Mindfulness, Self-Compassion, and Psychological Resilience on Mental Health Outcomes in Racially Minoritized Adults. Psychol. Rep. 2023, 128, 4015–4034. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Boyraz, G.; Legros, D.N.; Berger, W.B. Self-criticism, self-compassion, and perceived health: Moderating effect of ethnicity. J. General. Psychol. 2021, 148, 149–167. [Google Scholar] [CrossRef] [Scilit]
  32. Howick, J.; Dudko, M.; Feng, S.N.; Ahmed, A.A.; Alluri, N.; Nockels, K.; Winter, R.; Holland, R. Why might medical student empathy change throughout medical school? a systematic review and thematic synthesis of qualitative studies. BMC Med. Educ. 2023, 23, 270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Cohen, J. Statistical Power Analysis for the Behavioral Sciences; Lawrence Erlbaum Associates Inc.: Hillsdale, NJ, USA, 1988; p. 19. [Google Scholar]
  34. Smith, K.E.; Norman, G.J.; Decety, J. The complexity of empathy during medical school training: Evidence for positive changes. Med. Educ. 2017, 51, 1146–1159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Rosenthal, S.; Howard, B.; Schlussel, Y.R.; Herrigel, D.; Smolarz, B.G.; Gable, B.; Vasquez, J.; Grigo, H.; Kaufman, M. Humanism at Heart: Preserving Empathy in Third-Year Medical Students. Acad. Med. 2011, 86, 350. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Wolf, S.J.; Lockspeiser, T.M.; Gong, J.; Guiton, G. Students’ Perspectives on the Fourth Year of Medical School: A Mixed-Methods Analysis. Acad. Med. 2014, 89, 602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Triffaux, J.-M.; Tisseron, S.; Nasello, J.A. Medical Students’ Empathy during the COVID-19 Pandemic: A Cross-Sectional Study. Int. J. Emot. Educ. 2023, 15, 73–88. [Google Scholar] [CrossRef] [Scilit]
  38. Ahrweiler, F.; Neumann, M.; Goldblatt, H.; Hahn, E.G.; Scheffer, C. Determinants of physician empathy during medical education: Hypothetical conclusions from an exploratory qualitative survey of practicing physicians. BMC Med. Educ. 2014, 14, 122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Girard, A.O.; Qiu, C.; Lake, I.V.; Chen, J.; Lopez, C.D.; Yang, R. US Medical Student Perspectives on the Impact of a Pass/Fail USMLE Step 1. J. Surg. Educ. 2022, 79, 397–408. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Liao, K.Y.-H.; Stead, G.B.; Liao, C.-Y. A Meta-Analysis of the Relation Between Self-Compassion and Self-Efficacy. Mindfulness 2021, 12, 1878–1891. [Google Scholar] [CrossRef] [Scilit]
  41. Babenko, O.; Oswald, A. The roles of basic psychological needs, self-compassion, and self-efficacy in the development of mastery goals among medical students. Med. Teach. 2019, 41, 478–481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Dyrbye, L.N.; Power, D.V.; Massie, F.S.; Eacker, A.; Harper, W.; Thomas, M.R.; Szydlo, D.W.; A Sloan, J.; Shanafelt, T.D. Factors associated with resilience to and recovery from burnout: A prospective, multi-institutional study of US medical students. Med. Educ. 2010, 44, 1016–1026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Yarnell, L.M.; Stafford, R.E.; Neff, K.D.; Reilly, E.D.; Knox, M.C.; Mullarkey, M. Meta-Analysis of Gender Differences in Self-Compassion. Self Identity 2015, 14, 499–520. [Google Scholar] [CrossRef] [Scilit]
  44. Rochat, M.J. Sex and gender differences in the development of empathy. J. Neurosci. Res. 2023, 101, 718–729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Gardiner, P.; Pérez-Aranda, A.; Bell, N.; Clark, D.R.; Schuman-Olivier, Z.; Lin, E.H. Self-Compassion for Healthcare Communities: Exploring the Effects of a Synchronous Online Continuing Medical Education Program on Physician Burnout. J. Contin. Educ. Health Prof. 2025, 45, 119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Cherry, M.G.; Fletcher, I.; O’Sullivan, H.; Dornan, T. Emotional intelligence in medical education: A critical review. Med. Educ. 2014, 48, 468–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Cognitive empathy differences across medical school cohorts.
Ime 05 00056 g001
Figure 2. Compassion differences across medical school cohorts.
Ime 05 00056 g002
Figure 3. Self-compassion differences across medical school cohorts.
Ime 05 00056 g003
Table 1. Sample cohort distribution and demographic characteristics.
CharacteristicTotal Sample, N = 98
Age, M (SD), Age range26.34 (2.86), 22–40
Cohort, n (%)
              MS125 (25.5)
              MS225 (25.5)
              MS320 (20.4)
              MS426 (26.5)
              Missing2 (2.0)
Gender identity, n (%)
              Female57 (58.2)
              Male39 (39.9)
              Missing2 (2.0)
Race/ethnicity, n (%)
              Asian32 (32.7)
              Black3 (3.1)
              Hispanic/Latinx10 (10.2)
              Multiracial13 (13.3)
              White37 (37.8)
              Missing3 (3.1)
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.