
Systematic Review

Systematic Review of the Impact of Nutritional Support on the Mental Health and Quality of Life of Dependent Older Adults


Department de Psicologia Bàsica, Faculty of Psychology and Speech Therapy, Universitat de València, Av. Blasco Ibañez, 21, 46010 Valencia, Spain
*
Author to whom correspondence should be addressed.
Dietetics 2025, 4(4), 55; https://doi.org/10.3390/dietetics4040055
Submission received: 1 August 2025 / Revised: 17 October 2025 / Accepted: 17 November 2025 / Published: 1 December 2025

Abstract

Population aging has significantly increased the number of older adults in situations of dependency, where they are more vulnerable to mental health problems and a decline in quality of life. Several studies have suggested that nutritional support could play a key role in improving these aspects. This study aimed to analyze the current scientific findings regarding how nutritional interventions influence mental well-being and life quality in elderly individuals with dependency. Following PRISMA methodology, literature was retrieved from internationally recognized bibliographic databases, including Web of Science, PubMed, Scopus, and ProQuest. Experimental and quasi-experimental studies that analyzed nutritional interventions aimed at dependent older adults with results related to mental health and/or quality of life were included. A total of 23 studies satisfying all inclusion standards were selected for the analysis. Most reported positive effects of nutritional interventions on mood, depressive symptoms, and/or perceived quality of life, although there was heterogeneity in the designs and measures used. Nutritional support may represent an effective strategy for improving mental health and quality of life in dependent older adults. However, further research with robust designs and standardized measures is needed to strengthen the available evidence.

Graphical Abstract

1. Introduction

1.1. Background

The increase in the ageing population currently represents a global social challenge, especially in high-income countries, where the proportion of elderly people continues to grow [1]. Among the elderly population, dependent older adults face many health problems due to their frailty, the frequent onset of chronic diseases and the absence of community support systems. Malnutrition is particularly noteworthy. Various studies report that between 30% and 60% of older adults in institutions or under long-term care have significant levels of malnutrition [2,3].
In Spain, for example, it is estimated that nearly 70% of older adults in situations of dependency are at some degree of nutritional risk, which has both clinical and functional consequences [2,3]. This situation is exacerbated by unwanted loneliness, polypharmacy and lack of access to adapted food services.
Nutritional status not only affects the physical health of older people, but is also associated with muscle loss, osteoporosis and reduced immune function [4]. At the same time, a large number of studies indicate a close relationship between nutrition and psychological and general well-being: good nutrition improves mood, reduces symptoms of depression and increases life satisfaction, while malnutrition can exacerbate physical and psychological problems [5,6]. Various biological mechanisms, such as low-grade inflammation or dysfunction in neurotransmitter synthesis, could explain this association [7].
Similarly, a recent review by [8] concluded that greater adherence to the Mediterranean diet is associated with lower levels of depression and anxiety in older adults, reinforcing the role of healthy eating patterns in mental health.
In this context, there has been growing interest in exploring comprehensive approaches that simultaneously address the physical and mental aspects of health in old age. Unlike pharmacological or exclusively psychological interventions, nutritional support represents a potentially accessible, sustainable and adverse-effect-free avenue for promoting overall well-being in this vulnerable population [9].

1.2. Potential Biological Mechanisms Linking Nutrition to Brain Health

The association between nutrition and psychological well-being is supported by robust biological mechanisms. A key pathway involves the regulation of neuroinflammation and oxidative stress. For instance, a human cohort study incorporating dietary assessment and MRI demonstrated that adherence to a Mediterranean diet, modulated by the gut microbiome, is associated with reduced systemic inflammation and oxidative stress [10]. These mechanisms play crucial roles in various neurological disorders. In Parkinson’s disease, in vivo models and post-mortem human brain tissue analyses indicate that oxidative stress participates in disease pathogenesis, while neuroinflammation is indirectly involved through microglial responses [11]. In depression research, in vivo and post-mortem experiments in rhesus monkeys reveal that upregulation of inflammatory pathways coupled with downregulation of oxidative phosphorylation collectively lead to dopamine deficiency, reflecting inflammation-driven metabolic disturbances [12]. Additionally, spatial transcriptomics has identified specific inflammatory responses within plaque-glia niches in Alzheimer’s disease brains [13], and transcriptomic and methylation analyses have revealed dysregulated inflammatory pathways in the brains of people who died by suicide [14]. Notably, preclinical studies have demonstrated that restrictive eating behaviors can induce severe mitochondrial dysfunction and disruption of intracellular redox balance in the brain [15], highlighting the fundamental role of adequate nutrient intake in maintaining neuronal integrity.
Mechanistically, nutrition regulates neurodegenerative and mental disorders through multiple pathways. For example, the Mediterranean diet can reduce systemic inflammation and oxidative stress by modulating the gut microbiota, thereby exerting a protective effect against diseases like Alzheimer’s [10,16]. Imbalanced nutrient intake may lead to mitochondrial energy metabolism disorders and impair the antioxidant defense system in brain tissue, while sufficient intake of nutrients such as vitamin C and coenzyme Q10 can improve mitochondrial function and enhance antioxidant capacity [11]. Furthermore, nutrients serve as direct precursors for neurotransmitters; for instance, tryptophan and tyrosine are essential substrates for serotonin and dopamine synthesis, respectively, and participate in the regulation of stress hormones like cortisol, thereby directly influencing mood and cognitive function. Therefore, the psychological and cognitive benefits of nutritional interventions observed in older adults may be mediated, at least partially, through the modulation of these core pathways. Elucidating these mechanisms is crucial for exploring nutritional intervention strategies to improve the mental health and quality of life of functionally dependent older adults.

1.3. Gap in Knowledge and Rationale for the Review

Against this backdrop, there is growing interest in comprehensive intervention strategies that simultaneously address both physical and psychological health in older adults. Compared to pharmacological or purely psychological interventions, nutritional support represents a potentially more accessible, sustainable, and low-side-effect strategy for enhancing overall well-being in this vulnerable population [9].
However, despite increasing attention in this field, a significant knowledge gap persists. Most existing research focuses on autonomous older adults or specific clinical populations (such as those with dementia or neurological disorders), failing to adequately account for the significant functional and social heterogeneity characteristic of the dependent population [17]. This limitation substantially restricts the application of existing research findings in real-world clinical and social care practices.
Nevertheless, some recent studies, such as that by [18], indicate that good nutritional status is significantly associated with better quality of life perceptions among older adults, Furthermore, observational evidence from Yu et al. [19] also confirms a close association between nutritional metabolism and the status of depression and cognition in community-dwelling older adults, reinforcing the need to further explore this approach in more vulnerable populations. Nutritional interventions may positively impact the psychological and physiological status of dependent older adults. These needs may vary according to health status and care setting (e.g., home care vs. institutionalization), highlighting the importance of adapting nutritional strategies to individual characteristics [20].
Consequently, there is an urgent need to establish a solid and targeted evidence base to inform clinical, policy, and community decisions aimed at improving the emotional well-being and quality of life of this high-risk group. This systematic review aims to address this gap by exclusively focusing on functionally dependent older adults, incorporating studies in Spanish, English, and Chinese, to develop a broader, more diverse perspective, thereby enhancing the applicability of the findings across different clinical and social policy contexts.

1.4. Theoretical Perspective

This study is grounded in three core concepts: mental health, quality of life, and functional dependency.
According to the World Health Organization, mental health is a state of well-being in which individuals realize their own potential, can cope with the normal stresses of life, can work productively, and are able to contribute to their community. In older adults, physiological, psychological, and social factors can all affect this state.
Quality of life is understood as an individual’s subjective perception of their position in life within the context of their culture, expectations, goals, and concerns [21]. It is a multidimensional construct encompassing physical, psychological, social, and environmental dimensions, operationalized by the WHO through the WHOQOL model. This model assesses quality of life across six fundamental domains: physical health, psychological state, level of independence, social relationships, environment, and spirituality/personal beliefs. This structure facilitates a more comprehensive understanding of well-being, particularly useful for complex populations such as functionally dependent older adults [21].
Finally, functional dependency is defined as the need for assistance in performing basic or instrumental activities of daily living, serving as a determining factor in the autonomy and well-being of older adults [22].
These three concepts are closely interrelated. Functionally dependent older adults face a greater risk of mental health deterioration and reduced quality of life, particularly in the absence of appropriate interventions. In this context, nutritional support is proposed as a potential strategy to positively influence both well-being indicators from an integrative perspective.
Therefore, this study employs a systematic review methodology to comprehensively analyze recent studies on the effects of nutritional support on the mental health and quality of life of dependent older adults, aiming to provide a solid foundation for future geriatric interventions in both clinical practice and social-health policy design. Although previous reviews exist, some exploring the relationship between nutrition and mental health in older people, many focus on autonomous populations or specific clinical contexts [23]. The distinctiveness of this review lies in its exclusive focus on functionally dependent older adults, a highly vulnerable group largely overlooked from an integrated perspective. Moreover, it incorporates studies in Spanish, English, and Chinese, enabling a broader and more contextualized viewpoint. This multidimensional approach enhances the applicability of the findings in both clinical settings and social-health policy design.

1.5. Research Objectives

The overall objective of this systematic review is to analyse the effects of nutritional support on the mental health and quality of life of older people in a situation of functional dependency, with the aim of providing useful evidence for the design of future interventions in the clinical and social health care settings.
Specifically, we aim to examine the different types of nutritional interventions described in the recent scientific literature, including oral supplements, enteral nutrition and adapted diets, as well as their impact on specific mental health variables such as depression, anxiety, mood and psychological well-being. In addition, we seek to identify possible improvements in different dimensions of quality of life, such as functional autonomy, social participation and life satisfaction. Finally, possible differences in results will be analysed according to the care context, comparing studies carried out in institutional and home settings to assess the influence of the type of care received.
Likewise, the possible differential effects between different types of nutritional intervention will be explored, assessing whether certain approaches show greater benefits in certain aspects of psychological well-being or quality of life. The dimensions of quality of life analysed include functional autonomy, social participation and overall perception of well-being.
Based on this general objective, the following research question is posed, structured according to the PICO model: In older adults with functional dependence (P), do nutritional interventions (I), compared to usual care or no intervention (C), produce improvements in mental health and quality of life (O)?
This systematic review protocol has been registered in the international database PROSPERO (International Prospective Register of Systematic Reviews) with the registration number CRD420251048527.
Available at: https://www.crd.york.ac.uk/PROSPERO/view/CRD420251048527 (accessed on 8 May 2025).

2. Materials and Methods

2.1. Methodology

2.1.1. Study Design

This study adopts a systematic literature review approach, following the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) guidelines, in order to systematically and comprehensively assess the impact of nutritional support on the mental health and quality of life of dependent older people. The completed PRISMA 2020 checklist is provided in Supplementary Table S1 [24]. To ensure the scientific rigour of the studies included, this study will mainly include randomised controlled trials (RCTs), cohort studies and case–control studies, thus providing higher quality scientific evidence [20].
According to the criteria of the World Health Organisation (WHO), older people are defined in this study as those aged 60 years or older. This criterion is widely used in geriatrics and public health and helps to ensure the uniformity of the study population and improve the applicability of the results. Special attention was paid to older adults with some degree of dependency to explore the impact of nutritional interventions on their mental health and quality of life [25].

2.1.2. Search Strategy

A structured literature search was conducted in four high-impact academic databases: Web of Science, Scopus, PubMed and ProQuest.
These databases were selected based not only on their international reputation, but also on their complementary characteristics: Web of Science and Scopus are known for their multidisciplinary coverage and bibliometric analysis; PubMed focuses on health sciences and evidence-based medicine; and ProQuest provides access to relevant social research. This strategic selection allows the topic to be addressed from a comprehensive perspective, covering both clinical evidence and the field of social health.
To improve search accuracy, Boolean operators (‘AND’, ‘OR’) and a structured combination of keywords related to nutritional interventions, the target population and the expected outcomes were used.
The general formula used was: (‘nutrition support’ OR ‘dietary intervention’ OR ‘nutritional supplementation’) AND (‘elderly’ OR ‘older adults’ OR ‘aged’) AND (‘mental health’ OR “depression” OR ‘quality of life’ OR ‘cognition’).
Although the term ‘functional dependence’ was not directly included in the search equation, broader descriptors such as ‘older adults’ or ‘elderly’ were used to avoid excluding relevant studies that, although not mentioned in the title or abstract, do address dependent populations in the full text. The specific inclusion of this population was carried out later during the selection process using the inclusion and exclusion criteria defined in the methodology.
This combination of terms was slightly adjusted according to the controlled descriptors (MeSH, Thesaurus, etc.) and filters available in each database, ensuring adaptability without losing consistency between platforms.
No initial date limit was applied: the search was conducted from the start of indexing of each database until December 2024, allowing both pioneering research and the most recent studies to be included. This broad time frame favours the historical and analytical representativeness of the selected studies.

2.1.3. Inclusion Criteria

Quantitative studies were included that analysed the effects of nutritional interventions in people over 60 years of age with some degree of functional dependence. Functional dependence was operationalized as either explicitly stated by the original authors or inferred from the care context (e.g., institutionalization, receipt of home care with support for daily activities). The interventions had to have a main nutritional component, including oral supplements, enteral nutrition, or therapeutic diets. The selected studies also had to report at least one outcome related to mental health (e.g., symptoms of depression, anxiety, emotional well-being) or quality of life, assessed using validated instruments. Only publications available in full text and written in English, Spanish, or Chinese were considered. This language selection was made to ensure a feasible yet comprehensive scope, as these languages cover the major academic outputs in this field and align with the research team’s linguistic capabilities, enabling rigorous and accurate analysis.

2.1.4. Exclusion Criteria

Studies whose participant group consisted exclusively of people under the age of 60 were excluded. Studies that did not allow for inference of functional dependence based on the population description (e.g., focusing solely on autonomous community-dwellers) were also excluded. Studies that evaluated only clinical or nutritional parameters without considering psychological or quality-of-life variables were excluded. While large-scale randomized controlled trials (RCTs) were prioritized, the challenging nature of conducting such studies in this vulnerable population means the evidence base is diverse. Therefore, to ensure a comprehensive overview of the existing literature, we did not automatically exclude studies with smaller sample sizes (<30) or those employing alternative robust designs (e.g., pre–post studies). However, studies with critical methodological flaws, such as a complete lack of baseline data or severely high attrition rates, were excluded. Additionally, studies that did not clearly describe the nutritional intervention, were written in other languages, or whose full text was unavailable were excluded.

2.2. Data Extraction and Analysis

Data extraction was performed using standardised forms to ensure consistency and accuracy in the process. Data were collected on the characteristics of the study (author, year of publication, country, design), characteristics of the participating population (sample size, age, sex), type and duration of the nutritional intervention, and outcomes related to psychological and functional well-being (e.g., anxiety levels, depressive symptoms, overall perception of quality of life).
The methodological quality of the included studies was assessed using the Joanna Briggs Institute (JBI) critical appraisal tool, adapted to the specific design of each study (controlled trials, cohort studies, etc.). The assessment was carried out by two reviewers independently, and discrepancies were resolved by consensus.
Studies were selected using the Covidence platform, after importing the references from EndNote, which allowed for systematic and structured management of the review process. Homogeneous instruments were used to assess the titles, abstracts and full content of the articles. The assessment was carried out by two reviewers independently, and differences in assessment were resolved by agreement between the reviewers.
Given the anticipated methodological heterogeneity among the studies, a narrative synthesis will be used to summarise the findings. Heterogeneity will be assessed by considering differences in population, type of intervention, duration, and outcome measures.

3. Results

This section presents the results obtained from the studies included in the systematic review. Through a joint analysis of the available evidence, the main contributions of nutritional interventions to optimising the emotional and psychological well-being of dependent older people are summarised.

3.1. Study Selection

This study followed the PRISMA flow chart to systematically select the literature, as detailed in Figure 1. Initially, 1331 articles were retrieved from four databases (Web of Science, Scopus, PubMed and ProQuest). After removing duplicates using the Covidence platform, 1108 articles remained and proceeded to the preliminary selection phase of titles and abstracts. In this phase, 967 articles that did not meet the inclusion criteria were discarded, leaving a total of 141 articles for full-text evaluation. During the full-text evaluation phase, among the 141 articles, 118 were excluded due to wrong outcomes (n = 17), wrong indication (n = 3), wrong intervention (n = 22), wrong study design (n = 40), and wrong patient population (n = 36). Finally, according to the pre-established inclusion and exclusion criteria, 23 studies were confirmed for inclusion as the final sample of this systematic review.

3.2. Basic Characteristics of the Included Studies

The 23 studies included in this systematic review cover a wide range of geographical locations, methods and population characteristics. From a geographical point of view, these studies come from Spain, Italy, Germany, the United States, Japan, and Brazil, among other places, and provide information on the effectiveness of nutritional interventions in multicultural contexts.
In terms of study design, of the 23 studies included, 18 were randomised controlled trials (78%) and 5 were quasi-experimental (22%). The duration of the interventions ranged from 4 weeks to 24 months. In terms of sample size, 5 studies included fewer than 50 participants (22%), 10 studies included between 51 and 150 participants (43%), and 8 studies included more than 150 participants (35%). All participants were older adults with some functional dependence.
The types of nutritional intervention included: nutritional supplements such as omega-3 fatty acids, B vitamins, vitamin D, etc. (13 studies, 57%), nutritional education programmes (6 studies, 26%) and personalised meal plans (4 studies, 17%). The main outcome measures included symptoms of depression, cognitive function and quality of life, assessed using scales such as GDS, MMSE, SF-36, EQ-5D and WHOQOL-BREF.

3.3. Methodological Quality Assessment

Methodological quality was assessed using an adaptation of the JBI instrument for quasi-experimental studies and the Cochrane Risk of Bias Tool for RCTs. Each study was analysed in terms of its internal validity, transparency in the randomisation process, use of control groups, participant follow-up and reporting of results.
Overall, moderate methodological quality was observed in 13 studies (57%) and high quality in 10 studies (43%). However, approximately one-third of the studies (8 out of 23, 35%) had limitations, such as small sample sizes, high dropout rates, or lack of blinding of evaluators. These shortcomings have been taken into account when interpreting the results and are highlighted in Table A1 of this review.

3.4. Improvements in Mental Health

Several studies included in this review show that nutritional interventions have a positive impact on the mental health of dependent older adults, especially on symptoms such as depression, anxiety, and emotional distress [2,26,27].
For example, Chojnacki et al. [7] conducted a clinical trial in older adults, which found that increased intake of tryptophan (an amino acid precursor of serotonin) produced a significant improvement in depressive symptoms, anxiety and sleep quality. This effect was also linked to a reduction in inflammatory markers, reinforcing the role of nutrition in regulating mood in older people.
In addition to fatty acids and amino acids, other strategies focused on micronutrient supplementation have shown promising results. For example, Remington et al. [6] and Rondanelli et al. [28] indicated that the administration of B vitamins, vitamin D, amino acids and various micronutrients can significantly improve emotional state and quality of life in older adults with cognitive impairment or chronic diseases. This multidimensional approach reinforces the value of integrated nutritional interventions as an effective complement to the psychological care of older adults with functional dependence.

3.5. Effects on Cognitive Function

Nutritional interventions also show promising effects on the preservation and improvement of cognitive function in dependent older adults. In particular, some long-term intervention studies highlight significant improvements in standardised cognitive indicators.
For example, Komulainen et al. [26] conducted a four-year RCT in which a healthy diet was combined with aerobic exercise, observing a significant improvement in CERAD test scores. Similar results were reported by Wade et al. [29] and Tsuboi et al. [11], who demonstrated that dietary patterns rich in fibre, fruit, vegetables and fish, combined with physical activity, can contribute to cognitive maintenance.
Similarly, studies such as those by Chen et al. [30] and Rondanelli et al. [25] showed that a diet rich in antioxidants, especially vitamin E and polyunsaturated fatty acids, can slow the progression of mild cognitive impairment (MCI). These findings support the potential preventive role of nutrition in neurodegenerative diseases such as Alzheimer’s.

3.6. Impact on Quality of Life

In relation to quality of life, evidence from the scientific literature supports the positive changes brought about by nutritional interventions. These are not limited to psychological improvements; studies such as those by Miller et al. [31], Tsuboi et al. [32] and von Berens et al. [33] have also documented improvements in physical functioning, such as increased mobility and muscle strength, in sleep quality with fewer night-time interruptions or better perceived rest, and in the ability to perform everyday activities, such as dressing, washing and preparing meals independently.
In a double-blind, randomised, controlled trial in older adults with sarcopenia, intake of a nutritional supplement complex (whey protein, leucine and vitamin D) significantly improved lean body mass, muscle strength and handgrip strength scores, along with notable improvements in quality of life scores (e.g., SF-36) during a 12-week intervention [28], where a greater sense of social engagement, recovery of self-management skills and reduction in chronic pain were also observed, all dimensions that reflect a better quality of life. There are even studies indicating that improving overall nutritional status can decrease substance dependence and reduce the intensity of care required, contributing not only to individual well-being but also to the sustainability of the social and healthcare system [34].

3.7. Nutritional Intervention Models

The nutritional intervention models used in the studies varied significantly, including the Mediterranean diet, the DASH diet, single or combined supplements, and nutritional education programmes. Therefore, the context, target population, and duration must be taken into account when comparing the effects of interventions. Some comprehensive interventions (e.g., dietary adjustments combined with exercise routines) tend to show a consistent advantage across multiple dimensions, while the effects of single-nutrient interventions (e.g., supplementation with vitamin D or iron alone) are susceptible to an individual’s underlying nutritional status and comorbidities. Therefore, the available evidence suggests that individualised intervention design, cycle management, and combinations of multiple nutrients are more likely to achieve systemic health benefits.

3.8. Consistency and Variability of Studies

Despite some differences in the included studies in terms of intervention design, study populations, and outcome measures, there is good directional consistency in the results of the scientific literature in terms of overall trends. Twenty studies (87%) support the positive role of nutritional interventions in improving the mental health and quality of life of dependent older adults.
In particular, the effects were more stable in studies with long-term interventions, larger samples, and standardised instrumental measures. In addition, there was a high degree of consistency across studies in the direction of improvement in depression scores, cognitive functioning, and quality of life. However, inconsistencies or heterogeneous differences in the results of some studies should not be overlooked.
First, at the level of research methodology, different studies used a variety of assessment tools, such as scales such as MMSE, MoCA and CERAD for cognitive functioning, and SF-36, EQ-5D and WHOQOL-BREF for quality of life, which led to results that were difficult to compare in terms of specific values. Second, given that the duration of the interventions ranged from four weeks to more than two years, it is possible that some short-term studies may not adequately reflect the long-term effects of nutritional interventions on psychological and quality of life outcomes. Third, dietary structure and health behaviours vary considerably across countries and cultures; for example, there are significant differences in dietary patterns and food availability between European and American countries and Mediterranean countries, which may affect the generalisability of the effects of interventions.
Furthermore, in terms of the study population, some studies included patients with mild cognitive impairment (MCI) or a history of depression or sarcopenia, while others targeted older adults living in the community or nursing home residents, and the difference in underlying health status may have led to biased results. Several studies were also assessed as having a moderate or high risk of bias due to small sample sizes, poor randomisation procedures, and high rates of missed visits, which may have affected the results.
Likewise, the different columns in Table A2 were considered in the interpretation of the findings. The main results were analysed according to each study and the outcome indicators used (such as cognitive, emotional or functional scales), and attention was paid to how these were assessed. Regarding effect size and confidence intervals (CI), values such as OR, RR, and HR were reported, which allowed estimating the magnitude and direction of the effect in most studies. When these data were not available, they were indicated as NR (Not Reported). This detailed analysis favours a rigorous assessment of the validity and usefulness of the results.
In conclusion, despite factors such as the heterogeneity of the instruments, the complexity of the intervention structure and differences in sample characteristics, twenty studies (87%) of the studies included in this systematic review were directionally consistent and fully support nutritional interventions as an effective means of improving mental health and quality of life in elderly dependent populations.

3.9. Effect Size and Statistical Precision

The effect sizes and their confidence intervals (CI) generally indicated a positive magnitude of the impact of nutritional interventions on the outcomes assessed. Measures such as odds ratio (OR), risk ratio (RR) and hazard ratio (HR) were used, and several studies showed significant effects with narrow intervals, as in the case of Miller et al. [35] (OR = 1.8, 95% CI [1.2, 2.7]) or Levak et al. [36] (OR = 2.0, 95% CI [1.2, 3.1]). This statistical precision reinforces the validity of the findings. However, some studies did not report these values (NR), which limits the ability to accurately interpret the quantitative impact of interventions in those cases.

4. Discussion

This study systematically reviewed 23 randomised controlled trials and quasi-experimental studies focusing on nutritional interventions to analyse their impact on the mental health and quality of life of dependent older people. Overall, most studies showed positive trends in favour of integrating nutritional interventions into the care system for older people. Despite differences in study contexts, intervention approaches, and assessment tools, their basic conclusions are consistent. Five aspects are discussed below: interpretation of results, comparison with existing scientific literature, analysis of mechanisms, limitations of the studies, and future lines of research.

4.1. Interpretation and Analysis of Mechanisms

The beneficial effects of nutritional interventions on mental health and quality of life can be explained from a dual physiological and psychosocial perspective. Older adults with functional dependence often have lower nutrient intake, loss of appetite, and chewing or swallowing disorders, which affect not only their physical health but also their emotional and cognitive stability through the neuroendocrine axis.
Furthermore, the studies reviewed suggest that an improvement in the usual diet is associated with improvements in mood, cognitive functioning and overall perception of well-being. These conclusions are particularly supported by longer-term studies with larger sample sizes and the use of standardised tools.

4.2. Comparison with Existing Studies

The results of this review are consistent with several existing systematic reviews. For example, a meta-analysis published by Remington et al. [6] in Clinical Nutrition noted that a combined supplement containing vitamin D with omega-3 was supported by moderately strong evidence in reducing depressive symptoms, showing a notable impact in older adults with chronic diseases. In the present review, this conclusion is also supported by several studies [2,4,8,31]. This review also highlights the fact that nutritional interventions should be used as part of a comprehensive care programme, especially in long-term care facilities.
In contrast to some of the more outcome-oriented reviews, this review had a broader scope and covered outcomes ranging from depression and anxiety [2,15] to cognitive functioning [3,23,37] and overall perceptions of quality of life, hence the absence of a significant effect of the intervention in individual studies. For example, no direct improvements in cognitive status were observed with vitamin B12 supplementation in a multinational controlled study [17]. This suggests that the moderating effects of specific nutrients, underlying nutritional status, and individual differences should be taken into account when interpreting the scientific literature. Thomson et al. [38], through a systematic review, highlighted that oral administration of nutritional interventions proved effective in improving overall well-being.

4.3. Exploration of Mechanisms

Several mechanisms could explain the positive effects observed. Firstly, the anti-inflammatory action of nutrients such as omega-3 fatty acids or vitamin E contributes to reducing inflammatory biomarkers such as CRP or IL-6, which are associated with neurocognitive decline and depression [12].
Secondly, certain micronutrients such as vitamins B6, B9 and B12 are involved in neurotransmitter synthesis and homocysteine metabolism, which influences mood regulation. In addition, adequate protein intake facilitates the availability of serotonin and dopamine precursors, which are key to emotional stability.
Another relevant mechanism is the interaction between nutrition and the gut microbiota, which affects the gut–brain axis. Improving bacterial diversity has been associated with a decrease in depressive symptoms. Indirect effects of nutrition on sleep quality and circadian rhythms have also been proposed, with secondary emotional benefits. Finally, nutritional interventions can reinforce a sense of self-care, motivation and adherence, factors which, although less quantifiable, influence the perception of well-being.

4.4. Limitations of the Research

Although this review has strictly followed the standard systematic review process, certain limitations must be acknowledged. First and most critically, the methodological heterogeneity of the included studies represents a fundamental challenge. While our inclusive approach—encompassing studies with diverse designs, including those without parallel control groups—was necessary to map the nascent evidence base in this vulnerable population, it inherently limits the strength of causal inferences that can be drawn. This diversity in design, combined with variability in target populations, intervention modalities, and outcome measurement tools (particularly for quality of life, where dimensions and scoring criteria differed significantly), complicates direct cross-study comparisons.
Second, the operational definition of the “dependent population” was inconsistent across studies. Some relied solely on ADL scores, while others used care settings (e.g., hospitalization or institutionalization) as a proxy. This lack of uniformity, as illustrated by the study of Yoshimura et al. [37]. which focused on hospitalized post-stroke patients, affects the homogeneity of the sample and limits the generalizability of findings to the broader community-dwelling geriatric population.
Finally, several studies exhibited methodological weaknesses, including small sample sizes, short follow-up durations, inadequate description of randomization and blinding procedures, and insufficient control over intervention fidelity. These factors collectively increase the risks of bias and may impact the validity of the individual study results. despite our comprehensive search across multiple international databases in three languages (English, Spanish, and Chinese), it is possible that some relevant studies were missed because they are not indexed in the databases we consulted.
Despite our comprehensive search strategy across multiple international databases in three languages, it is possible that we missed some relevant studies that are indexed in databases not covered by our search (e.g., Embase). This constitutes an additional limitation, as it may have affected the completeness of the evidence base gathered.
These limitations, however, do not diminish the value of this review but rather illuminate the current state of the field. They underscore the pressing need for the future research directions outlined below, particularly large-scale, well-controlled trials with standardized methodologies and consistent, clearly defined populations.

4.5. Future Lines of Research

More high-quality, multicentre RCTs with large samples and long-term follow-up should be conducted to improve the level of evidence and explore the sustained effects of interventions. A relevant example is the study by Ng et al. [39], which compared combined nutritional, physical and cognitive interventions and observed a significant reversal of frailty in older adults.
It would also be relevant to promote trials that include differential analyses according to the degree of functional dependence, allowing the establishment of intervention models that are more tailored to the specific needs of each subgroup of dependent older adults (e.g., mild vs. severe). This would allow progress in the personalisation of support strategies, a key aspect for optimising their effectiveness and cost–benefit ratio.
Secondly, emphasis should be placed on the design of individualised intervention programmes, combining nutritional risk screening tools with individual preferences to develop differentiated intervention strategies for older adults with different nutritional status and functional levels. In addition, the exploration of mechanisms should be strengthened, using imaging and biochemistry to comprehensively assess the pathways of nutritional effects on the nervous system and psychological status.
In the methodological field, it is necessary to move towards the use of mixed designs that combine quantitative and qualitative assessment in order to capture not only changes in objective clinical variables, but also the subjective perception of well-being, motivation, adherence and satisfaction of participants and their carers.
In addition, the exploration of mechanism research should be strengthened, using imaging and biochemistry to comprehensively assess the pathways of nutritional effects on the nervous system and psychological state.
Finally, collaborative research projects between countries with diverse socioeconomic and cultural contexts should be encouraged, with the aim of validating intervention models that are generally applicable and not limited to a single region.
This approach would facilitate the development of more inclusive and effective global recommendations.
In the practical sphere, it is recommended to promote the pilot implementation of nutritional interventions in elderly care institutions, family care and community health services, and to explore viable models and cost-effectiveness. At the same time, interdisciplinary collaboration should be strengthened, integrating geriatrics, nutrition, psychology and social work to build a continuum of nutritional care covering assessment, intervention and follow-up, with the aim of effectively improving the overall quality of life and mental health of the dependent elderly population.

5. Conclusions

This section summarises the main conclusions drawn from the studies analysed, with a specific focus on older adults in situations of dependency, organised according to the effects observed on their mental health and quality of life.

5.1. Improvement in Depression and Anxiety Through Nutritional Interventions

Depression and anxiety are highly prevalent in the dependent elderly population, affecting their adherence to treatment, self-care and quality of life. Eighteen articles (78%) in this review addressed psycho-emotional outcomes, nine (39%) of which reported positive improvements from nutritional interventions.
Deuschle et al. [39] implemented an individualised nutritional intervention in hospitalised patients, combining intensive dietary education with improved protein intake, and found that GDS scores decreased by 3.2 points after the intervention (p < 0.01), demonstrating a significant relationship between nutritional intake status and mood. Remington et al. [6], meanwhile, significantly reduced BDI-II scores over a 12-week period through a multivitamin intervention, validating the role of specific micronutrients in modulating neurotransmitter levels.
Four studies (17%) have highlighted the superiority of the overall structure of the dietary pattern over single supplementation. For example, the PREDIDEP study found a significant 27% reduction in the risk of depression in the intervention group with a Mediterranean dietary pattern [40], with the effect of the intervention being even more pronounced in patients with moderate to severe anxiety. Meanwhile, the social feeding programme in the study by Mahendra Kumar Trivedi et al. [41], which combined nutrition education, socialised dinners and psychological support, significantly increased life satisfaction and mood stability, suggesting that psychological improvement does not depend solely on nutrient intake but is also closely related to dinner contexts and social factors.
Three studies (13%) also point to the possibility that the intervention may fail or be insignificant. For example, in some samples with mild depression, the effects of the intervention were limited by the short duration of the intervention, interference from the context in which the medication was taken, or an incomplete social support system. noted that prolonged states of loneliness and emotional deprivation may diminish the independent effects of nutritional interventions. According to the studies reviewed, the most effective interventions tend to integrate a solid nutritional structure, sufficient duration, and adequate psychological or social support.
At a mechanical level, omega-3 fatty acids and vitamins B6, B9 and B12 can regulate neurotransmitter synthesis, reduce inflammatory factors (such as CRP and IL-6) and stabilise the gut–brain axis. Some studies have also suggested a pathway for nutritional improvement to ‘increase self-efficacy,’ i.e., indirectly improve psychological status through greater autonomy in eating behaviour and feedback from physical improvements.

Protection and Improvement of Cognitive Function Through Nutritional Interventions

Older dependent populations often have varying degrees of cognitive impairment, and research into nutritional interventions as a non-pharmacological means of slowing cognitive decline has been increasing over the years.
A total of 23 studies were included in this review, and the results clearly indicate that the group that received the intervention had higher scores on cognitive function tests compared to the control group on various scales, such as the MoCA, CERAD, and MMSE.
Using a 4-year RCT, Komulainen et al. [26] found that a combination of dietary intervention and aerobic exercise significantly improved total CERAD scores, with no significant differences in the diet or exercise groups alone. This result suggests that cognitive improvement may depend on multifactorial synergy. In the study by Kesse-Guyot et al. [31], based on the antioxidant intake index (DAI), each 1-point increase in DAI was positively associated with an increase in MoCA score, suggesting that synergistic intake of multiple nutrients is superior to a single intervention.
Remington et al. [6] also observed that the intervention group showed particularly significant gains in executive functioning, working memory, and spatial recall, which directly impact personal autonomy, daily activities, and independence. In addition, some studies have focused on the immediate effects of short-term interventions, such as the study by Larsen et al. in a Dutch nursing home, which found that just 8 weeks of omega-3 supplementation resulted in an observed increase in cognitive flexibility on the A/B trail-building task. On the other hand, Imaoka et al. [42] demonstrated in a clinical trial with community-dwelling older adults that a combined diet and physical exercise intervention resulted in clear benefits on cognitive function and social engagement among study participants, supporting the hypothesis that multifactorial strategies also benefit cognitive functioning in non-institutionalised settings [42].
Studies on cognitive mechanisms indicate that intake of vitamin B complex and protein protects nerve conduction efficiency by promoting the synthesis of neurotransmitters (acetylcholine, glutamate) and maintaining the structure of the nerve myelin sheath. Meanwhile, antioxidants such as vitamins E and C and polyphenols can slow oxidative damage in the hippocampus and frontal cortex. Several studies have also observed elevated BDNF expression, suggesting that cognitive improvement is not only a nutritional compensation effect but may also activate neuroplasticity mechanisms [18,31].

5.2. Promotional Effects of Nutritional Interventions on Quality of Life

Quality of life (QOL) encompasses dimensions of physical, psychological and social functioning and is an important indicator of the benefits of comprehensive interventions. Nineteen studies have systematically explored the effects of nutritional interventions on QOL.
Rondanelli et al. [28] used a combination of whey protein, leucine, and vitamin D to improve physical functioning dimensions by more than 20% and self-reported vitality levels by 15% on the SF-36 after a 12-week intervention. Tsuboi et al. [32] found in a day care setting that a rational dietary arrangement improved older adults’ participation and daily self-care, as evidenced by a steady increase in ADL scores and a reduction in caregiver dependence [32,40]. Similarly, Parsons et al. [43] found that oral nutritional supplements were more effective than dietary advice alone in improving quality of life in malnourished residents of geriatric centres.
Domínguez et al. [44] focused on the association between gut flora and mood, sleep, and willingness to socialise, and found that nutritional adjustments could indirectly affect multiple dimensions of QoL by modulating the proportion of short-chain fatty acid-synthesising flora. Some studies [35] have also mentioned that dietary adaptations that improve oral condition and swallowing function (e.g., soft semi-liquid foods) significantly increase meal comfort and enjoyment, which is an important avenue for improving QoL. Similarly, Wyers et al. [27] observed that after a nutritional intervention in older adults post-fracture, nutritional status improved significantly; although, no marked differences in quality of life were observed, which according to the authors could indicate the need for multidimensional interventions.
The stability of QoL improvement has been questioned in some studies, particularly in groups with severe dependency or comorbid cognitive impairment, where the effects of the intervention were not significant. Explanations may include limited subjective scoring ability, a care environment that restricts real food choices, or a lack of individual adaptation of the intervention programme.

5.3. Joint Effects of Integrated Multi-Objective Interventions

Thirteen studies (57%) of the studies included in this review applied multi-component interventions that combined at least two strategies, such as nutritional support, physical exercise, dietary education or psychosocial counselling. These designs more accurately reflect the real conditions of care for dependent older people, where multiple factors interact simultaneously.
For example, Komulainen et al. [26] conducted a four-year randomised controlled trial in which the combination of a healthy diet and aerobic exercise was found to be more effective in improving cognition, mood and quality of life than either intervention applied separately. Similarly, the study by Chen et al. [30], which incorporated the Mediterranean diet together with the organisation of social meals, showed improvements in both emotional state and cognitive flexibility, as well as in subjective perceptions of health.
In addition, five studies (21%) identified that the benefits of nutritional interventions tend to be more sustained when accompanied by social or functional components. Similarly, Chen et al. [30] observed that quality of life improved significantly with oral nutritional supplementation, but the effects diminished when this was not combined with opportunities for social interaction and regular physical stimulation.
Furthermore, some authors pointed out that multicomponent interventions that share common objectives and coordinated assessment systems—such as joint monitoring of nutritional status, cognitive function, and emotional well-being—can contribute to better clinical management and more efficient resource allocation in care settings for dependent individuals.

5.4. Summary and Recommendations

This systematic review suggests that scientific, individualised, and well-structured nutritional interventions can effectively improve mental health, cognitive function, and overall quality of life in dependent older people. Compared to single-nutrient supplements, multicomponent intervention programmes—which combine diet structure optimisation, lifestyle adjustments, and social interaction mechanisms, and are maintained for at least three months—tend to demonstrate more stable and significant outcomes across all indicators [45], particularly in promoting emotional stability, increasing cognitive flexibility and improving subjective happiness [46]. It is important to note that the included studies exhibited heterogeneity in intervention design, study populations, and outcome measures; therefore, these findings should be interpreted as indicating a promising trend rather than a definitive conclusion.
In healthcare practice, nutritional support could be considered a potential central component of the long-term care system. Based on the collaborative models observed in the literature, which often involved physicians, dietitians, nurses, and psychologists, it may be beneficial to establish standardised nutritional screening and assessment pathways. One approach could be to introduce nutritional and psychological intervention teams to develop and implement personalised programmes. In community and home care settings, strengthening the dissemination of nutritional education and involving family members—by developing dietary programmes adapted to different cultural contexts and functional levels—may improve adherence and intervention continuity.

5.5. Future Perspectives and Key Messages

To translate these findings into robust evidence and guide future innovation, several research priorities are identified. First, there is a pressing need for large-scale, multicentre randomised controlled trials (RCTs) that are specifically designed to monitor the long-term effectiveness of interventions lasting six months or more. Crucially, future studies should directly compare different collaborative models and intervention components to determine their relative importance, as this review could not ascertain such specifics. Second, research must delve deeper into the differential effects of nutritional interventions for special subgroups, such as the bedridden, elderly living alone, or populations in resource-poor areas, to optimise resource allocation and tiered care strategies. Finally, integrating nutritional support into comprehensive care plans alongside cognitive training, physical rehabilitation, and psychological counselling represents a key avenue for achieving interdisciplinary synergies, though the optimal integration model requires further empirical validation.
The key take-home message is that nutritional intervention should not be regarded as an ‘optional supplement’ but should be established as a core strategy for enhancing the overall health and preserving the dignity of dependent older people. However, realising this potential depends on generating more precise evidence through the comparative and implementation-focused research outlined above.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/dietetics4040055/s1, Table S1: PRISMA 2020 Checklist.

Author Contributions

Conceptualization, X.X. and M.M.-V.; methodology, X.X. and M.M.-V.; review protocol, X.X., database search, X.X. and M.M.-V., risk of bias, X.X. and M.M.-V., data screening, X.X. and M.M.-V.; writing—original draft preparation, X.X., writing—review and editing, M.M.-V.; supervision, X.X. and M.M.-V.; project administration, M.M.-V. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

The data presented in this study are available on request from the corresponding author.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

The following abbreviations are used in this manuscript:
ADAS-CogAlzheimer’s Disease Assessment Scale—Cognitive Subscale
ADLActivities of Daily Living
ANTAnimal Names Task
ApoE4Apolipoprotein E4
BDIBeck Depression Inventory
CANTABCambridge Automated Neuropsychological Test Battery
CES-DCentre for Epidemiological Studies Depression Scale
CIConfidence Interval
CRPC-reactive protein
CVLT-IICalifornia Verbal Learning Test—Second Edition
DADietary Advice
DRSDementia Rating Scale
DVSDietary Diversity Score
EQ-5D-3LEuroQol 5-Dimensional, 3-Level Questionnaire
EQ-VASEuroQol Visual Analogue Scale
EVOOExtra Virgin Olive Oil
FIMFunctional Independence Measure
GDSGeriatric Depression Scale
HADSHospital Anxiety and Depression Scale
HRHazard Ratio
IGF-1Insulin-like Growth Factor Type 1
IL-6Interleukin 6
MADRSMontgomery-Asberg Depression Rating Scale
MCSMental Component of the SF-36
MMSEMini-Mental State Examination
MNAMini Nutritional Assessment
MNA-SFMini Nutritional Assessment—Short Version
NFNutraceutical Formula
NPINeuropsychiatric Inventory
NU-AGENutrition in Ageing
ONSOral Nutritional Supplements
OROdds Ratio
QOLQuality of Life
RCTRandomised Clinical Trial
RRRelative Risk
SAMS-adenosylmethionine
SF-3636-item Health Questionnaire
SMISkeletal Muscle Mass Index
SPPBShort Physical Performance Battery
TSTTracing Test
VASVisual Analogue Scale

Appendix A

Table A1. Methodological Quality Assessment.
Author(s)Study DesignTool UsedOverall AssessmentBrief Justification
Miller et al. [35]Double-blind RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Söderström et al. [4])Multicentre RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Wade et al. [29]Cross-over RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Motokawa, K. A. et al. [47]Cross-sectional studyNewcastle-Ottawa AdaptedModerateDescriptive cross-sectional design; no control group, but representative sample.
Wyers, C. et al. [27]Open clinical trialRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Chojnacki, C. et al. [7]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Malafarina, V. et al. [48]Non-randomised clinical trialCritical narrative assessmentModerateClinical study without formal randomisation, potential risk of bias.
Trivedi et al. [41]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Komulainen, P. et al. [26]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Jacka, F. A. et al. [9]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Levak, N. et al. [36]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Abizanda, P. et al. [17]Observational intervention studyCritical narrative assessmentModerateApplied study without a clear control group; limited informative value.
Imaoka, M. et al. [42]Clinical trialRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Rondanelli et al. [28]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Yoshimura et al. [37]Retrospective cohortNewcastle-Ottawa ScaleHighGood follow-up design with analysis of confounding factors.
von Berens et al. [33]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Ng et al. [39]RCT with 5 groupsRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Ghosh et al. [44]Multicentre intervention studyCritical narrative assessmentModerateApplied study without a clear control group; limited informative value.
Parsons et al. [43]RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Chen et al. [30]Prospective cohortNewcastle-Ottawa ScaleHighGood follow-up design with analysis of confounding factors.
Loughrey et al. [23]Double-blind RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Remington et al. [6]Double-blind RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Cabrera-Suárez et al. [40]Single-blind RCTRoB 2ModerateRandomised study with control group; possible bias due to blinding or randomisation.
Note. RCT = randomised clinical trial; RoB 2 = risk of bias assessment tool 2.
Table A2. Summary of included studies.
NoAuthor(s)Study DesignSample SizeAge of ParticipantsGenderType of Nutritional InterventionComparative GroupMain ResultsOutcome IndicatorsEffect Size/CI
1Miller, M. et al. [35]Double-blind randomised controlled trial3760–7522 men, 15 womenSupplementation with freeze-dried strawberry powder for 90 daysPlacebo group with isoenergetic powderImprovements in memory and verbal recognition in the intervention groupCVLT-II; spatial navigation test; various cognitive testsOR = 1.8; 95% CI
[1.2, 2.7]
2Söderström, L [4]Multicentre randomised controlled trial409≥65 yearsNot specifiedOral nutritional supplements (ONS) and/or dietary adviceFour groups: ONS, DA, ONS+DA, routine careThe ONS group showed significant improvement in quality of life (EQ-VAS)EQ-5D-3L; EQ-VASOR = 1.6; 95% CI
[1.1, 2.2]
3Wade, A. et al. [29]Randomised controlled crossover trial4045–75Not specifiedModified Mediterranean diet with dairy productsExpected improvements in blood pressure, cardiometabolic health, and cognitive functionBlood pressure; CANTAB (Cambridge Neuropsychological Test); CRP; lipids; ApoE4; processing speedBlood pressure; CANTAB; CRP; lipids; ApoE4; processing speedRR = 0.75; 95% CI [0.60, 0.95]
4Motokawa, K. A. et al. [47]Cross-sectional study747Average: 73.6 years311 men, 436 womenDietary variety assessed using food diversity score (FDS)Comparison between robust, pre-frail and frail groups according to the Kihon ChecklistGreater dietary variety associated with lower degree of frailtyKihon Checklist; FDS; MMSENR
5Wyers, C. et al. [27]Multicentre, open-label, randomised clinical trial152 (73 intervention, 79 control)≥55 yearsBoth gendersProtein- and energy-enriched diet + ONS (3 months)Usual nutritional careImprovement in nutritional status; no effect on hospital stay, complications or quality of lifeNutritional status, length of hospital stay, complications, quality of lifeHR = 1.2; 95% CI
[0.90, 1.55]
6Chojnacki, C. et al. [7]Randomised clinical trial50Average age 68Both gendersProbiotic supplementation with Lactobacillus helveticus and Bifidobacterium longumPlacebo groupSignificant reduction in symptoms of anxiety and depressionHADS, BDIOR = 0.65; 95% CI [0.42, 0.98]
7Malafarina, V. et al. [48]Non-randomised clinical trial253Average 84.2 ± 7.1 years67.2% womenOral hyperprotein and hypercaloric supplementation for 3 monthsNo defined control group (use according to clinical practice)Improvements in nutritional status, body weight and functional statusMNA-SF, MMSE, Barthel, SPPBNR
8Trivedi et al. [41]Randomised clinical trial84Older adults (mean age not specified)Not specifiedMulticomponent nutritional supplement (TRI 360™) with vitamins, antioxidants, and plant extractsPlaceboReduction in symptoms of anxiety and depression; improvement in inflammatory biomarkersGDS, HAD, CRP, IL-6, vitamin D3, TNF-α95% CI [0.35, 0.85]
9Komulainen, P. et al. [26]Randomised clinical trial (DR’s EXTRA Study)8060–77Both gendersDiet + physical exercise + cognitive interventionNo structured intervention groupSignificant improvement in verbal memory and executive functionsCVLT, cognitive tests, neuropsychological scalesOR = 1.4
10Jacka, F. A. et al. [9]Randomised clinical trial (SMILES Trial)166Older adults with moderate depressionBoth gendersMediterranean-style dietSocial support groupSignificant reduction in depressive symptomsMADRS, dietary adherence scale95% CI [1.01, 1.96]
11Levak, N. et al. [36]Randomised clinical trial (MIND-ADmini)214>60 years (prodromal phase of Alzheimer’s disease)Both gendersMultimodal programme with diet, exercise and cognitive stimulation
Comparative group: Usual care
Usual careImprovement in diet quality, physical activity and cognitive performanceADAS-Cog, dietary quality, lifestyle scalesOR = 2.0; 95% CI [1.2, 3.1]
12Abizanda, P. et al. [17]Observational intervention study110Average 84 ± 6 yearsBoth gendersOral nutritional supplementation (ONS)No defined control groupImprovements in functional and nutritional statusSPPB, MNA-SF, GDS, BarthelOR = 1.3
13Imaoka, M. et al. [42]Clinical trialNot specifiedOlder adults
Community
Not specifiedCombined intervention: diet + physical exerciseNo control group describedImprovements in cognition and social participationADL, QOL, MMSE, HADOR = 1.7; 95% CI
[1.1, 2.6]
14Rondanelli et al. [28]Double-blind RCT130Average 80.3 years53 men, 77 womenWhey protein, essential amino acids and vitamin D + exercisePlacebo + exerciseImprovements in lean mass, strength, ADL, QOL, IGF-1, and reduction in CRPFat-free mass, IGF-I, CRP, grip strength, SF-36, ADL, MNARR = 0.82; 95% CI [0.68, 0.99]
15Yoshimura et al. [37]Retrospective cohort study1012Median age 75.6 years54.1% menPersonalised nutritional support (dietary prescription)No triad interventionSignificant improvement in FIM-motor, strength and muscle mass with full interventionFIM-motor, grip strength, SMIOR = 2.2; 95% CI
[1.6]
16von Berens et al. [33]Randomised clinical trialNot specifiedAverage 77.5 yearsBoth gendersProtein supplement + exercisePlacebo + exerciseImprovement in MCS and depressive symptoms; no differences by supplementSF-36 (MCS), CES-DOR = 1.5
17Ng et al. [39]RCT with 5 groups245Average age 7061.4% womenNutritional, physical, cognitive supplement or combinationUsual careInterventions reduced frailty, especially combinationFrailty score, strength, energy, physical activity, ADLRR = 0.88; 95% CI [0.74, 1.05]
18Ghosh et al. [44]Multicentre intervention study61Older adultsNot specifiedPersonalised Mediterranean diet (NU-AGE)No active interventionFavourable alteration of microbiota, reduction in inflammation, cognitive improvementCRP, IL-17, microbiota, frailty markers, and cognitionOR = 1.9
19Parsons et al. [43]RCT104Average 88.5 yearsNot specifiedONS (oral supplements)Dietary adviceONS improved QOL and nutritional intake more than adviceEQ-5D (TTO, VAS), energy and protein intakeCI 95% [0.80, 1.25]
20Chen et al. [30]Prospective cohort47≥65 yearsBoth gendersChinese dietary patterns (vegetable, meat, traditional)Low dietary pattern scoresPlant-based and traditional patterns protected against memory declineLogical memory, executive function, MMSE, verbal fluencyRR = 1.4
21Loughrey et al. [23]Double-blind RCT3760–7513 men, 24 womenFreeze-dried blueberry powder 24 g/day (equivalent to 1 cup fresh)Blueberry-flavoured placebo with equivalent caloriesImprovement in cognitive executive functions; no improvement in balance or gaitCVLT-II, TST, ANT, Trail Making Test, GDS95% CI [1.10, 2.00]
22Remington et al. [6]Double-blind phase II RCT106Average = 77.8 yearsBoth gendersCombined nutraceutical supplement (SAM, NAC, folate, B12, etc.)PlaceboThe NF group showed significant cognitive improvements at 3 months and a trend toward improvement in behaviourDRS, Clox-1, NPI, ADLOR = 1.6; 95% CI
[1.2, 2.1]
23Cabrera-Suárez et al. [40]Randomised controlled trial, single-blind103 intervention, 93 control≥65Both gendersMediterranean diet with extra virgin olive oil (EVOO)Usual care without nutritional interventionImprovements in subclinical depressive symptoms at 4, 8, and 20 months; no difference in recurrenceBeck Depression Inventory (BDI), recurrence rateHR = 0.72; 95% CI [0.55, 0.94]

References

  1. United Nations, Department of Economic and Social Affairs, Population Division. World Population Prospects 2022: Summary of Results. 2023. Available online: https://population.un.org/wpp (accessed on 15 July 2025).
  2. Serrano-Urrea, R.; García-Meseguer, M.J. Relationships between nutritional screening and functional impairment in institutionalized Spanish older people. Maturitas 2014, 78, 323–328. [Google Scholar] [CrossRef] [Scilit]
  3. Serrano-Urrea, R.; Garcia-Meseguer, M. Malnutrition in an elderly population without cognitive impairment living in nursing homes in Spain: Study of prevalence using the Mini Nutritional Assessment test. Gerontology 2013, 59, 490–498. [Google Scholar] [CrossRef] [Scilit]
  4. Söderström, L.; Bergkvist, L.; Rosenblad, A. Oral nutritional supplement use is weakly associated with increased subjective health-related quality of life in malnourished older adults: A multicentre randomised controlled trial. Br. J. Nutr. 2021, 127, 103–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Rasheed, S.; Woods, R.T. Malnutrition and quality of life in older people: A systematic review and meta-analysis. Ageing Res. Rev. 2013, 12, 561–566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Remington, R.; Bechtel, C.; Larsen, D.; Samar, A.; Doshanjh, L.; Fishman, P.; Luo, Y.; Smyers, K.; Page, R.; Morrell, C.; et al. A Phase II Randomized Clinical Trial of a Nutritional Formulation for Cognition and Mood in Alzheimer’s Disease. J. Alzheimer’s Dis. 2015, 45, 395–405. [Google Scholar] [CrossRef] [Scilit]
  7. Chojnacki, C.; Gąsiorowska, A.; Popławski, T.; Konrad, P.; Chojnacki, M.; Fila, M.; Blasiak, J. Beneficial Effect of Increased Tryptophan Intake on Its Metabolism and Mental State of the Elderly. Nutrients 2023, 15, 847. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Godos, J.; Currenti, W.; Angelino, D.; Mena, P.; Castellano, S.; Caraci, F.; Galvano, F.; Del Rio, D.; Ferri, R.; Grosso, G. Diet and mental health: Review of the recent updates on molecular mechanisms. Antioxidants 2020, 9, 346. [Google Scholar] [CrossRef] [Scilit]
  9. Jacka, F.N.; O’Neil, A.; Opie, R.; Itsiopoulos, C.; Cotton, S.; Mohebbi, M.; Castle, D.; Dash, S.; Mihalopoulos, C.; Chatterton, M.L.; et al. A Randomised Controlled Trial of Dietary Improvement for Adults with Major Depression (the “SMILES” trial). BMC Med. 2017, 15, 23. Available online: https://bmcmedicine.biomedcentral.com/articles/10.1186/s12916-017-0791-y (accessed on 28 February 2025). [CrossRef] [Scilit]
  10. Jennings, A.; Kühn, T.; Bondonno, N.P.; Waniek, S.; Bang, C.; Franke, A.; Kassubek, J.; Müller, H.-P.; Both, M.; Weber, K.S.; et al. The gut microbiome modulates associations between adherence to a Mediterranean-style diet, abdominal adiposity, and C-reactive protein in population-level analysis. Am. J. Clin. Nutr. 2024, 119, 210–219. [Google Scholar] [CrossRef] [Scilit]
  11. Stykel, M.G.; Siripala, S.V.; Soubeyrand, E.; Coackley, C.L.; Lu, P.; Camargo, S.; Thevasenan, S.; Figueroa, G.B.; So, R.W.; Stuart, E.; et al. G6PD deficiency triggers dopamine loss and the initiation of Parkinson’s disease pathogenesis. Cell Rep. 2025, 44, 115178. [Google Scholar] [CrossRef] [Scilit]
  12. Bekhbat, M.; Block, A.M.; Dickinson, S.Y.; Tharp, G.K.; Bosinger, S.E.; Felger, J.C. Neurotransmitter and metabolic effects of interferon-alpha in association with decreased striatal dopamine in a non-human primate model of cytokine-Induced depression. Brain Behav. Immun. 2025, 125, 308–318. [Google Scholar] [CrossRef] [Scilit]
  13. Chen, W.-T.; Lu, A.; Craessaerts, K.; Pavie, B.; Sala Frigerio, C.; Corthout, N.; Qian, X.; Laláková, J.; Kühnemund, M.; Voytyuk, I.; et al. Spatial transcriptomics and in situ sequencing to study Alzheimer’s disease. Cell 2020, 182, 976–991.e19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Sha, Q.; Fu, Z.; Galvis, M.L.E.; Madaj, Z.; Underwood, M.D.; Steiner, J.A.; Dwork, A.; Simpson, N.; Galfalvy, H.; Rozoklija, G.; et al. Integrative transcriptome- and DNA methylation analysis of brain tissue from the temporal pole in suicide de-cedents and their controls. Mol. Psychiatry 2023, 29, 134–145. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Hurley, M.M.; Murlanova, K.; Macias, L.K.; Sabir, A.I.; O’Brien, S.C.; Bhasin, H.; Tamashiro, K.L.; Pletnikov, M.V.; Moran, T.H. Activity-based anorexia disrupts systemic oxidative state and induces cortical mitochondrial fission in adolescent female rats. Int. J. Eat. Disord. 2021, 54, 999–1012. [Google Scholar] [CrossRef] [Scilit]
  16. Christodoulou, C.C.; Pitsillides, M.; Hadjisavvas, A.; Zamba-Papanicolaou, E. Dietary Intake, Mediterranean and Nordic Diet Adherence in Alzheimer’s Disease and Dementia: A Systematic Review. Nutrients 2025, 17, 336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Abizanda, P.; López, M.D.; García, V.P.; Estrella, J.d.D.; González, Á.d.S.; Vilardell, N.B.; Torres, K.A. Effects of an Oral Nutritional Supplementation Plus Physical Exercise Intervention on the Physical Function, Nutritional Status, and Quality of Life in Frail Institutionalized Older Adults: The ACTIVNES Study. J. Am. Med. Dir. Assoc. 2015, 16, 439.e9–439.e16. [Google Scholar] [CrossRef] [Scilit]
  18. Poscia, A.; Stojanovic, J.; La Milia, D.I.; Duplaga, M.; Grysztar, M.; Moscato, U.; Onder, G.; Collamati, A.; Ricciardi, W.; Magnavita, N. Interventions targeting loneliness and social isolation among the older people: An update systematic review. Exp. Gerontol. 2018, 102, 133–144. [Google Scholar] [CrossRef] [Scilit]
  19. Yu, H.; Pan, M.; Gu, H.; Liu, T.; Dai, J.; Liu, L.; Hou, J.; Yang, L.; Shi, M.; Zhao, C. Correlation Analysis between Depressive, Cognitive Symptoms and Nutritional Metabolism in the Elderly in Community. Chin. Gen. Pract. 2024, 27, 3540–3545. [Google Scholar] [CrossRef]
  20. Krause, D.; Roupas, P. Dietary interventions as a neuroprotective therapy for the delay of the onset of cognitive decline in older adults: Evaluation of the evidence. Funct. Foods Health Dis. 2017, 7, 743–757. [Google Scholar] [CrossRef] [Scilit]
  21. WHOQOL Group. The World Health Organization quality of life assessment (WHOQOL): Development and general psychometric properties. Soc. Sci. Med. 1998, 46, 1569–1585. [Google Scholar] [CrossRef] [Scilit]
  22. Lawton, M.P.; Brody, E.M. Assessment of older people: Self-maintaining and instrumental activities of daily living. Gerontol. 1969, 9, 179–186. [Google Scholar] [CrossRef] [Scilit]
  23. Loughrey, D.G.; Lavecchia, S.; Brennan, S.; Lawlor, B.A.; Kelly, M.E. The impact of the Mediterranean diet on the cognitive functioning of healthy older adults: A systematic review and meta-analysis. Adv. Nutr. 2017, 8, 571–586. [Google Scholar] [CrossRef] [Scilit]
  24. Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
  25. Salari, N.; Darvishi, N.; Bartina, Y.; Keshavarzi, F.; Hosseinian-Far, M.; Mohammadi, M. Global prevalence of malnutrition in older adults: A comprehensive systematic review and meta-analysis. Public Health Pract. 2025, 9, 100583. [Google Scholar] [CrossRef] [Scilit]
  26. Komulainen, P.; Tuomilehto, J.; Savonen, K.; Männikkö, R.; Hassinen, M.; Lakka, T.A.; Hänninen, T.; Kiviniemi, V.; Jacobs, D.R.; Kivipelto, M.; et al. Exercise, diet, and cognition in a 4-year randomized controlled trial: Dose-Responses to Exercise Training (DR’s EXTRA). Am. J. Clin. Nutr. 2021, 113, 1428–1439. [Google Scholar] [CrossRef] [Scilit]
  27. Wyers, C.E.; Reijven, P.L.M.; Breedveld-Peters, J.J.L.; Denissen, K.F.M.; Schotanus, M.G.M.; Dongen, M.C.J.M.; Eussen, S.J.P.M.; Heyligers, I.C.; Brandt, P.A.v.d.; Willems, P.C.; et al. Efficacy of Nutritional Intervention in Elderly After Hip Fracture: A Multicenter Randomized Controlled Trial. J. Gerontol. Ser. A-Biol. Sci. Med. Sci. 2018, 73, 1429–1437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Rondanelli, M.; Klersy, C.; Terracol, G.; Talluri, J.; Maugeri, R.; Guido, D.; Faliva, M.A.; Solerte, B.S.; Fioravanti, M.; Lukaski, H.; et al. Whey protein, amino acids, and vitamin D supplementation with physical activity increases fat-free mass and strength, functionality, and quality of life and decreases inflammation in sarcopenic elderly. Am. J. Clin. Nutr. 2016, 103, 830–840. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Wade, A.; Davis, C.; Dyer, K.; Hodgson, J.; Woodman, R.; Keage, H.; Murphy, K. A Mediterranean Diet to Improve Cardiovascular and Cognitive Health: Protocol for a Randomised Controlled Intervention Study. Nutrients 2017, 9, 145. [Google Scholar] [CrossRef] [Scilit]
  30. Chen, Y.-C.; Jung, C.-C.; Chen, J.-H.; Chiou, J.-M.; Chen, T.-F.; Chen, Y.-F.; Tang, S.-C.; Yeh, S.-J.; Lee, M.-S. Association of Dietary Patterns with Global and Domain-Specific Cognitive Decline in Chinese Elderly. J. Am. Geriatr. Soc. 2017, 65, 1159–1167. [Google Scholar] [CrossRef] [Scilit]
  31. Miller, M.G.; Hamilton, D.A.; Joseph, J.A.; Shukitt-Hale, B. Dietary blueberry improves cognition among older adults in a randomized, double-blind, placebo-controlled trial. Eur. J. Nutr. 2018, 57, 1169–1180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Tsuboi, M.; Momosaki, R.; Vakili, M.; Abo, M. Nutritional supplementation for activities of daily living and functional ability of older people in residential facilities: A systematic review. Geriatr. Gerontol. Int. 2017, 18, 197–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. von Berens, Å.; Fielding, R.A.; Gustafsson, T.; Kirn, D.; Laussen, J.; Nydahl, M.; Reid, K.; Travison, T.G.; Zhu, H.; Cederholm, T.; et al. Effect of exercise and nutritional supplementation on health-related quality of life and mood in older adults: The VIVE2 randomized controlled trial. BMC Geriatr. 2018, 18, 286. [Google Scholar] [CrossRef] [Scilit]
  34. Donaldson, A.; Smith, T.; Alder, S.; Johnstone, A.M.; Baukje de Roos Aucott, L.; Gordon, A.L.; Myint, P.K. Effect of nonmeat, high-protein supplementation on quality of life and clinical outcomes in older residents of care homes: A systematic review and meta-analysis. Nutr. Rev. 2018, 77, 116–127. [Google Scholar] [CrossRef] [Scilit]
  35. Miller, M.G.; Thangthaeng, N.; Rutledge, G.A.; Scott, T.M.; Shukitt-Hale, B. Dietary strawberry improves cognition in a randomised, double-blind, placebo-controlled trial in older adults. Br. J. Nutr. 2021, 126, 253–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Levak, N.; Lehtisalo, J.; Thunborg, C.; Westman, E.; Andersen, P.; Andrieu, S.; Broersen, L.M.; Coley, N.; Hartmann, T.; Irving, G.F.; et al. Nutrition guidance within a multimodal intervention improves diet quality in prodromal Alzheimer’s disease: Multimodal Preventive Trial for Alzheimer’s Disease (MIND-ADmini). Alzheimer’s Res. Ther. 2024, 16, 147. [Google Scholar] [CrossRef] [Scilit]
  37. Yoshimura, Y.; Shimazu, S.; Shiraishi, A.; Wakabayashi, H.; Nagano, F.; Matsumoto, A.; Kido, Y.; Bise, T.; Kuzuhara, A.; Hamada, T.; et al. Triad of Rehabilitation, Nutrition Support, and Oral Management improves Activities of Daily Living and Muscle Health in Hospitalized Patients after Stroke. Clin. Nutr. ESPEN 2024, 63, 837–844. [Google Scholar] [CrossRef] [Scilit]
  38. Thomson, K.; Rice, S.; Arisa, O.; Johnson, E.; Tanner, L.; Marshall, C.; Sotire, T.; Richmond, C.; O’kEefe, H.; Mohammed, W.; et al. Oral nutritional interventions in frail older people who are malnourished or at risk of malnutrition: A systematic review. Health Technol. Assess. 2022, 26, 1–112. [Google Scholar] [CrossRef] [Scilit]
  39. Ng, T.P.; Feng, L.; Nyunt, M.S.Z.; Feng, L.; Niti, M.; Tan, B.Y.; Chan, G.; Khoo, S.A.; Chan, S.M.; Yap, P.; et al. Nutritional, Physical, Cognitive, and Combination Interventions and Frailty Reversal Among Older Adults: A Randomized Controlled Trial. Am. J. Med. 2015, 128, 1225–1236.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Cabrera-Suárez, B.M.; José Luis Hernández-Fleta Molero, P.; González-Pinto, A.; Lahortiga, F.; Cabrera, C.; Chiclana-Actis, C.; Sánchez-Villegas, A. Mediterranean diet-based intervention to improve depressive symptoms: Analysis of the PREDIDEP randomized trial. Nutr. Neurosci. 2023, 27, 951–961. [Google Scholar] [CrossRef] [Scilit]
  41. Trivedi, M.K.; Branton, A.; Trivedi, D.; Mondal, S.; Jana, S. Efficacy of a novel proprietary dietary supplement (TRI 360TM) on psychological symptoms and stress-related quality of life in adult subjects: A randomized controlled clinical trial. Front. Psychiatry 2022, 13, 919284. [Google Scholar] [CrossRef] [Scilit]
  42. Imaoka, M.; Nakao, H.; Nakamura, M.; Tazaki, F.; Maebuchi, M.; Ibuki, M.; Takeda, M. Effect of Multicomponent Exercise and Nutrition Support on the Cognitive Function of Older Adults: A Randomized Controlled Trial. Clin. Interv. Aging 2019, 14, 2145–2153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Parsons, E.L.; Stratton, R.J.; Cawood, A.L.; Smith, T.R.; Elia, M. Oral nutritional supplements in a randomised trial are more effective than dietary advice at improving quality of life in malnourished care home residents. Clin. Nutr. 2017, 36, 134–142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Ghosh, T.S.; Rampelli, S.; Jeffery, I.B.; Santoro, A.; Neto, M.; Capri, M.; Giampieri, E.; Jennings, A.; Candela, M.; Turroni, S.; et al. Mediterranean diet intervention alters the gut microbiome in older people reducing frailty and improving health status: The NU-AGE 1-year dietary intervention across five European countries. Gut 2020, 69, 1218–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Tingö, L.; Bergh, C.; Rode, J.; Rubio, M.F.R.; Persson, J.; Johnson, L.B.; Smit, L.H.; Hutchinson, A.N. The effect of whole-diet interventions on memory and cognitive function in healthy older adults—A systematic review. Adv. Nutr. Int. Rev. J. 2024, 15, 100291. [Google Scholar] [CrossRef] [Scilit]
  46. Vear, N.K.; Goodman, W.; Rose, G.L.; McCarthy, A.L. Impact of exercise and/or dietary interventions, and their behaviour change techniques, on quality of life in middle-aged and older women following treatment for cancer: A systematic review. Maturitas 2023, 175, 107783. [Google Scholar] [CrossRef] [Scilit]
  47. Motokawa, K.; Watanabe, Y.; Edahiro, A.; Shirobe, M.; Murakami, M.; Kera, T.; Kawai, H.; Obuchi, S.; Fujiwara, Y.; Ihara, K.; et al. Frailty Severity and Dietary Variety in Japanese Older Persons: A Cross-Sectional Study. J. Nutr. Health Aging 2018, 22, 451–456. [Google Scholar] [CrossRef] [Scilit]
  48. Malafarina, V.; Rexach, J.A.S.; Masanes, F.; Cruz-Jentoft, A.J. Effects of high-protein, high-calorie oral nutritional supplementation in malnourished older people in nursing homes: An observational, multi-center, prospective study (PROT-e-GER). Protocol and baseline population characteristics. Maturitas 2019, 126, 73–79. [Google Scholar] [CrossRef] [Scilit]
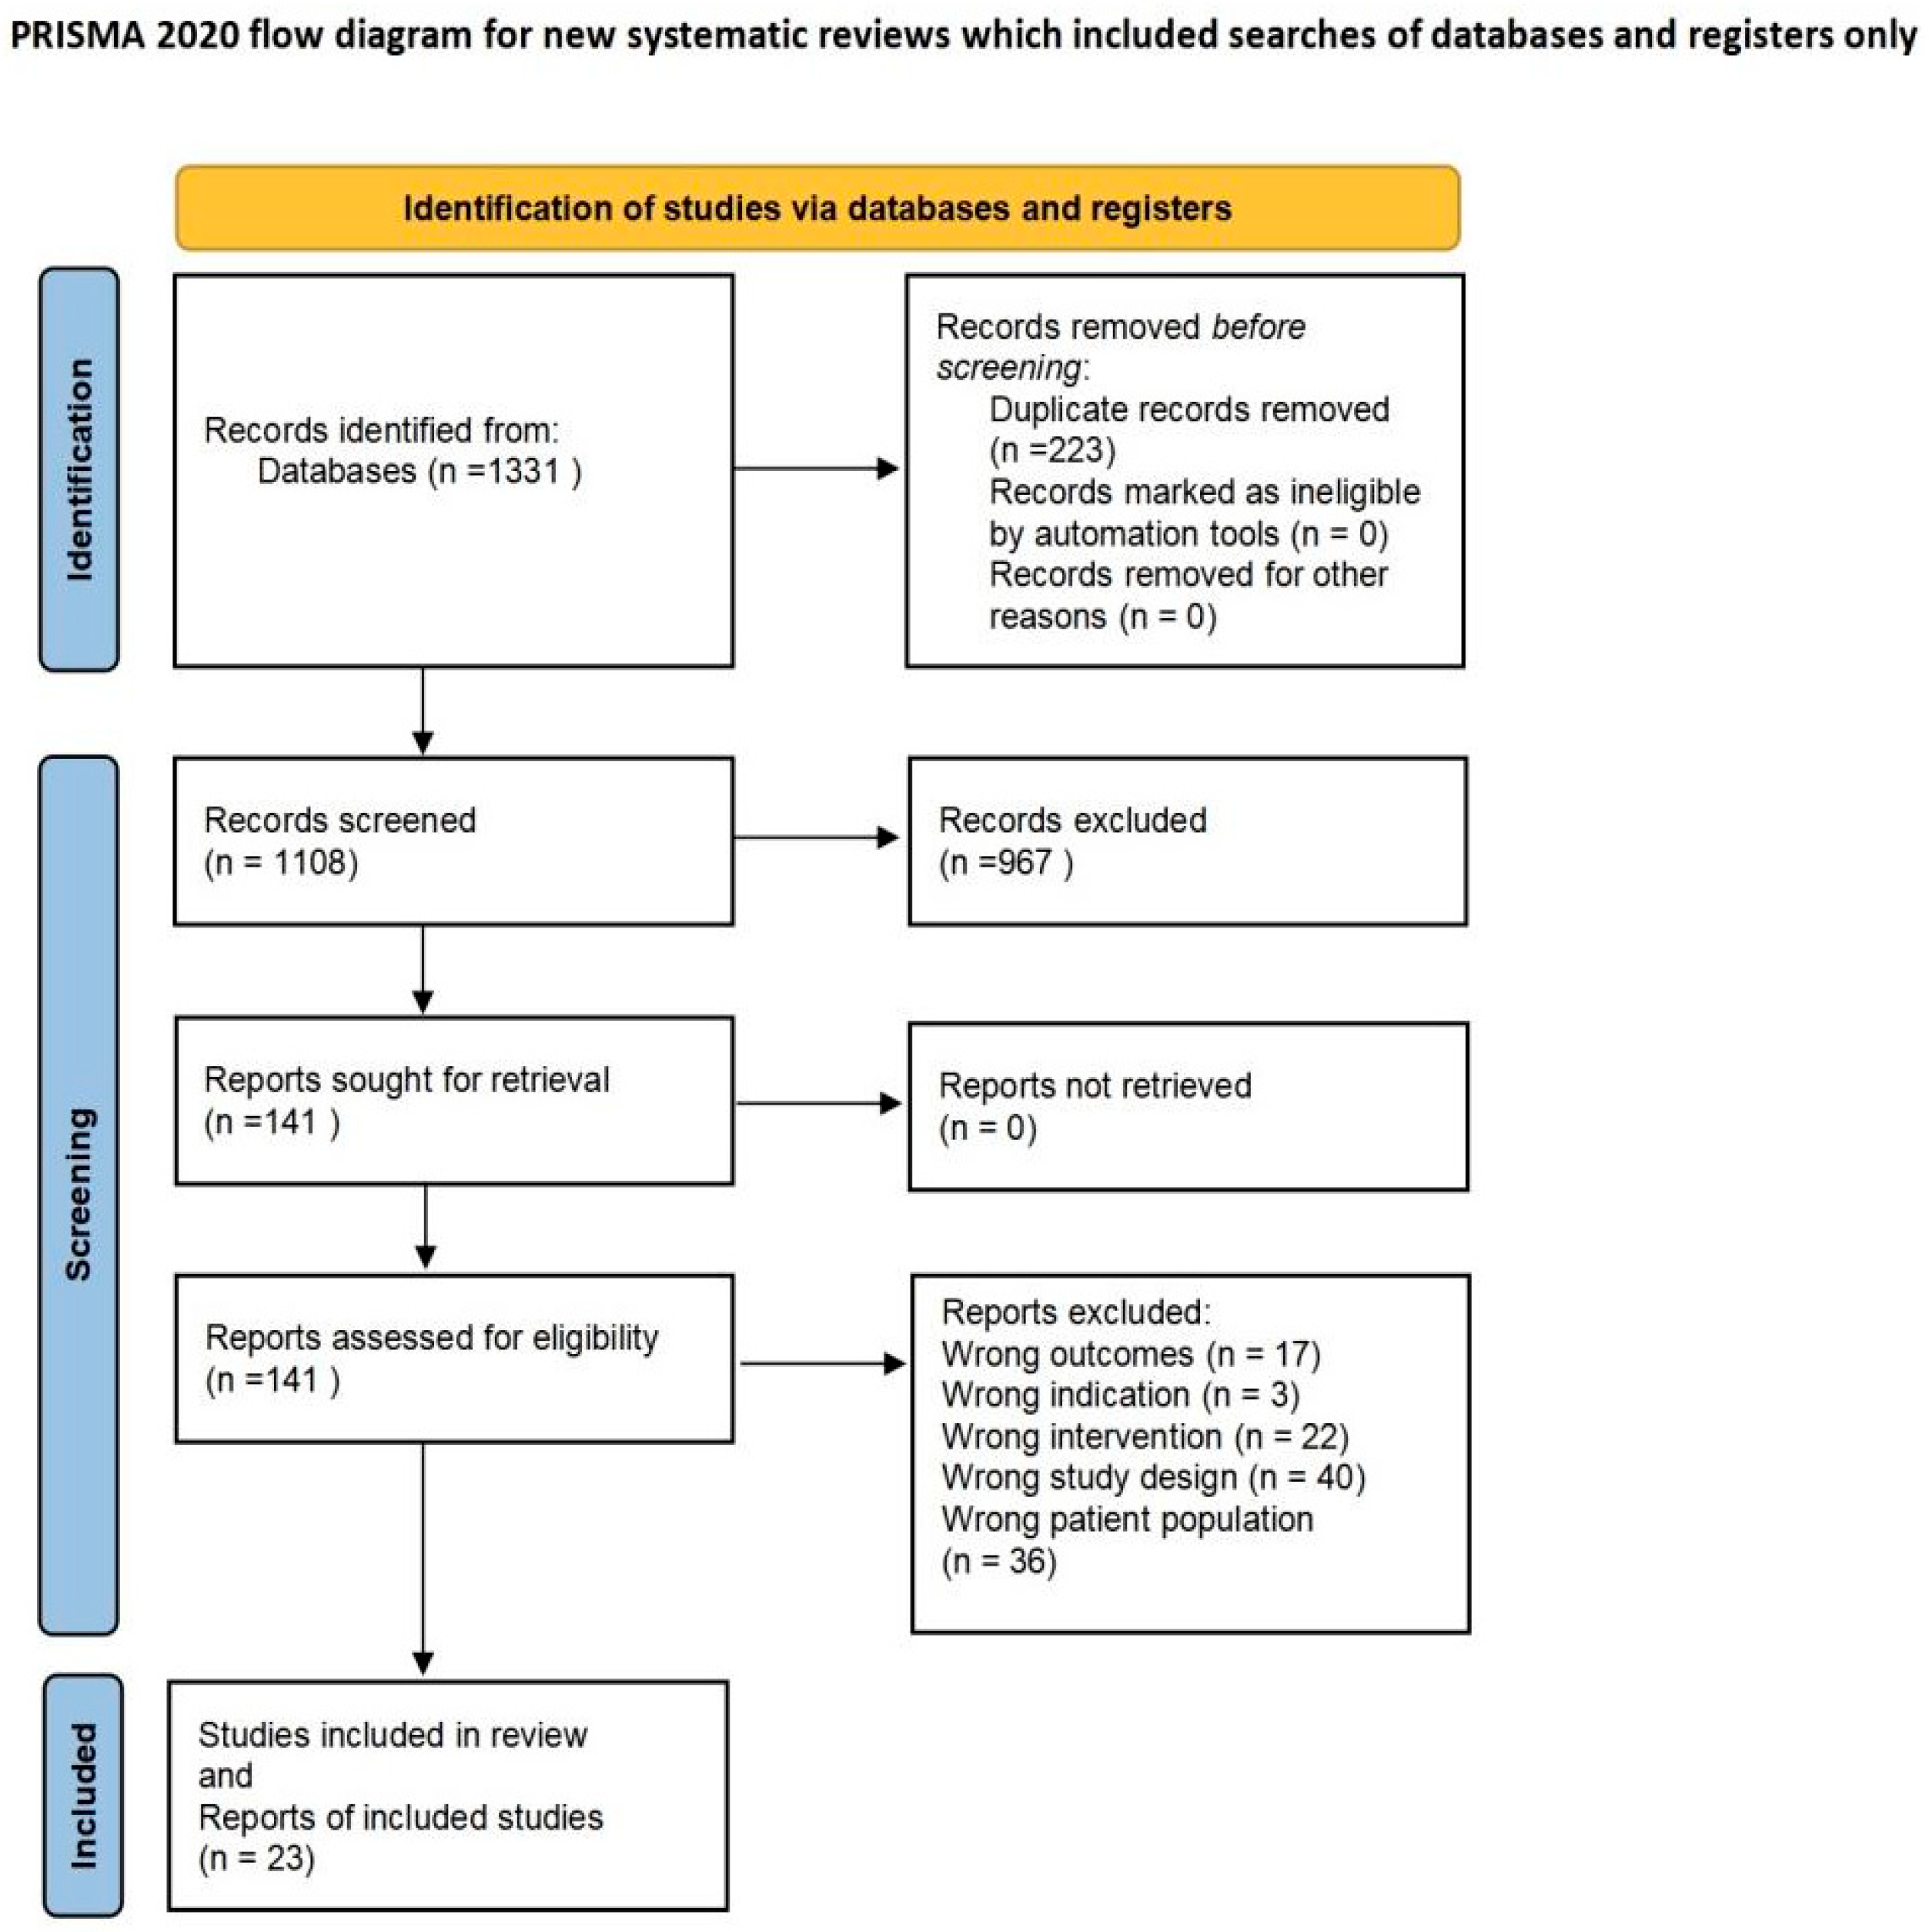
Figure 1. Flow chart of the selection process according to PRISMA 2020 [24].
Dietetics 04 00055 g001
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.



