Review

Ozone Therapy as a Controlled Modulator of Redox Signaling and Adaptive Stress Responses: Molecular Mechanisms, Hormetic Effects, and Biomedical Implications

by
Francesca Perra
1,
Faustina Barbara Cannea
2 and
Alessandra Padiglia
2,*
1
Private Medical Practice, 09134 Cagliari, CA, Italy
2
Department of Life and Environmental Sciences (DiSVA), Biomedical Section, University of Cagliari, Cittadella Universitaria di Monserrato, 09042 Monserrato, CA, Italy
*
Author to whom correspondence should be addressed.
Oxygen 2026, 6(3), 18; https://doi.org/10.3390/oxygen6030018
Submission received: 22 May 2026 / Revised: 8 July 2026 / Accepted: 9 July 2026 / Published: 11 July 2026

Abstract

Medical ozone has emerged as a potential redox-modulating intervention in inflammatory and degenerative conditions, particularly in dermatological contexts characterized by chronic oxidative imbalance and impaired tissue remodeling. Unlike conventional pharmacological agents, ozone exerts its biological activity through rapid chemical reactions generating transient reactive and electrophilic species that activate endogenous adaptive signaling pathways. Controlled oxidative perturbations activate antioxidant transcriptional programs, primarily mediated by the nuclear factor erythroid 2-related factor 2 (Nrf2) pathway, while modulating inflammatory signaling networks, including nuclear factor kappa B (NF-κB) and the NOD-like receptor family pyrin domain-containing 3 (NLRP3) inflammasome. This dual behavior reflects hormetic responses in which low-dose exposure promotes adaptive cellular signaling, whereas excessive oxidative burden leads to structural and functional damage. This review summarizes current knowledge on the molecular mechanisms underlying ozone-induced redox modulation, with emphasis on chemical reactivity, spatiotemporal signaling dynamics, thiol-based sensing, and metabolic reinforcement of antioxidant defenses. Particular attention is given to skin and subcutaneous adipose tissue, where oxidative stress, immune activation, and extracellular matrix remodeling converge. Dose dependency, safety constraints, and methodological variability are critically discussed, highlighting the narrow threshold between adaptive signaling and oxidative injury and the need for rigorous mechanistic and clinical validation.

1. Introduction

Redox homeostasis is a central determinant of cellular and tissue function, integrating metabolic fluxes, inflammatory signaling, and adaptive stress responses [1,2,3,4,5]. Disruption of this equilibrium represents a common pathogenic denominator across chronic inflammatory disorders, degenerative diseases, metabolic dysfunction, and impaired tissue repair [1,4,5]. Reactive oxygen species (ROS), once considered merely toxic by-products of aerobic metabolism, are now recognized as tightly regulated signaling mediators whose spatial and temporal dynamics critically influence immune activation, extracellular matrix turnover, and cellular resilience [3,4,5,6,7,8,9,10]. Within this framework, hormesis describes how transient and controlled oxidative stimuli can elicit adaptive responses, whereas sustained or excessive oxidative stress promotes structural damage and progressive dysfunction [11,12].
Medical ozone has been investigated as a redox-modulating intervention in a variety of clinical contexts, including inflammatory dermatoses, impaired wound healing, and localized adipose alterations [13,14,15,16,17,18,19,20]. Due to its high chemical reactivity and extremely short half-life in biological systems, ozone does not act through classical receptor-mediated mechanisms. Instead, its biological activity originates from rapid reactions with biomolecular targets, particularly unsaturated lipids and aqueous-phase components, leading to the generation of secondary ROS and electrophilic mediators [13,14,15,21,22,23]. These downstream products interact with endogenous regulatory networks, and their biological impact is critically influenced by dose, route of administration, and the intrinsic redox buffering capacity of the target tissue [14,15,16,17].
Experimental evidence indicates that controlled ozone exposure activates antioxidant transcriptional programs, primarily through the Nrf2 pathway, while modulating key inflammatory signaling cascades, including NF-κB and the NLRP3 inflammasome [15,16,24,25,26,27,28,29,30,31,32,33]. These interconnected pathways coordinate oxidative, metabolic, and immune responses, providing a mechanistic link between transient redox perturbations and disease-associated signaling networks. Importantly, the biological effects of medical ozone are largely mediated through indirect modulation of endogenous adaptive systems, rather than direct cytotoxic or pharmacological actions, a distinction critical for interpreting both experimental and clinical findings [13,14,15,16].
It is also important to distinguish medically administered oxygen–ozone mixtures from environmental ozone exposure, as these represent fundamentally different biological contexts. They differ in exposure route, administered dose, duration of exposure, biological interface, and intended biological outcome. This distinction is essential for the correct interpretation of both mechanistic and clinical observations and is discussed in greater detail in Section 8.
Skin and subcutaneous adipose tissue represent biologically and clinically relevant compartments where oxidative stress, immune activation, and metabolic dysregulation converge [34,35,36,37,38,39,40]. These tissues are continuously exposed to environmental and endogenous stressors, exhibit active immune surveillance, and undergo dynamic extracellular matrix remodeling [35,36,41,42,43,44]. Persistent redox imbalance within this axis contributes to the pathogenesis of inflammatory dermatoses, delayed wound healing, tissue laxity, pigmentary alterations, and adipose dysfunction [34,36,37,38,39,40,45]. Consequently, interventions capable of modulating redox and inflammatory tone in a controlled manner may hold translational relevance in these settings.
This review aims to integrate current knowledge on the molecular mechanisms underlying ozone-induced redox modulation, with particular emphasis on chemical reactivity, spatiotemporal signaling dynamics, and cross-talk with inflammatory and metabolic pathways. Critical aspects related to dose dependency, safety constraints, and methodological heterogeneity are systematically examined to delineate a mechanistically grounded framework for evaluating therapeutic plausibility [7,27,28,29,30]. By positioning medical ozone within a systems-level perspective of redox regulation, this work seeks to clarify its biological rationale and identify key evidentiary gaps that must be addressed to support robust and reproducible clinical applications.

2. Chemical Reactivity of Ozone in Biological Systems

Ozone (O3) is a triatomic allotrope of oxygen characterized by strong electrophilic reactivity and an extremely short lifetime in biological environments [13,14,46,47,48,49,50,51]. Following administration, ozone does not persist as a stable molecular entity but is rapidly consumed through reactions with aqueous and lipid substrates [13,14,15,16,17,18,19,20,46]. Consequently, its biological effects arise not from direct receptor-mediated interactions, but from a cascade of rapid redox reactions that generate secondary oxidation products acting as signaling intermediates [14,15,16,17,18,19,20,46,51].
Chemically, ozone preferentially reacts with electron-rich moieties, particularly carbon–carbon double bonds in unsaturated fatty acids within cellular membranes and lipoproteins [21,22,23,52,53,54,55,56]. Under physiological conditions, these reactions proceed predominantly via the Criegee ozonolysis mechanism, a non-radical cycloaddition leading to unstable primary ozonides (molozonides) [53,54]. These intermediates rapidly decompose into a range of secondary products, including lipid hydroperoxides, hydrogen peroxide (H2O2), and electrophilic aldehydes such as 4-hydroxynonenal (4-HNE) and related α,β-unsaturated alkenals [21,22,23,52,55,56,57]. Importantly, these secondary species, rather than ozone itself, represent the principal mediators of downstream biological activity [14,15,16,17,18,19,20].
The electrophilic nature of these aldehydic derivatives enables covalent modification of nucleophilic amino acid residues, particularly cysteine thiols in redox-sensitive proteins [21,22,23,56,57]. Lipid hydroperoxides and reactive aldehydic derivatives generated during controlled oxidative reactions may therefore function not only as products of lipid oxidation, but also as bioactive mediators capable of modulating redox-sensitive signaling pathways [58,59]. Such modifications can alter protein conformation, stability, and activity, thereby initiating signal transduction processes [22,24,25,26,60,61,62,63,64,65]. Within the Nrf2 pathway, electrophile-mediated modification of specific cysteine residues within Kelch-like ECH-associated protein 1 (Keap1) disrupts its inhibitory interaction with Nrf2, enabling nuclear translocation and transcriptional activation of antioxidant response genes [24,25,26,60,61,62,63,64,65].
In this context, ozone-derived electrophiles can be conceptualized as transient redox signals engaging cytoprotective adaptive programs [15,16,26,63].
Kinetic constraints critically shape these processes. Ozone is consumed near the site of administration, limiting diffusion and preventing systemic persistence [13,14,17,19,46]. Consequently, the induced oxidative perturbation is spatially confined and temporally restricted, resembling a transient redox pulse rather than sustained oxidative stress [15,16,46,51]. The magnitude and duration of this pulse are determined by local substrate availability, membrane lipid composition, antioxidant buffering capacity, and administered dose [14,15,16,17,46].
The selectivity of ozone reactivity further influences biological outcomes. Monounsaturated fatty acids represent preferential targets due to isolated double bonds [21,52,53,54]. Although polyunsaturated fatty acids can undergo secondary oxidation, controlled low-dose exposure typically does not promote extensive radical chain propagation [14,15,16,21,22,23,55,56,57]. This distinction is mechanistically critical: uncontrolled lipid peroxidation amplifies oxidative injury, whereas limited generation of electrophilic lipid derivatives may function as regulated signaling cues within a hormetic range [11,12,15,16,21,22,23].
The biological relevance of ozone-induced lipid oxidation products lies in their capacity to interface with established redox signaling networks [21,22,23,24,25,26,60,61,62,63,64,65]. Subtoxic concentrations of lipid hydroperoxides and electrophilic aldehydes are associated with increased glutathione biosynthesis, modulation of intracellular redox couples (e.g., GSH/GSSG), and activation of transcriptional programs coordinating antioxidant and anti-inflammatory responses [24,25,26,60,61,62,63,64,65]. Through these mechanisms, electrophile-driven signaling links primary chemical reactivity to downstream metabolic and inflammatory adaptation [26,63,65].
The transition between adaptive signaling and pathological oxidative damage is quantitatively and contextually determined [1,2,3,4,5,6,7,11,12]. Excessive oxidation results in irreversible modification of lipids, proteins, and nucleic acids, overwhelming repair systems and antioxidant defenses [21,22,23,55,56,57,58]. In contrast, a limited and transient oxidative stimulus may recalibrate redox-sensitive pathways and enhance cellular resilience [11,12,15,16,24,25,26,60,61,62,63,64,65]. Ozone can thus be conceptualized as a trigger of controlled electrophilic signaling, with biological consequences dependent on dose, temporal dynamics, and tissue-specific redox status [15,16,46,51].
Recognition of these chemical and kinetic determinants is essential for interpreting experimental observations and for distinguishing toxicological exposure from medically controlled redox modulation [13,14,15,16,17,18,19,20,46,47,51]. The downstream biological effects attributed to medical ozone arise from a defined cascade of secondary redox reactions that engage endogenous adaptive circuitry, rather than from persistence or systemic distribution of the oxidant itself [14,15,16,17,18,19,20,46].

3. Redox Compartmentalization and Temporal Dynamics of Ozone Signaling

Redox signaling is intrinsically governed by spatial compartmentalization and temporal progression [3,4,5,6,7,8,9]. ROS and electrophilic mediators generated following ozone exposure are not uniformly distributed but remain confined to discrete microenvironments defined by substrate availability, diffusion constraints, and local antioxidant buffering capacity [3,5,6,8]. This spatial restriction is a critical determinant of biological outcomes, enabling selective engagement of signaling pathways while limiting indiscriminate oxidative damage [3,4,5,6,7].
In dermatological contexts, such compartmentalization is particularly relevant. Localized redox perturbations within dermal and subcutaneous compartments can influence fibroblast function, immune cell activation, and extracellular matrix remodeling without inducing systemic oxidant dissemination [34,35,36,66]. This localized nature of redox signaling provides a mechanistic basis for tissue-specific responses to controlled ozone exposure [13,14,15,16,17,18,19,20,46].
During gas-based administration, tissue architecture further constrains ozone reactivity [13,14,15,16,17,18,19,20]. Following subcutaneous or intradermal injection, ozone rapidly dissolves in interstitial fluids and reacts within a restricted diffusion radius [13,14,17,19]. Primary oxidative events occur predominantly at extracellular interfaces and membrane-proximal lipid domains, generating hydrogen peroxide (H2O2) and lipid-derived electrophiles [21,22,23,52,53,54]. Because the parent oxidant is rapidly consumed, downstream biological effects are mediated by these secondary reactive species, rather than by direct oxidant diffusion [14,15,16,17,18,19,20].
The earliest phase of exposure, occurring within seconds to minutes, is characterized by a localized oxidative pulse accompanied by transient oxidation of extracellular and membrane-associated thiols [3,5,6,24,25,26,60,61,62,63]. The magnitude and spatial extent of this perturbation are tightly regulated by endogenous antioxidant systems, including glutathione pools, protein thiols, and extracellular antioxidants [1,2,3,4,5,6,24,25,26,60,61,62,63,64,65]. Under controlled low-dose conditions, this buffering capacity constrains both intensity and duration of oxidation, favoring regulated redox signaling over nonspecific macromolecular damage [11,12,15,16].
At subsequent time scales, ranging from minutes to hours, secondary redox mediators modulate intracellular signaling pathways [3,4,5,6,21,22,23]. Hydrogen peroxide, owing to its relative stability and membrane permeability, can diffuse across cellular compartments and reversibly oxidize redox-sensitive cysteine residues in target proteins [3,5,6]. In parallel, electrophilic lipid derivatives covalently modify nucleophilic residues, particularly within redox-regulatory proteins such as those in the Keap1–Nrf2 system [21,22,23,24,25,26,60,61,62,63]. These processes facilitate Nrf2 pathway activation and coordinate antioxidant gene expression, translating transient chemical events into sustained transcriptional responses [24,25,26,60,61,62,63,64,65].
Mitochondria act as a central integration hub within this redox cascade [60]. Although ozone itself does not directly access mitochondrial compartments under typical clinical conditions, cytosolic redox alterations can indirectly influence mitochondrial function by modulating peroxide tone, metabolic flux, mitochondrial bioenergetics, and inflammatory signaling pathways [60,66,67,68,69,70,71,72,73,74]. Adaptive responses may include enhanced antioxidant capacity, optimized redox balance, and increased tolerance to subsequent stressors [11,12,21,22,23,24,25,26,60,61,62,63,64,65]. Conversely, excessive oxidative input can impair mitochondrial integrity, disrupt bioenergetic homeostasis, and amplify inflammatory signaling [67,68,69,70,71,72,73,74,75].
The biological effects of ozone exposure therefore evolve across distinct temporal phases: an immediate chemical reaction phase, an intermediate signaling phase, and a delayed transcriptional and metabolic adaptation phase [15,16,21,22,23,24,25,26,60,61,62,63,64,65]. The transition from adaptive modulation to pathological damage is determined by the balance between oxidative input and tissue-specific redox reserve [1,2,3,4,5,6,7,11,12]. Tissues with chronic oxidative stress or reduced antioxidant capacity may exhibit altered thresholds, resulting in heterogeneous, context-dependent responses [7,34,36,37,38,39,40].
This spatiotemporal framework provides a physiologically coherent explanation of how a highly reactive oxidant can, under controlled conditions, engage endogenous adaptive pathways relevant to inflammation, metabolic regulation, and tissue remodeling [15,16,26,76,77,78,79]. It also underscores the need for quantitative assessment of redox biomarkers to define therapeutic windows, ensure reproducibility, and minimize the risk of unintended oxidative injury [7,46,51].
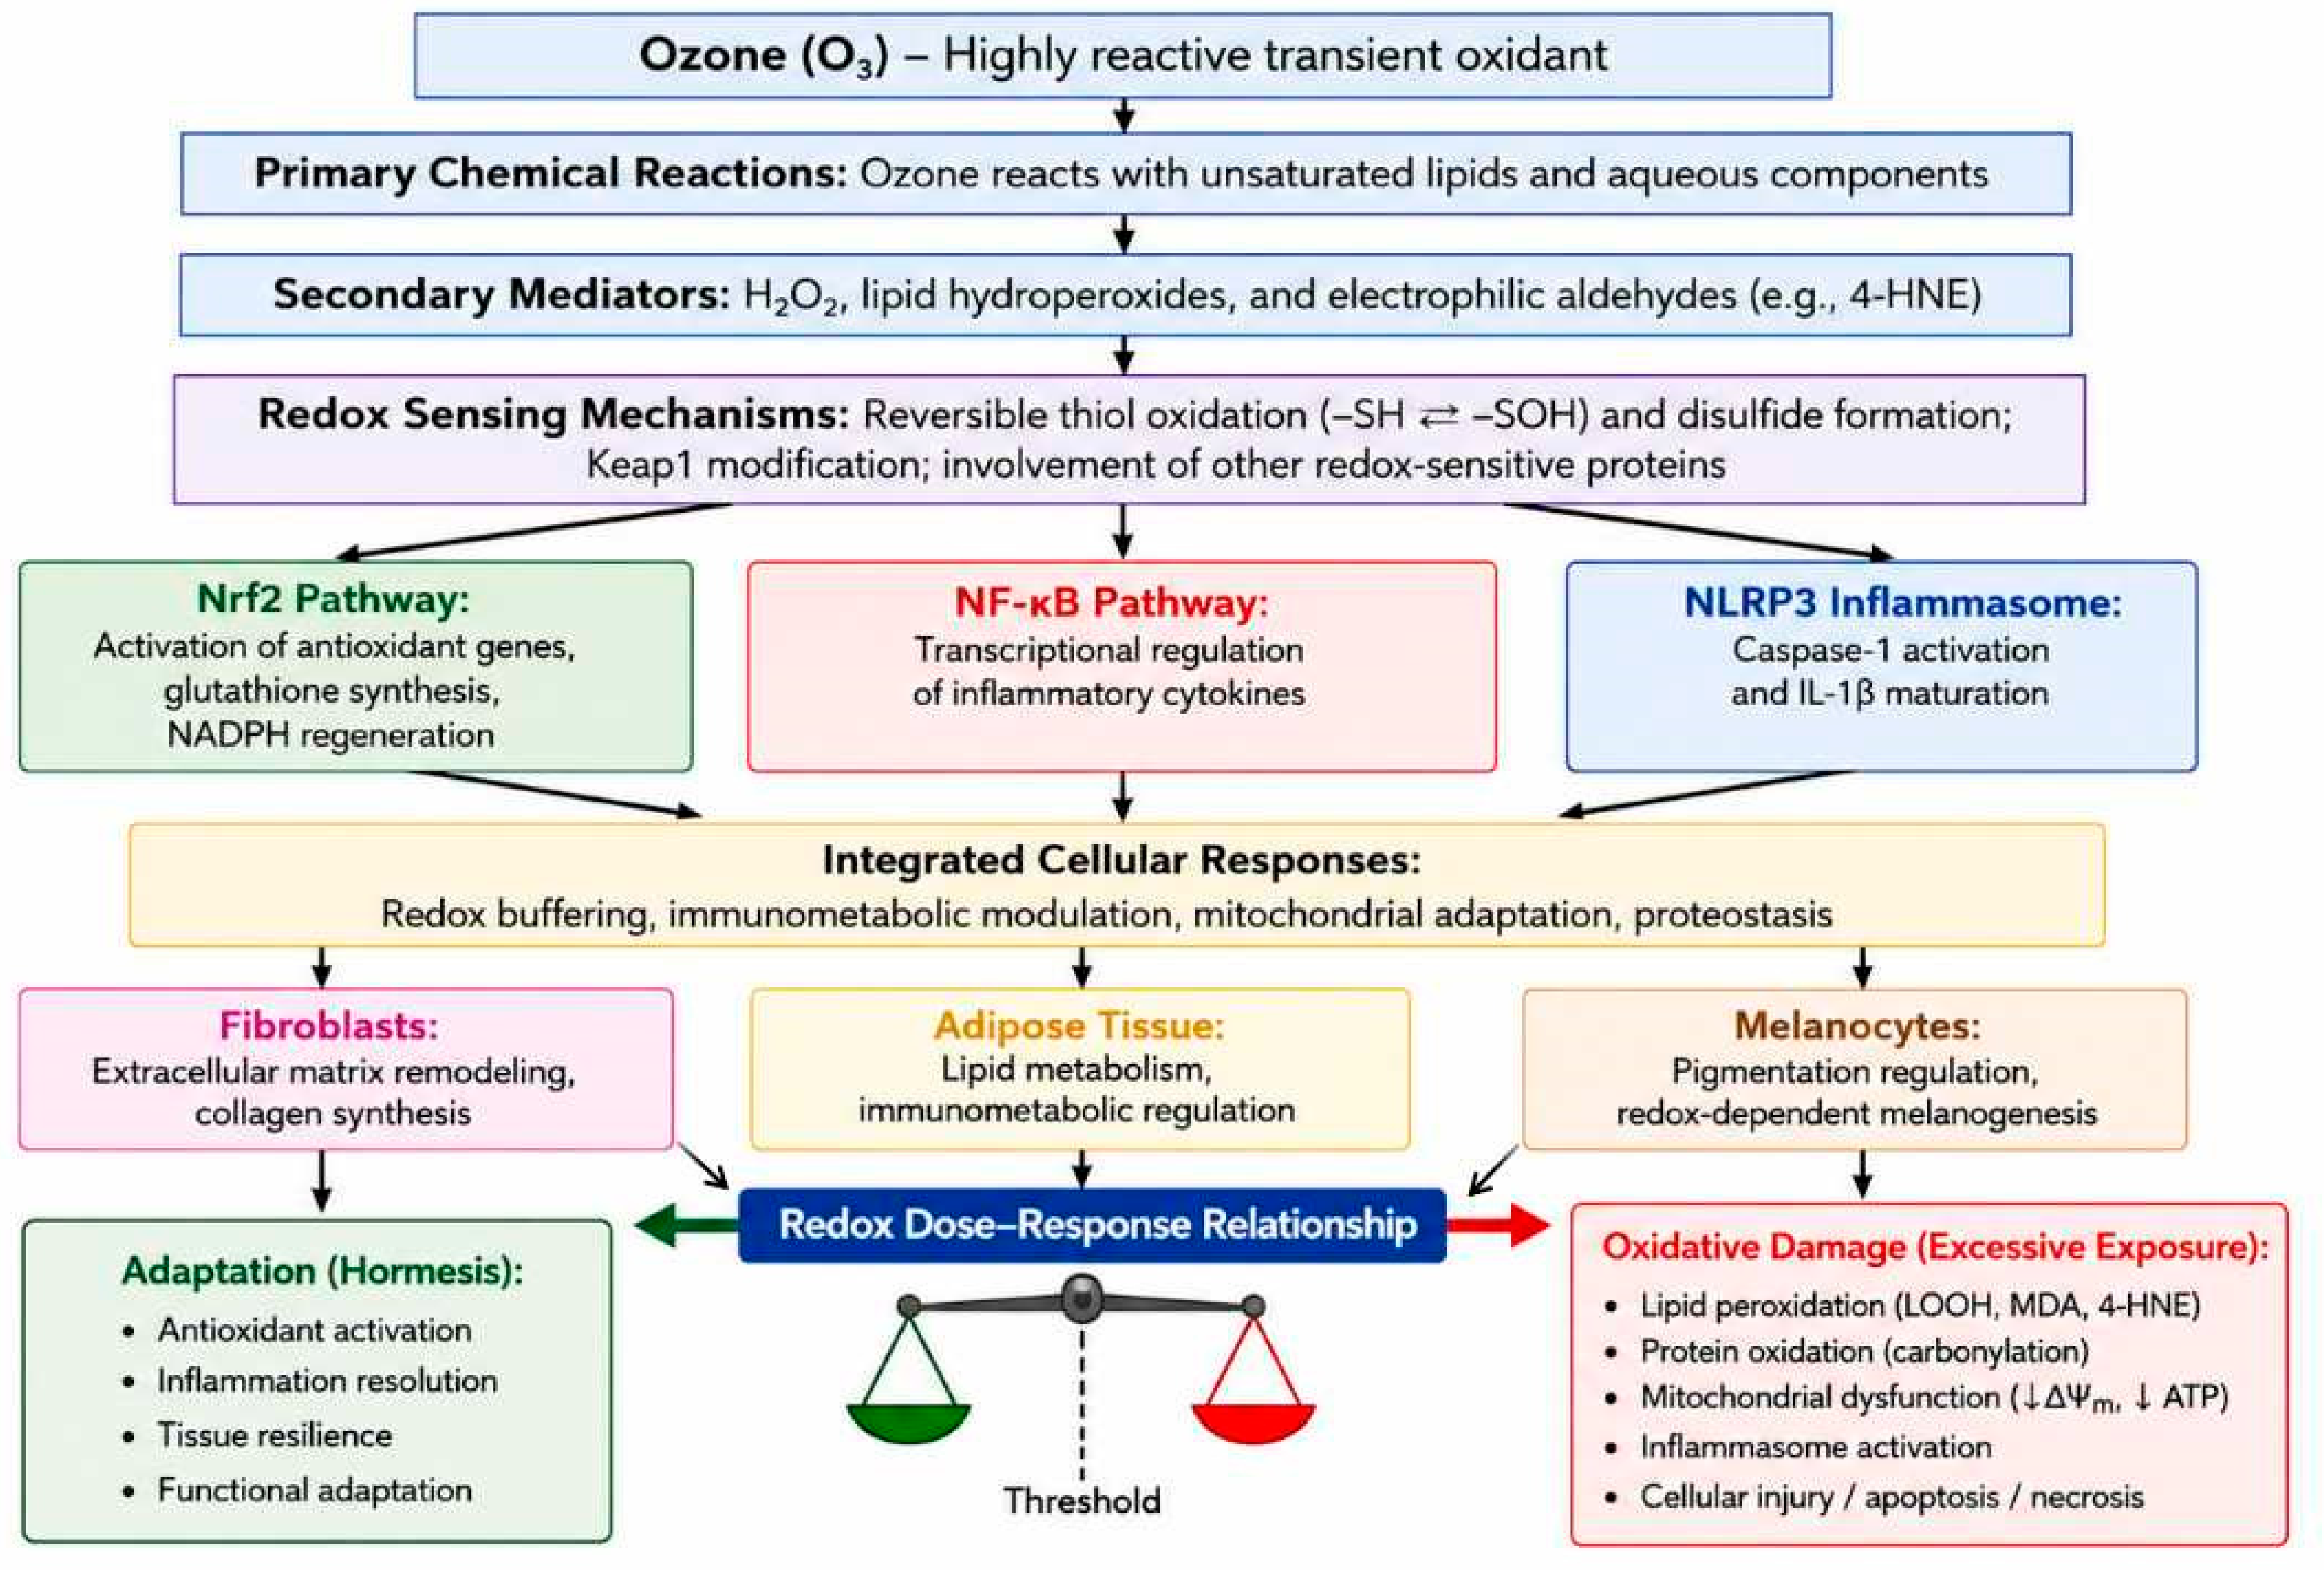
Collectively, these interconnected processes define a coordinated redox-responsive network linking ozone-induced chemical reactivity to adaptive signaling, inflammatory modulation, metabolic regulation, and tissue-specific responses within a dose-dependent framework. Figure 1 summarizes the principal mechanistic interactions underlying these processes and highlights the central role of the redox dose–response relationship in determining the balance between adaptive hormetic responses and oxidative injury.

4. Redox Signaling and Antioxidant Network Reprogramming

The spatiotemporal characteristics described above provide the biological framework through which transient oxidative perturbations are translated into coordinated antioxidant and metabolic responses.
ROS act as context-dependent signaling intermediates, whose biological effects are determined by concentration, subcellular localization, and temporal dynamics rather than by mere presence [3,4,5,6,78]. Cellular redox homeostasis reflects a dynamic equilibrium sustained by thiol buffering systems, enzymatic detoxification pathways, and transcriptional feedback circuits [79]. Within this framework, controlled ozone exposure can be conceptualized as an electrophile-driven signal capable of engaging endogenous redox networks without requiring persistent oxidant accumulation [15,16,22,78].
A central integrative node in this response is the Nrf2 pathway [24,25,26,63,64]. Under basal conditions, Nrf2 undergoes continuous ubiquitination and proteasomal degradation through its interaction with the redox-sensitive adaptor Keap1 [24,25,26]. Electrophilic modification of critical cysteine residues in Keap1 induces conformational changes that attenuate Nrf2 ubiquitination, promoting stabilization and nuclear translocation [24,25,26,63,65]. Notably, this activation relies on selective thiol reactivity rather than on global oxidative burden, highlighting the specificity of redox sensing within the Keap1 complex [26,63,65].
Upon activation, Nrf2 orchestrates a broad transcriptional program extending beyond canonical antioxidant enzymes [24,25,26,80]. In addition to superoxide dismutase, catalase, and glutathione peroxidase, Nrf2 regulates genes involved in glutathione biosynthesis, NADPH regeneration, thioredoxin systems, and phase II detoxification pathways [24,25,26,63,65]. These coordinated responses enhance the cellular capacity to buffer peroxide flux, detoxify electrophiles, and maintain thiol redox homeostasis [24,25,26,60,61,62,63,64,65]. Importantly, such transcriptional reprogramming shifts the intracellular redox set point, promoting sustained adaptive competence rather than merely resolving an acute oxidative perturbation [63,65,79,80]. While Nrf2 represents a central hub, additional pathways, including mitogen-activated protein kinase (MAPK-) and AP-1-dependent networks, may contribute to context-dependent responses to electrophilic and oxidative stimuli [5,6,63].
Redox adaptation is tightly coupled to metabolic control [65,68,69,70,71,72]. Maintenance of reduced glutathione (GSH) requires continuous nicotinamide adenine dinucleotide phosphate (NADPH) supply, linking Nrf2 activity to the pentose phosphate pathway and other metabolic nodes that sustain cellular reductive capacity [65,68,69,73]. In this context, ozone-induced electrophile sensing can be viewed as a trigger synchronizing transcriptional antioxidant reinforcement with metabolic flux adjustments [15,16,26,65]. The effectiveness of this adaptation depends not only on gene induction but also on the availability of reducing equivalents and substrate turnover [68,69,70,71,72,73,74].
Integration with inflammatory signaling further defines the systems-level consequences of redox reprogramming [27,28]. NF-κB acts as a master regulator of inflammatory transcriptional programs, controlling the expression of pro-inflammatory cytokines, adhesion molecules, and inflammasome-related components in response to redox perturbations [27,28,81]. Crosstalk between Nrf2 and NF-κB occurs via multiple mechanisms, including modulation of intracellular peroxide tone, competition for transcriptional co-activators, and reciprocal regulation of target genes [26,27,28]. Reinforcement of antioxidant buffering may constrain sustained NF-κB amplification loops, reshaping inflammatory network dynamics without direct pharmacological inhibition of individual cytokines [26,27,28].
Experimental studies of controlled ozone exposure report associations between Nrf2 activation and reduced expression of inflammatory mediators, including tumor necrosis factor-α, interleukin-1β, and interleukin-6 [15,16,46,51]. These findings support a model in which redox modulation recalibrates immune signaling through network-level adaptation rather than direct suppression of individual targets [15,16,26,27,28].
The biological outcome of this network reprogramming remains strongly dose-dependent and context-sensitive [11,12,15,16]. When electrophile-driven signaling is maintained within the system’s buffering capacity, adaptive transcriptional and metabolic reinforcement predominates [11,12,15,16,24,25,26,65]. Conversely, excessive oxidative input depletes thiols, induces irreversible protein oxidation, and triggers enzymatic dysfunction, shifting the response toward cellular injury [1,2,3,4,5,6,7,21,22,23,55,56,57,58]. In cutaneous tissues, Nrf2-dependent activation is associated with enhanced resilience to oxidative stress, modulation of inflammatory signaling, and preservation of tissue homeostasis [34,36,66]. These observations highlight potential relevance in dermatological conditions characterized by chronic redox imbalance, though the extent of clinical translation remains to be fully defined.
Collectively, these considerations support a model in which medical ozone acts as a transient electrophilic stimulus that engages interconnected antioxidant, metabolic, and inflammatory networks [15,16,24,25,26,68,69,79,80]. The resulting biological phenotype reflects coordinated systems-level adaptation rather than isolated biochemical effects, reinforcing the interpretation of ozone exposure as a context-dependent redox modulator.

5. Redox Control of Inflammatory and Inflammasome Signaling

Inflammatory signaling is tightly coupled to cellular redox status [3,4,5,6,7,8,9,10,27,28,81,82]. ROS and reactive nitrogen species (RNS) contribute not only to antimicrobial defense but also to the initiation, amplification, and resolution of immune responses [10,27,28,81,82]. Physiological oxidative bursts generated by innate immune cells are spatially confined and temporally regulated, supporting effective pathogen clearance and tissue repair [3,4,5,6,76,77,78,79]. In contrast, persistent redox imbalance sustains inflammatory circuit activation and promotes progressive tissue dysfunction [1,2,3,4,5,6,7,27,28,81,82]. Within this framework, the immunological effects of medical ozone are best interpreted as indirect consequences of redox network modulation, rather than as direct immunosuppressive activity [13,14,15,16,46,51].
Although ozone exhibits intrinsic antimicrobial activity through rapid oxidation of microbial membranes and biofilm components [13,83], its broader immunological relevance resides in host cell signaling [15,16,46,51]. Under controlled exposure conditions, ozone-derived secondary mediators modulate intracellular redox tone in innate immune cells, including macrophages, neutrophils, and dendritic cells [15,16,24,25,26]. These redox shifts can influence cytokine production, phagocytic capacity, and metabolic programming in a dose- and context-dependent manner [27,28,68,69,70,71,72].
A central redox-sensitive platform in innate immunity is the NLRP3 inflammasome [29,30,31,32,33,67,84]. The priming phase, often mediated by NF-κB, induces transcriptional upregulation of inflammasome components and pro-Interleukin-1 beta (IL-1β) [27,28,29,30,31,32,33,84]. The activation phase is triggered by cellular stress signals, including ionic fluxes (notably potassium efflux), mitochondrial perturbation, and changes in oxidant production, ultimately leading to inflammasome assembly and caspase-1 activation [29,30,31,32,33,67]. Mitochondrial ROS have been implicated in modulating this activation, although the precise intermediates and causal hierarchy remain incompletely defined [30,31,32,33].
Controlled redox modulation may influence both priming and activation [15,16,24,25,26,27,28,29,30,33,84]. Reinforcement of antioxidant capacity via Nrf2-dependent transcriptional programs can limit sustained oxidant accumulation that supports inflammasome amplification [24,25,26,63,64,65]. Concurrent attenuation of NF-κB-driven priming may constrain expression of NLRP3 components and pro-inflammatory cytokines [26,27,28]. Experimental models of controlled ozone exposure have reported associations with reduced inflammasome activity and decreased secretion of IL-1β, tumor necrosis factor alpha (TNF-α), and interleukin-6 (IL-6) under controlled dosing conditions [15,16,46,50,51]. These observations suggest attenuation of inflammasome-associated inflammatory output, although direct causal relationships require further clarification.
Redox regulation of inflammation extends to immunometabolic control [68,69,70,71,72,85]. Innate immune cell function is closely linked to metabolic state, and redox balance influences the distribution between glycolytic and oxidative programs [68,69,70,71,72,85]. Pro-inflammatory macrophage activation is associated with enhanced glycolysis and mitochondrial stress, whereas resolution phases restore redox buffering and oxidative metabolism [68,69,70,71,72,85]. Transient electrophile signaling, coupled with reinforcement of antioxidant systems, may bias immune cells toward phenotypes compatible with inflammatory resolution and tissue repair [15,16,26,68,69,70,71,72]. Although direct evidence linking ozone-derived mediators to sustained immunometabolic reprogramming is limited, this interpretation aligns with principles of redox–metabolic coupling in innate immunity [68,69,70,71,72,85].
The boundary between adaptive recalibration and pro-oxidant inflammatory activation is quantitatively and contextually determined [1,2,3,4,5,6,7,11,12]. When redox modulation remains within buffering capacity, chronic oxidant-driven amplification loops are constrained [15,16,24,25,26,60,61,62,63,64,65]. When oxidative input exceeds cellular reserve, mitochondrial dysfunction and uncontrolled ROS generation potentiate inflammatory signaling [30,31,32,33,67,68,69,70,71,72,73,74,75]. Biological outcomes are therefore shaped by dose, baseline inflammatory status, and tissue-specific antioxidant capacity [7,11,12].
Viewed in a systems-level framework, medical ozone does not function as a conventional anti-inflammatory agent targeting a single cytokine pathway. Rather, it acts as a redox-modulating stimulus interfacing with integrated inflammatory networks, influencing transcriptional priming, inflammasome dynamics, and immunometabolic programming [15,16,24,25,26,27,28,29,30,33,67,68,69,70,71,72,79,80,84]. Rigorous delineation of these mechanisms is essential to distinguish adaptive redox modulation from uncontrolled oxidative immune activation [7,46,50,51].
These mechanisms may have translational relevance in dermatological conditions characterized by persistent inflammasome and inflammatory pathway activation, including chronic inflammatory dermatoses and impaired wound healing [34,36,44,66].
However, clinical applicability depends on precise control of exposure parameters and requires further validation in well-designed studies [46,50,51,86].
The integrated signaling mechanisms described above ultimately converge at the tissue level, where redox regulation coordinates the responses of fibroblasts, immune cells, and skin-associated subcutaneous adipose tissue.
The molecular pathways discussed above do not operate as isolated signaling modules but rather as components of an integrated redox-responsive network. Table 1 summarizes the principal regulatory axes, molecular triggers, and systems-level consequences associated with controlled ozone-induced oxidative signaling.

6. Tissue-Level Integration of Redox Signaling in the Skin and Subcutaneous Tissue

Skin and subcutaneous adipose tissue represent metabolically active and redox-sensitive compartments, where oxidative signaling intersects with extracellular matrix turnover, immune surveillance, vascular regulation, and metabolic control [34,35,36,37,38,39,40,76,77,78,79]. Rather than functioning as passive structural layers, these tissues act as dynamic redox interfaces, continuously exposed to environmental stressors, inflammatory stimuli, and fluctuations in oxygen availability [34,35,36]. Persistent disruption of redox homeostasis within this axis contributes to chronic inflammation, impaired repair, pigmentary alterations, and progressive structural remodeling associated with aging and metabolic dysfunction [34,35,36,37,38,39,40]. Controlled ozone exposure provides a framework for examining how localized oxidative cues can be integrated at the tissue level [46,51].
Within the skin, dermal fibroblasts and the underlying subcutaneous adipose tissue function as closely interconnected components of a single functional unit. Through reciprocal biochemical and mechanical interactions, these compartments coordinate extracellular matrix remodeling, inflammatory signaling, and local metabolic adaptation, thereby contributing to tissue homeostasis and repair. This functional integration is particularly relevant in dermatological and regenerative medicine, where local redox balance emerges from coordinated interactions among multiple cellular and tissue compartments rather than from isolated responses. Accordingly, the following sections focus specifically on the role of the local subcutaneous adipose tissue in redox homeostasis and tissue remodeling, rather than on systemic adipose tissue biology [34,35,36,37,38,39,40,41,42,43,44,45,68,69,70,71,72].

6.1. Fibroblast Redox Regulation and Matrix Dynamics

Dermal fibroblasts are central regulators of extracellular matrix homeostasis [34,35,36,41,42,43]. Their activity is governed by redox-sensitive pathways that influence collagen synthesis, matrix metalloproteinase expression, cytoskeletal organization, and growth factor responsiveness [41,42,43,44,45]. Both excessive oxidative stress and insufficient redox signaling impair matrix integrity, indicating that fibroblast function depends on a finely tuned oxidative tone [34,36].
Electrophile- and peroxide-mediated signaling can reinforce intracellular antioxidant capacity and modulate transcriptional programs linked to matrix production [24,25,26,63,65,66]. Activation of the Nrf2 pathway enhances glutathione biosynthesis and detoxification systems, stabilizing the intracellular environment required for collagen synthesis and post-translational processing [24,25,26,63,65]. Redox modulation may also intersect with transforming growth factor beta (TGF-β)-dependent signaling and matrix remodeling enzymes, influencing the balance between matrix deposition and degradation [34,35,36,41,42,43,44,45].Tissue remodeling arises from coordinated regulation of redox balance, inflammatory mediators, and metabolic state, rather than isolated induction of structural proteins [11,12,26,34,36]. Under controlled ozone exposure, redox modulation may support a fibroblast phenotype compatible with reparative processes [15,16,26]. When oxidative input exceeds buffering capacity, matrix degradation and functional decline are more likely [11,12,34,36]. Tissue outcomes are therefore contingent upon intracellular redox reserve and local inflammatory context.

6.2. Adipose Tissue as an Immunometabolic Redox Organ

Adipose tissue functions as an endocrine and immunometabolic organ, in which redox status influences lipid turnover, cytokine secretion, immune cell recruitment, and cellular differentiation [37,38,39,40,68,69,70,71,72,85,87,88]. Chronic oxidative imbalance contributes to adipocyte dysfunction, insulin resistance, and low-grade inflammation, whereas restoration of redox buffering capacity may recalibrate metabolic and inflammatory tone [37,38,39,40].
Lipolysis is regulated via cAMP-dependent pathways, converging on hormone-sensitive lipase activation and perilipin phosphorylation [87,88]. Redox-sensitive modulation of phosphodiesterase activity and kinase signaling provides a potential mechanistic link between oxidative cues and triglyceride mobilization [70,71,72,73,74,87]. These interactions are indirect and context-dependent, reflecting integration of electrophile signaling with metabolic control rather than direct oxidative degradation of lipids [68,69,70,71,72,73,74,88].
Beyond lipid mobilization, redox state influences adipocyte differentiation and macrophage polarization within adipose depots [37,38,39,40,68,69,70,71,72,85]. Activation of antioxidant transcriptional programs may attenuate oxidative stress-associated adipogenic signaling and inflammatory cytokine production [26,68,69,70,71,72]. Controlled redox modulation could thus shift adipose tissue toward a more balanced immunometabolic profile, though direct mechanistic evidence in ozone-specific systems remains limited [15,16,46,51].

6.3. Melanocyte Redox Homeostasis and Pigmentation Networks

Melanogenesis is intrinsically dependent on redox balance [89,90,91,92]. Tyrosinase activity and melanin synthesis involve oxidation reactions modulated by intracellular peroxide levels and thiol availability [89,90,91,92]. Perturbations in redox homeostasis can amplify melanogenic flux and contribute to pigmentary dysregulation [90,91,92].
Reinforcement of antioxidant systems may stabilize melanocyte redox tone and indirectly influence microphthalmia-associated transcription factor (MITF) activity through modulation of oxidative and inflammatory signaling pathways [26,36,66,89,90,91,92]. Within this framework, ozone-associated redox signaling modulates the oxidative microenvironment governing pigment synthesis rather than directly inhibiting melanogenesis [15,16,46]. Chronic oxidative stress also contributes to accumulation of oxidized macromolecules and impaired proteostasis in aging tissues [34,36]. Enhancing thiol homeostasis and antioxidant buffering may support proteolytic turnover and limit oxidative pigment accumulation [26,36,65].

6.4. Integrated Redox Adaptation in Tissue Aging and Remodeling

Cutaneous aging and adipose remodeling reflect cumulative alterations in redox signaling, mitochondrial function, inflammatory tone, and extracellular matrix dynamics [34,35,36,37,38,39,40]. The Nrf2 and NF-κB pathways represent counterbalancing regulatory axes coordinating antioxidant defense and inflammatory amplification [26,27,28,81]. Tissue resilience depends on the dynamic equilibrium between these networks [26,27,28,34].
Controlled redox modulation may transiently engage protective transcriptional programs and metabolic buffering across multiple cell populations within the cutaneous–subcutaneous unit [11,12,15,16,24,25,26,68,69,70,71,72,79,80]. The resulting phenotype emerges from coordinated network integration, not from isolated molecular events. As previously discussed, the adaptive range is biologically constrained; once buffering systems are exceeded, redox signaling shifts toward structural damage and inflammatory escalation [1,2,3,4,5,6,7,11,12].
Skin and adipose tissue thus provide biologically relevant systems in which localized oxidative signals are translated into coordinated transcriptional, metabolic, and inflammatory adaptation [34,36,37,38,39,40,76,77,78,79,80]. Clinical interpretation requires careful quantification of dosing, redox biomarkers, and long-term functional outcomes, avoiding attribution of tissue-level changes to single pathways [7,46,50,51].
These coordinated tissue responses provide the mechanistic basis for interpreting the potential translational implications discussed in the following section.
To integrate these tissue-specific considerations within a unified redox framework, Table 2 summarizes the principal regulatory nodes through which localized oxidative signaling propagates into coordinated transcriptional, metabolic, and inflammatory responses across the cutaneous–subcutaneous axis.

7. Translational Integration: From Redox Mechanisms to Clinical Hypotheses

The mechanistic framework outlined above provides a biochemical basis for interpreting reported clinical observations [3,7,15,16,24,25,26,46,51]. These effects are more appropriately understood as downstream manifestations of redox-mediated adaptive responses, rather than direct pharmacological effects of ozone [3,7,15,16]. The goal is to delineate mechanistic plausibility within a redox biology framework, rather than to infer disease-specific efficacy. Translational relevance ultimately depends on whether controlled oxidative perturbations can reproducibly engage endogenous regulatory networks within biologically constrained adaptive ranges [11,12].
From a dermatological standpoint, these mechanisms offer a conceptual framework for interpreting clinical observations related to skin inflammation, tissue remodeling, and aesthetic outcomes, emphasizing the need for rigorous validation through well-controlled studies incorporating molecular and redox endpoints [34,35,36,66].

7.1. Inflammatory Skin Disorders

Inflammatory dermatoses are characterized by sustained redox imbalance, microbial dysbiosis, and activation of innate immune pathways [27,28,29,30,31,32,33,34,35,36,81,82]. Although ozone exhibits intrinsic antimicrobial activity, its broader biological relevance is likely mediated through host redox signaling [13,14,15,16,46,52]. Electrophile-driven activation of antioxidant pathways may attenuate NF-κB-dependent priming and constrain NLRP3 inflammasome activation, thereby limiting self-sustaining inflammatory amplification loops [26,27,28,29,30,31,32,33,81].
These effects reflect modulation of redox–inflammatory coupling rather than direct cytokine inhibition [26,27,28]. The magnitude, spatial specificity, and temporal persistence of this modulation depend on dose, tissue redox reserve, and baseline inflammatory status [11,12,15,16,76,77,78,79]. Randomized controlled trials with molecular and redox biomarkers are required to determine whether mechanistic plausibility translates into reproducible clinical benefit [46,50,51].

7.2. Adipose Tissue Remodeling

Localized adiposity is often associated with oxidative stress, impaired microvascular perfusion, and low-grade inflammation [37,38,39,40]. Redox-sensitive modulation of metabolic pathways, including cAMP-dependent lipolysis and Nrf2-mediated antioxidant reinforcement, provides a mechanistic context for structural changes observed following ozone exposure [24,25,26,68,69,70,71,72,73,74,85,87,88].
Adipose remodeling reflects integrated processes involving vascular function, immune cell infiltration, extracellular matrix turnover, and mitochondrial dynamics [37,38,39,40,68,69,70,71,72,73,74,75,85,87,88]. Redox perturbation alone is unlikely to account for structural outcomes unless coupled with coordinated changes across these interconnected systems. Establishing causal relationships requires quantitative assessment of metabolic flux, inflammatory mediators, mitochondrial function, and extracellular matrix remodeling in rigorously controlled experimental settings.

7.3. Tissue Repair and Structural Aging

Cutaneous aging and impaired wound repair result from cumulative oxidative damage, persistent inflammatory signaling, and dysregulated extracellular matrix dynamics [34,35,36,44]. Reinforcement of antioxidant transcriptional programs and attenuation of sustained inflammatory priming may create a biochemical environment conducive to fibroblast function and matrix organization [24,25,26,34,63,65,66].
Transient redox adaptation, however, should not be equated with durable structural remodeling. Apparent improvements in dermal architecture or wound closure must be substantiated by quantitative analyses of matrix composition, gene expression, and validated redox biomarkers before mechanistic conclusions can be drawn [36,41,42,43,44].

7.4. Pigmentation Dynamics

Melanogenic pathways are highly sensitive to intracellular oxidative tone [89,90,91,92]. Changes in thiol availability and inflammatory signaling can influence melanocyte transcriptional programs and enzymatic flux [89,90,91,92]. Reinforcement of antioxidant systems may theoretically stabilize pigment homeostasis, but direct evidence linking ozone exposure to sustained modulation of melanogenesis is limited [26,66,89,90,91,92].
Clinical observations of pigmentation changes should thus be interpreted within the context of network-level redox behavior, rather than attributed to direct enzymatic inhibition or melanocyte suppression [76,77,78,79].

7.5. Translational Boundaries and Evidence Gaps

Across these contexts, a unifying hypothesis emerges: localized oxidative signaling engages endogenous adaptive programs capable of recalibrating redox set points and inflammatory tone [3,11,12,15,16,24,25,26,76,77,78,79,80]. However, the progression from molecular adaptation to sustained tissue remodeling remains incompletely defined.
Challenges include heterogeneity in administration protocols, variability in dosing strategies, lack of standardized redox biomarkers, and limited randomized controlled trials incorporating mechanistic endpoints [14,15,16,17,18,19,20,46,50,51]. Without rigorous integration of biochemical measurements, functional outcomes, and long-term safety data, clinical interpretations risk exceeding the available evidence.
From a redox systems perspective, translational relevance depends less on disease-specific indications than on reproducible engagement of adaptive signaling within biologically constrained ranges [11,12,76,77,78,79,80]. Future studies should integrate precise redox characterization, standardized dosing frameworks, and longitudinal outcome assessments to determine whether controlled oxidative modulation can yield sustained adaptive responses within defined biological limits.
Despite this mechanistic framework, important challenges remain regarding dose standardization, biomarker validation, and the quality of the available clinical evidence, all of which are critical for defining the therapeutic boundaries of medical ozone.
Although several clinical studies have reported encouraging results in selected dermatological and wound healing settings, the available evidence remains heterogeneous with respect to study design, patient selection, ozone administration protocols, and outcome measures. Therefore, current clinical observations should be interpreted primarily as supporting mechanistic hypotheses rather than as definitive evidence of therapeutic efficacy [18,46,50,51,86,93,94].

8. Dose-Dependent Redox Dynamics and Safety Constraints

Interpretation of biological and clinical findings related to medical ozone rests on a fundamental principle: its effects are inherently dose-dependent and governed by non-linear redox dynamics [1,3,7,11,12]. As a potent oxidant, ozone spans a continuum of responses, from regulated adaptive signaling to irreversible oxidative injury [13,14,15,16,52]. Failure to distinguish between these regimes has contributed to skepticism and overextension of therapeutic claims, highlighting the need for a quantitatively grounded mechanistic framework [7,46,51].

8.1. Hormetic Windows and Threshold Behavior

Hormesis provides a framework for understanding how low-intensity oxidative perturbations can engage adaptive stress responses and reinforce cellular resilience, whereas excessive oxidative burden promotes irreversible dysfunction and tissue injury [11,12,95]. Low-intensity redox perturbations may activate cytoprotective transcriptional programs, reinforce thiol buffering systems, and recalibrate inflammatory tone [3,15,16,24,25,26]. At higher intensities, depletion of antioxidant reserves and accumulation of irreversible macromolecular oxidation shift the system toward structural damage and dysfunction [21,22,23,55,56,57,58].
In the context of ozone exposure, this transition is determined not solely by administered concentration, but by the relationship between oxidative input and tissue-specific buffering capacity [2,73,75,79]. Glutathione availability, NADPH regeneration, mitochondrial integrity, and baseline inflammatory status all influence the threshold at which adaptive signaling gives way to injury [2,65,68,69,70,71,72,73,74,75]. The hormetic window is therefore context-dependent rather than fixed, reflecting tissue-specific differences in antioxidant buffering capacity, metabolic state, route of administration, and baseline redox status, rather than being defined by universally applicable quantitative thresholds [11,12].
Although concepts such as redox reserve, buffering capacity, adaptive range, and therapeutic boundaries are widely used throughout the ozone and redox biology literature, they should currently be regarded as functional biological concepts rather than standardized operational parameters. Their quantitative definition remains limited by the absence of harmonized dosing protocols and validated biomarkers capable of identifying the transition between adaptive redox signaling and oxidative injury across different tissues, routes of administration, and clinical contexts.
Consequently, these concepts describe the tissue-specific adaptive capacity of biological systems rather than fixed quantitative criteria applicable across different experimental and clinical settings. Establishing standardized dosing protocols together with validated molecular biomarkers capable of defining these concepts remains one of the major priorities for future mechanistic and translational research [7,46,50,51]. Several candidate biomarkers, including the GSH/GSSG ratio, protein thiol oxidation, lipid peroxidation products, and expression of Nrf2 target genes, have been proposed to assess redox status. However, none has yet been validated as a standardized surrogate of tissue-specific redox reserve.
Experimental evidence suggests that limited formation of lipid-derived electrophiles and peroxides engages Nrf2-associated pathways and modulates inflammatory signaling without triggering extensive radical chain propagation [22,23,24,25,26,63]. Once antioxidant systems are exceeded, protein carbonylation, propagation of lipid oxidation, and mitochondrial dysfunction predominate [21,22,23,55,56,57,58,67,68,69,70,71,72,73,74,75]. These thresholds remain insufficiently defined. The dose-dependent transition between adaptive redox signaling and oxidative injury can be conceptualized within a hormetic framework integrating electrophilic signaling, antioxidant buffering capacity, and mitochondrial resilience. The principal biological consequences associated with different levels of ozone-induced oxidative perturbation are summarized in Table 3.

8.2. Safety Constraints and Redox Buffering Capacity

Environmental ozone exposure and medically administered oxygen–ozone mixtures should not be considered biologically equivalent. Environmental ozone typically involves chronic inhalational exposure to uncontrolled atmospheric concentrations, resulting in sustained oxidative stress, antioxidant depletion, lipid peroxidation, and inflammatory responses [47,48]. In contrast, medical ozone consists of controlled oxygen–ozone mixtures administered locally using defined delivery systems and exposure protocols designed to generate transient redox signaling within a limited biological compartment. Consequently, the biological response depends not only on ozone concentration but also on the route of administration, delivery system, exposure protocol, tissue interface, and local antioxidant buffering capacity [14,17,20,46,51].
Ozone’s high reactivity and short half-life impose intrinsic kinetic constraints on biological behavior [13,14,15,16,17,18,19,20,52,53,54]. In non-inhalational medical applications, oxidative reactions are largely confined to local microenvironments, where extracellular substrates and thiol buffers determine the amplitude of the redox signal [13,14,15,16,17,18,19,20,76,77,78,79]. Such localization reduces systemic persistence, but focal oxidative injury may occur when buffering capacity is exceeded [11,12,21,22,23,55,56,57,58].
These biological features clearly distinguish controlled medical ozone applications from the toxicological effects associated with environmental ozone exposure, which primarily result from chronic inhalational exposure and pulmonary epithelial injury [47,48]. Nevertheless, even in controlled therapeutic settings, the lack of standardized dosing metrics and limited biochemical monitoring complicate safety evaluation [46,50,51].
A robust safety framework therefore requires quantitative assessment of oxidative and redox biomarkers, characterization of antioxidant reserve, and evaluation of mitochondrial function, rather than reliance on clinical observation alone [1,3,7,46,73,74,75].

8.3. Methodological Heterogeneity and Evidence Quality

Substantial heterogeneity across experimental and clinical protocols remains a central limitation in ozone research [14,15,16,17,18,19,20,46,51]. Variability in concentration, delivery modality, exposure duration, and tissue context impairs reproducibility and obscures dose–response relationships. Mechanistic investigations and clinical studies are often misaligned in design and endpoints, limiting robust causal inference.
Reported biological and clinical outcomes are likewise inconsistent, with some studies failing to demonstrate reproducible or durable effects. Many clinical reports are based on small cohorts, observational designs, or uncontrolled case series [18,86,93,94]. While useful for hypothesis generation, such studies cannot define therapeutic windows or establish long-term safety margins. The absence of standardized molecular endpoints, particularly validated redox biomarkers, further limits interpretability [7,46,50,51].
Progress in this field requires integration of quantitative redox profiling with rigorously designed randomized controlled trials incorporating both molecular and functional endpoints [7,46,50,51]. To facilitate the interpretation of current evidence and provide a translational perspective, Table 4 presents a conceptual framework of representative candidate biomarkers currently used to investigate ozone-induced redox responses. The biomarkers are organized according to the principal biological processes they primarily reflect, including oxidative damage, adaptive redox signaling, inflammatory activation, and integrated biomarker assessment, together with the biological matrices in which they are commonly assessed and their potential translational applications. This framework is intended to summarize the current evidence rather than to propose validated clinical biomarkers for medical ozone applications.
Taken together, the inconsistencies observed across the current literature likely reflect differences in ozone concentration, route of administration, treatment protocols, patient selection, biological matrices, and overall methodological quality. Consequently, conflicting findings should not necessarily be interpreted as contradictory biological effects but rather as evidence of substantial experimental and clinical heterogeneity. Collectively, these observations further underscore the need for standardized study designs, harmonized outcome measures, and validated molecular biomarkers to improve the reproducibility and translational value of future investigations.

8.4. Regulatory Variability and Conceptual Framing

Regulatory positions on medical ozone vary substantially across jurisdictions, reflecting divergent interpretations of available evidence and differing clinical traditions [46,50,51,86,93,94]. Some guidance relies heavily on expert consensus rather than controlled mechanistic or clinical data [46,93].
From a redox biology perspective, ozone should not be viewed as a conventional pharmacological agent with linear dose–response behavior, but as a redox-modulating stimulus whose effects emerge from interactions with endogenous adaptive systems [3,11,12,24,25,26,78,79,80]. Without this distinction, interpretative extremes—overextension of claims or indiscriminate rejection—do not advance mechanistic understanding.

8.5. Critical Perspective and Future Directions

Medical ozone should be evaluated within the framework of controlled oxidative modulation, focusing on whether transient redox perturbations can reproducibly engage endogenous adaptive circuitry within biologically constrained ranges [11,12,15,16,24,25,26,76,77,78,79,80]. Scientific legitimacy depends on activation of protective transcriptional, metabolic, and inflammatory programs without transition into oxidative injury [21,22,23,55,56,57,58,67,68,69,70,71,72,73,74,75].
Meaningful progress requires shifting from descriptive clinical reporting toward quantitatively anchored mechanistic investigation. Clear definition of dose–response relationships, identification of biomarkers discriminating adaptive signaling from oxidative damage, and characterization of tissue-specific buffering variability are essential [1,2,3,4,5,6,7,11,12].
Future research should prioritize standardized administration parameters, integration of redox chemistry with systems-level signaling analyses, and controlled clinical investigations incorporating molecular endpoints and long-term safety assessment [7,46,50,51]. Only through such integrated approaches can the therapeutic plausibility of controlled oxidative modulation be objectively defined and distinguished from both unsubstantiated enthusiasm and categorical rejection.

9. Conclusions

Medical ozone represents a distinctive model of controlled oxidative modulation, whose biological effects fall outside conventional receptor-based pharmacological paradigms. Owing to its rapid chemical reactivity and transient persistence in biological environments, ozone does not act as a stable bioactive agent, but rather as an electrophilic initiator of redox-sensitive signaling cascades. The resulting biological outcomes arise from localized chemical interactions that are translated into coordinated transcriptional, metabolic, and inflammatory responses through endogenous sensing systems.
The evidence synthesized here supports a framework in which ozone-derived redox signals engage interconnected regulatory networks centered on Nrf2-dependent antioxidant control and redox-sensitive inflammatory circuitry. Within defined biological constraints, these processes may contribute to recalibration of tissue redox balance and modulation of systems-level behavior. Accordingly, tissue-level responses observed in cutaneous and adipose compartments are more appropriately interpreted as emergent properties of integrated network adaptation rather than as direct biochemical effects of the oxidant itself. Because tissue responsiveness is shaped by antioxidant reserve, metabolic context, and inflammatory status, translation of mechanistic insight into clinical application must remain quantitatively grounded and supported by rigorous evidence.
Future progress will depend on the integration of redox chemistry with systems-level analyses and rigorously designed clinical investigation. Precise characterization of electrophile formation, thiol redox dynamics, mitochondrial adaptation, and transcriptional reprogramming will be essential to define context-dependent thresholds and tissue specificity. Standardized dosing strategies and molecularly anchored safety assessment will likewise be required to establish reproducible therapeutic boundaries.
In dermatological contexts, this perspective provides a mechanistic framework for interpreting the biological effects reported following ozone-based interventions, without implying established therapeutic efficacy.
Within this framework, medical ozone is best regarded not as a disease-specific therapeutic agent, but as a redox-modulating tool for probing adaptive capacity in complex biological systems. Its potential clinical relevance will ultimately depend on whether these mechanistic hypotheses can be confirmed through standardized experimental investigations and well-designed randomized clinical studies incorporating robust molecular and functional endpoints.

Author Contributions

Conceptualization, F.P., F.B.C., A.P.; methodology, F.P., F.B.C., A.P.; software, A.P.; validation, F.P., F.B.C., A.P.; investigation, F.P., F.B.C., A.P.; data curation, F.P., F.B.C., A.P.; writing—original draft preparation, A.P.; writing—review and editing, F.P., F.B.C., A.P.; visualization, F.P., F.B.C., A.P.; supervision, A.P. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

No new data were created or analyzed in this study.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

The following abbreviations are used in this manuscript:
4-HNE4-Hydroxynonenal
IL-1βInterleukin-1 beta
IL-6Interleukin-6
Keap1Kelch-like ECH-associated protein 1
MAPKMitogen-activated protein kinase
MITFMicrophthalmia-associated transcription factor
NADPHNicotinamide adenine dinucleotide phosphate (reduced form)
NF-κBNuclear factor kappa b
NLRP3Nod-like receptor family pyrin domain-containing 3
Nrf2Nuclear factor erythroid 2–related factor 2
ROSReactive oxygen species
RNSReactive nitrogen species
TGF-βTransforming growth factor beta
TNF-αTumor necrosis factor alpha

References

  1. Sies, H.; Berndt, C.; Jones, D.P. Oxidative stress. Annu. Rev. Biochem. 2017, 86, 715–748. [Google Scholar] [CrossRef] [Scilit]
  2. Jones, D.P. Redefining oxidative stress. Antioxid. Redox Signal. 2006, 8, 1865–1879. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Sies, H. Hydrogen peroxide as a central redox signaling molecule in physiological oxidative stress: Oxidative eustress. Redox Biol. 2017, 11, 613–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Schieber, M.; Chandel, N.S. ROS function in redox signaling and oxidative stress. Curr. Biol. 2014, 24, R453–R462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Holmström, K.M.; Finkel, T. Cellular mechanisms and physiological consequences of redox-dependent signalling. Nat. Rev. Mol. Cell Biol. 2014, 15, 411–421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Forman, H.J.; Maiorino, M.; Ursini, F. Signaling functions of reactive oxygen species. Biochemistry 2010, 49, 835–842. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Forman, H.J.; Zhang, H. Targeting oxidative stress in disease: Promise and limitations of antioxidant therapy. Nat. Rev. Drug Discov. 2021, 20, 689–709. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Winterbourn, C.C. Reconciling the chemistry and biology of reactive oxygen species. Nat. Chem. Biol. 2008, 4, 278–286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Murphy, M.P.; Holmgren, A.; Larsson, N.G.; Halliwell, B.; Chang, C.J.; Kalyanaraman, B.; Rhee, S.G.; Thornalley, P.J.; Partridge, L.; Gems, D.; et al. Unraveling the biological roles of reactive oxygen species. Cell Metab. 2011, 13, 361–366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Nathan, C.; Cunningham-Bussel, A. Beyond oxidative stress: An immunologist’s guide to reactive oxygen species. Nat. Rev. Immunol. 2013, 13, 349–361. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Calabrese, E.J.; Baldwin, L.A. Hormesis: The dose-response revolution. Annu. Rev. Pharmacol. Toxicol. 2003, 43, 175–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Calabrese, E.J. Hormetic mechanisms. Crit. Rev. Toxicol. 2013, 43, 580–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Bocci, V. Ozone as Janus: This controversial gas can be either toxic or medically useful. Mediat. Inflamm. 2004, 13, 3–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Bocci, V.; Borrelli, E.; Travagli, V.; Zanardi, I. The ozone paradox: Ozone is a strong oxidant as well as a medical drug. Med. Res. Rev. 2009, 29, 646–682. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Sagai, M.; Bocci, V. Mechanisms of action involved in ozone therapy: Is healing induced via a mild oxidative stress? Med. Gas Res. 2011, 1, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Bocci, V.A.; Zanardi, I.; Travagli, V. Ozone acting on human blood yields a hormetic dose-response relationship. J. Transl. Med. 2011, 9, 66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Bocci, V.; Zanardi, I.; Travagli, V. Oxygen/ozone as a medical gas mixture: A critical evaluation of the various methods clarifies positive and negative aspects. Med. Gas Res. 2011, 1, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Elvis, A.M.; Ekta, J.S. Ozone therapy: A clinical review. J. Nat. Sci. Biol. Med. 2011, 2, 66–70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Travagli, V.; Zanardi, I.; Bocci, V. A realistic evaluation of the action of ozone on whole human blood. Int. J. Biol. Macromol. 2006, 39, 317–320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Zanardi, I.; Borrelli, E.; Valacchi, G.; Travagli, V.; Bocci, V. Ozone: A multifaceted molecule with unexpected therapeutic activity. Curr. Med. Chem. 2016, 23, 304–314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Ayala, A.; Muñoz, M.F.; Argüelles, S. Lipid peroxidation: Production, metabolism, and signaling mechanisms of malondialdehyde and 4-hydroxy-2-nonenal. Oxid. Med. Cell. Longev. 2014, 2014, 360438. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Higdon, A.; Diers, A.R.; Oh, J.Y.; Landar, A.; Darley-Usmar, V.M. Cell signalling by reactive lipid species: New concepts and molecular mechanisms. Biochem. J. 2012, 442, 453–464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Uchida, K. 4-Hydroxy-2-nonenal: A product and mediator of oxidative stress. Prog. Lipid Res. 2003, 42, 318–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Yamamoto, M.; Kensler, T.W.; Motohashi, H. The KEAP1-NRF2 system: A thiol-based sensor-effector apparatus for maintaining redox homeostasis. Physiol. Rev. 2018, 98, 1169–1203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Baird, L.; Yamamoto, M. The molecular mechanisms regulating the KEAP1-NRF2 pathway. Mol. Cell. Biol. 2020, 40, e00099-20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Cuadrado, A.; Rojo, A.I.; Wells, G.; Hayes, J.D.; Cousin, S.P.; Rumsey, W.L.; Attucks, O.C.; Franklin, S.; Levonen, A.L.; Kensler, T.W.; et al. Therapeutic targeting of the NRF2 and KEAP1 partnership in chronic diseases. Nat. Rev. Drug Discov. 2019, 18, 295–317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Morgan, M.J.; Liu, Z.G. Crosstalk of reactive oxygen species and NF-κB signaling. Cell Res. 2011, 21, 103–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Liu, T.; Zhang, L.; Joo, D.; Sun, S.C. NF-κB signaling in inflammation. Signal Transduct. Target. Ther. 2017, 2, 17023. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Schroder, K.; Tschopp, J. The inflammasomes. Cell 2010, 140, 821–832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. He, Y.; Hara, H.; Núñez, G. Mechanism and regulation of NLRP3 inflammasome activation. Trends Biochem. Sci. 2016, 41, 1012–1021. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Zhou, R.; Yazdi, A.S.; Menu, P.; Tschopp, J. A role for mitochondria in NLRP3 inflammasome activation. Nature 2011, 469, 221–225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Kelley, N.; Jeltema, D.; Duan, Y.; He, Y. The NLRP3 inflammasome: An overview of mechanisms of activation and regulation. Int. J. Mol. Sci. 2019, 20, 3328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Swanson, K.V.; Deng, M.; Ting, J.P.Y. The NLRP3 inflammasome: Molecular activation and regulation to therapeutics. Nat. Rev. Immunol. 2019, 19, 477–489. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Rinnerthaler, M.; Bischof, J.; Streubel, M.K.; Trost, A.; Richter, K. Oxidative stress in aging human skin. Biomolecules 2015, 5, 545–589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Krutmann, J.; Bouloc, A.; Sore, G.; Bernard, B.A.; Passeron, T. The skin aging exposome. J. Dermatol. Sci. 2017, 85, 152–161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Kammeyer, A.; Luiten, R.M. Oxidation events and skin aging. Ageing Res. Rev. 2015, 21, 16–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Reilly, S.M.; Saltiel, A.R. Adapting to obesity with adipose tissue inflammation. Nat. Rev. Endocrinol. 2017, 13, 633–643. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Hotamisligil, G.S. Inflammation and metabolic disorders. Nature 2006, 444, 860–867. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Gregor, M.F.; Hotamisligil, G.S. Inflammatory mechanisms in obesity. Annu. Rev. Immunol. 2011, 29, 415–445. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Furukawa, S.; Fujita, T.; Shimabukuro, M.; Iwaki, M.; Yamada, Y.; Nakajima, Y.; Nakayama, O.; Makishima, M.; Matsuda, M.; Shimomura, I. Increased oxidative stress in obesity and its impact on metabolic syndrome. J. Clin. Investig. 2004, 114, 1752–1761. [Google Scholar] [CrossRef] [PubMed]
  41. Quan, T.; Qin, Z.; Xia, W.; Shao, Y.; Voorhees, J.J.; Fisher, G.J. Matrix-degrading metalloproteinases in photoaging. J. Investig. Dermatol. Symp. Proc. 2009, 14, 20–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Fisher, G.J.; Kang, S.; Varani, J.; Bata-Csorgo, Z.; Wan, Y.; Datta, S.; Voorhees, J.J. Mechanisms of photoaging and chronological skin aging. Arch. Dermatol. 2002, 138, 1462–1470. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Pittayapruek, P.; Meephansan, J.; Prapapan, O.; Komine, M.; Ohtsuki, M. Role of matrix metalloproteinases in photoaging and photocarcinogenesis. Int. J. Mol. Sci. 2016, 17, 868. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Eming, S.A.; Martin, P.; Tomic-Canic, M. Wound repair and regeneration: Mechanisms, signaling, and translation. Sci. Transl. Med. 2014, 6, 265sr6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Briganti, S.; Picardo, M. Antioxidant activity, lipid peroxidation and skin diseases: What’s new. J. Eur. Acad. Dermatol. Venereol. 2003, 17, 663–669. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Travagli, V.; Iorio, E.L. The biological and molecular action of ozone and its derivatives: State-of-the-art, enhanced scenarios, and quality insights. Int. J. Mol. Sci. 2023, 24, 8465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Mudway, I.S.; Kelly, F.J. Ozone and the lung: A sensitive issue. Mol. Asp. Med. 2000, 21, 1–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  48. Kelly, F.J.; Fussell, J.C. Air pollution and airway disease. Clin. Exp. Allergy 2011, 41, 1059–1071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Halliwell, B.; Gutteridge, J.M.C. Free Radicals in Biology and Medicine, 5th ed.; Oxford University Press: New York, NY, USA, 2015. [Google Scholar] [CrossRef] [Scilit]
  50. Alimohammadi, M.; Khoshnazar, S.M.; Khajehpour, H.; Izadi, M.; Einollahi, B.; Hushmandi, K. Effect of ozone therapy on oxidative stress indices in chronic inflammatory diseases: A systematic review and meta-analysis of randomized clinical trials. Adv. Redox Res. 2025, 17, 100143. [Google Scholar] [CrossRef] [Scilit]
  51. Viebahn-Haensler, R.; León Fernández, O.S. Ozone in medicine: The low-dose ozone concept and its basic biochemical mechanisms of action in chronic inflammatory diseases. Int. J. Mol. Sci. 2021, 22, 7890. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Pryor, W.A.; Squadrito, G.L.; Friedman, M. The cascade mechanism to explain ozone toxicity: The role of lipid ozonation products. Free Radic. Biol. Med. 1995, 19, 935–941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Criegee, R. Mechanism of ozonolysis. Angew. Chem. Int. Ed. Engl. 1975, 14, 745–752. [Google Scholar] [CrossRef] [Scilit]
  54. Hassan, Z.; Lehmann, C.W.; Götte, M.; Alcarazo, M. Criegee Intermediates Beyond Ozonolysis: Synthetic and Mechanistic Insights. Angew. Chem. Int. Ed. 2021, 60, 15138–15152. [Google Scholar] [CrossRef] [Scilit]
  55. Esterbauer, H.; Schaur, R.J.; Zollner, H. Chemistry and biochemistry of 4-hydroxynonenal, malonaldehyde and related aldehydes. Free Radic. Biol. Med. 1991, 11, 81–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Schaur, R.J. Basic aspects of the biochemical reactivity of 4-hydroxynonenal. Mol. Asp. Med. 2003, 24, 149–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Zarkovic, N. 4-Hydroxynonenal as a bioactive marker of pathophysiological processes. Mol. Asp. Med. 2003, 24, 281–291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Marnett, L.J. Oxy radicals, lipid peroxidation and DNA damage. Toxicology 2002, 181–182, 219–222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Girotti, A.W. Lipid hydroperoxide generation, turnover, and effector action in biological systems. J. Lipid Res. 1998, 39, 1529–1542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  60. Dinkova-Kostova, A.T.; Abramov, A.Y. The emerging role of Nrf2 in mitochondrial function. Free Radic. Biol. Med. 2015, 88, 179–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  61. Kobayashi, M.; Yamamoto, M. Nrf2-Keap1 regulation of cellular defense mechanisms against electrophiles and reactive oxygen species. Adv. Enzym. Regul. 2006, 46, 113–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  62. Kansanen, E.; Kuosmanen, S.M.; Leinonen, H.; Levonen, A.L. The Keap1-Nrf2 pathway: Mechanisms of activation and dysregulation in cancer. Redox Biol. 2013, 1, 45–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Tebay, L.E.; Robertson, H.; Durant, S.T.; Vitale, S.R.; Penning, T.M.; Dinkova-Kostova, A.T.; Hayes, J.D. Mechanisms of activation of the transcription factor Nrf2 by redox stressors, nutrient cues, and energy status and the pathways through which it attenuates degenerative disease. Free Radic. Biol. Med. 2015, 88, 108–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  64. Ma, Q. Role of Nrf2 in oxidative stress and toxicity. Annu. Rev. Pharmacol. Toxicol. 2013, 53, 401–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  65. Hayes, J.D.; Dinkova-Kostova, A.T. The Nrf2 regulatory network provides an interface between redox and intermediary metabolism. Trends Biochem. Sci. 2014, 39, 199–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Schäfer, M.; Werner, S. Nrf2—A regulator of keratinocyte redox signaling. Free Radic. Biol. Med. 2015, 88, 243–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  67. Billingham, L.K.; Stoolman, J.S.; Vasan, K.; Rodriguez, A.E.; Poor, T.A.; Szibor, M.; Jacobs, H.T.; Reczek, C.R.; Rashidi, A.; Zhang, P.; et al. Mitochondrial electron transport chain is necessary for NLRP3 inflammasome activation. Nat. Immunol. 2022, 23, 692–704. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  68. O’Neill, L.A.; Pearce, E.J. Immunometabolism governs dendritic cell and macrophage function. J. Exp. Med. 2016, 213, 15–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  69. Mills, E.L.; Kelly, B.; Logan, A.; Costa, A.S.H.; Varma, M.; Bryant, C.E.; Tourlomousis, P.; Däbritz, J.H.M.; Gottlieb, E.; Latorre, I.; et al. Succinate dehydrogenase supports metabolic repurposing of mitochondria to drive inflammatory macrophages. Cell 2016, 167, 457–470.e13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  70. Galván-Peña, S.; O’Neill, L.A.J. Metabolic reprogramming in macrophage polarization. Front. Immunol. 2014, 5, 420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  71. Kelly, B.; O’Neill, L.A.J. Metabolic reprogramming in macrophages and dendritic cells in innate immunity. Cell Res. 2015, 25, 771–784. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  72. Van den Bossche, J.; O’Neill, L.A.J.; Menon, D. Macrophage immunometabolism: Where are we (going)? Trends Immunol. 2017, 38, 395–406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  73. Stincone, A.; Prigione, A.; Cramer, T.; Wamelink, M.M.; Campbell, K.; Cheung, E.; Olin-Sandoval, V.; Grüning, N.M.; Krüger, A.; Tauqeer Alam, M.; et al. The return of metabolism: Biochemistry and physiology of the pentose phosphate pathway. Biol. Rev. 2015, 90, 927–963. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  74. Newman, J.C.; He, W.; Verdin, E. Mitochondrial protein acylation and intermediary metabolism: Regulation by sirtuins and implications for metabolic disease. J. Biol. Chem. 2012, 287, 42436–42443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  75. Murphy, M.P. How mitochondria produce reactive oxygen species. Biochem. J. 2009, 417, 1–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  76. Kaludercic, N.; Deshwal, S.; Di Lisa, F. Reactive oxygen species and redox compartmentalization. Front. Physiol. 2014, 5, 285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  77. Lennicke, C.; Cochemé, H.M. Redox metabolism: ROS as specific molecular regulators of cell signaling and function. Mol. Cell 2021, 81, 3691–3707. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  78. Sies, H.; Jones, D.P. Reactive oxygen species (ROS) as pleiotropic physiological signalling agents. Nat. Rev. Mol. Cell Biol. 2020, 21, 363–383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  79. Go, Y.M.; Jones, D.P. Redox compartmentalization in eukaryotic cells. Biochim. Biophys. Acta 2008, 1780, 1273–1290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  80. Tonelli, C.; Chio, I.I.C.; Tuveson, D.A. Transcriptional regulation by Nrf2. Antioxid. Redox Signal. 2018, 29, 1727–1745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  81. Karin, M. NF-κB as a critical link between inflammation and cancer. Cold Spring Harb. Perspect. Biol. 2009, 1, a000141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  82. Lawrence, T. The nuclear factor NF-κB pathway in inflammation. Cold Spring Harb. Perspect. Biol. 2009, 1, a001651. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  83. Komanapalli, I.R.; Lau, B.H.S. Ozone-induced damage of Escherichia coli K-12. Appl. Microbiol. Biotechnol. 1996, 46, 610–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  84. Bauernfeind, F.G.; Horvath, G.; Stutz, A.; Alnemri, E.S.; MacDonald, K.; Speert, D.; Fernandes-Alnemri, T.; Wu, J.; Monks, B.G.; Fitzgerald, K.A.; et al. Cutting edge: NF-κB activating pattern recognition and cytokine receptors license NLRP3 inflammasome activation by regulating NLRP3 expression. J. Immunol. 2009, 183, 787–791. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  85. O’Neill, L.A.J.; Kishton, R.J.; Rathmell, J. A guide to immunometabolism for immunologists. Nat. Rev. Immunol. 2016, 16, 553–565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  86. Wen, Q.; Liu, D.; Wang, X.; Zhang, Y.; Fang, S.; Qiu, X.; Chen, Q. A systematic review of ozone therapy for treating chronically refractory wounds and ulcers. Int. Wound J. 2022, 19, 853–870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  87. Lefkimmiatis, K.; Zaccolo, M. cAMP signaling in subcellular compartments. Pharmacol. Ther. 2014, 143, 295–304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  88. Greenberg, A.S.; Coleman, R.A.; Kraemer, F.B.; McManaman, J.L.; Obin, M.S.; Puri, V.; Yan, Q.W.; Miyoshi, H.; Mashek, D.G. The role of lipid droplets in metabolic disease in rodents and humans. J. Clin. Investig. 2011, 121, 2102–2110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  89. Slominski, A.; Tobin, D.J.; Shibahara, S.; Wortsman, J. Melanin pigmentation in mammalian skin and its hormonal regulation. Physiol. Rev. 2004, 84, 1155–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  90. Denat, L.; Kadekaro, A.L.; Marrot, L.; Leachman, S.A.; Abdel-Malek, Z.A. Melanocytes as instigators and victims of oxidative stress. J. Investig. Dermatol. 2014, 134, 1512–1518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  91. D’Mello, S.A.; Finlay, G.J.; Baguley, B.C.; Askarian-Amiri, M.E. Signaling pathways in melanogenesis. Int. J. Mol. Sci. 2016, 17, 1144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  92. Hearing, V.J. Determination of melanin synthetic pathways. J. Investig. Dermatol. 2011, 131, E8–E11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  93. Smith, N.L.; Wilson, A.L.; Gandhi, J.; Vatsia, S.; Khan, S.A. Ozone therapy: An overview of pharmacodynamics, current research, and clinical utility. Med. Gas Res. 2017, 7, 212–219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  94. Liu, Q.; Liu, J.; Cao, G.; Liu, Y.; Huang, Y.; Jiang, X. Ozone therapy for knee osteoarthritis: A literature visualization analysis of research hotspots and prospects. Med. Gas Res. 2025, 15, 356–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  95. Mattson, M.P. Hormesis defined. Ageing Res. Rev. 2008, 7, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Systems-level overview of ozone-induced redox signaling and adaptive responses. Ozone acts as a highly reactive transient oxidant that rapidly interacts with unsaturated lipids and aqueous biological components, generating secondary reactive and electrophilic mediators, including hydrogen peroxide (H2O2), lipid hydroperoxides, and electrophilic aldehydes. These species engage redox-sensitive sensing mechanisms through reversible thiol oxidation and modification of Keap1 and other redox-responsive proteins, promoting activation of interconnected signaling pathways, including Nrf2, NF-κB, and the NLRP3 inflammasome. Integration of these pathways coordinates antioxidant, metabolic, inflammatory, mitochondrial, and tissue-specific responses involving fibroblasts, skin-associated subcutaneous adipose tissue, and melanocytes. The central Redox Dose–Response Relationship illustrates the dose-dependent balance between adaptive hormetic responses and oxidative injury, indicating that tissue-specific biological outcomes are determined by the interaction between ozone-induced redox signaling and local redox buffering capacity. The green and red arrows represent the divergence toward adaptive responses or pathological oxidative injury according to tissue-specific redox buffering capacity. Black arrows indicate the direction of the signaling cascade, whereas the dashed vertical line represents the threshold separating adaptive hormetic responses from pathological oxidative injury. The different box colors are used only to distinguish the principal functional modules of the proposed mechanistic framework.
Oxygen 06 00018 g001
Table 1. Major Molecular Pathways Modulated by Ozone-Derived Redox Signaling.
Pathway/Regulatory AxisPrincipal Molecular TriggerBiological ConsequencePredominant Functional OutcomeRepresentative References
Nrf2–Keap1 pathwayElectrophilic cysteine modification and peroxide-mediated signalingAntioxidant transcriptional activation and metabolic reinforcementAdaptive redox reprogramming[24,25,26,60,61,62,63,64,65,79,80]
NF-κB signalingRedox-sensitive inflammatory activationTranscription of inflammatory cytokines and adhesion moleculesInflammatory amplification[27,28,81,82]
NLRP3 inflammasomeMitochondrial ROS generation; ionic fluxes; redox stressCaspase-1 activation and IL-1β maturationInnate inflammatory activation[29,30,31,32,33,67,84]
Immunometabolic pathwaysRedox-dependent metabolic rewiringGlycolytic and oxidative metabolic reprogrammingImmune adaptation and inflammatory modulation[68,69,70,71,72,73,74,85]
Redox compartmentalizationLocalized ROS and electrophile signalingSpatially restricted adaptive signalingContext-dependent tissue adaptation[76,77,78,79]
Inflammatory redox integrationCrosstalk between antioxidant and inflammatory signaling pathwaysCoordination of antioxidant buffering capacity and inflammatory primingSystems-level inflammatory recalibration[24,25,26,27,28,63,64,65,81,82]
Table 2. Tissue-Specific Redox Regulatory Nodes, Molecular Mechanisms, and Systems-Level Consequences of Controlled Ozone-Induced Oxidative Signaling.
Biological CompartmentRedox Regulatory NodeMolecular MechanismSystems-Level ConsequencePredominant Evidence ContextRepresentative References
Dermal fibroblastsKeap1–Nrf2 signaling axisElectrophile-mediated cysteine modification; induction of glutathione biosynthesis and peroxide-detoxifying enzymesReinforcement of intracellular redox buffering; modulation of matrix synthesis–degradation balanceIn vitro; selected in vivo models[24,25,26,63,64,65,66]
Dermal fibroblastsRedox modulation of cytokine networksAttenuation of NF-κB-dependent transcription; limitation of oxidant-driven amplification loopsShift toward matrix remodeling profiles compatible with reparative responsesIn vitro; selected in vivo models[27,28,34,35,36,37,38,39,40,41,42,43,44,45,66]
AdipocytescAMP-dependent metabolic signalingRedox-sensitive modulation of phosphodiesterase and kinase activity; indirect regulation of hormone-sensitive lipaseContext-dependent modulation of triglyceride mobilization and metabolic adaptationIn vitro; limited in vivo evidence[68,69,70,71,72,73,74,87,88]
Adipose tissueNrf2-driven metabolic adaptationInduction of antioxidant and NADPH-regenerating pathwaysRedox-mediated attenuation of oxidative stress-associated adipogenic signaling; potential immunometabolic rebalancingPredominantly in vitro[24,25,26,37,38,39,40,65,68,69,70,71,72,85]
MelanocytesRedox control of melanogenic enzymesModulation of intracellular oxidative tone affecting tyrosinase activity and thiol availabilityStabilization of melanogenic flux under controlled redox conditionsIn vitro[89,90,91,92]
MelanocytesRedox-sensitive transcriptional regulationIndirect modulation of microphthalmia-associated transcription factor activity via oxidative and inflammatory signalingRedox-mediated adjustment of pigment homeostasisIn vitro[26,66,89,90,91,92]
Innate immune cellsNLRP3 inflammasome regulationModulation of redox-associated activation signals; attenuation of caspase-1 activationPotential attenuation of pro-inflammatory cytokine maturationIn vitro and in vivo models[29,30,31,32,33,67,84]
Innate immune cellsNrf2 pathway–NF-κB signaling network interactionReinforcement of antioxidant transcriptional programs; modulation of inflammatory primingRecalibration of inflammatory signaling networksIn vitro and in vivo models[24,25,26,27,28,63,64,65,81,82]
Epidermal and dermal cellsRedox-dependent proteostasisMaintenance of thiol homeostasis; support of lysosomal and proteolytic functionPreservation of cellular turnover and structural integrityIn vitro; selected in vivo models[34,35,36,65,66]
Cutaneous–subcutaneous unitIntegrated redox network responseCoordinated transcriptional, metabolic, and inflammatory adaptation following localized redox perturbationSystems-level redox re-equilibration within a constrained adaptive rangeMechanistic integration of experimental evidence[11,12,15,16,24,25,26,27,28,68,69,70,71,72,76,77,78,79,80]
Table 3. Dose-Dependent Redox Responses to Ozone Exposure.
Ozone-Induced ConditionPredominant Redox EventsAdaptive ResponsesPotential Pathological ConsequencesRepresentative References
Low-dose/controlled exposureTransient electrophile formation; moderate peroxide generation; localized thiol oxidationNrf2 activation; antioxidant reinforcement; metabolic adaptation; reinforcement of redox buffering capacityMinimal or absent structural injury[11,12,15,16,24,25,26,63,64,65,95]
Intermediate exposureIncreased lipid oxidation; partial saturation of antioxidant buffering systemsContext-dependent adaptive signaling with variable tissue responsivenessModerate oxidative stress and inflammatory amplification[21,22,23,55,56,57,60,61,62,63,64,65,76,77,78,79,80]
Excessive exposureROS amplification; thiol depletion; mitochondrial dysfunction; propagation of lipid oxidationFailure of adaptive redox compensationProtein oxidation; inflammasome activation; tissue injury; inflammatory amplification[21,22,23,30,31,32,33,55,56,57,58,67,68,69,70,71,72,73,74,75]
Table 4. Representative Candidate Biomarkers for Translational Evaluation of Ozone-Induced Redox Responses.
Biological ProcessRepresentative BiomarkersCommon Biological MatrixPotential Translational RelevanceRepresentative References
Oxidative damageProtein carbonyls; 4-HNE; lipid hydroperoxidesTissue; plasma; wound exudateAssessment of oxidative injury[21,22,23,55,56,57,58,59]
Adaptive redox signalingGSH/GSSG ratio; HO-1; NQO1; expression of Nrf2 target genesTissue; bloodEvaluation of adaptive redox responses[24,25,26,60,61,62,63,64,65]
Inflammatory activationIL-1β; TNF-α; IL-6; NLRP3-related markersBlood; wound exudate; tissueAssessment of inflammatory modulation[27,28,29,30,31,32,33,67,81,82,84]
Integrated biomarker assessmentCombined evaluation of oxidative damage, adaptive redox signaling, and inflammatory biomarkersBlood and/or tissueIntegrated evaluation of biological responses[7,46,50,51]
Note. The biomarkers listed above represent candidate biomarkers currently used in mechanistic and translational studies. They should not be regarded as validated clinical endpoints or standardized surrogate markers of tissue-specific redox reserve or therapeutic response.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.