1. Introduction
Heart rate variability (HRV) is an important physiological marker reflecting autonomic nervous system function and has been widely associated with cardiovascular risk and overall health status [
1,
2]. Reduced HRV has also been shown to predict future cardiovascular events in large longitudinal cohort studies such as the Framingham Heart Study [
3]. In addition, HRV exhibits pronounced temporal variability at both individual and population levels, with well-documented patterns across multiple time scales, including circadian and seasonal variations. Multi-ethnic cohort studies such as the MESA study have further demonstrated that HRV distributions vary across sex and racial groups, highlighting substantial inter-individual variability [
4].
Previous studies have reported clear seasonal variation and regional differences in HRV. Large-scale population-based studies have demonstrated substantial variation in HRV across demographic and population characteristics [
5,
6]. In Japan, analyses using the nationwide Holter electrocardiogram (ECG) database, ALLSTAR (Allostatic State Mapping by Ambulatory ECG Repository), have further examined seasonal variation in HRV and its association with regional variability [
7]. However, these studies have primarily focused on HRV itself, and the role of physical activity (PA) has not been fully investigated due to the limited availability of concurrent activity data.
PA is a major behavioral factor influencing HRV, and prospective cohort studies have demonstrated associations between habitual physical activity and HRV [
8]. Since PA also exhibits seasonal variation and regional differences, it is considered a key candidate factor underlying seasonal HRV variation. Recent large-scale cohort studies using device-measured PA have advanced population-level PA assessment and health outcome analyses [
9,
10]. However, although big data analyses of HRV and PA have rapidly advanced, most previous studies have focused on average associations, and investigations explicitly targeting seasonal HRV variation remain limited.
An additional important aspect is the presence of HRV variation that cannot be explained by PA. Seasonal variation in HRV can be conceptually characterized by components associated with PA and residual variation not explained by PA, arising from other factors such as environmental conditions, psychological stress, and lifestyle patterns. In particular, it remains unclear whether regional differences in HRV are primarily reflected in responsiveness to PA or in the unexplained component.
In this study, we used a weighted least squares framework incorporating accelerometry-derived PA to examine seasonal HRV variation. This approach enables an integrated evaluation of population-level consistency in HRV responsiveness to PA (slope) and the regional heterogeneity of unexplained variability (residual component).
We define the period from April 2015 to March 2020 as the “normal period” and use it as a baseline representing daily life under minimal social restrictions. In contrast, the period from April 2020 to March 2021 (COVID-19 period) is treated as a natural experiment to examine changes in the PA–HRV relationship under altered societal and behavioral conditions.
Using a large-scale dataset of over 130,000 Holter ECG recordings from eight regions across Japan in the ALLSTAR database, we compared the normal and COVID-19 periods to quantify the association between PA and seasonal HRV variation and to characterize region-specific residual variability not explained by PA.
2. Materials and Methods
2.1. ALLSTAR Big Data Repository
The ALLSTAR project was established to enable large-scale analysis of cardiovascular and autonomic nervous system function under real-world conditions and has been widely used in studies of HRV, sleep physiology, and lifestyle-related cardiovascular characteristics [
11].
The database consists of anonymized electrocardiogram (ECG) recordings collected during routine clinical practice at medical institutions across Japan, along with basic demographic and recording information. Most recordings were obtained using wearable Holter ECG devices (Cardy 303 pico+, Suzuken Corporation, Nagoya, Japan) equipped with tri-axial accelerometers, allowing simultaneous acquisition of ECG signals and PA data during unrestricted daily life. In these devices, ECG and acceleration signals were digitized at sampling rates of 125 Hz and 31.25 Hz, respectively. The database may contain both single recordings and repeated recordings from the same individual, reflecting its origin in routine clinical practice.
Because the ALLSTAR data were collected for clinical purposes rather than under controlled experimental conditions, the dataset includes a heterogeneous population with diverse physiological and clinical backgrounds, including both individuals undergoing routine screening and patients with suspected or diagnosed diseases. Accordingly, the recordings reflect real-world physiological states influenced by multiple interacting factors, such as underlying conditions, medication use, behavioral patterns, and environmental factors.
Importantly, these factors were not controlled in the present study, and the observed associations may therefore be subject to potential confounding. Consequently, the relationships identified in this study should not be interpreted as strict causal effects but rather as integrated physiological responses under natural conditions. This heterogeneity is not merely a limitation but represents an essential characteristic of large-scale real-world data.
The data analyzed in this study were obtained from records collected between 1 April 2015 and 31 March 2021, during which tri-axial accelerometry was available. From this dataset, we extracted a subset of ALLSTAR records with simultaneous ECG and tri-axial acceleration measurements to examine the relationship between PA and seasonal variation in HRV indices. Further details of the ALLSTAR project and recording procedures have been described elsewhere [
12].
2.2. Study Population and Data Selection
From the ALLSTAR database, we extracted records in which ECG data and tri-axial acceleration data were simultaneously recorded. A total of 136,533 records were included in the present study.
To ensure data quality and physiological interpretability, records were selected based on the following criteria: (1) sinus rhythm accounted for at least 80% of the recording, and (2) the total recording duration was at least 80% of a 24-h measurement. In addition, records with atrial fibrillation (AF) and pacemaker rhythms were excluded from the analysis. Premature atrial and ventricular beats identified by the Holter analysis system (Cardy Analyzer 05, Suzuken Corporation, Nagoya, Japan) were removed from the RR interval series and corrected using spline interpolation prior to HRV analysis.
The dataset comprised individuals across a wide age range (20s to 80s) and exhibited non-uniform distributions across both geographic regions and years. Because the number of records per year was insufficient to reliably estimate seasonal variation, data from multiple years were combined.
Specifically, records collected between April 2015 and March 2020 were aggregated and used as the primary analysis period (normal period), representing typical conditions before the COVID-19 period. In addition, records from April 2020 to March 2021 were analyzed separately as a secondary analysis period (COVID-19 period), corresponding to substantial behavioral and environmental changes associated with COVID-19.
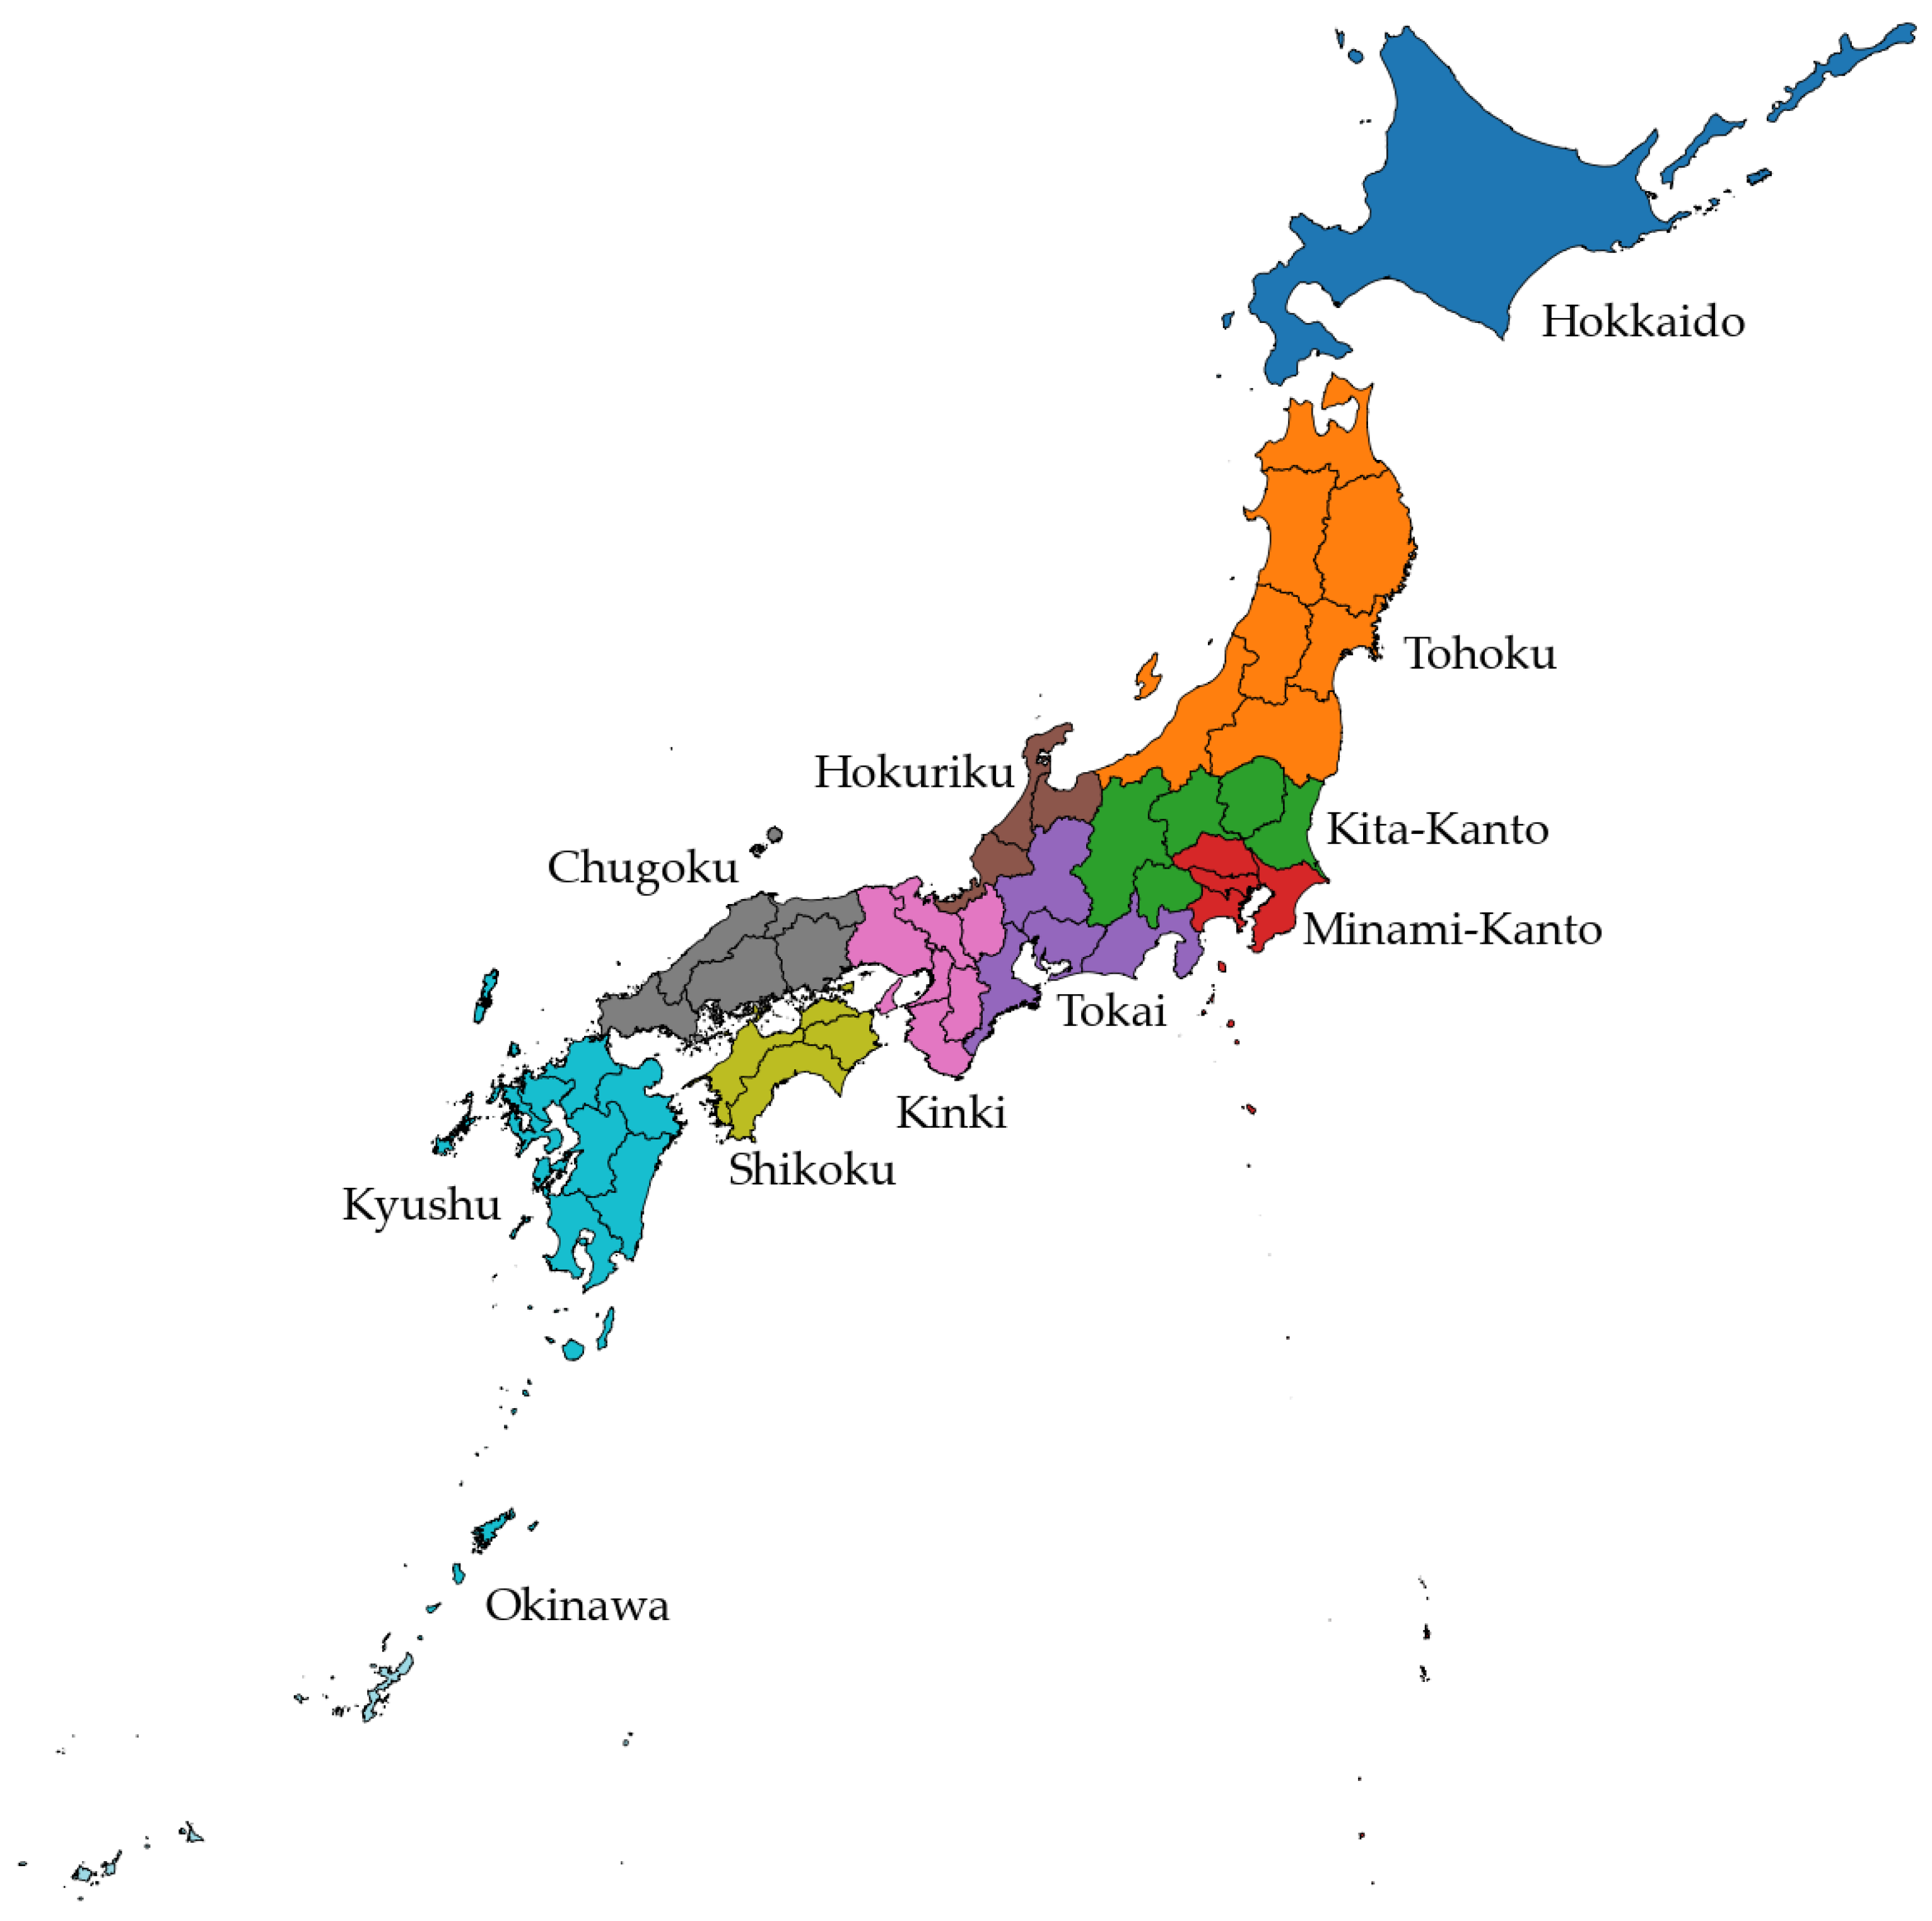
For regional analysis, as shown in
Figure 1, subjects were initially classified into 11 geographic regions within Japan (Hokkaido, Tohoku, Kita-Kanto, Minami-Kanto, Tokai, Hokuriku, Kinki, Chugoku, Shikoku, Kyushu, and Okinawa) based on the regional classification defined by the Cabinet Office of Japan [
13]. However, three regions (Chugoku, Shikoku, and Okinawa) were excluded from the main analysis due to substantially smaller sample sizes compared to the other regions. In these regions, the limited number of records within certain age groups and periods could lead to unstable estimation of seasonal variation metrics. After exclusion, a total of 133,747 records remained for the regional analysis. Accordingly, the final analysis was conducted using eight regions (Hokkaido, Tohoku, Kita-Kanto, Minami-Kanto, Tokai, Hokuriku, Kinki, and Kyushu), which contained substantially larger numbers of records than the excluded regions and therefore provided more stable subgroup-level seasonal variation estimates. This classification was used to evaluate spatial heterogeneity in the relationship between PA and HRV indices.
The numbers of records by region and by age group for each analysis period are summarized in
Table 1 and
Table 2, respectively. Values represent the number of records, with the proportion of female participants indicated in parentheses. The distributions of records across regions and age groups were non-uniform, reflecting the real-world nature of the dataset.
2.3. Calculation of HRV and PA
- (a)
HRV indices
HRV indices were calculated from 24-h R–R interval (RRI) time series. The RRI series was resampled at 2 Hz using interpolation, followed by frequency-domain analysis using the fast Fourier transform (FFT). Time-domain indices included mean RRI (ms) and the standard deviation of RRI (SDRR, ms). Frequency-domain indices included ultra-low frequency (ULF, <0.0033 Hz), very-low frequency (VLF, 0.0033–0.04 Hz), low frequency (LF, 0.04–0.15 Hz), high frequency (HF, 0.15–0.40 Hz), and the LF/HF ratio [
1].
Frequency-domain indices were defined as the integrated power within each frequency band of the power spectral density (PSD), i.e., the area under the spectrum, and were natural log-transformed (ln).
SDRR reflects the overall magnitude of HRV. ULF has been associated with long-term regulatory processes, including circadian influences, whereas VLF, LF, and HF are thought to reflect multiple physiological mechanisms, including autonomic, behavioral, and environmental factors. HF is commonly associated with parasympathetic modulation, while LF has been associated with baroreflex-related regulation and other physiological influences; however, the physiological interpretation of these frequency-domain components remains complex, particularly in long-term ambulatory recordings [
14]. The LF/HF ratio has traditionally been used as a marker related to autonomic regulation, although its physiological interpretation remains controversial and context-dependent [
15].
- (b)
PA index
PA was defined using the vector magnitude of tri-axial acceleration to provide a unified measure of movement intensity at each time point. The coordinate system was defined such that the x-axis represented the rightward direction, the y-axis the downward vertical direction, and the z-axis the forward direction.
The vector magnitude
A(
t) was calculated as the Euclidean norm of the three acceleration components:
where
x(
t),
y(
t), and
z(
t) represent the acceleration components at time t along each axis. The raw signals were corrected for offset and gain to reduce sensor-specific bias and scaling effects.
The tri-axial acceleration components were first combined to obtain a resultant acceleration signal. The resulting signal was resampled at 10 Hz and processed using a high-pass finite impulse response (FIR) filter with a cutoff frequency of 0.5 Hz to remove low-frequency components related to gravity and posture, based on previously reported methods for deriving activity-related fluctuation components from tri-axial acceleration signals [
16]. The absolute value of the filtered signal was then taken to obtain a non-negative activity intensity measure reflecting the magnitude of movement. PA was defined as the time-integrated (summed in discrete form) value of this activity intensity signal, normalized by the recording duration
T (hours):
where
AHP(
t) denotes the high-pass filtered acceleration signal. Finally, an log10 transformation was applied to reduce skewness and improve suitability for statistical analysis.
2.4. Definition of Seasonal Variation Metrics
To quantify seasonal variation, the mean values of HRV indices and PA were computed for each region r, group g, and season s, denoted as HRVg,r,s and, PAg,r,s, respectively.
Seasonal variation was defined as the difference between the maximum and minimum seasonal mean values:
The HRV indices analyzed were defined as:
Seasons were defined as spring (April–June), summer (July–September), autumn (October–December), and winter (January–March). The subgroup g was defined by the combination of sex (male, female) and age group (20s, 30s, …, 80s). Each subgroup was represented by seasonal mean values calculated from all available records within the subgroup.
In the present study, seasonal variation was defined as the difference between the maximum and minimum seasonal mean values (max–min) to directly capture the amplitude of seasonal fluctuation, consistent with previous ALLSTAR-based analyses of seasonal HRV variation [
7]. The primary objective of the present study was to evaluate the magnitude of seasonal variation rather than its detailed temporal dynamics. Therefore, a max–min metric was adopted as a simple and interpretable measure of seasonal amplitude that can be applied consistently across HRV indices and PA.
Seasonal means were used because they reflect the overall level of the population within each season after averaging individual differences and short-term variability. Although alternative approaches such as harmonic regression, cyclic regression, or time series decomposition may provide a more detailed characterization of seasonal dynamics, these methods were beyond the scope of the present study, which focused on comparing seasonal variation amplitude across subgroups and physiological indices.
Although alternative robust measures such as medians or percentile-based indices are less sensitive to outliers, they primarily represent typical values and are less suitable for capturing changes in the overall population level (i.e., amplitude), which was the primary objective of this study. While mean values can be influenced by outliers, the seasonal means in this study were derived from multiple records within each subgroup, thereby mitigating the impact of individual extreme values. Furthermore, because seasonal variation was derived from four aggregated seasonal values, percentile-based measures (e.g., interquartile range or percentile ranges) were not applicable.
For the weighted least squares (WLS) analysis, aggregated observations were further defined by combining sex (2 categories), age group (7 categories), and region (8 categories), resulting in 112 subgroup-level observations for each HRV index (2 × 7 × 8). Each observation represented a seasonal variation index derived from subgroup-level averages. Because the number of underlying records varied across subgroups, the precision of the estimated seasonal variation indices was expected to differ across observations. Therefore, WLS regression was adopted, with weights defined as the square root of subgroup sample size (). This weighting scheme allowed observations derived from larger samples to contribute more strongly to model fitting while avoiding excessive dominance of very large groups. Region was included as a fixed effect in the WLS models, and cluster-robust standard errors were calculated using region as the clustering unit to account for potential within-region dependence and heteroscedasticity.
Because the analysis was conducted using aggregated seasonal variation metrics, the estimated associations should be interpreted as subgroup-level covariation rather than individual-level relationships.
2.5. Statistical Analysis for Hypothesis Testing
2.5.1. Hypothesis 1 (Additional Explanatory Value of PA)
We hypothesized that seasonal Δ
HRV cannot be sufficiently explained by sex, age, and regional differences alone and that incorporating seasonal Δ
PA would significantly improve model performance. To test this hypothesis, two nested WLS were constructed and compared. Baseline model:
The association of ΔPA with seasonal HRV variation was evaluated by assessing the improvement in model fit after including ΔPA.
2.5.2. Hypothesis 2 (Sex Differences)
We hypothesized that the relationship between Δ
PA and Δ
HRV differs by sex, such that the sensitivity of HRV responses to PA varies between males and females. To test this hypothesis, an interaction term between Δ
PA and sex was included:
The significance of the interaction term β5 was used to evaluate sex differences in the ΔPA–ΔHRV relationship.
2.5.3. Hypothesis 3a (Regional Heterogeneity in Sensitivity)
We hypothesized that the relationship between Δ
PA and Δ
HRV varies across regions even after accounting for sex and age. To test this hypothesis, a WLS model including interaction terms between Δ
PA and region was constructed:
In this model, significant interaction terms (ΔPA × Region) indicate regional heterogeneity in the sensitivity of HRV responses to PA.
2.5.4. Hypothesis 3b (Residual Variability)
We hypothesized that the unexplained component of seasonal HRV variation exhibits region-specific variability. To test this hypothesis, residuals obtained from the WLS model including interaction terms (Hypothesis 3a) were defined as:
where the fitted values
were obtained from the model described in Hypothesis 3a.
The residuals were treated as the unexplained component, and their variance and distributional characteristics were compared across regions. Regional differences in residual variance were evaluated using Levene’s test.
2.5.5. Statistical Analysis
All statistical analyses were performed using Python 3.12.7. WLS were implemented using the statsmodels.formula.api module, and Levene’s test was conducted using scipy.stats.levene from the SciPy library. Statistical significance was set at a two-sided p-value of 0.05. Because multiple HRV indices were analyzed simultaneously, p-values were adjusted for multiple comparisons using the Benjamini–Hochberg false discovery rate (FDR) procedure, and FDR-adjusted p-values were used to determine statistical significance where applicable.
To assess the data distribution, the distribution of PA was examined using histograms and descriptive statistics.
Regression coefficients (β) represent the estimated associations obtained from the WLS models at the subgroup level, reflecting the relationship between ΔPA and ΔHRV across aggregated subgroups.
Because the analysis was based on subgroup-level data, these associations may be subject to ecological bias and do not necessarily reflect individual-level relationships. The interaction term (ΔPA × Sex) represents the difference in the ΔPA–ΔHRV relationship between sexes.
3. Results
3.1. Distribution of PA
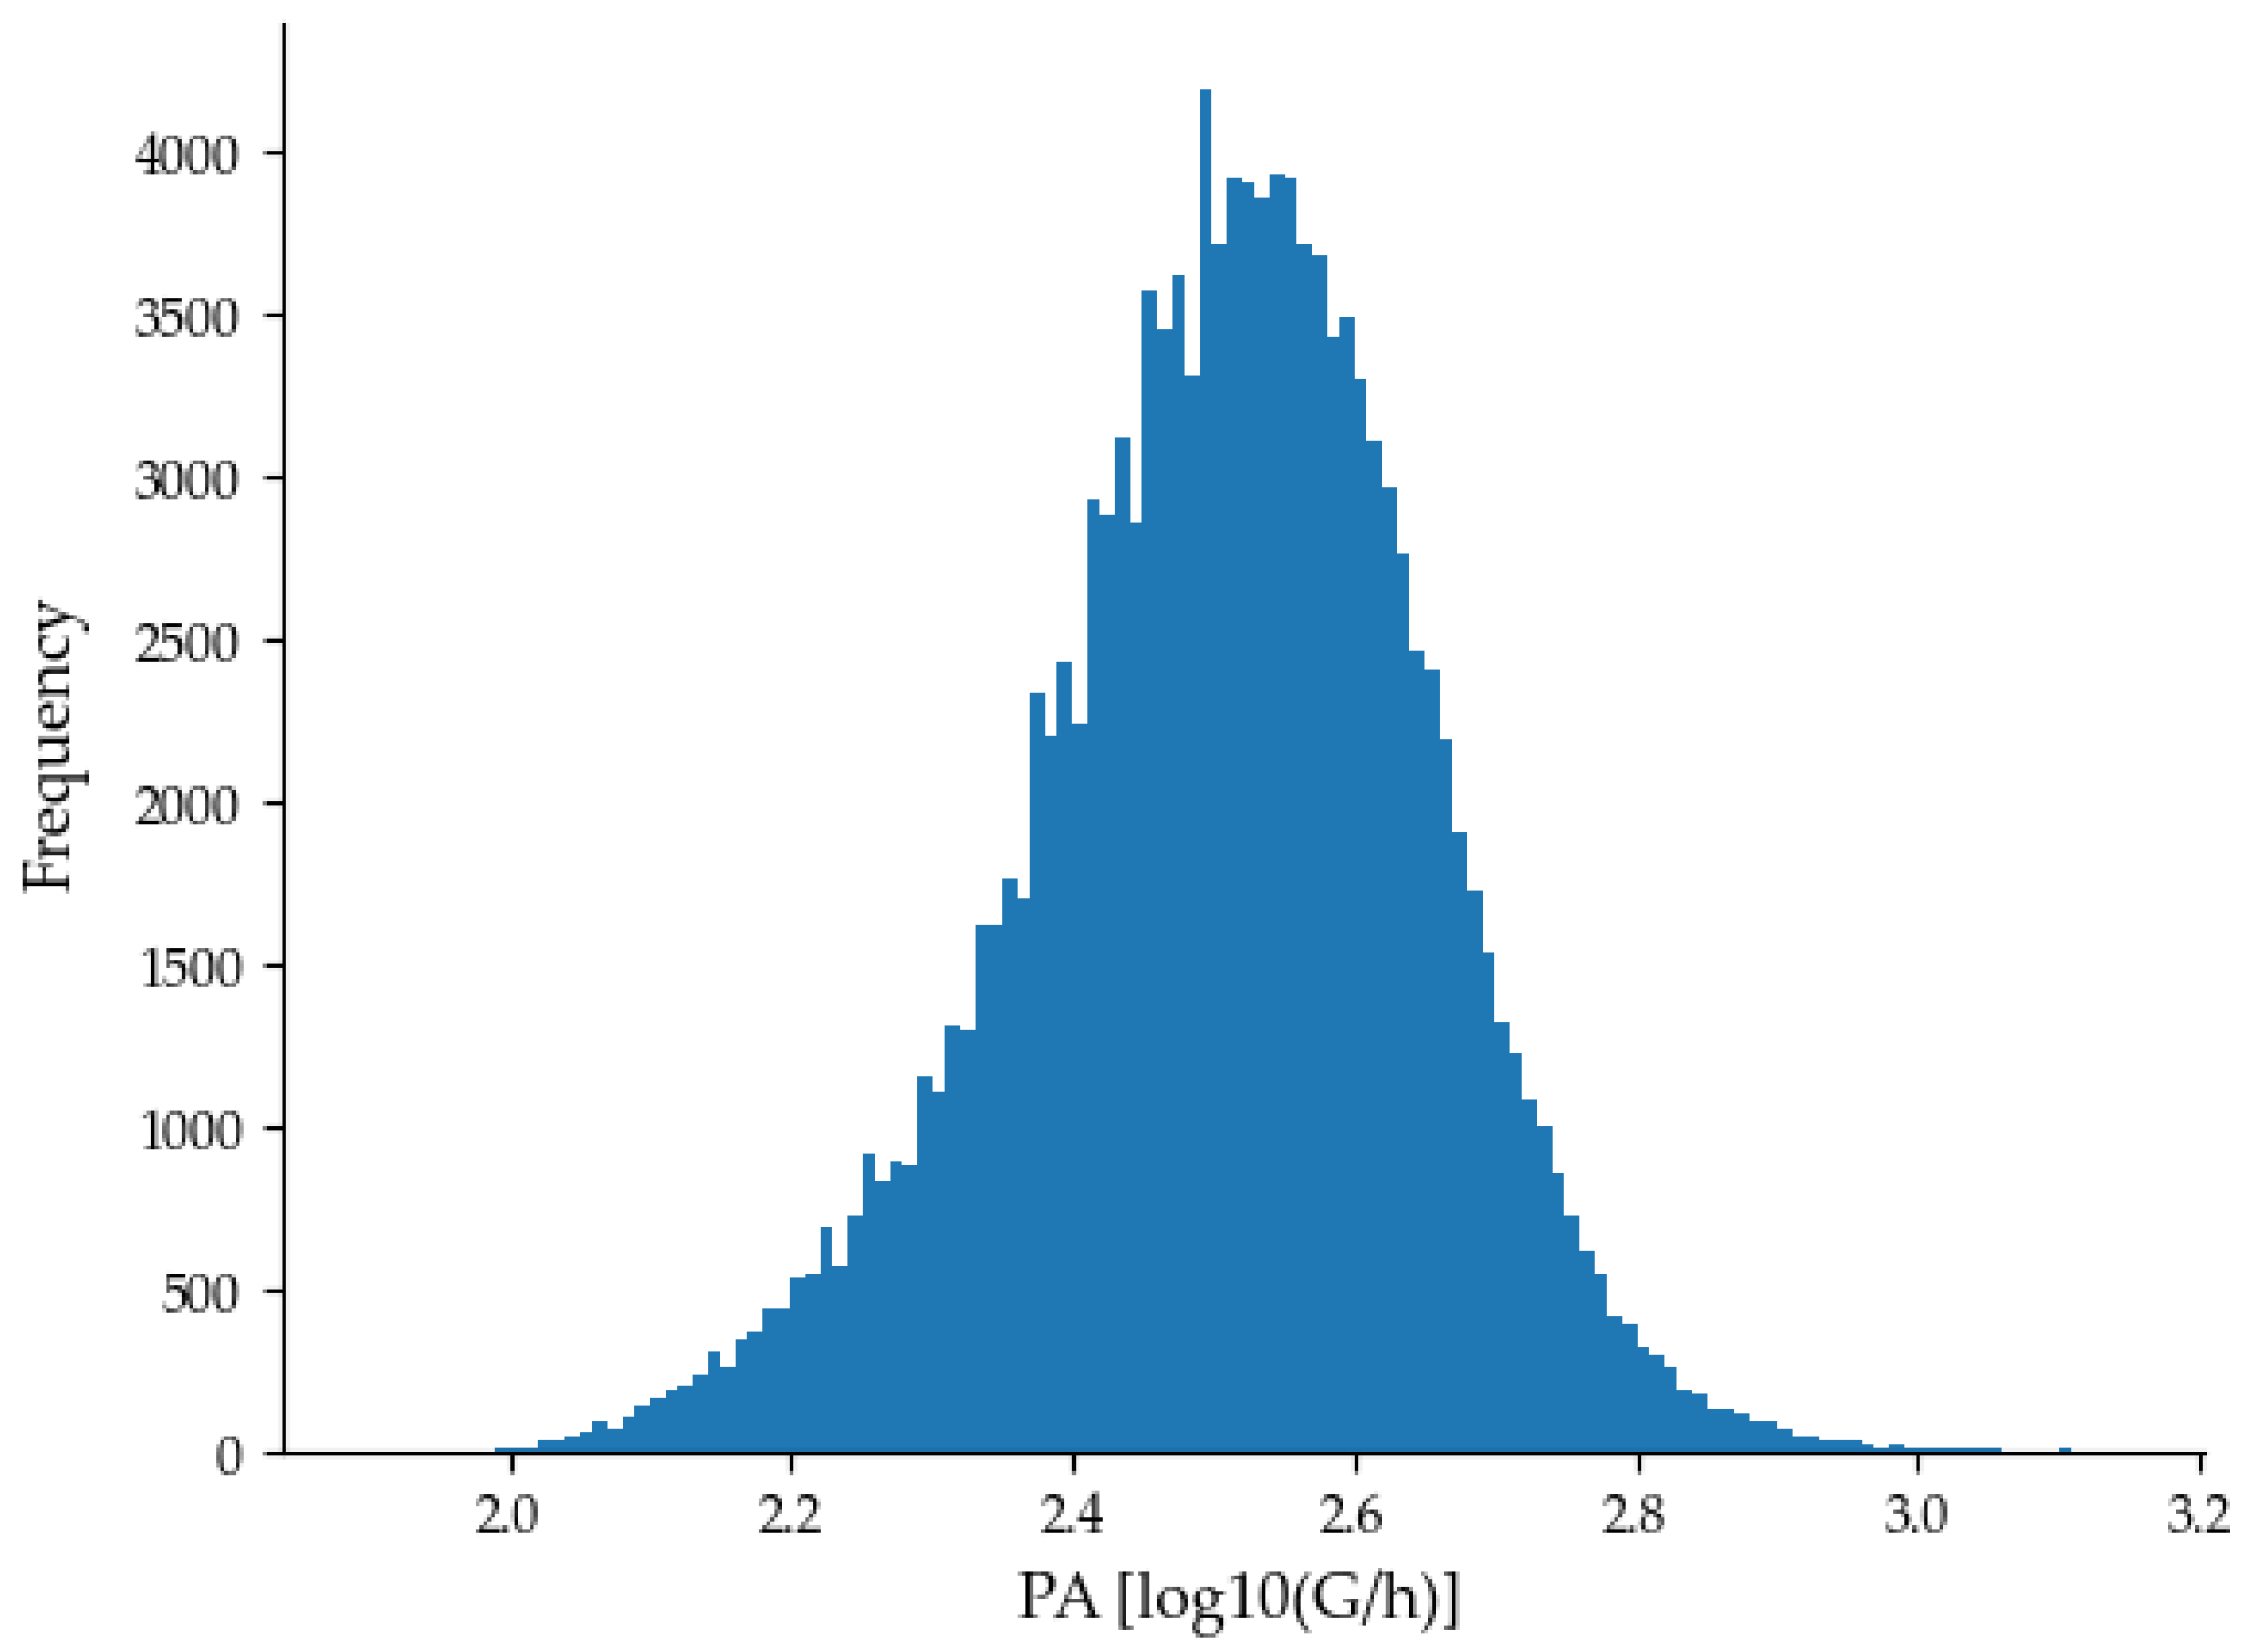
The distribution of PA was evaluated. PA showed a mean of 2.508 ± 0.148 and a median of 2.516 (range: 1.925–4.665). The distribution was approximately symmetric (skewness = −0.100, kurtosis = 1.037), with no apparent skewness or outliers (
Figure 2).
3.2. Association Between PA and Seasonal HRV Variation (Hypotheses 1 and 2)
The association between Δ
PA and Δ
HRV was evaluated separately for the normal and COVID-19 periods (
Table 3). During the normal period, significant associations between Δ
PA and Δ
HRV indices were observed for several indices. Specifically, significant positive associations were found for Δ
ULF (
β = 0.300,
p = 0.008), Δ
VLF (
β = 0.206,
p = 0.013), Δ
HF (
β = 0.454,
p = 0.011), and Δ
LF/
HF (
β = 0.216,
p = 0.006), whereas no significant associations were observed for Δ
RRI, Δ
SDRR, or Δ
LF (all FDR-adjusted
p ≥ 0.05).
In contrast, during the COVID-19 period, significant associations were observed for ΔRRI (β = 229.31, p < 0.001), ΔSDRR (β = 39.90, p = 0.013), and ΔLF/HF (β = 0.190, p = 0.015), whereas no significant associations were found for ΔULF, ΔVLF, ΔLF, or ΔHF (all FDR-adjusted p ≥ 0.05). The interaction between ΔPA and sex (ΔPA × Sex) showed no significant effects after FDR correction in either period (all FDR-adjusted p ≥ 0.05).
Model comparisons between the baseline models and the models including Δ
PA are summarized in
Table 4 and
Table 5. In the normal period, inclusion of Δ
PA resulted in changes in AIC ranging from −8.83 to 0.27, changes in BIC ranging from −6.11 to 2.99, and increases in adjusted
R2 ranging from 0.004 to 0.039. In the COVID-19 period, changes in AIC ranged from −11.74 to 1.02, changes in BIC from −9.02 to 3.74, and changes in adjusted
R2 from −0.001 to 0.063.
3.3. Regional Differences in HRV Sensitivity to PA (Hypothesis 3a)
To evaluate regional differences in the relationship between Δ
PA and Δ
HRV, weighted least squares models including interaction terms (Δ
PA × Region) were applied (
Table 6).
In the normal period, several HRV indices showed significant regional differences in the Δ
PA–Δ
HRV relationship. Significant interaction terms were observed across all HRV indices, and representative regional slope differences are presented in
Table 6. The direction and magnitude of these effects varied by region, indicating heterogeneous relationships between Δ
PA and Δ
HRV.
In the COVID-19 period, significant interaction terms were also observed across HRV indices, indicating that regional differences in the ΔPA–ΔHRV relationship persisted. However, the patterns of regional slope differences differed from those observed in the normal period.
The reference slope (β for ΔPA) was significant for ΔVLF, ΔHF, and ΔLF/HF in the normal period, whereas in the COVID-19 period, none of the reference slopes reached statistical significance.
3.4. Regional Heterogeneity of the Unexplained Component (Hypothesis 3b)
To evaluate regional differences in the unexplained component of Δ
HRV, residual variance was compared across regions using Levene’s test (
Table 7). In the normal period, significant regional differences in residual variance were observed for Δ
SDRR, Δ
VLF, Δ
LF, and Δ
HF after FDR correction, whereas no significant differences were found for Δ
RRI, Δ
ULF, or Δ
LF/
HF. In the COVID-19 period, significant regional differences in residual variance were observed for Δ
RRI, Δ
ULF, Δ
VLF, Δ
LF, Δ
HF, and Δ
LF/
HF after FDR correction, while Δ
SDRR did not show significant differences.
To further characterize these patterns, regions were classified based on residual variability during the normal period (
Table 8). Residuals were derived from models including sex, age, Δ
PA, and region effects. Hokuriku exhibited relatively high residual variability across multiple HRV indices, whereas Minami-Kanto tended to show relatively low variability. Intermediate patterns varied depending on the HRV index. For example, Kyushu and Tohoku frequently appeared among regions with relatively high residual variability for certain indices, whereas Tokai, Kinki, and Hokkaido tended to exhibit moderate or relatively lower variability depending on the index.
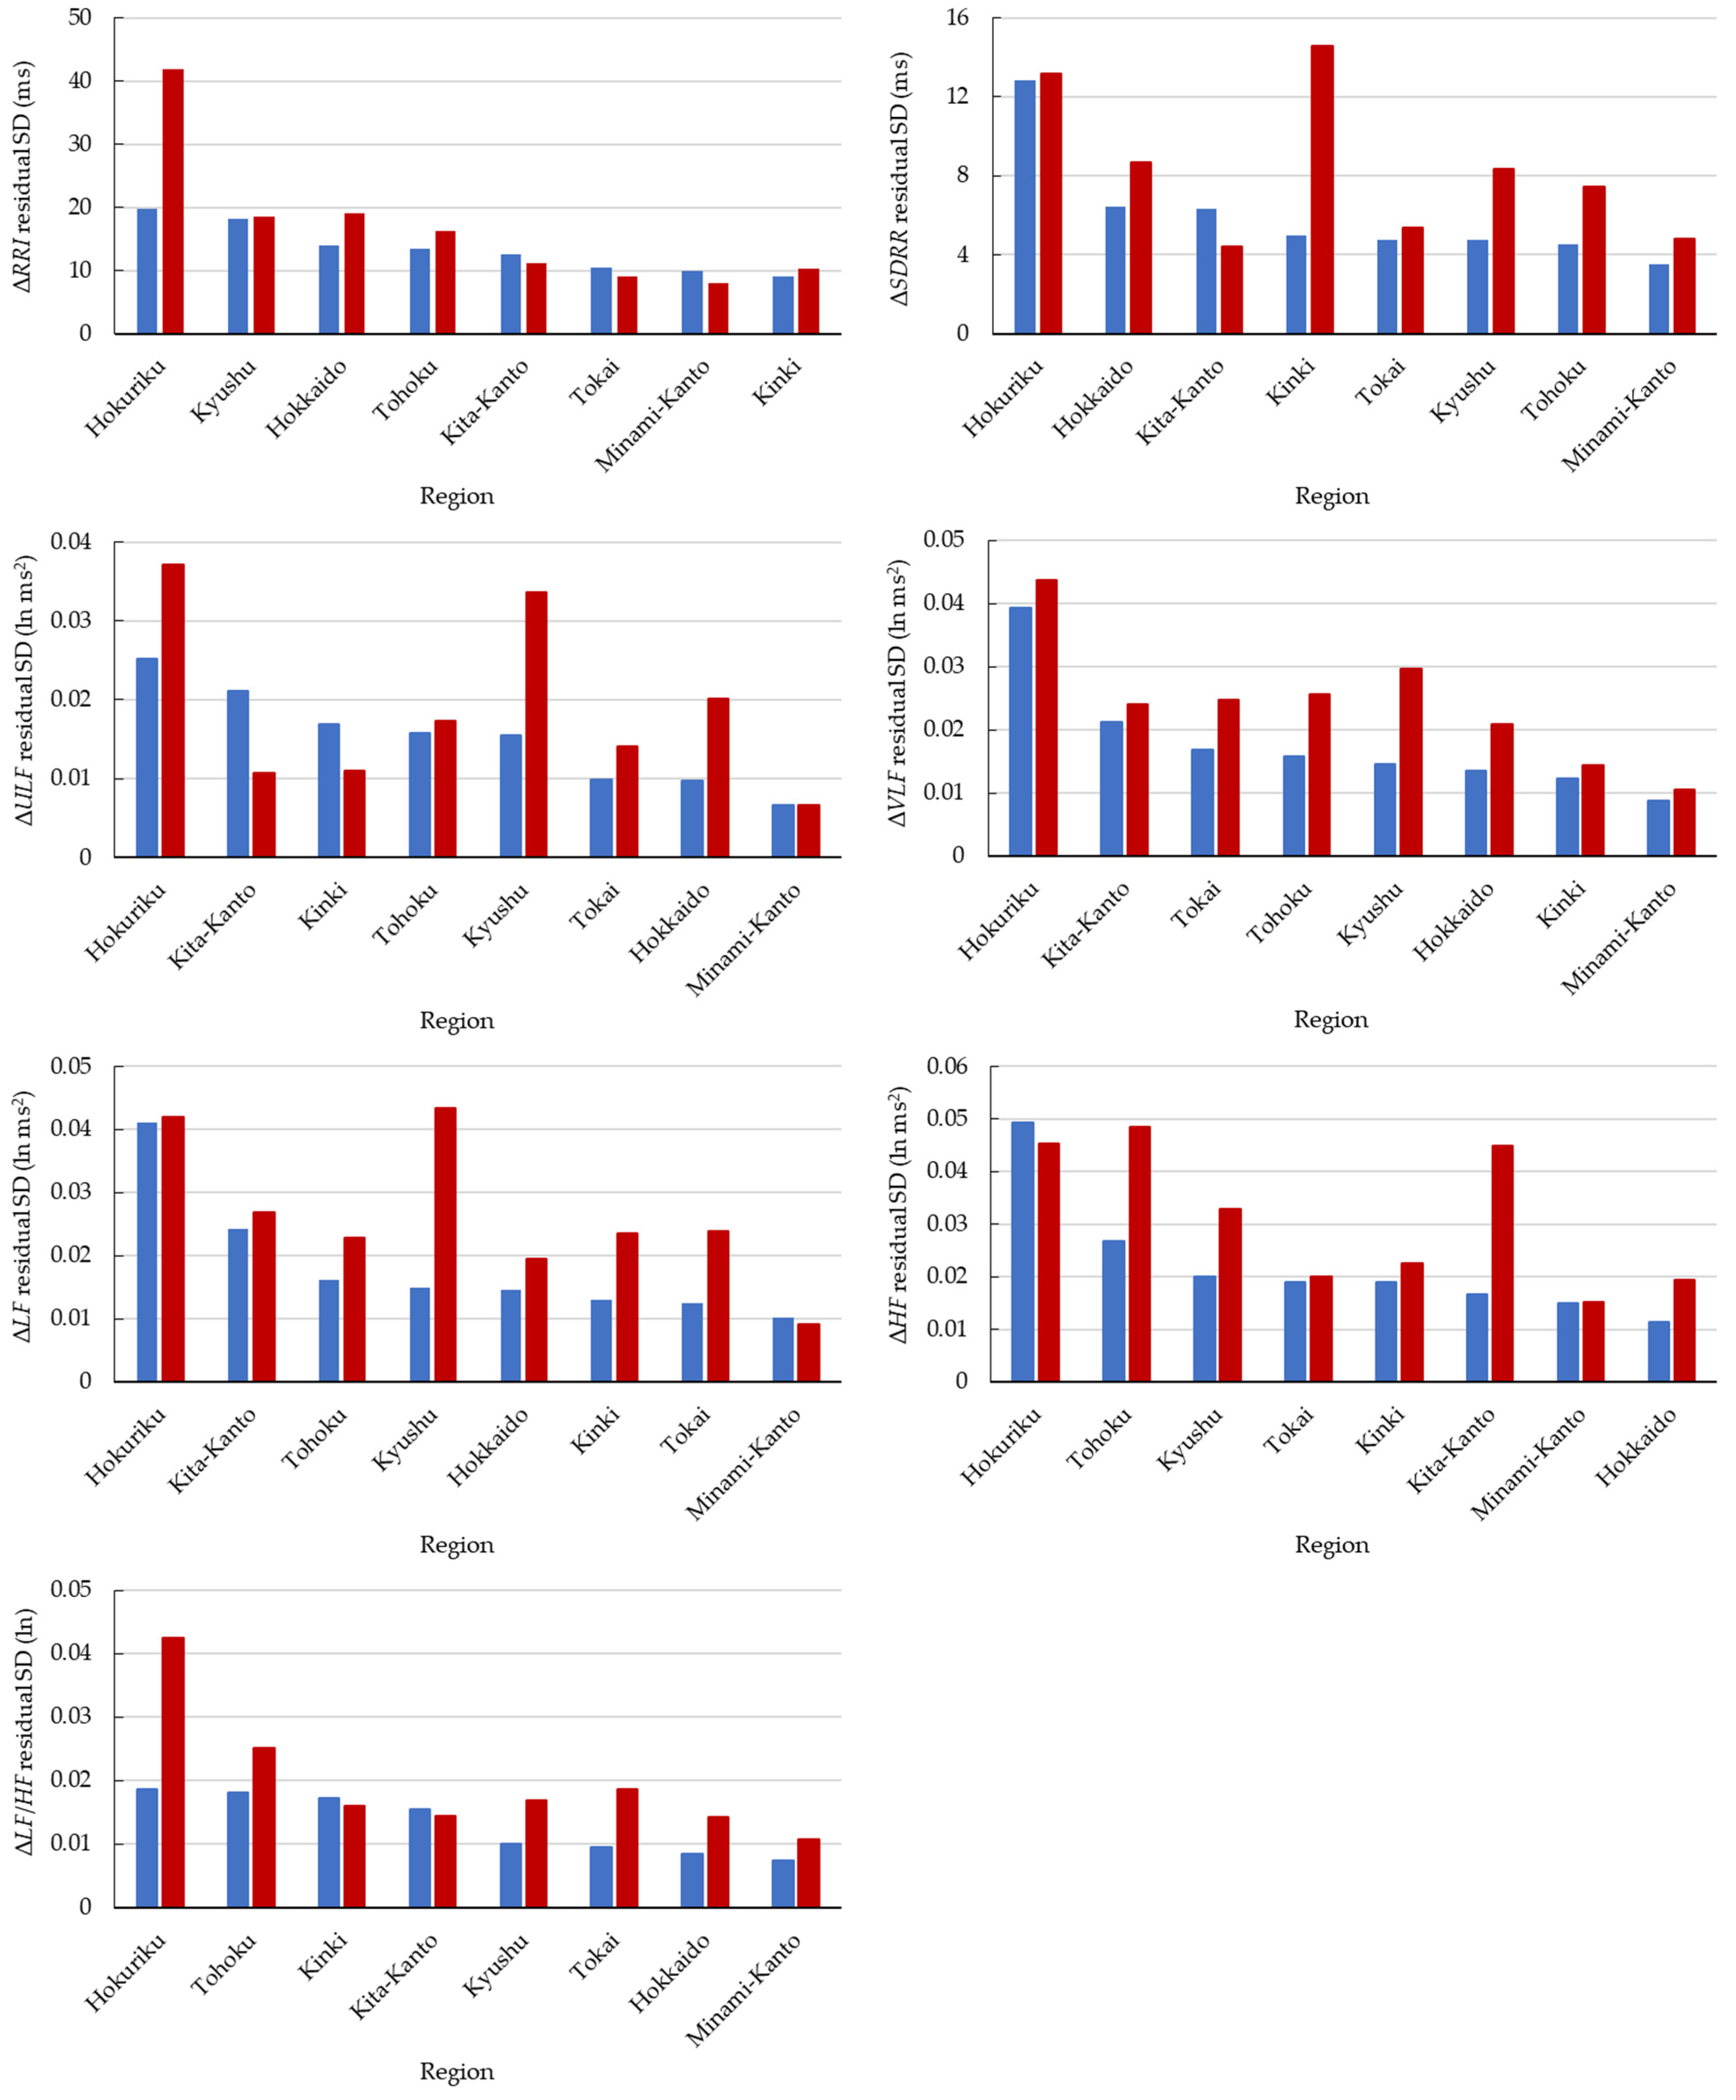
Figure 3 illustrates regional patterns of residual variability across HRV indices during the normal and COVID-19 periods. Regions are ordered based on residual variability in the normal period. In the normal period, consistent regional patterns were observed across multiple HRV indices, with Hokuriku showing the highest residual variability for most indices and Minami-Kanto showing the lowest variability. Other regions exhibited intermediate variability, although their relative rankings varied depending on the HRV index.
During the COVID-19 period, changes in residual variability were heterogeneous across regions and indices. Some regions, such as Hokuriku and Kyushu, showed increases in variability for certain indices, whereas other regions exhibited smaller changes or decreases. In addition, shifts in the relative ranking of regions were observed for several HRV indices, indicating changes in the regional heterogeneity of the unexplained component.
3.5. Summary of Hypothesis Testing Results
The results of hypothesis testing regarding the relationship between PA and HRV are summarized in
Table 9.
For Hypothesis 1 (main effect of ΔPA), significant associations were observed for specific HRV indices during the normal period, including ΔULF, ΔVLF, ΔHF, and ΔLF/HF, whereas other indices were not significant. During the COVID-19 period, the pattern differed, with significant associations observed for ΔRRI, ΔSDRR, and ΔLF/HF, while the remaining indices showed no significant associations.
For Hypothesis 2 (ΔPA × Sex interaction), no significant interactions were observed after FDR correction for any HRV index in either period.
For Hypothesis 3a (regional differences in the ΔPA–ΔHRV relationship), significant regional interaction effects (ΔPA × Region) were observed across all HRV indices in both periods, indicating that the association between ΔPA and ΔHRV varied by region.
For Hypothesis 3b (regional differences in residual variance), significant regional differences were observed for multiple HRV indices in both periods. In the normal period, significant differences were observed for ΔSDRR, ΔVLF, ΔLF, and ΔHF, whereas in the COVID-19 period, significant differences were observed for ΔRRI, ΔULF, ΔVLF, ΔLF, ΔHF, and ΔLF/HF.
4. Discussion
4.1. Overview of Findings
This study aimed to characterize subgroup-level seasonal HRV variation in relation to PA and the residual variability not explained by PA within the current model.
The results suggest that seasonal HRV variation is not explained by a single dominant factor but instead consists of multiple interacting determinants. Specifically, the findings indicate that (1) the association with PA is index-specific, (2) sex-dependent modulation was not statistically supported after FDR correction in either period, and (3) regional heterogeneity is primarily expressed in the unexplained residual component rather than in the direct PA–HRV relationship.
These results collectively suggest that seasonal HRV variation reflects the combined influence of behavioral, regional, and other unmeasured contextual factors and cannot be adequately explained by a single determinant.
Given that reduced HRV has been shown to predict future cardiovascular events in large longitudinal cohort studies such as the Framingham Heart Study [
3], understanding the determinants of HRV variation is of particular clinical relevance.
Furthermore, the dominant source of HRV variation appears to shift from behavioral factors to region-specific heterogeneity when examined at the population level.
4.2. PA–HRV Association and COVID-19 Effect
Although PA is widely considered a major behavioral determinant of HRV, the present results indicate that the association with PA is index-specific, consistent with previous studies demonstrating associations between PA and HRV [
8]. During the normal period, significant associations between Δ
PA and Δ
HRV were observed only for specific indices, particularly Δ
ULF, Δ
VLF, Δ
HF, and Δ
LF/
HF, whereas other indices did not show significant relationships.
During the COVID-19 period, the pattern of association changed, with significant effects observed for ΔRRI, ΔSDRR, and ΔLF/HF, while the remaining indices showed no significant relationship. These findings suggest that the association of PA with seasonal HRV variation differs across HRV indices.
Previous studies have shown that HRV indices, particularly LF/HF, are strongly influenced by behavioral factors such as body posture. For example, LF/HF decreases with increasing time spent in a lying position during ambulatory monitoring [
17]. These findings support the interpretation that HRV variation is partly driven by behavioral factors such as PA.
The COVID-19 period can be interpreted as a natural experiment in which behavioral patterns and environmental conditions were substantially altered. Under these conditions, the PA–HRV relationship became less uniform and more index-specific, consistent with the interpretation that long-term HRV is influenced by multiple physiological, behavioral, and environmental factors beyond physical activity alone.
Previous studies have reported reductions in PA, increases in sedentary behavior, and elevated levels of psychological stress during the COVID-19 period [
18,
19,
20,
21]. These factors have been associated with changes in autonomic regulation and HRV in previous studies [
22]. However, because no direct measurements of psychological stress, behavioral changes, or other contextual factors were available in the present study, the mechanisms underlying the observed COVID-19-related differences cannot be determined directly. Therefore, the observed patterns should be interpreted as population-level associations that may reflect the combined influence of multiple behavioral, environmental, healthcare-related, and societal factors during the COVID-19 period.
The inclusion of ΔPA resulted in improvements in model fit, as indicated by reductions in AIC and BIC and increases in adjusted R2. However, the magnitude of these improvements was modest. These findings suggest that while subgroup-level seasonal variation in PA contributes to explaining subgroup-level seasonal variation in HRV, its explanatory power is limited, supporting the presence of substantial residual variability not captured by behavioral factors.
While most HRV indices showed consistent patterns between statistical significance and model improvement, Δ
LF exhibited a distinct pattern during the COVID-19 period. Although inclusion of Δ
PA substantially improved model fit for Δ
LF (
Table 5), the main effect of Δ
PA did not reach statistical significance. This suggests that the association between PA and Δ
LF is not well captured by a simple linear effect but may depend on interactions or subgroup-specific factors.
It should also be noted that the normal period (2015–2020) and COVID-19 period (2020–2021) differed substantially in duration. However, the primary outcome of the present study was seasonal variation, quantified as the difference between the maximum and minimum seasonal mean values. Accordingly, the comparison focused on the magnitude of seasonal variation rather than on direct comparisons of observation periods with different durations.
These findings should not be interpreted as evidence of causal effects of PA on HRV but rather as subgroup-level covariation reflecting shared seasonal drivers.
4.3. Sex Differences in the PA–HRV Relationship
Sex differences in the association between ΔPA and ΔHRV were limited in the present study. Although an interaction effect was observed for ΔSDRR during the normal period before correction, this effect did not remain statistically significant after FDR adjustment and should therefore be interpreted with caution.
These findings indicate that, at the subgroup level examined in this study, the relationship between seasonal PA variation and HRV variation is largely consistent across sexes. While previous studies have reported sex-related differences in HRV [
23,
24], such differences may be more strongly expressed at the individual level or under specific physiological conditions rather than in aggregated seasonal variation metrics.
It should be noted that non-significant results do not necessarily indicate the absence of sex-related modulation, but rather suggest that such effects, if present, are relatively small compared to other sources of variability, such as behavioral or regional factors.
Taken together, the present results suggest that sex plays a limited role in modulating the PA–HRV relationship at the population level in the context of seasonal variation.
4.4. Regional Effects: Slope Versus Residual Variability
A key finding of this study is that regional differences in HRV are not primarily expressed in the sensitivity to PA (slope), but rather in the unexplained residual component.
WLS models including ΔPA × Region interaction terms showed statistically significant regional differences in the PA–HRV relationship; however, the direction and magnitude of these effects varied across regions and HRV indices, indicating heterogeneous rather than uniform regional sensitivity to PA.
In contrast, residual variability exhibited clear and consistent regional differences across multiple HRV indices. These patterns were observed in both the normal and COVID-19 periods, although the specific indices showing significant differences varied between periods. Similar variability in HRV across demographic, population, and regional settings has been reported in previous large-scale studies [
5,
6,
7].
Regional classification based on residual variability revealed stable patterns, with Hokuriku consistently exhibiting high variability and Minami-Kanto showing low variability across indices, while other regions showed index-dependent intermediate patterns.
Although residual variability tended to be higher in regions with smaller sample sizes, this relationship was not strictly monotonic. Regions with comparable sample sizes exhibited different levels of variability, indicating that sample size alone cannot account for the observed regional heterogeneity, even after weighting by subgroup size.
These findings suggest that regional heterogeneity in HRV reflects region-specific factors not explained by PA within the current model. Such variability is consistent with findings from multi-ethnic cohort studies such as the MESA study, which have demonstrated substantial inter-individual differences in HRV across populations [
4].
The contrast between Hokuriku and Minami-Kanto may be related to differences in environmental conditions, climate, and lifestyle patterns. For example, Hokuriku is characterized by a colder climate and greater seasonal constraints on outdoor activity, whereas Minami-Kanto represents a highly urbanized environment with relatively stable living conditions, as described in climate reports for Japan [
25].
Previous studies have also reported that environmental and climatic factors, including temperature, influence autonomic regulation and HRV [
26,
27]. However, regional differences in HRV and their seasonal variation cannot be explained solely by climatic factors but instead reflect the combined influence of environmental and lifestyle-related factors [
7].
Furthermore, the COVID-19 period included phases of emergency declarations, relaxation of restrictions, and subsequent waves of infection, and these measures were not implemented uniformly across regions. The timing, duration, and intensity of restrictions varied across prefectures and over time, which may have contributed to regional differences in PA and HRV. Therefore, regional variation in public health measures may have partially contributed to the observed heterogeneity during the COVID-19 period.
In addition, differences in occupational structure, PA patterns, dietary habits, and healthcare access may contribute to the observed regional heterogeneity. Although Japan has a universal health insurance system [
28], regional differences in healthcare resources, referral patterns, and healthcare-seeking behavior may still influence the characteristics of the populations represented in the ALLSTAR database. These factors were not directly evaluated in the present study but are known to influence HRV through complex physiological, behavioral, and environmental pathways [
29,
30,
31] and are not directly captured by PA measurements. Therefore, they are likely reflected in the residual component of HRV variation and may contribute to the unexplained variability observed in the present study.
The residual component should not be interpreted as a direct indicator of regional autonomic characteristics. Rather, it may reflect the combined influence of multiple unmeasured health-related, behavioral, environmental, and socioeconomic factors. Accordingly, the observed regional residual variability should be interpreted as region-specific variability not captured by the current model rather than as evidence of latent autonomic organization.
4.5. Physiological Interpretation of HRV Indices
The physiological interpretation of HRV indices, particularly LF, HF, and LF/HF, remains controversial in long-term ambulatory recordings. Although HF is commonly associated with parasympathetic modulation and LF/HF has historically been interpreted as a marker of sympathovagal balance, these relationships are not universally accepted because 24-h recordings integrate multiple influences, including posture, physical activity, sleep, environmental exposure, and daily behavioral patterns [
14,
15].
Previous studies have shown that LF/HF varies systematically with behavioral factors such as body posture. For example, we previously reported that LF/HF decreased with increasing time spent in the lying position during ambulatory monitoring [
17]. These findings suggest that LF/HF reflects, at least in part, behavioral and environmental conditions encountered during daily life. Therefore, in the present study, LF/HF was interpreted primarily as an HRV index associated with behavioral and environmental conditions rather than as a direct quantitative measure of sympathovagal balance.
The present results indicate that the association between PA and seasonal HRV variation is strongly index-specific, reflecting differences in the underlying physiological mechanisms.
In particular, significant associations were observed for Δ
ULF and Δ
VLF during the normal period. ULF is known to reflect very long-term regulatory processes, including circadian rhythms, whereas VLF has been associated with vasomotor activity, thermoregulation, and metabolic processes [
1]. These components operate over extended time scales and are likely influenced by seasonal behavioral patterns such as physical activity and daily routines. Therefore, the observed associations suggest that long-term regulatory components of HRV are sensitive to behavioral modulation at the population level.
In contrast, HF, which is commonly associated with parasympathetic modulation, also showed significant associations with ΔPA, indicating that vagal regulation is partially modulated by behavioral factors such as physical activity. However, HF responses may also be influenced by psychological and environmental conditions, which may explain the variability observed across periods.
On the other hand, Δ
LF did not show statistically significant associations with Δ
PA in either period. LF is known to reflect both sympathetic and parasympathetic modulation and is closely associated with baroreflex-mediated cardiovascular regulation [
1,
32]. The absence of a significant association suggests that Δ
LF may represent a regulatory component that is less directly driven by behavioral factors such as PA and more influenced by intrinsic or complex physiological mechanisms.
Taken together, these findings indicate that different HRV indices reflect distinct physiological processes with varying sensitivity to behavioral and environmental influences, supporting the interpretation that seasonal HRV variation arises from multiple interacting regulatory systems.
4.6. Implications and Novelty
The primary novelty of this study lies in the characterization of subgroup-level seasonal HRV variation in relation to PA, using a large-scale real-world dataset.
Unlike previous studies that have focused primarily on mean-level associations, the present study demonstrates that regional differences in HRV are not mainly expressed through variability in PA sensitivity but rather through the residual component of HRV variation not accounted for by PA within the current analytical framework. This finding shifts the perspective from average-based comparisons to the determinants of seasonal HRV variation and its residual variability.
Specifically, the results suggest that HRV variation consists of components associated with PA that are shared across populations, as well as region-specific residual components that vary systematically across regions. These findings indicate that HRV should not be interpreted as a homogeneous response but rather as a composite of common and region-dependent influences.
These findings highlight the importance of considering residual variability as a key feature of physiological data, particularly in large-scale observational datasets where multiple interacting factors are present [
31]. From a clinical perspective, the presence of region-specific variability suggests that baseline HRV characteristics may differ across populations beyond measurable behavioral factors, implying that uniform reference values or predictive models may not fully capture regional differences in HRV variation patterns [
1].
Incorporating region-specific variability into HRV-based risk assessment models may improve their accuracy and generalizability. Furthermore, the identification of residual variability not explained by PA within the current model underscores the importance of environmental and contextual factors in HRV interpretation [
31]. These findings are also consistent with recent perspectives suggesting that population-level averages may not fully represent underlying variability [
33], supporting the need for more individualized approaches to cardiovascular risk evaluation and intervention.
4.7. Limitations
This study has several limitations. First, as an observational study, causal relationships cannot be established.
Second, the underlying factors contributing to regional differences were not directly measured, and therefore the specific mechanisms driving residual variability remain unclear. Given that HRV is influenced by multiple physiological, behavioral, and environmental factors, the unexplained component likely reflects a combination of such interacting influences. The residual component may also reflect the influence of unmeasured confounding factors such as medication use, comorbidities, sleep behavior, socioeconomic conditions, and healthcare access. In particular, cardiovascular disease, diabetes, beta-blocker use, arrhythmia burden, sleep disorders, and psychiatric conditions are known to substantially influence HRV and may have contributed to the observed regional differences, COVID-19-related changes, and residual variability.
Third, the ALLSTAR database consists of records from individuals who visited medical institutions, and thus the findings may reflect the characteristics of a clinical population rather than those of the general population. Previous studies have noted that HRV characteristics may differ depending on population context and health status. However, such large-scale real-world datasets combining ECG and PA are rare, and the present study provides valuable insights into the multiple determinants of HRV variation. Accordingly, differences in disease prevalence and treatment patterns across regions may have partially contributed to the observed regional heterogeneity.
Finally, although efforts were made to ensure sufficient sample size for each region, residual variability may still be partially influenced by differences in data availability. This may affect the stability of the estimated regional patterns and should be considered when interpreting the results.
Because the present analysis is based on subgroup-level aggregated seasonal variation metrics, the observed relationships should be interpreted as population-level covariation of seasonal amplitudes rather than individual-level causal effects. In addition, such aggregated analyses may be subject to ecological bias, including the possibility of Simpson’s paradox, whereby relationships observed at the subgroup level may differ from those at the individual level.