Review

Genomic and Antigenic Evolution of Influenza A(H3N2) After the COVID-19 Era: A Scoping Review with Focus on J and K Subclades and Implications for Vaccine Effectiveness


1
Department of Medicine, Surgery and Dentistry ‘’Scuola Medica Salernitana”, University of Salerno, 84081 Salerno, Italy
2
Hospital “San Giovanni di Dio e Ruggi d’Aragona”, 84081 Salerno, Italy
3
Integrated Care Department of Health Hygiene and Evaluative Medicine, San Giovanni di Dio e Ruggi d’Aragona University Hospital, 84131 Salerno, Italy
4
Hospital and Epidemiological Hygiene Unit, San Giovanni di Dio and Ruggi D’Aragona University Hospital, 18 Hospital, 84131 Salerno, Italy
*
Author to whom correspondence should be addressed.
These authors contributed equally to this work.
Germs 2026, 16(3), 18; https://doi.org/10.3390/germs16030018
Submission received: 10 February 2026 / Revised: 17 March 2026 / Accepted: 9 July 2026 / Published: 16 July 2026

Abstract

Post-COVID-19, influenza A(H3N2) has re-emerged with accelerated genetic diversification. The rise in antigenically drifted subclades raises concerns regarding immune escape and vaccine mismatch. To synthesize the available evidence on the post-pandemic evolution of influenza A(H3N2), with particular attention to emerging subclades and their potential public health implications, a scoping review (PRISMA-ScR) was conducted across six databases in January 2026, including studies on genomic surveillance, antigenic characterization, and vaccine effectiveness (VE). Twenty studies were included. While clade 2a.3a.1 (J lineage) predominated, reports highlighted the rapid emergence of the antigenically distinct K subclade (formerly J.2.4.1). Genetic and laboratory assays (HI/neutralization) confirmed immune escape and reduced vaccine match. Observational estimates indicated diminished VE against drifted strains, though no consistent increase in clinical severity was observed. Post-pandemic A(H3N2) is defined by rapid drift and diversification. Emerging variants like the K subclade challenge vaccine selection and seasonal preparedness. Integrated surveillance remains vital for timely vaccine updates and mitigating public health impact.

1. Introduction

The circulation of influenza A(H3N2) viruses remains a persistent global public health challenge due to their high evolutionary rate, pronounced antigenic drift, and recurrent association with reduced vaccine effectiveness compared with other seasonal influenza subtypes. Seasonal epidemics dominated by influenza A(H3N2) have historically been associated with greater clinical severity, higher hospitalization rates, and increased mortality compared with other influenza subtypes, particularly among older adults and vulnerable populations. These characteristics have made A(H3N2) one of the most challenging influenza viruses for surveillance and vaccine strain selection. Among influenza A viruses, A(H3N2) has historically demonstrated the greatest capacity for rapid antigenic change, driven by accumulation of mutations in the hemagglutinin (HA) gene that alter antigenic sites and facilitate immune escape [1,2]. Although seasonal influenza activity was markedly suppressed during the early phases of the COVID-19 pandemic, the subsequent relaxation of non-pharmaceutical interventions (NPIs) has been followed by an atypical resurgence of influenza worldwide, characterized by altered seasonality, increased genetic diversity, and the emergence of drifted viral variants [3,4].
Post-pandemic influenza dynamics have differed substantially from pre-2020 patterns. Several regions have reported delayed or prolonged influenza seasons, off-season epidemics, and shifts in subtype dominance, with influenza A(H3N2) re-emerging as a major contributor to disease burden in multiple settings [5,6]. These epidemiological changes have occurred in the context of population-level “immunity gaps” resulting from reduced viral circulation during the pandemic, waning vaccine-induced immunity, and heterogeneous vaccination coverage across age groups and regions [7,8]. Together, these factors have created ecological conditions conducive to the rapid selection and expansion of antigenically drifted influenza viruses.
Genomic surveillance has played a central role in documenting the accelerated evolution of influenza A(H3N2) in the post-COVID era. High-throughput sequencing and global data-sharing platforms, such as GISAID and WHO FluNet, have enabled near-real-time tracking of emerging clades and subclades, revealing substantial diversification within the HA phylogeny [9,10]. Recent reports have highlighted the global circulation of clade 2a.3a.1 (J lineage) viruses and the subsequent emergence of antigenically distinct descendants, including variants later designated as subclade K (J.2.4.1), which have shown evidence of reduced antigenic similarity to contemporaneous vaccine strains [11,12]. Such evolutionary trajectories raise concerns regarding immune escape, vaccine mismatch, and the adequacy of existing strain-selection processes.
Antigenic drift in influenza A(H3N2) has important implications for vaccine performance. Even in non-pandemic contexts, A(H3N2) vaccines have consistently demonstrated lower effectiveness than vaccines targeting A(H1N1) pdm09 or influenza B viruses, partly due to egg-adaptation effects and rapid antigenic change [13,14]. Post-pandemic surveillance data suggest that antigenic divergence between circulating A(H3N2) strains and vaccine reference viruses may be increasing, potentially contributing to reduced protection against infection and medically attended disease [15,16]. While reduced vaccine effectiveness does not necessarily translate into increased clinical severity, it may amplify transmission, healthcare utilization, and pressure on health systems during intense or prolonged influenza seasons.
Beyond virological and immunological considerations, the emergence of drifted influenza A(H3N2) variants has broader public health implications. Early detection of novel variants relies on integrated surveillance systems that combine genomic, epidemiological, syndromic, and digital data streams [17,18]. In the post-COVID landscape, the importance of early-warning public health intelligence has been increasingly recognized, particularly for respiratory viruses with pandemic potential or high societal impact [19,20,21]. At the same time, the communication of emerging variant signals poses challenges, as premature or poorly contextualized messaging may contribute to misinformation, risk misperception, or public fatigue following the COVID-19 infodemic [22,23].
Despite a rapidly expanding body of literature on post-pandemic influenza dynamics, evidence related to emerging antigenically drifted A(H3N2) variants remains fragmented across disciplinary boundaries. Genomic studies, antigenic analyses, epidemiological reports, vaccine effectiveness evaluations, and surveillance summaries are often published in parallel, without integrated synthesis. Moreover, early signals of variant emergence may appear in surveillance or preprint literature before formal nomenclature is established, complicating retrieval and interpretation through conventional systematic review approaches. In this context, a scoping review is particularly well-suited to map the breadth, nature, and gaps of available evidence, without restricting inclusion to narrowly defined outcomes or study designs [2,24].

Objectives and Review Questions

The objective of this scoping review is to systematically map current evidence on emerging antigenic drift variants of influenza A(H3N2) in the post-COVID-19 era, with particular attention to variants later designated as subclade K (J.2.4.1). Specifically, this review aims to address the following review questions:
  • Virology and mutation: What genetic and antigenic characteristics distinguish emerging A(H3N2) variants, including subclade K, from previously circulating strains?
  • Transmission and epidemiology: What evidence exists regarding geographic spread, growth advantage, and transmission dynamics of these variants?
  • Immune escape and vaccination: What is known about immune escape, vaccine mismatch, and implications for vaccine effectiveness?
  • Surveillance and early warning: How were these variants detected, and what role did genomic, digital, and syndromic surveillance systems play?
  • Health system impact: What early evidence is available regarding clinical severity, healthcare burden, and system preparedness?
  • Communication and infodemic: How has the emergence of these variants been communicated in scientific and public channels, and what misinformation patterns have been observed?
By addressing these questions, this scoping review seeks to support integrated public health interpretation of emerging influenza A(H3N2) variants and to inform future surveillance, vaccine strategy, and preparedness efforts.

2. Materials and Methods

2.1. Study Design and Reporting Framework

This scoping review was conducted in accordance with the methodological guidance for scoping reviews provided by the Joanna Briggs Institute (JBI) [25]. The review followed an evidence-mapping approach aimed at describing the extent, characteristics, and distribution of available evidence on emerging antigenic drift variants of influenza A(H3N2) in the post-COVID-19 period. Reporting was guided by the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) [26]. The study selection process was documented using the PRISMA 2020 flow diagram framework, and the completed PRISMA checklist is provided in the Supplementary File S1 [27]. The review protocol was prospectively registered on the Open Science Framework [28]. The review was conducted between January and February 2026 by a multidisciplinary research team. Two reviewers independently (SE and SQ) screened records and performed data charting, with disagreements resolved through discussion and adjudication by a senior reviewer (AC).

2.2. Review Question and Conceptual Framework

The scoping review was designed to address the following research question: What is currently known about emerging antigenic drift variants of influenza A(H3N2), including the variant later designated as subclade K (J.2.4.1), in terms of epidemiological patterns, immune escape, surveillance signals, and public health implications?
The question was operationalized using a Population–Exposure–Comparator–Outcome (PECO) framework adapted for emergent strain reviews. The population comprised human populations exposed to circulating influenza A(H3N2) viruses. The exposure was defined as infection with emerging antigenically drifted H3N2 variants, including variants later classified as subclade K (J.2.4.1). A formal comparator was not applicable, given the exploratory and descriptive nature of the review. Outcomes of interest encompassed epidemiological, virological, immunological, surveillance-related, and public health domains.

2.3. Eligibility Criteria

Eligibility criteria were defined a priori in line with scoping review methodology. We included primary research studies and surveillance-based reports that provided data on influenza A(H3N2) and described emerging clades, subclades, variants, or antigenic drift phenomena, with relevance to at least one of the outcomes of interest. Eligible records were required to include epidemiological, virological, antigenic, clinical, vaccine-related, or surveillance information and to be published between January 2024 and January 2026.
We excluded studies focusing exclusively on influenza B or non-H3N2 strains, animal-only or in vitro studies without direct public health relevance, articles dealing solely with historical influenza strains without linkage to contemporary circulation, editorials or opinion pieces without original data, and publications not available in English.

2.4. Information Sources and Search Strategy

A comprehensive literature search was conducted across six electronic databases: PubMed/MEDLINE, Scopus, Ovid, EBSCOhost, CINAHL, and the Cochrane Library. The final search was executed in January 2026. The search strategy was designed to capture both established and emerging terminology related to influenza A(H3N2) antigenic drift and variant classification.
The search string was:
((“influenza A”[tiab] OR influenza[tiab]) AND (H3N2[tiab] OR “A(H3N2)”[tiab]) AND (clade*[tiab] OR subclade*[tiab] OR variant*[tiab] OR “antigenic drift”[tiab] OR “immune escape”[tiab] OR “vaccine mismatch”[tiab]) AND (2024:2026[pdat]))
Equivalent search strategies were adapted for the remaining databases. The search approach was intentionally sensitive to early signals that might precede stable nomenclature, consistent with the objectives of a scoping review focused on emerging variants.
Full electronic search strategies for all databases are reported in Supplementary File S2.

2.5. Study Selection Process

All records retrieved from the database searches were imported into the Zotero (version 7.0, Roy Rosenzweig Center for History and New Media, George Mason University, Fairfax, VA, USA), and duplicate records were removed prior to screening [29]. Two reviewers independently screened titles and abstracts against the predefined eligibility criteria. Full texts were obtained for all records deemed potentially relevant or where eligibility could not be determined from the abstract alone.
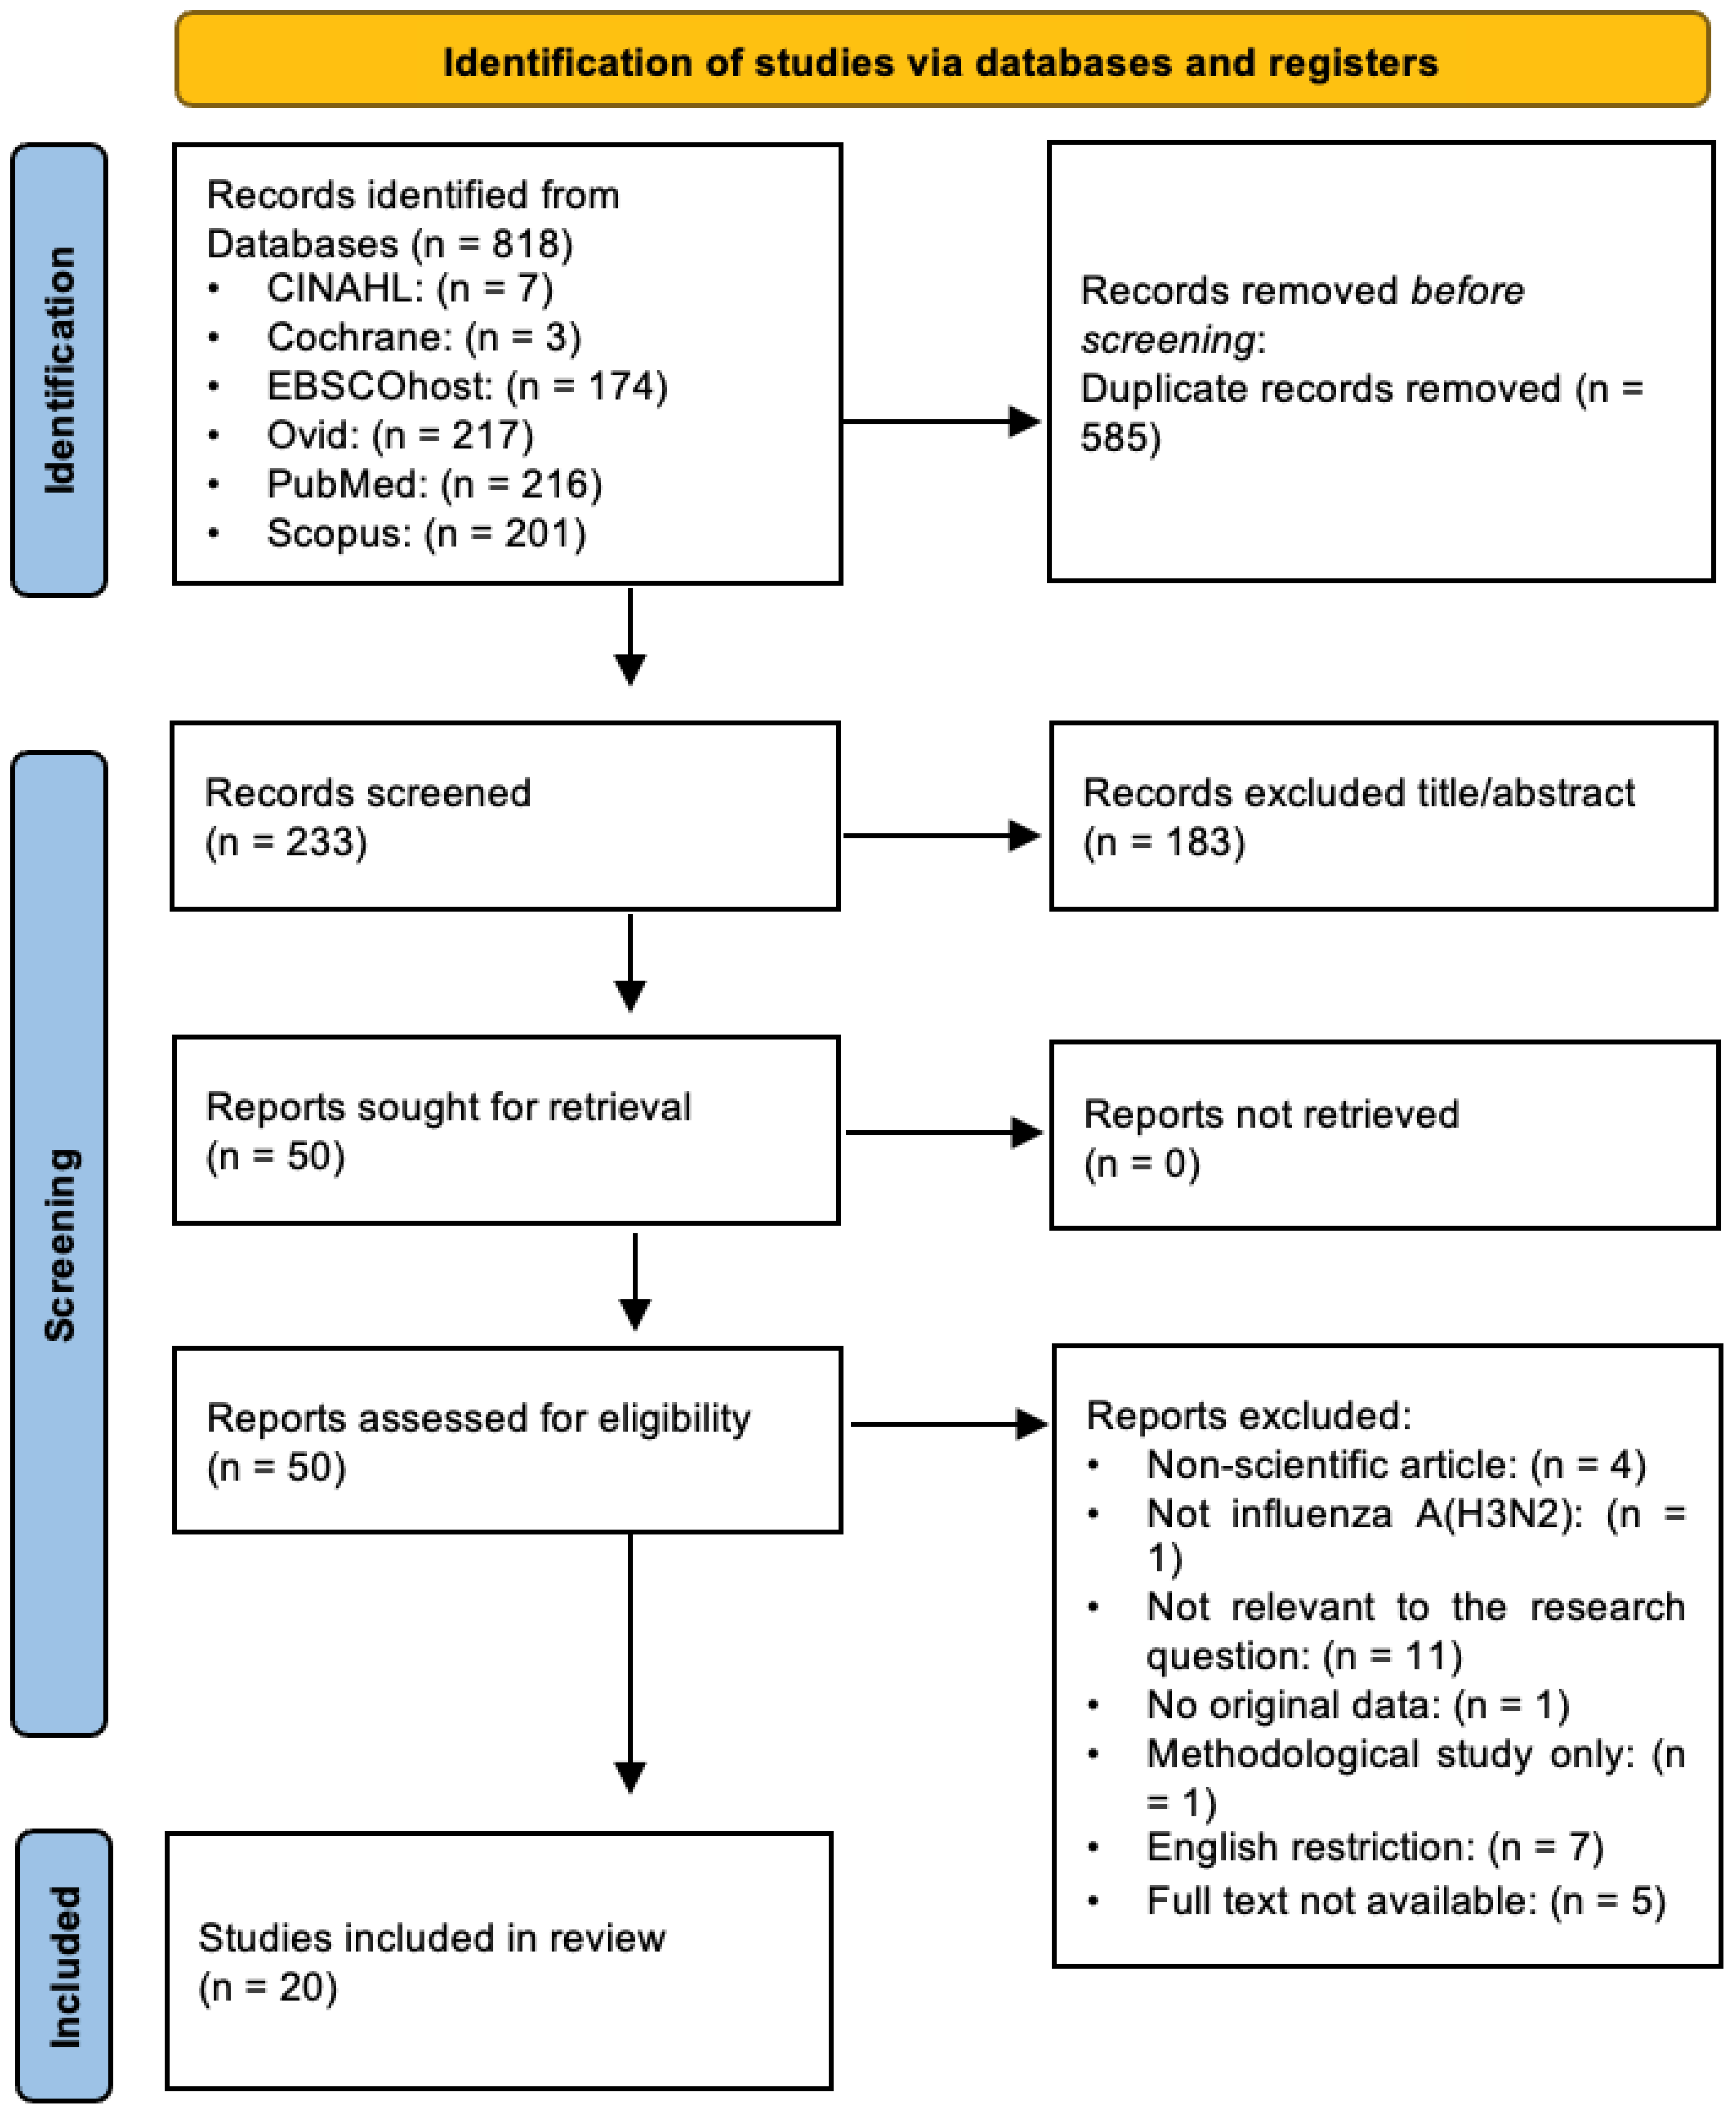
Full-text articles were assessed independently by the same reviewers, and reasons for exclusion at this stage were documented. Disagreements were resolved through discussion, with arbitration by a senior reviewer when necessary. The overall study selection process is summarized in the PRISMA flow diagram in Section 3 (Figure 1).

2.6. Outcomes of Interest

Outcomes of interest were defined a priori in alignment with the objectives of the scoping review and an early-signal public health intelligence perspective. Outcomes were conceptual rather than comparative and reflected the multidimensional nature of evidence related to emerging influenza A(H3N2) variants.
Specifically, outcomes included epidemiological patterns such as geographic spread, temporal trends, and transmission dynamics; virological and antigenic characteristics, including genetic mutations, antigenic drift, and subclade designation; immune escape and vaccine-related signals, such as evidence of antigenic mismatch or reduced vaccine effectiveness; surveillance and detection indicators derived from genomic, sentinel, or syndromic systems; and public health implications, including signals related to clinical severity, healthcare burden, and preparedness. Outcomes were captured as reported by study authors, without restriction to predefined quantitative metrics.

2.7. Data Charting and Management

A standardized data-charting framework was developed prior to data extraction and pilot-tested on a subset of included studies to ensure consistency and clarity. Data charting was conducted independently by two reviewers (SE and SQ), with iterative refinement of variables to accommodate the heterogeneity of evidence typical of emerging variant research.
Charted data included bibliographic information, study design and setting, population characteristics, subtype and subclade classification, genomic and antigenic data sources, key mutations, vaccine-related information, surveillance context, and reported public health implications. Data integrity and consistency were monitored throughout the process, and discrepancies were resolved through discussion and adjudication by the senior reviewer (AC), consistent with good practice for reproducible evidence synthesis [25]. Data were extracted using a standardized and piloted charting form developed a priori. The extraction included bibliographic information, geographic setting, study design, data sources, subclade classification, and outcome domains of interest. The complete data extraction table, including study characteristics, subclade classification, data sources, and outcome domains, is provided as Supplementary Table S3.

2.8. Data Synthesis and Analytical Approach

Data synthesis followed a descriptive and thematic approach, consistent with scoping review methodology. Evidence was mapped across predefined thematic domains aligned with the review question, allowing individual studies to contribute to multiple domains where applicable. Results were summarized narratively and through tabular and graphical representations to illustrate the distribution of evidence by geography, study design, data source, and thematic focus.
Attention was given to the temporal sequencing of signals related to emerging H3N2 subclades, enabling linkage between early genomic or antigenic findings and subsequent epidemiological, vaccine-related, or public health evidence.
To facilitate interpretation of heterogeneous evidence, included studies were grouped according to their primary analytical focus, including genomic surveillance, antigenic characterization, vaccine effectiveness assessment, and clinical or epidemiological outcomes.
Given the diversity of study designs and surveillance systems across geographic regions, the evidence synthesis followed a descriptive and thematic mapping approach rather than a quantitative comparison. Differences in methodology, surveillance context, and laboratory approaches were considered during interpretation and are reflected in the narrative synthesis.

2.9. Statistical Analysis

All data extracted from the included studies were analyzed descriptively. Proportions were reported as n/N (%) and, where appropriate, accompanied by 95% confidence intervals calculated using the Wilson method for descriptive purposes. Continuous variables (such as sample sizes of human participants or genomic datasets) were summarized using median and interquartile range [IQR] and, where reported, mean ± standard deviation, together with minimum and maximum values.
No meta-analysis or quantitative pooling of effect estimates was performed, in accordance with the objectives and methodological framework of a scoping review. All summaries were derived directly from the standardized data extraction tables using established descriptive statistical formulas.

2.10. Critical Appraisal

In accordance with JBI guidance and PRISMA-ScR recommendations, a formal risk-of-bias assessment was not performed. Given the heterogeneity of study designs and the objective to map emerging evidence and early signals rather than to evaluate intervention effects, study limitations reported by the original authors were charted and considered narratively to contextualize the strength and applicability of the evidence.

2.11. Ethics and Dissemination

This study synthesized data from published and publicly available sources and did not involve the collection of individual-level identifiable data; therefore, formal ethics approval was not required. The reporting and dissemination of findings follow PRISMA-ScR principles to ensure transparency and reproducibility, with protocol registration on the Open Science Framework providing public documentation of the a priori methods [28].

3. Results

3.1. Across the Databases Searched, a Total of Study Selection

818 records were identified (CINAHL: 7; Cochrane Library: 3; EBSCOhost: 174; Ovid: 217; PubMed: 216; Scopus: 201). After removal of 585 duplicate records, 233 unique records remained and were screened at the title and abstract level.
Of these, 183 records were excluded (161 at title screening and 22 at abstract screening), primarily because they did not address Influenza A(H3N2), focused on historical strains, or lacked relevance to the research question.
A total of 50 full-text articles were retrieved and assessed for eligibility. Among these, 30 articles were excluded for predefined reasons: non-scientific article (n = 4), not Influenza A(H3N2) (n = 1), not relevant to the review objectives (n = 11), absence of original data (n = 1), methodological study only (n = 1), non-English language (n = 7), and full text not available (n = 5).
Ultimately, 20 studies met the inclusion criteria and were included in the scoping review. No additional exclusions occurred during data charting. The study selection process is summarized in Figure 1.

3.2. Descriptive Overview of Included Studies

The 20 included studies, published between 2024 and 2026, comprised a heterogeneous body of evidence addressing emerging antigenic drift variants of Influenza A(H3N2) from epidemiological, virological, immunological, and surveillance perspectives.

3.3. Geographic Distribution

The included studies demonstrated a broad geographic distribution across multiple world regions (Table 1). Europe accounted for the largest proportion of included studies (6/20; 30.0%, 95% CI 14.5–51.9), reflecting a strong representation of national and regional influenza surveillance systems. European evidence derived from Poland [30], Italy [31], France [32], the United Kingdom [33], Bulgaria [34], and Romania [35], encompassing genomic surveillance, epidemiological monitoring, and vaccine effectiveness analyses.
East and Southeast Asia represented the second most frequent geographic area (5/20; 25.0%, 95% CI 11.2–46.9). Studies originated from Hong Kong SAR [36,37] and mainland China [38,39,40]. These investigations were primarily based on laboratory- or hospital-derived surveillance data and focused on post-pandemic molecular and genomic characterization of circulating influenza A(H3N2) viruses.
South Asia was represented by a single study (1/20; 5.0%, 95% CI 0.9–23.6), conducted in Sri Lanka [41], which contributed hospital-based surveillance data from a paediatric population.
North America accounted for 3/20 studies (15.0%, 95% CI 5.2–36.0), including investigations from the United States [42,43] and Canada [44]. These studies addressed genomic epidemiology, digital surveillance, and vaccine-related outcomes within healthcare and community-based surveillance systems.
Africa, the Middle East, and Oceania were each represented by a single study (1/20; 5.0% each, 95% CI 0.9–23.6). African data derived from genomic surveillance conducted in Cameroon [45], while the Middle East was represented by hospital-based surveillance from Saudi Arabia [46]. Oceania contributed a large multinational surveillance study from Australia and New Zealand [47], based on extensive virological sequencing datasets.
Finally, multi-region or global surveillance studies accounted for 2/20 publications (10.0%, 95% CI 2.8–30.1). These included EU/EEA-wide influenza surveillance coordinated across multiple countries [48] and an international genomic surveillance study integrating data from the United States, Hong Kong SAR, and Japan [49], underscoring the role of transnational monitoring networks in capturing post-pandemic influenza A(H3N2) circulation.

3.4. Subclade Focus and Virological Characterization

Most included studies focused on clade J–related lineages, including J and J-derived subclades (e.g., clade 2a.3a.1), reflecting their global predominance during the post-pandemic period (15/20 studies; 75.0%, 95% CI 53.1–88.8). These studies consistently reported widespread circulation of J-derived A(H3N2) viruses across Europe, Asia, North America, and Oceania, based on genomic surveillance and phylogenetic analyses [30,31,32,33,34,35,36,37,38,39,40,41,42,45,48].
Explicit reference to the K subclade (J.2.4.1) was reported in 4 studies (4/20; 20.0%, 95% CI 8.1–41.6), primarily in the context of late-season emergence, rapid expansion, and potential antigenic drift. These included large-scale genomic surveillance and regional case series documenting replacement of earlier J-derived variants [31,35,47,48].
Two studies (2/20; 10.0%, 95% CI 2.8–30.1) addressed other clades or subclades outside the J/K continuum or focused on broader evolutionary patterns without detailed J/K attribution [46,49]. One study (1/20; 5.0%, 95% CI 0.9–23.6) did not report a specific clade or subclade designation, focusing instead on outbreak dynamics and clinical characteristics [44].
The distribution of subclade focus across included studies is summarised in Table 2.

3.5. Methodological Composition of Included Studies

The methodological composition of the included studies is summarised in Table 3. Surveillance-based studies represented the predominant methodological design, accounting for 12 studies (12/20; 60.0%, 95% CI 38.7–78.1). These investigations were primarily based on routine genomic surveillance, FluNet reporting, or national and regional influenza monitoring systems and included studies from multiple geographic settings [30,31,32,34,36,37,38,39,40,41,45,48].
Studies explicitly assessing vaccine effectiveness or vaccine–virus mismatch accounted for 4 studies (4/20; 20.0%, 95% CI 8.1–41.6) [33,35,42,44]. These studies employed heterogeneous designs, including test-negative approaches, observational analyses, and outbreak investigations, limiting direct quantitative comparability.
Computational or modeling-based studies represented 2 studies (2/20; 10.0%, 95% CI 2.8–30.1) and focused on integrating genomic and surveillance data to explore evolutionary dynamics and post-pandemic circulation patterns [43,49].
Finally, clinical case series and immunological neutralization studies were each represented by a single publication (1/20; 5.0%, 95% CI 0.9–23.6). The clinical case series reported virologically confirmed A(H3N2) infections with atypical clinical manifestations [47], while the immunological study assessed neutralization profiles against circulating strains without population-level surveillance data [46].

3.6. Evidence Mapping Across Outcome Domains

An evidence map was constructed to visualize the distribution of evidence across predefined outcome domains, including genomic surveillance, antigenic characterization, immune escape signals, vaccine effectiveness assessment, clinical outcomes, surveillance or early warning signals, and policy relevance (Table 4).
Most included studies contributed evidence on genomic surveillance and antigenic characterization, reflecting the central role of molecular epidemiology in post-pandemic influenza monitoring. In contrast, immune escape signals and vaccine effectiveness outcomes were addressed less consistently and often indirectly. Evidence related to clinical outcomes, health system impact, and policy relevance was comparatively sparse and unevenly distributed across studies, highlighting important gaps in the current evidence base.
Overall, the evidence mapping illustrates substantial overlap across upstream surveillance domains, while downstream clinical and policy-oriented outcomes remain under-represented, a pattern consistent with the exploratory nature of scoping reviews.
Each row represents an individual study (n = 20), while columns correspond to predefined outcome domains. Colored cells indicate the presence of data addressing the respective domain within each study. The figure illustrates the heterogeneity and overlap of evidence domains typical of scoping reviews.

3.7. Summary of Key Descriptive Findings

Overall, the included evidence highlights a rapidly evolving Influenza A(H3N2) landscape in the post-COVID-19 period, characterized by the predominance of J-related clades and the emergent detection of the K (J.2.4.1) subclade within global surveillance systems. While genomic and antigenic data are increasingly available, evidence on immune escape, vaccine mismatch, and downstream public health implications remains fragmented, underscoring the importance of integrated early-warning surveillance approaches.

4. Discussion

This scoping review synthesized early post-pandemic evidence on the genomic and antigenic evolution of influenza A(H3N2), with a specific focus on J-related lineages (including 2a.3a.1/J.*) and the subsequent emergence of the K subclade (J.2.4.1), integrating epidemiological, virological, vaccine-related, and surveillance-relevant signals. Across the 20 included studies, the evidence base was dominated by genomic surveillance and molecular epidemiology, with fewer contributions addressing clinical severity, immunological correlations, or policy translation. This pattern is coherent with the “early-signal” intent of the review: evolutionary transitions are typically detected first through sequence-based monitoring and antigenic characterization, while clinical and health-system consequences are documented later and often indirectly. The distribution of geographic settings and the methodological predominance of surveillance designs (Table 1, Table 2 and Table 3) suggest that post-pandemic H3N2 evolution is being observed primarily through countries and networks with mature sequencing capacity and established influenza monitoring infrastructures, potentially biasing early signal detection toward higher-resource contexts [32,33,36,40,42,48].

4.1. Virological and Antigenic Evolution: Why J Lineages Dominated and What “K” Adds

A central signal across studies is the sustained predominance of J-related clades/subclades in the post-pandemic period (Table 2). Multiple datasets spanning Europe and Asia reported high proportions of clade 2a.3a.1/J.* among sequenced H3N2 viruses, consistent with an evolutionary landscape in which antigenic drift continues to occur within a broadly successful genetic backbone rather than via abrupt lineage replacement [32,34,35,36,37,38,39,48].
From a mechanistic perspective, the studies that reported amino acid substitutions in HA repeatedly emphasized changes positioned in or near antigenic sites and receptor-binding-adjacent regions, patterns consistent with incremental immune escape under population immunity pressure [31,32,36,39,48]. Importantly, not all papers coupled genetic findings with antigenic assays, and several inferred antigenic relevance from sequence changes alone (a common but non-equivalent surrogate). This heterogeneity matters: inferences based on HA substitutions can overestimate functional drift if compensatory or context-dependent effects are not tested [31,38,39].
Within this broader J-dominant landscape, explicit K (J.2.4.1) labeling was limited (Table 2), but the studies that did report or center K portrayed it as a recognizable drift step with measurable antigenic consequences, rather than a purely nomenclatural relabeling. The Australia–New Zealand analysis (explicitly framed around K) highlighted antigenic divergence detected through haemagglutination inhibition approaches, supporting the interpretation of K as an operationally meaningful drift variant [47]. Additional K-relevant signals also emerged in multinational work spanning the USA, Hong Kong, and Japan, suggesting that detection of the K drift step is not geographically isolated and may be identifiable across diverse surveillance environments once the classification is applied [49].
The evidence suggests continuity (J-related lineages remain globally predominant) coexisting with punctuated drift “events” within that background (K/J.2.4.1 as a notable antigenic step). This supports a practical message for surveillance: subclade naming alone is insufficient—what matters is whether the subclade correlates with antigenic readouts, an unusual growth advantage, or vaccine mismatch signals. The included studies document that such a correlation is plausible for K, but the evidence base remains thin and uneven across regions [47,48,49].

4.2. Transmission and Epidemiology: Spread Signals and Post-Pandemic Dynamics

Although the review targeted epidemiological patterns as an outcome, most studies approached epidemiology indirectly through sequencing-derived descriptors rather than formal transmission modeling [33,36,38,39,48]. Where epidemiological context was present, it often emphasized the post-pandemic rebound of influenza activity and the re-expansion of H3N2 diversity following periods of reduced circulation during COVID-19 non-pharmaceutical interventions—an ecological setting that plausibly increases opportunities for rapid drift when population immunity landscapes shift [32,33,36,48,50].
However, the absence of consistent growth-advantage estimation is notable: only a minority of studies used computational approaches that could quantify relative fitness or model-driven expansion, and even those typically relied on curated sequence datasets rather than integrated epidemiological denominators [40,43,49]. This gap limits confident inference about whether K’s emergence reflects intrinsic transmissibility, immune-driven selection, founder effects, or surveillance intensity artifacts.

4.3. Immune Escape and Vaccine Mismatch: Evidence Strongest Where Antigenic Assays Were Performed

The most actionable immune-escape signals were reported by studies combining genomic change with antigenic characterization, because they link sequence drift to measurable antigenic distance [32,36,47,48]. Across these studies, drift variants demonstrated reduced recognition by antisera raised against prior vaccine strains, supporting the plausibility of vaccine mismatch risk during drift transitions.
Evidence tied explicitly to vaccine effectiveness was present but not predominant (Table 3). Studies evaluating VE used heterogeneous designs, limiting direct comparability [33,42,44,48]. In addition, several studies referenced VE contextually without providing variant-specific estimates, constraining causal interpretation [31,32,48].
Interpretive synthesis. The evidence supports a cautious but operationally important conclusion: antigenic drift signals—especially when aligned with K/J.2.4.1 classification—may precede periods of reduced vaccine match. However, the literature does not consistently quantify variant-specific VE or standardize how drift evidence informs vaccine strain decisions or risk communication [33,47,48].
The emergence of the K subclade (J.2.4.1) has also raised important considerations for vaccine strain selection. Influenza vaccine composition is updated annually through the WHO Global Influenza Surveillance and Response System (GISRS), which integrates genomic, antigenic, and epidemiological data to inform strain selection. Signals of antigenic drift associated with newly emerging subclades, such as K, may contribute to discussions on candidate vaccine viruses when antigenic divergence from existing vaccine strains is observed.
However, the interpretation of reported reductions in vaccine effectiveness must consider substantial heterogeneity across studies, including differences in geographic circulation patterns, vaccination coverage, study design (e.g., test-negative vs. observational approaches), and population characteristics. These methodological and epidemiological differences likely contribute to the variability observed in VE estimates across regions and seasons.

4.4. Surveillance and Early Warning: The Value—and Limitations—of Genomic-First Detection

A defining feature of the included evidence is the reliance on genomic surveillance (Table 4). Many studies used routine sequencing coupled with phylogenetics to describe drift patterns and emerging clusters, demonstrating that the first detection of drift variants is frequently genomic rather than clinical [31,32,33,34,35,36,37,38,39,45,46,47,48,49].
At the same time, the early-warning concept was inconsistently operationalized. Some studies explicitly framed drift detection as surveillance-relevant, while others provided high-resolution genomic descriptions without linking findings to alert thresholds or public health action [32,36,45,46,48]. Only a subset of studies explicitly addressed policy relevance or system-level preparedness, contributing to the lower coverage of that domain in Table 4 [32,33,35,48].

4.5. Clinical Severity and Health-System Implications: Limited, Heterogeneous, and Mostly Indirect

Clinical outcomes were reported in a minority of studies (Table 4) and were largely descriptive rather than standardized [30,41,42,44,46]. As a result, the review can suggest plausible clinical implications—such as increased burden during periods of vaccine mismatch—but cannot robustly attribute changes in severity to K/J.2.4.1 based on current evidence [42,47,48].

4.6. Communication and Infodemic Considerations: An Under-Addressed Domain

Despite being a pre-specified analytical domain, communication and infodemic patterns were rarely addressed as explicit outcomes. This absence should be interpreted as an evidence gap rather than a negative finding. Given that antigenic drift and vaccine updates often trigger public concern and influence vaccine uptake, future early-signal scoping work may benefit from integrating public-facing communication datasets alongside genomic surveillance. Only a small subset of studies indirectly hinted at public health relevance beyond laboratory findings [32,33,45,46].

4.7. Evidence Gaps, Strengths, and Implications for Future Surveillance and Research

Strengths of the mapped evidence. The review identified substantial genomic surveillance capacity across multiple regions and demonstrated that post-pandemic H3N2 drift is being actively tracked using modern phylogenetic and molecular approaches (Table 4). This provides a robust base for early detection of drift variants and for generating hypotheses about vaccine mismatch risk [33,36,38,39,48].
Key gaps. Three gaps emerged consistently. First, antigenic characterization is not uniformly paired with genomic reporting, limiting functional interpretation of substitutions [31,38,39]. Second, variant- or subclade-specific VE estimates remain limited and methodologically heterogeneous, constraining the ability to connect drift to real-world vaccine performance [33,42,44]. Third, evidence linking drift detection to explicit early warning thresholds and policy actions is sparse, and communication/infodemic outcomes are underrepresented despite their public health importance [45,46,48].
Practical implications. The synthesis suggests that the most policy-relevant approach to post-pandemic H3N2 drift—and particularly to K/J.2.4.1—will require integrated surveillance pipelines that: (i) combine sequence-based detection with antigenic assays, (ii) prioritize standardized reporting of drift-relevant substitutions alongside antigenic readouts, and (iii) link laboratory signals to VE monitoring and decision-oriented communication. The included studies collectively provide the components of this pipeline, but the literature shows that these components are often siloed rather than fully integrated [32,33,47,48,49].
This scoping review shows that post-pandemic influenza A(H3N2) evolution is characterized by rapid genetic diversification, in which emerging subclades such as K (J.2.4.1) represent early surveillance signals rather than established variants of clinical concern, underscoring the need for integrated genomic and antigenic monitoring.

4.8. Limitations of This Scoping Review

As a scoping review, this work aimed to map and characterize the evidence rather than to produce pooled effect estimates or causal attribution. The included evidence base is inherently heterogeneous by design, setting, laboratory methods, and reporting granularity; therefore, findings should be interpreted as an overview of signals and evidence coverage rather than as definitive estimates of variant impact. In addition, geographic distribution likely reflects differences in sequencing capacity and surveillance maturity rather than the true absence of drift variants in underrepresented regions. Finally, the evolving nature of subclade nomenclature may have contributed to under-ascertainment of studies describing K-like viruses without explicitly using the “J.2.4.1/K” label at publication time [32,45,46,47,48,49].

5. Conclusions

This scoping review provides a comprehensive synthesis of post-pandemic evidence on the genomic and antigenic evolution of influenza A(H3N2), with particular attention to J-related lineages and the emerging K subclade (J.2.4.1). By mapping 20 recent studies across multiple geographic regions, methodological designs, and outcome domains, the review highlights how contemporary H3N2 evolution is being primarily detected and characterized through genomic surveillance and antigenic analyses, while downstream clinical, vaccine performance, and policy-relevant evidence remains comparatively limited.
Across the included literature, J-related clades continued to dominate the post-pandemic H3N2 landscape, supporting the notion of evolutionary continuity within a successful genetic backbone rather than abrupt lineage replacement. Within this context, the emergence of the K subclade appears as a discrete antigenic drift step identified through a limited number of studies, suggesting potential functional relevance but also underscoring the uneven global recognition of this variant at the time of publication. The findings collectively indicate that subclade designation alone is insufficient to guide public health interpretation unless supported by antigenic, epidemiological, or vaccine-related evidence.
From a surveillance perspective, the review confirms the central role of genomic-first detection as an early warning mechanism for influenza evolution. However, it also reveals important gaps in the translation of genomic and antigenic signals into standardized assessments of vaccine mismatch, clinical impact, and actionable public health decision-making. Evidence on vaccine effectiveness and immune escape was heterogeneous and methodologically diverse, while explicit links between drift detection and health system preparedness or policy response were infrequently addressed.
Importantly, the limited coverage of clinical outcomes and communication-related domains reflects the temporal dynamics of influenza surveillance: evolutionary signals are identified early, whereas clinical burden, health system impact, and public communication consequences often emerge later and require longer observation windows. This temporal mismatch reinforces the value of scoping approaches for capturing early signals while simultaneously highlighting areas where future research and surveillance integration are urgently needed.
Overall, this review underscores the need for more integrated influenza surveillance frameworks that combine high-resolution genomic monitoring with systematic antigenic characterization, harmonized vaccine effectiveness evaluation, and explicit pathways for translating early drift signals into policy-relevant guidance and public communication. In the post-pandemic era, where influenza A(H3N2) evolution appears accelerated and less predictable, such integration is essential not only for optimizing vaccine strain selection but also for strengthening early warning capacity and maintaining public trust in seasonal influenza control strategies.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/germs16030018/s1. Supplementary File S1: Completed PRISMA 2020 checklist; Supplementary File S2: Complete search strategies for all electronic databases searched, including PubMed, Scopus, CINAHL, Ovid, EBSCOhost, and the Cochrane Library; Supplementary File S3: Complete data extraction table for all studies included in the scoping review; Supplementary File S4: Supplementary figures and tables, including the PRISMA 2020 flow diagram (Figure S1), geographic distribution of the included studies (Table S1), distribution of influenza A(H3N2) subclades (Table S2), methodological characteristics of the included studies (Table S3), and an evidence map showing coverage across the predefined outcome domains (Table S4).

Author Contributions

Conceptualization, A.C. and E.S.; methodology, A.P. and R.M.; validation, A.C., E.S. and G.B.; formal analysis, A.C. and E.S.; investigation, M.N., S.Q. and S.E.; data curation, E.S.; writing—original draft preparation, A.P., R.M., M.N., D.F.; M.N., M.C. and S.Q.; writing—review and editing, A.C., E.S. and G.B.; supervision, G.B. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Informed Consent Statement

Informed consent was obtained from all subjects involved in the study.

Data Availability Statement

De-identified data are openly available in the Open Science Framework (OSF) at https://doi.org/10.17605/OSF.IO/QF837. Additional materials are available from the corresponding author upon reasonable request.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Belongia, E.A.; McLean, H.Q. Efficacia del vaccino antinfluenzale: Definire il problema H3N2. Clin. Infect. Dis. 2019, 69, 1817–1823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
  3. Olsen, S.J.; Azziz-Baumgartner, E.; Budd, A.P.; Brammer, L.; Sullivan, S.; Pineda, R.F.; Cohen, C.; Fry, A.M. Decreased Influenza Activity During the COVID-19 Pandemic—United States, Australia, Chile, and South Africa, 2020. MMWR Morb. Mortal. Wkly. Rep. 2020, 69, 1305–1309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Adlhoch, C.; Mook, P.; Lamb, F.; Ferland, L.; Melidou, A.; Amato-Gauci, A.J.; Pebody, R. The European Influenza Surveillance Network; European Influenza Surveillance Network; European Influenza Surveillance Network; et al. European Influenza Surveillance Network. Pochissima influenza nella regione europea dell’OMS durante la stagione 2020/21, settimane dalla 40a del 2020 all’8a del 2021. Euro. Surveill. 2021, 26, 2100221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Centers for Disease Control and Prevention. Seasonal Influenza—Annual Epidemiological Report for 2023/2024; European Centre for Disease Prevention and Control: Stockholm, Sweden, 2024; Available online: https://www.ecdc.europa.eu/en/publications-data/seasonal-influenza-annual-epidemiological-report-20232024 (accessed on 1 February 2026).
  6. Centers for Disease Control and Prevention. Influenza Activity in the United States during the 2023–2024 Season and Composition of the 2024–2025 Influenza Vaccine; MMWR; CDC: Atlanta, GA, USA, 2024. Available online: https://www.cdc.gov/flu/whats-new/flu-summary-2023-2024.html (accessed on 1 February 2026).
  7. Rotulo, G.A.; Percivale, B.; Molteni, M.; Naim, A.; Brisca, G.; Piccotti, E.; Castagnola, E. The impact of COVID-19 lockdown on infectious diseases epidemiology: The experience of a tertiary Italian Pediatric Emergency Department. Am. J. Emerg. Med. 2021, 43, 115–117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. MC Rose, A.; Lucaccioni, H.; Marsh, K.; Kirsebom, F.; Whitaker, H.; Emborg, H.-D.; Botnen, A.B.; O’dOherty, M.G.; Pozo, F.; Hameed, S.S.; et al. European IVE group; Members of the European IVE group. Interim 2024/25 influenza vaccine effectiveness: Eight European studies, September 2024 to January 2025. Euro. Surveill. 2025, 30, 2500102, Erratum in Euro. Surveill. 2025, 30, 240320c. https://doi.org/10.2807/1560-7917.ES.2025.30.11.240320c. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. World Health Organization. Recommended Composition of Influenza Virus Vaccines for Use in the 2023–2024 Northern Hemisphere Influenza Season; WHO: Geneva, Switzerland, 2023; Available online: https://www.who.int/publications/m/item/recommended-composition-of-influenza-virus-vaccines-for-use-in-the-2023-2024-northern-hemisphere-influenza-season (accessed on 30 January 2026).
  10. Shu, Y.; McCauley, J. GISAID: Global initiative on sharing all influenza data—From vision to reality. Euro. Surveill. 2017, 22, 30494. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. World Health Organization. Recommended Composition of Influenza Virus Vaccines for Use in the 2024–2025 Northern Hemisphere Influenza Season; WHO: Geneva, Switzerland, 2024; Available online: https://www.who.int/publications/m/item/recommended-composition-of-influenza-virus-vaccines-for-use-in-the-2024-2025-northern-hemisphere-influenza-season (accessed on 30 January 2026).
  12. Jallow, M.M.; Barry, M.A.; Ndiaye, N.K.; Touré, C.T.; Talla, C.; Kiori, D.; Sagne, S.N.; Sy, S.; Goudiaby, D.; Niang, M.N.; et al. Caratterizzazione genetica e antigenica del virus dell’influenza A(H3N2) dopo 13 anni consecutivi di sorveglianza dell’influenza in Senegal, 2010–2022. J. Med. Virol. 2024, 96, e70010. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Zost, S.J.; Parkhouse, K.; Gumina, M.E.; Kim, K.; Perez, S.D.; Wilson, P.C.; Treanor, J.J.; Sant, A.J.; Cobey, S.; Hensley, S.E. Contemporary H3N2 influenza viruses have a glycosylation site that alters binding of antibodies elicited by egg-adapted vaccine strains. Proc. Natl. Acad. Sci. USA 2017, 114, 12578–12583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Tenforde, M.W.; Patel, M.M.; Lewis, N.M.; Adams, K.; Gaglani, M.; Steingrub, J.S.; Shapiro, N.I.; Duggal, A.; Prekker, M.E.; Peltan, I.D.; et al. Influenza and Other Viruses in the Acutely Ill (IVY) Network. Vaccine Effectiveness Against Influenza A(H3N2)-Associated Hospitalized Illness: United States, 2022. Clin. Infect. Dis. 2023, 76, 1030–1037. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Belongia, E.A.; Simpson, M.D.; King, J.P.; Sundaram, M.E.; Kelly, N.S.; Osterholm, M.T.; McLean, H.Q. Variable influenza vaccine effectiveness by subtype and season: Implications for strain evolution. J. Infect. Dis. 2023, 228, 845–854. Available online: https://stacks.cdc.gov/view/cdc/222767 (accessed on 30 January 2026).
  16. Maurel, M.; Pozo, F.; Pérez-Gimeno, G.; Buda, S.; Sève, N.; Oroszi, B.; Hooiveld, M.; Gomez, V.; Domegan, L.; Martínez-Baz, I.; et al. VEBIS study team. Influenza vaccine effectiveness in Europe: Results from the 2022–2023 VEBIS (Vaccine Effectiveness, Burden and Impact Studies) primary care multicentre study. Influenza Other Respir. Viruses 2024, 18, e13243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. O’Shea, J. Digital disease detection: A systematic review of event-based internet biosurveillance systems. Int. J. Med. Inform. 2017, 101, 15–22. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Brownstein, J.S.; Freifeld, C.C.; Madoff, L.C. Digital disease detection--harnessing the Web for public health surveillance. N. Engl. J. Med. 2009, 360, 2153–2157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Biggerstaff, M.; Slayton, R.B.; Johansson, M.A.; Butler, J.C. Improving Pandemic Response: Employing Mathematical Modeling to Confront Coronavirus Disease 2019. Clin. Infect. Dis. 2022, 74, 913–917. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Cianciulli, A.; Santoro, E.; Manente, R.; Pacifico, A.; Barberio, I.; Satriani, V.; Boccia, G. Clinical and Symptom Profiles of Long-COVID Patients in Italy: A Cross-Sectional Analysis. Healthcare 2025, 13, 2706. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Cianciulli, A.; Santoro, E.; Manente, R.; Pacifico, A.; Comunale, G.; Finizio, M.; Capunzo, M.; De Caro, F.; Franci, G.; Moccia, G.; et al. Validation of a Questionnaire on the Post-COVID-19 Condition (Long COVID): A Cross-Sectional Study in Italy. Infect. Dis. Rep. 2025, 17, 69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Word Health Organization. Managing the COVID-19 Infodemic: Promoting Healthy Behaviours and Mitigating the Harm from Misinformation and Disinformation; WHO: Geneva, Switzerland, 2020; Available online: https://www.who.int/news/item/23-09-2020-managing-the-covid-19-infodemic-promoting-healthy-behaviours-and-mitigating-the-harm-from-misinformation-and-disinformation (accessed on 30 January 2026).
  23. Lewandowsky, S.; Ecker, U.K.H.; Cook, J. Beyond misinformation: Understanding and coping with the “post-truth” era. J. Appl. Res. Mem. Cogn. 2017, 6, 353–369. [Google Scholar] [CrossRef] [Scilit]
  24. Peters, M.D.J.; Marnie, C.; Tricco, A.C.; Pollock, D.; Munn, Z.; Alexander, L.; McInerney, P.; Godfrey, C.M.; Khalil, H. Updated methodological guidance for the conduct of scoping reviews. JBI Evid. Synth. 2020, 18, 2119–2126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Peters, M.D.; Godfrey, C.; McInerney, P.; Khalil, H.; Larsen, P.; Marnie, C.; Pollock, D.; Tricco, A.C.; Munn, Z. Best practice guidance and reporting items for the development of scoping review protocols. JBI Evid. Synth. 2022, 20, 953–968. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Open Science Framework. Protocol Registration Record. OSF Registries 2026. Available online: https://osf.io/qf837/overview (accessed on 2 February 2026).
  29. Roy Rosenzweig Center for History and New Media. Zotero; George Mason University: Fairfax, VA, USA, 2006; Available online: http://www.zotero.org (accessed on 2 February 2026).
  30. Brydak, L.B.; Masny, A.; Poznańska, A.; Szymański, K.; Kondratiuk, K.; Czajkowska, E.; Mańkowski, B.; Łuniewska, K. Monitoring of Influenza and Influenza-Like Viruses in the 2022/2023 and 2023/2024 Epidemic Seasons Using the SENTINEL and NON-SENTINEL Surveillance Systems in Poland. Med. Sci. Monit. Int. Med. J. Exp. Clin. Res. 2025, 31, e949615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Centrone, F.; Melilli, R.; Marziani, A.; Orlando, V.A.; Peccarisi, L.; Casulli, D.; Sallustio, A.; Chironna, M. Non-mumps parotitis associated with influenza A/H3N2: A case series from Southern Italy during the 2024–2025 influenza season. J. Infect. Public Health 2025, 18, 102907. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. De Clercq, A.; Blanquart, F.; Vieillefond, V.; Visseaux, B.; Chakra, C.N.A.; Nunes, M.C.; Jacques, A.; Haim-Boukobza, S.; Wehrle, V.; Deleglise, G.; et al. RELAB study group. Influenza vaccine effectiveness and genetic diversity: Insights from end-of-season community surveillance, France, 2024–2025. Emerg. Microbes Infect. 2025, 14, 2562045. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Kirsebom, F.C.; Thompson, C.; Talts, T.; Kele, B.; Whitaker, H.J.; Andrews, N.; Aziz, N.A.; Rawlinson, C.; Green, R.E.; Quinot, C.; et al. Early influenza virus characterisation and vaccine effectiveness in England in autumn 2025, a period dominated by influenza A(H3N2) subclade K. Euro Surveill. 2025, 30, 2500854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Korsun, N.; Trifonova, I.; Pavlova, D.; Uzunova, Y.; Ivanov, I.; Ivanov, D.; Velikov, P.; Voleva, S.; Tcherveniakova, T.; Christova, I. Etiological Spectrum of Acute Respiratory Infections in Bulgaria During the 2023-2024 Season and Genetic Diversity of Circu-lating Influenza Viruses. Viruses 2025, 17, 270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Vlaicu, O.; Banica, L.; Hohan, R.; Surleac, M.; Florea, D.; Miron, V.D.; Tudor, A.; Săndulescu, O.; Drăgănescu, A.C.; Oțelea, D.; et al. Antigenic Divergence from the Seasonal Vaccine of the Influenza Virus Strains Circulating in Romania During Three Successive Seasons (2021–2024). Microorganisms 2024, 12, 2363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Bian, J.; Fung, J.; Lee, L.-K.; Tam, W.-Y.; Wong, L.C.-H.; Wong, C.K.-W.; Lau, M.Y.-X.; Jiang, B.; Tang, N.H.-L.; Ho, A.Y.-M.; et al. Genetic Characterization of Influenza A Viruses Circulating in Hong Kong, China, 2023: The First Influenza Epidemic after the Lifting of 2.5 Years of COVID-19 Non-Pharmaceutical Interventions. Emerg. Microbes Infect. 2025, 14, 2521850. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Murphy, C.; Kwan, M.Y.; Chan, E.L.; Wong, J.S.; Sullivan, S.G.; Peiris, M.; Cowling, B.J.; Lee, S.-L. Influenza vaccine effectiveness against hospitalizations associated with influenza A(H3N2) in Hong Kong children aged 9 months to 17 years, June-November 2023. Vaccine 2024, 42, 1878–1882. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Lv, T.; Chen, J.; Li, H.; Chen, X.; Zhang, N.; Ma, C.; Zhang, Y.; You, P. Influenza A virus continues to circulate among children in Linyi, northern China, after the relaxation of COVID-19 control measures. Sci. Rep. 2024, 14, 30164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Song, Y.; Zhang, X.; Ji, J.; Li, L.; Zhou, Y.; Li, P.; Ren, G.; Lv, S.; Zhang, X.; Yan, Y.; et al. Genetic characteristics of influenza A/H3N2 virus in Jiaxing, China (2019–2024). Virol. J. 2025, 22, 359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Geng, L.; He, J.; Liu, P. FluAttn: Antigenicity prediction of influenza A/H3N2 through attention-based feature mining. Infect. Dis. Model. 2025, 11, 428–437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Jayadas, T.T.P.; Jeewandara, C.; Senadheera, B.; Kuruppu, H.; Wickramanayake, R.; Chathurangika, P.H.; Senatilleke, N.; Warnakulasuriya, N.; Bary, F.; Wijewickrama, A.; et al. Genomic Surveillance and Evolutionary Dynamics of Influenza A Virus in Sri Lanka. medRxiv 2024. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Yunker, M.; Villafuerte, D.A.; Fall, A.; Norton, J.M.; Abdullah, O.; Rothman, R.E.; Fenstermacher, K.Z.; Morris, C.; Pekosz, A.; Klein, E.; et al. Genomic evolution of influenza during the 2023–2024 season, the johns hopkins health system. J. Clin. Virol. 2024, 174, 105718. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Scotch, M.; Faleye, T.O.; Wright, J.M.; Finnerty, S.; Halden, R.U.; Varsani, A. Campus-based genomic surveillance uncovers early emergence of a future dominant A(H3N2) influenza clade. medRxiv 2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Separovic, L.; Zhan, Y.; Kaweski, S.E.; Sabaiduc, S.; Carazo, S.; Olsha, R.; Mather, R.G.; Dickinson, J.A.; Hasso, M.; Meunier, I.; et al. Interim estimates of vaccine effectiveness against influenza A(H1N1)pdm09 and A(H3N2) during a delayed influenza season, Canada, 2024/25. Euro Surveill. 2025, 30, 2500059. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Tsafack, D.T.; Monamele, C.G.; Moumbeket-Yifomnjou, M.H.; Essengue, L.L.M.; Bilounga, C.N.; Njankouo, M.R.; Touoyem, P.I.; Tamoufe, U.; Koro, F.K.; Njouom, R. Evolving Dynamics of Whole-Genome Influenza A/H3N2 Viruses Isolated in Cameroon. Adv. Virol. 2025, 2025, 3668615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Naeem, A.; Hakami, M.; Aljami, H.; Almiqbel, H.S.; Alzahrani, N.; Aljohani, S.; Bosaeed, M. Integrated Phenotypic-Genotypic Surveillance of Neuraminidase Inhibitor Susceptibility in Influenza A(H1N1), A(H3N2), and B/Victoria Viruses in Saudi Arabia, 2024–2025. J. Med. Virol. 2026, 98, e70796. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Dapat, C.; Peck, H.; Jelley, L.; Diefenbach-Elstob, T.; Slater, T.; Hussain, S.; Britton, P.; Cheng, A.C.; Wood, T.; Howard-Jones, A.; et al. Extended influenza seasons in Australia and New Zealand in 2025 due to the emergence of influenza A(H3N2) subclade K viruses. Euro Surveill. 2025, 30, 2500894, Erratum in Euro Surveill. 2025, 30, 251218c. https://doi.org/10.2807/1560-7917.ES.2025.30.50.251218c. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  48. Broberg, E.K.; Vukovikj, M.; Svartström, O.; Hasibra, I.; Riess, M.; Melidou, A. Members of the ERLI-Net Network. Antigenic Changes in Influenza A(H3N2) Driven by Genetic Evolution: Insights from Virological Surveillance, EU/EEA, Week 40/2023 to Week 9/2024. Euro Surveill. 2024, 29, 2400395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Kikawa, C.; Huddleston, J.; Loes, A.N.; Turner, S.A.; Lee, J.; Barr, I.G.; Cowling, B.J.; Englund, J.A.; Greninger, A.L.; Harvey, R.; et al. Near real-time data on the human neutralizing antibody landscape to influenza virus to inform vaccine-strain selection in September 2025. bioRxiv 2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Aliberti, S.M.; Schiavo, L.; Boccia, G.; Santoro, E.; Franci, G.; Ruggiero, A.; De Caro, F.; Capunzo, M. Gender and AB0 Blood Type Differences in a Unicentric Group of University Professors in Southern Italy Who Received the Vaxzevria COVID-19 Vaccine: A Cross-Sectional Survey of Vaccine Side Effects, Attitudes, and Hesitation. Vaccines 2022, 10, 373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Flow chart of the study selection process.
Germs 16 00018 g001
Table 1. Geographic distribution of included studies (n = 20).
Region/Arean%95% CI (Wilson)
Europe630.014.5–51.9
East and Southeast Asia525.011.2–46.9
South Asia15.00.9–23.6
North America315.05.2–36.0
Africa15.00.9–23.6
Middle East15.00.9–23.6
Oceania15.00.9–23.6
Multi-region/Global210.02.8–30.1
Table 2. Subclade focus across included studies.
Subclade Categoryn%95% CI (Wilson)
J/J-derived (incl. J.*)1575.053.1–88.8
K (J.2.4.1)420.08.1–41.6
Other clades/subclades210.02.8–30.1
Not reported15.00.9–23.6
* J-derived includes all viruses classified within the J lineage and its descendant subclades.
Table 3. Methodological composition of included studies.
Study Design Categoryn%95% CI (Wilson)
Surveillance/routine monitoring1260.038.7–78.1
Vaccine effectiveness420.08.1–41.6
Computational/modeling210.02.8–30.1
Clinical case series15.00.9–23.6
Immunology/neutralization15.00.9–23.6
Table 4. Coverage of outcome domains across included studies.
Outcome DomainStudies Addressing Domain n (%)95% CI (Wilson)Studies
Genomic surveillance18 (90.0%)69.9–97.2[30,31,32,33,34,35,36,37,38,39,40,41,42,43,45,47,48,49]
Antigenic characterization14 (70.0%)48.1–85.5[32,33,34,35,36,37,38,39,40,41,42,46,47,49]
Immune escape signals10 (50.0%)29.9–70.1[32,33,35,36,37,39,40,46,47,49]
Vaccine effectiveness assessed8 (40.0%)21.9–61.3[30,31,33,35,42,43,44,48]
Clinical outcomes reported5 (25.0%)11.2–46.9[41,44,45,46,47]
Surveillance/early warning signal6 (30.0%)14.5–51.9[36,37,40,45,48,49]
Policy relevance4 (20.0%)8.1–41.6[30,33,35,48]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.