Review

Types and Diagnosis of Childhood Intellectual Disabilities: Advancing Accuracy for Better Outcomes


1
Department of Physiology, RAK College of Medical Sciences, RAK Medical and Health Sciences University, Ras Al Khaimah 11172, United Arab Emirates
2
Department of Pathology, RAK College of Medical Sciences, RAK Medical and Health Sciences University, Ras Al Khaimah 11172, United Arab Emirates
3
Department of General Education, Psychology, RAK College of Medical Sciences, RAK Medical and Health Sciences University, Ras Al Khaimah 11172, United Arab Emirates
4
Department of Community Medicine, RAK College of Medical Sciences, RAK Medical and Health Sciences University, Ras Al Khaimah 11172, United Arab Emirates
*
Author to whom correspondence should be addressed.
Children 2025, 12(12), 1585; https://doi.org/10.3390/children12121585
Submission received: 26 October 2025 / Revised: 13 November 2025 / Accepted: 20 November 2025 / Published: 22 November 2025
(This article belongs to the Section Pediatric Neurology & Neurodevelopmental Disorders)

Highlights

What are the main findings?
Updated DSM-5-TR/ICD-11 criteria highlight adaptive functioning and standardized assessments for accurate ID diagnosis.
Genetic testing greatly improves identifying the underlying causes of ID.
What is the implication of the main finding?
Earlier and precise diagnosis enables timely interventions and better individualized outcomes.
Aetiology-based diagnosis strengthens prognosis, family counseling, and targeted management.

Abstract

Intellectual disability (ID)—termed intellectual developmental disorder in DSM-5-TR and disorders of intellectual development in ICD-11—is a heterogeneous spectrum of neurodevelopmental conditions characterized by impairments in general intellectual abilities and adaptive functioning, with onset during the developmental period. Precise and early recognition of ID can alter developmental trajectories by clarifying prognosis, guiding targeted genetic and medical investigations, initiating time-sensitive interventions, preventing diagnostic overshadowing, and informing educational planning and family counseling. This narrative review synthesizes contemporary diagnostic standards from DSM-5-TR and ICD-11, recent updates in epidemiology, and an aetiology-oriented framework for classifying “types” of intellectual disability. It further outlines current best practices in diagnostic work-up—including developmental surveillance and screening, standardized cognitive and adaptive assessments, genomic testing (microarray, exome/genome sequencing, and syndrome-specific assays), selective metabolic studies, and neuroimaging or EEG when indicated. Additionally, the review explores culturally responsive and equitable assessment, special diagnostic contexts (such as profound impairment, sensory and motor confounds, and bilingualism), and the frequent co-occurrence of other neurodevelopmental and medical disorders. The discussion concludes with practical, stepwise diagnostic pathways that clinicians can readily apply and anticipates emerging frontiers—such as genomic medicine and digital phenotyping—that promise to enhance diagnostic yield and clinical utility in the near future.

1. Introduction

According to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR), the condition termed Intellectual Developmental Disorder (Intellectual Disability) is diagnosed when three criteria are met: (i) deficits in intellectual functions identified through individually administered tests; (ii) concurrent limitations in adaptive functioning that restrict independence across conceptual, social, and practical domains; and (iii) onset during the developmental period [1]. In both DSM-5-TR and the International Classification of Diseases, 11th Revision (ICD-11), severity is categorized as mild, moderate, severe, or profound [2].
For clarity, the terms Intellectual Disability (ID), Intellectual Developmental Disorder (IDD) (DSM-5-TR), and Disorders of Intellectual Development (ICD-11) are used interchangeably in this review. The abbreviation ID is retained throughout for consistency with current clinical and research usage.
Crucially, this classification emphasizes adaptive functioning rather than IQ alone, as everyday competence provides a more accurate reflection of autonomy and social participation [3]. ICD-11 refers to the condition as Disorders of Intellectual Development (6A00) and requires standardized assessments demonstrating performance approximately two standard deviations below the population mean, accompanied by functional impairment [4]. To accommodate developmental variability, ICD-11 introduces a provisional category for very young children (typically under four years) or for those whose severe sensory or motor impairments preclude valid testing [5]. The 2024 Clinical Descriptions and Diagnostic Requirements (CDDR) further refine these criteria, offering harmonized thresholds suitable for cross-cultural application [6]. Figure 1 visually compares the diagnostic criteria for intellectual disability across DSM-5-TR and ICD-11, highlighting their convergences and nuanced distinctions.
Global point prevalence estimates for intellectual disability in the general population range from 1% to 3%, with variability largely reflecting methodological and definitional differences across studies [7]. Analyses based on GBD 2019 data suggest that approximately 1.4% of the global population was affected in 2019, though considerable regional variation persists. Complementary UNICEF and GBD syntheses highlight the broader spectrum of childhood developmental disabilities—encompassing hundreds of millions of children worldwide—within which intellectual disability constitutes a significant subset [8]. In U.S. surveillance data (NHIS 2019–2021), diagnosed intellectual disability among children aged 3–17 years remained stable at approximately 1.7–2.2%, despite an overall rise in developmental disability diagnoses [9]. Such variation reflects disparities in ascertainment, diagnostic criteria, and health-system infrastructure rather than biological differences. Detection is strongly influenced by developmental monitoring and screening policies. The American Academy of Pediatrics (AAP) currently recommends standardized developmental screening at 9, 18, and 30 months and autism-specific screening at 18 and 24 months, embedded within continuous developmental surveillance—an approach that also facilitates the earlier recognition of many children who are later diagnosed with intellectual disability [10]. Therefore, this review aims to comprehensively synthesize contemporary understanding of the classification and diagnostic frameworks for childhood intellectual disabilities, emphasizing how refinements in nosology and assessment can strengthen early recognition, inform intervention planning, and ultimately improve long-term developmental outcomes.

1.1. Types of Intellectual Disability: A Clinically Useful, Aetiology-Oriented Framing

Because DSM-5-TR and ICD-11 classify intellectual disability only by severity, clinicians and researchers often adopt an aetiology-based framework to enhance diagnostic clarity and management. This structure organizes causes by timing—prenatal, perinatal, and postnatal—and by causal category, including genetic, environmental, and acquired factors. Such an approach not only facilitates comprehensive diagnostic work-ups but also informs recurrence risk counselling and guides individualized management strategies [11]. (Figure 2 provides a visual synthesis of these major aetiologic categories—prenatal, perinatal, postnatal, and idiopathic—illustrating how temporal classification supports diagnostic reasoning and prevention planning.)

1.1.1. Prenatal Genetic Causes

Chromosomal copy number variants (e.g., 22q11.2 deletions), aneuploidies (e.g., trisomy 21), and single-gene disorders (such as FMR1 expansions, MECP2, TSC1/2, and UBE3A mutations) account for a significant proportion of moderate-to-severe intellectual disability. Contemporary genomic practice recognizes that exome and genome sequencing substantially increase diagnostic yield beyond that achieved with chromosomal microarray, often reshaping surveillance protocols and refining family counselling [12].

1.1.2. Prenatal Teratogenic and Infectious Exposures

Fetal alcohol spectrum disorders (FASDs) remain under-recognized despite their prevalence and preventability. Updated American Academy of Pediatrics (AAP) guidance emphasizes multidisciplinary diagnostic assessment and meticulous documentation of prenatal exposure. Congenital cytomegalovirus (CMV) infection—the most common congenital infection globally, occurring in approximately one in every 200 births in high-income regions—represents a major cause of sensorineural hearing loss and neurodevelopmental disability. The long-term cognitive and functional sequelae of CMV vary considerably depending on whether the infant was symptomatic at birth [13,14].
Beyond CMV, other congenital infections within the TORCHES spectrum—namely Toxoplasma gondii, Rubella virus, Treponema pallidum, Herpes simplex virus, and emerging pathogens such as Zika virus—are also established causes of neurodevelopmental impairment and intellectual disability. Their prevention through maternal screening, vaccination (for rubella), and infection control during pregnancy remains a cornerstone of global public health efforts to reduce congenital neurodisability [15].

1.1.3. Perinatal Complications and Postnatal Causes

Perinatal factors such as extreme prematurity, neonatal encephalopathy, and severe hyperbilirubinemia significantly elevate the risk of intellectual impairment. These are best conceptualized through the lens of early brain injury and disrupted neuronal connectivity, though advances in neonatal intensive care continue to mitigate risk [16].
Postnatal or acquired causes include severe traumatic brain injury, meningitis or encephalitis, and chronic exposure to environmental toxins, particularly lead. Recognizing the neurotoxic impact of even low-level exposure, the U.S. Centers for Disease Control and Prevention (CDC) lowered the blood lead reference value to 3.5 µg/dL in 2021 to prompt earlier intervention [17].

1.1.4. Idiopathic or Cryptogenic Intellectual Disability

Despite extensive diagnostic evaluation, a subset of cases remains unresolved and is thus classified as idiopathic or cryptogenic. However, this fraction continues to decline as genomic technologies advance and periodic reanalysis of previously nondiagnostic exome data yields new gene–disease associations and additional molecular diagnoses over time [18].

2. Diagnosis

Establishing an accurate diagnosis of intellectual disability is pivotal, as it directly determines management strategies, intervention pathways, and long-term outcomes [19]. Identifying a specific etiology, whether genetic, teratogenic, or acquired, guides clinical care in several critical ways: it clarifies the natural history of the condition, identifies comorbidity risks such as epilepsy or cardiac and renal anomalies within syndrome-specific contexts, and informs anticipatory medical surveillance [20]. A precise diagnostic conclusion also facilitates targeted therapeutic interventions, such as the use of mTOR inhibitors in tuberous sclerosis, streamlines educational and behavioral planning, and provides families with accurate recurrence-risk counselling [21]. Moreover, prompt and confident diagnostic confirmation helps prevent prolonged diagnostic delays and repeated evaluations across multiple providers, reducing the emotional and financial strain often experienced by families seeking answers [22].
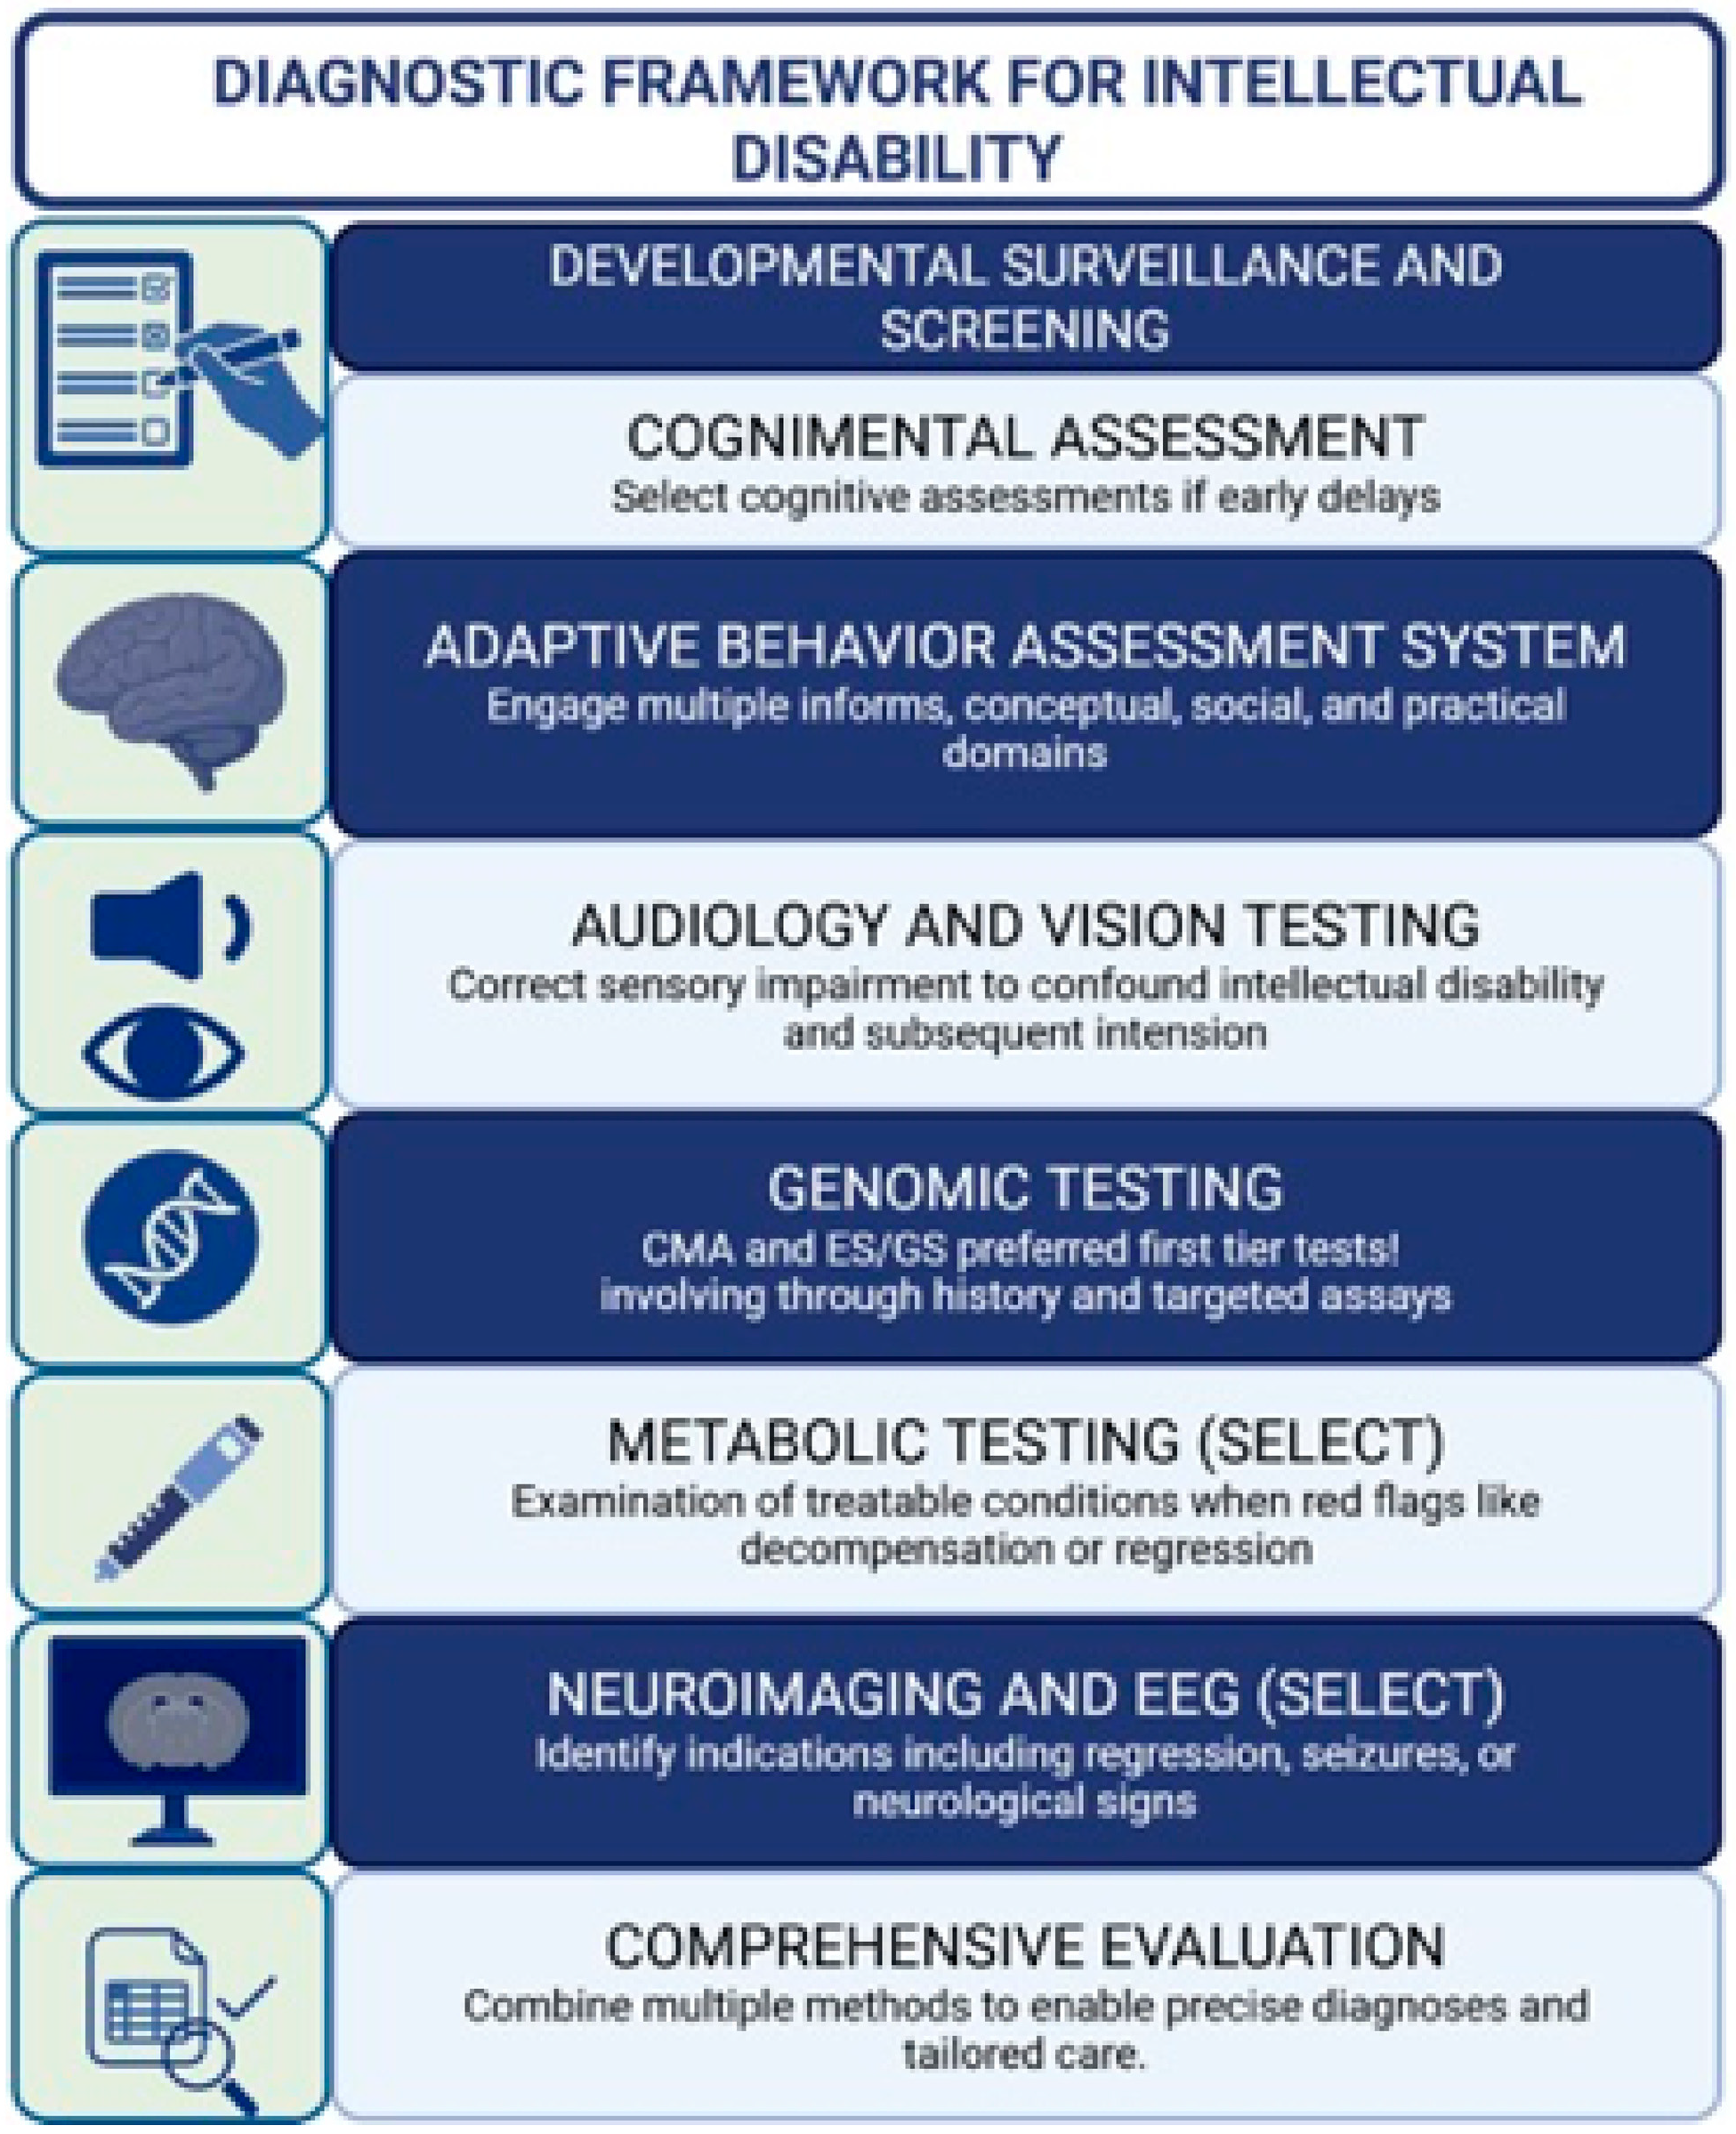
Diagnosis begins even before formal testing, with the developmental assessment itself (Figure 3). Attentive listening to parental concerns, detailed review of developmental milestones, appraisal of prenatal and perinatal exposures, and awareness of social determinants often yield the earliest indicators of developmental delay [23,24]. The American Academy of Pediatrics (AAP) recommends standardized developmental screening at 9, 18, and 30 months, along with autism-specific screening at 18 and 24 months, integrated into continuous developmental surveillance at every well-child visit. Importantly, referral for early intervention should proceed without delay, even in the absence of a confirmed aetiologic label [25]. (Figure 3 summarizes this diagnostic framework—from developmental screening to comprehensive evaluation—illustrating how each assessment domain contributes to timely recognition and personalized management.)
When standardized testing is undertaken, cognitive assessment forms the cornerstone of diagnostic evaluation. For infants and toddlers, the Bayley Scales of Infant and Toddler Development, Fourth Edition (Bayley-4) remains the gold standard, assessing cognitive, language, and motor domains from 16 days to 42 months of age [26]. In preschool years, the Wechsler Preschool and Primary Scale of Intelligence, Fourth Edition (WPPSI-IV), offers early cognitive profiles, while the Wechsler Intelligence Scale for Children, Fifth Edition (WISC-V), is standard for ages 6–16, providing index scores aligned with DSM-5-TR and ICD-11 domains [27]. For children with significant language or hearing limitations, or those from linguistically diverse backgrounds, the Leiter International Performance Scale, Third Edition (Leiter-3), serves as a fully nonverbal alternative, spanning ages 3–75 [28]. Selection of the most appropriate instrument should be individualized, taking into account linguistic, sensory, and motor factors, as well as cultural context. Interpretation of results must extend beyond numerical scores to include qualitative observations and performance validity [29].
Because the classification of severity in intellectual disability is primarily based on adaptive functioning rather than IQ scores alone, every comprehensive evaluation should incorporate a norm-referenced measure of adaptive behaviour. The Vineland Adaptive Behavior Scales, Third Edition (Vineland-3), and the Adaptive Behavior Assessment System, Third Edition (ABAS-3), are among the most widely used instruments, each providing standardized domain and composite scores across conceptual, social, and practical areas of functioning. To ensure accuracy, information should be gathered from multiple informants—such as parents, teachers, and caregivers—as reliance on a single rater can introduce bias and may not fully capture the child’s performance across different settings [30].
Audiologic and visual assessments are foundational to any diagnostic process. Unrecognized sensory impairment can mimic or exacerbate cognitive deficits, and since interventions in this domain are often actionable, hearing and vision testing should precede or accompany cognitive evaluation [31].
The genomic era has revolutionized diagnostic pathways. The American College of Medical Genetics and Genomics (ACMG) now recommends exome or genome sequencing (ES/GS) as a first- or second-tier test for children presenting with developmental delay, congenital anomalies, or intellectual disability [32]. These techniques demonstrate higher diagnostic yield and greater cost-effectiveness when implemented early, outperforming chromosomal microarray (CMA), though CMA continues to hold value as an initial investigation. Fragile X testing remains crucial, particularly in males or where family history is suggestive [33]. The 2025 AAP clinical report offers a structured algorithm integrating comprehensive history-taking, physical examination, CMA, ES/GS, and phenotype-directed assays such as methylation testing for Prader–Willi or Angelman syndromes, and MECP2 analysis in girls with Rett-like regression [34,35]. Periodic reanalysis of previously nondiagnostic exomes is strongly encouraged as gene–disease associations continue to expand. Evidence from real-world studies confirms that exome sequencing not only enhances diagnostic yield but also produces tangible improvements in medical management, especially in conditions requiring syndrome-specific surveillance [36].
Metabolic testing, though no longer routinely indicated for all cases, remains essential when specific red flags are present—such as episodic metabolic decompensation, developmental regression, multisystem involvement, or consanguinity. Many contemporary protocols now employ a “screen-for-treatable” strategy to ensure that rare but actionable disorders are not missed [37].
Neuroimaging and electroencephalography (EEG) play targeted but important roles. Brain MRI is recommended when neurological abnormalities, seizures, atypical head growth, or developmental regression are observed, while EEG should be performed in the presence of suspected epilepsy or unexplained paroxysmal episodes. Diagnostic yield is maximized when these investigations are guided by neurological examination and phenotypic cues, rather than applied indiscriminately [38].
Environmental and teratogenic factors must also be considered as part of a comprehensive evaluation. The CDC currently defines a blood lead reference value of 3.5 µg/dL as the threshold for clinical intervention. Fetal alcohol spectrum disorders (FASDs) require multidisciplinary assessment following updated AAP diagnostic frameworks. Congenital cytomegalovirus (CMV) should be a strong consideration in infants presenting with hearing loss, microcephaly, or characteristic neuroimaging findings. Several regions have initiated universal or targeted newborn CMV screening programs to facilitate early antiviral therapy and structured audiological follow-up [17,39].
Collectively, this integrative diagnostic framework underscores that the goal of diagnosis extends far beyond classification—it is the key to transforming care through earlier recognition, precision in assessment, and equitable access to timely interventions.
Figure 3 illustrates the sequential diagnostic pathway, emphasizing the integration of developmental surveillance, cognitive and adaptive testing, and tiered investigations to achieve timely and precise diagnosis. This helps clinicians visualize how each assessment domain contributes to a comprehensive diagnostic picture.
By combining structured developmental surveillance, robust cognitive and adaptive assessments, early genetic testing, and judicious use of metabolic, neuroimaging, and environmental evaluations, clinicians can achieve earlier and more precise diagnoses. This approach directly improves outcomes by enabling tailored medical care, timely interventions, and equitable access to services for children and families affected by intellectual disabilities [40,41].

2.1. Differential Diagnosis and Frequent Co-Occurrences

Intellectual disability (ID) seldom occurs in isolation; it is frequently associated with other neurodevelopmental and medical conditions. Commonly co-occurring disorders include autism spectrum disorder (ASD), attention-deficit/hyperactivity disorder (ADHD), language impairments, epilepsy, and motor coordination disorders. Recognizing and delineating these overlapping presentations is essential to prevent diagnostic overshadowing, a phenomenon in which the presence of one condition obscures recognition of another [42].
Recent U.S. surveillance data indicate that approximately 40% of eight-year-old children diagnosed with ASD also meet IQ-based criteria for ID, underscoring the reciprocal need to evaluate both cognitive and adaptive functioning in autism assessments and to screen for autism traits among children already diagnosed with ID [43]. In addition, unrecognized hearing or vision impairments, as well as severe speech–motor limitations, may artificially lower cognitive test scores, thus mimicking intellectual impairment. Comprehensive sensory evaluations and the use of suitable accommodations—such as nonverbal cognitive measures (e.g., Leiter-3) and augmentative or alternative communication supports—are therefore critical to ensure valid assessment outcomes [44,45].
Effective differential diagnosis requires a cohesive, multidisciplinary approach that integrates neurological, psychological, and developmental expertise. Such collaboration allows clinicians to capture the interplay between neurodevelopmental disorders, medical comorbidities, and sensory or motor constraints, ultimately yielding a precise functional profile that guides both intervention and prognostic planning [46].

2.2. Special Diagnostic Scenarios

Certain clinical situations necessitate adapted diagnostic approaches to ensure validity and fairness. Profound intellectual impairment or very early developmental age presents particular challenges, as conventional IQ testing may not provide reliable results. In these cases, developmentally anchored instruments such as the Bayley Scales of Infant and Toddler Development, Fourth Edition (Bayley-4), are preferred. The ICD-11 also allows the use of a provisional category in situations where formal testing cannot be appropriately conducted due to age or severe sensory and motor impairments [47,48]. Diagnostic emphasis in such instances should shift toward evaluating adaptive behaviour, identifying coexisting medical conditions, and ensuring immediate access to early intervention services while the etiologic investigation—most often genetic—proceeds in parallel [49].
In bilingual and culturally diverse children, diagnostic accuracy relies heavily on fairness and contextual sensitivity. Instruments that minimize linguistic demands, such as the Leiter-3, are recommended, along with the engagement of trained interpreters and the collection of collateral data from multiple environments, including home, school, and community. This methodology aligns with DSM-5-TR’s emphasis on equitable assessment practices and the World Health Organization’s Clinical Descriptions and Diagnostic Requirements (CDDR), both of which prioritize cross-cultural validity to reduce the risk of misclassification [50,51].
When sensory or motor confounds are present, collaboration with audiologists and ophthalmologists is essential. Testing environments should be adapted accordingly, and when fine-motor output is substantially limited, clinicians should select assessment tools that minimize motor demands. Observational methods and dynamic, learning-potential assessments—used alongside standardized testing—can provide a more authentic representation of a child’s cognitive and adaptive capacities [52].
Figure 4 summarizes adapted diagnostic strategies for complex presentations such as profound impairment, bilingual or culturally diverse children, and cases with sensory or motor confounds, underscoring the need for fairness and individualized assessment.

2.3. From Diagnosis to Outcome

Accurate and timely diagnosis forms the cornerstone of effective care, as it profoundly influences both immediate interventions and long-term developmental outcomes. Early identification facilitates prompt access to early intervention services, individualized educational programs, and structured family support systems, all of which are known to markedly improve developmental trajectories and adaptive functioning. Moreover, a precise diagnosis enables syndrome-specific surveillance, allowing clinicians to anticipate and monitor comorbidities such as epilepsy, cardiac anomalies, and metabolic disturbances before they become clinically apparent [53,54].
Timely diagnosis also mitigates the emotional and financial toll of prolonged diagnostic odysseys by reducing unnecessary or repetitive investigations. Importantly, an established etiologic diagnosis allows affected children to be enrolled in condition-specific registries and clinical trials, thereby advancing research and opening opportunities for participation in emerging targeted therapies. For families, genetic clarification provides essential recurrence-risk counseling, supporting informed reproductive decision-making and facilitating long-term psychosocial adjustment [55,56].
Consensus statements increasingly affirm that genetic diagnoses directly influence care by refining surveillance strategies, guiding therapeutic planning, and informing family counseling. Furthermore, evidence suggests that genetic testing is most cost-effective when integrated early in the diagnostic process, rather than after exhaustive conventional investigations. Ultimately, diagnostic timeliness transforms the process from a purely descriptive exercise into a dynamic, action-oriented tool that enhances intervention outcomes, ensures equitable access to care, and improves the overall quality of life for children and their families [57].

2.4. Practical, Stepwise Pathway You Can Implement Now

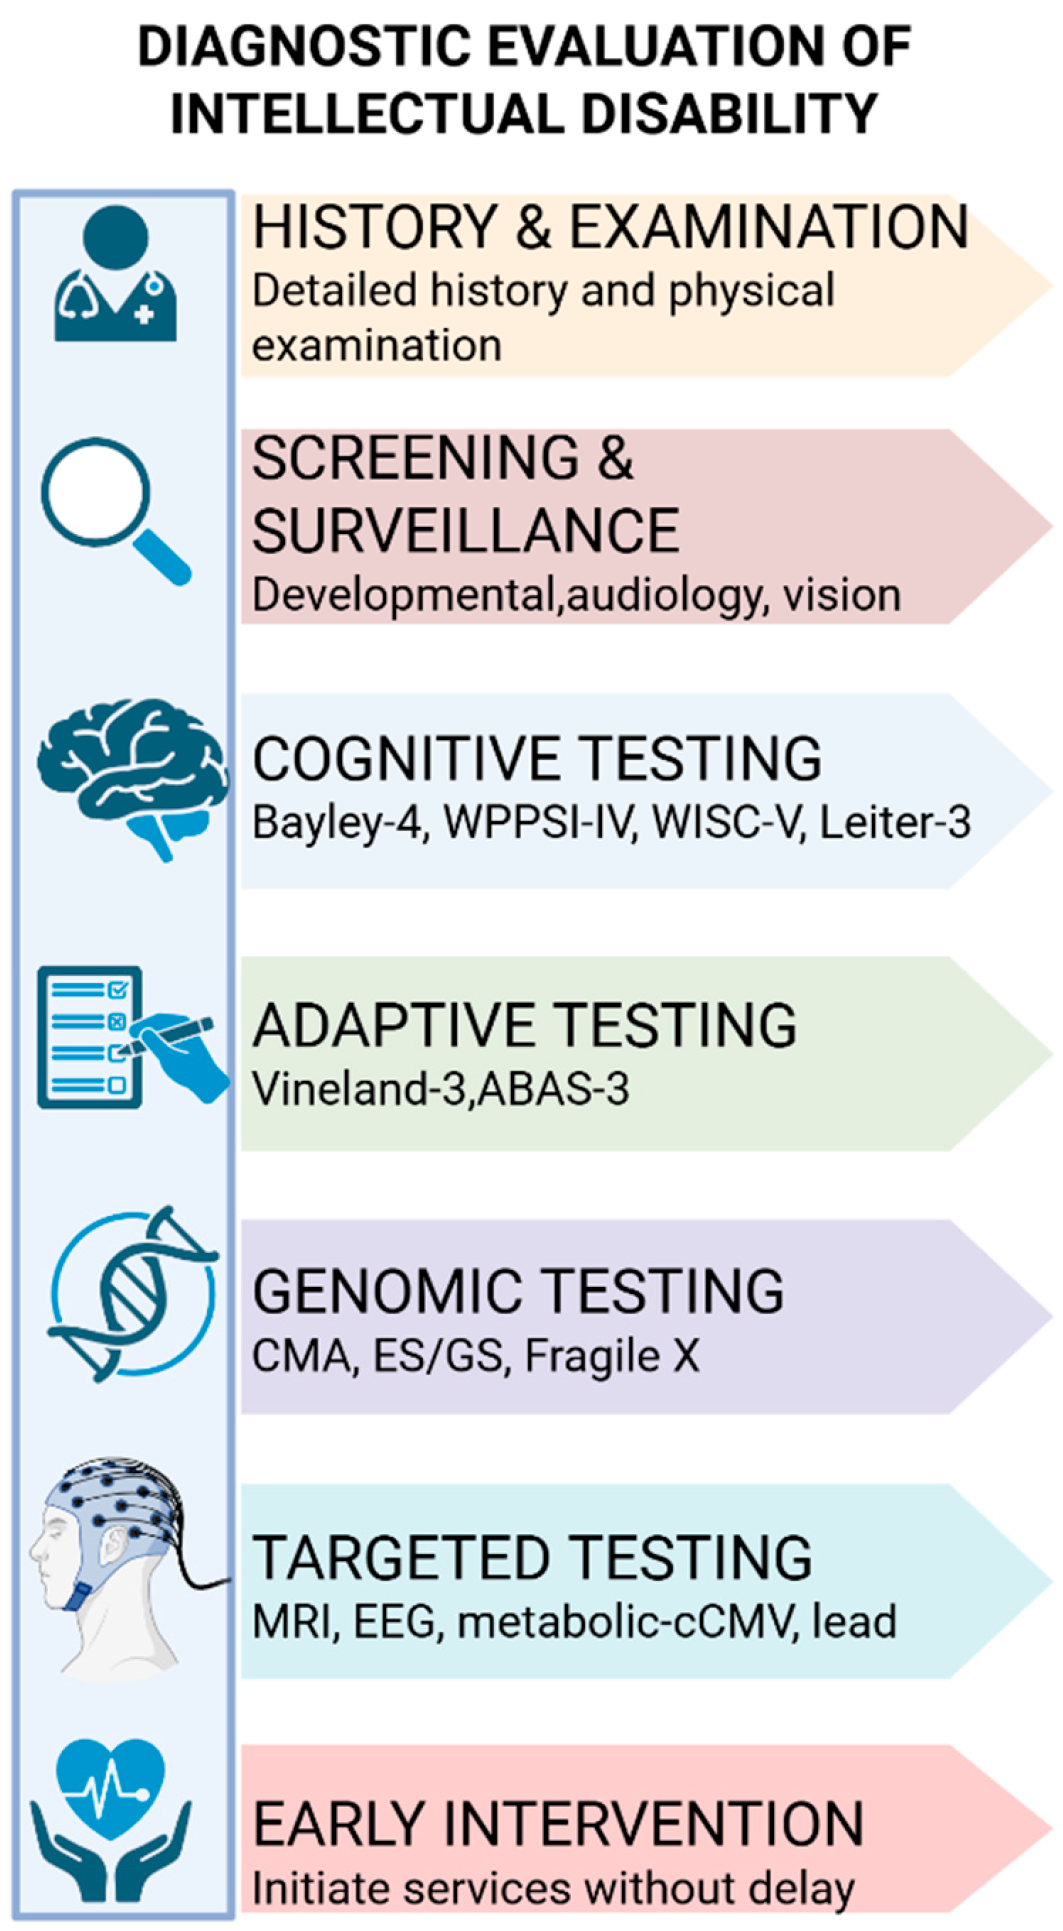
A structured, stepwise diagnostic pathway ensures precision, efficiency, and continuity of care in evaluating intellectual disability. The process begins with a comprehensive medical history and physical examination, encompassing detailed prenatal, perinatal, and postnatal exposures, as well as a thorough family history to identify potential hereditary or environmental factors. This foundation is complemented by developmental surveillance and standardized screening, together with audiologic and visual evaluations, since uncorrected sensory impairments may mimic or aggravate cognitive limitations [58,59].
Cognitive and adaptive assessments should then be tailored to the child’s developmental level. The Bayley Scales of Infant and Toddler Development, Fourth Edition (Bayley-4), remain optimal for infants and toddlers, while the Wechsler Preschool and Primary Scale of Intelligence, Fourth Edition (WPPSI-IV), and the Wechsler Intelligence Scale for Children, Fifth Edition (WISC-V), are appropriate for preschool and school-age groups, respectively. Nonverbal instruments such as the Leiter International Performance Scale, Third Edition (Leiter-3), are particularly valuable for children with limited speech or hearing. Assessment of adaptive functioning using the Vineland-3 or ABAS-3 is indispensable, as contemporary classifications determine severity primarily through adaptive abilities rather than IQ alone [60,61].
Genomic testing should be initiated in accordance with best-practice guidelines. Standard evaluation includes chromosomal microarray (CMA) and exome or genome sequencing (ES/GS), supplemented by Fragile X testing when indicated, particularly in males or where family history suggests risk. Additional targeted studies—such as methylation assays for Prader–Willi or Angelman syndromes—are warranted when the phenotype is suggestive. Given rapid advances in genomic interpretation, periodic reanalysis of previously nondiagnostic exomes is advised to capture new gene–disease associations [62,63].
When “red-flag” features are present—such as developmental regression, episodic metabolic crises, multisystem involvement, or parental consanguinity—metabolic testing should be incorporated, following a “screen-for-treatables” model. Neuroimaging (MRI) is recommended in the presence of neurological abnormalities, seizures, or atypical head growth, while EEG should be reserved for suspected epilepsy or unexplained paroxysmal episodes [64,65].
Environmental and infectious factors must also be addressed. In infants with suspicious clinical features, congenital cytomegalovirus (cCMV) should be confirmed or excluded promptly because of its implications for antiviral therapy and auditory follow-up. In at-risk populations, blood lead screening should follow the CDC’s 3.5 µg/dL reference threshold to guide early intervention.
Above all, developmental therapy and family support should begin as soon as delays are identified—well before the etiologic investigation is complete. This parallel, integrated approach—combining comprehensive assessment, tiered investigations, and early therapeutic engagement—maximizes developmental potential while minimizing diagnostic delays [66,67].
Figure 5 outlines the structured, stepwise approach from clinical history to targeted investigations, clarifying the parallel processes of evaluation and early intervention that optimize developmental outcomes.

3. Methodological and Ethical Considerations in Assessment

Validity and Fairness:
Standardized measures of intellectual and adaptive functioning are indispensable for diagnosis but not without limitations. All IQ and adaptive behavior instruments contain inherent measurement error, and results may be influenced by rater bias, cultural or linguistic mismatch, or limited familiarity with formal testing contexts [68].
Standardized measures of intellectual and adaptive functioning are indispensable for diagnosis but not without limitations. All IQ and adaptive behavior instruments contain inherent measurement error, and results may be influenced by rater bias, cultural or linguistic mismatch, or limited familiarity with formal testing contexts. It is also important to recognize that most standardized IQ tests are culturally bound and normed primarily on Western populations. Consequently, they may have limited validity or availability in many regions, underscoring the urgent need for culturally adapted measures and context-sensitive interpretation to ensure diagnostic fairness worldwide [68,69].
Ongoing psychometric discussions—such as those surrounding the structural properties of the Vineland-3—underscore the need for cautious and contextual interpretation. Clinicians are therefore advised to synthesize findings from multiple informants and environments rather than relying on rigid numerical cut-offs. The DSM-5-TR’s deliberate shift toward adaptive functioning was designed, in part, to minimize the risk of misclassification arising from IQ-based thresholds that fail to capture real-world competence [70].
Equity:
Access to comprehensive diagnostic evaluation is uneven across populations. Socioeconomic disparities, geographic isolation, and fragmented healthcare infrastructure frequently delay both assessment and intervention, disproportionately affecting children in underserved settings. Embedding developmental surveillance and screening within primary care—an approach strongly recommended by the American Academy of Pediatrics—and facilitating first-line genetic testing at the point of initial clinical suspicion can significantly reduce these inequities. Culturally equitable assessment also requires sensitivity to linguistic and contextual variation, ensuring that diagnostic tools, normative data, and interpretive frameworks reflect the child’s sociocultural background [71].
Communication:
Ethical diagnostic practice extends beyond accuracy to the quality of communication. Families should receive results in clear, empathetic, and family-centered language that highlights both the child’s strengths and areas of need, accompanied by practical next steps. Guidance should encompass educational rights, access to community-based services, and long-term planning, with recommendations revisited periodically as the child develops. Transparent, compassionate communication reduces stigma, promotes family coping, and fosters collaborative decision-making [72].

Emerging Frontiers Likely to Raise Diagnostic Yield and Utility

Rapid technological and clinical advances are reshaping the diagnostic landscape for intellectual disabilities. Genome sequencing and reanalysis pipelines represent a leading frontier: as variant databases expand and bioinformatic tools mature, periodic reanalysis of previously nondiagnostic exomes or genomes is increasingly yielding new insights. Whole-genome sequencing (GS) extends beyond exome sequencing (ES) by detecting structural and noncoding variants, thereby closing long-standing diagnostic gaps [73].
Condition-specific newborn screening and targeted early detection offer another promising direction. Several jurisdictions are now piloting universal or risk-based newborn screening for congenital cytomegalovirus (CMV)—the most common congenital infection worldwide. Early identification enables timely antiviral therapy and structured audiologic monitoring, with broader adoption anticipated as cost-effectiveness evidence grows. Comparable strategies may eventually extend to other genetic and metabolic disorders as novel therapeutic interventions become available [74].
Digital phenotyping and remote assessment are also expanding diagnostic accessibility. Tele-practice adaptations of adaptive behavior scales, such as the Vineland-3, demonstrated strong feasibility and scalability during the COVID-19 pandemic. Hybrid diagnostic models—combining in-clinic standardized testing with caregiver-reported data and digital behavioral metrics—are increasingly validated, reducing access barriers while maintaining psychometric integrity [75].
Gene-directed therapies further highlight the transformative impact of precise molecular diagnosis. In monogenic neurodevelopmental syndromes, genetic findings already guide condition-specific monitoring and targeted interventions—for example, mTOR inhibition in tuberous sclerosis. The expanding range of targeted therapies underscores the urgency of early and accurate diagnosis, as molecular confirmation determines eligibility for disease-modifying treatments and participation in clinical trials [76,77].
Together, these emerging frontiers depict a future in which diagnosis is dynamic rather than static—continually refined through genomic discovery, digital innovation, and translational therapeutics. Precision in classification will increasingly intersect with precision in intervention, ensuring that diagnostic advances translate directly into improved outcomes. (Figure 6 conceptually integrates these frontiers, linking genetic reanalysis, digital phenotyping, and gene-targeted therapies within a unified precision-diagnosis framework.)
Figure 6 conceptually links ongoing advances—genomic reanalysis, digital phenotyping, and gene-directed therapies—to a dynamic, precision-based model of diagnosis that continually evolves with scientific progress.

4. Future Directions

4.1. Personalized In Vivo Gene Editing

A recent landmark—the first personalized CRISPR-based therapy delivered via lipid nanoparticles to treat a newborn with severe CPS1 deficiency—demonstrates how precision gene editing can be rapidly tailored to individual genetic conditions. This modular, patient-specific approach may soon translate into early, etiologically targeted treatments for select monogenic intellectual disability syndromes [78].

4.2. Affordable Gene Therapy Scale-Up

The Innovative Genomics Institute (IGI) is actively developing strategies for reducing the cost of genetic and genome-editing therapies by up to tenfold through novel funding models, manufacturing innovations, and alternative licensing strategies. This cost paradigm shift could make cutting-edge genomic treatments far more accessible across diverse healthcare settings [79].

4.3. Gene-Editing for Chromosome-Level Disorders

CRISPR-Cas9 has been recently applied to remove the extra copy of chromosome 21 in cells from individuals with Down syndrome, normalizing gene expression and cellular growth patterns. While ethically and technically complex, such approaches suggest a future in which previously intractable aneuploid conditions might one day be addressed at a cellular or even organismal level [80].

4.4. New FDA-Approved Oral Therapy for Phenylketonuria (PKU)

In July 2025, the U.S. FDA approved Sephience, a novel oral drug that significantly increases phenylalanine hydroxylase (PAH) activity, lowering blood phenylalanine by ~63% in PKU patients and easing dietary restrictions. PKU is a classic cause of intellectual disability when untreated, so this advancement underscores how a diagnostic label can now directly guide a small-molecule intervention with major quality-of-life implications.

4.5. Integrating Emerging Therapeutics with Diagnostic Frameworks

Collectively, these emerging innovations—from gene editing and affordable genomic therapies to digital phenotyping and condition-specific screening—represent the translational continuum of the diagnostic principles outlined earlier in this review. The precision emphasized in DSM-5-TR, ICD-11, and the Clinical Descriptions and Diagnostic Requirements (CDDR)—with their focus on adaptive functioning, developmental context, and equitable access—forms the foundation upon which these novel interventions rest. Accurate and early diagnosis enables timely enrollment in gene-based trials, identification of targetable pathways, and informed family counseling, transforming the diagnostic process from a static classification into a gateway for precision therapy. Thus, advances in diagnostic accuracy and therapeutic innovation are mutually reinforcing, converging toward a unified vision of personalized, equitable care for children with intellectual disabilities.

5. Conclusions

Childhood intellectual disability is both common and heterogeneous, yet importantly, it is also actionable. Contemporary nosologies such as the DSM-5-TR and ICD-11 have shifted diagnostic emphasis from IQ thresholds to adaptive functioning, aligning classification more closely with lived abilities, support needs, and real-world outcomes. This conceptual change underscores the centrality of functional skills in guiding eligibility for services and intervention planning.
The diagnostic pathway that delivers the greatest clinical gains is also the most parsimonious: begin with vigilant listening, developmental surveillance, and early screening; evaluate cognition and adaptive behavior with age-appropriate, culturally fair tools; and implement genomic testing—preferably exome or genome sequencing—early in the process, supplemented by phenotype-driven targeted studies. Additional investigations, including metabolic screening, neuroimaging, EEG, and environmental or teratogenic evaluations, should be undertaken selectively when red flags are present. Crucially, early intervention must commence as soon as developmental delays are detected, without waiting for the full etiologic work-up to conclude.
When applied consistently, this framework shortens the diagnostic odyssey, reduces inequities in access to care, and transforms diagnosis from a static label into a dynamic platform for personalized surveillance, timely intervention, and family-centered planning. Looking ahead, the integration of genomic medicine, digital phenotyping, and emerging gene-directed therapies holds the potential not only to refine diagnostic yield but also to open pathways for targeted treatments. By advancing diagnostic accuracy and ensuring equitable access, clinicians and policymakers can measurably improve the developmental trajectories and quality of life of children and families affected by intellectual disability.

Author Contributions

Writing—original draft preparation, R.B. and M.M.S.; writing—review and editing, R.B., R.A.S., H.K.A. and M.M.S.; supervision, R.A.S. and H.K.A. Visualization; R.B. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

Not applicable.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

The following abbreviations are used in this manuscript:
IDIntellectual disability
DSM-5-TRDiagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision
ICD-11International Classification of Diseases, 11th Revision
CDDRClinical Descriptions and Diagnostic Requirements
GBDGlobal Burden Disease
AAPAmerican Academy of Pediatrics
ASDAutism Spectrum Disorder
FASDFatal alcohol spectrum disorders
WPPSIWechsler Preschool and Primary Scale of Intelligence—Fourth Edition
WISC-VWechsler Intelligence Scale for Children—Fifth Edition
Vineland-3Vineland Adaptive Behavior Scales, Third Edition
ABAS-3Adaptive Behavior Assessment System, Third Edition
ACMGAmerican College of Medical Genetics and Genomics
CMAChromosomal Microarray
EEGElectroencephalography
CMVCongenital cytomegalovirus
ADHDAttention-deficit/hyperactivity disorder
IGIInnovative Genomics Institute

References

  1. Regier, D.A.; Kuhl, E.A.; Kupfer, D.J. The DSM-5: Classification and criteria changes. World Psychiatry 2013, 12, 92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Committee to Evaluate the Supplemental Security Income Disability Program for Children with Mental Disorders; Board on the Health of Select Populations; Board on Children, Youth, and Families; Institute of Medicine; Division of Behavioral and Social Sciences and Education; The National Academies of Sciences, Engineering, and Medicine. 9 Clinical Characteristics of Intellectual Disabilities. In Mental Disorders and Disabilities Among Low-Income Children; Boat, T.F., Wu, J.T., Eds.; National Academies Press: Washington, DC, USA, 2015. Available online: https://www.ncbi.nlm.nih.gov/books/NBK332877/ (accessed on 1 November 2025).
  3. APA (American Psychiatric Association). Diagnostic and Statistical Manual of Mental Disorders, 5th ed.; APA: Washington, DC, USA, 2013. [Google Scholar]
  4. Bertelli, M.O.; Munir, D.K.; Harris, D.J.; Salvador-Carulla, D.L. “Intellectual developmental disorders”: Reflections on the international consensus document for redefining “mental retardation-intellectual disability” in ICD-11. Adv. Ment. Health Intellect. Disabil. 2016, 10, 36. [Google Scholar] [CrossRef] [Scilit]
  5. Stein, D.J.; Szatmari, P.; Gaebel, W.; Berk, M.; Vieta, E.; Maj, M.; Roest, A.M.; Maercker, A.; Brewin, C.R.; Pike, K.M.; et al. Mental, behavioral and neurodevelopmental disorders in the ICD-11: An international perspective on key changes and controversies. BMC Med. 2020, 18, 21. [Google Scholar] [CrossRef] [Scilit]
  6. Kestel, D.; Reed, G.M. Global launch of the ICD-11 Clinical Descriptions and Diagnostic Requirements (CDDR). World Psychiatry 2024, 23, 310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. McBride, O.; Heslop, P.; Glover, G.; Taggart, T.; Hanna-Trainor, L.; Shevlin, M.; Murphy, J. Prevalence estimation of intellectual disability using national administrative and household survey data: The importance of survey question specificity. Int. J. Popul. Data Sci. 2021, 6, 1342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Olusanya, B.O.; Kancherla, V.; Shaheen, A.; Ogbo, F.A.; Davis, A.C. Global and regional prevalence of disabilities among children and adolescents: Analysis of findings from global health databases. Front. Public Health 2022, 10, 977453. [Google Scholar] [CrossRef] [Scilit]
  9. Zablotsky, B.; Ng, A.E.; Black, L.I.; Blumberg, S.J. Diagnosed Developmental Disabilities in Children Aged 3–17 Years: United States, 2019–2021; NCHS Data Brief, no 473; National Center for Health Statistics: Hyattsville, MD, USA, 2023. [CrossRef] [Scilit]
  10. Zubler, J.M.; Wiggins, L.D.; Macias, M.M.; Whitaker, T.M.; Shaw, J.S.; Squires, J.K.; Pajek, J.A.; Wolf, R.B.; Slaughter, K.S.; Broughton, A.S.; et al. Evidence-informed milestones for developmental surveillance tools. Pediatrics 2022, 149, e2021052138. [Google Scholar] [CrossRef] [Scilit]
  11. Eisma, M.C. Prolonged grief disorder in ICD-11 and DSM-5-TR: Challenges and controversies. Aust. New Zealand J. Psychiatry 2023, 57, 944. [Google Scholar] [CrossRef] [Scilit]
  12. Cai, M.; Lin, N.; Su, L.; Wu, X.; Xie, X.; Li, Y.; Lin, Y.; Huang, H.; Xu, L. Prenatal diagnosis of 22q11.2 copy number abnormalities in fetuses via single nucleotide polymorphism array. Mol. Biol. Rep. 2020, 47, 7529. [Google Scholar] [CrossRef] [Scilit]
  13. Hoyme, H.E.; Kalberg, W.O.; Elliott, A.J.; Blankenship, J.; Buckley, D.; Marais, A.S.; Manning, M.A.; Robinson, L.K.; Adam, M.P.; Abdul-Rahman, O.; et al. Updated Clinical Guidelines for Diagnosing Fetal Alcohol Spectrum Disorders. Pediatrics 2016, 138, e20154256. [Google Scholar] [CrossRef] [Scilit]
  14. Hur, Y.M.; Choi, J.; Park, S.; Oh, S.S.; Kim, Y.J. Prenatal maternal alcohol exposure: Diagnosis and prevention of fetal alcohol syndrome. Obstet. Gynecol. Sci. 2022, 65, 385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Devaraju, M.; Li, A.; Ha, S.; Li, M.; Shivakumar, M.; Li, H.; Nishiguchi, E.P.; Gérardin, P.; Waldorf, K.A.; Al-Haddad, B.J. Beyond TORCH: A narrative review of the impact of antenatal and perinatal infections on the risk of disability. Neurosci. Biobehav. Rev. 2023, 153, 105390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Volpe, J.J. The Encephalopathy of Prematurity—Brain Injury and Impaired Brain Development Inextricably Intertwined. Semin. Pediatr. Neurol. 2009, 16, 167. [Google Scholar] [CrossRef] [Scilit]
  17. Paulson, J.A.; Brown, M.J. The CDC blood lead reference value for children: Time for a change. Environ. Health 2019, 18, 16. [Google Scholar] [CrossRef] [Scilit]
  18. Savatt, J.M.; Myers, S.M. Genetic Testing in Neurodevelopmental Disorders. Front. Pediatr. 2021, 9, 526779. [Google Scholar] [CrossRef] [Scilit]
  19. Doody, O.; Cithambaram, K.; Ryan, J.; Ryan, R.; Conway, M.; Corby, D. Indicators for Intellectual Disability Where No Formal Diagnosis Exists but Nursing Knowledge Demonstrates Grounds for a Formal Assessment: A Scoping Review. Healthcare 2024, 13, 1489. [Google Scholar] [CrossRef] [Scilit]
  20. Lee, S.; Kim, S.H.; Kim, B.; Lee, S.T.; Choi, J.R.; Kim, H.D.; Lee, J.S.; Kang, H.C. Genetic diagnosis and clinical characteristics by etiological classification in early-onset epileptic encephalopathy with burst suppression pattern. Epilepsy Res. 2020, 163, 106323. [Google Scholar] [CrossRef] [Scilit]
  21. Curatolo, P.; Moavero, R. mTOR Inhibitors in Tuberous Sclerosis Complex. Curr. Neuropharmacol. 2012, 10, 404–415. [Google Scholar] [CrossRef]
  22. Superson, W.; Prokopiak, A.; Wodziński, M. Experiences of an Autism Diagnosis in Adulthood: The Role of Grassroots Epistemology in Clinical Settings. J. Clin. Med. 2024, 14, 4315. [Google Scholar] [CrossRef] [Scilit]
  23. Bellman, M.; Byrne, O.; Sege, R. Developmental assessment of children. BMJ 2013, 346, e8687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Vitrikas, K.; Savard, D.; Bucaj, M. Developmental Delay: When and How to Screen. Am. Fam. Physician 2017, 96, 36–43. [Google Scholar]
  25. Felix, G.; Deavenport-Saman, A.; Stavros, S.; Farboodi, N.; Durazo-Arvizu, R.; Garcia, J.; Yin, L.; Gera, M.P. Standardizing and Improving Primary Care-Based Electronic Developmental Screening for Young Children in Federally Qualified Health Center Clinics. Matern. Child Health J. 2024, 28, 1716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Caemmerer, J.M.; deLeyer-Tiarks, J.M.; Dale, B.A.; Winter, E.L.; Charamut, N.R.; Scudder, A.M.; Peters, E.C.; Bray, M.A.; Kaufman, A.S. Does the Bayley-4 measure the same constructs across girls and boys and infants, toddlers, and preschoolers? Psychol. Assess. 2024, 36, 643–653. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Salonen, J.; Slama, S.; Haavisto, A.; Rosenqvist, J. Comparison of WPPSI-IV and WISC-V cognitive profiles in 6–7-year-old Finland-Swedish children—Findings from the FinSwed study. Child Neuropsychol. 2023, 29, 687–709. [Google Scholar] [CrossRef] [Scilit]
  28. Mazurek, M.O.; Kanne, S.M. Leiter International Performance Scale, Third Edition. In Encyclopedia of Clinical Neuropsychology; Kreutzer, J.S., DeLuca, J., Caplan, B., Eds.; Springer: Cham, Switzerland, 2018. [Google Scholar] [CrossRef] [Scilit]
  29. Borsa, J.; Bandeira, D. Cross-Cultural Adaptation and Validation of Psychological Instruments: Some Considerations. Paidéia 2012, 22, 10. [Google Scholar]
  30. Farmer, C.; Adedipe, D.; Bal, V.; Chlebowski, C.; Thurm, A. Concordance of the Vineland Adaptive Behavior Scales, Second and Third Editions. J. Intellect. Disabil. Res. JIDR 2019, 64, 18. [Google Scholar] [CrossRef] [Scilit]
  31. Mikos, A.; Fartdinova, N.; Seifert, A.; Giroud, N.; Riese, F. Association of hearing and vision impairment with cognitive impairment in nursing home residents in Switzerland. Eur. J. Ageing 2025, 22, 39. [Google Scholar] [CrossRef] [Scilit]
  32. Manickam, K.; McClain, M.R.; Demmer, L.A.; Biswas, S.; Kearney, H.M.; Malinowski, J.; Massingham, L.J.; Miller, D.; Yu, T.W.; Hisama, F.M.; et al. Exome and genome sequencing for pediatric patients with congenital anomalies or intellectual disability: An evidence-based clinical guideline of the American College of Medical Genetics and Genomics (ACMG). Genet. Med. 2021, 23, 2029–2037. [Google Scholar] [CrossRef] [Scilit]
  33. Awuah, W.A.; Shah, M.H.; Sanker, V.; Mannan, K.M.; Ranganathan, S.; Nkrumah-Boateng, P.A.; Frimpong, M.; Darko, K.; Tan, J.K.; Abdul-Rahman, T.; et al. Advances in chromosomal microarray analysis: Transforming neurology and neurosurgery. Brain Spine 2025, 5, 104197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Ayet-Roger, A.; Joga-Elvira, L.; Caixàs, A.; Corripio, R. Cognitive and adaptive effects of early growth hormone treatment in Prader-Willi syndrome patients: A cohort study. J. Clin. Med. 2022, 11, 1592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Driscoll, D.J.; Miller, J.L.; Cassidy, S.B. Adam, M.P., Feldman, J., Mirzaa, G.M., Pagon, R.A., Wallace, S.E., Amemiya, A., Eds.; Prader-Willi Syndrome. In GeneReviews®; University of Washington: Seattle, WA, USA, 1998. Available online: https://www.ncbi.nlm.nih.gov/books/NBK1330/ (accessed on 1 November 2025).
  36. Ji, J.; Leung, M.L.; Baker, S.; Deignan, J.L.; Santani, A. Clinical Exome Reanalysis: Current Practice and Beyond. Mol. Diagn. Ther. 2021, 25, 529. [Google Scholar] [CrossRef] [Scilit]
  37. Karimzadeh, P.; Taghdiri, M.M.; Abasi, E.; Amouzadeh, M.H.; Naghavi, Z.; Ghazavi, A.; Nasehi, M.M.; Alipour, A. Metabolic Screening in Children with Neurodevelopmental Delay, Seizure and/or Regression. Iran. J. Child Neurol. 2017, 11, 42–47. Available online: https://pmc.ncbi.nlm.nih.gov/articles/PMC5582359/ (accessed on 1 November 2025).
  38. Doescher, J.S.; Musick, B.S.; Dunn, D.W.; Kalnin, A.J.; Egelhoff, J.C.; Byars, A.W.; Mathews, V.P.; Austin, J.K. Magnetic resonance imaging (MRI) and electroencephalographic (EEG) findings in a cohort of normal children with newly diagnosed seizures. J. Child Neurol. 2006, 21, 491–495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Flannery, B.M.; Middleton, K.B. Updated interim reference levels for dietary lead to support FDA’s Closer to Zero action plan. Regul. Toxicol. Pharmacol. 2022, 133, 105202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. González, D.A.; Gonzales, M.M.; Jennette, K.J.; Soble, J.R.; Fongang, B. Cognitive screening with functional assessment improves diagnostic accuracy and attenuates bias. Alzheimer’s Dement. Diagn. Assess. Dis. Monit. 2021, 13, e12250. [Google Scholar] [CrossRef] [Scilit]
  41. Harshaw, C. Interoceptive Dysfunction: Toward An Integrated Framework for Understanding Somatic and Affective Disturbance in Depression. Psychol. Bull. 2014, 141, 311. [Google Scholar] [CrossRef] [Scilit]
  42. Leitner, Y. The Co-Occurrence of Autism and Attention Deficit Hyperactivity Disorder in Children—What Do We Know? Front. Hum. Neurosci. 2014, 8, 268. [Google Scholar] [CrossRef] [Scilit]
  43. Yu, Y.; Ozonoff, S.; Miller, M. Assessment of Autism Spectrum Disorder. Assessment 2023, 31, 24. [Google Scholar] [CrossRef] [Scilit]
  44. Usha, G.P.; Rani Alex, J.S. Speech assessment tool methods for speech impaired children: A systematic literature review on the state-of-the-art in Speech impairment analysis. Multimed. Tools Appl. 2023, 82, 35021–35058. [Google Scholar] [CrossRef] [Scilit]
  45. Wolski, L.; Leroi, I.; Regan, J.; Dawes, P.; Charalambous, A.P.; Thodi, C.; Prokopiou, J.; Villeneuve, R.; Helmer, C.; Yohannes, A.M.; et al. The need for improved cognitive, hearing and vision assessments for older people with cognitive impairment: A qualitative study. BMC Geriatr. 2019, 19, 328. [Google Scholar] [CrossRef] [Scilit]
  46. Bertollo, A.G.; Puntel, C.F.; Da Silva, B.V.; Martins, M.; Bagatini, M.D.; Ignácio, Z.M. Neurobiological Relationships Between Neurodevelopmental Disorders and Mood Disorders. Brain Sci. 2025, 15, 307. [Google Scholar] [CrossRef] [Scilit]
  47. National Research Council (US) Committee on Disability Determination for Mental Retardation. Chapter 4, The Role of Adaptive Behavior Assessment. In Mental Retardation: Determining Eligibility for Social Security Benefits; Reschly, D.J., Myers, T.G., Hartel, C.R., Eds.; National Academies Press: Washington, DC, USA, 2002. Available online: https://www.ncbi.nlm.nih.gov/books/NBK207541/ (accessed on 1 November 2025).
  48. Kaat, A.J.; Bishop, S.; Condy, E.; Sullivan, N.R.; Soorya, L.; Thurm, A. Prerequisite Skills in Cognitive Testing: Innovations in theory and recommendations for practice. Cogn. Dev. 2021, 58, 101038. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Hadders-Algra, M. Early Diagnostics and Early Intervention in Neurodevelopmental Disorders—Age-Dependent Challenges and Opportunities. J. Clin. Med. 2021, 10, 861. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Peña, E.D.; Bedore, L.M.; Kester, E.S. Assessment of language impairment in bilingual children using semantic tasks: Two languages classify better than one. Int. J. Lang. Commun. Disord. 2015, 51, 192. [Google Scholar] [CrossRef] [Scilit]
  51. Hertel, I.; Chilla, S.; Abed Ibrahim, L. Special Needs Assessment in Bilingual School-Age Children in Germany. Languages 2022, 7, 4. [Google Scholar] [CrossRef] [Scilit]
  52. Sugiyama, T.; Liew, L. The Effects of Sensory Manipulations on Motor Behavior: From Basic Science to Clinical Rehabilitation. J. Mot. Behav. 2016, 49, 67. [Google Scholar] [CrossRef] [Scilit]
  53. Sapiets, S.J.; Totsika, V.; Hastings, R.P. Factors influencing access to early intervention for families of children with developmental disabilities: A narrative review. J. Appl. Res. Intellect. Disabil. 2020, 34, 695. [Google Scholar] [CrossRef] [Scilit]
  54. Olson, A.P.; Graber, M.L. Improving Diagnosis Through Education. Acad. Med. 2020, 95, 1162. [Google Scholar] [CrossRef] [Scilit]
  55. Bauskis, A.; Strange, C.; Molster, C.; Fisher, C. The diagnostic odyssey: Insights from parents of children living with an undiagnosed condition. Orphanet J. Rare Dis. 2022, 17, 233. [Google Scholar] [CrossRef] [Scilit]
  56. Faye, F.; Crocione, C.; Bellagambi, S.; Peñaloza, L.E.; Hunter, A.; Jensen, L.; Oosterwijk, C.; Schoeters, E.; Faivre, L.; Wilbur, M.; et al. Time to diagnosis and determinants of diagnostic delays of people living with a rare disease: Results of a Rare Barometer retrospective patient survey. Eur. J. Hum. Genet. 2024, 32, 1116. [Google Scholar] [CrossRef] [Scilit]
  57. Pollard, S.; Weymann, D.; Dunne, J.; Mayanloo, F.; Buckell, J.; Buchanan, J.; Wordsworth, S.; Friedman, J.M.; Stockler-Ipsiroglu, S.; Dragojlovic, N.; et al. Toward the diagnosis of rare childhood genetic diseases: What do parents value most? Eur. J. Hum. Genet. 2021, 29, 1491. [Google Scholar] [CrossRef] [Scilit]
  58. AlMutiri, R.; Malta, M.; Shevell, M.I.; Srour, M. Evaluation of Individuals with Non-Syndromic Global Developmental Delay and Intellectual Disability. Children 2023, 10, 414. [Google Scholar] [CrossRef] [Scilit]
  59. Hou, K.; Zheng, X. A 10-Year Review on Advancements in Identifying and Treating Intellectual Disability Caused by Genetic Variations. Genes 2024, 15, 1118. [Google Scholar] [CrossRef] [Scilit]
  60. Balasundaram, P.; Avulakunta, I.D. Bayley Scales of Infant and Toddler Development. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2022. Available online: https://www.ncbi.nlm.nih.gov/books/NBK567715/ (accessed on 1 November 2025).
  61. Grzadzinski, R.; Janvier, D.; Kim, S.H. Recent Developments in Treatment Outcome Measures for Young Children With Autism Spectrum Disorder (ASD). Semin. Pediatr. Neurol. 2020, 34, 100806. [Google Scholar] [CrossRef] [Scilit]
  62. Srivastava, S.; Love-Nichols, J.A.; Dies, K.A.; Ledbetter, D.H.; Martin, C.L.; Chung, W.K.; Firth, H.V.; Frazier, T.; Hansen, R.L.; Prock, L.; et al. Meta-analysis and multidisciplinary consensus statement: Exome sequencing is a first-tier clinical diagnostic test for individuals with neurodevelopmental disorders. Genet. Med. 2019, 21, 2413. [Google Scholar] [CrossRef] [Scilit]
  63. Miller, D.T.; Adam, M.P.; Aradhya, S.; Biesecker, L.G.; Brothman, A.R.; Carter, N.P.; Church, D.M.; Crolla, J.A.; Eichler, E.E.; Epstein, C.J.; et al. Consensus statement: Chromosomal microarray is a first-tier clinical diagnostic test for individuals with developmental disabilities or congenital anomalies. Am. J. Hum. Genet. 2010, 86, 749–764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  64. Ortigoza-Escobar, J.D. A Proposed Diagnostic Algorithm for Inborn Errors of Metabolism Presenting with Movements Disorders. Front. Neurol. 2020, 11, 582160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  65. Cendes, F.; Theodore, W.H.; Brinkmann, B.H.; Sulc, V.; Cascino, G.D. Neuroimaging of epilepsy. Handb. Clin. Neurol. 2016, 136, 985. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Szulc, W.; Szydłowska, N.; Smyk, J.M.; Majewska, A. Progress and Challenges in the Management of Congenital Cytomegalovirus Infection. Clin. Pract. 2024, 14, 2445–2462. [Google Scholar] [CrossRef] [Scilit]
  67. Gievers, L.L.; Holmes, A.V.; Loyal, J.; Larson, I.A.; Oliveira, C.R.; Waldman, E.H.; Khaki, S. Ethical and Public Health Implications of Targeted Screening for Congenital Cytomegalovirus. Pediatrics 2020, 146, e20200617. [Google Scholar] [CrossRef] [Scilit]
  68. Fletcher, J.M.; Miciak, J. Assessment of Specific Learning Disabilities and Intellectual Disabilities. Assessment 2023, 31, 53. [Google Scholar] [CrossRef] [Scilit]
  69. Mattie, L.J.; Loveall, S.J.; Channell, M.M.; Rodgers, D.B. Perspectives on adaptive functioning and intellectual functioning measures for intellectual disabilities behavioral research. Front. Psychol. 2023, 14, 1084576. [Google Scholar] [CrossRef] [Scilit]
  70. Selau, T.; Filho, M.; Bandeira, D.R. Evidence of validity and reliability of the adaptive functioning scale for intellectual disability (EFA-DI). Psicol. Reflex. Crit. Rev. Semest Dep. Psicol. UFRGS 2020, 33, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  71. Sultan, M.A. Equitable access to sustainable healthcare services for children with autism. BJPsych Int. 2025, 22, 11. [Google Scholar] [CrossRef] [Scilit]
  72. Noorulhuda, M.; Grady, C.; Wakim, P.; Bernhard, T.; Cho, H.L.; Danis, M. Communication of patients’ and family members’ ethical concerns to their healthcare providers. BMC Med. Ethics 2023, 24, 56. [Google Scholar] [CrossRef] [Scilit]
  73. Fattahi, Z.; Shokouhian, E.; Peymani, F.; Babanejad, M.; Beheshtian, M.; Edizadeh, M.; Molaei, N.; Alagha, P.; Ghodratpour, F.; Keshavarzi, F.; et al. Improved Diagnostic Yield in Recessive Intellectual Disability Utilizing Systematic Whole Exome Sequencing Data Reanalysis. Clin. Genet. 2025, 107, 612–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  74. Cradeur, A.; Jackson, A.; Ware, E.; Fourrier, T.L.; Mankekar, G. Congenital Cytomegalovirus (cCMV) Infection as a Leading Cause of Pediatric Hearing Loss: Review. Children 2025, 12, 613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  75. Jagesar, R.R.; Roozen, M.C.; van der Heijden, I.; Ikani, N.; Tyborowska, A.; Penninx, B.W.J.H.; Ruhe, H.G.; Sommer, I.E.C.; Kas, M.J.; Vorstman, J.A.S. Digital phenotyping and the COVID-19 pandemic: Capturing behavioral change in patients with psychiatric disorders. Eur. Neuropsychopharmacol. 2021, 42, 115–120. [Google Scholar] [CrossRef] [Scilit]
  76. de Vries, P.J. Targeted treatments for cognitive and neurodevelopmental disorders in tuberous sclerosis complex. Neurotherapeutics 2010, 7, 275–282. [Google Scholar] [CrossRef] [Scilit]
  77. Boff, M.O.; Xavier, F.A.; Diz, F.M.; Gonçalves, J.B.; Ferreira, L.M.; Zambeli, J.; Pazzin, D.B.; Previato, T.T.; Erwig, H.S.; Gonçalves, J.I.; et al. MTORopathies in Epilepsy and Neurodevelopmental Disorders: The Future of Therapeutics and the Role of Gene Editing. Cells 2024, 14, 662. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  78. Musunuru, K.; Grandinette, S.A.; Wang, X.; Hudson, T.R.; Briseno, K.; Berry, A.M.; Hacker, J.L.; Hsu, A.; Silverstein, R.A.; Hille, L.T.; et al. Patient-Specific In Vivo Gene Editing to Treat a Rare Genetic Disease. N. Engl. J. Med. 2025, 392, 2235–2243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  79. Witkowsky, L.; Norstad, M.; Glynn, A.R.; Kliegman, M. Towards affordable CRISPR genomic therapies: A task force convened by the Innovative Genomics Institute. Gene Ther. 2023, 30, 747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  80. Hashizume, R.; Wakita, S.; Sawada, H.; Takebayashi, S.I.; Kitabatake, Y.; Miyagawa, Y.; Hirokawa, Y.S.; Imai, H.; Kurahashi, H. Trisomic rescue via allele-specific multiple chromosome cleavage using CRISPR-Cas9 in trisomy 21 cells. PNAS Nexus 2025, 4, pgaf022. [Google Scholar] [CrossRef] [Scilit]
Figure 1. This is a figure that compares the diagnostic criteria for Intellectual Disability according to the DSM-5-TR (Diagnostic and Statistical Manual of Mental Disorders, Text Revision) and the ICD-11 (International Classification of Diseases, 11th Revision). Created in BioRender. Babiker, R. (2025) https://BioRender.com/ta2y687.
Children 12 01585 g001
Figure 2. This figure is an overview of intellectual disability etiology showing major categories: prenatal, perinatal, postnatal, and idiopathic causes. Created in BioRender. Babiker, R. (2025) https://BioRender.com/31lnob7.
Children 12 01585 g002
Figure 3. This figure summarizes the diagnostic framework for intellectual disability from screening to comprehensive evaluation. It involves developmental, cognitive, and adaptive assessments, followed by sensory, genetic, metabolic, and neuroimaging tests as indicated. Integration of findings enables accurate diagnosis and personalized management. Created in BioRender. Babiker, R. (2025) https://BioRender.com/yq08oxp.
Children 12 01585 g003
Figure 4. The special diagnostic scenarios for assessing profound impairment, bilingual and culturally diverse children, and sensory or motor confounders. Created in BioRender. Babiker, R. (2025) https://BioRender.com/39fe15u.
Children 12 01585 g004
Figure 5. Schemes follow the same formatting. A structured diagnostic pathway is essential to ensure accuracy, efficiency, and timelines in evaluating intellectual disability. The process begins with a comprehensive history and physical examination. Created in BioRender. Babiker, R. (2025) https://BioRender.com/9ygdqw0.
Children 12 01585 g005
Figure 6. This is a figure that illustrates a future in which diagnosis is not static but dynamic—refined through genomic science, digital innovation, and therapeutic translation—ultimately linking precision in classification with opportunities for intervention. Created in BioRender. Babiker, R. (2025) https://BioRender.com/u7e3m4m.
Children 12 01585 g006
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.