Maternal Experiences with Exclusive Pumping—An Online Survey

 , , , and
Highlights
- Most exclusively pumping women had originally intended to partially or fully breastfeed, with only 5% reporting that exclusive pumping was their original plan.
- Exclusively pumping women reported a lack of resources and information to guide pumping logistics, milk storage and feeding.
- Targeted education for health professionals on support and information needed by exclusively pumping women is recommended.
- Tailored, evidence-based guidelines will help to support exclusively pumping women and improve maternal well-being.
Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design and Participants
2.2. Statistical Analysis
2.3. Qualitative Analysis
3. Results
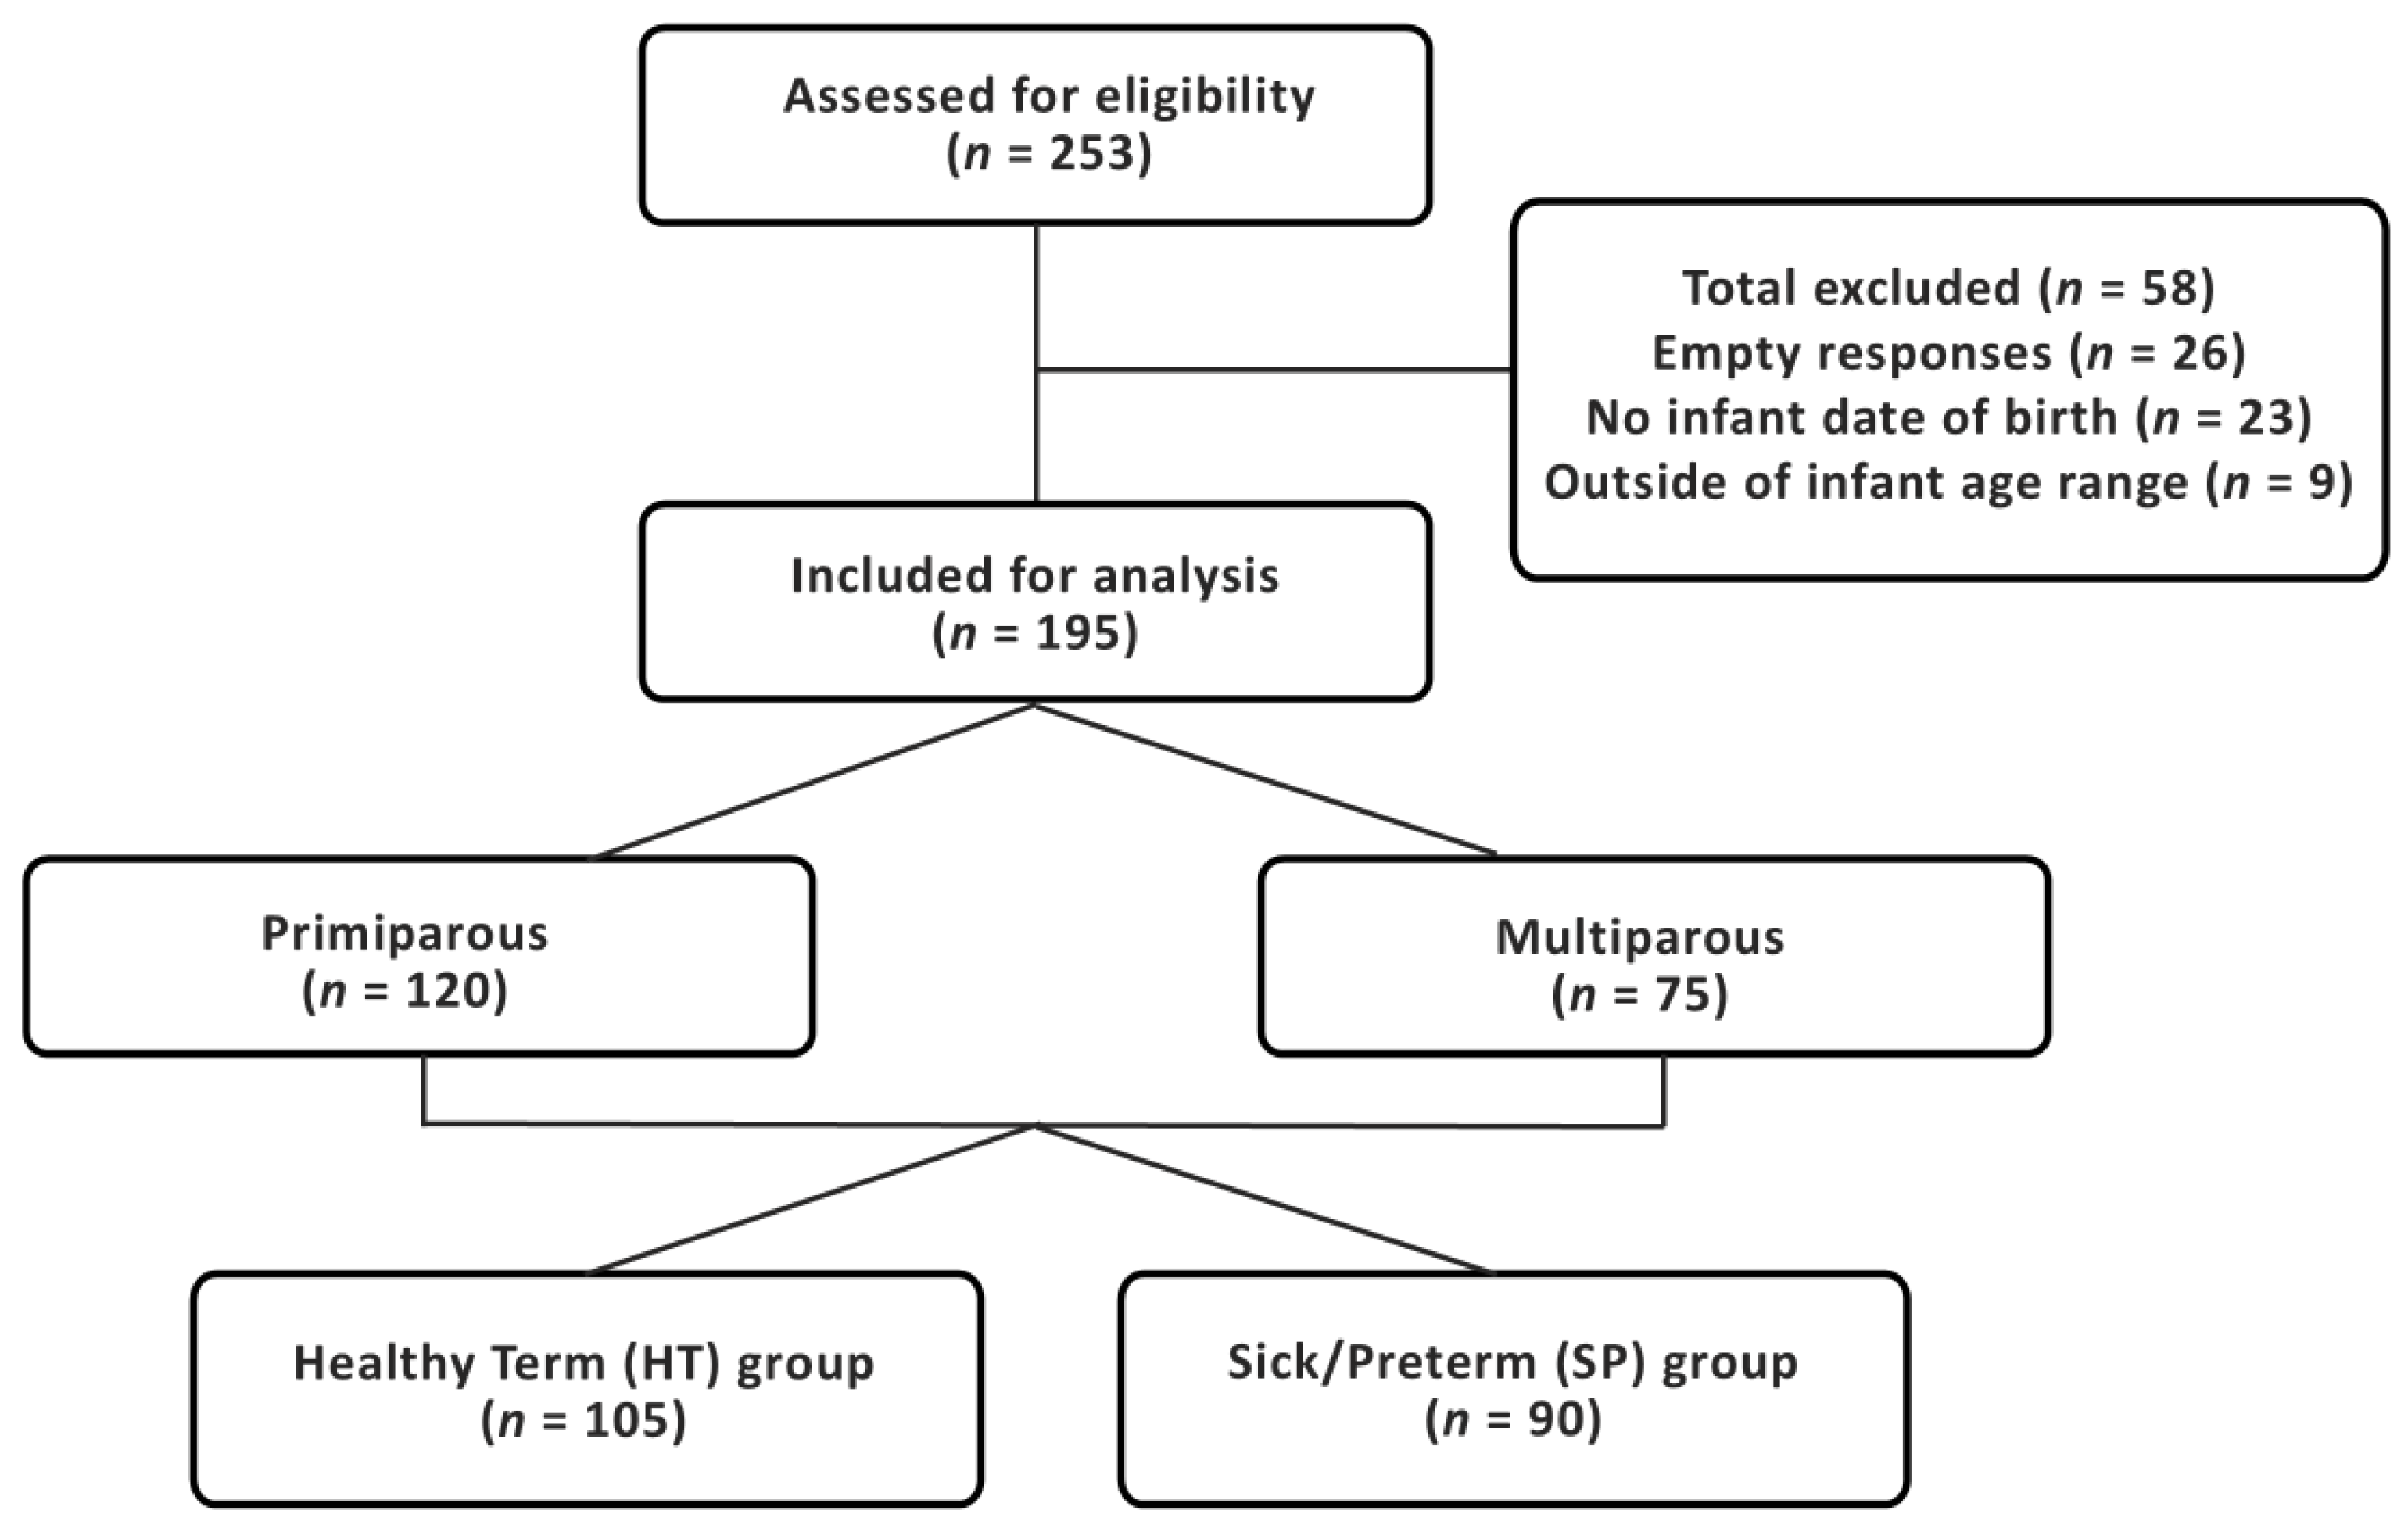
3.1. Participants’ Demographics and Expressing Status
3.2. Breastfeeding Intentions and Information Seeking During Pregnancy
3.3. Participants’ Perinatal, Health and Breastfeeding Characteristics
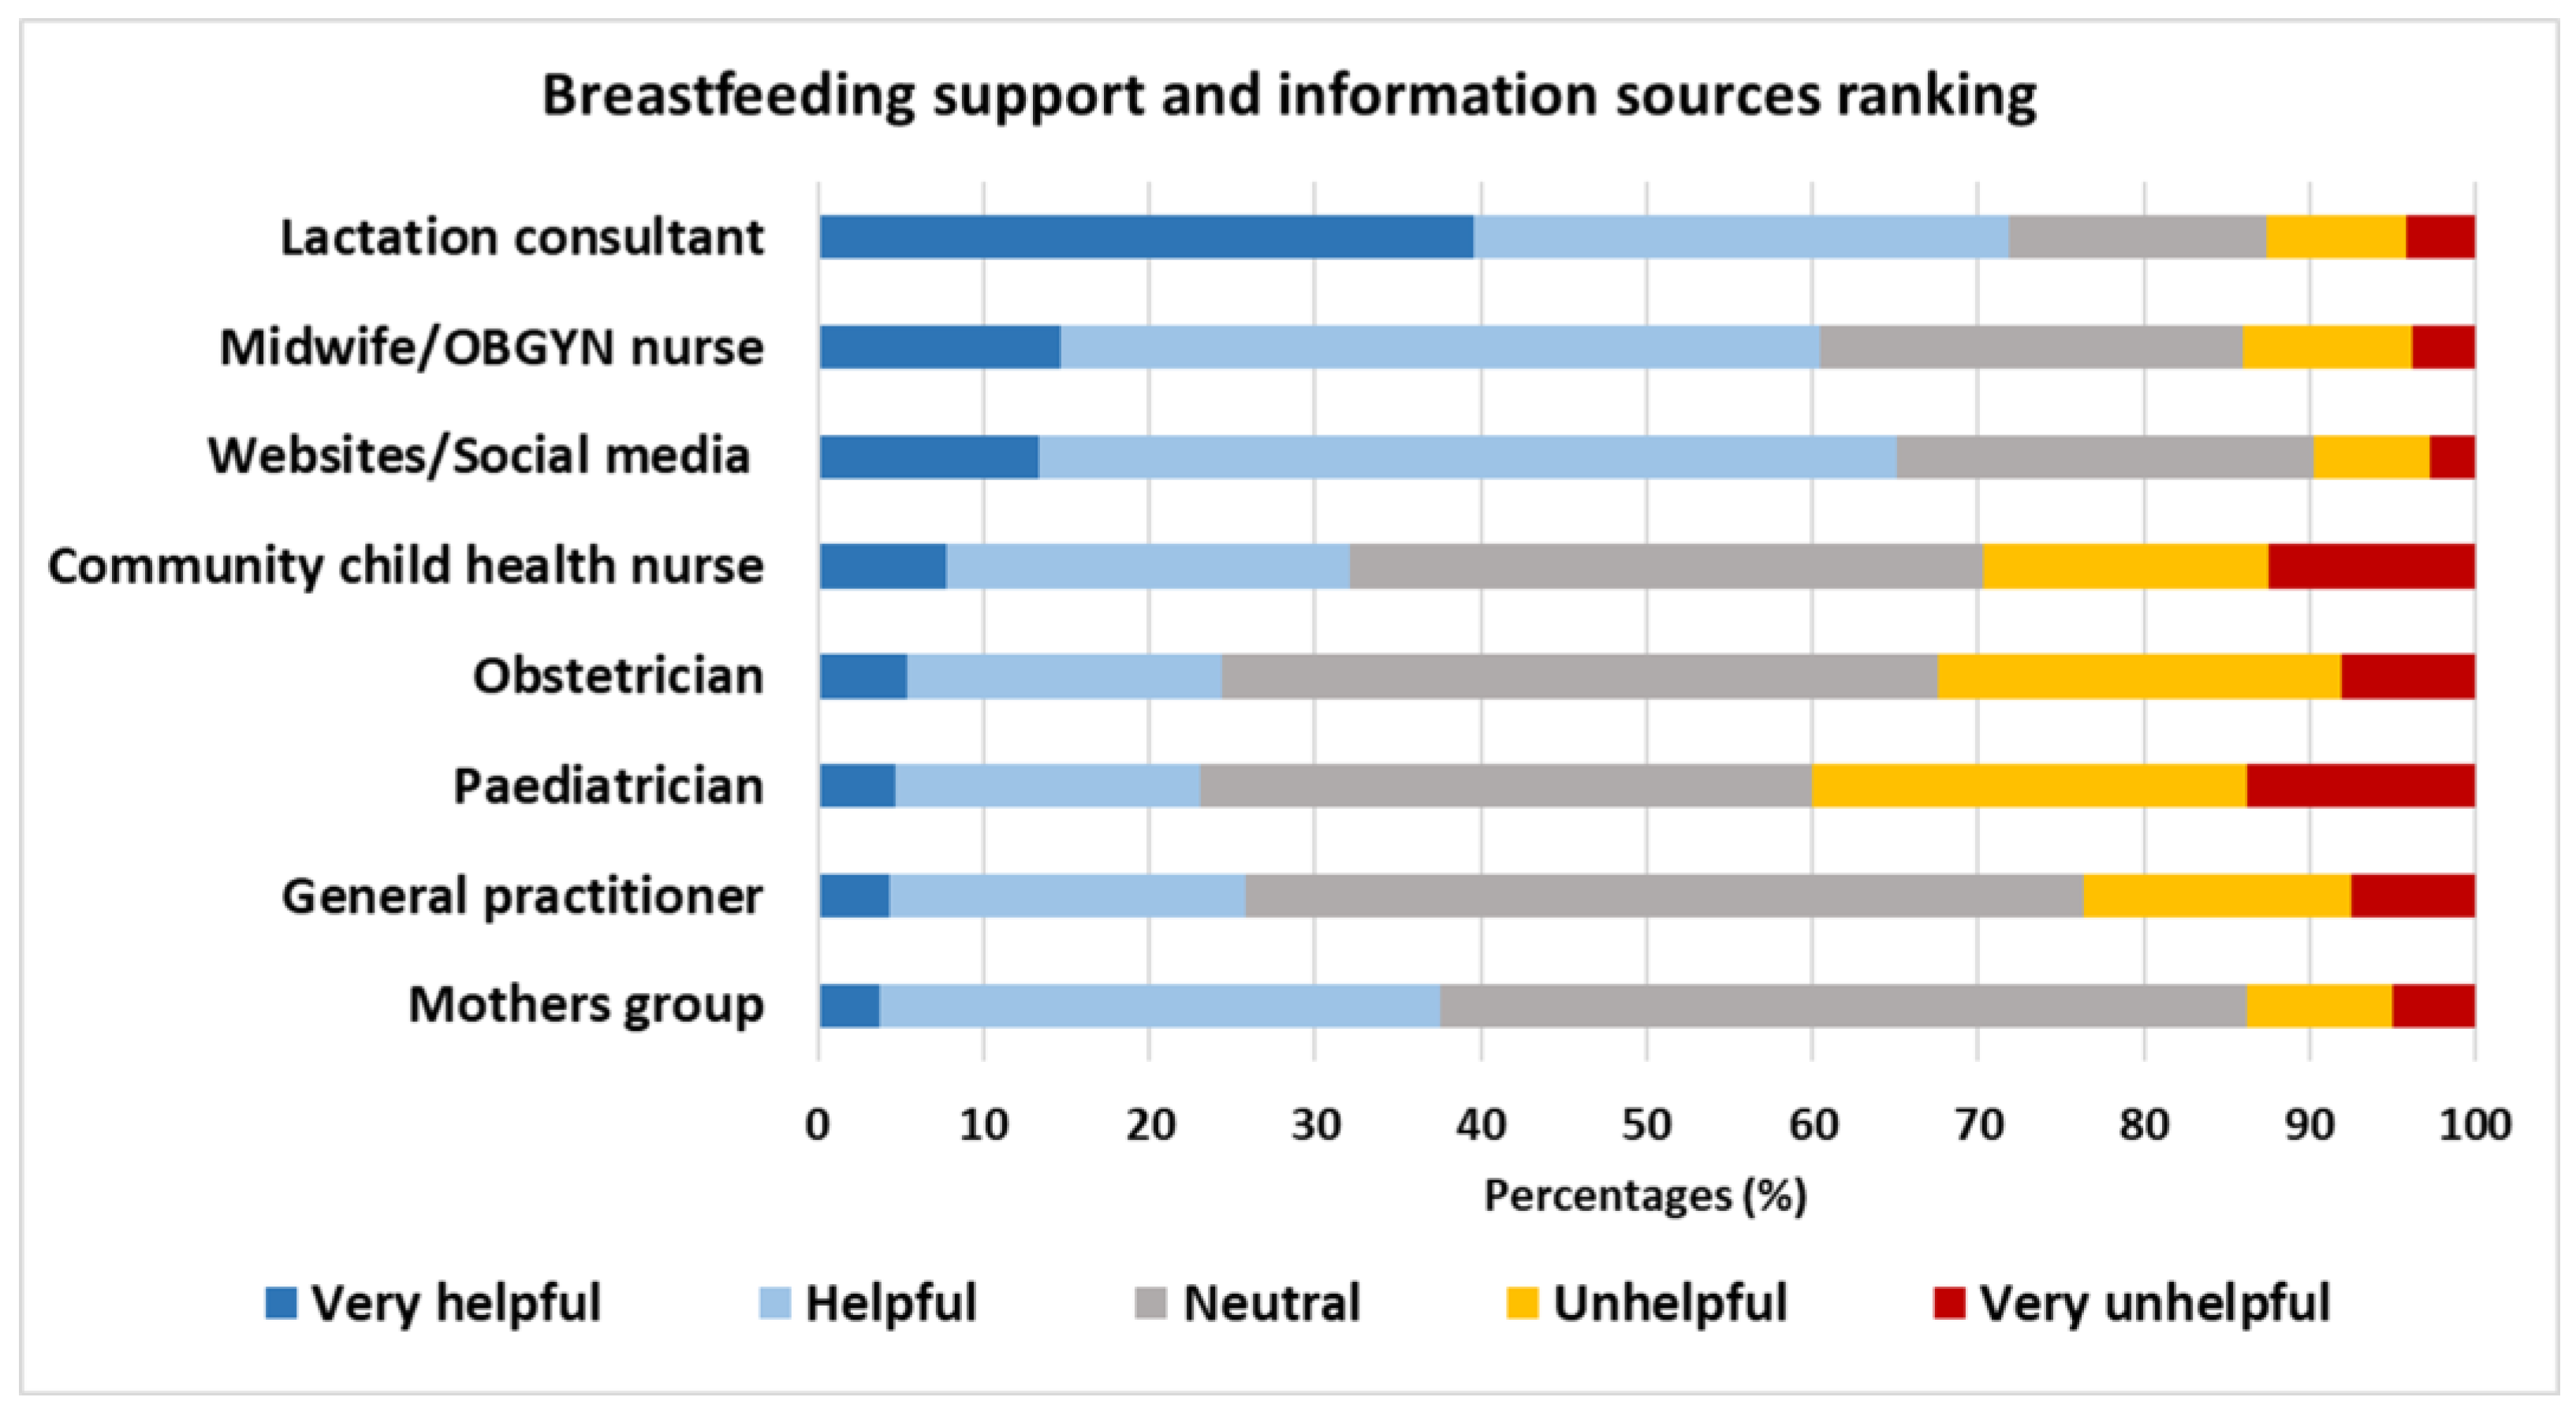
3.4. Lactation Challenges and Accessed Breastfeeding Services
3.5. Comparison with the General Population
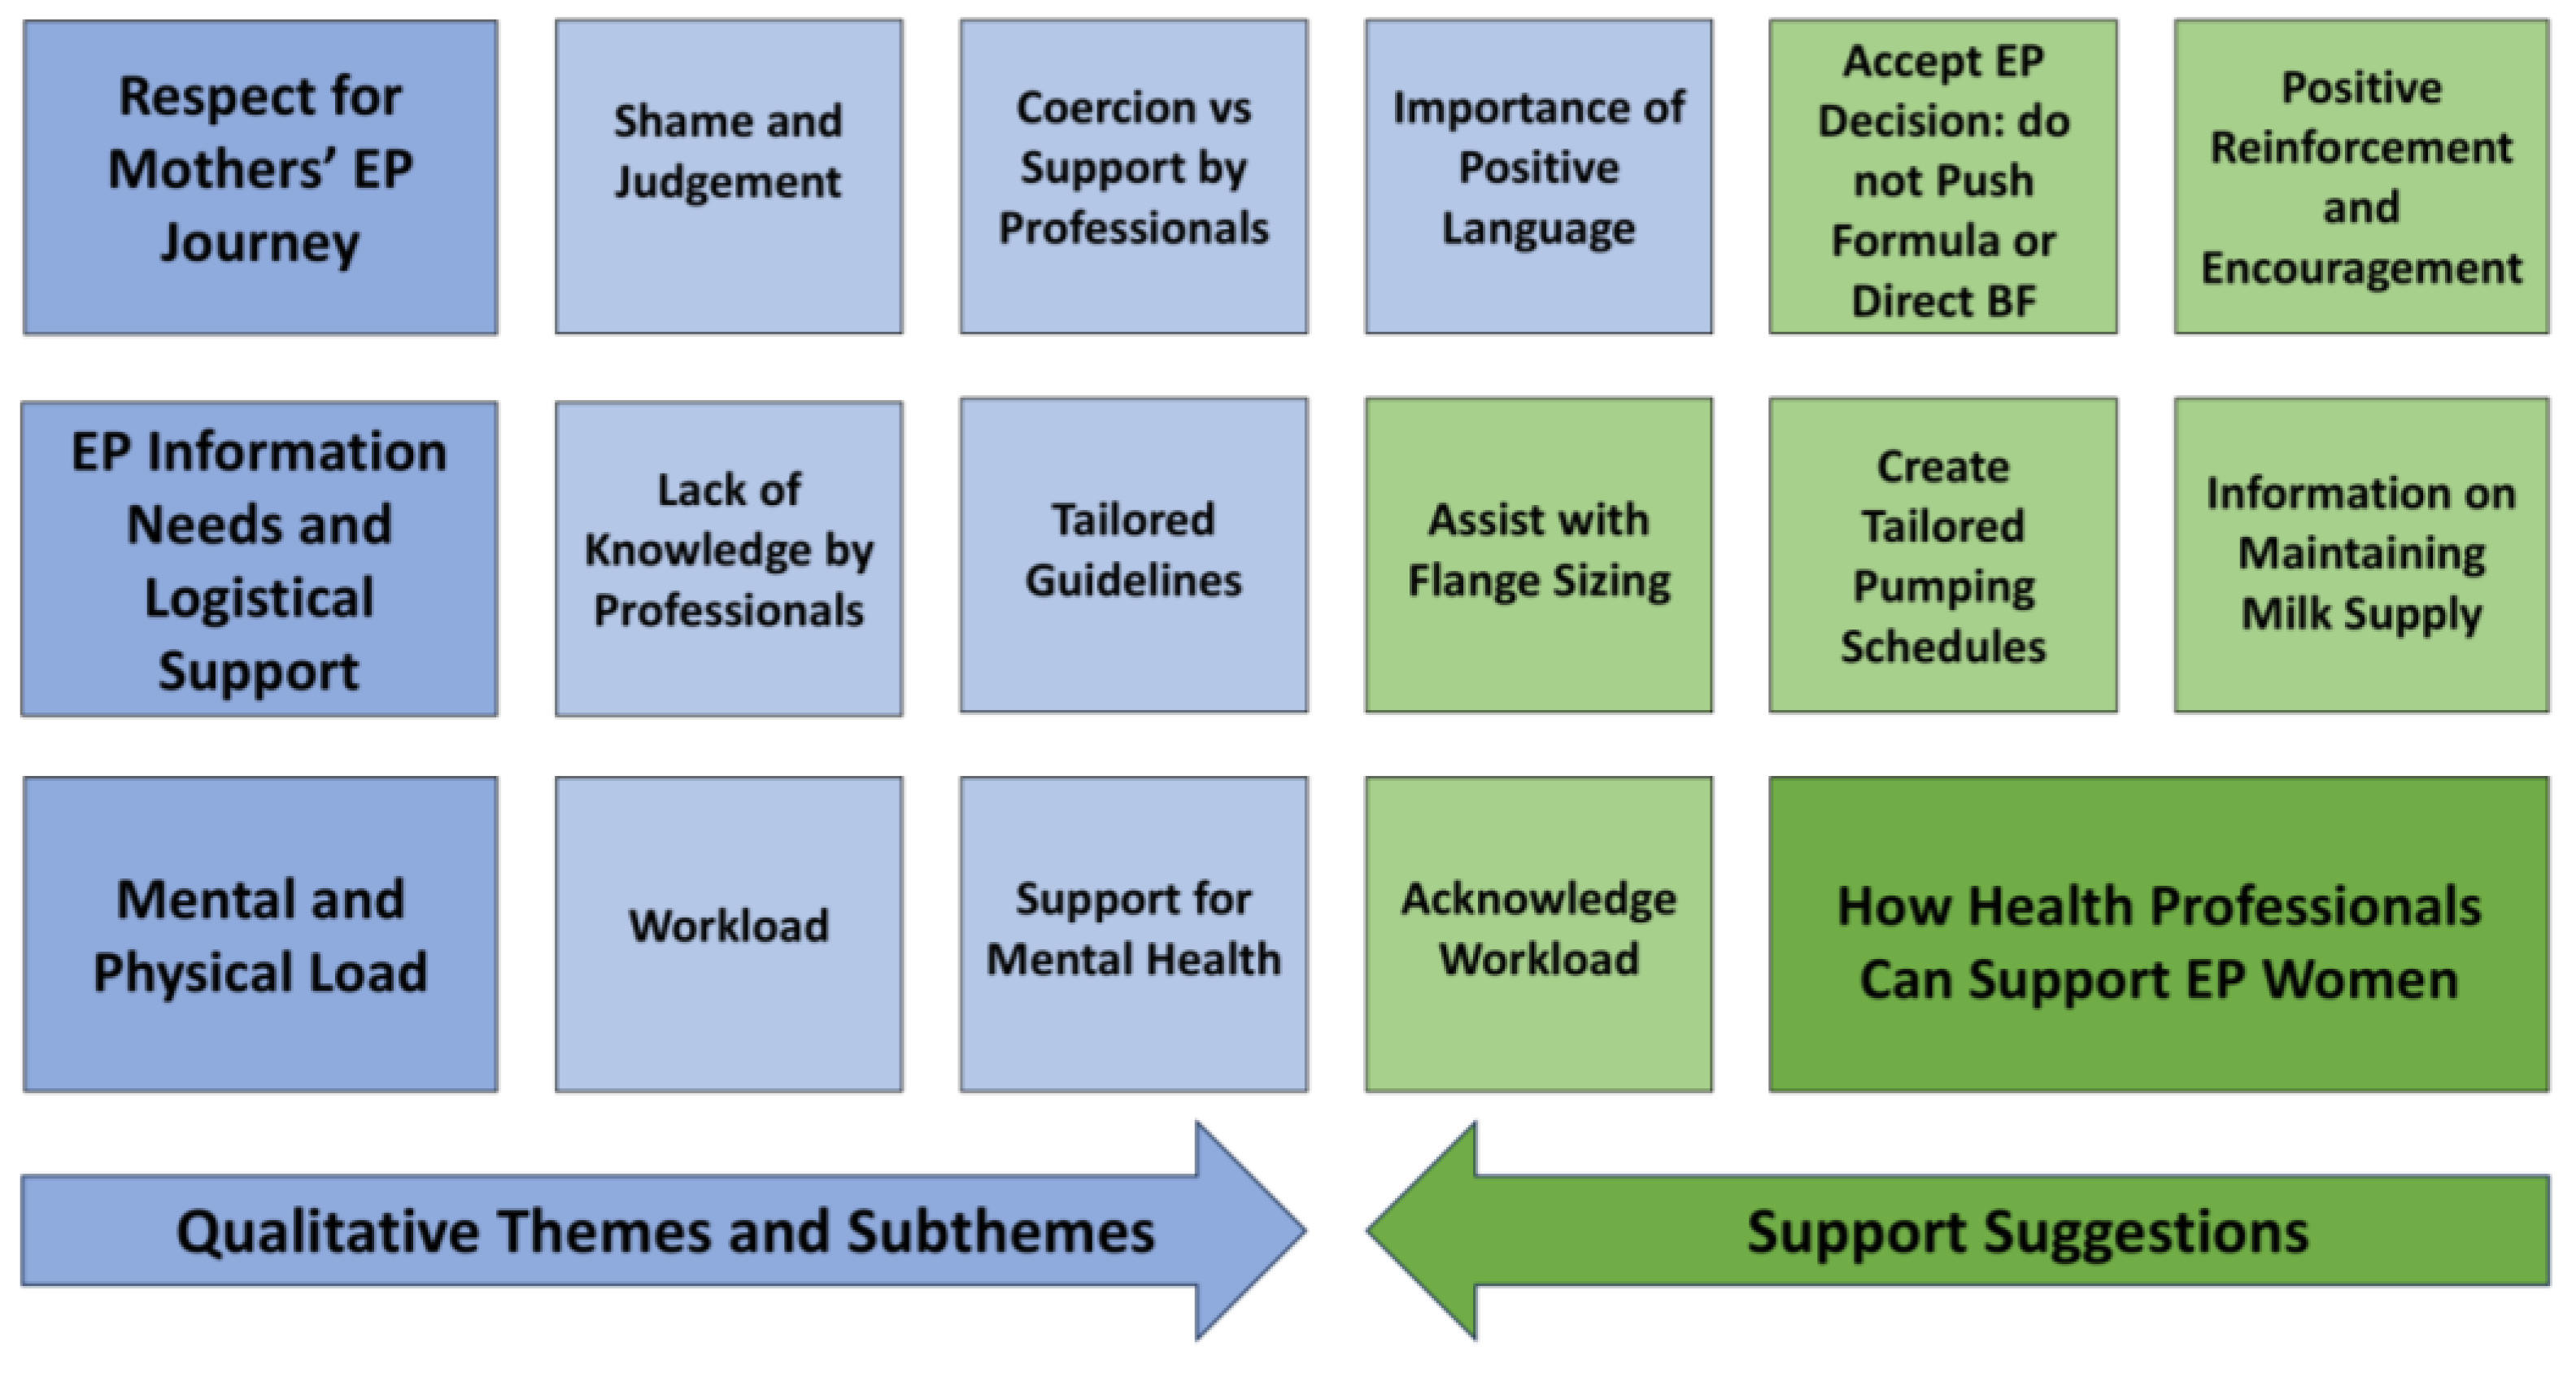
3.6. Qualitative Findings
3.6.1. Theme 1. Respect for Mothers’ EP Journey
- Subtheme 1 (Shame and Judgement) represented how health professionals can perpetuate feelings of inadequacy and shame due to harmful narratives associated with EP being seen as inferior to direct breastfeeding. Importantly, consistent acknowledgement that EP is breastfeeding was seen to reduce feelings of failure:
“Don’t just put “bottle feeding” down, specify it’s my milk! I work hard for that.”(M)
“I think one of the biggest things support people and health professionals could do is help reduce the shame that often surrounds not feeding directly from the breast. There’s still such a strong narrative that “real” breastfeeding only means feeding at the breast, which can leave exclusive pumpers feeling like they’re failing or missing out. It would help so much if professionals consistently acknowledged (and reinforced to families) that pumping is breastfeeding—that it’s valid, valuable, and just as nourishing.”(P)
“Family members don’t understand pumping. They just see you giving a bottle and judge you straight away.”(P)
“Wish husband had been more supportive—to him he was behind whatever I wanted but when I struggled with EP he would always be like “we can switch to formula if you want.”(P)
- Subtheme 2 (Coercion versus Support by Professionals) highlighted that many health professionals did not provide individualised care, with women feeling like their personal needs and wants were not being heard or acknowledged. This resulted in many women feeling coerced into using a feeding method preferred by the care provider against their own wishes. Coercion included pressure to switch to formula or to persist in trying to directly breastfeed despite the woman not being able or no longer wanting to:
“Some community nurses I saw were really pushy about trying to breastfeed even though I knew she would struggle to cope with my fast flow and short nipples. All my kids have. It was frustrating to have them push it on me as though they had the answer to my problems even though I knew from experience that my kids need time and to grow a little. I wanted to breastfeed rather than exclusively pumping so if it was possible I would’ve already been breastfeeding.”(M)
“Formula is thrown around as the easier better option I was told by several people friends professionals whatever that formula could just solve all our issues and bub would be ok. Well, no bub wouldn’t be ok drinking powdered chemical processed junk with water, women aren’t supported instead told to do what’s easier and best for mom and lying and saying it’s best for bub, there needs to be better education classes on flanges, pump schedules, routines, access to affordable pumps etc.”(P)
“Acknowledge that it’s a valid way of feeding the baby, ask what we need to make it easier, ask how we are going/coping with it, ask about problems we’ve run into, don’t suggest formula instead just ask us what our goals are.”(P)
- Subtheme 3 (Importance of Positive Language) addressed the impact of encouraging and supportive language on EP women’s confidence and self-esteem. Women felt validated when health professionals made direct statements of encouragement:
“Unfortunately I had lost a lot confidence in pumping after a second bout of mastitis (around 10 weeks) and a lactation adviser I saw simply said how great it was that I had come so far and had not given up—and it was such a needed boost!”(M)
“When pediatrician asked about feeding I said I was exclusively pumping—her response was “so breastfeeding” made me feel validated.”(P)
3.6.2. Theme 2. EP Information and Logistical Support
- Subtheme 4 (Lack of Knowledge by Professionals) highlighted the lack of EP-specific knowledge among health professionals. Many women stated that a lack of evidence-based, practical guidelines meant that contradictory advice was given, further contributing to the stress of EP: “More pumping education in the midwife/health nurse space. A lot provide outdated or conflicting advice.” (M)
“There is very little information for people who express exclusively. This means that even supportive people don’t quite know what to say.”(M)
“Community maternal child health nurses and lactation consults should be able to assist pumping mothers. None measured my nipples to ensure correct flange size, I had to work this out via social media channels.”(P)
- Subtheme 5 (Tailored Guidelines) focused on the importance of tailored guidelines for EP:
“Provide more information on exclusively pumping—how often to pump, types of pumps, flange sizes, sterilisation requirements for equipment, recommendations around how often to clean the pump and parts.”(P)
“Knowledge around specifics e.g., importance of correct flange size and how to measure. Blanket adherence to one recommendation re: timed breastmilk safety (e.g., sometimes told breastmilk is ok out of fridge for up to 8 h, other times told only 2 h)”.(M)
“Health professionals could better support us by giving practical help and resources specifically for pumping: creating personalised plans, helping navigate supply issues, and recognising the mental load involved. Even small things like acknowledging how hard and impressive it is to keep going would make a huge difference. Overall, more empathy, validation, and tailored guidance for pumping parents would go a long way.”(P)
3.6.3. Theme 3. Mental and Physical Load
- Subtheme 6 (Workload) highlighted a commonly identified challenge of EP, the physical workload and time demand that EP places on women during the vulnerable postpartum time. The additional work involved with EP included time spent pumping and then feeding EBM to the infant, cleaning and maintaining pumping equipment, and handling and storing EBM:
“I think there needs to be much more understanding of the sheer work involved. Pumping is incredibly demanding and stressful, particularly long term—it’s not just feeding the baby, but also managing sterilisation, scheduling sessions, washing parts, storing milk, and often doing it all alone in the middle of the night. It’s physically and emotionally exhausting.”(P)
“I think so many people give up as washing/drying/sterilising 8+ times a day on top of trying to raise a newborn with no sleep absolutely becomes too much at times.”(P)
“Support the mother, ask what they can do to help. Offer resources that are appropriate. Respect her decision, acknowledge how difficult it is and the effort she’s making to provide breastmilk for her baby.”(P)
- Subtheme 7 (Support for Mental Health) explored how recognition of maternal mental health reduced the pressure on EP women. Open communication and providing various options and education meant women felt supported to make decisions that worked best for them:
“The support I had in the NICU give me lots of options and education in breastfeeding and exclusively pumping with how to increase my supply, they gave me lots of support with my low supply and discussed mixed feeding and if it was to become too stressful for me or if it was affecting my mental health they would supportive if I needed to stop for that reason.”(P)
4. Discussion
4.1. Breastfeeding Intentions of Exclusively Pumping Women and Early Feeding Practices
4.2. Birth Mode and Prematurity and/or Neonatal Unit Admission Associations
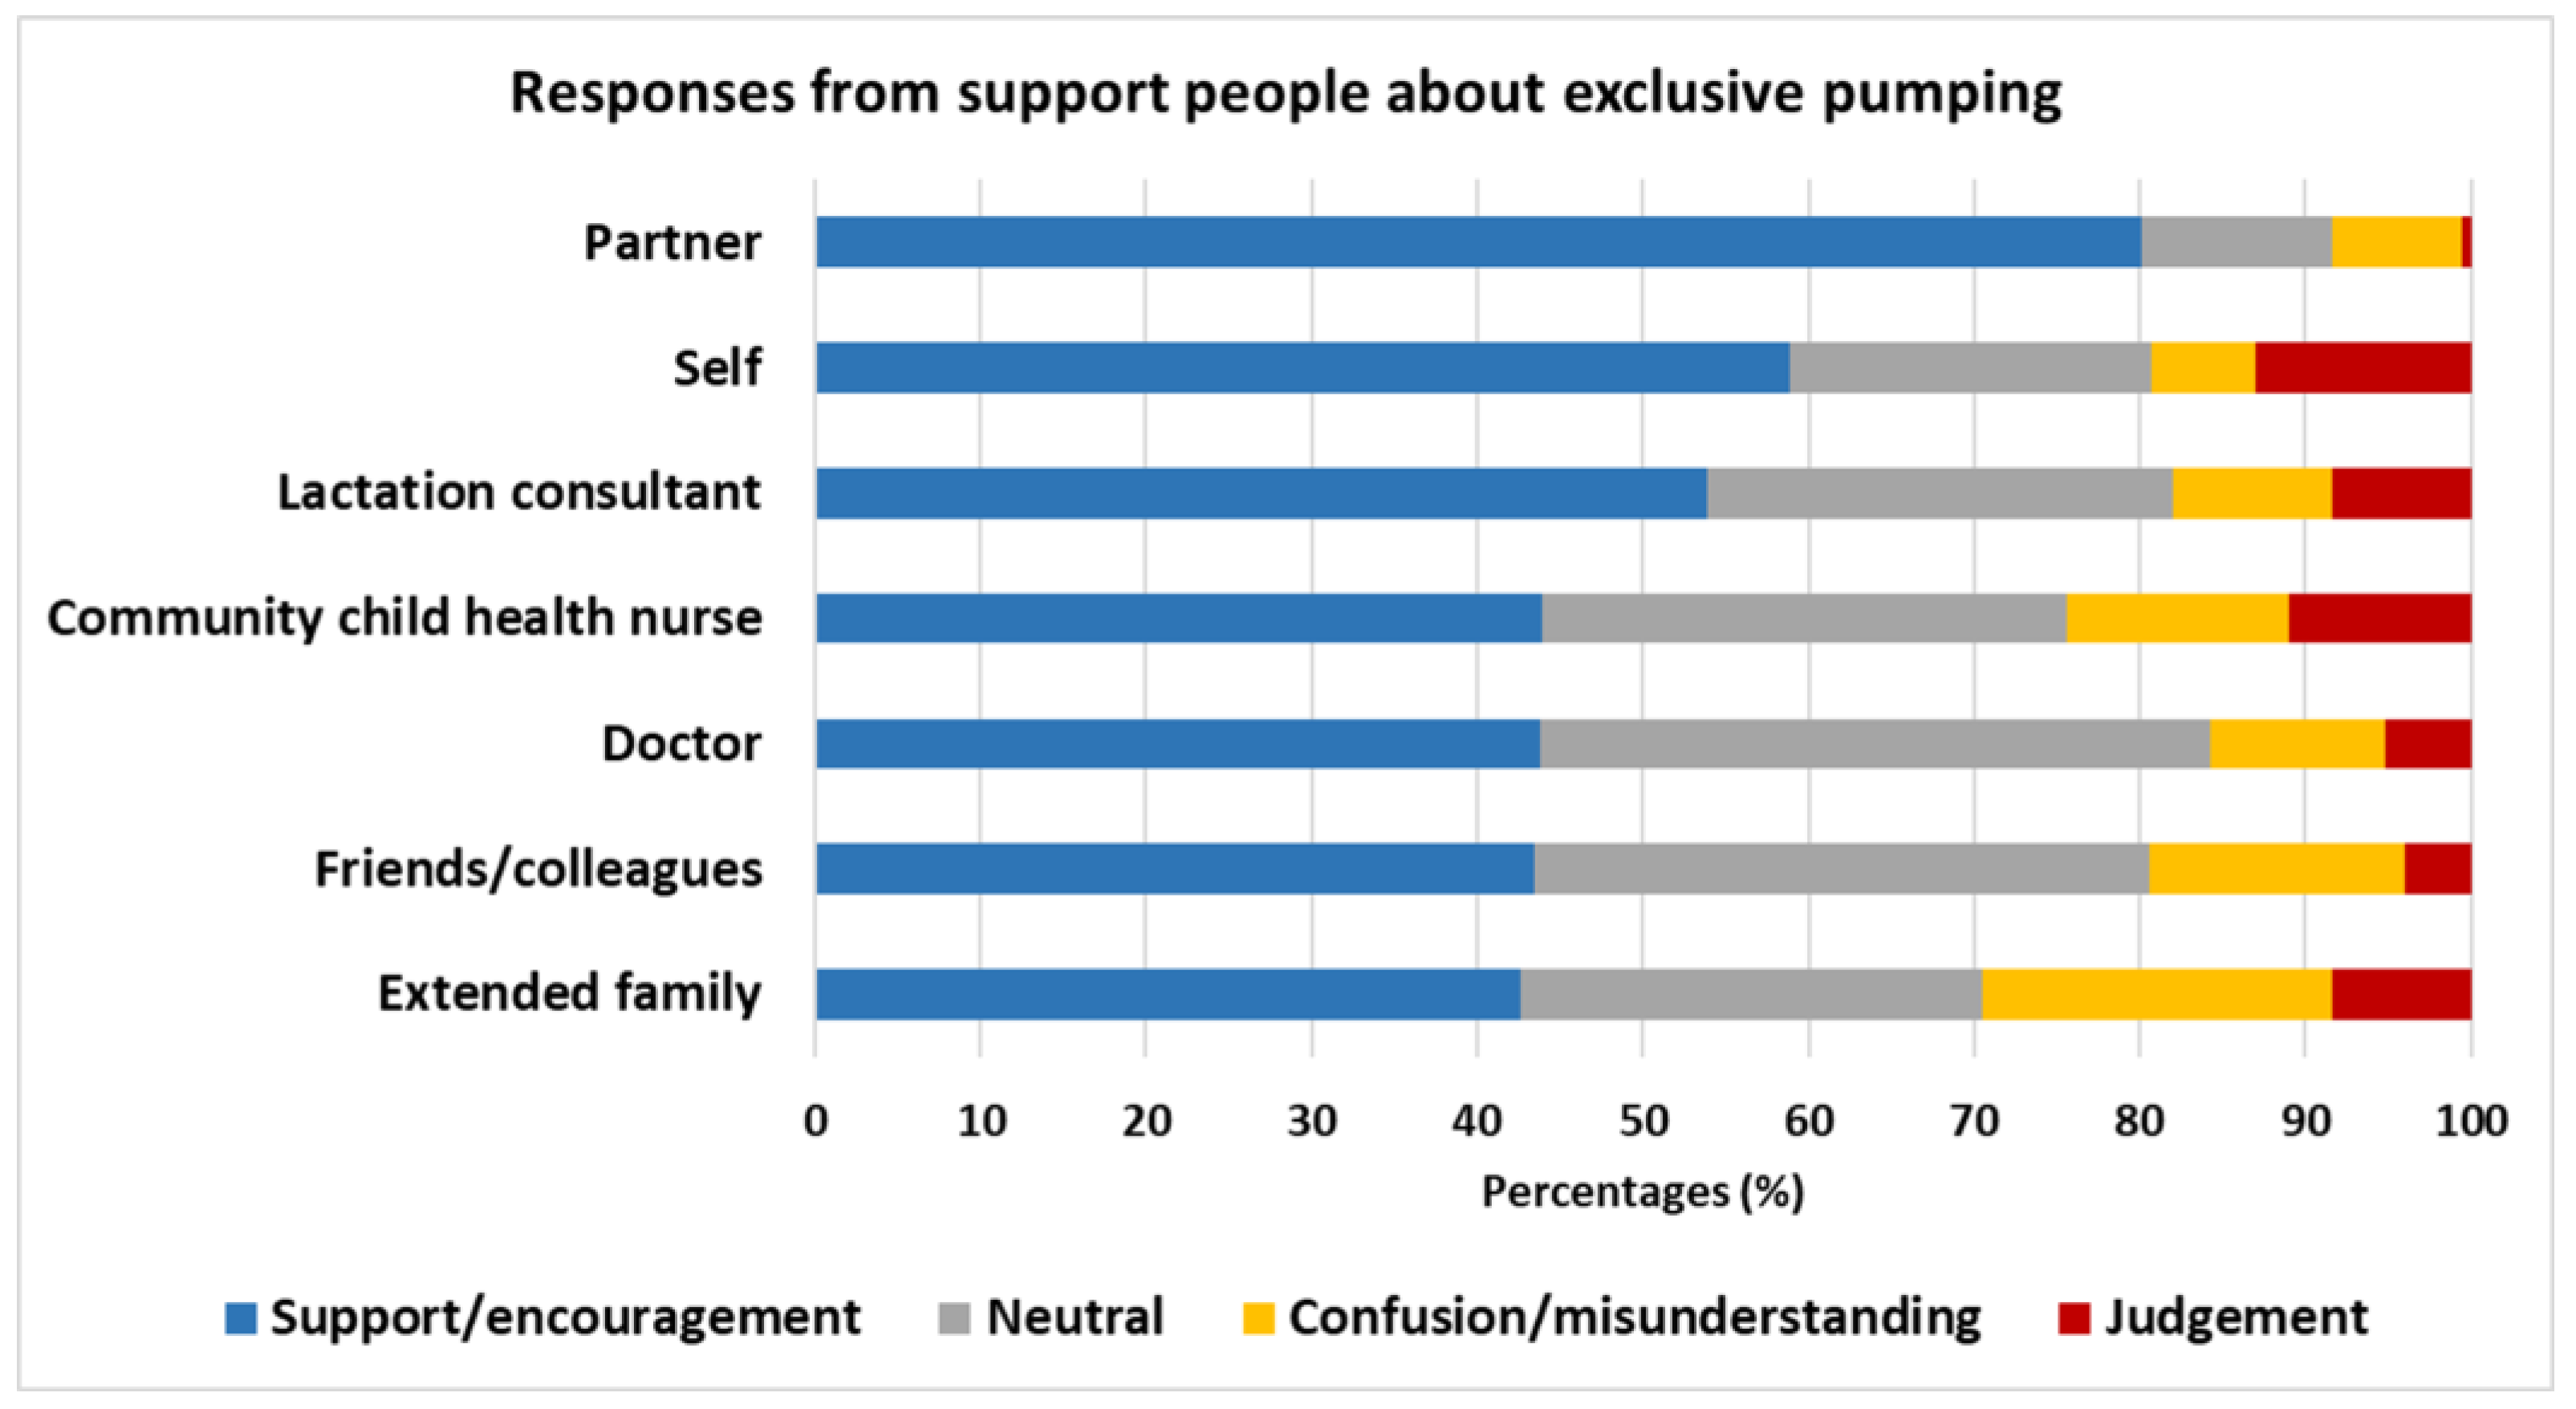
4.3. Experience of Care by Health Professionals
4.4. Challenges Associated with Exclusive Pumping
4.5. Study Strengths and Limitations
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| BF | Breastfeeding |
| BMI | Body mass index |
| EBM | Expressed breast milk |
| EP | Exclusive/exclusively pumping |
| GDM | Gestational diabetes mellitus |
| HT | Healthy term |
| NICU | Neonatal intensive care unit |
| REDCap | Research Electronic Data Capture |
| SP | Sick/preterm |
| WHO | World Health Organization |
References
- Lyons, K.E.; Ryan, C.A.; Dempsey, E.M.; Ross, R.P.; Stanton, C. Breast milk, a source of beneficial microbes and associated benefits for infant health. Nutrients 2020, 12, 1039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Exclusively Breastfeed for 6 Months. Available online: https://www.emro.who.int/nutrition/breastfeeding/index.html (accessed on 4 August 2025).
- Dieterich, C.M.; Felice, J.P.; O’Sullivan, E.; Rasmussen, K.M. Breastfeeding and health outcomes for the mother-infant dyad. Pediatr. Clin. N. Am. 2013, 60, 31–48. [Google Scholar] [CrossRef] [Scilit]
- Mantzorou, M.; Papandreou, D.; Vasios, G.K.; Pavlidou, E.; Antasouras, G.; Psara, E.; Taha, Z.; Poulios, E.; Giaginis, C. Exclusive breastfeeding for at least four months is associated with a lower prevalence of overweight and obesity in mothers and their children after 2–5 years from delivery. Nutrients 2022, 14, 3599. [Google Scholar] [CrossRef] [Scilit]
- Victora, C.G.; Bahl, R.; Barros, A.J.D.; Franca, G.V.A.; Horton, S.; Krasevec, J.; Murch, S.; Sankar, M.J.; Walker, N.; Rollins, N.C.; et al. Breastfeeding in the 21st century: Epidemiology, mechanisms, and lifelong effect. Lancet 2016, 387, 475–490. [Google Scholar] [CrossRef] [Scilit]
- Horta, B.L.; Victora, C.G. Long-Term Effects of Breastfeeding: A Systematic Review; World Health Organization: Geneva, Switzerland, 2013; pp. 1–69. Available online: https://www.who.int/publications/i/item/9789241505307 (accessed on 31 March 2026).
- Horta, B.L.; Loret de Mola, C.; Victora, C.G. Breastfeeding and intelligence: A systematic review and meta-analysis. Acta Pediatr. 2015, 104, 14–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Global Breastfeeding Scorecard 2023: Rates of Breastfeeding Increase Around the World Through Improved Protection and Support. Available online: https://www.who.int/publications/i/item/WHO-HEP-NFS-23.17 (accessed on 10 December 2025).
- Morrison, A.H.; Gentry, R.; Anderson, J. Mothers’ reasons for early breastfeeding cessation. MCN Am. J. Matern. Child Nurs. 2019, 44, 325–330. [Google Scholar] [CrossRef] [Scilit]
- Miranda, A.R.; Barral, P.E.; Scotta, A.V.; Cortez, M.V.; Soria, E.A. An overview of reviews of breastfeeding barriers and facilitators: Analyzing global research trends and hotspots. Glob. Epidemiol. 2025, 9, 100192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hobbs, A.J.; Mannion, C.A.; McDonald, S.W.; Brockway, M.; Tough, S.C. The impact of caesarean section on breastfeeding initiation, duration and difficulties in the first four months postpartum. BMC Pregnancy Childbirth 2016, 16, 90. [Google Scholar] [CrossRef] [Scilit]
- Perrella, S.L.; Abelha, S.G.; Vlaskovsky, P.; McEachran, J.L.; Prosser, S.A.; Geddes, D.T. Australian women’s experiences of establishing breastfeeding after caesarean birth. Int. J. Environ. Res. Public. Health 2024, 21, 296. [Google Scholar] [CrossRef] [Scilit]
- Smith, A.E.; Sweigart, E.; Falatic, K.; Stuart, D.; Szugye, H.; Lam, S.K.; Aly, H.; Das, A. Direct breastfeeding frequency of late preterm and term infants in the neonatal intensive care unit and availability of mother’s own milk at six months of age. A retrospective cohort study. J. Perinatol. 2024, 44, 1307–1311. [Google Scholar] [CrossRef] [Scilit]
- Bai, D.L.; Fong, D.Y.; Lok, K.Y.; Wong, J.Y.; Tarrant, M. Practices, predictors and consequences of expressed breast-milk feeding in healthy full-term infants. Public Health Nutr. 2017, 20, 492–503. [Google Scholar] [CrossRef] [Scilit]
- Rosenbaum, K.; McAlister, B. An integrative review of exclusive breast milk expression. J. Midwifery Womens Health 2025, 70, 325–335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Johns, H.M.; Amir, L.H.; McLachlan, H.L.; Forster, D.A. Breast pump use amongst mothers of healthy term infants in Melbourne, Australia: A prospective cohort study. Midwifery 2016, 33, 82–89. [Google Scholar] [CrossRef] [Scilit]
- Pang, W.W.; Bernard, J.Y.; Thavamani, G.; Chan, Y.H.; Fok, D.; Soh, S.E.; Chua, M.C.; Lim, S.B.; Shek, L.P.; Yap, F.; et al. Direct vs. expressed breast milk feeding: Relation to duration of breastfeeding. Nutrients 2017, 9, 547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DiTomasso, D.; Basley, S.; DeSanto-Madeya, S.; Palmer, M. Breast milk expression in mothers of full-term infants: A scoping review of available information. J. Hum. Lact. 2026. online ahead of print. [Google Scholar] [CrossRef] [Scilit]
- Meier, P.P.; Patel, A.L.; Hoban, R.; Engstrom, J.L. Which breast pump for which mother: An evidenced-based approach to individualizing breast pump technology. J. Perinatol. 2016, 36, 493–499. [Google Scholar] [CrossRef] [Scilit]
- Labiner-Wolfe, J.; Fein, S.B.; Shealy, K.R.; Wang, C. Prevalence of breast milk expression and associated factors. Pediatrics 2008, 122, S63–S68. [Google Scholar] [CrossRef] [Scilit]
- Gridneva, Z.; Warden, A.H.; McEachran, J.L.; Perrella, S.L.; Lai, C.T.; Geddes, D.T. Maternal and infant characteristics and pumping profiles of women that predominantly pump milk for their infants. Nutrients 2025, 17, 366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, R.; Fein, S.B.; Grummer-Strawn, L.M. Do infants fed from bottles lack self-regulation of milk intake compared wth directly breastfed infants? Pediatrics 2010, 125, e1386–e1393. [Google Scholar] [CrossRef] [Scilit]
- Li, R.; Magadia, J.; Fein, S.B.; Grummer-Strawn, L.M. Risk of bottle-feeding for rapid weight gain during the first year of life. Arch. Pediatr. Adolesc. Med. 2012, 166, 431–436. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Li, Y.; Qian, L.; Han, P.; Feng, H.; Jiang, H. Mothers’ experiences of breast milk expression during separation from their hospitalized infants: A systematic review of qualitative evidence. BMC Pregnancy Childbirth 2024, 24, 124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosenbaum, K.A. Exclusive breastmilk pumping: A concept analysis. Nurs. Forum 2022, 57, 946–953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pang, W.W.; Aris, I.M.; Fok, D.; Soh, S.E.; Chua, M.C.; Lim, S.B.; Saw, S.M.; Kwek, K.; Gluckman, P.D.; Godfrey, K.; et al. Determinants of Breastfeeding Practices and Success in a Multi-Ethnic Asian Population. Birth 2016, 43, 68–77. [Google Scholar] [CrossRef] [Scilit]
- Jiang, B.; Hua, J.; Wang, Y.; Fu, Y.; Zhuang, Z.; Zhu, L. Evaluation of the impact of breast milk expression in early postpartum period on breastfeeding duration: A prospective cohort study. BMC Pregnancy Childbirth 2015, 15, 268. [Google Scholar] [CrossRef] [Scilit]
- Foong, S.C.; Tan, M.L.; Foong, W.C.; Ho, J.J.; Rahim, F.F. Comparing breastfeeding experiences between mothers spending the traditional Chinese confinement period in a confinement centre and those staying at home: A cohort study. Int. Breastfeed. J. 2021, 16, 4. [Google Scholar] [CrossRef] [Scilit]
- Fan, H.S.L.; Fong, D.Y.T.; Lok, K.Y.W.; Tarrant, M. Experiences of expressed human milk feeding: A qualitative study. Sex. Reprod. Healthc. 2023, 38, 100903. [Google Scholar] [CrossRef] [Scilit]
- Kent, J.C.; Mitoulas, L.R.; Cregan, M.D.; Ramsay, D.T.; Doherty, D.A.; Hartmann, P.E. Volume and frequency of breastfeedings and fat content of breast milk throughout the day. Pediatrics 2006, 117, e387–e395. [Google Scholar] [CrossRef] [Scilit]
- Keim, S.A.; Boone, K.M.; Oza-Frank, R.; Geraghty, S.R. Pumping milk without ever feeding at the breast in the Moms2Moms Study. Breastfeed. Med. 2017, 12, 422–429. [Google Scholar] [CrossRef] [Scilit]
- Jardine, F.M. Breastfeeding Without Nursing: The Lived Experiences of Exclusive Pumpers; University of Maryland: College Park, MD, USA, 2020. [Google Scholar]
- Jardine, F.M. When online support groups prevail: The information experience of chest/breastfeeders who only express their milk. In Proceedings of the ISIC: The Information Behaviour Conference, Pretoria, South Africa, 28 September–1 October 2020. [Google Scholar]
- Hackman, N.M.; Schaefer, E.W.; Beiler, J.S.; Rose, C.M.; Paul, I.M. Breastfeeding outcome comparison by parity. Breastfeed. Med. 2015, 10, 156–162. [Google Scholar] [CrossRef] [Scilit]
- Wang, L.L.; Ma, J.J.; Meng, H.H.; Zhou, J. Mothers’ experiences of neonatal intensive care: A systematic review and implications for clinical practice. World J. Clin. Cases 2021, 9, 7062–7072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, P.A.; Taylor, R.; Thielke, R.; Payne, J.; Gonzalez, N.; Conde, J.G. Research electronic data capture (REDCap)—A metadata-driven methodology and workflow process for providing translational research informatics support. J. Biomed. Inform. 2009, 42, 377–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, P.A.; Taylor, R.; Minor, B.L.; Elliott, V.; Fernandez, M.; O’Neal, L.; McLeod, L.; Delacqua, G.; Delacqua, F.; Kirby, J.; et al. The REDCap consortium: Building an international community of software platform partners. J. Biomed. Inform. 2019, 95, 103208. [Google Scholar] [CrossRef] [Scilit]
- Li, R.; Ingol, T.T.; Smith, K.; Oza-Frank, R.; Keim, S.A. Reliability of maternal recall of feeding at the breast and breast milk expression 6 years after delivery. Breastfeed. Med. 2020, 15, 224–236. [Google Scholar] [CrossRef] [Scilit]
- Schneider, B.C.; Cata-Preta, B.O.; Gräf, D.D.; Silva, D.; Santos, F.S.; Dias, M.; Lautenschläger, P.; Weber, P.; Reyes Matos, U.; Martins-Silva, T.; et al. Validation of maternal recall on exclusive breastfeeding 12 months after childbirth. Public Health Nutr. 2020, 23, 2494–2500. [Google Scholar] [CrossRef] [Scilit]
- Faul, F.; Erdfelder, E.; Buchner, A.; Lang, A.-G. Statistical power analyses using G*Power 3.1: Tests for correlation and regression analyses. Behav. Res. Methods 2009, 41, 1149–1160. [Google Scholar] [CrossRef] [Scilit]
- Bausell, R.B.; Li, Y.-F. Power Analysis for Experimental Research; Cambridge University Press: New York, NY, USA, 2006; p. 363. [Google Scholar]
- Indrayan, A.; Mishra, A. The importance of small samples in medical research. J. Postgrad. Med. 2021, 67, 219–223. [Google Scholar] [CrossRef] [Scilit]
- Australian Institute of Health and Welfare. Australia’s Mothers and Babies. Available online: https://www.aihw.gov.au/reports/mothers-babies/australias-mothers-babies (accessed on 19 February 2025).
- Australian Institute of Health and Welfare. Diabetes: Australian Facts; AIHW: Canberra, Australia, 2024. [Google Scholar]
- Varanasi, L.C.; Subasinghe, A.; Jayasinghe, Y.L.; Callegari, E.T.; Garland, S.M.; Gorelik, A.; Wark, J.D. Polycystic ovarian syndrome: Prevalence and impact on the wellbeing of Australian women aged 16–29 years. Aust. N. Z. J. Obstet. Gynaecol. 2018, 58, 222–233. [Google Scholar] [CrossRef] [Scilit]
- Australian Bureau of Statistics. Mental Health; ABS: Canberra, Australia, 2018. [Google Scholar]
- Kent, J.C.; Ashton, E.; Hardwick, C.M.; Rowan, M.K.; Chia, E.S.; Fairclough, K.A.; Menon, L.L.; Scott, C.; Mather-McCaw, G.; Navarro, K.; et al. Nipple pain in breastfeeding mothers: Incidence, causes and treatments. Int. J. Environ. Res. Public. Health 2015, 12, 12247–12263. [Google Scholar] [CrossRef] [Scilit]
- Amir, L.H.; Forster, D.A.; Lumley, J.; McLachlan, H. A descriptive study of mastitis in Australian breastfeeding women: Incidence and determinants. BMC Public Health 2007, 7, 62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kent, J.C.; Ashton, E.; Hardwick, C.M.; Rea, A.; Murray, K.; Geddes, D.T. Causes of perception of insufficient milk supply in Western Australian mothers. Matern. Child. Nutr. 2021, 17, e13080. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamshidian, M.; Mata, M. 2—Advances in Analysis of Mean and Covariance Structure when Data are Incomplete. In Handbook of Computing and Statistics with Applications; Lee, S.-Y., Ed.; North-Holland: Amsterdam, The Netherlands, 2007; Volume 1, pp. 21–44. [Google Scholar]
- Braun, V.; Clarke, V. Using thematic analysis in psychology. Qual. Res. Psychol. 2006, 3, 77–101. [Google Scholar] [CrossRef] [Scilit]
- Bartick, M.; Smith, J.; Gribble, K. Pumps, patriarchy, and profits: The rise of breast pumping and “human milk feeding” and why preserving “breastfeeding” is important. Int. Breastfeed. J. 2026, 21, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jones, R.A.; Elhindi, J.; Lowe, G.; Henry, L.; Maheshwari, R.; Culcer, M.R.; Pasupathy, D.; Melov, S.J. Investigating short-stay admission to a neonatal intensive care unit as a risk factor for reduced breast feeding at discharge in infants ≥ 36 weeks’ gestation: A retrospective cohort study. BMJ Open 2023, 13, e075658. [Google Scholar] [CrossRef] [Scilit]
- Jiang, X.; Jiang, H.; Shan, S.S.; Huang, R. Breastfeeding experience of postnatal mothers separated from preterm infants after discharge: A phenomenology qualitative approach. BMC Pregnancy Childbirth 2024, 24, 28. [Google Scholar] [CrossRef] [Scilit]
- Seetho, S.; Kongwattanakul, K.; Saksiriwuttho, P.; Thepsuthammarat, K. Epidemiology and factors associated with preterm births in multiple pregnancy: A retrospective cohort study. BMC Pregnancy Childbirth 2023, 23, 872. [Google Scholar] [CrossRef] [Scilit]
- Zukova, S.; Krumina, V.; Buceniece, J. Breastfeeding preterm born infant: Chance and challenge. Int. J. Pediatr. Adolesc. Med. 2021, 8, 94–97. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fisher, J.; Hammarberg, K.; Wynter, K.; McBain, J.; Gibson, F.; Boivin, J.; McMahon, C. Assisted conception, maternal age and breastfeeding: An Australian cohort study. Acta Paediatr. 2013, 102, 970–976. [Google Scholar] [CrossRef] [Scilit]
- Barrera, C.M.; Kawwass, J.F.; Boulet, S.L.; Nelson, J.M.; Perrine, C.G. Fertility treatment use and breastfeeding outcomes. Am. J. Obstet. Gynecol. 2019, 220, 261.e261–261.e267. [Google Scholar] [CrossRef] [Scilit]
- Vizzari, G.; Morniroli, D.; D’Auria, A.; Travella, P.; Bezze, E.; Sannino, P.; Rampini, S.; Marchisio, P.; Plevani, L.; Mosca, F.; et al. Feeding difficulties in late preterm infants and their impact on maternal mental health and the mother-infant relationship: A literature review. Nutrients 2023, 15, 2180. [Google Scholar] [CrossRef] [Scilit]
- Kinoshita, M.; White, M.J.; Doolan, A. Clinical assessment of breastfeeding in preterm infants. Eur. J. Clin. Nutr. 2024, 78, 825–829. [Google Scholar] [CrossRef] [Scilit]
- Thomson, G.; McNally, L.; Nowland, R. Experiences and impacts of psychological support following adverse neonatal experiences or perinatal loss: A qualitative analysis. BMC Pregnancy Childbirth 2024, 24, 569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malouf, R.; Harrison, S.; Pilkington, V.; Opondo, C.; Gale, C.; Stein, A.; Franck, L.S.; Alderdice, F. Factors associated with posttraumatic stress and anxiety among the parents of babies admitted to neonatal care: A systematic review. BMC Pregnancy Childbirth 2024, 24, 352. [Google Scholar] [CrossRef] [Scilit]
- Gong, J.; Fellmeth, G.; Quigley, M.A.; Gale, C.; Stein, A.; Alderdice, F.; Harrison, S. Prevalence and risk factors for postnatal mental health problems in mothers of infants admitted to neonatal care: Analysis of two population-based surveys in England. BMC Pregnancy Childbirth 2023, 23, 370. [Google Scholar] [CrossRef] [Scilit]
- Leach, L.S.; Poyser, C.; Fairweather-Schmidt, K. Maternal perinatal anxiety: A review of prevalence and correlate. Clin. Psychol. 2017, 21, 4–19. [Google Scholar] [CrossRef] [Scilit]
- Bobevski, I.; Rowe, H.; Clarke, D.M.; McKenzie, D.P.; Fisher, J. Early postnatal demoralisation among primiparous women in the community: Measurement, prevalence and associated factors. BMC Pregnancy Childbirth 2015, 15, 259. [Google Scholar] [CrossRef] [Scilit]
- Nakamura, Y.; Okada, T.; Morikawa, M.; Yamauchi, A.; Sato, M.; Ando, M.; Ozaki, N. Perinatal depression and anxiety of primipara is higher than that of multipara in Japanese women. Sci. Rep. 2020, 10, 17060. [Google Scholar] [CrossRef] [Scilit]
- Sandi, C.; Haller, J. Stress and the social brain: Behavioural effects and neurobiological mechanisms. Nat. Rev. Neurosci. 2015, 16, 290–304. [Google Scholar] [CrossRef] [Scilit]
- Bontempo, A.C. The effect of personalized invalidation of symptoms by healthcare providers on patient depression: The mediating role of self-esteem. Patient Educ. Couns. 2022, 105, 1598–1605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strauch, L.; Sweet, L.; Scott, H.; Müller, A. Mechanisms of support for exclusive breastmilk expressers in the community: A scoping review. BMC Pregnancy Childbirth 2019, 19, 511. [Google Scholar] [CrossRef] [Scilit]
- Yakov, Y.Y. Perceived insufficient milk supply (pims) in lactating mothers. In Multiple Pregnancy; Hassan, S.A., Ed.; IntechOpen: London, UK, 2022; pp. 1–8. [Google Scholar]
- Bookhart, L.H.; Anstey, E.H.; Kramer, M.R.; Perrine, C.G.; Reis-Reilly, H.; Ramakrishnan, U.; Young, M.F. A nation-wide study on the common reasons for infant formula supplementation among healthy, term, breastfed infants in US hospitals. Matern. Child. Nutr. 2022, 18, e13294. [Google Scholar] [CrossRef] [Scilit]
- Jin, X.; Lai, C.T.; Perrella, S.L.; McEachran, J.L.; Gridneva, Z.; Geddes, D.T. Maternal breast growth and body mass index are associated with low milk production in women. Nutrients 2024, 16, 2854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karaburun, I.E.G.; Yalçın, S.S. Breast refusal: An analysis of frequency, onset timing, recovery status, and their interplay with breastfeeding self-efficacy and maternal depression. BMC Public Health 2024, 24, 3568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burns, E.; Elcombe, E.; Pierce, H.; Hugman, S.; Gannon, S. Breastfeeding after return to work: An Australian national workplace survey. Matern. Child. Nutr. 2023, 19, e13516. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Colbenson, G.A.; Hoff, O.; Olson, E.M.; Ducharme-Smith, A. The impact of wearable breast pumps on physicians’ breastfeeding experience and success. Breastfeed. Med. 2022, 17, 537–543. [Google Scholar] [CrossRef] [Scilit]
- Holowko, N.; Jones, M.; Koupil, I.; Tooth, L.; Mishra, G. High education and increased parity are associated with breast-feeding initiation and duration among Australian women. Public Health Nutr. 2016, 19, 2551–2561. [Google Scholar] [CrossRef] [Scilit]



| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Infant age at survey (months) | 7.1 [3.9, 14.0] 1 | 6.3 [3.4, 11.9] | 8.1 [3.9, 16.6] | 0.061 |
| Primiparous | 120 (61.5) | 60 (57.1) | 60 (66.7) | 0.037 |
| EP status | ||||
| Currently EP | 113 (58.0) | 61 (58.1) | 52 (57.8) | 0.96 |
| Previously EP | 82 (42.0) | 44 (41.9) | 38 (42.2) | 0.96 |
| EP ceased 3 | n = 81 | n = 44 | n = 38 | |
| Infant age at EP cessation (months) 3 | 6.0 [4.0, 9.0] | 6.0 [4.0, 9.0] | 5.0 [3.0, 10.5] | 0.67 |
| Reasons for EP cessation 4 | ||||
| Too difficult to pump and take care of infant | 34 (42.0) | 19 (44.2) | 15 (39.5) | 0.67 |
| Low milk supply | 22 (27.2) | 10 (23.3) | 12 (31.6) | 0.40 |
| Infant started to direct BF | 20 (24.7) | 10 (23.3) | 10 (26.3) | 0.75 |
| Pumping was too painful or uncomfortable | 6 (7.4) | 5 (11.6) | 1 (2.6) | 0.21 |
| Having large amounts of frozen milk | 6 (7.4) | 5 (11.6) | 1 (2.6) | 0.21 |
| Mental health | 5 (6.2) | 4 (9.3) | 1 (2.6) | 0.36 |
| Other 5 | 24 (29.6) | 13 (30.2) | 11 (28.9) | 0.90 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Country | ||||
| Australia | 180 (92.3) 1 | 93 (88.6) | 87 (96.7) | 0.034 |
| United States of America | 8 (4.1) | 6 (5.7) | 2 (2.2) | 0.29 |
| United Kingdom | 3 (1.5) | 2 (1.9) | 1 (1.1) | 1.00 |
| New Zealand | 3 (1.5) | 3 (2.9) | 0 (0.0) | 0.18 |
| France | 1 (0.5) | 1 (0.9) | 0 (0.0) | 1.00 |
| Education level | ||||
| High school | 22 (11.3) | 13 (12.4) | 9 (10.0) | 0.66 |
| Certificate/diploma | 45 (23.1) | 24 (22.9) | 21 (23.3) | 0.94 |
| Bachelor’s degree or above | 128 (65.6) | 68 (64.8) | 60 (66.7) | 0.78 |
| Marital status | ||||
| Never married or de facto | 10 (5.1) | 7 (6.7) | 3 (3.3) | 0.35 |
| Married or de facto | 182 (93.3) | 98 (93.3) | 84 (93.3) | 1.00 |
| Separated or divorced | 3 (1.6) | 0 (0.0) | 3 (3.3) | 0.097 |
| Pre-pregnancy BMI (kg/m2) | 27.6 [23.8, 32.5] | 28.7 [25.1, 33.1] | 26.7 [22.5, 31.0] | 0.001 |
| Current BMI (kg/m2) | n = 192 | n = 105 | n = 87 | |
| 29.1 [24.8, 32.8] | 30.1 [26.3, 33.9] | 27.5 [23.3, 32.1] | 0.001 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Planned infant feeding method | ||||
| Exclusive BF | 97 (49.7) 1 | 58 (55.2) | 39 (43.3) | 0.097 |
| Mix of breastfeeding and pumping | 51 (26.2) | 28 (26.7) | 23 (25.6) | 0.86 |
| Mix of BF, pumping and formula feeding | 15 (7.7) | 5 (4.8) | 10 (11.1) | 0.11 |
| Exclusive bottle feeding of EBM | 10 (5.1) | 4 (3.8) | 6 (6.7) | 0.52 |
| Exclusive formula feeding | 4 (2.1) | 0 (0.0) | 4 (4.4) | 0.044 |
| No plans | 18 (9.2) | 10 (9.5) | 8 (8.9) | 1.00 |
| Intended BF length (months) | n = 192 | n = 103 | n = 89 | |
| 12.0 [9.8, 14.5] | 12.0 [12.0, 12.0] | 12.0 [8.0, 18.0] | 0.94 | |
| BF information sources accessed 3 | n = 195 | n = 105 | n = 90 | |
| Did not access BF information | 43 (22.1) | 11 (10.5) | 32 (35.6) | <0.001 |
| Midwife/OBGYN nurse | 91 (46.7) | 55 (52.4) | 36 (40.0) | 0.084 |
| Online/social media | 84 (43.1) | 58 (55.2) | 26 (28.9) | <0.001 |
| Lactation consultant | 65 (33.3) | 38 (36.2) | 27 (30.0) | 0.36 |
| BF class | 48 (24.6) | 24 (22.9) | 24 (26.7) | 0.54 |
| Online forums/groups | 42 (21.5) | 27 (25.7) | 15 (16.7) | 0.13 |
| Obstetrician | 28 (14.4) | 17 (15.2) | 12 (13.3) | 0.61 |
| GP/family physician | 22 (11.3) | 13 (12.4) | 9 (10.0) | 0.66 |
| Doula | 2 (1.0) | 2 (1.9) | 0 (0.0) | 0.50 |
| Other 4 | 10 (5.1) | 8 (7.6) | 2 (2.2) | 0.11 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Number of births for this pregnancy | ||||
| Singleton birth | 181 (92.8) 1 | 104 (99.0) | 77 (85.6) | <0.001 |
| Multiple births (twins) | 14 (7.2) | 1 (1.0) | 13 (14.4) | <0.001 |
| Pregnancy complications 3 | ||||
| No complications | 68 (34.9) | 50 (47.6) | 18 (20.0) | <0.001 |
| Gestational diabetes mellitus | 44 (22.6) | 22 (21.0) | 22 (24.4) | 0.56 |
| Hypertension | 34 (17.4) | 17 (16.2) | 17 (18.9) | 0.62 |
| Foetal growth restriction | 34 (17.4) | 6 (5.7) | 28 (31.1) | <0.001 |
| Preeclampsia | 29 (14.9) | 6 (5.7) | 23 (25.6) | <0.001 |
| Placental insufficiency | 16 (8.2) | 2 (1.9) | 14 (15.6) | <0.001 |
| Anaemia | 14 (7.2) | 10 (9.5) | 4 (4.4) | 0.27 |
| Other 4 | 42 (21.5) | 13 (12.4) | 29 (32.2) | <0.001 |
| Breast growth during pregnancy | ||||
| Breasts grew by one bra cup size or more | 147 (75.4) | 74 (70.5) | 73 (81.1) | 0.086 |
| No breast growth | 33 (16.9) | 19 (18.1) | 14 (15.6) | 0.64 |
| Unsure | 15 (7.7) | 12 (11.4) | 3 (3.3) | 0.056 |
| Perceived change in breast density | ||||
| Breast density increased | 157 (80.5) | 81 (77.1) | 76 (84.4) | 0.20 |
| Breast density did not change | 29 (14.9) | 18 (17.1) | 11 (12.2) | 0.34 |
| Unsure | 9 (4.6) | 6 (5.7) | 3 (3.3) | 0.51 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Maternal health conditions 3 | ||||
| No health conditions | 84 (43.1) 1 | 49 (46.7) | 35 (38.9) | 0.27 |
| Anxiety 4 | 62 (31.8) | 31 (29.5) | 31 (34.4) | 0.46 |
| Depression 4 | 39 (20.0) | 21 (20.0) | 18 (20.0) | 1.00 |
| Fertility issues | 31 (15.9) | 10 (9.5) | 21 (23.3) | 0.009 |
| Polycystic ovary syndrome | 29 (14.9) | 16 (15.2) | 13 (14.4) | 0.88 |
| Thyroid disorder | 12 (6.2) | 6 (5.7) | 6 (6.7) | 0.75 |
| Insulin resistance | 8 (4.1) | 4 (3.8) | 4 (4.4) | 1.00 |
| Diabetes | 1 (0.5) | 0 (0.0) | 1 (1.1) | 0.46 |
| Other | 25 (12.8) | 14 (13.3) | 11 (12.2) | 0.82 |
| Breast conditions/surgery 3 | ||||
| No conditions | 114 (58.5) | 64 (61.0) | 50 (55.6) | 0.45 |
| Mastitis | 35 (18.0) | 16 (15.2) | 19 (21.1) | 0.29 |
| Large nipples | 28 (14.4) | 19 (18.1) | 9 (10.0) | 0.15 |
| Nipple piercing | 19 (9.7) | 11 (10.5) | 8 (8.9) | 0.81 |
| Flat/short nipples | 15 (7.7) | 8 (7.6) | 7 (7.8) | 1.00 |
| Cysts | 9 (4.6) | 7 (6.7) | 2 (2.2) | 0.18 |
| Benign lump | 3 (1.5) | 1 (1.0) | 2 (2.2) | 0.60 |
| Breast augmentation | 2 (1.0) | 1 (1.0) | 1 (1.1) | 1.00 |
| Breast reduction | 2 (1.0) | 1 (1.0) | 1 (1.1) | 1.00 |
| Breast lumpectomy | 2 (1.0) | 1 (1.0) | 1 (1.1) | 1.00 |
| Breast abscess | 1 (0.5) | 0 (0.0) | 1 (1.1) | 0.46 |
| Other | 5 (2.6) | 4 (3.8) | 1 (1.1) | 0.38 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Type of birth | ||||
| Unassisted vaginal birth | 63 (32.3) 1 | 51 (48.6) | 12 (13.3) | <0.001 |
| Vacuum-assisted vaginal birth | 7 (3.6) | 6 (5.7) | 1 (1.1) | 0.13 |
| Forceps-assisted vaginal birth | 7 (3.6) | 4 (3.8) | 3 (3.3) | 1.00 |
| Planned caesarean section | 46 (23.6) | 25 (23.8) | 21 (23.3) | 0.94 |
| Unplanned caesarean section | 72 (36.9) | 19 (18.1) | 53 (58.9) | <0.001 |
| Infant characteristics | ||||
| Birth gestation (weeks) | 38.6 [35.3, 39.4] | 39.1 [38.7, 40.1] | 34.6 [30.1, 37.6] | <0.001 |
| Preterm infants (all; <37 weeks) | 62 (31.8) | 0 (0.0) | 62 (68.9) | <0.001 |
| Extremely preterm (<28 weeks) | 18 (9.2) | 0 (0.0) | 18 (20.0) | <0.001 |
| Very preterm (28–32 weeks) | 14 (7.2) | 0 (0.0) | 14 (15.6) | <0.001 |
| Moderate-to-late preterm (32–37 weeks) | 30 (15.4) | 0 (0.0) | 30 (33.3) | <0.001 |
| Term (>37 weeks) | 133 (68.2) | 105 (100.0) | 28 (31.1) | <0.001 |
| Neonatal unit admission | 83 (42.6) | 0 (0.0) | 83 (92.2) | <0.001 |
| Infant health condition | 52 (26.7) | 12 (11.4) | 40 (44.4) | <0.001 |
| Direct BF attempted | 152 (78.0) | 102 (97.1) | 50 (55.6) | <0.001 |
| Infant latch in 1st week | n = 152 | n = 102 | n = 50 | |
| Infant did not latch well most/all of the time | 71 (46.7) | 40 (39.2) | 31 (62.0) | 0.008 |
| Latch caused pain | 50 (32.9) | 38 (37.3) | 12 (24.0) | 0.10 |
| Infant latched well most/all of the time | 31 (20.4) | 24 (23.5) | 7 (14.0) | 0.20 |
| Infant diet in the 1st week 3 | n = 195 | n = 105 | n = 90 | |
| EBM | 165 (84.6) | 81 (77.1) | 84 (93.3) | 0.002 |
| Breast milk directly from the breast | 89 (45.6) | 70 (66.7) | 19 (21.1) | <0.001 |
| Commercial milk formula | 64 (32.8) | 38 (36.2) | 26 (28.9) | 0.28 |
| Donor human milk | 18 (9.2) | 2 (1.9) | 16 (17.8) | <0.001 |
| Other | 4 (2.1) | 1 (1.0) | 3 (3.3) | 0.34 |
| Duration of attempting direct BF | n = 152 | n = 102 | n = 50 | |
| 1st week | 30 (19.7) | 22 (21.6) | 8 (16.0) | 0.52 |
| 1st month | 43 (28.3) | 31 (30.4) | 12 (24.0) | 0.41 |
| 2–3 months | 38 (25.0) | 23 (22.5) | 15 (30.0) | 0.32 |
| 3–6 months | 14 (9.2) | 12 (11.8) | 2 (4.0) | 0.15 |
| Direct BF still attempted | 27 (17.8) | 14 (13.7) | 13 (26.0) | 0.15 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| Lactation challenges 3 | ||||
| No challenges | 0 (0.0) 1 | 0 (0.0) | 0 (0.0) | 1.00 |
| Latching issues | 144 (73.9) | 85 (81.0) | 59 (65.6) | 0.015 |
| Perceived low milk supply | 84 (43.1) | 42 (40.0) | 42 (46.7) | 0.35 |
| Blocked ducts | 83 (42.6) | 46 (43.8) | 37 (41.1) | 0.70 |
| Damaged/painful nipples from BF | 80 (41.0) | 57 (54.3) | 23 (25.6) | <0.001 |
| Damaged/painful nipples from pumping | 80 (41.0) | 37 (35.2) | 43 (47.8) | 0.076 |
| Oversupply | 58 (29.7) | 28 (26.7) | 30 (33.3) | 0.31 |
| Mastitis | 50 (25.6) | 26 (24.8) | 24 (26.7) | 0.76 |
| Nipple bleb | 44 (22.6) | 28 (26.7) | 16 (17.8) | 0.11 |
| BF services/information sources accessed 3 | ||||
| No BF services or information accessed | 9 (4.6) | 4 (3.8) | 5 (5.6) | 0.74 |
| Lactation consultant | 157 (80.5) | 84 (80.0) | 73 (81.1) | 0.85 |
| Midwife | 104 (53.3) | 56 (53.3) | 48 (53.3) | 1.00 |
| Websites | 88 (45.1) | 53 (50.5) | 35 (38.9) | 0.11 |
| Community child health nurse | 74 (37.9) | 45 (42.9) | 29 (32.2) | 0.13 |
| General practitioner | 48 (24.6) | 25 (23.8) | 23 (25.6) | 0.78 |
| Breastfeeding helpline | 44 (22.6) | 25 (23.8) | 19 (21.1) | 0.65 |
| Mothers group | 41 (21.0) | 29 (27.6) | 12 (13.3) | 0.015 |
| Paediatrician | 29 (14.9) | 19 (18.1) | 10 (11.1) | 0.098 |
| Obstetrician | 21 (10.8) | 9 (8.6) | 12 (13.3) | 0.36 |
| Other | 12 (6.2) | 8 (7.6) | 4 (4.4) | 0.39 |
| Characteristics | Total n = 195 | HT Group n = 105 | SP Group n = 90 | p-Value 2 |
|---|---|---|---|---|
| When did the woman first learn about EP? | ||||
| Before this pregnancy | 83 (42.6) 1 | 52 (49.5) | 31 (34.4) | 0.034 |
| During this pregnancy | 26 (13.3) | 14 (13.3) | 12 (13.3) | 1.00 |
| After the birth of this infant | 79 (40.5) | 36 (34.3) | 43 (47.8) | 0.056 |
| Unsure | 7 (3.6) | 3 (2.9) | 4 (4.4) | 0.71 |
| Factors leading to EP 3 | ||||
| Latching issues | 121 (62.1) | 78 (74.3) | 43 (47.8) | <0.001 |
| Mother wanted to know milk intake | 69 (35.4) | 41 (39.0) | 28 (31.1) | 0.25 |
| Infant breast refusal | 66 (33.9) | 44 (41.9) | 22 (24.4) | 0.010 |
| Neonatal unit admission | 64 (32.8) | 0 (0.0) | 64 (71.1) | <0.001 |
| Sharing infant feeding responsibility | 56 (28.7) | 31 (29.5) | 25 (27.8) | 0.79 |
| Pain during direct breastfeeding | 49 (25.1) | 38 (36.2) | 11 (12.2) | <0.001 |
| Infant health condition | 42 (21.5) | 16 (15.2) | 26 (28.9) | 0.021 |
| Personal choice | 24 (12.3) | 13 (12.3) | 11 (12.2) | 0.97 |
| Low milk supply | 22 (11.3) | 12 (11.4) | 10 (11.1) | 0.94 |
| Returning to paid work | 17 (8.7) | 13 (12.3) | 4 (4.4) | 0.073 |
| Slow infant weight gain | 11 (5.6) | 10 (9.5) | 1 (1.1) | 0.012 |
| Multiple infants | 10 (5.1) | 1 (1.0) | 9 (10.0) | 0.006 |
| Other 4 | 28 (14.4) | 16 (15.2) | 11 (12.2) | 0.54 |
| EP challenges experienced 3 | ||||
| Time constraints of pumping | 166 (85.1) | 91 (86.7) | 75 (83.3) | 0.51 |
| Managing pumping around infant care | 162 (83.1) | 94 (89.5) | 68 (75.6) | 0.010 |
| Nighttime pumping | 141 (72.3) | 80 (76.2) | 61 (67.8) | 0.19 |
| Discomfort caused by pumping | 111 (56.9) | 68 (64.8) | 43 (47.8) | 0.017 |
| Sore nipples | 99 (50.8) | 49 (46.7) | 50 (55.6) | 0.22 |
| Cost of pumping supplies | 98 (50.3) | 54 (51.4) | 44 (48.9) | 0.72 |
| Painful breasts | 84 (43.1) | 45 (42.9) | 39 (43.3) | 0.95 |
| Low milk supply | 81 (41.5) | 38 (36.2) | 43 (47.8) | 0.10 |
| EBM storage | 74 (38.0) | 41 (39.0) | 33 (36.7) | 0.73 |
| Judgement | 73 (37.4) | 43 (41.0) | 30 (33.3) | 0.27 |
| Lack of knowledge | 63 (32.3) | 35 (33.3) | 28 (31.1) | 0.74 |
| Oversupply | 52 (26.7) | 28 (26.7) | 24 (26.7) | 1.00 |
| Thawing of frozen EBM | 42 (21.5) | 23 (21.9) | 19 (21.1) | 0.89 |
| Faulty pump | 27 (13.9) | 14 (13.3) | 11 (12.2) | 0.82 |
| Work commitments | 23 (11.8) | 12 (10.0) | 9 (10.0) | 0.82 |
| Other | 16 (8.2) | 9 (8.6) | 7 (7.8) | 1.00 |
| Characteristics | EP Women Frequency n = 180 | General Population Frequency | Total Sample Size | p-Value 2 |
|---|---|---|---|---|
| Mode of birth | ||||
| Caesarean section | 112 (62.2) 1 | 114,440 (39.0) 3 | 293,615 | <0.001 |
| Pregnancy complications and infant health conditions | ||||
| GDM | 42 (23.3) | 53,900 (18.0) 4 | 299,624 | 0.063 |
| Gestational hypertension | 31 (17.2) | 8758 (3.2) 5 | 267,654 | <0.001 |
| Preterm birth | 58 (32.2) | 23,888 (8.4) 6 | 285,485 | <0.001 |
| Neonatal unit admission | 81 (45.0) | 29,548 (17.9) 6 | 164,823 | <0.001 |
| Maternal health conditions | ||||
| Anxiety/depression | 91 (50.5) | 1,917,557 (15.7) 7 | 12,213,920 | <0.001 |
| Polycystic ovary syndrome | 27 (15.0) | 31 (12.2) 8 | 434 | 0.40 |
| Lactation challenges | ||||
| Nipple pain | 141 (78.3) | 169 (36.0) 9 | 649 | <0.001 |
| Percieved low milk supply | 79 (43.9) | 171 (44.2) 10 | 567 | 0.95 |
| Mastitis | 47 (26.1) | 206 (17.0) 11 | 1373 | 0.004 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Gridneva, Z.; McEachran, J.L.; Ireland, D.J.; Perrella, S.L.; Geddes, D.T. Maternal Experiences with Exclusive Pumping—An Online Survey. Healthcare 2026, 14, 1361. https://doi.org/10.3390/healthcare14101361
Gridneva Z, McEachran JL, Ireland DJ, Perrella SL, Geddes DT. Maternal Experiences with Exclusive Pumping—An Online Survey. Healthcare. 2026; 14(10):1361. https://doi.org/10.3390/healthcare14101361
Chicago/Turabian StyleGridneva, Zoya, Jacki L. McEachran, Demelza J. Ireland, Sharon L. Perrella, and Donna T. Geddes. 2026. "Maternal Experiences with Exclusive Pumping—An Online Survey" Healthcare 14, no. 10: 1361. https://doi.org/10.3390/healthcare14101361
APA StyleGridneva, Z., McEachran, J. L., Ireland, D. J., Perrella, S. L., & Geddes, D. T. (2026). Maternal Experiences with Exclusive Pumping—An Online Survey. Healthcare, 14(10), 1361. https://doi.org/10.3390/healthcare14101361