


Characteristics, Attitudes and Preferences of an End-Stage Kidney Disease Population at the Beginning of an Exercise Program: A Pragmatic Multicenter Trial
 , ,
 , ,
 ,
 , and
Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design and Settings
2.2. Inclusion Criteria
2.3. Intervention: First Contact with ESKD Patients
2.4. Intervention: Training Options
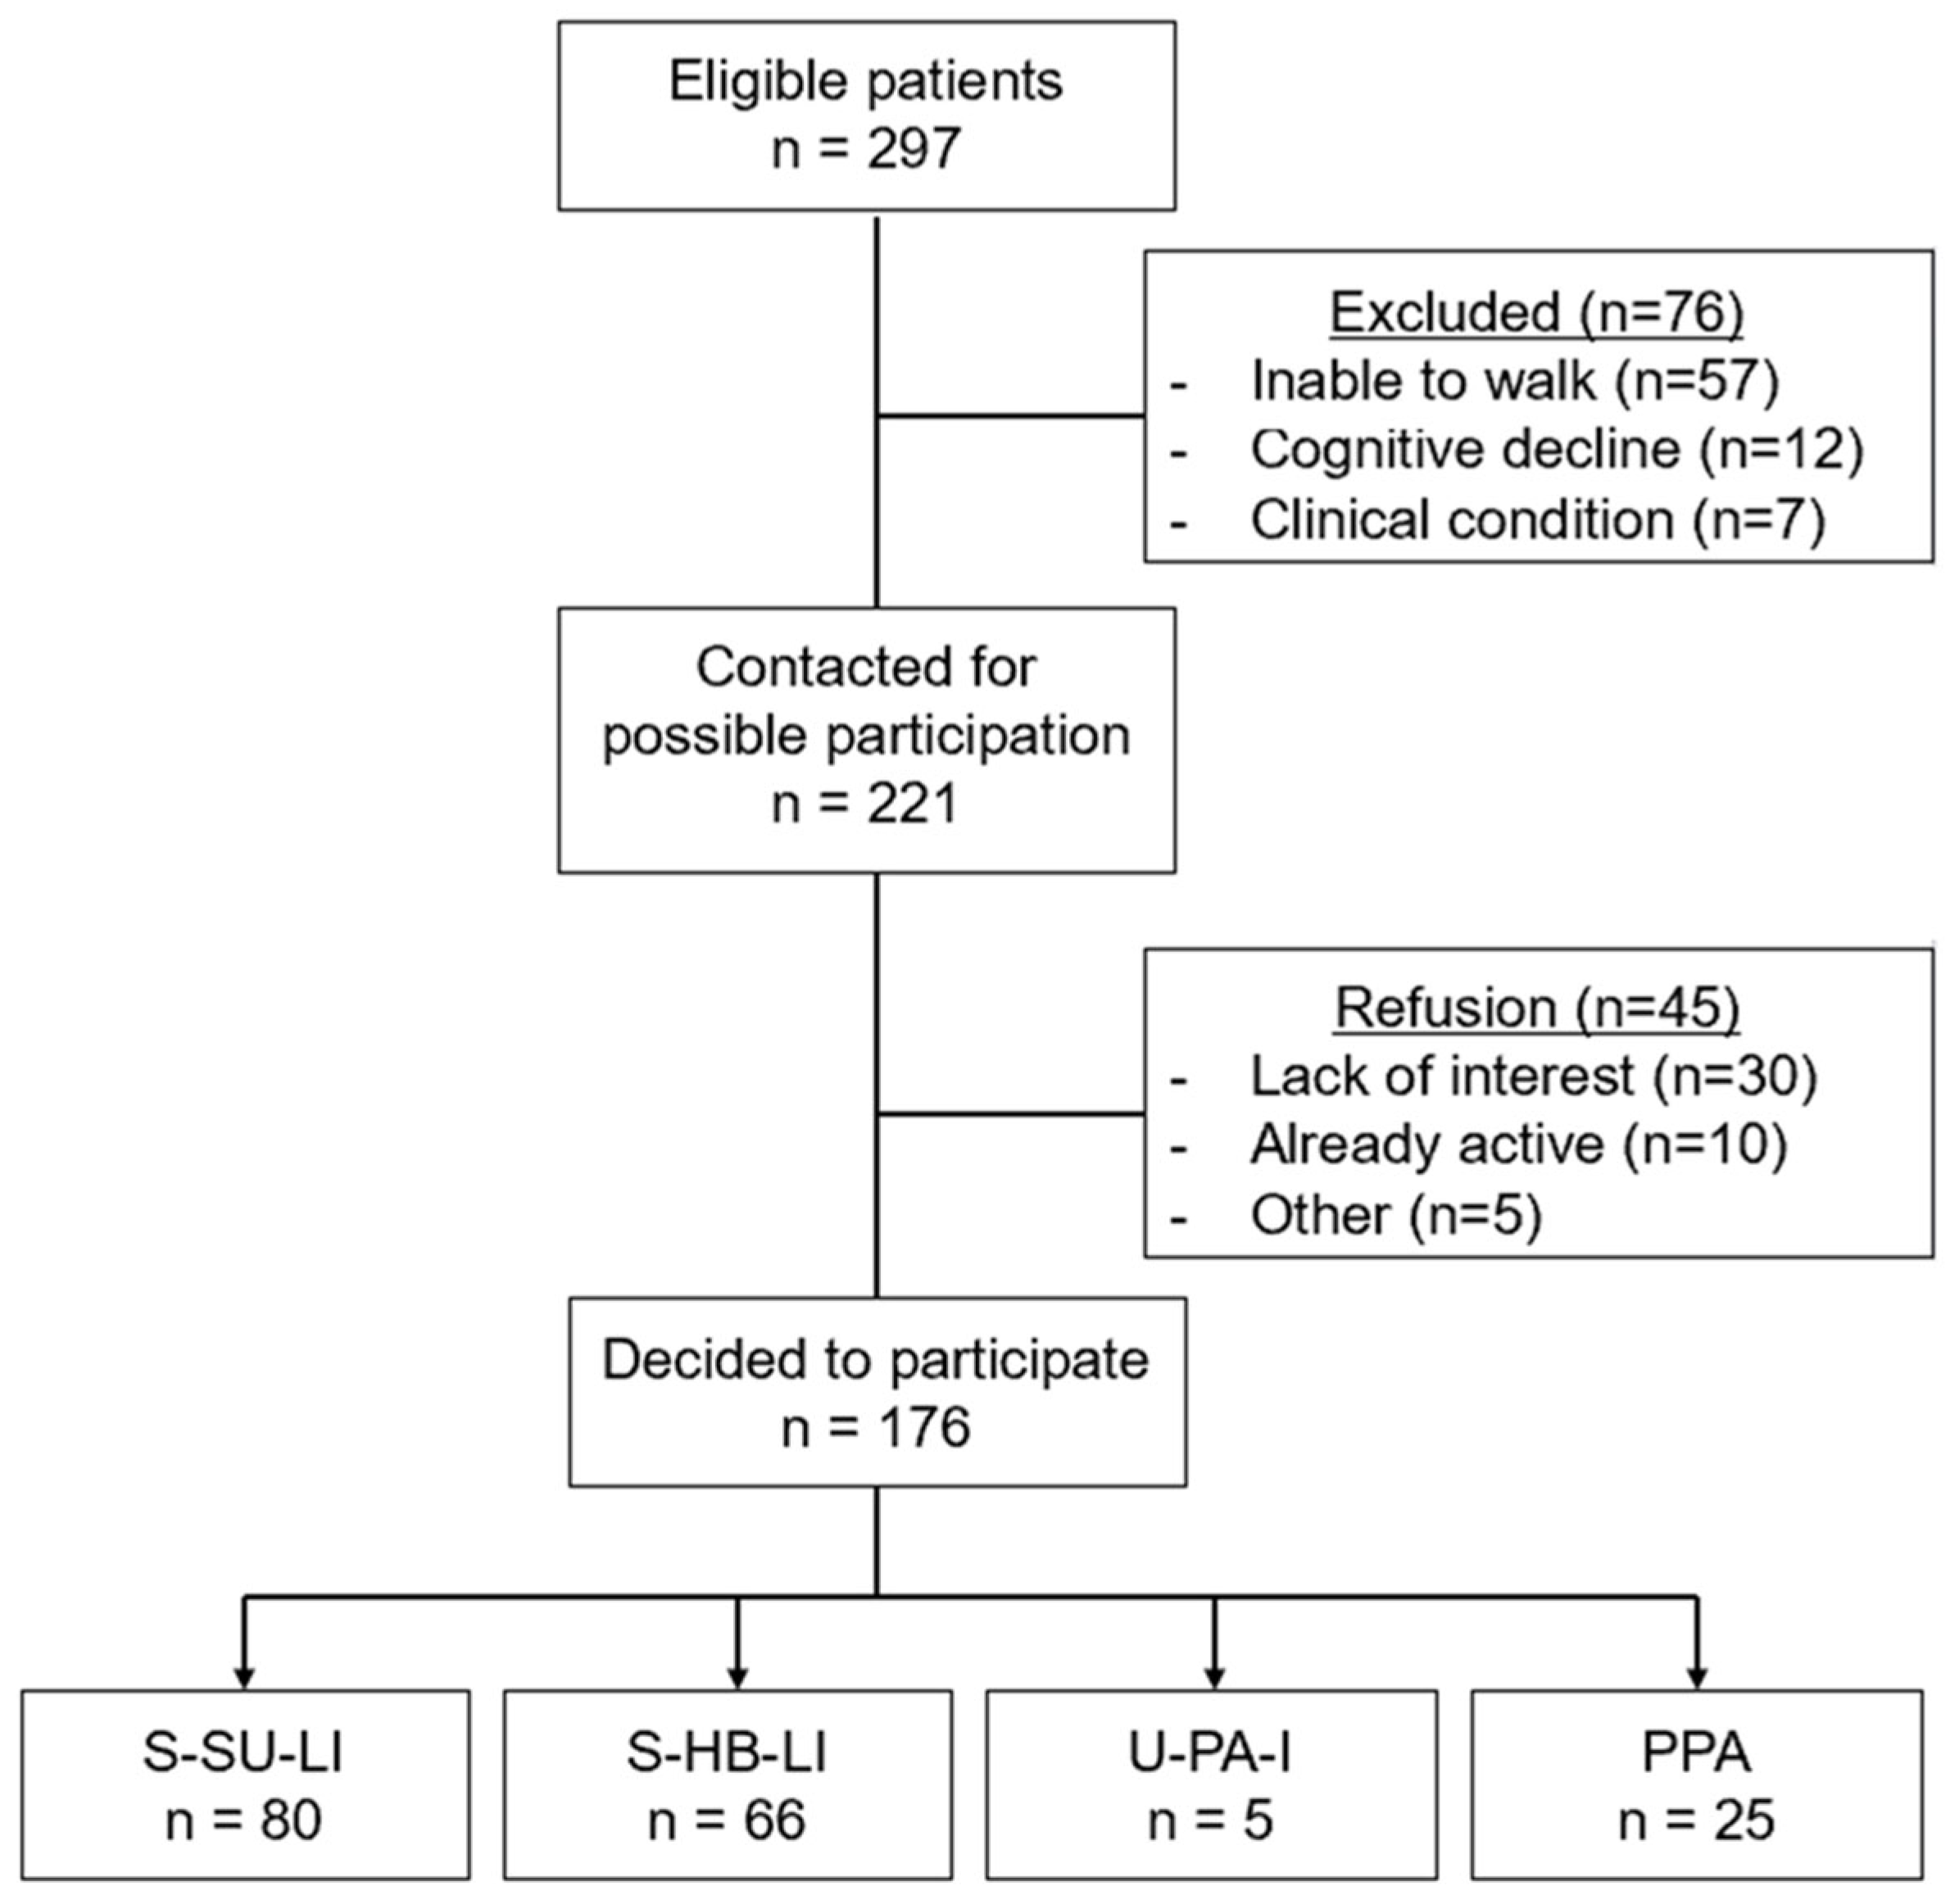
- Unstructured physical activity (U-PA-I): In accordance with the guidelines for physical activity for people on dialysis, advice was given on recommended amounts of exercise, although no structured programs were provided for implementation [65]. This intervention required no specific material;
- Structured home-based low-intensity exercise (S-HB-LI): According to each patient’s baseline physical activity level, a semipersonalized walking program was provided composed of a 1 min walking:1 min resting ratio to be repeated 6 or 8 times according to the patient’s baseline functional capacity. The training speed, which was maintained through a metronome, progressively increased throughout the program [46,66]. The equipment for this option was represented by a metronome, in the form of an instrument or a smartphone application that was downloadable at no cost;
- Structured supervised low-intensity exercise (S-SU-LI): Patients met at a specified location (room or corridor) into the dialysis unit for the exercise program in groups of a maximum of four subjects. The thirty-minute training sessions were scheduled on a 2- or 3-time/week pattern, and they were performed immediately before or after the dialysis treatment or according to patients’ preferences and considering the postdialysis fatigue that affects this population [67]. Each exercise session was composed of a low-intensity interval walking component and a strengthening component for the lower and upper limb muscles. The training intensity progressed throughout the program [62]. The equipment, in addition to the metronome reported above, required four ankle weights of different loads;
- Physical performance assessment only (PPA): Patients who chose this option did not begin any exercise program, but they performed the outcome measures session only. A switch to another treatment, periodically proposed by the EF, was always possible.
2.5. Intervention: Outcome Measures
- Gait speed through the 10 m walk test. The subjects were asked to walk as fast as possible over a distance of 10 m, without putting themselves at risk, and to use any walking aids if necessary. The time taken to cover the central 6 m was recorded. The test was repeated twice, and the best result was reported [69];
- Lower limb strength was measured by the 5-time sit-to-stand test (5STS). Patients were placed in a standard chair and asked to stand up and sit down from the chair five times as quickly as possible without using their arms for support. The data collected were the time between the first stand-up and the moment when the subject’s glutes touched the chair for the fifth time [70];
- Health-related QoL was measured by the Italian version of the Short Form Health Survey (SF-36). The questionnaire, which was administered to patients during dialysis sessions, consists of 36 questions that explore how much a person’s health status impacts their perceived quality of life. The results are expressed in eight domains, each with a score from 0 to 100, concerning aspects related to physical and mental health [71];
- Fear of falling was assessed through the Short Falls Efficacy Scale (S-FES-I). This tool consists of seven items that measure the subject’s perceived fear of falling while performing different activities. The total score ranges from 7 to 28, with higher values corresponding to greater fear of falling [72];
- Depression was evaluated by the Beck Depression Inventory-II (BDI-II). This questionnaire consists of 21 items that measure the subject’s level of depression through a series of questions related to the previous two weeks. The score ranges from 0 to 63, with the degree of depression increasing as the score increases [73];
2.6. Sample Size
2.7. Statistical Analyses
3. Results
3.1. Contact with the Eligible Patients
3.2. Factors Associated with Patients’ Choice of Different Active Programs
3.3. Age and Sex
3.4. Dialysis History and Comorbidities
3.5. Transportation
3.6. Level of Physical Functioning at Entry
3.7. Depressive Symptoms and Quality of Life
4. Discussion
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| EF | Exercise facilitator |
| ESKD | End-stage kidney disease |
| U-PA-I | Advised physical activity increase |
| S-HB-LI | Structured home-based walking exercise |
| S-SU-LI | Supervised walking and resistance low-intensity training |
| PPA | Performance assessment only |
| CKD | Chronic kidney disease |
| HD | Hemodialysis |
| 5STS | 5-time sit-to-stand test |
| SF-36 | Short Form Health Survey |
| S-FES-I | Short Falls Efficacy Scale |
| BDI-II | Beck Depression Inventory-II |
| SD | Standard deviation |
| n.a. | Not available |
| 6MWD | Six-minute walking distance |
| T10m | Ten-meter walking test |
| DASI | Duke’s activity status index |
| SDT | Self-determination theory |
References
- Jadoul, M.; Aoun, M.; Masimango Imani, M. The major global burden of chronic kidney disease. Lancet Glob. Health 2024, 12, e342–e343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney Int. 2024, 105, S117–S314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Himmelfarb, J.; Vanholder, R.; Mehrotra, R.; Tonelli, M. The current and future landscape of dialysis. Nat. Rev. Nephrol. 2020, 16, 573–585. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piva, G.; Storari, A.; Battaglia, Y.; Manfredini, F.; Lamberti, N. Exercise, Dialysis, and Environment: A Narrative Review in an Ecological Perspective. Kidney Blood Press. Res. 2024, 49, 773–786. [Google Scholar] [CrossRef] [Scilit]
- Kooman, J.P.; Kotanko, P.; Schols, A.M.W.J.; Shiels, P.G.; Stenvinkel, P. Chronic kidney disease and premature ageing. Nat. Rev. Nephrol. 2014, 10, 732–742. [Google Scholar] [CrossRef] [Scilit]
- Johansen, K.L.; Chertow, G.M.; Jin, C.; Kutner, N.G. Significance of frailty among dialysis patients. J. Am. Soc. Nephrol. 2007, 18, 2960–2967. [Google Scholar] [CrossRef] [Scilit]
- Johansen, K.L.; Dalrymple, L.S.; Delgado, C.; Kaysen, G.A.; Kornak, J.; Grimes, B.; Chertow, G.M. Association between body composition and frailty among prevalent hemodialysis patients: A US Renal Data System special study. J. Am. Soc. Nephrol. 2014, 25, 381–389. [Google Scholar] [CrossRef] [Scilit]
- Sheshadri, A.; Elia, J.R.; Garcia, G.; Abrams, G.; Adey, D.B.; Lai, J.C.; Sudore, R.L. Barriers and Facilitators to Exercise in Older Adults Awaiting Kidney Transplantation and Their Care Partners. Kidney Med. 2024, 6, 100779. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.-K.; Kim, S.G.; Oh, J.-E.; Lee, Y.-K.; Noh, J.-W.; Kim, H.J.; Song, Y.R. Impact of sarcopenia on long-term mortality and cardiovascular events in patients undergoing hemodialysis. Korean J. Intern. Med. 2019, 34, 599–607. [Google Scholar] [CrossRef] [Scilit]
- Robinson-Cohen, C.; Littman, A.J.; Duncan, G.E.; Roshanravan, B.; Ikizler, T.A.; Himmelfarb, J.; Kestenbaum, B.R. Assessment of physical activity in chronic kidney disease. J. Ren. Nutr. 2013, 23, 123–131. [Google Scholar] [CrossRef] [Scilit]
- Painter, P. Implementing exercise: What do we know? Where do we go? Adv. Chronic Kidney Dis. 2009, 16, 536–544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bossola, M.; Marino, C.; Di Napoli, A.; Agabiti, N.; Tazza, L.; Davoli, M.; On behalf of the Dialysis and Transplant Lazio Region Registry Scientific Committee. Functional impairment and risk of mortality in patients on chronic hemodialysis: Results of the Lazio Dialysis Registry. J. Nephrol. 2018, 31, 593–602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manfredini, F.; Lamberti, N.; Malagoni, A.M.; Felisatti, M.; Zuccalà, A.; Torino, C.; Tripepi, G.; Catizone, L.; Mallamaci, F.; Zoccali, C. The role of deconditioning in the end-stage renal disease myopathy: Physical exercise improves altered resting muscle oxygen consumption. Am. J. Nephrol. 2015, 41, 329–336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bennett, P.N.; Kohzuki, M.; Bohm, C.; Roshanravan, B.; Bakker, S.J.L.; Viana, J.L.; MacRae, J.M.; Wilkinson, T.J.; Wilund, K.R.; Van Craenenbroeck, A.H.; et al. Global Policy Barriers and Enablers to Exercise and Physical Activity in Kidney Care. J. Ren. Nutr. 2022, 32, 441–449. [Google Scholar] [CrossRef] [Scilit]
- Schold, J.; Srinivas, T.R.; Sehgal, A.R.; Meier-Kriesche, H.-U. Half of kidney transplant candidates who are older than 60 years now placed on the waiting list will die before receiving a deceased-donor transplant. Clin. J. Am. Soc. Nephrol. 2009, 4, 1239–1245. [Google Scholar] [CrossRef] [Scilit]
- Kirkman, D.L.; Edwards, D.G.; Lennon-Edwards, S. Exercise as an Adjunct Therapy In Chronic Kidney Disease. Ren. Nutr. Forum 2014, 33, 1–8. [Google Scholar]
- Hayden, C.M.T.; Begue, G.; Gamboa, J.L.; Baar, K.; Roshanravan, B. Review of Exercise Interventions to Improve Clinical Outcomes in Nondialysis CKD. Kidney Int. Rep. 2024, 9, 3097–3115. [Google Scholar] [CrossRef] [Scilit]
- Cobo, G.; Gallar, P.; Gama-Axelsson, T.; Di Gioia, C.; Qureshi, A.R.; Camacho, R.; Vigil, A.; Heimbürger, O.; Ortega, O.; Rodriguez, I.; et al. Clinical determinants of reduced physical activity in hemodialysis and peritoneal dialysis patients. J. Nephrol. 2015, 28, 503–510. [Google Scholar] [CrossRef] [Scilit]
- Farrington, K.; Covic, A.; Nistor, I.; Aucella, F.; Clyne, N.; De Vos, L.; Findlay, A.; Fouque, D.; Grodzicki, T.; Iyasere, O.; et al. Clinical Practice Guideline on management of older patients with chronic kidney disease stage 3b or higher (eGFR < 45 mL/min/1.73 m2). Nephrol. Dial. Transplant. 2017, 32, 9–16. [Google Scholar]
- Goldberg, A.P.; Hagberg, J.; Delmez, J.A.; Carney, R.M.; McKevitt, P.M.; Ehsani, A.A.; Harter, H.R. The metabolic and psychological effects of exercise training in hemodialysis patients. Am. J. Clin. Nutr. 1980, 33, 1620–1628. [Google Scholar] [CrossRef] [Scilit]
- Goldberg, A.P.; Hagberg, J.M.; Delmez, J.A.; Haynes, M.E.; Harter, H.R. Metabolic effects of exercise training in hemodialysis patients. Kidney Int. 1980, 18, 754–761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldberg, A.P.; Geltman, E.M.; Hagberg, J.M.; Gavin, J.R.; Delmez, J.A.; Carney, R.M.; Naumowicz, A.; Oldfield, M.H.; Harter, H.R. Therapeutic benefits of exercise training for hemodialysis patients. Kidney Int. Suppl. 1983, 16, S303–S309. [Google Scholar] [PubMed]
- Shalom, R.; Blumenthal, J.A.; Sanders Williams, R.; McMurray, R.G.; Dennis, V.W. Feasibility and benefits of exercise training in patients on maintenance dialysis. Kidney Int. 1984, 25, 958–963. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Painter, P.L.; Nelson-Worel, J.N.; Hill, M.M.; Thornbery, D.R.; Shelp, W.R.; Harrington, A.R.; Weinstein, A.B. Effects of Exercise Training during Hemodialysis. Nephron 1986, 43, 87–92. [Google Scholar] [CrossRef] [Scilit]
- Goldberg, A.P.; Geltman, E.M.; Gavin, J.R., III; Carney, R.M.; Hagberg, J.M.; Delmez, J.A.; Naumovich, A.; Oldfield, M.H.; Harter, H.R. Exercise Training Reduces Coronary Risk and Effectively Rehabilitates Hemodialysis Patients. Nephron 1986, 42, 311–316. [Google Scholar] [CrossRef] [Scilit]
- Williams, A.; Stephens, R.; McKnight, T.; Dodd, S. Factors affecting adherence of end-stage renal disease patients to an exercise programme. Br. J. Sports Med. 1991, 25, 90–93. [Google Scholar] [CrossRef] [Scilit]
- Salhab, N.; Karavetian, M.; Kooman, J.; Fiaccadori, E.; El Khoury, C.F. Effects of intradialytic aerobic exercise on hemodialysis patients: A systematic review and meta-analysis. J. Nephrol. 2019, 32, 549–566. [Google Scholar] [CrossRef] [Scilit]
- Zoccali, C.; Manfredini, F.; Kanbay, M.; Mallamaci, F. Intradialysis exercise in haemodialysis patients: Effective but complex and costly. Nephrol. Dial. Transplant. 2023, 39, 7–9. [Google Scholar] [CrossRef] [Scilit]
- Segura-Ortí, E.; García-Testal, A. Intradialytic virtual reality exercise: Increasing physical activity through technology. Semin. Dial. 2019, 32, 331–335. [Google Scholar] [CrossRef] [Scilit]
- Kang, X.; Zhang, Y.; Sun, C.; Zhang, J.; Che, Z.; Zang, J.; Zhang, R. Effectiveness of Virtual Reality Training in Improving Outcomes for Dialysis Patients: Systematic Review and Meta-Analysis. J. Med. Internet Res. 2025, 27, e58384. [Google Scholar] [CrossRef] [Scilit]
- Bernier-Jean, A.; Beruni, N.A.; Bondonno, N.P.; Williams, G.; Teixeira-Pinto, A.; Craig, J.C.; Wong, G. Exercise training for adults undergoing maintenance dialysis. Cochrane Database Syst. Rev. 2022, 1, CD014653. [Google Scholar]
- Sheng, K.; Zhang, P.; Chen, L.; Cheng, J.; Wu, C.; Chen, J. Intradialytic exercise in hemodialysis patients: A systematic review and meta-analysis. Am. J. Nephrol. 2014, 40, 478–490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pu, J.; Jiang, Z.; Wu, W.; Li, L.; Zhang, L.; Li, Y.; Liu, Q.; Ou, S. Efficacy and safety of intradialytic exercise in haemodialysis patients: A systematic review and meta-analysis. BMJ Open 2019, 9, e020633. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferreira, G.D.; Bohlke, M.; Correa, C.M.; Dias, E.C.; Orcy, R.B. Does Intradialytic Exercise Improve Removal of Solutes by Hemodialysis? A Systematic Review and Meta-analysis. Arch. Phys. Med. Rehabil. 2019, 100, 2371–2380. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bündchen, D.C.; Sousa, H.; Afreixo, V.; Frontini, R.; Ribeiro, O.; Figueiredo, D.; Costa, E. Intradialytic exercise in end-stage renal disease: An umbrella review. Clin. Rehabil. 2021, 35, 812–828. [Google Scholar] [CrossRef] [Scilit]
- Zang, W.; Fang, M.; He, H.; Mu, L.; Zheng, X.; Shu, H.; Ge, N.; Wang, S. Comparative efficacy of exercise modalities for cardiopulmonary function in hemodialysis patients: A systematic review and network meta-analysis. Front. Public Health 2022, 10, 1040704. [Google Scholar] [CrossRef] [Scilit]
- Greenwood, S.A.; Koufaki, P.; Macdonald, J.H.; Bhandari, S.; Burton, J.O.; Dasgupta, I.; Farrington, K.; Ford, I.; Kalra, P.A.; Kean, S.; et al. Randomized Trial—PrEscription of intraDialytic exercise to improve quAlity of Life in Patients Receiving Hemodialysis. Kidney Int. Rep. 2021, 6, 2159–2170. [Google Scholar] [CrossRef] [Scilit]
- Pender, D.; McGowan, E.; McVeigh, J.G.; McCullagh, R. The Effects of Intradialytic Exercise on Key Indices of Sarcopenia in Patients With End-stage Renal Disease: A Systematic Review. Arch. Rehabil. Res. Clin. Transl. 2023, 5, 100252. [Google Scholar]
- Verrelli, D.; Sharma, A.; Alexiuk, J.; Tays, Q.; Rossum, K.; Sharma, M.; Ford, E.; Iansavitchene, A.; Al-Jaishi, A.A.; Whitlock, R.; et al. Effect of Intradialytic Exercise on Cardiovascular Outcomes in Maintenance Hemodialysis. Kidney360 2024, 5, 390–413. [Google Scholar] [CrossRef] [Scilit]
- Ferrari, F.; Andrade, F.P.; Teixeira, M.S.; Ziegelmann, P.K.; Carvalho, G.; Bittencourt, E.S.S.; Barcellos, F.C.; Stein, R. Efficacy of six exercise-based interventions for individuals undergoing hemodialysis: A network meta-analysis. Nephrol. Dial. Transplant. 2023, 38, 2389–2406. [Google Scholar] [CrossRef] [Scilit]
- Anding-Rost, K.; von Gersdorff, G.; von Korn, P.; Ihorst, G.; Josef, A.; Kaufmann, M.; Huber, M.; Bär, T.; Zeißler, S.; Höfling, S.; et al. Exercise during Hemodialysis in Patients with Chronic Kidney Failure. NEJM Evid. 2023, 2, EVIDoa2300057. [Google Scholar] [CrossRef] [Scilit]
- Martínez-Olmos, F.J.; Gómez-Conesa, A.A.; García-Testal, A.; Ortega-Pérez-de-Villar, L.; Valtueña-Gimeno, N.; Gil-Gómez, J.A.; Garcia-Maset, R.; Segura-Ortí, E. An intradialytic non-immersive virtual reality exercise programme: A crossover randomized controlled trial. Nephrol. Dial. Transplant. 2022, 37, 1366–1374. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bogataj, Š.; Pajek, M.; Kren, A.; Kurnik Mesarič, K.; Pajek, J. Randomized Controlled Trial of Intradialytic Cognitive and Physical Training to Enhance Functional Capacity. Kidney Int. Rep. 2024, 9, 2028–2036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, X.; Sun, J.; Wang, Z.; Zhang, N.; Liu, Y.; Wang, Z.; Wang, N.; Jian, G.; Cheng, D.; Sheng, X.; et al. The impact of intradialytic elastic band exercise on physical and cognitive abilities in patients on maintenance hemodialysis: A randomized controlled trial. Ren. Fail. 2025, 47, 2482124. [Google Scholar] [CrossRef] [Scilit]
- Manfredini, F.; Mallamaci, F.; D’Arrigo, G.; Baggetta, R.; Bolignano, D.; Torino, C.; Lamberti, N.; Bertoli, S.; Ciurlino, D.; Rocca-Rey, L.; et al. Exercise in Patients on Dialysis: A Multicenter, Randomized Clinical Trial. J. Am. Soc. Nephrol. 2017, 28, 1259–1268. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manfredini, F.; D’arrigo, G.; Lamberti, N.; Torino, C.; Tripepi, G.; Mallamaci, F.; Zoccali, C. The legacy effect of a home walking exercise programme in kidney failure patients on dialysis. Nephrol. Dial. Transplant. 2022, 37, 1974–1981. [Google Scholar] [CrossRef] [Scilit]
- Bulighin, F.; Aucella, F.; Bellizzi, V.; Cupisti, A.; Faga, T.; Gambaro, G.; Regolisti, G.; Storari, A.; Capitanini, A.; Battaglia, Y. Physical activity and exercise programs for kidney patients: An Italian survey of nephrology centres. J. Nephrol. 2024, 37, 695–705. [Google Scholar] [CrossRef] [Scilit]
- Chen, H.; Guan, Y.; Zhou, Z.; Shi, J.; Li, L.; Shi, J.; Wang, Q.; Zou, H. Home-based exercise in dialysis patients with end-stage renal disease: A systematic review and meta-analysis. Complement. Ther. Clin. Pract. 2024, 54, 101822. [Google Scholar] [CrossRef] [Scilit]
- Battaglia, Y.; Amicone, M.; Mantovani, A.; Combe, C.; Mitra, S.; Basile, C.; EuDial Working Group of ERA. Home-based exercise in patients on maintenance dialysis: A systematic review and meta-analysis of randomized clinical trials. Nephrol. Dial. Transplant. 2023, 38, 2550–2561. [Google Scholar] [CrossRef] [Scilit]
- Clarke, A.L.; Jhamb, M.; Bennett, P.N. Barriers and facilitators for engagement and implementation of exercise in end-stage kidney disease. Semin. Dial. 2019, 32, 308–319. [Google Scholar] [CrossRef] [Scilit]
- Mahjur, M.; Norasteh, A.A. The Effect of Unsupervised Home-Based Exercise Training on Physical Functioning Outcomes in Older Adults. Biol. Res. Nurs. 2021, 23, 504–512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Junqué-Jiménez, A.; Esteve-Simó, V.; Andreu-Periz, L.; Segura-Ortí, E. A nurse-led home-based exercise program for patients with chronic kidney disease. Worldviews Evid.-Based Nurs. 2023, 20, 79–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fiaccadori, E.; Sabatino, A.; Schito, F.; Angella, F.; Malagoli, M.; Tucci, M.; Cupisti, A.; Capitanini, A.; Regolisti, G. Barriers to Physical Activity in Chronic Hemodialysis Patients: A Single-Center Pilot Study in an Italian dialysis facility. Kidney Blood Press. Res. 2014, 39, 169–175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Regolisti, G.; Maggiore, U.; Sabatino, A.; Gandolfini, I.; Pioli, S.; Torino, C.; Aucella, F.; Cupisti, A.; Pistolesi, V.; Capitanini, A.; et al. Interaction of healthcare staff’s attitude with barriers to physical activity in hemodialysis patients: A quantitative assessment. PLoS ONE 2018, 13, e0196313. [Google Scholar]
- Rossum, K.; Finlay, J.; McCormick, M.; Desjarlais, A.; Vorster, H.; Fontaine, G.; Talson, M.; Da Silva, P.F.; Soroka, K.V.; Sass, R.; et al. A Mixed Method Investigation to Determine Priorities for Improving Information, Interaction, and Individualization of Care Among Individuals on In-center Hemodialysis: The Triple I Study. Can. J. Kidney Health Dis. 2020, 7, 2054358120953284. [Google Scholar] [CrossRef] [Scilit]
- Jhamb, M.; McNulty, M.L.; Ingalsbe, G.; Childers, J.W.; Schell, J.; Conroy, M.B.; Forman, D.E.; Hergenroeder, A.; Dew, M.A. Knowledge, barriers and facilitators of exercise in dialysis patients: A qualitative study. BMC Nephrol. 2016, 17, 192. [Google Scholar] [CrossRef] [Scilit]
- Cardol, C.K.; Boslooper-Meulenbelt, K.; van Middendorp, H.; Meuleman, Y.; Evers, A.W.M.; van Dijk, S. Psychosocial barriers and facilitators for adherence to a healthy lifestyle among patients with chronic kidney disease. BMC Nephrol. 2022, 23, 205. [Google Scholar] [CrossRef] [Scilit]
- Li, T.; Lv, A.; Xu, N.; Huang, M.; Su, Y.; Zhang, B.; Li, X. Barriers and facilitators to exercise in haemodialysis patients: A systematic review of qualitative studies. J. Adv. Nurs. 2021, 77, 4679–4692. [Google Scholar] [CrossRef] [Scilit]
- Escudero-Lopez, M.; Martinez-Andres, M.; Marcilla-Toribio, I.; Moratalla-Cebrian, L.L.; Perez-Moreno, A.; Bartolome-Gutierrez, R. Barriers and facilitators in self-care and management of chronic kidney disease in dialysis patients. J. Clin. Nurs. 2024, 33, 3815–3830. [Google Scholar] [CrossRef] [Scilit]
- Tao, X.; Chow, S.K.Y.; Wong, F.K.Y. A nurse-led case management program on home exercise training for hemodialysis patients: A randomized controlled trial. Int. J. Nurs. Stud. 2015, 52, 1029–1041. [Google Scholar] [CrossRef] [Scilit]
- Battaglia, Y.; Baciga, F.; Bulighin, F.; Amicone, M.; Mosconi, G.; Storari, A.; Brugnano, R.; Pozzato, M.; Motta, D.; D’aLessandro, C.; et al. Physical activity and exercise in chronic kidney disease: Consensus statements from the Physical Exercise Working Group of the Italian Society of Nephrology. J. Nephrol. 2024, 37, 1735–1765. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manfredini, F.; Lamberti, N.; Battaglia, Y.; Straudi, S.; Belvederi Murri, M.; Donadi, M.; Piva, G.; Fabbian, F.; López-Soto, P.J.; Grassi, L.; et al. A Personalized Patient-Centered Intervention to Empower through Physical Activity the Patient in the Dialysis Center. Methods Protoc. 2020, 3, 83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Des Jarlais, D.C.; Lyles, C.; Crepaz, N.; TREND Group. Improving the reporting quality of nonrandomized evaluations of behavioral and public health interventions: The TREND statement. Am. J. Public Health 2004, 94, 361–366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Folstein, M.F.; Folstein, S.E.; McHugh, P.R. “Mini-mental state”: A practical method for grading the cognitive state of patients for the clinician. J. Psychiatr. Res. 1975, 12, 189–198. [Google Scholar] [CrossRef] [Scilit]
- Johansen, K.L.; Painter, P. Exercise in individuals with CKD. Am. J. Kidney Dis. 2012, 59, 126–134. [Google Scholar] [CrossRef] [Scilit]
- Malagoni, A.M.; Catizone, L.; Mandini, S.; Soffritti, S.; Manfredini, R.; Boari, B.; Russo, G.; Basaglia, N.; Zamboni, P.; Manfredini, F. Acute and long-term effects of an exercise program for dialysis patients prescribed in hospital and performed at home. J. Nephrol. 2008, 21, 871–878. [Google Scholar] [CrossRef] [Scilit]
- Cromm, K.; Fischer, K.I. Striking new path(way)s-how a conceptual model of patient outcomes can help us advance outcomes that matter to patients. Nephrol. Dial. Transplant. 2021, 36, 956–959. [Google Scholar] [CrossRef] [Scilit]
- Enright, P.L.; McBurnie, M.A.; Bittner, V.; Tracy, R.P.; McNamara, R.; Arnold, A.; Newman, A.B. The 6-min walk test: A quick measure of functional status in elderly adults. Chest 2003, 123, 387–398. [Google Scholar] [CrossRef] [Scilit]
- Peters, D.M.; Fritz, S.L.; Krotish, D.E. Assessing the reliability and validity of a shorter walk test compared with the 10-meter walk test for measurements of gait speed in healthy, older adults. J. Geriatr. Phys. Ther. 2013, 36, 24–30. [Google Scholar] [CrossRef] [Scilit]
- Csuka, M.; McCarty, D.J. Simple method for measurement of lower extremity muscle strength. Am. J. Med. 1985, 78, 77–81. [Google Scholar] [CrossRef] [Scilit]
- Ware, J.E., Jr.; Sherbourne, C.D. The MOS 36-item short-form health survey (SF-36). I. Conceptual framework and item selection. Med. Care 1992, 30, 473–483. [Google Scholar] [CrossRef] [Scilit]
- Kempen, G.I.; Yardley, L.; van Haastregt, J.C.; Zijlstra, G.A.R.; Evenhuis, H.M.; Delbaere, K. The Short FES-I: A shortened version of the falls efficacy scale-international to assess fear of falling. Age Ageing 2008, 37, 45–50. [Google Scholar] [CrossRef] [Scilit]
- Beck, A.T.; Steer, R.A.; Brown, G. Beck Depression Inventory–II (BDI-II); The Psychological Corporation: San Antonio, TX, USA, 1996. [Google Scholar]
- Pascali, G.; Colella, D. Adapted Sports Practice and the Educational Process. Form. Insegn. 2024, 22, 94–104. [Google Scholar]
- Chalder, M.; Wiles, N.J.; Campbell, J.; Hollinghurst, S.; Haase, A.M.; Taylor, A.H.; Fox, K.R.; Costelloe, C.; Searle, A.; Baxter, H.; et al. Facilitated physical activity as a treatment for depressed adults: Randomised controlled trial. BMJ 2012, 344, e3554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daley, A.J.; Blamey, R.V.; Jolly, K.; Roalfe, A.K.; Turner, K.M.; Coleman, S.; McGuinness, M.; Jones, I.; Sharp, D.J.; MacArthur, C. A pragmatic randomized controlled trial to evaluate the effectiveness of a facilitated exercise intervention as a treatment for postnatal depression: The PAM-PeRS trial. Psychol. Med. 2015, 45, 2413–2425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, T.; Kerry, S.M.; Victor, C.R.; Ekelund, U.; Woodcock, A.; Iliffe, S.; Whincup, P.H.; Beighton, C.; Ussher, M.; Limb, E.S.; et al. A primary care nurse-delivered walking intervention in older adults: PACE (Physical Activity changes in the elderly) pilot randomised controlled trial. PLoS Med. 2015, 12, e1001783. [Google Scholar] [CrossRef] [Scilit]
- Peacock, O.J.; Western, M.J.; Batterham, A.M.; Chowdhury, E.A.; Stathi, A.; Standage, M.; Tapp, A.; Bennett, P.; Thompson, D. Effect of novel technology-enabled multidimensional physical activity feedback in primary care patients at risk of chronic disease—The MIPACT study. Int. J. Behav. Nutr. Phys. Act. 2020, 17, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Hellberg, M.; Höglund, P.; Svensson, P.; Clyne, N. Randomized Controlled Trial of Exercise in CKD-The RENEXC Study. Kidney Int. Rep. 2019, 4, 963–976. [Google Scholar] [CrossRef] [Scilit]
- Greenwood, S.A.; Young, H.M.L.; Briggs, J.; Castle, E.M.; Walklin, C.; Haggis, L.; Balkin, C.; Asgari, E.; Bhandari, S.; Burton, J.O.; et al. Evaluating the effect of a digital health intervention to enhance physical activity in people with chronic kidney disease (Kidney BEAM): A multicentre, randomised controlled trial in the UK. Lancet Digit. Health 2024, 6, e23–e32. [Google Scholar] [CrossRef] [Scilit]
- Kelly, J.T.; Conley, M.; Hoffmann, T.; Craig, J.C.; Tong, A.; Reidlinger, D.P.; Reeves, M.M.; Howard, K.; Krishnasamy, R.; Kurtkoti, J.; et al. A Coaching Program to Improve Dietary Intake of Patients with CKD: ENTICE-CKD. Clin. J. Am. Soc. Nephrol. 2020, 15, 330–340. [Google Scholar] [CrossRef] [Scilit]
- Wilkinson, T.J.; Clarke, A.L.; Nixon, D.G.D.; Hull, K.L.; Song, Y.; Burton, J.O.; Yates, T.; Smith, A.C. Prevalence and correlates of physical activity across kidney disease stages: An observational multicentre study. Nephrol. Dial. Transplant. 2021, 36, 641–649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilkinson, T.J.; MacRae, J.M.; Thompson, S.; Bohm, C. Making the Case for Standardized Outcome Measures in Exercise and Physical Activity Research in Chronic Kidney Disease. Kidney Dial. 2023, 3, 219–228. [Google Scholar] [CrossRef] [Scilit]
- Heiwe, S.; Jacobson, S.H. Exercise training for adults with chronic kidney disease. Cochrane Database Syst. Rev. 2011, 10, CD003236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alibhai, S.M.H.; Papadopoulos, E.; Durbano, S.; Tomlinson, G.; Mina, D.S.; Ritvo, P.; Sabiston, C.M.; Matthew, A.G.; Chiarotto, J.; Sidani, S.; et al. Preference-based versus randomized controlled trial in prostate cancer survivors. Front. Oncol. 2022, 12, 1033229. [Google Scholar] [CrossRef] [Scilit]
- Silva, C.G.D.; Crossetti, M.D.G.O.; Fernández, M.G.; Prates, J.D.S. Middle-range theory of the existential dimension of being-in-the-world of chronic kidney disease. Rev. Bras. Enferm. 2024, 77, e20230152. [Google Scholar]
- Teixeira, P.J.; Carraça, E.V.; Markland, D.; Silva, M.N.; Ryan, R.M. Exercise, physical activity, and self-determination theory: A systematic review. Int. J. Behav. Nutr. Phys. Act. 2012, 9, 78. [Google Scholar] [CrossRef] [Scilit]
- Hollman, H.; Updegraff, J.A.; Lipkus, I.M.; Rhodes, R.E. Perceptions of physical activity and sedentary behaviour guidelines among end-users and stakeholders: A systematic review. Int. J. Behav. Nutr. Phys. Act. 2022, 19, 21. [Google Scholar] [CrossRef] [Scilit]
- von Gersdorff, G.; von Korn, P.; Duvinage, A.; Ihorst, G.; Josef, A.; Kaufmann, M.; Baer, T.; Fellerhoff, T.; Fuhrmann, I.; Koesel, E.; et al. Cluster Randomized Controlled Trial on the Effects of 12 Months of Combined Exercise Training during Hemodialysis. Methods Protoc. 2021, 4, 60. [Google Scholar] [CrossRef] [Scilit]
- Greenwood, S.A.; Koufaki, P.; Macdonald, J.H.; Bulley, C.; Bhandari, S.; Burton, J.O.; Dasgupta, I.; Farrington, K.; Ford, I.; Kalra, P.A.; et al. Exercise programme to improve quality of life for patients with end-stage kidney disease receiving haemodialysis: The PEDAL RCT. Health Technol. Assess. 2021, 25, 1–52. [Google Scholar] [CrossRef] [Scilit]
- Halle, M.; Manfredini, F.; Floege, J.; Zoccali, C. Physical exercise in haemodialysis patients: Which type of exercise is more convenient? Clin. Kidney J. 2024, 17, sfae165. [Google Scholar] [CrossRef] [Scilit]
- Huang, M.; Lv, A.; Wang, J.; Xu, N.; Ma, G.; Zhai, Z.; Zhang, B.; Gao, J.; Ni, C. Exercise Training and Outcomes in Hemodialysis Patients: Systematic Review and Meta-Analysis. Am. J. Nephrol. 2019, 50, 240–254. [Google Scholar] [CrossRef] [Scilit]
- Battaglia, Y.; Shroff, R.; Meijers, B.; Nistor, I.; Alfano, G.; Franssen, C.; Luyckx, V.; Liakopoulos, V.; Mantovani, A.; Baciga, F.; et al. Haemodiafiltration versus high-flux haemodialysis-a Consensus Statement from the EuDial Working Group of the ERA. Nephrol. Dial. Transplant. 2025, 40, 1590–1614. [Google Scholar] [CrossRef] [Scilit]

| Answer |
|---|
| I knew I needed to exercise, but I did not know who to turn to. Without EF at the dialysis center, I would not have been able to train at home or at the gym. |
| I am already physically active, but I believe that the opportunity to perform exercises that I would not do on my own, under the supervision of the EF, is an opportunity to be seized. |
| Due to my disease, I thought I would not be able to follow any exercise program. The opportunity to engage with an expert on a daily basis helped me find an exercise program that was compatible with my condition. |
| I think I have good autonomy, but I am glad to be able to undergo free assessment sessions at the dialysis center. |
| I do not truly like exercising. However, talking to EF helped me identify some exercises that can benefit me and that I enjoy doing. |
| I would have liked to do supervised exercise, but due to transportation issues, this is impossible for me. I appreciated that EF was able to give mean exercise program to do at home, which I can follow despite my limitations. |
| I was interested in being independent in my household activities, and I did not want to start any very demanding programs. The prospect of gaining independence with little effort seemed appealing to me. |
| I have some friends who go to the gym, but the prospect of training with more active people has always discouraged me. The opportunity to exercise under the supervision of an expert, together with other people in my condition, seemed like an ideal situation. |
| N | Females, n (%) | Age, Mean (SD) | Reason |
|---|---|---|---|
| 1 | 0 (0) | 74 (n.a.) | I am incapable of following a program at home, and I am unable to participate in a supervised program. |
| 1 | 1 (100) | 78 (n.a.) | I am seeing a physiotherapist privately with benefits, and I do not feel the need to participate in the program. |
| 10 | 1 (10) | 66.3 (16.1) | I consider myself sufficiently active, and I do not believe I need to increase my level of physical activity. |
| 3 | 1 (33) | 63.7 (24.4) | I do not have enough free time to exercise. |
| 30 | 9 (30) | 77.0 (11.8) | I do not think I need to exercise/I do not believe my health would improve by participating in the program. |
| Participants (n = 176) | Non Participants (n = 45) | p Value | |
|---|---|---|---|
| Age | 70.0 ± 12.8 | 72.5 ± 14.9 | 0.12 |
| Male sex, n (%) | 124 (71) | 33 (73) | 0.82 |
| Dialysis vintage, years | 7 ± 3 | 7 ± 4 | 0.74 |
| Distance from dialysis center, km | 19.5 ± 16.5 | 21.8 ± 15.6 | 0.43 |
| Cardiovascular disease | 132 (75) | 32 (71) | 0.67 |
| Stroke | 21 (12) | 4 (9) | 0.23 |
| Pulmonary disease | 25 (14) | 5 (12) | 0.45 |
| Rheumatic disorder | 32 (18) | 6 (16) | 0.82 |
| Cancer | 58 (33) | 16 (35) | 0.77 |
| Charlson Index * | 5.6 ± 4.1 | 5.8 ± 3.9 | 0.88 |
| S-SU-LI (n = 80) | S-HB-LI (n = 66) | U-PA-I (n = 5) | PPA (n = 25) | p Value | Effect Size (95% CI) | |
|---|---|---|---|---|---|---|
| Age | 74.5 ± 10.6 | 66.7 ± 13.5 * | 58.6 ± 8.0 * | 63.7 ± 12.0 * | <0.001 | 0.124 (0.015–0.225) |
| Male sex, n (%) | 54 (68) | 50 (76) | 3 (60) | 20 (80) | 0.49 | 0.105 |
| Dialysis vintage, years | 7.6 ± 3.1 | 5.9 ± 2.4 * | 8.3 ± 8.0† | 6.6 ± 6.2 | 0.032 | 0.072 (−0.022–0.175) |
| Charlson Index | 6.4 ± 2.1 | 5.8 ± 1.9 † | 4.3 ± 1.5 * † | 4.0 ± 1.5 * † | 0.006 | 0.099 (−0.021–0.215) |
| Distance from dialysis center, km | 17.4 ± 13.9 | 20.3 ± 14.7 | 14.8 ± 11.8 | 16.5 ± 13.6 | 0.44 | −0.022 (−0.033–0.017) |
| Mean of transportation | * | * † ‡ | * | 0.002 | 0.160 | |
| Autonomous | 24 (27) | 30 (50) | 5 (100) | 12 (48) | ||
| Caregiver/Service | 58 (66) | 18 (30) | 0 (0) | 10 (40) | ||
| Public | 6 (7) | 12 (20) | 0 (0) | 3 (12) | ||
| Italy/Europe | 53/27 | 44/22 | 4/1 | 17/8 | 0.86 | |
| Outcome measures | ||||||
| 6MWD, m | 251 ± 107 | 316 ± 122 * | 285 ± 154 | 368 ± 126 * | <0.001 | 0.105 (0.024–0.187) |
| T10m, s | 7.52 ± 4.32 | 6.98 ± 7.54 | 10.54 ± 8.29 | 4.17 ± 1.80 * † | 0.10 | 0.048 (0.000–0.112) |
| 5STS, s | 16.71 ± 10.72 | 15.11 ± 6.64 | 14.73 ± 5.23 | 12.18 ± 3.11 * † | 0.28 | 0.041 (−0.021–0.087) |
| S-FES-I | 11.7 ± 5.4 † | 9.3 ± 3.4 | 10.8 ± 3.8 | 11.3 ± 10.3 † | 0.26 | 0.084 (0.000–0.182) |
| DASI | 24.4 ± 15.0 | 33.9 ± 15.5 * | 27.7 ± 14.0 | 33.6 ± 18.0 * | 0.14 | 0.118 (0.001–0.234) |
| S-SU-LI (n = 80) | S-HB-LI (n = 66) | U-PA-I (n = 5) | PPA (n = 25) | p Value | η2 (95% CI) | |
|---|---|---|---|---|---|---|
| BDI-II | 10.7 ± 2.0 | 9.2 ± 2.1 * | 9.5 ± 2.2 | 9.0 ± 1.8 * | 0.052 | 0.823 (0.000–0.187) |
| SF-36 questionnaire domains | ||||||
| Physical functioning | 59 ± 28 | 73 ± 19 * | 50 ± 41 | 77 ± 18 * | 0.011 | 0.106 (0.005–0.210) |
| Role-Physical | 57 ± 36 | 61 ± 36 | 38 ± 43 † | 48 ± 47 | 0.52 | 0.020 (0.000–0.075) |
| Role-Emotional | 67 ± 36 | 85 ± 33 * | 50 ± 58 † | 67 ± 41 | 0.053 | 0.076 (0.000–0.170) |
| Vitality | 54 ± 19 | 57 ± 16 | 35 ± 33 | 60 ± 15 | 0.08 | 0.068 (0.000–0.159) |
| Mental Health | 68 ± 20 | 71 ± 14 | 60 ± 24 | 72 ± 23 | 0.64 | 0.016 (0.000–0.066) |
| Social functioning | 64 ± 28 | 72 ± 24 | 47 ± 48 | 70 ± 28 | 0.25 | 0.041 (0.000–0.117) |
| Bodily pain | 69 ± 31 | 72 ± 20 | 62 ± 34 | 73 ± 29 | 0.82 | 0.009 (0.000–0.043) |
| General health | 41 ± 20 | 45 ± 15 | 26 ± 9 | 43 ± 28 | 0.24 | 0.042 (0.000–0.119) |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Piva, G.; Labrador, F.; Momenté, C.; Lamberti, N.; Crepaldi, A.; Di Maria, A.; Battaglia, Y.; Martin-Malo, A.; Manfredini, F.; Lopez-Soto, P.J.; et al. Characteristics, Attitudes and Preferences of an End-Stage Kidney Disease Population at the Beginning of an Exercise Program: A Pragmatic Multicenter Trial. J. Clin. Med. 2026, 15, 1547. https://doi.org/10.3390/jcm15041547
Piva G, Labrador F, Momenté C, Lamberti N, Crepaldi A, Di Maria A, Battaglia Y, Martin-Malo A, Manfredini F, Lopez-Soto PJ, et al. Characteristics, Attitudes and Preferences of an End-Stage Kidney Disease Population at the Beginning of an Exercise Program: A Pragmatic Multicenter Trial. Journal of Clinical Medicine. 2026; 15(4):1547. https://doi.org/10.3390/jcm15041547
Chicago/Turabian StylePiva, Giovanni, Francisco Labrador, Claudia Momenté, Nicola Lamberti, Anna Crepaldi, Alessio Di Maria, Yuri Battaglia, Alejandro Martin-Malo, Fabio Manfredini, Pablo Jesus Lopez-Soto, and et al. 2026. "Characteristics, Attitudes and Preferences of an End-Stage Kidney Disease Population at the Beginning of an Exercise Program: A Pragmatic Multicenter Trial" Journal of Clinical Medicine 15, no. 4: 1547. https://doi.org/10.3390/jcm15041547
APA StylePiva, G., Labrador, F., Momenté, C., Lamberti, N., Crepaldi, A., Di Maria, A., Battaglia, Y., Martin-Malo, A., Manfredini, F., Lopez-Soto, P. J., & Storari, A. (2026). Characteristics, Attitudes and Preferences of an End-Stage Kidney Disease Population at the Beginning of an Exercise Program: A Pragmatic Multicenter Trial. Journal of Clinical Medicine, 15(4), 1547. https://doi.org/10.3390/jcm15041547

