1. Introduction
Resistance training (RT) is a primary stimulus for skeletal muscle hypertrophy and improvements in maximal force production [
1,
2]. Beyond these adaptations, RT may also influence tissue electrical properties, which can be assessed non-invasively using bioelectrical impedance analysis (BIA)-derived phase angle (PhA) and other raw parameters [
3]. Impedance (Z) represents the opposition to an applied alternating electrical current and is influenced by water and electrolytes in body fluids and tissues [
4]. It comprises resistance (R), reflecting conductive opposition to current flow, and reactance (Xc), representing current delay associated with cell membranes and tissue interfaces. Capacitance (CAP), which is related to Xc at a given frequency, contributes to the phase shift between current and voltage, geometrically expressed as PhA [
4,
5]. Given the limitations of prediction equations in BIA-derived body composition estimates, examining R, Xc, PhA, and mathematically derived CAP avoids reliance on proprietary body-composition algorithms. Nevertheless, these variables remain device- and configuration-dependent bioelectrical descriptors rather than direct measures of muscle mass, intracellular water, membrane integrity, or cellular health [
6,
7].
Although RT has been associated with changes in PhA, the physiological meaning of these changes remains uncertain because PhA is an indirect and device-dependent bioelectrical descriptor [
3,
6]. Previous research reports increases in PhA following hypertrophy-oriented RT [
8], whereas others show no change or even decreases, particularly under conditions involving high metabolic stress or fluid shifts [
9,
10]. This variability suggests that training variables, including proximity to momentary muscular failure, may influence bioelectrical responses [
11,
12].
Proximity-to-failure is a key variable in RT programming [
13,
14]. Although training to failure is often recommended to maximize motor unit recruitment, current evidence has not identified a consistent advantage of training to failure over repetitions in reserve (RIR) for strength and hypertrophy outcomes [
13,
14,
15]. From a bioelectrical perspective, RT may be accompanied by changes in R, Xc, and consequently PhA. Although associations between these parameters, tissue water, and soft tissue characteristics have been reported [
3,
16], they do not permit direct inference regarding intracellular water, myocyte volume, muscle hypertrophy, or membrane integrity. Their interpretation remains dependent on hydration status, analyzer technology, measurement frequency, electrode configuration, and the BIA approach used [
7,
17,
18]. Studies examining RT-induced bioelectrical changes have used whole-body, segmental/regional, and localized electrode configurations [
3,
19]. Therefore, the present segmental arm and leg estimates should not be interpreted as whole-body values or as localized measurements obtained directly over the trained elbow flexors and knee extensors.
Thus, raw parameters should be interpreted alongside PhA to determine whether changes in this composite index reflect a coherent bioelectrical pattern. Because PhA may vary with multiple biological and technical factors, different proximity-to-failure strategies may induce distinct bioelectrical responses [
3,
7]. However, whether such differences occur in traditional RT remains unclear. To date, no study has directly compared RT performed to failure versus an RIR approach on segmental raw bioelectrical parameters within a controlled framework. A recent review highlighted the scarcity of studies and the need for direct comparisons of training variables [
20].
Accordingly, the primary aim of this study was to compare the effects of eight weeks of RT performed either to momentary muscular failure or with a predetermined number of RIR on segmental bioelectrical parameters, including PhA, derived R, and Xc. A secondary aim was to examine whether these between-protocol patterns differed by sex. Based on the current proximity-to-failure literature [
13,
14,
15], we hypothesized that between-protocol differences would be small and uncertain, with no consistent directional pattern favoring either condition.
2. Materials and Methods
2.1. Study Design
A unilateral, within-subject randomized experimental design was employed to compare the effects of an 8-week RT intervention performed to momentary muscular failure (FAIL) versus repetitions in reserve (RIR). Each participant completed unilateral preacher curls (elbow flexors) and unilateral leg extensions (knee extensors), with one limb allocated to FAIL and the contralateral limb allocated to RIR. Limb allocation was determined by simple randomization using a coin toss, performed separately for upper and lower limbs. Limb dominance was not considered in the allocation procedure. Thus, baseline limb asymmetries may occur. This design ensured that, for each exercise, participants served as their own control [
15]. Accordingly, the primary inferential focus was on longitudinal changes from baseline within each protocol and on whether these changes differ between FAIL and RIR, rather than on absolute between-limb differences at a single time point.
2.2. Participants
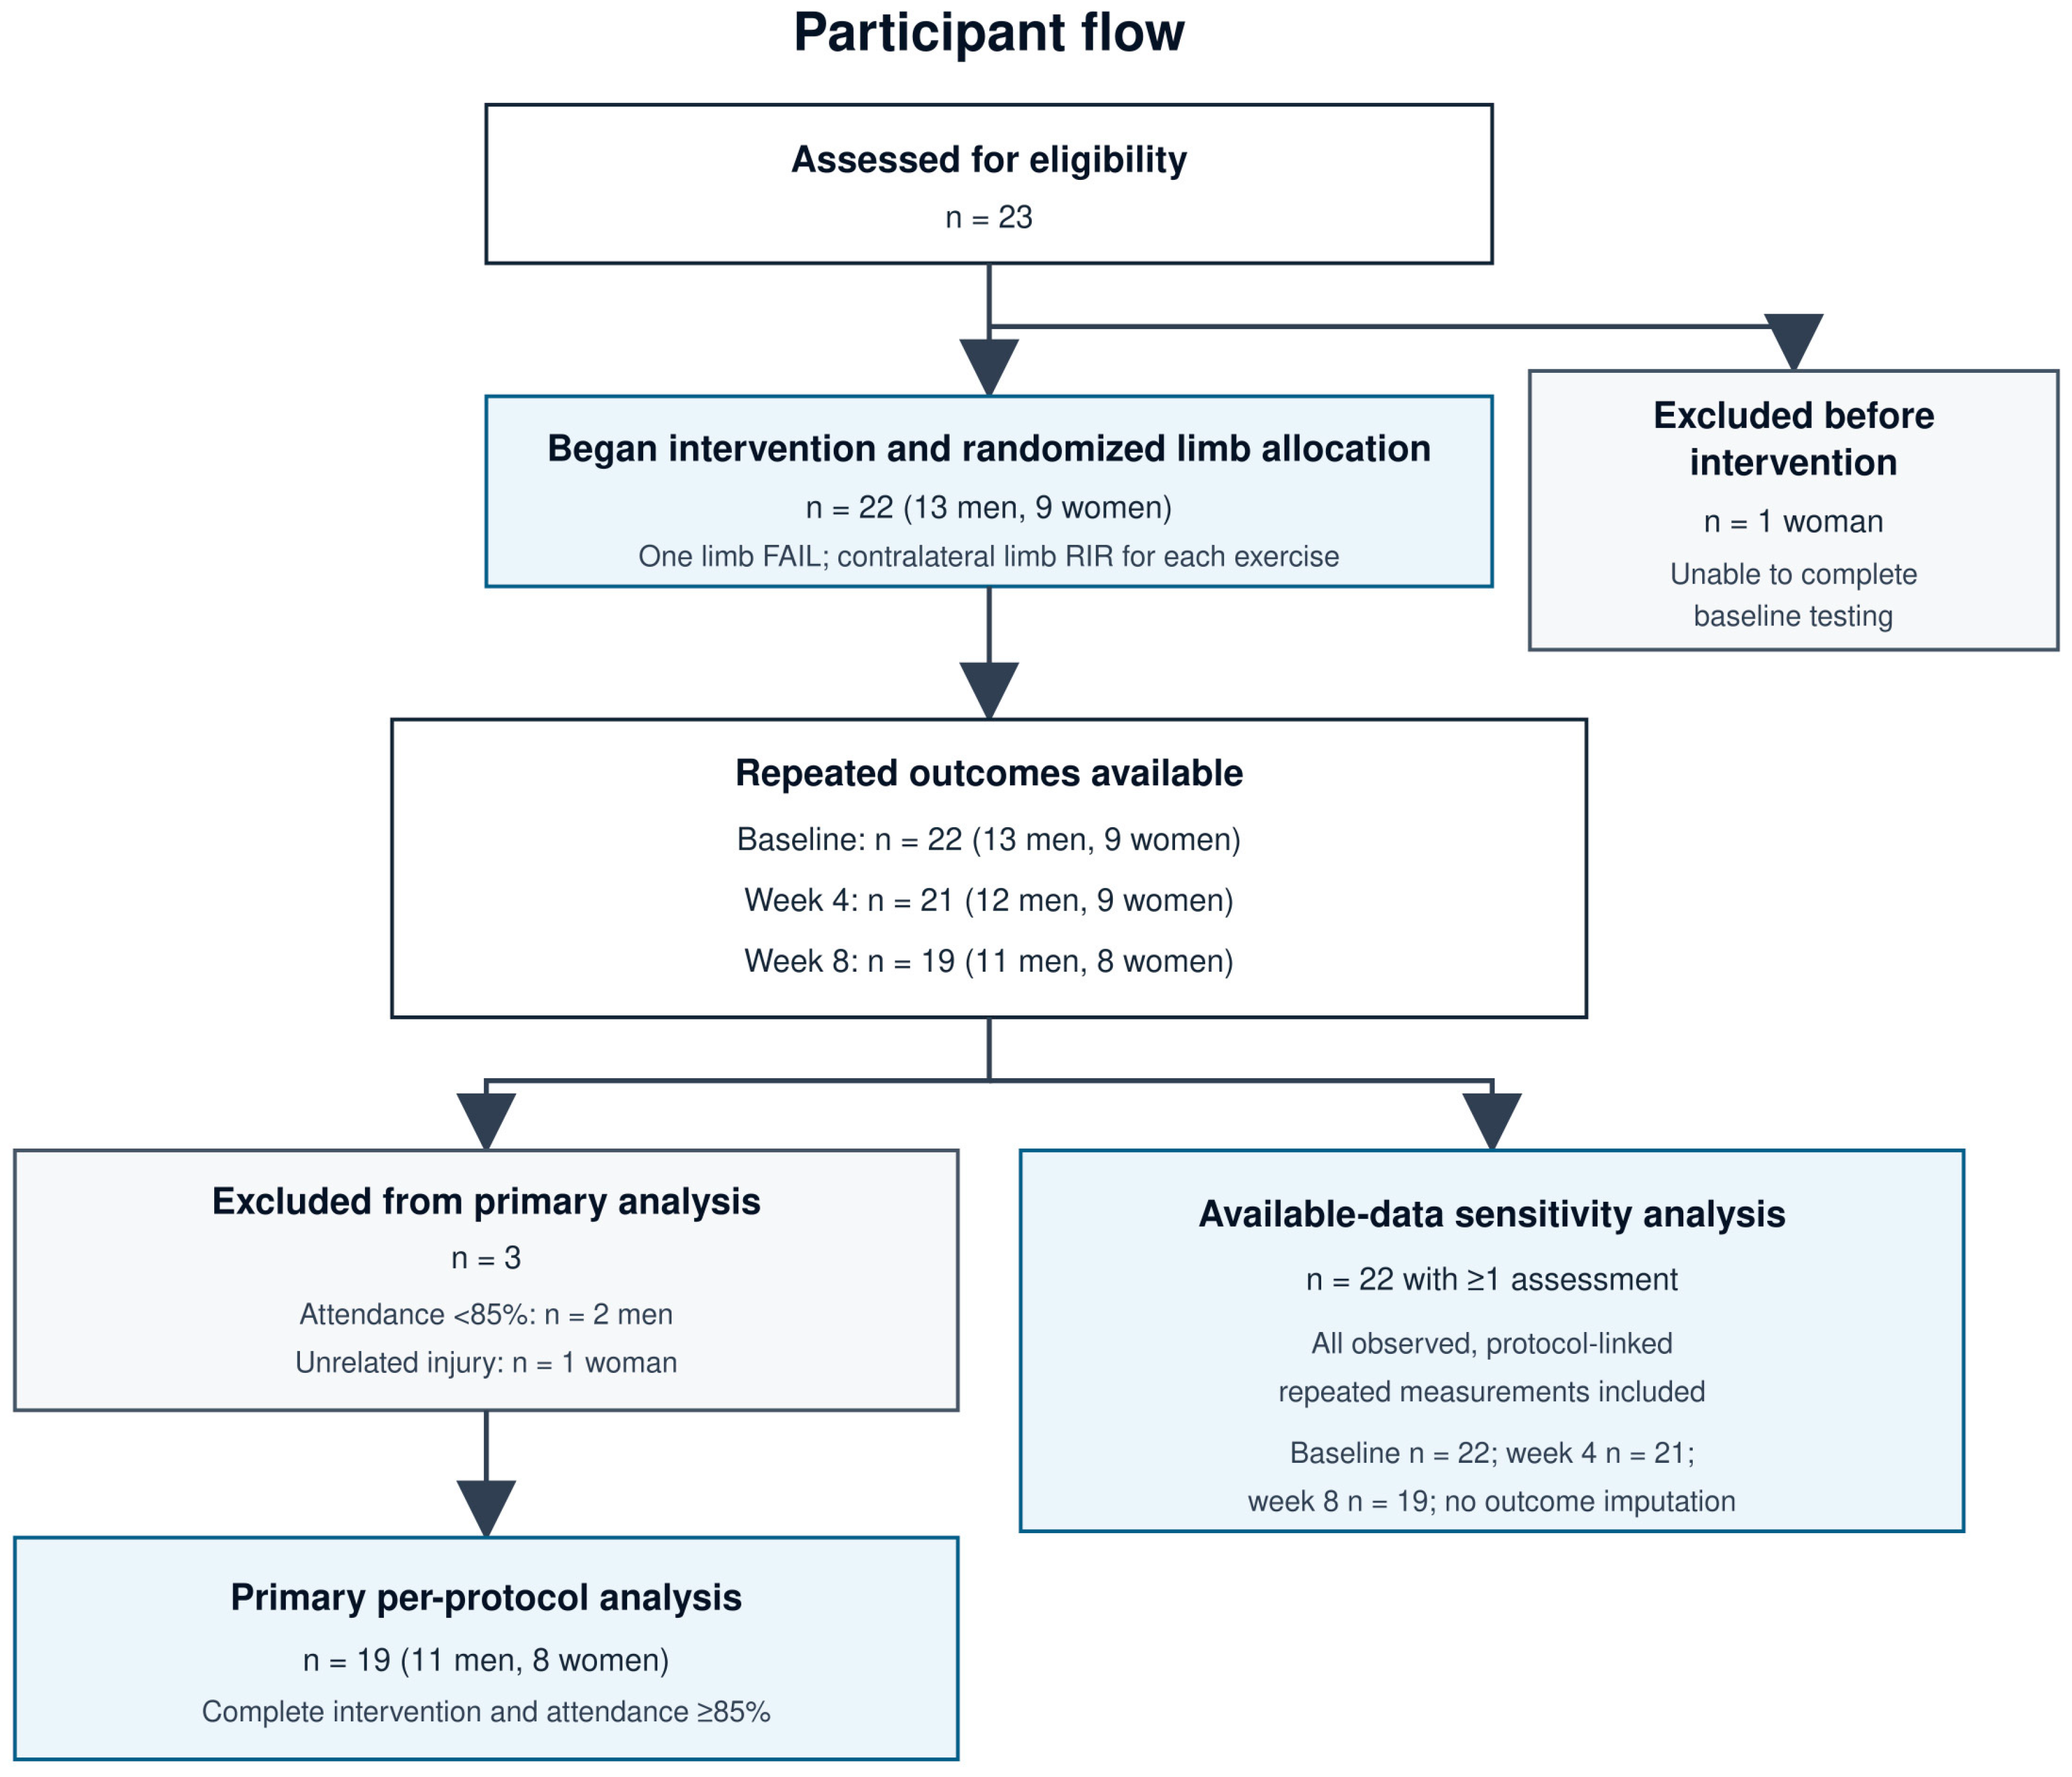
Twenty-three resistance-trained young adults were recruited. One female participant was excluded before commencing the intervention due to an inability to complete baseline testing procedures, resulting in twenty-two participants beginning the intervention (13 males and 9 females). Participant flow is presented in
Figure 1. During the intervention, three participants were excluded from the final analysis due to insufficient training attendance (
n = 2 males) or an unrelated injury sustained mid-intervention (
n = 1 female). The final analytical sample therefore comprised nineteen participants (11 males and 8 females). Thus, the final analysis was conducted on a sample of nineteen participants, comprising eleven males (mean ± SD: Age = 20.4 ± 1.8 y; Height = 172.7 ± 5.6 cm; Body Mass = 74.9 ± 7.6 kg) and eight adult females (mean ± SD: Age = 24.8 ± 4.7 y; Height = 164.1 ± 8.0 cm; Body Mass = 63.0 ± 10.1 kg).
Participants were recruited from the local University School of Sport via flyers, email announcements, and word of mouth. Eligibility criteria required participants to: (1) be engaged in regular RT for ≥2 y at a frequency of ≥3 sessions per week [
15,
21]; (2) be free from musculoskeletal injury or medical condition contraindicating participation; (3) report lifetime abstinence from anabolic steroid use; and (4) not be concurrently undertaking structured training involving additional exercises specifically targeting the elbow flexors or knee extensors outside the study protocol. Participants using ergogenic supplements (e.g., creatine) prior to study commencement were permitted to maintain habitual use but were instructed not to initiate any new supplementation during the intervention. Participants were excluded from analysis if they failed to meet the minimum training attendance requirement (≥85% of supervised sessions), initiated new supplementation during the intervention, or sustained an injury preventing completion of post-intervention assessments.
All participants provided written informed consent. The study was approved by the “Comissão de Ética da Unidade de Investigação do IPSantarém” on 11 October 2023 (Ethics Approval Number: 19A-2023ESDRM) and conducted in accordance with the Declaration of Helsinki.
2.3. Sample Size Justification
The target sample size was determined a priori to retain a minimum of 19 participants after attrition; accordingly, 23 participants were recruited. No formal sample size calculation was based on a single primary bioelectrical outcome because no prior study had directly compared FAIL and RIR using segmental raw bioelectrical parameters. The sample size was primarily justified by pragmatic considerations and resource constraints associated with the fully supervised RT intervention and was comparable to that of a closely related within-subject study examining proximity to failure [
15]. General principles for transparent sample-size justification were followed [
22].
For descriptive purposes, a conventional sensitivity analysis assuming a two-sided paired comparison, α = 0.05, 80% power, and n = 19 yielded a minimum detectable standardized paired effect of approximately dz = 0.68. This calculation was used only to characterize the approximate sensitivity of the achieved sample and does not represent the Bayesian longitudinal models or the protocol × time × sex interactions.
The study was not powered to provide definitive sex-specific inference. Therefore, analyses examining whether between-protocol longitudinal patterns differed by sex were interpreted as exploratory and with caution given the small number of women and men in the final analytical sample.
2.4. Resistance Training Intervention
Participants completed two supervised RT sessions per week for 8 weeks [
15]. Sessions were separated by a minimum of 48 h and a maximum of 96 h to support recovery [
15,
23,
24,
25]. An investigator directly supervised all sessions to ensure adherence to protocol allocation and standardized technique. The intervention targeted unilateral preacher curl and unilateral leg extension, performed on both limbs each session (i.e., one limb under FAIL and the contralateral limb under RIR for each exercise).
Under FAIL, all sets were performed to momentary muscular failure, defined as the inability to complete the concentric phase of a repetition despite attempting to do so (for at least two seconds) and maximal effort while maintaining the prescribed technique [
15,
24,
26,
27]. Under RIR, the prescribed target was 2 RIR; values between 1 and 3 RIR were accepted as a predefined operational tolerance rather than as alternative targets [
15,
24,
28,
29]. Training loads were initially selected to correspond to ~70–80% of pre-intervention 1RM, to complete 8–12 repetitions at the assigned set-termination endpoint [
1,
15,
30,
31]. Progressive overload was applied throughout: if participants achieved 12 repetitions or more, loads were increased in subsequent sessions (approximately 1–2 kg for the preacher curl and 2.5–5 kg for the leg extension) [
15,
28,
32]. Intra-session load adjustments were permitted when repetition performance deviated substantially from the target range while respecting the assigned endpoint. Specifically, under FAIL, if participants were unable to achieve a minimum of 8 repetitions with the selected load on a given set, the load was reduced for the subsequent set (≈1–2 kg for preacher curl; 2.5–5 kg for leg extension); however, to avoid excessive load manipulation, some decay in repetitions (e.g., to ~4–5 repetitions) was tolerated before implementing a reduction. Under RIR, if participants consistently performed fewer than 8 repetitions to reach the 2-RIR endpoint, the load was similarly reduced for the subsequent set. Minor deviations from the 8–12 repetition target were tolerated on occasion to prevent excessive intra-session adjustments, with repetition self-regulation to maintain the assigned endpoint remaining the primary mechanism for dose control. The program comprised 5 sets per muscle group and per limb from the beginning of the intervention until week 4. Thereafter, one additional set was added, resulting in 6 sets per muscle group and per limb from week 5 to week 8.
The unilateral preacher curl was always performed before the unilateral leg extension. Rest intervals were standardized at 2 min between sets and 5 min between exercises. To balance potential fatigue effects between conditions, the starting limb (FAIL vs. RIR) alternated across sessions. All training sessions were performed using commercial-grade equipment (Technogym, Gambettola, Italy), including a unilateral preacher curl setup with adjustable dumbbells and a unilateral leg extension machine.
Participants were permitted to continue habitual RT for non-targeted muscle groups but were instructed to refrain from additional elbow flexor or knee extensor exercises throughout the intervention; adherence was verbally confirmed at each supervised session.
2.5. RIR Scale Familiarization
Before baseline data collection, participants completed one to two familiarization weeks to calibrate their perception of the RIR scale. These sessions were separated by ≥48 h. Participants performed the study exercises bilaterally with continuous visual access to a printed RIR scale and standardized verbal anchors (e.g., “Do you feel you could do exactly 2 more repetitions?”) [
15,
28]. Investigators occasionally instructed participants to continue to failure after reporting the target RIR to verify correspondence between predicted and actual repetitions, enabling immediate calibration. During the intervention, termination of FAIL sets at momentary muscular failure was recorded by the investigators. In the RIR condition, participants verbally reported their perceived RIR at the end of each set, and this value was recorded. RIR accuracy was not objectively verified after every training set.
2.6. Intervention Fidelity Assessment
The supervised-training records were reviewed descriptively to characterize attendance and protocol implementation. For each condition, completed repetitions, external load, session volume-load, load progression, and set-termination records were summarized. Volume-load was calculated as external load multiplied by completed repetitions. The prescribed number of direct sets for each target muscle was matched between conditions. Volume-load was not constrained because the number of repetitions completed was an inherent consequence of the assigned set-termination procedure. It was nevertheless summarized descriptively to characterize the external work performed under each condition and to support interpretation of the bioelectrical outcomes. All intervention-fidelity comparisons were descriptive, and no inferential tests were performed.
2.7. Bioelectrical Impedance Assessment
Raw bioelectrical parameters were assessed using a multi-tactile bioimpedance analyzer (InBody S10, Biospace, Seoul, Korea) at 50 kHz, with participants evaluated in the supine position [
33]. Assessments were conducted in the morning (08:00–10:00), under standardized conditions: overnight fast; same time-of-day across repeated assessments; ≥48 h without RT prior to testing; no caffeine or alcohol consumption in the preceding 24 h; bladder voided immediately before assessment; removal of metallic objects; and controlled room temperature (22–23 °C) [
34]. These pre-assessment instructions were applied at baseline, week 4, and week 8, and the ≥48 h restriction applied to resistance training irrespective of whether it involved the study-targeted or non-targeted muscle groups. The exact interval beyond this minimum was not standardized, and dietary, carbohydrate, and fluid intake outside the prescribed overnight fast was not quantitatively monitored or replicated across assessments. Participants rested quietly for 10 min before electrode placement and measurement [
35]. Skin sites were cleaned with alcohol and cotton before electrode placement. For female participants, menstruation status at the time of assessment (i.e., whether they were currently menstruating or not) was obtained by self-report. However, no formal tracking of cycle day or menstrual cycle phase, nor hormonal verification, was performed. Accordingly, menstrual cycle phase was not treated as a controlled variable in the present study.
Bioelectrical measurements were obtained using manufacturer-supplied tactile electrodes placed according to the standardized InBody S10 procedures. Hand electrodes were connected to the thumbs and middle fingers of both hands, and foot electrodes were positioned between the ankle bone and heel of both feet (Inbody S10 user’s manual). Participant positioning was standardized to avoid limb contact and facilitate stable fluid distribution during measurement. Although the device uses a hand-to-foot electrode configuration, the present study did not analyze whole-body values as the primary outcomes. Instead, raw parameters were extracted from the device-provided segmental outputs for the right arm, left arm, right leg, and left leg. Therefore, the analyzed values should be interpreted as segmental limb-level estimates rather than localized bioimpedance measurements obtained directly over the trained elbow flexors or knee extensors.
The InBody S10 provided device-exported segmental impedance magnitude (Z), reactance (Xc), and phase angle (PhA) for each limb. The outcomes analyzed in the present study were device-exported PhA (degrees), device-exported Xc (Ω), derived resistance (R, Ω), and derived capacitance (CAP, pF). PhA is physically defined as PhA = arctan (Xc/R) × 180/π. Device-exported PhA values were used in the primary analyses, and internal consistency checks confirmed close agreement with PhA recalculated from derived R and Xc, with discrepancies compatible with rounding. Because R was not available as an explicit exported variable in the analytical dataset, segmental resistance was derived from device-exported Z and Xc as R = √(Z2 − Xc2). CAP was not measured directly by the device but was derived from Xc at 50 kHz as CAP = [1/(2πf · Xc)] × 1012, where f = 50 kHz, and expressed in pF.
To minimize error, all assessments were performed under consistent pre-test constraints, and within-device longitudinal comparisons were prioritized given known differences in absolute values across analyzers. However, because each segmental current path encompasses tissues beyond the trained elbow flexors or knee extensors, localized adaptations may have been diluted within the broader limb-level estimate. Although segmental resistance changes have been associated with segmental changes in lean soft tissue following resistance training [
16], this does not establish the sensitivity of the InBody S10 raw segmental outputs to adaptations confined to these specific muscle groups. Accordingly, the outcomes were interpreted as within-device segmental responses rather than localized indicators of muscle-specific adaptation [
19]. The analyzed parameters were treated exclusively as segmental electrical descriptors and were not interpreted as direct measures or surrogate indicators of muscle hypertrophy, intracellular water, membrane integrity, or cellular health.
2.8. Statistical Analysis
All analyses were performed in R (v 4.0.2; R Core Team,
https://www.r-project.org/ (accessed on 19 July 2026)) using Bayesian Gaussian mixed-effects models fitted with brms (v2.23.0) [
36]. The primary models used a Gaussian likelihood with identity link on the observed outcome scale. Primary models were specified separately for PhA, R, and Xc in each limb region. CAP models were retained only as supplementary sensitivity analyses of an alternative derived representation of Xc and were not interpreted as providing independent evidence. No single bioelectrical outcome was formally designated as a confirmatory primary endpoint. Accordingly, PhA, R, and Xc were evaluated as related bioelectrical outcomes in the primary models, with the within-participant protocol × time contrast representing the principal inferential comparison; protocol × time × sex interactions were considered secondary and exploratory. Fixed effects included protocol (FAIL vs. RIR), time (baseline, week 4, and week 8), sex (female and male), and all interactions (protocol × time × sex). The primary models used the per-protocol population of 19 participants who completed the intervention and met the minimum attendance requirement. To evaluate the potential influence of post-allocation exclusions, all eight final models were additionally refitted as an available-data sensitivity analysis using every protocol-linked observation from the 22 participants who began the intervention (baseline
n = 22, week 4
n = 21, and week 8
n = 19). These models retained the likelihood, fixed-effects specification, selected random-effects structure, and prior distributions of the corresponding primary model. Missing outcomes were not imputed; therefore, this analysis was interpreted as an available-data sensitivity analysis rather than as a complete intention-to-treat analysis.
Candidate random-effects structures were defined from the experimental hierarchy. All models included a participant-level random intercept, (1 | id), to account for the correlation among repeated observations from the same participant. A nested candidate additionally included a side-within-participant random intercept, (1 | id) + (1 | id:side), allowing for persistent differences between limbs across repeated assessments. The same two candidate structures, with identical fixed effects and priors, were evaluated for every outcome-region combination. Predictive performance was compared primarily using Pareto-smoothed importance sampling leave-one-out cross-validation (PSIS-LOO) [
37], with WAIC calculated descriptively. The nested structure was retained in seven of the eight models. The only exception was leg PhA, for which the additional side-within-participant intercept did not improve predictive performance and the simpler participant-intercept model was retained. Because the magnitude of limb-level heterogeneity may differ across outcomes and regions, the additional variance component was not imposed when it provided no predictive improvement. All retained models met the reported stability criteria of maximum R-hat ≤1.01, no divergent transitions, and minimum bulk ESS ≥ 400 (
Supplementary Table S1). Outcome-scaled weakly informative priors were used throughout. For PhA, population-level coefficients followed normal (0, 0.5) priors; the intercept followed normal (ӯ, max [1.5sy, 0.75]); and group-level and residual standard deviations followed half-Student-t distributions with 3 degrees of freedom, location 0, and scale 0.5. For R, Xc, and CAP, population-level coefficients followed normal (0, max [0.25sy, 0.1]) priors; the intercept followed normal (ӯ, max [1.5sy, 0.75]); and group-level and residual standard deviations followed half-Student-t distributions with 3 degrees of freedom, location 0, and scale max (sy, 0.5), where ӯ and sy denote the observed outcome-specific mean and standard deviation. The exact numerical priors for every outcome-region model are reported in
Supplementary Table S13. All models were fit with 4 Markov chains, thin = 1, adapt_delta = 0.99, and max_treedepth = 13.
Prior predictive checks were used to evaluate the outcome distributions implied by the complete models before conditioning on the observed outcomes [
38]. Prior sensitivity was assessed by refitting every final model using a skeptical prior set, in which all prior scales were multiplied by 0.5, and a diffuse prior set, in which all scales were multiplied by 2.0, while retaining the original prior locations and distribution families. Posterior predictive checks compared observed distributions and summary statistics with replicated data for every outcome-region model. For CAP, the Gaussian likelihood was additionally compared with an otherwise identical Student-t likelihood, with ν ~ Gamma (2, 0.1), using posterior predictive checks and PSIS-LOO [
37]. Additional model-fitting details are provided in the
Supplementary Materials. Posterior summaries are reported as posterior means, 95% credible intervals (CrI), and posterior probabilities that the estimated effect was positive (Pr > 0). The primary aim was the difference between FAIL and RIR in change from baseline to week 4 and from baseline to week 8 for PhA, R, and Xc. Baseline FAIL-RIR contrasts were reported descriptively but were not the primary inferential target. The protocol × time × sex interactions addressed a secondary exploratory objective and were not interpreted as confirmatory evidence for or against sex moderation. Results were interpreted through the magnitude and uncertainty of the posterior estimates rather than through dichotomous thresholds. Full model diagnostics, key interaction summaries, complete fixed-effect exports, and extended direct FAIL-RIR contrasts are provided in the
Supplementary Materials (Tables S1–S7; Figures S1–S9).
As an ancillary measurement-error analysis, short-term repeatability of the bioelectrical variables was described using duplicate same-day measurements obtained within participants. Duplicate same-day measurements were available from six distinct participant-date groups; because these data were not collected as part of a formal reliability design, they were not used to estimate protocol- or time-specific reliability.
The primary analysis retained all technically valid same-day pairs. One arm acquisition containing non-physiological device outputs was excluded as technically invalid. Typical error was calculated as the SD of paired differences divided by √2, and CV% was calculated as typical error divided by the corresponding mean which was then multiplied by 100. The additional exclusion of pairs whose absolute percentage difference exceeded the outcome-specific Q3 + 3 × IQR threshold was not predefined and was conducted only as a post hoc sensitivity analysis. Different-day repeated measurements were considered exploratory because they may incorporate biological or training-related changes. Given the limited number of same-day duplicate datasets, these estimates were interpreted as descriptive measurement-error indicators rather than as a formal reliability analysis.
3. Results
The primary per-protocol analyses included 19 participants who completed the intervention and met the minimum attendance requirement. All primary models converged adequately, with maximum R-hat values ranging from 1.002 to 1.009 and no divergent transitions (
Supplementary Table S2).
The available data sensitivity analysis included all 22 participants who began the intervention, with data available from 22 participants at baseline, 21 at week 4, and 19 at week 8. All eight sensitivity models converged adequately (maximum R-hat = 1.0098; minimum bulk ESS = 507; minimum tail ESS = 864), with no divergent transitions or maximum-treedepth hits. All 24 focal protocol × time and protocol × time × sex coefficients for the primary outcomes PhA, R, and Xc retained 95% CrI spanning zero. The same was true for the eight supplementary CAP coefficients. Although three posterior means close to zero changed direction, no consistent protocol-specific or sex-specific pattern emerged, and the principal interpretation was unchanged (
Supplementary Table S16).
All prior-sensitivity and alternative-likelihood models converged without divergent transitions or maximum-treedepth hits (maximum R-hat = 1.0105; minimum bulk effective sample size = 640; minimum tail effective sample size = 585). Across the 24 focal protocol × time and protocol × time × sex coefficients for the primary outcomes PhA, R, and Xc, all 95% CrI spanned zero under the main, skeptical, and diffuse prior specifications. The same was true for the eight supplementary CAP coefficients. Some posterior means close to zero changed direction under the alternative priors, but no specification produced a consistent protocol-specific or sex-specific pattern. Posterior predictive checks reproduced the observed means and standard deviations within 3% across the six primary models and two supplementary CAP models. The CAP interaction estimates were closely comparable under Gaussian and Student-t likelihoods, despite region-specific differences in predictive performance (
Supplementary Tables S13–S15; Figures S10–S12).
Regarding intervention fidelity, all participants included in the primary analysis completed at least 13 of the 16 supervised training sessions. Set termination at momentary muscular failure was documented in 97.4% of the recorded FAIL sets for both body regions. A participant-reported RIR between 1 and 3 was recorded at the end of 96.3% of arm and 98.4% of leg RIR sets, with exactly 2 RIR reported in 80.9% and 85.9%, respectively. These records confirm that the two conditions were implemented using distinct set-termination procedures.
Median repetitions per documented set were 9 [
7,
10] for arm FAIL, 9 [
8,
10] for arm RIR, and 10 [
8,
11] for both leg conditions. Median load per documented set was 12 kg in both arm conditions and 45 kg in both leg conditions. Among paired complete sessions, the median FAIL-RIR difference in session volume-load was −4.5% [−12.0%, 3.2%] for the arm and +8.1% [−1.7%, 16.9%] for the leg. Median load progression from week 1 to week 8 was 40.0% for arm FAIL, 38.5% for arm RIR, 30.2% for leg FAIL, and 28.7% for leg RIR. Complete intervention-fidelity data are presented in
Supplementary Table S17.
Across outcomes and regions, posterior estimates for the protocol × time coefficients representing the additional change in FAIL relative to RIR from baseline to each follow-up were generally small and estimated with substantial uncertainty, as reflected by wide 95% CrI spanning zero. Accordingly, the models did not identify a consistent directional advantage for either condition; however, the uncertainty around the estimates precludes conclusions of equivalence between protocols. Selected protocol × time interaction terms are provided in
Supplementary Table S3.
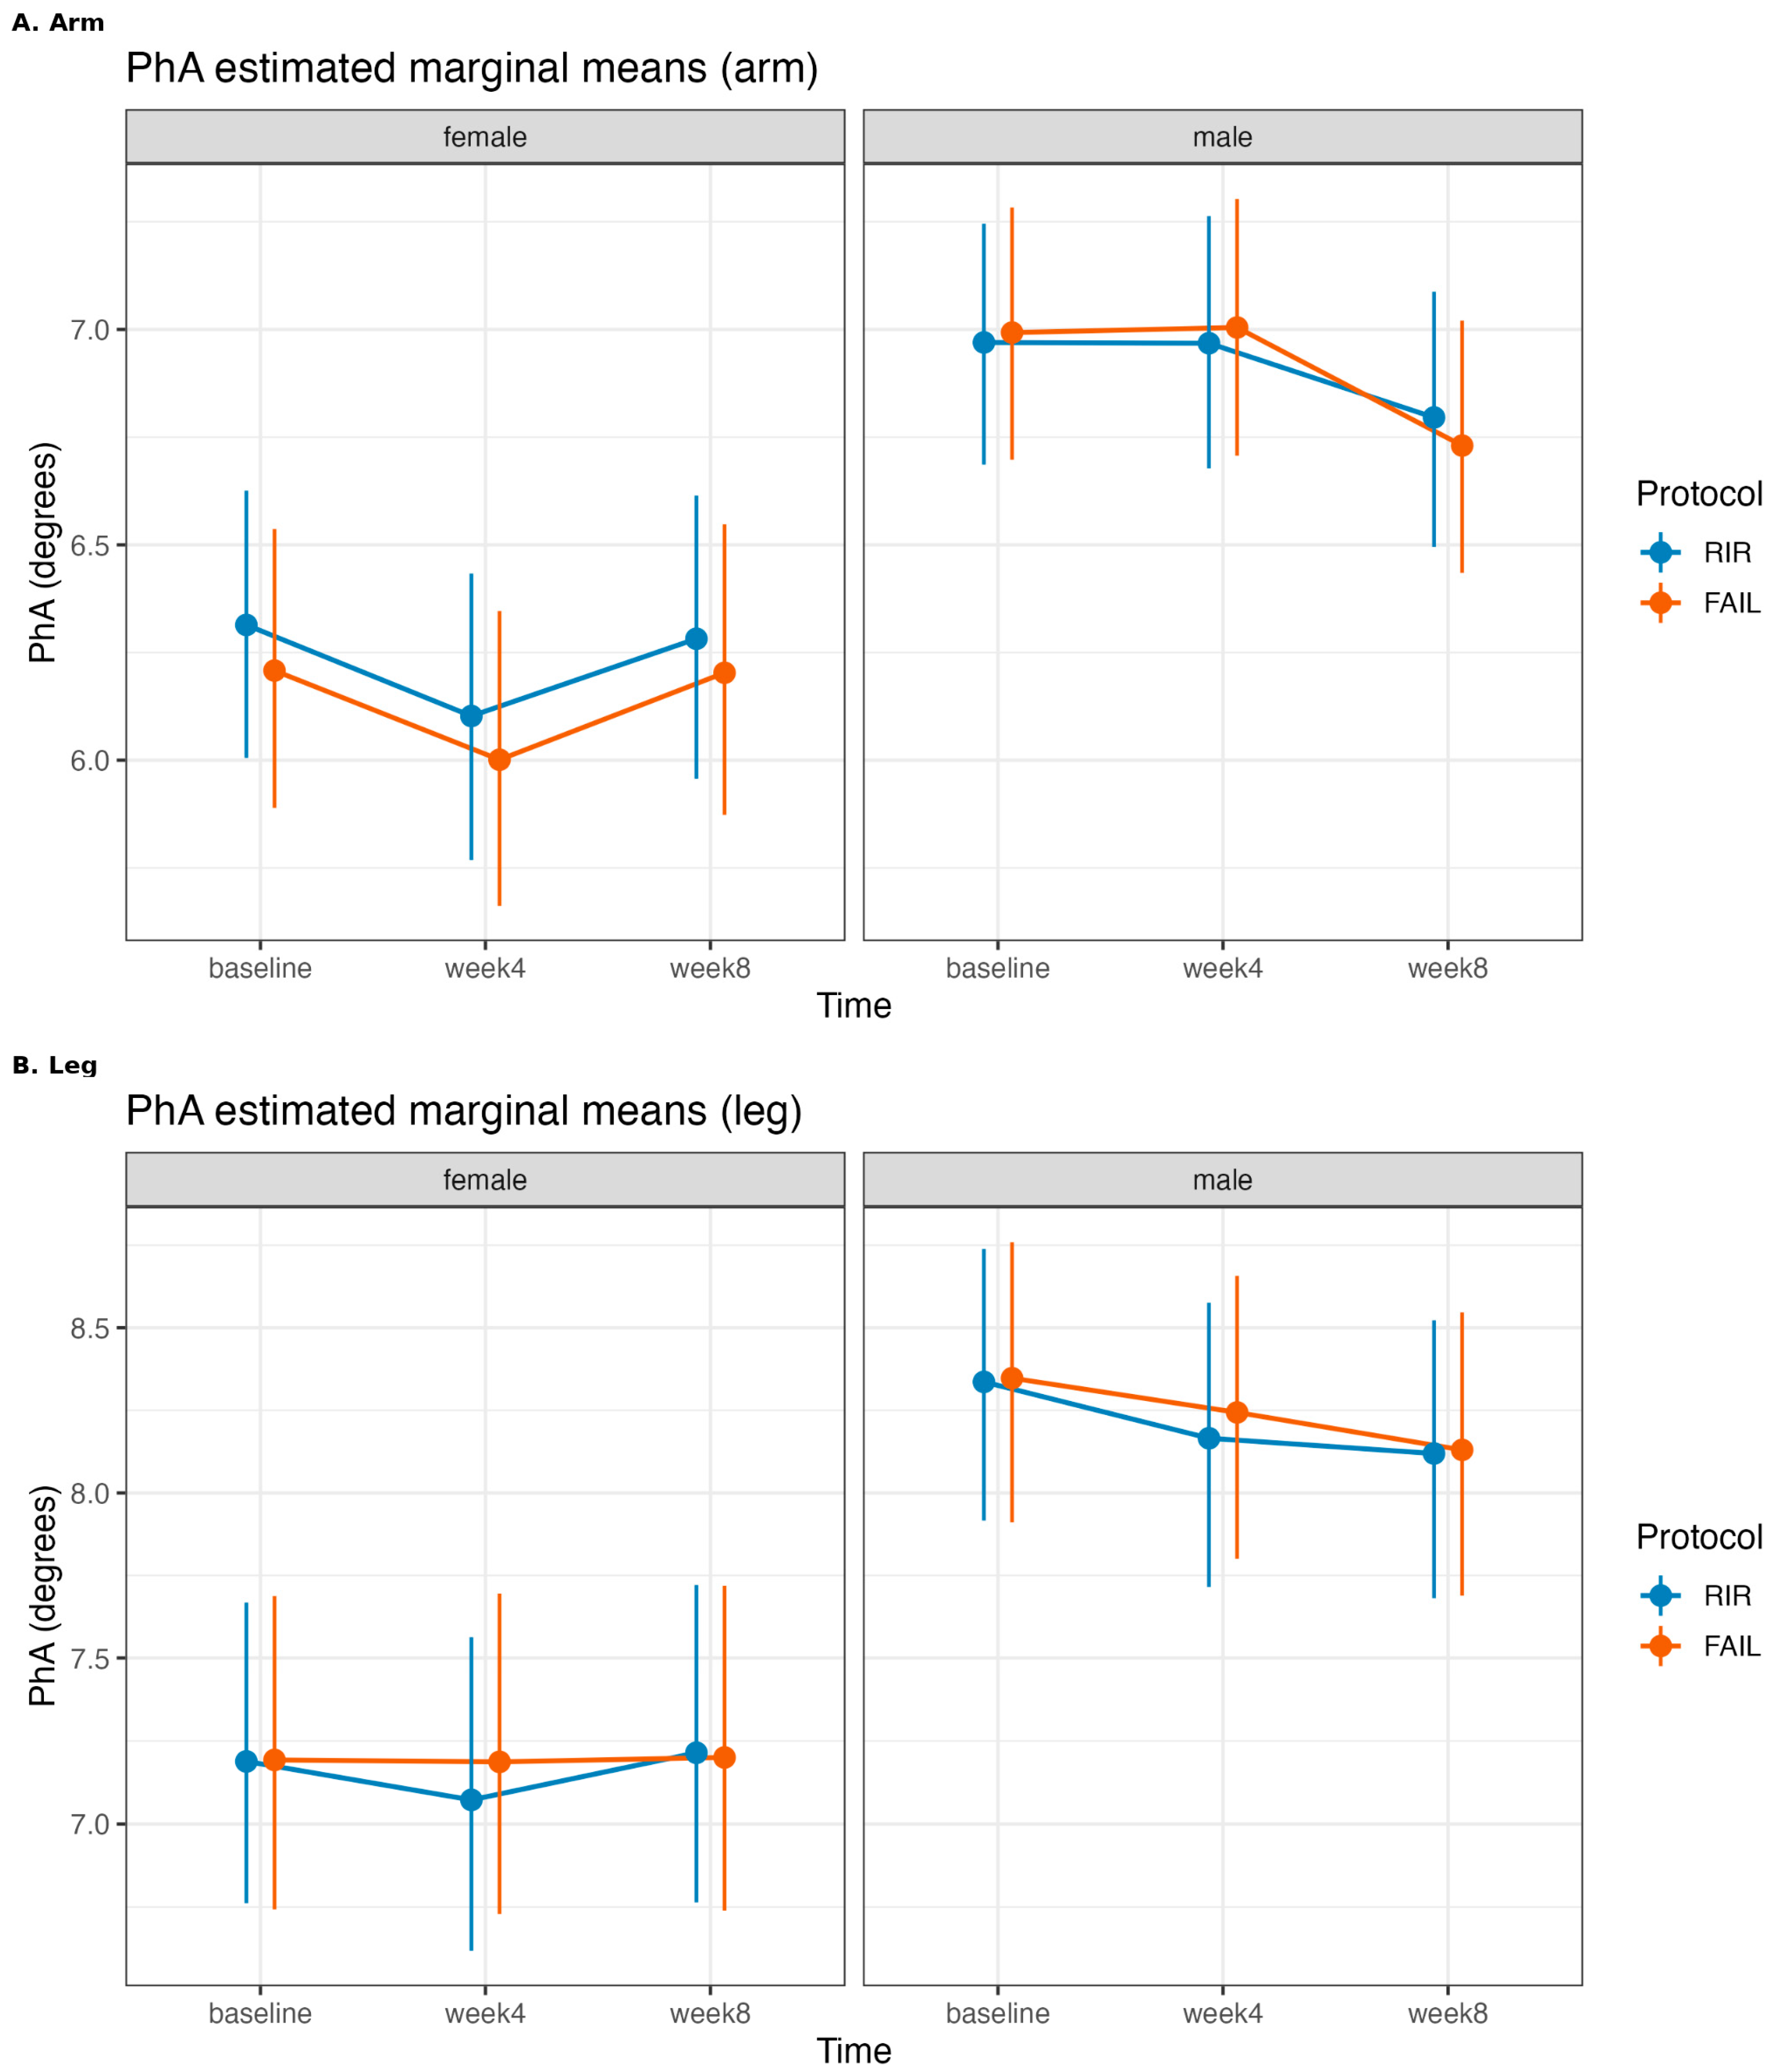
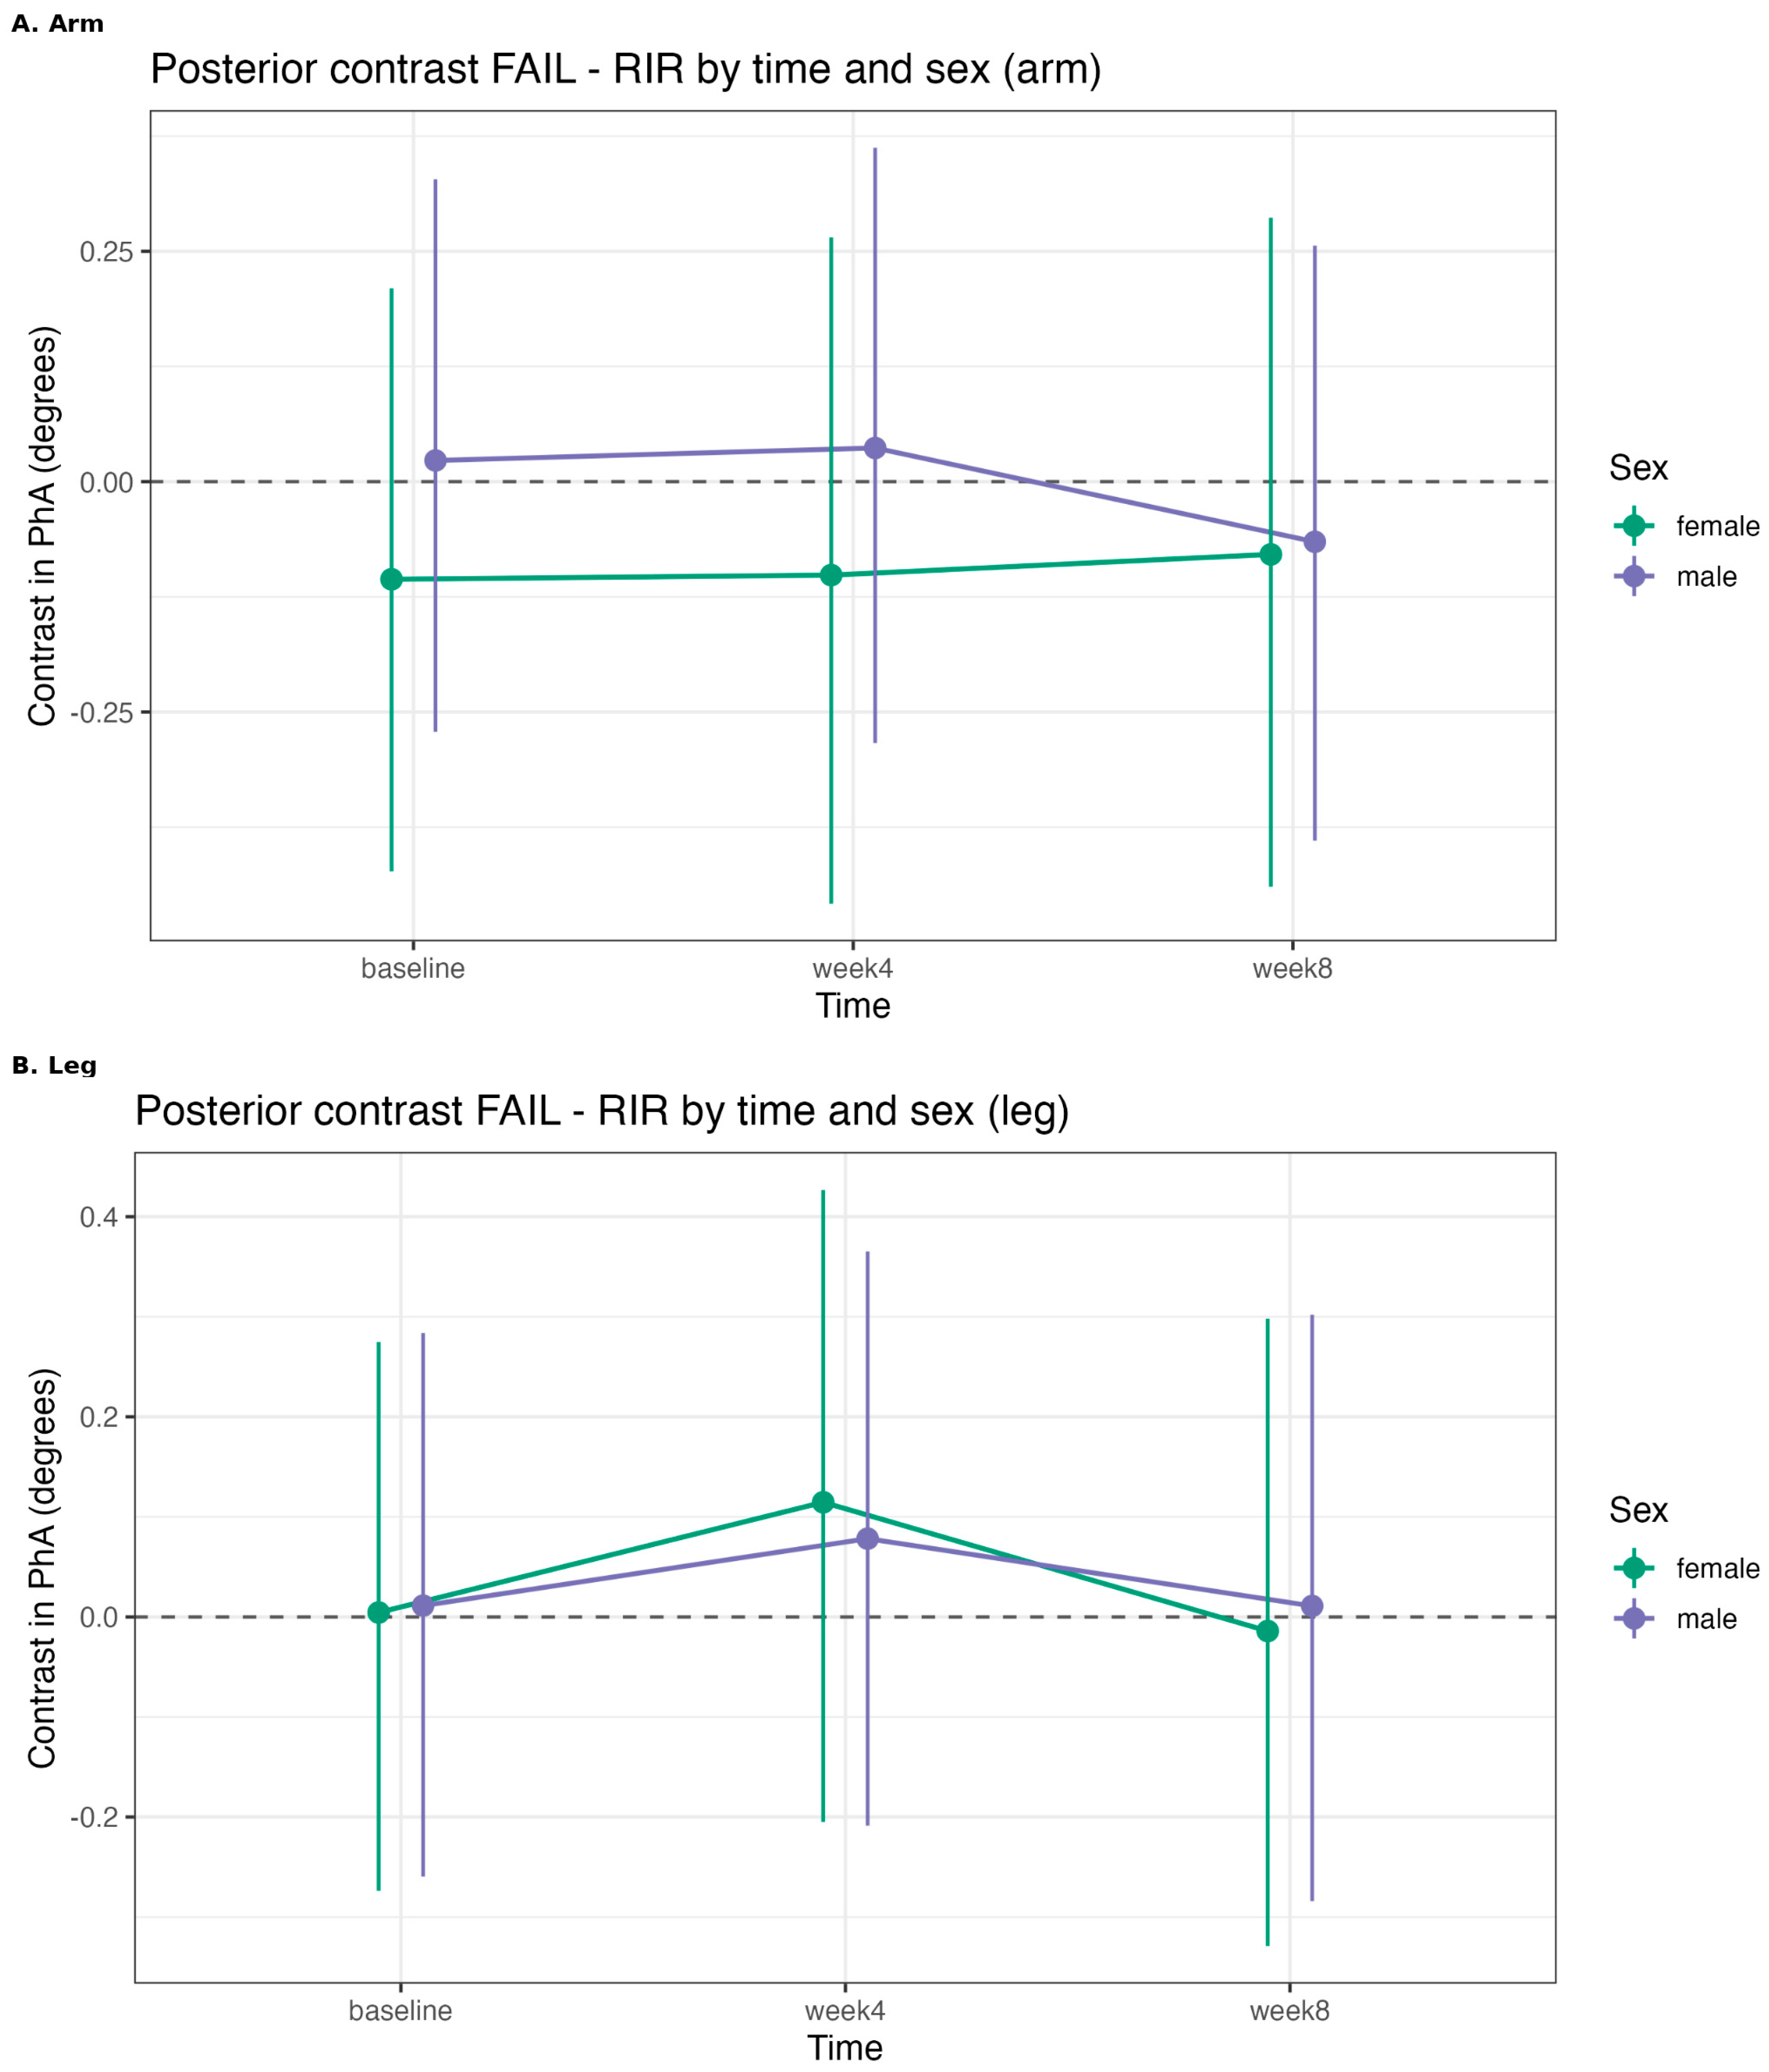
In the arm, contrasts remained small across time in both sexes (e.g., females: −0.106 [95% CrI: −0.423 to 0.210] at baseline and −0.079 [95% CrI: −0.440 to 0.286] at week 8; males: 0.023 [95% CrI: −0.271 to 0.328] at baseline and −0.065 [95% CrI: −0.390 to 0.256] at week 8). In the leg, week 4 contrasts were modestly positive but uncertain (females: 0.115 [95% CrI: −0.205 to 0.427]; males: 0.078 [95% CrI: −0.209 to 0.365]) and approached zero again by week 8. Taken together, these PhA results were more compatible with small and uncertain between-protocol differences than with a clear protocol-specific divergence over time.
For R and Xc, the focal protocol × time estimates were small or directionally inconsistent and were accompanied by wide 95% CrI across regions and follow-up time points (
Table 3). The corresponding exploratory protocol × time × sex estimates were also uncertain and did not indicate a consistent male-specific deviation from the female reference estimates. Full model coefficients, sex-specific direct FAIL-RIR contrasts at each assessment, and supplementary plots for R and Xc are provided in
Supplementary Tables S6 and S7 and Supplementary Figures S4–S7.
Because CAP represents a deterministic inverse transformation of Xc at 50 kHz, it was not interpreted as an independent outcome. The CAP analyses are retained in the
Supplementary Materials for transparency and did not alter the interpretation based on Xc.
The secondary exploratory protocol × time × sex interaction estimates were directionally inconsistent and imprecise across outcomes and regions (
Table 2;
Supplementary Tables S5 and S6). Their wide credible intervals preclude conclusions regarding either the presence or absence of sex moderation. Accordingly, the principal interpretation was based on the within-participant protocol × time comparisons, and no main conclusion was derived from the sex-specific estimates.
Duplicate same-day measurements were available for six participant-date groups. In the primary analysis of technically valid pairs, typical error and CV were 0.039° and 0.64% for arm PhA, 2.66 Ω and 0.83% for arm R, 0.17 Ω and 0.50% for arm Xc, and 713 pF and 0.73% for arm CAP. The corresponding leg values were 0.749° and 9.50% for PhA, 9.67 Ω and 4.31% for R, 1.38 Ω and 4.54% for Xc, and 4686 pF and 4.33% for CAP. Across the 16 focal protocol × time estimates, 13 were smaller in absolute magnitude than the corresponding typical error. In particular, the leg PhA estimated at weeks 4 and 8 were 0.110° and −0.019°, respectively, compared with a typical error of 0.749°. These comparisons indicate that many of the observed protocol-specific effects were not clearly distinguishable from short-term measurement variability.
4. Discussion
The primary aim of this study was to compare the longitudinal effects of resistance training performed to momentary failure versus with RIR on segmental bioelectrical parameters. To our knowledge, this is the first randomized within-participant longitudinal comparison of segmental PhA, R, and Xc responses under a controlled manipulation of proximity to failure, addressing a gap identified in the recent literature [
20]. Across outcomes, the direct FAI-RIR estimates were generally small or directionally inconsistent, but their credible intervals were wide. Accordingly, the findings provide no clear evidence of protocol-specific divergence under the conditions examined, while the limited precision precludes conclusions of similarity, equivalence, or absence of meaningful differences. These findings are restricted to the measured segmental bioelectrical responses and should not be extrapolated to unmeasured physiological or morphological adaptations.
The longitudinal patterns observed across R, Xc, and PhA can be interpreted considering the characteristics of these bioelectrical parameters. R was derived from device-reported impedance magnitude and Xc and therefore represents the resistive component of the segmental impedance vector rather than a directly exported device variable. On the one hand, R alone should not be interpreted as a direct indicator of specific fluid compartments such as ECW or ICW [
17]. On the other hand, Xc is a frequency-dependent parameter related to the capacitive properties of tissue interfaces and cells suspended in conductive fluid. At the fixed measurement frequency of 50 kHz, CAP was calculated as CAP = [1/(2πf Xc)] × 10
12 and expressed in pF [
4,
19]. It therefore represents a deterministic inverse transformation of Xc and contains no independent measured information beyond Xc. Accordingly, derived CAP should not be interpreted as a separate physiological outcome or as a direct measure of intracellular water, muscle cell mass, or membrane integrity [
17,
35]. CAP was retained only as an alternative descriptive representation of Xc and was not used to strengthen the interpretation of the primary findings. Accordingly, R, Xc, and PhA were treated as segmental bioelectrical outcomes and not as direct measures of body-water compartments, glycogen availability, membrane integrity, muscle mass, or hypertrophy.
Finally, PhA is mathematically determined by R and Xc and should be interpreted as a composite segmental bioelectrical descriptor rather than as a direct measure of fluid distribution and membrane properties [
18]. However, interpretation of PhA and its components should consider device-specific factors, including analyzer technology, electrode configuration, frequency, and reproducibility of the raw outputs. This is particularly relevant when comparing the present findings with studies using other analyzers, such as Akern systems, because analyzer technology, electrode configuration, and reproducibility may affect absolute values and longitudinal sensitivity of raw BIA parameters [
39]. Therefore, findings from studies using other BIA systems should not be assumed to translate directly to segmental estimates obtained with the InBody S10. The near-zero and uncertain PhA contrasts indicate no clear protocol-specific divergence in the measured PhA responses, but they do not establish similarity in the underlying physiological adaptations. Because PhA is mathematically determined by R and Xc, the corresponding patterns across these variables should be interpreted as internal consistency among related representations of the impedance signal, rather than as independent physiological confirmation. These findings are broadly consistent with the literature on proximity to failure, which suggests that resistance-training responses are often comparable when sets are performed to failure or terminated just short of it. Grgic et al. [
40] found no clear overall advantage of failure over non-failure training for muscular strength or hypertrophy, whereas Robinson et al. [
14] suggested that any effect of proximity to failure is likely modest and outcome dependent. In a more direct design, Refalo et al. [
15] reported no clear between-condition difference in quadriceps muscle thickness changes following training to momentary muscular failure or with 1–2 RIR. These hypertrophy findings provide contextual evidence concerning proximity to failure but cannot establish the physiological basis of the present segmental bioelectrical responses. In the present study, no reproducible directional advantage of either protocol was identified across the segmental bioelectrical parameters.
Because R, Xc, and PhA are indirect and mathematically related segmental bioelectrical descriptors, the present data cannot identify the biological mechanisms underlying their longitudinal variation. Previous studies have reported associations between raw bioelectrical parameters, fluid distribution, and soft-tissue characteristics [
3,
16,
17]. However, these relationships are dependent on the measurement approach and do not demonstrate that changes observed in the present study reflect intracellular water, muscle hypertrophy, cellular integrity, or membrane remodeling. Accordingly, no muscle-specific or mechanistic inference can be drawn from the present bioelectrical outcomes.
Direct FAIL-RIR contrasts were generally small and directionally inconsistent across regions and time points. This was most evident for PhA, for which the estimated contrasts remained close to zero across both sexes and regions (
Table 1;
Supplementary Table S4).
The corresponding contrasts for R, Xc, and CAP showed no reproducible directional pattern, despite wider uncertainty, particularly for CAP (
Supplementary Table S7; Figures S4–S9). Accordingly, the present findings do not support a consistent advantage of training to failure for any of the segmental raw bioelectrical outcomes examined.
The uncertainty around these estimates likely reflects the combined influence of the modest sample size, interindividual variability in training and bioelectrical responses, biological fluctuations in fluid distribution, and potential measurement variability associated with segmental BIA. Therefore, the absence of consistent between-protocol differences should be interpreted as no clear evidence of protocol-specific divergence, rather than as definitive evidence of equivalence between FAIL and RIR.
These findings should nevertheless be interpreted with caution. Between-protocol differences were small relative to the uncertainty around the estimates, and within-study reliability of the bioelectrical measurements was not formally assessed, limiting confidence in the interpretation of small changes. Additionally, no clear sex-specific pattern emerged, although these estimates were among the least precise in the study. Thus, the absence of interaction effects should be interpreted as limited evidence for sex-specific divergence rather than evidence of equivalence. Longitudinal evidence regarding sex-specific responses in raw bioelectrical parameters remains scarce.
Future research should determine whether proximity-to-failure effects on raw bioelectrical parameters become more apparent under designs imposing a greater contrast between conditions or longer intervention durations. Combining segmental bioelectrical parameters with direct assessments of hypertrophy, glycogen content, and fluid compartmentalization may help clarify the mechanisms underlying these responses. Additionally, further work is needed to establish whether segmental bioelectrical responses are consistent across sexes, training statuses, and body regions.
Limitations
Despite the practical relevance of the present findings, several methodological limitations should be considered when interpreting the results. First, control of menstrual-related variability in female participants was incomplete. Although participants reported whether they were currently menstruating at the time of assessment, no formal tracking of cycle day or menstrual cycle phase, nor hormonal verification, was performed. Accordingly, female participants may have been assessed under different hormonal conditions across repeated assessments, which could have influenced fluid distribution and, consequently, BIA-derived parameters [
41,
42]. Although early follicular assessments could theoretically reduce hormonal variability, menstruation is also associated with behavioral and physiological factors (e.g., bleeding, symptoms, changes in fluid intake) and increased prostaglandin activity, which may affect hydration status and capillary permeability. Together, these factors may introduce variability in BIA-derived parameters. However, considering the study time required to evaluate each athlete, it is not possible to always evaluate the female athlete in the same phase, and thus, it must be mentioned as a limitation. Similar approaches have been used in other studies [
43]. Because both protocol-assigned limbs were assessed concurrently within each female participant, such menstrual-cycle-related variation would not be expected to systematically favor FAIL or RIR at a given assessment. However, variation in hormonal status across measurement occasions may have increased longitudinal variability and reduced the precision of the exploratory protocol × time × sex estimates.
Second, hydration status was not directly assessed using objective markers (e.g., urine-specific gravity or osmolality) and using at least two independent methods according to the most recent recommendations [
44], which is a relevant limitation given the sensitivity of BIA to fluid distribution. Although consistent pre-assessment instructions were applied, including morning testing, an overnight fast, and at least 48 h without RT, the exact interval beyond this minimum was not standardized, and dietary, carbohydrate, and fluid intake was not quantitatively monitored or replicated across assessments. Consequently, residual variation in recovery, hydration, or glycogen status across measurement occasions cannot be excluded. Third, the modest sensitivity to detect small effects reduced the precision of interaction estimates, particularly for sex-specific analyses. In addition, three participants who began the intervention were excluded from the primary per-protocol analysis, which may have introduced participant-level selection bias. Because each participant received both randomized conditions contralaterally, each exclusion removed observations from both FAIL and RIR rather than selectively depleting one protocol. The available data sensitivity analysis including all 22 participants who began the intervention produced the same overall inferential pattern. Nevertheless, this analysis cannot exclude bias arising from missing outcomes if missingness was related to unobserved responses.
Fourth, ancillary same-day repeatability analyses were performed. These were based on a limited subset of duplicate measurements and should be interpreted as pragmatic measurement-error descriptors rather than as a formal validation of the accuracy or long-term reliability of the InBody S10. This is relevant because small changes in R, Xc, PhA, and derived CAP may be difficult to distinguish from biological and technical variability, particularly for parameters with larger CVs such as leg PhA. Indeed, the focal leg PhA estimates were substantially smaller than the corresponding typical error. More broadly, most protocol × time estimates were of a similar or smaller magnitude than the outcome-specific measurement error. Small protocol-specific effects should therefore not be interpreted as reliably detected changes or as evidence of equivalence between conditions. Moreover, because raw BIA parameters and their reproducibility may differ across analyzers and electrode configurations, direct comparison with studies using other devices should be made cautiously.
Fifth, direct measures of muscle-specific adaptation were not incorporated into the present analysis, and the segmental InBody S10 current paths encompassed the entire arm or leg rather than the specifically trained muscle groups. Consequently, localized adaptations may have been diluted within the limb-level estimates, and the observed bioelectrical responses cannot be linked directly to changes in muscle size or interpreted as evidence of muscle hypertrophy. Sixth, RIR was based on the participants’ reports at set termination and was not objectively verified after every set. Nevertheless, the familiarization procedures included occasional continuation-to-failure trials to calibrate RIR perception, and the recorded set endpoints indicate that the FAIL and RIR conditions were implemented using clearly distinct termination procedures. Nevertheless, the accepted 1–3 RIR operational tolerance means that some RIR sets may have been terminated closer to failure than the prescribed 2-RIR target, potentially reducing the effective contrast between conditions.
Additionally, although the unilateral within-participant design reduces between-participant confounding, it cannot completely exclude systemic or interlimb interference [
45]. Both limbs were trained within the same session, and shared responses related to fluid balance, glycogen availability, inflammation, or recovery could have attenuated protocol-specific differences. Cross-education has been demonstrated primarily for strength outcomes and is considered predominantly neural in origin [
46], whereas direct evidence regarding resting segmental bioelectrical parameters is lacking. Alternating the starting limb across sessions prevented training order from systematically favoring either condition, but it does not exclude shared systemic or contralateral effects. Accordingly, the within-participant comparisons may underestimate protocol-specific divergence and may not generalize directly to whole-body training contexts. Finally, the intervention duration (8 weeks) may not have been sufficient to capture longer-term adaptations in bioelectrical properties.