Mediastinal Lymphangioma of the Adult: Case Report and Literature Review

 ,
Abstract
1. Introduction
2. Materials and Methods
2.1. Case Report Presentation
2.2. Literature Search Strategy
2.3. Ethical Considerations
2.4. Statistical Analysis
3. Results
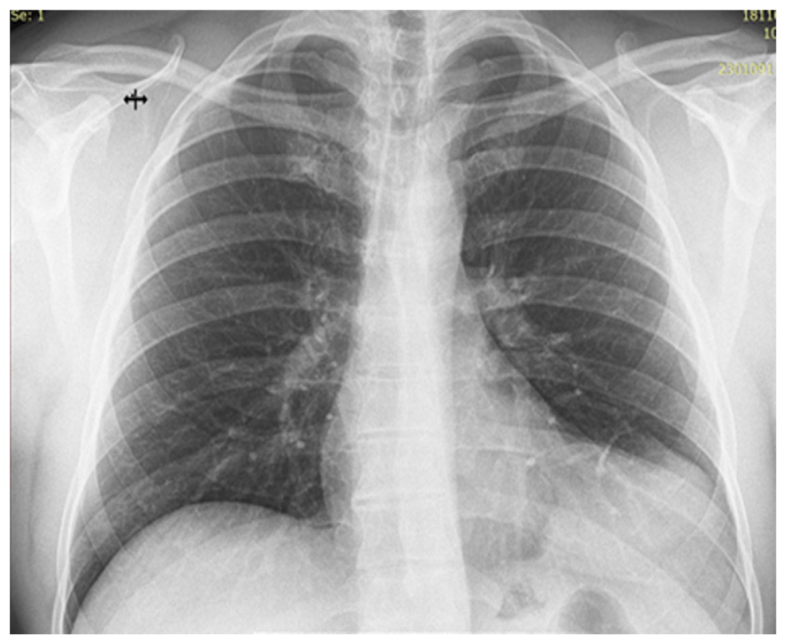
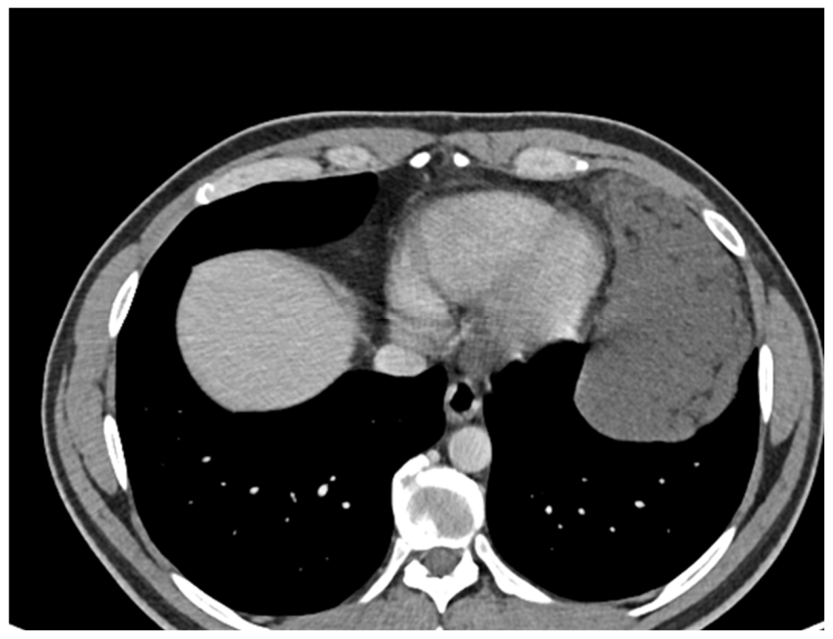
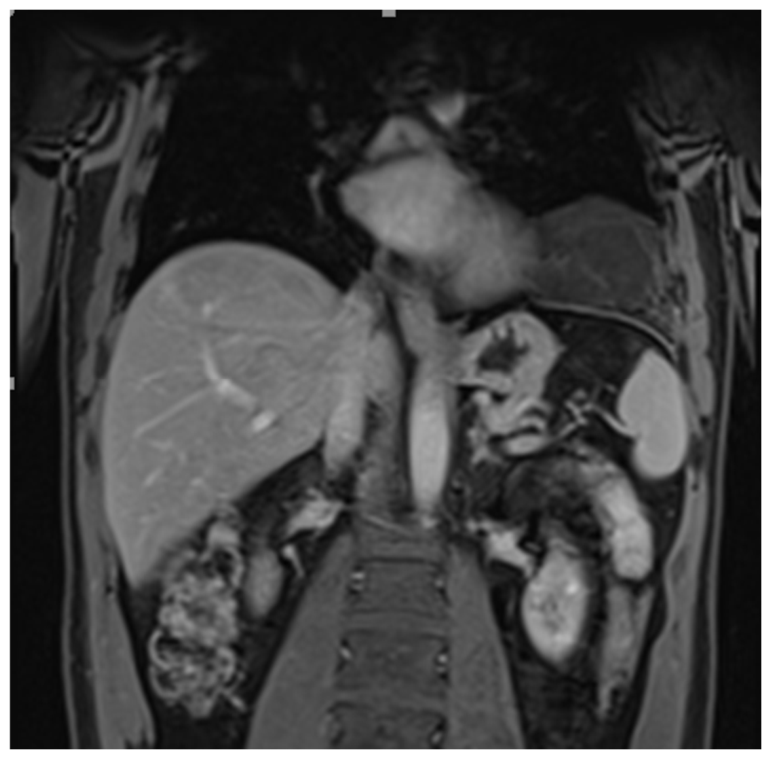
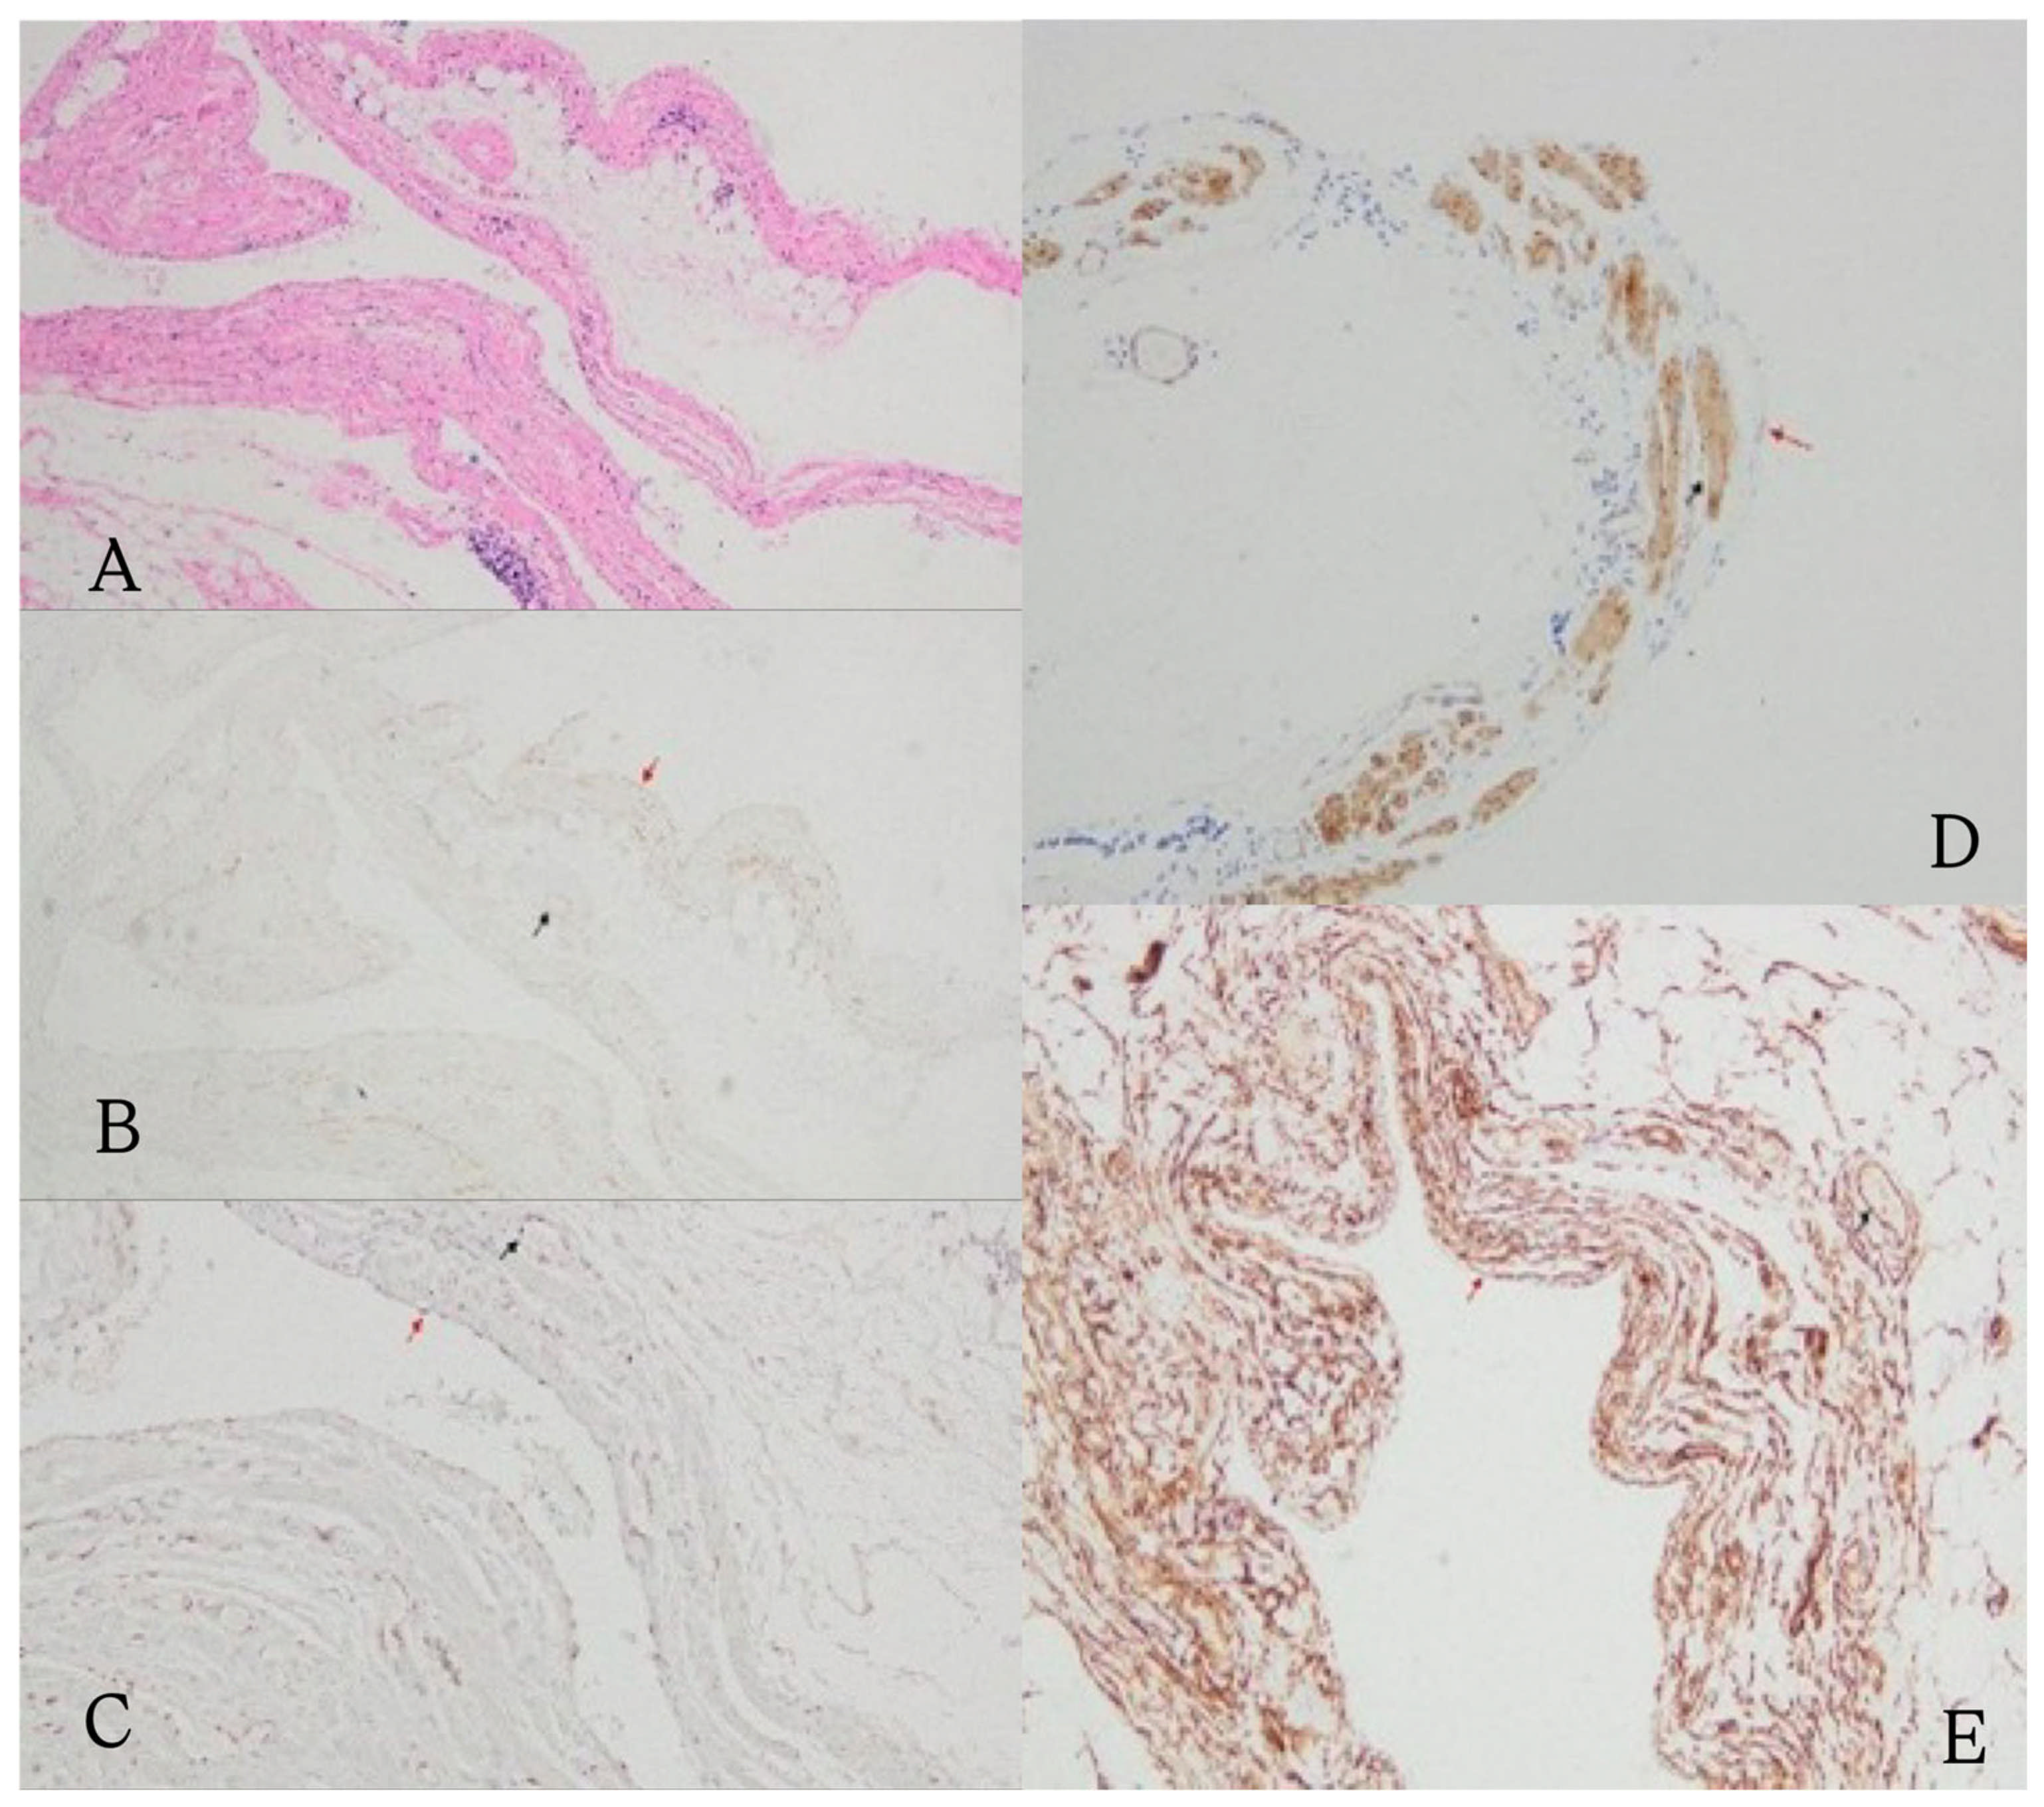
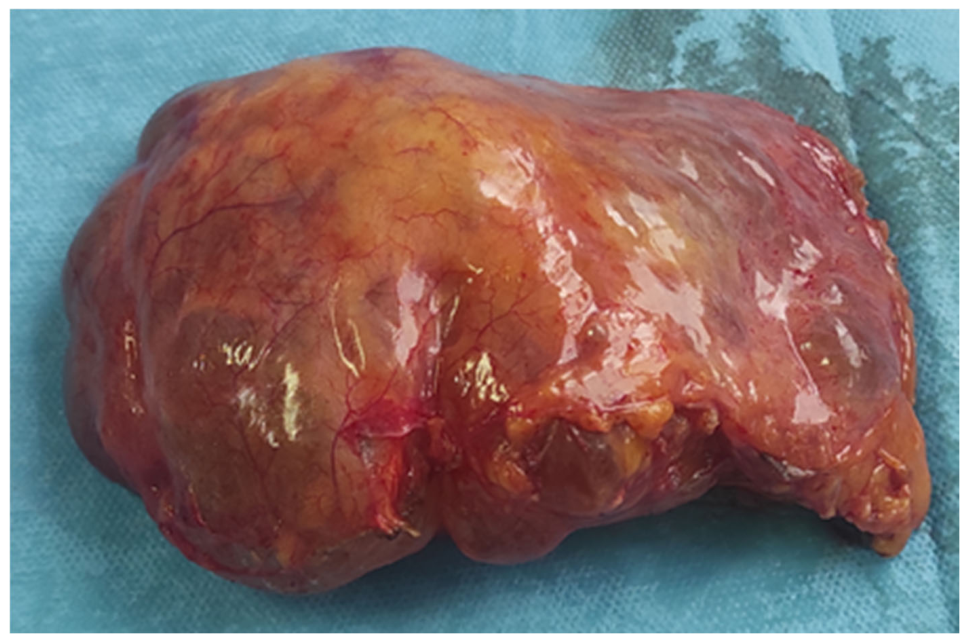
3.1. Case Report
- •
- Lipoma or liposarcoma, hypothesized due to the heterogeneous tissue densities and complex internal composition observed on cross-sectional imaging;
- •
- Lymphangioma, which remained the primary presumptive diagnosis supported by the characteristic MRI findings.
3.2. Literature Review
4. Discussion
- •
- Diaphragmatic hernia: suspected due to trauma history and inferior supradiaphragmatic positioning.
- •
- Lipoma or liposarcoma: considered because of adipose-density tissue elements on CT.
- •
- Thymoma or bronchogenic cyst: typical primary mediastinal cystic differential entities.
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| CD31 | Cluster of differentiation 31 |
| CD34 | Cluster of differentiation 34 |
| CT | Computed tomography |
| DLCO | Diffusing capacity of the lung for carbon monoxide |
| EBUS | Endobronchial ultrasound |
| ERG | ETS-related gene |
| FNA | Fine-needle aspiration |
| HE | Hematoxylin and eosin |
| IQR | Interquartile range |
| KCO | Carbon monoxide transfer coefficient |
| LM | Mediastinal lymphangioma |
| MRI | Magnetic resonance imaging |
| mTOR | Mammalian target of rapamycin |
| N/R | Not reported |
| PET-CT | Positron emission tomography–computed tomography |
| PIK3CA | Phosphatidylinositol-4,5-bisphosphate 3-kinase catalytic subunit alpha |
| RATS | Robotic-assisted thoracic surgery |
| SD | Standard deviation |
| SMA | Smooth muscle actin |
| US | Ultrasonography |
| VATS | Video-assisted thoracic surgery |
| VEGF | Vascular endothelial growth factor |
Appendix A

| Year | Author | No Cases | Sex | Age (Years) * | Clinical Presentation | Imaging | Size (CM) | Positioning in the Mediastinum | Surgical Approach | Histopathology |
|---|---|---|---|---|---|---|---|---|---|---|
| 2001 | Oshikiri et al. [50] | 5 | 2M 3F | 20–74 | 4 Asymptomatic, 1 dyspnea and superior vena cava syndrome | 5CT 1MRI | 11 | 1 Anterior 1 Superior 3 Posterior | N/R | 3 cystic LM 1 cavernous LM 1 mixed LM |
| 2002 | Kim et al. [21] | 1 | M | 77 | Cough | CT +MRI | N/R | Anterior mediastinum | Mediastinoscopy + partial sternotomy + biopsy | Cavernous LM |
| 2002 | Yoo et al. [25] | 1 | M | 38 | Sudden onset of anterior chest and neck pain | CT | N/R | Anterior mediastinum | N/R | Cavernous LM |
| 2003 | Kim et al. [38] | 3 | F | 48 | Asymptomatic | CT | N/R | Superior, anterior, middle, and posterior mediastinum | N/R | Cystic LM |
| M | 31 | Asymptomatic | CT + MRI | 4 × 4 | Anterior mediastinum | VATS | Cystic LM | |||
| M | 30 | Asymptomatic | CT + MRI | 13 × 10.5 × 0.2 | Middle mediastinum | Thoracotomy | Cystic LM | |||
| 2003 | Shetty et al. [51] | 1 | M | 43 | Gradual dysphagia and significant weight loss | CT | 15 × 10 × 7 | Middle mediastinum | Right posterolateral thoracotomy | Cystic LM |
| 2003 | Zahirifard et al. [52] | 1 | M | 28 | 1.5-month history of dyspnea on exertion and palpitations, with worsening dyspnea in the two weeks prior to admission | CT | N/R | All mediastinum compartments | Right posterolateral thoracotomy. | Cavernous LM |
| 2004 | Daya et al. [53] | 1 | M | 45 | Acute chest pain + intermittent episodes 2 weeks prior | CT | 12 × 10 | Anterior mediastinum | Median sternotomy | Cystic LM |
| 2004 | Parker et al. [39] | 1 | M | 47 | Asymptomatic | CT | 15 × 7 | Posterior mediastinum | VATS biopsy | Esophageal LM |
| 2005 | Coffing et al. [7] | 1 | F | 46 | Incidental finding | CT | 5.2 | Posterior mediastinum | None | |
| 2005 | Pop et al. [54] | 1 | M | 60 | Cardiac tamponade initially, 1 year later palpitations, dyspnea, tachycardia and pleural effusion | CT | 9 × 5.5 | Anterior mediastinum | Bilateral VATS | Cystic LM |
| 2006 | Misthos et al. [55] | 4 | 4M | 23–54 (mean 38.7) | Asymptomatic | CT | 7–13 (mean 9.5) | Superior mediastinum | Muscle-sparing lateral minithoracotomy | Cystic LM |
| 2006 | Park et al. [22] | 8 | F | 48 | Chest pain, dyspnea | CT | N/R | Right superior and middle mediastinum | Primary: Thoracotomy (performed in 6 cases as the initial procedure). Diagnostic/Secondary: Mediastinoscopy (3 patients) and Mediastinotomy (3 patients) were used to obtain diagnosis or for patients with smaller/accessible paratracheal lesions | Cavernous or cystic LM |
| M | 66 | Dyspnea | CT | N/R | Right and middle mediastinum | |||||
| F | 81 | Dyspnea | CT | N/R | Right superior and middle mediastinum | |||||
| F | 26 | Chest pain, dyspnea, hemoptysis | CT | N/R | Superior mediastinum | |||||
| F | 41 | Asymptomatic | CT | N/R | Right superior and posterior mediastinum | |||||
| F | 70 | Chest pain, dyspnea, hemoptysis | CT | N/R | Right anterior mediastinum | |||||
| F | 39 | Dyspnea | CT | 4 | Right superior mediastinum | |||||
| M | 47 | Fever | CT | 7 × 8 × 5 | Right superior mediastinum | |||||
| 2006 | Saleiro et al. [56] | 1 | F | 44 | Asymptomatic | CT | 4 × 5 | Anterior and superior mediastinum | Right posterolateral thoracotomy | Cystic LM |
| 2008 | Correia et al. [5] | 1 | M | 50 | Incidental finding on X-ray | CT | 4.5 | Superior mediastinum | Right lateral thoracotomy | Cystic LM |
| 2008 | Teramoto et al. [57] | 1 | F | 43 | One-month history of cough, dyspnea, and recurrent high fevers (up to 40 °C) | CT + MRI | 3.8 × 3 × 7.5 | Posterior mediastinum | VATS converted to right thoracotomy | Cavernous LM |
| 2009 | Hunt et al. [40] | 1 | F | 43 | Asymptomatic | CT | N/R | Superior mediastinum | VATS | Cystic LM |
| 2009 | Melo et al. [58] | 1 | F | 59 | Asymptomatic | CT | 4.5 | Mediastinum right paratracheal | Right lateral thoracotomy | Cystic LM |
| 2009 | Sun yi-feng et al. [59] | 7 | 3M 4F | 18–67 (average 40) | Asymptomatic | CT | 5–8 | Superior mediastinum | Median sternotomy (4 patients), right posterolateral thoracotomy (1 patient), cervical supraclavicular incision (2 patients) | Cystic LM |
| 2011 | Conte et al. [26] | 1 | F | 60 | Palpitations | MRI | 2.5 × 7 | Located between the visceral and parietal pericardium; attached to the heart but not infiltrating the ventricular wall | N/R | Cystic LM |
| 2011 | Kanzaki et al. [41] | 1 | F | 20 | Palpitation, cough, and dyspnea | CT + MRI | 13 × 10 | Anterior mediastinum | Bilateral VATS | Cystic LM |
| 2012 | Choi et al. [27] | 1 | M | 29 | Dry cough | CT + MRI | 13.7 | N/R | N/R | Cystic LM |
| 2014 | Mizutani et al. [60] | 1 | M | 38 | Asymptomatic | CT + MRI | 7 | Left anterior mediastinum | VATS | Cystic LM |
| 2014 | Fokkema et al. [32] | 1 | M | 29 | Dysphagia | CT | N/R | Anterior and middle mediastinum | Partial sternotomy/Hemiclamshell thoracotomy | N/R |
| 2014 | Komatsu et al. [61] | 1 | M | 70 | Dyspnea on exertion | CT + MRI | 8 | Superior mediastinum | VATS | Cystic LM |
| 2014 | Lazopoulos et al. [42] | 1 | M | 30 | Asymptomatic | CT + MRI | 19 × 9.8 × 16.3 | Anterior mediastinum | Right VATS | Cystic LM |
| 2014 | Sadrizadeh et al. [23] | 1 | M | 80 | Cough and rest dyspnea | CT | N/R | Superior and middle mediastinum | Video-assisted mediastinoscopy | Cystic LM |
| 2014 | Yang et al. [62] | 1 | M | 46 | Asymptomatic | CT | 18 | Right anterior mediastinum | VATS | Cystic LM |
| 2015 | Golinelli et al. [28] | 1 | F | 43 | Right-side supraclavicular mass (present for ~1 year) with accelerated growth in recent months. Painless and soft-elastic consistency | US, Doppler US and MRI | 10 × 13 | Anterior and superior mediastinum | N/R | Cystic LM |
| 2015 | Lee et al. [63] | 1 | F | 66 | Asymptomatic | CT | 3.4 | Right upper anterior mediastinum | VATS | Cystic LM |
| 2015 | Suehisa et al. [13] | 1 | M | 35 | Asymptomatic | CT + MRI | 7.5 | Left anterior Mediastinum | left VATS | Cystic LM |
| 2016 | Swarnakar et al. [43] | 1 | M | 36 | One-year history of dyspnea on exertion; one-month history of low-grade fever | CT | N/R | Middle mediastinum | VATS | Cystic LM |
| 2017 | Rali et al. [29] | 1 | M | 23 | Chronic dyspnea and wheezing; 2-month history of progressive extremity weakness, paresthesia, and numbness | Ct + MRI | 17 × 16 × 12 | Middle and posterior mediastinum | N/R | Cystic LM |
| 2017 | Zhou et al. [14] | 1 | F | 69 | Chest pain for 1 month | CT | 10.5 × 7.5 | Posterior mediastinum | Right VATS | Cystic LM |
| 2018 | Malhotra et al. [30] | 1 | F | 21 | Initially: Pleuritic chest pain and night sweats. 8 months later: Pericardial tamponade and cardiac arrest | CT + lymphangiography | 9 × 5.3 | Anterior mediastinum | N/R | N/R |
| 2018 | Nasser et al. [31] | 1 | F | 32 | Subacute onset of fever, shortness of breath, and fatigue; presented with decompensated cardiac tamponade and hemodynamic instability | US + MRI | 13 × 11.8 | Middle mediastinum | N/R | N/R |
| 2019 | Dionisio et al. [35] | 1 | F | 36 | Presented to ER for unrelated weakness and vomiting. Denied chest pain, dyspnea, cough, or fever | CT +MRI | 20 × 13 × 14 | Medial and anterior mediastinum | N/R | Cystic LM |
| 2019 | Dirol et al. [64] | 1 | M | 46 | Asymptomatic | CT | 7.5 × 4.5 | Anterior and superior mediastinum | Right lateral thoracotomy | Cystic LM |
| 2019 | Salehi et al. [37] | 1 | F | 18 | Left-sided chest pain and worsening shortness of breath | CT + US | N/R | Left middle mediastinum | VATS to thoracotomy | Cystic LM |
| 2021 | Reddy et al. [36] | 1 | F | 27 | 4-day history of upper abdominal discomfort and breathing difficulty in the left lateral position; presented with impending cardiac tamponade | US | N/R | Middle mediastinum | Right VATS | Cystic LM |
| 2021 | Youssef et al. [65] | 1 | M | 44 | Incidental discovery on X-ray; however, patient retrospectively reported 6 months of cough, dyspnea on exertion, and shoulder pain | CT | 6.5 × 3.5 × 4 | Superior mediastinum | Right posterolateral thoracotomy | Cystic LM |
| 2022 | Li et al. [48] | 1 | F | 50 | Acute onset of left-sided pleuritic chest pain | CT + MRI | 13.2 | Mediastinum and entire left hemithorax | Emergency thoracotomy | Cystic LM |
| 2024 | Quaher et al. [8] | 1 | F | 35 | Persistent, dull, non-radiating central chest pain for two months | CT + MRI + PET-CT | 6.5 × 4.2 × 5 | Anterior and superior mediastinum | VATS | Cystic LM |
| 2025 | Akiba et al. [66] | 1 | F | 76 | Asymptomatic | CT + MRI | 7 | Anterior mediastinum | VATS | Cystic LM |
| 2025 | Kuzucuoğlu et al. [24] | 1 | M | 61 | Hoarseness | CT + PET-CT | 2 × 1.2 | Superior mediastinum | Mediastinoscopy + excision | Cystic LM |
| 2026 | Al Mahrizi et al. [33] | 1 | M | 24 | Chest pain, cough, intermittent fever, night sweats, decreased appetite | CT | 7.5 × 5.2 × 6.8 | Anterior mediastinum | Robotic-assisted thoracoscopic resection | N/R |
References
- Patel, N.J.; Sciubba, J. Oral lesions in young children. Pediatr. Clin. 2003, 50, 469–486. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, Z.; Xu, R.; Dai, P.; Chen, J.; Xiao, Z. A case report of pulmonary adenocarcinoma with thoracic duct lymphangioma and chylothorax. Front. Med. 2025, 12, 1712061. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salimath, S.; Harish, G.; Sathish, C.; Parvathy, A.; Lal, N.S.; Narayanasamy, S. A Rare Case of Pulmonary Lymphangioma; European Respiratory Society: Lausanne, Switzerland; Brussels, Belgium; Sheffield, UK, 2023. [Google Scholar]
- Charruau, L.; Parrens, M.; Jougon, J.; Montaudon, M.; Blachere, H.; Latrabe, V.; Laurent, F. Mediastinal lymphangioma in adults: CT and MR imaging features. Eur. Radiol. 2000, 10, 1310–1314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Correia, F.M.A.V.; Seabra, B.; Rego, A.; Duarte, R.; Miranda, J. Cystic lymphangioma of the mediastinum. J. Bras. Pneumol. 2008, 34, 982–984. [Google Scholar] [PubMed]
- Liu, X.; Cheng, C.; Chen, K.; Wu, Y.; Wu, Z. Recent progress in lymphangioma. Front. Pediatr. 2021, 9, 735832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coffing, B.; Gutmann, E.J. Lymphangioma of the posterior mediastinum in an adult: Diagnosis via cytopathologist-assisted fine-needle aspiration biopsy with cell block. Diagn. Cytopathol. 2005, 33, 412–415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qaher, F.M.; Husain, M.A.; Almansoor, M.F.; Abdulameer, F.H.; Al-Ammar, A.A. Adult Mediastinal Lymphangioma Presenting As Persistent Chest Pain: A Case Report. Cureus 2024, 16, e75771. [Google Scholar] [PubMed]
- Wunderbaldinger, P.; Paya, K.; Partik, B.; Turetschek, K.; Hörmann, M.; Horcher, E.; Bankier, A.A. CT and MR imaging of generalized cystic lymphangiomatosis in pediatric patients. Am. J. Roentgenol. 2000, 174, 827–832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, M.; Li, L.; Huo, M.; Sun, L.; Zhang, C.; Sun, Y.; Wang, R. Imaging and Clinical Features of Primary Thoracic Lymphangioma. Curr. Med. Imaging 2025, 21, e15734056346925. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jain, V.; Ahuja, J.; Strange, C.D.; Agrawal, R.; Palacio, D.M.; Truong, M.T.; Marom, E.M. Imaging of mediastinal masses. Radiol. Clin. 2025, 63, 609–631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bochor, N.; Gera, P. Exploring Lymphangioma: A Synthesis of the Literature and Clinical Perspectives. Lymphatics 2025, 3, 4. [Google Scholar] [CrossRef] [Scilit]
- Suehisa, H.; Ueno, T.; Sawada, S.; Yamashita, M.; Teramoto, N. A case of mediastinal cystic lymphangioma. Acta Med. Okayama 2015, 69, 361–363. [Google Scholar] [PubMed]
- Zhou, H.; Zhong, C.; Fu, Q.; Tang, S.; Luo, Q.; Yu, L.; Liu, L. Thoracoscopic resection of a huge mediastinal cystic lymphangioma. J. Thorac. Dis. 2017, 9, E887. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fujino, A.; Moriya, Y.; Morikawa, Y.; Hoshino, K.; Watanabe, T.; Shimojima, N.; Kitajima, M. A role of cytokines in OK-432 injection therapy for cystic lymphangioma: An approach to the mechanism. J. Pediatr. Surg. 2003, 38, 1806–1809. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baskın, D.; Tander, B.; Bankaoğlu, M. Local bleomycin injection in the treatment of lymphangioma. Eur. J. Pediatr. Surg. 2005, 15, 383–386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, V.; Kumar, P.; Pandey, A.; Gupta, D.; Shukla, R.; Sharma, S.; Gangopadhyay, A. Intralesional bleomycin in lymphangioma: An effective and safe non-operative modality of treatment. J. Cutan. Aesthetic Surg. 2012, 5, 133–136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nadolski, G.J.; Itkin, M. Feasibility of ultrasound-guided intranodal lymphangiogram for thoracic duct embolization. J. Vasc. Interv. Radiol. 2012, 23, 613–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Radzikowska, E.; Blasinska-Przerwa, K.; Skronska, P.; Wiatr, E.; Switaj, T.; Skoczylas, A. Lymphangioma in patients with pulmonary lymphangioleiomyomatosis-Results of sirolimus treatment. J. Cancer Sci. Ther. 2016, 8, 233–239. [Google Scholar] [CrossRef]
- Rawat, J.; Sinha, S.K.; Kanojia, R.P.; Wakhlu, A.; Kureel, S.; Tandon, R. Non surgical management of cystic lymphangioma. Indian J. Otolaryngol. Head. Neck Surg. 2006, 58, 355–357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, S.T.; Yong, S.J.; Lee, W.Y.; Kim, M.H.; Shin, K.C.; Kim, S.H.; Ahn, M.S.; Sung, K.J. A case of cavernous lymphangioma of the mediastinum in adult. Tuberc. Respir. Dis. 2002, 52, 640–644. [Google Scholar] [CrossRef] [Scilit]
- Park, J.G.; Aubry, M.-C.; Godfrey, J.A.; Midthun, D.E. Mediastinal lymphangioma: Mayo Clinic experience of 25 cases. In Proceedings of the Mayo Clinic Proceedings; Elsevier: Amsterdam, The Netherlands, 2006; pp. 1197–1203. [Google Scholar]
- Sadrizadeh, A.; Bagheri, R.; Afghani, R.; Molaei, M. Video-assisted mediastinoscopic resection of mediastinal cyst (lymphangioma). Asian Cardiovasc. Thorac. Ann. 2014, 22, 1119–1121. [Google Scholar] [PubMed]
- Kuzucuoğlu, M.; Albayrak, İ.; Uygun, A.Ç. Cystic Lymphangioma of the Mediastinum. Respir. Case Rep. 2025, 14, 24–26. [Google Scholar] [CrossRef] [Scilit]
- Yoo, S.Y.; Goo, J.M.; Im, J.-G. Mediastinal lymphangioma and chylothorax: Thoracic involvement of Gorham’s disease. Korean J. Radiol. 2002, 3, 130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Conte, G.; Aldrovandi, A.; Reverberi, C.; Cademartiri, F.; Ardissino, D. Mediastinal Cystic Lymphangioma. JACC 2011, 57, e207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, S.H.; Kim, L.; Lee, K.-H.; Cho, J.H.; Ryu, J.-S.; Kwak, S.M.; Nam, H.-S. Mediastinal lymphangioma treated using endobronchial ultrasound-guided transbronchial needle aspiration. Respiration 2012, 84, 518–521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Golinelli, G.; Toso, A.; Borello, G.; Aluffi, P.; Pia, F. Percutaneous sclerotherapy with OK-432 of a cervicomediastinal lymphangioma. Ann. Thorac. Surg. 2015, 100, 1879–1881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rali, P.; Gandhi, V.; Malik, K. Recurring giant mediastinal cystic lymphangioma. Am. J. Respir. Crit. Care Med. 2017, 196, e1–e3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malhotra, G.; Chick, J.F.B.; Srinivasa, R.N.; Hussain, J.S.; Gemmete, J.J.; Srinivasa, R.N. Mediastinal Lymphangioma Complicated by Chylopericardium, Tamponade, and Cardiac Arrest Treated with an Endolymphatic Stent Graft. J. Vasc. Interv. Radiol. 2018, 29, 1438–1439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nasser, M.; Ahmad, K.; Cottin, V. Mediastinal lymphangioma in an adult. J. Thorac. Cardiovasc. Surg. 2018, 155, e195–e197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fokkema, J.; Paul, M.; Vrouenraets, B. Mediastinal lymphangioma in an adult. Ann. R. Coll. Surg. Engl. 2014, 96, e24–e25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Mahrizi, A.D.; Mossolem, F.; Gregory, B.; Gill, H.; Kaplan, A.; Rejendran, J. Idiopathic anterior mediastinal lymphangioma in a young adult: A rare case report and review of management. Int. J. Surg. Case Rep. 2026, 10, 1097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahuja, J.; Strange, C.D.; Agrawal, R.; Erasmus, L.T.; Truong, M.T. Approach to imaging of mediastinal masses. Diagnostics 2023, 13, 3171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dionísio, A.C.; Gomes, R.; Cernadas, E.; Caballero, I.; Proença, J.; Lages, D.; Vicente, L. Giant cystic mediastinal lymphangioma. Eur. J. Case Rep. Intern. Med. 2019, 7, 001323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reddy, C.M.; Reddy, H.R. Spontaneous chylopericardium in an adult due to mediastinal cystic hygroma. Indian. J. Thorac. Cardiovasc. Surg. 2021, 37, 591–595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salehi, F.; Landis, M.; Inculet, R.; Wiseman, D. Case report of a rare cystic mediastinal lymphangioma mimicking recurrent pleural effusion. Case Rep. Radiol. 2019, 2019, 1301845. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, K.C.; Koh, W.-J.; Kwon, O.J.; Lee, B.-H.; Hwang, J.H.; Kang, E.H.; Suh, G.Y.; Chung, M.P.; Kim, H.; Han, J. Mediastinal lymphangioma in adults: Three case reports. Tuberc. Respir. Dis. 2003, 55, 303–310. [Google Scholar] [CrossRef] [Scilit]
- Parker, R.; Cadman, P.; Wathen, C. Lymphangioma: A rare cause of a mediastinal mass. Thorax 2004, 59, 820. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunt, I.; Eaton, D.; Dalal, P.; Burke, M.; Anikin, V. Minimally invasive excision of a mediastinal cystic lymphangioma. Can. J. Surg. 2009, 52, E201. [Google Scholar] [PubMed]
- Kanzaki, M.; Kikkawa, T.; Obara, T.; Onuki, T. Successful excision of an isolated mediastinal cystic lymphangioma with bilateral thoracoscopic surgery. Ann. Thorac. Cardiovasc. Surg. 2011, 17, 570–572. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lazopoulos, G.; Pavlopoulos, D.; Kambitakis, E.; Koutsopoulos, A.; Chalkiadakis, G. Huge cystic lymphangioma of the mediastinum successfully treated with thoracoscopic surgery. Ann. Thorac. Surg. 2014, 98, 2233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Swarnakar, R.N.; Hazarey, J.D.; Dhoble, C.; Vaghani, B.; Ainsley, A.S.; Khargie, J.F.; Likaj, L. A 36-year-old female with recurrent left sided pleural effusion: A rare case of mediastinal lymphangioma. Am. J. Case Rep. 2016, 17, 799. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brcic, L.; Roden, A.C. Histopathological features of giant mediastinal tumors—A literature review. Mediastinum 2023, 7, 37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bawazir, O.A.; Bawazir, R.; Bawazir, A.; Kausar, N.; Said, H. Efficacy and clinical outcomes of bleomycin in the treatment of lymphangiomas: A multicenter experience. Dermatol. Surg. 2021, 47, 948–952. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ardıçlı, B.; Karnak, İ.; Çiftçi, A.Ö.; Tanyel, F.C.; Şenocak, M.E. Sclerotherapy with bleomycin versus surgical excision for extracervical cystic lymphatic malformations in children. Surg. Today 2016, 46, 97–101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pires, A.M.K.S.; Reinehr, C.; Boff, F.; Nazar, F.L. Intralesional bleomycin sclerotherapy of lymphangioma: Partial response to treatment. Dermatol. Surg. 2015, 41, 175–177. [Google Scholar] [PubMed]
- Li, O.; Sallam, Y.T.; Kwan, K.F.; Qiabi, M.; Paul, N.S.; Abdelrazek, M.A. Resection of a large hemorrhagic mediastinal lymphangioma in an adult patient: A radiologic-pathologic correlation. Radiol. Cardiothorac. Imaging 2022, 4, e210043. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Savu, C.; Petreanu, C.; Melinte, A.; Posea, R.; Balescu, I.; Iliescu, L.; Diaconu, C.; Galie, N.; Bacalbasa, N. Persistent left superior vena cava–accidental finding. In Vivo 2020, 34, 935–941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oshikiri, T.; Morikawa, T.; Jinushi, E.; Kawakami, Y.; Katoh, H. Five cases of lymphangioma of the mediastinum in adult. Ann. Thorac. Cardiovasc. Surg. 2001, 7, 103–105. [Google Scholar] [PubMed]
- Shetty, R.C.; Aggarwal, B.K.; Kamath, S.G.; Prabhu, P.; Aggarwal, M.; Rao, L. Giant cystic lymphangioma of the middle mediastinum. Indian J. Chest Dis. Allied Sci. 2003, 45, 125–130. [Google Scholar] [PubMed]
- Zahirifard, S.; Bakhshayesh-Karam, M.; Kaynama, K.; Omid Tahbaz, M.; Mir-Afshariyeh, S.A.; Abbasi Dezfouli, A. Case Presentation and Imaging Review of an Adult Mediastinal Cavernous Lymphangioma; Case Report. Tanaffos 2003, 2, 71–76. [Google Scholar]
- Daya, S.K.; Gowda, R.M.; Gowda, M.R.; Khan, I.A. Thoracic cystic lymphangioma (cystic hygroma): A chest pain syndrome: A case report. Angiology 2004, 55, 561–564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pop, D.; Benizri, E.; Venissac, N.; Leo, F.; Padovani, B.; Mouroux, J. Mediastinal cystic lymphangioma: Is resection always necessary? Thorac. Cardiovasc. Surg. 2005, 53, 243–244. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Misthos, P.; Sepsas, E.; Kokotsakis, I.; Skottis, I. Asymptomatic solitary mediastinal cystic lymphangioma: A rare entity. Asian Cardiovasc. Thorac. Ann. 2006, 14, 476–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saleiro, S.; Magalhães, A.; Souto, M.C.; Hespanhol, V.; Marques, J.A.; Carneiro, F.; Monteiro, H. Mediastinal cystic lymphangioma. Rev. Port. Pneumol. 2006, 12, 731–735. [Google Scholar] [CrossRef] [Scilit]
- Teramoto, K.; Suzumura, Y. Mediastinal cavernous lymphangioma in an adult. Gen. Thorac. Cardiovasc. Surg. 2008, 56, 88–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Melo, I.A.; Camargo, J.d.J.P.; de Moraes Gomes, B.; Cabrera, G.A.; Machuca, T.N. Linfangioma cístico isolado do mediastino. Rev. Port. Pneumol. 2009, 15, 697–703. [Google Scholar] [CrossRef] [Scilit]
- Yi-feng, S.; Yun-qing, M.; Jing, F.; Xi-sheng, W.; Yong-xin, Z.; Qiang, J. Diagnosis and Surgical Management of Mediastinal Cystic Lymphangioma. Cancer Res. Prev. Treat. 2009, 36, 317–318. [Google Scholar] [CrossRef]
- Mizutani, E.; Morita, R.; Kitamura, S. Mediastinal cystic lymphangioma; report of a case. Kyobu Geka Jpn. J. Thorac. Surg. 2012, 65, 510–512. [Google Scholar]
- Komatsu, T.; Takahashi, Y. Mediastinal cystic lymphangioma in a patient with situs inversus totalis. Case Rep. Surg. 2014, 2014, 781874. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, B.; Jiang, C.; Zhang, B.; Ren, Q.; Tang, T.; Xu, S.; Xu, H.; Yao, H.; Han, Y.; Liu, S. Giant primary cystic mediastinal lymphangioma: A case report. Oncol. Lett. 2014, 8, 1246–1248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, J.M.; Lee, S.H.; Park, Y.; Kim, C.Y.; Goag, E.K.; Lee, E.H.; Park, J.E.; Lee, C.Y.; Kim, S.K. A late onset solitary mediastinal cystic lymphangioma in a 66-year-old woman who underwent kidney transplantation. J. Yeungnam Med. Sci. 2015, 32, 155–158. [Google Scholar] [CrossRef] [Scilit]
- Dirol, H.; Deniz, F.; Çilli, A.; Dertsiz, L. Adult Mediastinal Cystic Hygroma: A Case Report. Respir. Case Rep. 2019, 8, 115. [Google Scholar] [CrossRef] [Scilit]
- Youssef, S.; Iftikhar, S.; Haris, M.; Sundararajan, S.; Abid, Q. Incidental solitary cystic mediastinal lymphangioma with mass effect complications. Br. J. Hosp. Med. 2021, 82, 1–3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akiba, Y.; Iwata, Y.; Ito, T.; Okasaka, T. Mediastinal Lymphangioma: Report of a Case. Kyobu Geka Jpn. J. Thorac. Surg. 2025, 78, 1139–1142. [Google Scholar]



| Clinical Presentation/Symptom Category | No. of Patients (n) | Percentage (%) |
|---|---|---|
| Asymptomatic (Incidental Discovery) | 28 | 41.8% |
| Symptomatic | 39 | 58.2% |
| 1. Respiratory and Cardiovascular Compression | ||
| — Dyspnea on Exertion | 13 | 19.4% |
| — Chronic Dry Cough | 8 | 11.9% |
| — Palpitations/Arrhythmias | 3 | 4.5% |
| 2. Thoracic Pain and Discomfort | ||
| — Vague Chest Discomfort | 9 | 13.4% |
| — Acute/Pleuritic Chest Pain | 6 | 9.0% |
| 3. Severe Mass Effect and Emergencies | ||
| — Cardiac Compression | 2 | 3.0% |
| — Superior Vena Cava Syndrome | 2 | 3.0% |
| Approach Category | Specific Surgical Method | Percentage (n/N) |
|---|---|---|
| Minimally Invasive | VATS/RATS (Total) | 48.0% ) |
| Completed minimally invasive (VATS/RATS) | ) | |
| Converted to open thoracotomy | ) | |
| Open Approach | Thoracotomy/Sternotomy (Total) | ) |
| Thoracotomy | ) | |
| Median sternotomy | ) |
| Year/Reference | Specific Local Procedure | Tumor Size |
|---|---|---|
| 2002/Kim et al. [21] | Mediastinoscopy + partial sternotomy (biopsy) | Not reported |
| 2006/Park et al. [22] | Diagnostic mediastinoscopy () | Not reported |
| 2014/Sadrizadeh et al. [23] | Video-assisted mediastinoscopy | Not reported |
| 2025/Kuzucuoglu et al. [24] | Mediastinoscopy + excision | 2.1 × 1.2 cm |
| Year/Reference | Therapeutic Strategy and Clinical Rationale |
|---|---|
| 2002 Yoo et al. [25] | Diagnostic fluid aspiration and an incisional biopsy, followed by external radiation therapy. Resection was not performed due to the systemic nature of his underlying disease (Gorham’s Disease). |
| 2005 Coffing et al. [7] | FNA (fine-needle aspiration) of an asymptomatic 5.2 cm posterior mediastinal LM, in a patient with aggressive ovarian carcinoma |
| 2011 Conte et al. [26] | Monitoring for an asymptomatic LM diagnosed 20 years prior |
| 2012 Choi et al. [27] | EBUS aspiration of a large asymptomatic LM |
| 2015 Golinelli et al. [28] | US-guided percutaneous sclerotherapy using OK-432 (Picibanil) for a 10 × 13 cm LM t near critical neurovascular bundles and vital structures |
| 2017 Rali et al. [29] | Decompressive hemilaminectomies (C4–T5) to relieve spinal cord compression caused by a massive posterior mediastinal LM in a high-risk candidate. |
| 2018 Malhotra et al. [30] | Emergency pericardial drainage and an endolymphatic stent graft (Viabahn endoprosthesis) across the thoracic duct in a LM previously treated with mTOR (Mammalian Target of Rapamycin) inhibitors. |
| 2018 Nasser et al. [31] | Creation of a pericardial window followed by long-term mTOR inhibitor therapy (sirolimus) for an infiltrative mass encasing the aortopulmonary window. |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Tivadar, M.-B.; Sabha, A.-A.; Grigorie, V.; Bobocea, R.; Bobocea, A.-C. Mediastinal Lymphangioma of the Adult: Case Report and Literature Review. Clin. Pract. 2026, 16, 144. https://doi.org/10.3390/clinpract16080144
Tivadar M-B, Sabha A-A, Grigorie V, Bobocea R, Bobocea A-C. Mediastinal Lymphangioma of the Adult: Case Report and Literature Review. Clinics and Practice. 2026; 16(8):144. https://doi.org/10.3390/clinpract16080144
Chicago/Turabian StyleTivadar, Mihaela-Beatrice, Amir-Andrei Sabha, Vasile Grigorie, Raluca Bobocea, and Andrei-Cristian Bobocea. 2026. "Mediastinal Lymphangioma of the Adult: Case Report and Literature Review" Clinics and Practice 16, no. 8: 144. https://doi.org/10.3390/clinpract16080144
APA StyleTivadar, M.-B., Sabha, A.-A., Grigorie, V., Bobocea, R., & Bobocea, A.-C. (2026). Mediastinal Lymphangioma of the Adult: Case Report and Literature Review. Clinics and Practice, 16(8), 144. https://doi.org/10.3390/clinpract16080144