Case Report

Coexisting Onychomycosis and Subungual Malignant Melanoma: A Case Series Illustrating Diagnostic Complexity in Podiatric Practice

1
Department of Orthopaedic Surgery, Hospital for Special Surgery Main Hospital, New York, NY 10021, USA
2
Department of Surgery, NYU Langone Health, New York, NY 10016, USA
3
Department of Podiatry, Maimonides Midwood Community Hospital, New York, NY 11230, USA
*
Author to whom correspondence should be addressed.
J. Am. Podiatr. Med. Assoc. 2026, 116(4), 55; https://doi.org/10.3390/japma116040055
Submission received: 5 March 2026 / Revised: 31 July 2026 / Accepted: 3 August 2026 / Published: 19 August 2026

Abstract

Background: Subungual malignant melanoma (SMM) is an uncommon but potentially life-threatening neoplasm that frequently mimics benign nail disorders, particularly onychomycosis. Although misdiagnosis of SMM as fungal infection is well documented, laboratory-confirmed coexistence of onychomycosis and melanoma within the same nail unit is exceedingly rare and remains insufficiently characterized in the literature. Methods: A two-patient case series is presented in which both individuals underwent comprehensive clinical evaluation, nail unit biopsy, histopathologic examination with special staining, and molecular and/or mycologic testing. Longitudinal follow-up was obtained to evaluate clinical course and outcomes. Results: Both patients presented with chronic hallux nail dystrophy and laboratory-confirmed onychomycosis. In each case, fungal infection was confirmed, however, persistent symptoms prompted subsequent biopsies, that revealed malignant melanoma. In Case 1, a 71-year-old man with Candida parapsilosis onychomycosis underwent an initial nail unit biopsy demonstrating at least melanoma in situ with ulceration. Repeat biopsy confirmed invasive melanoma with an approximate Breslow thickness of 1.0 mm, while final pathology following partial hallux amputation revealed residual ulcerated melanoma with a Breslow thickness of 2.1 mm, negative margins, and negative sentinel lymph nodes, consistent with Stage IIB disease. In Case 2, an 88-year-old woman with dermatophytic onychomycosis consistent with Trichophyton species had an initial fragmented biopsy demonstrating invasive subungual melanoma with an estimated Breslow thickness of 0.6 mm. Final pathology following distal hallux amputation confirmed residual acral melanoma with a Breslow thickness of 0.6 mm, no ulceration, a mitotic rate of less than 1/mm2, and negative margins, consistent with pT1a disease. Factors contributing to delayed melanoma recognition differed between cases: prior trauma, delayed intervention, and chronic ulceration complicated Case 1, whereas treatment for presumed onychomycosis without improvement delayed suspicion in Case 2. Conclusions: These findings demonstrate that positive mycologic results do not exclude concurrent melanoma and underscore the potential for diagnostic anchoring bias, supporting early biopsy consideration in refractory or atypical nail dystrophy.

1. Introduction

Coexisting onychomycosis and subungual malignant melanoma (SMM) within the same nail are a rare but clinically significant diagnostic challenge. SMM is a rare but potentially fatal neoplasm arising from the nail unit apparatus, accounting for approximately 0.7–3.5% of all cutaneous melanomas in Caucasian populations, and up to 75% in non-Caucasian populations [1,2,3]. Subungual melanoma is frequently misdiagnosed as onychomycosis, chronic trauma, or subungual hematoma, significantly delaying treatment and reducing chances for early intervention [4]. The broader differential diagnosis includes bacterial infection, particularly Pseudomonas, drug-induced pigmentation, vascular lesions, lichen planus, benign melanocytic lesions such as lentigo or nevus, and malignant conditions such as Bowen disease. The mean time from initial symptom to correct diagnosis of subungual melanoma is approximately 2 years, contributing to the poor 10-year survival rate of only 43% in some series [5].
Diagnostic difficulty arises because both onychomycosis and melanoma may present with nail discoloration, dystrophy, and subungual debris [2]. Onychomycosis itself accounts for approximately 50% of all nail disorders, making it the most common cause of abnormal nails in podiatric practice. Prevalence increases with age, affecting at least 20% of individuals over 60 years and up to 50% of those over ≥70 years [6]. In high-risk populations such as patients with diabetes, clinical suspicion of onychomycosis does not reliably correlate with laboratory confirmation; only approximately 40% of clinically suspected cases are confirmed by mycological testing [7].
These data underscore an important clinical principle: although fungal infection is common, a substantial proportion of dystrophic nails are not fungal in origin, and even laboratory-confirmed onychomycosis does not exclude the possibility of concurrent malignancy. Therefore, chronic, atypical, or treatment-refractory nail lesions, particularly those associated with ulceration, persistent dystrophy, or pigmentary change, warrant histopathologic evaluation to exclude other diagnoses, including a nail unit melanoma.
In light of these considerations, two patients are reported with biopsy-proven SMM occurring concurrently with laboratory-confirmed fungal infection of the same nail unit, Candida parapsilosis in one case and dermatophytic onychomycosis with a Trichophyton morphologic pattern in the other, are presented. These cases warrant documentation because the current literature is largely limited to isolated reports, and additional cases may help identify an underrecognized clinical pattern.

2. Patients and Methods

This retrospective two-patient case series included patients treated at a private podiatric practice in Brooklyn, New York between 2019 and the present. Cases were identified through review of clinical and pathology records and included patients with laboratory-confirmed fungal infection and histopathologically confirmed melanoma involving the same hallux nail unit. Both cases involved lesions affecting the hallux nail unit and were evaluated through clinical examination, histopathologic analysis, and appropriate diagnostic staining. The cases were documented and reported in accordance with the CARE guidelines.
Demographic and clinical data extracted from the medical records included age, sex, relevant comorbidities, prior treatments, clinical presentation, pathologic findings, surgical management, and follow-up outcomes. Comorbidities included hypertension, hyperlipidemia, diabetes mellitus, coronary artery disease, Parkinson disease, vertigo, smoking history, peripheral artery disease, and chronic kidney disease. Intraoperative and postoperative data were also reviewed to assess clinical outcomes.
Histopathologic evaluation included hematoxylin and eosin (H&E) staining; fungal stains, including periodic acid–Schiff (PAS), Gomori methenamine silver (GMS), and/or periodic acid–Schiff with Alcian blue (PAS–AB); and melanocytic immunohistochemical markers, including Melan-A, melanoma antigen recognized by T cells 1 (MART-1), preferentially expressed antigen in melanoma (PRAME), and the Ki-67 proliferation marker, as indicated. Case 1 additionally underwent real-time polymerase chain reaction (PCR) testing for fungal organisms, outside pathology review, and definitive pathologic evaluation following partial hallux amputation. Case 2 underwent dermatopathologic evaluation of the nail unit and final pathologic assessment following distal hallux amputation. Longitudinal outcomes were obtained from podiatric, dermatologic, oncologic, and pathology records.

3. Results

3.1. Case Presentation 1

A 71-year-old male with a medical history significant for hypertension and hyperlipidemia presented with a two-year history of left hallux nail trauma resulting in nail plate splitting. One year after the initial injury, complete nail removal had been recommended at an outside practice; however, the patient declined intervention. Approximately one month prior to presentation to our clinic, he developed a persistent ulcer along the left hallux nail margin that failed to improve with topical bacitracin. No prior fungal cultures or diagnostic nail testing had been performed.
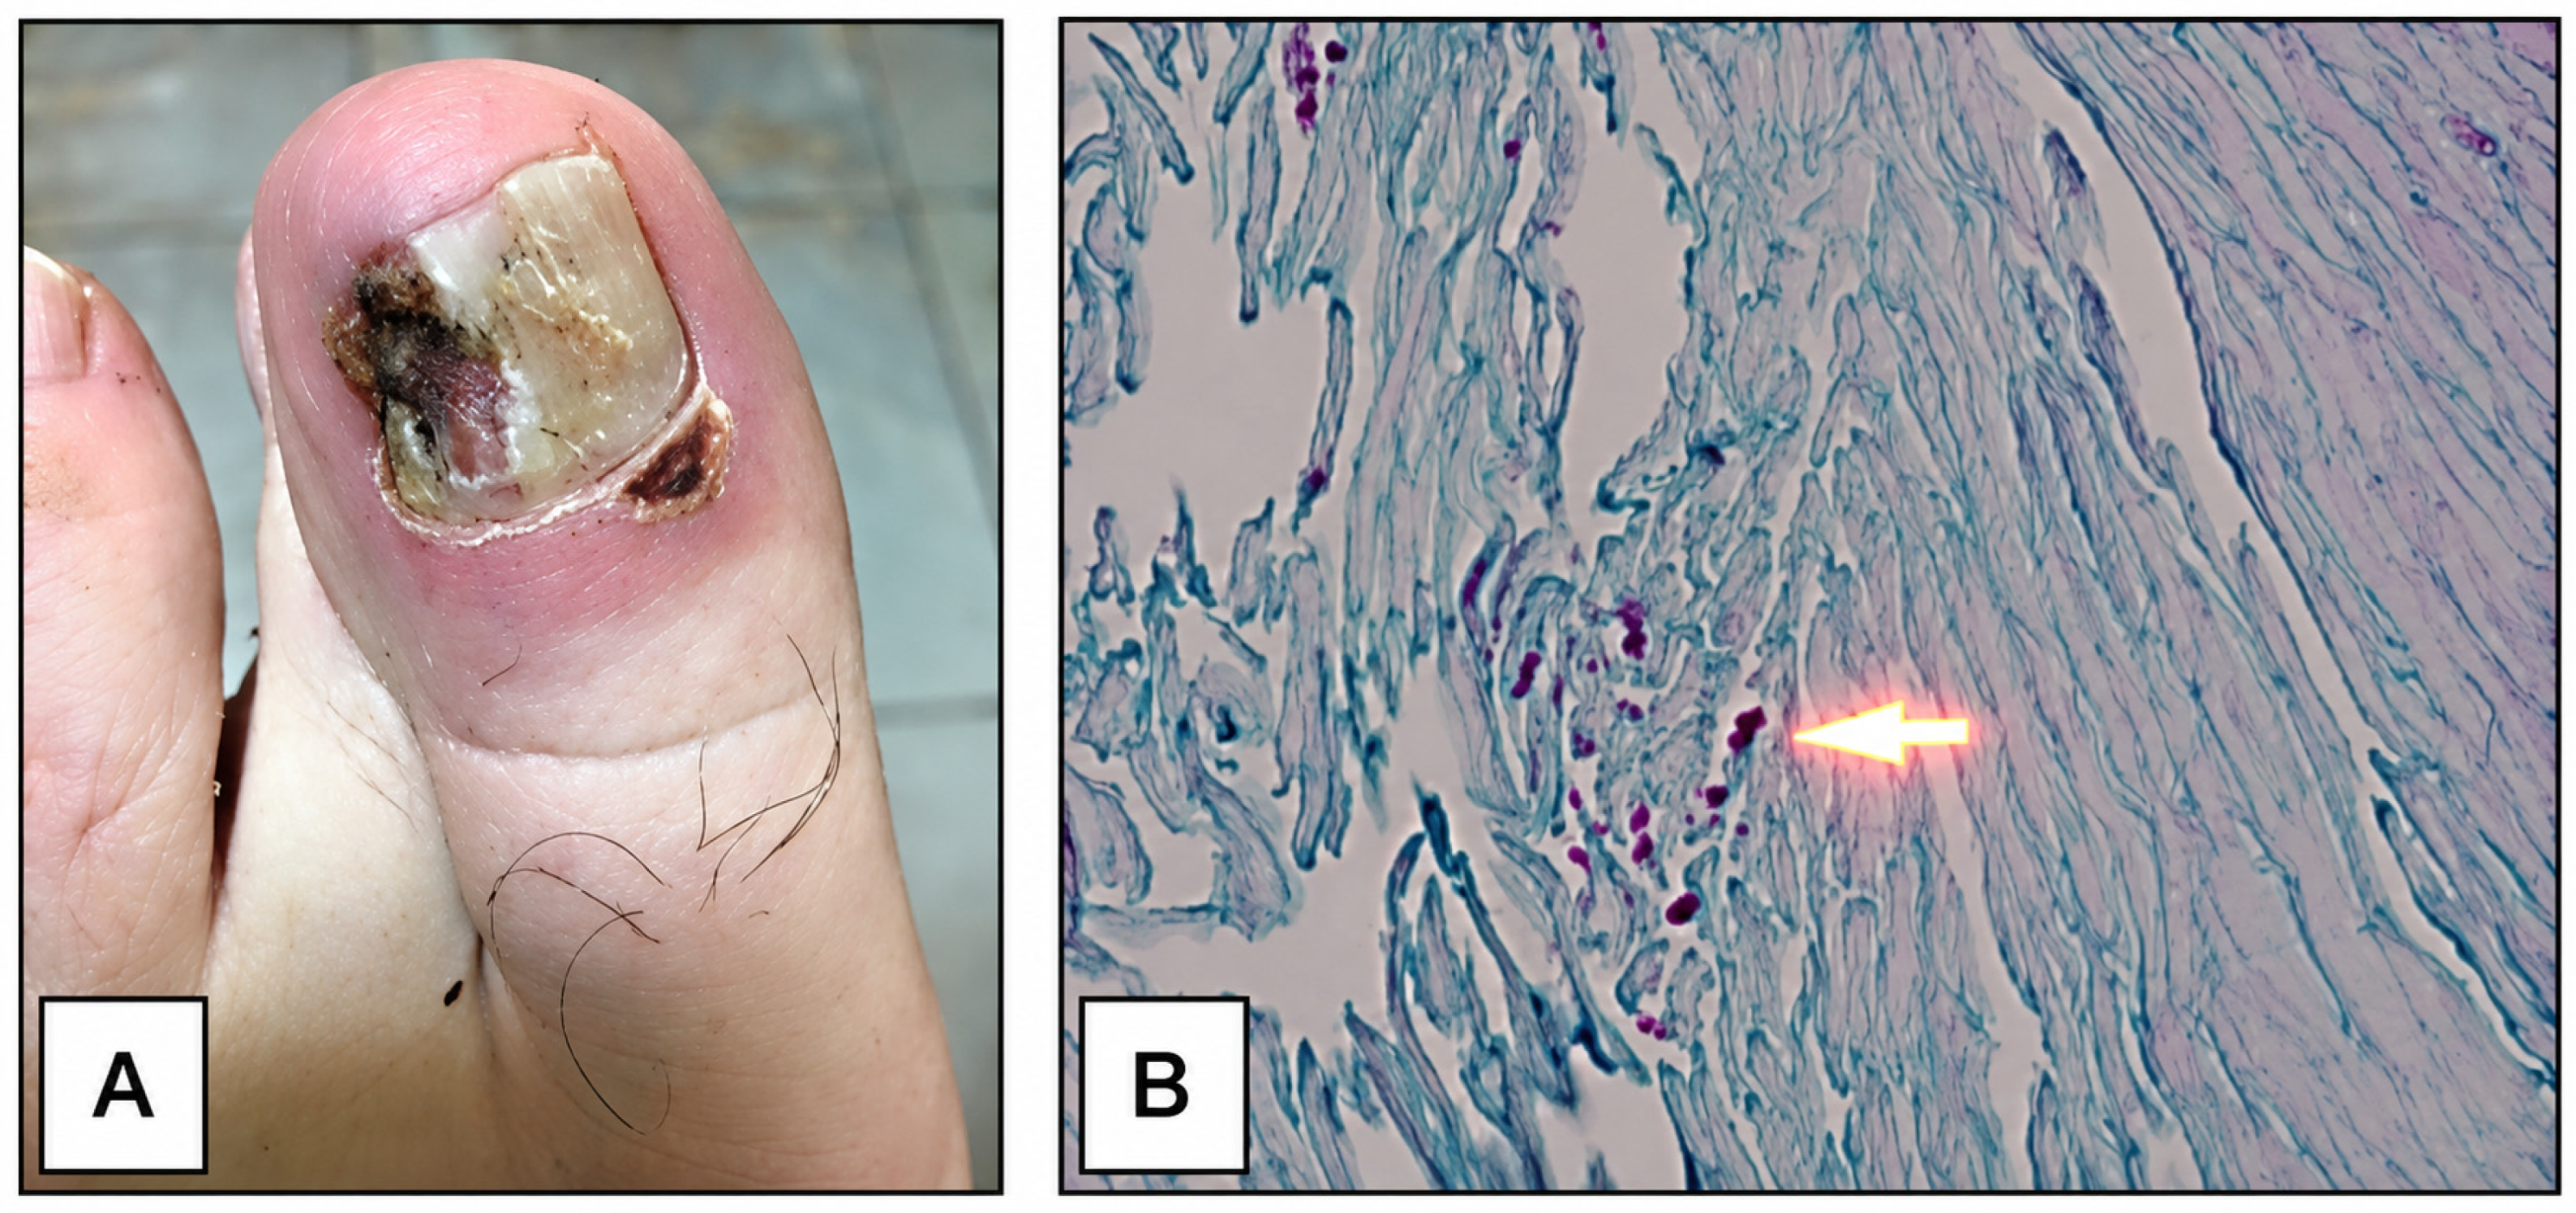
Physical examination revealed intact integument bilaterally without evidence of varicosities, additional ulcerations, edema, or systemic signs of infection. Evaluation of the left hallux demonstrated a dystrophic nail plate characterized by yellow discoloration, thickening, and brittleness, with tenderness to palpation. A well-demarcated granular ulcer was present along the lateral aspect of the nail plate, measuring 0.7 × 0.5 × 0.1 cm. Serous exudate was noted in the absence of purulence or malodor. Periungual erythema and cellulitis were observed at the proximal and lateral nail folds Distolateral black discoloration appeared clinically consistent with superficial debris rather than necrotic tissue (Figure 1A). Histopathologic evaluation with periodic acid–Schiff staining confirmed fungal elements, while Fontana–Masson staining was negative for melanin-producing organisms (Figure 1B).

3.1.1. Pathologic Evaluation

At the initial evaluation, nail plate clippings from the dystrophic left hallux nail were obtained and submitted for histopathologic and molecular evaluation. Histopathologic examination of the nail plate clipping specimen demonstrated onychomycosis with a subungual growth pattern, most consistent with yeast forms. PAS and GMS stains demonstrated fungal elements, while Fontana-Masson stain was negative (Figure 1). Histologic features of persistent microtrauma were also present. Gross examination revealed multiple fragments of keratogenous tissue measuring 0.9 × 0.2 × 0.1 cm in aggregate, submitted in toto for histology and PCR studies. Real-time PCR onychodystrophy screening detected Candida genus, specifically Candida parapsilosis. Candida albicans, Candida guilliermondii, Candida tropicalis, dermatophytic fungi, and saprophytic fungi were not detected. The findings were interpreted as consistent with Candida onychomycosis in the appropriate clinical context, though contamination could not be entirely excluded.

3.1.2. Clinical Course and Surgical Management

At four-week follow-up, the ulceration remained unresolved despite conservative management. Due to persistent ulceration and concern for an underlying malignancy, total nail avulsion and a separate 2 mm punch biopsy of the exposed nail bed were performed.
After informed consent was obtained, the procedure was performed under local anesthesia using 3 mL of 1% plain lidocaine. The nail plate was removed in toto using standard instrumentation. A 2 mm punch biopsy was subsequently obtained from the exposed nail bed for histopathologic analysis. Hemostasis was achieved with topical silver nitrate application. The surgical site was dressed with medical-grade honey, non-adherent petrolatum gauze, and a sterile compressive dressing. The patient received both verbal and written postoperative care instructions and was scheduled for follow-up evaluation in 14 days.

3.1.3. Multidisciplinary Evaluation and Intervention

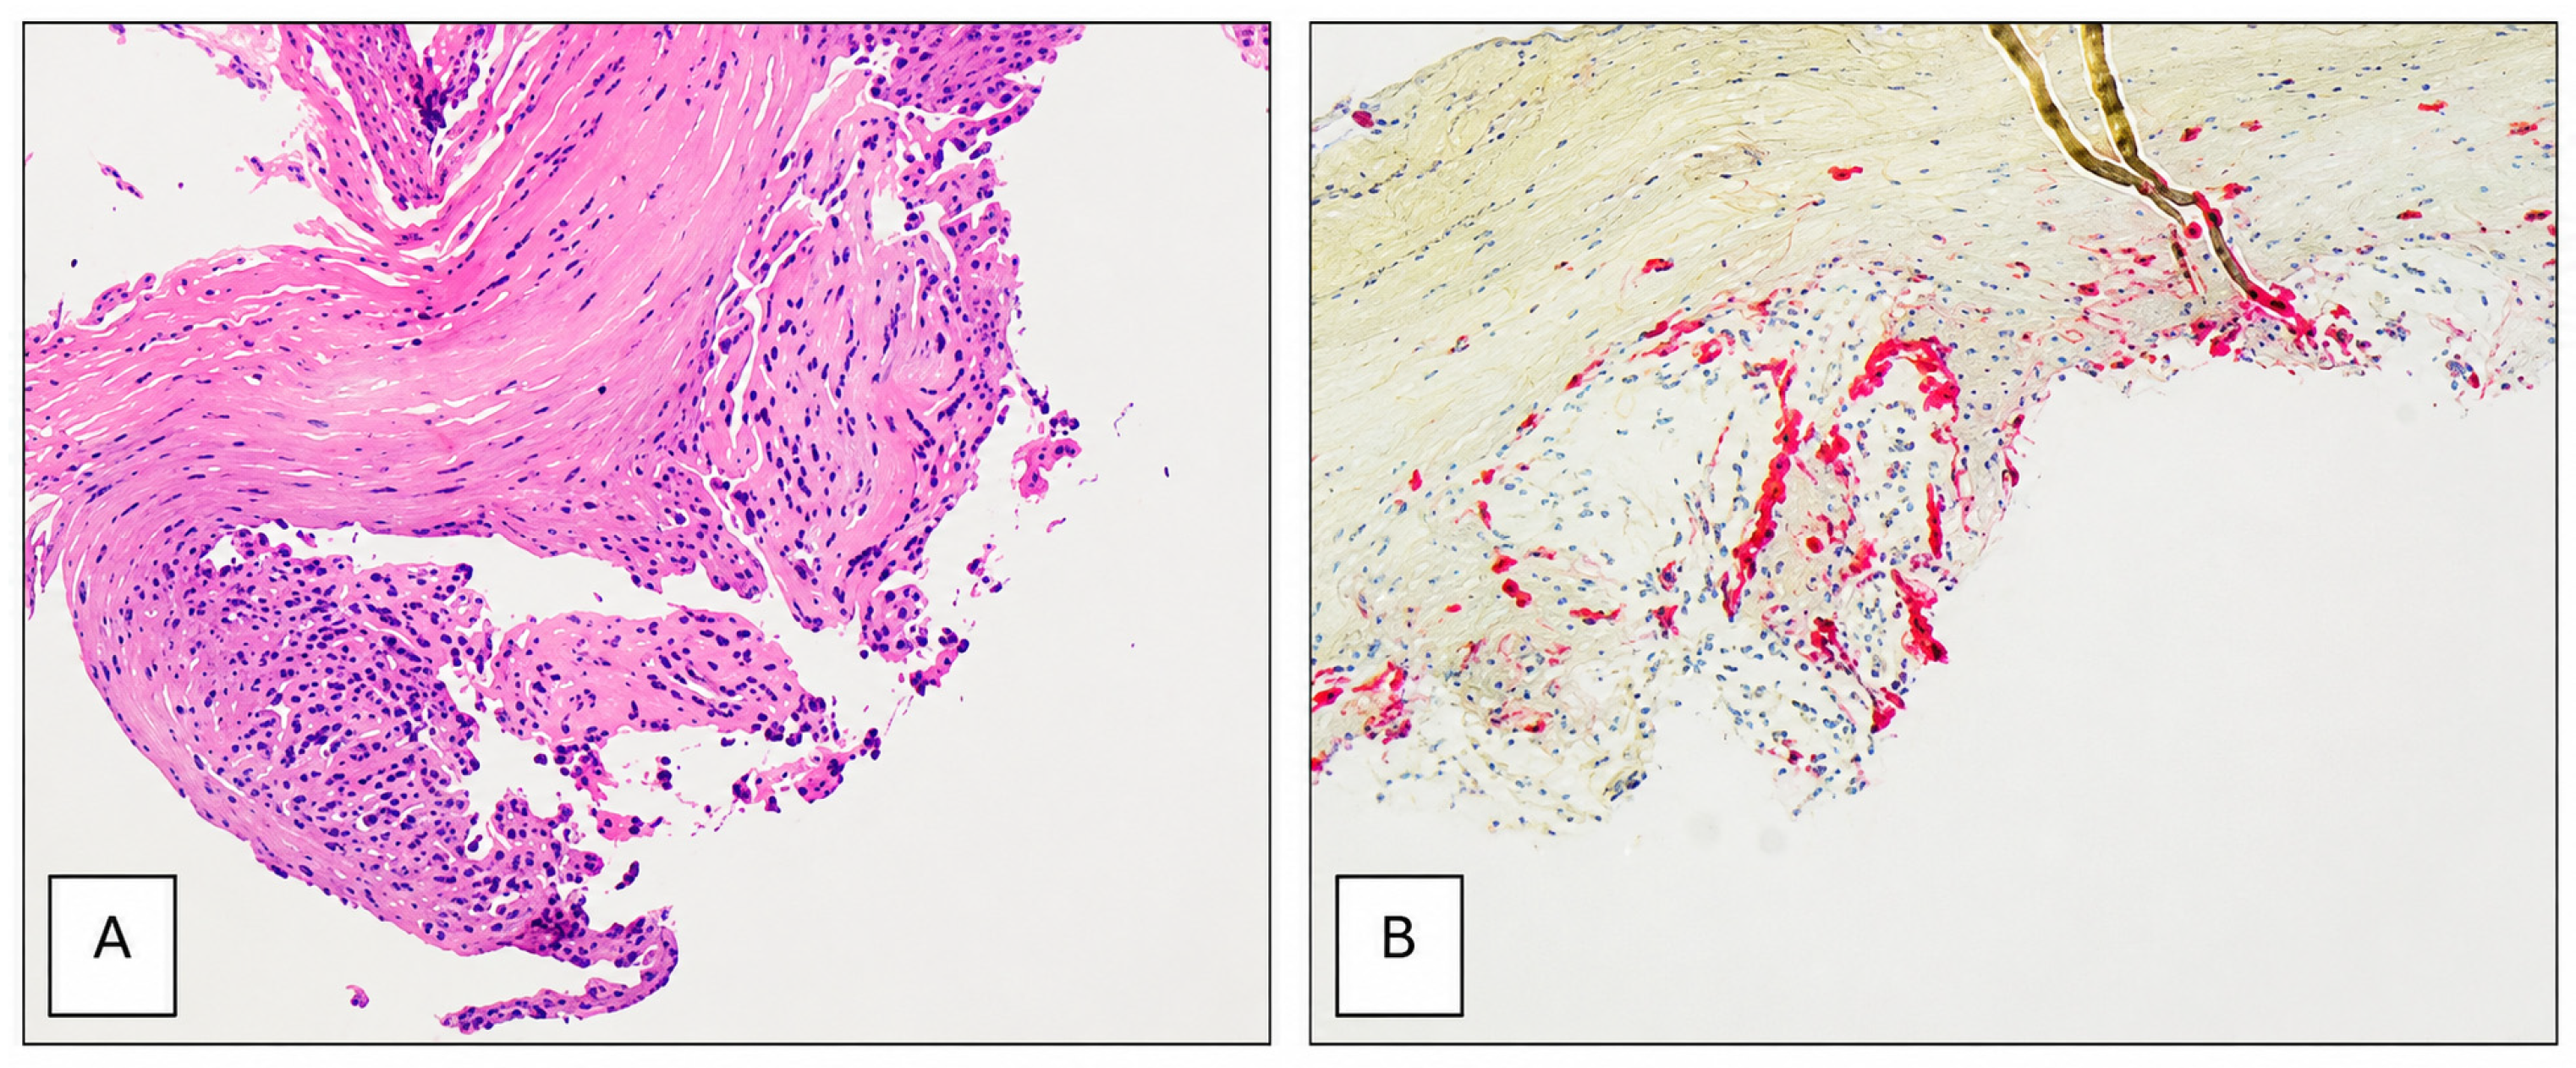
Histopathologic examination of the excised nail unit matrix, bed, and plate demonstrated at least malignant melanoma in situ with ulceration. Melan-A immunostaining was positive, supporting the diagnosis (Figure 2). Although no definitive invasive component was identified, the specimen contained minimal underlying dermis, precluding complete exclusion of invasion. Re-excision was recommended.
Gross examination revealed soft tissue measuring 2.2 × 1.7 × 0.8 cm and a separate keratogenous nail specimen measuring 2.5 × 1.6 × 0.4 cm, submitted in toto. Microscopically, there was proliferation of intraepidermal melanocytes with confluence along the dermal-epidermal junction. Enlarged melanocytes were present at all levels of the epidermis, and solitary melanocytes outnumbered nests in several high-power fields. The underlying dermis appeared uninvolved in examined sections.
The case was discussed with cutaneous surgical oncology. The initial pathology report incorrectly documented the lesion as involving the right hallux; this was subsequently clarified and corrected to the left hallux. Because the initial specimen contained insufficient underlying dermis to exclude invasion, a repeat biopsy of the left hallux nail bed and surrounding tissue was performed at an outside institution for definitive staging. Histopathologic examination confirmed invasive melanoma with an approximate Breslow thickness of 1.0 mm, ulceration, and a mitotic rate of less than 1/mm2. Sentinel lymph node biopsy and partial hallux amputation were subsequently recommended as definitive surgical management.

3.1.4. Intraoperative Course

Preoperative lymphoscintigraphy identified drainage to two left inguinal lymph nodes. The patient underwent left great toe partial amputation and concurrent left inguinal sentinel lymph node biopsy using dual tracers. He was brought to the operating room and placed supine. Following induction of anesthesia and sterile preparation of the left lower extremity and inguinal region, a left inguinal sentinel lymph node biopsy was performed. Using preoperative lymphoscintigraphy guidance, intraoperative gamma probe localization and blue dye, the sentinel lymph nodes were identified and excised in toto. Hemostasis was achieved, and the incision was closed in layered fashion.
Attention was then directed to the left great toe. A partial hallux amputation was performed at the predetermined level, just proximal to the interphalangeal joint, to achieve appropriate oncologic margins of at least 1 cm. The specimen was removed in toto and sent for permanent histopathologic evaluation. The wound was irrigated, hemostasis secured, and the surgical site closed in layers. A sterile dressing was applied, and the patient was transferred to recovery in stable condition.

3.1.5. Postoperative Course

Final pathology following a partial left hallux amputation revealed residual invasive melanoma with a Breslow thickness of 2.1 mm, ulceration, and a mitotic rate of 1/mm2. Surgical margins were negative, with the closest margins measuring 11 mm from the invasive component and 8 mm from the melanoma in situ component. Both left inguinal sentinel lymph nodes were negative for metastatic melanoma (0/2). Based on the definitive surgical pathology, the disease was classified as Stage IIB. The postoperative course was complicated by mild cellulitis at the amputation site, which was successfully treated with oral antibiotics. The patient declined referral to medical oncology to discuss adjuvant therapy. At 6 years and 10 months following treatment, he remains alive without evidence of local, regional, or distant disease.

3.2. Case Presentation 2

An 88-year-old woman presented with a greater than one-year history of splitting and progressive discoloration of the right hallux nail. She had received approximately two months of treatment for presumed onychomycosis without clinical improvement, and no prior nail biopsy had been performed.
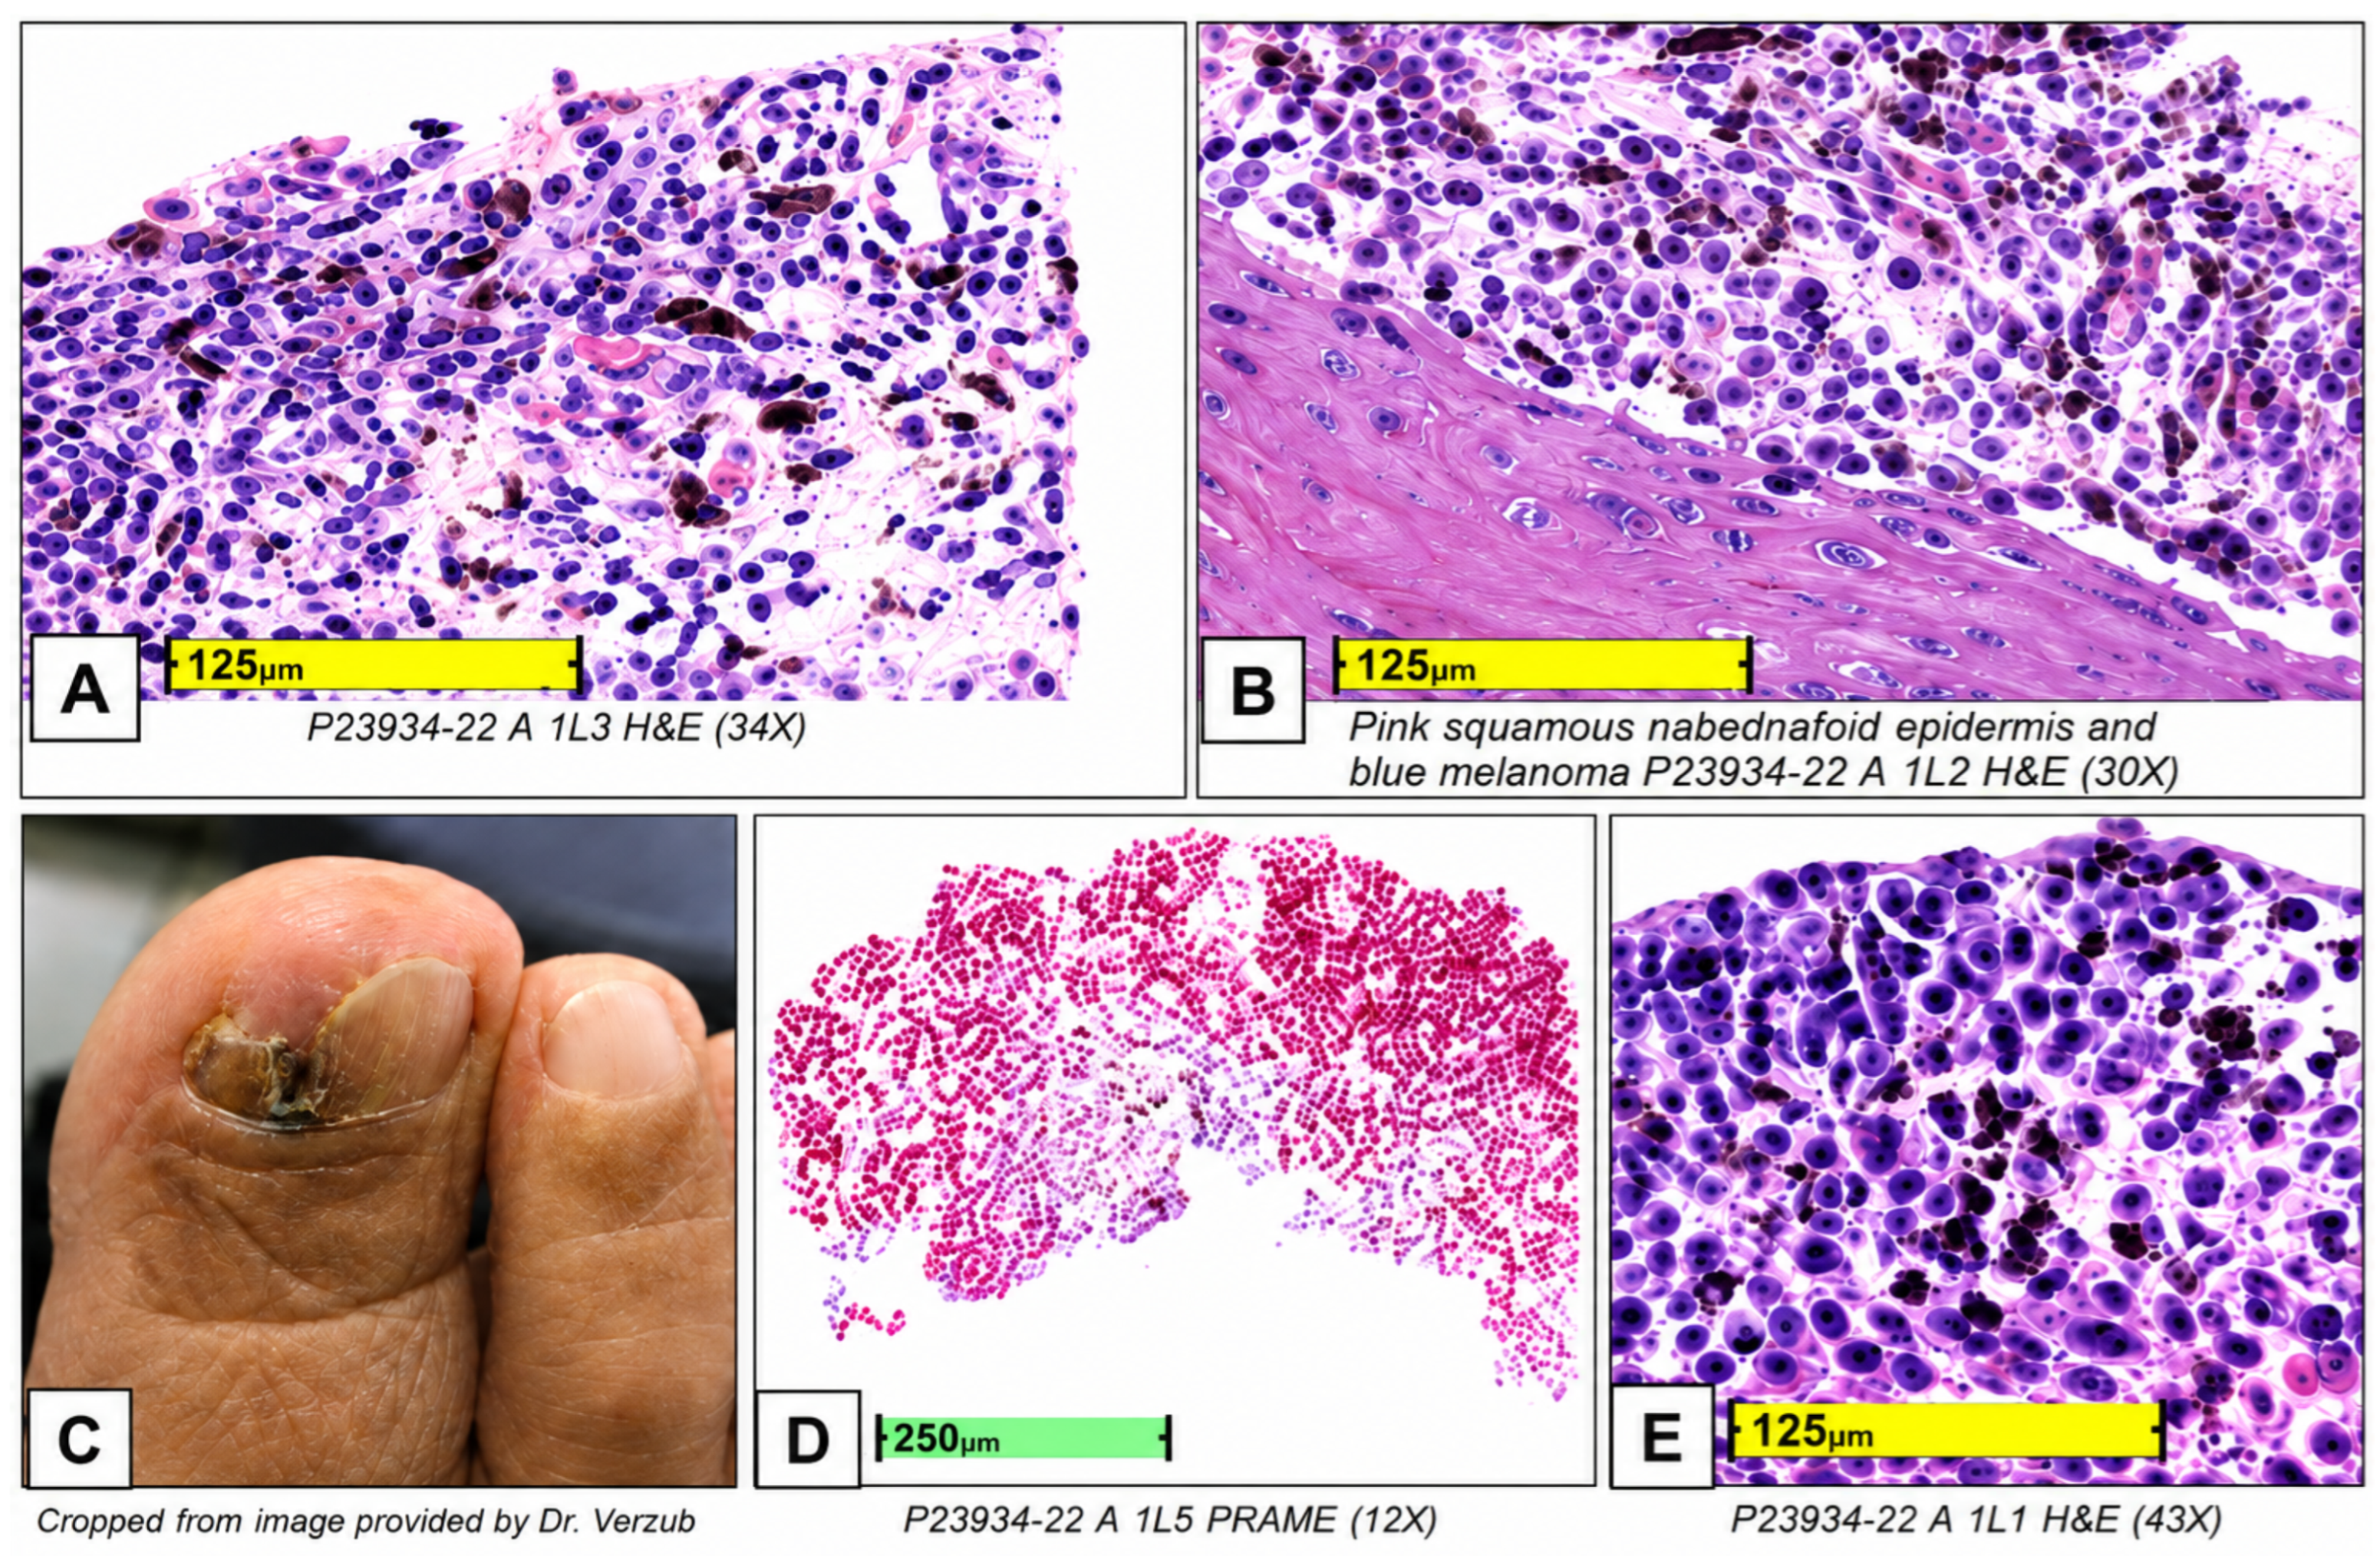
Focused examination demonstrated a split, dystrophic, and discolored nail plate with a subungual hematoma measuring approximately 0.5 × 0.3 cm and extending proximally toward the cuticle. Distal hyperpigmentation was also present (Figure 3D). Given the lesion’s chronicity, lack of response to antifungal therapy, and persistent pigmentary changes, further diagnostic evaluation was pursued to exclude an underlying neoplastic process.

3.2.1. Diagnostic and Surgical Intervention

Due to the persistent nature of the lesion and lack of response to prior antifungal therapy, a biopsy was indicated to establish a definitive diagnosis and exclude malignancy. The differential diagnosis included dermatophytic onychomycosis, bacterial infection such as Pseudomonas, traumatic nail dystrophy, subungual hematoma, drug-induced pigmentation, vascular lesions, lichen planus, benign melanocytic lesions such as lentigo or nevus, Bowen disease, and subungual melanoma. The risks, benefits, limitations, and alternatives to biopsy were discussed in detail, and informed written consent was obtained.
Under sterile conditions and digital ring block anesthesia with 3 mL of 2% lidocaine without epinephrine, the lateral half of the nail plate was removed and submitted for mycologic evaluation; no gross pigmentation was observed. Three 2 mm punch biopsies were obtained from the pigmented and dystrophic areas of the nail bed for evaluation of malignancy. Hemostasis was achieved, a sterile dressing was applied, and postoperative instructions were provided.

3.2.2. Pathologic Evaluation

Right Hallux Nail Unit
Microscopic examination demonstrated a proliferation of atypical, markedly dendritic melanocytes, with cytoplasmic processes extending into the upper spinous layers of the nail matrix epithelium and hyperkeratotic nail fold (Figure 3A). The interface between the squamous epithelium of the nail unit and the underlying melanoma is shown (Figure 3B). A clinical examination of the right hallux demonstrated nail dystrophy and discoloration, as shown in the clinical photograph (Figure 3C). Superficial infiltration into the upper dermis and scattered mitotic figures were also identified. Immunohistochemical staining revealed diffuse positivity for MART-1 and PRAME within the atypical melanocytic population, with diffuse nuclear PRAME positivity demonstrated (Figure 3D). High-magnification examination highlighted marked cytologic atypia and pagetoid spread of melanocytes (Figure 3E). Ki-67 immunostaining demonstrated an elevated proliferative index, estimated at approximately 30% among lesional melanocytes.
These findings were diagnostic of subungual malignant melanoma of the right hallux nail unit, with an estimated Breslow thickness of approximately 0.6 mm. Due to fragmentation of the specimen, precise determination of maximum depth of invasion was limited. Pathologic staging was assigned as pT1a, consistent with melanoma measuring less than 0.8 mm in thickness, without ulceration and with a mitotic rate of less than 1/mm2. The lateral margin was involved by melanoma in situ. Histopathologic regression, perineural invasion, tumor-infiltrating lymphocytes, and satellite nodules were not identified.

3.2.3. Right Hallux Nail Plate

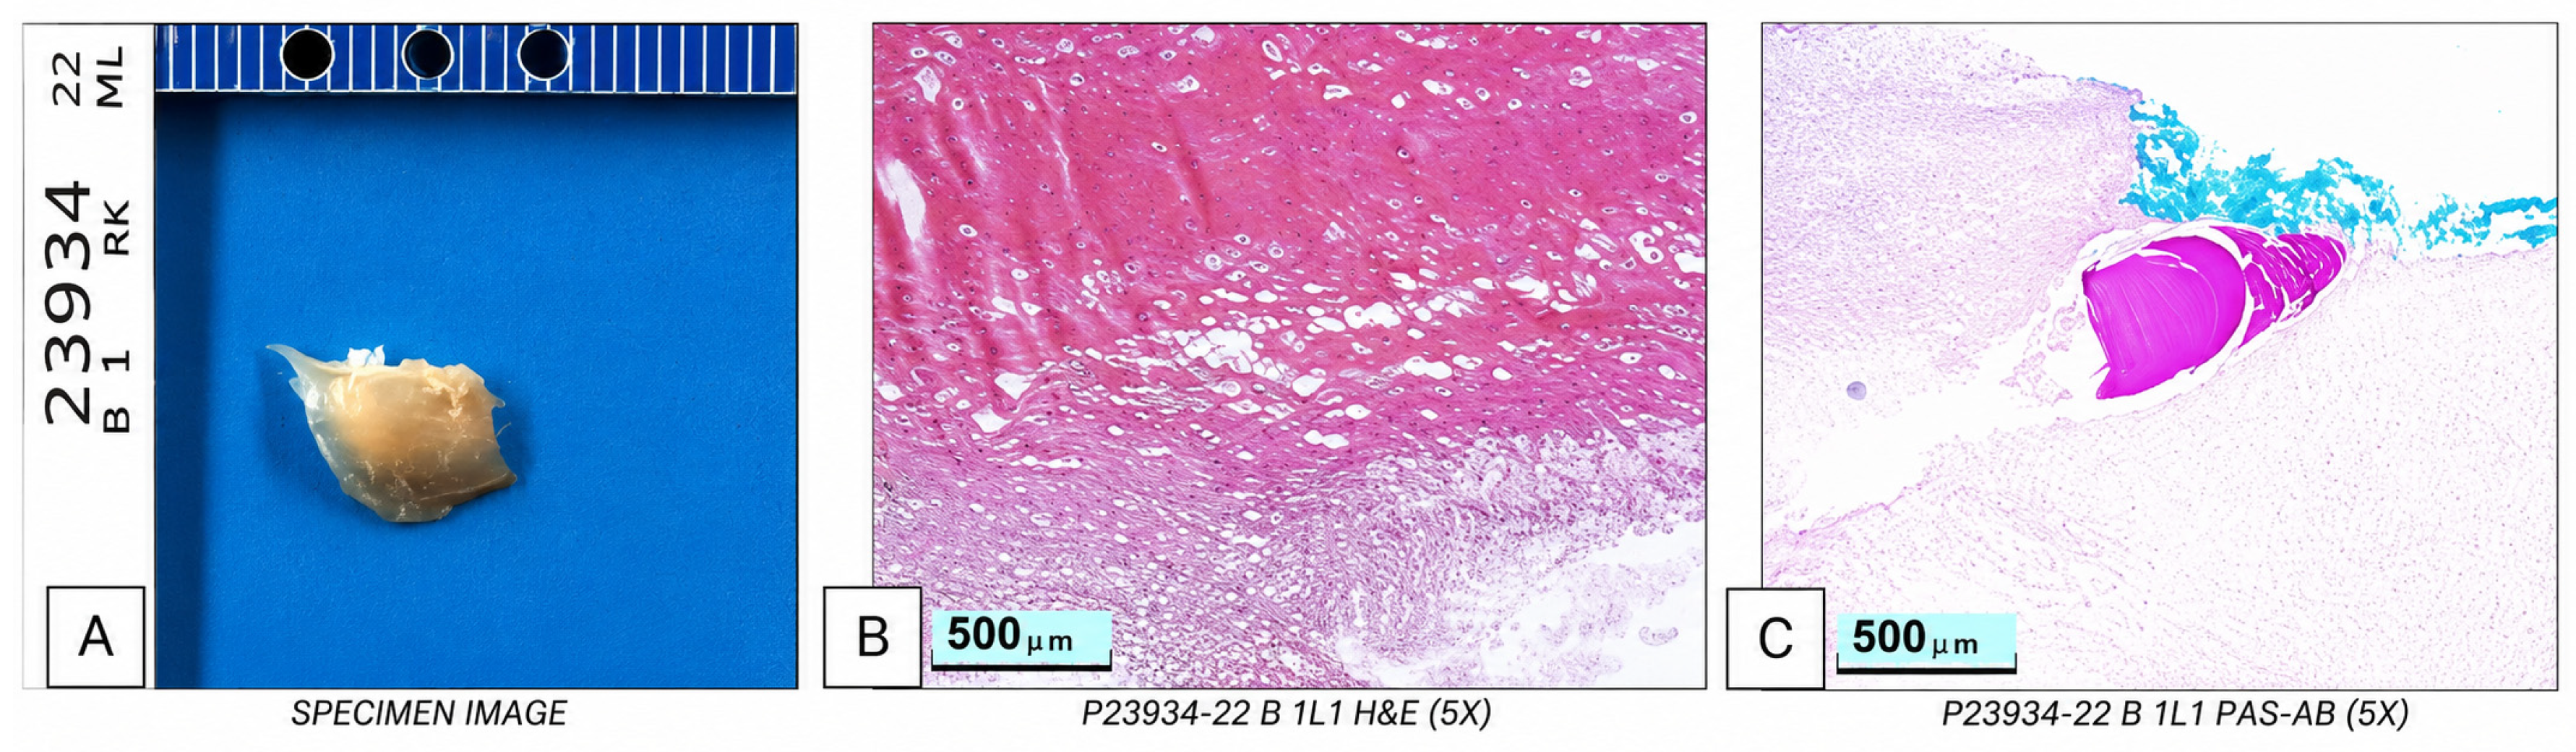
A separate nail plate specimen measuring 9 × 8 × 1.6 mm was submitted dry and processed for evaluation (Figure 4A). Histologic examination revealed marked nail plate thickening with associated parakeratosis. PAS with Alcian blue staining demonstrated fungal elements, including scattered septate hyphae (Figure 4B,C). No evidence of neoplasia was present in these sections. The findings were consistent with onychomycosis of the right hallux nail bed with associated onychogryphosis, exhibiting a dermatophytic pattern characteristic of Trichophyton species. The presence of septate hyphae was morphologically compatible with Trichophyton rubrum or Trichophyton mentagrophytes.

3.2.4. Initial Pathology and Oncologic Evaluation

The initial fragmented right hallux nail unit biopsy demonstrated invasive subungual melanoma with an estimated Breslow thickness of approximately 0.6 mm and a provisional classification of pT1a. However, fragmentation of the specimen limited accurate assessment of the maximum depth of invasion, and deeper involvement could not be definitively excluded. Therefore, definitive surgical excision was recommended to achieve oncologic margins and permit complete pathologic evaluation.
In light of this staging uncertainty, the case was reviewed at a tertiary oncologic institution. Given the inability to reliably determine the true Breslow thickness and the potential for upstaging following complete excision, definitive surgical management was recommended. Right distal great toe amputation was advised to achieve appropriate oncologic margins and permit accurate pathologic staging. Concurrent right inguinal sentinel lymph node biopsy was also recommended to provide comprehensive regional nodal assessment in the setting of indeterminate depth and possible occult invasion.

3.2.5. Intraoperative Course

The patient underwent right distal toe amputation with concurrent right inguinal sentinel lymph node biopsy. After induction of anesthesia and sterile preparation, sentinel lymph node biopsy of the right inguinal basin was performed using preoperative lymphoscintigraphy and intraoperative gamma probe localization, and the identified node was excised in toto. Attention was then directed to the right distal toe, where amputation was performed at the predetermined level to achieve appropriate oncologic margins. The specimen was removed in toto, hemostasis was achieved, and both surgical sites were closed in layers.

3.2.6. Final Surgical Pathology

Final surgical pathology following right distal hallux amputation demonstrated residual acral melanoma with a Breslow thickness of 0.6 mm, no identified ulceration, and a mitotic rate of less than 1/mm2. Tumor-infiltrating lymphocytes were non-brisk, and regression, lymphovascular invasion, neurotropism, and microscopic or macroscopic satellite nodules were not identified. Surgical margins were negative. The primary tumor was classified as pT1a according to the AJCC 8th edition.
Gross examination of the amputation specimen identified a 0.8 × 0.8 cm tan-brown lesion involving the medial nail bed. The lesion was located 1.4 cm from the ventral margin, 2.2 cm from the dorsal margin, 0.8 cm from the medial margin, 2.2 cm from the lateral margin, and 1.6 cm from the deep bone and soft-tissue margin. The specimen was submitted entirely for histopathologic examination following decalcification.
Right groin ultrasound showed no evidence of metastatic disease; however, the sentinel lymph node pathology result was unavailable. Therefore, the regional lymph nodes were classified as pNX, and the overall AJCC stage group could not be confirmed.

3.2.7. Follow-Up and Clinical Course

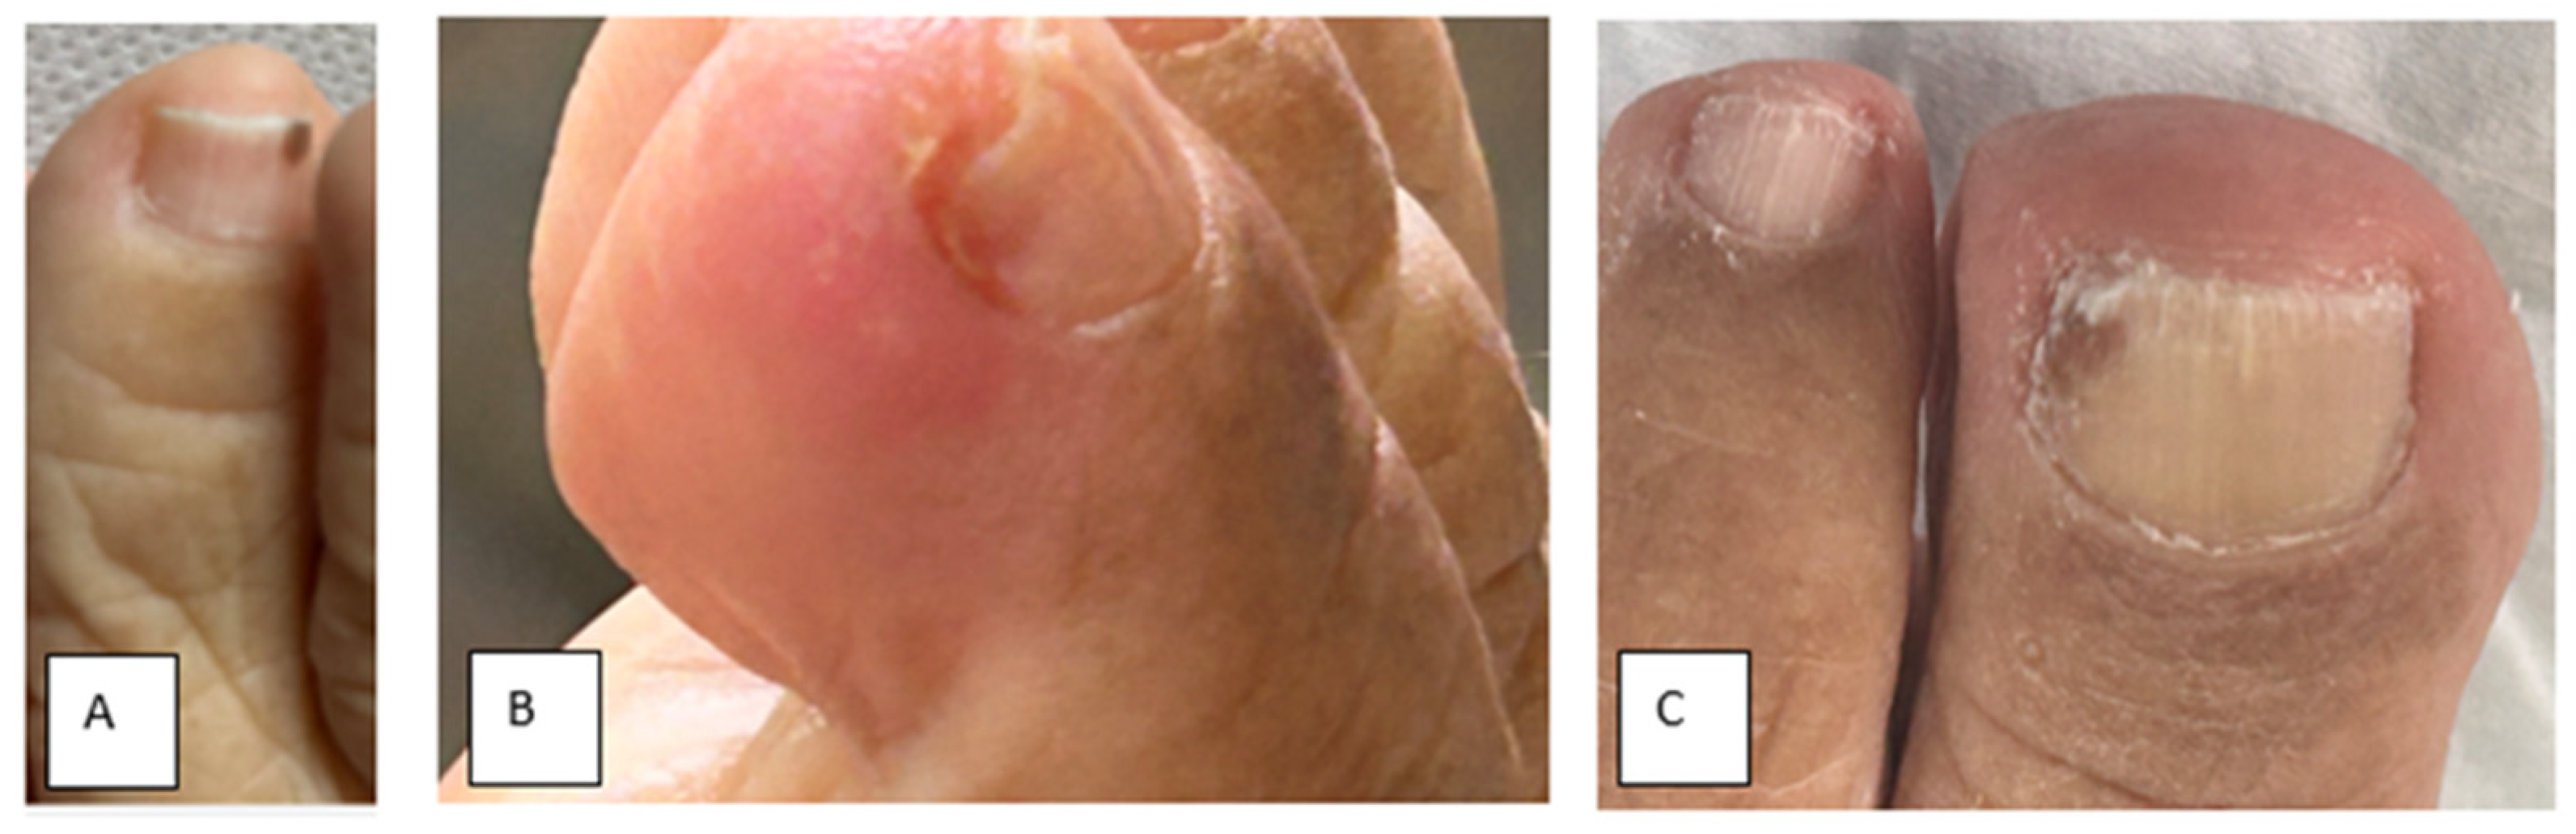
Following right distal hallux amputation, the patient remained under coordinated oncologic and podiatric surveillance. Serial examinations over 26 months demonstrated no clinical evidence of local recurrence, regional nodal disease, or distant metastasis. Intermittent pigmentary changes involving other toes were evaluated and determined to be consistent with resolving subungual hematomas (Figure 5). Nononcologic podiatric conditions were managed as needed and did not interfere with melanoma surveillance. Continued oncologic follow-up and education regarding melanoma warning signs were reinforced.

4. Discussion

SMM remains one of the most diagnostically challenging because its clinical features frequently overlap with common benign nail disorders, including onychomycosis, trauma, and subungual hematoma [2]. The present case series demonstrates an additional layer of complexity, as the confirmed coexistence of onychomycosis and nail unit melanoma within the same nail. Although melanoma misdiagnosed as fungal infection has been reported, laboratory-confirmed coexistence of onychomycosis and melanoma within the same nail unit remains uncommon and has largely been described in isolated case reports [8,9,10]. To our knowledge, based on the available literature, this may represent the first reported case series describing the laboratory-confirmed coexistence of onychomycosis and subungual melanoma.
Despite its rarity, SMM is associated with disproportionately poor outcomes, largely attributable to delayed diagnosis. Reported mean time from initial symptom onset to definitive diagnosis ranges from 1.5 to 2 years, with some cases experiencing delays of up to 30 years [5,11,12]. It is important to note that tumor thickness at diagnosis remains the most important prognostic factor when diagnosing [13].
Furthermore, misdiagnosis is common in such events. Phan et al. reported that 30–60% of subungual melanoma cases are initially attributed to benign conditions such as onychomycosis, subungual hematoma, trauma, or verruca [14]. This diagnostic delay reflects the clinical overlap between melanoma and more prevalent nail disorders. Gupta et al. demonstrated that onychomycosis alone accounts for approximately 50% of all nail abnormalities encountered in clinical practice [15]. Additionally, the prevalence of onychomycosis may be ≥20% in subjects aged ≥ 60 years and ≥50% in those aged ≥ 70 years, whereas older males are 2.1 times more prone to onychomycosis than are females [6]. In a cohort of patients with diabetes and clinically suspected toenail onychomycosis, central laboratory fungal culture confirmed infection in only 42.4% of cases, highlighting the limited reliability of clinical appearance alone [16].
The present case series an additional diagnostic consideration by demonstrating the confirmed coexistence of onychomycosis and nail unit melanoma within the same nail. In both patients, fungal infection was verified histopathologically and/or by molecular testing, with Candida parapsilosis identified in Case 1 and dermatophytic onychomycosis consistent with a Trichophyton morphologic pattern identified in Case 2. Both patients also had biopsy-proven melanoma. Case 1 had a final Breslow thickness of 2.1 mm and Stage IIB disease, whereas Case 2 had a Breslow thickness of approximately 0.6 mm and was classified as pT1a. The factors contributing to delayed melanoma recognition differed between the two patients. In Case 1, the history of trauma, delayed intervention, and chronic ulceration complicated the clinical assessment, whereas in Case 2, prior treatment for presumed onychomycosis without improvement delayed consideration of an underlying malignancy. In both cases, subsequent laboratory testing confirmed that fungal infection and melanoma coexisted within the same nail unit. While the literature documents frequent misdiagnosis of melanoma as fungal infection, true concurrent disease confirmed within the same nail unit is rarely reported and is largely limited to isolated case reports [8,9,10].
These cases underscore a critical clinical principle: that laboratory-confirmed fungal infection does not exclude the presence of concurrent melanoma [8,9,10]. Diagnostic anchoring bias may lead clinicians to attribute all pathologic findings to a common and prevalent condition such as onychomycosis [15,17]. Red-flag features include chronicity exceeding one year, failure of antifungal therapy, ulceration, progressive dystrophy, or pigmentary change, which should prompt histopathologic evaluation regardless of positive mycologic findings [18]. For podiatric clinicians who routinely evaluate nail dystrophy, confirming suspected onychomycosis while remaining alert to alternative inflammatory or neoplastic causes is essential, particularly when lesions are atypical or persistent and may require biopsy [19].
Beyond diagnostic delay, additional challenges arise in staging accuracy. Even when appropriate biopsy methods are employed, melanoma may be understaged on initial sampling. In the present series, Case 1 demonstrated significant understaging on initial biopsy. In Case 2, fragmentation initially limited accurate assessment of Breslow thickness; however, definitive amputation pathology confirmed a Breslow thickness of 0.6 mm and pT1a classification. Such discrepancies are well documented in acral melanoma, where Lee et al. reported differences between initial biopsy thickness and final excision thickness in approximately 43% of acral melanoma cases, with a median discrepancy of 1.6 mm and T-category upstaging occurring in 32% of patients. Notably, this phenomenon was more pronounced in subungual (46%) and palmar (38%) melanomas compared with plantar lesions (28%) [20].
Although variation in Breslow thickness between punch biopsy and final excision is common in acral melanoma, its impact on survival remains uncertain. In a cohort of 124 patients, Kim et al. found that discrepancies in thickness did not significantly affect melanoma-specific mortality (hazard ratio [HR] 0.55, p = 0.447) [21]. Instead, the most significant prognostic factors were greater Breslow thickness (>2 mm; HR 9.93, p = 0.046) and nodal metastasis (HR 5.66, p = 0.041) [21]. These findings suggest that timely and accurate diagnosis may be more critical than precise initial thickness measurement alone. Nevertheless, given the substantial risk of understaging, clinicians should maintain heightened vigilance for acral melanomas initially diagnosed as melanoma in situ or T1 lesions. Current National Comprehensive Cancer Network (NCCN) guidelines recommend that when residual invasive melanoma is identified in the wide excision specimen, pathologists incorporate findings from both the initial biopsy and the excision specimen, specifically the greatest tumor thickness and the presence of ulceration, to determine the final pathologic T stage [22].

Limitations

However, this case series is subject to several limitations. The small sample size inherent to a two-patient report limits generalizability and precludes conclusions regarding incidence, prevalence, or a causal relationship between onychomycosis and subungual melanoma. As an observational study, it cannot determine whether the coexistence of fungal infection and melanoma represents a true pathophysiologic association or a coincidental finding. Although laboratory confirmation of fungal infection was obtained in both cases, the temporal relationship between fungal colonization and melanoma development cannot be established. Despite these limitations, the cases highlight an important diagnostic consideration in podiatric practice and support a low threshold for biopsy in chronic, atypical, or treatment-refractory nail lesions, even in the presence of confirmed onychomycosis.

5. Conclusions

To our knowledge, this may represent one of the first reported case series describing the laboratory-confirmed coexistence of onychomycosis and subungual malignant melanoma. These cases illustrate the diagnostic challenges posed by concurrent fungal infection and malignancy within the same nail unit. Although onychomycosis is the most common cause of nail dystrophy, laboratory-confirmed fungal infection does not exclude underlying melanoma. Reliance on clinical appearance or positive mycologic findings alone may contribute to diagnostic anchoring and delayed evaluation. A high index of suspicion and prompt histopathologic assessment are essential in chronic, atypical, or treatment-refractory nail lesions, particularly those associated with ulceration or pigmentary change. Further reporting of similar cases is needed to determine whether this coexistence represents a rare coincidence or an underrecognized clinical pattern.

Author Contributions

Conceptualization, F.A., E.B.F. and I.V.; methodology, F.A., E.B.F. and I.V.; software, F.A. and I.V.; validation, F.A., E.B.F. and I.V.; formal analysis, E.B.F. and I.V.; investigation, F.A., E.B.F. and I.V.; resources, E.B.F. and I.V.; data curation, F.A., E.B.F. and I.V.; writing—original draft preparation, F.A.; writing—review and editing, F.A., E.B.F. and I.V.; visualization, F.A. and I.V.; supervision, E.B.F. and I.V.; project administration, F.A.; funding acquisition, not applicable. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

This retrospective case series was conducted in a private practice setting and did not undergo formal Institutional Review Board review. The report used only de-identified clinical information obtained during routine care and did not involve research-specific intervention, patient contact, or identifiable private information. Accordingly, the report was considered below the threshold of human-subjects research under applicable U.S. federal regulations, including 45 CFR 46.102, and New York Public Health Law Article 24-A, § 2441. The study was conducted in accordance with the Declaration of Helsinki.

Informed Consent Statement

Informed consent was not required because this retrospective case presentation/case series used only de-identified clinical information collected during routine care, without research-specific intervention, patient contact, or identifiable private information. The report was considered below the threshold of human-subjects research under applicable U.S. federal regulations, including 45 CFR 46.102, and New York Public Health Law Article 24-A, § 2441.

Data Availability Statement

The data presented in this study are not publicly available due to patient privacy and confidentiality restrictions. De-identified data may be made available from the corresponding author upon reasonable request and with appropriate institutional approvals.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

The following abbreviations are used in this manuscript:
ABCDEAsymmetry, Border irregularity, Color variation, Diameter >6 mm, Evolution
ABIAnkle–Brachial Index
cmCentimeter
GMSGomori Methenamine Silver
H&EHematoxylin and Eosin
HRHazard Rati
Ki-67Proliferation Marker Ki-67
MART-1Melanoma Antigen Recognized by T Cells 1
mmMillimeter
NCCNNational Comprehensive Cancer Network
PASPeriodic Acid–Schiff
PCRPolymerase Chain Reaction
PRAMEPreferentially Expressed Antigen in Melanoma
pT1aPathologic Tumor Stage T1a
SMMSubungual Malignant Melanoma

References

  1. Nowowiejska, J.; Ordon, A.J.; Purpurowicz, P.; Argenziano, G.; Piccolo, V. Many faces of melanoma: A comparison between cutaneous, mucosal, acral, nail, and ocular malignancy. Pigment Cell Melanoma Res. 2025, 38, e70051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Levit, E.K.; Kagen, M.H.; Scher, R.K.; Grossman, M.; Altman, E. The ABC rule for clinical detection of subungual melanoma. J. Am. Acad. Dermatol. 2000, 42, 269–274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Wang, Y.; Zhao, Y.; Ma, S. Racial differences in six major subtypes of melanoma: Descriptive epidemiology. BMC Cancer 2016, 16, 691. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. De Giorgi, V.; Saggini, A.; Grazzini, M.; Gori, A.; Rossari, S.; Scarfì, F.; Verdelli, A.; Chimenti, S.; Lotti, T.; Massi, D. Specific challenges in the management of subungual melanoma. Expert Rev. Anticancer Ther. 2011, 11, 749–761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Wollina, U.; Nenoff, P.; Haroske, G.; Haenssle, H.A. The diagnosis and treatment of nail disorders. Dtsch. Arztebl. Int. 2016, 113, 509–518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Gupta, A.K.; Venkataraman, M.; Talukder, M. Onychomycosis in older adults: Prevalence, diagnosis, and management. Drugs Aging 2022, 39, 191–198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Aragón-Sánchez, J.; López-Valverde, M.E.; Víquez-Molina, G.; Milagro-Beamonte, A.; Torres-Sopena, L. Onychomycosis and tinea pedis in the feet of patients with diabetes. Int. J. Low. Extrem. Wounds 2023, 22, 321–327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Riahi, R.R.; Cohen, P.R.; Goldberg, L.H. Subungual amelanotic melanoma masquerading as onychomycosis. Cureus 2018, 10, e2307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Lee, J.; Yun, J.; Shin, K.; Ko, H.; Kim, B.; Kim, M.B.; Kim, H. Ungual melanoma disguised by onychomycosis. J. Mycol. Infect. 2022, 27, 32–40. [Google Scholar] [CrossRef] [Scilit]
  10. Chatterjee, P.B.; Hiwale, K.M.; Ghosh, S. A misdiagnosed case of malignant melanoma in an infected nail: A case report. Cureus 2024, 16, e60236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Lee, W.J.; Lee, J.H.; Won, C.H.; Chang, S.E.; Choi, J.H.; Moon, K.C.; Lee, M.W. Nail apparatus melanoma: A comparative clinicoprognostic study of the initial clinical and morphological characteristics of 49 patients. J. Am. Acad. Dermatol. 2015, 73, 213–220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Darmawan, C.C.; Ohn, J.; Mun, J.H.; Kim, S.; Lim, Y.; Jo, S.J.; Kim, Y.G.; Kim, B.; Seong, M.W.; Kim, B.J.; et al. Diagnosis and treatment of nail melanoma: A review of the clinicopathologic, dermoscopic, and genetic characteristics. J. Eur. Acad. Dermatol. Venereol. 2022, 36, 651–660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Song, J.; El-Khashab, I. Malignant melanoma. In Podiatry Institute Update; Podiatry Institute: Tucker, GA, USA, 2013; pp. 101–105. [Google Scholar]
  14. Phan, A.; Touzet, S.; Dalle, S.; Ronger-Savlé, S.; Balme, B.; Thomas, L. Acral lentiginous melanoma: A clinicoprognostic study of 126 cases. Br. J. Dermatol. 2006, 155, 561–569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Gupta, A.K.; Wang, T.; Cooper, E.A.; Lincoln, S.A.; Foreman, H.C.; Scherer, W.P.; Bakotic, W.L. Clinical diagnosis and laboratory testing of abnormal-appearing toenails: A retrospective assessment of confirmatory testing for onychomycosis in the United States, 2022–2023. J. Fungi 2024, 10, 149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Rich, P.; Harkless, L.B.; Atillasoy, E.S. Dermatophyte test medium culture for evaluating toenail infections in patients with diabetes. Diabetes Care 2003, 26, 1480–1484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Ly, D.P.; Shekelle, P.G.; Song, Z. Evidence for Anchoring Bias During Physician Decision-Making. JAMA Intern. Med. 2023, 183, 818–823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Jin, A.; Haynes, D.; Rodriguez, O.; Park, J.H.; Jellinek, N.; Rubin, A.I. A review of the histopathology of nail unit tumors, including selection of the optimal surgical sampling. Ski. Appendage Disord. 2024, 10, 443–458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. de Berker, D. Fungal nail disease. N. Engl. J. Med. 2009, 360, 2108–2116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Lee, A.Y.; Friedman, E.B.; Sun, J.; Potdar, A.; Daou, H.; Farrow, N.E.; Farley, C.R.; Vetto, J.T.; Han, D.; Tariq, M.; et al. The Devil’s in the Details: Discrepancy Between Biopsy Thickness and Final Pathology in Acral Melanoma. Ann. Surg. Oncol. 2020, 27, 5259–5266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Kim, T.H.; Kim, J.C.; Kwon, J.E.; Kim, Y.C.; Choi, J.W. Effect of changes in Breslow thickness between the initial punch biopsy results and final pathology reports in acral lentiginous melanoma patients. Sci. Rep. 2021, 11, 19885. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. National Comprehensive Cancer Network. NCCN Guidelines for Patients: Melanoma; National Comprehensive Cancer Network: Plymouth Meeting, PA, USA, 2026; Available online: https://www.nccn.org/patientguidelines (accessed on 16 July 2026).
Figure 1. Fungal Onychomycosis of the Left Hallux. (A) Clinical presentation of the left hallux demonstrating a dystrophic nail plate with lateral ulceration. (B) Periodic acid–Schiff (PAS) stain demonstrating fungal elements, indicated by the arrow. Fontana–Masson staining was negative for melanin-producing organisms.
Japma 116 00055 g001
Figure 2. Histopathologic evaluation of the excised left hallux nail unit. (A) Higher magnification showing confluence of atypical melanocytes along the dermal–epidermal junction with pagetoid spread and predominance of solitary melanocytes over nested forms (H&E). (B) Immunohistochemical staining positive for Melan-A, demonstrating intraepidermal melanocytic proliferation. No definitive dermal invasion is identified in the examined sections; however, limited underlying dermis precludes complete exclusion of an invasive component.
Japma 116 00055 g002
Figure 3. Malignant melanoma of the right hallux nail unit. (A) Hematoxylin and eosin (H&E) staining at approximately 34× magnification demonstrating an atypical melanocytic proliferation; scale bar = 125 μm. (B) H&E staining at approximately 30× magnification demonstrating the interface between the squamous epithelium of the nail unit and the underlying melanoma; scale bar = 125 μm. (C) Clinical photograph of the right hallux demonstrating nail dystrophy and discoloration. (D) PRAME immunohistochemical staining at approximately 12× magnification demonstrating diffuse nuclear positivity in neoplastic melanocytes; scale bar = 250 μm. (E) High-magnification H&E staining at approximately 43× magnification highlighting marked cytologic atypia and upward migration of atypical melanocytes; scale bar = 125.
Japma 116 00055 g003
Figure 4. Right Hallux Nail Plate: Onychomycosis (A) Gross image of excised nail plate specimen. (B) H&E stain (low magnification) demonstrating marked nail plate thickening with associated parakeratosis. (C) Periodic acid–Schiff with Alcian blue (PAS-AB) stain highlighting septate fungal hyphae within the nail plate, consistent with dermatophytic onychomycosis (Trichophyton morphologic pattern).
Japma 116 00055 g004
Figure 5. Longitudinal follow-up findings. (A) Clinical photograph obtained at 17–19 months demonstrating hyperpigmentation of the left hallux, assessed as consistent with resolving subungual hematoma without evidence of melanoma recurrence. (B) Left second toe paronychia at approximately 23 months, treated with incision and drainage under local anesthesia. A similar episode occurred contralaterally at 24 months. (C) Bilateral nail debridement and removal of symptomatic nail spicules at 26 months during routine high-risk diabetic foot care follow-up.
Japma 116 00055 g005
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.