Article

Novel Approach to Plantar Fasciitis Treatment: Pulsed Electromagnetic Field Therapy

by
Christopher Bromley
1,*,†,
Caitlyn McManus
2 and
Daniel McManus
3
1
Silver Care Group, Delray Beach, FL 33483, USA
2
Oregon Foot Clinic, Portland, OR 97213, USA
3
Elite Foot and Ankle, Sandy, OR 97055, USA
*
Author to whom correspondence should be addressed.
Dr. Bromley is now with Silver Care Group CEO, Delray Beach, FL, USA.
J. Am. Podiatr. Med. Assoc. 2026, 116(4), 24136; https://doi.org/10.7547/24-136
Submission received: 6 August 2024 / Revised: 25 November 2024 / Accepted: 18 December 2024 / Published: 13 August 2026

Abstract

Background: Pulsed electromagnetic field (PEMF) therapy is a conservative, noninvasive, nonpharmacologic option for the treatment of plantar fasciitis that accelerates the body’s anti-inflammatory and healing responses. Methods: In this case series, adult patients presenting with more than 2 weeks of heel pain due to plantar fasciitis were treated with the OrthoCor Active System PEMF device for 12 weeks. Efficacy was measured at 0 (baseline), 4, 8, and 12 weeks of treatment. Ultrasound was used to measure maximum plantar fascia thickness and hypoechoic region width. Function was evaluated using the Foot and Ankle Disability Index (FADI) and Patient-Specific Functional Scale (PSFS) survey scores. Results: Repeated measures analysis of variance showed a statistically significant improvement in all assessments with PEMF therapy. The mean plantar fascia thickness decreased by 34%, the mean hypoechoic region width decreased by 79%, the mean FADI score improved by 46%, and the mean PSFS score improved by 166%. Compared with data from other studies, PEMF and stretching therapy reduced plantar fascia thickness by 34% compared with 16% for dexamethasone injection and 6% for placebo saline injection; the FADI improved by 46% after 12 weeks of PEMF therapy compared with 43% after 1 year of treatment with indomethacin, heat and shoe pads, plantar fascia stretching, or calf stretching; and PSFS improved by 166% after PEMF therapy compared with 96% after primal reflex release treatment. Conclusions: Pulsed electromagnetic field therapy was effective for stimulating healing and improving function in patients with plantar fasciitis, as demonstrated by significant improvements in ultrasound measures and functional scores. This study suggests that PEMF therapy is an effective conservative, nonpharmacologic treatment option for plantar fasciitis.

1. Introduction

Heel pain is one of the leading musculoskeletal complaints seen by podiatrists and Orthopedists. An estimated one in ten people in the United States develops heel pain during their lifetime [1]. This equates to approximately 2000 patients with heel pain for each podiatrist in the United States. The prevalence of heel pain is slightly higher in middle-aged obese women and young male athletes. Risk factors associated with heel pain include age over 40, female sex, improper footwear, muscle imbalances in the lower leg, obesity, and exercise that loads stress on the heel. Common etiologies seen with heel pain are Achilles tendinitis, calcaneal fracture, plantar fibroma, posterior tibial tendinitis, retrocalcaneal bursitis, plantar calcaneal exostosis, retrocalcaneal exostosis, tarsal tunnel syndrome, neuroma, Baxter’s nerve entrapment, and lumbar radiculopathy; the most common diagnosis is plantar fasciitis [2,3]
The term plantar fasciitis implies inflammation of the plantar fascia; however, pathologic changes are more consistent with degeneration of the plantar fascia, so more appropriate terms may be plantar fasciosis or plantar fasciopathy. Lemont et al. [4] reviewed 50 cases of heel spur surgery performed for plantar fasciitis and found histologic evidence of degeneration of the plantar fascia without inflammation, supporting the concept that plantar fasciitis is a degenerative rather than an inflammatory process.
The plantar fascia is a dense connective tissue made of type I collagen and is divided into central, medial, and lateral bands. These bands originate from the medial and lateral tubercles of the calcaneus and split at the midmetatarsal level into five separate fibrocartilaginous slips that attach to the plantar skin, the base of the proximal phalanges via the plantar plate, the metatarsophalangeal joints via collateral ligaments, and the deep transverse ligaments [5].
Ultrasound has been shown to reveal plantar fascia thickening, as well as hypoechoic changes that indicate microtrauma and degeneration of the plantar fascia [1,6,7], with thickening greater than 4 mm and hypoechoic abnormalities as key indicators of plantar fasciitis [7,8]. Ultrasound can measure changes in the thickness, echogenicity, and stiffness of the plantar fascia to assess the effects of different interventions [9]. Ultrasound can be operator-dependent but is specific, reliable, inexpensive, and radiation-free. A validated tool for evaluating the function of patients with plantar fasciitis is the Foot and Ankle Disability Index (FADI) survey [10,11,12,13].
The diagnosis and treatment of plantar fasciitis start with a thorough history, biomechanical evaluation, appropriate imaging, and patient education. The literature demonstrates that 90% of plantar fasciitis cases can be eliminated with conservative measures, including proper stretching and strengthening exercises, taping and strapping, custom orthotics, physical therapy, nonsteroidal anti-inflammatory medications, night splints, and walking casts [5,14]. Porter et al. found that calf stretching for 3 min three times per day or five sets of 20 s intervals twice daily is beneficial for heel pain [15]. Ribeiro et al. demonstrated that pain significantly decreased with the use of foot orthoses by supporting the function of the longitudinal arch and allowing pressure to disperse instead of overloading the plantar surface [16]. Once more conservative measures are exhausted, plantar fasciitis is treated with steroid injections, platelet-rich plasma injections, and surgery [5,14].
Two of the most common treatments for plantar fasciitis are nonsteroidal anti-inflammatory medications and corticosteroid injections. However, nonsteroidal anti-inflammatory medications can inhibit the healing response and increase the risk of internal bleeding, heart attack, stroke, and high blood pressure [17]. Disadvantages of steroid injections include risk of nerve damage, elevated blood glucose in the diabetic population, and increased risk of plantar fascia rupture. A systematic review of 39 studies found that steroid injections reduce heel pain for the first month but have little impact beyond that [18].
Emerging conservative treatments for plantar fasciitis include extracorporeal shockwave therapy and low-level laser therapy. Extracorporeal shockwave therapy provides stimulation of the vasculature and encourages collagen synthesis in degenerative soft tissues [19]. Low-level laser therapy is a photobiomodulation therapy that initiates an anti-inflammatory response and stimulates cell proliferation, angiogenesis, microcirculation, and collagen production. Wang et al. performed a meta-analysis that showed that low-level laser therapy reduced heel pain [20].
An innovative treatment for plantar fasciitis is pulsed electromagnetic field (PEMF) therapy, which accelerates the body’s anti-inflammatory and recovery responses. Pulsed electromagnetic field therapy is delivered using an inductive loop antenna to transmit a magnetic field into the target tissue without direct contact. At the molecular level, PEMF therapy promotes the binding of calcium to calmodulin, which activates the nitric oxide cascade [21,22]. Nitric oxide is essential for the body’s natural healing response and functions as a natural vasodilator. The production of nitric oxide leads to a reduction in pain and swelling and an acceleration in soft tissue healing. Pulsed electromagnetic field therapy has been shown to reduce chronic pain, swelling, and postoperative pain [23]. Pulsed electromagnetic field therapy is a nonpharmacologic and noninvasive pain relief therapy that should be considered for the conservative management of plantar fasciitis. A prior study of patients with plantar fasciitis found that morning pain scores decreased by 40% with 7 days of PEMF use compared with 7% with placebo [24].
The OrthoCor Active System (OrthoCor Medical, Inc, Blaine, Minnesota) is a portable, battery-operated, noninvasive device that applies a PEMF at a frequency of 27.12 MHz for the treatment of pain in superficial soft tissue, such as in the ankle, back, knee, wrist, elbow, shoulder, foot, or neck. The system uses disposable, single-use, air-activated OrthoPods that provide heat for the temporary relief of minor musculoskeletal aches and pains associated with overexertion, strains, sprains, and arthritis. The present study sought to elucidate the clinical results of PEMF therapy in patients with plantar fasciitis.

2. Materials and Methods

The study enrolled patients consecutively from an urban, hospital-based podiatry clinic. The protocol for this study was reviewed and approved by the Western Institutional Review Board (study number 1297396). Inclusion criteria comprised men and women between the ages of 18 and 65 years with a history of persistent heel pain due to plantar fasciitis lasting more than 2 weeks. Exclusion criteria included corticosteroid injections within the past 6 months, prior plantar fascia surgery, history of tarsal tunnel syndrome, lumbar radiculopathy, complex regional pain syndrome, smoking, diabetes, and current immunotherapy treatment. Participants were given 12 weeks of PEMF therapy. The onset of injury, medical history, weight, and prior treatments for each patient were recorded prior to starting therapy.
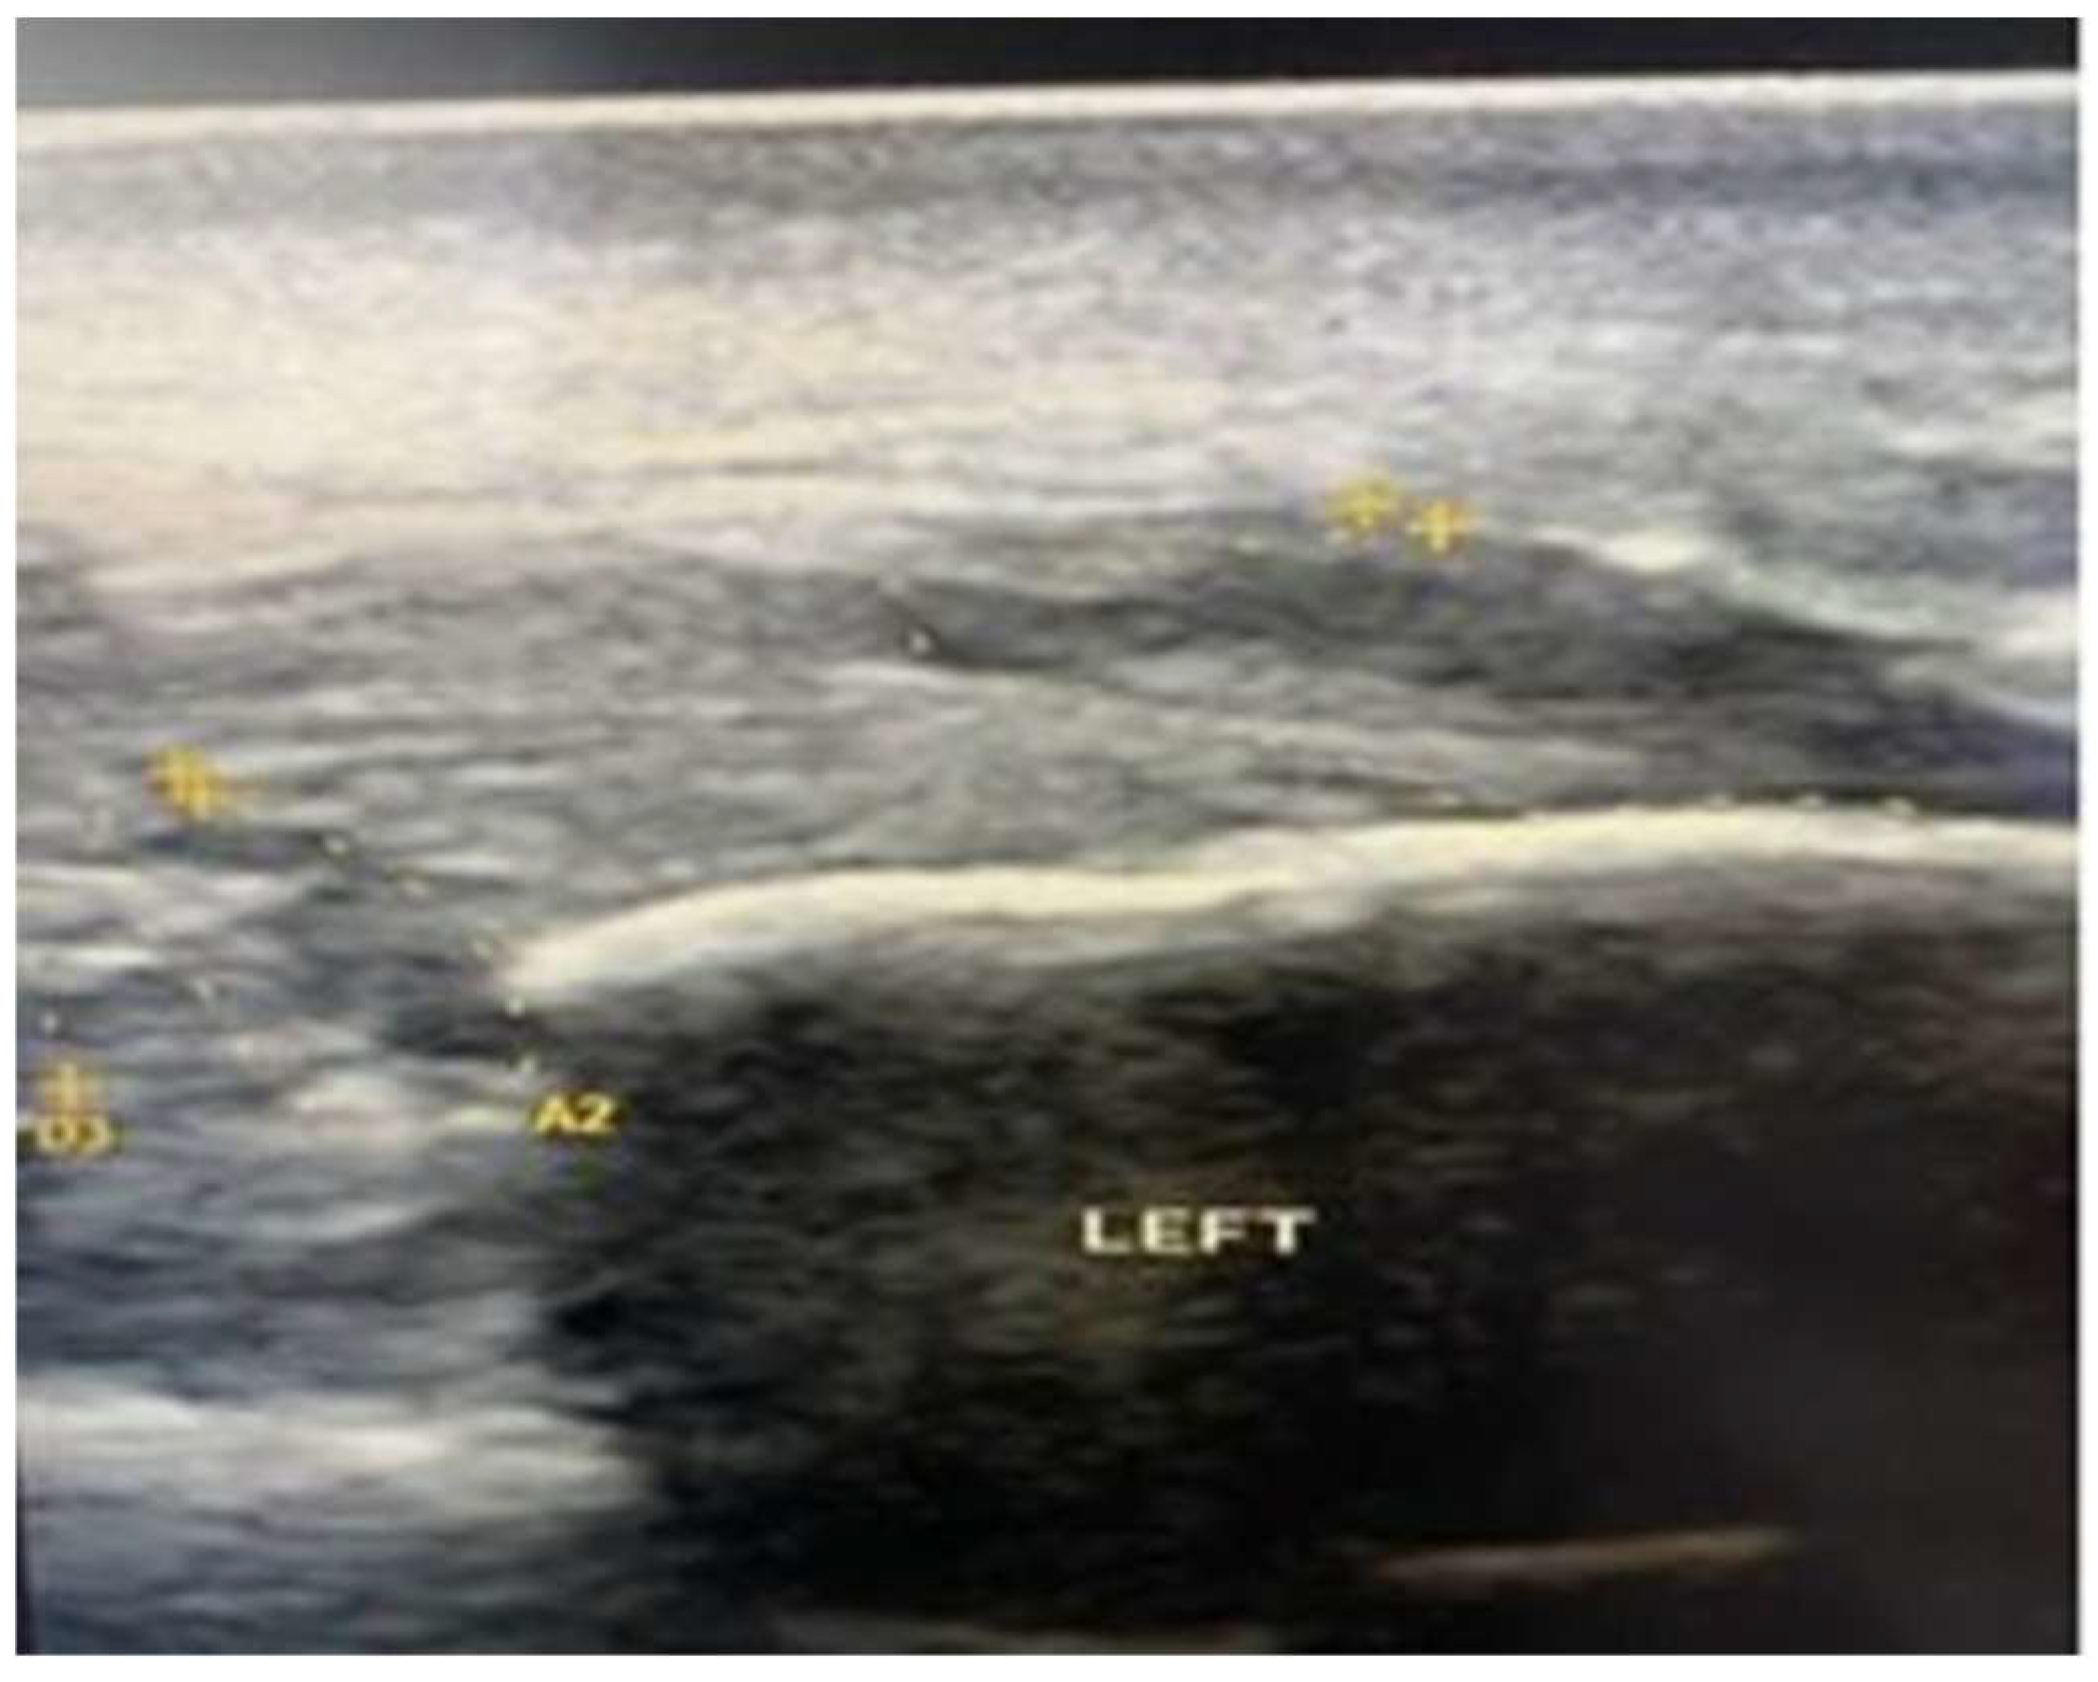
All patients were issued an OrthoCor Active System foot device (Figure 1) to use for 2 h per day along with at-home stretching exercises and appropriate footwear. Patients were advised to avoid walking or standing barefoot and to avoid using oral anti-inflammatory medications. Ultrasound evaluation of the involved foot was used to measure the hypoechoic region width and plantar fascia thickness (Figure 2). Ultrasound evaluation was performed at the initial, 4-week, 8-week, and 12-week visits. At the same visits, symptoms were measured and recorded using the FADI (maximum score = 104) and Patient-Specific Functional Scale (PSFS) (maximum score = 10) surveys. A total of 12 patients were used in the data analysis after patients with partial data were excluded. Additional patients were planned, but further enrollment and follow-up visits were cut short when the primary investigator left the study.
The data were analyzed using JASP statistical software. The Shapiro–Wilk test was used to assess normality. A repeated measures analysis of variance (ANOVA) was conducted on each outcome variable to account for correlation among repeated measures for the same participant. The data were approximately normal and the Mauchly test indicated that the assumption of sphericity (differences between weeks had equal variance) held for each variable except hypoechoic width, to which a Greenhouse–Geisser sphericity correction was applied prior to ANOVA.

3. Results

Data from 12 patients (nine women and three men) with complete data were analyzed. The patients’ age (mean ± SD) was 51 ± 11 years. The patients’ weight (mean ± SD) was 187 ± 62 pounds (85 ± 28 kg), with a range of 115 to 300 pounds (52–136 kg). There were no adverse effects reported by any of the patients.
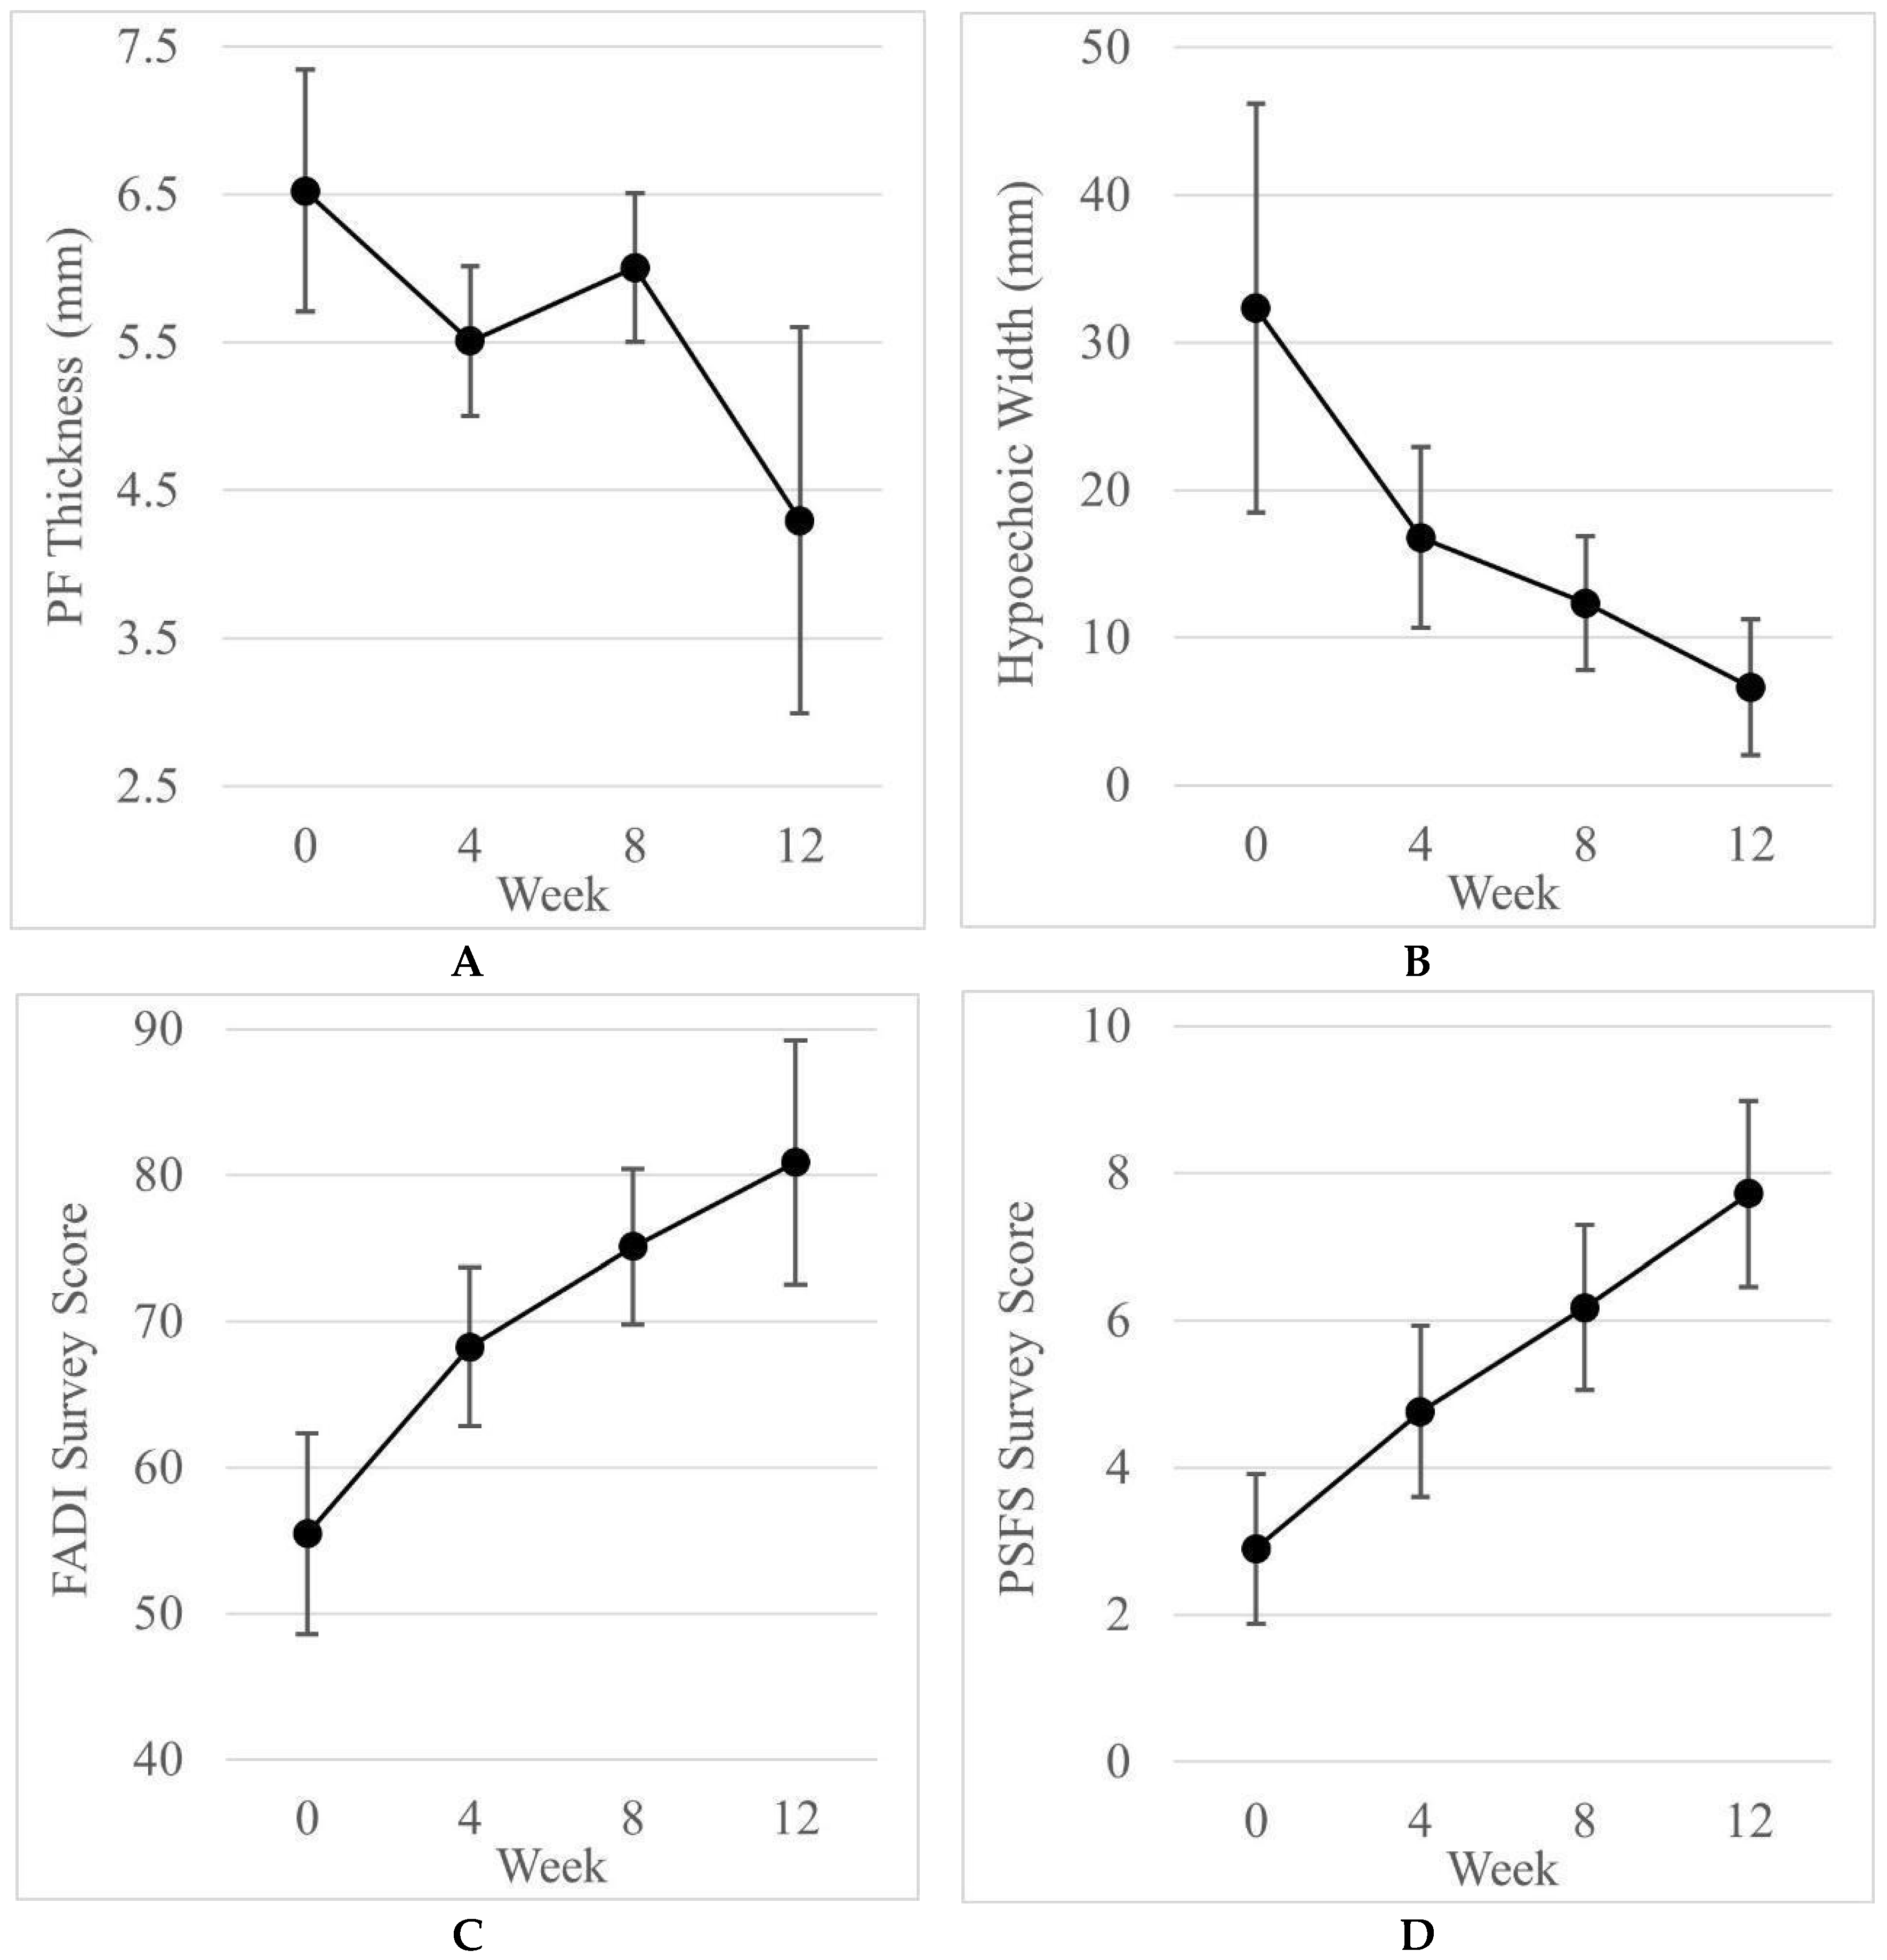
Mean thickness of the plantar fascia decreased from 6.5 mm at the initial visit to 4.3 mm after 12 weeks of PEMF treatment (Table 1, Figure 3). Repeated measures ANOVA showed that the difference from week 0 to week 12 was statistically significant, with a p-value of 0.005 and a decrease in mean thickness of 2.2 mm (34%), with a 95% confidence interval of 0.56 to 3.9 mm (15–60%).
Mean width of the hypoechoic region in the plantar fascia decreased from 32 mm at the initial visit to 6.6 mm after 12 weeks of PEMF treatment. Repeated measures ANOVA showed that the difference from week 0 to week 12 was statistically significant, with a p-value of 0.004 and a decrease in mean hypoechoic width of 25.6 mm (79%), with a 95% confidence interval of 11 to 32 mm (34–100%). An example ultrasound is shown in Figure 2.
Mean FADI survey scores improved from 55 at the initial visit to 81 after 12 weeks of PEMF treatment (Table 2, Figure 4). Repeated measures ANOVA showed that the difference from week 0 to week 12 was statistically significant, with a p-value of less than 0.001 and an increase in the mean FADI score of 25.4 (46%), with a 95% confidence interval of 16 to 34 (30–62%).
Mean PSFS survey scores improved from 2.9 at the initial visit to 7.7 after 12 weeks of PEMF treatment (Table 2, Figure 4). Repeated measures ANOVA showed that the difference from week 0 to week 12 was statistically significant, with a p-value of less than 0.001 and an increase in mean PSFS score of 4.8 (166%), with a 95% confidence interval of 3.2 to 6.4 (111–222%).

4. Discussion

The results from this study were compared with data from other studies. With PEMF treatment, plantar fascia thickness decreased more in this study than in a prior study with 82 patients in two groups: one treated with a 0.25 mg dexamethasone injection and the other treated with a placebo saline injection [25]. After 12 weeks of treatment, the decrease in plantar fascia thickness with PEMF therapy was 34% (6.5–4.3 mm), whereas in the prior study it was 16% (6.67–5.74 mm) for the dexamethasone group and 6% (6.29–5.94 mm) for the saline group.
Ultrasound measurements such as hypoechoic width are underused tools for diagnosing and evaluating soft tissue injury. Plantar fascia thickness and hypoechoic width are powerful tools for complementing history, physical exam, and functional evaluation to provide a full picture of the patient. In this study, hypoechoic width improved more quickly than plantar fascia thickness. Because of the paucity of studies using ultrasound measurements, no study was found that presented comparable data for hypoechoic width.
In this study, similar FADI results were achieved after 12 weeks of PEMF therapy (46% improvement [55–81]) compared with 1 year of treatment (43% improvement [63.6–90.7]) in a study with 140 patients in four groups treated with 75 mg of indomethacin (group 1), moist heat and shoe pads (group 2), plantar fascia stretching (group 3), and calf stretching (group 4) [26]. The data in the prior study were pooled to represent the spectrum of common treatments. The prior study also excluded patients with a body mass index >25 kg/m2 or pain in the hip or knee, and the authors’ patients had higher scores before and after treatment, suggesting less severity in the patients in that trial.
The 166% improvement in PSFS scores (2.9–7.7) after 12 weeks of PEMF therapy in this study compares favorably to a 96% improvement (4.95–9.71) reported in a case series after primal reflex release [27]. However, the comparison may be limited because the treatment duration in the prior study ranged from 1 to 48 days, and the study population primarily consisted of young division I athletes aged 19 to 21 years. Again, the PSFS scores were higher in the prior study both before and after treatment, suggesting less severity.
Repeated measures ANOVA showed that PEMF therapy led to a statistically significant improvement in all measured outcome variables. A repeated measures ANOVA was used to account for correlation among repeated measures for the same participant, which meant the confidence intervals for the ANOVA were tighter than the confidence intervals for the mean, analogous to using a paired versus unpaired t-test. The mean thickness measurements of the plantar fascia decreased, then increased, and then decreased substantially; however, all other measures decreased or improved linearly, suggesting variation in measurement technique. Notably, the hypoechoic width and FADI score improved slightly more from week 0 to week 4 than in any other interval, suggesting that more healing may occur during the first 4 weeks of treatment.
Ultrasound examination was able to detect decreases in plantar fascia thickness and hypoechoic region width that were consistent with healing. These changes correlated with functional improvements, as evaluated by FADI and PSFS scores. The improvement in the PSFS score was greater than the improvement in the FADI score, likely because the FADI score captures general lower-extremity health, whereas the PSFS score is more specific to the complaint.
The deviation from the normal distribution had a minimal impact on the ANOVA. The assumption of sphericity (variance in the differences between weeks was equal) held for all outcomes except hypoechoic width, to which a sphericity correction was applied. The p-values for the ANOVAs were far below 0.05, suggesting that even if there were slight deviations from normality, they would not change the conclusions. This was seen with the hypoechoic width ANOVA, for which the sphericity correction changed the p-value from less than 0.001 to 0.004.
Pulsed electromagnetic field therapy has been shown to modify cellular signaling by increasing intracellular calcium ions, which bind to calmodulin to induce the production of nitric oxide [21,22]. Intracellular calcium levels regulate many cellular processes, with low levels favoring quiescence and high levels promoting activity and proliferation [28]. Tong et al. demonstrated that PEMF therapy applied to osteoblasts in the presence of extracellular stimuli altered transient intracellular calcium ion signals, increasing both the proportion of responding cells and the magnitude of the response [29]. The authors eliminated the effect by applying PEMF therapy after the stimuli and by chelating the intracellular calcium ions. This suggests that PEMF therapy amplifies existing cell repair signals or increases sensitivity to stimuli rather than inducing new signals. This corresponds to the absence of known adverse effects from PEMF therapy. The pulsatile increases in calcium ions stimulate endothelial nitric oxide synthase to generate pulses of low levels of nitric oxide that limit inflammation [21,22].
Vasodilation by nitric oxide is an example of this type of cell signaling. G protein-coupled receptor activation of phospholipase C leads to the creation of inositol 1,4,5-triphosphate and diacylglycerol, which allow calcium ions into the cytosol from the endoplasmic reticulum and then into the extracellular space. Cytosolic calcium ions bind to calmodulin, which upregulates endothelial nitric oxide synthase, creating a burst of nitric oxide that diffuses to nearby smooth muscle cells, causing relaxation and vasodilation [30].
The molecular and clinical effects of PEMF therapy are difficult to compare between studies, owing to the heterogeneity of PEMF signals and treatment parameters. Commercially available PEMF treatments may have carrier frequencies of 30 to 30,000 kHz and pulse repetition frequencies of 1 to 150 Hz, whereas the magnetic field strength is often unreported and often varies by orders of magnitude [31]. Future studies could further characterize how plantar fascia thickness and hypoechoic width decrease as the patient recovers, test different PEMF signal parameters, and test PEMF therapy against other treatments for plantar fasciitis.

5. Conclusions

Pulsed electromagnetic field therapy with the OrthoCor Active System combined with stretching was effective in stimulating healing and improving function in patients with plantar fasciitis. Ultrasound demonstrated decreases in plantar fascia thickness of 34% and hypoechoic region width of 79%, which correlated with functional improvements in survey scores of 46% for the FADI and 166% for the PSFS. Repeated measures ANOVA showed that PEMF therapy led to a statistically significant improvement in all measured outcome variables. These results compare favorably with several prior studies using a variety of treatments, including dexamethasone injection, indomethacin, moist heat, shoe pads, and stretching. Pulsed electromagnetic field therapy shows promise as a conservative treatment option for plantar fasciitis.

Author Contributions

Conceptualization, C.B.; methodology, C.B. and C.M.; investigation, C.M.; formal analysis, C.M.; data curation, C.M.; writing—original draft preparation, C.M.; writing—review and editing, C.B., C.M. and D.M.; supervision, C.B.; project administration, C.B. All authors have read and agreed to the published version of the manuscript.

Funding

This study was sponsored by OrthoCor Medical, maker of the OrthoCor Active System. No funding was received from OrthoCor Medical or any other commercial entity for this study.

Institutional Review Board Statement

The study was conducted in accordance with the Declaration of Helsinki and was approved by the Institutional Review Board of OrthoCor Medical (protocol code WCG, Sponsor Protocol Number: 2020OC, date of approval 11 January 2021, Study Number 1297.396).

Informed Consent Statement

Informed consent was obtained from all participants involved in the study.

Data Availability Statement

The raw data supporting the conclusions of this article will be made available by the authors upon request.

Acknowledgments

The authors thank all study participants for their participation and contribution to this research, including Kai Kroll and OrthoCor Medical.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Radwan, A.; Wyland, M.; Applequist, L.; Bolowsky, E.; Klingensmith, H.; Virag, I. Ultrasonography, an effective tool in diagnosing plantar fasciitis: A systematic review of diagnostic trials. Int. J. Sports Phys. Ther. 2016, 11, 663–671. [Google Scholar] [PubMed]
  2. Papaliodis, D.N.; Vanushkina, M.A.; Richardson, N.G.; DiPreta, J.A. The foot and ankle examination. Med. Clin. N. Am. 2014, 98, 181–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Tu, P.; Bytomski, J.R. Diagnosis of heel pain. AM. Fam. Physician 2011, 84, 909–916. [Google Scholar] [PubMed]
  4. Lemont, H.; Ammirati, K.M.; Usen, N. Plantar fasciitis: A degenerative process (fasciosis) without inflammation. J. AM. Podiatr. Med. Assoc. 2003, 93, 234–237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Tahririan, M.A.; Motififard, M.; Tahmasebi, M.N.; Siavashi, B. Plantar fasciitis. J. Res. Med. Sci. 2012, 17, 799–804. [Google Scholar] [PubMed]
  6. Akfirat, M.; Sen, C.; Günes, T. Ultrasonographic appearance of the plantar fasciitis. Clin. Imaging 2003, 27, 353–357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Hossain, M.; Makwana, N. “Not Plantar Fasciitis”: The differential diagnosis and management of heel pain syndrome. Orthop. Trauma 2011, 25, 198–206. [Google Scholar] [CrossRef] [Scilit]
  8. McMillan, A.M.; Landorf, K.B.; Barrett, J.T.; Menz, H.B.; Bird, A.R. Diagnostic imaging for chronic plantar heel pain: A systematic review and meta-analysis. J. Foot Ankle Res. 2009, 2, 32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Khammas, A.S.A.; Mahmud, R.; Hassan, H.A.; Ibrahim, I.; Mohammed, S.S. An assessment of plantar fascia with ultrasound findings in patients with plantar fasciitis: A systematic review. J. Ultrasound 2023, 26, 13–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Martin, R.L.; Burdett, R.G.; Irrgang, J.J. Development of the foot and ankle disability index (FADI). J. Orthop. Sports Phys. Ther. 1999, 29, A32–A33. [Google Scholar]
  11. Pugia, M.L.; Middel, C.J.; Seward, S.W.; Pollock, J.L.; Hall, R.C.; Lowe, L.; Mahony, L.; Henderson, N.E. Comparison of acute swelling and function in subjects with lateral ankle injury. J. Orthop. Sports Phys. Ther. 2001, 31, 384–388. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Hale, S.A.; Hertel, J. Reliability and Sensitivity of the Foot and Ankle Disability Index in Subjects with Chronic Ankle Instability. J. Athl. Train. 2005, 40, 35–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Martin, R.L.; Irrgang, J.J. A survey of self-reported outcome instruments for the foot and ankle. J. Orthop. Sports Phys. Ther. 2007, 37, 72–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Puttaswamaiah, R.; Chandran, P. Degenerative plantar fasciitis: A review of current concepts. Foot 2007, 17, 3–9. [Google Scholar] [CrossRef] [Scilit]
  15. Porter, D.; Barrill, E.; Oneacre, K.; May, B.D. The effects of duration and frequency of Achilles tendon stretching on dorsiflexion and outcome in painful heel syndrome: A randomized, blinded, control study. Foot Ankle Int. 2002, 23, 619–624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Ribeiro, A.P.; Trombini-Souza, F.; Tessutti, V.D.; Lima, F.R.; João, S.M.A.; Sacco, I.C.N. The effects of plantar fasciitis and pain on plantar pressure distribution of recreational runners. Clin. Biomech. 2011, 26, 194–199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Lai, T.W.; Ma, H.L.; Lee, M.S.; Chen, P.M.; Ku, M.C. Ultrasonography and clinical outcome comparison of extracorporeal shock wave therapy and corticosteroid injections for chronic plantar fasciitis: A randomized controlled trial. J. Musculoskelet. Neuronal Interact. 2018, 18, 47–54. [Google Scholar] [PubMed]
  18. David, J.A.; Sankarapandian, V.; Christopher, P.R.; Chatterjee, A.; Macaden, A.S. Injected corticosteroids for treating plantar heel pain in adults. Cochrane Database Syst. Rev. 2017, 6, CD009348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Kudo, P.; Dainty, K.; Clarfield, M.; Coughlin, L.; Lavoie, P.; Lebrun, C. Randomized, placebo-controlled, double-blind clinical trial evaluating the treatment of plantar fasciitis with an extracoporeal shockwave therapy (ESWT) device: A North American confirmatory study. J. Orthop. Res. 2006, 24, 115–123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Wang, W.; Jiang, W.; Tang, C.; Zhang, X.; Xiang, J. Clinical efficacy of low-level laser therapy in plantar fasciitis: A systematic review and meta-analysis. Medicine 2019, 98, e14088. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Caliogna, L.; Medetti, M.; Bina, V.; Brancato, A.M.; Castelli, A.; Jannelli, E.; Ivone, A.; Gastaldi, G.; Annunziata, S.; Mosconi, M.; et al. Pulsed Electromagnetic Fields in Bone Healing: Molecular Pathways and Clinical Applications. Int. J. Mol. Sci. 2021, 22, 7403. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Strauch, B.; Herman, C.; Dabb, R.; Ignarro, L.J.; Pilla, A.A. Evidence-based use of pulsed electromagnetic field therapy in clinical plastic surgery. Aesthetic Surg. J. 2009, 29, 135–143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Yang, X.; He, H.; Ye, W.; Perry, T.A.; He, C. Effects of Pulsed Electromagnetic Field Therapy on Pain, Stiffness, Physical Function, and Quality of Life in Patients With Osteoarthritis: A Systematic Review and Meta-Analysis of Randomized Placebo-Controlled Trials. Phys. Ther. 2020, 100, 1118–1131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Brook, J.; Dauphinee, D.M.; Korpinen, J.; Rawe, I.M. Pulsed radiofrequency electromagnetic field therapy: A potential novel treatment of plantar fasciitis. J. Foot Ankle Surg. 2012, 51, 312–316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. McMillan, A.M.; Landorf, K.B.; Gilheany, M.F.; Bird, A.R.; Morrow, A.D.; Menz, H.B. Ultrasound guided corticosteroid injection for plantar fasciitis: Randomised controlled trial. BMJ 2012, 344, e3260. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Gupta, R.; Malhotra, A.; Masih, G.D.; Khanna, T.; Kaur, H.; Gupta, P.; Kashyap, S. Comparing the Role of Different Treatment Modalities for Plantar Fasciitis: A Double Blind Randomized Controlled Trial. Indian. J. Orthop. 2020, 54, 31–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Hansberger, B.L.; Baker, R.T.; May, J.; Nasypany, A. A novel approach to treating plantar fasciitis—effects of primal reflex release technique: A case series. Int. J. Sports Phys. Ther. 2015, 10, 690–699. [Google Scholar] [PubMed]
  28. Bootman, M.D.; Bultynck, G. Fundamentals of Cellular Calcium Signaling: A Primer. Cold Spring Harb. Perspect. Biol. 2020, 12, a038802. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Tong, J.; Sun, L.; Zhu, B.; Fan, Y.; Ma, X.; Yu, L.; Zhang, J. Pulsed electromagnetic fields promote the proliferation and differentiation of osteoblasts by reinforcing intracellular calcium transients. Bioelectromagnetics 2017, 38, 541–549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. da Silva, G.M.; da Silva, M.C.; Nascimento, D.V.G.; Silva, E.M.L.; Gouvêa, F.F.F.; Lopes, L.G.d.F.; Araújo, A.V.; Pereira, K.N.F.; de Queiroz, T.M. Nitric Oxide as a Central Molecule in Hypertension: Focus on the Vasorelaxant Activity of New Nitric Oxide Donors. Biology 2021, 10, 1041. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Flatscher, J.; Loriè, E.P.; Mittermayr, R.; Meznik, P.; Slezak, P.; Redl, H.; Slezak, C. Pulsed Electromagnetic Fields (PEMF)—Physiological Response and Its Potential in Trauma Treatment. Int. J. Mol. Sci. 2023, 24, 11239. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Figure 1. The OrthoCor Active System foot device used in this study uses a pulsed electromagnetic field to stimulate the body’s natural healing response. Patients with plantar fasciitis received treatments for 2 h per day for 12 weeks.
Japma 116 24136 g001
Figure 2. Ultrasound from the initial visit showing two tears, or hypoechoic regions, in the plantar fascia (left). Representative ultrasound image demonstrating plantar fascia thickening and hypoechoic degeneration consistent with plantar fasciitis.
Japma 116 24136 g002
Figure 3. Representative ultrasound image demonstrating the plantar fascia morphology evaluated during the study.
Japma 116 24136 g003
Figure 4. (A) Mean plantar fascia thickness at baseline, 4 weeks, 8 weeks, and 12 weeks. (B) Mean hypoechoic region width at baseline, 4 weeks, 8 weeks, and 12 weeks. (C) Mean Foot and Ankle Disability Index (FADI) scores at baseline, 4 weeks, 8 weeks, and 12 weeks. (D) Mean Patient-Specific Functional Scale (PSFS) scores at baseline, 4 weeks, 8 weeks, and 12 weeks. Error bars indicate 95% confidence intervals.
Japma 116 24136 g004
Table 1. Plantar fascia thickness and hypoechoic widths.
Plantar Fascia ThicknessHypoechoic Width
WeekMean95% CIMean95% CI
06.55.7–7.33218–46
45.55.0–6.01711–23
86.05.5–6.5127.8–17
124.33.0–5.66.62.0–11
Note: Data are presented in millimeters. Abbreviation: CI, confidence interval.
Table 2. Foot and Ankle Disability Index and Patient-Specific Functional Scale survey scores.
FADI Survey ScorePSFS Survey Score
WeekMean95% CIMean95% CI
05549–622.91.9–3.9
46863–744.83.6–5.9
87570–806.25.1–7.3
128172–897.76.5–9.0
Note: FADI survey maximum score = 104; PSFS survey maximum score = 10. Abbreviations: CI, confidence interval; FADI, Foot and Ankle Disability Index; PSFS, Patient-Specific Functional Scale.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.