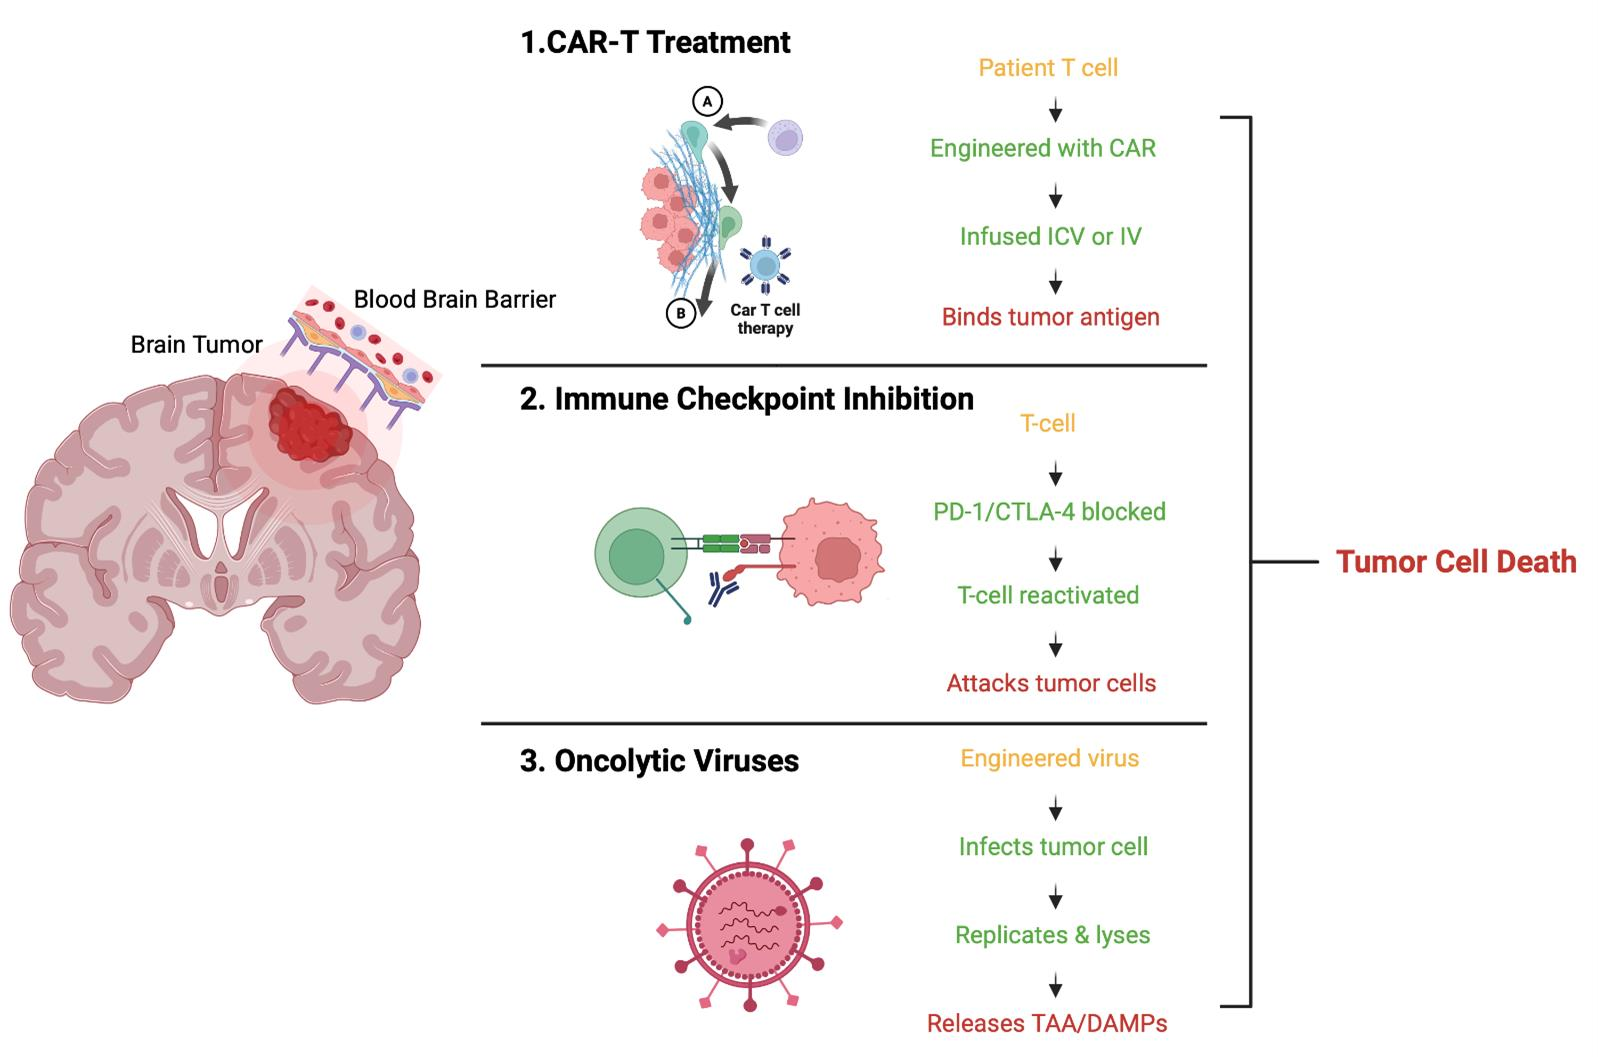
Cellular and Immunotherapy for Pediatric Brain Tumors: A Primer


Simple Summary
Abstract
1. Introduction
2. Adoptive Cellular Therapy: CAR T Cell Therapy
2.1. Biology
2.2. Development and Administration
2.3. Clinical Applications of CAR T Cell Therapy in Brain Tumors
2.4. CAR T Cell Therapy Related Challenges/Toxicities
2.5. Future Directions
3. Active Immunotherapy
Immune Checkpoint Inhibitors (ICI)
4. Oncolytic Viruses (OV)
4.1. Mechanism of Action
4.1.1. Tumor Selective Viral Replication and Cytolysis
4.1.2. Immune Activation
4.2. Oncolytic Viral Platforms in Pediatric Brain Tumors
4.3. Clinical Trials of Oncolytic Virotherapy in Pediatric CNS Tumors

| Virus | Platform | Tumor Type | Trial Phase | Delivery Method | Key Findings |
|---|---|---|---|---|---|
| HSV-1 [86] NCT02457845 | G207 | Recurrent pediatric high-grade glioma | Phase I | Intratumoral injection + radiation | Favorable safety profile; immune activation observed; radiographic responses in subset of patients |
| HSV-1 NCT04482933 | G207 | Recurrent pediatric high-grade glioma | Phase II | Intratumoral injection + radiation | Funding withdrawn without single enrollment. |
| HSV1 NCT03911388 | G207 | Recurrent pediatric cerebellar high-grade tumors | Phase I | Intratumoral+ Radiation | Active, recruiting |
| HSV-1 (NCT02031965) | HSV1716 | Recurrent/refractory pediatric brain tumors | Phase I | Intra/peritumoral injection | Trial terminated early after enrolling two patients; no formal efficacy results reported |
| Adenovirus [87] (NCT03178032) | DNX-2401 (Delta-24-RGD) | Newly diagnosed DIPG | Phase I | Intratumoral injection | Median OS 17.18 months; acceptable safety profile |
| Poliovirus [89] NCT03043391 | PVSRIPO (Lerapolturev) | Recurrent Pediatric high grade CNS tumors | Phase Ib | Convection-enhanced delivery | No treatment related irreversible G4 AE or deaths. The median overall survival was 4.1 months (95% CI 1.2–10.1). One patient remains alive after 22 months. |
| Reovirus NCT02444546 | Pelareorep | Recurrent pediatric high grade CNS tumors | Phase I | Intravenous + GM-CSF | DLT were observed in the sixth patient, and the study was closed. No complete or partial responses were observed, and all patients experienced progression within 60 days. |
| Measles NCT02962167 | MV-NIS | Recurrent medulloblastoma or ATRT | Phase I | Intratumor or subarachnoid space | Data not published |
4.4. Limitations and Future Directions
5. Conclusions
Author Contributions
Funding
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- Wang, S.S.; Bandopadhayay, P.; Jenkins, M.R. Towards Immunotherapy for Pediatric Brain tumors. Trends Immunol. 2019, 40, 748–761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sampson, J.H.; Maus, M.V.; June, C.H. Immunotherapy for Brain tumors. J. Clin. Oncol. 2017, 35, 2450–2456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hwang, E.I.; Sayour, E.J.; Flores, C.T.; Grant, G.; Wechsler-Reya, R.; Hoang-Minh, L.B.; Kieran, M.W.; Salcido, K.; Prins, R.M.; Figg, J.W.; et al. The current landscape of immunotherapy for pediatric brain tumors. Nat. Cancer 2022, 3, 11–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- June, C.H.; Sadelain, M. Chimeric Antigen Receptor Therapy. N. Engl. J. Med. 2018, 379, 64–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Syrimi, E.; Bailey, S. What are CAR T-cells? Arch. Dis. Child. Educ. Pract. Ed. 2024, 109, 191–195. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patterson, J.D.; Henson, J.C.; Breese, R.O.; Bielamowicz, K.J.; Rodriguez, A. CAR T Cell therapy for pediatric brain tumors. Front. Oncol. 2020, 10, 1582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thomas, B.C.; Staudt, D.E.; Douglas, A.M.; Monje, M.; Vitanza, N.A.; Dun, M.D. CAR-T cell therapies for diffuse midline glioma. Trends Cancer 2023, 9, 791–804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dagher, O.K.; Posey, A.D. Forks in the road for CAR T and CAR NK cell cancer therapies. Nat. Immunol. 2023, 24, 1994–2007. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cappell, K.M.; Kochenderfer, J.N. Long-term outcomes following CAR T cell therapy: What we know so far. Nat. Rev. Clin. Oncol. 2023, 20, 359–371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maalej, K.M.; Merhi, M.; Inchakalody, V.P.; Mestiri, S.; Alam, M.; Maccalli, C.; Cherif, H.; Uddin, S.; Steinhoff, M.; Marincola, F.M.; et al. CAR-cell therapy in the era of solid tumor treatment: Current challenges and emerging therapeutic advances. Mol. Cancer 2023, 22, 20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Majzner, R.G.; Theruvath, J.L.; Nellan, A.; Heitzeneder, S.; Cui, Y.; Mount, C.W.; Rietberg, S.P.; Linde, M.H.; Xu, P.; Rota, C.; et al. CAR T cells targeting B7-H3, a Pan-cancer antigen, demonstrate potent preclinical activity against pediatric solid tumors and brain tumors. Clin. Cancer Res. 2019, 25, 2560–2574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vitanza, N.A.; Wilson, A.L.; Huang, W.; Siedel, K.; Brown, C.; Gustafson, J.A.; Yokoyama, J.K.; Johnson, A.J.; Baxter, B.A.; Koning, R.W.; et al. Intraventricular B7-H3 CAR T cells for Diffuse Intrinsic Pontine Glioma: Preliminary First-in-Human Bioactivity and Safety. Cancer Discov. 2023, 13, 114–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gust, J.; Cole, B.L.; Ronsley, R.; Wilson, A.L.; Seidel, K.; Wendler, J.; Pattabhi, S.; Brown, C.; Rawlings-Rhea, S.D.; Shtanukhina, N.; et al. Locoregional infusion of EGFR806-CAR T cells for recurrent or refractory pediatric CNS tumors: Results of the completed BrainChild02 phase 1 clinical trial. Neuro-Oncol. 2025, 27, 2170–2181. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Majzner, R.G.; Ramakrishna, S.; Yeom, K.W.; Patel, S.; Chinnasamy, H.; Schultz, L.M.; Richards, R.M.; Jiang, L.; Barsan, V.; Mancusi, R.; et al. GD2-CAR T cell therapy for H3K27M-mutated diffuse midline gliomas. Nature 2022, 603, 934–941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheresh, D.A.; Pierschbacher, M.D.; Herzig, M.A.; Mujoo, K. Disialogangliosides GD2 and GD3 are involved in the attachment of human melanoma and neuroblastoma cells to extracellular matrix proteins. J. Cell Biol. 1986, 102, 688–696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vitanza, N.A.; Johnson, A.J.; Wilson, A.L.; Brown, C.; Yokoyama, J.K.; Kunkele, A.; Chang, C.A.; Rawlings-Rhea, S.D.; Huang, W.; Seidel, K.; et al. Locoregional infusion of HER2-specific CAR T cells in children and young adults with recurrent or refractory CNS tumors: An interim analysis. Nat. Med. 2021, 27, 1544–1552. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, L.; Oill, A.T.; Blanchar, M.; Wu, M.; Hibbard, J.; Sepulveda, S.; Peter, L.; Kilpatrick, J.; Munoz, M.; Stiller, T.; et al. Expansion of endogenous T Cells in CSF of pediatric CNS tumor patients undergoing locoregional delivery of IL13Rα2-targeting CAR T cells: An interim analysis. Res. Sq. 2023, Preprint. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Foster, J.B.; Griffin, C.; Rokita, J.L.; Stern, A.; Brimley, C.; Rathi, K.; Lane, M.V.; Buongervino, S.N.; Smith, T.; Madsen, P.J.; et al. Development of GPC2-directed chimeric antigen receptors using mRNA for pediatric brain tumors. J. Immunother. Cancer 2022, 10, e004450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jin, L.; Ge, H.; Long, Y.; Yang, C.; Chang, Y.; Mu, L.; Sayour, E.J.; De Leon, G.; Wang, A.J.; Yang, J.C.; et al. CD70, a novel target of CAR T-cell therapy for gliomas. Neuro Oncol. 2018, 20, 55–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flieswasser, T.; Van den Eynde, A.; Audenaerde, J.V.; De Waele, J.; Lardon, F.; Riether, C.; de Haard, H.; Smits, E.; Pauwels, P.; Jacobs, J.; et al. The CD70-CD27 axis in Oncology: The new kids on the block. J. Exp. Clin. Cancer Res. 2022, 41, 12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akhavan, D.; Alizadeh, D.; Wang, D.; Weist, M.R.; Shepphird, J.K.; Brown, C.E. CAR T cells for brain tumors: Lessons learned and road ahead. Immunol. Rev. 2019, 290, 60–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahdi, J.; Dietrich, J.; Straathof, K.; Roddie, C.; Scott, B.J.; Davidson, T.B.; Prolo, L.M.; Batchelor, T.T.; Campen, C.J.; Davis, K.L.; et al. Tumor inflammation-associated neurotoxicity. Nat. Med. 2023, 29, 803–810. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ronsley, R.; Bertrand, K.C.; Song, E.Z.; Timpanaro, A.; Choe, M.; Tlais, D.; Vitanza, N.A.; Park, J.R. CAR T cell therapy for pediatric central nervous system tumors: A review of the literature and current North American Trials. Cancer Metastatic Rev. 2024, 43, 1205–1216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahdi, J.; Trivedi, V.; Monje, M. The promise of Immunotherapy for central nervous system tumors. Nat. Rev. Immunol. 2026, 26, 213–229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neelapu, S.S.; Tummala, S.; Kebriaei, P.; Wierda, W.; Gutierrez, C.; Locke, F.L.; Komanduri, K.V.; Lin, Y.; Jain, N.; Daver, N.; et al. Chimeric antigen receptor T-cell therapy-assessment and management of toxicities. Nat. Rev. Clin. Oncol. 2018, 15, 47–62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahdi, J.; Gust, J.A.; Vitanza, N.A.; Scott, B.; Monje, M.; Ronsley, R. Neurotoxicity in central nervous system tumors treated with CAR T cell therapy: A review. J. Neuro-Oncol. 2026, 176, 60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morris, E.C.; Neelapu, S.S.; Giavridis, T.; Sadelain, M. Cytokine release syndrome and associated neurotoxicity in cancer immunotherapy. Nat. Rev. Immunol. 2022, 22, 85–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, S.C.; Duffy, C.R.; Allison, J.P. Fundamental Mechanisms of Immune Checkpoint Blockade Therapy. Cancer Discov. 2018, 8, 1069–1086. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Geoerger, B.; Kang, H.J.; Yalon-Oren, M.; Marshall, L.V.; Vezina, C.; Pappo, A.; Laetsch, T.W.; Petrilli, A.S.; Ebinger, M.; Toporski, J.; et al. Pembrolizumab in paediatric patients with advanced melanoma or a PD-L1-positive, advanced, relapsed, or refractory solid tumour or lymphoma (KEYNOTE-051): Interim analysis of an open-label, single-arm, phase 1–2 trial. Lancet Oncol. 2020, 21, 121–133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gröbner, S.N.; Worst, B.C.; Weischenfeldt, J.; Buchhalter, I.; Kleinheinz, K.; Rudneva, V.A.; Johann, P.D.; Balasubramanian, G.P.; Segura-Wang, M.; Brabetz, S.; et al. The landscape of genomic alterations across childhood cancers. Nature 2018, 555, 321–327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bouffet, E.; Larouche, V.; Campbell, B.B.; Merico, D.; de Borja, R.; Aronson, M.; Durno, C.; Krueger, J.; Cabric, V.; Ramaswamy, V.; et al. Immune Checkpoint Inhibition for Hypermutant Glioblastoma Multiforme resulting from Germline Biallelic Mismatch Repair Deficiency. J. Clin. Oncol. 2016, 34, 2206–2211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, A.; Tabori, U.; Sambira Nahum, L.C.; Collins, N.B.; Deyell, R.; Dvir, R.; Faure-Conter, C.; Hassall, T.E.; Minturn, J.E.; Edwards, M.; et al. Efficacy of Nivolumab in Pediatric Cancers with High Mutation Burden and Mismatch Repair Deficiency. Clin. Cancer Res. 2023, 29, 4770–4783. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Campbell, B.B.; Galati, M.A.; Stone, S.C.; Riemenschneider, A.N.; Edwards, M.; Sudhaman, S.; Siddaway, R.; Komosa, M.; Nunes, N.M.; Nobre, L.; et al. Mutations in the RAS/MAPK Pathway Drive Replication Repair-Deficient Hypermutated Tumors and Confer Sensitivity to MEK Inhibition. Cancer Discov. 2021, 11, 1454–1467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Campbell, B.B.; Light, N.; Fabrizio, D.; Zatzman, M.; Fuligni, F.; de Borja, R.; Davidson, S.; Edwards, M.; Elvin, J.A.; Hodel, K.P.; et al. Comprehensive Analysis of Hypermutation in Human Cancer. Cell 2017, 171, 1042–1056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, A.; Sudhaman, S.; Morgenstern, D.; Coblentz, A.; Chung, J.; Stone, S.C.; Alsafwani, N.; Liu, Z.A.; Karsaneh, O.A.A.; Soleimani, S.; et al. Genomic predictors of response to PD-1 inhibition in children with germline DNA replication repair deficiency. Nat. Med. 2022, 28, 125–135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Touat, M.; Li, Y.Y.; Boynton, A.N.; Spurr, L.F.; Iorgulescu, J.B.; Bohrson, C.L.; Cortes-Ciriano, I.; Birzu, C.; Geduldig, J.E.; Pelton, K.; et al. Mechanisms and therapeutic implications of hypermutation in gliomas. Nature 2020, 580, 517–523. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fernandez, N.R.; Tabori, U. Mutation patterns drive mismatch repair-deficient glioma evolution. Nat. Genet. 2026, 58, 16–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, A.; Bianchi, V.; Edwards, M.; Varghese, N.; Sudhaman, S.; Farah, R. MBRS-54. Poor survival in replication repair deficient hypermutant medulloblastoma and CNS embryonal tumors: A report from the international RRD consortium. Neuro Oncol. 2020, 22, iii407. [Google Scholar] [CrossRef] [Scilit]
- Briggs, M.; Das, A.; Firth, H.; Levine, A.; Sánchez-Ramírez, S.; Negm, L.; Ercan, A.B.; Chung, J.; Bianchi, V.; Jalloh, I.; et al. Recurrent posterior fossa group A (PFA) ependymoma in a young child with constitutional mismatch repair deficiency (CMMRD). Neuropathol. Appl. Neurobiol. 2023, 49, e12862. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ausejo-Mauleon, I.; Labiano, S.; de la Nava, D.; Laspidea, V.; Zalacain, M.; Marrodán, L.; Garcia-Moure, M.; Gonzalez-Haurriz, M.; Hervas-Corpion, I.; Dhandapani, L.; et al. TIM-3 blockade in diffuse intrinsic pontine glioma models promotes tumor regression and antitumor immune memory. Cancer Cell 2023, 41, 1911–1926. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andrade, A.F.; Annett, A.; Karimi, E.; Topouza, D.G.; Rezanejad, M.; Liu, Y.; McNicholas, M.; Gonzalez Santiago, E.G.; Llivichuzhca-Loja, D.; Gehlhaar, A.; et al. Immune landscape of oncohistone-mutant gliomas reveals diverse myeloid populations and tumor-promoting function. Nat. Comm. 2024, 15, 7769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Monnikhof, M.; Schakelaar, M.Y.; Meulenbroeks, C.; Quist, M.; Perzolli, A.; Selten, A.; Koster, C.J.M.; Maassen, D.S.C.; Montoro Canelo, A.; Fredriks, M.; et al. Dual targeting of CD155/TIGIT and PD-L1/PD-1 immune checkpoints potentiate NK cell-mediated cytotoxicity in medulloblastoma. Neurooncol Adv. 2025, 7, vdaf099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levine, A.B.; Nobre, L.; Das, A.; Milos, S.; Bianchi, V.; Johnson, M.; Fernandez, N.R.; Stengs, L.; Ryall, S.; Ku, M.; et al. Immuno-oncologic profiling of pediatric brain tumors reveals major clinical significance of the tumor immune microenvironment. Nat. Comm. 2024, 15, 5790. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okada, H.; Weller, M.; Huang, R.; Finocchiaro, G.; Gilbert, M.R.; Wick, W.; Ellingson, B.M.; Hashimoto, N.; Pollack, I.F.; Brandes, A.A.; et al. Immunotherapy response assessment in neuro-oncology: A report of the RANO working group. Lancet Oncol. 2015, 16, e534–e542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wen, P.Y.; van den Bent, M.; Youssef, G.; Cloughesy, T.F.; Ellingson, B.M.; Weller, M.; Galanis, E.; Barboriak, D.P.; de Groot, J.; Gilbert, M.R.; et al. RANO 2.0: Update to the Response Assessment in Neuro-Oncology Criteria for High- and Low-Grade Gliomas in Adults. J. Clin. Oncol. 2023, 41, 5187–5199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ellingson, B.M.; Sanvito, F.; Cloughesy, T.F.; Huang, R.Y.; Villanueva-Meyer, J.E.; Pope, W.B.; Barboriak, D.P.; Shankar, L.K.; Smits, M.; Kaufman, T.J.; et al. A Neuroradiologist’s Guide to Operationalizing the Response Assessment in Neuro-Oncology (RANO) Criteria Version 2.0 for Gliomas in Adults. AJNR Am. J. Neuroradiol. 2024, 45, 1846–1856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yenidogan, I.; Tabori, U.; Das, A. Immune Checkpoint Inhibitors in pediatric central nervous system tumors: Biology, clinical experience, and translational pathways to precision immunotherapy. J. Neurooncol. 2026, 177, 27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, A.; Fernandez, N.R.; Levine, A.; Bianchi, V.; Stengs, L.K.; Chung, J.; Negm, L.; Dimayacyac, J.R.; Chang, Y.; Nobre, L.; et al. Combined Immunotherapy improves outcome for replication-repair-deficient (RRD) High-Grade glioma failing anti-PD-1 monotherapy: A report from the international RRD consortium. Cancer Discov. 2024, 14, 258–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gikandi, A.; Chi, S.N.; Yeo, K.K.; O’Neill, A.F.; Shulman, D.S.; Dubois, S.G.; Collins, N.B. Off-label prescribing of immune checkpoint inhibitor therapy at a single pediatric cancer center. Cancer Med. 2024, 13, e7154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blumenthal, D.T.; Yalon, M.; Vainer, G.W.; Lossos, A.; Yust, L.; Tzach, L.; Cagnano, E.; Limon, D.; Bokstein, F. Pembrolizumab: First experience with recurrent primary central nervous system (CNS) tumors. J. Neuro-Oncol. 2016, 129, 453–460. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gorsi, H.S.; Malicki, D.M.; Barsan, V.; Tumblin, M.; Yeh-Nayre, L.; Milburn, M.; Elster, J.D.; Crawford, J.R. Nivolumab in the treatment of recurrent or refractory pediatric brain tumors: A single institutional experience. J. Pediatr. Hematol. Oncol. 2019, 41, e235–e241. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cacciotti, C.; Choi, J.; Alexandrescu, S.; Zimmerman, M.A.; Cooney, T.M.; Chordas, C.; Clymer, J.; Chi, S.; Yeo, K.K. Immune checkpoint inhibition for pediatric patients with recurrent/refractory CNS tumors: A single institution experience. J. Neuro-Oncol. 2020, 149, 113–122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kline, C.; Liu, S.J.; Duriseti, S.; Banerjee, A.; Nicolaides, T.; Raber, S.; Gupta, N.; Haas-Kogan, D.; Braunstein, S.; Mueller, S. Reirradiation and PD-1 inhibition with nivolumab for the treatment of recurrent diffuse intrinsic pontine glioma: A single institution experience. J. Neuro-Oncol. 2018, 140, 629–638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- AlHarbi, M.; Mobark, N.A.; AlMubarak, L.; Aljelaify, R.; Alsaeed, M.; Almutairi, A.; Alqubaishi, F.; Hussain, M.E.; O Balbaid, A.A.; Marie, A.S.; et al. Durable response to nivolumab in a pediatric patient with refractory Glioblastoma and constitutional biallelic mismatch repair deficiency. Oncologist 2018, 23, 1401–1406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Henderson, J.J.; Das, A.; Morgenstern, D.A.; Sudhaman, S.; Bianchi, V.; Chung, J.; Negm, L.; Edwards, M.; Kram, D.E.; Osborn, M.; et al. Immune checkpoint inhibition as single therapy for synchronous cancers exhibiting hypermutation: An IRRDC study. JCO Precis. Oncol. 2022, 6, e2100286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jhawar, S.R.; Thandoni, A.; Bommareddy, P.K.; Hassan, S.; Kohlhapp, F.J.; Goyal, S.; Schenkel, J.M.; Silk, A.W.; Zloza, A. Oncolytic viruses- natural and genetically engineered cancer immunotherapies. Front. Oncol. 2017, 7, 295393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strong, J.E.; Coffey, M.C.; Tang, D.; Sabinin, P.; Lee, P.W. The molecular basis of viral oncolysis: Usurpation of the Ras signaling pathway by reovirus. EMBO J. 1998, 17, 3351–3362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bulstrode, H.; Girdler, G.C.; Gracia, T.; Aivazidis, A.; Moutsopoulos, I.; Young, A.M.H.; Hancock, J.; He, X.; Ridley, K.; Xu, Z.; et al. Myeloid cell interferon secretion restricts Zika flavivirus infection of developing and malignant human neural progenitor cells. Neuron 2022, 110, 3936–3951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suzuki, K.; Fueyo, J.; Krasnykh, V.; Reynolds, P.N.; Curiel, D.T.; Alemany, R. A conditionally replicative adenovirus with enhanced infectivity shows improved oncolytic potency. Clin. Cancer Res. 2001, 7, 120–126. [Google Scholar] [PubMed]
- Kawai, T.; Akira, S. Toll-like receptors and their crosstalk with other innate receptors in infection and immunity. Immunity 2011, 34, 637–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loré, K.; Betts, M.R.; Brenchley, J.M.; Kuruppu, J.; Khojasteh, S.; Perfetto, S.; Roederer, M.; Seder, R.A.; Koup, R.A. Toll-like receptor ligands modulate dendritic cells to augment cytomegalovirus- and HIV-1-specific T cell responses. J. Immunol. 2003, 171, 4320–4328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garcia-Moure, M.; Gonzalez-Huarriz, M.; Labiano, S.; Guruceaga, E.; Bandres, E.; Zalacain, M.; Marrodan, L.; de Andrea, C.; Vilalba, M.; Martinez-Velez, N.; et al. Delta-24-RGD, an oncolytic adenovirus, increases survival and promotes proinflammatory immune landscape remodeling in models of AT/RT and CNS-PNET. Clin. Cancer Res. 2021, 27, 1807–1820. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ribas, A.; Dummer, R.; Puzanov, I.; VanderWalde, A.; Andtbacka, R.H.I.; Michielin, O.; Olszanski, A.J.; Malvehy, J.; Cebon, J.; Fernandez, E.; et al. Oncolytic virotherapy promotes intratumoral T cell infiltration and improves anti-PD-1 immunotherapy. Cell 2017, 170, 1109–1119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gujar, S.; Pol, J.G.; Kroemer, G. Heating it up: Oncolytic viruses make tumors “hot” and suitable for checkpoint blockade immunotherapies. Oncoimmunology 2018, 7, e1442169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Puigdelloses, M.; Garcia-Moure, M.; Labiano, S.; Laspidea, V.; Gonzalez-Haurriz, M.; Zalacain, M.; Marrodan, L.; Martinez-Velez, N.; De la Nava, D.; Ausejo, I.; et al. CD137 and PD-L1 targeting immuno-virotherapy induces a potent and durable antitumor immune response in glioblastoma models. J. ImmunoTher. Cancer 2021, 9, e002644. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ghajar-Rahimi, G.; Kang, K.D.; Totsch, S.K.; Gary, S.; Rocco, A.; Blitz, S.; Kachurak, K.; Chamber, M.R.; Li, R.; Beierle, E.A.; et al. Clinical advances in oncolytic virotherapy for pediatric brain tumors. Pharm. Ther. 2022, 23, 108193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Whitley, R.J.; Kern, E.R.; Chatterjee, S.; Chou, J.; Roizman, B. Replication, establishment of latency, and induced reactivation of herpes simplex virus gamma 1 34.5 deletion mutants in rodent models. J. Clin. Investig. 1993, 91, 2837–2843. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mineta, T.; Rabkin, S.D.; Yazaki, T.; Hunter, W.D.; Martuza, R.L. Attenuated multi-mutated herpes simplex virus-1 for the treatment of malignant gliomas. Nat. Med. 1995, 1, 938–943. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Todo, T.; Martuza, R.L.; Rabkin, S.D.; Johnson, P.A. Oncolytic herpes simplex virus vector with enhanced MHC class I presentation and tumor cell killing. Proc. Natl. Acad. Sci. USA 2001, 98, 6396–6401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coen, D.; Goldstein, D.; Weller, S. Herpes simplex virus ribonucleotide reductase mutants are hypersensitive to acyclovir. Antimicrob. Agents Chemother. 1989, 33, 1395–1399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patel, D.M.; Foreman, P.M.; Nabors, L.B.; Riley, K.O.; Gillespie, G.Y.; Markert, J.M. Design of Phase I Clinical Trial to Evaluate M032, a Genetically Engineered HSV-1 Expressing IL-12, in Patients with Recurrent/Progressive Glioblastoma Multiforme, Anaplastic Astrocytoma, or Gliosarcoma. Hum. Gene Ther. Clin. Dev. 2016, 27, 69–78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bernstock, J.D.; Vicario, N.; Li, R.; Nan, L.; Totsch, S.K.; Schlappi, C.; Gessler, F.; Han, X.; Parenti, R.; Beierle, E.A.; et al. Safety and efficacy of oncolytic HSV-1 G207 inoculated into the cerebellum of mice. Cancer Gene Ther. 2020, 27, 246–255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, G.K.; Langford, C.P.; Coleman, J.M.; Cassady, K.A.; Parker, J.N.; Markert, J.M.; Yancey Gillespie, G. Engineered herpes simplex viruses efficiently infect and kill CD133+ human glioma xenograft cells that express CD111. J. Neurooncol. 2009, 95, 199–209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, G.K.; Moore, B.P.; Nan, L.; Kelly, V.M.; Etminan, T.; Langford, C.P.; Xu, H.; Han, X.; Markert, J.M.; Beierle, E.A.; et al. Pediatric medulloblastoma xenografts including molecular subgroup 3 and CD133+ and CD15+ cells are sensitive to killing by oncolytic herpes simplex viruses. Neuro Oncol. 2016, 18, 227–235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, G.K.; Bernstock, J.D.; Chen, D.; Nan, L.; Moore, B.P.; Kelly, V.M.; Youngblood, S.L.; Langford, C.P.; Han, X.; Ring, E.K.; et al. Enhanced Sensitivity of Patient-Derived Pediatric High-Grade Brain Tumor Xenografts to Oncolytic HSV-1 Virotherapy Correlates with Nectin-1 Expression. Sci. Rep. 2018, 8, 13930. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Studebaker, A.W.; Hutzen, B.J.; Pierson, C.R.; Haworth, K.B.; Cripe, T.P.; Jackson, E.M.; Leonard, J.R. Oncolytic Herpes Virus rRp450 Shows Efficacy in Orthotopic Xenograft Group 3/4 Medulloblastomas and Atypical Teratoid/Rhabdoid Tumors. Mol. Ther. Oncolytics 2017, 6, 22–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fueyo, J.; Alemany, R.; Gomez-Manzano, C.; Fuller, G.N.; Khan, A.; Conrad, C.A.; Liu, T.J.; Jiang, H.; Lemoine, M.G.; Suzuki, K.; et al. Preclinical characterization of the antiglioma activity of a tropism-enhanced adenovirus targeted to the retinoblastoma pathway. J. Natl. Cancer Inst. 2003, 95, 652–660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinez-Velez, N.; Garcia-Moure, M.; Marigil, M.; Gonzalez-Huarriz, M.; Puigdelloses, M.; Perez- Larraya, G.J.; Zalacain, M.; Marrodan, L.; Varela-Garruceaga, M.; Laspidea, V.; et al. The oncolytic virus Delta-24- RGD elicits an antitumor effect in pediatric glioma and DIPG mouse models. Nat. Commun. 2019, 10, 2235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinez-Velez, N.; Marigil, M.; Garcia-Moure, M.; Gonzalez-Huarriz, M.; Aristu, J.J.; Ramos-Garcia, L.I.; Tejada, S.; Diez-Valle, R.; Patino-Garcia, A.; Becher, O.J.; et al. Delta-24-RGD combined with radiotherapy exerts a potent anti-tumor effect in diffuse intrinsic pontine glioma and pediatric high grade glioma models. Acta Neuropathol. Commun. 2019, 7, 64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garcia-Moure, M.; Martinez-Velez, N.; Gonzalez-Huarriz, M.; Marradan, L.; Cascallo, M.; Alemany, R.; Patino-Garcia, A.; Alonso, M.M. The oncolytic adenovirus VCN-01 promotes anti-tumor effect in primitive neuroectodermal tumor models. Sci. Rep. 2019, 9, 14368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chastkofsky, M.I.; Pituch, K.C.; Katagi, H.; Zannikou, M.; Ilut, L.; Xiao, T.; Han, Y.; Sonabend, A.M.; Curiel, D.T.; Bonner, E.R.; et al. Mesenchymal stem cells successfully deliver oncolytic virotherapy to diffuse intrinsic pontine glioma. Clin. Cancer Res. 2020, 27, 1766–1777. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thompson, E.M.; Brown, M.; Dobrikova, E.; Ramaswamy, V.; Taylor, M.D.; McLendon, R.; Sanks, J.; Chandramohan, V.; Bigner, D.; Gromeier, M. Poliovirus receptor (CD155) expression in pediatric brain tumors mediates oncolysis of medulloblastoma and pleomorphic xanthoastrocytoma. J. Neuropathol. Exp. Neurol. 2018, 77, 696–702. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coffey, M.C.; Strong, J.E.; Forsyth, P.A.; Lee, P.W.K. Reovirus therapy of tumors with activated ras pathway. Science 1998, 282, 1332–1334. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Studebaker, A.W.; Hutzen, B.; Pierson, C.R.; Russel, S.J.; Galanis, E.; Raffel, C. Oncolytic measles virus prolongs survival in a murine model of cerebral spinal fluid disseminated medulloblastoma. Neuro Oncol. 2012, 14, 459–470. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Studebaker, A.W.; Hutzen, B.; Pierson, C.R.; Shaffer, T.A.; Raffel, C.; Jackson, E.M. Oncolytic measles virus efficacy in murine xenograft models of atypical teratoid rhabdoid tumors. Neuro Oncol. 2015, 17, 1568–1577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, J.M.; Johnston, J.M.; Bag, A.K.; Bernstock, J.D.; Li, R.; Aban, I.; Kachurak, K.; Nan, L.; Kang, K.D.; Totsch, S.; et al. GYG. Oncolytic HSV-1 G207 immunovirotherapy for pediatric high- grade gliomas. N. Engl. J. Med. 2021, 384, 1613–1622. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gallego Pérez-Larraya, J.; Garcia-Moure, M.; Labiano, S.; Patino-Garcia, A.; Dobbs, J.; Gonzalez-Haurriz, M.; Zalacain, M.; Marrodan, L.; Martinez-Velez, N.; Puigdelloses, M.; et al. Oncolytic DNX- 2401 virus for pediatric diffuse intrinsic pontine glioma. N. Engl. J. Med. 2022, 386, 2471–2481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Velammal, P.N.K.P.; Dhasakeerthi, T.; Varghese, J.R.; Agrawal, M.; Veluswami, K.; Manickavelan, H.V.; Srinivasan, G. The effect of oncolytic virotherapy on pediatric brain tumor- a systematic review. Childs Nerv. Syst. 2025, 41, 315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thompson, E.M.; Landi, D.; Brown, M.C.; Friedman, H.S.; McLendon, R.; Herndon, J.E.; Buckley, E.; Bolognesi, D.P.; Lipp, E.; Schroeder, K.; et al. Recombinant polio–rhinovirus immunotherapy for recurrent pediatric high-grade glioma: A phase 1b trial. Lancet Child Adolesc. Health 2023, 7, 471–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
| Antigen | Brain Tumor Expression | Expression in Normal Tissue | Function | References |
|---|---|---|---|---|
| B7-homolog 3 protein (B7-H3)-CD276 | HGG, DMG, MBL | Expressed in normal tissues- lung, liver, bladder, testis and lymphoid organs | Increased expression contributes to tumor immune evasion, metastatic potential, poor prognosis | [11,12] |
| Epidermal Growth Factor Receptor (EGFR)-EGFR806 | HGG, DMG, EPN, MBL, ATRT | EGFRvIII is restricted to GBM | Cell surface receptor, regulate cell growth, survival, migration. | [13] |
| Disialoganglioside 2 (GD2) | DMG, HGG | Brain, Peripheral nerves, skin (melanocytes) | Cell–Cell attachment to fibronectin | [14,15] |
| ERBB2 receptor tyrosine kinase (HER2) | GBM, EPN, MBL | Epithelial tissue, skin, muscle | Cell cycle homeostasis. | [16] |
| Interleukin 13 receptor subunit α2(IL-13Rα2) | HGG, GBM, MBL | Testis | Apoptosis escape mechanism | [17] |
| Glypican 2(GPC2) | ETMR, MBL, CNS-ET, CPC, HGG, DMG | Testis, skin | Surface oncoprotein | [18] |
| CD70 | HGG, GBM | Activated B, T cells NK and Dendritic cells | Increased expression promotes stemness, invasion, migration. | [19,20] |
| Clinical Trial Number (NCT#) | Title | Phase | Target | Delivery | Eligible Tumors | Status |
|---|---|---|---|---|---|---|
| 06221553 | Safety and Efficacy of Loco-regional B7H3 IL-7Ra CAR T Cell in DIPG (CMD03DIPG) | 1 | B7H3 | ICV | DMG (DIPG) | Recruiting |
| 06946680 | IL-8 Receptor-modified CD70 CAR T Cell Therapy in CD70+ Pediatric High-grade Glioma (HGG) (IMPACT) | 1 | CD70 | IV | pHGG | Recruiting |
| 04099797 | C7R-GD2.CAR T Cells for Patients with GD2-expressing Brain Tumors (GAIL-B) | 1 | GD2 | IV, ICV | DMG, HGG, MBL, ATRT, EPN | Recruiting |
| 05298995 | GD2-CAR T Cells for Pediatric Brain Tumors | 1 | GD2 | IV | HGG, DMG, MBL, ATRT | Recruiting |
| 07087002 | GPC2-CAR T Cell Therapy for Relapsed or Refractory Medulloblastoma in Children and Young Adults | 1 | GPC2 | ICV | MBL, ATRT, ETMR, CNS-ET, Pineoblastoma | Recruiting |
| 04510051 | CAR T Cells After Lymphodepletion for the Treatment of IL13Rα2 Positive Recurrent or Refractory Brain Tumors in Children | 1 | IL-13Rα2 | ICV | HGG, GBM, MBL | Recruiting |
| 04661384 | Brain Tumor-Specific Immune Cells (IL13Ralpha2-CAR T Cells) for the Treatment of Leptomeningeal Glioblastoma, Ependymoma, or Medulloblastoma | 1 | IL-13Rα2 | ICV | Leptomeningeal GBM, MBL, EPN | Active, Not recruiting |
| 05768880 | Study of B7-H3, EGFR806, HER2, And IL13-Zetakine (Quad) CAR T Cell Locoregional Immunotherapy for Pediatric Diffuse Intrinsic Pontine Glioma, Diffuse Midline Glioma, And Recurrent or Refractory Central Nervous System Tumors | 1 | B7-H3, EGFR806, HER2, and IL-13-zetakine | ICV | DIPG, DMG, recurrent/refractory brain tumors | Recruiting |
| ACTRN12622000675729 (*) | A Phase I Study of the Safety of Autologous GD2-Specific Chimeric Antigen Receptor-Expressing T Cells in Children with Diffuse Midline Glioma | 1 | GD2 | IV | DMG, DIPG, HGG | Recruiting |
| Trial/Study (NCT) | Phase | Tumor Types | Agent(s) | Efficacy | Status |
|---|---|---|---|---|---|
| NCT02332668 2015–2027 | Phase I/II | Advanced melanoma; PD-L1+ relapsed/refractory solid tumors and lymphoma; small subset with CNS involvement | Pembrolizumab | A separate MSI-H cohort of KEYNOTE-51 enrolled 7 pediatric patients (6 with CNS malignancies), one HGG patient achieved durable complete response after initial progression (at cycle 6, maintained cycle 20) | Ongoing long-term follow-up |
| NCT02359565 2015–2025 | Phase I | High-Grade CNS tumors | Pembrolizumab | Early results-2018 ISPNO: 5 patients with DIPG progressed more rapidly than historical controls with a median PFS of 1 month, prompting an amendment to the study to exclude recurrent DIPG. | Completed, results not posted |
| NCT02541604 2015–2019 | Phase 1/2 | Solid Tumors | Atezolizumab | 4 of ~87 (about 5%) achieved even a partial response by 6 months | Completed; contributes pharmacokinetic and biomarker data for pediatric atezolizumab |
| NCT02793466 2016–2023 | Phase I | Solid Tumors, Lymphoma | Durvalumab monotherapy ± chemotherapy/RT in disease- and age-defined cohorts | 3 of 5 ependymoma patients had clinical benefit and one achieved a formal RECIST partial response | Completed, supports further biology-driven studies rather than broad use |
| NCT02992964 2017–2023 | Phase 1/2 | Hypermutant solid and CNS tumors | Nivolumab | Response rate rose from 20% at first assessment to 50% with longer follow-up, and 4 patients—3 with malignant glioma—remained in complete remission at a median 37 months | Completed, reinforces TMB/MMRd as the operative selection criterion |
| NCT03130959 2017–2022 | Phase 1b/2 | High-grade CNS tumors | Nivolumab monotherapy vs. nivolumab + ipilimumab | Median OS in newly diagnosed DIPG was 11.7 months (nivolumab) and 10.8 months (combination) | Completed; negative trial for unselected pediatric CNS tumors; informs design of biomarker-enriched studies |
| NCT04323046 2020–2029 | Phase 1 | Recurrent/ progressive CNS tumors | PD-1/PD-L1-based immunotherapy regimen before/after Surgery | Results pending | Ongoing; will clarify role of next-generation PD-1/PD-L1 strategies in pediatric CNS tumors |
| Registry and Cohort Studies | |||||
| Study | Phase | Tumor types | Agent(s) | Efficacy | Status |
| Das e al. 2022 [35] | International Consortium Registry Study | MMRD and PPD cancers | Nivolumab, Pembrolizumab | 41.4% 3-year survival (n = 45); TMB and MS-indel burden predict response via distinct mechanisms | Supports further biology-driven studies |
| Das et al. 2024 RRD-HGG multinational cohort [48] | Retrospective multicenter cohort | RRD HGG | PD-1 inhibitor + RT/CTLA-4 inhibitor/MEK inhibitor | 11.6-month post-progression survival (n = 38, p < 0.001) | Supports reirradiation continuing ICI-based salvage after first-line ICI fails |
| Gikandi et al. 2024 mixed pediatric CNS ICI cohort [49] | Retrospective single-/multicenter series | Hematologic malignancies, solid tumors and CNS tumors | Nivolumab/pembrolizumab ± combinations (e.g., bevacizumab, RT, chemotherapy) | irAE occurrence was associated with significantly improved progression-free survival | Supports that unselected pediatric CNS tumors rarely derive major benefit from ICI |
| Case Reports | |||||
| Study | Phase | Tumor types (strata) | Agent(s)/Schema | Efficacy | Status |
| Blumenthal et al. 2016 early PD-1 experience [50] | 5 pediatric patients with recurrent CNS tumors | 2 diffuse brainstem gliomas, 1 GB, 1 ATRT, 1 medulloblastoma. | Pembrolizumab ± bevacizumab | 5 children treated with pembrolizumab, all had progressive disease; median OS was only 3.2 months in children—prompting the authors to explicitly advise against further unselected use | Negative for unselected patients |
| Gorsi et al. 2019 [51] | Retrospective; 10 pediatric patients | 5 HGG, 1 LGG, 1 pineoblastoma, 1 medulloblastoma, 1 ependymoma, 1 CNS embryonal tumor NOS | Nivolumab | Among 10 nivolumab-treated patients, 3 had partial responses at the primary site | Negative in unselected, heavily pretreated pediatric brain tumors, with different median survival by PD-L1 status despite a very low median TMB of 1.3 mut/Mb |
| Cacciotti et al. 2020 (11-patient series) [52] | Retrospective series; 11 pediatric patients | DIPG [2], HGG [5], ependymoma [1], craniopharyngioma [1], high-grade neuroepithelial tumor (HGNET) [1], and NGGCT/choriocarcinoma [1] | Ipilimumab, nivolumab, pembrolizumab | In 11 patients iRANO-based responses were 3 PR, 7 SD, 1 PD, with 2 durable responders; treatment stopped for progression in 7 and for toxicity in only 2 | Completed; exploratory signal that biology-enriched subsets may respond |
| Kline et al. 2018 DIPG nivolumab ± re-irradiation [53] | Retrospective single-institution cohort; recurrent DIPG after initial RT | 31 pediatric DIPG at recurrence after initial RT (8 re-irradiation + nivolumab, 4 re-irradiation alone, 19 historical RT-only) DIPG | Concurrent re-irradiation with nivolumab followed by maintenance nivolumab vs. re-irradiation alone vs. RT-only historical cohort | Median OS was 22.9 months with reirradiation plus nivolumab vs. 20.4 months with reirradiation alone vs. 8.3 months with neither | Supports feasibility and safety of combining PD-1 blockade with re-irradiation |
| AlHarbi et al. 2018 [54] | Single-patient case report | supratentorial glioblastoma (WHO grade IV), CMMRD-associated | Nivolumab monotherapy | A 5-year-old female with CMMRD with 60% tumor shrinkage on nivolumab with no adverse reactions through 10 months, remaining fully ambulatory with a normal neurologic exam. | Supports germline MMRd can have ICI sensitivity |
| Henderson et al. 2022 ICI for Synchronous Hypermutated Cancers [55] | Two patients with synchronous, progressive, and metastatic malignancies | GBM + rectal adenocarcinoma Grade 3 Astrocytoma + Transitional cell carcinoma | Pembrolizumab, Nivolumab | Prolonged survival | Demonstrates the efficacy of immunotherapy as a rational approach for patients with CMMRD and synchronous cancers |
| Viral Platform | Representative Constructs | Key Genetic Modifications | Mechanism of Tumor Selectivity | Preclinical Evidence in Pediatric Brain Tumors |
|---|---|---|---|---|
| Herpes Simplex Virus (HSV-1) [66,67,68,69,70,71,72,73,74,75] | G207, HSV1716, rRp450, rQNestin, G47Delta, M032 and C134 | γ134.5 deletion; UL39 inactivation; α47 deletion; cytokine transgene insertion (e.g., IL-12) | Replicates in tumor cells with impaired antiviral responses; enhanced antigen presentation and immune activation | Models of pediatric high-grade glioma, DIPG, MBL, and ATRT |
| Adenovirus [62,76,77,78,79,80,81] | DNX-2401 (Δ24-RGD), CRAd-S-pK7, ICOVIR17K, | E1A deletion targeting RB pathway; arginine-glycine-aspartate (RGD) peptide fiber modification to enhance integrin binding | Selective replication in RB-deficient tumor cells; improved tumor cell entry via integrin receptors | Demonstrated antitumor activity in ATRT and CNS-PNET xenograft models; MSC-mediated delivery explored in DIPG models, pediatric high-grade glioma, DIPG, ETMR |
| Poliovirus [82] | PVSRIPO (PV (Sabin)-Rhinovirus IRES PV Open reading frame) (Lerapolturev) | Recombinant poliovirus targeting CD155 receptor | Targets CD155 receptor | Medulloblastoma, PXA, ATRT, PNET |
| Reovirus [83] | Pelareorep | Naturally occurring oncolytic RNA virus | Preferential replication in tumors with activated Ras signaling | MBL |
| Measles Virus [84,85] | MV-CEA (human carcinoembryonic antigen), MV-NIS (sodium iodide symporter) | Engineered measles strains expressing reporter or therapeutic genes | Utilizes CD46 receptor overexpressed in tumor cells | MBL, ATRT |
| Vaccinia Virus | ddVV (double-deleted modified version of Vaccina virus) | Deletion of thymidine kinase (TK) and vaccinia grow factor (VGF) genes | Replicates preferentially in tumors with dysregulated signaling pathways | ATRT |
| Myxoma Virus | Exploits defects in antiviral signaling pathways | Selective infection of tumor cells with impaired antiviral responses | MBL |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Yenidogan, I.; Thacker, N.; Das, A.; Vanan, M.I. Cellular and Immunotherapy for Pediatric Brain Tumors: A Primer. Curr. Oncol. 2026, 33, 522. https://doi.org/10.3390/curroncol33090522
Yenidogan I, Thacker N, Das A, Vanan MI. Cellular and Immunotherapy for Pediatric Brain Tumors: A Primer. Current Oncology. 2026; 33(9):522. https://doi.org/10.3390/curroncol33090522
Chicago/Turabian StyleYenidogan, Irem, Nirav Thacker, Anirban Das, and Magimairajan Issai Vanan. 2026. "Cellular and Immunotherapy for Pediatric Brain Tumors: A Primer" Current Oncology 33, no. 9: 522. https://doi.org/10.3390/curroncol33090522
APA StyleYenidogan, I., Thacker, N., Das, A., & Vanan, M. I. (2026). Cellular and Immunotherapy for Pediatric Brain Tumors: A Primer. Current Oncology, 33(9), 522. https://doi.org/10.3390/curroncol33090522