Article

Reclassification of BRCA2 Variants of Uncertain Significance Using Saturation Genome Editing Combined with Clinical Phenotypes in Breast Cancer


Familial & Hereditary Cancer Center, Key Laboratory of Carcinogenesis and Translational Research (Ministry of Education/Beijing), Peking University Cancer Hospital & Institute, Beijing 100142, China
*
Authors to whom correspondence should be addressed.
Curr. Oncol. 2026, 33(9), 521; https://doi.org/10.3390/curroncol33090521
Submission received: 27 May 2026 / Revised: 14 August 2026 / Accepted: 22 August 2026 / Published: 31 August 2026
(This article belongs to the Section Breast Cancer)

Simple Summary

Genetic testing for breast cancer often finds changes in the BRCA2 gene that have unknown effects, making it difficult to guide patient management. In this study of 15,092 breast cancer patients, we used published saturation genome editing (SGE) results, combined with clinical and family history data, to assess 88 uncertain variants in exons 15–26 of BRCA2. We found that 15 variants were functionally pathogenic and associated with stronger family histories of cancer, particularly breast and ovarian cancers, whereas 66 variants were functionally benign. These findings suggest that combining SGE with patient characteristics can improve BRCA2 variant interpretation. This approach may support future genetic counseling, cancer risk assessment, and variant classification guidelines, although further validation in larger and more diverse populations is needed.

Abstract

Purpose: To evaluate the pathogenicity of BRCA2 variants of uncertain significance (VUS) located within the functionally critical exons 15–26 using published SGE data, and to reclassify these VUS by integrating clinical phenotypes. Methods: A total of 15,092 breast cancer patients were enrolled in this study, among which 457 distinct BRCA2 VUS were identified in 1051 carriers. Based on SGE scores, 88 BRCA2 VUSs within exons 15–26 were functionally assessed and carriers reclassified as functionally pathogenic, functionally benign, or remaining VUS. Clinicopathological characteristics were subsequently compared across variant groups. Results: Of these 88 evaluated BRCA2 VUSs (187 carriers), 15 were reclassified as functionally pathogenic (20 carriers), 66 as functionally benign (154 carriers), and 7 remained VUS (13 carriers). Compared with non-carriers, carriers with functionally pathogenic variants exhibited a significantly higher prevalence of a family history of any cancer (65.0% vs. 31.1%, p = 0.002), particularly breast and/or ovarian cancer (35.0% vs. 10.0%, p = 0.002), as well as a trend toward a higher incidence of bilateral breast cancer (10.0% vs. 2.4%, p = 0.085). In contrast, individuals harboring functionally benign variants demonstrated clinicopathological characteristics similar to non-carriers. Conclusion: SGE-based functional scoring system provides a reliable approach for reclassifying BRCA2 VUS. When integrated with clinical phenotypes, it enhanced the accuracy of pathogenicity assessment.

1. Introduction

BRCA2 is a well-established breast cancer (BC) susceptibility gene that plays a critical role in DNA damage repair [1,2,3]. It encodes an essential component of the homologous recombination pathway, which mediates the repair of DNA double-strand breaks and maintains genomic stability [4,5]. Pathogenic germline variants in BRCA2 significantly increase the risk of breast cancer and represent a major genetic cause of hereditary breast cancer [6,7,8,9,10]. Notably, patients with BRCA-deficient tumors often benefit from poly (ADP-ribose) polymerase (PARP) inhibitors [11,12,13]. Therefore, accurate classification of BRCA2 variants is essential for risk assessment, individualized treatment selection, and clinical management, including genetic counseling [14,15,16].
As genetic testing becomes widely applied, an increasing number of BRCA2 variants of uncertain significance (VUS) are being identified [17,18]. This uncertainty greatly limits their clinical utility and complicates evidence-based decision-making [19]. According to the ClinVar database, 13,201 single-nucleotide variants (SNVs) have been reported in BRCA2, of which approximately 59% are categorized as variants of uncertain significance [20]. Recently, saturation genome editing (SGE) has been applied to systematically evaluate more than 6000 variants within the functionally critical regions encoded by using SGE functional scores from those studies [20,21]. This high-throughput functional approach provides an objective framework for resolving the clinical ambiguity of BRCA2 VUS and offering a promising strategy [21].
In the present study, we reclassified BRCA2 VUS identified in a large hospital-based breast cancer cohort using SGE functional scores. By integrating comprehensive clinicopathological data, we further characterized the clinical features of patients harboring reclassified functionally pathogenic variants, in comparison with non-carriers and carriers of known pathogenic BRCA2 variants.

2. Materials and Methods

2.1. Patients and Sequencing Data

Data from a total of 15,092 patients treated at Peking University Cancer Hospital were included in this study, consisting of 13,781 consecutive breast cancer patients from October 2003 to November 2018, and 1311 breast cancer patients from December 2018 to August 2021. All patients underwent BRCA2 variant screening using Sanger sequencing and/or multigene panel sequencing [22]. Products were sequenced on a HiSeq 2500 (Illumina, San Diego, CA, USA) to at least an average depth of 200-fold coverage (BGI Genomics Co., Ltd., Beijing, China or Novogene Co., Ltd., Beijing, China). Variants were annotated in accordance with the Human Genome Variation Society (HGVS) nomenclature guidelines, based on the National Center for Biotechnology Information (NCBI) reference sequence NM_000059.4 [23,24]. Family history and clinicopathological data were obtained through telephone interviews and/or extracted from medical records. This study was approved by the Research and Ethical Committee of Peking University Cancer Hospital, and written informed consent was obtained from all participants.

2.2. Variant Classification

Following the guidelines of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology (ACMG/AMP) [25], we systematically classified BRCA2 variants from 15,092 patients. Truncating variants (nonsense and frameshift variants) were classified as pathogenic only if they were predicted to undergo nonsense-mediated mRNA decay (NMD), consistent with ACMG/AMP PVS1 criteria. All other variants were considered pathogenic or likely pathogenic based on ClinVar database (http://www.ncbi.nlm.nih.gov/clinvar/, accessed on 30 May 2025) and/or reports the literature. Variants categorized as benign or likely benign in ClinVar were classified as benign. All remaining variants were considered variants of uncertain significance (VUSs). Patients carrying more than one variant were assigned to the highest-risk category according to the most clinically consequential alteration. For statistical analysis, non-carriers were defined as individuals with benign/likely benign variants or no identified variants whatsoever.

2.3. Variants Reclassification by Saturation Genome Editing

The pathogenicity of BRCA2 VUSs identified in this cohort of breast cancer patients was evaluated using functional scores derived from saturation genome editing (SGE), as previously reported [20,21]. To ensure analytical rigor, a variant was classified as functionally pathogenic only if concordant pathogenic classifications were obtained from two independent SGE studies of BRCA2. Similarly, a variant was classified as functionally benign only if both studies consistently indicated a benign functional impact. Variants with discordant classifications between the two studies were retained as variants of uncertain significance (VUS). For variants reclassified in only one study and not evaluated in the other, the available classification result was used.

2.4. Definition of Variable

Definitions of study variables, including family history of malignant tumor, family history of breast cancer, tumor size, estrogen receptor (ER)/progesterone receptor (PR)/human epidermal growth factor receptor 2 (HER2) status, tumor grade, and lymph node status have been described in our previous studies [26]. Age at breast cancer diagnosis was defined as the patient’s age at initial diagnosis. Bilateral BC was defined as the occurrence of contralateral primary BC, either synchronously or metachronously.

2.5. Statistical Analysis

Categorical variables were compared using the χ2 test or Fisher’s exact test, as appropriate. Continuous variables were analyzed using independent t-tests. A p-value < 0.05 was considered statistically significant. The Bonferroni correction was applied to account for multiple comparisons, with the corrected significance threshold noted in the table legend for reference. All statistical analyses were performed using R 4.3.2.

3. Results

3.1. BRCA2 Variants of Uncertain Significance in Breast Cancer Patients

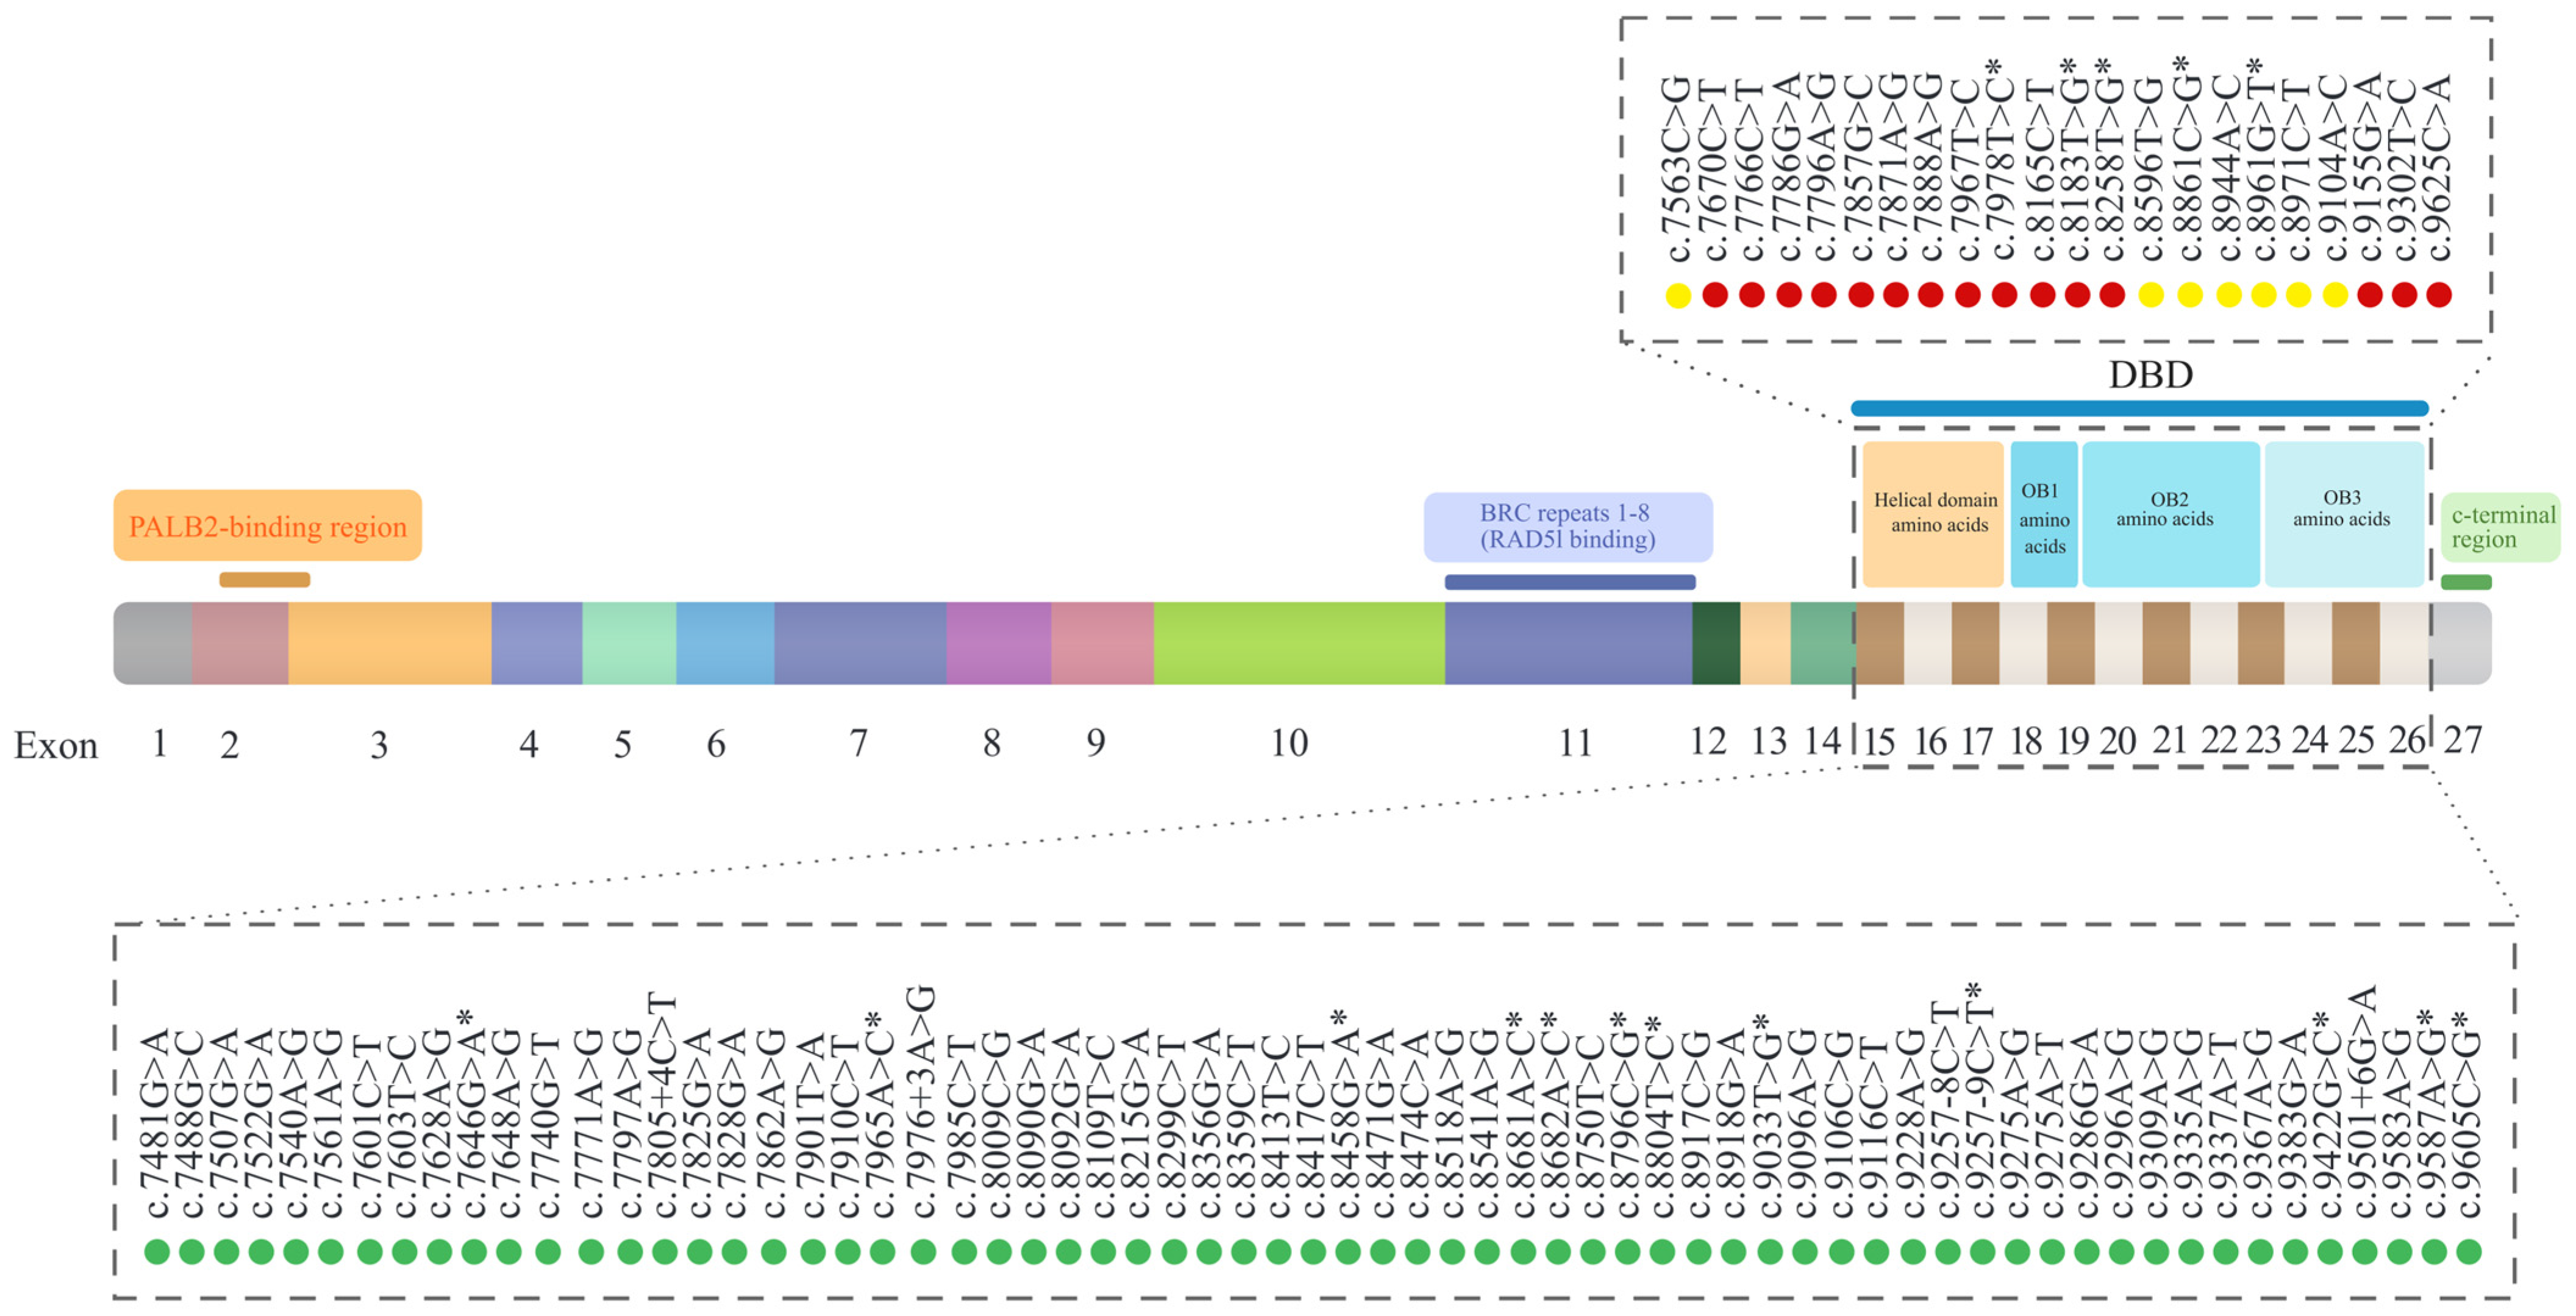
Among the 15,092 patients, 316 pathogenic or likely pathogenic variants were identified in 506 carriers, 162 benign or likely benign variants in 13,395 carriers (per ClinVar annotations), and 140 patients had no identifiable BRCA2 mutations. In addition, 457 BRCA2 variants of uncertain significance (VUS) were identified in 1051 patients. Of these VUSs, 88 variants located within exons 15–26 (identified in 187 carriers) were classifiable based on SGE functional scoring criteria, as they were the only VUSs from our cohort that were also evaluated in the two published SGE studies (Table 1) [20,21]. These 88 VUSs were further categorized into three categories: functionally pathogenic (n = 15; 20 carriers), VUS (n = 7; 13 carriers), and functionally benign (n = 66; 154 carriers) (Figure 1 and Figure 2). Data for each individual variant, including population frequency and computational functional predictions, are summarized in Supplementary Table S1.

3.2. Clinical Phenotypes of BRCA2 VUS Carriers Stratified by SGE Results

Compared with non-carriers, patients harboring functionally pathogenic variants showed a significantly higher prevalence of a family history of malignant tumor (65.0% versus 31.1%, p = 0.002), particularly breast cancer and/or ovarian cancer (35.0% vs. 10.0%, p = 0.002). In addition, carriers with functionally pathogenic variants had a higher incidence of contralateral breast cancer than non-carriers (10.0% versus 2.4%, p = 0.085) (Table 2). In contrast, patients with functionally benign variants exhibited no significant differences in clinicopathological characteristics compared with non-carriers (Table 2).

3.3. Reclassification of BRCA2 VUSs Based on SGE and ACMG

We further integrated SGE functional scores with ACMG criteria to reclassify these 88 VUSs into five categories: pathogenic, likely pathogenic, VUS, likely benign, and benign. Of these 88 reclassified variants, 6 were reclassified as pathogenic (9 carriers), 18 as VUS (27 carriers), and 64 as benign (151 carriers). A total of 11 variants showed discrepant classifications between SGE alone and the combined SGE-ACMG framework (Supplementary Tables S2 and S3).

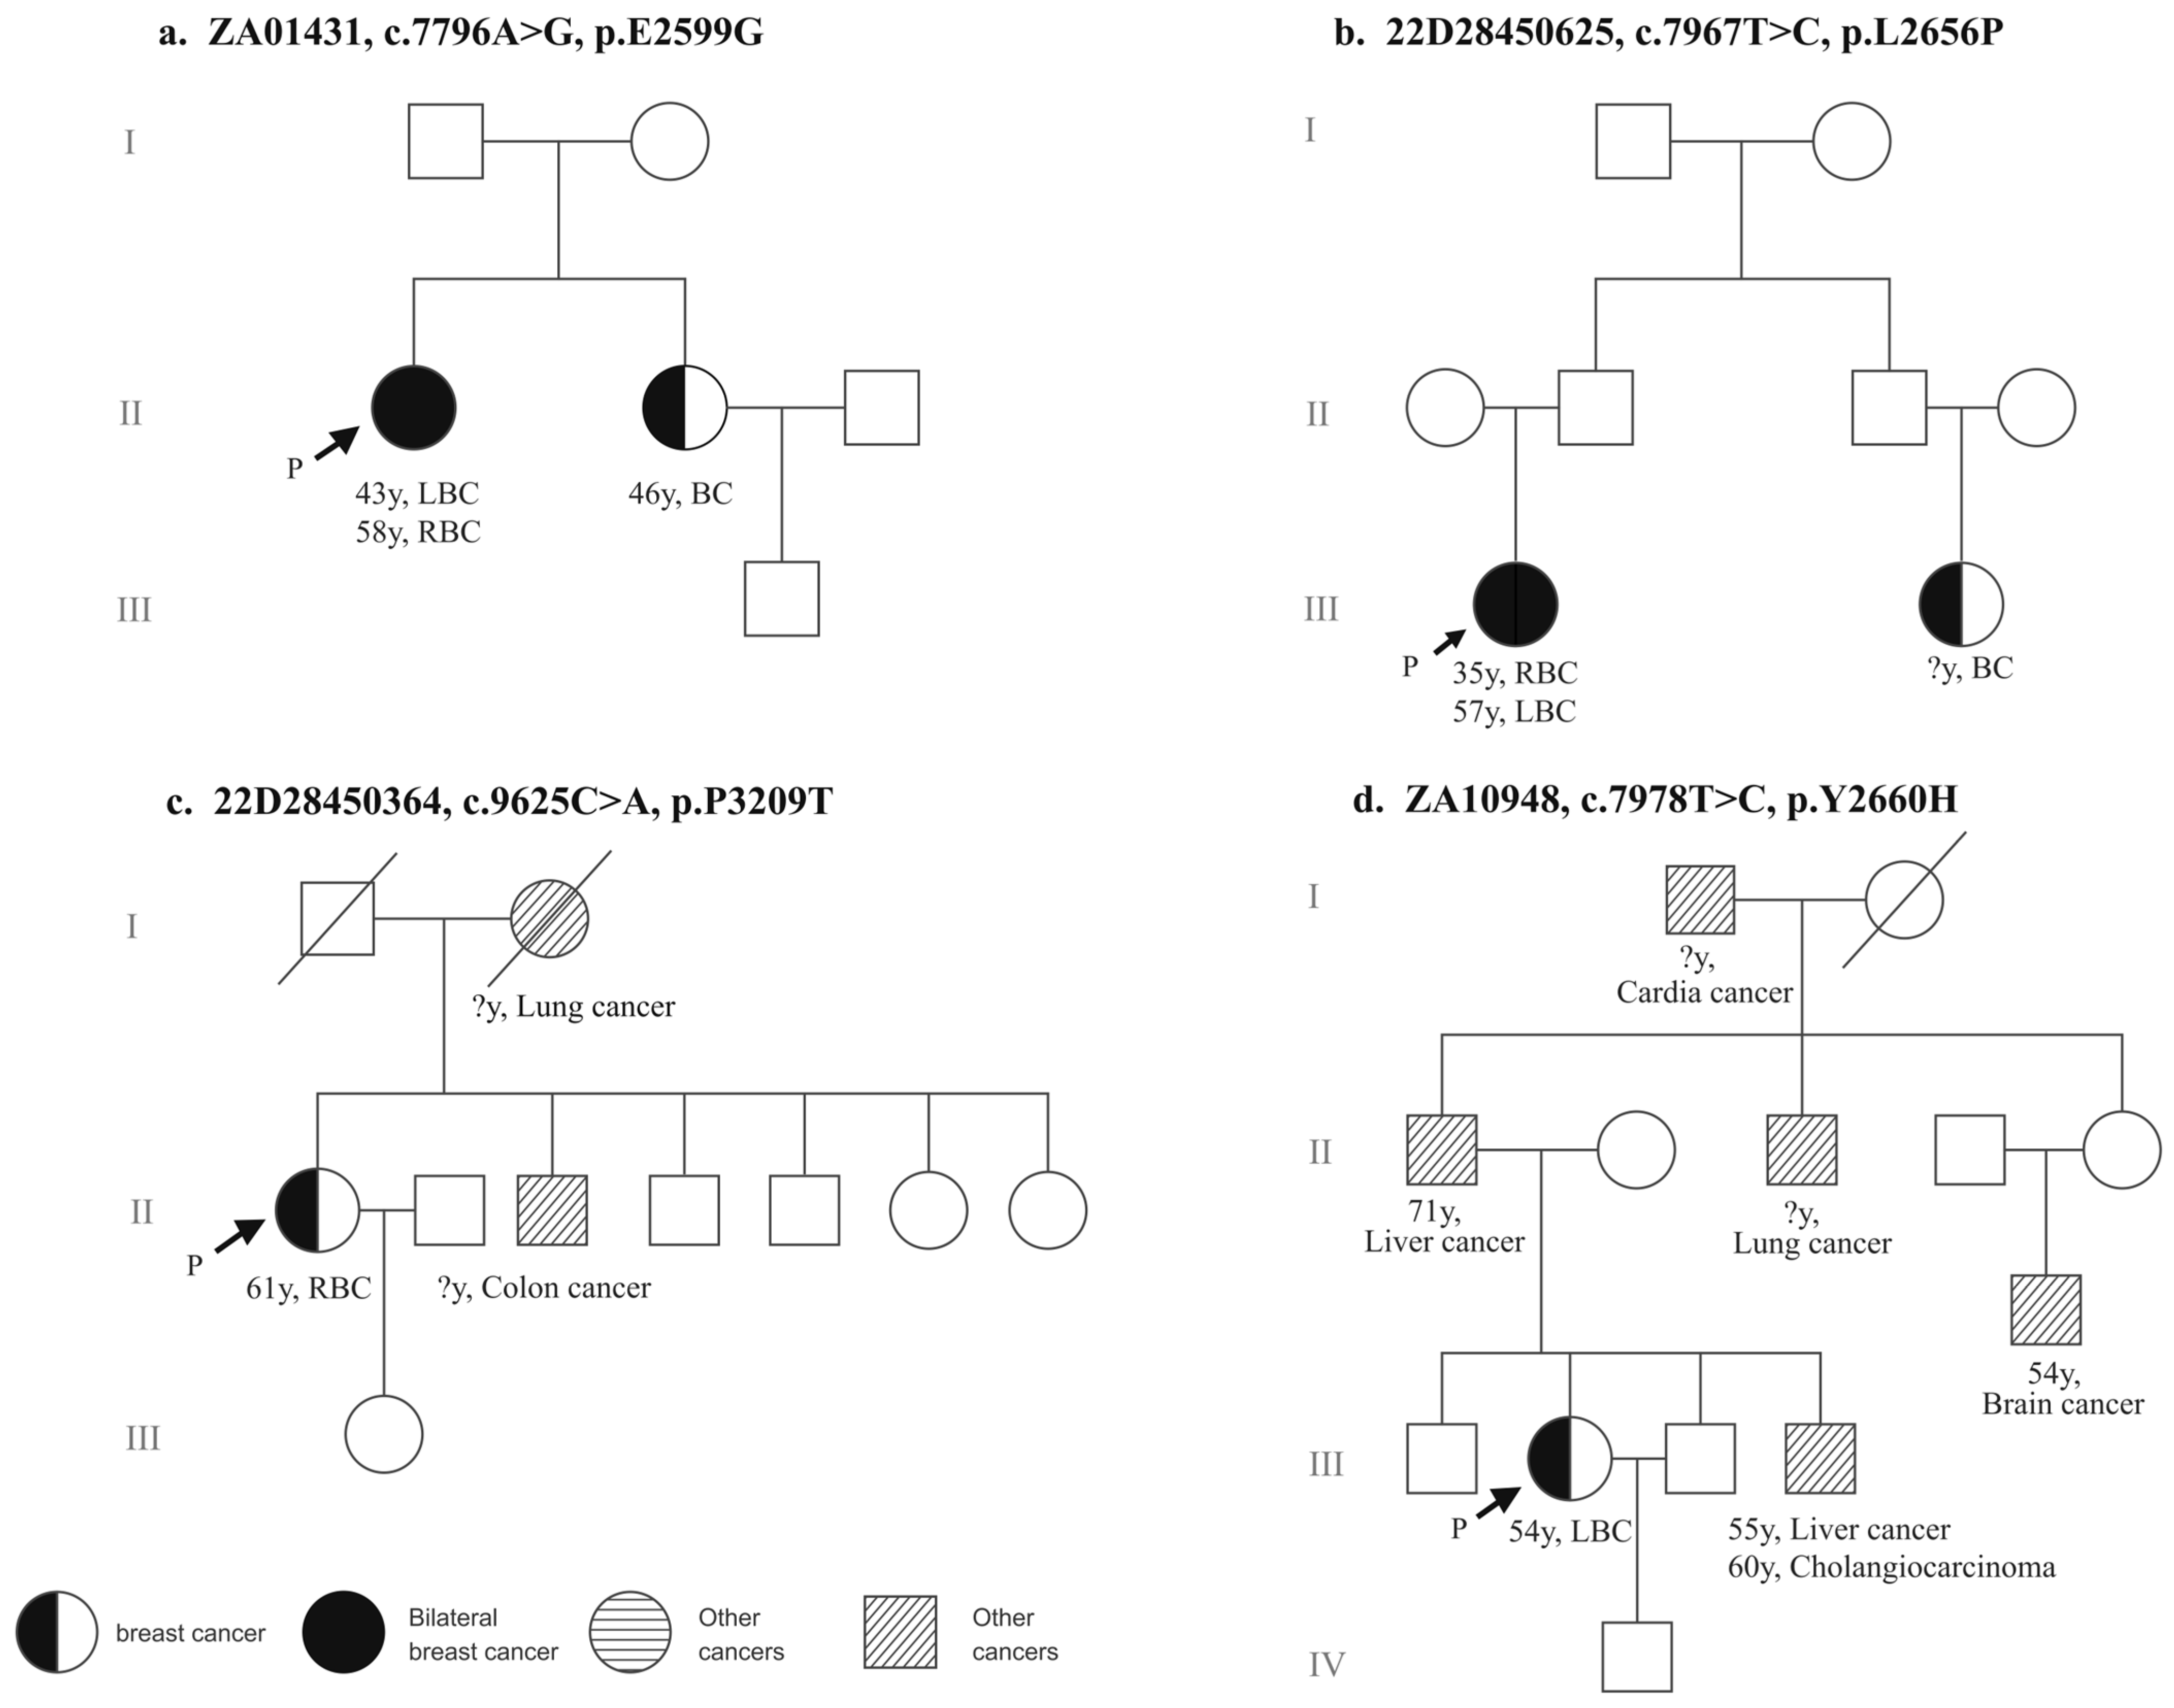
3.4. Pedigrees of Functionally Pathogenic Variants

Among the 20 carriers of functionally pathogenic BRCA2 variants, 13 patients had a family history of malignant tumors, including 7 with a family history of breast cancer or ovarian cancer. Detailed telephone follow-up was conducted for 9 families to construct comprehensive pedigrees.
Patient ZA01431 (c.7796A>G) was diagnosed with left-sided BC at age 43 and contralateral BC at 58; her sister was also diagnosed with BC at age 46. Patient 22D28450625 (c.7967T>C) developed right-sided BC at age 35 and contralateral BC at 57, with a first-cousin diagnosed with BC (age at onset unknown). Additionally, patients 22D28450364 (c.9625C>A) and ZA10948 (c.7978T>C) had had family histories of multiple other cancer types. The complete pedigrees of these well-characterized families are shown in Figure 3. Five additional carriers—23D04591198 (c.9302T>C), M32–17210 (c.7857G>C), 24D04024913 (c.9625C>A), ZA02478 (c.7888A>G), and 22D28449761 (c.8165C>T)—had BC family history involving first-degree relatives (mothers or sisters). Collectively, these familial clustering events provide supporting evidence for the pathogenicity of these eight functionally pathogenic variants.

4. Discussion

In this study, we applied saturation genome editing (SGE) [20,21] functional scores to reclassify 88 BRCA2 variants of uncertain significance identified in a large real-world cohort of 15,092 patients with breast cancer. Functional assessment classified 15 variants as functionally pathogenic and 66 as functionally benign, while 7 remained unresolved. Notably, patients with functionally pathogenic BRCA2 variants exhibited significantly higher prevalence of a family history of cancer, particularly breast cancer and ovarian cancer, as well as an increased incidence of contralateral breast cancer. These findings align with the established phenotypic spectrum of hereditary BC and support the clinical validity of SGE-based functional classification in BRCA2 [27,28].
A major challenge in clinical genetic testing is the high proportion of VUS in BRCA, the majority of which are missense variants [14,29]. Conventional interpretation strategies, which depend on in silico prediction, population frequency, and evolutionary conservation, often provide insufficient or conflicting evidence, thereby limiting their clinical utility [30]. SGE addresses these limitations by introducing variants into their endogenous genomic context and quantitatively measuring their functional impact at single-nucleotide resolution [31,32]. This high-throughput approach enables systematic and reproducible functional annotation across large genomic regions [32], providing quantitative evidence that can directly inform variant classification within established frameworks such as ACMG/AMP.
Consistent with prior studies in BRCA1 and other homologous recombination genes [22,31,33], our findings demonstrate that SGE-based functional classification reliably distinguishes pathogenic from benign variants and correlates with clinically relevant phenotypes. Our previous work in BRCA1 showed that loss-of-function variants were associated with more aggressive clinicopathological features [22]. Here, we extend these observations to BRCA2 and demonstrate a similar concordance between functional classification and clinical presentation. Together, these cross-gene data support the robustness and generalizability of SGE as a functional assay for cancer susceptibility genes.
Importantly, integration of SGE results with ACMG criteria further improved clinical interpretability. Among the 88 VUS, 6 were reclassified as pathogenic and 64 as benign, substantially reducing diagnostic uncertainty. However, discrepant classifications were observed in a subset of variants, underscoring the necessity of incorporating multiple lines of evidence for accurate interpretation. In addition, pedigree analyses provided independent support for pathogenicity, with several functionally pathogenic variants associated with early-onset disease, bilateral BC, and familial clustering of BC or OC. These findings highlight the value of combining functional genomics with clinical and familial data to refine risk stratification. Recently, Shin et al. evaluated concordance of two SGE assays and available functional evidence for clinical variant classification [34]. Our work additionally analyzed correlations between SGE-based classifications, clinical phenotypes and familial cancer clustering in a large unselected breast cancer cohort. Together, these two studies validate the clinical value of consistent SGE evidence.
The DNA-binding domain (DBD) of BRCA2 is central to its tumor-suppressor function and represents a clinically important hotspot for missense variants [35,36]. Disruption of this region may compromise DNA repair [37]. Functionally pathogenic variants such as c.7857G>C(p.W2619C) and c.9155G>A(p.R3052Q) are located within the BRCA2 C-terminal DNA-binding domain (DBD) and may affect conserved residues. The non-conservative amino acid substitutions are predicted to impair protein stability or DNA-binding affinity based on structural and evolutionary conservation analyses [38,39]. Indeed, definitive pathogenic classification for variants still requires further validation through clinical evidence and complementary functional experiments.
Beyond BRCA2, SGE offers a scalable platform for comprehensive functional interrogation of nearly all possible single-nucleotide variants within a gene [40,41,42]. Its ability to generate high-resolution, quantitative functional maps provides a distinct advantage over traditional approaches and has demonstrated high sensitivity and specificity in multiple validation studies [31,32,43,44]. As such, SGE has the potential to substantially reduce the burden of VUS in clinical genetic testing and improve the precision of genetic counseling and risk assessment [20,45].
Several limitations should be acknowledged. First, the number of carriers with functionally pathogenic variants was relatively small, which may limit statistical power. Second, comprehensive co-segregation analyses were not available for all families. Third, variants outside the SGE-targeted regions could not be evaluated. Future studies should aim to expand SGE coverage to the full coding region of BRCA2 and more genes, include larger and more diverse cohorts, and incorporate longitudinal follow-up to assess clinical outcomes. In addition, the relationship between SGE-derived functional status and therapeutic response—particularly to PARP inhibitors and platinum-based chemotherapy—warrants further investigation.

5. Conclusions

In summary, SGE provides robust and reliable functional evidence for BRCA2 VUS classification. Functionally pathogenic BRCA2 variants are associated with distinct adverse clinical phenotypes similar to canonical pathogenic mutations. Integration of SGE with clinicopathological and pedigree data improves the accuracy and clinical actionability of variant interpretation. Our findings support the broader implementation of SGE in routine genetic testing to advance precision prevention and management of hereditary breast cancer.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/curroncol33090521/s1, Table S1. Comprehensive annotation and SGE-based reclassification of 88 BRCA2 variants of uncertain significance. Table S2. Classification Status of 88 BRCA2 Variants of Uncertain Significance (VUS) Loci in Two SGE Experiments. Table S3. Clinicopathological characteristics among BRCA2 germline variant carriers (Based on SGE and ACMG).

Author Contributions

Conceptualization, Y.X. (Ye Xu) and Y.X. (Yuntao Xie); methodology, Y.S., J.C., L.H. and J.S.; software, Y.S., J.C., L.H. and J.S.; validation, J.Z. and L.Y. and Y.X. (Ye Xu); formal analysis, Y.S., J.C., L.H. and J.S.; investigation, Y.S., J.C., L.H. and J.S.; data curation, J.C., L.H., J.S., J.Z. and L.Y.; writing—original draft preparation, Y.X. (Ye Xu), J.C., L.H. and J.S.; writing—review and editing, Y.X. (Ye Xu) and Y.X. (Yuntao Xie); visualization, Y.S. and J.C.; supervision, Y.X. (Ye Xu) and Y.X. (Yuntao Xie); project administration, Y.X. (Ye Xu) and Y.X. (Yuntao Xie); funding acquisition, Y.X. (Ye Xu) and Y.X. (Yuntao Xie). All authors have read and agreed to the published version of the manuscript.

Funding

This study was supported by grants No. 82072898 and No. 92359201 from the National Natural Science Foundation of China.

Institutional Review Board Statement

All procedures performed in studies involving human participants were in accordance with the ethical standards of the institutional and/or national research committee and with the 1964 Helsinki declaration and its later amendments or comparable ethical standards. This study was approved on 30 April 2021 by the Ethics Committee of Peking University Cancer Hospital (No. 2021KT65).

Informed Consent Statement

Informed consent was obtained from all individual participants included in the study.

Data Availability Statement

The data supporting the findings of this study are available from the corresponding author upon reasonable request.

Acknowledgments

The authors sincerely thank all patients and their families for their participation in and support of this study. We also gratefully acknowledge the clinicians, nurses, and laboratory personnel at Peking University Cancer Hospital for their valuable contributions to sample collection and clinical data collection. ChatGPT (OpenAI, GPT–5) was used exclusively for English-language editing to improve the grammar, clarity, and readability of the manuscript. It was not used to generate scientific content, perform data analysis or interpretation, or draw scientific conclusions. All AI-assisted revisions were carefully reviewed and verified by the authors, who take full responsibility for the accuracy and integrity of the manuscript.

Conflicts of Interest

The authors have declared no conflicts of interest.

References

  1. von Nicolai, C.; Ehlén, Å.; Martin, C.; Zhang, X.; Carreira, A. A second DNA binding site in human BRCA2 promotes homologous recombination. Nat. Commun. 2016, 7, 12813. [Google Scholar] [CrossRef] [Scilit]
  2. Pellegrini, L.; Yu, D.S.; Lo, T.; Anand, S.; Lee, M.; Blundell, T.L.; Venkitaraman, A.R. Insights into DNA recombination from the structure of a RAD51-BRCA2 complex. Nature 2002, 420, 287–293. [Google Scholar] [CrossRef] [Scilit]
  3. Belan, O.; Greenhough, L.; Kuhlen, L.; Anand, R.; Kaczmarczyk, A.; Gruszka, D.T.; Yardimci, H.; Zhang, X.; Rueda, D.S.; West, S.C.; et al. Visualization of direct and diffusion-assisted RAD51 nucleation by full-length human BRCA2 protein. Mol. Cell 2023, 83, 2925–2940.e8. [Google Scholar] [CrossRef] [Scilit]
  4. Chen, C.C.; Feng, W.; Lim, P.X.; Kass, E.M.; Jasin, M. Homology-Directed Repair and the Role of BRCA1, BRCA2, and Related Proteins in Genome Integrity and Cancer. Annu. Rev. Cancer Biol. 2018, 2, 313–336. [Google Scholar] [CrossRef] [Scilit]
  5. Zhao, W.; Wiese, C.; Kwon, Y.; Hromas, R.; Sung, P. The BRCA Tumor Suppressor Network in Chromosome Damage Repair by Homologous Recombination. Annu. Rev. Biochem. 2019, 88, 221–245. [Google Scholar] [CrossRef] [Scilit]
  6. Dunce, J.M.; Davies, O.R. BRCA2 stabilises RAD51 and DMC1 nucleoprotein filaments through a conserved interaction mode. Nat. Commun. 2024, 15, 8292. [Google Scholar] [CrossRef] [Scilit]
  7. Arun, B.; Couch, F.J.; Abraham, J.; Tung, N.; Fasching, P.A. BRCA-mutated breast cancer: The unmet need, challenges and therapeutic benefits of genetic testing. Br. J. Cancer 2024, 131, 1400–1414. [Google Scholar] [CrossRef] [Scilit]
  8. Bedrosian, I.; Somerfield, M.R.; Achatz, M.I.; Boughey, J.C.; Curigliano, G.; Friedman, S.; Kohlmann, W.K.; Kurian, A.W.; Laronga, C.; Lynce, F.; et al. Germline Testing in Patients With Breast Cancer: ASCO-Society of Surgical Oncology Guideline. J. Clin. Oncol. 2024, 42, 584–604. [Google Scholar] [CrossRef] [Scilit]
  9. Kraya, A.A.; Maxwell, K.N.; Wubbenhorst, B.; Wenz, B.M.; Pluta, J.; Rech, A.J.; Dorfman, L.M.; Lunceford, N.; Barrett, A.; Mitra, N.; et al. Genomic Signatures Predict the Immunogenicity of BRCA-Deficient Breast Cancer. Clin. Cancer Res. 2019, 25, 4363–4374. [Google Scholar] [CrossRef] [Scilit]
  10. Górski, B.; Narod, S.A.; Lubinski, J. A common missense variant in BRCA2 predisposes to early onset breast cancer. Breast Cancer Res. 2005, 7, R1023–R1027. [Google Scholar] [CrossRef] [Scilit]
  11. Bryant, H.E.; Schultz, N.; Thomas, H.D.; Parker, K.M.; Flower, D.; Lopez, E.; Kyle, S.; Meuth, M.; Curtin, N.J.; Helleday, T. Specific killing of BRCA2-deficient tumours with inhibitors of poly(ADP-ribose) polymerase. Nature 2005, 434, 913–917. [Google Scholar] [CrossRef] [Scilit]
  12. Tutt, A.N.J.; Garber, J.E.; Kaufman, B.; Viale, G.; Fumagalli, D.; Rastogi, P.; Gelber, R.D.; de Azambuja, E.; Fielding, A.; Balmaña, J.; et al. Adjuvant Olaparib for Patients with BRCA1- or BRCA2-Mutated Breast Cancer. N. Engl. J. Med. 2021, 384, 2394–2405. [Google Scholar] [CrossRef] [Scilit]
  13. Moore, K.; Colombo, N.; Scambia, G.; Kim, B.G.; Oaknin, A.; Friedlander, M.; Lisyanskaya, A.; Floquet, A.; Leary, A.; Sonke, G.S.; et al. Maintenance Olaparib in Patients with Newly Diagnosed Advanced Ovarian Cancer. N. Engl. J. Med. 2018, 379, 2495–2505. [Google Scholar] [CrossRef] [Scilit]
  14. Hu, C.; Susswein, L.R.; Roberts, M.E.; Yang, H.; Marshall, M.L.; Hiraki, S.; Berkofsky-Fessler, W.; Gupta, S.; Shen, W.; Dunn, C.A.; et al. Classification of BRCA2 Variants of Uncertain Significance (VUS) Using an ACMG/AMP Model Incorporating a Homology-Directed Repair (HDR) Functional Assay. Clin. Cancer Res. 2022, 28, 3742–3751. [Google Scholar] [CrossRef] [Scilit]
  15. Spearman, A.D.; Sweet, K.; Zhou, X.P.; McLennan, J.; Couch, F.J.; Toland, A.E. Clinically applicable models to characterize BRCA1 and BRCA2 variants of uncertain significance. J. Clin. Oncol. 2008, 26, 5393–5400. [Google Scholar] [CrossRef] [Scilit]
  16. Mesman, R.L.S.; Calléja, F.; Hendriks, G.; Morolli, B.; Misovic, B.; Devilee, P.; van Asperen, C.J.; Vrieling, H.; Vreeswijk, M.P.G. The functional impact of variants of uncertain significance in BRCA2. Genet. Med. 2019, 21, 293–302. [Google Scholar] [CrossRef] [Scilit]
  17. Nakahara, H.; Niitsu, H.; Toshida, A.; Goto, K.; Yamauchi, M.; Saipova, K.M.; Hayes, C.N.; Hinata, N.; Oka, S.; Hinoi, T. A prioritization framework for BRCA1/2 variants of uncertain significance identified by comprehensive genomic profiling. Eur. J. Hum. Genet. 2026, 34, 1104–1111. [Google Scholar] [CrossRef] [Scilit]
  18. Li, H.; LaDuca, H.; Pesaran, T.; Chao, E.C.; Dolinsky, J.S.; Parsons, M.; Spurdle, A.B.; Polley, E.C.; Shimelis, H.; Hart, S.N.; et al. Classification of variants of uncertain significance in BRCA1 and BRCA2 using personal and family history of cancer from individuals in a large hereditary cancer multigene panel testing cohort. Genet. Med. 2020, 22, 701–708. [Google Scholar] [CrossRef] [Scilit]
  19. Eccles, D.M.; Mitchell, G.; Monteiro, A.N.; Schmutzler, R.; Couch, F.J.; Spurdle, A.B.; Gómez-García, E.B. BRCA1 and BRCA2 genetic testing-pitfalls and recommendations for managing variants of uncertain clinical significance. Ann. Oncol. 2015, 26, 2057–2065. [Google Scholar] [CrossRef] [Scilit]
  20. Sahu, S.; Galloux, M.; Southon, E.; Caylor, D.; Sullivan, T.; Arnaudi, M.; Zanti, M.; Geh, J.; Chari, R.; Michailidou, K.; et al. Saturation genome editing-based clinical classification of BRCA2 variants. Nature 2025, 638, 538–545. [Google Scholar] [CrossRef] [Scilit]
  21. Huang, H.; Hu, C.; Na, J.; Hart, S.N.; Gnanaolivu, R.D.; Abozaid, M.; Rao, T.; Tecleab, Y.A.; Pesaran, T.; Lyra, P.C.M.; et al. Functional evaluation and clinical classification of BRCA2 variants. Nature 2025, 638, 528–537. [Google Scholar] [CrossRef] [Scilit]
  22. Wan, Q.; Hu, L.; Ouyang, T.; Li, J.; Wang, T.; Fan, Z.; Fan, T.; Lin, B.; Xu, Y.; Xie, Y. Clinical phenotypes combined with saturation genome editing identifying the pathogenicity of BRCA1 variants of uncertain significance in breast cancer. Fam. Cancer 2021, 20, 85–95. [Google Scholar] [CrossRef] [Scilit]
  23. O’Leary, N.A.; Wright, M.W.; Brister, J.R.; Ciufo, S.; Haddad, D.; McVeigh, R.; Rajput, B.; Robbertse, B.; Smith-White, B.; Ako-Adjei, D.; et al. Reference sequence (RefSeq) database at NCBI: Current status, taxonomic expansion, and functional annotation. Nucleic Acids Res. 2016, 44, D733–D745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Nikolényi, A.; Dobi, Á.; Sántha, D.; Kószó, R.; Iványi, M.; Horváth, E.; Enyedi, M.Z.; Priskin, K.; Csányi, B.; Patócs, A.; et al. Germline BRCA testing in routine clinical practice: A single-center experience. Pathol. Oncol. Res. 2026, 32, 1612238. [Google Scholar] [CrossRef] [Scilit]
  25. Richards, S.; Aziz, N.; Bale, S.; Bick, D.; Das, S.; Gastier-Foster, J.; Grody, W.W.; Hegde, M.; Lyon, E.; Spector, E.; et al. Standards and guidelines for the interpretation of sequence variants: A joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genet. Med. 2015, 17, 405–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Abubakar, M.; Guo, C.; Koka, H.; Sung, H.; Shao, N.; Guida, J.; Deng, J.; Li, M.; Hu, N.; Zhou, B.; et al. Clinicopathological and epidemiological significance of breast cancer subtype reclassification based on p53 immunohistochemical expression. npj Breast Cancer 2019, 5, 20. [Google Scholar] [CrossRef] [Scilit]
  27. Li, J.; Wen, W.X.; Eklund, M.; Kvist, A.; Eriksson, M.; Christensen, H.N.; Torstensson, A.; Bajalica-Lagercrantz, S.; Dunning, A.M.; Decker, B.; et al. Prevalence of BRCA1 and BRCA2 pathogenic variants in a large, unselected breast cancer cohort. Int. J. Cancer 2019, 144, 1195–1204. [Google Scholar] [CrossRef] [Scilit]
  28. Chen, B.; Zhang, G.; Li, X.; Ren, C.; Wang, Y.; Li, K.; Mok, H.; Cao, L.; Wen, L.; Jia, M.; et al. Comparison of BRCA versus non-BRCA germline mutations and associated somatic mutation profiles in patients with unselected breast cancer. Aging 2020, 12, 3140–3155. [Google Scholar] [CrossRef] [Scilit]
  29. Biswas, K.; Mitrophanov, A.Y.; Sahu, S.; Sullivan, T.; Southon, E.; Nousome, D.; Reid, S.; Narula, S.; Smolen, J.; Sengupta, T.; et al. Sequencing-based functional assays for classification of BRCA2 variants in mouse ESCs. Cell Rep. Methods 2023, 3, 100628. [Google Scholar] [CrossRef] [Scilit]
  30. Stella, S.; Vitale, S.R.; Massimino, M.; Martorana, F.; Tornabene, I.; Tomarchio, C.; Drago, M.; Pavone, G.; Gorgone, C.; Barone, C.; et al. In Silico Prediction of BRCA1 and BRCA2 Variants with Conflicting Clinical Interpretation in a Cohort of Breast Cancer Patients. Genes 2024, 15, 943. [Google Scholar] [CrossRef] [Scilit]
  31. Olvera-León, R.; Zhang, F.; Offord, V.; Zhao, Y.; Tan, H.K.; Gupta, P.; Pal, T.; Robles-Espinoza, C.D.; Arriaga-González, F.G.; Matsuyama, L.; et al. High-resolution functional mapping of RAD51C by saturation genome editing. Cell 2024, 187, 5719–5734.e5719. [Google Scholar] [CrossRef] [Scilit]
  32. Findlay, G.M.; Daza, R.M.; Martin, B.; Zhang, M.D.; Leith, A.P.; Gasperini, M.; Janizek, J.D.; Huang, X.; Starita, L.M.; Shendure, J. Accurate classification of BRCA1 variants with saturation genome editing. Nature 2018, 562, 217–222. [Google Scholar] [CrossRef] [Scilit]
  33. Ngeow, J.; Chiang, J.; Astiazaran-Symonds, E.; Balmaña, J.; Cass, I.; Kommoss, F.K.F.; Foulkes, W.D.; James, P.A.; Katcher, A.; Klugman, S.; et al. Management of individuals with heterozygous germline pathogenic variants in RAD51C, RAD51D, and BRIP1: A clinical practice resource of the American College of Medical Genetics and Genomics (ACMG). Genet. Med. 2025, 27, 101557. [Google Scholar] [CrossRef] [Scilit]
  34. Shin, J.H.; Park, K.S.; Kim, Y.G.; Jang, M.A.; Jang, J.H.; Kim, J.W. Clinical variant interpretation comparing two saturation genome editing-based functional studies for BRCA2. Front. Genet. 2026, 17, 1803717. [Google Scholar] [CrossRef] [Scilit]
  35. Alvaro-Aranda, L.; Petitalot, A.; Djeghmoum, Y.; Panigada, D.; Singh, J.K.; Ehlén, Å.; Vugic, D.; Martin, C.; Miron, S.; Contreras-Perez, A.; et al. The BRCA2 R2645G variant increases DNA binding and induces hyper-recombination. Nucleic Acids Res. 2024, 52, 6964–6976. [Google Scholar] [CrossRef] [Scilit]
  36. Hu, C.; Huang, H.; Na, J.; Lumby, C.; Abozaid, M.; Holdren, M.A.; Rao, T.J.; Karam, R.; Pesaran, T.; Weyandt, J.D.; et al. Functional analysis and clinical classification of 462 germline BRCA2 missense variants affecting the DNA binding domain. Am. J. Hum. Genet. 2024, 111, 584–593. [Google Scholar] [CrossRef] [Scilit]
  37. Lee, M.; Shorthouse, D.; Mahen, R.; Hall, B.A.; Venkitaraman, A.R. Cancer-causing BRCA2 missense mutations disrupt an intracellular protein assembly mechanism to disable genome maintenance. Nucleic Acids Res. 2021, 49, 5588–5604. [Google Scholar] [CrossRef] [Scilit]
  38. Shi, Q.; Gao, J.; Yu, H.; Niu, Y.; Yuan, E.; Guo, Y.; Song, L.; Fang, Y.; Wang, Y.; Yuan, E.; et al. Characterization and functional analysis of BRCA1 and BRCA2 variants in a cohort of 100 unselected patients undergoing germline screening. Transl. Oncol. 2025, 59, 102471. [Google Scholar] [CrossRef] [Scilit]
  39. Mishra, A.P.; Hartford, S.; Chittela, R.K.; Sahu, S.; Kharat, S.S.; Alvaro-Aranda, L.; Contreras-Perez, A.; Sullivan, T.; Martin, B.K.; Albaugh, M.; et al. Characterization of BRCA2 R3052Q variant in mice supports its functional impact as a low-risk variant. Cell Death Dis. 2023, 14, 753. [Google Scholar] [CrossRef] [Scilit]
  40. Funk, J.S.; Klimovich, M.; Drangenstein, D.; Pielhoop, O.; Hunold, P.; Borowek, A.; Noeparast, M.; Pavlakis, E.; Neumann, M.; Balourdas, D.I.; et al. Deep CRISPR mutagenesis characterizes the functional diversity of TP53 mutations. Nat. Genet. 2025, 57, 140–153. [Google Scholar] [CrossRef] [Scilit]
  41. Hemker, S.L.; Marsh, A.; Hernandez, F.; Glick, E.; Clark, G.; Bashir, A.; Jiang, K.; Kitzman, J.O. Saturation mapping of MUTYH variant effects using DNA repair reporters. Am. J. Hum. Genet. 2025, 112, 2010–2026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Hu, C.; Sahu, S.; Chen, W.; Galloux, M.; Richardson, M.E.; Bishop, M.F.; Karam, R.; Pesaran, T.; Na, J.; Huang, H.; et al. Combining multiplexed assays of variant effect for enhanced BRCA2 variant classification. Nat. Commun. 2026, 17, 4847. [Google Scholar] [CrossRef] [Scilit]
  43. Waters, A.J.; Brendler-Spaeth, T.; Smith, D.; Offord, V.; Tan, H.K.; Zhao, Y.; Obolenski, S.; Nielsen, M.; van Doorn, R.; Murphy, J.E.; et al. Saturation genome editing of BAP1 functionally classifies somatic and germline variants. Nat. Genet. 2024, 56, 1434–1445. [Google Scholar] [CrossRef] [Scilit]
  44. Buckley, M.; Terwagne, C.; Ganner, A.; Cubitt, L.; Brewer, R.; Kim, D.K.; Kajba, C.M.; Forrester, N.; Dace, P.; De Jonghe, J.; et al. Saturation genome editing maps the functional spectrum of pathogenic VHL alleles. Nat. Genet. 2024, 56, 1446–1455. [Google Scholar] [CrossRef] [Scilit]
  45. Sahu, S.; Sullivan, T.L.; Mitrophanov, A.Y.; Galloux, M.; Nousome, D.; Southon, E.; Caylor, D.; Mishra, A.P.; Evans, C.N.; Clapp, M.E.; et al. Saturation genome editing of 11 codons and exon 13 of BRCA2 coupled with chemotherapeutic drug response accurately determines pathogenicity of variants. PLoS Genet. 2023, 19, e1010940. [Google Scholar] [CrossRef] [Scilit]
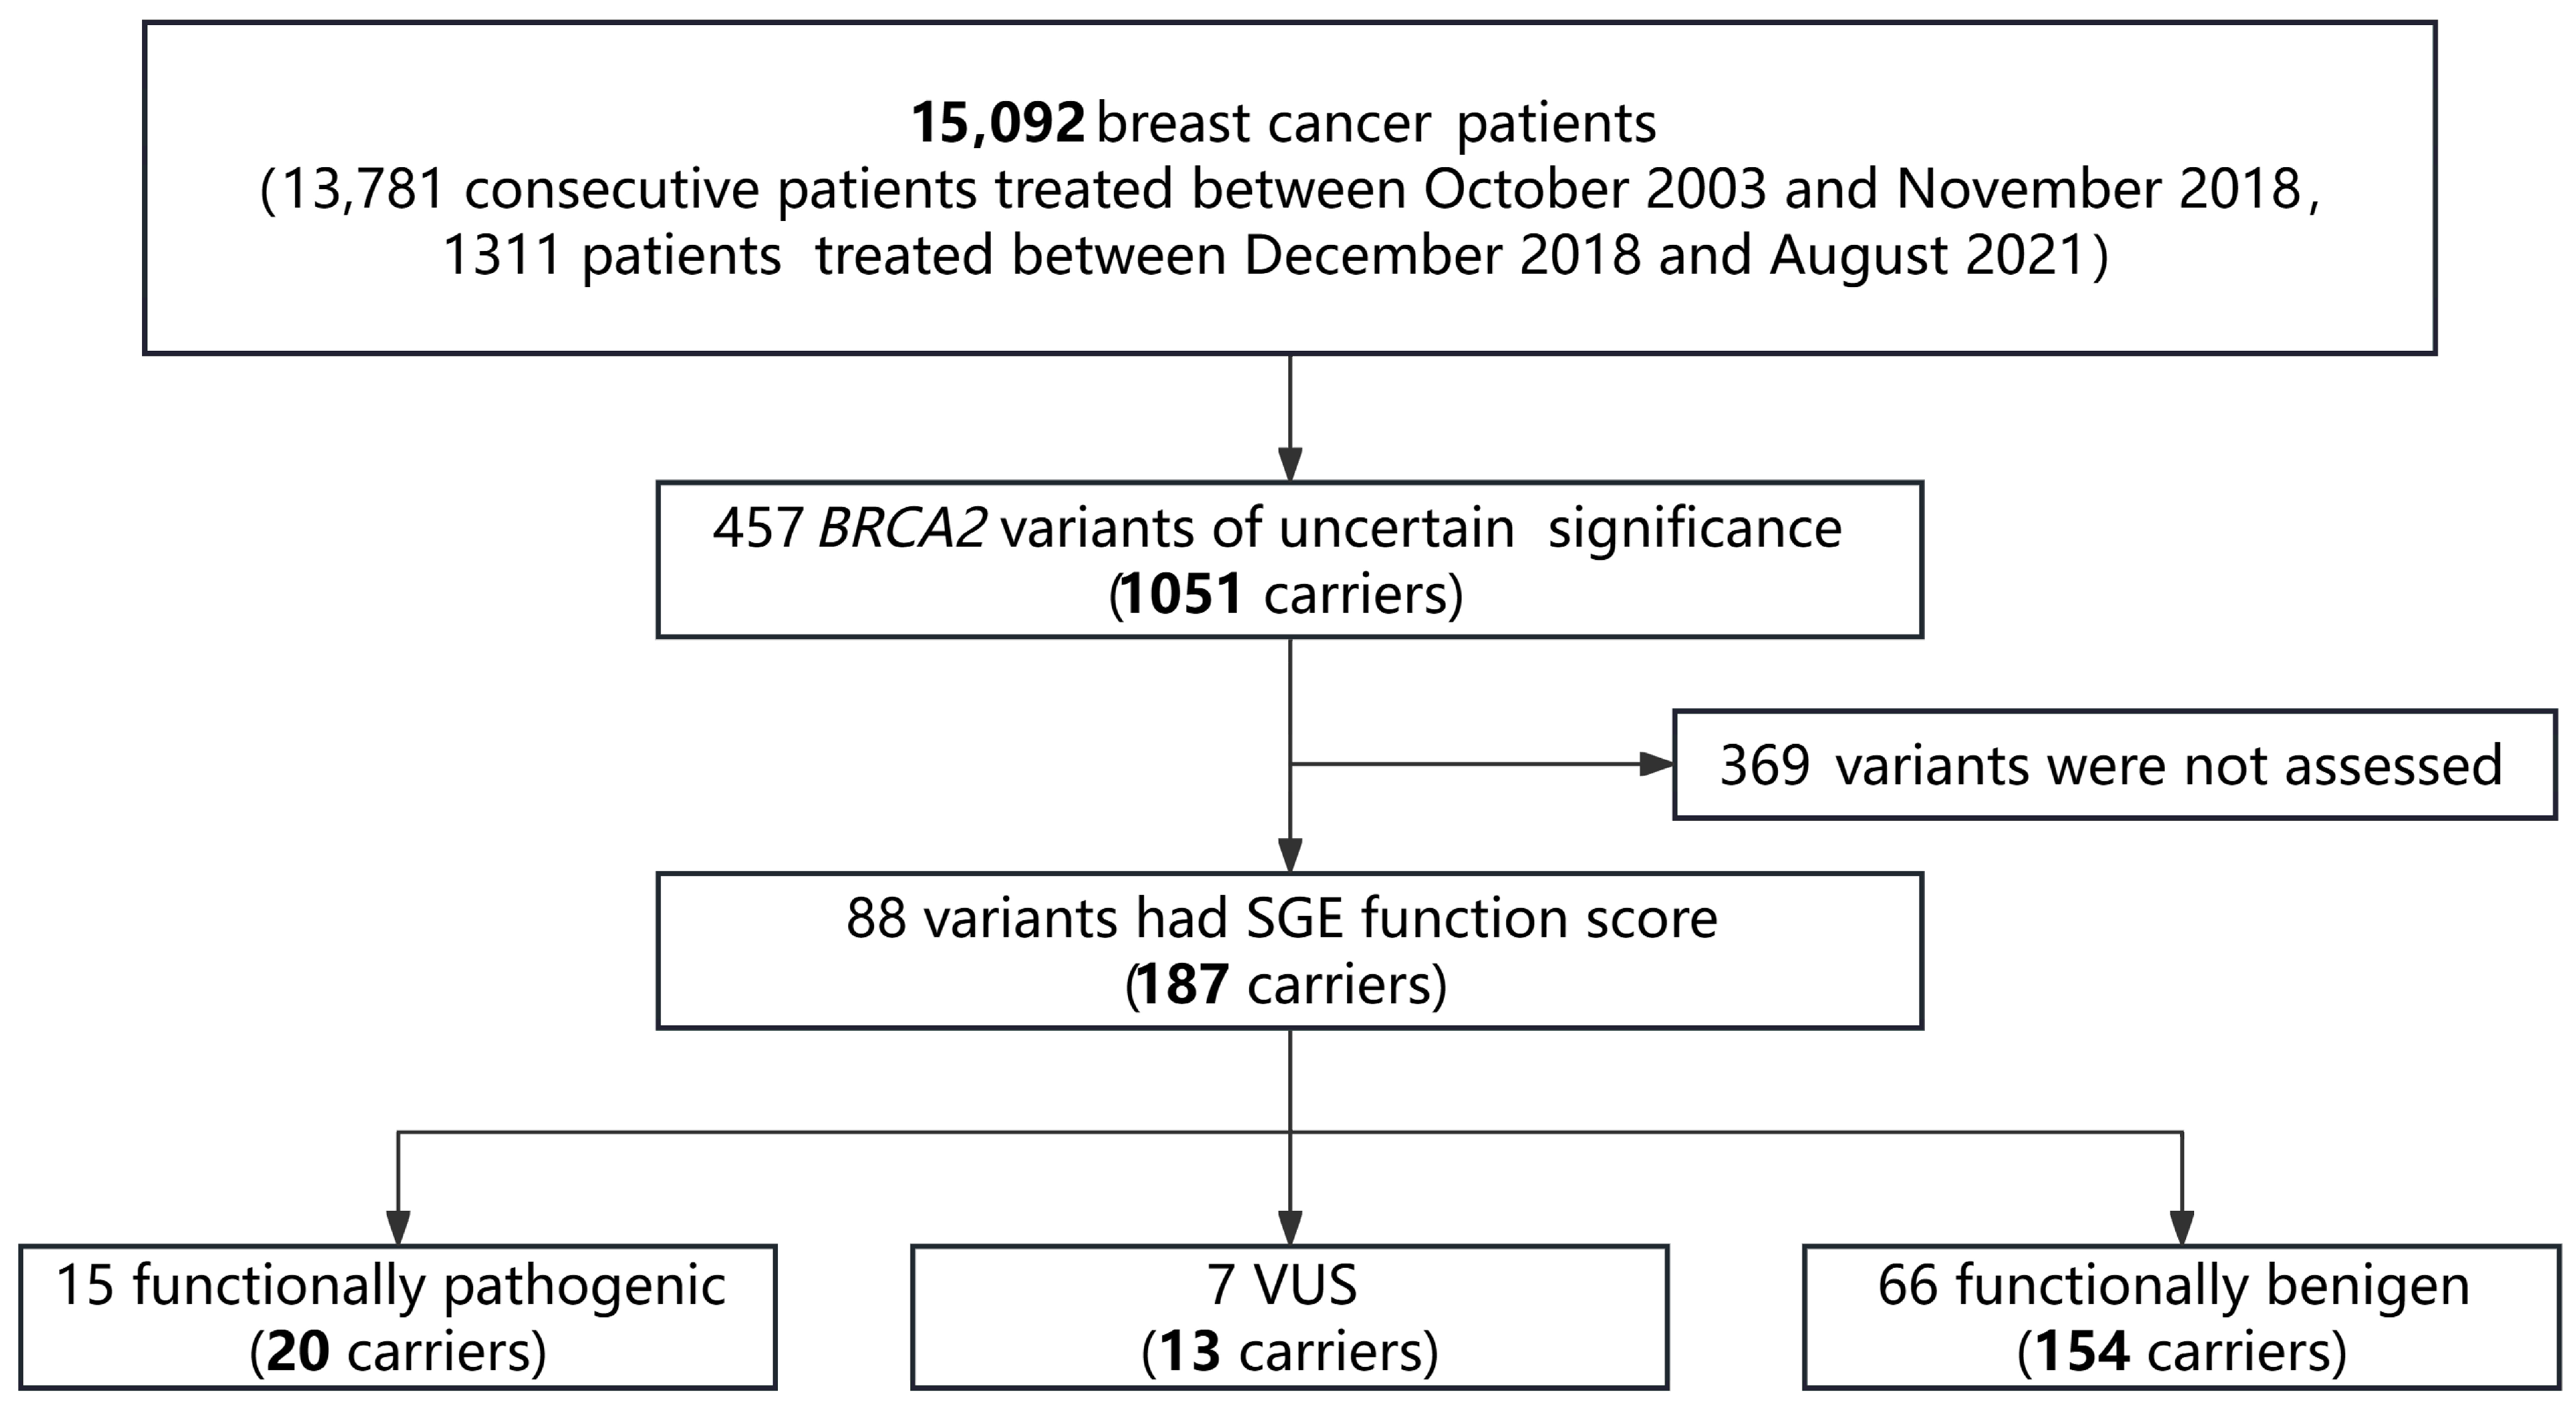
Figure 1. Classification of BRCA2 variants of uncertain significance found in 15,092 breast cancer patients according to saturation genome editing function score. VUS, variant of uncertain significance.
Curroncol 33 00521 g001
Figure 2. Schematic of BRCA2 protein domains and distribution of variants classified by saturation genome editing (SGE). Red dots represent variants reclassified as functionally pathogenic, yellow dots represent variants that remained variants of uncertain significance, and green dots represent variants reclassified as functionally benign. * Indicates novel variants that had not been reported in disease databases (the deadline for ClinVar is 30 May 2025). DBD, DNA-binding domain; OB, Oligonucleotide/oligosaccharide-binding fold.
Curroncol 33 00521 g002
Figure 3. Pedigrees of probands carrying functionally pathogenic variants. Pedigrees were collected for four probands ((a), ZA01431, (b), 22D28450625, (c), 22D28450364 and (d), ZA10948). In each pedigree, the degree of relationship is indicated on the left, and the age at cancer diagnosis and current age, where applicable, are shown below each symbol. Circles and squares represent females and males, respectively. A diagonal line through a symbol indicates that the individual is deceased. The letter “P” and an arrow identify the proband in each family. Roman numerals indicate the generations in each pedigree. BC, breast cancer; LBC, left breast cancer; RBC, right breast cancer.
Curroncol 33 00521 g003
Table 1. Functional classification and carrier counts of 88 BRCA2 VUS.
Functionally PathogenicVUSFunctionally Benign
VariantsNumber of CarriersVariantsNumber of CarriersVariantsNumber of Carriers
c.7670C>T(p.A2557V)1c.7563C>G(p.I2521M)1c.7481G>A(p.R2494Q)1
c.7766C>T(p.P2589L)1c.8596T>G(p.F2866V)1c.7488G>C(p.K2496N)3
c.7786G>A(p.G2596R)1c.8861C>G *(p.S2954C)1c.7507G>A(p.V2503I)1
c.7796A>G(p.E2599G)1c.8944A>C(p.K2982Q)2c.7522G>A(p.G2508S)44
c.7857G>C(p.W2619C)1c.8961G>T *(p.=)1c.7540A>G(p.K2514E)1
c.7871A>G(p.Y2624C)1c.8971C>T(p.R2991C)6c.7561A>G(p.I2521V)1
c.7888A>G(p.K2630E)1c.9104A>C(p.Y3035S)1c.7601C>T(p.A2534V)3
c.7967T>C(p.L2656P)1 c.7603T>C(p.C2535R)3
c.7978T>C *(p.Y2660H)1 c.7628A>G(p.Y2543C)1
c.8165C>T(p.T2722I)3 c.7646G>A *(p.C2549Y)1
c.8183T>G *(p.V2728G)1 c.7648A>G(p.I2550V)1
c.8258T>G *(p.L2753R)1 c.7740G>T(p.Q2580H)1
c.9155G>A(p.R3052Q)2 c.7771A>G(p.N2591D)1
c.9302T>C(p.L3101P)1 c.7797A>G(p.=)1
c.9625C>A(p.P3209T)3 c.7805+4C>T(p.?)1
c.7825G>A(p.G2609S)1
c.7828G>A(p.V2610M)3
c.7862A>G(p.Y2621C)1
c.7901T>A(p.M2634K)5
c.7910C>T(p.A2637V)3
c.7965A>C *(p.Q2655H)1
c.7976+3A>G(p.?)1
c.7985C>T(p.T2662M)1
c.8009C>G(p.S2670W)3
c.8090G>A(p.S2697N)8
c.8092G>A(p.A2698T)9
c.8109T>C(p.=)1
c.8215G>A(p.V2739I)1
c.8299C>T(p.P2767S)1
c.8356G>A(p.A2786T)2
c.8359C>T(p.R2787C)4
c.8413T>C(p.=)1
c.8417C>T(p.S2806L)1
c.8458G>A *(p.V2820I)1
c.8471G>A(p.R2824K)1
c.8474C>A(p.A2825E)4
c.8518A>G(p.I2840V)2
c.8541A>G(p.=)1
c.8681A>C *(p.Q2894P)2
c.8682A>C *(p.Q2894H)2
c.8750T>C(p.L2917P)1
c.8796C>G *(p.H2932Q)2
c.8804T>C *(p.M2935T)1
c.8917C>G(p.R2973G)2
c.8918G>A(p.R2973H)1
c.9033T>G *(p.=)1
c.9096A>G(p.=)1
c.9106C>G(p.Q3036E)2
c.9116C>T(p.P3039L)3
c.9228A>G(p.=)1
c.92578C>T(p.?)1
c.92579C>T *(p.?)1
c.9275A>G(p.Y3092C)3
c.9275A>T(p.Y3092F)1
c.9286G>A(p.E3096K)1
c.9296A>G(p.N3099S)1
c.9309A>G(p.I3103M)1
c.9335A>G(p.D3112G)1
c.9337A>T(p.I3113F)1
c.9367A>G(p.S3123G)1
c.9383G>A(p.R3128Q)1
c.9422G>C *(p.G3141A)1
c.9501+6G>A(p.?)2
c.9583A>G(p.T3195A)1
c.9587A>G *(p.K3196R)1
c.9605C>G *(p.P3202R)1
VUS, variant of uncertain significance; RefSeq for BRCA2: NM_000059.4; “*” indicates novel variants that had not been reported in disease databases (the deadline for ClinVar is 30 May 2025). The 88 variants were classified according to the results of saturation genome editing; “Number of carriers” indicates the number of individuals carrying each variant.
Table 2. Clinicopathological characteristics among BRCA2 germline variant carriers.
CharacteristicsPathogenic
Variant Carriers
Functionally Pathogenic
VUS Carriers
Functionally Benign
VUS Carriers
Non-CarriersP1P2P3P4
(n = 506)(n = 20)(n = 154)(n = 13,535)
No.%No.%No.%No.%
Age at BC diagnosis, years
Mean ± SD47.3 ± 10.5 48.2 ± 9.4 49.9 ± 10.5 51.3 ± 11.3 <0.0010.150.120.69
≤40 years14428.5315.02415.6225616.7<0.0011.000.800.29
>40 years36271.51785.013084.411,27983.3
Family history of malignant tumor<0.0010.0020.440.32
Yes25851.01365.04327.9421431.1
No24849.0735.011172.1932168.9
Family history of breast or ovarian cancer<0.0010.0020.971.00
Yes17735.0735.01610.4135210.0
No32965.01365.013889.612,18390.0
Bilateral breast cancer<0.0010.0850.281.00
Yes6112.1210.063.93302.4
No44587.91890.014896.113,20597.6
Tumor size0.100.620.700.81
≤2 cm18036.3736.85838.9528441.1
>2–5 cm28156.71052.78355.7675052.5
>5 cm357.0210.585.48286.4
Unknown10 1 5 673
ER status<0.0010.290.600.039
Negative9619.0840.04429.1354726.9
Positive40881.01260.010770.9964573.1
Unknown2 0 3 343
PR status <0.0010.0511.000.005
Negative12424.61155.04932.5418232.1
Positive38075.4945.010267.5885567.9
Unknown2 0 3 498
HER2 status<0.0010.590.910.48
Negative42887.71583.310273.4907374.2
Positive6012.3316.73726.6316225.8
Unknown18 2 15 1300
Lymph nodes status0.210.340.860.50
Negative27455.0844.48859.5741158.4
Positive22045.01055.66040.5528041.6
Unknown12 2 6 844
Non-carriers: Patients carrying BRCA2 benign variants or without any BRCA2 variant. p values: P1, BRCA2 pathogenic variant carriers versus non-carriers; P2, functionally pathogenic VUS carriers versus non-carriers; P3, functionally benign VUS carriers versus non-carriers; P4, pathogenic variant carriers versus functionally pathogenic VUS carriers. Abbreviations: BC, breast cancer; SD, standard deviation; ER, estrogen receptor; PR, progesterone receptor; HER2, human epidermal growth factor receptor 2; VUS, variant of uncertain significance. Statistical note: Pairwise comparisons were adjusted using the Bonferroni correction (p < 0.0125).
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.