

Impact of Decision Aids for Shared Decision-Making for Patients with Early Stage Breast Cancer: A Systematic Review

 , ,
 , , , , and

Simple Summary
Abstract
1. Introduction
2. Methodology
2.1. Search Strategy
- Population: female patients with early stage breast cancer;
- Intervention: Patient Decision Aids (PDAs);
- Comparison: control groups (where applicable) or none;
- Outcomes: the impact of PDAs on decision-making, decision quality, satisfaction, knowledge, usefulness, or effectiveness in treatment decision-making, as well as their acceptability, usability, and feasibility for implementation in routine clinical practice;
- Study design: quantitative, qualitative, and mixed-methods studies.
2.2. Eligibility Criteria
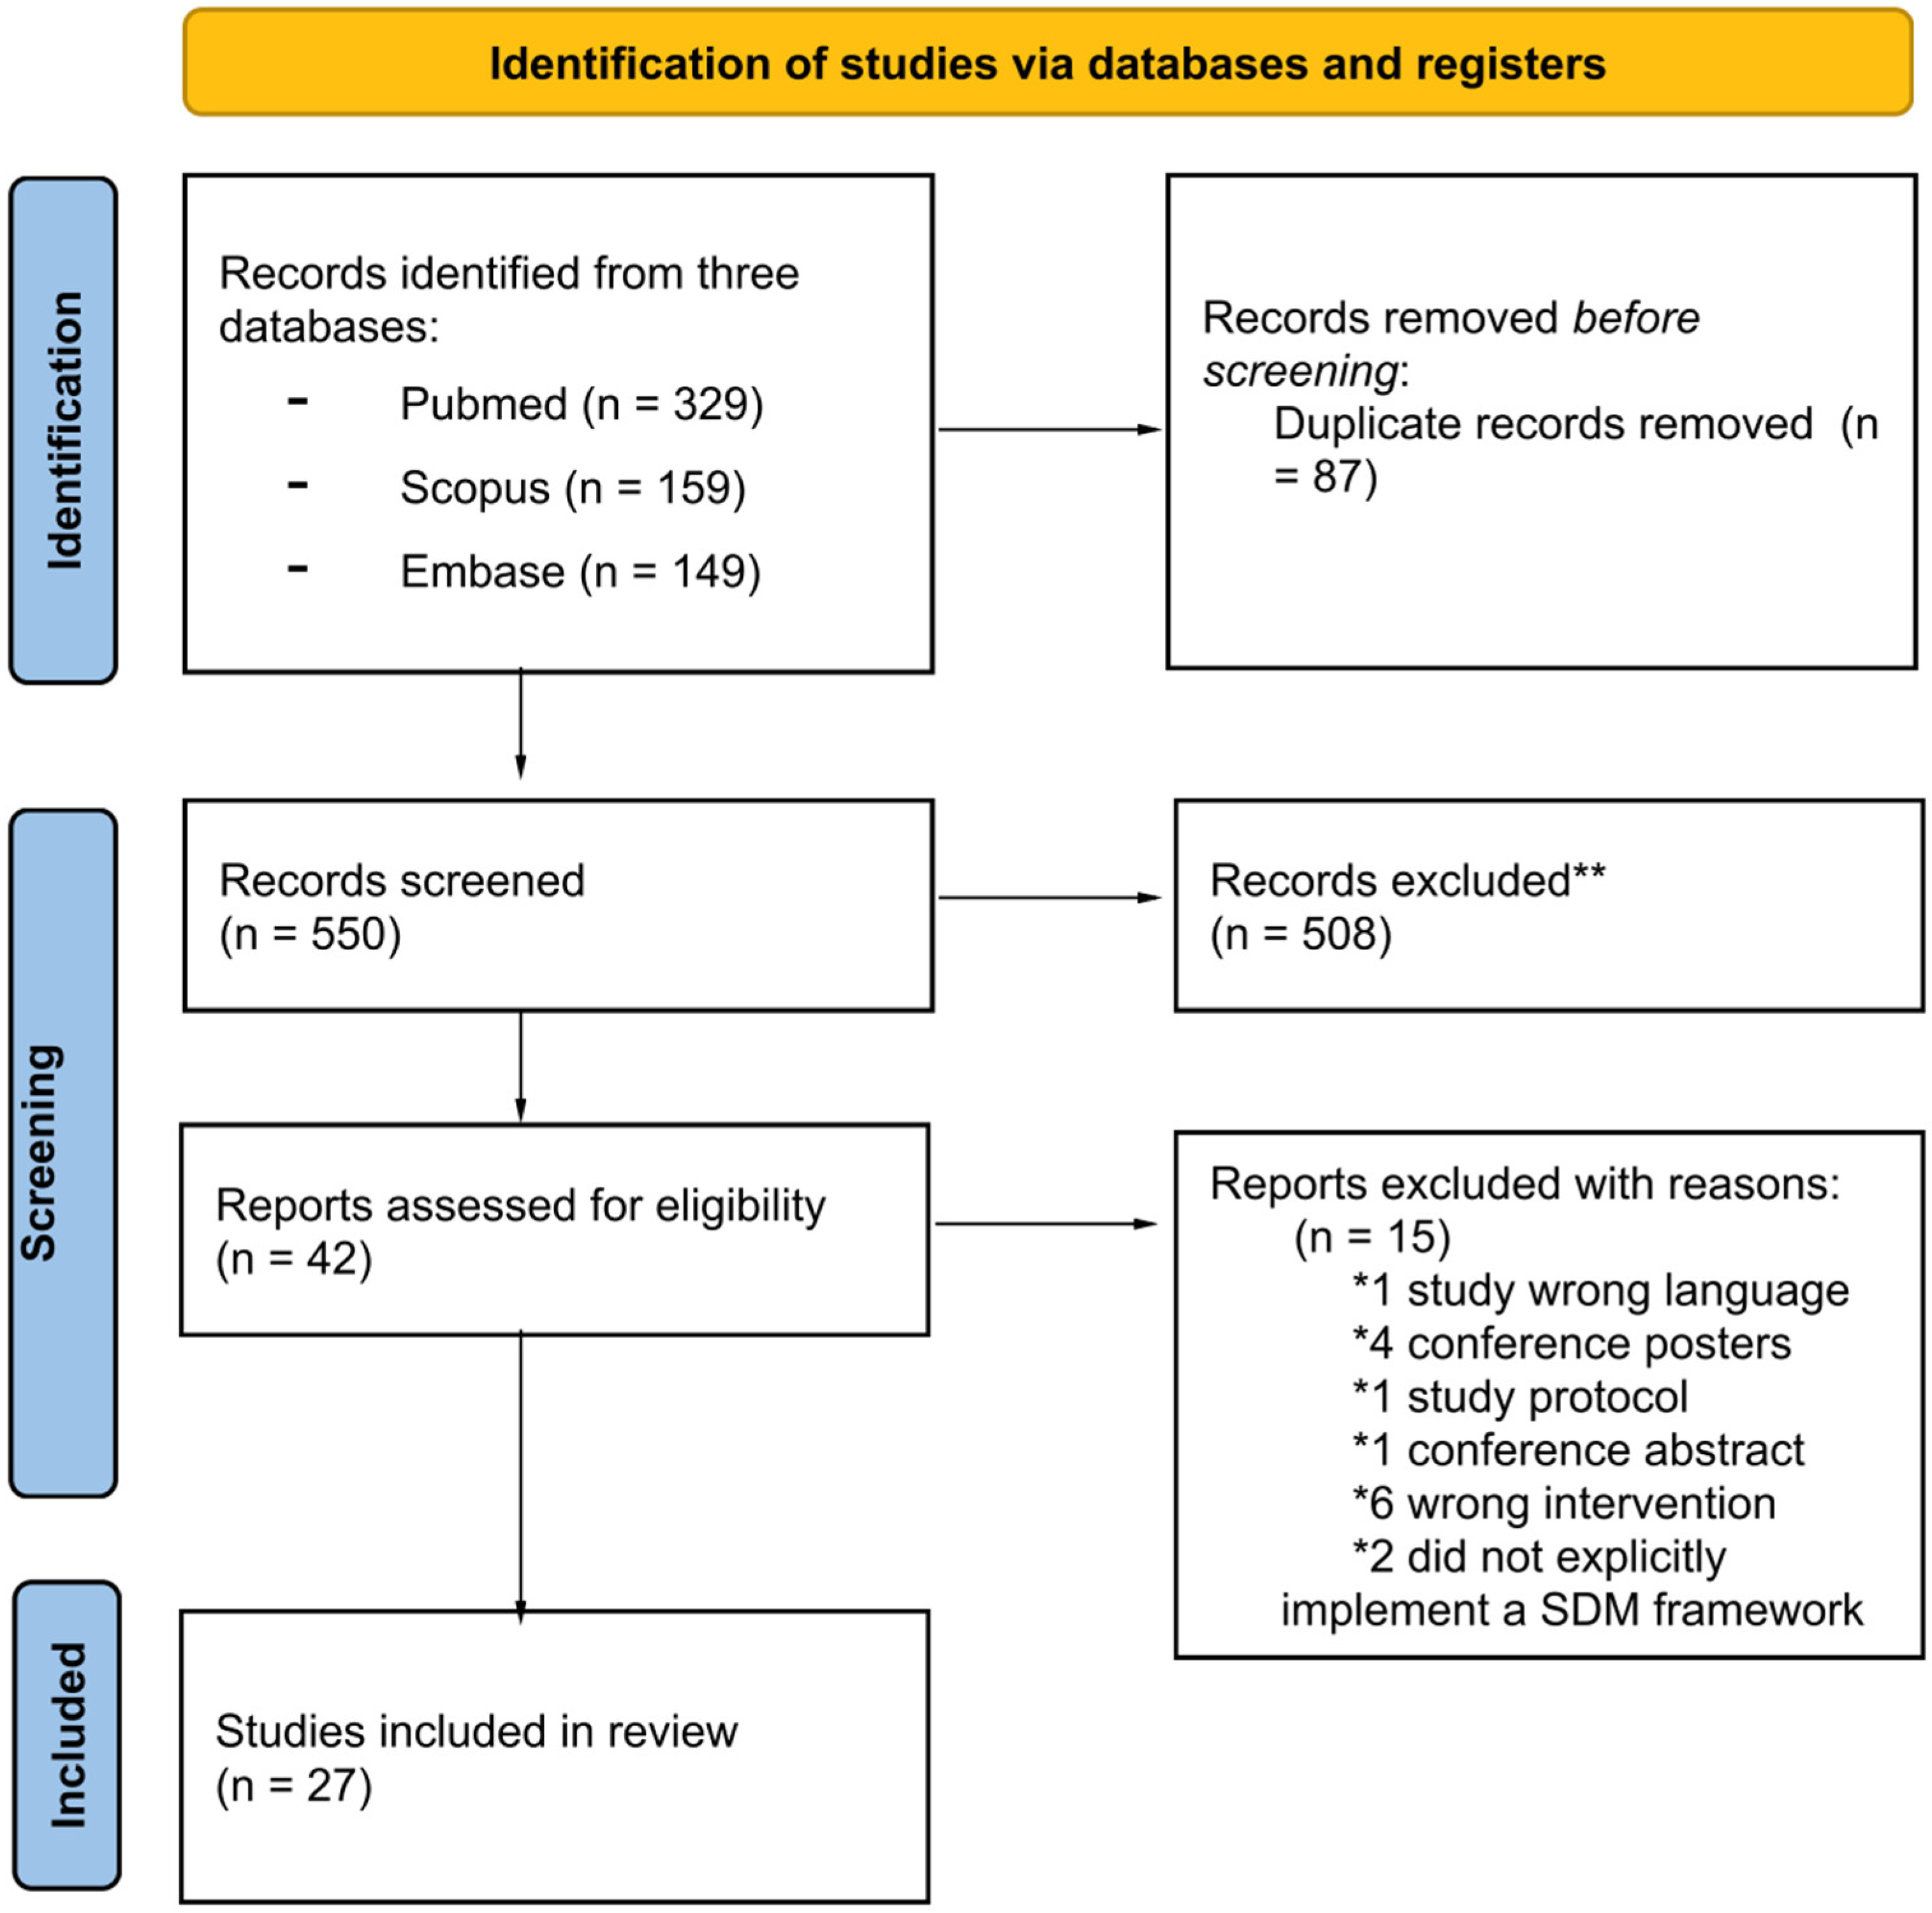
2.3. Selection of Sources of Evidence
2.4. Data Extraction Process
2.5. Quality Assessment of the Included Studies
2.6. Data Synthesis and Analysis
3. Results
3.1. Included Studies Characteristics
3.1.1. Sociodemographic Characteristics of the Included Studies
3.1.2. Characteristics of PDAs Implemented by the Included Studies
3.1.3. Quality Assessment of Included Studies
3.2. Quantitative Results
3.2.1. Decision-Related Outcomes
3.2.2. Knowledge-Related Outcomes
3.2.3. Psychological Well-Being and Quality of Life
3.3. Qualitative Outcomes Related to PDAs Implemented
3.4. Outcomes from Lower SES and Lower Literacy Populations
3.5. Other Outcomes Related to PDA Implementation
4. Discussion
5. Strengths and Limitations
6. Conclusions and Clinical Implications
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Appendix A

| STUDY | SCREENING QUESTIONS | QUANTITATIVE STUDIES | QUALITATIVE STUDIES | MIXED METHODS STUDIES | TOTAL MMAT SCORE |
|---|---|---|---|---|---|
| [25] | 1; 1 | 1; 1; 1; CAN’T TELL; 1 | 6 | ||
| [26] | 0; CAN’T TELL | CAN’T TELL; CAN’T TELL; 1; 1; 1 | 3 | ||
| [27] | 1; 1 | CAN’T TELL; 0; 0; CAN’T TELL; 1 | 3 | ||
| [28] | 1; 1 | 0; CAN’T TELL; CAN’T TELL; 0; 1 | 3 | ||
| [29] | 1; 1 | 1; 1; 1; CAN’T TELL; 1 | 6 | ||
| [30] | 1; 1 | CAN’T TELL; 1; 0; 1; 0 | 4 | ||
| [31] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [32] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [33] | 1; 1 | 1; CAN’T TELL; 1; CAN’T TELL; 1 | 5 | ||
| [34] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [35] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [36] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [37] | 1; 1 | CAN’T TELL; 1; 1; 1; 0 | 5 | ||
| [38] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [39] | 1; 1 | 1; 1; 0; CAN’T TELL; 1 | 5 | ||
| [40] | 1; 1 | 1; 1; 1; 0; 1 | 6 | ||
| [41] | 1; 1 | 0; 1; 1; 1; 1 | 6 | ||
| [42] | 1; 1 | 1; 1; 1; CAN’T TELL; 1 | 6 | ||
| [43] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [44] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [45] | 1; 1 | 1; 1; 1; 0; 1 | 6 | ||
| [46] | 1; 1 | 1; 1; 1; 0; 1 | 6 | ||
| [47] | 1; 1 | 1; CAN’T TELL; 0; CAN’T TELL; 1 | 4 | ||
| [48] | 1; 1 | 1; 1; 1; CAN’T TELL; 1 | 6 | ||
| [49] | 1; 1 | 1; 1; 1; 1; 1 | 7 | ||
| [50] | 1; 1 | 1; 1; 1; CAN’T TELL; 1 | 6 | ||
| [51] | 1; 1 | 1; 1; 1; CAN’T TELL; CAN’T TELL | 5 |
References
- Łukasiewicz, S.; Czeczelewski, M.; Forma, A.; Baj, J.; Sitarz, R.; Stanisławek, A. Breast Cancer-Epidemiology, Risk Factors, Classification, Prognostic Markers, and Current Treatment Strategies—An Updated Review. Cancers 2021, 13, 4287. [Google Scholar] [CrossRef] [Scilit]
- Stages Archives. National Breast Cancer Foundation. Available online: https://www.nationalbreastcancer.org/breast-cancer-staging/ (accessed on 31 January 2026).
- AJCC Version 9 Cancer Staging System. Available online: https://www.facs.org/quality-programs/cancer-programs/american-joint-committee-on-cancer/version-9/ (accessed on 5 August 2026).
- Franceschini, G.; Sanchez, A.M.; Di Leone, A.; Magno, S.; Moschella, F.; Accetta, C.; Masetti, R. New trends in breast cancer surgery: A therapeutic approach increasingly efficacy and respectful of the patient. Il G. Di Chir.-J. Ital. Assoc. Hosp. Surg. 2015, 36, 145–152. [Google Scholar] [CrossRef] [Scilit]
- van der Horst, D.E.M.; Garvelink, M.M.; Bos, W.J.W.; Stiggelbout, A.M.; Pieterse, A.H. For which decisions is Shared Decision Making considered appropriate?—A systematic review. Patient Educ. Couns. 2023, 106, 3–16. [Google Scholar] [CrossRef] [Scilit]
- Politi, M.C.; Lewis, C.L.; Frosch, D.L. Supporting shared decisions when clinical evidence is low. Med. Care Res. Rev. 2013, 70, 113S–128S. [Google Scholar] [CrossRef] [Scilit]
- Elwyn, G.; Frosch, D.; Thomson, R.; Joseph-Williams, N.; Lloyd, A.; Kinnersley, P.; Cording, E.; Tomson, D.; Dodd, C.; Rollnick, S.; et al. Shared Decision Making: A Model for Clinical Practice. J. Gen. Intern. Med. 2012, 27, 1361–1367. [Google Scholar] [CrossRef] [Scilit]
- Charles, C.; Gafni, A.; Whelan, T. Self-reported use of shared decision-making among breast cancer specialists and perceived barriers and facilitators to implementing this approach. Health Expect. Int. J. Public Particip. Health Care Health Policy 2004, 7, 338–348. [Google Scholar] [CrossRef] [Scilit]
- Kini, V.; Ho, P.M. Interventions to Improve Medication Adherence: A Review. JAMA 2018, 320, 2461–2473. [Google Scholar] [CrossRef] [Scilit]
- Riva, S.; Monti, M.; Iannello, P.; Pravettoni, G.; Schulz, P.J.; Antonietti, A. A preliminary mixed-method investigation of trust and hidden signals in medical consultations. PLoS ONE 2014, 9, e90941. [Google Scholar] [CrossRef] [Scilit]
- Stacey, D.; Légaré, F.; Lewis, K.; Barry, M.J.; Bennett, C.L.; Eden, K.B.; Holmes-Rovner, M.; Llewellyn-Thomas, H.; Lyddiatt, A.; Thomson, R.; et al. Decision aids for people facing health treatment or screening decisions. Cochrane Database Syst. Rev. 2017, 4, CD001431. [Google Scholar] [CrossRef] [Scilit]
- Stacey, D.; Samant, R.; Bennett, C. Decision making in oncology: A review of patient decision aids to support patient participation. CA Cancer J. Clin. 2008, 58, 293–304. [Google Scholar] [CrossRef] [Scilit]
- Sebri, V.; Marzorati, C.; Dorangricchia, P.; Monzani, D.; Grasso, R.; Prelaj, A.; Provenzano, L.; Mazzeo, L.; Dumitrascu, A.D.; Sonnek, J.; et al. The impact of decision tools during oncological consultation with lung cancer patients: A systematic review within the I3LUNG project. Cancer Med. 2024, 13, e7159. [Google Scholar] [CrossRef] [Scilit]
- O’Brien, M.A.; Whelan, T.J.; Villasis-Keever, M.; Gafni, A.; Charles, C.; Roberts, R.; Schiff, S.; Cai, W. Are cancer-related decision aids effective? A systematic review and meta-analysis. J. Clin. Oncol. Off. J. Am. Soc. Clin. Oncol. 2009, 27, 974–985. [Google Scholar] [CrossRef] [Scilit]
- McAlpine, K.; Lewis, K.B.; Trevena, L.J.; Stacey, D. What Is the Effectiveness of Patient Decision Aids for Cancer-Related Decisions? A Systematic Review Subanalysis. JCO Clin. Cancer Inform. 2018, 2, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Ter Stege, J.A.; Woerdeman, L.A.E.; Kieffer, J.M.; Sherman, K.A.; Agelink van Rentergem, J.A.; van Duijnhoven, F.H.; van Huizum, M.A.; Gerritsma, M.A.; Kuenen, M.; Corten, E.M.L.; et al. Efficacy of a Decision Aid in Breast Cancer Patients Considering Immediate Reconstruction: Results of a Randomized Controlled Trial. Plast. Reconstr. Surg. 2024, 154, 706–722. [Google Scholar] [CrossRef] [Scilit]
- Tariman, J.D.; Berry, D.L.; Cochrane, B.; Doorenbos, A.; Schepp, K. Preferred and actual participation roles during health care decision making in persons with cancer: A systematic review. Ann. Oncol. Off. J. Eur. Soc. Med. Oncol. 2010, 21, 1145–1151. [Google Scholar] [CrossRef] [Scilit]
- Hahlweg, P.; Kriston, L.; Scholl, I.; Brähler, E.; Faller, H.; Schulz, H.; Weis, J.; Koch, U.; Wegscheider, K.; Mehnert, A.; et al. Cancer patients’ preferred and perceived level of involvement in treatment decision-making: An epidemiological study. Acta Oncol. 2020, 59, 967–974. [Google Scholar] [CrossRef] [Scilit]
- Kehl, K.L.; Landrum, M.B.; Arora, N.K.; Ganz, P.A.; van Ryn, M.; Mack, J.W.; Keating, N.L. Association of Actual and Preferred Decision Roles with Patient-Reported Quality of Care: Shared Decision Making in Cancer Care. JAMA Oncol. 2015, 1, 50–58. [Google Scholar] [CrossRef] [Scilit]
- Vogel, B.A.; Helmes, A.W.; Hasenburg, A. Concordance between patients’ desired and actual decision-making roles in breast cancer care. Psycho-Oncol. J. Psychol. Soc. Behav. Dimens. Cancer 2008, 17, 182–189. [Google Scholar] [CrossRef] [Scilit]
- Durand, M.-A.; Carpenter, L.; Dolan, H.; Bravo, P.; Mann, M.; Bunn, F.; Elwyn, G. Do Interventions Designed to Support Shared Decision-Making Reduce Health Inequalities? A Systematic Review and Meta-Analysis. PLoS ONE 2014, 9, e94670. [Google Scholar] [CrossRef] [Scilit]
- Amir-Behghadami, M.; Janati, A. Population, Intervention, Comparison, Outcomes and Study (PICOS) design as a framework to formulate eligibility criteria in systematic reviews. Emerg. Med. J. 2020, 37, 387. [Google Scholar] [CrossRef] [Scilit]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan-a web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit]
- Hong, Q.N.; Fàbregues, S.; Bartlett, G.; Boardman, F.; Cargo, M.; Dagenais, P.; Gagnon, M.-P.; Griffiths, F.; Nicolau, B.; O’Cathain, A.; et al. The Mixed Methods Appraisal Tool (MMAT) version 2018 for information professionals and researchers. Educ. Inf. 2018, 34, 285–291. [Google Scholar] [CrossRef] [Scilit]
- Joshi, S.; Ramarajan, L.; Ramarajan, N.; Lee, S.S.; Deshpande, O.; Fernandes, E.; Engineer, M.; Srivastava, G.; Vanmali, V.; Kannan, S.; et al. Effectiveness of a Decision Aid Plus Standard Care in Surgical Management Among Patients with Early Breast Cancer: A Randomized Clinical Trial. JAMA Netw. Open 2023, 6, e2335941. [Google Scholar] [CrossRef] [Scilit]
- Schubbe, D.; Yen, R.W.; Saunders, C.H.; Elwyn, G.; Forcino, R.C.; O’Malley, A.J.; Politi, M.C.; Margenthaler, J.; Volk, R.J.; Sepucha, K.; et al. Implementation and sustainability factors of two early-stage breast cancer conversation aids in diverse practices. Implement. Sci. 2021, 16, 51. [Google Scholar] [CrossRef] [Scilit]
- Durand, M.-A.; Yen, R.W.; O’Malley, A.J.; Schubbe, D.; Politi, M.C.; Saunders, C.H.; Dhage, S.; Rosenkranz, K.; Margenthaler, J.; Tosteson, A.N.A.; et al. What matters most: Randomized controlled trial of breast cancer surgery conversation aids across socioeconomic strata. Cancer 2021, 127, 422–436. [Google Scholar] [CrossRef] [Scilit]
- Hawley, S.T.; Newman, L.; Griggs, J.J.; Kosir, M.A.; Katz, S.J. Evaluating a Decision Aid for Improving Decision Making in Patients with Early-stage Breast Cancer. Patient-Patient-Centered Outcomes Res. 2016, 9, 161–169. [Google Scholar] [CrossRef] [Scilit]
- Lam, W.W.T.; Chan, M.; Or, A.; Kwong, A.; Suen, D.; Fielding, R. Reducing Treatment Decision Conflict Difficulties in Breast Cancer Surgery: A Randomized Controlled Trial. J. Clin. Oncol. 2013, 31, 2879–2885. [Google Scholar] [CrossRef] [Scilit]
- Marziliano, A.; Miller, S.M.; Fleisher, L.G.; Ropka, M.E.; Stanton, A.L.; Wen, K.Y.; Cornelius, T.; Lapitan, E.; Diefenbach, M.A. Examining the impact of a multimedia intervention on decisional conflict and psychological distress among early-stage breast cancer patients: Results from a nationwide RCT. Transl. Behav. Med. 2023, 13, 727–735. [Google Scholar] [CrossRef] [Scilit]
- Minami, C.A.; Freedman, R.A.; Karamourtopoulos, M.; Pinheiro, A.; Gilliam, E.; Aliberti, G.; Pories, S.E.; Recht, A.; Lotz, M.; Dominici, L.S.; et al. Acceptability of a patient decision aid for women aged 70 and older with stage I, estrogen receptor-positive, HER2-negative breast cancer. J. Geriatr. Oncol. 2021, 12, 724–730. [Google Scholar] [CrossRef] [Scilit]
- Belkora, J.K.; Volz, S.; Teng, A.E.; Moore, D.H.; Loth, M.K.; Sepucha, K.R. Impact of decision aids in a sustained implementation at a breast care center. Patient Educ. Couns. 2012, 86, 195–204. [Google Scholar] [CrossRef] [Scilit]
- Jibaja-Weiss, M.L.; Volk, R.J.; Granchi, T.S.; Neff, N.E.; Robinson, E.K.; Spann, S.J.; Aoki, N.; Friedman, L.C.; Beck, J.R. Entertainment education for breast cancer surgery decisions: A randomized trial among patients with low health literacy. Patient Educ. Couns. 2011, 84, 41–48. [Google Scholar] [CrossRef] [Scilit]
- Savelberg, W.; Smidt, M.; Boersma, L.J.; van der Weijden, T. Elicitation of preferences in the second half of the shared decision making process needs attention; a qualitative study. BMC Health Serv. Res. 2020, 20, 635. [Google Scholar] [CrossRef] [Scilit]
- Yen, R.W.; Durand, M.-A.; Harris, C.; Cohen, S.; Ward, A.; O’Malley, A.J.; Schubbe, D.; Saunders, C.H.; Elwyn, G. Text-only and picture conversation aids both supported shared decision making for breast cancer surgery: Analysis from a cluster randomized trial. Patient Educ. Couns. 2020, 103, 2235–2243. [Google Scholar] [CrossRef] [Scilit]
- Sawka, C.A.; Goel, V.; Mahut, C.A.; Taylor, G.A.; Thiel, E.C.; O’Connor, A.M.; Ackerman, I.; Burt, J.H.; Gort, E.H. Development of a patient decision aid for choice of surgical treatment for breast cancer. Health Expect. 1998, 1, 23–36. [Google Scholar] [CrossRef] [Scilit]
- Alam, S.; Elwyn, G.; Percac-Lima, S.; Grande, S.; Durand, M.-A. Assessing the acceptability and feasibility of encounter decision aids for early stage breast cancer targeted at underserved patients. BMC Med. Inform. Decis. Mak. 2016, 16, 147. [Google Scholar] [CrossRef] [Scilit]
- Schonberg, M.A.; Freedman, R.A.; Recht, A.R.; Jacobson, A.R.; Aliberti, G.M.; Karamourtopoulos, M.; Nakhlis, F.; McCarthy, E.P.; Pories, S.E.; Sharma, R.; et al. Developing a patient decision aid for women aged 70 and older with early stage, estrogen receptor positive, HER2 negative, breast cancer. J. Geriatr. Oncol. 2019, 10, 980–986. [Google Scholar] [CrossRef] [Scilit]
- Osaka, W.; Nakayama, K. Effect of a decision aid with patient narratives in reducing decisional conflict in choice for surgery among early-stage breast cancer patients: A three-arm randomized controlled trial. Patient Educ. Couns. 2017, 100, 550–562. [Google Scholar] [CrossRef] [Scilit]
- Pesavento, C.M.; Kazemi, R.J.; Kappelman, A.; Thompson, J.L.; Jobin, C.; Wang, T.; Dossett, L.A. Pilot testing a patient decision aid as a strategy to reduce overtreatment for older women with early-stage breast cancer. Am. J. Surg. 2024, 235, 115774. [Google Scholar] [CrossRef] [Scilit]
- Durand, M.-A.; Alam, S.; Grande, S.W.; Elwyn, G. “Much clearer with pictures”: Using community-based participatory research to design and test a Picture Option Grid for underserved patients with breast cancer. BMJ Open 2016, 6, e010008. [Google Scholar] [CrossRef] [Scilit]
- Whelan, T.; Levine, M.; Willan, A.; Gafni, A.; Sanders, K.; Mirsky, D.; Chambers, S.; O’Brien, M.A.; Reid, S.; Dubois, S. Effect of a decision aid on knowledge and treatment decision making for breast cancer surgery: A randomized trial. JAMA 2004, 292, 435–441. [Google Scholar] [CrossRef] [Scilit]
- Wilkins, E.G.; Lowery, J.C.; Copeland, L.A.; Goldfarb, S.L.; Wren, P.A.; Janz, N.K. Impact of an Educational Video on Patient Decision Making in Early Breast Cancer Treatment. Med. Decis. Mak. 2006, 26, 589–598. [Google Scholar] [CrossRef] [Scilit]
- Molenaar, S.; Sprangers, M.A.; Rutgers, E.J.T.; Luiten, E.J.; Mulder, J.; Bossuyt, P.M.; van Everdingen, J.J.; Oosterveld, P.; de Haes, H.C. Decision Support for Patients with Early-Stage Breast Cancer: Effects of an Interactive Breast Cancer CDROM on Treatment Decision, Satisfaction, and Quality of Life. J. Clin. Oncol. 2001, 19, 1676–1687. [Google Scholar] [CrossRef] [Scilit]
- Jibaja-Weiss, M.L.; Volk, R.J.; Granch, T.S.; Nefe, N.E.; Spann, S.J.; Aoki, N.; Robinson, E.K.; Freidman, L.C.; Beck, J.R. Entertainment education for informed breast cancer treatment decisions in low-literate women: Development and initial evaluation of a patient decision aid. J. Cancer Educ. Off. J. Am. Assoc. Cancer Educ. 2006, 21, 133–139. [Google Scholar] [CrossRef] [Scilit]
- Jibaja-Weiss, M.L.; Volk, R.J.; Friedman, L.C.; Granchi, T.S.; Neff, N.E.; Spann, S.J.; Robinson, E.K.; Aoki, N.; Robert Beck, J. Preliminary testing of a just-in-time, user-defined values clarification exercise to aid lower literate women in making informed breast cancer treatment decisions. Health Expect. Int. J. Public Particip. Health Care Health Policy 2006, 9, 218–231. [Google Scholar] [CrossRef] [Scilit]
- Stankowski-Drengler, T.J.; Tucholka, J.L.; Bruce, J.G.; Steffens, N.M.; Schumacher, J.R.; Greenberg, C.C.; Wilke, L.G.; Hanlon, B.; Steiman, J.; Neuman, H.B. A Randomized Controlled Trial Evaluating the Impact of Pre-Consultation Information on Patients’ Perception of Information Conveyed and Satisfaction with the Decision-Making Process. Ann. Surg. Oncol. 2019, 26, 3275–3281. [Google Scholar] [CrossRef] [Scilit]
- Tucholka, J.L.; Yang, D.-Y.; Bruce, J.G.; Steffens, N.M.; Schumacher, J.R.; Greenberg, C.C.; Wilke, L.G.; Steiman, J.; Neuman, H.B. A Randomized Controlled Trial Evaluating the Impact of Web-Based Information on Breast Cancer Patients’ Knowledge of Surgical Treatment Options. J. Am. Coll. Surg. 2018, 226, 126. [Google Scholar] [CrossRef] [Scilit]
- D’Alimonte, L.; Angus, J.; Wong, J.; Paszat, L.; Soren, B.; Szumacher, E. Working Toward a Decision: The Development and First Impressions of a Decision Aid for Older Women with Early-stage Breast Cancer. J. Med. Imaging Radiat. Sci. 2012, 43, 60–65. [Google Scholar] [CrossRef] [Scilit]
- Politi, M.C.; Myckatyn, T.M.; Cooksey, K.; Olsen, M.A.; Smith, R.M.; Foraker, R.; Parrish, K.; Phommasathit, C.; Brock, G.; Janse, S.; et al. A Randomized Controlled Trial of the Implementation of BREASTChoice, a Multilevel Breast Reconstruction Decision Support Tool with Personalized Risk Prediction. Ann. Surg. 2024, 10-1097, 6354. [Google Scholar] [CrossRef] [Scilit]
- Schumacher, J.R.; Hanlon, B.M.; Zahrieh, D.; Rathouz, P.J.; Tucholka, J.L.; McKinney, G.; Tan, A.D.; Breuer, C.R.; Bailey, L.; Higham, A.M.; et al. Impact of a Web-Based Decision Aid on Socioeconomically Disadvantaged Patients’ Engagement in Breast Surgery Decision-Making: Stepped-Wedge Clinical Trial (Alliance-A231701CD). Ann. Surg. Oncol. 2025, 32, 5540–5550. [Google Scholar] [CrossRef] [Scilit]
- ASBrS. Shared Decision-Making Tools. Available online: https://www.breastsurgeons.org/management/practice/shair_collaborative (accessed on 9 February 2026).
- Roy, M.K.; Higgins, M.G.; Adams, M.; Tevis, S. Improving value-concordant shared decision making through the use of patient decision aids in breast cancer: A narrative review. Ann. Breast Surg. 2025, 9, 4. [Google Scholar] [CrossRef] [Scilit]
- Stacey, D.; Lewis, K.B.; Smith, M.; Carley, M.; Volk, R.; Douglas, E.E.; Pacheco-Brousseau, L.; Finderup, J.; Gunderson, J.; Barry, M.J.; et al. Decision aids for people facing health treatment or screening decisions. Cochrane Database Syst. Rev. 2024, 4, CD001431. [Google Scholar] [CrossRef] [Scilit]
- Fagerlin, A.; Sepucha, K.R.; Couper, M.P.; Levin, C.A.; Singer, E.; Zikmund-Fisher, B.J. Patients’ knowledge about 9 common health conditions: The DECISIONS survey. Med. Decis. Mak. Int. J. Soc. Med. Decis. Mak. 2010, 30, 35S–52S. [Google Scholar] [CrossRef] [Scilit]
- Oers, H.V.; Schlebusch, L. Breast Cancer Patients’ Experiences of Psychological Distress, Hopelessness, and Suicidal Ideation. J. Nat. Sci. Med. 2021, 4, 250. [Google Scholar] [CrossRef] [Scilit]
- Lawlor, V.M.; Webb, C.A.; Wiecki, T.V.; Frank, M.J.; Trivedi, M.; Pizzagalli, D.A.; Dillon, D.G. Dissecting the impact of depression on decision-making. Psychol. Med. 2020, 50, 1613–1622. [Google Scholar] [CrossRef] [Scilit]
- Hartley, C.A.; Phelps, E.A. Anxiety and decision-making. Biol. Psychiatry 2012, 72, 113–118. [Google Scholar] [CrossRef] [Scilit]
- Sebri, V.; Policardo, G.R.; Pravettoni, G. How to improve emotional regulation in breast cancer survivors? A psychological intervention. Front. Psychol. 2024, 15, 1443635. [Google Scholar] [CrossRef] [Scilit]
- Sebri, V.; Dorangricchia, P.; Monzani, D.; Marzorati, C.; Grasso, R.; Conti, L.; Russo, G.L.; Provenzano, L.; Dumitrascu, A.D.; Pravettoni, G. The Implementation of Decision Aids During Medical Consultations for Lung Cancer Patients: A Focus Group Within I3LUNG Project. J. Cancer Educ. Off. J. Am. Assoc. Cancer Educ. 2025, 40, 713–725. [Google Scholar] [CrossRef] [Scilit]
- Noteboom, E.A.; May, A.M.; van der Wall, E.; de Wit, N.J.; Helsper, C.W. Patients’ preferred and perceived level of involvement in decision making for cancer treatment: A systematic review. Psycho-Oncology 2021, 30, 1663–1679. [Google Scholar] [CrossRef] [Scilit]
- Goodwin, J.S.; Li, S.; Zhou, J.; Kuo, Y.-F.; Nattinger, A. Variation among hospitals in the continuity of care for older hospitalized patients: A cross-sectional cohort study. BMC Health Serv. Res. 2021, 21, 552. [Google Scholar] [CrossRef] [Scilit]
- Lucero, R.J.; Lake, E.T.; Aiken, L.H. Variations in nursing care quality across hospitals. J. Adv. Nurs. 2009, 65, 2299–2310. [Google Scholar] [CrossRef] [Scilit]
- Kondylakis, H.; Koumakis, L.; Tsiknakis, M.; Marias, K.; Genitsaridi, E.; Pravettoni, G.; Gorini, A.; Mazzocco, K. Smart Recommendation Services in Support of Patient Empowerment and Personalized Medicine. In Multimedia Services in Intelligent Environments: Recommendation Services; Tsihrintzis, G.A., Virvou, M., Jain, L.C., Eds.; Springer International Publishing: Berlin/Heidelberg, Germany, 2013; pp. 39–61. ISBN 978-3-319-00375-7. [Google Scholar]
- Mathur, S.; Sutton, J. Personalized medicine could transform healthcare. Biomed. Rep. 2017, 7, 3–5. [Google Scholar] [CrossRef] [Scilit]
- Lognos, B.; Boulze-launay, I.; Élodie, M.; Bourrel, G.; Amouyal, M.; Gocko, X.; Bernard, C.; Ninot, G.; Oude Engberink, A. The central role of peers facilitators in the empowerment of breast cancer patients: A qualitative study. BMC Women’s Health 2022, 22, 308. [Google Scholar] [CrossRef] [Scilit]
- Ellermann, C.; Hinneburg, J.S.; Wilhelm, C.; Rebitschek, F.G. Can health information and decision aids decrease inequity in health care? A systematic review. BMJ Public Health 2025, 3, 1923. [Google Scholar] [CrossRef] [Scilit]
- Arcia, A.; Bales, M.E.; Brown, W.; Co, M.C.; Gilmore, M.; Lee, Y.J.; Park, C.S.; Prey, J.; Velez, M.; Woollen, J.; et al. Method for the Development of Data Visualizations for Community Members with Varying Levels of Health Literacy. AMIA Annu. Symp. Proc. 2013, 2013, 51–60. [Google Scholar]
- Berkman, N.D.; Sheridan, S.L.; Donahue, K.E.; Halpern, D.J.; Crotty, K. Low health literacy and health outcomes: An updated systematic review. Ann. Intern. Med. 2011, 155, 97–107. [Google Scholar] [CrossRef] [Scilit]
- Stacey, D.; Volk, R.J. The International Patient Decision Aid Standards (IPDAS) Collaboration: Evidence Update 2.0. Med. Decis. Mak. 2021, 41, 729–733. [Google Scholar] [CrossRef] [Scilit]
- Lopez-Fernandez, O.; Aguilar Castillo, C.P.; Horrillo, B.; Sánchez de Molina Ramperez, M.L.; Guadalajara, H. The Implementation of Shared Decision-Making Using Patient Decision Aid Tools to Select Breast Cancer Treatment Options: A Systematic Review in the Time of Minimum Quality Standards. Healthcare 2025, 13, 748. [Google Scholar] [CrossRef] [Scilit]
- O’Brien, M.A.; Whelan, T.J.; Charles, C.; Ellis, P.M.; Gafni, A.; Lovrics, P.; Hasler, A.; Dimitry, S. Women’s perceptions of their treatment decision-making about breast cancer treatment. Patient Educ. Couns. 2008, 73, 431–436. [Google Scholar] [CrossRef] [Scilit]
- Clayman, M.L.; Scheibler, F.; Rüffer, J.U.; Wehkamp, K.; Geiger, F. The Six Steps of SDM: Linking theory to practice, measurement and implementation. BMJ Evid.-Based Med. 2024, 29, 75–78. [Google Scholar] [CrossRef] [Scilit]
| STUDY | COUNTRY | SAMPLE SIZE | AGE (Years) | LEVEL OF EDUCATION; HEALTH LITERACY; SES | BREAST TUMOR STAGES | Type of PDA and FORMAT | PDA Content |
|---|---|---|---|---|---|---|---|
| Joshi, S. et al., 2023 [25] | India | N = 245; | median 48; range 23–76 | 58,6% lower or middle SES, 46.4% did not complete college | median tumor size 2.5 cm (0–6); | Navya Patient Preference Tool (Navya-PPT)—online-based | Surgical options; cosmetic outcomes; radiation; treatment costs; patient preferences. |
| [26] | USA | N = 43 | mean 56.6; SD 12.0 | 26%lower SES; 2% never attended high school; 26% high school diploma; 21% some college; 14% 2-year degree; 37% 4-year degree or higher | I–IIIA stages | Option Grid; Picture Option Grid—paper-based | Surgical options; FAQs; survival; recurrence; chemotherapy information. |
| [27] | USA | N = 616; | mean 59.7; SD 12.5 | 44.8% low health literacy; 33% lower SES | I–IIIA stages | Option Grid; Picture Option Grid—paper-based | Surgical options; FAQs; survival; recurrence; chemotherapy information. |
| [28] | USA | N = 101 | mean 53; range 30–80 | 66% some college or more | 0–II stages | unique to the study—online-based | Surgical options; risks/benefits; values clarification; communication support; recurrence and cosmetic outcomes. |
| [29] | China | N = 276 | Experimental group: mean 56.8; SD 10.8; CG: mean 54.6; SD 10.1 | EG: 10.9% tertiary education; 51.4% secondary education; 37.7% primary or no formal education. CG: 10.1% tertiary educaton; 52.9% secondary education; 37% primary or no formal education | I–III stages | unique to the study—paper-based | Treatment options; pros/cons; values clarification; decision guidance. |
| [30] | USA | N = 388 | mean 55.50; SD 11.13 | 48.7% completed college or higher | non metastatic | Healing Choices—online, interactive | Educational resources; patient stories; question prompts; information management. |
| [31] | USA | N = 33 | mean 74.4; SD 3.8 | 72% college graduates | I stage | unique to the study—paper-based | Surgical, radiation and endocrine treatment information. |
| [32] | USA | N = 437 | mean 54; median 54 | 32% lower than college graduates; 32% college graduates; 34% higher than college graduates | 18% stage 0; 67% stage I or II; 15% stage III or IV | 5 different PDAs unique to the study—online-based | Five PDAs covering surgery, reconstruction, adjuvant therapy, DCIS and metastatic disease. |
| [33] | USA | N = 76 | EG: mean 49.5; SD 10.3. CG: mean 52.4; SD 12.1 | patients have no medical insurance and many have a high school education or less | I–IIIA stages | unique to the study—online, interactive | Interactive patient story; treatment information; decision guidance; common concerns. |
| [34] | Netherlands | N = 60 [N = 40 quantitative data; N = 20 qualitative data] | Quantitative data: mean 54, SD 10.1 Qualitative data: mean 53; SD 9.7 | N = 4 primary and lower secondary education; N = 7 upper secondary education, post-secondary education and short cycle tertiary education; N = 9 bachelor, master or doctorate degrees | I or II stages | unique to the study—online-based | Surgical information; SDM implementation; communication support. |
| [35] | USA | N = 311 | mean 60.5; SD 12.2 | education received = 64.6% less than college degree; 35.4% 4-year college degree or higher. health literacy = 54% adequate, 45.3% inadequate, 0.6% missing/prefer not to say. 66.6% higher SES | I–IIIA stages | Option Grid; Picture Option Grid—paper-based | Surgical options; FAQs; survival; recurrence; chemotherapy information. |
| [36] | Canada | N = 50 [Focus group N = 22; Pilot 1: N = 18; Pilot 2 N = 10] | Pilot 1: mean 55; median 52; range 37–74. Pilot 2: mean 52; median 43; range 34–78 | Pilot 1: N = 5 high school; N = 6 some college; N = 7 some university. Pilot 2: N = 3 high school, N = 4 some college; N = 3 some university | I or II stages | unique to the study—paper-based + audio | Surgery; radiation; recurrence; complications; reconstruction; values clarification. |
| [37] | USA | N = 288 [N = 5 focus group; N = 268 web-based questionnaire; N = 15 Interviews] | Focus group: N/A Web-based questionnaires: 79% between 45 and 74 years Interviews: 40% between 55 and 64 years; mean 56.8; SE 4.40 | Focus group: N/A Web-based questionnaires: 1.5% some high school or less; 22.8% high school graduate; 27.2% some college/technical school; 24.3% college graduate. Interviews: N = 10 women of lower SES | I to IIIC stages | Option Grid; Picture Option Grid; Comic Option Grid (adapted for a low SES and low literacy populations)—paper-based | Surgical options; FAQs; survival; recurrence; chemotherapy information. |
| [38] | USA | N = 35 | mean 74.3; SD 3.3 | 6% high school; 26% some college; 29% completed college; 40% beyond college | early stage, max 3 cm | unique to the study—paper-based | General health; treatment options; values clarification; endocrine therapy; FAQs. |
| [39] | Japan | N = 210 | DA + Narratives EG: mean 50.2; SD 10.7 DA EG: mean 49.7; SD 9.9. CG: mean 48.6; SD 8.9. | DA + Narratives EG: 25.9% high school; 44.8% technical school; 27.6% college; 1.7%graduate. DA EG: 21.3% High school; 50.9% technical school; 26.2% college; 1.6% graduate. CG: 18.2% High school; 38.2% technical school; 36.4% college; 7.3% graduate. | 0–III stage | developed ad hoc; developed ad hoc + patients narratives—paper-based | Surgical options; benefits/harms; values clarification; decision guidance; patient narratives. |
| [40] | USA | N = 16 | median 75; range 72–79 | 12,5% high school or less; 12,5% some college; 25% bachelor; 50% higher education | early stage, noninvasive | unique to the study—paper-based | Treatment options; overall health; endocrine therapy; values clarification; FAQs. |
| [41] | USA | N = 81 [N = 18 & N = 53 for phase 1; N = 10 for phase 2] | mean 56.8; range 31–75 | N = 7 high school or less; N = 2 some college; N = 1 graduate | I to IIIA stages | Option Grid Adapted—paper-based | Surgical options; FAQs; survival; recurrence; chemotherapy information. |
| [42] | Canada | N = 201 | EG: median 58.2. CG: median 58.1 | EG: 47% high school; CG: 50% high school | I or II stages | unique to the study—paper-based | Treatment options; adverse effects; survival; quality of life. |
| [43] | USA | N = 101 | mean 54.9; SD 9.8 | N/A | I or II stages | unique to the study—online-based | Breast cancer information; treatment risks/benefits; outcome probabilities; patient experiences. |
| [44] | Netherlands | N = 180 | EG: mean 55.4; SD 10.8; CG: mean 54.6; SD 10.6 | EG: 8% less than compulsory, 47% compusory; 21% more than compulsory, less than university; 16% university. CG: 8% less than compulsory; 51% compulsory; 14% more than compulsory, less than university; 15% university | I or II stages | CDROM—online-based | Surgical options; benefits/harms; printable consultation summary. |
| [45] | USA | N = 44 | N/A | N/A | I–IIIB stages | unique to the study—online, interactive (soap opera) | Cancer information; misconceptions; treatment; support; personalized decision guidance. |
| [46] | USA | N = 44 | range 29–70 | N/A | I–IIIA stages | unique to the study—online, interactive (soap opera) | Cancer information; misconceptions; treatment; support; personalized decision guidance. |
| [47] | USA | N = 201 | median full sample: 59 CG: median 58, range 27–79; EG: medan 61; range 29–80 | 62% college educated | 0–III stages | unique to the study—online-based | Breast reconstruction; educational modules; values clarification; video vignettes. |
| [48] | USA | N = 227 | median full sample: 59 CG: median 57, range 27–78. EG: median 61, range 29–80 | 65% college educated | 0–III stages | unique to the study—online-based | Breast reconstruction; educational modules; values clarification; video vignettes. |
| [49] | Canada | N = 12 | median 76, range 70–84 | N/A | I stage | unique to the study—paper-based | Not reported. |
| [50] | USA | N = 369 [experimental group N = 184; control group N = 185] | EG: mean, 51.0, SD = 10.8; CG: 51.2, SD = 11.2 | EG: High school or less 10.6% Some college 21.8% college degree 33.4% graduate 34.5%; CG: high school or less 10.1% Some college 17.1% college degree 36.7% graduate 36.1% | EG 87,6% stages 0–II; CG 88,1% stages 0–II | BREASTChoice—online-based | Breast reconstruction; complication risks; preference elicitation; clinician feedback. |
| [51] | USA | N = 573 | median 60; range 27–90 | Area Deprivation index 5 (1–10); 23% socioeconomically disadvantaged | 72% of participants stage I or II | unique to the study—online-based | Not reported. |
| Study | Design | Decision-Related Processes | Knowledge | Psychological Well-Being | Acceptability/Usability | Implementation Issues | Lower SES/Health Literacy | Total MMAT Score |
|---|---|---|---|---|---|---|---|---|
| [25] | RCT | Improved decisional conflict; improved certainty regarding treatment preference | — | — | — | Family involvement supported PDA use | — | 6 |
| [26] | Qualitative | PDA influenced treatment decisions | — | — | PDA perceived as concise and useful | Clinicians required training before routine implementation; patients preferred receiving PDA throughout the consultation | Pictorial format preferred by lower SES patients | 3 |
| [27] | RCT | Improved decision quality; improved SDM; improved care coordination; decreased decision regret | Improved knowledge | No effect reported | — | — | Picture Option Grid reduced disparities in knowledge; SES influenced decision regret outcomes | 3 |
| [28] | RCT | Improved value concordance; improved satisfaction with decision-making | Slight improvement | — | — | — | — | 3 |
| [29] | RCT | Decreased decisional conflict; decreased decision regret; improved satisfaction with decision process | No effect | Decreased depression; no effect on anxiety | — | — | — | 6 |
| [30] | RCT | Improved perceived support during decision-making | — | Increased psychological distress | — | — | — | 4 |
| [31] | Mixed methods | Different preferences regarding involvement in SDM | Improved knowledge | — | PDA perceived positively | Timing of PDA should be individualized | — | 7 |
| [32] | Quantitative NR | Decreased decisional conflict | Improved knowledge | — | — | — | — | 7 |
| [33] | RCT | Decreased decisional conflict; improved informed choice; improved values clarity | Improved knowledge | — | Improved satisfaction | — | — | 5 |
| [34] | Qualitative | Patients perceived SDM, although preference discussions were sometimes lacking | — | — | PDA perceived as useful | Improvements needed in PDA delivery during consultations | — | 7 |
| [35] | RCT | Improved observed SDM; improved patient-reported SDM | — | — | — | — | Lower SES associated with different SDM patterns | 7 |
| [36] | Mixed methods | Decreased decisional conflict | Improved knowledge | Emotional distress hindered information uptake | Positive feedback | Home viewing suggested | — | 7 |
| [37] | Mixed methods | — | — | — | Picture Option Grid most appreciated; PDA easy to understand | Treatment costs should be addressed | Positive feedback from lower SES women | 5 |
| [38] | Qualitative | Improved preparation for decision-making | — | No effect on anxiety | Appropriate length, balanced and useful | Older women preferred receiving paper PDA before consultation | — | 7 |
| [39] | RCT | Decreased decisional conflict; improved satisfaction with decision-making | — | No effect on anxiety | — | — | — | 5 |
| [40] | Quantitative descriptive | Improved satisfaction with decision | — | — | High acceptability and usability | Different surgeon recommendations complicated implementation | — | 6 |
| [41] | Qualitative | — | — | — | PDA considered feasible, useful and acceptable | Pictorial format appreciated | Better accessibility for patients with limited literacy | 6 |
| [42] | RCT | Decreased decisional conflict; improved satisfaction with decision-making | Improved knowledge | No effect on anxiety or depression | — | — | — | 6 |
| [43] | Quantitative NR | No effect | No effect | No effect | PDA positively evaluated | — | — | 7 |
| [44] | Quantitative NR | Improved satisfaction with decision-making | — | Improved quality of life | — | — | — | 7 |
| [45] | Quantitative NR | — | Improved knowledge | — | PDA positively evaluated | — | — | 6 |
| [46] | Quantitative NR | Decreased decisional conflict; improved clarity about treatment options | — | — | — | — | — | 6 |
| [47] | RCT | No effect of PDA on perceived SDM; surgeon influence predominated | — | — | — | Surgeon-related factors influenced implementation | Education level influenced satisfaction | 4 |
| [48] | RCT | — | Improved knowledge | — | PDA perceived as useful | — | — | 6 |
| [49] | Qualitative | — | — | — | PDA considered acceptable, informative and visually appealing | Timing and support barriers identified | — | 7 |
| [50] | RCT | No effect on decisional conflict or SDM | No significant improvement | — | Good usability | — | — | 6 |
| [51] | RCT | No effect on patient engagement | — | — | — | — | Socioeconomic disadvantage associated with lower engagement | 5 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Sdinami, S.; Conti, L.; Capetti, B.; Sebri, V.; Zagami, P.; Grasso, R.; Criscitiello, C.; Curigliano, G.; Pravettoni, G. Impact of Decision Aids for Shared Decision-Making for Patients with Early Stage Breast Cancer: A Systematic Review. Curr. Oncol. 2026, 33, 518. https://doi.org/10.3390/curroncol33090518
Sdinami S, Conti L, Capetti B, Sebri V, Zagami P, Grasso R, Criscitiello C, Curigliano G, Pravettoni G. Impact of Decision Aids for Shared Decision-Making for Patients with Early Stage Breast Cancer: A Systematic Review. Current Oncology. 2026; 33(9):518. https://doi.org/10.3390/curroncol33090518
Chicago/Turabian StyleSdinami, Serena, Lorenzo Conti, Benedetta Capetti, Valeria Sebri, Paola Zagami, Roberto Grasso, Carmen Criscitiello, Giuseppe Curigliano, and Gabriella Pravettoni. 2026. "Impact of Decision Aids for Shared Decision-Making for Patients with Early Stage Breast Cancer: A Systematic Review" Current Oncology 33, no. 9: 518. https://doi.org/10.3390/curroncol33090518
APA StyleSdinami, S., Conti, L., Capetti, B., Sebri, V., Zagami, P., Grasso, R., Criscitiello, C., Curigliano, G., & Pravettoni, G. (2026). Impact of Decision Aids for Shared Decision-Making for Patients with Early Stage Breast Cancer: A Systematic Review. Current Oncology, 33(9), 518. https://doi.org/10.3390/curroncol33090518

