Article

Adult Vaccination and Healthy Aging in the UAE: Uptake, Determinants, and Policy Perspectives

by
Areeba Irfan
1,
Jinnu Jimmy
1,
Zahraa Farhad
2,
Anugraha Lisa Ciju
2,3,
Reel Louai
1,
Aadith Soorya Arunkumar Maivizhichelvi
4,
Liju Susan Mathew
5,
Sneha Reji
6,7,8 and
Jayakumary Muttappallymyalil
9,10,*
1
MD Program, College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
2
HDPCS Program, College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
3
MD Program, Medical University of Lublin, 4184 Lublin, Poland
4
MPH Program, College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
5
Department of Biomedical Sciences, College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
6
Department of Family & Community Medicine and Behavioral Sciences, College of Medicine, University of Sharjah, Sharjah 27272, United Arab Emirates
7
College of Health Sciences, Gulf Medical University, Ajman 4184, United Arab Emirates
8
College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
9
Department of Community Medicine, College of Medicine, Gulf Medical University, Ajman 4184, United Arab Emirates
10
Thumbay Institute of Population Health, Gulf Medical University, Ajman 4184, United Arab Emirates
*
Author to whom correspondence should be addressed.
Int. J. Environ. Res. Public Health 2026, 23(9), 1136; https://doi.org/10.3390/ijerph23091136
Submission received: 8 May 2026 / Revised: 30 June 2026 / Accepted: 25 August 2026 / Published: 31 August 2026
(This article belongs to the Section Global Health)

Highlights

Public health relevance—How does this work relate to a public health issue?
  • Adult vaccination uptake is important as there is a growing burden of vaccine-preventable diseases among adults and older populations across the globe.
  • Understanding determinants, barriers, and enablers of vaccination can support strategies to improve healthy aging and reduce healthcare burden.
Public health significance—Why is this work of significance to public health?
  • This study provides evidence on factors influencing adult vaccine utilization in the UAE, contributing to limited regional data on adult immunization.
  • The findings can guide targeted awareness campaigns, healthcare interventions, and national vaccination policies for adults.
Public health implications—What are the key implications or messages for practitioners, policy makers and/or researchers in public health?
  • Strengthening public awareness, physician recommendation, and accessibility of vaccines may improve adult vaccination coverage in the UAE.
  • Policymakers and researchers should prioritize adult immunization programs and further studies to support evidence-based healthy aging initiatives.

Abstract

Adult vaccination is a critical component of preventive healthcare, reducing morbidity and mortality from vaccine-preventable diseases. Despite established recommendations, adult immunisation coverage remains suboptimal, particularly for vaccines beyond influenza and COVID-19. In the United Arab Emirates (UAE), limited evidence exists regarding adult vaccine uptake and determinants influencing immunisation behaviour within its diverse population. Understanding vaccine-specific coverage and associated sociodemographic, healthcare, and workplace factors is essential to guide targeted strategies that strengthen adult immunisation. A cross-sectional study was conducted among 1330 adults aged ≥ 18 years residing in the UAE. Data were collected using a structured self- or interviewer-administered questionnaire assessing uptake of recommended adult vaccines, including COVID-19, influenza, pneumococcal, herpes zoster, Tdap, and HPV. Sociodemographic characteristics, healthcare access, insurance status, workplace factors, and perceived barriers were also assessed. Descriptive statistics summarised vaccination coverage, and associations between uptake and key determinants were examined using SPSS version 30. Statistical significance was defined as p < 0.05. Overall, 71.0% reported receiving at least one adult vaccine. Uptake was highest for COVID-19 (64.9%) and influenza (57.8%), while pneumococcal, herpes zoster, and Tdap coverage remained low (12–13%). HPV uptake was 22.6% among females and 18.9% among males. Higher uptake was observed among females and adults. Social encouragement, insurance coverage, and healthcare access were associated with vaccination, whereas lack of awareness and logistical barriers hindered uptake. Although overall uptake was moderate, significant gaps persist. Integrating vaccination into routine healthcare services and addressing structural and communication barriers are necessary to improve adult vaccination coverage.

1. Introduction

Vaccination is one of the most effective public health interventions for preventing infectious diseases, reducing morbidity and mortality, and strengthening global health security. While childhood immunization programs have achieved substantial success worldwide, adult vaccination remains underutilized despite the growing burden of vaccine-preventable diseases among adults and aging populations. The World Health Organization promotes life-course immunization to ensure protection across all age groups; however, adult vaccine uptake is limited by vaccine hesitancy, complex schedules, low awareness, and inadequate health system support [1]. These challenges are particularly evident in the Middle East, where disparities in access, healthcare infrastructure, and socio-cultural factors influence immunization behaviors, even in high-income countries such as the United Arab Emirates [2].
Despite adult immunization guidelines, coverage remains suboptimal globally. In the Eastern Mediterranean, uptake of seasonal influenza, pneumococcal, and herpes zoster vaccines is low. In Saudi Arabia, the UAE, and Turkey, influenza coverage among older adults and high-risk groups is below 50%, pneumococcal uptake is under 15%, and herpes zoster coverage is below 5% [3]. Similar trends exist worldwide, even in high-income countries, reflecting differences in policy, funding, and healthcare delivery [4]. In Europe, adult coverage remains below targets despite established programs, with heterogeneity across Germany, France, the UK, Italy, Spain, Sweden, and Romania [5]. These findings highlight adult vaccination as a persistent global public health challenge.
The Middle East and North Africa (MENA) region struggles with vaccination beyond childhood. Uptake of vaccines such as HPV, pneumococcal, and rotavirus is uneven. Financial constraints, international funding, conflict-related disruptions, and weak surveillance have delayed vaccine introduction in several middle-income countries [6]. Vaccine hesitancy, driven by safety concerns, misinformation, cultural or religious considerations, low awareness, and insufficient healthcare provider engagement, further limits uptake [7]. Adults in MENA continue to experience a substantial burden of vaccine-preventable diseases, particularly invasive bacterial infections, emphasizing the need for region-specific strategies [8].
Adult vaccine uptake is shaped by complex, context-specific factors. Barriers include concerns about side effects, time constraints, and fear of needles, while enablers include perceived protection, reminders, and social support [9]. In the UAE, trust in vaccines, healthcare systems, and national policies supports uptake, but hesitancy persists over potential long-term effects [10]. Globally, adult vaccination is challenged by limited funding, fragmented registries, and weak incentives, with inconsistent policies across Europe compounding these barriers [11].
Studies in the UAE reveal a gap between availability and acceptance. Despite influenza vaccine access, many remain unvaccinated due to misconceptions and low perceived risk. Lack of time is cited by 16% [12], while over half of hesitant individuals report side effect concerns [13]. Limited awareness of vaccines such as HPV highlights knowledge gaps [14]. With advanced healthcare and a diverse population, the UAE offers a strong setting to study adult vaccination, enablers, and barriers to guide targeted interventions and strengthen public health resilience. Hence, this study was conducted to assess adult vaccination coverage in the UAE and identify the sociodemographic, healthcare, economic, and workplace factors associated with vaccine uptake, in order to inform public health strategies to improve adult immunization across the adult population.

2. Materials and Methods

2.1. Study Design, Study Population, Sample Size, and Sampling

A cross-sectional study was conducted among 1330 adults, which focuses on determining adult vaccine uptake and its factors. Inclusion criteria were adults aged ≥18 years residing in the UAE who provided informed consent. Individuals younger than 18 years or unwilling to participate were excluded. Both male and female participants, of any nationality, residing in the UAE, took part in the research. The sample size for this cross-sectional study was calculated using the standard formula: N = 4PQ/L2, where P represents the estimated prevalence of the condition, Q is calculated as (1 − P), and L denotes the desired level of precision. The prevalence of the vaccine uptake was estimated at 24% (P = 0.24), yielding a corresponding Q value of 0.76. With a precision level of 2.4% (L = 0.024), the sample size was calculated as follows: N = (4 × 0.24 × 0.76)/(0.024)2 = 0.7296/0.000576 = 1267. A precision level of 2.4% was selected to increase estimate accuracy while remaining feasible given available resources. The calculated minimum required sample size was 1267 participants. To improve statistical precision and account for potential non-response or incomplete questionnaires, a total of 1330 participants were recruited and included in the final analysis. The achieved sample of 1330 exceeded the minimum required sample size, increasing statistical precision. The study employed convenience sampling, a non-probability sampling method, to recruit eligible participants (see File S1).

2.2. Questionnaire and Validation

This study employed a structured questionnaire comprising both open- and closed-ended questions, developed from an extensive review of the relevant literature. The questionnaire was organized into four sections. The questionnaire was conceptually guided by Andersen’s Behavioral Model of Health Services Utilization, which classifies determinants of healthcare utilization into predisposing, enabling, and need factors. Accordingly, the questionnaire included items assessing these domains to identify factors associated with adult vaccine uptake. This framework has been widely applied in studies examining healthcare utilization and adult vaccination behaviours. The first section collected socio-demographic information, including age, gender, nationality, educational background, occupation, and marital status. The second section gathered information related to adult vaccine uptake. The third section assessed participants’ perceptions of factors that facilitate or hinder vaccine uptake. The fourth section explored behavioral, cultural, economic, medical, and medicine-related factors that may influence vaccine uptake.
Following the development of the draft questionnaire, a validation procedure was conducted. Three subject-matter experts assessed face and content validity, and their feedback was incorporated to refine and modify the questionnaire accordingly. Subsequently, a pilot study was conducted to evaluate the clarity and comprehensibility of the questions, as well as the feasibility of the questionnaire in terms of the time required for completion.

2.3. Methodology

Data collection was conducted after obtaining approval from the Institutional Review Board of the Medical University. Permission was obtained from the authorities at the study site prior to initiating the study. Eligible participants included adults aged 18 years and above residing in the UAE, irrespective of gender or nationality, who were willing to provide written informed consent. Individuals younger than 18 years or those unwilling to participate were excluded from the study. Participants were recruited through universities, community settings, healthcare facilities, and public locations using QR-code-based and interviewer-assisted questionnaires. Participants completed the questionnaire independently, while the researchers were available on-site to clarify any questions or concerns during the data collection period. Data collection was conducted between April 2025 and October 2025.

2.4. Data Analysis

The primary outcome variable was adult vaccine uptake, defined as the self-reported receipt of at least one adult vaccine from the list included in the questionnaire. For statistical analysis, the outcome was coded as a binary variable (yes/no), as illustrated in Figure 1. Statistical analyses were performed using SPSS version 29 (IBM, Chicago). Statistical analyses were performed in a stepwise manner. Descriptive statistics were first used to summarize participants’ sociodemographic characteristics and vaccination status. Vaccine-specific uptake frequencies, enabling factors, and barriers were then described. Bivariate associations between the outcome variable and independent variables were assessed using the chi-square test. Variables of interest were subsequently entered into a multivariable logistic regression model to identify independent predictors of adult vaccine uptake. Statistical significance was defined as p < 0.05. No missing data were observed for the variables included in the analyses; therefore, all 1330 participants were included in the final analysis.

2.5. Ethical Aspects

Ethical clearance for this study was granted by the Institutional Review Board of a medical university in Ajman, UAE (Reference No. IRB-COM-STD-120-Mar-2025). Informed consent was obtained from all participants after explaining the purpose of the research. Participation was completely voluntary, and measures were taken to ensure participants’ confidentiality, anonymity, and privacy throughout the study. This research followed the Declaration of Helsinki.

3. Results

The study included 1330 participants, most of whom were under 40 years old (76.9%). Females formed the majority of respondents (60.4%). Nearly half held a bachelor’s degree (46.3%), while 39.2% had a high-school education or less. A large proportion were unemployed (67.4%), and most participants were single (61.9%). Smaller percentages were over 40 years old, employed, married, or had postgraduate qualifications.
Figure 1 shows the distribution of participants based on their use of adult vaccines. Most respondents reported having received at least one adult vaccine, accounting for 944 participants (71.0%). However, 386 participants (29.0%) indicated that they had not received any adult vaccinations.
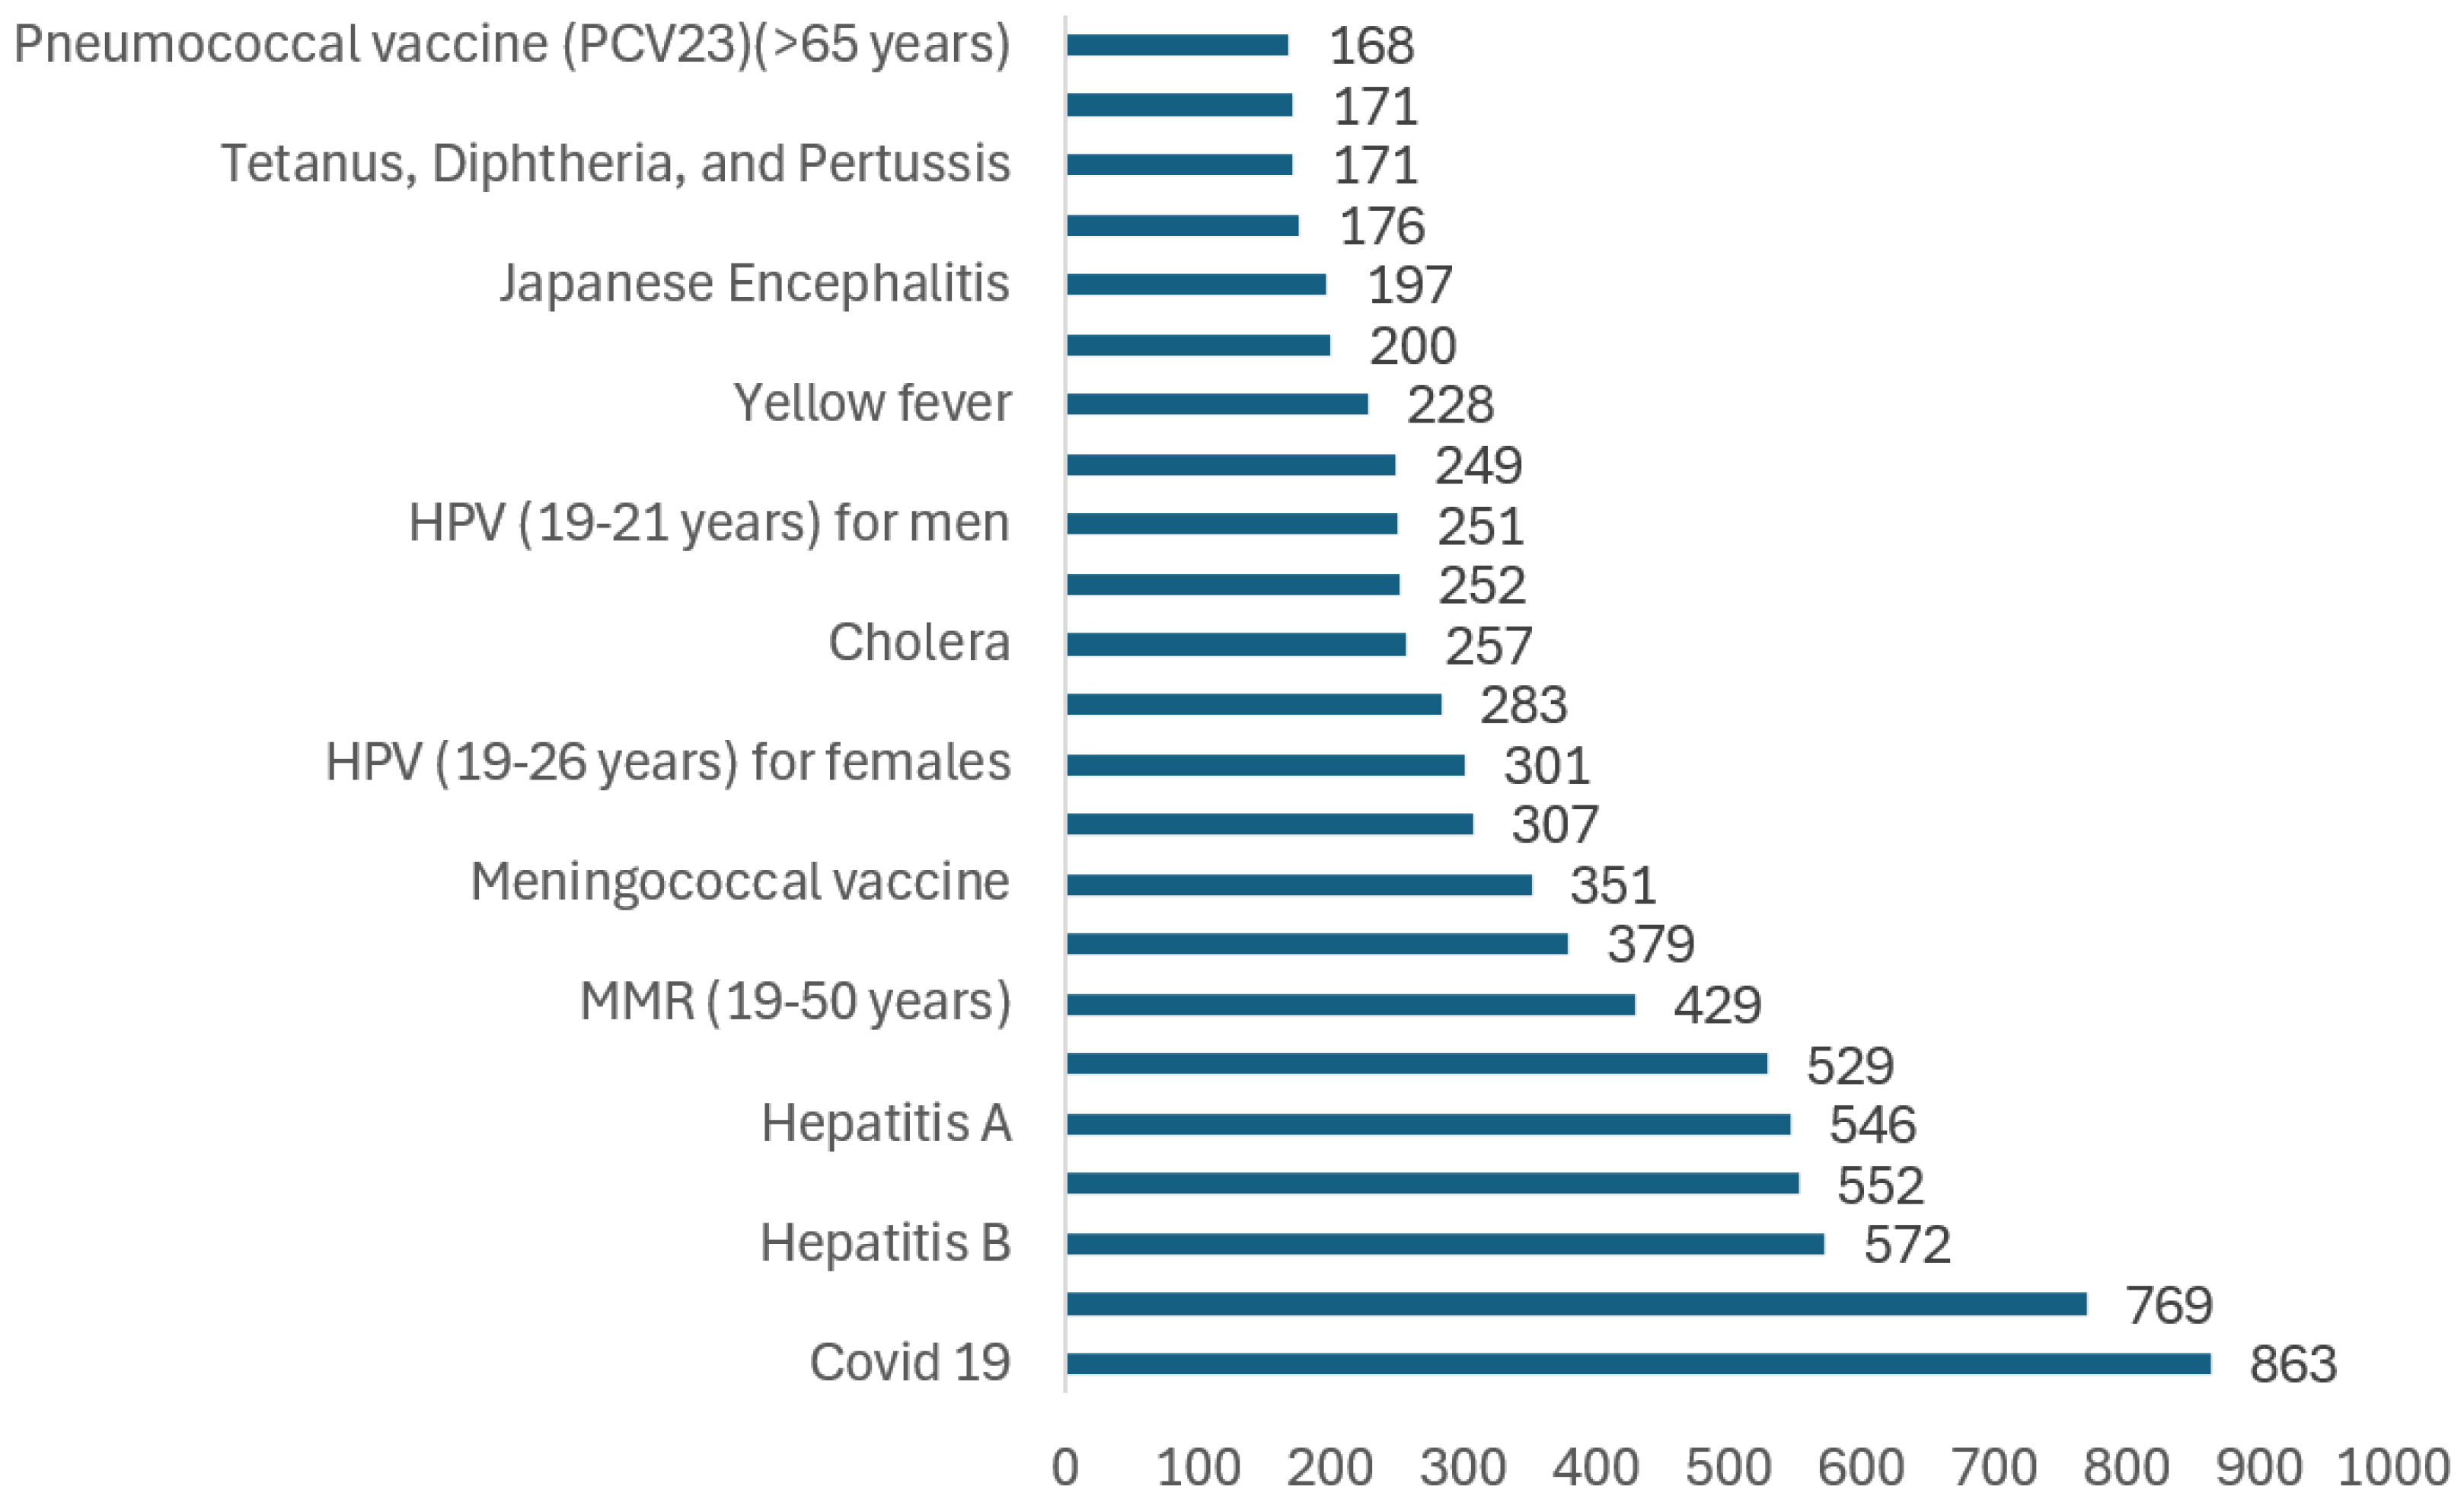
In Figure 2 uptake is defined as receiving at least one adult vaccine from the list and it shows that COVID-19 (64.9%) and influenza (57.8%) vaccines had the highest uptake. Moderate coverage was seen for hepatitis B (43.0%), hepatitis A (41.1%), chickenpox (41.5%), and Hib (39.8%). Among female participants, 22.6% reported receiving the HPV vaccine, compared with 18.9% of male participants. In contrast, several adult and travel-related vaccines, such as Tdap (12.9%), herpes zoster (12.9%), and pneumococcal vaccination (12.6–13.2%, depending on formulation) had the lowest uptake among participants. Most respondents had not received tuberculosis vaccination (71.5%).
Table 1 summarizes the enabling factors associated with vaccine uptake among vaccinated participants. It shows that social encouragement strongly influenced uptake, with 79.7% guided by friends and 75.8% describing themselves as health-conscious. Practical access mattered: 67.5% had nearby doctors, 69.2% found information easy, 67.4% perceived good service quality, and 65.5% obtained quick appointments, while 64.1% could attend evenings or weekends. Financial and workplace factors mattered too: 59.4% insured, 60.6% affordable services, 62.2% employer support, 62.1% on-site clinics, but only 32.6% flexible hours.
Table 2 shows multiple barriers to vaccine uptake among unvaccinated participants across different domains. The most commonly reported barriers were health system–related, particularly long waiting times (32.6%) and lack of nearby healthcare facilities (32.1%), followed by cultural beliefs influencing healthcare decisions (31.9%). Economic barriers were also important, with 27.5% reporting insufficient money, 24.3% perceiving vaccines as expensive, and 20.9% lacking insurance. Moderate proportions reported issues related to awareness and trust, including lack of awareness of vaccination services (27.5%), distrust in healthcare providers (24.6%), and fear of infection at healthcare facilities (23.1%). Language-related difficulties were also notable, particularly language barriers with healthcare providers (47.4%), along with difficulty understanding medical terminology (25.6%). Workplace concerns affected a smaller but relevant proportion, including fear of being sent back home (43.4%), fear of job loss (29.5%), and difficulty obtaining medical leave (24.0%). Transportation barriers were relatively less common, affecting about 24–25% of participants.
Table 3 shows a significant association between vaccine uptake and all sociodemographic variables (p < 0.001). Vaccine uptake was highest among participants aged <40 years (77.5%), followed by those aged 40–60 years (61.9%), and lowest among those aged ≥60 years (27.4%), indicating a clear decline with increasing age. Females had higher vaccine uptake (77%) compared to males (63.4%). Single participants showed greater uptake (80.1%) than married participants (56.2%). Regarding education, uptake was highest among those with high school education and below (80.3%), followed by bachelor’s degree holders (66.1%), and lowest among those with master’s and above (61.5%). Employment status also showed a significant difference, with higher uptake among the unemployed (78.4%) compared to the employed (59.3%). Participants with health insurance also demonstrated significantly higher vaccine uptake (84.5%) compared to those without health insurance (57.5%) (p < 0.001), indicating that health insurance coverage was positively associated with vaccine uptake.
Table 4 presents the crude and adjusted logistic regression analysis of factors associated with adult vaccine uptake. After adjustment, age, gender, marital status, education level, and employment status were all significantly associated with vaccine uptake (all p < 0.001).
Compared to participants aged below 40 years, those aged 40–60 years (AOR = 0.46, 95% CI: 0.33–0.66) and ≥60 years (AOR = 0.10, 95% CI: 0.06–0.15) had significantly lower odds of vaccine uptake. Female participants had higher odds of vaccine uptake than males (AOR = 2.09, 95% CI: 1.59–2.75). Married participants were less likely to receive adult vaccines than single participants (AOR = 0.32, 95% CI: 0.25–0.43). Participants with a bachelor’s degree (AOR = 0.46, 95% CI: 0.34–0.63) and a master’s degree or above (AOR = 0.36, 95% CI: 0.24–0.54) had lower odds of vaccine uptake compared to those with a high school education or below. Unemployed participants had higher odds of vaccine uptake than employed participants (AOR = 2.21, 95% CI: 1.69–2.90).

4. Discussion

This study provides a comprehensive assessment of adult vaccination uptake among the study population in the UAE and identifies key sociodemographic, health system, economic, and workplace-related determinants influencing vaccination behavior. Overall vaccine uptake was relatively high, with 71.0% of participants having received at least one adult vaccine, yet notable gaps persisted for several routinely recommended vaccines. These findings reflect both the strengths and ongoing challenges of adult immunization within a high-income Middle Eastern setting. The findings are interpreted within Andersen’s Behavioral Model of Health Services Utilization, which categorizes determinants of healthcare utilization into predisposing, enabling, and need-related factors. This framework provides a basis for understanding the sociodemographic, health system, and behavioural determinants of adult vaccine uptake identified in the present study.
In the present study, nearly three-fourths of participants reported receiving at least one adult vaccine, indicating moderate overall uptake. However, because overall vaccine uptake was defined as receipt of at least one adult vaccine, the relatively high coverage of COVID-19 and influenza vaccines may have inflated the overall estimate and should be considered when interpreting these findings. From the perspective of Andersen’s model, the observed uptake likely reflects the influence of enabling factors such as widespread vaccine availability, strong public health infrastructure, and extensive vaccination campaigns in the UAE. A multicountry review reported adult vaccination uptake ranging between 40–60% in most middle- and high-income countries, depending on vaccine type and target population [15,16]. Similarly, adult vaccination coverage across many European countries remains below 65%, even for recommended vaccines [16]. The relatively higher uptake observed in this study may be attributed to the UAE’s strong public health infrastructure, frequent travel of people to other countries, widespread vaccine availability, and the extensive vaccination campaigns, which likely enhanced awareness and acceptance of adult immunization. However, the finding that nearly 29% of adults remained unvaccinated highlights persistent gaps in awareness, access, and perceived necessity [17].
Vaccine-specific analysis showed that COVID-19 and influenza vaccines had the highest uptake among all assessed vaccines. In this study, 64.9% of participants reported getting a COVID-19 vaccination, while 57.8% reported getting an influenza vaccination. These findings are consistent with global evidence. A study reported COVID-19 vaccine acceptance rates between 60–80%, influenced by trust in health systems, perceived vaccine safety, and access [18]. Influenza vaccine uptake in the present study exceeded that reported in some high-income settings. For example, A population-based study from Canada reported adult influenza vaccination coverage of 41–44% before, during, and after the COVID-19 pandemic [19]. The higher uptake observed in the UAE may reflect sustained public health messaging, workplace-based vaccination initiatives, and improved access to free or subsidized vaccines following the pandemic.
In contrast, uptake of pneumococcal, herpes zoster, and Tdap vaccines was uniformly low, with each reported by only 12–13% of participants. This pattern aligns with international evidence of persistently suboptimal coverage of non-respiratory adult vaccines. In Belgium, pneumococcal vaccination uptake among people living with HIV reached 37.8%, higher than in the present study but still insufficient given the elevated disease risk [20]. Differences in uptake may reflect variations in healthcare engagement, perceived risk, and the presence of structured reminder systems.
Herpes zoster uptake in the present study (~12%) mirrors findings from Saudi Arabia, where only 12% of adults aged ≥50 years with chronic diseases were vaccinated [21]. In that study, low perceived susceptibility and limited knowledge were major barriers, while physician recommendation was the strongest predictor of uptake. Similarly, evidence from Turkey indicates a substantial pneumococcal disease burden alongside persistently low adult vaccination coverage, attributed to fragmented policies, limited public awareness, and reliance on opportunistic vaccination strategies [22]. Collectively, these findings suggest that insufficient provider recommendation, low perceived risk, and poor integration of adult vaccination into routine care contribute to low uptake.
HPV vaccine uptake in this study was 22.6% among females and 18.9% among males, indicating modest coverage. These figures are comparable to recent UAE data reporting an HPV vaccination rate of 18.9% among young adults, the highest among Gulf Cooperation Council countries, yet still reflecting overall low uptake [23]. Globally, adult HPV vaccination coverage remains considerably lower than adolescent coverage in countries without adult catch-up programs. Cultural perceptions, misconceptions regarding age appropriateness, and limited physician recommendations are frequently cited barriers [24]. Limited promotion of HPV vaccination beyond adolescence in the UAE likely contributes to these findings.
Sociodemographic differences in vaccination uptake were evident. Females were more likely to be vaccinated than males, consistent with international evidence demonstrating higher preventive healthcare utilization among females. Evidence from a systematic review suggests that women generally have higher odds of adult vaccine uptake than men, which has been attributed to greater health awareness and more frequent healthcare interactions [25]. Our findings are consistent with this evidence, as females in the present study demonstrated higher vaccine uptake than males.
Younger adults demonstrated higher vaccination uptake than older adults in this study, contrasting with population-based studies reporting higher coverage among older age groups, particularly for age-targeted vaccines [26]. A multicounty European analysis similarly found adults aged ≥60 years to be more likely to receive recommended vaccines [27]. In the UAE, younger adults may benefit from greater exposure to employer-based vaccination campaigns, while older adults may face access barriers or reduced engagement with preventive services.
Several enabling and barrier factors further contextualize these findings. Social influence emerged as a major enabler, with nearly 80% of vaccinated participants reporting encouragement from family or friends, consistent with evidence highlighting the role of social norms in collectivist societies [28]. Health system accessibility, including flexible clinic hours and service availability, was also associated with uptake. Evidence from the wider literature suggests that workplace-based vaccination programs and extended service hours can improve adult vaccination uptake. Similarly, previous studies indicate that individuals with health insurance are more likely to receive recommended vaccines because financial barriers are reduced [29]. These findings are consistent with our observation that workplace support and health insurance were associated with higher vaccine uptake.
Conversely, logistical barriers such as long waiting times and appointment difficulties were commonly reported. A meta-analysis reported that logistical barriers accounted for 30–40% of missed adult vaccination opportunities [25]. Our findings were consistent with this evidence, with long waiting times and appointment difficulties identified as important barriers to vaccine uptake. Language and communication barriers were particularly relevant in the UAE’s multicultural population and have similarly been linked to reduced preventive healthcare utilization among migrant populations [30].
Adult vaccination is essential for healthy aging, preventing infections like influenza, pneumococcal disease, and COVID-19. It reduces severe illness, hospitalizations, and complications, preserving physical health, independence, and quality of life. Integrating vaccines into routine adult care supports preventive health, enhances resilience, and promotes longevity in aging populations.
The multivariable logistic regression analysis confirmed that age, gender, marital status, education level, and employment status were independent predictors of adult vaccine uptake. Participants aged 40 years and older had significantly lower odds of vaccination, whereas females and unemployed individuals had higher odds of vaccination. Similar to a recent study by Barqawi et al. [1], females demonstrated more positive attitudes toward adult vaccination and lower vaccine hesitancy than males. However, unlike our findings, the same study reported greater vaccine hesitancy among middle-aged and highly educated individuals, suggesting that determinants of vaccine uptake may vary across different adult populations in the UAE [31].
The lower vaccine uptake observed among married, more educated, and employed participants was unexpected. One possible explanation is that the study sample was predominantly composed of younger, single students, who may have been more recently exposed to institutional vaccination campaigns. Similarly, the lower uptake among participants with higher educational attainment may reflect the demographic composition of the sample rather than a true effect of education. In addition, many participants classified as unemployed were students who may have had greater flexibility to access vaccination services, whereas employed individuals may have faced time constraints and workplace-related barriers. These findings highlight the importance of interpreting vaccine uptake within the context of the study population.
This study provides a detailed, percentage-based analysis of adult vaccination uptake and its determinants in the UAE. Despite limitations related to self-reported data and cross-sectional design, the findings offer valuable insights into immunization gaps and highlight opportunities for targeted, system-level interventions to strengthen adult vaccination coverage. A further limitation of this study is that overall adult vaccine uptake was defined as receipt of at least one adult vaccine. Consequently, the relatively high uptake of COVID-19 and influenza vaccines may have inflated the overall estimate. Because enabling factors and barriers were assessed for overall adult vaccine uptake rather than individual vaccine types, vaccine-specific analyses excluding COVID-19 and influenza vaccines could not be performed. Although the initial analyses included descriptive statistics and bivariate chi-square tests, multivariable logistic regression was subsequently performed to identify independent predictors of adult vaccine uptake while adjusting for measured confounding variables. However, because of the cross-sectional study design, causal relationships cannot be inferred, and residual confounding due to unmeasured variables cannot be excluded. Additionally, the use of convenience sampling through QR-code-based and interview-assisted recruitment may have preferentially included younger and more digitally connected individuals, contributing to the high proportion of participants aged below 40 years. This may have introduced selection bias and limited the generalizability of the findings to the broader adult population of the UAE. Because most participants were younger than 40 years, the findings should be interpreted primarily in the context of a predominantly young adult population, and conclusions regarding older adults should be made with caution.

5. Conclusions

This study evaluated adult vaccination uptake and its determinants in the UAE, revealing moderate coverage alongside persistent gaps. Overall, 71% of participants reported receiving at least one adult vaccine, with the highest uptake for COVID-19 (64.9%) and influenza (57.8%), driven by public health campaigns and workplace initiatives. Coverage for non-respiratory vaccines, including pneumococcal, herpes zoster, Tdap, and HPV, remained low. Vaccination behavior was influenced by sociodemographic factors, health system access, insurance, and social influence, while lack of awareness and logistical barriers hindered uptake. Strengthening physician recommendations, routine integration, workplace delivery, and culturally tailored communication could improve adult immunization in the UAE.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ijerph23091136/s1, File S1: STROBE Statement—Checklist of items that should be included in reports of cross-sectional studies.

Author Contributions

Conceptualization: A.I., J.J. and J.M. Methodology: A.I., A.L.C., J.J., R.L., L.S.M., J.M. and A.S.A.M. Software: A.I., J.J., L.S.M. and J.M. Validation: A.L.C., R.L., A.S.A.M. and L.S.M. Formal analysis: A.I., J.J., Z.F., R.L., A.S.A.M., L.S.M., S.R. and J.M. Investigation: A.I., J.J., Z.F., A.L.C., R.L., A.S.A.M., L.S.M. and S.R. Resources: J.J., Z.F., A.L.C., R.L. and S.R. Data curation: A.I., J.J., Z.F., A.L.C., R.L., A.S.A.M., L.S.M. and S.R. Writing—original draft preparation: A.I., J.J., Z.F., A.L.C., R.L., A.S.A.M., L.S.M., S.R. and J.M. Writing—review and editing: A.S.A.M. and J.M. Supervision: J.M. Project administration: A.S.A.M. and J.M. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of GULF Medical University, Academic Health Center (protocol code IRB-COM-STD-120-Mar-2025 and date of approval 20 March 2025).

Informed Consent Statement

Informed consent was obtained from all participants prior to data collection. Participation was voluntary, and all responses were anonymized to maintain confidentiality.

Data Availability Statement

The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Barqawi, H.J.; Samara, K.A.; Hassan, M.S.; Amawi, F.B. Adult Vaccination in the United Arab Emirates: A Physicians’ Knowledge and Knowledge Sources Study. Front. Public Health 2022, 10, 865759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. AL-Eitan, L.N.; Almahdawi, D.L.; Abu Khiarah, R.; Alghamdi, M.A. Bridging Gaps in Vaccine Access and Equity: A Middle Eastern Perspective. Vaccines 2025, 13, 806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Koksal, I.; Al Awaidy, S.; Assiri, A.M.; Ozudogru, O.; Khalaf, M.; Yeşiloğlu, C.; Badur, S. Adult Vaccination in Three Eastern Mediterranean Countries: Current Status, Challenges and the Way Forward. Expert Rev. Vaccines 2024, 23, 1068–1084. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Lentakis, E.; Seale, H.; Lazarus, R.; Mounier-Jack, S. Exploring the Delivery of Adult Vaccination Outside of Primary Care Settings: A Mixed Methods Scoping Review. Vaccine 2024, 42, 126458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Lanza, T.E.; Lombardi, G.S.; Tumelero, S.; Paladini, A.; Castagna, C.; Cadeddu, C. Barriers and Strength Factors of Adult Immunization Plans in Seven Countries of the European Region. J. Public Health 2024, 32, 2307–2314. [Google Scholar] [CrossRef] [Scilit]
  6. Bishop, C.; Parashar, D.; Kizza, D.; Griffiths, U.; Malm, S.; Kadandale, S.; Farrukh, S. New Vaccine Introduction in Middle-Income Countries across the Middle East and North Africa: Progress and Challenges. Vaccines 2025, 13, 860. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Galal, B.; Lazieh, S.; Al-Ali, S.; Khoshnood, K. Assessing Vaccine Hesitancy in Arab Countries in the Middle East and North Africa (MENA) Region: A Scoping Review Protocol. BMJ Open 2022, 12, e045348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Bizri, A.R.; Althaqafi, A.; Kaabi, N.; Obeidat, N.; Al Akoury, N.; Haridy, H. The Burden of Invasive Vaccine-Preventable Diseases in Adults in the Middle East and North Africa (MENA) Region. Infect. Dis. Ther. 2021, 10, 663–685. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Cogan, N.; Gallant, A.J.; Nicholls, L.A.B.; Rasmussen, S.; Young, D.; Williams, L. Improving Older Adults’ Vaccination Uptake: Are Existing Measures of Vaccine Hesitancy Valid and Reliable for Older People? J. Health Psychol. 2022, 27, 2898–2908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Elbarazi, I.; Al-Hamad, S.; Alfalasi, S.; Aldhaheri, R.; Dubé, E.; Alsuwaidi, A.R. Exploring Vaccine Hesitancy among Healthcare Providers in the United Arab Emirates: A Qualitative Study. Hum. Vaccin. Immunother. 2021, 17, 2018–2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Kurpas, D.; Stefanicka-Wojtas, D.; Soll-Morka, A.; Lomper, K.; Uchmanowicz, B.; Blahova, B.; Bredelytė, A.; Dumitra, G.; Hudáčková, V.; Javorska, K.; et al. Vaccine Hesitancy and Immunization Patterns in Central and Eastern Europe: Sociocultural, Economic, Political, and Digital Influences Across Seven Countries. Risk Manag. Healthc. Policy 2025, 18, 1911–1934. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Saeed, B.; Imtiaz, B.; Alhaj, S.; Alnoman, S.; Nouh, A.; Homsi, K.A.; Adrees, A.O.; Alsalhi, N.; Fahady, K.S. Knowledge, Attitudes, Behaviors and Risk Perception towards Seasonal Influenza and Vaccination among Adult Population of UAE. Period. Eng. Nat. Sci. 2022, 10, 30–40. [Google Scholar] [CrossRef] [Scilit]
  13. Albahri, A.H.; Alnaqbi, S.A.; Alshaali, A.O.; Alnaqbi, S.A.; Shahdoor, S.M. COVID-19 Vaccine Acceptance in a Sample From the United Arab Emirates General Adult Population: A Cross-Sectional Survey, 2020. Front. Public Health 2021, 9, 614499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Alsous, M.M.; Ali, A.; Al-Azzam, S.; Karasneh, R.; Amawi, H. Knowledge about Cervical Cancer and Awareness about Human Papillomavirus Vaccination among Medical Students in Jordan. PeerJ 2021, 9, e11611. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Eiden, A.L.; Barratt, J.; Nyaku, M.K. Drivers of and Barriers to Routine Adult Vaccination: A Systematic Literature Review. Hum. Vaccin. Immunother. 2022, 18, 2127290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Maltezou, H.C.; Cassimos, D.C.; Sipsas, N.V.; Medic, S. Adult Vaccinations Today—Innovations and Challenges for the Coming Years. Vaccines 2025, 13, 583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. World Health Organization (WHO). Vaccinating at Every Age Is Key to Unlocking the Full Potential of Immunization. 5 June 2025. Available online: https://www.who.int/news/item/05-06-2025-vaccinating-at-every-age-is-key-to-unlocking-the-full-potential-of-immunization (accessed on 24 January 2026).
  18. Abate, B.B.; Tilahun, B.D.; Yayeh, B.M. Global COVID-19 Vaccine Acceptance Level and Its Determinants: An Umbrella Review. BMC Public Health 2024, 24, 5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Chen, R.; Gilbert, N.L.; Dubé, E. Adult Influenza Vaccination Coverage before, during and after the COVID-19 Pandemic in Canada. BMC Public Health 2024, 24, 3357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Destordeur, L.C.; Lopez Delhoulle, V.; Papadopoulos, I.; Maes, N.; Fombellida, K.; El Moussaoui, M.; Darcis, G. Factors Contributing to Pneumococcal, COVID-19, and Influenza Vaccine Uptake among People Living with HIV in Belgium: A Retrospective Study. Open Forum Infect. Dis. 2025, 12, ofaf513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. AlSaif, H.I.; AlMuaawi, L.; Alsenani, S.; Aljohani, A.; Alharbi, A.; Alrashidi, A.; Alshammari, H.; Alshammari, N.; Alghamdi, S.; Alotaibi, N.; et al. Uptake, Willingness, and Determinants of Herpes Zoster Vaccination in Adults with Chronic Diseases in Riyadh, Saudi Arabia. Healthcare 2025, 13, 2495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Durusu-Tanrıöver, M.; Adaş, M.; Çiçekçioğlu, H.; Özger, H.Ş.; Zeren-Öztürk, G.; Sönmezer, M.Ç.; Yazıcı, B.; Saydam, O.; Aydoğdu, O.; Sayıner, A. Burden of Pneumococcal Disease and Adult Vaccination Landscape: An Overview with Data and Policy Insights from Türkiye. Infect. Dis. Clin. Microbiol. 2025, 7, 337–349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Mahmoud, I.; Al Marzouqi, M.; Mohamed, M.A.; Al Hammadi, F.; Al Shamsi, M.; Al Ketbi, L.; Al Suwaidi, H.; Al Kaabi, J. Human Papillomavirus Vaccination and Pap Test Uptake, Awareness, and Barriers among Young Adults in Gulf Cooperation Council Countries: A Comparative Cross-Sectional Survey. J. Infect. Public Health 2024, 17, 102525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Li, W.; Jin, Y.; Li, X.; Jin, M. Human Papillomavirus and Vaccine Knowledge, Willingness, and Uptake among University Students: A Systematic Review and Meta-Analysis. BMC Public Health 2025, 25, 4268. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Tan, P.S.; Patone, M.; Clift, A.K.; Dambha-Miller, H.; Saatci, D.; Ranger, T.A.; Garriga, C.; Zaccardi, F.; Shah, B.R.; Coupland, C.; et al. Factors Influencing Influenza, Pneumococcal and Shingles Vaccine Uptake and Refusal in Older Adults: A Population-Based Cross-Sectional Study in England. BMJ Open 2023, 13, e058705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Liu, B.; Zhang, X.; Lai, Y.; Sun, T.; Wang, C.; Zhao, T.; Zhang, S.; Shi, B.; Li, Y.; Cui, F. Global Vaccine Confidence Trends among Adults above and below Age 65. npj Vaccines 2025, 10, 256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Rimal, R.N.; Ganjoo, R.; Jamison, A.; Parida, M.; Tharmarajah, S. Social Norms, Vaccine Confidence, and Interpersonal Communication as Predictors of Vaccination Intentions: Findings from Slum Areas in Varanasi, India. Vaccine 2024, 42, 126038. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Jaca, A.; Mathebula, L.; Malinga, T.; Rampersadh, K.; Zulu, M.; Hohlfeld, A.S.-J.; Wiysonge, C.S.; Jacobson Vann, J.C.; Ndwandwe, D. Interventions to Improve Vaccination Uptake among Adults: A Systematic Review and Meta-Analysis. Vaccines 2025, 13, 811. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Doherty, T.M.; Ecarnot, F.; Gaillat, J.; Privor-Dumm, L. Nonstructural Barriers to Adult Vaccination. Hum. Vaccin. Immunother. 2024, 20, 2334475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Fuller, H.R.; Huseth-Zosel, A.L.; Van Vleet, B.; Carson, P.J. Barriers to Vaccination among Older Adults: Demographic Variation and Links to Vaccine Acceptance. Aging Health Res. 2024, 4, 100176. [Google Scholar] [CrossRef] [Scilit]
  31. Kim, E. Determinants Associated with COVID-19 Vaccination among Korean Adults: Based on Andersen’s Model. Behav. Sci. 2024, 14, 905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
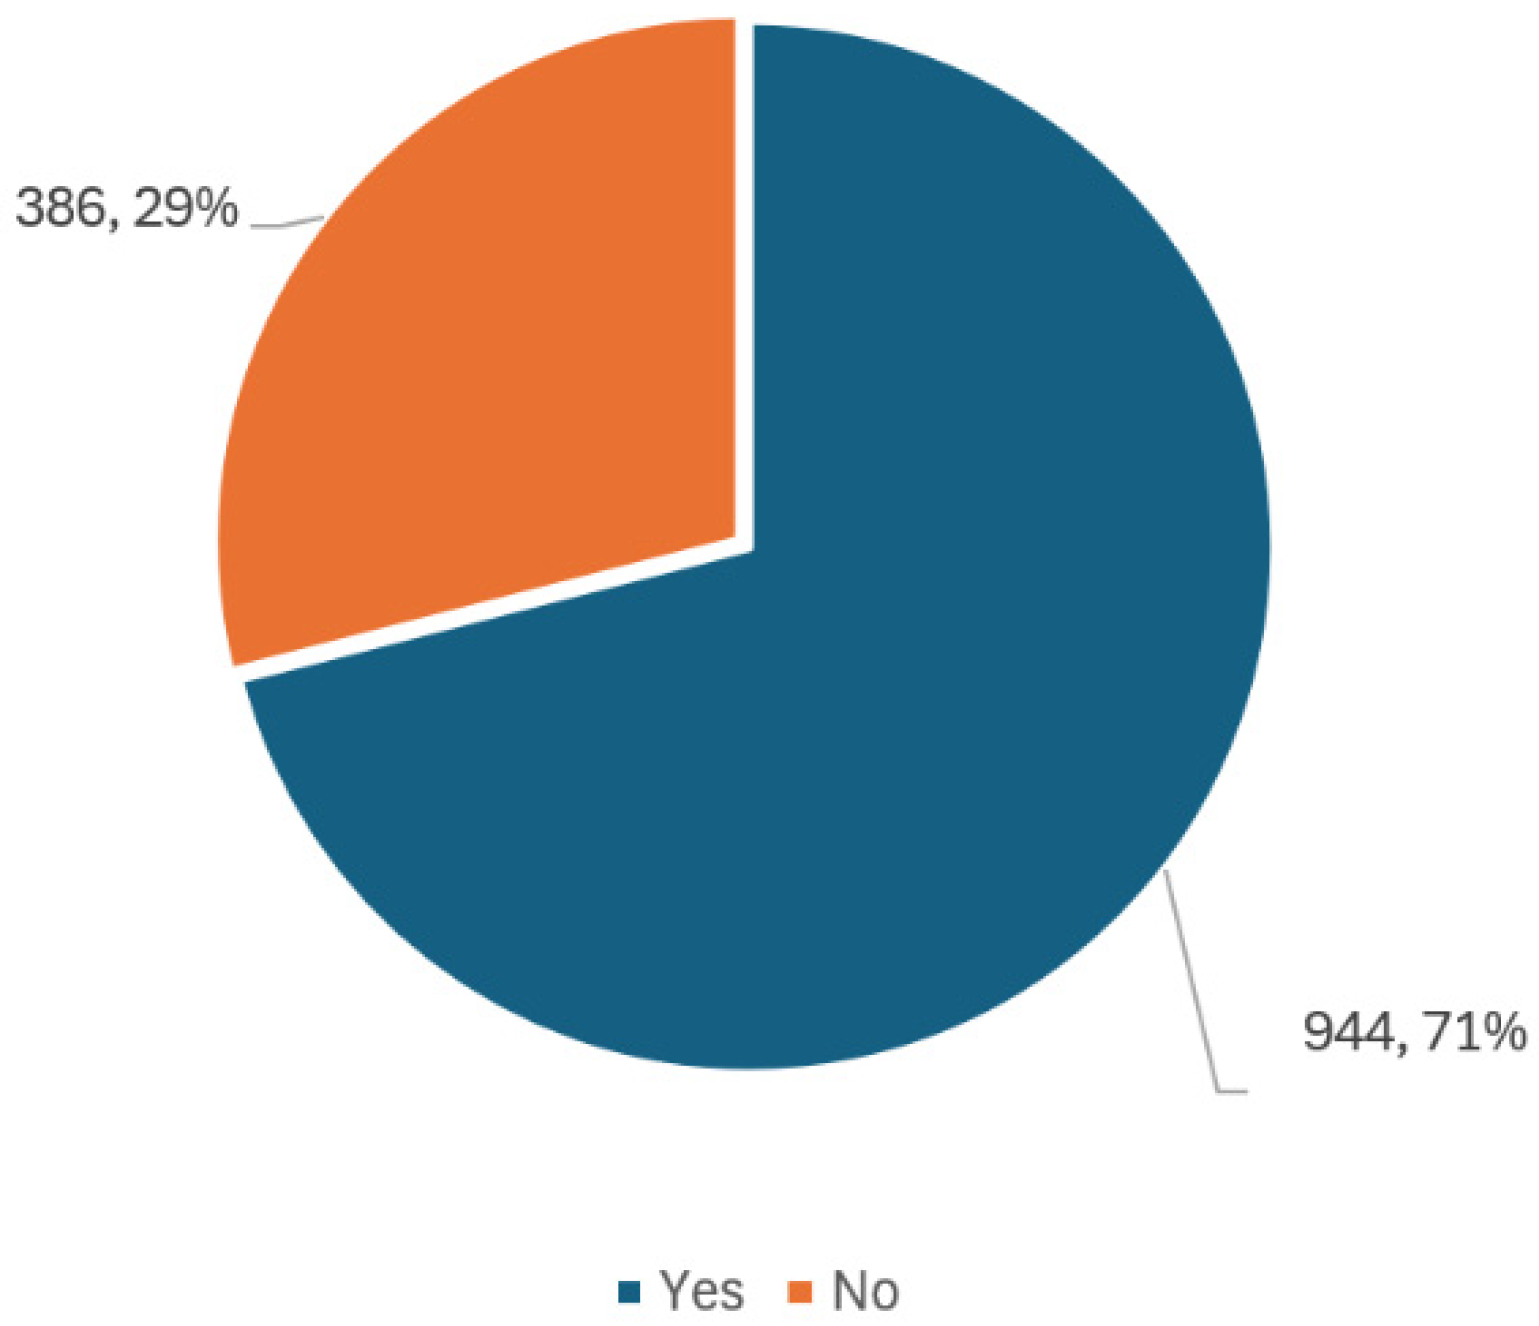
Figure 1. Distribution of participants according to utilization of adult vaccines.
Ijerph 23 01136 g001
Figure 2. Distribution of Participants according to the vaccine uptake in the past year.
Ijerph 23 01136 g002
Table 1. Distribution of participants according to predisposing and enabling factors associated with adult vaccine uptake.
Themes/FactorsGroupsFrequency%
Predisposing factors
Friends or family recommended itYes75279.7
No19220.3
Transportation availableYes58962.4
No35537.6
Health Conscious Yes71675.8
No22824.2
Enabling factors
The doctor is close (Accessibility)Yes63767.5
No30732.5
You can find information easilyYes65369.2
No29130.8
Quality of vaccination servicesYes63667.4
No30832.6
Fast appointmentsYes61865.5
No32634.5
Availability of vaccination services on weekends/eveningsYes60564.1
No33935.9
Enabling factors
Providers who speak the same language/good communication skillsYes55859.1
No38640.9
Enabling factors
You have health insuranceYes56159.4
No38340.6
Affordable Vaccination servicesYes57260.6
No37239.4
Access to low-cost or government-sponsored vaccination servicesYes49665.6
No36034.4
Availability of employer-supported vaccination benefitsYes58762.2
No37537.8
Enabling factors
Your employer helps/supports Yes58762.2
No35737.8
Availability of on-site medical clinicsYes58662.1
No35837.9
Flexibility in work hours to attend vaccination servicesYes12632.6
No26067.4
Positive peer influence on healthcare-seeking behaviorYes50358.8
No35341.2
Note: Percentages are based on the number of participants who responded to each individual item. Therefore, the frequencies for some items do not sum to the total number of vaccinated participants (n = 944) due to item-level non-response.
Table 2. Distribution of participants according to key barriers to vaccine uptake.
Themes/FactorsGroupsFrequency%
Enabling barriers
No insuranceYes7120.9
No26879.1
Not enough moneyYes10627.5
No28072.5
High cost of VaccinesYes8124.3
No25375.7
Predisposing barriers
Cultural beliefs or practices affecting healthcare decisionsYes12331.9
No26368.1
Social stigma associated with certain health conditionsYes8425.1
No25074.9
Lack of awareness about available vaccination servicesYes10627.5
No28072.5
Fear of discrimination or mistreatmentYes6318.9
No27181.1
Lack of family support Yes7221.6
No26278.4
Enabling barriers
No doctors or hospitals nearbyYes12432.1
No26267.9
Don’t know where to find a doctor or nurse for vaccinationYes7723.1
No25776.9
Don’t trust doctors or nursesYes9524.6
No29175.4
Scared of becoming infected at the hospital or clinic Yes7723.1
No25776.9
Long waiting timeYes12632.6
No26067.4
Inability to get appointmentsYes7723.1
No25776.9
Challenges in finding vaccination care Yes6135.3
No11264.7
Enabling barriers
Lack of public transportation optionsYes3024.6
No9275.4
Transportation costsYes2924.0
No9276.0
Enabling barriers
Language barriers with healthcare providers Yes8247.4
No9152.6
Difficulty understanding medical terminologyYes3125.6
No9074.4
Enabling barriers
Afraid of getting sent back home Yes7543.4
No9856.6
Scared of losing a job Yes5129.5
No12270.5
Faced challenges in obtaining medical leave or permissionYes2924.0
No9276.0
Percentages are based on responses to each individual item among the 386 unvaccinated participants. Row totals may not equal 100% because of item-level non-response.
Table 3. Association between vaccine uptake and participants’ sociodemographic characteristics and health insurance status.
Sociodemographic CharacteristicsGroupsVaccine Uptakep-Value
YesNo
No.%No.%
Age (years)<4079377.523022.5<0.001
40–6012061.97438.1
≥603127.48272.6
GenderMale37463.421636.6<0.001
Female5707717023
Marital statusSingle65980.116419.9<0.001
Married28556.222243.8
Education
level
High school and below41980.310319.7<0.001
Bachelors40766.120933.9
Master’s and above11861.57438.5
EmployedEmployed30759.321140.7<0.001
Unemployed63678.417521.6
Health InsuranceYes56184.510315.5<0.001
No38357.528342.5
Table 4. Distribution of predictors of adult vaccine uptake.
VariablesGroupAdult Vaccine Uptake
CrudeAdjusted
ORCIp ValueORCIp Value
Age group<401--1--
40–600.470.34–0.65<0.0010.460.33–0.66<0.001
≥600.110.07–0.17<0.0010.100.06–0.15<0.001
GenderMale1-----
Female1.941.52–2.42<0.0012.091.59–2.75<0.001
Marital statusSingle1--1--
Married0.320.24–0.40<0.0010.320.25–0.43<0.001
Education levelHigh school and below1--1--
Bachelors0.480.36–0.630.0010.460.34–0.63<0.001
Master’s and above0.390.27–0.56<0.0010.360.24–0.54<0.001
Employment statusEmployed1--1--
Unemployed2.501.96–3.18<0.0012.211.69–2.90<0.001
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.