Article

Emerging Heat Risk in South Florida: Temperature Trends, Hospitalizations, and Lessons from India to Inform Early Public Health Adaptation Strategies

Department of Health Promotion & Disease Prevention, Robert Stempel College of Public Health & Social Work, Florida International University, 11200 SW 8th Street AHC 5, Miami, FL 33199, USA
*
Author to whom correspondence should be addressed.
Int. J. Environ. Res. Public Health 2026, 23(9), 1135; https://doi.org/10.3390/ijerph23091135
Submission received: 13 April 2026 / Revised: 18 August 2026 / Accepted: 24 August 2026 / Published: 31 August 2026

Highlights

Public health relevance—How does this work relate to a public health issue?
  • Rising temperature trends are increasingly linked with heat-related illness and hospitalizations, creating a growing public health concern worldwide.
  • Heat vulnerability is shaped not only by temperature, but also by humidity, aging, occupational exposure, housing conditions, and access to cooling, and this burden is exacerbated in hot, humid climates like South Florida and India.
Public health significance—Why is this work of significance to public health?
  • This study links long-term temperature trends with heat-related hospitalization patterns in South Florida, showing that rising temperatures are associated with a measurable increase in healthcare burden.
  • Using India as a high-burden reference case helps place South Florida’s emerging risk in context and highlights lessons from a region with longer experience responding to extreme heat.
Public health implications—What are the key implications or messages for practitioners, policy makers and/or researchers in public health?
  • South Florida may benefit from earlier, more coordinated heat preparedness, including surveillance, early warning systems, cooling access, and protections for vulnerable populations.
  • Future research should move beyond temperature alone to examine the environmental, social, demographic, and occupational drivers that shape heat-related health outcomes.

Abstract

Rising global temperatures are intensifying the frequency, duration, and severity of extreme heat events, posing a growing public health burden worldwide. Heat exposure is increasingly recognized as a major contributor to morbidity and mortality, particularly in regions with high baseline temperatures and large vulnerable populations. This study examines long-term temperature trends and their unadjusted association with heat-related health outcomes across major cities in India and counties across South Florida from 2005 to 2023. Major cities in India are used as a high-burden reference setting with established heat adaptation strategies, providing a framework for understanding how similar risks are emerging in South Florida. This comparison is conceptual, given differences in data structure and availability across regions. A retrospective ecological analysis was conducted using secondary data. Climate variables included annual mean temperature, while health outcomes focused on age-adjusted heat-related hospitalization rates. Temporal trends were assessed using graphical analysis and exploratory statistical analysis to inform early public health adaptation strategies. South Florida exhibited a warming rate of approximately +0.0265 °F/year compared to +0.0230 °F/year in major Indian cities, indicating a slightly faster pace of temperature increase in the subtropical region. County-level regression models in South Florida showed strong model fit, with R2 values ranging from 0.356 to 0.615 (all p < 0.01), indicating a consistent positive relationship between summer mean temperature and heat-related hospitalization rates. Miami-Dade County demonstrated the strongest association (R2 = 0.615), while Palm Beach County showed greater variability despite maintaining a statistically significant relationship (p = 0.007). Across all counties, heat-related hospitalization trends increased over time in parallel with rising temperatures. These findings, even though exploratory and unadjusted, position South Florida as an emerging high-risk region, where increasing temperature trends are beginning to mirror patterns observed in historically heat-burdened settings such as India. Lessons from India’s implementation of heat action plans, early warning systems, and community-level interventions provide a framework for strengthening climate adaptation strategies in South Florida.

1. Introduction

Global climate change has emerged as one of the most pressing public health challenges of the 21st century. Global temperature trends show a consistent upward trajectory across all continents since the mid-20th century, with particularly sharp increases observed in recent decades [1]. While earlier fluctuations were modest, the post-1980 period reflects accelerated warming, with most regions experiencing temperatures well above historical baselines [2]. This burden has been further intensified by record-breaking temperatures reported in recent years across countries such as Algeria, Morocco, Peru, Portugal, and Spain. Heat-related morbidity and mortality remain substantial in several Asian countries, including India and Thailand. For instance, Thailand reports approximately 2500–3000 cases of heat-related illness annually, while India recorded over 31,000 heat-related deaths between 2017 and 2021 [3,4].
Extreme heat poses a unique health risk due to its gradual onset and lack of early signs. Prolonged exposure can overwhelm the body’s thermoregulatory mechanisms, leading to dehydration, cardiovascular strain, heat exhaustion, and heat stroke [5,6]. Temperature alone does not tell the whole story when it comes to heat stress; the interaction between heat and humidity is what truly drives physiological strain. Because high humidity impairs the body’s ability to cool itself through sweat evaporation, researchers rely on the heat index to accurately measure this combined thermal load. Studies consistently show that this interaction sharply increases core body temperature and cardiovascular stress, making humidity just as critical to human health outcomes as the raw air temperature [7].
A combination of environmental, social, and demographic factors influences heat-related vulnerability. Environmental conditions amplify risk; for instance, the urban heat island effect increases temperatures in densely built areas or regions already experiencing rising temperatures. When paired with high humidity, this reduces the body’s ability to cool, thereby increasing physiological stress [8]. Biological and demographic factors further contribute to risk, particularly among vulnerable populations. Elderly individuals, infants, pregnant women, and those with chronic diseases are at increased risk of severe outcomes. Vulnerability is also disproportionately higher among outdoor laborers, individuals of lower socioeconomic status, and populations lacking access to adequate ventilation and cooling systems [9]. Social factors play a critical role, as housing quality, access to ventilation, occupational exposure, and healthcare access significantly shape health outcomes [10]. Overall, environmental exposures, coupled with social determinants such as housing conditions, healthcare access, and occupational risk, amplify susceptibility to heat-related illnesses [11].
India has long been recognized as one of the global hotspots for heat-related morbidity and mortality, with rising temperatures contributing to a substantial and growing public health burden. Evidence suggests that heat-related mortality among older adults has increased by nearly 68% over the past two decades, with Asia accounting for a significant proportion of global heat-related deaths [12,13]. Across major cities in India, widespread exposure, high population density, and underlying vulnerabilities have resulted in large segments of the population being at high to very high risk of heat-related illness. Clinically, heat-related illness in the Indian context often presents with severe complications, including multi-organ dysfunction and significant mortality, highlighting the severity of the burden [14]. At the same time, sustained exposure to this burden has pushed India to move toward active heat adaptation. Interventions such as heat action plans, early warning systems, and community-based strategies have been introduced to improve preparedness and reduce risk [15,16]. While gaps in implementation remain, these efforts offer a strong, real-world framework for how health systems can respond to extreme heat.
Unlike major cities in India, South Florida represents an emerging risk environment where rapid warming is not yet matched by equally developed public health response systems. The region’s high humidity, aging population, and urban heat island effect contribute to increased physiological stress and heat-related illness [17,18]. While healthcare infrastructure is more developed and readily available, disparities persist; limited access for lower-income families continues to drive vulnerability. Research has demonstrated an increasing rate of heat-related hospitalizations across South Florida, highlighting a growing burden of extreme heat in subtropical urban environments [5]. Moreover, rising surface temperatures due to greenhouse gas emissions have increased the frequency and severity of extreme heat events worldwide [19]. These environmental changes are associated with substantial increases in heat-related mortality and morbidity.
Major cities in India and South Florida share a comparative framework: both regions experience high temperatures, but they differ in infrastructure, socioeconomic conditions, and healthcare access. India is one of the world’s hotspots for heat-related mortality and morbidity, characterized by consistently high baseline temperatures and extreme heat waves. It also faces heatwaves that affect large populations, particularly working people and aging populations [20]. In contrast, South Florida, while buffered by coastal influences, is experiencing a rapid acceleration of the warming trend. Even though South Florida has more developed healthcare systems and greater clinical capacity than India, it faces compounding risks from high ambient humidity, rapid urbanization, an aging population, and a large outdoor workforce [17,21].
Despite increasing concern around rising temperatures, there remains limited research specifically examining how long-term heat trends translate into measurable health outcomes in South Florida. Heat-related hospitalizations serve as a critical and observable indicator of population-level burden, as they capture severe manifestations of heat exposure that require clinical care and reflect strain on the healthcare system [11]. While existing studies have documented rising temperatures and general health risks, there is a lack of integrated analysis linking these trends to hospitalization patterns at a regional level. This gap is particularly important in South Florida, where rapid warming, high humidity, and underlying population vulnerabilities intersect, yet the extent to which these conditions are already translating into increased healthcare burden remains underexplored.
In contrast, major cities in India have already experienced a sustained and severe burden of heat-related illness, providing an important reference point for understanding how South Florida might compare as temperatures continue to rise [13]. For example, a prehospital surveillance study in Telangana, India, recorded a heat illness incidence of 1.5 cases per 100,000 population during the 2018–2019 heat wave seasons, rising to 4.5 per 100,000 among rural and tribal populations [22], and a comprehensive multi-city analysis estimated approximately 1116 heatwave-attributable deaths per year across ten major Indian cities, including three of the cities examined here: Delhi, Chennai, and Mumbai [13]. Climatically, this comparison is grounded in a shared thermodynamic burden where both regions experience humid subtropical conditions, i.e., persistent-near-saturation humidity compounded by high temperatures [23,24]. This humidity-heat interaction severely impairs sweat evaporation, creating identical physiological strain and thermal risk profiles for outdoor populations in both settings. These patterns provide a benchmark for understanding where South Florida stands relative to a high-burden setting. Moreover, given India’s long-standing experience with heat-related illness, it serves as a critical reference case from which actionable lessons can be drawn to inform early and proactive public health responses in emerging high-risk regions. The purpose of this comparison is not to establish direct socioeconomic equivalence, but to anchor South Florida, an emerging humid subtropical risk zone, against a benchmark region with long-standing exposure to extreme heat-humidity interactions. By comparing a rapidly warming coastal context with an established high-burden setting, this framework highlights how severe physiological stress operates across different infrastructural landscapes. Although geographic and seasonal variability exist, including winter temperature differences and considerable climatic heterogeneity within India, baseline heat exposure remains consistently elevated in both settings [20]. Importantly, India also serves as a reference model for large-scale heat adaptation, having implemented interventions such as heat action plans, early warning systems, and community-based response strategies that have demonstrated measurable reductions in heat-related mortality. This comparison is intended as a conceptual benchmarking approach rather than a direct pooled statistical analysis, given differences in data availability, structure, and context across the two regions.
This study examines how rising temperature trends in South Florida compare to those observed in India, evaluates how these trends are associated with heat-related hospitalizations in South Florida, and explores how insights from India can inform early public health adaptation strategies. The comparison with India is intentional, as it represents a high-burden setting that has already experienced sustained heat-related health impacts and has begun implementing adaptation strategies. While prior research has largely examined temperature trends or heat-related health outcomes separately, there remains limited work that directly links long-term climate patterns to real-world healthcare burden in emerging subtropical regions such as South Florida, or that uses high-burden global settings to inform early response strategies. This study addresses that gap by integrating temperature trends with hospitalization data in South Florida, while using India as a reference case to better understand risk patterns and identify practical, early-stage public health responses to rising heat exposure.

2. Materials and Methods

2.1. Study Design

A retrospective observational study design was used to examine long-term temperature trends and their association with heat-related health outcomes. The analysis was conducted in two components: (1) cross-regional temperature trend benchmarking between India and South Florida, and (2) an assessment of the relationship between temperature trends and heat-related hospitalizations in South Florida. Annual mean temperature was selected as the primary exposure variable because it captures the sustained thermal burden experienced by a population across a full warm season, rather than isolated peak events. While acute heat-related health effects are often driven by daily maximum temperatures and short-duration extreme events, annual mean temperature provides a consistent measure of cumulative exposure and is appropriate for examining long-term population-level trends in heat burden. This measure is appropriate for detecting gradual, long-term shifts in heat exposure and is consistently available across both study regions, supporting cross-regional comparability. Linear regression was chosen as the primary analytic method given the study’s ecological design, the continuous nature of both the exposure and outcome variables, and the goal of estimating directional trends over an 18-year period, a context in which linear models provide interpretable, reproducible estimates without overfitting.

2.2. Study Setting

The study focused on two regions with differing climate profiles and public health contexts: India, representing a high-burden setting with prolonged exposure to extreme heat, and South Florida, representing an emerging high-risk subtropical region characterized by increasing temperatures, high humidity, and population vulnerability.

2.3. Data Sources

2.3.1. Temperature Data

Temperature data were obtained from publicly available climate monitoring datasets:
  • India (1951–2024): Daily temperature data for major Indian cities were obtained from OpenCity Data [25].
  • South Florida (1931–2025): Historical temperature data were obtained from the Florida Climate Center [26].
Major Indian cities included (Bengaluru, Chennai, Delhi, Kolkata, and Mumbai) in the analysis were selected based on data availability and completeness of long-term temperature records, with the aim of capturing representative urban climate patterns across high-burden settings. For both regions, temperature data were aggregated to annual mean temperature values to allow for cross-regional comparison.

2.3.2. Health Outcome Data

Data on heat-related hospitalizations in South Florida were obtained from the publicly available Florida Department of Health—Public Health Tracking System [27]. These datasets included county-level hospitalization rates for heat-related illnesses across Broward, Miami-Dade, and Palm Beach counties.
  • Exposure Variable:
Annual mean temperature (°F)
  • Outcome Variable:
Age-adjusted heat-related hospitalization rates (per 100,000 population)
  • Time Variable:
Year (continuous)
Given the conceptual and exploratory nature of this study, the analysis did not adjust for potential confounders such as humidity, population aging, socioeconomic status, air conditioning access, and healthcare availability. These factors may influence the observed relationship and limit the ability to draw causal inferences or assess directionality.

2.4. Data Processing and Harmonization

All datasets were cleaned, standardized, and harmonized prior to analysis. Temperature data from India and South Florida were aligned to ensure comparability in temporal resolution and unit of measurement (°F). Daily temperature observations were aggregated to annual means for each location and year, providing a consistent, comparable unit of analysis across both regions. Missing values in the temperature record were handled by excluding years with insufficient daily coverage rather than imputation, to avoid introducing artificial smoothing into the trend estimates. Hospitalization data were matched by year and county to corresponding temperature data for South Florida, with no interpolation applied across non-overlapping time windows. Differences in temporal coverage between temperature and hospitalization datasets reflect data availability across sources; analyses were therefore restricted to overlapping periods for exposure–outcome assessment, while longer temperature records were retained for trend benchmarking. A key assumption underlying the harmonization is that annual mean temperature is a valid proxy for cumulative heat exposure within each year, an assumption that is appropriate for detecting long-term trends but that would not capture within-year variability or the distinct health effects of short-duration heat waves. Cross-regional data were not combined into a single model; India and South Florida data were analyzed separately and compared descriptively, avoiding the analytic assumptions that a pooled cross-continental model would require.

2.5. Statistical Analysis

2.5.1. Temperature Trend Analysis

Temporal trends in temperature were assessed using graphical visualization and linear regression models. Linear regression over time (year as the independent variable, annual mean temperature as the dependent variable) provides a straightforward, interpretable estimate of the average warming rate across the study period, expressed as °F per year. This approach is standard in long-term climate trend analysis and was applied consistently to both regions to allow direct comparison of warming rates. Warming rates (°F/year) derived from these models were used to characterize and compare the pace of temperature change between India and South Florida.

2.5.2. Association Between Temperature and Hospitalization Data in South Florida

To evaluate the relationship between temperature and health outcomes, simple linear regression models were used to assess the association between annual mean summer temperature (independent variable) and age-adjusted heat-related hospitalization rates per 100,000 population (dependent variable) across South Florida counties. Linear regression was appropriate here because both variables are continuous, the relationship was hypothesized to be monotonically positive based on the prior literature, and the ecological study design does not support the more complex individual-level modeling approaches (e.g., time-series or case-crossover designs) that would require individual-level exposure and outcome data. Age-adjusted hospitalization rates were used as the outcome measure to account for differences in county age distribution over time and across counties, reducing the potential for confounding by demographic change. Spearman’s rho was added to confirm the association is not driven by outliers.
Separate models were developed for Broward, Miami-Dade, and Palm Beach counties, as well as a combined model pooling all county-years. County-specific models allow for detection of heterogeneity in the temperature–hospitalization relationship across the region, while the combined model provides a regional-level estimate. Model fit was evaluated using R2 values, which indicate the proportion of variance in hospitalization rates explained by summer mean temperature, and statistical significance was determined at p < 0.05. The models were not adjusted for additional covariates, consistent with standard practice for exploratory, time-trend ecological analyses, in which the goal is to characterize population-level directional patterns rather than estimate individual-level causal effects [28,29]; this is acknowledged as a limitation in Section 4.7.

2.6. Data Visualization

Time-series plots were used to illustrate temperature trends and hospitalization patterns over time. Scatter plots with fitted regression lines were generated to visualize the association between temperature and hospitalization rates across counties.

2.7. Software and Tools

All analyses were conducted using Python 3.13.9 (Anaconda, Clang 20.1.8 build). Data processing, statistical modeling, and visualization were performed using standard Python libraries such as statsmodels 0.14.5, pandas 2.3.3, matplotlib.pyplot 3.10.6 and numpy 2.3.5. ClaudeAI (Sonnet 5) and Codex (5.6 Sol) were used to support coding efficiency and validation during the analytical process. ChatGPT (5.6 Sol) was used for language editing purposes only. ClaudeAI (Sonnet 5) was used to fix referencing and citation errors. Each citation, code and sentence was independently validated by authors. The complete analysis pipeline, including data processing, statistical modeling, and figure generation code, is publicly available online [30].

3. Results

This section presents the observed temperature trends, temporal patterns in heat-related hospitalizations, statistical associations between temperature and hospitalization rates, and a cross-regional comparison of warming trajectories.
Table 1 summarizes the temperature records and heat-related hospitalization data included in the study. The analysis included seven South Florida weather stations spanning 1912–2025 and five Indian cities spanning 1951–2024, although the 2024 Indian observations represent only a partial calendar year. Mean annual temperatures varied across locations, with greater cross-location temperature variability among the Indian cities than among the South Florida stations. Both regions demonstrated positive long-term warming trends, with the mean station-level rate estimated at +0.0253 °F per year in South Florida and +0.0230 °F per year in India. Descriptive Characteristics of Temperature Records, Warming Trends, and Heat-Related Hospitalizations in South Florida and India are shown in Table 1, Table 2, Table 3, Table 4 and Table 5.
Between 2005 and 2023, the three South Florida counties recorded 2653 heat-related hospitalizations. Broward reported the highest total number of hospitalizations, while Palm Beach had the highest mean age-adjusted hospitalization rate. South Florida’s summer mean temperature increased from 83.87 °F in 2005 to 85.02 °F in 2023, although the estimated linear trend was not statistically significant. These findings provide a descriptive overview of the temperature and hospitalization patterns examined in the study.

3.1. Temperature Trends

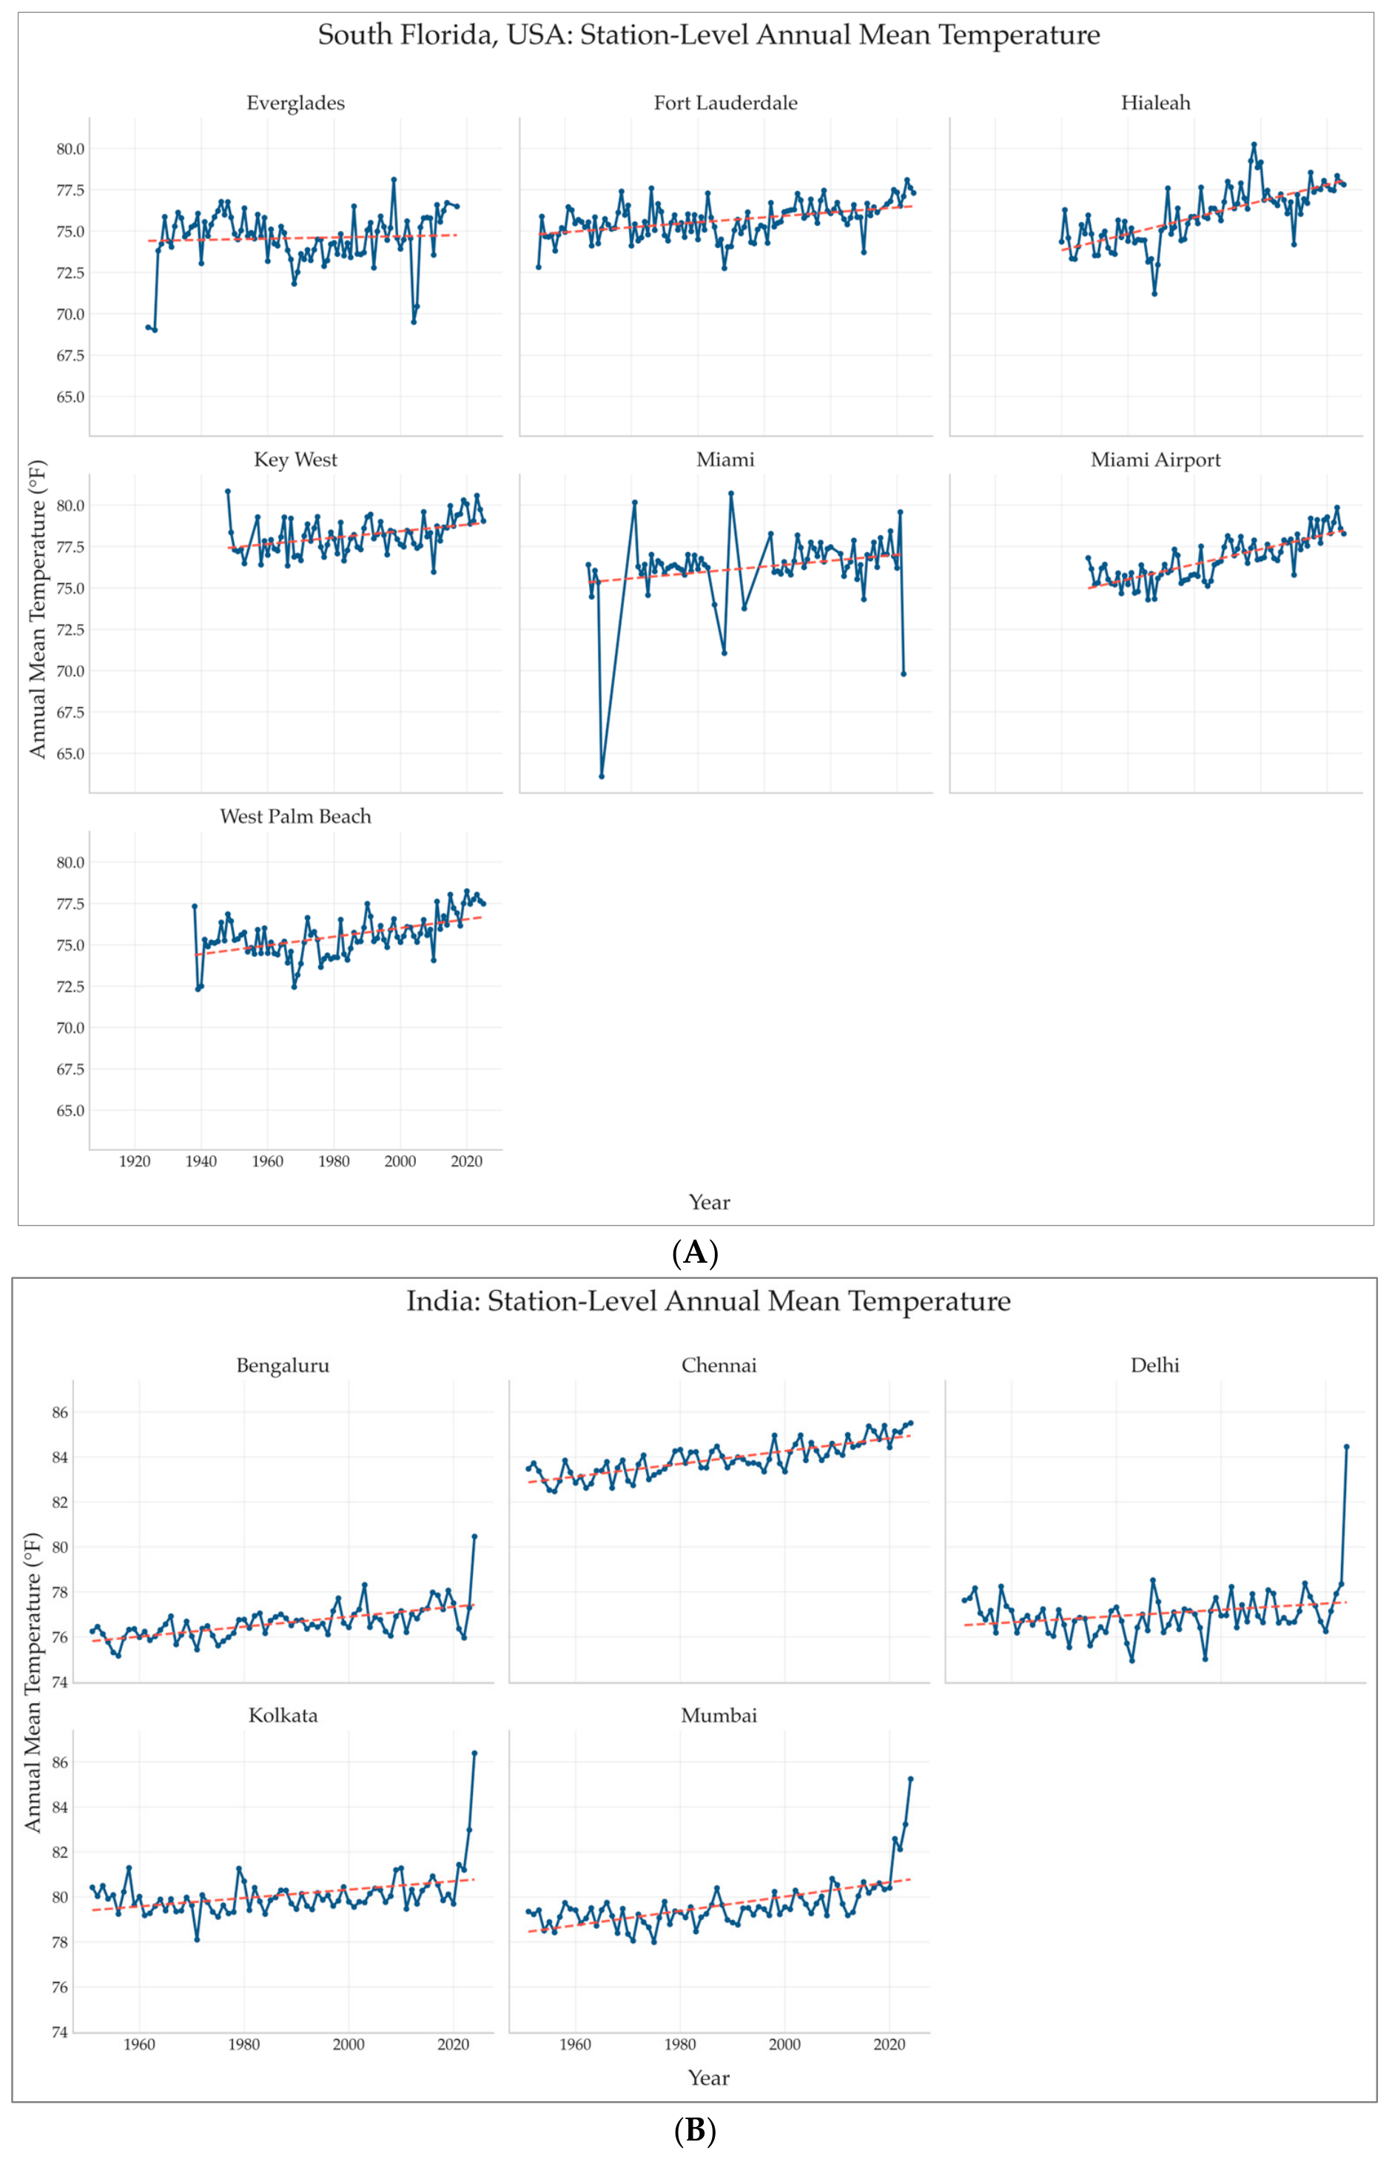
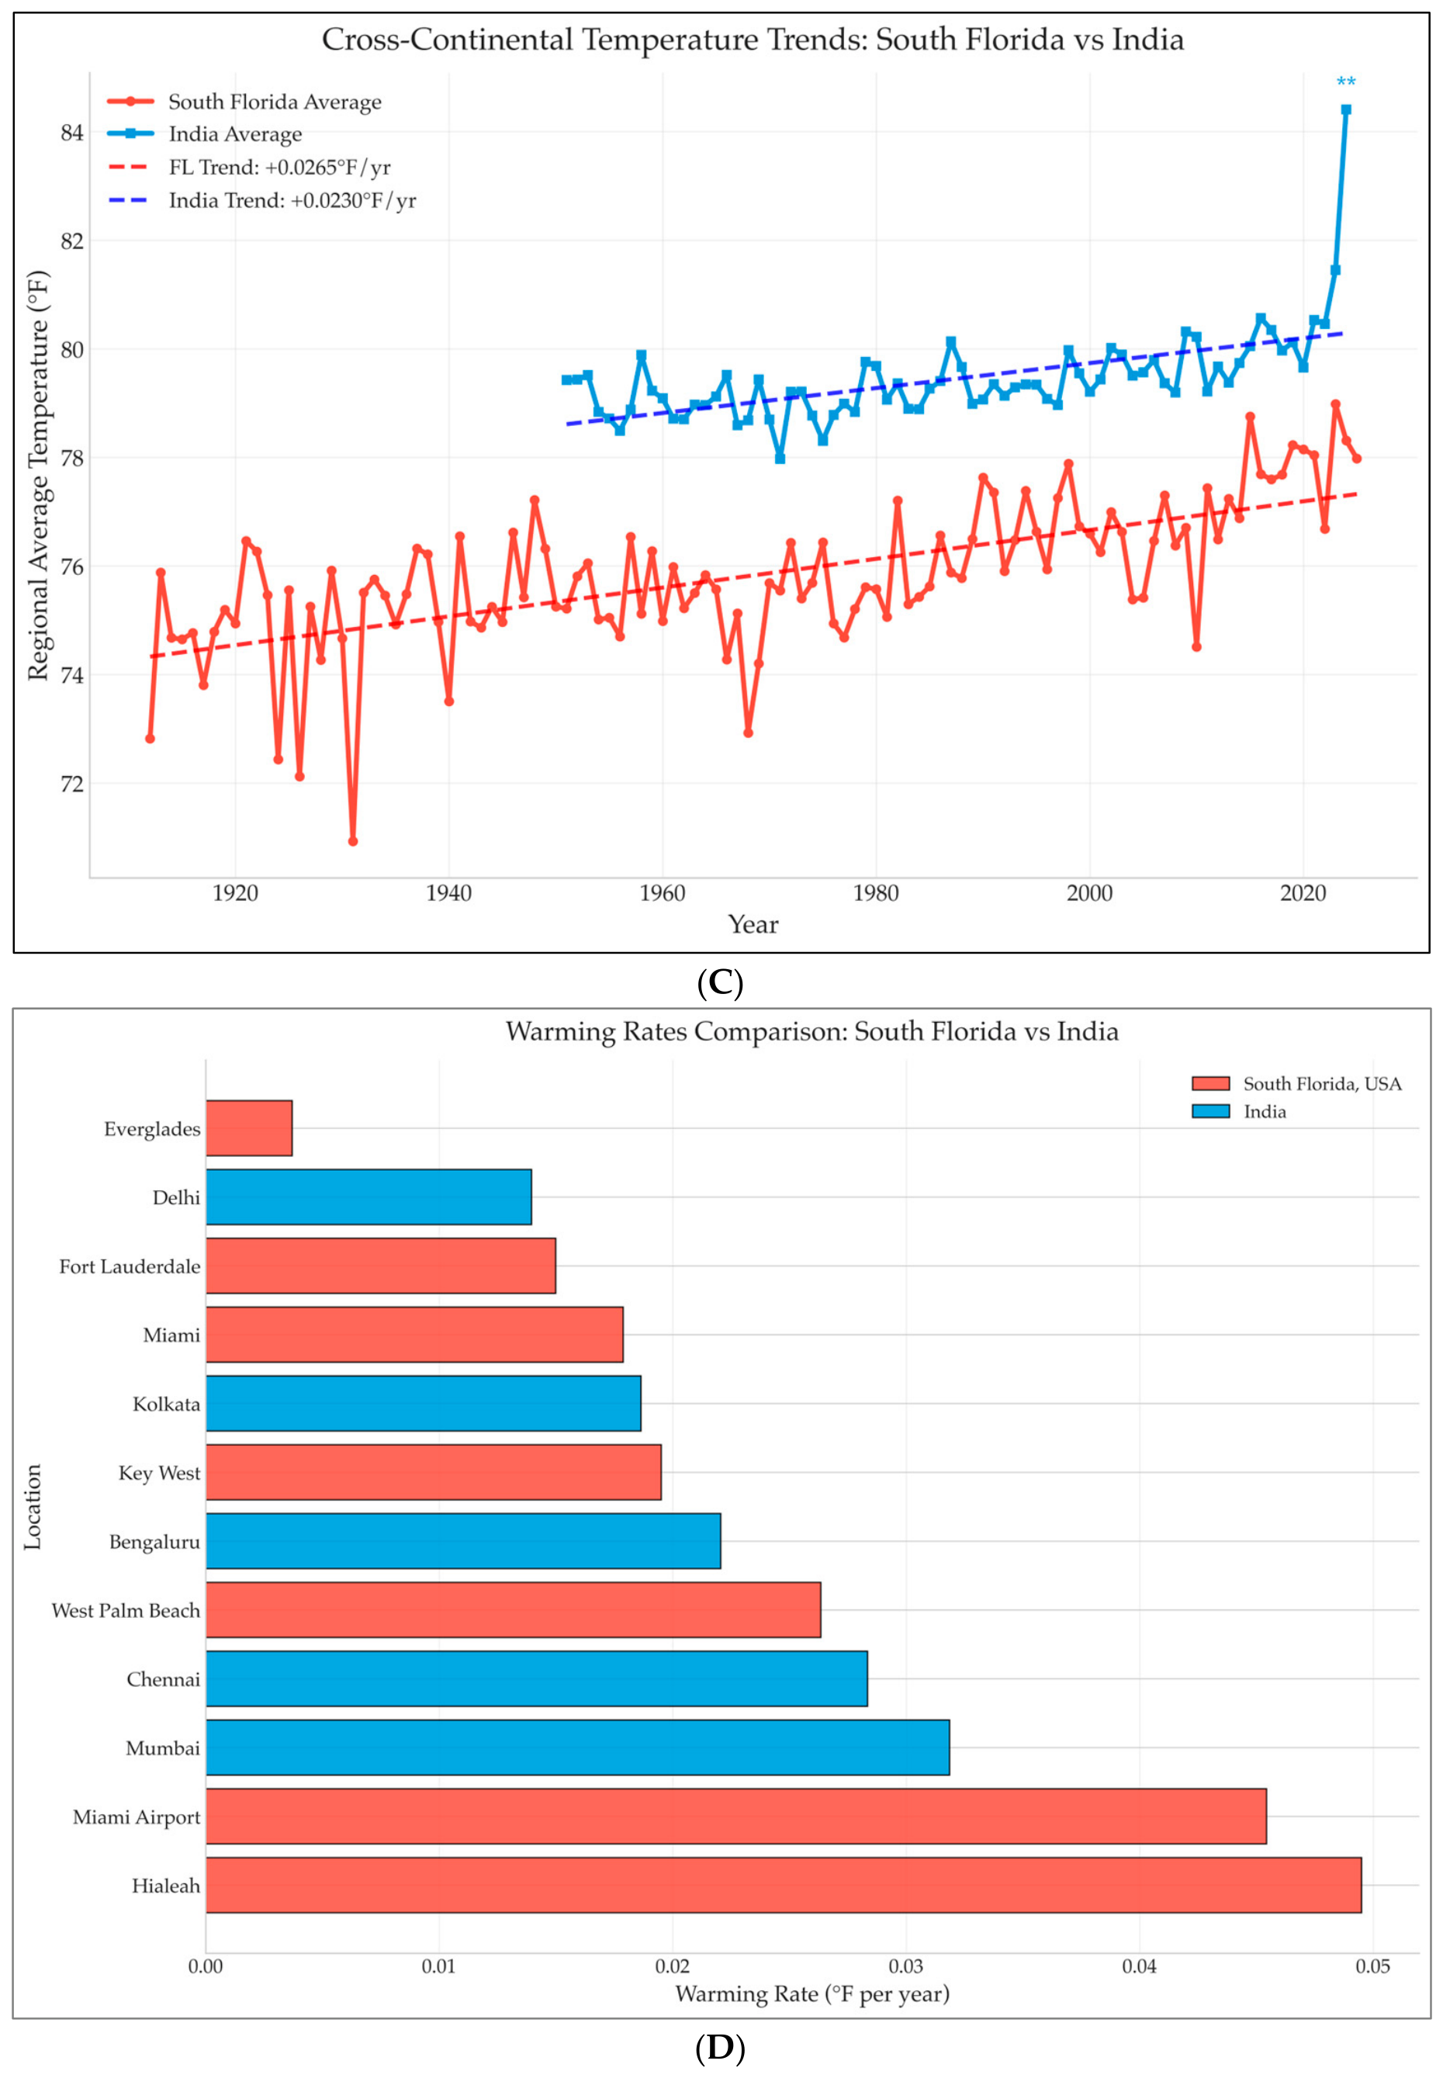
Both South Florida and India exhibited clear and sustained upward temperature trends over the study period, as illustrated in Figure 1A–D.
Figure 1A illustrates long-term annual mean temperature patterns across seven South Florida weather stations. Although the stations differ in record length and year-to-year variability, most show an upward temperature trajectory over their available observation periods. The strongest warming trends are visible in Hialeah and Miami Airport, while Everglades shows a comparatively modest increase. Miami displays greater annual variability and several pronounced temperature departures, whereas Fort Lauderdale, Key West, and West Palm Beach follow steadier upward patterns. Taken together, these station-level records indicate that warming has occurred across much of South Florida, although its magnitude and consistency vary by location.
Figure 1B presents long-term annual mean temperature patterns for Bengaluru, Chennai, Delhi, Kolkata, and Mumbai. All five cities show positive warming trajectories across their available records, although the pace and year-to-year variability differ by location. Mumbai and Chennai exhibit the strongest estimated warming rates, while Delhi shows a more gradual long-term increase. Bengaluru and Kolkata also demonstrate sustained upward patterns despite periodic annual fluctuations. The pronounced increases at the end of several series should be interpreted cautiously within the broader historical record. Overall, the city-level findings describe a broadly consistent pattern of warming across geographically and climatically diverse areas of India.
Figure 1C compares the regional annual mean temperature trends for South Florida and India. Both regions exhibit sustained upward trajectories over their respective observation periods. South Florida warmed at approximately +0.0265 °F per year, compared with approximately +0.0230 °F per year in India, a difference of about 0.0035 °F per year. South Florida’s record shows substantial year-to-year fluctuation, particularly during the earlier portion of the series, while India’s regional average follows a somewhat more stable upward path before a pronounced increase in the latest observation. Despite these differences in variability and record length, the descriptive trends show that both regions experienced long-term warming, with South Florida displaying a slightly higher estimated annual rate.
Figure 1D compares the estimated annual warming rates for each South Florida station and Indian city. All included locations show positive warming rates, but the magnitude of warming varies considerably. Hialeah and Miami Airport display the highest estimated rates, at approximately +0.0495 °F and +0.0454 °F per year, respectively. Among the Indian cities, Mumbai shows the highest rate at approximately +0.0319 °F per year, followed by Chennai at +0.0283 °F per year. Everglades and Delhi exhibit the lowest estimated rates within their respective regions. These findings highlight the geographic variability underlying the broader regional trends: warming is evident across the included locations, but it has not occurred at the same pace everywhere. Because the station records cover different observation periods, the rates should be viewed as descriptive summaries of each location’s available record rather than strictly equivalent comparisons.

3.2. Temporal Trends in Heat and Hospitalizations in South Florida

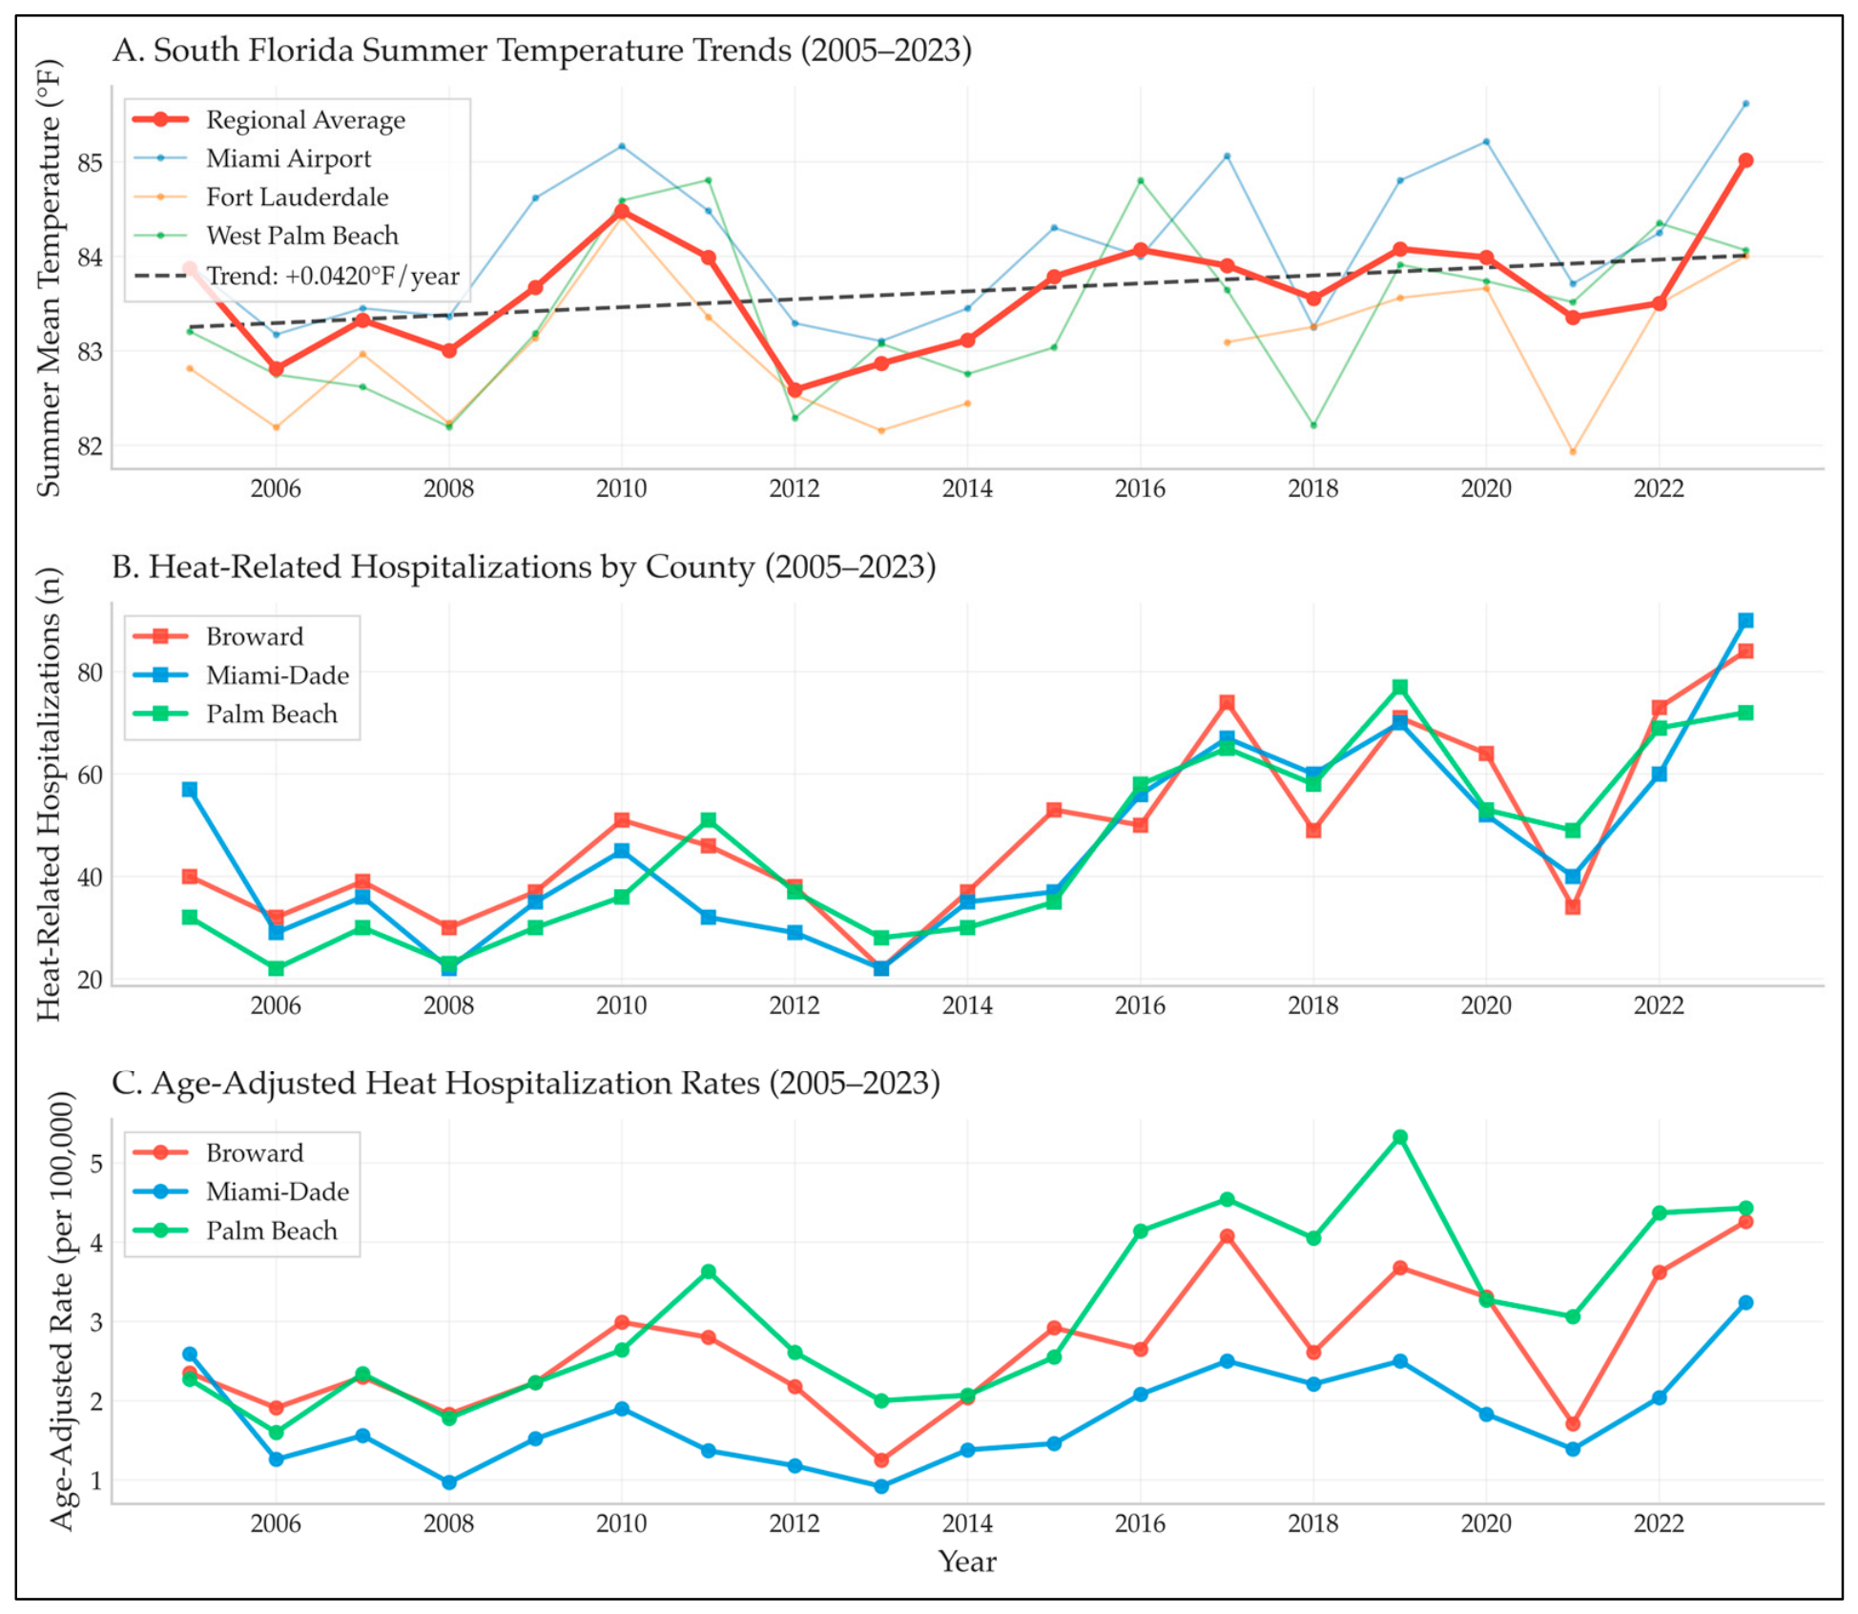
South Florida has shown a steady increase in temperature, with warming accelerating in recent years as show in Figure 2. India showed a similar upward trend, though with greater year-to-year variability attributable to monsoon seasonality and regional climate diversity. Critically, heat-related hospitalization rates in South Florida rose in parallel with this warming signal, indicating that temperature increases are already occurring alongside a rise in measurable healthcare burden. The regression analysis confirmed statistically significant positive association trends in both temperature and hospitalization outcomes across the study period, showing a consistent temporal association between rising ambient temperatures and increased heat-related health events.

3.3. Association Between Temperature and Hospitalizations

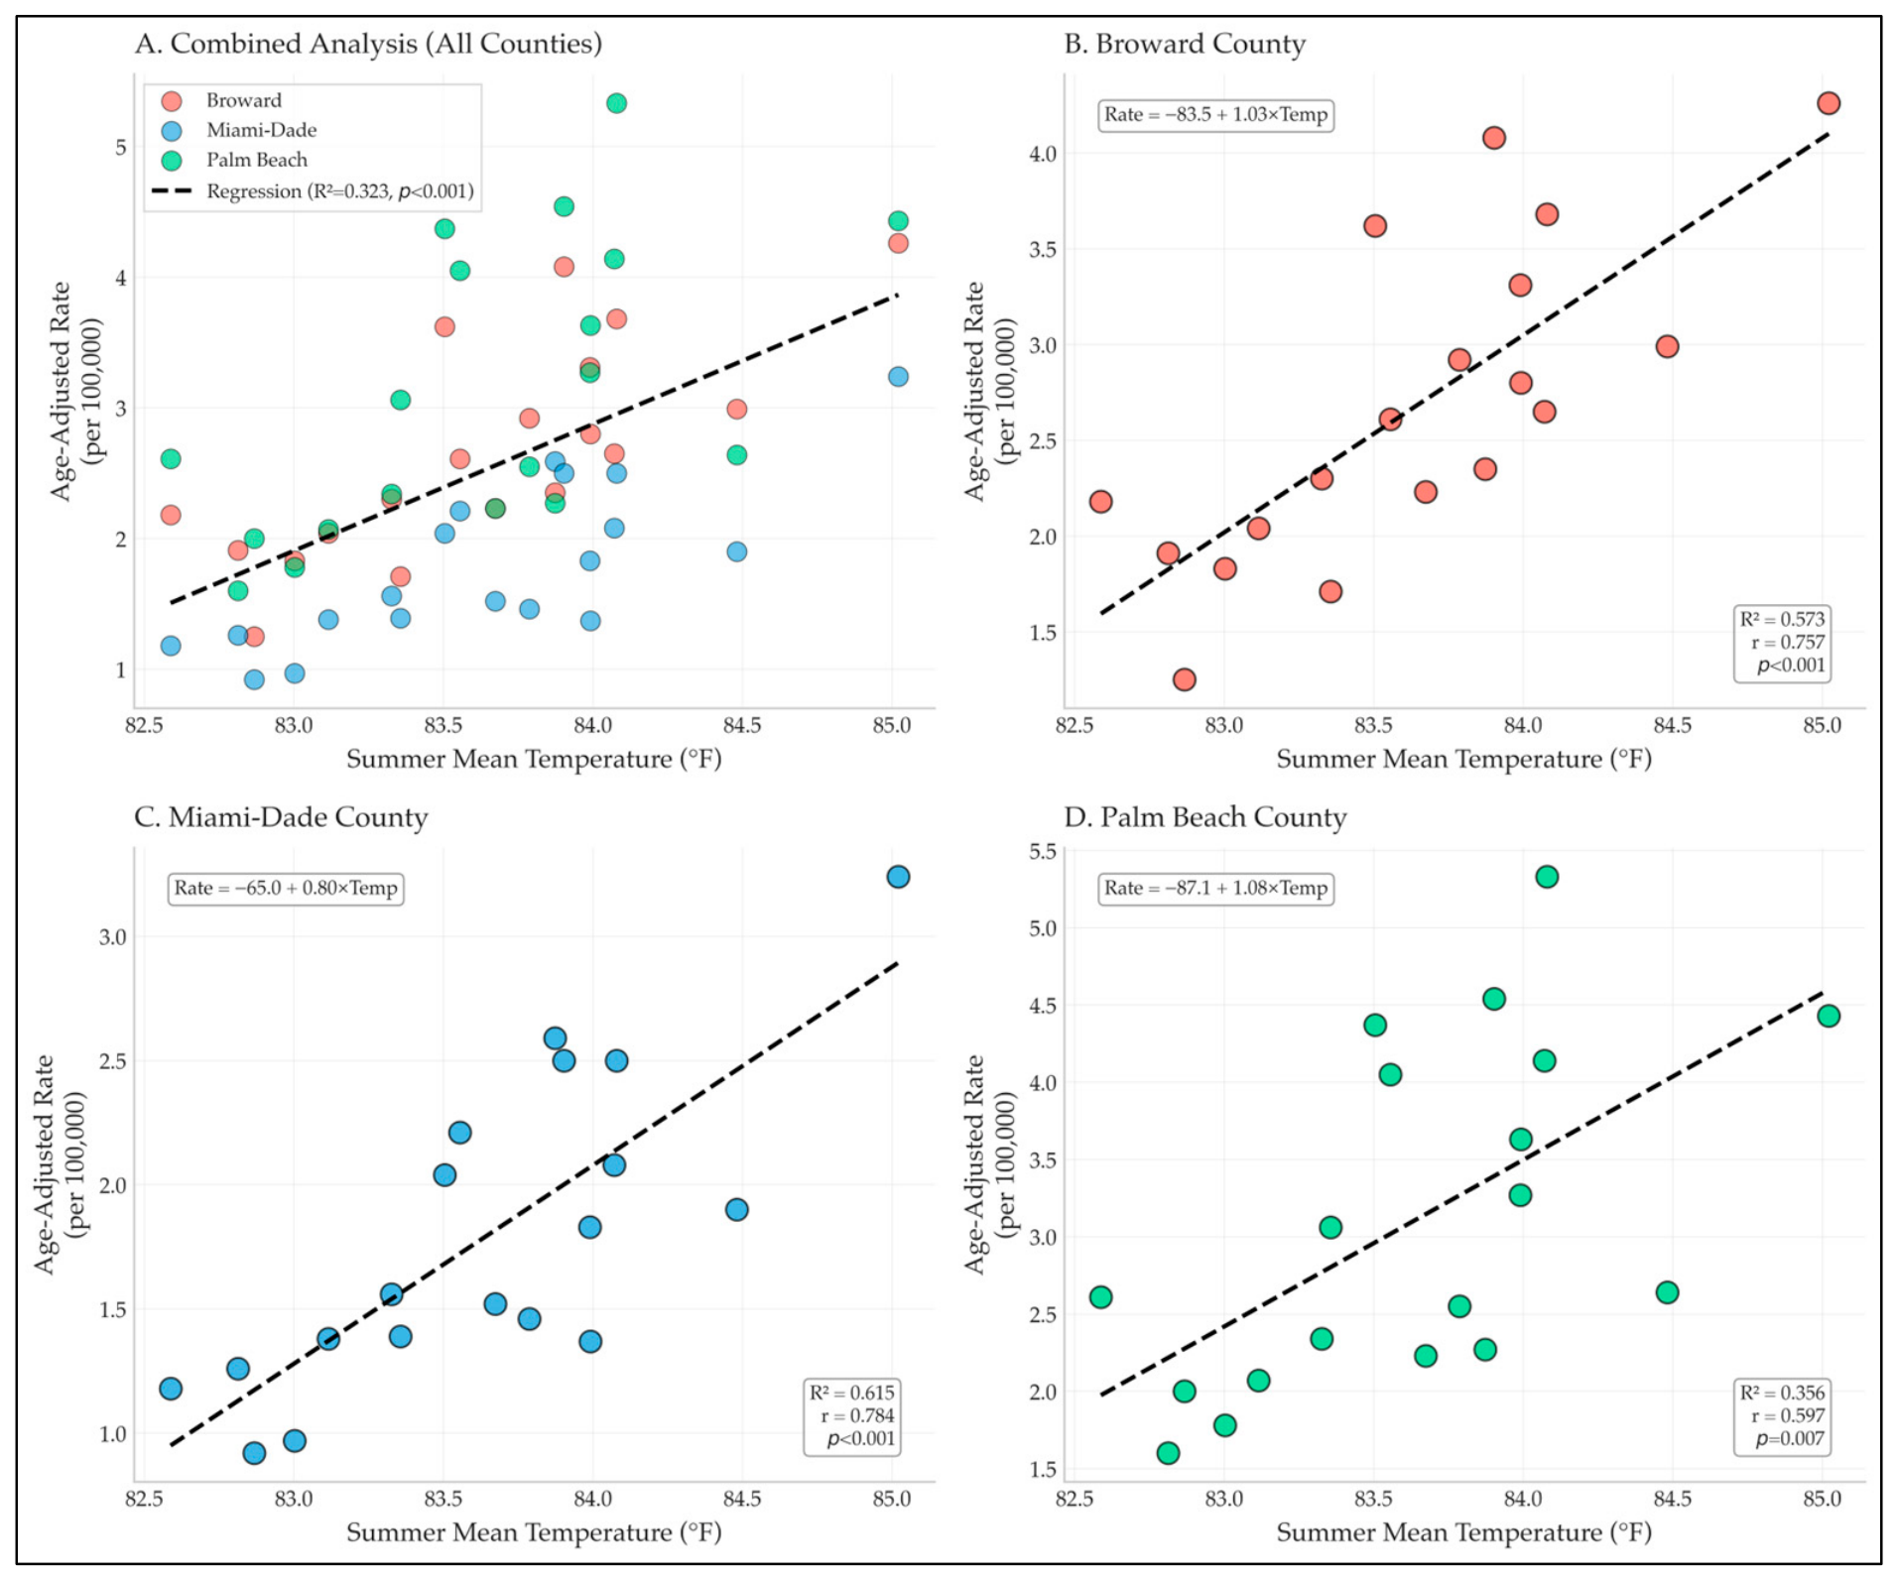
Table 2 summarizes the association between summer mean temperatures and age-adjusted heat-related hospitalization rates across South Florida. These findings are exploratory and should not be interpreted as causal or predictive. All three counties demonstrated statistically significant positive relationships between temperature and hospitalization rates, accompanying a measurable increase in heat-related healthcare demand. Miami-Dade County showed the strongest model fit (R2 = 0.615, p < 0.001), meaning that summer mean temperature alone accounts for approximately 62% of the variation in age-adjusted hospitalization rates, a substantial explanatory share for a single predictor in an ecological model. The regression equation for Miami-Dade (Hospitalization Rate = −65.0 + 0.80 × T) implies that for each 1 °F increase in mean summer temperature, hospitalization rates rise by approximately 0.80 cases per 100,000 population. Broward County showed a similarly strong association (R2 = 0.573, p < 0.001), with a slightly steeper slope (1.03 per °F), suggesting that each degree of warming in Broward corresponds to roughly one additional hospitalization per 100,000 residents. Palm Beach County showed a weaker model fit (R2 = 0.356, p = 0.007), indicating greater variability in hospitalization rates that temperature alone does not fully explain, possibly reflecting differences in population age distribution, access to cooling infrastructure, or local reporting patterns. Nevertheless, the relationship remains statistically significant, reinforcing the regional pattern. The combined model across all counties (R2 = 0.373, p < 0.001) confirms a consistent positive association at the regional level. Associations between Summer Temperature and Heat-Related Hospitalizations in South Florida (2005 to 2023) are depicted across Table 6, Table 7 and Table 8.
Summer mean temperature was positively associated with age-adjusted heat-related hospitalization rates across all three South Florida counties (Table 6, Table 7 and Table 8). The direction of the association remained consistent whether it was measured using Pearson correlation or the rank-based Spearman correlation. The county-specific Pearson correlations ranged from 0.597 in Palm Beach County to 0.784 in Miami-Dade County, and all three associations were statistically significant.
Miami-Dade showed the strongest linear model fit, with summer mean temperature accounting for approximately 62% of the observed variation in its annual age-adjusted hospitalization rate (R2 = 0.615). Each 1 °F difference in summer mean temperature was associated with an estimated difference of 0.80 hospitalizations per 100,000 population (95% CI: 0.48–1.12). Broward showed a similarly strong pattern (R2 = 0.573), with an estimated difference of 1.03 hospitalizations per 100,000 for each 1 °F difference in temperature (95% CI: 0.58–1.48).
The association in Palm Beach was more variable but remained positive and statistically significant. Each 1 °F difference in summer mean temperature was associated with an estimated difference of 1.08 hospitalizations per 100,000 (95% CI: 0.34–1.82), and the model accounted for approximately 36% of the observed variation in annual rates (R2 = 0.356). The wider confidence interval reflects greater uncertainty around the Palm Beach estimate.
When observations from all three counties were combined, the model showed a moderate positive association (r = 0.568, R2 = 0.323, p < 0.0001). The pooled coefficient indicated an estimated difference of 0.97 hospitalizations per 100,000 for each 1 °F difference in summer mean temperature (95% CI: 0.59–1.35). However, this estimate should be interpreted cautiously because the same annual regional temperature was assigned to all three counties, and the pooled model’s residuals did not satisfy the normality test. Moreover, the small sample size (N = 19 per county) makes R2 and p-values less stable.
Figure 3 makes these patterns easier to see. The county-specific panels show positive fitted slopes in Broward, Miami-Dade, and Palm Beach, while also showing the annual variation around each regression line. Together, Table 6, Table 7 and Table 8 and Figure 3 describe a consistent positive association between warmer summers and higher heat-related hospitalization rates during 2005–2023. These findings remain exploratory and do not establish that temperature alone caused the observed changes in hospitalizations, particularly given limited access to granular data and the absence of key variables that may confound or modify this relationship.


4. Discussion

4.1. Summary of Key Findings

This study shows that rising temperatures in South Florida are associated with a measurable increase in heat-related hospitalizations, with regression models explaining up to 62% of the variation in county-level hospitalization rates using summer mean temperature alone. This is a substantial finding for an ecological analysis with a single predictor: it indicates that ambient temperature is meaningfully associated with healthcare demand, not merely a contextual backdrop. The faster warming rate observed in South Florida (+0.0265 °F/year) relative to major Indian cities (+0.0230 °F/year) is particularly significant because South Florida is warming from a baseline that already generates meaningful physiological heat stress. The public health implication is direct. Without proactive adaptation, the burden of heat-related illness in South Florida could potentially continue to grow in proportion to rising temperatures and reduce the chances for low-cost prevention mechanisms [5,31].

4.2. Drivers of Heat Vulnerability in South Florida: Socioeconomic Disparities

South Florida’s vulnerability to heat reflects a convergence of environmental and demographic risk factors that potentially amplify the physiological burden of rising temperatures. Therefore, there is a need to address geographic and socioeconomic disparities when discussing heat burden. High ambient humidity reduces the effectiveness of evaporative cooling, meaning that the body must work harder to dissipate heat at any given temperature compared to drier climates [8]. Dense urban development intensifies the urban heat island effect, raising surface and air temperatures in built-up areas above regional averages [10]. Meanwhile, the region’s aging population faces disproportionate risk: older adults experience diminished thermoregulatory capacity, higher rates of chronic disease, and greater dependence on medications that impair heat tolerance [9]. Miami-Dade County’s stronger temperature–hospitalization association (R2 = 0.615) compared to Palm Beach (R2 = 0.356) is consistent with this pattern, as Miami-Dade has greater urban density, a larger proportion of low-income residents with limited cooling access, and a higher share of heat-exposed populations, including agricultural and farmworkers, outdoor and construction workers, individuals experiencing homelessness, migrant or undocumented populations, and those with limited access to stable housing or cooling, in addition to pregnant women and children [24,32,33,34]. These overlapping risks highlight that South Florida’s challenge is not solely environmental, but one of climate-amplified social vulnerability. Addressing this burden therefore requires approaches that consider both heat exposure and the underlying conditions that increase susceptibility. While this study did not include data on these underlying drivers, factors such as occupational exposure, housing conditions, access to air conditioning, socioeconomic status, and healthcare access likely play a critical role in shaping observed hospitalization patterns. Future hypothesis-driven studies incorporating these variables are needed to better understand these relationships and inform targeted, population-specific interventions [35].

4.3. Current Public Health Infrastructure and Gaps

South Florida has existing heat-related public health infrastructure, including heat warning systems coordinated through the Centers for Disease Control and Prevention (CDC) and National Oceanic and Atmospheric Administration (NOAA), and urban planning efforts such as tree canopy expansion and reflective building materials in select areas [36,37,38,39]. These are meaningful first steps, but they remain insufficient relative to the scale and pace of the warming trend documented here. Heat warning systems are only effective when they reach vulnerable populations in time to prompt protective action, yet low-income residents and outdoor workers who face the greatest exposure are often the least connected to formal warning channels and the least able to modify their behavior in response [35,40]. Occupational heat protection for outdoor workers remains limited and inconsistently enforced across Florida, leaving a critical gap in prevention precisely among the population subgroup at highest risk of severe heat-related illness. Strengthening enforcement of occupational heat standards, expanding cooling center access, and improving targeted outreach to high-risk communities would address identified gaps without requiring new clinical infrastructure [5].
Looking ahead, the trajectory established by this study points toward an escalating burden. If current trends continue, this may warrant monitoring South Florida’s heat-related hospitalization rates and temperatures, as the region can potentially expect a compounding increase in heat-related healthcare demand over the coming decades. This may have implications for emergency department capacity, hospital admissions, and healthcare costs, with these burdens falling disproportionately on public health systems already strained by an aging population. Addressing this trajectory requires a shift from reactive, event-driven responses toward integrated, data-driven prevention [40]. Specifically, this means embedding real-time temperature and heat index data into hospital surge planning, developing heat-specific early warning protocols that activate clinical and community resources before hospitalization rates spike, and building heat surveillance into routine public health monitoring systems [11]. The regression models developed in this study, while ecological and not individually predictive, provide a foundation for the county to build projection systems that health planners could use to anticipate plausible high-risk periods and deploy resources proactively.

4.4. Structural Barriers and Policy Implications

Structural barriers constrain the effectiveness of existing interventions and must be addressed for any heat response strategy to reach the populations most at risk. Heat surveillance in South Florida lacks the spatial granularity needed to identify which neighborhoods are experiencing the highest burden in real time, making it difficult to direct resources efficiently during heat events [33,41]. Policy fragmentation across municipal, county, state, and federal levels further complicates coordinated responses, as heat action plans developed at one level may not align with enforcement capacity or funding at another [42]. Targeted investment in cooling infrastructure for low-income housing, expansion of publicly accessible cooling centers with extended hours, and integration of heat response into existing social service networks can collectively reduce the structural exposure to heat burden across the region [43].

4.5. Lessons from India’s Heat Action Plan

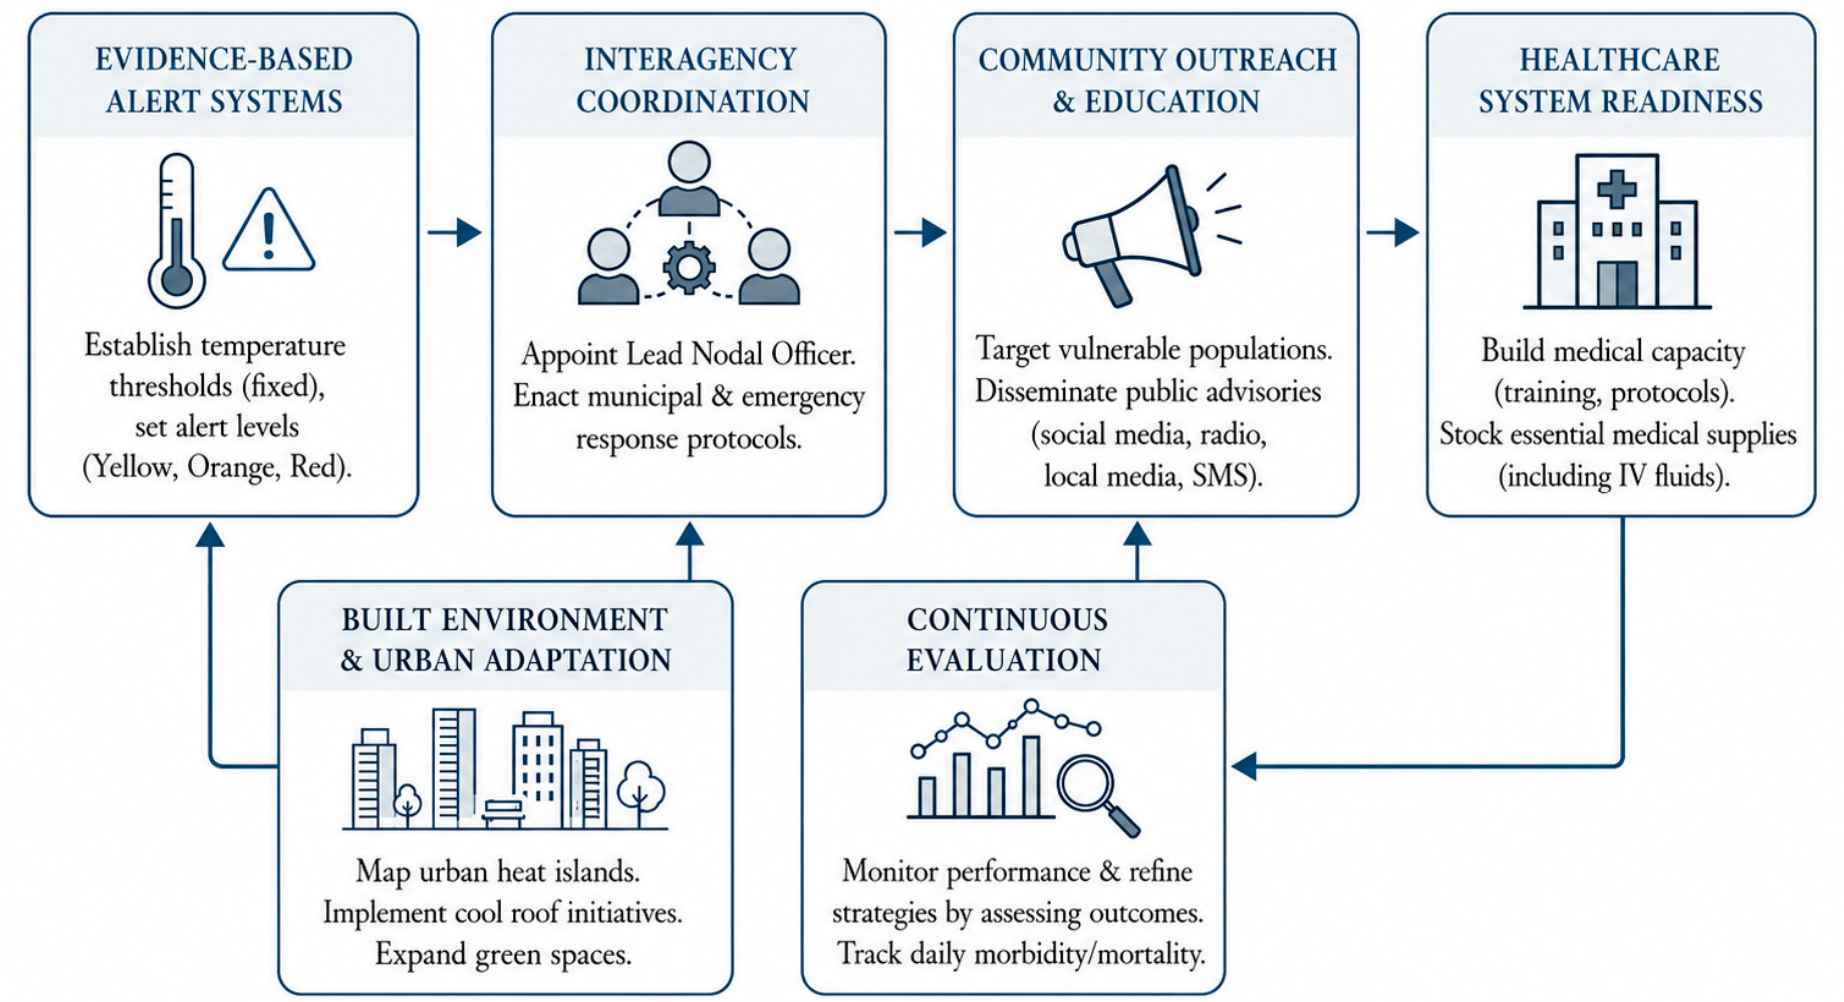
India’s experience offers a concrete and evidence-based model for the kind of systematic heat response that South Florida has yet to fully develop. The Ahmedabad Heat Action Plan, implemented after a devastating 2010 heat wave that caused over 1300 excess deaths, demonstrated that coordinated multi-agency responses incorporating probabilistic early warning systems, tiered alert levels, targeted outreach to vulnerable populations, and health system capacity building can meaningfully reduce heat-related mortality, even in resource-constrained settings [15,44,45]. Key pointers are extracted and built into a framework in Figure 4 that can be used in a similar context.
The relevance for South Florida is direct: if a rapidly growing city in a low-to-middle income country can build an effective institutional framework for heat response, a high-income subtropical region with established healthcare infrastructure and public health agencies has both the capacity and the obligation to do so. The key lessons extend beyond technical considerations and center on organizational coordination. Effective heat action requires clear inter-agency ownership, pre-defined response thresholds tied to meteorological forecasts, dedicated communication channels to reach high-risk communities, and routine post-season evaluation to improve future response [46]. South Florida already has the institutional actors needed for such a framework; what is needed is the formal coordination structure to activate them systematically [47]. It is also important to note that the drivers and impacts of heat-related risk differ between South Florida and India, reflecting variations in environmental exposure and population vulnerability. In South Florida, aging populations and high humidity increase physiological stress, accompanying a growing burden of heat-related hospitalizations as individuals are more likely to seek and access clinical care [5]. In contrast, in India, heat-related risk is more strongly shaped by occupational exposure and socioeconomic status, where large segments of the population are exposed to extreme heat through outdoor labor with limited access to cooling or healthcare, which is associated with higher heatwave-related mortality [48]. These differences highlight how similar temperature increases can lead to distinct public health outcomes depending on the social and environmental context and reinforce the need for culturally tailored public health strategies rather than a uniform regional approach.

4.6. Priorities for South Florida

Taken together, the findings of this study and the lessons drawn from India’s experience point toward a coherent set of priorities for South Florida. In the near term, strengthening heat surveillance, closing occupational protection gaps, expanding cooling access for vulnerable populations, and formalizing inter-agency heat response coordination may help reduce the hospitalization burden that is already visible in the data. Over the longer term, integrating heat risk into urban planning, housing policy, and climate adaptation frameworks is essential to building regional resilience against a warming trajectory that shows no sign of slowing. South Florida is not yet where India has been, but the findings presented here are consistent with the direction and calls for action well ahead of a heat-related burden hazard [49,50]. These findings also suggest increasing strain on healthcare systems, as some heat-related hospitalizations may be preventable with improved preventive and adaptation measures. These findings warrant further investigation of rising temperatures on potential economic burden at the population level, particularly in high-risk regions such as South Florida. Future work should quantify these costs and evaluate the cost-effectiveness of preventive strategies, including heat action plans and early warning systems.

4.7. Limitations

Several limitations should be considered when interpreting these findings. First, this study used a retrospective ecological design, meaning that associations are observed at the population level and cannot be attributed to individual-level exposure or outcomes. It is not possible to infer that any specific person was hospitalized because of heat exposure; rather, the findings describe aggregate trends across counties and years. Second, the analysis relied on aggregated annual data, which smooths out within-season variation and likely understates/underestimates the true health effects of discrete extreme heat events or short-duration heat waves. A finer temporal resolution such as monthly or event-level data would allow more precise characterization of the exposure–outcome relationship. Third, the linear regression models used in this study did not adjust for several potential confounding factors, including relative humidity, population growth, changes in age distribution over time, socioeconomic conditions, healthcare access, and air conditioning availability. These factors can independently influence both heat exposure and hospitalization rates, meaning that part of the observed association may reflect these underlying conditions rather than temperature alone. In addition, this study did not incorporate the heat index, a measure that combines temperature and humidity to better capture perceived heat stress. Due to the lack of consistently available daily humidity data at comparable resolution across both regions over the full study period, annual mean temperature was used instead as a more accessible, though less physiologically precise, proxy for cumulative heat exposure.
Fourth, data quality and comparability between India and South Florida present inherent challenges. Indian temperature and health data vary in coverage, collection methodology, and completeness across cities and time periods, making direct quantitative comparison with South Florida’s standardized county-level datasets difficult. This study uses India primarily as a qualitative/conceptual reference setting rather than a paired statistical comparator, which appropriately limits inferential claims across regions. Fifth, heat-related illness is widely recognized as substantially underreported in both settings. Hospitalizations capture only the most severe cases requiring clinical care; a larger burden of heat-related morbidity including emergency department visits, outpatient encounters, and unreported cases is not reflected in these data. Underreporting is likely more pronounced in India, where healthcare utilization for heat illness may be lower due to structural access barriers. As a result, the true magnitude of the heat-health burden in both regions is probably greater than what hospitalization data alone can demonstrate. These limitations do not negate the study’s findings, but they underscore the need for more granular, individually linked, and confounder-adjusted analyses in future research.

5. Conclusions

This study examined whether rising temperatures in South Florida are associated with measurable increases in heat-related hospitalizations and contextualized that relationship against the experience of India, a region with a longer and more severe history of heat-related illness. The findings indicate a clear and consistent positive association. Linear regression models for all three South Florida counties returned statistically significant positive associations between summer mean temperature and age-adjusted hospitalization rates, with model fit ranging from R2 = 0.356 in Palm Beach County to R2 = 0.615 in Miami-Dade County. South Florida is also warming faster (+0.0265 °F/year) than the major Indian cities used as a reference benchmark (+0.0230 °F/year), meaning the observed warming has not plateaued within the study period but is instead on a trajectory of accelerating exposure. Taken together, these findings on heat exposure and hospitalization data are consistent with an emerging high-risk pattern, paralleling conditions associated with heat-related mortality in India [13].
These findings may inform strategies and implications for public health policy and climate adaptation planning. In the near term, South Florida needs to close specific gaps: strengthening enforcement of occupational heat protections, expanding access to cooling centers for low-income and elderly residents, and formalizing heat-specific coordination across county health departments and emergency management agencies. In the medium term, integrating heat risk into routine public health surveillance, such as using temperature and hospitalization data together to anticipate high-risk periods, would shift the regional response from reactive to proactive. India’s Ahmedabad Heat Action Plan offers a tested, scalable model: tiered warning systems, community outreach, and inter-agency response protocols have demonstrably reduced heat-related mortality in a resource-constrained setting [15]. South Florida, with more institutional capacity but a less developed heat response framework, is well-positioned to adapt and implement these lessons before the burden grows further. The central message of this study is not that South Florida is in crisis, but that the data indicate it is moving in that direction, and the time to act is now, while efforts remain less costly than response. Climate change will not pause while health systems deliberate; regions that build preparedness infrastructure ahead of peak demand will protect their populations far more effectively than those that wait for hospitalizations to become undeniable.

Author Contributions

L.A. led the conceptualization of the study and the literature review. N.S.D. led the data analysis, manuscript writing, project administration, methodology and overall revision and editing. S.R. contributed to the Introduction and Discussion sections. L.A., N.S.D. and S.R. share first authorship. B.B., as the second author, contributed to the critical review of the manuscript and provided substantive feedback. J.D. served as the senior author, providing overall mentorship, scientific guidance, and oversight throughout the development of the manuscript. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not Applicable.

Informed Consent Statement

Not Applicable.

Data Availability Statement

Data were obtained from publicly available sources, including the Florida Department of Health and IMD Mausam—India Meteorological Department.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. World Health Organization; World Meteorological Organization. Heatwaves and Health: Guidance on Warning-System Development; World Health Organization: Geneva, Switzerland, 2015; Available online: https://www.who.int/publications/m/item/heatwaves-and-health--guidance-on-warning-system-development (accessed on 6 August 2026).
  2. Lindsey, R.; Dahlman, L. Climate Change: Global Temperature; National Oceanic and Atmospheric Administration: Washington, DC, USA, 2024. Available online: https://www.climate.gov/news-features/understanding-climate/climate-change-global-temperature (accessed on 6 August 2026).
  3. Gasparrini, A.; Guo, Y.; Hashizume, M.; Lavigne, E.; Zanobetti, A.; Schwartz, J.; Tobias, A.; Tong, S.; Rocklöv, J.; Forsberg, B.; et al. Mortality risk attributable to high and low ambient temperature: A multicountry observational study. Lancet 2015, 386, 369–375. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Matsee, W.; Charoensakulchai, S.; Khatib, A.N. Heat-related illnesses are an increasing threat for travellers to hot climate destinations. J. Travel Med. 2023, 30, taad072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Harduar Morano, L.; Watkins, S.; Kintziger, K. A comprehensive evaluation of the burden of heat-related illness and death within the Florida population. Int. J. Environ. Res. Public Health 2016, 13, 551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. O’Neill, M.S.; Carter, R.; Kish, J.K.; Gronlund, C.J.; White-Newsome, J.L.; Manarolla, X.; Zanobetti, A.; Schwartz, J.D. Preventing heat-related morbidity and mortality: New approaches in a changing climate. Maturitas 2009, 64, 98–103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Baldwin, J.W.; Benmarhnia, T.; Ebi, K.L.; Jay, O.; Lutsko, N.J.; Vanos, J.K. Humidity’s role in heat-related health outcomes: A heated debate. Environ. Health Perspect. 2023, 131, 55001. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Tong, S.; Prior, J.; McGregor, G.; Shi, X.; Kinney, P. Urban heat: An increasing threat to global health. BMJ 2021, 375, n2467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Kenny, G.P.; Yardley, J.; Brown, C.; Sigal, R.J.; Jay, O. Heat stress in older individuals and patients with common chronic diseases. Can. Med. Assoc. J. 2010, 182, 1053–1060. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Khatana, S.A.M.; Bhatla, A.; Nathan, A.S.; Giri, J.; Shen, C.; Kazi, D.S.; Yeh, R.W.; Groeneveld, P.W. Association of extreme heat and cardiovascular mortality in the United States: A county-level longitudinal analysis. Circulation 2022, 146, 249–261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Chandra N, S.V.S.; Lee, J.K.W. A systematic review of heat health warning systems: Enhancing the framework towards effective health outcomes. Curr. Environ. Health Rep. 2025, 12, 31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Swain, S.; Bhattacharya, S.; Dutta, A.; Pati, S.; Nanda, L. Vulnerability and adaptation to extreme heat in Odisha, India: A community-based comparative study. Int. J. Environ. Res. Public Health 2019, 16, 5065. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. de Bont, J.; Nori-Sarma, A.; Stafoggia, M.; Banerjee, T.; Ingole, V.; Jaganathan, S.; Mandal, S.; Rajiva, A.; Krishna, B.; Kloog, I.; et al. Impact of heatwaves on all-cause mortality in India: A comprehensive multi-city study. Environ. Int. 2024, 184, 108461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Yadav, V.K.; Bijalwan, V.; Solanki, P.K.; Sinha, A.P. Heat-related illness—Clinical profile and predictors of outcome from a healthcare center in South India. J. Fam. Med. Prim. Care 2020, 9, 4210–4215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Hess, J.J.; Sathish, L.M.; Knowlton, K.; Saha, S.; Dutta, P.; Ganguly, P.; Tiwari, A.; Jaiswal, A.; Sheffield, P.; Sarkar, J.; et al. Building resilience to climate change: Pilot evaluation of the impact of India’s first heat action plan on all-cause mortality. J. Environ. Public Health 2018, 2018, 7973519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. India Health Fund. Adapting India’s Health System to Extreme Heat: A Policy Agenda for Clinical, Infrastructural and Financial Preparedness; India Health Fund: Mumbai, India, 2024; Available online: https://www.indiahealthfund.org/adapting-indias-health-system-to-extreme-heat-a-policy-agenda-for-clinical-infrastructural-and-financial-preparedness/ (accessed on 6 August 2026).
  17. Jung, J.; Uejio, C.K.; Kintziger, K.W.; Duclos, C.; Reid, K.; Jordan, M.; Spector, J.T. Heat illness data strengthens vulnerability maps. BMC Public Health 2021, 21, 2015. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Stone, B.; Hess, J.J.; Frumkin, H. Urban form and extreme heat events: Are sprawling cities more vulnerable to climate change than compact cities? Environ. Health Perspect. 2010, 118, 1425–1428. Available online: https://pubmed.ncbi.nlm.nih.gov/21114000/ (accessed on 6 August 2026). [CrossRef] [Scilit] [PubMed]
  19. Intergovernmental Panel on Climate Change. Climate Change 2021: The Physical Science Basis; Cambridge University Press: Cambridge, UK, 2021; Available online: https://www.ipcc.ch/report/ar6/wg1/ (accessed on 6 August 2026).
  20. Ravindra, K.; Bhardwaj, S.; Ram, C.; Goyal, A.; Singh, V.; Venkataraman, C.; Bhan, S.C.; Sokhi, R.S.; Mor, S. Temperature projections and heatwave attribution scenarios over India: A systematic review. Heliyon 2024, 10, e26431. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Miami-Dade County Office of Resilience. Extreme Heat; Miami-Dade County: Miami, FL, USA, 2023. Available online: https://www.miamidade.gov/global/environment/heat/home.page (accessed on 6 August 2026).
  22. Nadarajan, G.D.; Rao, G.R.; Reddy, K.; Gimkala, A.; Janumpally, R.; Ang, Y.; Woo, C.T.Z.; Neo, T.H.; Wong, X.Y.; Ong, M.E.H. Characteristics of prehospital heat illness cases during the annual heat wave period in Telangana, India. Prehospital Disaster Med. 2021, 36, 385–392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Deoras, A.; Turner, A.G.; Lekshmi, S.; Birch, C.E.; Volonté, A.; Menon, A.; Schiemann, R.K.H.; Wilcox, L.J. Anatomy of moist heatwaves in India during the summer monsoon season. Clim. Dyn. 2026, 64, 103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Rudner, N.; Elon, L.; Xiuhtecutli, N.; Ruiz, E.; Chicas, R. Heat exposure, rest breaks, dehydration, and heat-related illness among agricultural workers in Florida summer heat. J. Health Care Poor Underserved 2025, 36, 590–604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. OpenCity Data. Daily Temperature: 70 Years Data for Major Indian Cities. Available online: https://data.opencity.in/dataset/daily-temperature-70-years-data-for-major-indian-cities (accessed on 6 August 2026).
  26. Florida Climate Center. Downloadable Data; Florida State University: Tallahassee, FL, USA; Available online: https://climatecenter.fsu.edu/climate-data-access-tools/downloadable-data (accessed on 6 August 2026).
  27. Florida Department of Health. Florida Health Tracking: Heat Stress Indicators. Available online: https://www.floridatracking.com/healthtracking/topic.htm?i=13 (accessed on 6 August 2026).
  28. Morgenstern, H. Ecologic studies in epidemiology: Concepts, principles, and methods. Annu. Rev. Public Health 1995, 16, 61–81. [Google Scholar] [CrossRef] [PubMed]
  29. Susser, M. The logic in ecological: I. The logic of analysis. Am. J. Public Health 1994, 84, 825–829. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Singh-Dias, N. South Florida Heat Risk and Lessons from India’s Heat Response: Analysis Code. GitHub: San Francisco, CA, USA, 6 August 2026. Available online: https://github.com/professor-dias/heat_risk_southflorida (accessed on 6 August 2026).
  31. Cloutier-Bisbee, S.R.; Raghavendra, A.; Milrad, S.M. Heat waves in Florida: Climatology, trends, and related precipitation events. J. Appl. Meteorol. Climatol. 2019, 58, 447–466. [Google Scholar] [CrossRef] [Scilit]
  32. Ahn, Y.; Uejio, C.K.; Wong, S.; Powell, E.; Holmes, T. Spatial disparities in air conditioning ownership in Florida, United States. J. Maps 2023, 19, 2253262. [Google Scholar] [CrossRef] [Scilit]
  33. Hutton, G.M. Geography of Erasure: Manufactured Housing, Heat Exposure, and State Neglect in Florida. Undergraduate Thesis, Pomona College, Claremont, CA, USA, 2026. Available online: https://scholarship.claremont.edu/pomona_theses/366/ (accessed on 6 August 2026).
  34. Marudo, C.P.; Mohan, V.; Paidas, M.J.; Toledo, P.; Fu, E.S.; Santos, H.P.; Shepherd, J.M.; McHugh, E.G.; Fletcher, M.M.; Shultz, J.M. Expert review: Confronting climate-driven heat risks to maternal and fetal health. Obstet. Gynecol. Surv. 2025, 80, 174–185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Turek-Hankins, L.L.; Cruz, M.; Brown, N.; Muse, N.; Clement, A.; Mach, K.J. Interactions between indoor heat and energy affordability amplify household risks in hot-humid U.S. climate zones. One Earth 2025, 8, 101235. [Google Scholar] [CrossRef] [Scilit]
  36. Centers for Disease Control and Prevention. Extreme Heat and Your Health. 2024. Available online: https://www.cdc.gov/extreme-heat/about/index.html (accessed on 6 August 2026).
  37. Centers for Disease Control and Prevention. Regional Health Effects—Southeast. 2024. Available online: https://www.cdc.gov/climate-health/php/regions/southeast.html (accessed on 6 August 2026).
  38. Centers for Disease Control and Prevention. Environmental Public Health Tracking Network: Heat Stress Indicators. Available online: https://ephtracking.cdc.gov (accessed on 6 August 2026).
  39. National Oceanic and Atmospheric Administration. Miami–South Florida. 2025. Available online: https://www.weather.gov/media/mfl/news/TempWildfireWeb_2025.pdf (accessed on 6 August 2026).
  40. O’Connor, F.K.; Oberai, M.; Xu, Z.; Binnewies, S.; Rutherford, S.; Meade, R.D.; Baker, S.; Jackman, E.; Forbes, C.; Bach, A.J.E. Promoting targeted heat early warning systems for at-risk populations. Nat. Clim. Change 2025, 15, 806–808. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Cruz, M.; Mach, K.J.; Turek-Hankins, L.L.; Ashad-Bishop, K.C.; Bailey, Z.D.; Evans, S.D.; Fanning, A.; Fernandez-Burgos, M.; Gilbert, J.; Howard, B.; et al. Where heat does not come in waves: A framework for understanding and managing chronic heat. Environ. Res. Clim. 2025, 4, 023002. [Google Scholar] [CrossRef] [Scilit]
  42. Eyni, A.; Zaitchik, B.F.; Hobbs, B.F.; Hadjimichael, A.; Shi, R. Distributional outcomes of urban heat island reduction pathways under climate extremes. Sci. Rep. 2025, 15, 9594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Bedi, N.S.; Adams, Q.H.; Hess, J.J.; Wellenius, G.A. The role of cooling centers in protecting vulnerable individuals from extreme heat. Epidemiology 2022, 33, 611–615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Cresswell, K.; Mitsova, D.; Liu, W.; Fadiman, M.; Hindle, T. Gauging heat vulnerability in Southeast Florida: A multimodal approach integrating physical exposure, sensitivity, and adaptive capacity. ISPRS Int. J. Geo-Inf. 2023, 12, 242. [Google Scholar] [CrossRef] [Scilit]
  45. Vicedo-Cabrera, A.M.; Sera, F.; Gasparrini, A. Hands-on tutorial on a modeling framework for projections of climate change impacts on health. Epidemiology 2021, 32, 321–329. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Guardaro, M. Strengthening heat action plans in the United States. Am. J. Public Health 2023, 113, 465–467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Miami-Dade County. Climate and Heat Health Task Force; Miami-Dade County: Miami, FL, USA, 2022. Available online: https://www.miamidade.gov/global/government/taskforce/climate-heat-health-task-force.page (accessed on 6 August 2026).
  48. Srinivasan, K.; Maruthy, K.; Venugopal, V.; Ramaswamy, P. Research in occupational heat stress in India: Challenges and opportunities. Indian J. Occup. Environ. Med. 2016, 20, 73–78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Anderson, G.B.; Bell, M.L. Heat waves in the United States: Mortality risk during heat waves and effect modification by heat wave characteristics in 43 U.S. communities. Environ. Health Perspect. 2011, 119, 210–218. Available online: https://pmc.ncbi.nlm.nih.gov/articles/PMC3040608/ (accessed on 6 August 2026). [CrossRef] [Scilit] [PubMed]
  50. Azhar, G.S.; Mavalankar, D.; Nori-Sarma, A.; Rajiva, A.; Dutta, P.; Jaiswal, A.; Sheffield, P.; Knowlton, K.; Hess, J.J. Heat-related mortality in India: Excess all-cause mortality associated with the 2010 Ahmedabad heat wave. PLoS ONE 2014, 9, e91831. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. (A) Station-Level Annual Mean Temperature Trends Across South Florida. (B) Station-Level Annual Mean Temperature Trends across Major Cities In India. (C) Cross-Continental Temperature Trends: South Florida and India. ** The sharp increase at the end of the Indian temperature series should be interpreted cautiously because the 2024 observations represent only a partial calendar year, primarily covering the warmer months from January or February through June, rather than a complete annual temperature record. (D) Comparison of Location-Specific Warming Rates in South Florida and India.
Ijerph 23 01135 g001aIjerph 23 01135 g001b
Figure 2. Temporal trends in annual mean temperature and heat-related hospitalization rates in South Florida (2005–2023).
Ijerph 23 01135 g002
Figure 3. Association between temperature and age-adjusted heat-related hospitalization rates.
Ijerph 23 01135 g003
Figure 4. Schematic Flow Chart of Heat Action Plan (HAP) Framework Components. Adapted from Ref. [15].
Ijerph 23 01135 g004
Table 1. Merged Temperature Dataset.
LocationLocationsYear Range
South Florida, USA71912–2025
India51951–2024 *
* 2024 Indian observations represent only a partial calendar year.
Table 2. South Florida and India Station Temperatures.
LocationNo. of YearsYear RangeMean Temp (F°)SD Temp (F°)Min Temp (F°)Max Temp (F°)
South Florida
Everglades911924–201774.57°1.57°69.01°78.11°
Fort Lauderdale1121912–202575.64°1.03°72.75°78.09°
Hialeah861940–202575.94°1.69°71.20°80.24°
Key West751948–202578.19°1.05°75.96°80.84°
Miami711927–202276.26°2.19°63.60°80.72°
Miami Airport781948–202576.72°1.29°74.29°79.86°
West Palm Beach881938–202575.52°1.27°72.30°78.24°
India
Bengaluru741951–2024 *76.62°0.77°75.16°80.46°
Chennai741951–2024 *83.90°0.75°82.46°85.50°
Delhi741951–2024 *77.03°1.15°74.94°84.46°
Kolkata741951–2024 *80.09°1.01°78.10°86.39°
Mumbai741951–2024 *79.61°1.11°77.99°85.25°
* 2024 Indian observations represent only a partial calendar year.
Table 3. South Florida vs. India Comparison.
LocationNo. of LocationsRegional Mean Temp (F°)Warming Rate F° per YearCross Location SD (F°) *
South Florida, USA775.83°0.02533°1.292°
India579.45°0.02297°2.666°
* Cross location (SD) is Pooled SD of location deviations from the corresponding annual regional mean.
Table 4. Heat-Related Hospitalizations By County (2005–2023).
MetricBrowardMiami-DadePalm BeachRegional Total
Total Hospitalizations (2005–2023)9248748552653
Mean Annual Hospitalizations48.64645139.6
Annual Hospitalizations (SD)17.318.217.650.5
Range Hospitalizations22–8422–9022–77
Mean Age Adjusted Rate2.671.783.1
Age Adjusted Rate (SD)0.830.621.1
Range Age Adjusted Rate1.25–4.260.92–3.241.60–5.33
Table 5. Temperature-Hospitalization Regression Sample (2005–2023).
AnalysisNMean Temp (F°)SD Temperature (F°)Mean Age-Adjusted RateSD Age Adjusted Rate
Overall (All Counties)5783.63°0.6°2.521.02
Broward1983.63°0.61°2.670.83
Miami-Dade1983.63°0.61°1.780.62
Palm Beach1983.63°0.61°3.11.1
Table 6. Correlation analyses.
AnalysisNPearson rp-ValueSpearman ρp-Value
Overall—all counties570.568<0.0001 *0.604<0.0001 *
Broward County190.7570.0002 *0.802<0.0001 *
Miami-Dade County190.784<0.0001 *0.7350.0003 *
Palm Beach County190.5970.0070 *0.6910.0010 *
Note. Pearson correlations describe linear associations, whereas Spearman correlations describe monotonic associations and are less sensitive to extreme observations. The analyses are exploratory and ecological; they should not be interpreted as causal or predictive. * p-value < 0.05.
Table 7. Linear regression analyses.
Analysisb, Cases per 100,000 per 1 °FSE95% CIInterceptR2
Overall—all counties0.9690.1890.590–1.349−78.550.323
Broward County1.0300.2160.576–1.485−83.490.573
Miami-Dade County0.7990.1530.475–1.122−65.020.615
Palm Beach County1.0790.3520.336–1.821−87.120.356
Note. The outcome was the annual age-adjusted heat-related hospitalization rate per 100,000 population. The regression coefficient (b) represents the estimated difference in the hospitalization rate associated with a 1 °F difference in summer mean temperature. CI, confidence interval; SE, standard error. The analyses are exploratory and ecological; they should not be interpreted as causal or predictive.
Table 8. Regression assumption checks.
AnalysisShapiro–Wilk Wp-ValueBreusch–Pagan p-Value
Overall—all counties0.9560.0368 *0.2513
Broward County0.9210.11820.9645
Miami-Dade County0.9640.65450.0567
Palm Beach County0.9580.53000.2558
Note. The overall model did not satisfy the Shapiro–Wilk normality test at the 0.05 level, although the Breusch–Pagan tests did not identify statistically significant heteroscedasticity in any model, so the combined-model estimates should be interpreted with added caution. * p-value < 0.05.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.