Review

From Exposure to Intervention: A Scoping Review and Evidence Mapping of Nature-Based Approaches for Postpartum Depression


1
Department of Social Work, Academy of Wellness and Human Development, Hong Kong Baptist University, Hong Kong 999077, China
2
Department of Clinical Medicine, School of Medicine, Nankai University, 94 Weijin Road, Nankai District, Tianjin 300071, China
3
Department of Geography, Academy of Geography, Sociology and International Studies, Hong Kong Baptist University, Hong Kong 999077, China
4
Smart Society Lab, Hong Kong Baptist University, Hong Kong 999077, China
*
Author to whom correspondence should be addressed.
Int. J. Environ. Res. Public Health 2026, 23(9), 1134; https://doi.org/10.3390/ijerph23091134
Submission received: 25 April 2026 / Revised: 14 July 2026 / Accepted: 15 July 2026 / Published: 31 August 2026

Highlights

Public health relevance—How does this work relate to a public health issue?
  • Postpartum depression (PPD) affects around 15–20% of women globally; however, substantial accessibility challenges confront current non-pharmacological interventions, including high costs and a shortage of qualified therapists.
  • Observational evidence consistently suggests associations between nature exposure (e.g., green space, tree canopy) and improved perinatal mental health, but direct intervention evidence for women with PPD remains critically limited.
Public health significance—Why is this work of significance to public health?
  • This scoping review and evidence mapping identify a major evidence gap. Despite promising observational data linking green space exposure to reduced PPD risk, no randomized controlled trial has evaluated a structured nature-based approach specifically for women with PPD.
  • The findings demonstrate that observational associations cannot substitute for clinical trial evidence, underscoring the urgent need to translate environmental health findings into actionable interventions for this vulnerable population.
Public health implications—What are the key implications or messages for practitioners, policy makers and/or researchers in public health?
  • Researchers should prioritize the development and evaluation of standardized, theoretically informed nature-based protocols specifically tailored for women with PPD, moving beyond passive environmental exposure studies.
  • Practitioners and policymakers should recognize that enhancing access to green spaces constitutes a low-risk health promotion strategy; however, robust evidence validating nature-based approaches as a clinical treatment for PPD is currently lacking, necessitating rigorous trials before clinical recommendations can be made.

Abstract

Background: Postpartum depression (PPD) affects about 15–20% of women worldwide. While observational studies have increasingly linked nature exposure to improved perinatal mental health, the extent to which nature-based approaches constitute a viable non-pharmacological intervention for PPD remains unclear. This scoping review and evidence mapping aimed to systematically characterize the current evidence base for nature-based approaches in PPD and perinatal populations. Methods: We searched PubMed, Web of Science, PsycINFO, Embase, Cochrane Library, Medline, CNKI, and WanFang Data from inception to December 2025. Two independent reviewers screened titles/abstracts and full texts against predefined inclusion criteria, with disagreements resolved through discussion. Empirical studies investigating any nature-based approach (NBA) (e.g., nature exposure, green space, forest therapy) in pregnant or postpartum women were incorporated. The review followed the PRISMA extension for Scoping Reviews (PRISMA-ScR) guidelines. No formal risk-of-bias assessment was conducted, consistent with scoping review methodology. The narrative synthesis and evidence mapping methodology were used to classify findings by population type and research design. Results: Of 1245 screened records, 11 studies fulfilled the inclusion criteria. To address the specific question of nature-based approaches for PPD, we classified evidence by its directness: studies on women with clinically significant PPD symptoms were treated as direct evidence; studies on general perinatal populations were treated as indirect evidence. Evidence mapping uncovered a significant deficiency: there are no randomized controlled trials (RCTs) that have specifically assessed NBA for women with PPD. Direct evidence was confined to two qualitative studies elucidating favorable experiences of nature engagement among postpartum women facing mental health challenges. Indirect evidence from observational studies (n = 10) generally supported associations between exposure to residential green space—especially tree canopy cover—and reduced risk of PPD and psychological distress, although some studies reported null findings. Physical activity was identified as a partial mediator in several studies. Only one pilot RCT focused on general postpartum women, indicating feasibility but not achieving significant depression reduction. Conclusions: Although encouraging observational data suggest a correlation between nature exposure and improved perinatal mental health, robust RCT evidence for structured Nature-Based Interventions in postpartum depression populations is lacking. Subsequent research must formulate and evaluate standardized, theoretically informed NBA protocols specifically tailored for women experiencing PPD.

1. Introduction

Postpartum depression (PPD) is a major depressive episode that occurs after childbirth, lasting at least two weeks and impairing daily functioning. It is more severe and persistent than the transient “baby blues.” Clinically, PPD is a non-psychotic depressive episode beginning in or extending into the postpartum period, usually within the first weeks to months after delivery, with symptoms like depressed mood, loss of interest, low energy, sleep disturbance, anxiety, and sometimes suicidal thoughts [1]. It uses the same symptom criteria as major depressive disorder, with a “postpartum” (or “peripartum”) specifier indicating timing around childbirth [2]. Many definitions in research and practice allow onset at any time within the first 12 months after birth, reflecting that risk remains high across the first postpartum year [3]. The length of postpartum depression, on the other hand, is different for each person. Systematic reviews and large-scale cohort studies show that postpartum depression can last up to two or even three years postpartum [4,5]. For this review, we adopted a broad and inclusive operational definition. We defined PPD as depressive symptoms occurring within the first 12 months postpartum, measured by validated screening instruments (e.g., Edinburgh Postnatal Depression Scale (EPDS)) or clinical diagnosis. This 12-month window was chosen to align with the most commonly used definition in the existing literature and to maximize the inclusion of relevant studies. Numerous extensive systematic reviews and meta-analyses indicate that the worldwide prevalence of postpartum depression is roughly 15–20% [6,7]. Postpartum depression harms the mother herself and has a chain of adverse effects on the baby, family relationships, and the social system [8].
Existing interventions for postpartum depression include pharmacological and non-pharmacological treatments. The safety of medication use during lactation is a legitimate concern, as drugs may transfer into breast milk [9]. However, the available evidence indicates that many antidepressants—particularly certain selective serotonin reuptake inhibitors (SSRIs) such as sertraline and paroxetine—have favorable safety profiles during breastfeeding, with minimal infant exposure [10,11]. Nevertheless, factors such as complementary feeding and the infant’s health status require consideration [12], and the broader evidence base remains limited in certain areas, making informed decision-making challenging for some healthcare providers and mothers [13]. Importantly, untreated maternal depression itself carries substantial risks for both the mother and child, including impaired mother-infant bonding, adverse child developmental outcomes, and, in severe cases, maternal mortality [8]. Therefore, treatment decisions must carefully weigh the risks of medication exposure against the well-documented harms of untreated PPD [14]. This complex risk-benefit calculus underscores the importance of accessible, low-risk non-pharmacological alternatives, which we explore in this review. The primary non-pharmacological therapies presently available include Cognitive Behavioral Therapy (CBT) and Interpersonal Therapy (IPT) [15,16]. However, they all face accessibility challenges. Globally, there is a well-documented shortage of qualified mental health professionals, particularly in low- and middle-income countries where the treatment gap for mental disorders can exceed 80% [17]. It is also important to recognize that even when evidence-based treatments are available, uptake depends on women’s individual preferences. Research suggests that postpartum women have diverse and often strong preferences regarding treatment format, delivery modality, and content [18]. New mothers often prefer talking therapies or supportive interventions over pharmacologic treatment for postpartum depression [19]. Understanding and accommodating these preferences is critical for developing acceptable and effective interventions—a perspective that has been insufficiently emphasized in the NBA literature to date. Consequently, it is imperative to pursue more accessible and cost-effective intervention methods.
Beyond the perinatal context, NBAs have emerged as a promising non-pharmacological approach for depression and anxiety in general adult populations. The most extensively studied form of NBAs is forest therapy (Shinrin-yoku), which originated in Japan and typically involves structured, guided immersion in forest environments [20]. A recent systematic review and meta-analysis by Qin et al. (2026) [21], synthesizing 25 studies involving 1876 participants, found that forest therapy was associated with moderate-to-large reductions in psychological stress (SMD = −0.71), depressive symptoms (SMD = −0.68), and anxiety symptoms (SMD = −0.77). However, substantial heterogeneity (I2 > 74%) was noted across studies [21]. The most comprehensive evidence to date comes from Jessen et al. (2025) [22], who conducted the first systematic review and meta-analysis focusing exclusively on individuals diagnosed with anxiety, depression, or stress—excluding healthy student populations that had diluted effects in earlier reviews. Pooling data from 19 studies (eight RCTs and 11 cohort studies), they found that participation in nature-based health interventions (NBHI) led to a large reduction in depressive symptoms (standardized mean change = −0.87, 95% CI: −1.18 to −0.56) and a moderate improvement in overall mental health (SMC = 0.58, 95% CI: 0.39 to 0.77) [22]. Importantly, among the eight included RCTs, only half reported superior effects of NBA compared to control conditions, underscoring the need for more rigorous trial designs [22]. Beyond forest therapy specifically, broader categories of NBA—including therapeutic horticulture, green exercise (e.g., nature walking), and blue space activities (e.g., coastal or riverine walks)—have demonstrated similar promising effects [23]. It is important to distinguish between two conceptually distinct categories of nature-based approaches that recur throughout this review: active interventions and passive exposure. Active interventions involve structured, intentional engagement with nature, typically delivered in group or individual formats with specific therapeutic goals. Examples include Shinrin-yoku, therapeutic horticulture (structured gardening activities with a therapist or facilitator), green exercise (nature-based physical activity such as guided walking groups), and blue space activities (e.g., coastal or riverine walks). These approaches share a common feature of prescribing or facilitating a specific activity in nature, often with a defined dose, frequency, and facilitator. Passive exposure refers to residential or neighborhood proximity to natural environments, measured objectively (e.g., Normalized Difference Vegetation Index (NDVI), tree canopy cover, percentage of green space within buffers) or subjectively (e.g., self-reported green space quality). These studies typically examine statistical associations between environmental characteristics and mental health outcomes, without any prescribed behavioral change. This distinction is critical: passive exposure studies suggest correlational relationships, whereas active intervention studies can, in principle, establish causal efficacy. Throughout this review, we maintain this distinction and classify evidence accordingly. Collectively, these findings from general and clinical populations provide a compelling theoretical rationale for extending NBA research into the perinatal period. Nevertheless, pregnant and postpartum women face unique physiological (e.g., hormonal fluctuations, physical limitations) [24], psychological (e.g., sleep deprivation [25], altered self-concept [26]), and logistical (e.g., childcare needs, time constraints) barriers [27] that may modify both the feasibility and efficacy of NBA, necessitating population-specific investigation.
To avoid conceptual ambiguity, we explicitly delineate the scope of this review along three dimensions: target population, exposure vs. intervention, and outcome focus. As regards target population, this review focuses primarily on postpartum women, with particular attention to those experiencing or at risk of PPD. Where evidence was lacking for this specific subgroup—which proved to be the case—we expanded the inclusion to the general perinatal population (including pregnant women and general postpartum samples) as indirect evidence, while clearly distinguishing this from direct evidence. We adopted a broad operational definition of nature-based approaches encompassing both passive environmental exposure (e.g., residential green space, tree canopy) and active, structured interventions (e.g., forest therapy, guided nature walks). However, a central analytical distinction is maintained throughout: observational exposure studies are treated as indirect evidence, whereas interventional studies (RCTs, quasi-experiments) are treated as direct evidence of treatment efficacy. The primary outcome of interest is postpartum depressive symptoms, measured by validated scales (e.g., EPDS, CES-D, PHQ-9). Secondary mental health outcomes (anxiety, perceived stress, psychological distress) are included where reported, but PPD remains the anchoring clinical endpoint.
Nevertheless, a preliminary examination of the literature found no randomized controlled trial evaluating the efficacy of a structured nature-based intervention specifically for women with PPD. This evidence gap hampers clinical recommendations and practice. However, to characterize the full landscape of available evidence—including observational associations, qualitative insights, and pilot intervention studies—a scoping review is more appropriate than a systematic review for the following reasons. (a) The evidence base is heterogeneous in design (including RCTs, cohort studies, qualitative studies, and mixed-methods designs), and scoping reviews are specifically suited for mapping evidence across diverse study types. (b) The literature is characterized by inconsistent terminology and exposure definitions, requiring a mapping exercise to clarify what has been studied under different labels. (c) A primary objective is to identify evidence gaps rather than to synthesize a homogeneous body of literature for effect estimation, which is the primary aim of a systematic review with meta-analysis.
Given these considerations, we conducted a scoping review and evidence mapping to systematically chart the current research landscape, categorize available evidence by its direct relevance to the PPD population, and identify priority areas for future research. The evidence mapping approach allowed us to visually display the concentration (‘hotspots’) and absence (‘blank areas’) of evidence across study populations and research designs, providing a clear roadmap for subsequent clinical trials.

2. Methods

2.1. Inclusion and Exclusion Criteria

Inclusion Criteria:
(1) Research type: any type of empirical research (RCT, quasi-experiment, cohort study, case study, or qualitative research); (2) Research content: studies that assessed the impact of any form of nature-based approach on postpartum health outcomes. We included studies measuring mental health outcomes (depression, anxiety, perceived stress, psychological distress) as primary or secondary endpoints. Studies that measured only physical health outcomes (e.g., BMI, weight, sleep quality) were included only if they reported on a postpartum population that was relevant to understanding the broader health context of perinatal women. However, we acknowledge that such studies do not provide direct evidence for PPD; (3) Research population: (a) PPD patients; (b) general pregnant women or postpartum women; (4) Only studies published in English or Chinese.
Exclusion Criteria:
(1) Non-experimental research (such as editorials, news reports); (2) Intervention measures in non-natural environments (such as indoor plants and VR natural landscapes); (3) Literature that cannot be fully accessed.

2.2. Search Strategy

We conducted searches in the following electronic databases from their inception to 14 December 2025: PubMed, Web of Science, PsycINFO, Embase, Cochrane Library, Medline, and the Chinese databases CNKI and WanFang Data. No restrictions were applied based on publication date.
The search strategy was built around two core concepts, grounded in the Population-Concept-Context (PCC) framework: the postpartum population and nature-based interventions. For each concept, a combination of free-text keywords (e.g., “postpartum”, “nature therapy”) and controlled vocabulary terms (e.g., MeSH: “depression, postpartum”, “forest therapy”) was used. Keywords were adapted for the syntax of each database. The full search strategy for PubMed is provided in Appendix A.

2.3. Study Selection and Data Extraction

The literature review was performed using web-based version of Rayyan.AI (https://www.rayyan.ai/) accessed on 14 December 2025 as a collaborative screening tool for initial screening and full-text assessment. During the initial screening phase, two independent researchers (HG and QW) reviewed titles and abstracts. Inter-rater agreement during the title/abstract screening was excellent (κ = 0.91, 95% CI: 0.82–1.00; percentage agreement = 99.37%). Disagreements were resolved through discussion, and when consensus could not be reached, a third reviewer (YG) was consulted. The same two reviewers conducted the full-text screening, with an agreement rate of 91.67% before consensus discussion. Subsequently, the full-text screening stage was conducted, during which the complete texts were reviewed, and any conflicts were resolved through discussion. We developed a standardized data extraction form that captured the following information: authors and year of publication, country, research design, sample characteristics (including population type and sample size), intervention details (such as forest type, duration, and frequency), details of the control group, primary outcome indicators and their measurement tools, as well as the main findings.

2.4. Data Synthesis and Evidence Mapping

Evidence mapping procedure: Following the narrative synthesis, we constructed a visual evidence map to systematically categorize the included studies by study population and research design. This approach was adapted from the evidence mapping methodology described by Miake-Lye et al. (2016) [28]. The classification framework was developed iteratively through the following steps:
(1)
Population classification: Studies were categorized into three population groups: (a) women with or at risk of PPD; (b) general postpartum women (unselected for PPD risk); (c) pregnant or mixed perinatal women. This categorization was designed to capture the directness of evidence to our primary research question.
(2)
Design classification: Studies were categorized into: (a) RCTs; (b) observational studies (cohort, cross-sectional, case–control); (c) qualitative studies (interviews, focus groups); (d) mixed-methods or intervention development studies.
(3)
Data extraction and mapping: Two reviewers independently extracted study characteristics using a standardized form (see Section 3.2). A matrix was then constructed with populations as rows and designs as columns. Each cell contains the number of studies in that intersection, allowing visual identification of evidence concentrations (‘hotspots’) and evidence gaps (‘blank areas’).
(4)
Reviewer responsibilities and conflict resolution: Both reviewers (HG and QW) independently classified each study according to the framework. Disagreements (occurring in <5% of classifications) were resolved through discussion with the senior author (YG). Final classifications were reached by consensus.
This evidence map provides a visual summary of the current evidence landscape and highlights priority areas for future research.

2.5. PRISMA-ScR and Protocol Registration

This scoping review was conducted in accordance with the PRISMA extension for Scoping Reviews (PRISMA-ScR) guidelines [29]. A detailed protocol was not pre-registered for this review. This decision was pragmatic: at the time of study initiation, our primary aim was an exploratory mapping of a rapidly emerging field with inconsistent terminology, and the scoping review methodology lacked an established registration platform comparable to PROSPERO for systematic reviews. Nevertheless, we acknowledge that protocol registration is a best practice for enhancing transparency and reducing the risk of selective outcome reporting. To mitigate this limitation, we have provided a comprehensive description of our methods, including the search strategy, inclusion criteria, and analysis framework, and we report all outcomes in accordance with PRISMA-ScR guidelines. (Supplementary Material File S1) Future updates of this review will consider Preregistration.

3. Results

To clearly distinguish between what is known about PPD specifically and what is inferred from broader perinatal populations, we applied the previously described directness classification framework and organized the findings into three levels of evidence, from most to least direct. Studies on women with clinically significant PPD symptoms were treated as direct evidence; studies on general perinatal populations were treated as indirect evidence.

3.1. Literature Retrieval and Screening Process

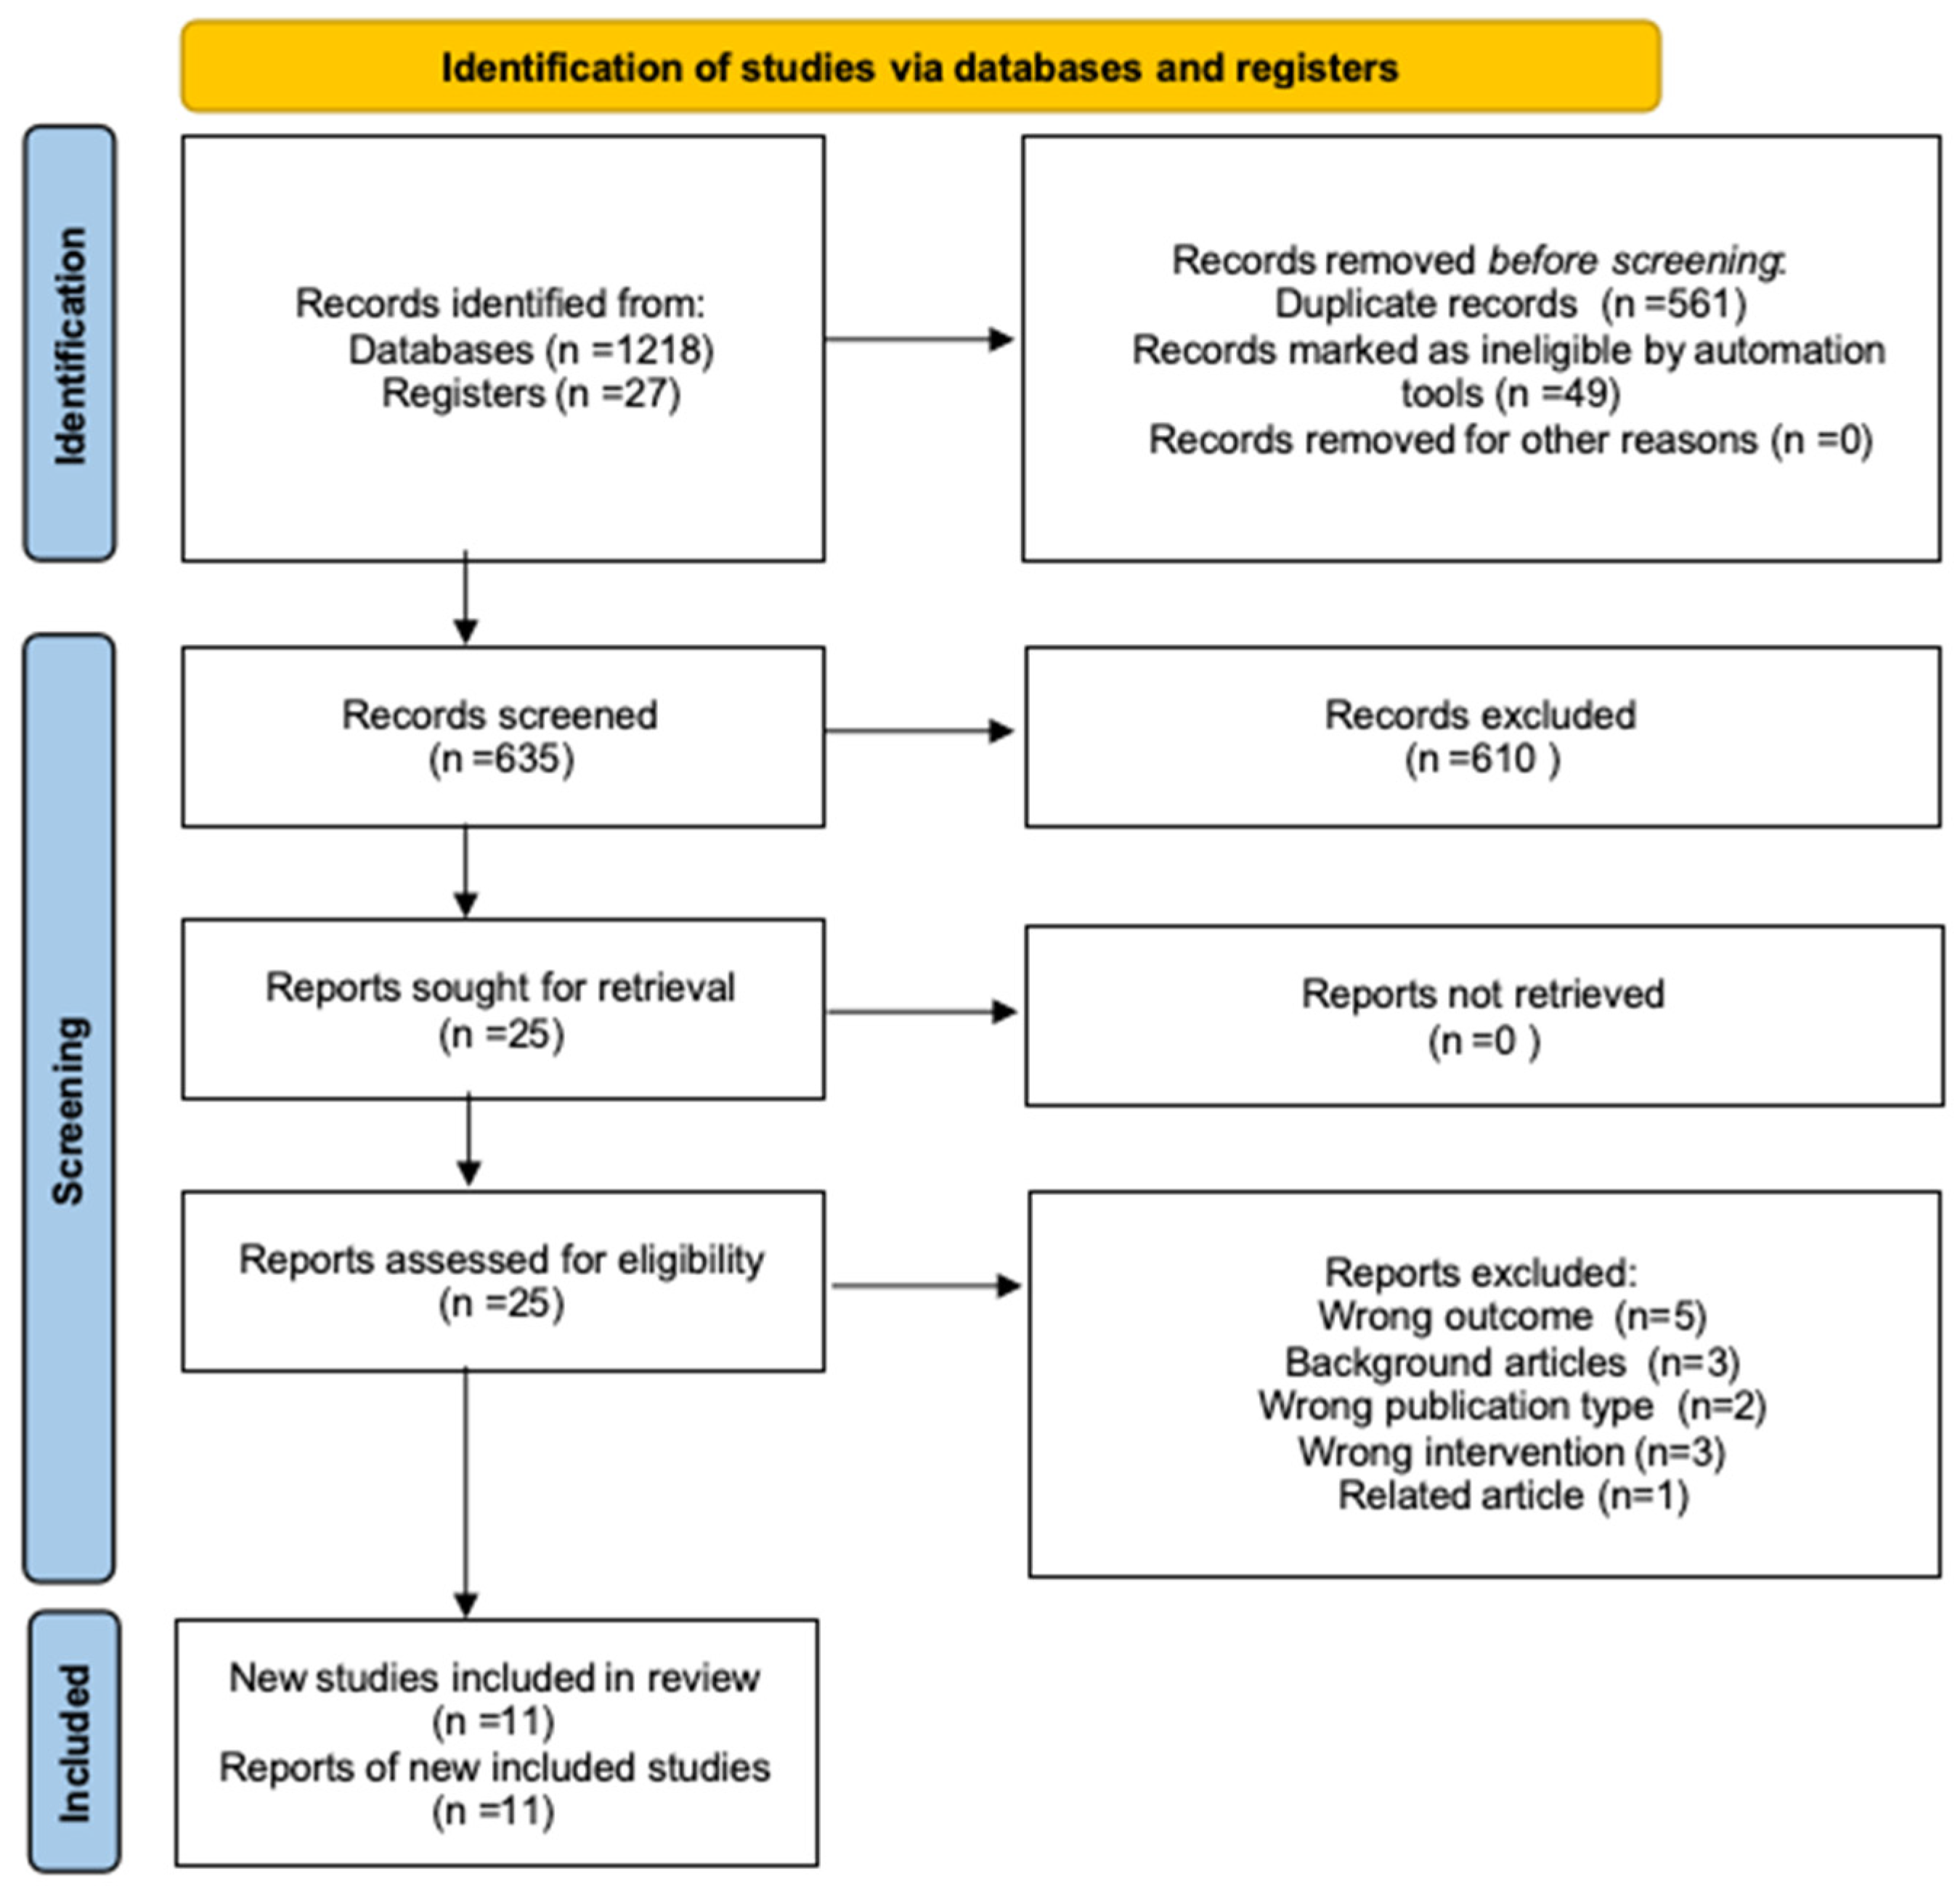
A total of 1245 documents were initially obtained. After removing duplicates, 635 documents remained. The initial screening was conducted by reading the titles and abstracts. After excluding documents that did not meet the inclusion criteria, 24 were selected for full-text screening. After reading the full texts, 11 documents were finally included for data extraction and analysis. Figure 1 shows the PRISMA flowchart of the screening process.

3.2. The Characteristics of the Included Literature

The detailed summaries of all included studies are provided in Table 1, Table 2 and Table 3.
As Table 1 shows, the 11 included studies, published between 2015 and 2025, represent a diverse body of research. Geographically, the studies were predominantly conducted in high-income Western countries, including the USA (four studies), and the UK (three studies), with additional studies from Canada, Australia, New Zealand and one from Ghana. Study designs varied. Eight studies were observational, including longitudinal and retrospective cohorts. The evidence base also includes one pilot randomized controlled trial (RCT), two qualitative studies, and one intervention development study. The study populations primarily consisted of women in the perinatal period, including pregnant women, general postpartum populations, and specific subgroups such as mothers with mental health difficulties or those from low-income urban areas. Sample sizes ranged from small-scale qualitative and pilot studies with 30 to 45 participants to large-scale cohort studies involving thousands, and in one case, over 400,000 individuals. As detailed in Table 2, most studies examined passive environmental exposure using objective measures (e.g., NDVI, satellite-derived tree canopy cover) or subjective self-reports of green space quality. At the same time, a smaller number investigated active interventions (e.g., a co-designed group nature program, a ‘Nature Coach’-led intervention). Table 3 summarizes the primary outcomes, effect sizes, and key findings across studies, with a strong focus on psychological health—including PPD, general depressive and anxiety symptoms, and perceived stress—alongside physical and behavioral outcomes.

3.3. Summary of Key Findings

(1)
Limited direct evidence
As shown in Table 4, we identified only two studies that directly focused on the relationship between postpartum women with or at risk of mental health problems and the natural environment, and both were qualitative studies. These studies described the positive experiences of postpartum women engaging with natural environments (e.g., parks and green spaces) in terms of emotional relaxation, stress relief, and social support, but did not provide quantitative causal evidence. For example, a focus group found that mothers could achieve psychological relaxation simply by coming into contact with local green spaces (e.g., a meadow), and emphasized the dual role of sensory experiences and social support. Currently, no randomized controlled trials have been conducted directly targeting this population to evaluate the clinical effectiveness of natural-based approaches.
(2)
Indirect evidence from the general postpartum women
Furthermore, Table 4 demonstrates that the general postpartum women group has the relatively richest observational evidence (three articles) among the population categories, and the only interventional evidence (one RCT). Observational evidence has reached a consistent conclusion: exposure to green spaces in residential areas (especially tree coverage based on street views) is associated with a lower risk of postpartum depression and psychological distress. The underlying mechanism has been repeatedly verified as a partial mediator of the effect of physical activity. Additionally, evidence suggests that green space quality (e.g., the perceived quality of parks) may be more important than its quantity alone. Interventional evidence: Only one pilot RCT has been conducted, indicating that behavioral interventions aimed at increasing access to nature are feasible and can effectively change behavior (e.g., increasing the number of visits). However, this study did not confirm a significant improvement in postpartum depression symptoms. This suggests that future interventions require stronger theoretical grounding, optimized dosages, and adequate statistical power to detect core mental health outcomes.
(3)
General indirect evidence from a mixed population of pregnant women and perinatal women
Table 4 also shows that two observational studies included both prenatal and postnatal participants. Their findings further support a positive association between the natural environment and perinatal mental health. For example, one longitudinal study found that the inverse association between greenness and depressive symptoms was strongest during pregnancy and persisted into the early postpartum period. Both studies provide evidence across the perinatal trajectory but still lack specific designs targeting women with PPD symptoms.

4. Discussion

This scoping review identifies a substantial and essential deficiency in the direct evidence supporting nature-based approaches as a treatment for PPD. The evidence landscape—as mapped by our directness classification framework—reveals a striking disjunction: indirect evidence from observational studies of general perinatal populations consistently suggests protective associations, yet direct evidence from RCTs targeting women with PPD is entirely absent, and even the single pilot RCT in general postpartum women failed to demonstrate symptom reduction. This gap between promising indirect signals and the absence of direct validation is the central finding of this review.

4.1. Synopsis of Evidence and Principal Deficiencies

The most significant conclusion is the total absence of RCTs assessing NBA specifically for women diagnosed with or at elevated risk for PPD. The direct evidence is limited to qualitative research, which, although useful for clarifying perceived therapeutic mechanisms—such as emotional relief, sensory involvement, and enhanced social interaction—fails to demonstrate clinical efficacy. The single identified RCT [33] focused on a general postpartum population and, while showing feasibility and enhanced nature involvement, failed to produce a significant decrease in depressed symptoms. This highlights a crucial challenge: the available evidence does not establish whether passive exposure to nature, as indicated by observational studies, is equivalent to a structured therapeutic intervention. It remains possible that the protective associations observed in cohort studies reflect non-causal confounding, dose-insufficient effects, or mechanisms that do not translate into clinically meaningful symptom reduction when delivered as a prescribed intervention. At minimum, our findings suggest that passive exposure and active intervention are conceptually distinct constructs that should not be treated as interchangeable in clinical reasoning, and this distinction must be tested through rigorous RCTs rather than assumed. The inadequacy of this pilot RCT underscores that merely promoting visits may constitute an insufficient “dose” without a more structured, theory-driven, and psychologically integrated procedure customized to the distinct requirements and obstacles encountered by women with PPD.
The persistent observational data, mainly from extensive cohort studies, establish a robust epidemiological basis for the advancement of additional interventions. The consistent evidence indicating that increased residential greenness, especially tree canopy [30,40], correlates with reduced risks of postpartum depression and psychological discomfort is persuasive. The mediating function of physical exercise [34] is a significant observation, indicating that NBA may function in part by encouraging beneficial health practices. Moreover, evidence suggests that the perceived quality of green space may matter more than mere quantity, highlighting the need for intervention design that prioritizes meaningful involvement over passive proximity.

4.2. Potential Mechanisms and Active Constituents of NBA for PPD

Although observational research consistently links green space exposure to improved prenatal mental health, the underlying mechanisms remain poorly understood. Identifying the “active ingredients” of NBA is crucial for developing targeted therapies and improving therapeutic dosages for women with PPD. Based on a recent conceptual review, which integrated putative pathways for postnatal NBA, various candidate processes across biological, psychological, and social domains merit examination [41].

4.2.1. Regulation of Circadian Rhythm via Light Exposure

A significant biological route encompasses light exposure and the regulation of circadian rhythms. The peripartum period is marked by substantial hormonal variations that can lead to circadian misalignment, resulting in mood and sleep disorders. Parry et al. (2023) established that pregnant women with depression display phase-advanced melatonin rhythms, whereas postpartum women with depression exhibit phase-delayed rhythms in relation to sleep scheduling [42]. In contrast, natural bright light exposure in outdoor environments, especially during morning hours, may enhance circadian phase alignment [43], providing a non-pharmacological method to rectify the circadian disturbances associated with the pathophysiology of PPD.

4.2.2. Restoration of Psychophysiological Stress

Two complementary psychological theories offer supplementary mechanistic frameworks. Attention Restoration Theory (ART) posits that natural environments invoke “soft fascination,” which is effortless, automatic attention that facilitates the recuperation of focused attention capacities [44]. Postpartum women often experience cognitive tiredness, concentration difficulties, and mental exhaustion—symptoms indicative of focused attention depletion [45]. They may experience natural environments that offer gentle stimulation (e.g., mottled light, whispering foliage, cascading water) as very rejuvenating. Simultaneously, Stress Reduction Theory (SRT) asserts that natural surroundings elicit positive emotional reactions and diminish psychophysiological stress through evolutionary predispositions to specific landscape characteristics (e.g., prospect-refuge combinations) [46]. Empirical research has evidenced diminished cortisol levels, reduced blood pressure, and decreased sympathetic nervous system activity after exposure to nature [47]. For postpartum women suffering from hyperarousal, anxiety, and stress-related symptoms, these restorative effects may directly address critical aspects of their clinical manifestation.

4.2.3. Physiological Pathways: Evidence from Observational and Experimental Studies

Physical exercise is the most consistently validated mediator in observational studies. Sun et al.’s (2023) extensive cohort study revealed that physical activity partially mediated the relationship between exposure to residential green space and a decreased risk of PPD [30]. The extent of mediation was limited, indicating that alternative pathways—such as those previously mentioned—function independently or in synergy. The NBA can enhance physical activity by creating visually appealing, secure, and accessible spaces for walking or other exercises, which subsequently yield antidepressant effects via neurobiological processes (e.g., endorphin release, elevation of brain-derived neurotrophic factor) [48].
Beyond observational evidence of physical activity as a mediator, experimental studies using virtual reality (VR) have provided direct evidence for the acute physiological effects of green space exposure. One VR experiment among pregnant women found that exposure to high-green environments significantly reduced systolic blood pressure (β = −4.57 mmHg, 95% CI: −8.51, −0.64) and salivary alpha-amylase (β = −1.22 ng/mL, 95% CI: −2.26, −0.18) following a laboratory stressor, and increased positive affect while reducing anxiety [33]. These findings demonstrate that even brief visual exposure to nature can elicit measurable physiological stress recovery—effects that may be particularly relevant for pregnant women who face mobility and childcare constraints that limit access to outdoor green spaces.
Together, observational and experimental evidence suggest that NBA influences PPD through multiple physiological pathways, including both behavioral (physical activity) and direct psychophysiological (stress recovery) mechanisms. However, the relative contribution of each pathway remains to be clarified in future research.

4.2.4. Social and Relational Pathways

Qualitative research on postpartum women has always emphasized social processes. Hall et al. (2023) indicated that group-oriented nature activities enhanced social support, diminished isolation, and offered a non-judgmental environment for mother-infant bonding [35]. These relational connections may be especially significant for postpartum women, who frequently encounter social withdrawal, loneliness, and diminished social support networks after childbirth [49,50]. Nature-based group therapies may diminish obstacles to social interaction relative to indoor therapeutic environments, alleviating stigma and anxiety linked to requesting assistance.

4.2.5. Overview of Mechanisms

Another possible mechanism—negative air ions (NAIs) in flowing water environments—has been suggested by controlled exposure trials [51,52], and coastal or riparian settings may offer a combination of NAIs, phytoncides, and multisensory stimuli [53,54]. However, this mechanism is speculative in the perinatal context and requires empirical investigation.
These mechanisms are not mutually exclusive and likely operate synergistically. Future RCTs should incorporate mediation analyses to clarify the relative contributions of different pathways, recognizing that the significance of each mechanism may vary by individual characteristics and environmental settings.

4.3. User Perspectives and Treatment Preferences

A notable gap in the nature-based approaches for PPD literature is the limited attention to women’s own perspectives, experiences, and preferences. Beyond biological and psychological mechanisms, therapeutic benefit may derive not only from direct exposure to nature but also from meaning-making, reflection, emotional processing, and patient preference. Both reviewed qualitative studies [31,35] suggest that postpartum women value nature for its sensory qualities, social opportunities, and non-judgmental environment—benefits that extend beyond symptom reduction to encompass emotional restoration and a sense of connection. However, these studies are small-scale and were conducted in a single cultural context (UK), leaving substantial uncertainty about the experiences of women from diverse backgrounds. Broader treatment preference research indicates that postpartum women have varied and often strong preferences regarding therapeutic format. Some prefer individual over group settings [55]; others prioritize flexibility (e.g., online or self-guided options) [56], cultural values, parity, socioeconomic status, and prior treatment experiences all shape these preferences. Women who decline or delay treatment may do so not because they do not need it, but because available options do not align with their preferences or circumstances. These findings have direct implications for the development of nature-based approaches. Rather than assuming a uniform approach, future interventions should involve women in co-design processes, offer flexible delivery formats (e.g., group vs. individual, guided vs. self-directed, in-person vs. online), and attend to the diverse meanings women attach to nature. Incorporating user preferences into intervention design is likely to enhance engagement, adherence, and ultimately effectiveness—making this a priority for the next generation of nature-based approaches research.

4.4. Methodological Considerations for Future RCTs: The Importance of Adequate Control Conditions

Future RCTs of NBA for PPD must carefully evaluate the criteria for an adequate control condition. Simple comparisons to waitlist controls or treatment-as-usual are insufficient because they fail to account for nonspecific factors such as participant expectancy, therapist attention, or the therapeutic alliance. Researchers should consider active control conditions, such as group walking in urban settings, seated relaxation indoors, or social support groups delivered in a comparable format to address this limitation. These conditions provide stronger control for these confounding factors. Rather than comparing NBA to non-NBA, a particularly rigorous approach includes removing or factorial designs that compare various doses or configurations of NBA (e.g., forest vs. urban walking, individual vs. group format, one-hour vs. three-hour sessions). These designs address the question of the optimal NBA configuration, rather than simply determining whether NBA is functional. It is also necessary to recognize the difficulty of blinding. In most NBA trials, participants cannot be blinded to their assignment, and even blinding outcome assessors is challenging when interventions are conducted in unique physical environments. The use of objective outcome measures (such as actigraphy and salivary cortisol) that are less vulnerable to expectancy effects, and the assessment of treatment credibility as a covariate in the primary analysis, are examples of practical improvement strategies in response to this. Reporting should adhere to the CONSORT guidelines for non-pharmacological interventions, which necessitate a comprehensive description of intervention components and a fidelity assessment.

4.5. Public Health Consequences of Implementing NBA for PPD

The potential benefit of establishing NBA as an evidence-based PPD remedy is significant from a public health standpoint. PPD impacts roughly 15–20% of the almost 140 million women who give birth each year globally [6,7]. Untreated PPD affects mothers, their infants, and the wider family environment [8]. Research shows harms across maternal physical and mental health [57], mother–infant bonding, child development [58], and—in severe cases—suicide and maternal mortality [59]. Furthermore, the financial strain is considerable. In 2017, the estimated financial burden of untreated perinatal mood and anxiety disorders, including postpartum depression, in the United States was US$14 billion, attributable to healthcare consumption, productivity losses, and intergenerational welfare costs [60]. Low- and middle-income nations disproportionately shoulder this cost owing to inadequate mental health infrastructure. Research consistently shows a mismatch between high need and weak infrastructure, workforce, and financing [61,62].
Therefore, there is an urgent need for accessible, low-stigma therapies that may be used in community settings. Present first-line interventions—CBT and IPT—encounter considerable accessibility obstacles, such as a deficiency of qualified therapists [17], elevated out-of-pocket expenses, prolonged appointment wait times, and the stigma linked to pursuing mental health treatment [63]. In terms of pharmacological interventions, many breastfeeding mothers discontinue or refrain from using antidepressants due to concerns about potential harm to their infants. Research indicates that while antidepressants do transfer into breast milk, average newborn exposure is small [64], and the consequences of untreated maternal depression can be significant [60]. Should further RCTs validate its efficacy, NBA may be incorporated into current maternal and child health frameworks at a comparatively minimal additional expense.
Potential delivery models encompass: (a) recommended nature excursions as an integral component of standard postpartum care (e.g., “nature prescriptions” provided by midwives or family practitioners); (b) community health clinics or home visiting programs provide group nature walking initiatives; (c) co-designed NBA groups established in local green areas, utilizing existing park infrastructure; (d) online-guided NBAs (e.g., audio-guided forest imagery or outdoor mindfulness) for women facing mobility or childcare limitations. These methods provide feasibility, a low per-participant cost, and diminished stigma relative to clinic-based mental health therapy. Furthermore, NBA may attract women who are hesitant to pursue conventional mental health services due to cultural norms, linguistic obstacles, or prior adverse encounters with healthcare institutions.
Beyond forest-based interventions and green space exposure, other forms of nature-based activities—including therapeutic horticulture, wilderness therapy, and blue care—have shown promise in general populations [65,66]. However, their application to postpartum depression remains almost entirely unexplored. Our review did not systematically target these specific modalities due to search-term constraints; however, their absence from the PPD literature further reinforces our overarching finding: structured, theory-driven, nature-based protocols for this population are urgently needed.

4.6. Limitations of This Scoping Review

Several constraints impacting our scoping review must be recognized. Although we performed an extensive search across eight databases, publication bias may be present, as research with null findings or negative relationships is less frequently published. Second, the variability in exposure metrics (e.g., NDVI, street-level greenery, and self-reported quality) and outcome measures among the studies considered hindered quantitative synthesis. Third, we did not formally assess the risk of bias or grade the certainty of evidence for included studies, consistent with scoping review methodology, which prioritizes mapping over quality appraisal [29]. However, readers should interpret observational findings with appropriate caution, as residual confounding is possible in all included cohort and cross-sectional studies. Fourth, the evidence base is predominantly drawn from high-income Western countries, with only one study from Ghana representing a low- or middle-income country. This restricts generalizability to other low- and middle-income contexts, particularly across the African continent, where the prevalence of PPD is greatest, and access patterns differ substantially. Fifth, our language restriction to English and Chinese publications may have introduced language bias, potentially excluding relevant studies published in other languages. Sixth, our search strategy was constructed around core nature-related terms and may not have fully captured studies using alternative nomenclature (e.g., therapeutic horticulture, gardening therapy), although any such studies would likely have included broader nature-related descriptors. Seventh, the search date of December 2025 means that studies published subsequently were excluded. Finally, this review was not prospectively registered, although we have provided comprehensive methods reporting to enhance transparency.

5. Conclusions

Although there is encouraging observational data connecting nature exposure to improved prenatal mental health, high-quality RCT evidence for organized NBAs in populations with PPD remains lacking. The current evidence base is limited to qualitative research and observational correlations, with a single pilot randomized controlled trial failing to show a substantial reduction in depression. This analysis highlights the pressing need for a new generation of research that connects epidemiological correlation with therapeutic application. Subsequent research should progress beyond evaluating general exposure to formulate and validate standardized, repeatable NBA techniques specifically tailored for PPD. These procedures must be theoretically anchored, incorporating the several possible processes previously mentioned—such as light exposure, negative air ions, stress alleviation, promotion of physical activity, and facilitation of social support—within a nature-based framework.
Researchers should emphasize robust RCT designs with sufficient control conditions, address blinding, pre-register methods, and report results in accordance with CONSORT standards for non-pharmacological therapies. Only through meticulously designed, methodologically rigorous clinical trials can the potential of NBA as a safe, accessible, and effective supplementary treatment for PPD be thoroughly assessed and actualized.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ijerph23091134/s1, File S1: Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) Checklist.

Author Contributions

Conceptualization, H.G. and Y.G.; methodology, H.G. and Q.W.; software, H.G. and Q.W.; validation, H.G., Q.W. and Y.G.; formal analysis, H.G.; investigation, H.G.; resources, Y.G.; data curation, H.G. and Q.W.; writing—original draft preparation, H.G.; writing—review and editing, H.G., Q.W. and Y.G.; visualization, H.G.; supervision, Y.G.; project administration, Y.G.; funding acquisition, Y.G. All authors have read and agreed to the published version of the manuscript.

Funding

The study is supported by The Initiation Grant for Faculty Niche Research Areas 2024/25—RC-FNRA-IG/24-25/FASS/05 (HKBU): “Gender difference in space-time mobility: a mixed method based on wearable technologies and media big data.”

Institutional Review Board Statement

This is a scoping review of published literature and did not involve direct contact with human participants. Therefore, ethical approval was not applicable. This study was conducted in accordance with the Declaration of Helsinki.

Informed Consent Statement

This is a scoping review of published literature and did not involve direct contact with human participants. Therefore, informed consent was not applicable.

Data Availability Statement

No new data were created or analyzed in this study. Data sharing is not applicable to this article

Acknowledgments

GenAI (Deepseek-V4) was used for language polishing. The authors take full responsibility for the content and accuracy.

Conflicts of Interest

The authors declare no conflicts of interest.

Appendix A

Scoping review search strategy PubMed:
“Depression, Postpartum” [Mesh]) OR (“postpartum depression” OR “post-partum depression” OR “postnatal depression” OR “post-natal depression” OR “puerperal depression” OR “maternal depression” OR “perinatal depression” OR “peri-natal depression” OR “postpartum mood disorder*” OR “postpartum psychological distress” OR “PPD” OR “PND” OR “baby blues” OR “postpartum” OR “post-partum” OR “postnatal” OR “post-natal” OR “puerperal” OR “new mother*” OR “new mom*” OR “after childbirth” OR “after delivery” OR “after giving birth” OR “Edinburgh Postnatal Depression Scale” OR “EPDS” OR “Postpartum Depression Screening Scale” OR “PDSS” OR “Center for Epidemiologic Studies Depression Scale” OR “CES-D” OR “PHQ-9” OR “BDI” OR “HAMD” OR “HAM-D” OR “HADS” OR “MADRS”OR “SDS” OR “Patient Health Questionnaire-9” OR “Beck Depression Inventory” OR “Hamilton Rating Scales for Depression” OR “Hamilton Depression Rating Scale” OR “Hospital Anxiety and Depression Scale” OR “Montgomery-Asberg Depression Rating Scale” OR “Zung Self-Rating Depression Scale” OR “Profile of Mood States” OR “Profiles of Mood States” OR “POMS” OR “POMS Inventory” OR “POMS Questionnaire” OR “POMS scale” OR “POMS test” OR “POMS-SF” OR “POMS Short Form” OR “POMS-Brief” OR “Brief Profile of Mood States” OR “Total Mood Disturbance” OR “TMD” OR “Mood States Profile”
AND
“Forest Therapy” [MeSH] OR (“Nature Therapy” OR “Ecotherapy” OR “forest bathing” OR “shinrin-yoku” OR “eco-therapy” OR “green therapy” OR “woodland therapy” OR “forest-based intervention” OR “nature immersion” OR “therapeutic landscape” OR “forest environment exposure” OR “green exposure” OR “forest exposure” OR “forest healing” OR “urban forest*” OR “green exercise” OR “green space*” OR “natural environment*” OR “park walk*”

References

  1. Sharma, V. Is postpartum depression a clinically useful concept? Expert Rev. Neurother. 2021, 21, 945–947. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Yim, I.S.; Tanner Stapleton, L.R.; Guardino, C.M.; Hahn-Holbrook, J.; Dunkel Schetter, C. Biological and psychosocial predictors of postpartum depression: Systematic review and call for integration. Annu. Rev. Clin. Psychol. 2015, 11, 99–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Khamidullina, Z.; Marat, A.; Muratbekova, S.; Mustapayeva, N.M.; Chingayeva, G.N.; Shepetov, A.M.; Ibatova, S.S.; Terzic, M.; Aimagambetova, G. Postpartum depression epidemiology, risk factors, diagnosis, and management: An appraisal of the current knowledge and future perspectives. J. Clin. Med. 2025, 14, 2418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Hellyer, E.; Nash, K.; Jones, E.; Sitch, A.; Jankovic, J.; Berrisford, G.; Casey, A.; MacArthur, C. Postnatal depression beyond 12 months: A systematic review and meta-analysis. Int. J. Ment. Health Nurs. 2025, 34, e70018. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Rubin, R. Postpartum depression persists longer than previously thought. JAMA 2020, 324, 2475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Hahn-Holbrook, J.; Cornwell-Hinrichs, T.; Anaya, I. Economic and health predictors of national postpartum depression prevalence: A systematic review, meta-analysis, and meta-regression of 291 studies from 56 countries. Front. Psychiatry 2018, 8, 248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Wang, Z.; Liu, J.; Shuai, H.; Cai, Z.; Fu, X.; Liu, Y.; Xiao, X.; Zhang, W.; Krabbendam, E.; Liu, S.; et al. Mapping global prevalence of depression among postpartum women. Transl. Psychiatry 2021, 11, 543. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Slomian, J.; Honvo, G.; Emonts, P.; Reginster, J.-Y.; Bruyère, O. Consequences of maternal postpartum depression: A systematic review of maternal and infant outcomes. Women’s Health 2019, 15, 1745506519844044. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Gasparyan, J.; Anderson, P.O.; Lewis, T.; Yeung, C.H.T. Rules of thumb for estimating drug levels in breast milk: How well do they work? Clin. Pharmacol. Ther. 2026, 119, 101–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Gong, C.; Bertagnolli, L.N.; Boulton, D.W.; Coppola, P. A Literature review of drug transport mechanisms during lactation. CPT Pharmacomet. Syst. Pharmacol. 2024, 13, 1870–1880. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Latendresse, G.; Elmore, C.; Deneris, A. Selective serotonin reuptake inhibitors as first-line antidepressant therapy for perinatal depression. J. Midwifery Women’s Health 2017, 62, 317–328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Hendson, L.; Shah, V.; Trkulja, S. Selective serotonin reuptake inhibitors or serotonin-norepinephrine reuptake inhibitors in pregnancy: Infant and childhood outcomes. Paediatr. Child Health 2021, 26, 321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Pilgrim, R.; Kwok, M.; May, A.; Chapman, S.; Jones, M.D. The effect of medication use on breastfeeding continuation: A systematic review with narrative synthesis. Int. Breastfeed. J. 2025, 20, 59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Hackett, L.; D’Arcy, D.M.; O’Connell, J.; Cromie, S.; Daly, D.; Grimes, T. What barriers and facilitators to self-management are experienced by mothers who wish to breastfeed but require concurrent pharmacotherapy in the first two years postpartum? A mixed-methods systematic review protocol. HRB Open Res. 2025, 8, 53. [Google Scholar] [CrossRef] [Scilit]
  15. Paramudita, L.T.; Nurrasyidah, R.; Sugita, S.; Prihati, D.R. Cognitive behavioral therapy alleviate postpartum depression symptomps. Genius Midwifery J. 2023, 2, 1–9. [Google Scholar] [CrossRef] [Scilit]
  16. Kang, H.K.; Bisht, B.; Kaur, M.; Alexis, O.; Worsley, A.; John, D. Effectiveness of interpersonal psychotherapy in comparison to other psychological and pharmacological interventions for reducing depressive symptoms in women diagnosed with postpartum depression in low- and middle-income countries: A systematic review. Campbell Syst. Rev. 2024, 20, e1399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Wang, Y.; Wilson, A.; Hu, Z.; Lu, L.; Li, W.; Peng, K.; Wu, L.; Xin, Y.; Drescher, J.; Ou, J.; et al. Counselling and psychotherapy service use in Chinese sexual minority populations: A nationwide survey. BMC Psychiatry 2021, 21, 11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Simhi, M.; Sarid, O.; Cwikel, J. Preferences for mental health treatment for post-partum depression among new mothers. Isr. J. Health Policy Res. 2019, 8, 84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Massoudi, P.; Strömwall, L.A.; Åhlen, J.; Kärrman Fredriksson, M.; Dencker, A.; Andersson, E. Women’s experiences of psychological treatment and psychosocial interventions for postpartum depression: A qualitative systematic review and meta-synthesis. BMC Women’s Health 2023, 23, 604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Li, Q. Effects of forest environment (shinrin-yoku/forest bathing) on health promotion and disease prevention—The establishment of “forest medicine”. Environ. Health Prev. Med. 2022, 27, 43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Qin, G.; Yang, J.; Liu, F.; Zhang, Z.; Pan, C. Forest therapy for psychological stress and emotional disorders: A systematic review and meta-analysis. BMC Public Health 2026, 26, 1736. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Jessen, N.H.; Løvschall, C.; Skejø, S.D.; Madsen, L.S.S.; Corazon, S.S.; Maribo, T.; Poulsen, D.V. Effect of nature-based health interventions for individuals diagnosed with anxiety, depression and/or experiencing stress—A systematic review and meta-analysis. BMJ Open 2025, 15, e098598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Coventry, P.A.; Brown, J.V.E.; Pervin, J.; Brabyn, S.; Pateman, R.; Breedvelt, J.; Gilbody, S.; Stancliffe, R.; McEachan, R.; White, P.C.L. Nature-based outdoor activities for mental and physical health: Systematic review and meta-analysis. SSM-Popul. Health 2021, 16, 100934. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Vesting, S.; Rembeck, G.; Fagevik Olsén, M.; Gutke, A.; Larsson, M.E.H. Surprised by the transition to an unknown body: Quantitative and qualitative aspects of activity limitations and physical changes during the first year post-partum. BMC Pregnancy Childbirth 2025, 25, 1002. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Edie, R.; Lacewell, A.; Streisel, C.; Wheeler, L.; George, E.; Wrigley, J.; Pietrosimone, L.; Figuers, C. Barriers to exercise in postpartum women: A mixed-methods systematic review. J. Women’s Pelvic Health Phys. Ther. 2021, 45, 83–92. [Google Scholar] [CrossRef] [Scilit]
  26. Boybay Koyuncu, S.; Duman, M. Body dissatisfaction of women during postpartum period and coping strategies. Women Health 2022, 62, 46–54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Bueno, S.V.; Clausen, D.; Sevdalis, V.; Nielsen, R.Ø. O.5.2-10 Barriers to physical activity among parous women postpartum: A qualitative study in Denmark. Eur. J. Public Health 2023, 33, ckad133.251. [Google Scholar] [CrossRef] [Scilit]
  28. Miake-Lye, I.M.; Hempel, S.; Shanman, R.; Shekelle, P.G. What Is an evidence map? A systematic review of published evidence maps and their definitions, methods, and products. Syst. Rev. 2016, 5, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA extension for scoping reviews (PRISMA-ScR): Checklist and explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Sun, Y.; Molitor, J.; Benmarhnia, T.; Avila, C.; Chiu, V.; Slezak, J.; Sacks, D.A.; Chen, J.-C.; Getahun, D.; Wu, J. Association between urban green space and postpartum depression, and the role of physical activity: A retrospective cohort study in Southern California. Lancet Reg. Health-Am. 2023, 21, 100462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Hall, K.; Evans, J.; Roberts, R.; Brown, R.; Duggan, L.; Williamson, M.; Moran, P.; Turner, K.M.; Barnes, C. Co-designing a nature-based intervention to promote postnatal mental health for mothers and their infants: A complex intervention development study in England. BMJ Open 2023, 13, e075366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Nichani, V.; Dirks, K.; Burns, B.; Bird, A.; Grant, C. Green space and depression during pregnancy: Results from the Growing Up in New Zealand Study. Int. J. Environ. Res. Public Health 2017, 14, 1083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Sun, Y. Green Space Exposure Assessment and Association with Maternal Mental Health; ProQuest Information & Learning: Ann Arbor, MI, USA, 2023; Volume 84. [Google Scholar]
  34. Boakye, S.K.; Danquah, L.; Antwi, M. Maternal mental health improvement in Ghana: Role of green spaces exposure. BMC Women’s Health 2025, 25, 328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Hall, K.; Evans, J.; Roberts, R.; Brown, R.; Barnes, C.; Turner, K. Mothers’ accounts of the impact of being in nature on postnatal wellbeing: A focus group study. BMC Women’s Health 2023, 23, 32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. South, E.C.; Lee, K.; Oyekanmi, K.; Buckler, D.G.; Tiako, M.J.N.; Martin, T.; Kornfield, S.L.; Srinivas, S. Nurtured in nature: A pilot randomized controlled trial to increase time in greenspace among urban-dwelling postpartum women. J. Urban Health 2021, 98, 822–831. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Feng, X.; Astell-Burt, T. Residential green space quantity and quality and symptoms of psychological distress: A 15-year longitudinal study of 3897 women in postpartum. BMC Psychiatry 2018, 18, 348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. McEachan, R.R.C.; Prady, S.L.; Smith, G.; Fairley, L.; Cabieses, B.; Gidlow, C.; Wright, J.; Dadvand, P.; Van Gent, D.; Nieuwenhuijsen, M.J. The association between green space and depressive symptoms in pregnant women: Moderating roles of socioeconomic status and physical activity. J. Epidemiol. Community Health 2016, 70, 253–259. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Singh, S.; Van De Wouw, M.; Tomfohr-Madsen, L.; Lebel, C.; Giesbrecht, G.F. The role of green and blue spaces in perinatal maternal mental health outcomes during the transition to parenthood. Environ. Int. 2025, 201, 109572. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Nguemeni Tiako, M.J.; South, E.; Shannon, M.M.; McCarthy, C.; Meisel, Z.F.; Elovitz, M.A.; Burris, H.H. Urban residential tree canopy and perceived stress among pregnant women. Environ. Res. 2021, 201, 111620. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Hall, K.; Barnes, C.; Duggan, L.; Walton, S.; Moran, P.; Turner, K.; Evans, J. The applicability of nature-based interventions to support mothers’ postnatal wellbeing: A conceptual review. Wellbeing Space Soc. 2024, 6, 100187. [Google Scholar] [CrossRef] [Scilit]
  42. Parry, B.L.; Meliska, C.J.; Sorenson, D.L.; Martinez, L.F.; Lopez, A.M.; Dawes, S.E.; Elliott, J.A.; Hauger, R.L. Critically-timed sleep+light interventions differentially improve mood in pregnancy vs. postpartum depression by shifting melatonin rhythms. J. Affect. Disord. 2023, 324, 250–258. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Burns, A.C.; Saxena, R.; Vetter, C.; Phillips, A.J.K.; Lane, J.M.; Cain, S.W. Time spent in outdoor light is associated with mood, sleep, and circadian rhythm-related outcomes: A cross-sectional and longitudinal study in over 400,000 UK Biobank participants. J. Affect. Disord. 2021, 295, 347–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Joye, Y.; Dewitte, S. Nature’s broken path to restoration. A critical look at attention restoration theory. J. Environ. Psychol. 2018, 59, 1–8. [Google Scholar] [CrossRef] [Scilit]
  45. Qiu, T.; Wen, H.; Liu, Z.-X.; Pan, X.-P.; Zeng, T. Investigation regarding early cognitive function of women in the postpartum period and the analysis of influencing factors. Risk Manag. Healthc. Policy 2021, 14, 3747–3754. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Ulrich, R.S.; Simons, R.F.; Losito, B.D.; Fiorito, E.; Miles, M.A.; Zelson, M. Stress recovery during exposure to natural and urban environments. J. Environ. Psychol. 1991, 11, 201–230. [Google Scholar] [CrossRef] [Scilit]
  47. Yao, W.; Zhang, X.; Gong, Q. The effect of exposure to the natural environment on stress reduction: A meta-analysis. Urban For. Urban Green. 2021, 57, 126932. [Google Scholar] [CrossRef] [Scilit]
  48. Zarza-Rebollo, J.A.; López-Isac, E.; Rivera, M.; Gómez-Hernández, L.; Pérez-Gutiérrez, A.M.; Molina, E. The relationship between BDNF and physical activity on depression. Prog. Neuro-Psychopharmacol. Biol. Psychiatry 2024, 134, 111033. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Kebede, A.A.; Gessesse, D.N.; Tsega, N.T.; Aklil, M.B.; Temesgan, W.Z.; Abegaz, M.Y.; Anteneh, T.A.; Tibebu, N.S.; Alemu, H.N.; Haile, T.T.; et al. Prevalence and factors associated with maternal loneliness during the postpartum period in Gondar City. Heliyon 2022, 8, e09891. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Sharifipour, F.; Javadnoori, M.; Behboodi Moghadam, Z.; Najafian, M.; Cheraghian, B.; Abbaspoor, Z. Interventions to improve social support among postpartum mothers: A systematic review. Health Promot. Perspect. 2022, 12, 141–150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  51. Terman, M.; Terman, J.S. Treatment of seasonal affective disorder with a high-output negative ionizer. J. Altern. Complement. Med. 1995, 1, 87–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Jiang, S.-Y.; Ma, A.; Ramachandran, S. Negative air ions and their effects on human health and air quality improvement. Int. J. Mol. Sci. 2018, 19, 2966. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Zhu, S.; Hu, F.; He, S.; Qiu, Q.; Su, Y.; He, Q.; Li, J. Comprehensive evaluation of healthcare benefits of different forest types: A case study in Shimen National Forest Park, China. Forests 2021, 12, 207. [Google Scholar] [CrossRef] [Scilit]
  54. Song, C.; Ikei, H.; Miyazaki, Y. Physiological effects of forest-related visual, olfactory, and combined stimuli on humans: An additive combined effect. Urban For. Urban Green. 2019, 44, 126437. [Google Scholar] [CrossRef] [Scilit]
  55. Peahl, A.F.; Novara, A.; Heisler, M.; Dalton, V.K.; Moniz, M.H.; Smith, R.D. Patient preferences for prenatal and postpartum care delivery: A survey of postpartum women. Obstet. Gynecol. 2020, 135, 1038–1046. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Makama, M.; Chen, M.; Moran, L.J.; Skouteris, H.; Harrison, C.L.; Choi, T.; Lim, S. Postpartum women’s preferences for lifestyle intervention after childbirth: A multi-methods study using the TIDieR Checklist. Nutrients 2022, 14, 4229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Cafiero, P.; Justich, P. Postpartum depression: Impact on pregnant women and the postnatal physical, emotional, and cognitive development of their children. An ecological perspective. Arch. Argent. Pediatr. 2024, 122, e202310217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Sasayama, D.; Owa, T.; Kudo, T.; Kaneko, W.; Makita, M.; Kuge, R.; Shiraishi, K.; Nomiyama, T.; Washizuka, S.; Honda, H. Postpartum maternal depression, mother-to-infant bonding, and their association with child difficulties in sixth grade. Arch. Women’s Ment. Health 2025, 28, 1283–1294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Hutchens, B.F.; Kearney, J. Risk factors for postpartum depression: An umbrella review. J. Midwifery Women’s Health 2020, 65, 96–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  60. Luca, D.L.; Margiotta, C.; Staatz, C.; Garlow, E.; Christensen, A.; Zivin, K. Financial toll of untreated perinatal mood and anxiety disorders among 2017 births in the United States. Am. J. Public Health 2020, 110, 888–896. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  61. Patel, V. Mental health in low- and middle-income countries. Br. Med. Bull. 2007, 81–82, 81–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  62. Bolton, P.; West, J.; Whitney, C.; Jordans, M.J.D.; Bass, J.; Thornicroft, G.; Murray, L.; Snider, L.; Eaton, J.; Collins, P.Y.; et al. Expanding mental health services in low- and middle-income countries: A task-shifting framework for delivery of comprehensive, collaborative, and community-based care. Glob. Ment. Health 2023, 10, e16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Viana, M.C.; Kazdin, A.E.; Harris, M.G.; Stein, D.J.; Vigo, D.V.; Hwang, I.; Manoukian, S.M.; Sampson, N.A.; Alonso, J.; Andrade, L.H.; et al. Barriers to 12-month treatment of common anxiety, mood, and substance use disorders in the World Mental Health (WMH) Surveys. Int. J. Ment. Health Syst. 2025, 19, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  64. Arbitman, L.; Chen, S.; Kim, B.; Lee, M.; Zou, P.; Doughty, B.; Li, Y.; Zhang, T. Assessment of infant exposure to antidepressants through breastfeeding: A literature review of currently available approaches. Pharmaceutics 2024, 16, 847. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  65. Panțiru, I.; Ronaldson, A.; Sima, N.; Dregan, A.; Sima, R. The impact of gardening on well-being, mental health, and quality of life: An umbrella review and meta-analysis. Syst. Rev. 2024, 13, 45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Britton, E.; Kindermann, G.; Domegan, C.; Carlin, C. Blue care: A systematic review of Blue Space Interventions for Health and Wellbeing. Health Promot. Int. 2020, 35, 50–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. PRISMA flowchart of the screening process.
Ijerph 23 01134 g001
Table 1. Characteristics of the included literature.
Author & YearCountryStudy DesignPopulation CategorySample SizeKey Demographics
Sun et al. (2023) [30]USARetrospective cohort studyGeneral Postpartum Population415,020Mean age 30.2 (SD = 5.8) years; 51.5% Hispanic
Hall et al. (2023) [31]England, UKIntervention development studyPostnatal mothers (including those with or at risk of mental health difficulties)45 (30 mothers + 15 professional stakeholders)Not explicitly stated; participants included diverse mothers (refugee, migrant, disabled)
Nichani et al. (2017) [32]New ZealandObservational cohort studyPregnant women (general)6772Mean age 30 years (SD = 6); 93% resided in urban areas; Ethnicity: European (53%), Māori (14%), Pacific (15%), Asian (15%)
Sun (2022) [33]USAMixed-methods design (Ecological + Retrospective cohort + RCT)Pregnant and postpartum womenThree sub-studies: ecological/method development (n = 2343), retrospective cohort (n = 415,020), VR experiment (n = 63).Cohort: mean age 30.2 years; Hispanic (51.5%), Non-Hispanic White (25.5%), Asian (12.8%), African American (7.7%); VR experiment: mean age ~32 years (Beijing, China)
Boakye et al. (2025) [34]GhanaHospital-based cross-sectional studyPostpartum mothers (child age 0–24 months)420Age: 31–35 years (48.4%); 26–30 years (25.8%); Married (55.2%); Employed (65.3%); Akan ethnicity (70.0%); Monthly income ≤ 1600 GHS (74.5%)
Hall et al. (2023) [35]UKQualitative (focus group study)Postpartum mothers with mental health difficulties30Age 20–42 years (majority 25–35); most had >1 child; youngest infant 3.5 weeks; most children aged 4 months to 2 years
South et al. (2021) [36]USAPilot randomized controlled trialPostpartum women (urban-dwelling, low-income, predominantly Black)36 (final analysis cohort)Mean age 28 ± 6 years; 69% Black; 5.6% Hispanic/Latinx; urban-dwelling, low-income, predominantly Black community sample
Feng & Astell-Burt (2018) [37]AustraliaLongitudinal observational studyPostpartum women3897Age 17–63 years; Aboriginal/Torres Strait Islander: 290 (7.4%)
Education: Postgraduate (3357), Undergraduate (12,172).
McEachan et al. (2015) [38]UKObservational cohort studyPregnant women with depressive symptoms7547Multi-ethnic UK cohort (Born in Bradford); mean NDVI: White British 0.50–0.54, South Asian 0.39–0.44; low education 58.8%; age 21–34 years (76.6%); first birth (40.0%)
Singh et al. (2025) [39]CanadaLongitudinal cohort studyPerinatal population (pregnant and postpartum)10,762Mean age 31.8 years (SD = 4.4); 82.6% White; median income $100,000–$124,999; median education = undergraduate degree; pan-Canadian COVID-19 cohort.
Nguementi Tiako et al. (2021) [40]USAObservational cohort study (secondary analysis)Pregnant women1294Mean age at delivery: 27.8 years (SD = 5.9); Race/Ethnicity: 70.6% non-Hispanic Black, 18.8% non-Hispanic White, 4.7% Hispanic, 6.0% Other; 60.4% on Medicaid/Uninsured
Abbreviations: NDVI, Normalized Difference Vegetation Index; SD, standard deviation; GHS, Ghanaian Cedi.
Table 2. Exposure/Intervention and Measurement Approaches.
Author & YearExposure/Intervention TypeEnvironment/Activity DetailsOutcome Measurement ToolExposure Measurement ApproachAdjusted Covariates
Sun et al. (2023) [30]Passive exposureResidential urban green space (200 m, 500 m, 1000 m buffers); measured via street-level greenery (trees, low vegetation, grass), NDVI, land cover green space, tree canopy cover, park accessibilityKPSC electronic health records (diagnosis codes and/or antidepressant prescriptions)Street-level imagery (Microsoft Bing) with deep learning; satellite-derived NDVI; tree canopy cover; distance to parksMain model: maternal age, race/ethnicity, educational level, block group-level household income; Sensitivity analyses: + smoking during pregnancy, season of conception, year of infant birth, insurance type, preterm birth, pregnancy-related comorbidities (preeclampsia, gestational hypertension, gestational diabetes); Mediation analyses: + pre-pregnancy BMI. Zip code fitted as a random effect.
Hall et al. (2023) [31]Active intervention (co-designed)co-designed group-based
forest-bathing program; sensory invitations and slow guided walk; group format (5–9 mother-baby dyads); 5–6 weekly sessions (2 h each)
Not applicable (intervention development study)Qualitative description; environmental risk assessmentNot applicable
Nichani et al. (2017) [32]Passive exposureGreen space as % within Census Area Units (parks, beaches, urban parklands/open spaces, forests, grasslands, croplands; excluding private gardens)Edinburgh Postnatal Depression Scale (EPDS)% green space within Census Area Units (GIS)Fully adjusted model included: age, self-identified ethnicity, educational attainment, employment status, area deprivation (NZDep2006), smoking during pregnancy, alcohol consumption during pregnancy, physical activity during/after first trimester, pre-pregnancy general health status, relationship status with biological father, parity, residential rurality, and length of stay at current residence (surrogate for neighborhood self-selection).
Sun (2022) [33]Mixed (passive exposure + active VR)Chapter 3: Street-level greenery via Microsoft Bing street-view; Chapter 4: VR videos (0% green, 12% green, 50% green park)—5 min immersion after Trier Social Stress Testcohort: EHR diagnosis/prescriptions;
VR experiment:
: SBP, DBP, HR, SCL, sAA, SC, PANAS
Deep learning model on street-view images; VR-controlled exposureCohort main model: maternal age, race/ethnicity, education, block group household income; Sensitivity: + smoking, season of conception, year of birth, insurance; Mediation: + pre-pregnancy BMI; VR experiment: randomization + double-blind (no additional adjustment)
Boakye et al. (2025) [34]Passive exposure (self-reported)Greenspace for leisure activities or physical activity; self-reported exposure (quantity, visibility, accessibility, frequency of use, quality, purpose)Perceived Stress Scale (PSS-9); Hamilton Anxiety Rating Scale (HAMA); Center for Epidemiologic Studies Depression Scale (CES-D-10)Self-reported questionnaireNot explicitly reported; only mentioned ‘adjusted for several socio-demographic factors’ without listing specific variables
Hall et al. (2023) [35]Active (unstructured)Time spent in nature (local parks, green spaces, beaches, woodlands, “anywhere with grass”); no fixed frequency or duration; self-directedQualitative thematic analysis (Reflexive Thematic Analysis)Qualitative focus group explorationNot applicable
South et al. (2021) [36]Active intervention (“Nature Coach”-guided)Individualized
4-week Nature Coach intervention: 1 home visit, 1 park visit, 1 phone check-in; weekly text nudges; personalized goals (walking, sitting, reading, listening to music, gardening)
Edinburgh Postnatal Depression Scale (EPDS); GPS data via AWARE appGPS tracking; intervention arm vs. control (10 min educational session only)None (small pilot RCT)
Feng & Astell-Burt (2018) [37]Passive exposureResidential green space quantity (% parkland in Statistical Area 2); self-reported quality (“good parks, playgrounds and play spaces”)Kessler 6 Psychological Distress Scale (K6)% parkland; self-reported perceived qualityMultilevel models adjusted for: age (linear + squared), Indigenous status, highest educational qualification, economic status, area disadvantage (SEIFA), geographic remoteness (ARIA), and years since childbirth (linear + squared). Models also included interaction terms between years since childbirth and green space measures.
McEachan et al. (2015) [38]Passive exposureResidential greenness (NDVI within 100 m, 300 m, 500 m buffers); access to major green space (>0.5 hectares) within 300 mGHQ-28 (4-item subset for depressive symptoms)Satellite-derived NDVI; GIS-based accessibilityFully adjusted model included: ethnicity/ethnolanguage grouping, age, parity, marital/cohabitation status, household size tertiles, maternal education, subjective poverty, Index of Multiple Deprivation (IMD) quintile, smoking, alcohol use, and physical activity.
Singh et al. (2025) [39]Passive exposureGreen space: NDVI and tree canopy cover within a 500 m radius of postal code; Blue space: distance to nearest water body (ocean, lake, river) within 5 kmEdinburgh Postnatal Depression Scale (EPDS); PROMIS Anxiety Scale (7-item)Satellite-derived NDVI and tree canopy cover; GIS-based distance to water bodiesIndividual-level SES: education, household income, food insecurity (combined as z-score); Neighborhood-level: material deprivation and social deprivation (Pamphalon Deprivation Index); Geographic: population density (large/medium/small population centers or rural); Random effects: random intercept for individuals and random effect for time.
Nguementi Tiako et al. (2021) [40]Passive exposureUrban residential tree canopy cover (100 m and 500 m buffers) derived from 2015 LiDAR dataCohen’s Perceived Stress Scale (PSS-14)LiDAR-derived tree canopy cover percentageIndividual-level: history of anxiety or depression, self-identified race/ethnicity, health insurance status, age at delivery, parity, level of education; Neighborhood-level: Neighborhood Deprivation Index; Seasonality: leaf-growing season (based on LMP).
Abbreviations: NDVI, Normalized Difference Vegetation Index; EHR, electronic health record; KPSC, Kaiser Permanente Southern California; EPDS, Edinburgh Postnatal Depression Scale; CES-D-10, Center for Epidemiologic Studies Depression Scale (10-item version); PSS-9, Perceived Stress Scale (9-item version); HAMA, Hamilton Anxiety Rating Scale; PROMIS, Patient-Reported Outcomes Measurement Information System; GPS, Global Positioning System; SBP, systolic blood pressure; DBP, diastolic blood pressure; HR, heart rate; SCL, skin conductance level; sAA, salivary alpha-amylase; SC, salivary cortisol; PANAS, Positive and Negative Affect Schedule; SEIFA, Socio-Economic Indexes for Areas; ARIA, Accessibility/Remoteness Index of Australia; GHQ-28, General Health Questionnaire (28-item version); SES, socioeconomic status; IMD, Index of Multiple Deprivation; BMI, body mass index; LMP, last menstrual period; LiDAR, Light Detection and Ranging.
Table 3. Key Findings and Author Conclusions.
Author & YearPrimary Outcome(s)Effect Size Estimates (95% CI) (Source)Key Findings (Source)Author’s Conclusion/Contribution (Source)
Sun et al. (2023) [30]PPDStreet greenery (500 m): OR = 0.98 (0.97–0.99) per IQR increase; Tree cover (500 m): OR = 0.98 (0.97–0.99); NDVI and park accessibility: not significantEach IQR increase in street-level total greenery (500 m buffer) was associated with reduced PPD risk. Tree cover was associated with reduced PPD risk. NDVI and park accessibility showed no significant association with PPD. PA mediated 2.7% to 7.2% of the effect of green space on PPD.Street-view-based greenery and tree cover were associated with lower PPD risk. The observed associations were primarily attributable to increased tree cover rather than low vegetation or grass. Increased physical activity was identified as one possible pathway linking green space to lower PPD risk.
Hall et al. (2023) [31]Not applicable (intervention development)Not applicableNot applicable—intervention development study; no efficacy assessment.The target users perceived that the intervention addressed their needs and preferences. Further research is needed to determine feasibility, clinical and cost-effectiveness.
Nichani et al. (2017) [32]Antenatal Depression (EPDS)Medium green space: OR = 1.10 (0.89–1.35); High: OR = 1.15 (0.94–1.41); Very high: OR = 1.21 (0.96–1.52)—all non-significantNo significant association between green space exposure (medium, high, very high) and antenatal depression.No significant association was found between green space exposure and antenatal depression in this New Zealand cohort, suggesting that the protective effects observed in other contexts may not generalize to all settings.
Sun (2022) [33]PPD (cohort); Physiological & Affective Response (VR)Cohort: Street greenery OR = 0.960 (0.934–0.987); Tree cover OR = 0.946 (0.921–0.972); Tree canopy OR = 0.969 (0.945–0.994); PA mediated 9.6–15.6% of effect. VR (High vs. Low green): SBP −4.57 mmHg (−8.51, −0.64); sAA −1.22 ng/mL (−2.26, −0.18); PANAS positive affect +6.62 (0.29, 12.95); Anxiety −2.62 (−5.19, −0.04)Street-level total greenery and street tree cover were associated with reduced PPD risk. Tree canopy cover also showed a protective association. Physical activity mediated 9.6–15.6% of the effect. High-green VR exposure was associated with greater reductions in systolic blood pressure and salivary alpha-amylase.Provides multi-level evidence: (1) deep learning can effectively classify street greenery types; (2) Low-SES neighborhoods had less street greenery; (3) cohort analysis linked street greenery and tree cover to reduced PPD risk via physical activity mediation; (4) VR experiment demonstrates acute stress recovery (reduced blood pressure and salivary alpha-amylase) in pregnant women.
Boakye et al. (2025) [34]Stress (PSS-9); Anxiety (HAMA); Depression (CES-D-10)Stress: β = −0.118 (95% CI: −0.118, 0.025); Anxiety: β = 0.117 (95% CI: 0.049, 0.491); Depression: β = 0.164 (95% CI: 0.205, 0.769)58.1% of mothers reported high levels of perceived stress. Using green space for leisure activities or physical exercise was negatively associated with stress levels. 42.5% of mothers reported high levels of anxiety. The belief that spending time in green spaces positively impacts overall health was positively associated with anxiety levels. 58.9% of mothers exhibited high levels of depressive symptoms. The aforementioned belief was positively associated with depression levels.Green space exposure has the potential to alleviate maternal stress, anxiety, and depression. Policies encouraging the establishment of green spaces and maternal use of green spaces should be promoted.
Hall et al. (2023) [35]Postnatal Wellbeing (qualitative)Not applicable (qualitative study)Main Theme 1: ‘That feels like nature to me’—Nature could be found in simple local settings such as parks and grassy areas; some mothers perceived “wild” natural environments away from the city as more tranquil. Main Theme 2: ‘You can feel that it’s different’—Multi-sensory experiences (touch, hearing, smell) enhanced wellbeing; perceiving the beauty and vastness of nature; mothers with disabilities connected with nature through non-visual senses. Barriers: weather, transport, inadequate facilities, mental health issues, physical recovery challenges (e.g., cesarean section), cultural practices (e.g., 40 days postpartum confinement), racial discrimination, lack of family support, feeling unwelcome. Facilitators: locally accessible green spaces, sensory experiences, improved infant sleep, social support, escape from indoor stress, enhanced self-efficacy.Nature contact enhances postnatal well-being through multiple mechanisms, including sensory experience, social support, stress relief, and a shift in perspective. However, the diverse barriers faced by mothers from different backgrounds must be considered. Mothers reported that spending time in nature had significant benefits for postnatal wellbeing, with potential to promote mental health, social connection, and physical health.
South et al. (2021) [36]Nature visits (GPS); Depression (EPDS)Nature visits (ITT): IRR = 2.6 (p = 0.059); (As-Treated): IRR = 3.1 (p = 0.025); EPDS: No significant difference between groups at any time pointITT analysis showed an increase in visit frequency that did not reach statistical significance (p = 0.059); As-Treated analysis showed a significant increase in visit frequency (p = 0.025). EPDS scores showed no significant group differences at any time point.The intervention significantly increased the number of nature visits among postpartum women and may be a useful population health tool in low-resource, predominantly Black communities.
Feng & Astell-Burt (2018) [37]Psychological Distress (K6); Serious Mental IllnessPsychological distress: “agreed” RR = 0.95 (0.91–0.98); “strongly agreed” RR = 0.89 (0.85–0.93); Serious mental illness: “agreed” OR = 0.88 (0.77–1.00); “strongly agreed” OR = 0.74 (0.64–0.86). Green space quantity: no associationWomen who agreed or strongly agreed that local parks were of good quality had fewer symptoms of psychological distress and lower odds of serious mental illness. No association was found with the quantity of green space.Green space quality, but not quantity, is associated with fewer symptoms of psychological distress and lower odds of serious mental illness among women up to 15 years postpartum. Community consultation is crucial for maximizing health benefits of urban greening.
McEachan et al. (2015) [38]Depressive Symptoms (GHQ-28)100 m buffer (Q3–Q5 vs. Q1): 18–23% lower odds; Education interaction (300 m): OR = 0.74 (0.59–0.94) for low education group; Physical activity interaction: OR = 0.42–0.63 for active individuals; PA mediation: 5.6–7.8% of total effectHigher residential greenness was associated with 18–23% lower odds of depressive symptoms. The association was stronger among individuals with lower education and those who were physically active. Physical activity mediated 5.6–7.8% of the total effect.Higher residential greenness is associated with a reduced likelihood of depressive symptoms; associations are stronger among those with lower education and among active women; physical activity is a small but significant partial mediator.
Singh et al. (2025) [39]Perinatal Depression (EPDS); Anxiety (PROMIS)Depression: NDVI β = −0.91 (−1.77, −0.05); Water distance β = −0.14 (−0.24, −0.03); NDVI-depression strongest prenatally β = −1.82 (−2.84, −0.80). Anxiety (prenatal only): NDVI β = −2.51 (−4.08, −0.94); Tree canopy β = −0.03 (−0.05, −0.01); Water distance: not associated with anxietyHigher NDVI and shorter distance to water bodies were associated with fewer depression symptoms. The NDVI-depression association varied over time and was strongest during pregnancy. NDVI and tree canopy cover were associated with lower anxiety only during pregnancy. Distance to water bodies was not associated with anxiety.Green spaces and blue spaces were associated with fewer perinatal depression and anxiety symptoms, particularly during pregnancy.
Nguementi Tiako et al. (2021) [40]Perceived Stress (PSS-14)Overall cohort (100 m): β = −0.02 (−0.43, 0.39) per SD increase; Overall cohort (500 m): β = 0.3 (−0.1, 0.6); High-risk group (anxiety/depression history, 100 m): β = −1.0 (−1.8, −0.2); High-risk group (500 m): not statistically significant; High canopy (>30%) vs. low (<10%) in high-risk group: aOR = 0.17 (0.03–0.81)No significant association was found between tree canopy cover and perceived stress in the overall cohort. Among women with a history of anxiety/depression, each SD increase in tree canopy cover was associated with lower perceived stress. High canopy cover (>30%) compared to low cover (<10%) was associated with 83% lower odds of high stress in the high-risk group.Residential tree canopy coverage was associated with reduced perceived stress among urban-dwelling pregnant women with a history of anxiety or depression. No association was found in the overall cohort.
Abbreviations: PA, physical activity; IQR, interquartile range; OR, odds ratio; RR, risk ratio; IRR, incidence rate ratio; β, beta coefficient; aOR, adjusted odds ratio; CI, confidence interval; ITT, intention-to-treat; EPDS, Edinburgh Postnatal Depression Scale; PSS-14, Perceived Stress Scale (14-item version); PROMIS, Patient-Reported Outcomes Measurement Information System; GHQ-28, General Health Questionnaire (28-item version); K6, Kessler 6 Psychological Distress Scale; PANAS, Positive and Negative Affect Schedule.
Table 4. Evidence mapping table.
Research Population/Research DesignObservational StudiesRCTQualitative ResearchTotal
Pregnant woman3 (Nichani 2017 [32], McEachan 2015 [38], Nguementi Tiako 2021 [40])003
Ordinary postpartum women3 (Sun 2023 [30], Boakye 2025 [34], Feng & Astell-Burt (2018) [37])1 (South 2021 [36])04
Postpartum women with or at risk of mental health issues002 (Hall 2023 [31], Hall 2023 [35])2
Mixed population (pregnant and postpartum)2 (Sun 2022 [33], Singh 2025 [39])002
Total81211
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.