1. Introduction
Asbestos has long been recognized as a critical occupational and environmental health hazard. The International Agency for Research on Cancer classifies asbestos as a Group 1 carcinogen, signifying its definite carcinogenicity in humans [
1]. Inhalation of asbestos fibers is strongly associated with chronic respiratory diseases, including asbestosis and diffuse pleural thickening, as well as malignancies such as lung cancer, malignant mesothelioma, laryngeal cancer, and ovarian cancer [
2,
3]. Acknowledging these grave consequences, more than 70 countries have adopted comprehensive bans on asbestos use [
4]. Nonetheless, asbestos remains widely used in many developing countries, with an estimated 125 million people exposed in occupational settings worldwide, leading to approximately 255,000 deaths annually from asbestos-related diseases (ARDs) [
5,
6].
Despite the magnitude of this risk, asbestos-related diseases remain underrecognized in Indonesia. National health reports lack systematic data on mesothelioma or other ARDs, and official statistics are virtually absent. The first reported case of asbestos-related cancer in the country was only reported in 2019 [
7]. However, recent evidence demonstrates that asbestos exposure is already contributing to Indonesia’s health burden. A hospital-based case–control study showed that workers with occupational asbestos exposure had more than three times the risk of lung cancer compared to non-exposed counterparts [
8].
Approximately 90% of imported raw asbestos in Indonesia is processed domestically into asbestos-cement products, primarily used for roofing sheets and construction materials [
9]. National statistics suggest that 8–10% of Indonesian households use asbestos-cement roofs, though the prevalence is substantially higher in certain regions. In Jakarta, for example, more than half of residential buildings are estimated to have asbestos roofing [
10]. This widespread usage has raised considerable public health concerns, as aging, weathering, or damage to these materials can release microscopic asbestos fibers into the air [
11].
In Java, the potential for asbestos exposure is shaped not only by the distribution of asbestos-containing roofing and the concentration of the population, but also by the island’s seismic setting. Java lies adjacent to the Sunda subduction zone and is also affected by intraslab earthquakes and multiple active crustal faults. Consequently, damaging ground shaking can occur in southern coastal areas as well as densely populated inland and metropolitan districts [
12,
13,
14]. Seismic activity is therefore relevant as a disturbance modifier rather than as a direct measure of asbestos exposure. Ground shaking may fracture asbestos-cement sheets or contribute to structural collapse, while subsequent demolition, debris handling, crushing, transport, and uncontrolled disposal may release respirable fibers. Experiences following earthquakes in Indonesia and other disaster settings support this pathway and indicate potential exposure among residents, emergency responders, and cleanup workers [
15,
16,
17].
These overlapping conditions such as uneven asbestos roof prevalence, very high population density, and spatially variable seismic hazard require assessment below the provincial level. A previous national study identified several provinces in Java among Indonesia’s highest-risk areas, but province-level analysis may conceal substantial differences between districts and municipalities [
18]. District-level mapping can therefore provide a more precise basis for identifying locations where chronic environmental exposure potential and earthquake-triggered disturbance may coincide.
Accordingly, this study aimed to develop a district-level asbestos exposure risk map for Java by integrating the prevalence of asbestos-cement roofing, population density, and seismic hazard. The resulting map is intended as a screening and prioritization tool to support asbestos control, public awareness, health surveillance, and disaster preparedness. It does not represent measured airborne asbestos concentrations or individual disease risk.
2. Materials and Methods
2.1. Study Design and Setting
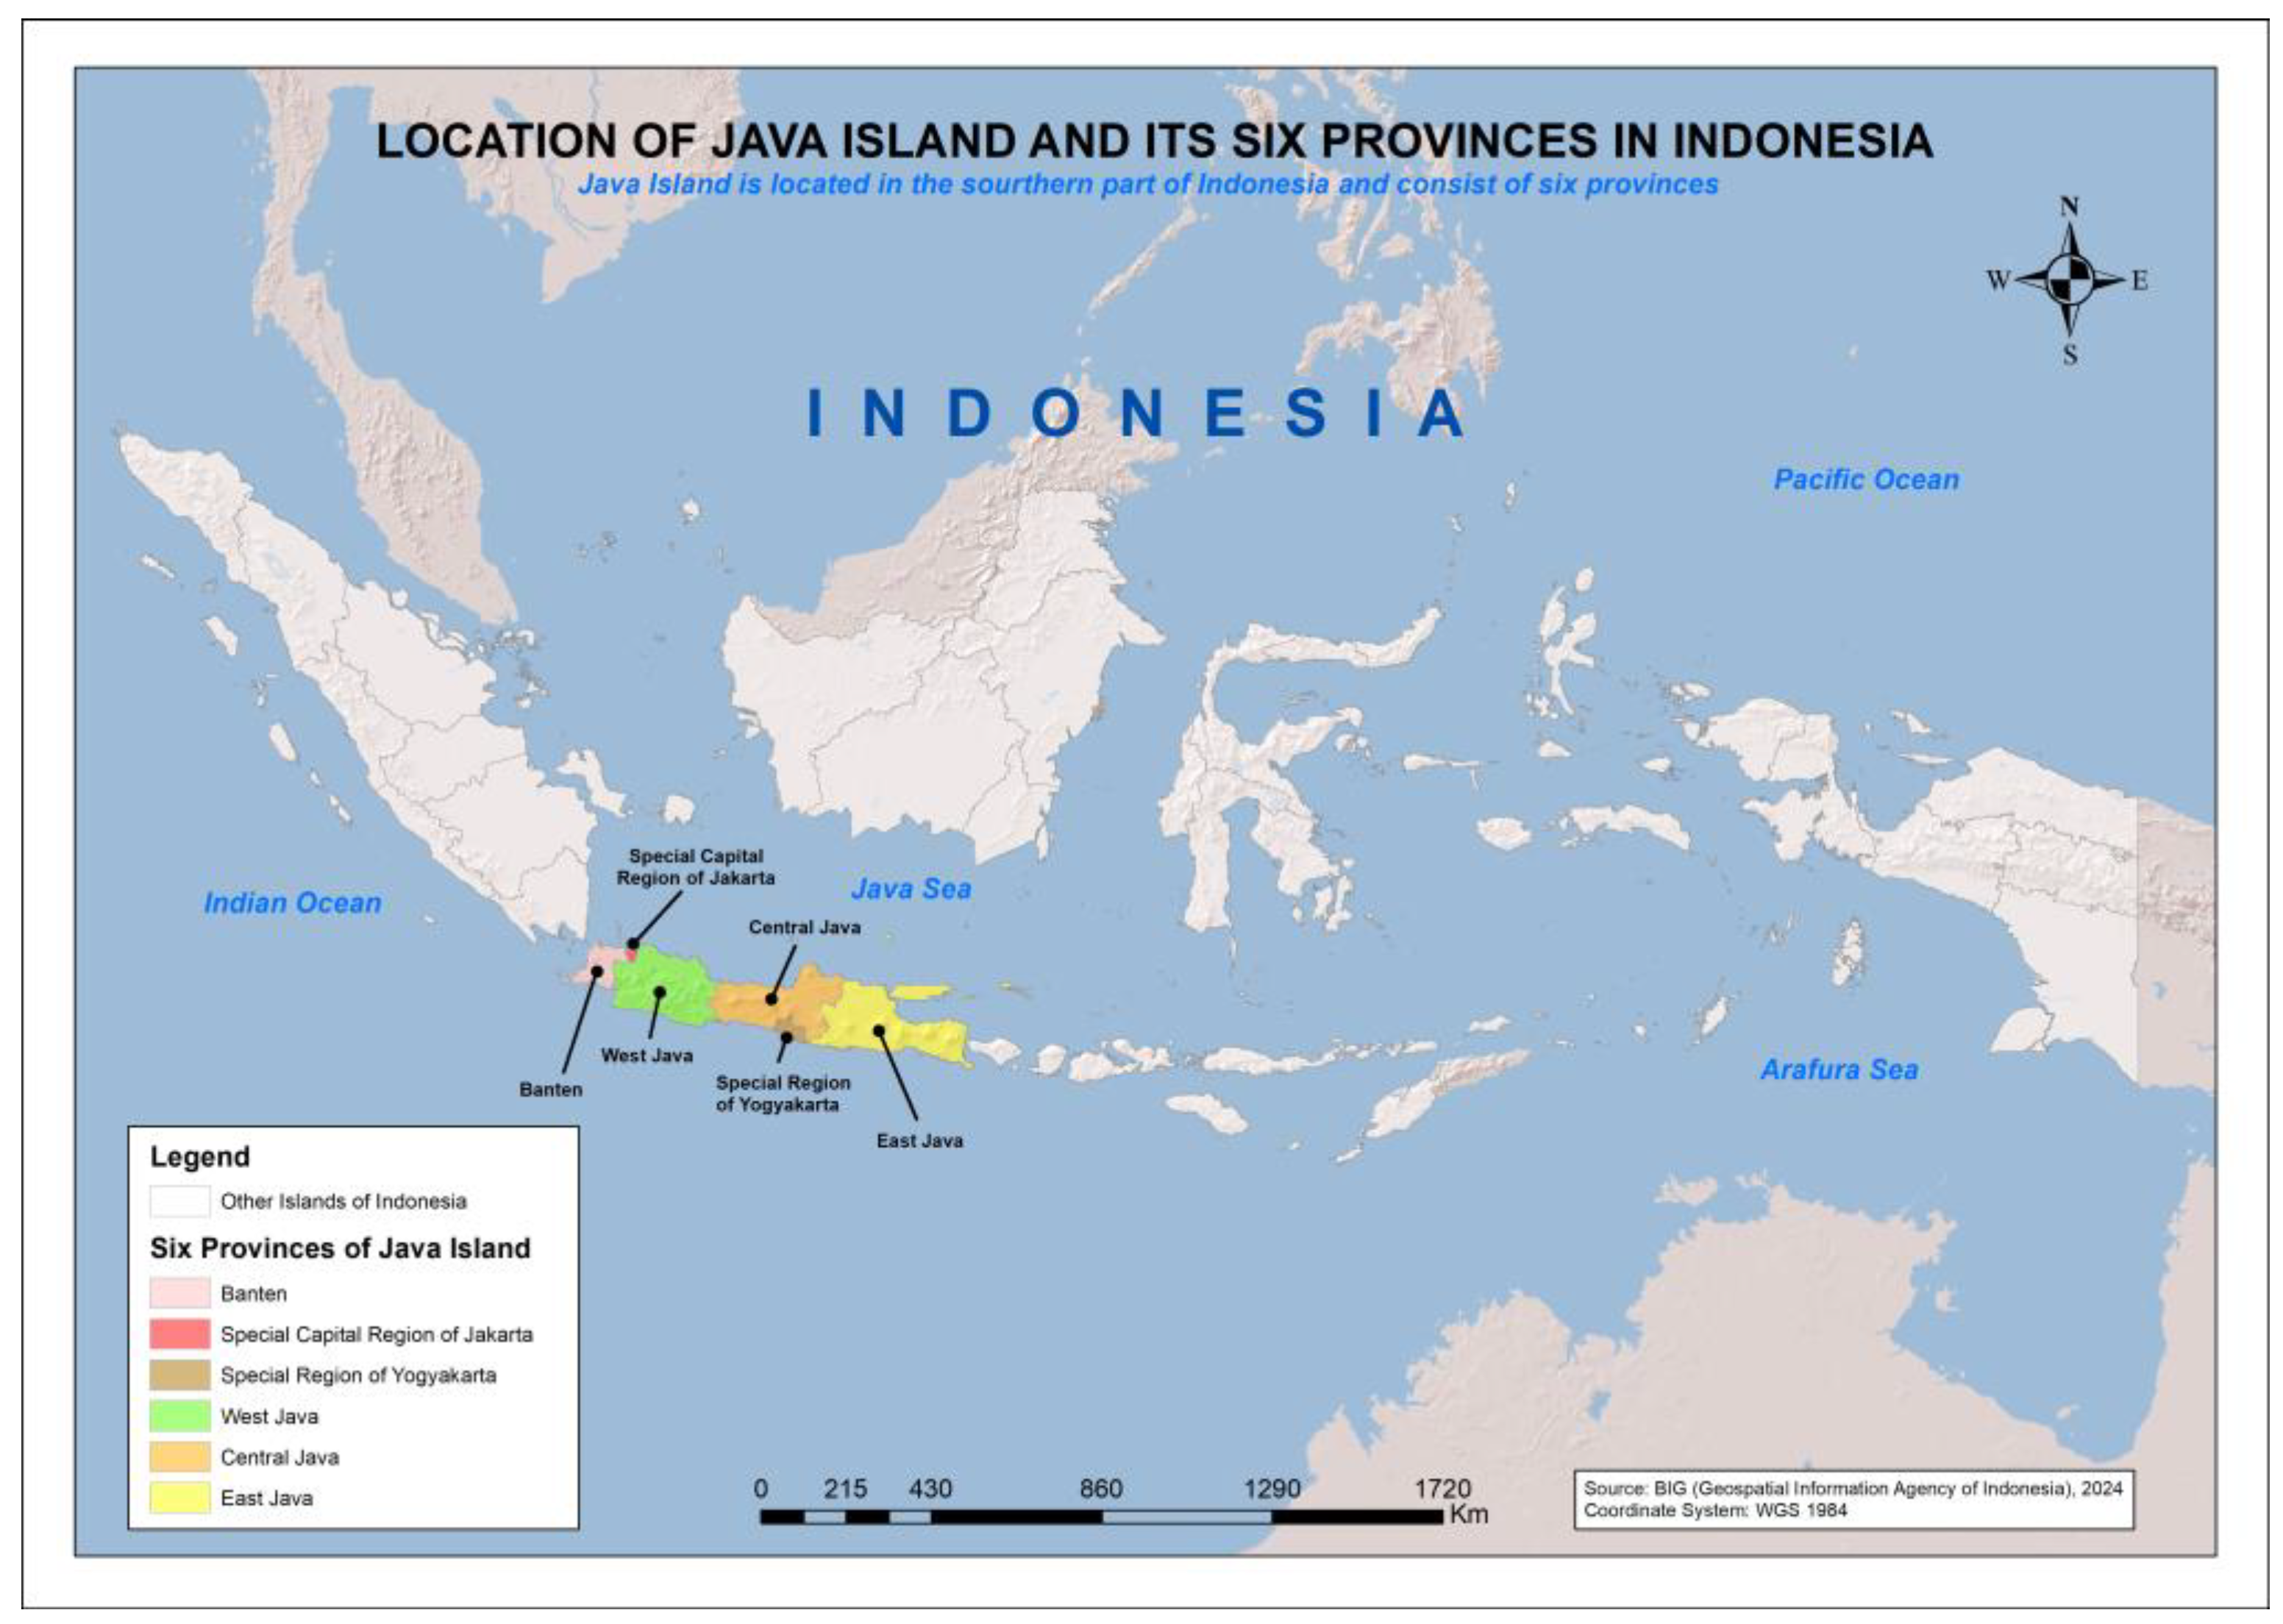
This study applied a descriptive, semi-quantitative design to map the risk of asbestos exposure conducted between June and September 2025. This research focused on Java Island, Indonesia, encompassing all districts and municipalities (kabupaten/kota) across six provinces as the units of analysis (
Figure 1). Java was selected given its high population density, urban growth, and widespread use of asbestos-cement products.
2.2. Data Sources and Variables
Secondary data were obtained from two official sources. First, the Indonesian Central Statistics Agency (Badan Pusat Statistik, BPS, Indonesia) provided district-level data on asbestos roofing and population density [
10,
19]. Asbestos data reflected the proportion of households using asbestos-cement roofing, while density was calculated from population counts and district area. Second, seismic hazard data were gathered from the Geological Disaster Mitigation Portal (Portal Mitigasi Bencana Geologi, PMBG, Indonesia), managed by the Center for Volcanology and Geological Hazard Mitigation (Pusat Vulkanologi dan Mitigasi Bencana Geologi, PVMBG, Indonesia) [
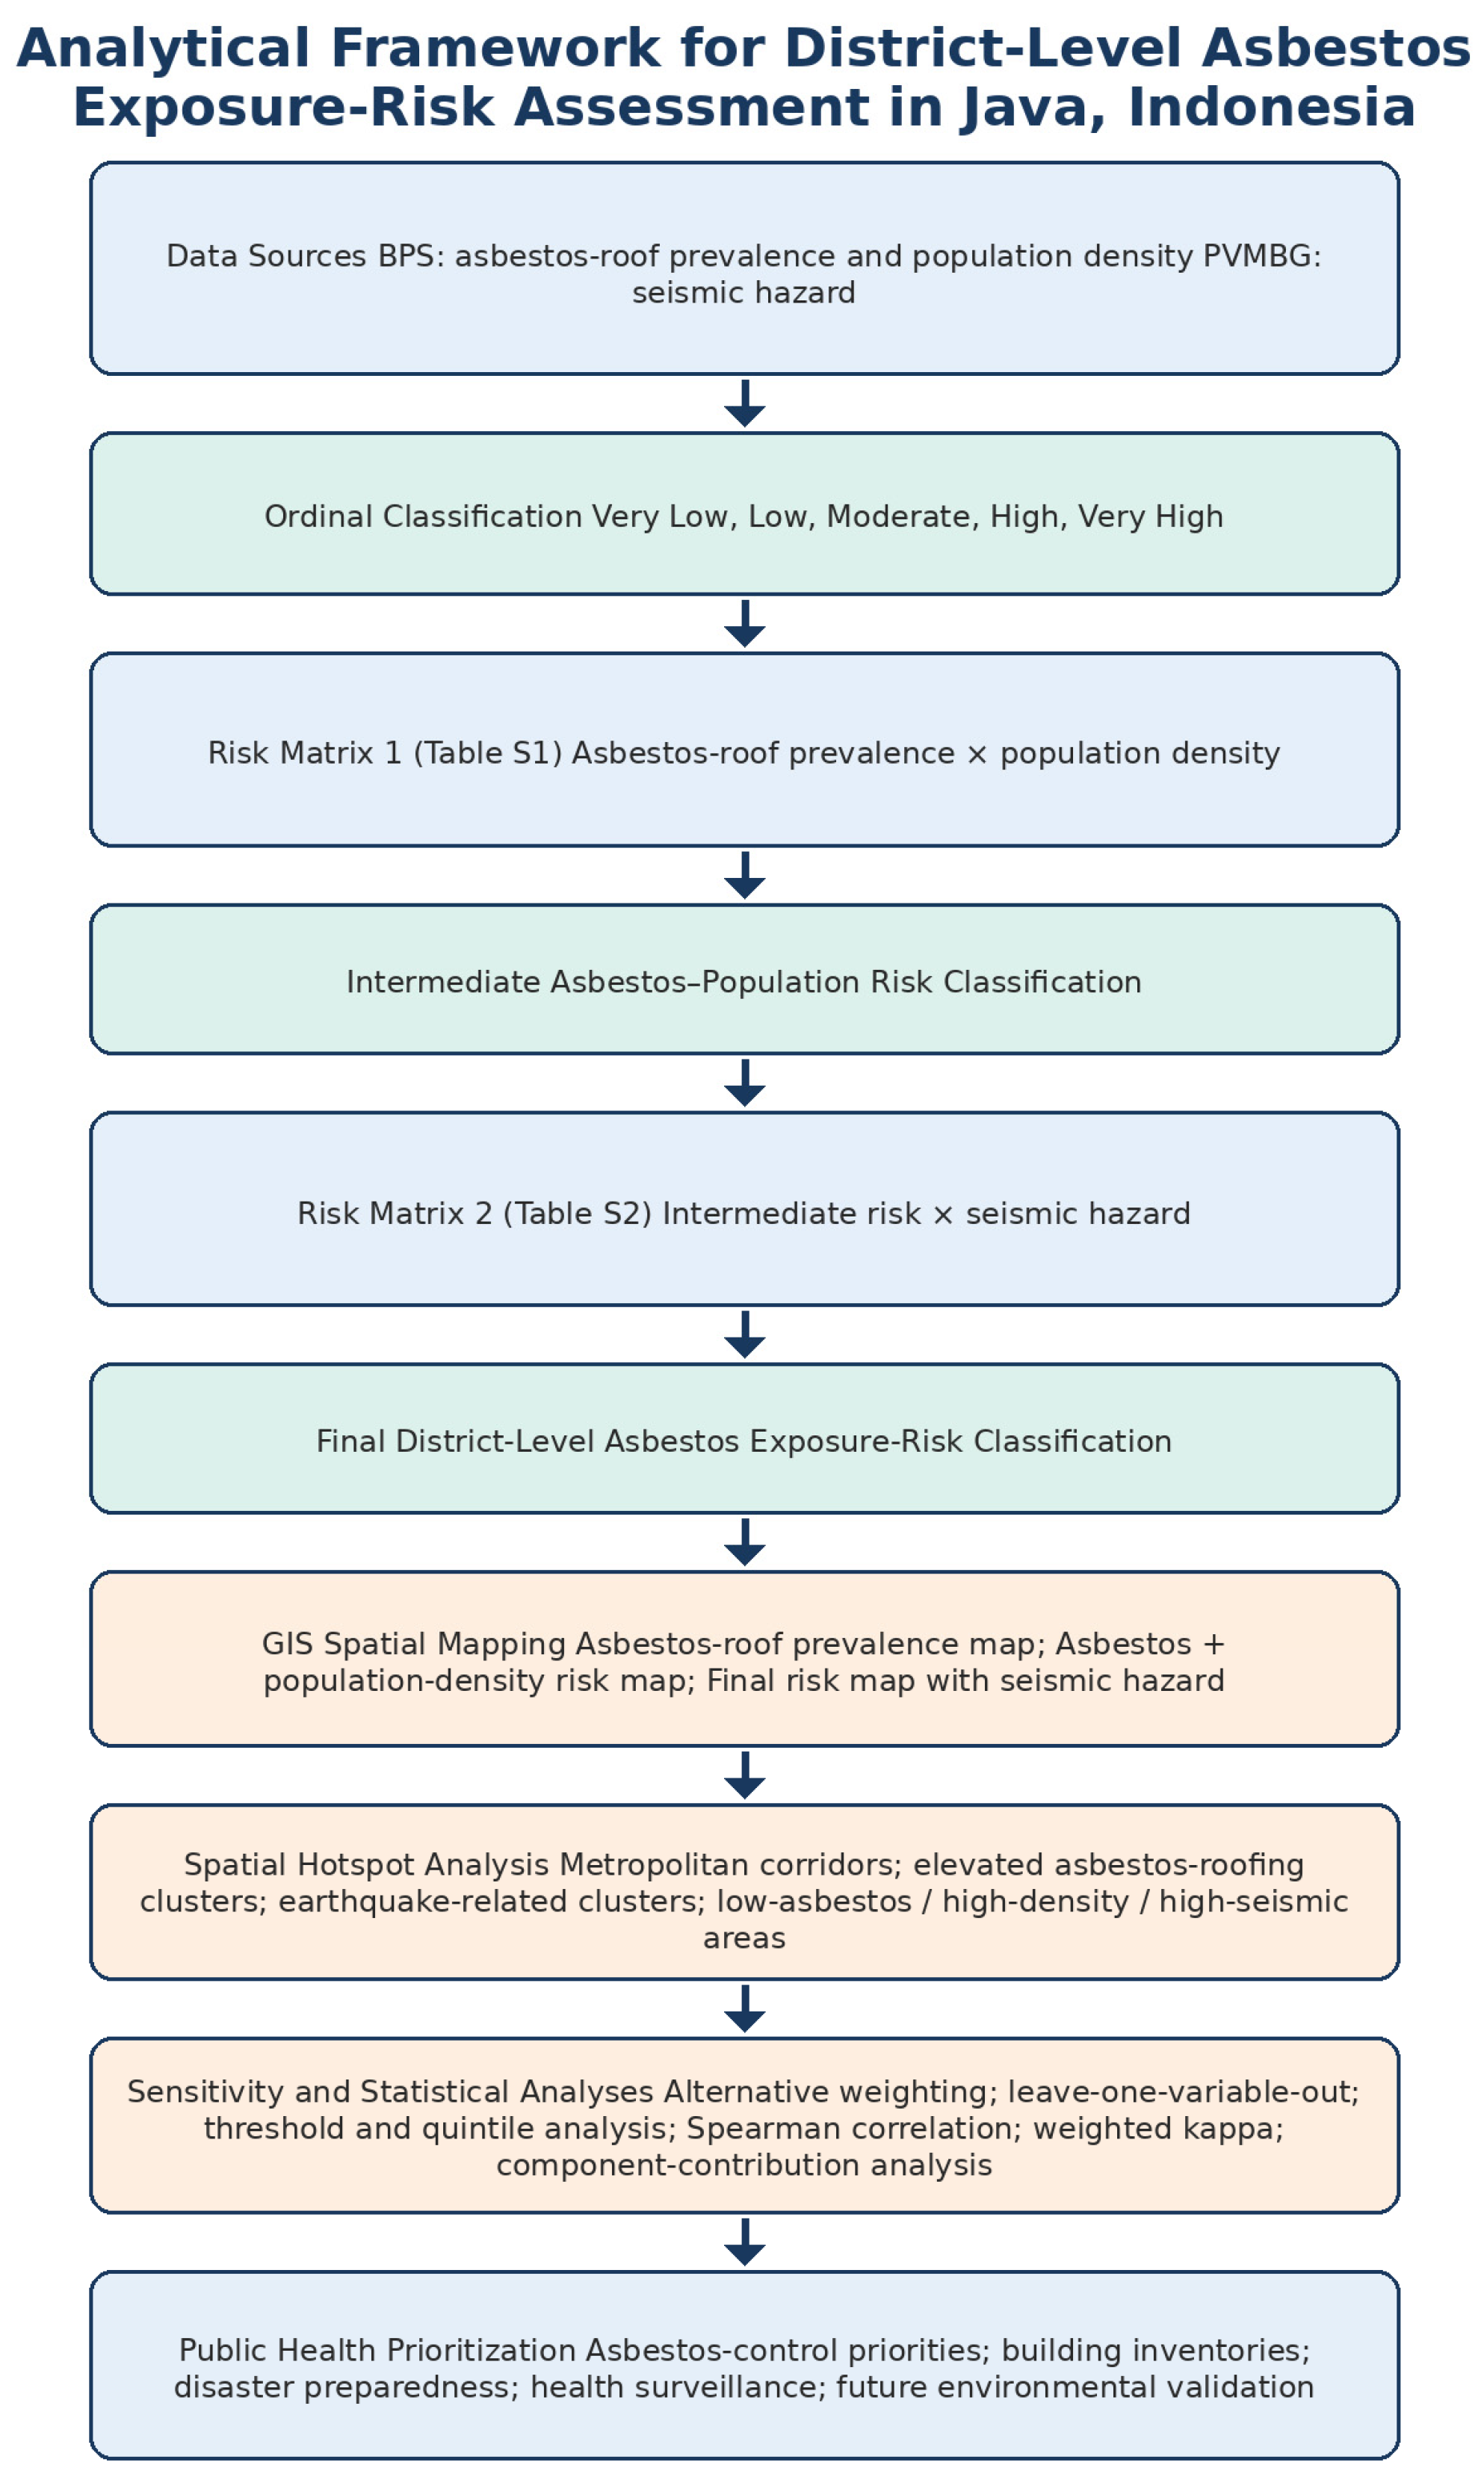
14]. The PMBG contains spatial data on fault lines, earthquake-prone zones, and district-level seismic classifications. Together, these datasets captured three critical risk dimensions: asbestos prevalence, human exposure, and disaster vulnerability. The overall analytical workflow of the study is summarized in
Figure 2.
2.3. Risk Factor Classification
To standardize the different indicators, three variables—prevalence of asbestos roofing, population density, and seismic hazard—were stratified into five ordinal categories: very low, low, moderate, high, and very high. This approach enabled a semi-quantitative comparison across the datasets. The extent of asbestos roofing in each administrative unit was defined as the percentage of buildings constructed with asbestos-containing materials. Regions with less than 1% asbestos roof coverage were classified as very low, 1–5% as low, >5–10% as moderate, >10–20% as high, and greater than 20% as very high [
18,
20]. Population density, expressed as the number of inhabitants per square kilometer, was categorized according to combined references from prior studies and the Ministry of Public Works and Housing Regulation No. 2 of 2016: <50 persons/km
2 (very low), 51–100 (low), 101–250 (moderate), 251–400 (high), and >401 (very high) [
21,
22]. These population density thresholds were adopted as pragmatic classification bands for comparative spatial screening and should not be interpreted as locally validated asbestos exposure–response thresholds; their influence on the classification was therefore examined in the sensitivity analyses.
Seismic hazard levels were derived from the PVMBG seismic risk maps, which apply the Modified Mercalli Intensity (MMI) scale to estimate the potential intensity of earthquakes across different zones [
14]. It was not interpreted as a direct measure of asbestos fiber release. Increasing MMI levels generally indicate greater potential for cracking, displacement, partial collapse, or complete collapse of buildings and brittle roofing materials. Such damage may increase the likelihood that asbestos-cement sheets are fractured and subsequently disturbed during demolition, transport, crushing, or debris disposal. However, no established quantitative relationship directly converts MMI level into airborne asbestos fiber concentration. The seismic variable was therefore included as a relative disturbance modifier in the composite risk model.
2.4. Risk Matrix Development and GIS Mapping
Two complementary risk matrices were developed to assess the potential burden of asbestos exposure. To formalize the semi-quantitative classification, the five ordinal categories were coded as 1 = very low, 2 = low, 3 = moderate, 4 = high, and 5 = very high. Let Ai, Pi, and Si denote the ordinal scores for asbestos roof prevalence, population density, and seismic hazard, respectively, for district or municipality i.
In the first stage, asbestos roof prevalence and population density were combined using the predefined 5 × 5 risk matrix in
Table S1 to generate an intermediate asbestos–population risk category:
where
is the intermediate risk category and
M1 represents the first-stage matrix function. This step reflects the premise that districts with both substantial asbestos use and high population density may have greater potential public health impact.
In the second stage, the intermediate risk category was combined with seismic hazard using the predefined matrix in
Table S2 to generate the final district-level risk classification:
where
Ri is the final risk category and
M2 represents the second-stage matrix function. The complete sequential classification can therefore be expressed as:
This matrix-based formulation was used for the primary GIS classification and was distinct from the arithmetic models used only in the sensitivity analyses. Thematic maps were produced to illustrate (1) asbestos roof prevalence, (2) combined asbestos roof prevalence and population density risk, and (3) the final combined risk incorporating seismic hazard. A standardized color gradient (green = very low, red = very high) was applied to enhance interpretability. Each map included legends, province boundaries, and scale bars and underwent peer review to ensure clarity, accuracy, and consistency.
2.5. Data Verification and Quality Assurance
To ensure reliability, several validation procedures were undertaken. First, asbestos roof prevalence figures from BPS were cross-checked against independent reports and national surveys, which estimate an average household prevalence of ~10%. Population density data were verified against the 2020 national census, showing close alignment. For seismic hazard, PVMBG geologists provided technical guidance to confirm our interpretation of qualitative hazard categories.
2.6. Sensitivity Analysis
Sensitivity analyses were conducted to assess the robustness of the primary GIS-based risk matrix classification to alternative modeling assumptions. For this purpose, an equal-weight arithmetic specification was used as the reference model for the sensitivity analyses. The ordinal scores for asbestos roof prevalence, population density, and seismic hazard were assigned equal weights (1:1:1), and their arithmetic mean was calculated to obtain a three-component reference score. Alternative weighting, leave-one-variable-out, threshold-modification, and distribution-based scenarios were subsequently compared with this equal-weight reference specification. These sensitivity analyses were supplementary to, and did not replace, the primary GIS-based risk matrix classification used to generate the spatial risk maps.
The influence of individual components was examined using a leave-one-variable-out approach. Three two-component models were constructed by combining: (1) asbestos roof prevalence and population density; (2) asbestos roof prevalence and seismic hazard; and (3) population density and seismic hazard. For each model, the arithmetic mean of the two retained ordinal scores was calculated and classified using the same category boundaries applied to the equal-weight arithmetic reference specification. The resulting classifications were then compared with the three-component equal-weight reference model.
Threshold sensitivity was evaluated by modifying the predefined cut-off values for asbestos roof prevalence and population density by ±15%. The asbestos roof prevalence thresholds of 1%, 5%, 10%, and 20% and the population density thresholds of 50, 100, 250, and 400 persons/km2 were simultaneously decreased and increased by 15%. The variables were then reclassified using the modified thresholds, and new equal-weight composite scores were calculated. The resulting classifications were compared with those obtained using the original thresholds in the equal-weight reference specification.
As an additional distribution-based sensitivity analysis, asbestos roof prevalence and population density were reclassified using empirical quintiles derived from the district-level distributions across Java. The 20th, 40th, 60th, and 80th percentiles were used as cut-points to assign ordinal scores from 1 to 5. The seismic hazard classification was retained unchanged, and an equal-weight composite score was recalculated using the revised component categories.
Agreement between the equal-weight arithmetic reference specification and each alternative sensitivity scenario was assessed using the proportion of districts remaining in the same risk category, the proportion remaining within one adjacent category, and the number of districts shifting by two or more categories. Spearman’s rank correlation coefficient was used to evaluate the consistency of composite score rankings, while quadratic weighted Cohen’s kappa was used to assess agreement between ordinal risk classifications. These analyses were intended to assess the internal robustness and stability of the constructed risk classification under alternative analytical assumptions and should not be interpreted as external validation against measured airborne asbestos concentrations, building-level asbestos inventories, or asbestos-related disease outcomes.
2.7. Statistical Analysis
Descriptive analyses were used to summarize the number and proportion of districts/municipalities included in each predefined spatial hotspot pattern. Because the hotspot patterns were defined using overlapping combinations of asbestos roof prevalence, population density, seismic hazard, and overall risk classification, they were treated as non-mutually exclusive and individual districts could be included in more than one pattern.
To examine how the three component indicators contributed to variation in the constructed risk classification, Spearman’s rank correlation coefficients were calculated between the ordinal scores for asbestos roof prevalence, population density, and seismic hazard and the corresponding composite risk score. Spearman correlation was selected because the component indicators were represented as ordinal categories. As a complementary analysis, correlations using the continuous asbestos roof prevalence and population density values were also examined to assess whether the observed relationships were influenced by categorization of these variables.
The relative numerical contribution of each component was calculated for each district by dividing its ordinal score by the sum of the three component scores and multiplying by 100. Mean component contributions were then summarized within each hotspot pattern to characterize the relative contribution of asbestos roof prevalence, population density, and seismic hazard to the constructed index. Components with the largest proportional contribution were described as the predominant numerical drivers of the index within each hotspot pattern. Because the composite score was mathematically derived from these component indicators, the correlation and contribution analyses were interpreted as descriptive assessments of the structure of the constructed risk index rather than as independent or causal estimates of actual asbestos exposure.
3. Results
Java Island comprises six provinces with a total of 119 districts and municipalities. The distribution of asbestos use prevalence across provinces in Indonesia shows substantial geographic variation, with clear clustering of higher prevalence in urbanized and densely populated areas, particularly in DKI Jakarta and parts of West Java and East Java.
In DKI Jakarta, asbestos use prevalence is consistently high across all municipalities, ranging from 46.16% in Jakarta Selatan to 66.89% in Jakarta Utara, with the highest value observed in Kepulauan Seribu (76.66%). This indicates a widespread reliance on asbestos-containing materials, likely reflecting older housing stock, dense settlements, and legacy construction practices.
In West Java, the pattern is more heterogeneous. Several urban areas demonstrate notably high prevalence, including Kota Depok (45.35%), Kota Bekasi (33.25%), and Kota Bogor (30.21%). High values are also observed in peri-urban districts such as Kabupaten Bogor (27.85%) and Kabupaten Bekasi (21.23%), suggesting spillover effects from metropolitan expansion. In contrast, more rural districts such as Kuningan (1.91%), Majalengka (1.15%), and Ciamis (3.04%) exhibit relatively low prevalence.
Banten Province shows moderate variability, with higher prevalence in urban centers such as Tangerang City (34.90%) and South Tangerang City (18.60%), while more rural districts like Serang District (7.92%) and Serang City (6.85%) report lower levels.
In Yogyakarta, asbestos use prevalence is generally low across all districts, ranging from 1.38% in Gunungkidul to 5.37% in Yogyakarta City, indicating limited reliance on asbestos-containing materials compared to other provinces.
Central Java demonstrates a predominantly low-to-moderate prevalence pattern, with most districts reporting values below 10%. However, some notable exceptions include Cilacap (18.45%), Banyumas (10.61%), and Semarang City (28.47%), suggesting localized hotspots. Several districts report very low prevalence, such as Sukoharjo (0.98%), Karanganyar (0.96%), and Klaten (1.01%).
In East Java, the overall prevalence is relatively low in most districts, typically below 5%, particularly in areas such as Ngawi (0.45%), Sampang (0.27%), and Jember (0.88%). However, higher prevalence is observed in several districts and urban centers, including Surabaya (32.14%), Mojokerto (9.58%), Kediri (9.51%), and Malang (8.89%), indicating uneven distribution. Industrialized and urban areas tend to exhibit higher prevalence compared to rural regions (
Table 1).
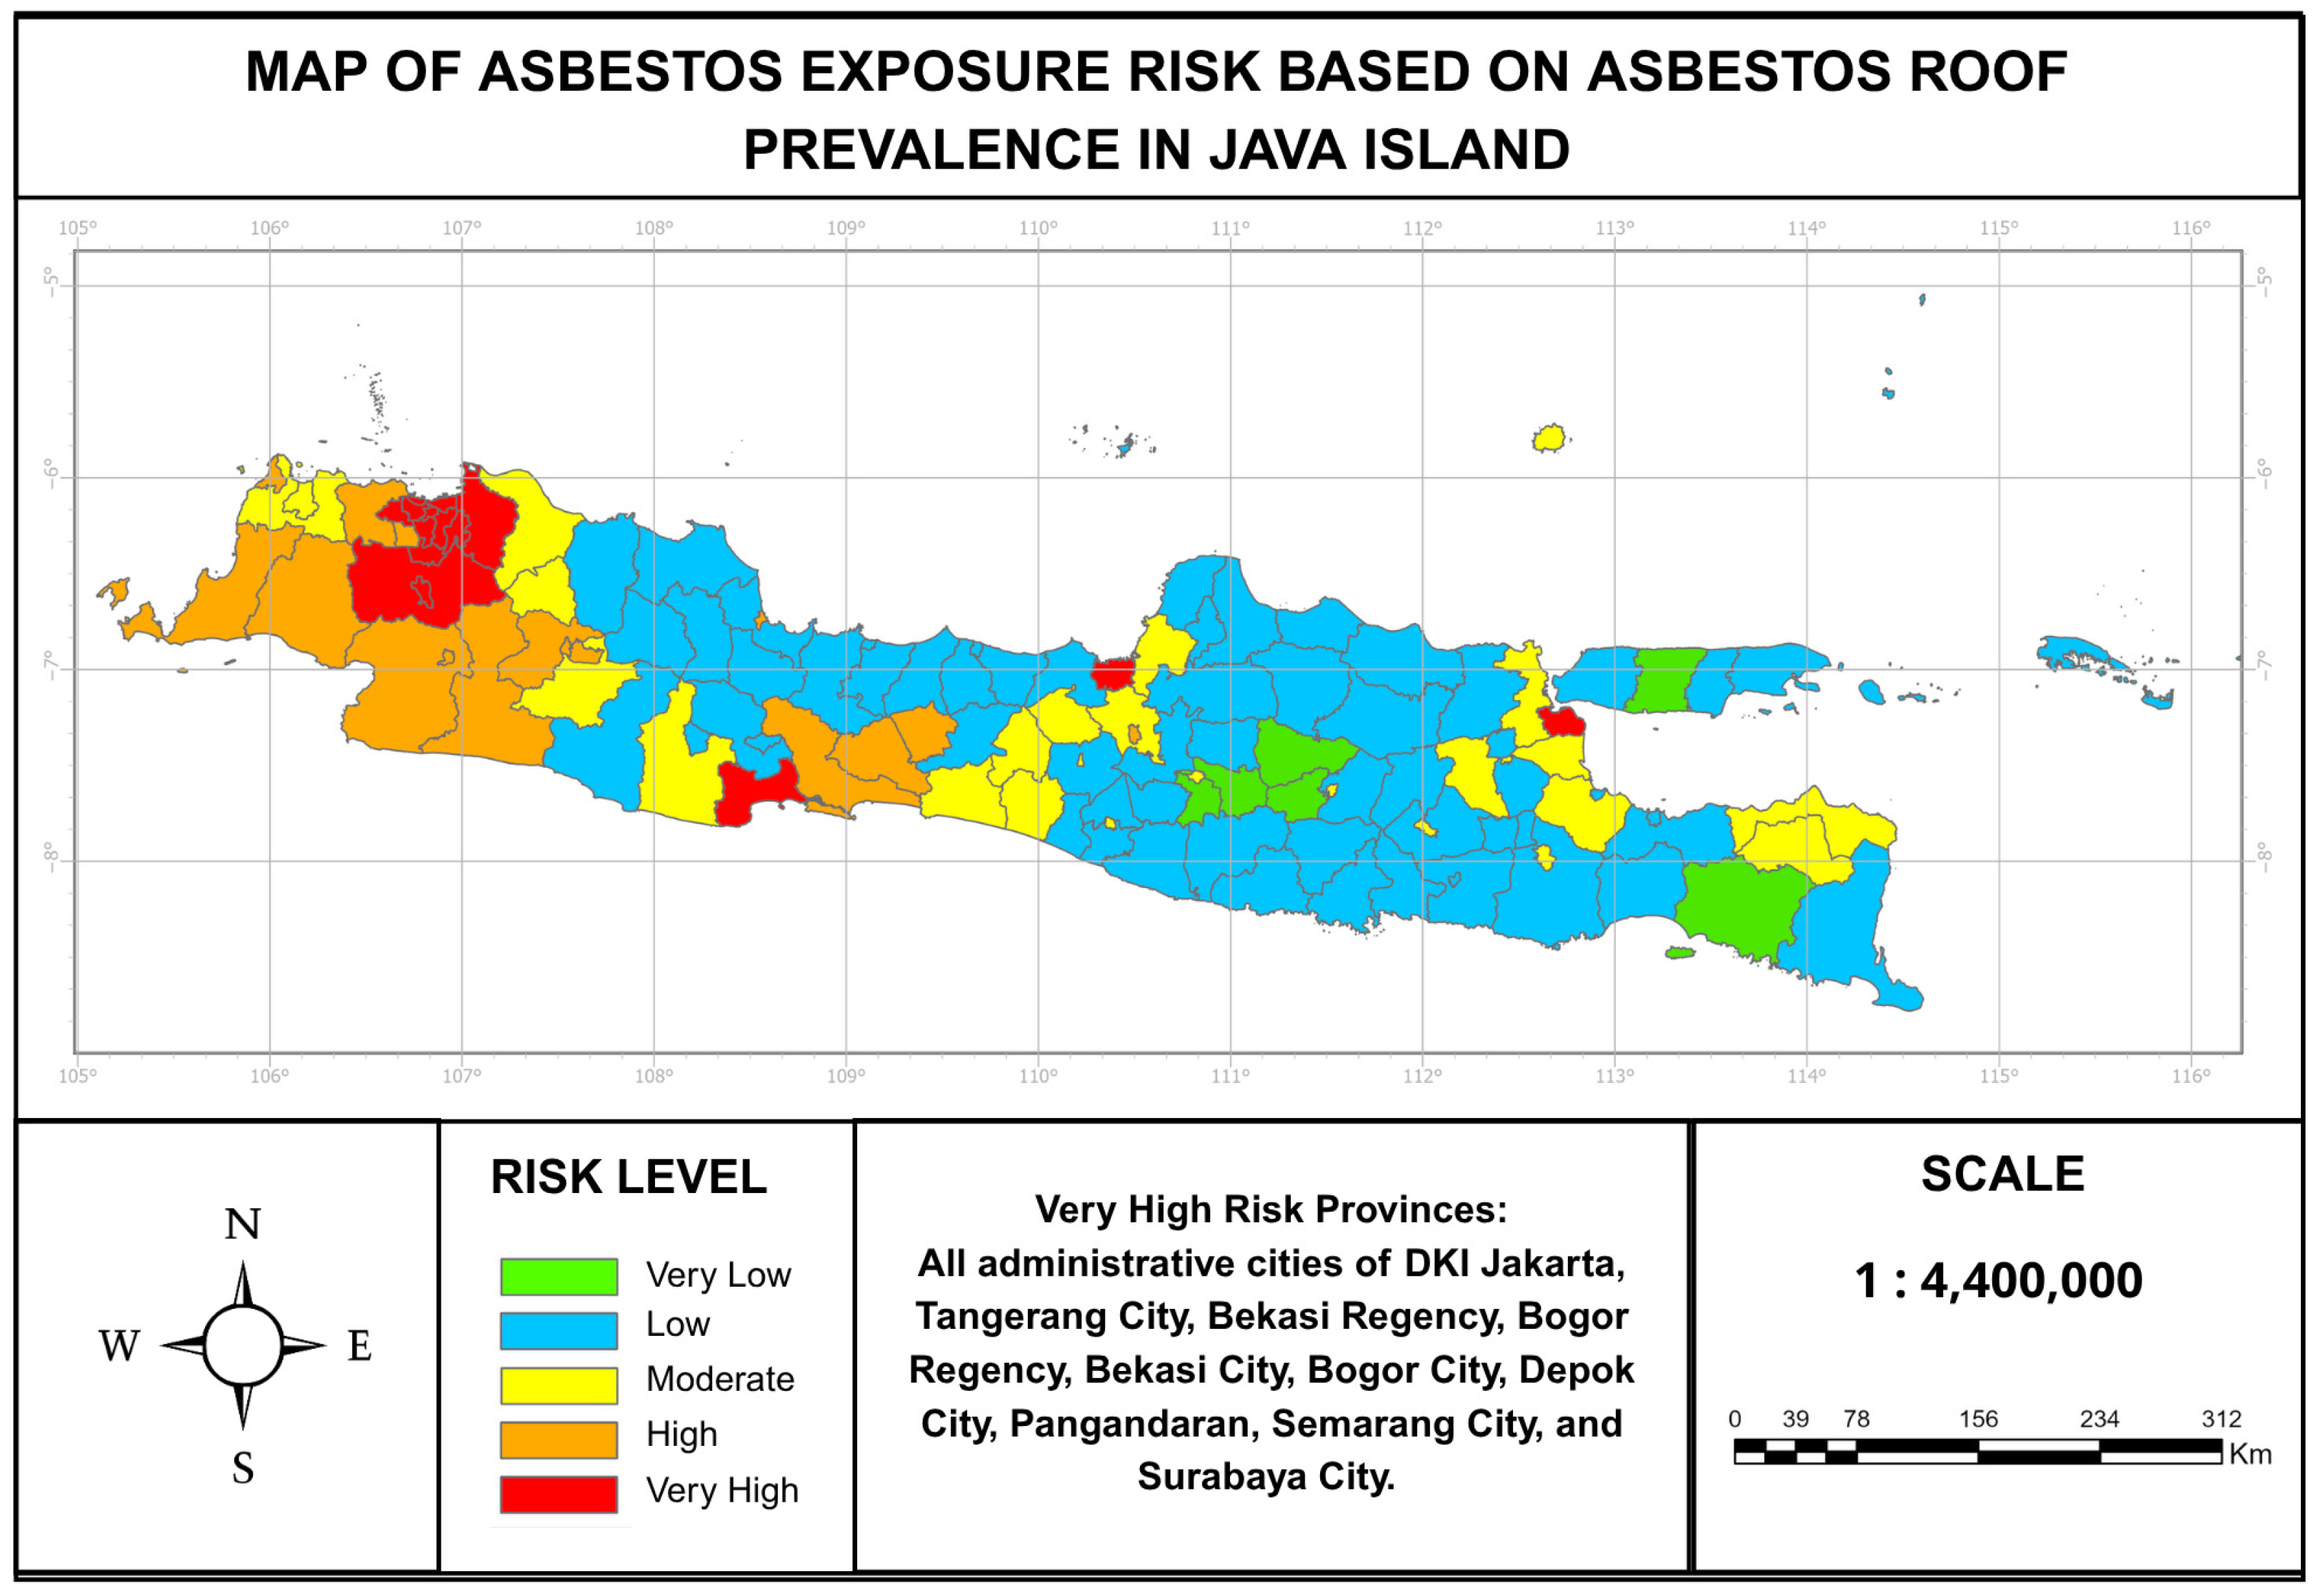
Very high levels of asbestos roof prevalence were identified in 15 districts/municipalities (12.6%), high in 16 (13.4%), moderate in 25 (21.0%), while the remainder fell within the low to very low categories (
Figure 3). All districts/municipalities on Java exhibited high to very high population density, whereas seismic hazard varied widely from very low to high across the island.
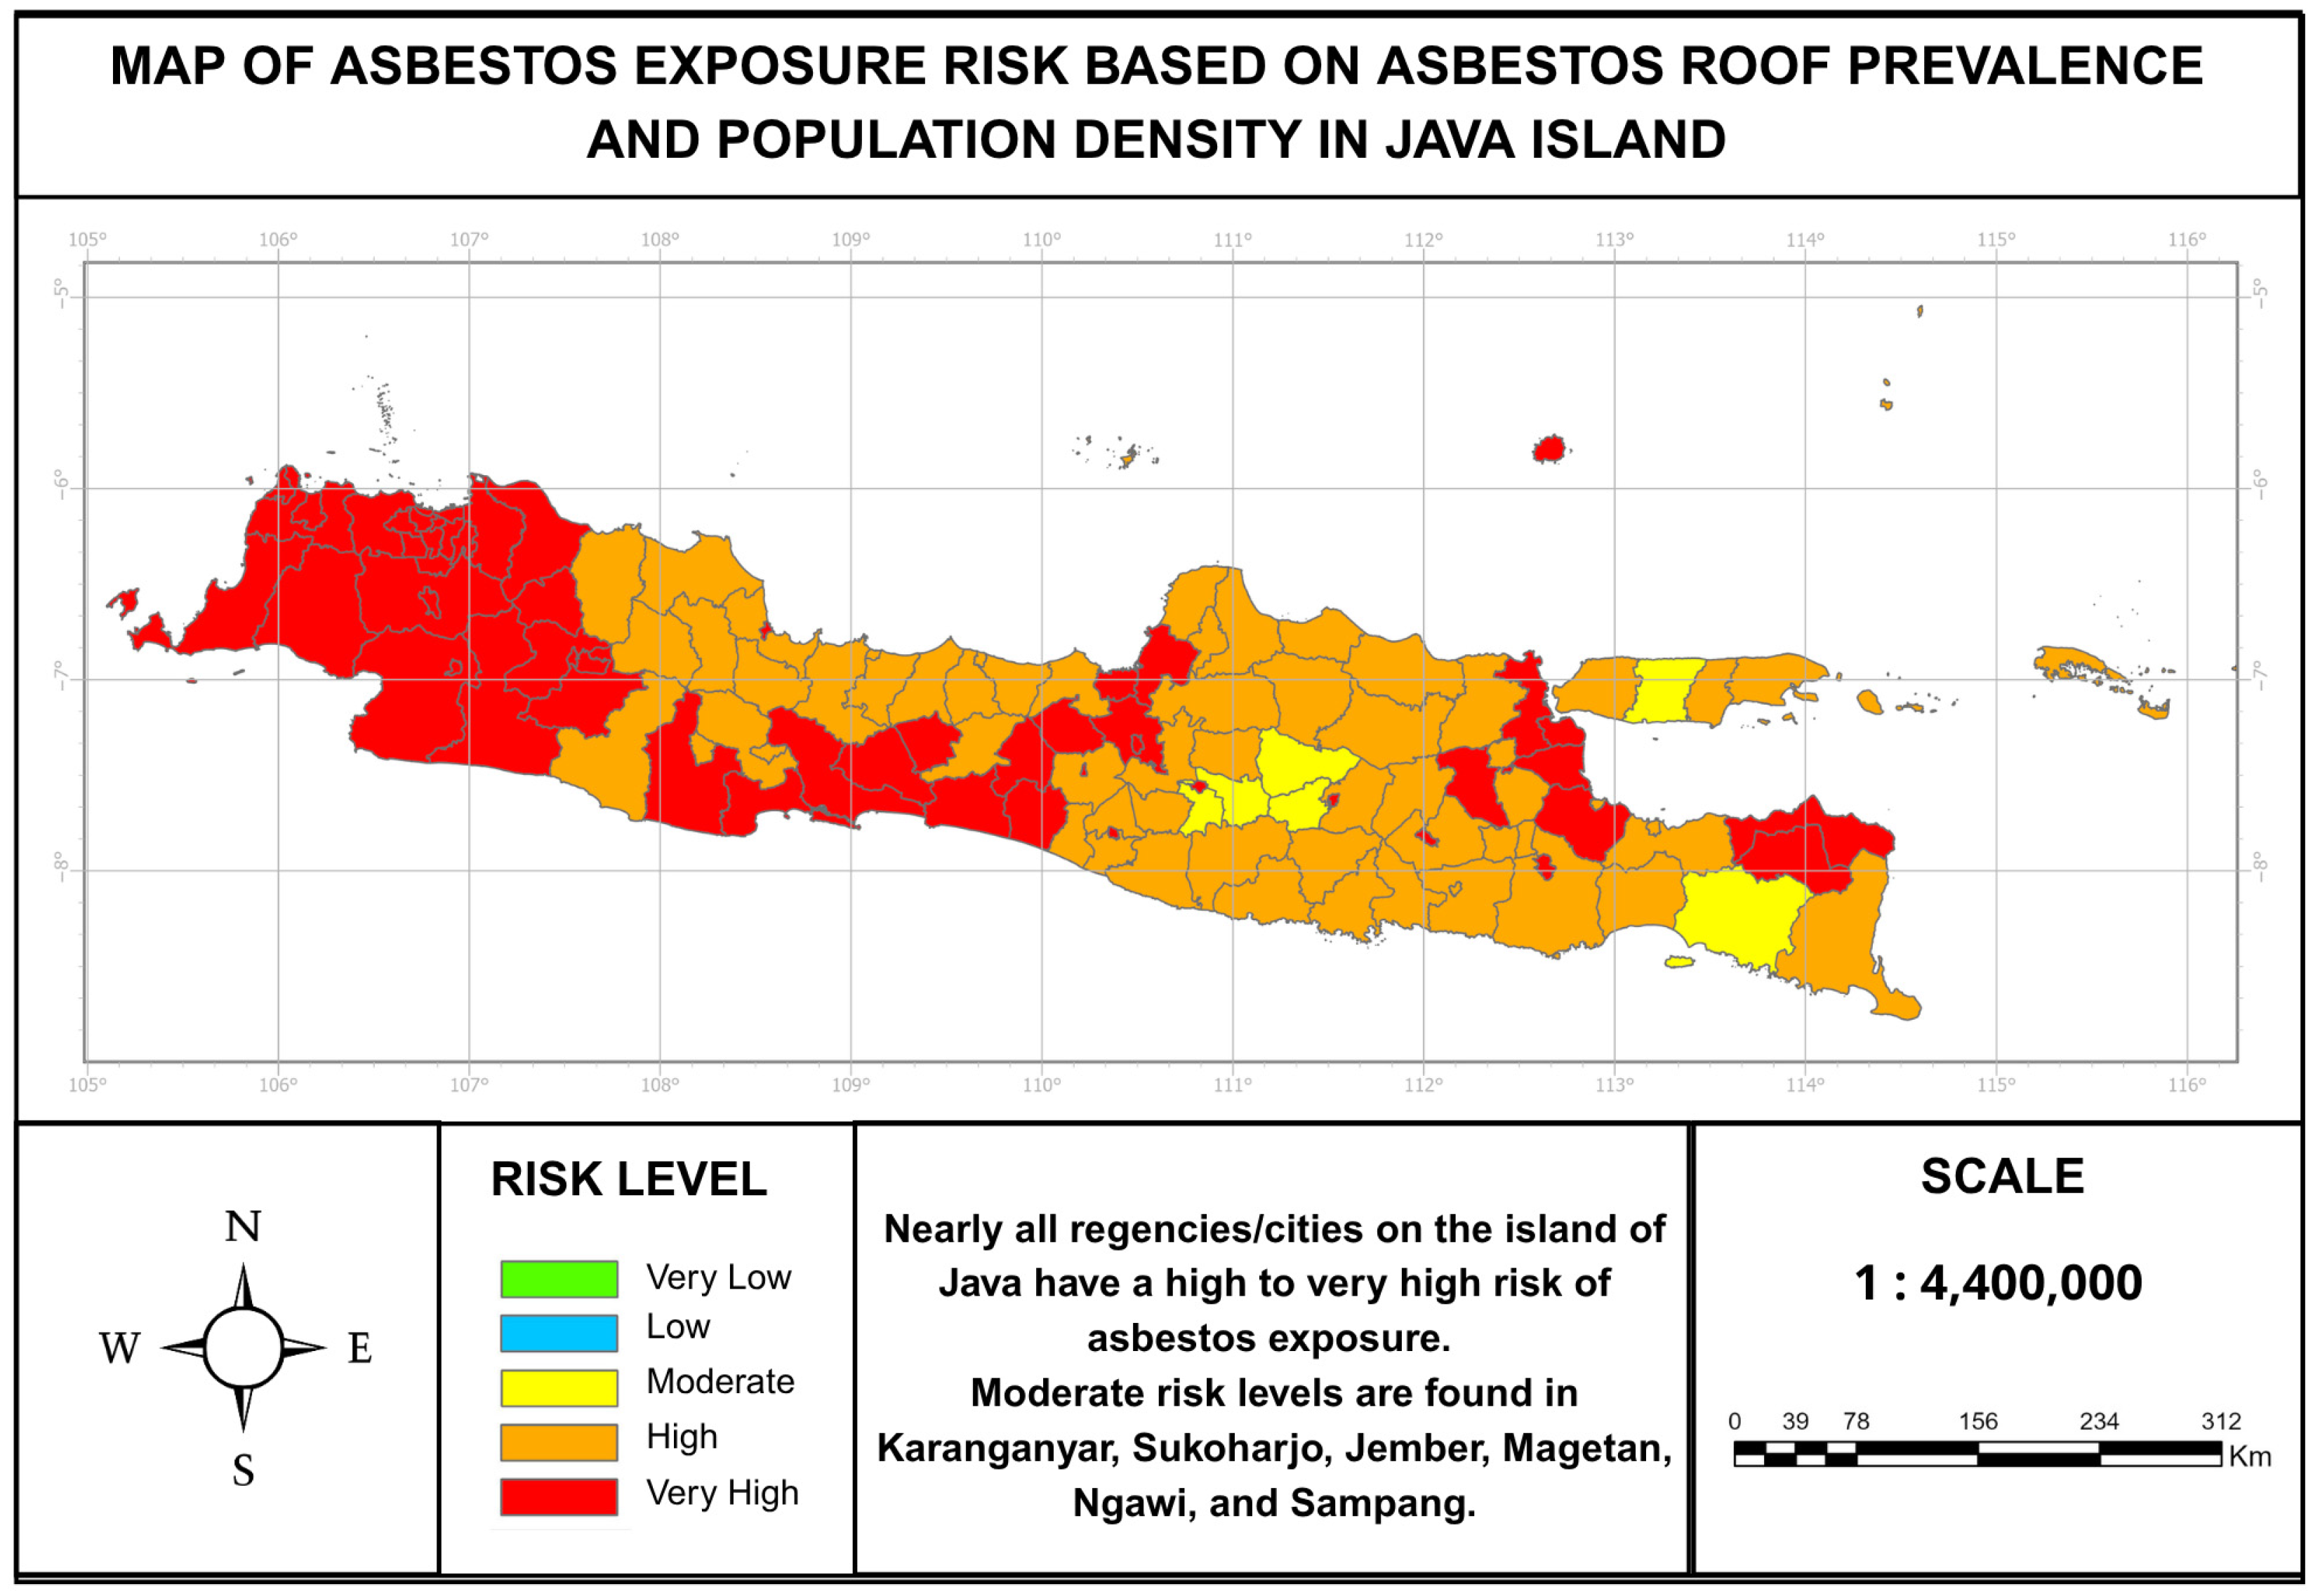
Figure 4 shows the map of asbestos exposure risk based on asbestos roof prevalence level and population density. Notably, more than 50% of districts and municipalities classified as very low or low in asbestos roof prevalence nevertheless demonstrated elevated asbestos exposure risk due to high to very high levels of population density.
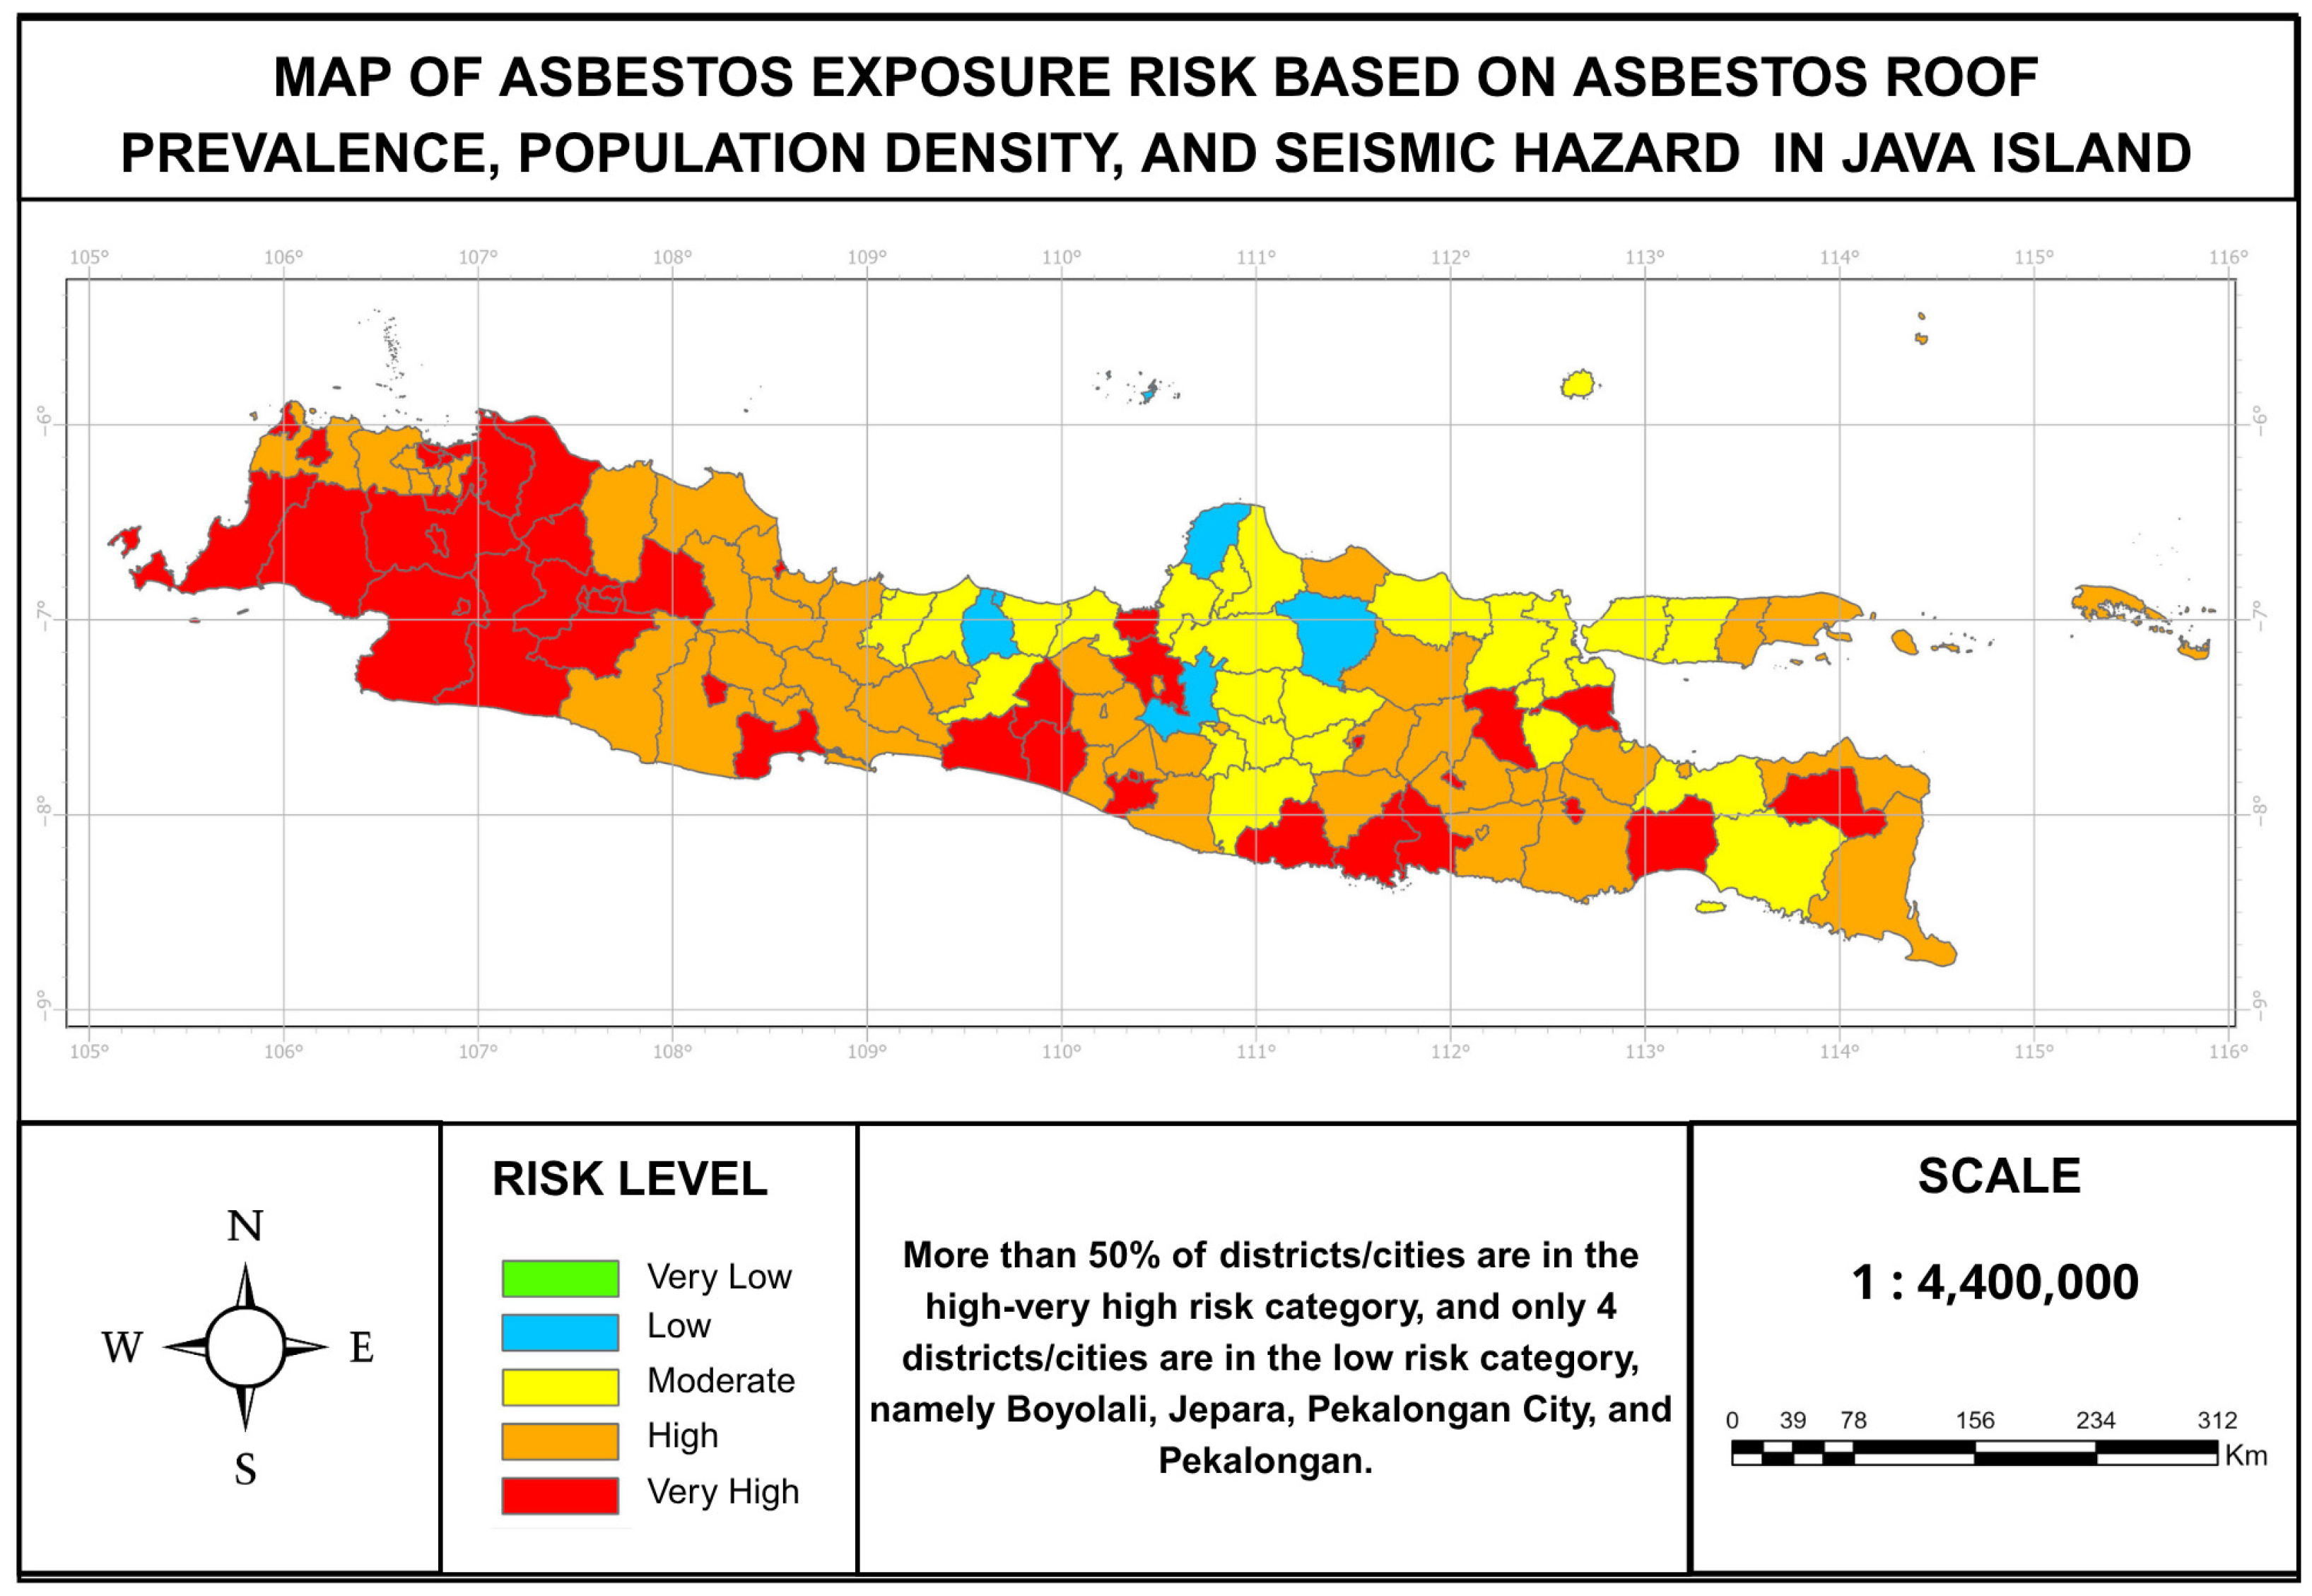
A similar pattern was observed with seismic hazard: the variation across Java amplified the complexity of risk, particularly in the southern coastal regions that are prone to seismic shocks. Integrating asbestos roof prevalence, population density, and seismic hazard, the composite asbestos exposure risk distribution indicated that the majority of districts and municipalities were categorized as high to very high risk, specifically: Very high risk: 43 (36%) districts/municipalities, High risk: 45 (38%) districts/municipalities, Moderate risk: 26 (22%) districts/municipalities, Low risk: 5 (4%) districts/municipalities (
Figure 5). District-level asbestos risk indicators and composite risk classifications across Java are presented in
Table S3.
3.1. Spatial Pattern Analysis and Priority Areas
3.1.1. Densely Populated Metropolitan Corridors
Major cities and peri-urban buffer zones in Greater Jakarta (Jabodetabek) and the Bandung metropolitan region emerge as areas of very high composite risk, despite some having only moderate to high asbestos roof prevalence. These include West Jakarta, Central Jakarta, North Jakarta, Bekasi City, Bogor City, Depok City, Bandung Regency, Bandung City, and Cimahi City. In these locations, extremely high population density substantially amplifies the risk of asbestos exposure and associated public health consequences.
3.1.2. Elevated Asbestos Roofing Cluster
Several districts in East Java stand out for their relatively high prevalence of asbestos roofing, placing them within the very high composite risk category, even though their seismic hazard levels range from moderate to low. Districts with the highest asbestos roof percentages in this cluster include Mojokerto City (≈9.6%), Kediri City (≈9.5%), Malang City (≈8.9%), Jombang (≈8.1%), Sidoarjo (≈7.1%), Madiun City (≈5.4%), Yogyakarta City (≈5.4%), and Bondowoso (≈5.2%). The combination of higher asbestos prevalence with substantial urban or peri-urban populations drives up the composite risk score, even where earthquakes are not the dominant factor.
3.1.3. Southern Coastal Earthquake-Related Cluster
A number of districts with low to moderate asbestos prevalence still fall into the very high composite risk category due to their high seismic hazard potential. Notable examples include Pacitan, Trenggalek, Lumajang, Bantul, Kebumen, and Cianjur. In this cluster, seismic hazard acts as an important disturbance modifier, as earthquake-related structural damage may fracture asbestos-containing materials and increase the potential for fiber release during demolition, debris handling, and cleanup.
3.1.4. Areas with Low Asbestos Roofing Prevalence but High Population Density and Seismic Hazard
There are 35 districts and municipalities where, despite low or very low asbestos roof prevalence, composite asbestos exposure risk escalates to high or very high. This is primarily due to two amplifying factors: high to very high population density and moderate to high seismic hazard. In East Java, they include Malang, Kediri, Blitar, Banyuwangi, and Bojonegoro. Outside of East Java, similar conditions are observed in Kulon Progo, Ciamis, Pamekasan, and Sumenep. Although asbestos roof prevalence is relatively low, exposure risk is elevated due to the interaction of very high population density with moderate-to-high seismic potential.
3.2. Sensitivity Analysis and Robustness of the Risk Classification
An equal-weight arithmetic specification (1:1:1) was used as the reference model for the sensitivity analyses. Alternative weighting, leave-one-variable-out, and threshold scenarios were compared with this reference specification to assess the stability of the constructed index under different modeling assumptions. These analyses were supplementary to, and did not replace, the primary risk matrix classification used for spatial mapping (
Table 2).
3.2.1. Alternative Weighting Analysis
The composite risk classification was generally robust to changes in the relative weighting of the three components. Compared with the equal-weight arithmetic reference specification, 96 of 119 districts (80.7%) retained the same category when asbestos roof prevalence was assigned twice the weight of population density and seismic hazard. All districts remained within one adjacent category, with a Spearman rank correlation of 0.974 and quadratic weighted kappa of 0.856.
When both asbestos roof prevalence and population density were assigned twice the weight of seismic hazard (2:2:1), agreement with the equal-weight arithmetic specification increased to 109 of 119 districts (91.6%), with all districts remaining within one adjacent category (Spearman ρ = 0.974; weighted κ = 0.924). Giving greater weight to seismic hazard (1:1:2) resulted in 93 districts (78.2%) retaining the same category, while all remained within one adjacent category (ρ = 0.955; κ = 0.804). No district shifted by two or more categories under any of the alternative weighting scenarios.
3.2.2. Leave-One-Variable-Out Analysis
Greater variation was observed when individual components were removed from the composite model. The model combining asbestos roof prevalence and population density retained the same risk category for 47 of 119 districts (39.5%; weighted κ = 0.477), although all districts remained within one adjacent reference category.
The asbestos roof prevalence and seismic hazard model showed the lowest exact categorical agreement, with only 11 districts (9.2%) retaining the same category and eight districts shifting by two or more categories (weighted κ = 0.520). In contrast, the population density and seismic hazard model retained the same classification for 41 districts (34.5%), with all districts remaining within one adjacent category (weighted κ = 0.332). These findings indicate that each component contributes to the resulting classification and that removal of individual variables substantially alters the categorical distribution.
Examination of the component distributions showed that population density had limited discriminatory capacity under the predefined thresholds. Of the 119 districts and municipalities, 118 were classified as having very high population density and only one as high population density. By comparison, asbestos roof prevalence was distributed across all five categories, while seismic hazard was distributed across four categories. This concentration of population density scores indicates that the predefined density thresholds provide limited differentiation within the highly populated Java context.
3.2.3. Threshold Sensitivity Analysis
The classifications were highly robust to moderate changes in the predefined asbestos roof and population density thresholds. When all thresholds were reduced by 15%, 114 of 119 districts (95.8%) retained their reference category, with a weighted kappa of 0.961. When thresholds were increased by 15%, 106 districts (89.1%) remained in the same category (κ = 0.891). All districts remained within one adjacent category under both scenarios, and no district shifted by two or more categories. Spearman correlations between the reference and alternative composite scores were 0.977 and 0.959 for the −15% and +15% threshold scenarios, respectively.
3.2.4. Distribution-Based Quintile Analysis
A larger difference was observed when the predefined thresholds were replaced by empirical quintiles derived from the Java district-level distributions. The quintile cut-points for asbestos roof prevalence were 1.616%, 3.032%, 6.470%, and 11.720%, while those for population density were 724.6, 1003.8, 1336.0, and 4985.8 persons/km2.
Under the quintile-based model, 53 of 119 districts (44.5%) remained in the same risk category as the reference model, while 98 districts (82.4%) remained within one adjacent category. Twenty-one districts shifted by two or more categories. Nevertheless, the composite scores remained positively correlated with the reference model (Spearman ρ = 0.800), although categorical agreement was moderate (weighted κ = 0.530).
These results indicate that the model is relatively stable under moderate variations in weighting and predefined thresholds but is more sensitive to substantial changes in the classification framework, particularly when population density is recalibrated to the distribution observed specifically within Java.
3.3. Quantification and Drivers of Spatial Hotspot Patterns
The four hotspot patterns differed in their geographic extent and component structure. The densely populated metropolitan corridor included nine districts/municipalities (7.6% of the 119 study areas), while the elevated asbestos roofing cluster included eight (6.7%) and the southern coastal earthquake-related cluster included six (5.0%). Using the predefined criteria of low or very low asbestos roof prevalence, high or very high population density, moderate-to-high seismic hazard, and an overall high or very high risk classification, 35 districts (29.4%) were identified in the low asbestos/high density and seismic group. Because the groups were not mutually exclusive, these percentages should not be summed.
Across all districts, the composite risk score showed a strong positive correlation with asbestos roof prevalence score (Spearman ρ = 0.823, p < 0.001) and a moderate positive correlation with seismic hazard score (ρ = 0.632, p < 0.001). The categorical population density score was not significantly correlated with variation in composite risk (ρ = −0.101, p = 0.272), reflecting the very limited variation in this indicator: 118 of 119 districts were categorized as having very high population density. However, continuous population density remained positively associated with the composite score (ρ = 0.365, p < 0.001).
Component-contribution analysis demonstrated different risk profiles among the hotspot groups. In the metropolitan corridor, asbestos roof prevalence, population density, and seismic hazard contributed an average of 35.3%, 38.8%, and 25.9% to the composite score, respectively, indicating codominance of asbestos prevalence and population concentration. In the elevated asbestos roofing group, the corresponding contributions were 27.3%, 45.5%, and 27.3%. In the southern coastal earthquake-related group, the relative contribution of seismic hazard increased to 34.9%, compared with 43.7% for population density and 21.4% for asbestos prevalence. Among districts with low asbestos prevalence but elevated population density and seismic hazard, population density contributed 49.1%, seismic hazard 31.3%, and asbestos prevalence 19.6% (
Table 3).
4. Discussion
4.1. Asbestos Exposure Risk in Java
This study demonstrates substantial geographic heterogeneity in potential asbestos exposure across Java, arising from the interaction of residential asbestos roof prevalence, population density, and seismic hazard. Major metropolitan areas, including Jakarta, Surabaya, and Semarang, were identified as priority areas because high asbestos use coincides with very dense populations. In Jakarta, asbestos roofing exceeds 50% in several municipalities, considerably above the national estimate of approximately 8–10% [
18]. Conversely, districts such as Cianjur and Pacitan achieve high composite risk classifications primarily because seismic hazard increases the likelihood that existing asbestos-containing materials may be damaged during earthquakes [
17].
The driver and sensitivity analyses further clarify these patterns. Asbestos roof prevalence contributed most strongly to variation in the composite score, while seismic hazard provided additional spatial differentiation. Population density remained important in determining the number of people potentially affected, but its discriminatory value was limited because 118 of 119 districts were classified as having very high density under the original thresholds. The sensitivity analyses of the alternative arithmetic specification showed relatively stable classifications under moderate weighting and threshold changes, but classifications changed more substantially when population density was recalibrated using Java-specific quintiles. These findings support the usefulness of the model as a screening tool while also indicating the need for local recalibration of population density categories.
The findings are particularly relevant because Indonesia continues to use asbestos-containing products while many countries have implemented comprehensive bans [
9,
23]. Continued incorporation of asbestos into the built environment, combined with the long latency of asbestos-related diseases, may prolong future disease burden even if exposure controls are strengthened. Indonesia therefore faces the dual challenge of preventing additional asbestos use while managing a substantial existing stock of asbestos-containing materials.
4.2. Seismic Hazard and Post-Disaster Asbestos Exposure
Java’s seismic setting provides an important rationale for incorporating earthquake hazard into asbestos risk assessment. The island is affected by the Sunda subduction zone, active crustal faults, and intraslab earthquake sources, resulting in spatially variable shaking potential across coastal, inland, and metropolitan districts. Seismic hazard should, however, be interpreted as a modifier of material disturbance rather than a direct measure of asbestos exposure [
12,
13,
24].
The principal exposure pathway may extend beyond the initial structural damage. Earthquake-induced cracking or collapse of asbestos-cement sheets can be followed by bulldozing, mechanical crushing, dry sweeping, loading, transport, uncontrolled demolition, and open dumping, all of which may further fragment asbestos-containing materials and disperse fibers. Residents, emergency responders, construction workers, volunteers, and waste handlers may therefore experience increased exposure during cleanup and reconstruction. The 2018 Lombok earthquake illustrated the large quantities of damaged asbestos-cement roofing that can enter post-disaster debris streams [
15], while international evidence has similarly identified debris handling as an important source of post disaster asbestos exposure [
16,
25,
26].
The present study cannot quantify a direct relationship between Modified Mercalli Intensity and airborne asbestos concentration. Fiber release depends not only on shaking intensity but also on the quantity, age, condition, and weathering of asbestos-containing materials, structural failure patterns, cleanup practices, rainfall, wind, and duration of disturbance. Accordingly, the seismic variable identifies areas where structural damage may increase the likelihood of asbestos release, but it should not be interpreted as a predictor of measured fiber concentration or individual exposure.
4.3. International Experience and Relevance to Indonesia
Experience from Japan, South Korea, and Australia demonstrates the value of combining asbestos bans with building inventories, risk mapping, controlled removal, waste management systems, and long-term management of legacy asbestos [
27,
28,
29]. South Korea, for example, incorporated surveys and asbestos mapping of public buildings into its control strategy, while Australia has developed coordinated national approaches to legacy asbestos management and spatial identification of asbestos-containing buildings.
However, these models were developed in socioeconomic and regulatory environments that differ considerably from Indonesia. Japan, South Korea, and Australia have comparatively established building control systems, occupational health regulation, specialized asbestos removal capacity, and hazardous waste infrastructure. Indonesia continues to use asbestos and has substantial informal construction, mixed material housing, uneven regulatory enforcement, limited building-level inventories, and variable waste management capacity. Frequent earthquakes, floods, landslides, fires, and other disasters further complicate asbestos management.
Thus, international experience should be adapted rather than directly replicated. Feasible priorities for Indonesia include clear institutional responsibility, phased asbestos inventories, prioritization of schools and health facilities, safe renovation and demolition procedures, controlled waste disposal, training of workers and emergency responders, and transparent risk communication. A district-based approach may be more practical than attempting uniform nationwide implementation from the outset.
4.4. Implications for Risk Management
The risk map can support differentiated interventions according to local risk profiles. In densely populated urban areas with substantial asbestos use, priorities should include building-level asbestos inventories, particularly for schools, health facilities, government buildings, markets, and densely occupied housing. Renovation and demolition activities should require prior identification of asbestos-containing materials, measures to minimize cutting and breakage, wet handling where appropriate, worker protection, and documented transport and disposal.
In earthquake-prone districts, asbestos management should be incorporated into disaster preparedness plans before an event occurs. Disaster management agencies should establish procedures for identifying and segregating asbestos-containing debris, designate temporary controlled storage areas, prohibit uncontrolled crushing and dumping, and ensure safe transport and disposal. Emergency responders, demolition workers, volunteers, and waste handlers should receive task-specific training and appropriate respiratory protection [
17].
Health-sector interventions should focus on feasible surveillance rather than population-wide screening. Clinicians in priority areas should be able to document occupational and environmental exposure histories and recognize clinical and radiological features of asbestos-related disease. Sentinel surveillance could initially target workers in asbestos manufacturing, construction, demolition, waste handling, and disaster cleanup, as well as communities near asbestos industries or major debris disposal sites. At the policy level, stronger product labeling, predemolition asbestos assessment, minimum debris management standards, and phased replacement of damaged asbestos roofing could provide practical intermediate steps toward long-term asbestos elimination.
4.5. Robustness, Limitations, and Future Research
The sensitivity analyses showed that the overall classification was relatively robust to moderate changes in weighting and threshold boundaries. Between 78.2% and 91.6% of districts retained the same category under alternative weighting schemes, and 89.1–95.8% remained unchanged when thresholds were shifted by ±15%. Nevertheless, greater instability emerged when population density was reclassified using Java-specific quintiles, indicating that the population density component is an important source of model uncertainty.
Several additional limitations should be considered. First, asbestos data were limited to residential roofing and therefore did not capture asbestos-containing materials in industrial, commercial, public, transport, or informal structures. Material age, deterioration, friability, and previous damage were also unavailable. Second, population density was based on residential population and did not account for commuting, temporary workers, migration, tourism, or post-disaster displacement. Third, the seismic component represented mapped hazard rather than a full probabilistic seismic risk model incorporating recurrence probability, site amplification, building fragility, or expected debris generation. Finally, the sensitivity analyses assessed internal model stability but did not constitute external validation against measured airborne fibers, detailed building inventories, or health outcomes.
The scarcity of empirical environmental and disease data is particularly important. Indonesia does not currently have comprehensive population-based mesothelioma surveillance, and available evidence is derived mainly from individual case reports and occupational or hospital-based studies. Consequently, the true national burden of mesothelioma and other asbestos-related diseases remains uncertain. Similarly, systematic ambient asbestos fiber measurements across Java are not available at a resolution suitable for validating the present district-level map. These gaps should be considered when interpreting the current findings.
Future studies should therefore combine geocoded building-level asbestos inventories, field verification or remote sensing, mobile population data, probabilistic seismic hazard models, and direct airborne fiber measurements. Post-disaster research should quantify fiber concentrations during demolition, crushing, transport, temporary storage, and disposal. Linking spatial asbestos risk indicators with mesothelioma, lung cancer, pleural disease, and asbestosis surveillance would provide an important external validation of the model, while recognizing the long latency of asbestos-related disease.
5. Conclusions
This study introduces a district-level semi-quantitative GIS framework that sequentially integrates asbestos roof prevalence, population density, and seismic hazard using a two-stage risk matrix approach to support spatial prioritization of potential asbestos exposure in Java. Applied to all 119 districts and municipalities, the framework identified 43 (36%) areas as very high risk and 45 (38%) as high risk. Major metropolitan corridors showed elevated risk where substantial asbestos roof prevalence coincided with very high population density, while several southern and inland districts gained priority because of higher seismic hazard.
The findings demonstrate that asbestos-related public health risk in Java is spatially heterogeneous and cannot be adequately characterized by asbestos use alone. The sequential integration of infrastructure, population concentration, and seismic disturbance provides a practical screening approach for identifying areas that may require greater attention for asbestos control, building inventories, disaster preparedness, and health surveillance. Sensitivity analyses further indicated that the classification was relatively stable under moderate changes in weighting and threshold assumptions, although population density categorization remained an important source of uncertainty.
The resulting classifications should therefore be interpreted as a screening and prioritization framework, rather than as direct measurements of airborne asbestos concentrations or individual exposure and disease risk. Future studies incorporating building-level asbestos inventories, population mobility, probabilistic seismic hazard modeling, environmental fiber measurements, and asbestos-related disease surveillance are needed to externally validate and refine the framework.