Efficacy and Safety of Oral Creatine Supplementation in Patients with Heart Failure: A PRISMA 2020 Systematic Review and Narrative Evidence Synthesis



Highlights
- Heart failure is frequently accompanied by exercise intolerance, skeletal-muscle dysfunction, and impaired quality of life; accessible adjunctive strategies that target peripheral muscle function are therefore of potential public health interest.
- Oral creatine is inexpensive and widely available, making a rigorous appraisal of its benefits and safety important to prevent unsupported use in a clinically vulnerable population.
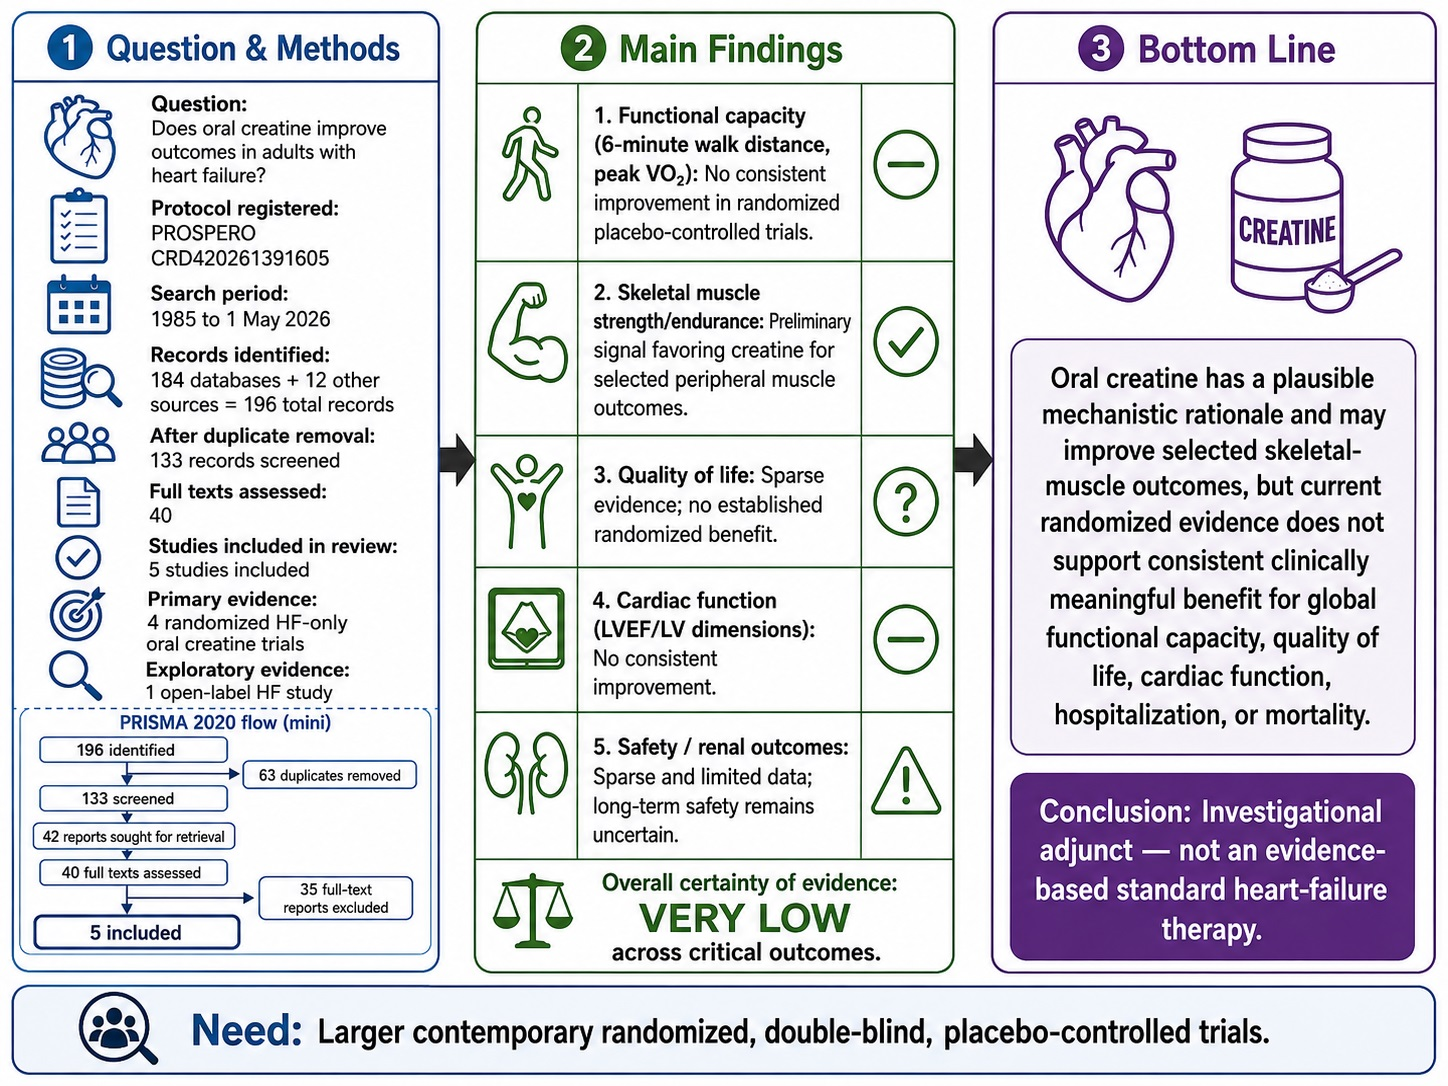
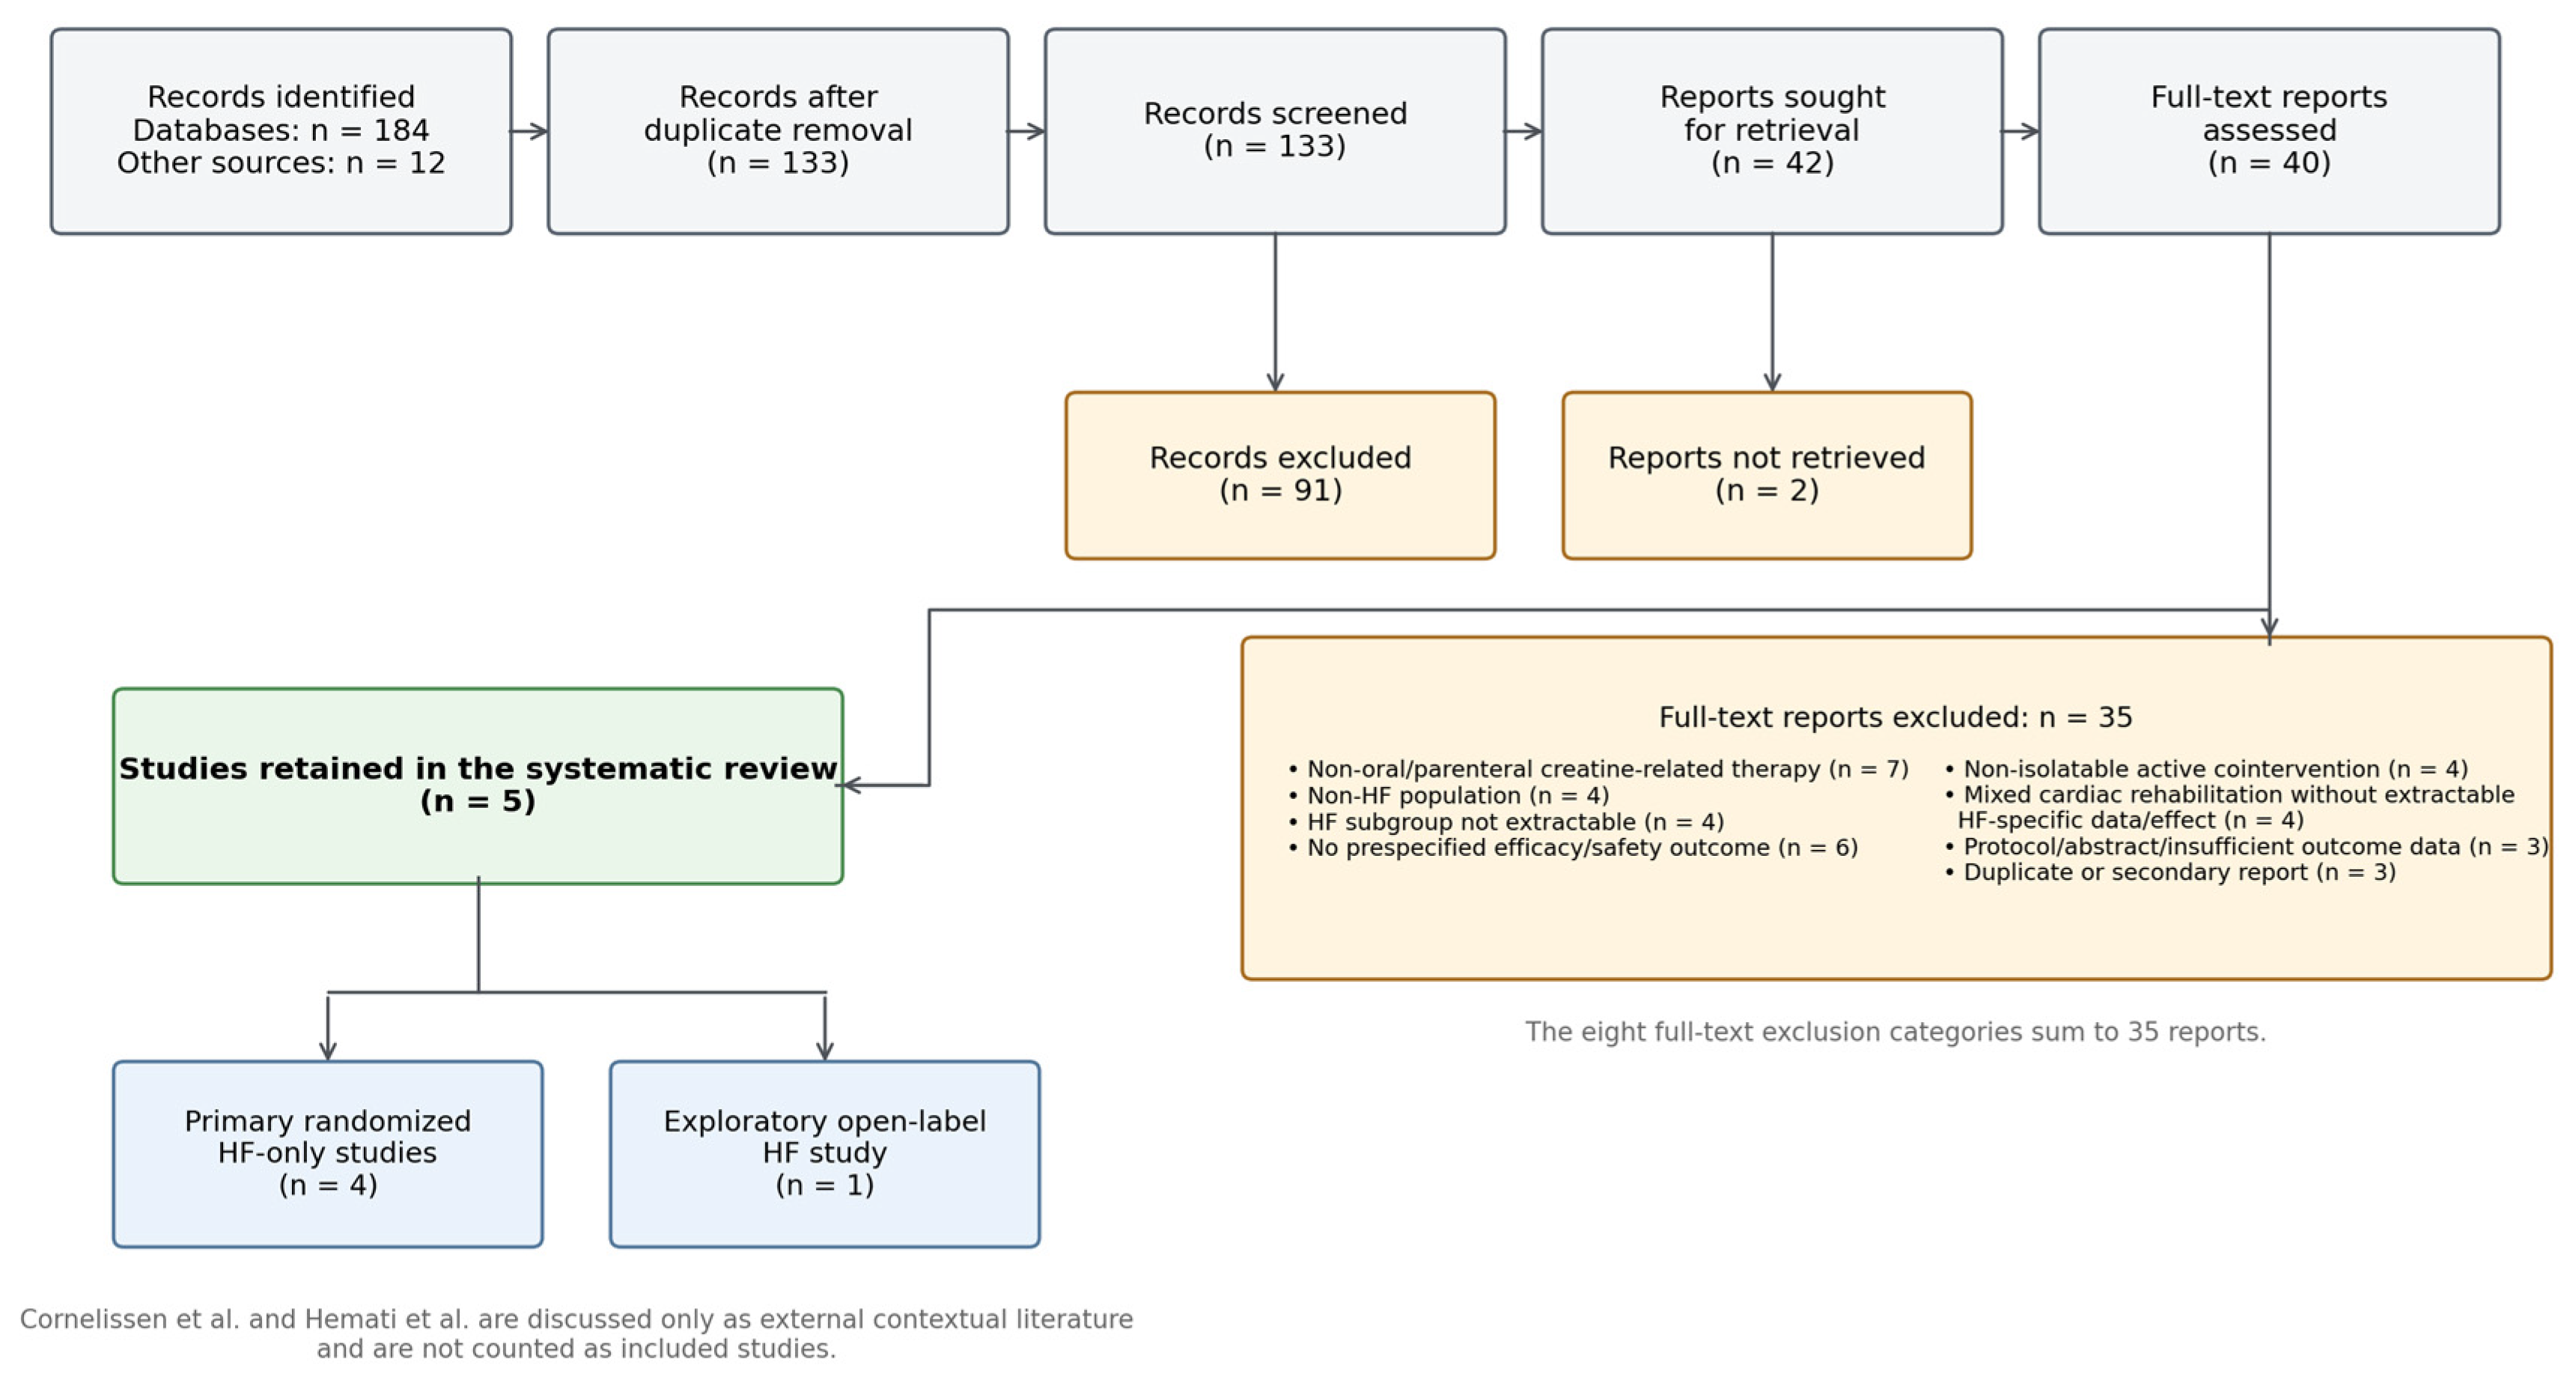
- Four randomized heart-failure-only trials form the primary causal evidence base; one additional heart-failure open-label study is retained as exploratory evidence, while mixed-population or mechanistic reports are discussed only as external context.
- Current evidence does not show a consistent benefit for peak oxygen uptake, 6-min walk distance, quality of life, cardiac systolic function, hospitalization, or mortality; certainty is very low across the evaluated critical outcomes.
- Oral creatine should currently be regarded as an investigational adjunct rather than standard evidence-based therapy for heart failure.
- Future trials should be adequately powered, double-blind, and placebo-controlled; include patients receiving contemporary guideline-directed therapy; and prioritize patient-centered functional outcomes, together with systematic renal and adverse-event surveillance.
Abstract
1. Introduction
2. Materials and Methods
3. Results
4. Discussion
5. Limitations
6. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
References
- McDonagh, T.A.; Metra, M.; Adamo, M.; Gardner, R.S.; Baumbach, A.; Böhm, M.; Burri, H.; Butler, J.; Čelutkienė, J.; Chioncel, O.; et al. 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur. Heart J. 2021, 42, 3599–3726. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McDonagh, T.A.; Metra, M.; Adamo, M.; Gardner, R.S.; Baumbach, A.; Böhm, M.; Burri, H.; Butler, J.; Čelutkienė, J.; Chioncel, O.; et al. 2023 Focused Update of the 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur. Heart J. 2023, 44, 3627–3639. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heidenreich, P.A.; Bozkurt, B.; Aguilar, D.; Allen, L.A.; Byun, J.J.; Colvin, M.M.; Deswal, A.; Drazner, M.H.; Dunlay, S.M.; Evers, L.R.; et al. 2022 AHA/ACC/HFSA guideline for the management of heart failure. J. Am. Coll. Cardiol. 2022, 79, e263–e421. [Google Scholar] [CrossRef] [Scilit]
- Bozkurt, B.; Coats, A.J.; Tsutsui, H.; Abdelhamid, M.; Adamopoulos, S.; Albert, N.; Anker, S.D.; Atherton, J.; Böhm, M.; Butler, J.; et al. Universal definition and classification of heart failure. J. Card. Fail. 2021, 27, 387–413. [Google Scholar] [CrossRef] [Scilit]
- O’cOnnor, C.M.; Whellan, D.J.; Lee, K.L.; Keteyian, S.J.; Cooper, L.S.; Ellis, S.J.; Leifer, E.S.; Kraus, W.E.; Kitzman, D.W.; Blumenthal, J.A.; et al. Efficacy and safety of exercise training in patients with chronic heart failure: HF-ACTION randomized controlled trial. JAMA 2009, 301, 1439–1450. [Google Scholar] [CrossRef] [Scilit]
- Flynn, K.E.; Piña, I.L.; Whellan, D.J.; Lin, L.; Blumenthal, J.A.; Ellis, S.J.; Fine, L.J.; Howlett, J.G.; Keteyian, S.J.; Kitzman, D.W.; et al. Effects of exercise training on health status in patients with chronic heart failure: HF-ACTION randomized controlled trial. JAMA 2009, 301, 1451–1459. [Google Scholar] [CrossRef] [Scilit]
- Taylor, R.S.; Long, L.; Mordi, I.R.; Madsen, M.T.; Davies, E.J.; Dalal, H.; Rees, K.; Singh, S.J.; Gluud, C.; Zwisler, A.-D. Exercise-based rehabilitation for heart failure: Cochrane systematic review, meta-analysis, and trial sequential analysis. JACC Heart Fail. 2019, 7, 691–705. [Google Scholar] [CrossRef] [Scilit]
- Sagar, V.A.; Davies, E.J.; Briscoe, S.; Coats, A.J.S.; Dalal, H.M.; Lough, F.; Rees, K.; Singh, S.; Taylor, R.S. Exercise-based rehabilitation for heart failure: Systematic review and meta-analysis. Open Heart 2015, 2, e000163. [Google Scholar] [CrossRef] [Scilit]
- Kinugawa, S.; Takada, S.; Matsushima, S.; Okita, K.; Tsutsui, H. Skeletal muscle abnormalities in heart failure. Int. Heart J. 2015, 56, 475–484. [Google Scholar] [CrossRef] [Scilit]
- Del Buono, M.G.; Arena, R.; Borlaug, B.A.; Carbone, S.; Canada, J.M.; Kirkman, D.L.; Garten, R.; Rodriguez-Miguelez, P.; Guazzi, M.; Lavie, C.J.; et al. Exercise intolerance in patients with heart failure: JACC state-of-the-art review. J. Am. Coll. Cardiol. 2019, 73, 2209–2225. [Google Scholar] [CrossRef] [Scilit]
- Springer, J.; Springer, J.I.; Anker, S.D. Muscle wasting and sarcopenia in heart failure and beyond: Update 2017. ESC Heart Fail. 2017, 4, 492–498. [Google Scholar] [CrossRef] [Scilit]
- Bielecka-Dabrowa, A.; Ebner, N.; dos Santos, M.R.; Ishida, J.; Hasenfuss, G.; von Haehling, S. Cachexia, muscle wasting, and frailty in cardiovascular disease. Eur. J. Heart Fail. 2020, 22, 2314–2326. [Google Scholar] [CrossRef] [Scilit]
- Takada, S.; Hirabayashi, K.; Kinugawa, S. Treatments for skeletal muscle abnormalities in heart failure. Am. J. Physiol. Heart Circ. Physiol. 2022, 322, H563–H575. [Google Scholar] [CrossRef] [Scilit]
- Coats, A.J.; Clark, A.L.; Piepoli, M.; Volterrani, M.; Poole-Wilson, P.A. Symptoms and quality of life in heart failure: The muscle hypothesis. Br. Heart J. 1994, 72, S36–S39. [Google Scholar] [CrossRef] [Scilit]
- Coats, A.J. The muscle hypothesis of chronic heart failure. J. Mol. Cell. Cardiol. 1996, 28, 2255–2262. [Google Scholar] [CrossRef] [Scilit]
- Mancini, D.M.; Walter, G.; Reichek, N.; Lenkinski, R.; McCully, K.K.; Mullen, J.L.; Wilson, J.R. Contribution of skeletal muscle atrophy to exercise intolerance and altered muscle metabolism in heart failure. Circulation 1992, 85, 1364–1373. [Google Scholar] [CrossRef] [Scilit]
- Curcio, F.; Testa, G.; Liguori, I.; Papillo, M.; Flocco, V.; Panicara, V.; Galizia, G.; Della-Morte, D.; Gargiulo, G.; Cacciatore, F.; et al. Sarcopenia and heart failure. Nutrients 2020, 12, 211. [Google Scholar] [CrossRef] [Scilit]
- Prokopidis, K.; Isanejad, M.; Akpan, A.; Stefil, M.; Tajik, B.; Giannos, P.; Venturelli, M.; Sankaranarayanan, R. Exercise and nutritional interventions on sarcopenia and frailty in heart failure: A narrative review of systematic reviews and meta-analyses. ESC Heart Fail. 2022, 9, 2787–2803. [Google Scholar] [CrossRef] [Scilit]
- Anker, S.D.; Ponikowski, P.; Varney, S.; Chua, T.P.; Clark, A.L.; Webb-Peploe, K.M.; Harrington, D.; Kox, W.J.; Poole-Wilson, P.A.; Coats, A.J. Wasting as independent risk factor for mortality in chronic heart failure. Lancet 1997, 349, 1050–1053. [Google Scholar] [CrossRef] [Scilit]
- von Haehling, S.; Ebner, N.; dos Santos, M.R.; Springer, J.; Anker, S.D. Muscle wasting and cachexia in heart failure: Mechanisms and therapies. Nat. Rev. Cardiol. 2017, 14, 323–341. [Google Scholar] [CrossRef] [Scilit]
- von Haehling, S. Muscle wasting and sarcopenia in heart failure: A brief overview of the current literature. ESC Heart Fail. 2018, 5, 1074–1082. [Google Scholar] [CrossRef] [Scilit]
- Valentova, M.; von Haehling, S.; Anker, S.D. Cardiac cachexia revisited: The role of wasting in heart failure. Heart Fail. Clin. 2020, 16, 61–69. [Google Scholar] [CrossRef] [Scilit]
- Wyss, M.; Kaddurah-Daouk, R. Creatine and creatinine metabolism. Physiol. Rev. 2000, 80, 1107–1213. [Google Scholar] [CrossRef] [Scilit]
- Harris, R.C.; Söderlund, K.; Hultman, E. Elevation of creatine in resting and exercised muscle of normal subjects by creatine supplementation. Clin. Sci. 1992, 83, 367–374. [Google Scholar] [CrossRef] [Scilit]
- Greenhaff, P.L.; Bodin, K.; Söderlund, K.; Hultman, E. Effect of oral creatine supplementation on skeletal muscle phosphocreatine resynthesis. Am. J. Physiol. 1994, 266, E725–E730. [Google Scholar] [CrossRef] [Scilit]
- Sahlin, K.; Harris, R.C. The creatine kinase reaction: A simple reaction with functional complexity. Amino Acids 2011, 40, 1363–1367. [Google Scholar] [CrossRef] [Scilit]
- Wallimann, T.; Tokarska-Schlattner, M.; Schlattner, U. The creatine kinase system and pleiotropic effects of creatine. Amino Acids 2011, 40, 1271–1296. [Google Scholar] [CrossRef] [Scilit]
- Kreider, R.B.; Kalman, D.S.; Antonio, J.; Ziegenfuss, T.N.; Wildman, R.; Collins, R.; Candow, D.G.; Kleiner, S.M.; Almada, A.L.; Lopez, H.L. International Society of Sports Nutrition position stand: Safety and efficacy of creatine supplementation in exercise, sport, and medicine. J. Int. Soc. Sports Nutr. 2017, 14, 18. [Google Scholar] [CrossRef] [Scilit]
- Devries, M.C.; Phillips, S.M. Creatine supplementation during resistance training in older adults-a meta-analysis. Med. Sci. Sports Exerc. 2014, 46, 1194–1203. [Google Scholar] [CrossRef] [Scilit]
- Lanhers, C.; Pereira, B.; Naughton, G.; Trousselard, M.; Lesage, F.X.; Dutheil, F. Creatine supplementation and lower limb strength performance: A systematic review and meta-analyses. Sports Med. 2015, 45, 1285–1294. [Google Scholar] [CrossRef] [Scilit]
- Lanhers, C.; Pereira, B.; Naughton, G.; Trousselard, M.; Lesage, F.X.; Dutheil, F. Creatine supplementation and upper limb strength performance: A systematic review and meta-analysis. Sports Med. 2017, 47, 163–173. [Google Scholar] [CrossRef] [Scilit]
- Chilibeck, P.D.; Kaviani, M.; Candow, D.G.; Zello, G.A. Effect of creatine supplementation during resistance training on lean tissue mass and muscular strength in older adults: A meta-analysis. Open Access J. Sports Med. 2017, 8, 213–226. [Google Scholar] [CrossRef] [Scilit]
- Harmon, K.K.; Stout, J.R.; Fukuda, D.H.; Pabian, P.S.; Rawson, E.S.; Stock, M.S. The application of creatine supplementation in medical rehabilitation. Nutrients 2021, 13, 1825. [Google Scholar] [CrossRef] [Scilit]
- Candow, D.G.; Forbes, S.C.; Kirk, B.; Duque, G. Current evidence and possible future applications of creatine supplementation for older adults. Nutrients 2021, 13, 745. [Google Scholar] [CrossRef] [Scilit]
- Kreider, R.B.; Stout, J.R. Creatine in health and disease. Nutrients 2021, 13, 447. [Google Scholar] [CrossRef] [Scilit]
- Wilkinson, T.J.; Lemmey, A.B.; Jones, J.G.; Sheikh, F.; Ahmad, Y.A.; Chitale, S.; Maddison, P.J.; O’BRien, T.D. Can creatine supplementation improve body composition and objective physical function in rheumatoid arthritis patients? A randomized controlled trial. Arthritis Care Res. 2016, 68, 729–737. [Google Scholar] [CrossRef] [Scilit]
- Balestrino, M. Role of creatine in the heart: Health and disease. Nutrients 2021, 13, 1215. [Google Scholar] [CrossRef] [Scilit]
- Del Franco, A.; Ambrosio, G.; Baroncelli, L.; Pizzorusso, T.; Barison, A.; Olivotto, I.; Recchia, F.A.; Lombardi, C.M.; Metra, M.; Chen, Y.F.F.; et al. Creatine deficiency and heart failure. Heart Fail. Rev. 2022, 27, 1605–1616. [Google Scholar] [CrossRef] [Scilit]
- Neubauer, S. The failing heart—An engine out of fuel. N. Engl. J. Med. 2007, 356, 1140–1151. [Google Scholar] [CrossRef] [Scilit]
- Nascimben, L.; Ingwall, J.S.; Pauletto, P.; Friedrich, J.; Gwathmey, J.K.; Saks, V.; Pessina, A.C.; Allen, P. Creatine kinase system in failing and nonfailing human myocardium. Circulation 1996, 94, 1894–1901. [Google Scholar] [CrossRef] [Scilit]
- Neubauer, S.; Horn, M.; Cramer, M.; Harre, K.; Newell, J.B.; Peters, W.; Pabst, T.; Ertl, G.; Hahn, D.; Ingwall, J.S.; et al. Myocardial phosphocreatine-to-ATP ratio is a predictor of mortality in patients with dilated cardiomyopathy. Circulation 1997, 96, 2190–2196. [Google Scholar] [CrossRef] [Scilit]
- Ingwall, J.S. Energy metabolism in heart failure and remodelling. Cardiovasc. Res. 2009, 81, 412–419. [Google Scholar] [CrossRef] [Scilit]
- Abshire, M.; Xu, J.; Baptiste, D.; Almansa, J.R.; Xu, J.; Cummings, A.; Andrews, M.J.; Himmelfarb, C.D. Nutritional interventions in heart failure: A systematic review of the literature. J. Card. Fail. 2015, 21, 989–999. [Google Scholar] [CrossRef] [Scilit]
- Sciatti, E.; Lombardi, C.; Ravera, A.; Vizzardi, E.; Bonadei, I.; Carubelli, V.; Gorga, E.; Metra, M. Nutritional deficiency in patients with heart failure. Nutrients 2016, 8, 442. [Google Scholar] [CrossRef] [Scilit]
- McKeag, N.A.; McKinley, M.C.; Harbinson, M.T.; Noad, R.L.; Dixon, L.H.; McGinty, A.; Neville, C.E.; Woodside, J.V.; McKeown, P.P. The effect of multiple micronutrient supplementation on left ventricular ejection fraction in patients with chronic stable heart failure: A randomized, placebo controlled trial. JACC Heart Fail. 2014, 2, 308–317. [Google Scholar] [CrossRef] [Scilit]
- Jain, A.; Mehta, R.; Al-Ani, M.; Hill, J.A.; Winchester, D.E. Determining the role of thiamine deficiency in systolic heart failure: A meta-analysis and systematic review. J. Card. Fail. 2015, 21, 1000–1007. [Google Scholar] [CrossRef] [Scilit]
- Mortensen, S.A.; Rosenfeldt, F.; Kumar, A.; Dolliner, P.; Filipiak, K.J.; Pella, D.; Alehagen, U.; Steurer, G.; Littarru, G.P.; Q-SYMBIO Study Investigators. The effect of coenzyme Q10 on morbidity and mortality in chronic heart failure: Results from Q-SYMBIO: A randomized double-blind trial. JACC Heart Fail. 2014, 2, 641–649. [Google Scholar] [CrossRef] [Scilit]
- Gordon, A.; Hultman, E.; Kaijser, L.; Kristjansson, S.; Rolf, C.J.; Nyquist, O.; Sylven, C. Creatine supplementation in chronic heart failure increases skeletal muscle creatine phosphate and muscle performance. Cardiovasc. Res. 1995, 30, 413–418. [Google Scholar] [CrossRef] [Scilit]
- Andrews, R.; Greenhaff, P.; Curtis, S.; Perry, A.; Cowley, A.J. The effect of dietary creatine supplementation on skeletal muscle metabolism in congestive heart failure. Eur. Heart J. 1998, 19, 617–622. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Kuethe, F.; Krack, A.; Richartz, B.M.; Figulla, H.R. Creatine supplementation improves muscle strength in patients with congestive heart failure. Pharmazie 2006, 61, 218–222. [Google Scholar] [PubMed]
- Carvalho, A.P.P.F.; Rassi, S.; Fontana, K.E.; Correa, K.S.; Feitosa, R.H.F. Influence of creatine supplementation on the functional capacity of patients with heart failure. Arq. Bras. Cardiol. 2012, 99, 623–629. [Google Scholar] [CrossRef] [Scilit]
- López-Clemente, J.C.; Fuertes-Kenneally, L.; Huerta, J.A.; Arcos, F.S.; González-López, J.; Lozano, R.M.; Moreno, J.A.C. Efficacy and safety of creatine supplementation in patients with heart failure and reduced ejection fraction: A pilot study. REC Cardio Clin. 2025, 60, 76–86. [Google Scholar] [CrossRef] [Scilit]
- Horjus, D.L.; Oudman, I.; van Montfrans, G.A.; Brewster, L.M. Creatine and creatine analogues in hypertension and cardiovascular disease. Cochrane Database Syst. Rev. 2011, 2011, CD005184. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; Moher, D.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. PRISMA 2020 explanation and elaboration: Updated guidance and exemplars for reporting systematic reviews. BMJ 2021, 372, n160. [Google Scholar] [CrossRef]
- Higgins, J.P.T.; Thomas, J.; Chandler, J.; Cumpston, M.; Li, T.; Page, M.J.; Welch, V.A. (Eds.) Cochrane Handbook for Systematic Reviews of Interventions; Version 6.5; Cochrane: London, UK, 2024; Available online: https://training.cochrane.org/handbook (accessed on 27 August 2026).
- Rethlefsen, M.L.; Kirtley, S.; Waffenschmidt, S.; Ayala, A.P.; Moher, D.; Page, M.J.; Koffel, J.B.; PRISMA-S Group. PRISMA-S: An extension to the PRISMA Statement for Reporting Literature Searches in Systematic Reviews. Syst. Rev. 2021, 10, 39. [Google Scholar] [CrossRef] [Scilit]
- Guyatt, G.H.; Sullivan, M.J.; Thompson, P.J.; Fallen, E.L.; Pugsley, S.O.; Taylor, D.W.; Berman, L.B. The 6-minute walk: A new measure of exercise capacity in patients with chronic heart failure. Can. Med. Assoc. J. 1985, 132, 919–923. [Google Scholar] [PubMed]
- Bittner, V.; Weiner, D.H.; Yusuf, S.; Rogers, W.J.; McIntyre, K.M.; Bangdiwala, S.I.; Kronenberg, M.W.; Kostis, J.B.; Kohn, R.M.; Guillotte, M.; et al. Prediction of mortality and morbidity with a 6-minute walk test in patients with left ventricular dysfunction. JAMA 1993, 270, 1702–1707. [Google Scholar] [CrossRef] [Scilit]
- Täger, T.; Hanholz, W.; Cebola, R.; Fröhlich, H.; Franke, J.; Doesch, A.; Katus, H.A.; Wians, F.H., Jr.; Frankenstein, L. Minimal important difference for 6-minute walk test distances among patients with chronic heart failure. Int. J. Cardiol. 2014, 176, 94–98. [Google Scholar] [CrossRef] [Scilit]
- Green, C.P.; Porter, C.B.; Bresnahan, D.R.; Spertus, J.A. Development and evaluation of the Kansas City Cardiomyopathy Questionnaire: A new health status measure for heart failure. J. Am. Coll. Cardiol. 2000, 35, 1245–1255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spertus, J.A.; Jones, P.G.; Sandhu, A.T.; Arnold, S.V. Interpreting the Kansas City Cardiomyopathy Questionnaire in clinical trials and clinical care: JACC state-of-the-art review. J. Am. Coll. Cardiol. 2020, 76, 2379–2390. [Google Scholar] [CrossRef] [Scilit]
- Cornelissen, V.; Defoor, J.; Stevens, A.; Schepers, D.; Hespel, P.; Decramer, M.; Mortelmans, L.; Dobbels, F.; Vanhaecke, J.; Fagard, R.; et al. Effect of creatine supplementation as a potential adjuvant therapy to exercise training in cardiac patients: A randomized controlled trial. Clin. Rehabil. 2010, 24, 988–999. [Google Scholar] [CrossRef] [Scilit]
- Hemati, F.; Rahmani, A.; Asadollahi, K.; Soleimannejad, K.; Khalighi, Z. Effects of complementary creatine monohydrate and physical training on inflammatory and endothelial dysfunction markers among heart failure patients. Asian J. Sports Med. 2016, 7, e28578. [Google Scholar] [CrossRef] [Scilit]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit]
- Guyatt, G.H.; Oxman, A.D.; Vist, G.E.; Kunz, R.; Falck-Ytter, Y.; Alonso-Coello, P.; Schünemann, H.J. GRADE: An emerging consensus on rating quality of evidence and strength of recommendations. BMJ 2008, 336, 924–926. [Google Scholar] [CrossRef] [Scilit]
- Fumagalli, S.; Fattirolli, F.; Guarducci, L.; Cellai, T.; Baldasseroni, S.; Tarantini, F.; Di Bari, M.; Masotti, G.; Marchionni, N. Coenzyme Q10 terclatrate and creatine in chronic heart failure: A randomized, placebo-controlled, double-blind study. Clin. Cardiol. 2011, 34, 211–217. [Google Scholar] [CrossRef] [Scilit]
- Longobardi, I.; Gualano, B.; Seguro, A.C.; Roschel, H. Is it time for a requiem for creatine supplementation-induced kidney failure? A narrative review. Nutrients 2023, 15, 1466. [Google Scholar] [CrossRef] [Scilit]
- McMurray, J.J.V.; Packer, M.; Desai, A.S.; Gong, J.; Lefkowitz, M.P.; Rizkala, A.R.; Rouleau, J.L.; Shi, V.C.; Solomon, S.D.; Swedberg, K.; et al. Angiotensin-neprilysin inhibition versus enalapril in heart failure. N. Engl. J. Med. 2014, 371, 993–1004. [Google Scholar] [CrossRef] [Scilit]
- McMurray, J.J.V.; Solomon, S.D.; Inzucchi, S.E.; Køber, L.; Kosiborod, M.N.; Martinez, F.A.; Ponikowski, P.; Sabatine, M.S.; Anand, I.S.; Bělohlávek, J.; et al. Dapagliflozin in patients with heart failure and reduced ejection fraction. N. Engl. J. Med. 2019, 381, 1995–2008. [Google Scholar] [CrossRef] [Scilit]
- Packer, M.; Anker, S.D.; Butler, J.; Filippatos, G.; Pocock, S.J.; Carson, P.; Januzzi, J.; Verma, S.; Tsutsui, H.; Brueckmann, M.; et al. Cardiovascular and renal outcomes with empagliflozin in heart failure. N. Engl. J. Med. 2020, 383, 1413–1424. [Google Scholar] [CrossRef] [Scilit]
- Anker, S.D.; Butler, J.; Filippatos, G.; Ferreira, J.P.; Bocchi, E.; Böhm, M.; Brunner–La Rocca, H.-P.; Choi, D.-J.; Chopra, V.; Chuquiure-Valenzuela, E.; et al. Empagliflozin in heart failure with a preserved ejection fraction. N. Engl. J. Med. 2021, 385, 1451–1461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Solomon, S.D.; McMurray, J.J.; Claggett, B.; de Boer, R.A.; DeMets, D.; Hernandez, A.F.; Inzucchi, S.E.; Kosiborod, M.N.; Lam, C.S.; Martinez, F.; et al. Dapagliflozin in heart failure with mildly reduced or preserved ejection fraction. N. Engl. J. Med. 2022, 387, 1089–1098. [Google Scholar] [CrossRef] [Scilit] [PubMed]


| Domain | Inclusion | Exclusion |
|---|---|---|
| Population | Adults with chronic heart failure, including HFrEF, HFmrEF, HFpEF, or investigator-defined congestive heart failure | Non-heart-failure populations without extractable HF data; animal or in vitro studies |
| Intervention | Oral creatine supplementation, preferably creatine monohydrate | Intravenous phosphocreatine, creatine phosphate sodium, and parenteral creatine-related compounds |
| Comparator | Placebo, usual care, same exercise intervention without creatine, or non-creatine control | No comparator for primary causal synthesis; non-isolatable active cointervention excluded from included evidence base |
| Outcomes | Functional capacity, muscle strength/endurance, quality of life, cardiac function, renal safety, adverse events, hospitalization, and mortality | Studies without extractable efficacy or safety outcomes |
| Study design | Randomized parallel-group or crossover trials for primary synthesis; selected non-randomized studies for narrative context | Case reports, reviews, editorials, and non-clinical studies |
| Study | Design/n | Population and Key Clinical Descriptors | Regimen | Comparator | Role |
|---|---|---|---|---|---|
| Gordon 1995 [48] | Double-blind placebo-controlled; n = 17 | Chronic HF; age, 43–70 years; LVEF < 40%; sex, NYHA class, background HF therapy, and funding not reported in the accessible abstract/extraction | 20 g/day; 10 days | Placebo | Primary RCT |
| Andrews 1998 [49] | Randomized placebo-controlled; n = 20 | Chronic HF; age, sex distribution, NYHA class, LVEF, background HF therapy, and funding not reported in the accessible abstract/extraction | 20 g/day; 5 days | Placebo | Primary RCT |
| Kuethe 2006 [50] | Double-blind crossover RCT; n = 20; 13 completers | CHF > 6 months; mean age, 59.5 years; 5 women/15 men; NYHA II (n = 12) or III (n = 8); LVEF 27.5 ± 10.2%; stable HF medication ≥ 3 months | 20 g/day; 6 weeks/period | Placebo | Primary RCT |
| Carvalho 2012 [51] | Randomized double-blind; n = 33 (17/16) | Men; NYHA II–IV; age 51.7 ± 10.5 years (creatine) vs. 59.9 ± 10.0 (placebo); LVEF 32.3 ± 13.6% vs. 35.1 ± 14.8%; common therapy included ACE inhibitors, diuretics, digitalis, and beta-blockers; no external funding | 5 g/day; 6 months | Maltodextrin | Primary RCT |
| López-Clemente 2025 [52] | Prospective single-center open-label pilot; n = 43 | HFrEF; mean age, 60.73 ± 11.73 years; 30.43% women; exact baseline LVEF, NYHA distribution, background HF therapy, and funding not reported in the accessible abstract/extraction | 5 g/day; 3 months; clinical follow-up to 1 year | No randomized control | Exploratory HF evidence |
| Study | Key Outcome Data | Safety, Attrition, and Interpretation |
|---|---|---|
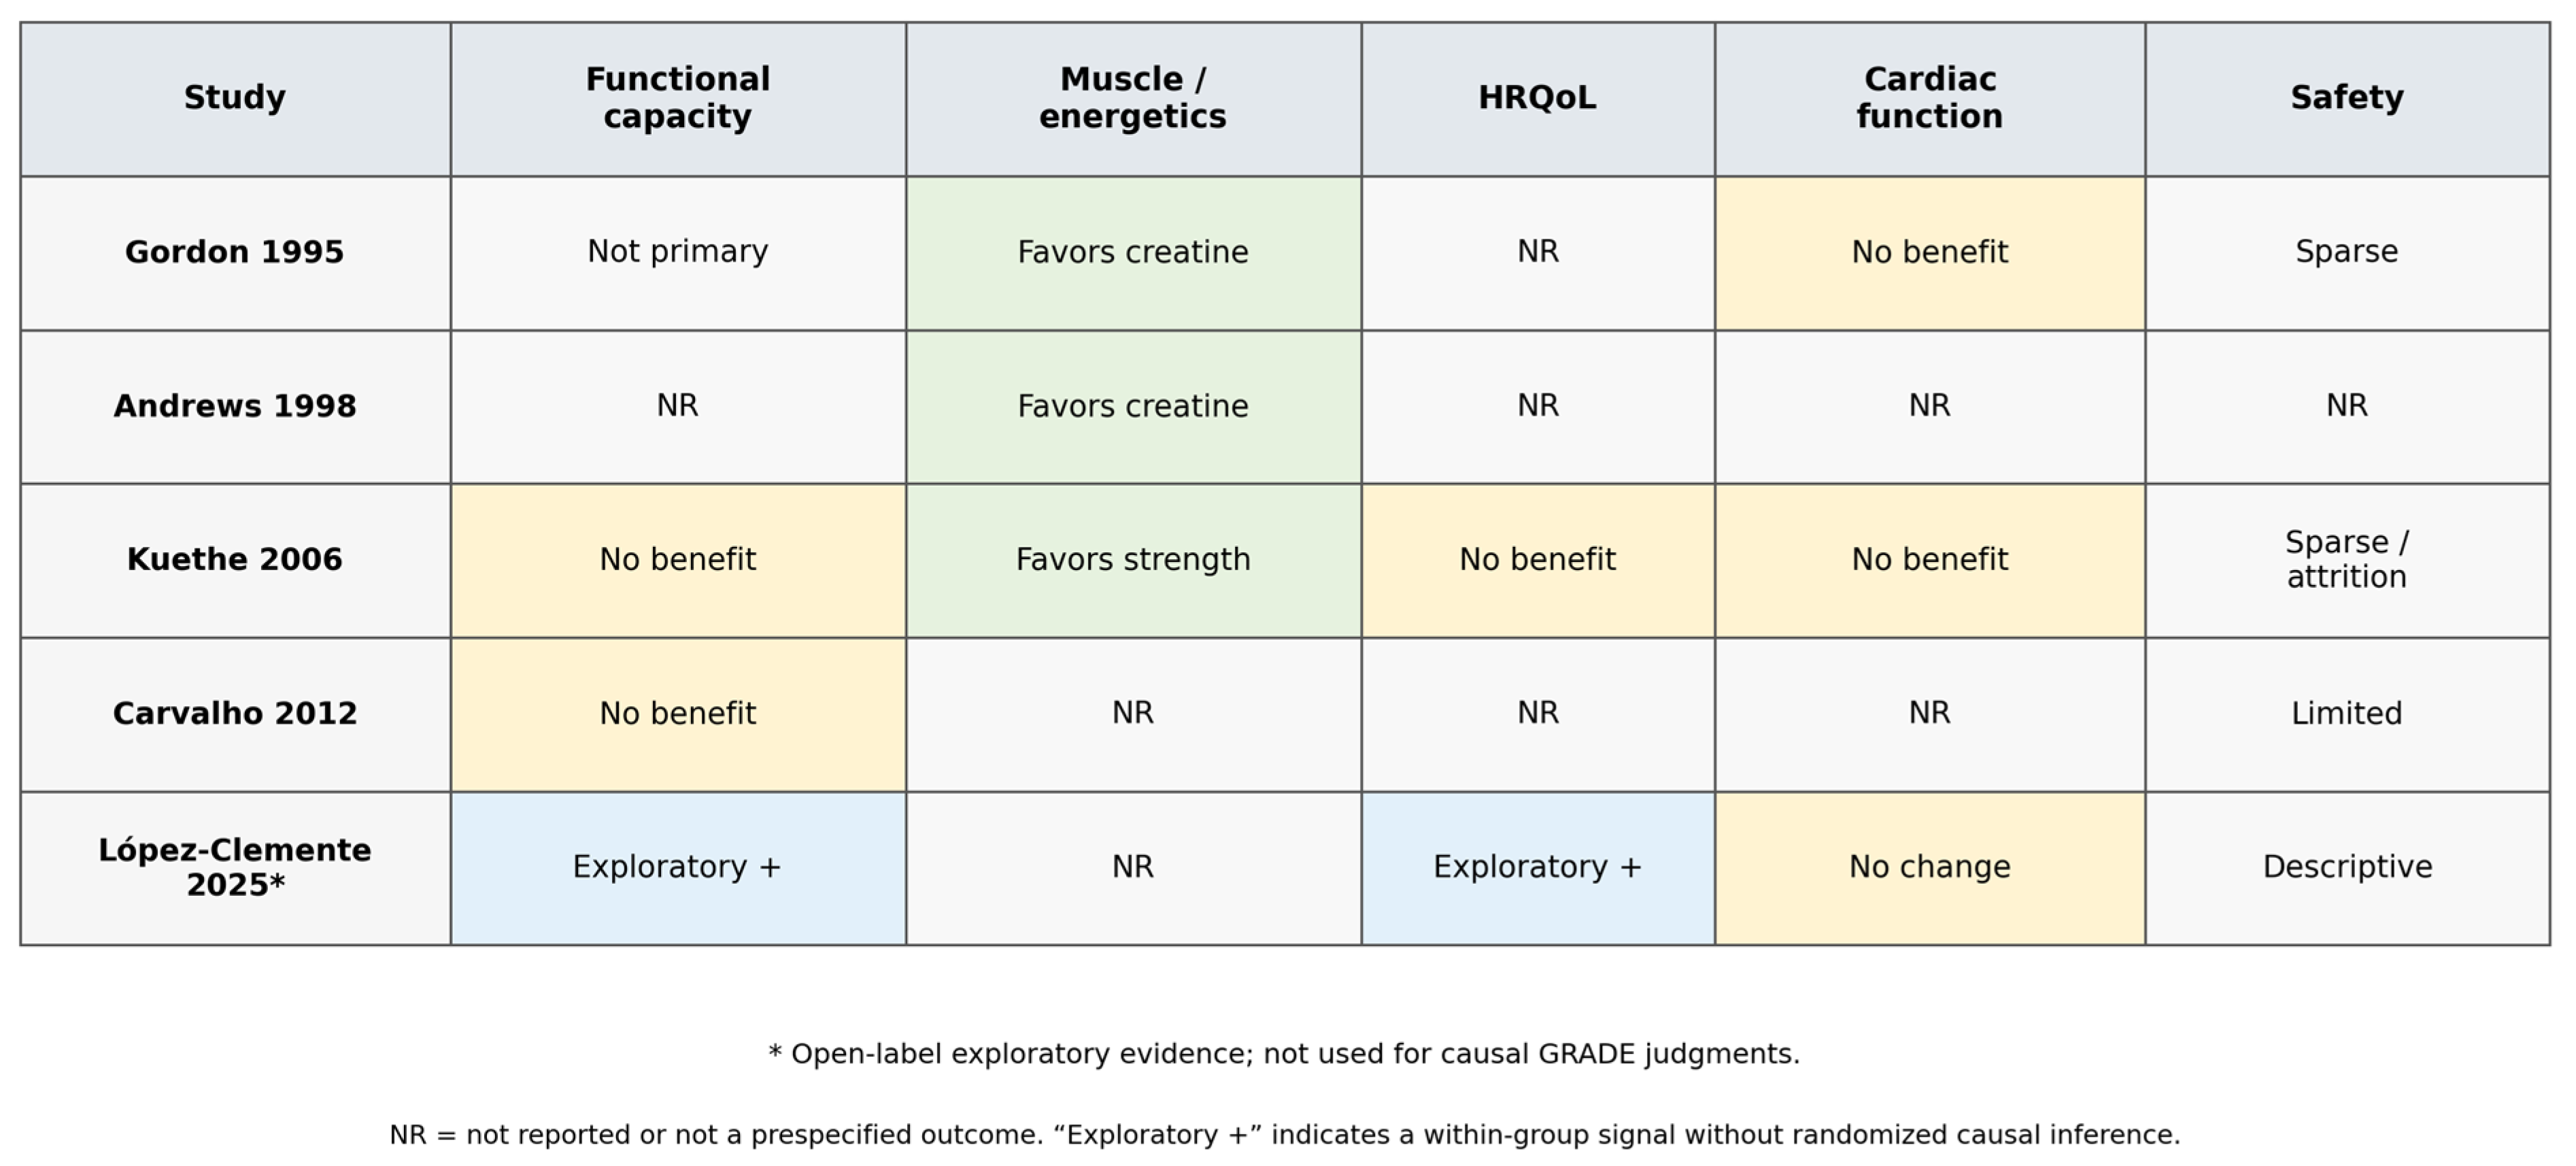
| Gordon 1995 [48] | Total muscle creatine +17 ± 4%; phosphocreatine +12 ± 4%; one-leg endurance +21%; two-leg performance +10%; peak torque +5%; ejection fraction unchanged. | Adverse-event and clinical-event reporting was limited. Preliminary peripheral muscle/energetic signal; randomized; 10-day intervention. |
| Andrews 1998 [49] | Contractions to exhaustion at 75% MVC increased from median 8 (IQR 6–14) to 14 (IQR 8–17), p = 0.025; ammonia per contraction decreased. | Adverse-event reporting was limited. Muscle-endurance/metabolic signal; randomized; 5-day intervention. |
| Kuethe 2006 [50] | Peak VO2 16.0 ± 4.2 with placebo vs. 14.8 ± 3.4 with creatine; 6MWT 604 ± 103 vs. 597 ± 125 m; elbow-flexor strength 88.3 ± 11.9 vs. 112.5 ± 14.8 mmHg (p < 0.05). | 13/20 completed both periods; 7/20 discontinued (3 during creatine and 4 during placebo). One death and one acute HF decompensation occurred among withdrawals, but treatment-period attribution was not reported. One participant reported transient mild gastric pain during creatine intake. Muscle-strength signal without global functional benefit; crossover RCT; paired-variance/carry-over reporting incomplete. |
| Carvalho 2012 [51] | Peak VO2 between-group difference 0.30 mL/kg/min (95% CI −3.47 to 4.08); 6MWT difference 25.29 m (95% CI −19.33 to 69.92); no benefit in AT or O2 pulse. | Creatinine 1.31 mg/dL (95% CI 1.21–1.42) vs. 1.20 (1.09–1.31), p = 0.1499; no urea difference. Neutral functional-capacity result; randomized; 6-month intervention. |
| López-Clemente 2025 [52] | 6MWT +48.69 ± 32.76 m (p = 0.005); HRQoL +4.08 ± 12.29 points (p = 0.03); no echocardiographic change. | Transient creatinine increase/eGFR decline normalized after discontinuation; no observed change in HF decompensation or mortality at follow-up. Hypothesis-generating exploratory open-label evidence only. |
| Outcome | Randomized Evidence | Why No Meta-Analysis | Synthesis Rule | Result |
|---|---|---|---|---|
| Functional capacity | Kuethe [50]; Carvalho [51] | Different trial structures/time points; crossover paired variance unavailable; heterogeneous measures | Prioritize randomized between-group end-of-treatment results | No consistent benefit |
| Muscle strength/ endurance | Gordon [48]; Andrews [49]; Kuethe [50] | Non-equivalent constructs/scales (knee endurance, peak torque, handgrip, and sphygmomanometer strength) | Direction + magnitude; no vote counting by p value | Preliminary favorable signal |
| Quality of life | Kuethe [50] | Too few comparable randomized data | Randomized evidence only for causal inference | No established benefit |
| Cardiac function | Gordon [48]; Kuethe [50] | Few small studies; different assessments | Narrative randomized evidence | No consistent benefit |
| Safety/ renal outcomes | Randomized reports sparse | Different definitions; few events; inconsistent denominators | Distinguish not reported from no event | Very uncertain |
| Hospitalization/ mortality | No adequately powered randomized evidence | Insufficient events | Exploratory only | Unknown |
| Outcome | Studies/ Participants | Effect Summary | GRADE Domains and Downgrading | Certainty |
|---|---|---|---|---|
| Functional capacity | 2 RCTs; up to 53 randomized (Kuethe 20; Carvalho 33) | No consistent benefit. Carvalho: peak VO2 difference of 0.30 mL/kg/min (95% CI −3.47 to 4.08); 6MWT difference of 25.29 m (95% CI −19.33 to 69.92). Kuethe reported no benefit; paired CI unavailable. | RoB: −1 (attrition/reporting); inconsistency: 0 (directionally neutral across RCTs); indirectness: 0; imprecision: −2 (small information size and intervals compatible with benefit/no benefit); publication bias: 0 (too few studies to assess; not downgraded). | Very low |
| Muscle/ energetics | 3 RCTs; up to 57 randomized | Directionally favorable selected peripheral muscle outcomes but measured with non-equivalent tests and without demonstrated patient-centered benefit. | RoB: −1; inconsistency: 0 (favorable direction, different constructs); indirectness: −1 (surrogate/peripheral outcomes); imprecision: −1 (small studies); publication bias: 0 (too few studies to assess; not downgraded). | Very low |
| HRQoL | 1 randomized crossover trial; n = 20 randomized, 13 completers | No established randomized benefit | RoB: −1; inconsistency: not assessable; indirectness: 0; imprecision: −2; publication bias: 0 (not assessable; not downgraded). | Very low |
| Cardiac function | 2 RCTs; up to 37 randomized | No consistent improvement in LVEF | RoB: −1; inconsistency: 0; indirectness: 0; imprecision: −2; publication bias: 0 (not assessable; not downgraded). | Very low |
| Safety/renal | Randomized evidence sparse; denominators inconsistently reported | Sparse randomized data; Carvalho showed no significant creatinine/urea difference, while Kuethe reported substantial attrition and limited event attribution. | RoB: −1; inconsistency: −1 (inconsistent reporting); indirectness: −1 (short follow-up and non-event-focused trials); imprecision: −2 (few participants/events); publication bias: 0 (not assessable; not downgraded). | Very low |
| Hospitalization/ mortality | No adequately powered randomized evidence | Effect unknown | Severe imprecision and absence of event-powered randomized evidence | Very low (effect not estimable) |
| Study | Randomization | Deviations | Missing Data | Outcome Measurement | Selection of Reported Result | Period/Carry-Over Effects | Overall |
|---|---|---|---|---|---|---|---|
| Gordon 1995 [48] Muscle/energetics; cardiac function | Some concerns | Low | Some concerns | Low | Some concerns | N/A (parallel-group trial) | Some concerns |
| Andrews 1998 [49] Muscle endurance/metabolism | Some concerns | Low | Some concerns | Low | Some concerns | N/A (parallel-group trial) | Some concerns |
| Kuethe 2006 [50] Functional capacity; muscle strength; HRQoL; cardiac function | Some concerns | Low | High (13/20 completed) | Low | Some concerns; paired-period and carry-over reporting incomplete | Some concerns: washout plausible, but period-specific paired estimates and formal carry-over testing incompletely reported | High |
| Carvalho 2012 [51] Functional capacity | Some concerns | Low | Some concerns | Low | Some concerns | N/A (parallel-group trial) | Some concerns |
| Study | Renal Markers | Adverse Events | Discontinuation/ Attrition | HF Hospitalization/ Mortality | Safety Interpretation |
|---|---|---|---|---|---|
| Gordon 1995 [48] | Not adequately reported | Not adequately reported | NR | NR | Too short/small for clinical safety |
| Andrews 1998 [49] | NR | NR | NR | NR | Safety cannot be inferred |
| Kuethe 2006 [50] | NR in report | One participant reported transient mild gastric pain during creatine intake; no other adverse event was specifically attributed to creatine in the accessible report | 7/20 discontinued (3 during creatine, 4 during placebo); reasons: cold (1), death (1), breast cancer (1), acute decompensation (1), and unstated (3) | One death and one acute HF decompensation occurred among withdrawals; treatment-period attribution not reported | Substantial attrition and limited attribution preclude a safety conclusion |
| Carvalho 2012 [51] | Creatinine 1.31 mg/dL (95% CI 1.21–1.42) vs. 1.20 (1.09–1.31), p = 0.1499; no significant urea difference | No systematic adverse-event denominator reported | NR | NR | Renal laboratory data reassuring over 6 months but trial underpowered for clinical events |
| López-Clemente 2025 [52] | Transient creatinine increase/eGFR decline; normalized after discontinuation | Reported descriptively | Open-label; no randomized attrition comparison | No observed change in HF decompensation or mortality during follow-up | Exploratory, non-randomized |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Epelde, F.; Martínez López, M.P. Efficacy and Safety of Oral Creatine Supplementation in Patients with Heart Failure: A PRISMA 2020 Systematic Review and Narrative Evidence Synthesis. Int. J. Environ. Res. Public Health 2026, 23, 1130. https://doi.org/10.3390/ijerph23091130
Epelde F, Martínez López MP. Efficacy and Safety of Oral Creatine Supplementation in Patients with Heart Failure: A PRISMA 2020 Systematic Review and Narrative Evidence Synthesis. International Journal of Environmental Research and Public Health. 2026; 23(9):1130. https://doi.org/10.3390/ijerph23091130
Chicago/Turabian StyleEpelde, Francisco, and María Pilar Martínez López. 2026. "Efficacy and Safety of Oral Creatine Supplementation in Patients with Heart Failure: A PRISMA 2020 Systematic Review and Narrative Evidence Synthesis" International Journal of Environmental Research and Public Health 23, no. 9: 1130. https://doi.org/10.3390/ijerph23091130
APA StyleEpelde, F., & Martínez López, M. P. (2026). Efficacy and Safety of Oral Creatine Supplementation in Patients with Heart Failure: A PRISMA 2020 Systematic Review and Narrative Evidence Synthesis. International Journal of Environmental Research and Public Health, 23(9), 1130. https://doi.org/10.3390/ijerph23091130