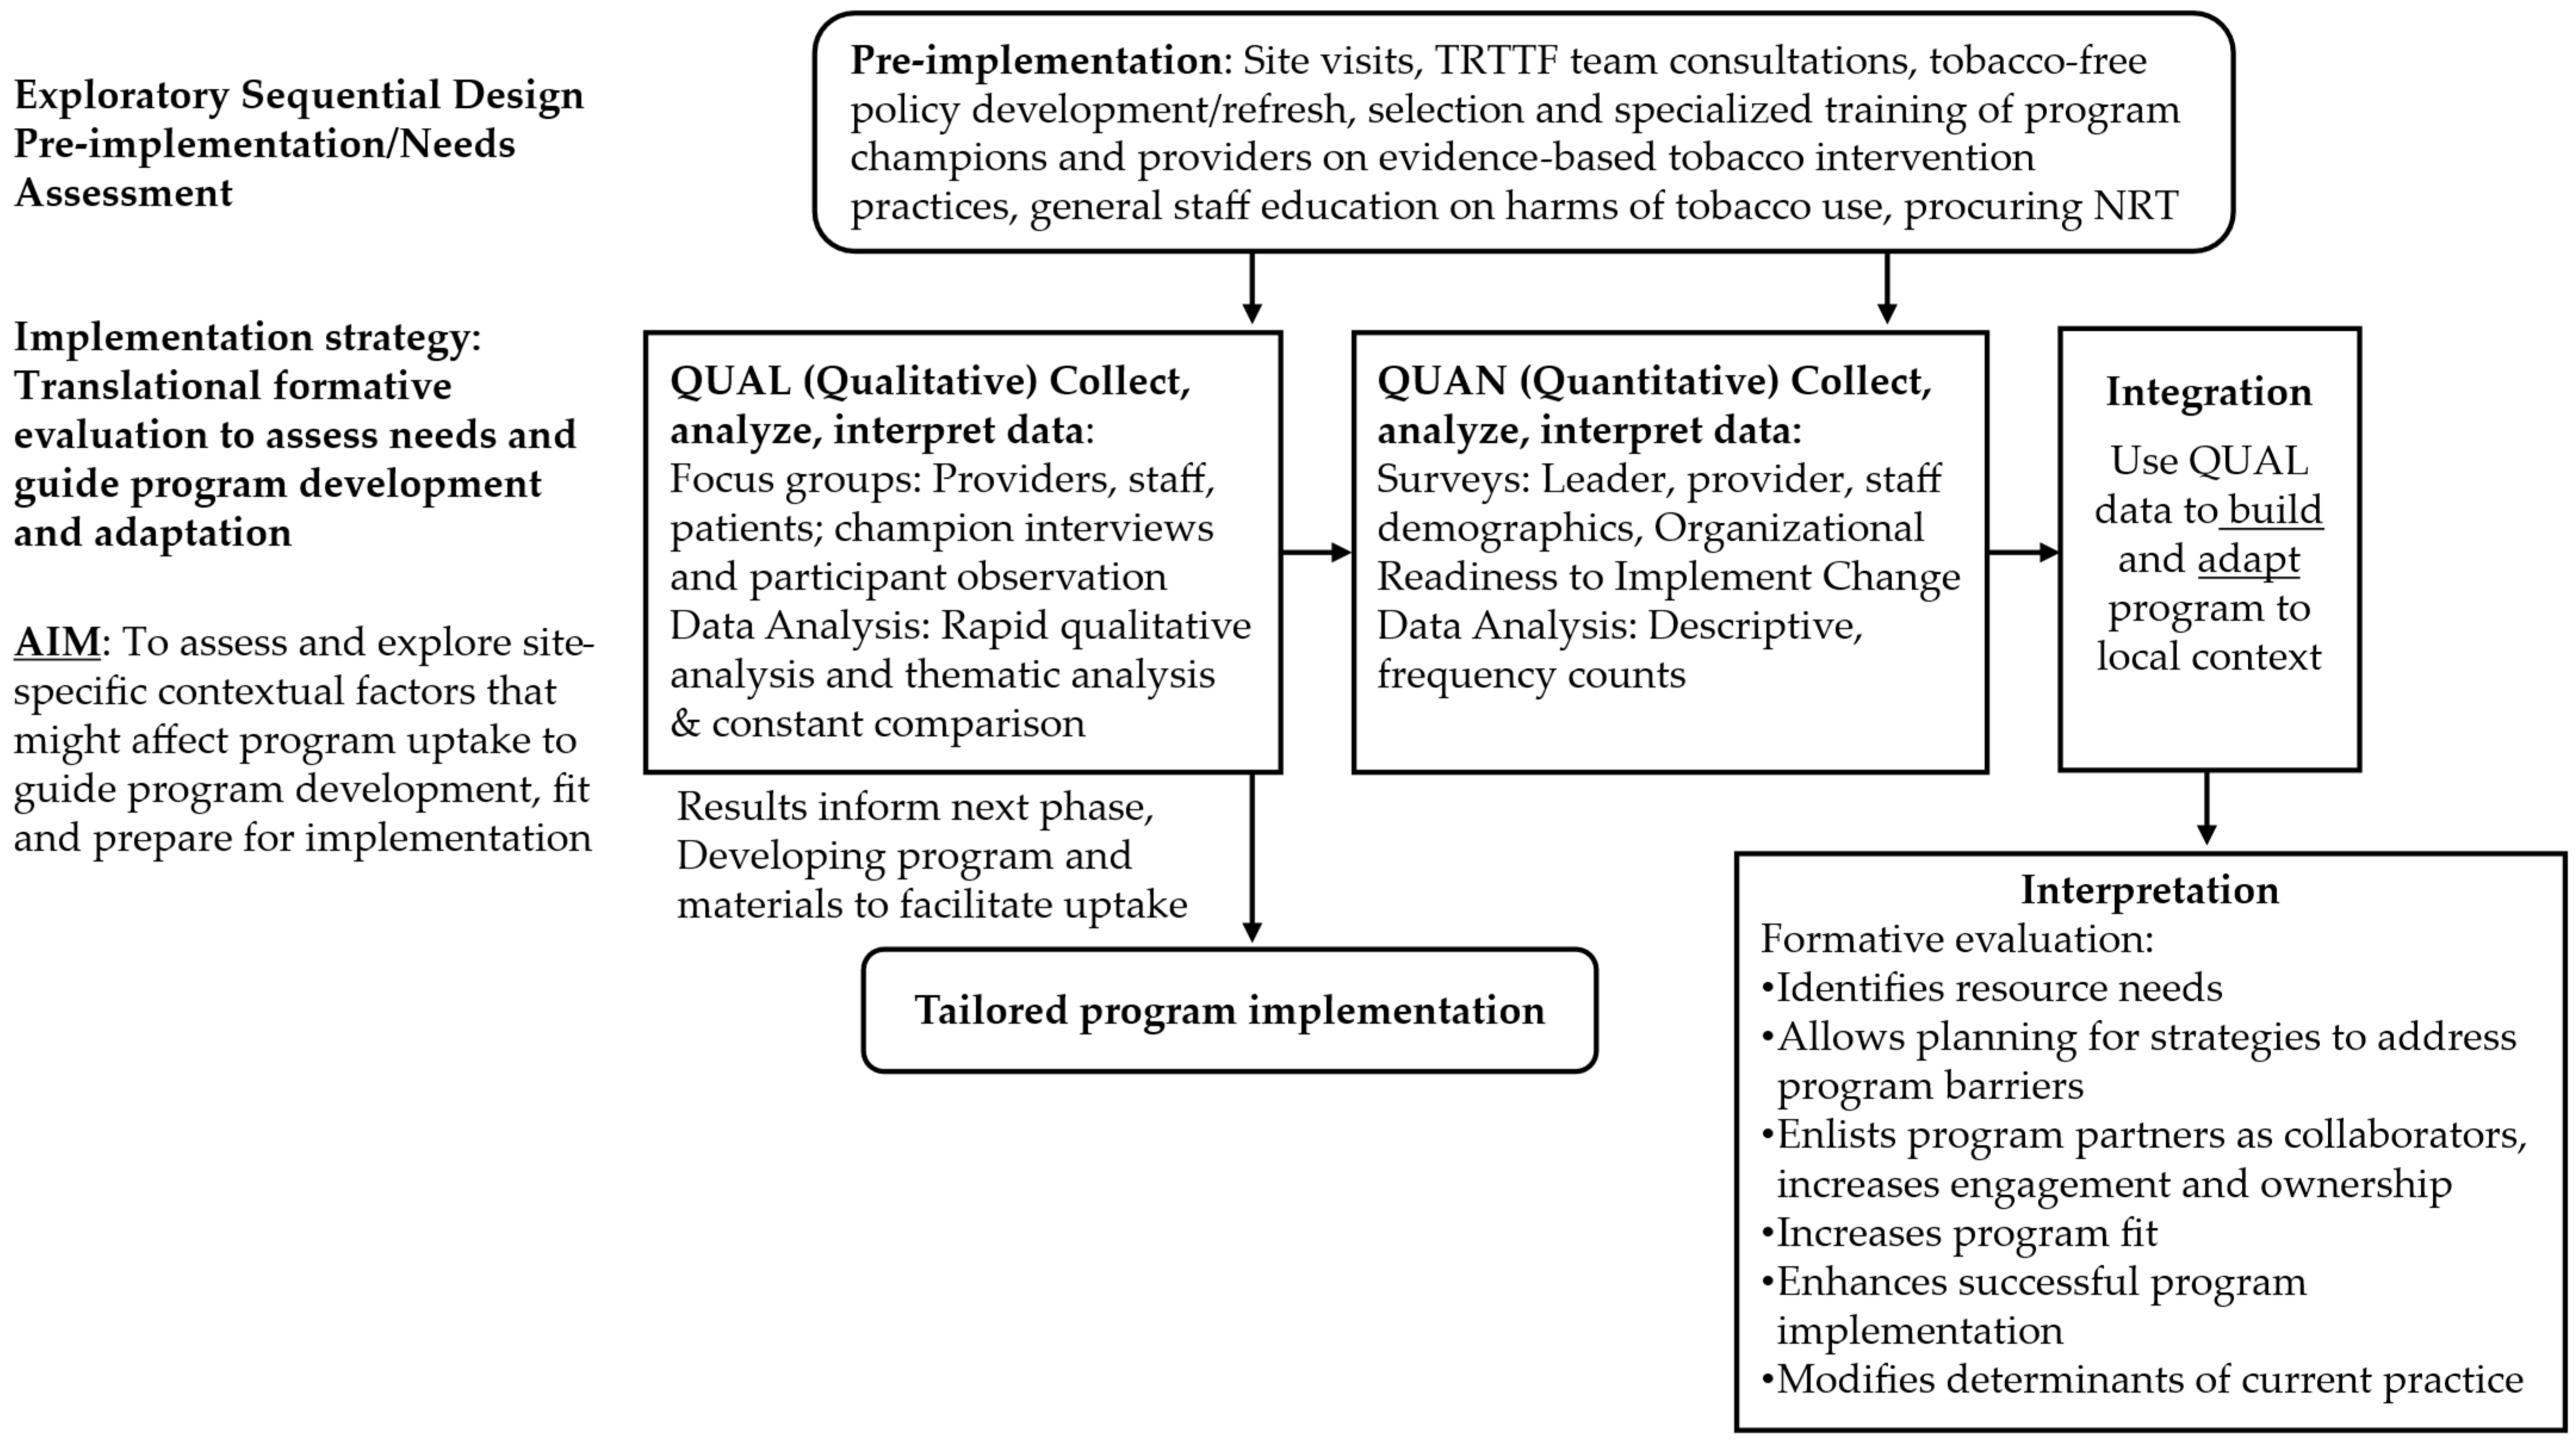
Provider Perspectives on a Tobacco-Free Workplace Program in Healthcare Settings Serving Rural and Medically Underserved Areas of Texas: A Mixed Methods Study on Perceived Resource Availability and Value
 , , , , ,

Highlights
- Compared to the general population, smoking rates are at least twice as high among people with substance use disorders, a group that is overrepresented in rural/medically underserved areas in the United States.
- Identifies barriers to and potential interventions for tobacco-free workplace programs as well as differences among healthcare settings that may contribute to successful future implementation outcomes.
- Outlines implications for strategic allocation of limited resources to organizations that will maximize impact.
- Providers at medical healthcare centers are significantly more likely to cite time as a resource barrier to tobacco cessation compared to those at substance use treatment centers; substance use treatment centers may be better positioned for early adoption of tobacco-free workplace programs.
- To strengthen organizational readiness and build greater capacity for tobacco cessation, provider attitudes, and organizational practices in treating tobacco dependence must be further developed and examined.
Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design
2.2. Procedures and Participants
2.2.1. Eligibility and Recruitment
2.2.2. Study Procedures
2.2.3. Approvals
2.2.4. Quantitative Sample
2.2.5. Qualitative Sample
2.3. Quantitative Measures
2.3.1. Healthcare Center Characteristics
2.3.2. Perceptions of Resource Availability
2.3.3. Perceived Value
2.4. Data Analysis
2.4.1. Quantitative Data
2.4.2. Qualitative Data
3. Results
3.1. Healthcare Center Characteristics
3.2. Quantitative Results
3.2.1. Information Assessment
3.2.2. Change Valence
3.3. Qualitative Results
3.3.1. Efficacy Gaps—Additional Training and Resources Are Needed to Build Capacity
“…we’ve been pretty successful with our employees but not our patients… So, I think we need to put a little more—emphasize it a little more. I think maybe with the proper training.”(Provider, MHC #4)
“…because we don’t have the proper tools and resources to help them, the only thing we have now is the Quit Now number. We don’t really offer like, ‘Are you wanting to quit?’ We don’t offer that until we get the resources with you all. That’s when we’ll start offering, like, ‘Hey, are you wanting to quit?’”(Provider, SUTC #6)
“I think we just have always needed more resources or more information for the patients, and us telling the patient that we are a smoke-free campus and that we have options to help them quit. If you don’t have information to hand to them or the product to hand to them, it definitely hurts their ability to be successful. So, I think now that we have all that, we will be better off.”(Provider, SUTC #7)
3.3.2. Organizational Factors—Limited Institutional Frameworks, Policies, and Practices
“I don’t think we have any policies about that [on-site tobacco use], but then I don’t think a lot of employees do smoke. I’m not too sure, honestly.”(Provider, MHC #1)
“In my experience, it’s so hard to kick. I think it’s the worst. It’s the nastiest, most expensive habit you can imagine, but I myself haven’t been able to stop smoking… Quite frankly, I’m not one to smoke in front of my employer’s building and stuff, but I don’t see many smokers around here, and that’s how I smoke… Yes, I can definitely learn a lot. I know it’s so hard [to quit].”(Provider, SUTC #3)
“I try to print some handouts, and I leave them out there on the table, but pretty much that’s all I do. We don’t have access to give them anything.”(Provider, SUTC #5)
“Maybe if there’s like an alternative that I can tell them, ‘There’s a number you call to speak about it whenever you decide if you want to stop,’ because sometimes, they don’t want to talk about it in person because I guess they feel like maybe it’s like an intervention almost.”(Provider, MHC #5)
3.3.3. Valuing—Tobacco Cessation Was Valued as Compatible but Not a Treatment Priority
“Typically, they’ve gotten to the point where they’re willing to give up their drug of choice, whatever it is, but—and so that’s the main area of focus. I know and I agree as far as nicotine being a drug, and not helping with healing, but I think it is treated differently in the sense that we’re like, ‘Okay, you’re still smoking in the program, but obviously, you’re not using these other drugs,’ if that makes sense.”(Provider, SUTC #2)
“I would say not the top priority. If they’re coming in with no alcoholism or—it’s not their number [one] priority at this time. It hasn’t been traditionally. It’s whatever the other person [‘s] substance of choice is.”(Provider, SUTC #2)
“Yes, unfortunately a lot of the time, it is letting them embrace the lesser of two evils view because yes, if the choice is doing meth or smoking cigarettes like, ‘Hey, go buy a pack. That’s way better.’ So, that’s partly might be why is just because like [name] was saying, our population, they are coming from usually a much more serious situation, so stepping down to smoking is usually like a win for us.”(Provider, SUTC #3)
“I’m so busy. I’m going to address what they’re there for. Those extra things that I don’t hit on them… it says twenty minutes. By the time I actually get in there, I might have five, depending on if the patient was late or what’s going on. I don’t have a lot of time with them. The time I do have, I hit on the main points.”(Provider, MHC #2)
3.3.4. Conflicting Attitudes—Negative Assumptions About Patient Tobacco Use and Smoking to Maintain Sobriety
“I would say 10% might be willing out of 90%, but I really was kind of shocked when people came in that some expressed that they wanted to quit smoking, to be honest with you.”(Provider, SUTC #6)
“I feel like if I were to [bring up smoking] like for the older generation, for example, I’ve had a patient where they’re smokers for 20-plus years, and I asked them a question of like, ‘Have you thought of like stopping smoking?’ They get a little bit angry. They don’t really like having that question being asked to them.”(Provider, MHC #5)
“Then, I think also sometimes it is used as a tool for maintaining sobriety. So, someone might be using tobacco to stay away from meth, heroin, or whatever it was they were using before. So, they’re using that to help maintain sobriety.”(Provider, SUTC #4)
3.4. Integrated Mixed Methods Findings
4. Discussion
Study Limitations and Implications
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- National Center for Chronic Disease Prevention and Health Promotion (US) Office on Smoking and Health. The Health Consequences of Smoking—50 Years of Progress: A Report of the Surgeon General; U.S. Department of Health and Human Services: Washington, DC, USA, 2014.
- U.S. Department of Health and Human Services Centers for Disease Control and Prevention National Center for Chronic Disease Prevention and Health Promotion Office on Smoking and Health. Eliminating Tobacco-Related Disease and Death: Addressing Disparities—A Report of the Surgeon General (Executive Summary); U.S. Department of Health and Human Services: Washington, DC, USA, 2024.
- Center for Disease Control and Prevention. Burden of Tobacco Use in the U.S. Center for Disease Control and Prevention. Available online: https://www.cdc.gov/tobacco/campaign/tips/resources/data/cigarette-smoking-in-united-states.html (accessed on 8 October 2025).
- Saloner, B.; Li, W.; Flores, M.; Progovac, A.M.; Lê Cook, B. A widening divide: Cigarette smoking trends among people with substance use disorder and criminal legal involvement. Health Aff. 2023, 42, 187–196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guydish, J.; Passalacqua, E.; Tajima, B.; Chan, M.; Chun, J.; Bostrom, A. Smoking prevalence in addiction treatment: A review. Nicotine Tob. Res. 2011, 13, 401–411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baca, C.T.; Yahne, C.E. Smoking cessation during substance abuse treatment: What you need to know. J. Subst. Abus. Treat. 2009, 36, 205–219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, B.; Volkow, N.D.; Blanco, C.; Tipperman, D.; Einstein, E.B.; Compton, W.M. Trends in prevalence of cigarette smoking among US adults with major depression or substance use disorders, 2006–2019. JAMA 2022, 327, 1566–1576. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Healton, C.; Nelson, K. Reversal of misfortune: Viewing tobacco as a social justice issue. Am. J. Public Health 2004, 94, 186–191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Voigt, K. Smoking and social justice. Public Health Ethics 2010, 3, 91–106. [Google Scholar] [CrossRef] [Scilit]
- Bandiera, F.C.; Anteneh, B.; Le, T.; Delucchi, K.; Guydish, J. Tobacco-related mortality among persons with mental health and substance abuse problems. PLoS ONE 2015, 10, e0120581. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chan, L.; Gary Hart, L.; Goodman, D.C.; Kreuter, W.; Ruiz, L.; Mueller, K.; Beaver, S.; Marth, N.; Rubadue, C. Geographic access to health care for rural medicare beneficiaries. J. Rural Health 2006, 22, 140–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pullen, E.; Oser, C. Barriers to substance abuse treatment in rural and urban communities: Counselor perspectives. Subst. Use Misuse 2014, 49, 891–901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buettner-Schmidt, K.; Miller, D.R.; Maack, B. Disparities in rural tobacco use, smoke-free policies, and tobacco taxes. West. J. Nurs. Res. 2019, 41, 1184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roberts, M.E.; Doogan, N.J.; Kurti, A.N.; Redner, R.; Gaalema, D.E.; Stanton, C.A.; White, T.J.; Higgins, S.T. Rural tobacco use across the United States: How rural and urban areas differ, broken down by census regions and divisions. Health Place 2016, 39, 153–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Northridge, M.E.; Vallone, D.; Xiao, H.; Green, M.; Weikle Blackwood, J.; Kemper, S.E.; Duke, J.; Watson, K.A.; Burrus, B.; Treadwell, H.M. The importance of location for tobacco cessation: Rural-urban disparities in quit success in underserved West Virginia Counties. J. Rural Health 2008, 24, 106–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hodge, F.S.; Fredericks, L.; Kipnis, P. Patient and smoking patterns in northern California American Indian Clinics: Urban and rural contrasts. Cancer 1996, 78, 1623–1628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villanti, A.C.; Klemperer, E.M.; Sprague, B.L.; Ahern, T.P. State-level rurality and cigarette smoking-associated cancer incidence and mortality: Do individual-level trends translate to population-level outcomes? Prev. Med. 2021, 152, 106759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Whitman, A.; De Lew, N.; Chappel, A.; Aysola, V.; Zuckerman, R.; Sommers, B.D. Addressing Social Determinants of Health: Examples of Successful Evidence-Based Strategies and Current Federal Efforts. 2022. Available online: https://aspe.hhs.gov/sites/default/files/documents/6ba4bbb2e9c9551355a6926f023f1585/SDOH-Evidence-Review.pdf (accessed on 18 November 2025).
- Arcury, T.A.; Preisser, J.S.; Gesler, W.M.; Powers, J.M. Access to transportation and health care utilization in a rural region. J. Rural Health 2005, 21, 31–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parker, M.A.; Weinberger, A.H.; Eggers, E.M.; Parker, E.S.; Villanti, A.C. Trends in rural and urban cigarette smoking quit ratios in the US from 2010 to 2020. JAMA Netw. Open 2022, 5, e2225326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raver, E.; Retchin, S.M.; Li, Y.; Carlo, A.D.; Xu, W.Y. Rural–urban differences in out-of-network treatment initiation and engagement rates for substance use disorders. Health Serv. Res. 2024, 59, e14299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rural Health Information Hub. Substance Use and Misuse in Rural Areas. Available online: https://www.ruralhealthinfo.org/topics/substance-use (accessed on 19 May 2025).
- Center for Disease Control and Prevention. Ten great public health achievements—United States, 2001–2010. Morb. Mortal. Wkly. Rep. (MMWR) 2011, 60, 619–623. [Google Scholar] [PubMed]
- Garrett, B.; Dube, S.; Babb, S.; McAfee, T. Addressing the social determinants of health to reduce tobacco-related disparities. Nicotine Tob. Res. 2015, 17, 892–897. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Center for Disease Control and Prevention. Best Practices for Comprehensive Tobacco Control Programs; US Department of Health and Human Services, Centers for Disease Control and Prevention, National Center for Chronic Disease Prevention and Health Promotion, Office on Smoking and Health: Atlanta, GA, USA, 2014. Available online: https://stacks.cdc.gov/view/cdc/21697 (accessed on 8 October 2025).
- Davis, K.C.; Patel, D.; Shafer, P.; Duke, J.; Glover-Kudon, R.; Ridgeway, W.; Cox, S. Association between media doses of the Tips from Former Smokers Campaign and cessation behaviors and intentions to quit among cigarette smokers, 2012–2015. Health Educ. Behav. 2017, 45, 52–60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, K.; Murphy-Hoefer, R.; Dutra, L.; King, B.; Bradfield, B.; Rodes, R.; Beistle, D. The impact of the Tips from Former Smokers® Campaign on reducing cigarette smoking relapse. J. Smok. Cessat. 2022, 2022, e3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vander Weg, M.W.; Cunningham, C.L.; Howren, M.B.; Cai, X. Tobacco use and exposure in rural areas: Findings from the Behavioral Risk Factor Surveillance System. Addict. Behav. 2011, 36, 231–236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ablah, E.; Dong, F.; Konda, K.; Ablah, E.; Dong, F.; Konda, K. Tobacco-free policies at worksites in Kansas. BMC Public Health 2017, 17, 566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American Lung Association. Cutting Tobacco’s Rural Roots: Tobacco Use in Rural Communities. 2012. Available online: https://healthforward.org/wp-content/uploads/2015/07/cutting-tobaccos-rural-roots.pdf (accessed on 8 October 2025).
- Talbot, J.A.; Williamson, M.E.; Pearson, K.B.; Lenardson, J.D.; Ziller, E.D.; Jimenez, F.; Paluso, N.; Munk, L.; Janis, J.; Clayton, P.F. Advancing Tobacco Prevention and Control in Rural America. 2019. Available online: https://digitalcommons.usm.maine.edu/behavioral_health/59/ (accessed on 8 October 2025).
- Rural Health Information Hub. Rural Mental Health. Available online: https://www.ruralhealthinfo.org/topics/mental-health#integration (accessed on 28 January 2026).
- Syamlal, G.; King, B.A.; Mazurek, J.M. Workplace smoke-free policies and cessation programs among U.S. working adults. Am. J. Prev. Med. 2019, 56, 548–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eby, L.T.; Laschober, T.C.; Curtis, S.L. Substance abuse-specific knowledge transfer or loss? Treatment program turnover versus professional turnover among substance abuse clinicians. J. Addict. Dis. 2014, 33, 243–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quinn, M.T.; Gunter, K.E.; Nocon, R.S.; Lewis, S.E.; Vable, A.M.; Tang, H.; Park, S.Y.; Casalino, L.P.; Huang, E.S.; Birnberg, J.; et al. Undergoing transformation to the patient centered medical home in safety net health centers: Perspectives from the front lines. Ethn. Dis. 2013, 23, 356–362. [Google Scholar] [PubMed]
- Kelly, J.F.; Fallah-Sohy, N.; Vilsaint, C.; Hoffman, L.A.; Jason, L.A.; Stout, R.L.; Cristello, J.V.; Hoeppner, B.B. New kid on the block: An investigation of the physical, operational, personnel, and service characteristics of recovery community centers in the United States. J. Subst. Abus. Treat. 2020, 111, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayashi, A.S.; Selia, E.; McDonnell, K. Stress and provider retention in underserved communities. J. Health Care Poor Underserved 2009, 20, 597–604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herschell, A.D.; Kolko, D.J.; Hart, J.A.; Brabson, L.A.; Gavin, J.G. Mixed method study of workforce turnover and evidence-based treatment implementation in community behavioral health care settings. Child Abus. Negl. 2020, 102, 104419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brabson, L.A.; Herschell, A.D.; Kolko, D.J.; Mrozowski, S.J. Associations Among Job Role, Training Type, and Staff Turnover in a Large-Scale Implementation Initiative. J. Behav. Health Serv. Res. 2019, 46, 399–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Britton, M.; Martinez Leal, I.; Jafry, M.Z.; Chen, T.A.; Rogova, A.; Kyburz, B.; Williams, T.; Reitzel, L.R. Influence of provider and leader perspectives about concurrent tobacco-use care during substance-use treatment on their tobacco intervention provision with clients: A mixed-methods study. Int. J. Environ. Res. Public Health 2023, 20, 5260. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siddiqi, A.D.; Britton, M.; Chen, T.A.; Carter, B.J.; Wang, C.; Martinez Leal, I.; Rogova, A.; Kyburz, B.; Williams, T.; Patel, M.; et al. Tobacco screening practices and perceived barriers to offering tobacco cessation services among Texas health care centers providing behavioral health treatment. Int. J. Environ. Res. Public Health 2022, 19, 9647. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pourat, N.; O’Masta, B.; Chen, X.; Lu, C.; Zhou, W.; Daniel, M.; Hoang, H.; Sripipatana, A. Examining trends in substance use disorder capacity and service delivery by Health Resources and Services Administration-funded health centers: A time series regression analysis. PLoS ONE 2020, 15, e0242407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenhalgh, T.; Robert, G.; Macfarlane, F.; Bate, P.; Kyriakidou, O. Diffusion of innovations in service organizations: Systematic review and recommendations. Milbank Q. 2004, 82, 581–629. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiner, B.J.; Amick, H.; Lee, S.Y.D. Conceptualization and measurement of organizational readiness for change: A review of the literature in health services research and other fields. Med. Care Res. Rev. 2008, 65, 379–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiner, B.J.; Lewis, M.A.; Linnan, L.A. Using organization theory to understand the determinants of effective implementation of worksite health promotion programs. Health Educ. Res. 2009, 24, 292–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiner, B.J. A theory of organizational readiness for change. Implement. Sci. 2009, 4, 67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hafez, A.Y.; Gonzalez, M.; Kulik, M.C.; Vijayaraghavan, M.; Glantz, S.A. Uneven access to smoke-free laws and policies and its effect on health equity in the United States: 2000–2019. Am. J. Public Health 2019, 109, 1568–1575. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pagano, A.; Tajima, B.; Guydish, J. Barriers and facilitators to tobacco cessation in a nationwide sample of addiction treatment programs. J. Subst. Abus. Treat. 2016, 67, 22–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sultana, S.; Inungu, J.; Jahanfar, S. Barriers and facilitators of tobacco cessation interventions at the population and healthcare system levels: A systematic literature review. Int. J. Environ. Res. Public Health 2025, 22, 825. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flocke, S.A.; Vanderpool, R.; Birkby, G.; Gullett, H.; Seaman, E.L.; Land, S.; Zeliadt, S. Addressing tobacco cessation at federally qualified health centers: Current practices & resources. J. Health Care Poor Underserved 2019, 30, 1024. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McClure, E.A.; Acquavita, S.P.; Dunn, K.E.; Stoller, K.B.; Stitzer, M.L. Characterizing smoking, cessation services, and quit interest across outpatient substance abuse treatment modalities. J. Subst. Abus. Treat. 2014, 46, 194–201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rogova, A.; Leal, I.M.; Britton, M.; Chen, T.A.; Lowenstein, L.M.; Kyburz, B.; Casey, K.; Skeene, K.; Williams, T.; Reitzel, L.R. Implementing a tobacco-free workplace program at a substance use treatment center: A case study. BMC Health Serv. Res. 2024, 24, 201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinez Leal, I.; Taing, M.; Correa-Fernández, V.; Obasi, E.M.; Kyburz, B.; Le, K.; Koshy, L.; Chen, T.A.; Williams, T.; Casey, K.; et al. Addressing smoking cessation among women in substance use treatment: A qualitative approach to guiding tailored interventions. Int. J. Environ. Res. Public Health 2021, 18, 5764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palmer, A.M.; Rojewski, A.M.; Chen, L.S.; Fucito, L.M.; Galiatsatos, P.; Kathuria, H.; Land, S.R.; Morgan, G.D.; Ramsey, A.T.; Richter, K.P.; et al. Tobacco treatment program models in US hospitals and outpatient centers on behalf of the SRNT Treatment Network. Chest 2021, 159, 1652–1663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siddiqi, A.D.; Carter, B.J.; Britton, M.; Chen, T.A.; Martinez Leal, I.; Moosa, A.B.; Williams, T.; Casey, K.; Sanchez, H.; Reitzel, L.R. Differences in provider beliefs and delivery of the 5As for cigarette and non-cigarette tobacco use between two types of healthcare centers serving rural and/or medically underserved areas of Texas, US. Healthcare 2025, 13, 338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siddiqi, A.D.; Carter, B.J.; Chen, T.A.; Leal, I.M.; Britton, M.; Correa-Fernández, V.; Rogova, A.; Kyburz, B.; Williams, T.; Reitzel, L.R. Initial leadership concerns and availability of tobacco cessation services moderate changes in employee-reported concerns about tobacco-free workplace policy implementation over time. Transl. Behav. Med. 2024, 14, 394–401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Twyman, L.; Bonevski, B.; Paul, C.; Bryant, J. Perceived barriers to smoking cessation in selected vulnerable groups: A systematic review of the qualitative and quantitative literature. BMJ Open 2014, 4, e006414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gentry, S.; Craig, J.; Holland, R.; Notley, C. Smoking cessation for substance misusers: A systematic review of qualitative studies on participant and provider beliefs and perceptions. Drug Alcohol Depend. 2017, 180, 178–192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Creswell, J.W. A Concise Introduction to Mixed Methods Research; SAGE publications: Thousand Oaks, CA, USA, 2021. [Google Scholar]
- Morgan, D.L. Basic and Advanced Focus Groups; SAGE Publications, Inc.: Thousand Oaks, CA, USA, 2019; Available online: https://methods.sagepub.com/book/mono/basic-and-advanced-focus-groups/toc (accessed on 11 January 2025).
- Creswell, J.W.; Clark, V.L.P. Designing and Conducting Mixed Methods Research; SAGE publications: Thousand Oaks, CA, USA, 2017. [Google Scholar]
- Greene, J.C.; Caracelli, V.J.; Graham, W.F. Toward a conceptual framework for mixed-method evaluation designs. Educ. Eval. Policy Anal. 1989, 11, 255–274. [Google Scholar] [CrossRef]
- O’Cathain, A.; Murphy, E.; Nicholl, J. Integration and publications as indicators of “yield” from mixed methods studies. J. Mix. Methods Res. 2007, 1, 147–163. [Google Scholar] [CrossRef] [Scilit]
- Samaha, H.L.; Correa-Fernández, V.; Lam, C.; Wilson, W.T.; Kyburz, B.; Stacey, T.; Williams, T.; Reitzel, L.R. Addressing tobacco use among consumers and staff at behavioral health treatment facilities through comprehensive workplace programming. Health Promot. Pract. 2017, 18, 561–570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Texas Association of Rural Health Clinics. Home. Available online: http://www.tarhc.org/ (accessed on 31 October 2024).
- Texas Association of Community Health Centers. Home. Available online: https://www.tahc.org/ (accessed on 31 October 2024).
- Texas Association of Addiction Professionals. Home. Available online: https://www.taap.org/ (accessed on 31 October 2024).
- Palinkas, L.A.; Horwitz, S.M.; Green, C.A.; Wisdom, J.P.; Duan, N.; Hoagwood, K. Purposeful sampling for qualitative data collection and analysis in mixed method implementation research. Adm. Policy Ment. Health 2015, 42, 533–544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hamilton, A. Qualitative Methods in Rapid Rurn-Around Health Services Research. Available online: https://www.hsrd.research.va.gov/cyberseminars/catalog-archive.cfm (accessed on 26 September 2025).
- Averill, J.B. Matrix analysis as a complementary analytic strategy in qualitative inquiry. Qual. Health Res. 2002, 12, 855–866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewinski, A.A.; Crowley, M.J.; Miller, C.; Bosworth, H.B.; Jackson, G.L.; Steinhauser, K.; White-Clark, C.; McCant, F.; Zullig, L.L. Applied rapid qualitative analysis to develop a contextually appropriate intervention and increase the likelihood of uptake. Med. Care 2021, 59, S242–S251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palinkas, L.A.; Mendon, S.J.; Hamilton, A.B. Innovations in mixed methods evaluations. Annu. Rev. Public Health 2019, 40, 423–442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nowell, L.S.; Norris, J.M.; White, D.E.; Moules, N.J. Thematic analysis: Striving to meet the trustworthiness criteria. Int. J. Qual. Methods 2017, 16, 1609406917733847. [Google Scholar] [CrossRef] [Scilit]
- Kowalski, C.P.; Nevedal, A.L.; Finley, E.P.; Young, J.P.; Lewinski, A.A.; Midboe, A.M.; Hamilton, A.B. Planning for and Assessing Rigor in Rapid Qualitative Analysis (PARRQA): A consensus-based framework for designing, conducting, and reporting. Implement. Sci. 2024, 19, 71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Health Resources and Services Administration. How We Define Rural. Available online: https://www.hrsa.gov/rural-health/about-us/what-is-rural (accessed on 28 January 2026).
- Health Resources and Services Administration. Rural Health Grants Eligibility Analyzer. Available online: https://data.hrsa.gov/topics/rural-health/rural-health-eligibility (accessed on 28 January 2026).
- Health Resources and Services Administration. Glossary. Available online: https://data.hrsa.gov/glossary (accessed on 28 January 2026).
- Health Resources and Services Administration. What Is Shortage Designation? Available online: https://bhw.hrsa.gov/workforce-shortage-areas/shortage-designation (accessed on 28 January 2026).
- Health Resources and Services Administration. Find MUA/P. Available online: https://data.hrsa.gov/topics/health-workforce/shortage-areas/mua-find (accessed on 28 January 2026).
- Nitturi, V.; Chen, T.A.; Kyburz, B.; Martinez Leal, I.; Correa-Fernandez, V.; O’Connor, D.P.; Williams, T.; Garey, L.; Stacey, T.; Wilson, W.T.; et al. Organizational characteristics and readiness for tobacco-free workplace program implementation moderates changes in clinician’s delivery of smoking interventions within behavioral health treatment clinics. Nicotine Tob. Res. 2021, 23, 310–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- LoParco, C.R.; Chen, T.A.; Martinez Leal, I.; Britton, M.; Carter, B.J.; Correa-Fernández, V.; Kyburz, B.; Williams, T.; Casey, K.; Rogova, A.; et al. Organization-level factors associated with changes in the delivery of the five A’s for smoking cessation following the implementation of a comprehensive tobacco-free workplace program within substance use treatment centers. Int. J. Environ. Res. Public Health 2022, 19, 11850. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siddiqi, A.D.; Chen, T.A.; Britton, M.; Martinez Leal, I.; Carter, B.J.; Correa-Fernández, V.; Rogova, A.; Kyburz, B.; Williams, T.; Casey, K.; et al. Changes in substance use treatment providers’ delivery of the 5A’s for non-cigarette tobacco use in the context of a comprehensive tobacco-free workplace program implementation. Int. J. Environ. Res. Public Health 2023, 20, 2730. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carter, B.J.; Siddiqi, A.D.; Chen, T.A.; Britton, M.; Martinez Leal, I.; Correa-Fernández, V.; Rogova, A.; Kyburz, B.; Williams, T.; Casey, K.; et al. Educating substance use treatment center providers on tobacco use treatments is associated with increased provision of counseling and medication to patients who use tobacco. Int. J. Environ. Res. Public Health 2023, 20, 4013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Le, K.; Correa-Fernández, V.; Leal, I.M.; Kyburz, B.; Chen, T.A.; Barrientos, D.; Saenz, E.; Williams, T.; O’Connor, D.P.; Obasi, E.M.; et al. Tobacco-free workplace program at a substance use treatment center. Am. J. Health Behav. 2020, 44, 652–665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feyisetan, J.A.; Britton, M.; Chen, T.A.; Martinez Leal, I.; Sekhar, M.S.; Williams, T.; Casey, K.; Siddiqi, A.D.; Reitzel, L.R. Tobacco-related knowledge among employees at substance use treatment and medical healthcare centers serving rural and medically underserved patients with substance use disorders in Texas, USA. Int. J. Environ. Res. Public Health 2025, 22, 1701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozga, J.E.; Romm, K.F.; Turiano, N.A.; Douglas, A.; Dino, G.; Alexander, L.; Blank, M.D. Cumulative disadvantage as a framework for understanding rural tobacco use disparities. Exp. Clin. Psychopharmacol. 2021, 29, 429–439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selove, R.; Combs, T.; Heckman, C.J.; Neil-Sztramko, S.E.; Scheuermann, T.S.; Ginossar, T.; Leng, J.; Walker, P.D.; Sidani, J.; Salloum, R.G. A scoping review of implementation science in planning and delivering tobacco control interventions in the United States from 2000 to 2020: Frameworks, intervention characteristics, and health equity considerations. Nicotine Tob. Res. 2025, 28, 3–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jørgensen, C.U.; Løkke, A.; Hjorth, P.; Pisinger, C.; Farver-Vestergaard, I. Barriers to implementation of smoking cessation support among healthcare professionals in the secondary healthcare sector: A qualitative and quantitative evaluation. Tob. Prev. Cessat. 2024, 10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Visser, J.E.M.; Nur, F.A.; Rozema, A.D.; Kunst, A.E.; Kuipers, M.A.G. Facilitators and barriers to smoking cessation support among professionals in social and community service settings: A systematic review and thematic synthesis. Health Educ. Res. 2025, 40, cyaf030. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- The Community Preventive Services Task Force. Tobacco Use: Smoke-Free Policies. Available online: https://www.thecommunityguide.org/findings/tobacco-use-smoke-free-policies.html (accessed on 3 November 2018).
- Eby, L.T.; Sparks, T.E.; Evans, E.; Selzer, J.A. A qualitative examination of the positive and negative consequences associated with going tobacco-free in substance abuse treatment: The NY State experience. Nicotine Tob. Res. 2012, 14, 1407–1417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guydish, J.; Yip, D.; Le, T.; Gubner, N.R.; Delucchi, K.; Roman, P. Smoking-related outcomes and associations with tobacco-free policy in addiction treatment, 2015–2016. Drug Alcohol Depend. 2017, 179, 355–361. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCuistian, C.; Kapiteni, K.; Le, T.; Safier, J.; Delucchi, K.; Guydish, J. Reducing tobacco use in substance use treatment: An intervention to promote tobacco-free grounds. J. Subst. Abus. Treat. 2022, 135, 108640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- San Francisco Health Plan. Counseling Your Patients About Tobacco Cessation: The 5A’s. Available online: https://www.sfhp.org/wp-content/files/Counseling-Your-Patients-about-Tobacco-Cessation.pdf (accessed on 30 November 2025).
- Jafry, M.Z.; Reuven, S.M.; Britton, M.; Chen, T.A.; Martinez Leal, I.; Rogova, A.; Kyburz, B.; Williams, T.; Patel, M.; Reitzel, L.R. Providers’ non-cigarette tobacco use intervention practices in relation to beliefs about patients, prioritization of and skills for intervention, and referral knowledge in Texas healthcare centers providing care to persons with behavioral health needs. Int. J. Environ. Res. Public Health 2022, 19, 14269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kilgore, E.A.; Waddell, E.N.; Tannert Niang, K.M.; Murphy, J.; Thihalolipavan, S.; Chamany, S. Provider attitudes and practices on treating tobacco dependence in New York City after 10 years of comprehensive tobacco control efforts. J. Prim. Care Community Health 2021, 12, 2150132720957448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalkhoran, S.; Benowitz Neal, L.; Rigotti Nancy, A. Prevention and treatment of tobacco use. JACC 2018, 72, 1030–1045. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dai, X.; Gil, G.F.; Reitsma, M.B.; Ahmad, N.S.; Anderson, J.A.; Bisignano, C.; Carr, S.; Feldman, R.; Hay, S.I.; He, J.; et al. Health effects associated with smoking: A Burden of Proof study. Nat. Med. 2022, 28, 2045–2055. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American Lung Association. Behavioral Health and Tobacco Use. Available online: https://www.lung.org/quit-smoking/smoking-facts/impact-of-tobacco-use/behavioral-health-tobacco-use (accessed on 28 January 2026).
- American Society of Addiction Medicine. Integrating Tobacco Use Disorder Interventions in Addiction Treatment. Available online: https://www.asam.org/quality-care/clinical-recommendations/tobacco (accessed on 28 January 2026).
- Jafry, M.Z.; Martinez, J.; Chen, T.A.; Britton, M.; Martinez Leal, I.; Rogova, A.; Kyburz, B.; Williams, T.; Patel, M.; Carter, B.J.; et al. Behavioral health care provider’s beliefs, confidence, and knowledge in treating cigarette smoking in relation to their use of the 5A’s intervention. Addict. Behav. Rep. 2023, 17, 100493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moylan, S.; Jacka, F.N.; Pasco, J.A.; Berk, M. How cigarette smoking may increase the risk of anxiety symptoms and anxiety disorders: A critical review of biological pathways. Brain Behav. 2013, 3, 302–326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parrott, A.C. Does cigarette smoking cause stress? Am. Psychol. 1999, 54, 817–820. [Google Scholar] [CrossRef] [PubMed]
- Marlatt, G.A.; Curry, S.; Gordon, J.R. A longitudinal analysis of unaided smoking cessation. J. Consult. Clin. Psychol. 1988, 56, 715–720. [Google Scholar] [CrossRef] [PubMed]
- Prochaska, J.J. Failure to treat tobacco use in mental health and addiction treatment settings: A form of harm reduction? Drug Alcohol Depend. 2010, 110, 177–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McKelvey, K.; Thrul, J.; Ramo, D. Impact of quitting smoking and smoking cessation treatment on substance use outcomes: An updated and narrative review. Addict. Behav. 2017, 65, 161–170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stuyt, E.B. Enforced abstinence from tobacco during in-patient dual-diagnosis treatment improves substance abuse treatment outcomes in smokers. Am. J. Addict. 2015, 24, 252–257. [Google Scholar] [CrossRef] [PubMed]
- Garner, L.; Ratschen, E. Tobacco smoking, associated risk behaviours, and experience with quitting: A qualitative study with homeless smokers addicted to drugs and alcohol. BMC Public Health 2013, 13, 951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kruger, J.; O’Halloran, A.; Rosenthal, A.C.; Babb, S.D.; Fiore, M.C. Receipt of evidence-based brief cessation interventions by health professionals and use of cessation assisted treatments among current adult cigarette-only smokers: National Adult Tobacco Survey, 2009–2010. BMC Public Health 2016, 16, 141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fiore, M. Treating Tobacco Use and Dependence 2008 Update: Clinical Practice Guideline; U.S. Department of Health and Human Services: Rockville, MD, USA, 2008.
- Martinez Leal, I.; Siddiqi, A.D.; Rogova, A.; Britton, M.; Chen, T.A.; Williams, T.; Casey, K.; Sanchez, H.; Reitzel, L.R. Enablers and inhibitors to implementing tobacco cessation interventions within homeless-serving agencies: A qualitative analysis of program partners’ experiences. Cancers 2024, 16, 2162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wani, H.; Britton, M.; Chen, T.A.; Siddiqi, A.D.; Moosa, A.B.; Williams, T.; Casey, K.; Reitzel, L.R.; Martinez Leal, I. Optimizing tobacco-free workplace programs: Applying rapid qualitative analysis to adapt interventions for Texas healthcare centers serving rural and medically underserved patients. Cancers 2025, 17, 2442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sorensen, G.; Barbeau, E.; Hunt, M.K.; Emmons, K. Reducing social disparities in tobacco use: A social-contextual model for reducing tobacco use among blue-collar workers. Am. J. Public Health 2004, 94, 230–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fixsen, D.L.; Naoom, S.; Blase, K.; Friedman, R.; Wallace, F. Implementation Research: A Synthesis of the Literature; Louis de la Parte Florida Mental Health Institute Publication: Tampa, FL, USA, 2005; pp. 23–34. [Google Scholar]


| Select Center Characteristics | All Centers (N = 19) | MHCs (n = 9) | SUTCs (n = 10) | MHCs vs. SUTCs | ||||
|---|---|---|---|---|---|---|---|---|
| Number of… | Mean (SD) | Sum (Range) | Mean (SD) | Sum (Range) | Mean (SD) | Sum (Range) | Statistic | p-Value |
| Counties served | 7.89 (11.51) | 122 (1–40) | 2.56 (1.67) | 23 (1–6) | 12.70 (14.43) | 110 (1–40) | −1.4143 | 0.1743 |
| Rural or partially rural counties served | 7.05 (10.57) | 114 (1–33) | 2.33 (1.73) | 21 (1–6) | 11.30 (13.37) | 102 (1–33) | −1.2743 | 0.2188 |
| Counties with medically underserved areas served | 5.68 (8.00) | 87 (0–29) | 2.11 (1.45) | 19 (0–5) | 8.90 (10.09) | 76 (0–29) | −1.3604 | 0.1905 |
| Unique patients/yearly † | 6094.56 (10,688.54) | 109,702 (21–46,000) | 6102.89 (4255.18) | 54,926 (1000–12,139) | 6086.22 (14,988.79) | 54,776 (21–46,000) | −2.0772 | 0.0532 |
| Total patient visits/yearly † | 21,470.89 (28,909.46) | 386476 (21–98,000) | 20,127.78 (11,386.81) | 181,150 (1750–40,000) | 22,814.00 (40,524.87) | 205,326 (21–98,000) | −1.5903 | 0.1302 |
| Staff (inclusive of healthcare providers) | 85.68 (136.40) | 1628 (3–600) | 68.00 (60.31) | 612 (15–205) | 101.60 (182.71) | 1016 (3–600) | 0.6940 | 0.4965 |
| Healthcare providers | 61.79 (83.66) | 1174 (2–350) | 58.67 (52.75) | 528 (9–170) | 64.60 (107.27) | 646 (2–350) | 0.8169 | 0.4247 |
| % [n] | % [n] | % [n] | ||||||
| Tobacco-free policy existence | 52.63 [10] | 44.44 [4] | 60.00 [6] | 0.4598 | 0.6563 | |||
| All (N = 347) | MHC (n = 173) | SUTC (n = 174) | MHCs vs. SUTCs | ||
|---|---|---|---|---|---|
| % Yes [n] | Statistic | p-Value | |||
| Resource Barriers to Tobacco Treatment | |||||
| Lack of training | 65.57 [179] | 65.94 [91] | 65.19 [88] | −0.108 | 0.914 |
| Lack of time to deliver care | 59.23 [154] | 68.38 [93] | 49.19 [61] | −2.780 | 0.006 |
| Lack of reimbursement | 42.86 [99] | 45.76 [54] | 39.82 [45] | −1.176 | 0.241 |
| Lack of community resources for patient referral | 56.30 [143] | 63.64 [84] | 48.36 [59] | −1.925 | 0.055 |
| Lack of patient education materials | 55.51 [146] | 59.26 [80] | 51.56 [66] | −1.030 | 0.304 |
| Existing Resources to Enforce a TFW policy * | |||||
| Center has resources | 93.08 [323] | 91.33 [158] | 94.83 [165] | −0.638 | 0.524 |
| All (N = 347) | MHC (n = 173) | SUTC (n = 174) | MHCs vs. SUTCs | ||
|---|---|---|---|---|---|
| % Yes [n] | Statistic | p-Value | |||
| TFW Policy * Value | |||||
| TFW policies provide a clean and safe environment for staff and patients | 71.76 [249] | 72.25 [125] | 71.26 [124] | −0.115 | 0.908 |
| TFW policies may help patients and staff quit smoking | 62.25 [216] | 63.58 [110] | 60.92 [106] | −0.607 | 0.544 |
| Tobacco Treatment Value | |||||
| Leadership interest/investment is not a barrier to providing this care | 43.72 [101] | 42.86 [51] | 44.64 [50] | 0.135 | 0.893 |
| Staff interest/investment is not a barrier to providing this care | 49.38 [119] | 46.03 [58] | 53.04 [61] | −0.273 | 0.785 |
| Cessation care is an important part of the center’s missions | 51.01 [170] | 55.49 [96] | 42.53 [74] | −1.249 | 0.213 |
| Themes | Subthemes | Key Findings |
|---|---|---|
| Efficacy Gaps: Additional training and resources are needed to build capacity |
| Pervasive lack of standardized and formal training, tobacco use assessments with regular follow-ups, and patient education materials represent a larger need to build capacity to integrate tobacco treatment services |
| Organizational Factors: Limited institutional frameworks, policies, and practices |
| Absence of individual tobacco-free workplace policies across centers is coupled with current tobacco treatment services ranging from no services and lack of awareness regarding the Quitline to some limited services |
| Valuing: Tobacco treatment was valued as compatible but not a treatment priority |
| Program implementation and training is generally compatible and valued by staff and leadership but treating tobacco use is not their priority |
| Conflicting Attitudes: Negative assumptions about patient tobacco use and smoking to maintain sobriety |
| Staff emphasize the importance of smoking as a “harm reduction” technique or coping mechanism and express concerns of patient disinterest and reluctance |
| Quantitative Results Summary | Qualitative Findings Summary | Integrated Summary of Quantitative and Qualitative Results | Applying Connected Quantitative and Qualitative Results to Inform Capacity Building | |||
|---|---|---|---|---|---|---|
| ORC Construct—Change Efficacy: Resource Availability | Resource barriers for providing tobacco cessation services: lack of resources for cessation care provision: training (65.57%; −0.108, p = 0.914), time to deliver care (59.23%; −2.780, p = 0.006), reimbursement for services (42.86%; −1.176, p = 0.214), community resources for patient referral (56.30%; −1.1925, p = 0.055), and patient education materials (55.51%; −1.030, p = 0.034) | Inadequate supports to deliver cessation care: “[We’ve been] unsuccessful until we get this training, to be honest with you. We have done nothing…” “It can be complicated by the fact that we’re the only provider in our rural area, which means we’re very busy…time is an issue.” “More education [materials]. I know our patients need some help; we’re not going the full—we’re not doing everything we can.” | Findings from both components indicate lack of adequate resources and need for organizational capacity building to support effective implementation of the TRTTF program | Resources provided to support partners included: (a) all-staff tobacco education training tailored to SUTC or MCH setting and patients served; (b) PCs sponsored to attend TTS training to gain expertise in treating tobacco use; (c) brief tobacco use interventions training (5A’s, 5R’s); (d) guidance to facilitate direct TQ referral; (e) selection or development of patient education materials tailored to their settings and populations such as veterans, IDD populations; (f) setting tailored T-t-T program | ||
| Available resources for task demands, to enforce TFW policy: providers reported having the resources to enforce TFWP (93.08%; −0.638, p = 0.524) | Limited concern about TFW policy adoption and enforcement: “I really don’t see that we’re going to have any issues staying a tobacco-free workplace. I think everybody is invested in this. We all see that as a recovery-oriented agency that this is something that we really need to put forth. We need the public to see that we’re invested in this as well.” | Both quantitative and qualitative results indicate capacity in change efficacy for TFW policy adoption and enforcement |  | To enhance capacity, team offered partners: (a) Quit cards for patients seen smoking with TQ contact information; (b) guidance on developing TFW policy aligned with center values; (c) endorsed provision of NRT products and tobacco services to staff | ||
| ORC Construct—Change Valence: Value placed on proposed change | TFW policy value: satisfactory endorsement of TFW policy benefits on: provides patients and staff clean and safe space (71.76%; −0.115, p = 0.908); may help to quit smoking (62.25%; −0.607 p = 0.544) | Providers support TFW policy adoption; concerns about second-hand smoke: “During breaks…a lot of [patients] smoke, and then it would smell very badly. I always prefer to avoid it when I can because it can affect my breathing.” | Results from both components indicate organizational capacity in change value for TFW policy adoption and enforcement | |||
| Cessation Care Value: tepid support from leadership (43.72%; 0.135, p = 0.893) and staff (49.38%; −0.273, p = 0.785) on investing in cessation interventions | Concerns about patient loss of census/complaints: “Possibly [due to] lack of training. We usually don’t implement things here that are not supported by upper administration so that clients could come back and complain.” |  | Qualitative findings support quantitative results that change valence for investing in and delivering patient tobacco cessation care is only moderately valued by leadership and staff |  | To increase valuing of treating tobacco use, center-wide training tailored to MHC/SUTC partners on: (a) how tobacco cessation bolsters SUDs and mental health recovery, how tobacco use is linked to ACEs, calling for the integration of TIC, harm of ENDs use, (MHCs/SUTCs); adverse effects on diabetes, HIV, eye and dental health, CVD, COPD, asthma, and pregnancy (MHCs); (b) dispelling misconceptions and fears such as TFW policy adoption is not linked to decreased patient census; (c) specific topics requested included articles, videos on treating ENDs among youth and during pregnancy | |
| Relative Valuing of Cessation Interventions: about half (51.01%; −1.249, p = 0.213) of providers perceived cessation care as central to their center’s mission | Contending patient priorities: “…our main concern when they come in is the addiction of alcoholism or substance abuse, right?… because we have so many different issues that we deal with in relation to the population we serve. So, it [tobacco use] is a concern, but it’s not a top priority.” |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Bergey, A.E.; Martinez Leal, I.; Britton, M.; Moosa, A.B.; Chen, T.A.; Goulbourne, T.D.; Siddiqi, A.D.; Williams, T.; Casey, K.; Reitzel, L.R. Provider Perspectives on a Tobacco-Free Workplace Program in Healthcare Settings Serving Rural and Medically Underserved Areas of Texas: A Mixed Methods Study on Perceived Resource Availability and Value. Int. J. Environ. Res. Public Health 2026, 23, 898. https://doi.org/10.3390/ijerph23070898
Bergey AE, Martinez Leal I, Britton M, Moosa AB, Chen TA, Goulbourne TD, Siddiqi AD, Williams T, Casey K, Reitzel LR. Provider Perspectives on a Tobacco-Free Workplace Program in Healthcare Settings Serving Rural and Medically Underserved Areas of Texas: A Mixed Methods Study on Perceived Resource Availability and Value. International Journal of Environmental Research and Public Health. 2026; 23(7):898. https://doi.org/10.3390/ijerph23070898
Chicago/Turabian StyleBergey, Abigail E., Isabel Martinez Leal, Maggie Britton, Asfand B. Moosa, Tzuan A. Chen, Tarik D. Goulbourne, Ammar D. Siddiqi, Teresa Williams, Kathleen Casey, and Lorraine R. Reitzel. 2026. "Provider Perspectives on a Tobacco-Free Workplace Program in Healthcare Settings Serving Rural and Medically Underserved Areas of Texas: A Mixed Methods Study on Perceived Resource Availability and Value" International Journal of Environmental Research and Public Health 23, no. 7: 898. https://doi.org/10.3390/ijerph23070898
APA StyleBergey, A. E., Martinez Leal, I., Britton, M., Moosa, A. B., Chen, T. A., Goulbourne, T. D., Siddiqi, A. D., Williams, T., Casey, K., & Reitzel, L. R. (2026). Provider Perspectives on a Tobacco-Free Workplace Program in Healthcare Settings Serving Rural and Medically Underserved Areas of Texas: A Mixed Methods Study on Perceived Resource Availability and Value. International Journal of Environmental Research and Public Health, 23(7), 898. https://doi.org/10.3390/ijerph23070898