Uncovering the Intricate and Heterogeneous Cellular Microenvironment of Cutaneous Melanoma

 ,
 ,
 , and
Abstract
1. Introduction
2. Materials and Methods
3. Intra-Tumoral Heterogeneity
4. Components of the TME
4.1. Cellular Components
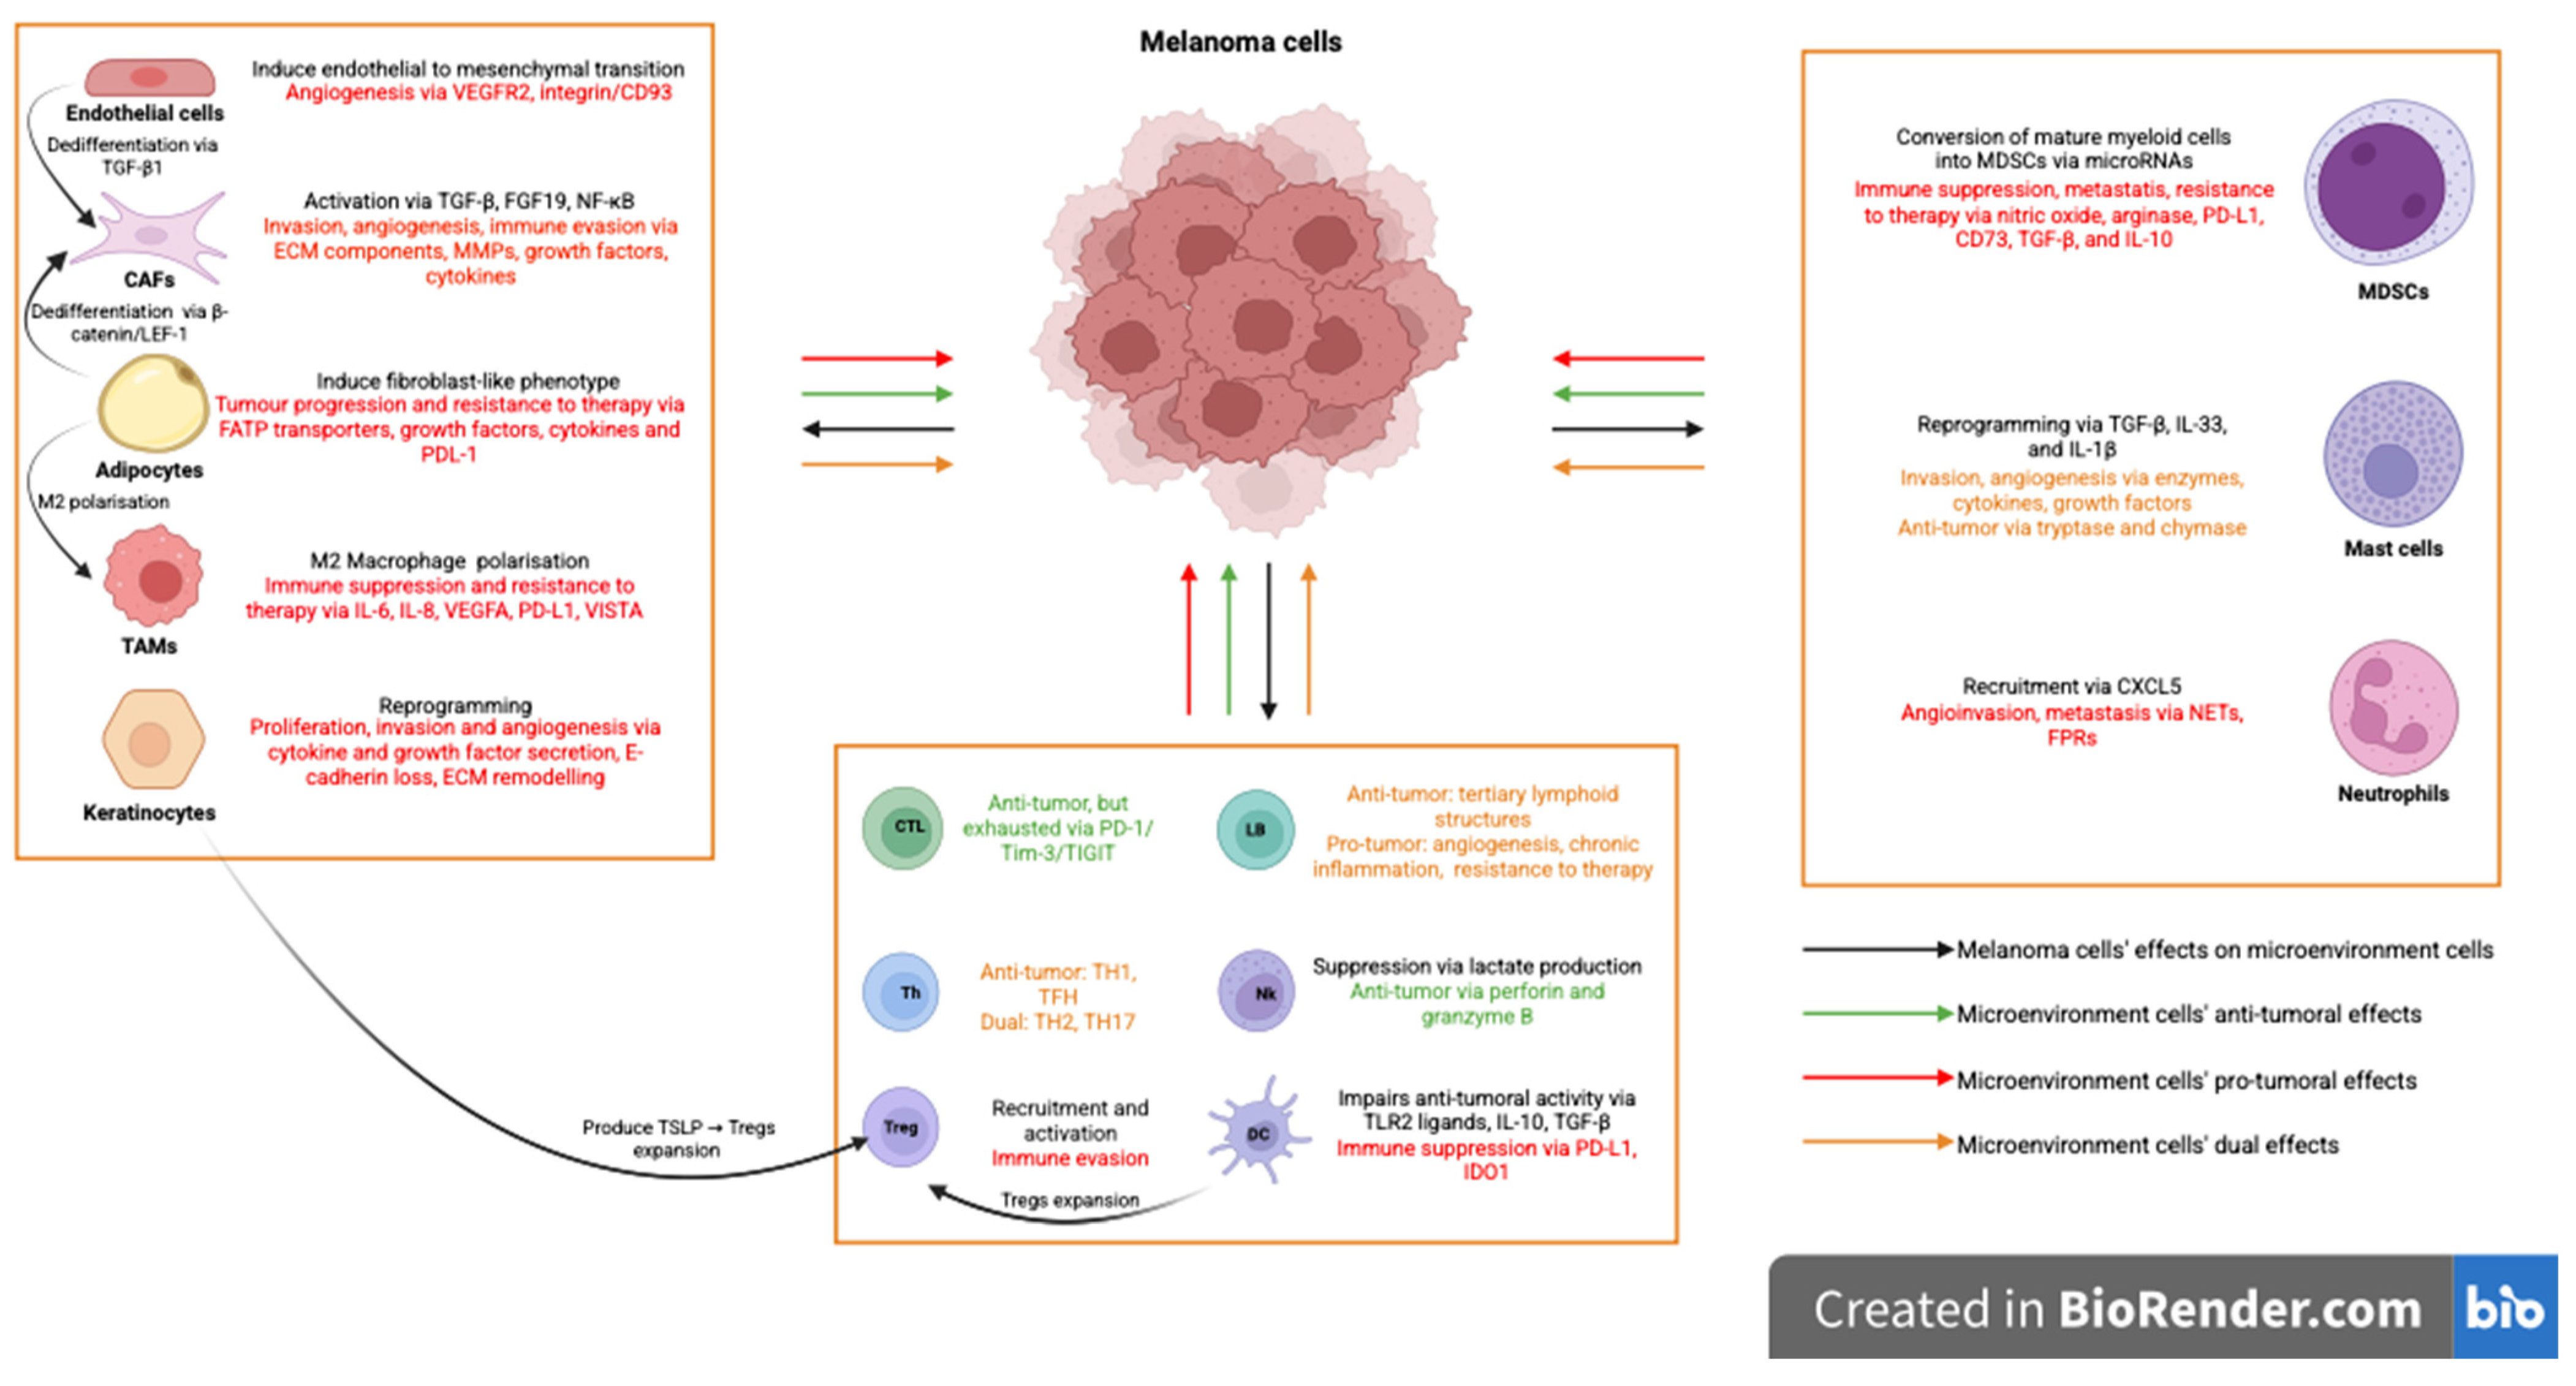
4.1.1. Stromal Cells
Cancer-Associated Fibroblasts (CAFs) Are Key Regulators in Melanoma Progression
The Role of Adipocytes in Melanoma Progression
4.1.2. Endothelial Cells
4.1.3. Immune Cells
Neutrophils Also Influence the Behavior of CM
Tumor-Associated Macrophages (TAMs)
Tumor Infiltrating Lymphocytes (TILs)
4.1.4. Keratinocytes
4.2. Non-Cellular Components
4.2.1. Extracellular Matrix: Composition, Remodeling, Role of Matrix Metalloproteinases, Adhesion Molecules
4.2.2. Cytokines and Growth Factors
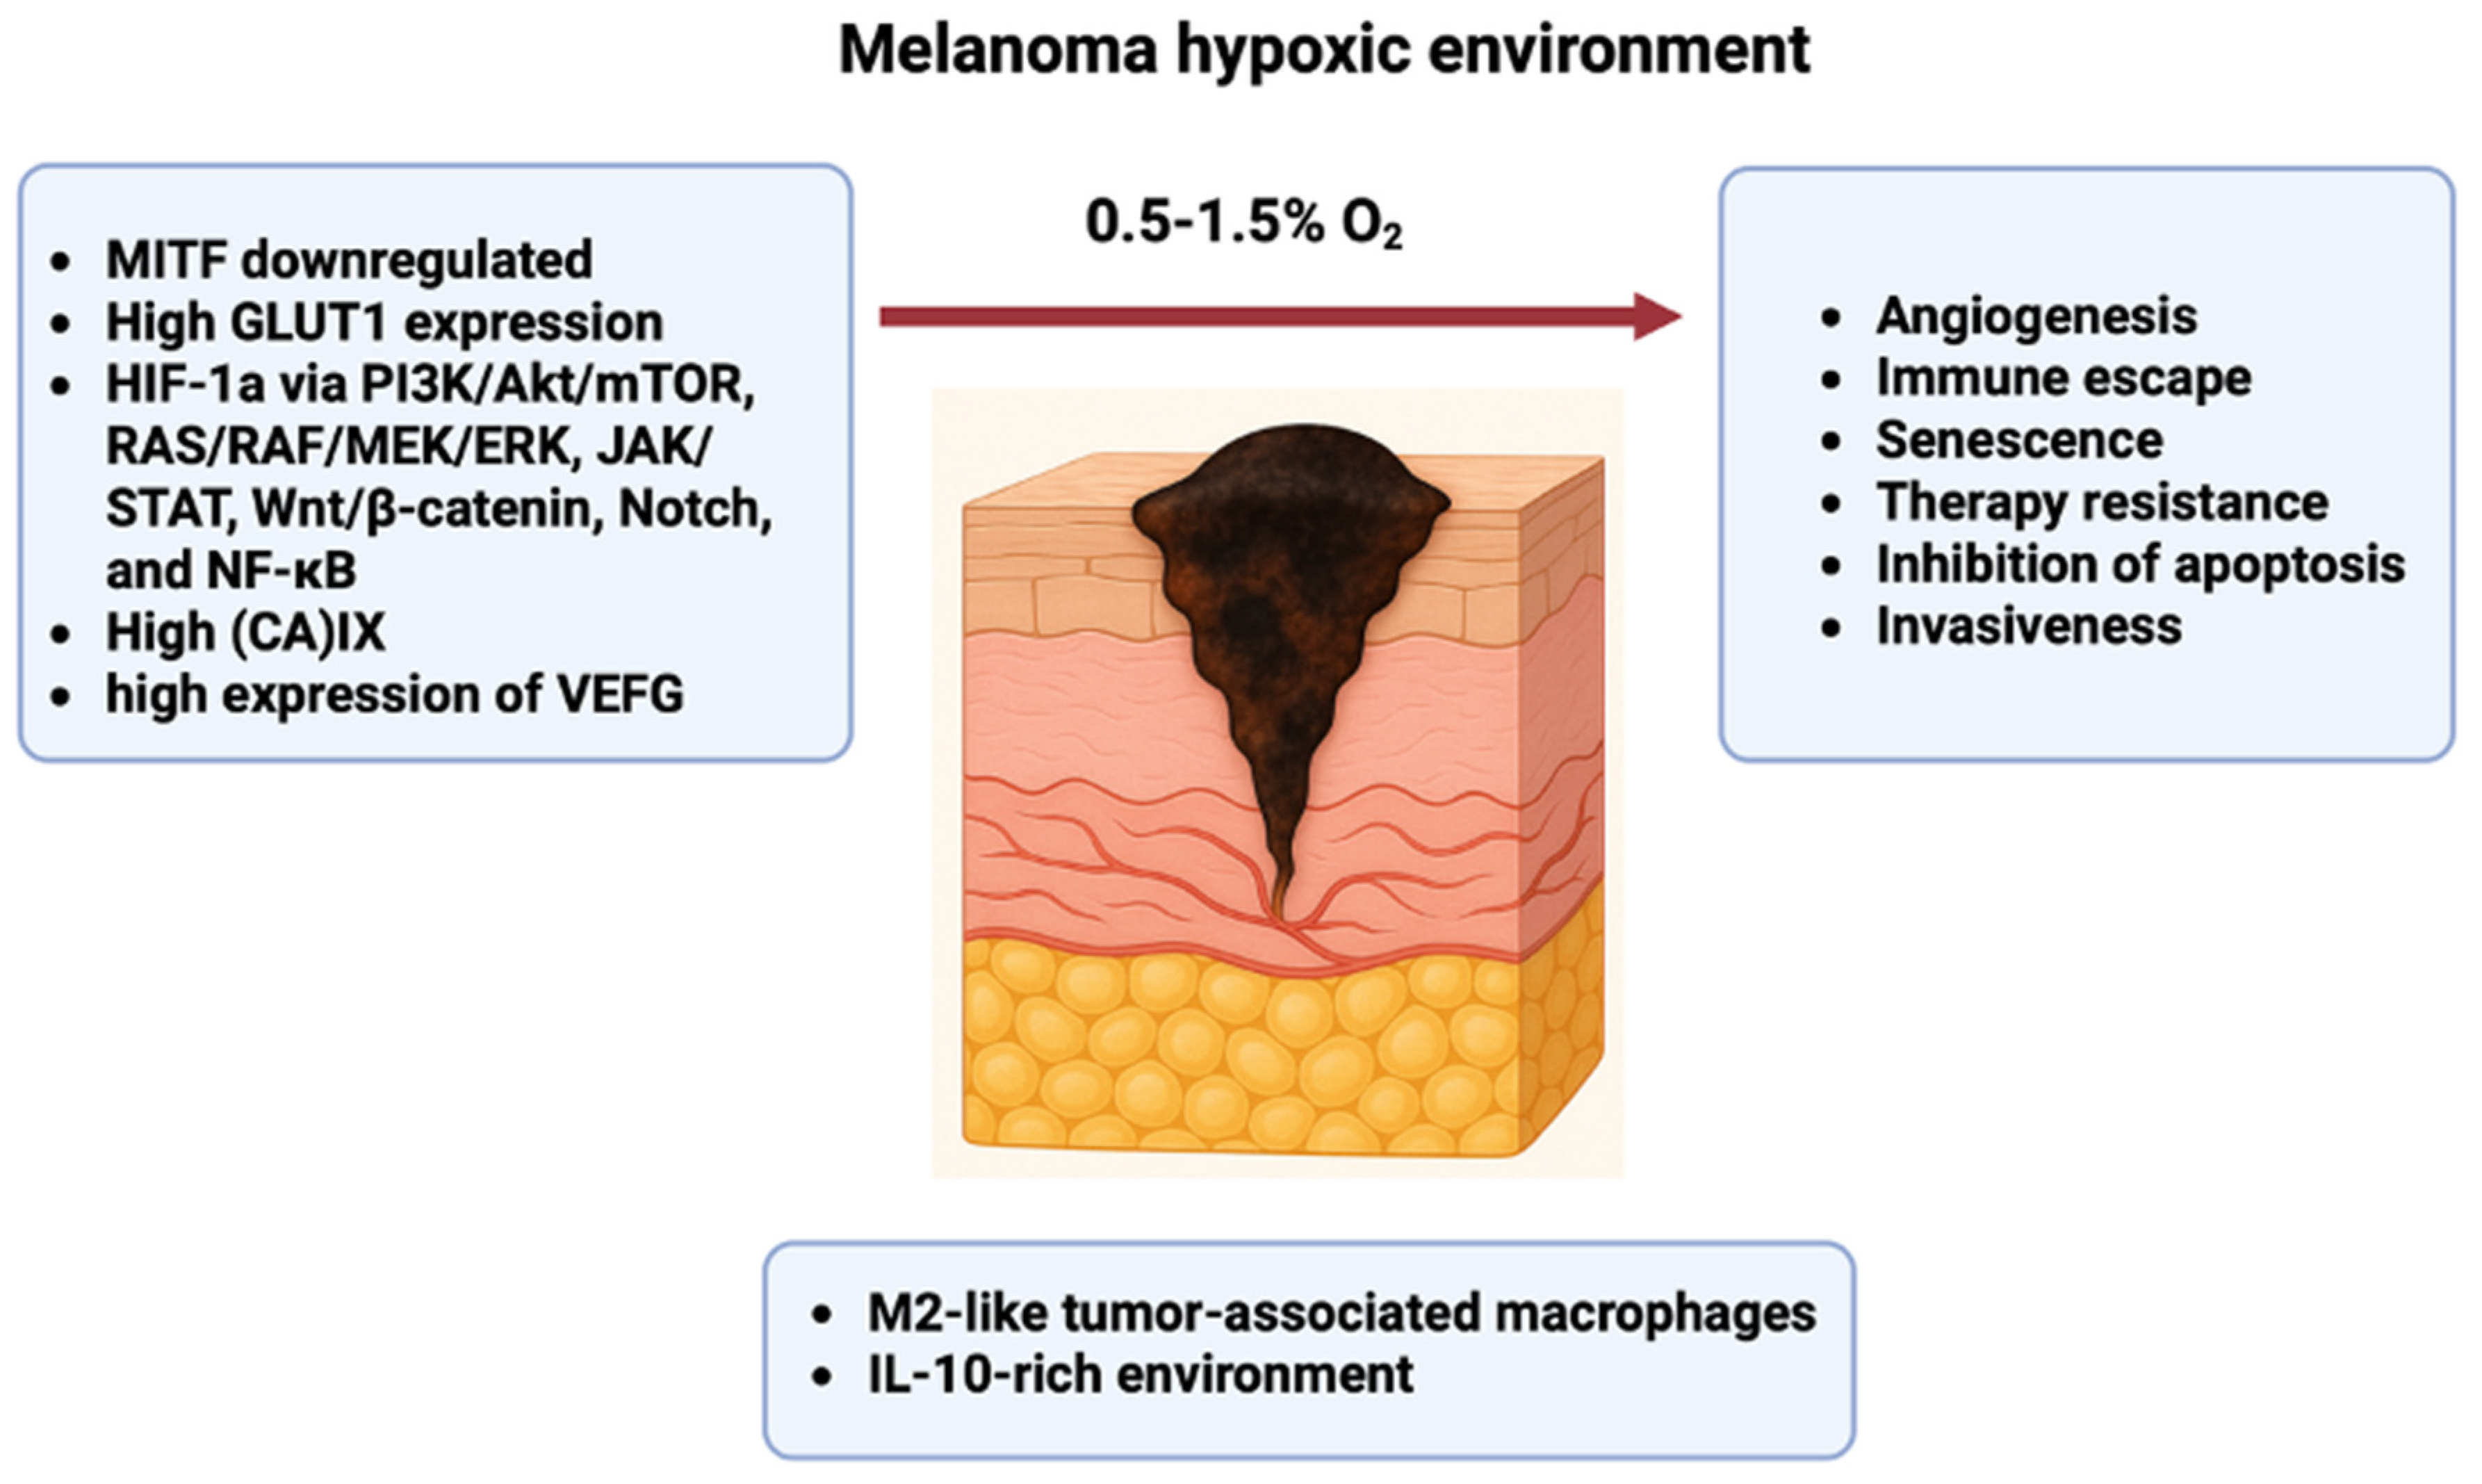
4.2.3. Hypoxic Environment
5. Therapeutic Implications and Future Perspectives
5.1. Prognostic Landscapes: Established vs. Controversial Markers
- Established prognostic markers: The presence of CD8+ cytotoxic T lymphocytes (CTLs) and B-cell signatures—specifically within Tertiary Lymphoid Structures (TLS)—is currently the most robust indicator of positive clinical outcomes and response to immunotherapy. Multiparameter immune and molecular profiling stratifies melanoma patients, enabling personalized TME-directed therapies. Circulating tumor DNA (ctDNA) levels and TME transcriptomic signatures predict responses and resistance mechanisms [251,252,253,254]. Integrating biomarker data guides rational therapeutic combinations and sequences, optimizing efficacy and minimizing toxicity.
- Controversial/context-dependent markers: As detailed in Section 4, while high densities of TAMs, CAFs, and MDSCs generally correlate with poor prognosis, their role can be ambivalent. For example, total macrophage density sometimes shows no association with survival unless polarized to the M2 phenotype [8,73]. Similarly, the role of mast cells remains a subject of ongoing research and lacks a definitive consensus for routine clinical use.
5.2. Therapeutic Targeting: Current Standards vs. Experimental Frontiers
- Targetable today (standard of care): Actionable clinical targets are dominated by the PD-1/CTLA-4 axes. New clinical trials are actively evaluating novel immune modulators such as checkpoint molecules Lymphocyte activation gene 3 (LAG-3), T-cell immunoglobulin and mucin-domain containing-3 (TIM-3), and TIGIT, which are upregulated on exhausted T cells within melanoma TME [255,256,257,258]. Notably, the recent integration of LAG-3 blockade has set a new standard, with dual LAG-3/PD-1 inhibition doubling progression-free survival (PFS) compared to monotherapy [259,260]. Bispecific antibodies targeting these receptors amplify TCR signaling, increasing CTL activation while preserving tolerability [261,262]. Oncolytic virotherapy (T-VEC) also remains a standard local intervention to trigger immunogenic cell death [263]. Oncolytic virotherapy employs viral vectors to trigger immunogenic tumor cell death and potentiate immune recognition [264,265]. Oncolytic viruses combined with checkpoint inhibitors increase T cell infiltration and tumor regression [266,267,268]. Talimogene laherparepvec (T-VEC) combined with pembrolizumab achieved a 39% important objective response rate (ORR), outperforming pembrolizumab monotherapy [263,269].
- Experimental frontiers (clinical trials): Several clinical studies have investigated the potential therapeutic roles of melanoma microenvironmental cellular components. For instance, Colony-stimulating factor 1 receptor (CSF1R) blockade reprograms macrophage phenotypes, enhancing CTL activity. In this context, Pexidartinib, a CSF1R inhibitor, has proven constructive interaction with anti-PD-1 antibodies, improving progression-free survival (PFS) in metastatic melanoma [270,271]. Phase II trials confirmed enhanced tumor regression and immune activation with combination regimens [272]. Next-generation strategies are also focusing on the “non-immune” TME. CAFs produce C-X-C Motif Chemokine Ligand 12 (CXCL12), which facilitates T cell exclusion and immunosuppression [273]. C-X-C Motif Chemokine Ligand 4 (CXCR4) antagonism, via AMD3100, disrupts this axis, allowing T cell tumor infiltration [274,275,276]. A clinical trial combining AMD3100 with pembrolizumab yielded an important objective response in PD-1 refractory melanoma [277]. Matrix metalloproteinase inhibitors such as Marimastat modulate ECM remodeling to decrease invasiveness and improve immune cell access [172]. Epigenetic modifiers, including DNMT and HDAC inhibitors, reverse tumor antigen silencing by increasing Major Histocompatibility Complex (MHC) expression and neoantigen presentation [278,279]. Notably, Entinostat combined with anti-PD-1 has yielded significant modifications of ORR in resistant models, with clinical trials reporting promising responses and manageable toxicity [280,281,282,283,284]. Regarding soluble factors, TGF-β signaling blockade with galunisertib reduced Treg recruitment and fibrosis, thereby increasing CD8+ T cell infiltration [285,286,287]. IL-10 receptor blockade activated DCs, augmenting antigen presentation and T cell priming [288,289,290,291]. These cytokine neutralizations, combined with checkpoint inhibitors, prove synergistic tumor control, supporting further clinical investigation [292].
5.3. Evidence Levels: Preclinical vs. Human Outcome Data
- Preclinical/early-phase data: Many metabolic and physical interventions remain largely in the preclinical or Phase I stage. Metabolic reprogramming in melanoma generates elevated lactate, which suppresses CTL function and promotes TAM differentiation [293]. Lactate dehydrogenase A (LDHA) inhibitors reduce lactate production, thereby restoring immune activity [294,295]. The glycolytic inhibitor 2-deoxy-D-glucose (2-DG) synergizes with PD-1 blockade, increasing CD8+ T cell tumor infiltration [296,297,298]. Early-phase clinical studies indicate LDHA inhibition combined with checkpoint blockade is well-tolerated and promotes tumor regression [299,300]. Combination therapies that target hypoxia pathways modulate the immune landscape and improve clinical outcomes. Hypoxia within melanoma TME upregulates HIF-1α, increasing VEGF and PD-L1 expression [188,301]. Evofosfamide, a hypoxia-activated molecule, selectively kills hypoxic melanoma cells, thereby enhancing the efficacy of PD-1 blockade and improving the response rate in murine models [302,303].
- Biomaterial-based systems deliver immunomodulators locally within melanoma TME. In this respect, early phase data have also shown that STING agonist-laden hydrogels enhanced DC maturation and CD8+ T cell recruitment, doubling survival in preclinical melanoma models [304,305,306]. Extracellular vesicles (EVs) mediate intercellular communication within melanoma TME by transferring immunosuppressive agents [307,308,309]. Suppressing EV biogenesis through a neutral sphingomyelinase (SMase) inhibitor—the GW4869—reduces metastasis and enhances T cell activation in murine models [310,311,312]. EV-based therapeutic platforms are under development for the targeted delivery of immunomodulators [313,314,315]. Nanoparticle-mediated siRNA targeting PD-L1 or IDO improved tumor-specific immune activation and reduced systemic exposure [316,317,318].
- Human-validated data: Strategies such as vasculature normalization with Bevacizumab are supported by high-level clinical evidence. Bevacizumab normalized vasculature and synergized with ipilimumab, extending median overall survival by six months compared to ipilimumab monotherapy [319,320,321]. Similarly, dual checkpoint blockade with LAG-3 and PD-1 prolongs PFS and induces durable responses [259,322,323]. The most promising clinical results involve multi-target strategies. Trials combining CSF1R and CXCR4 inhibitors with PD-1 blockade have yielded ORRs exceeding 40% in refractory populations [324,325,326,327]. Furthermore, combination therapies targeting different TME components with systemic checkpoint inhibitors continue to produce enhanced antitumor effects across diverse patient cohorts [15,328,329,330].
6. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
References
- Davis, L.E.; Shalin, S.C.; Tackett, A.J. Current state of melanoma diagnosis and treatment. Cancer Biol. Ther. 2019, 20, 1366–1379. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Ma, S.; Zhu, S.; Zhu, L.; Guo, W. Advances in Immunotherapy and Targeted Therapy of Malignant Melanoma. Biomedicines 2025, 13, 225. [Google Scholar] [CrossRef] [Scilit]
- Gosman, L.M.; Țăpoi, D.-A.; Costache, M. Cutaneous Melanoma: A Review of Multifactorial Pathogenesis, Immunohistochemistry, and Emerging Biomarkers for Early Detection and Management. Int. J. Mol. Sci. 2023, 24, 15881. [Google Scholar] [CrossRef] [Scilit]
- Boleti, A.P.D.A.; Jacobowski, A.C.; Monteiro-Alfredo, T.; Pereira, A.P.R.; Oliva, M.L.V.; Maria, D.A.; Macedo, M.L.R. Cutaneous Melanoma: An Overview of Physiological and Therapeutic Aspects and Biotechnological Use of Serine Protease Inhibitors. Molecules 2024, 29, 3891. [Google Scholar] [CrossRef] [Scilit]
- Țăpoi, D.A.; Derewicz, D.; Gheorghișan-Gălățeanu, A.-A.; Dumitru, A.V.; Ciongariu, A.M.; Costache, M. The Impact of Clinical and Histopathological Factors on Disease Progression and Survival in Thick Cutaneous Melanomas. Biomedicines 2023, 11, 2616. [Google Scholar] [CrossRef] [Scilit]
- Garrison, Z.R.; Hall, C.M.; Fey, R.M.; Clister, T.; Khan, N.; Nichols, R.; Kulkarni, R.P. Advances in Early Detection of Melanoma and the Future of At-Home Testing. Life 2023, 13, 974. [Google Scholar] [CrossRef] [Scilit]
- Kim, U.; Hoehn, R.S.; Koroukian, S.M.; Rose, J.; Bordeaux, J.S.; Carroll, B.T. Melanoma detection, treatment, survival, and mortality through year 2 of the pandemic. Arch. Dermatol. Res. 2025, 317, 209. [Google Scholar] [CrossRef] [Scilit]
- Zilberg, C.; Ferguson, A.L.; Lyons, J.G.; Gupta, R.; Damian, D.L. The tumor immune microenvironment in primary cutaneous melanoma. Arch. Dermatol. Res. 2025, 317, 273. [Google Scholar] [CrossRef] [Scilit]
- Fisher, R.; Pusztai, L.; Swanton, C. Cancer heterogeneity: Implications for targeted therapeutics. Br. J. Cancer 2013, 108, 479–485. [Google Scholar] [CrossRef] [Scilit]
- Fattore, L.; Ruggiero, C.F.; Liguoro, D.; Mancini, R.; Ciliberto, G. Single cell analysis to dissect molecular heterogeneity and disease evolution in metastatic melanoma. Cell Death Dis. 2019, 10, 827. [Google Scholar] [CrossRef] [Scilit]
- Jamal-Hanjani, M.; Quezada, S.A.; Larkin, J.; Swanton, C. Translational Implications of Tumor Heterogeneity. Clin. Cancer Res. 2015, 21, 1258–1266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Angelova, M.; Mlecnik, B.; Vasaturo, A.; Bindea, G.; Fredriksen, T.; Lafontaine, L.; Buttard, B.; Morgand, E.; Bruni, D.; Jouret-Mourin, A.; et al. Evolution of Metastases in Space and Time under Immune Selection. Cell 2018, 175, 751–765. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahmed, F.; Haass, N.K. Microenvironment-Driven Dynamic Heterogeneity and Phenotypic Plasticity as a Mechanism of Melanoma Therapy Resistance. Front. Oncol. 2018, 8, 173. [Google Scholar] [CrossRef] [Scilit]
- Mandalà, M.; Ugolini, F.; Caldirola, L.; Rulli, E.; Manca, A.; Sini, M.C.; Simi, S.; Baroni, G.; Costabile, S.; De Giorgi, V.; et al. Tumour microenvironment heterogeneity in primary and metastatic paired melanoma samples and its correlation with genetic features and prognosis. Eur. J. Cancer 2025, 229, 115755. [Google Scholar] [CrossRef] [Scilit]
- Sikorski, H.; Żmijewski, M.A.; Piotrowska, A. Tumor Microenvironment in Melanoma—Characteristic and Clinical Implications. Int. J. Mol. Sci. 2025, 26, 6778. [Google Scholar] [CrossRef] [Scilit]
- Mazurkiewicz, J.; Simiczyjew, A.; Dratkiewicz, E.; Pietraszek-Gremplewicz, K.; Majkowski, M.; Kot, M.; Ziętek, M.; Matkowski, R.; Nowak, D. Melanoma cells with diverse invasive potential differentially induce the activation of normal human fibroblasts. Cell Commun. Signal. 2022, 20, 63. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Liu, Y.; Yang, L.; Jiang, Y.; Qian, Q. TIM-3 shuttled by MV3 cells-secreted exosomes inhibits CD4+ T cell immune function and induces macrophage M2 polarization to promote the growth and metastasis of melanoma cells. Transl. Oncol. 2022, 18, 101334. [Google Scholar] [CrossRef] [Scilit]
- Simiczyjew, A.; Wądzyńska, J.; Pietraszek-Gremplewicz, K.; Kot, M.; Ziętek, M.; Matkowski, R.; Nowak, D. Melanoma cells induce dedifferentiation and metabolic changes in adipocytes present in the tumor niche. Cell. Mol. Biol. Lett. 2023, 28, 58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Z.; Gao, Y.; Cao, Y.; He, F.; Jiang, R.; Liu, H.; Cai, H.; Zan, T. Extracellular RNA in melanoma: Advances, challenges, and opportunities. Front. Cell Dev. Biol. 2023, 11, 1141543. [Google Scholar] [CrossRef] [Scilit]
- Bennett, P.E.; Bemis, L.; Norris, D.A.; Shellman, Y.G. miR in melanoma development: miRNAs and acquired hallmarks of cancer in melanoma. Physiol. Genom. 2013, 45, 1049–1059. [Google Scholar] [CrossRef] [Scilit]
- Díaz-Martínez, M.; Benito-Jardón, L.; Alonso, L.; Koetz-Ploch, L.; Hernando, E.; Teixidó, J. miR-204-5p and miR-211-5p Contribute to BRAF Inhibitor Resistance in Melanoma. Cancer Res. 2018, 78, 1017–1030. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Surman, M.; Jankowska, U.; Wilczak, M.; Przybyło, M. Similarities and Differences in the Protein Composition of Cutaneous Melanoma Cells and Their Exosomes Identified by Mass Spectrometry. Cancers 2023, 15, 1097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gerloff, D.; Lützkendorf, J.; Moritz, R.K.C.; Wersig, T.; Mäder, K.; Müller, L.P.; Sunderkötter, C. Melanoma-Derived Exosomal miR-125b-5p Educates Tumor Associated Macrophages (TAMs) by Targeting Lysosomal Acid Lipase A (LIPA). Cancers 2020, 12, 464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rahimi, A.; Malakoutikhah, Z.; Rahimmanesh, I.; Ferns, G.A.; Nedaeinia, R.; Ishaghi, S.M.M.; Dana, N.; Haghjooy Javanmard, S. The nexus of natural killer cells and melanoma tumor microenvironment: Crosstalk, chemotherapeutic potential, and innovative NK cell-based therapeutic strategies. Cancer Cell Int. 2023, 23, 312. [Google Scholar] [CrossRef] [Scilit]
- Andreucci, E.; Peppicelli, S.; Ruzzolini, J.; Bianchini, F.; Biagioni, A.; Papucci, L.; Magnelli, L.; Mazzanti, B.; Stecca, B.; Calorini, L. The acidic tumor microenvironment drives a stem-like phenotype in melanoma cells. J. Mol. Med. 2020, 98, 1431–1446. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Liu, H.; Li, J.; Fu, C.; Jiang, B.; Chen, B.; Zou, Y.; Yu, B.; Song, B. MLLT3 Regulates Melanoma Stemness and Progression by Inhibiting HMGB1 Nuclear Entry and MAGEA1 M5C Modification. Adv. Sci. 2024, 11, 2408529. [Google Scholar] [CrossRef] [Scilit]
- Kanai, M.; Shinagawa, A.; Ota, M.; Virgona, N.; Yano, T. Resveratrol Can Differentiate Human Melanoma Stem-like Cells from Spheroids Treated with All-Trans Retinoic Acid. Anticancer Res. 2024, 44, 5283–5292. [Google Scholar] [CrossRef] [Scilit]
- Li, L.; Dragulev, B.; Zigrino, P.; Mauch, C.; Fox, J.W. The invasive potential of human melanoma cell lines correlates with their ability to alter fibroblast gene expression in vitro and the stromal microenvironment in vivo. Int. J. Cancer 2009, 125, 1796–1804. [Google Scholar] [CrossRef] [Scilit]
- Papaccio, F.; Kovacs, D.; Bellei, B.; Caputo, S.; Migliano, E.; Cota, C.; Picardo, M. Profiling Cancer-Associated Fibroblasts in Melanoma. Int. J. Mol. Sci. 2021, 22, 7255. [Google Scholar] [CrossRef] [Scilit]
- Kanzaki, R.; Pietras, K. Heterogeneity of cancer-associated fibroblasts: Opportunities for precision medicine. Cancer Sci. 2020, 111, 2708–2717. [Google Scholar] [CrossRef] [Scilit]
- Falcone, I.; Conciatori, F.; Bazzichetto, C.; Ferretti, G.; Cognetti, F.; Ciuffreda, L.; Milella, M. Tumor Microenvironment: Implications in Melanoma Resistance to Targeted Therapy and Immunotherapy. Cancers 2020, 12, 2870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Del Curatolo, A.; Conciatori, F.; Cesta Incani, U.; Bazzichetto, C.; Falcone, I.; Corbo, V.; D’Agosto, S.; Eramo, A.; Sette, G.; Sperduti, I.; et al. Therapeutic potential of combined BRAF/MEK blockade in BRAF-wild type preclinical tumor models. J. Exp. Clin. Cancer Res. 2018, 37, 140. [Google Scholar] [CrossRef] [Scilit]
- Hutchenreuther, J.; Vincent, K.; Norley, C.; Racanelli, M.; Gruber, S.B.; Johnson, T.M.; Fullen, D.R.; Raskin, L.; Perbal, B.; Holdsworth, D.W.; et al. Activation of cancer-associated fibroblasts is required for tumor neovascularization in a murine model of melanoma. Matrix Biol. 2018, 74, 52–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, L.; Yang, K.; Wickett, R.R.; Kadekaro, A.L.; Zhang, Y. Targeted deactivation of cancer-associated fibroblasts by β-catenin ablation suppresses melanoma growth. Tumor Biol. 2016, 37, 14235–14248. [Google Scholar] [CrossRef] [Scilit]
- Straussman, R.; Morikawa, T.; Shee, K.; Barzily-Rokni, M.; Qian, Z.R.; Du, J.; Davis, A.; Mongare, M.M.; Gould, J.; Frederick, D.T.; et al. Tumour micro-environment elicits innate resistance to RAF inhibitors through HGF secretion. Nature 2012, 487, 500–504. [Google Scholar] [CrossRef] [Scilit]
- Perrichet, A.; Ghiringhelli, F.; Rébé, C. Understanding Inflammasomes and PD-1/PD-L1 Crosstalk to Improve Cancer Treatment Efficiency. Cancers 2020, 12, 3550. [Google Scholar] [CrossRef] [Scilit]
- Li, Z.; Zhou, J.; Zhang, J.; Li, S.; Wang, H.; Du, J. Cancer-associated fibroblasts promote PD-L1 expression in mice cancer cells via secreting CXCL5. Int. J. Cancer 2019, 145, 1946–1957. [Google Scholar] [CrossRef] [Scilit]
- Piotrowska, A.; Zaucha, R.; Król, O.; Żmijewski, M.A. Vitamin D Modulates the Response of Patient-Derived Metastatic Melanoma Cells to Anticancer Drugs. Int. J. Mol. Sci. 2023, 24, 8037. [Google Scholar] [CrossRef] [Scilit]
- Pizzurro, G.A.; Liu, C.; Bridges, K.; Alexander, A.F.; Huang, A.; Baskaran, J.P.; Ramseier, J.; Bosenberg, M.W.; Mak, M.; Miller-Jensen, K. 3D Model of the Early Melanoma Microenvironment Captures Macrophage Transition into a Tumor-Promoting Phenotype. Cancers 2021, 13, 4579. [Google Scholar] [CrossRef] [Scilit]
- Forsthuber, A.; Aschenbrenner, B.; Korosec, A.; Jacob, T.; Annusver, K.; Krajic, N.; Kholodniuk, D.; Frech, S.; Zhu, S.; Purkhauser, K.; et al. Cancer-associated fibroblast subtypes modulate the tumor-immune microenvironment and are associated with skin cancer malignancy. Nat. Commun. 2024, 15, 9678. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xin, L.; Gao, J.; Zheng, Z.; Chen, Y.; Lv, S.; Zhao, Z.; Yu, C.; Yang, X.; Zhang, R. Fibroblast Activation Protein-α as a Target in the Bench-to-Bedside Diagnosis and Treatment of Tumors: A Narrative Review. Front. Oncol. 2021, 11, 648187. [Google Scholar] [CrossRef] [Scilit]
- Munoz-Couselo, E.; Soria Rivas, A.; Sandhu, S.; Long, G.V.; Sanmamed, M.F.; Spreafico, A.; Buchbinder, E.; Sznol, M.; Prenen, H.; Fedenko, A.; et al. Phase Ib Study of Immunocytokine Simlukafusp Alfa (FAP-IL2v) Combined with Pembrolizumab for Treatment of Advanced and/or Metastatic Melanoma. Cancer Res. Commun. 2025, 5, 358–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, J.; Morley, T.S.; Kim, M.; Clegg, D.J.; Scherer, P.E. Obesity and cancer—Mechanisms underlying tumour progression and recurrence. Nat. Rev. Endocrinol. 2014, 10, 455–465. [Google Scholar] [CrossRef] [Scilit]
- Zoico, E.; Darra, E.; Rizzatti, V.; Tebon, M.; Franceschetti, G.; Mazzali, G.; Rossi, A.P.; Fantin, F.; Zamboni, M. Role of adipose tissue in melanoma cancer microenvironment and progression. Int. J. Obes. 2018, 42, 344–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malvi, P.; Chaube, B.; Pandey, V.; Vijayakumar, M.V.; Boreddy, P.R.; Mohammad, N.; Singh, S.V.; Bhat, M.K. Obesity induced rapid melanoma progression is reversed by orlistat treatment and dietary intervention: Role of adipokines. Mol. Oncol. 2015, 9, 689–703. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pandey, V.; Vijayakumar, M.V.; Ajay, A.K.; Malvi, P.; Bhat, M.K. Diet-induced obesity increases melanoma progression: Involvement of Cav-1 and FASN. Int. J. Cancer 2012, 130, 497–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pereira, F.V.; Melo, A.C.L.; Silva, M.B.; de Melo, F.M.; Terra, F.F.; Castro, I.A.; Perandini, L.A.; Miyagi, M.T.; Sato, F.T.; Origassa, C.S.T.; et al. Interleukin-6 and the Gut Microbiota Influence Melanoma Progression in Obese Mice. Nutr. Cancer 2021, 73, 642–651. [Google Scholar] [CrossRef] [Scilit]
- Zhang, M.; Di Martino, J.S.; Bowman, R.L.; Campbell, N.R.; Baksh, S.C.; Simon-Vermot, T.; Kim, I.S.; Haldeman, P.; Mondal, C.; Yong-Gonzales, V.; et al. Adipocyte-Derived Lipids Mediate Melanoma Progression via FATP Proteins. Cancer Discov. 2018, 8, 1006–1025. [Google Scholar] [CrossRef] [Scilit]
- Amalinei, C.; Grigoraș, A.; Lozneanu, L.; Căruntu, I.-D.; Giușcă, S.-E.; Balan, R.A. The Interplay Between Tumour Microenvironment Components in Malignant Melanoma. Medicina 2022, 58, 365. [Google Scholar] [CrossRef] [Scilit]
- Wu, B.; Chiang, H.-C.; Sun, X.; Yuan, B.; Mitra, P.; Hu, Y.; Curiel, T.J.; Li, R. Genetic ablation of adipocyte PD-L1 reduces tumor growth but accentuates obesity-associated inflammation. J. Immunother. Cancer 2020, 8, e000964. [Google Scholar] [CrossRef] [Scilit]
- Jeon, T.J.; Kim, O.-H.; Kang, H.; Lee, H.J. Preadipocytes potentiate melanoma progression and M2 macrophage polarization in the tumor microenvironment. Biochem. Biophys. Res. Commun. 2024, 721, 150129. [Google Scholar] [CrossRef] [Scilit]
- Gupta, A.; Das, D.; Taneja, R. Targeting Dysregulated Lipid Metabolism in Cancer with Pharmacological Inhibitors. Cancers 2024, 16, 1313. [Google Scholar] [CrossRef] [Scilit]
- Schuiveling, M.; Ter Maat, L.S.; Van Duin, I.A.J.; Verheijden, R.J.; Troenokarso, M.F.; Moeskops, P.; Verhoeff, J.J.C.; Elias, S.G.; van Amsterdam, W.A.C.; Burgers, F.; et al. Body composition and checkpoint inhibitor treatment outcomes in advanced melanoma: A multicenter cohort study. J. Natl. Cancer Inst. 2025, 117, 1245–1252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carmeliet, P. Angiogenesis in health and disease. Nat. Med. 2003, 9, 653–660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hashemi, G.; Dight, J.; Khosrotehrani, K.; Sormani, L. Melanoma Tumour Vascularization and Tissue-Resident Endothelial Progenitor Cells. Cancers 2022, 14, 4216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Donovan, P.; Patel, J.; Dight, J.; Wong, H.Y.; Sim, S.-L.; Murigneux, V.; Francois, M.; Khosrotehrani, K. Endovascular progenitors infiltrate melanomas and differentiate towards a variety of vascular beds promoting tumor metastasis. Nat. Commun. 2019, 10, 18. [Google Scholar] [CrossRef] [Scilit]
- Helal-Neto, E.; Brandão-Costa, R.M.; Saldanha-Gama, R.; Ribeiro-Pereira, C.; Midlej, V.; Benchimol, M.; Morandi, V.; Barja-Fidalgo, C. Priming Endothelial Cells with a Melanoma-Derived Extracellular Matrix Triggers the Activation of αvβ3/VEGFR2 Axis. J. Cell. Physiol. 2016, 231, 2464–2473. [Google Scholar] [CrossRef] [Scilit]
- Kumar, M.P.; Du, J.; Lagoudas, G.; Jiao, Y.; Sawyer, A.; Drummond, D.C.; Lauffenburger, D.A.; Raue, A. Analysis of Single-Cell RNA-Seq Identifies Cell-Cell Communication Associated with Tumor Characteristics. Cell Rep. 2018, 25, 1458–1468. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Chen, W.; Torphy, R.J.; Yao, S.; Zhu, G.; Lin, R.; Lugano, R.; Miller, E.N.; Fujiwara, Y.; Bian, L.; et al. Blockade of the CD93 pathway normalizes tumor vasculature to facilitate drug delivery and immunotherapy. Sci. Transl. Med. 2021, 13, eabc8922. [Google Scholar] [CrossRef] [Scilit]
- Demaria, O.; De Gassart, A.; Coso, S.; Gestermann, N.; Di Domizio, J.; Flatz, L.; Gaide, O.; Michielin, O.; Hwu, P.; Petrova, T.V.; et al. STING activation of tumor endothelial cells initiates spontaneous and therapeutic antitumor immunity. Proc. Natl. Acad. Sci. USA 2015, 112, 15408–15413. [Google Scholar] [CrossRef] [Scilit]
- Krizbai, I.A.; Gasparics, Á.; Nagyőszi, P.; Fazakas, C.; Molnár, J.; Wilhelm, I.; Bencs, R.; Rosivall, L.; Sebe, A. Endothelial-Mesenchymal Transition of Brain Endothelial Cells: Possible Role during Metastatic Extravasation. PLoS ONE 2015, 10, e0119655. [Google Scholar] [CrossRef] [Scilit]
- Medici, D.; Kalluri, R. Endothelial–mesenchymal transition and its contribution to the emergence of stem cell phenotype. Semin. Cancer Biol. 2012, 22, 379–384. [Google Scholar] [CrossRef] [Scilit]
- Nagai, N.; Ohguchi, H.; Nakaki, R.; Matsumura, Y.; Kanki, Y.; Sakai, J.; Aburatani, H.; Minami, T. Downregulation of ERG and FLI1 expression in endothelial cells triggers endothelial-to-mesenchymal transition. PLoS Genet. 2018, 14, e1007826. [Google Scholar] [CrossRef] [Scilit]
- Schmidt, H.; Suciu, S.; Punt, C.J.A.; Gore, M.; Kruit, W.; Patel, P.; Lienard, D.; von der Maase, H.; Eggermont, A.M.M.; Keilholz, U. Pretreatment Levels of Peripheral Neutrophils and Leukocytes As Independent Predictors of Overall Survival in Patients with American Joint Committee on Cancer Stage IV Melanoma: Results of the EORTC 18951 Biochemotherapy Trial. J. Clin. Oncol. 2007, 25, 1562–1569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jensen, T.O.; Schmidt, H.; Møller, H.J.; Donskov, F.; Høyer, M.; Sjoegren, P.; Christensen, I.J.; Steiniche, T. Intratumoral neutrophils and plasmacytoid dendritic cells indicate poor prognosis and are associated with pSTAT3 expression in AJCC stage I/II melanoma. Cancer 2012, 118, 2476–2485. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anselmi, M.; Fontana, F.; Marzagalli, M.; Gagliano, N.; Sommariva, M.; Limonta, P. Melanoma Stem Cells Educate Neutrophils to Support Cancer Progression. Cancers 2022, 14, 3391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bald, T.; Quast, T.; Landsberg, J.; Rogava, M.; Glodde, N.; Lopez-Ramos, D.; Kohlmeyer, J.; Riesenberg, S.; van den Boorn-Konijnenberg, D.; Hömig-Hölzel, C.; et al. Ultraviolet-radiation-induced inflammation promotes angiotropism and metastasis in melanoma. Nature 2014, 507, 109–113. [Google Scholar] [CrossRef] [Scilit]
- Bald, T.; Landsberg, J.; Jansen, P.; Gaffal, E.; Tüting, T. Phorbol ester-induced neutrophilic inflammatory responses selectively promote metastatic spread of melanoma in a TLR4-dependent manner. Oncoimmunology 2016, 5, e1078964. [Google Scholar] [CrossRef] [Scilit]
- Soler-Cardona, A.; Forsthuber, A.; Lipp, K.; Ebersberger, S.; Heinz, M.; Schossleitner, K.; Buchberger, E.; Gröger, M.; Petzelbauer, P.; Hoeller, C.; et al. CXCL5 Facilitates Melanoma Cell–Neutrophil Interaction and Lymph Node Metastasis. J. Investig. Dermatol. 2018, 138, 1627–1635. [Google Scholar] [CrossRef] [Scilit]
- Weide, L.M.; Schedel, F.; Weishaupt, C. Neutrophil Extracellular Traps Correlate with Tumor Necrosis and Size in Human Malignant Melanoma Metastases. Biology 2023, 12, 822. [Google Scholar] [CrossRef] [Scilit]
- Sandri, S.; Hebeda, C.B.; Broering, M.F.; de Paula Silva, M.; Moredo, L.F.; de Barros e Silva, M.J.; Sapata Molina, A.; Lopes Pinto, C.A.; Duprat Neto, J.P.; Reutelingsperger, C.P.; et al. Role of Annexin A1 Secreted by Neutrophils in Melanoma Metastasis. Cells 2023, 12, 425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Samaniego, R.; Gutiérrez-González, A.; Gutiérrez-Seijo, A.; Sánchez-Gregorio, S.; García-Giménez, J.; Mercader, E.; Márquez-Rodas, I.; Avilés, J.A.; Relloso, M.; Sánchez-Mateos, P. CCL20 Expression by Tumor-Associated Macrophages Predicts Progression of Human Primary Cutaneous Melanoma. Cancer Immunol. Res. 2018, 6, 267–275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salmi, S.; Siiskonen, H.; Sironen, R.; Tyynelä-Korhonen, K.; Hirschovits-Gerz, B.; Valkonen, M.; Auvinen, P.; Pasonen-Seppänen, S. The number and localization of CD68+ and CD163+ macrophages in different stages of cutaneous melanoma. Melanoma Res. 2019, 29, 237–247. [Google Scholar]
- Jensen, T.O.; Schmidt, H.; Møller, H.J.; Høyer, M.; Maniecki, M.B.; Sjoegren, P.; Christensen, I.J.; Steiniche, T. Macrophage Markers in Serum and Tumor Have Prognostic Impact in American Joint Committee on Cancer Stage I/II Melanoma. J. Clin. Oncol. 2009, 27, 3330–3337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sica, A.; Mantovani, A. Macrophage plasticity and polarization: In vivo veritas. J. Clin. Invest. 2012, 122, 787–795. [Google Scholar] [CrossRef] [Scilit]
- Smith, M.P.; Sanchez-Laorden, B.; O’Brien, K.; Brunton, H.; Ferguson, J.; Young, H.; Dhomen, N.; Flaherty, K.T.; Frederick, D.T.; Cooper, Z.A.; et al. The Immune Microenvironment Confers Resistance to MAPK Pathway Inhibitors through Macrophage-Derived TNFα. Cancer Discov. 2014, 4, 1214–1229. [Google Scholar] [CrossRef] [Scilit]
- Gutiérrez-Seijo, A.; García-Martínez, E.; Barrio-Alonso, C.; Pareja-Malagón, M.; Acosta-Ocampo, A.; Fernández-Santos, M.E.; Puig-Kröger, A.; Parra-Blanco, V.; Mercader, E.; Márquez-Rodas, I.; et al. CCL20/TNF/VEGFA Cytokine Secretory Phenotype of Tumor-Associated Macrophages Is a Negative Prognostic Factor in Cutaneous Melanoma. Cancers 2021, 13, 3943. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.; Zhou, J.; Liu, Z.; Wu, T.; Li, S.; Zhang, Y.; Yin, X.; Yang, G.; Zhang, G. Tumor cell-induced platelet aggregation accelerates hematogenous metastasis of malignant melanoma by triggering macrophage recruitment. J. Exp. Clin. Cancer Res. 2023, 42, 277. [Google Scholar] [CrossRef] [Scilit]
- Kuklinski, L.F.; Yan, S.; Li, Z.; Fisher, J.L.; Cheng, C.; Noelle, R.J.; Angeles, C.V.; Turk, M.J.; Ernstoff, M.S. VISTA expression on tumor-infiltrating inflammatory cells in primary cutaneous melanoma correlates with poor disease-specific survival. Cancer Immunol. Immunother. 2018, 67, 1113–1121. [Google Scholar] [CrossRef] [Scilit]
- Kakavand, H.; Jackett, L.A.; Menzies, A.M.; Gide, T.N.; Carlino, M.S.; Saw, R.P.M.; Thompson, J.F.; Wilmott, J.S.; Long, G.V.; Scolyer, R.A. Negative immune checkpoint regulation by VISTA: A mechanism of acquired resistance to anti-PD-1 therapy in metastatic melanoma patients. Mod. Pathol. 2017, 30, 1666–1676. [Google Scholar] [CrossRef] [Scilit]
- Van Dam, S.; Krijgsman, D.; Küçükköse, E.; Verdonschot, M.E.L.; Amini, M.; Blokx, W.A.M.; Van Eijs, M.J.M.; Verheijden, R.J.; Kranenburg, O.; Suijkerbuijk, K.P.M.; et al. Anti-PD-1 treatment response is associated with the influx of circulating myeloid and T-cell subsets into the metastatic melanoma tumor microenvironment. Br. J. Cancer 2025, 133, 1250–1264. [Google Scholar] [CrossRef] [Scilit]
- Lee, H.; Ferguson, A.L.; Quek, C.; Shklovskaya, E.; Lim, S.Y.; Ahmed, T.; Smith, J.L.; Phung, S.; Jakrot, V.; Attrill, G.H.; et al. Intratumoral CD16+ macrophages are associated with clinical outcomes of patients with metastatic melanoma treated with combination anti-PD-1 and anti-CTLA-4 therapy. Clin. Cancer Res. 2023, 29, 2513–2524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Su, X.; Huang, R.; Kang, D.; Wang, J.; Zhao, L.; Ren, Y.; Zhang, G.; Zou, Z. Blocking CCR1+ macrophages overcomes resistance to immune checkpoint inhibitors in melanoma. Cell Commun. Signal. 2025, 23, 475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rannikko, J.H.; Hollmén, M. Clinical landscape of macrophage-reprogramming cancer immunotherapies. Br. J. Cancer 2024, 131, 251–260. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.; Li, Z.; Wang, X.; Zhang, L.; Liu, J.; Wu, X.; Yang, H.; Zhao, Y. Modulating tumor-associated macrophages through CSF1R inhibition: A potential therapeutic strategy for HNSCC. J. Transl. Med. 2025, 23, 27. [Google Scholar] [CrossRef] [Scilit]
- Maibach, F.; Sadozai, H.; Seyed Jafari, S.M.; Hunger, R.E.; Schenk, M. Tumor-Infiltrating Lymphocytes and Their Prognostic Value in Cutaneous Melanoma. Front. Immunol. 2020, 11, 2105. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clark, W.H.; Elder, D.E.; Guerry, D.; Braitman, L.E.; Trock, B.J.; Schultz, D.; Synnestvedt, M.; Halpern, A.C. Model Predicting Survival in Stage I Melanoma Based on Tumor Progression. J. Natl. Cancer Inst. 1989, 81, 1893–1904. [Google Scholar] [CrossRef] [Scilit]
- Azimi, F.; Scolyer, R.A.; Rumcheva, P.; Moncrieff, M.; Murali, R.; McCarthy, S.W.; Saw, R.P.; Thompson, J.F. Tumor-Infiltrating Lymphocyte Grade Is an Independent Predictor of Sentinel Lymph Node Status and Survival in Patients with Cutaneous Melanoma. J. Clin. Oncol. 2012, 30, 2678–2683. [Google Scholar] [CrossRef] [Scilit]
- Taylor, R.C.; Patel, A.; Panageas, K.S.; Busam, K.J.; Brady, M.S. Tumor-Infiltrating Lymphocytes Predict Sentinel Lymph Node Positivity in Patients with Cutaneous Melanoma. J. Clin. Oncol. 2007, 25, 869–875. [Google Scholar] [CrossRef] [Scilit]
- Fu, Q.; Chen, N.; Ge, C.; Li, R.; Li, Z.; Zeng, B.; Li, C.; Wang, Y.; Xue, Y.; Song, X.; et al. Prognostic value of tumor-infiltrating lymphocytes in melanoma: A systematic review and meta-analysis. Oncoimmunology 2019, 8, e1593806. [Google Scholar] [CrossRef] [Scilit]
- Gyorki, D.E.; Sanelli, A.; Herschtal, A.; Lazarakis, S.; McArthur, G.A.; Speakman, D.; Spillane, J.; Henderson, M.A. Sentinel Lymph Node Biopsy in T4 Melanoma: An Important Risk-Stratification Tool. Ann. Surg. Oncol. 2016, 23, 579–584. [Google Scholar] [CrossRef] [Scilit]
- Boada, A.; Tejera-Vaquerizo, A.; Ribero, S.; Puig, S.; Moreno-Ramírez, D.; Osella-Abate, S.; Cassoni, P.; Malvehy, J.; Podlipnik, S.; Requena, C.; et al. Age as a prognostic factor in thick and ultrathick melanomas without lymph node metastasis. J. Eur. Acad. Dermatol. Venereol. 2020, 34, 2033–2039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, H.-J.; Cantor, H. CD4 T-cell Subsets and Tumor Immunity: The Helpful and the Not-so-Helpful. Cancer Immunol. Res. 2014, 2, 91–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mattes, J.; Hulett, M.; Xie, W.; Hogan, S.; Rothenberg, M.E.; Foster, P.; Parish, C. Immunotherapy of Cytotoxic T Cell–resistant Tumors by T Helper 2 Cells. J. Exp. Med. 2003, 197, 387–393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tatsumi, T.; Kierstead, L.S.; Ranieri, E.; Gesualdo, L.; Schena, F.P.; Finke, J.H.; Bukowski, R.M.; Mueller-Berghaus, J.; Kirkwood, J.M.; Kwok, W.W.; et al. Disease-associated Bias in T Helper Type 1 (Th1)/Th2 CD4 + T Cell Responses Against MAGE-6 in HLA-DRB10401 + Patients With Renal Cell Carcinoma or Melanoma. J. Exp. Med. 2002, 196, 619–628. [Google Scholar] [CrossRef] [Scilit]
- Martin-Orozco, N.; Muranski, P.; Chung, Y.; Yang, X.O.; Yamazaki, T.; Lu, S.; Hwu, P.; Restifo, N.P.; Overwijk, W.W.; Dong, C. T Helper 17 Cells Promote Cytotoxic T Cell Activation in Tumor Immunity. Immunity 2009, 31, 787–798. [Google Scholar] [CrossRef] [Scilit]
- Muranski, P.; Boni, A.; Antony, P.A.; Cassard, L.; Irvine, K.R.; Kaiser, A.; Paulos, C.M.; Palmer, D.C.; Touloukian, C.E.; Ptak, K.; et al. Tumor-specific Th17-polarized cells eradicate large established melanoma. Blood 2008, 112, 362–373. [Google Scholar] [CrossRef] [Scilit]
- Alvarez Arias, D.A.; Kim, H.-J.; Zhou, P.; Holderried, T.A.W.; Wang, X.; Dranoff, G.; Cantor, H. Disruption of CD8+ Treg Activity Results in Expansion of T Follicular Helper Cells and Enhanced Antitumor Immunity. Cancer Immunol. Res. 2014, 2, 207–216. [Google Scholar] [CrossRef] [Scilit]
- Ward-Hartstonge, K.A.; Kemp, R.A. Regulatory T-cell heterogeneity and the cancer immune response. Clin. Transl. Immunol. 2017, 6, e154. [Google Scholar] [CrossRef] [Scilit]
- Martin-Orozco, N.; Li, Y.; Wang, Y.; Liu, S.; Hwu, P.; Liu, Y.-J.; Dong, C.; Radvanyi, L. Melanoma Cells Express ICOS Ligand to Promote the Activation and Expansion of T-Regulatory Cells. Cancer Res. 2010, 70, 9581–9590. [Google Scholar] [CrossRef] [Scilit]
- Shields, J.D.; Kourtis, I.C.; Tomei, A.A.; Roberts, J.M.; Swartz, M.A. Induction of Lymphoidlike Stroma and Immune Escape by Tumors That Express the Chemokine CCL21. Science 2010, 328, 749–752. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ibrahim, Y.S.; Amin, A.H.; Jawhar, Z.H.; Alghamdi, M.A.; Al-Awsi, G.R.L.; Shbeer, A.M.; AL-Ghamdi, H.S.; Gabr, G.A.; Ramírez-Coronel, A.A.; Almulla, A.F. “To be or not to Be”: Regulatory T cells in melanoma. Int. Immunopharmacol. 2023, 118, 110093. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Gennaro, P.; Gerlini, G.; Caporale, R.; Sestini, S.; Brandani, P.; Urso, C.; Pimpinelli, N.; Borgognoni, L. T regulatory cells mediate immunosuppresion by adenosine in peripheral blood, sentinel lymph node and TILs from melanoma patients. Cancer Lett. 2018, 417, 124–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simpson, T.R.; Li, F.; Montalvo-Ortiz, W.; Sepulveda, M.A.; Bergerhoff, K.; Arce, F.; Roddie, C.; Henry, J.Y.; Yagita, H.; Wolchok, J.D.; et al. Fc-dependent depletion of tumor-infiltrating regulatory T cells co-defines the efficacy of anti–CTLA-4 therapy against melanoma. J. Exp. Med. 2013, 210, 1695–1710. [Google Scholar] [CrossRef] [Scilit]
- Bida, M.; Miya, T.V.; Hull, R.; Dlamini, Z. Tumor-infiltrating lymphocytes in melanoma: From prognostic assessment to therapeutic applications. Front. Immunol. 2024, 15, 1497522. [Google Scholar] [CrossRef] [Scilit]
- Dolton, G.; Rius, C.; Wall, A.; Szomolay, B.; Bianchi, V.; Galloway, S.A.E.; Hasan, M.S.; Morin, T.; Caillaud, M.E.; Thomas, H.L.; et al. Targeting of multiple tumor-associated antigens by individual T cell receptors during successful cancer immunotherapy. Cell 2023, 186, 3333–3349. [Google Scholar] [CrossRef] [Scilit]
- Hoellwerth, M.; Koelblinger, P.; Lang, R.; Harrer, A. Revisiting the Role of the CXCL13/CXCR5-Associated Immune Axis in Melanoma: Potential Implications for Anti-PD-1-Related Biomarker Research. Life 2023, 13, 553. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Phoon, Y.P.; Karlinsey, K.; Tian, Y.F.; Thapaliya, S.; Thongkum, A.; Qu, L.; Matz, A.J.; Cameron, M.; Cameron, C.; et al. A high OXPHOS CD8 T cell subset is predictive of immunotherapy resistance in melanoma patients. J. Exp. Med. 2022, 219, e20202084. [Google Scholar] [CrossRef] [Scilit]
- Fourcade, J.; Sun, Z.; Benallaoua, M.; Guillaume, P.; Luescher, I.F.; Sander, C.; Kirkwood, J.M.; Kuchroo, V.; Zarour, H.M. Upregulation of Tim-3 and PD-1 expression is associated with tumor antigen–specific CD8+ T cell dysfunction in melanoma patients. J. Exp. Med. 2010, 207, 2175–2186. [Google Scholar] [CrossRef] [Scilit]
- Chauvin, J.-M.; Pagliano, O.; Fourcade, J.; Sun, Z.; Wang, H.; Sander, C.; Kirkwood, J.M.; Chen, T.T.; Maurer, M.; Korman, A.J.; et al. TIGIT and PD-1 impair tumor antigen–specific CD8+ T cells in melanoma patients. J. Clin. Invest. 2015, 125, 2046–2058. [Google Scholar] [CrossRef] [Scilit]
- Peng, W.; Chen, J.Q.; Liu, C.; Malu, S.; Creasy, C.; Tetzlaff, M.T.; Xu, C.; McKenzie, J.A.; Zhang, C.; Liang, X.; et al. Loss of PTEN Promotes Resistance to T Cell–Mediated Immunotherapy. Cancer Discov. 2016, 6, 202–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsou, P.; Katayama, H.; Ostrin, E.J.; Hanash, S.M. The Emerging Role of B Cells in Tumor Immunity. Cancer Res. 2016, 76, 5597–5601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Griss, J.; Bauer, W.; Wagner, C.; Simon, M.; Chen, M.; Grabmeier-Pfistershammer, K.; Maurer-Granofszky, M.; Roka, F.; Penz, T.; Bock, C.; et al. B cells sustain inflammation and predict response to immune checkpoint blockade in human melanoma. Nat. Commun. 2019, 10, 4186. [Google Scholar] [CrossRef] [Scilit]
- Cabrita, R.; Lauss, M.; Sanna, A.; Donia, M.; Skaarup Larsen, M.; Mitra, S.; Johansson, I.; Phung, B.; Harbst, K.; Vallon-Christersson, J.; et al. Tertiary lymphoid structures improve immunotherapy and survival in melanoma. Nature 2020, 577, 561–565. [Google Scholar] [CrossRef] [Scilit]
- Amaria, R.N.; Reddy, S.M.; Tawbi, H.A.; Davies, M.A.; Ross, M.I.; Glitza, I.C.; Cormier, J.N.; Lewis, C.; Hwu, W.-J.; Hanna, E.; et al. Neoadjuvant immune checkpoint blockade in high-risk resectable melanoma. Nat. Med. 2018, 24, 1649–1654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Helmink, B.A.; Reddy, S.M.; Gao, J.; Zhang, S.; Basar, R.; Thakur, R.; Yizhak, K.; Sade-Feldman, M.; Blando, J.; Han, G.; et al. B cells and tertiary lymphoid structures promote immunotherapy response. Nature 2020, 577, 549–555. [Google Scholar] [CrossRef] [Scilit]
- Ladányi, A.; Kiss, J.; Mohos, A.; Somlai, B.; Liszkay, G.; Gilde, K.; Fejős, Z.; Gaudi, I.; Dobos, J.; Tímár, J. Prognostic impact of B-cell density in cutaneous melanoma. Cancer Immunol. Immunother. 2011, 60, 1729–1738. [Google Scholar] [CrossRef] [Scilit]
- Garg, K.; Maurer, M.; Griss, J.; Brüggen, M.-C.; Wolf, I.H.; Wagner, C.; Willi, N.; Mertz, K.D.; Wagner, S.N. Tumor-associated B cells in cutaneous primary melanoma and improved clinical outcome. Hum. Pathol. 2016, 54, 157–164. [Google Scholar] [CrossRef] [Scilit]
- Attrill, G.H.; Lee, H.; Tasker, A.T.; Adegoke, N.A.; Ferguson, A.L.; da Silva, I.P.; Saw, R.P.M.; Thompson, J.F.; Palendira, U.; Long, G.V.; et al. Detailed spatial immunophenotyping of primary melanomas reveals immune cell subpopulations associated with patient outcome. Front. Immunol. 2022, 13, 979993. [Google Scholar] [CrossRef] [Scilit]
- Iglesia, M.D.; Parker, J.S.; Hoadley, K.A.; Serody, J.S.; Perou, C.M.; Vincent, B.G. Genomic Analysis of Immune Cell Infiltrates Across 11 Tumor Types. J. Natl. Cancer Inst. 2016, 108, djw144. [Google Scholar] [CrossRef] [Scilit]
- DiLillo, D.J.; Yanaba, K.; Tedder, T.F. B Cells Are Required for Optimal CD4+ and CD8+ T Cell Tumor Immunity: Therapeutic B Cell Depletion Enhances B16 Melanoma Growth in Mice. J. Immunol. 2010, 184, 4006–4016. [Google Scholar] [CrossRef] [Scilit]
- Somasundaram, R.; Zhang, G.; Fukunaga-Kalabis, M.; Perego, M.; Krepler, C.; Xu, X.; Wagner, C.; Hristova, D.; Zhang, J.; Tian, T.; et al. Tumor-associated B-cells induce tumor heterogeneity and therapy resistance. Nat. Commun. 2017, 8, 607. [Google Scholar]
- Bosisio, F.M.; Wilmott, J.S.; Volders, N.; Mercier, M.; Wouters, J.; Stas, M.; Blokx, W.A.; Massi, D.; Thompson, J.F.; Scolyer, R.A.; et al. Plasma cells in primary melanoma. Prognostic significance and possible role of IgA. Mod. Pathol. 2016, 29, 347–358. [Google Scholar] [CrossRef] [Scilit]
- Verma, R.; Kumar, L. Plasma Cells in the Melanoma Tumor Microenvironment—Mechanistic Roles for IgA. Front. Immunol. 2020, 11, 979. [Google Scholar] [CrossRef] [Scilit]
- Lee, H.; Da Silva, I.P.; Palendira, U.; Scolyer, R.A.; Long, G.V.; Wilmott, J.S. Targeting NK Cells to Enhance Melanoma Response to Immunotherapies. Cancers 2021, 13, 1363. [Google Scholar] [CrossRef] [Scilit]
- Taggart, D.; Andreou, T.; Scott, K.J.; Williams, J.; Rippaus, N.; Brownlie, R.J.; Ilett, E.J.; Salmond, R.J.; Melcher, A.; Lorger, M. Anti–PD-1/anti–CTLA-4 efficacy in melanoma brain metastases depends on extracranial disease and augmentation of CD8 + T cell trafficking. Proc. Natl. Acad. Sci. USA 2018, 115, E1540–E1549. [Google Scholar] [CrossRef] [Scilit]
- Simiczyjew, A.; Dratkiewicz, E.; Mazurkiewicz, J.; Ziętek, M.; Matkowski, R.; Nowak, D. The Influence of Tumor Microenvironment on Immune Escape of Melanoma. Int. J. Mol. Sci. 2020, 21, 8359. [Google Scholar] [CrossRef] [Scilit]
- Marzagalli, M.; Ebelt, N.D.; Manuel, E.R. Unraveling the crosstalk between melanoma and immune cells in the tumor microenvironment. Semin. Cancer Biol. 2019, 59, 236–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, L.; Chen, Z.; Liu, G.; Pan, Y. Functional crosstalk and regulation of natural killer cells in tumor microenvironment: Significance and potential therapeutic strategies. Genes Dis. 2023, 10, 990–1004. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cristiani, C.M.; Garofalo, C.; Passacatini, L.C.; Carbone, E. New avenues for melanoma immunotherapy: Natural Killer cells? Scand. J. Immunol. 2020, 91, e12861. [Google Scholar] [PubMed]
- Garofalo, C.; De Marco, C.; Cristiani, C.M. NK Cells in the Tumor Microenvironment as New Potential Players Mediating Chemotherapy Effects in Metastatic Melanoma. Front. Oncol. 2021, 11, 754541. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mattiola, I. Immune Circuits to Shape Natural Killer Cells in Cancer. Cancers 2021, 13, 3225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mun, J.-Y.; Leem, S.-H.; Lee, J.H.; Kim, H.S. Dual Relationship Between Stromal Cells and Immune Cells in the Tumor Microenvironment. Front. Immunol. 2022, 13, 864739. [Google Scholar] [CrossRef] [Scilit]
- Tucci, M.; Passarelli, A.; Mannavola, F.; Felici, C.; Stucci, L.S.; Cives, M.; Silvestris, F. Immune System Evasion as Hallmark of Melanoma Progression: The Role of Dendritic Cells. Front. Oncol. 2019, 9, 1148. [Google Scholar] [CrossRef] [Scilit]
- Tang, M.; Diao, J.; Gu, H.; Khatri, I.; Zhao, J.; Cattral, M.S. Toll-like Receptor 2 Activation Promotes Tumor Dendritic Cell Dysfunction by Regulating IL-6 and IL-10 Receptor Signaling. Cell Rep. 2015, 13, 2851–2864. [Google Scholar] [CrossRef] [Scilit]
- Ahern, E.; Smyth, M.J.; Dougall, W.C.; Teng, M.W.L. Roles of the RANKL–RANK axis in antitumour immunity―implications for therapy. Nat. Rev. Clin. Oncol. 2018, 15, 676–693. [Google Scholar] [CrossRef] [Scilit]
- Gerlini, G.; Susini, P.; Sestini, S.; Brandani, P.; Giannotti, V.; Borgognoni, L. Langerhans Cells in Sentinel Lymph Nodes from Melanoma Patients. Cancers 2024, 16, 1890. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Monti, M.; Ferrari, G.; Gazzurelli, L.; Bugatti, M.; Facchetti, F.; Vermi, W. Plasmacytoid dendritic cells at the forefront of anti-cancer immunity: Rewiring strategies for tumor microenvironment remodeling. J. Exp. Clin. Cancer Res. 2024, 43, 196. [Google Scholar] [CrossRef] [Scilit]
- Gabrilovich, D.I.; Nagaraj, S. Myeloid-derived suppressor cells as regulators of the immune system. Nat. Rev. Immunol. 2009, 9, 162–174. [Google Scholar] [CrossRef] [Scilit]
- Cassetta, L.; Bruderek, K.; Skrzeczynska-Moncznik, J.; Osiecka, O.; Hu, X.; Rundgren, I.M.; Lin, A.; Santegoets, K.; Horzum, U.; Godinho-Santos, A.; et al. Differential expansion of circulating human MDSC subsets in patients with cancer, infection and inflammation. J. Immunother. Cancer 2020, 8, e001223. [Google Scholar] [CrossRef] [Scilit]
- Ozbay Kurt, F.G.; Lasser, S.; Arkhypov, I.; Utikal, J.; Umansky, V. Enhancing immunotherapy response in melanoma: Myeloid-derived suppressor cells as a therapeutic target. J. Clin. Investig. 2023, 133, e170762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Douglass, S.M.; Fane, M.E.; Sanseviero, E.; Ecker, B.L.; Kugel, C.H.; Behera, R.; Kumar, V.; Tcyganov, E.N.; Yin, X.; Liu, Q.; et al. Myeloid-Derived Suppressor Cells Are a Major Source of Wnt5A in the Melanoma Microenvironment and Depend on Wnt5A for Full Suppressive Activity. Cancer Res. 2021, 81, 658–670. [Google Scholar] [CrossRef] [Scilit]
- Huber, V.; Vallacchi, V.; Fleming, V.; Hu, X.; Cova, A.; Dugo, M.; Shahaj, E.; Sulsenti, R.; Vergani, E.; Filipazzi, P.; et al. Tumor-derived microRNAs induce myeloid suppressor cells and predict immunotherapy resistance in melanoma. J. Clin. Investig. 2018, 128, 5505–5516. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lasser, S.; Ozbay Kurt, F.G.; Fritz, L.; Gutzeit, N.; De La Torre, C.; Altevogt, P.; Utikal, J.; Umansky, V. Generation of Myeloid-Derived Suppressor Cells Mediated by MicroRNA-125a-5p in Melanoma. Int. J. Mol. Sci. 2024, 25, 6693. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marguier, A.; Laheurte, C.; Lecoester, B.; Malfroy, M.; Boullerot, L.; Renaudin, A.; Seffar, E.; Kumar, A.; Nardin, C.; Aubin, F.; et al. TIE-2 Signaling Activation by Angiopoietin 2 On Myeloid-Derived Suppressor Cells Promotes Melanoma-Specific T-cell Inhibition. Front. Immunol. 2022, 13, 932298. [Google Scholar] [CrossRef] [Scilit]
- Zimarino, C.; Moody, W.; Davidson, S.E.; Munir, H.; Shields, J.D. Disruption of CD47-SIRPα signaling restores inflammatory function in tumor-associated myeloid-derived suppressor cells. iScience 2024, 27, 109546. [Google Scholar] [CrossRef] [Scilit]
- Blattner, C.; Fleming, V.; Weber, R.; Himmelhan, B.; Altevogt, P.; Gebhardt, C.; Schulze, T.J.; Razon, H.; Hawila, E.; Wildbaum, G.; et al. CCR5+ Myeloid-Derived Suppressor Cells Are Enriched and Activated in Melanoma Lesions. Cancer Res. 2018, 78, 157–167. [Google Scholar] [CrossRef] [Scilit]
- Groth, C.; Arpinati, L.; Shaul, M.E.; Winkler, N.; Diester, K.; Gengenbacher, N.; Weber, R.; Arkhypov, I.; Lasser, S.; Petrova, V.; et al. Blocking Migration of Polymorphonuclear Myeloid-Derived Suppressor Cells Inhibits Mouse Melanoma Progression. Cancers 2021, 13, 726. [Google Scholar] [CrossRef] [Scilit]
- Gebhardt, C.; Sevko, A.; Jiang, H.; Lichtenberger, R.; Reith, M.; Tarnanidis, K.; Holland-Letz, T.; Umansky, L.; Beckhove, P.; Sucker, A.; et al. Myeloid Cells and Related Chronic Inflammatory Factors as Novel Predictive Markers in Melanoma Treatment with Ipilimumab. Clin. Cancer Res. 2015, 21, 5453–5459. [Google Scholar] [CrossRef] [Scilit]
- Steinberg, S.M.; Shabaneh, T.B.; Zhang, P.; Martyanov, V.; Li, Z.; Malik, B.T.; Wood, T.A.; Boni, A.; Molodtsov, A.; Angeles, C.V.; et al. Myeloid Cells That Impair Immunotherapy Are Restored in Melanomas with Acquired Resistance to BRAF Inhibitors. Cancer Res. 2017, 77, 1599–1610. [Google Scholar] [CrossRef] [Scilit]
- Siiskonen, H.; Poukka, M.; Bykachev, A.; Tyynelä-Korhonen, K.; Sironen, R.; Pasonen-Seppänen, S.; Harvima, I.T. Low numbers of tryptase+ and chymase+ mast cells associated with reduced survival and advanced tumor stage in melanoma. Melanoma Res. 2015, 25, 479–485. [Google Scholar] [CrossRef] [Scilit]
- Rajabi, P.; Bagheri, A.; Hani, M. Intratumoral and Peritumoral Mast Cells in Malignant Melanoma: An Immunohistochemical Study. Adv. Biomed. Res. 2017, 6, 46. [Google Scholar] [CrossRef] [Scilit]
- Tóth-Jakatics, R.; Jimi, S.; Takebayashi, S.; Kawamoto, N. Cutaneous malignant melanoma: Correlation between neovascularization and peritumor accumulation of mast cells overexpressing vascular endothelial growth factor. Hum. Pathol. 2000, 31, 955–960. [Google Scholar] [CrossRef] [Scilit]
- Ribatti, D.; Ennas, M.G.; Vacca, A.; Ferreli, F.; Nico, B.; Orru, S.; Sirigu, P. Tumor vascularity and tryptase-positive mast cells correlate with a poor prognosis in melanoma. Eur. J. Clin. Investig. 2003, 33, 420–425. [Google Scholar]
- Ch’ng, S.; Wallis, R.A.; Yuan, L.; Davis, P.F.; Tan, S.T. Mast cells and cutaneous malignancies. Mod. Pathol. 2006, 19, 149–159. [Google Scholar] [CrossRef] [Scilit]
- Bahri, R.; Kiss, O.; Prise, I.; Garcia-Rodriguez, K.M.; Atmoko, H.; Martínez-Gómez, J.M.; Levesque, M.P.; Dummer, R.; Smith, M.P.; Wellbrock, C.; et al. Human Melanoma-Associated Mast Cells Display a Distinct Transcriptional Signature Characterized by an Upregulation of the Complement Component 3 That Correlates With Poor Prognosis. Front. Immunol. 2022, 13, 861545. [Google Scholar] [CrossRef] [Scilit]
- Rabelo Melo, F.; Nyman, L.; Menander, I.Ö.; Grujic, M.; Pejler, G. Melanoma cells suppress mast cell function via a melanin-dependent mechanism. FEBS J. 2025, 292, 6075–6099. [Google Scholar] [CrossRef] [Scilit]
- Marrapodi, R.; Bellei, B. The Keratinocyte in the Picture Cutaneous Melanoma Microenvironment. Cancers 2024, 16, 913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dainese-Marque, O.; Garcia, V.; Andrieu-Abadie, N.; Riond, J. Contribution of Keratinocytes in Skin Cancer Initiation and Progression. Int. J. Mol. Sci. 2024, 25, 8813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Green, K.J.; Pokorny, J.; Jarrell, B. Dangerous liaisons: Loss of keratinocyte control over melanocytes in melanomagenesis. BioEssays 2024, 46, e202400135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, M.-Y.; Meier, F.E.; Nesbit, M.; Hsu, J.-Y.; Van Belle, P.; Elder, D.E.; Herlyn, M. E-Cadherin Expression in Melanoma Cells Restores Keratinocyte-Mediated Growth Control and Down-Regulates Expression of Invasion-Related Adhesion Receptors. Am. J. Pathol. 2000, 156, 1515–1525. [Google Scholar] [CrossRef] [Scilit]
- Kodet, O.; Lacina, L.; Krejčí, E.; Dvořánková, B.; Grim, M.; Štork, J.; Kodetová, D.; Vlček, Č.; Šáchová, J.; Kolář, M.; et al. Melanoma cells influence the differentiation pattern of human epidermal keratinocytes. Mol. Cancer 2015, 14, 1. [Google Scholar] [CrossRef] [Scilit]
- Burks, H.E.; Pokorny, J.L.; Koetsier, J.L.; Roth-Carter, Q.R.; Arnette, C.R.; Gerami, P.; Seykora, J.T.; Johnson, J.L.; Ren, Z.; Green, K.J. Melanoma cells repress Desmoglein 1 in keratinocytes to promote tumor cell migration. J. Cell Biol. 2023, 222, e202212031. [Google Scholar] [CrossRef] [Scilit]
- Arnette, C.R.; Roth-Carter, Q.R.; Koetsier, J.L.; Broussard, J.A.; Burks, H.E.; Cheng, K.; Amadi, C.; Gerami, P.; Johnson, J.L.; Green, K.J. Keratinocyte cadherin desmoglein 1 controls melanocyte behavior through paracrine signaling. Pigment Cell Melanoma Res. 2020, 33, 305–317. [Google Scholar] [CrossRef] [Scilit]
- Smatlik, N.; Drexler, S.K.; Burian, M.; Röcken, M.; Yazdi, A.S. ASC Speck Formation after Inflammasome Activation in Primary Human Keratinocytes. Oxid. Med. Cell. Longev. 2021, 2021, 7914829. [Google Scholar] [CrossRef] [Scilit]
- Yao, W.; German, B.; Chraa, D.; Braud, A.; Hugel, C.; Meyer, P.; Davidson, G.; Laurette, P.; Mengus, G.; Flatter, E.; et al. Keratinocyte-derived cytokine TSLP promotes growth and metastasis of melanoma by regulating the tumor-associated immune microenvironment. JCI Insight 2022, 7, e161438. [Google Scholar] [CrossRef] [Scilit]
- Chung, H.; Suh, E.-K.; Han, I.-O.; Oh, E.-S. Keratinocyte-derived Laminin-332 Promotes Adhesion and Migration in Melanocytes and Melanoma. J. Biol. Chem. 2011, 286, 13438–13447. [Google Scholar] [CrossRef] [Scilit]
- Marrapodi, R.; Kovacs, D.; Migliano, E.; Caputo, S.; Papaccio, F.; Pallara, T.; Cota, C.; Bellei, B. Melanoma–Keratinocyte Crosstalk Participates in Melanoma Progression with Mechanisms Partially Overlapping with Those of Cancer-Associated Fibroblasts. Int. J. Mol. Sci. 2025, 26, 7901. [Google Scholar] [CrossRef] [Scilit]
- Eberlein-König, B.; Jäger, C.; Przybilla, B. Ultraviolet B radiation-induced production of interleukin 1alpha and interleukin 6 in a human squamous carcinoma cell line is wavelength-dependent and can be inhibited by pharmacological agents. Br. J. Dermatol. 1998, 139, 415–421. [Google Scholar] [CrossRef] [Scilit]
- Cataisson, C.; Salcedo, R.; Hakim, S.; He, W.W.; Cheng, K.; Yardley, N.; Gherardini, L.; Quigley, D.; Balmain, A.; Trinchieri, G.; et al. IL-1R–MyD88 signaling in keratinocyte transformation and carcinogenesis. J. Exp. Med. 2012, 209, 1689–1702. [Google Scholar] [CrossRef] [Scilit]
- Young, H.L.; Rowling, E.J.; Bugatti, M.; Giurisato, E.; Luheshi, N.; Arozarena, I.; Acosta, J.C.; Kamarashev, J.; Frederick, D.T.; Cooper, Z.A.; et al. An adaptive signaling network in melanoma inflammatory niches confers tolerance to MAPK signaling inhibition. J. Exp. Med. 2017, 214, 1691–1710. [Google Scholar] [CrossRef] [Scilit]
- Winkler, J.; Abisoye-Ogunniyan, A.; Metcalf, K.J.; Werb, Z. Concepts of extracellular matrix remodelling in tumour progression and metastasis. Nat. Commun. 2020, 11, 5120. [Google Scholar] [CrossRef] [Scilit]
- Romano, V.; Belviso, I.; Venuta, A.; Ruocco, M.R.; Masone, S.; Aliotta, F.; Fiume, G.; Montagnani, S.; Avagliano, A.; Arcucci, A. Influence of Tumor Microenvironment and Fibroblast Population Plasticity on Melanoma Growth, Therapy Resistance and Immunoescape. Int. J. Mol. Sci. 2021, 22, 5283. [Google Scholar] [CrossRef] [Scilit]
- Mayasin, Y.P.; Osinnikova, M.N.; Kharisova, C.B.; Kitaeva, K.V.; Filin, I.Y.; Gorodilova, A.V.; Kutovoi, G.I.; Solovyeva, V.V.; Golubev, A.I.; Rizvanov, A.A. Extracellular Matrix as a Target in Melanoma Therapy: From Hypothesis to Clinical Trials. Cells 2024, 13, 1917. [Google Scholar] [CrossRef] [Scilit]
- Quatresooz, P.; Piérard, G.E. Immunohistochemical investigation of alpha1 (IV) and alpha5 (IV) collagen chains in a broad spectrum of melanocytic tumours. Melanoma Res. 2005, 15, 161–168. [Google Scholar] [CrossRef] [Scilit]
- Frey, K.; Fiechter, M.; Schwager, K.; Belloni, B.; Barysch, M.J.; Neri, D.; Dummer, R. Different patterns of fibronectin and tenascin-C splice variants expression in primary and metastatic melanoma lesions. Exp. Dermatol. 2011, 20, 685–688. [Google Scholar] [CrossRef] [Scilit]
- Smolle, J.; Fiebiger, M.; Hofmann-Wellenhof, R.; Kerl, H. Quantitative morphology of collagen fibers in cutaneous malignant melanoma and melanocytic nevus. Am. J. Dermatopathol. 1996, 18, 358–363. [Google Scholar] [CrossRef] [Scilit]
- Wight, T.N. Versican: A versatile extracellular matrix proteoglycan in cell biology. Curr. Opin. Cell Biol. 2002, 14, 617–623. [Google Scholar] [CrossRef] [Scilit]
- Smart, J.A.; Oleksak, J.E.; Hartsough, E.J. Cell Adhesion Molecules in Plasticity and Metastasis. Mol. Cancer Res. 2021, 19, 25–37. [Google Scholar] [CrossRef] [Scilit]
- Lecacheur, M.; Berestjuk, I.; Carminati, A.; Bouvet, O.; Diazzi, S.; Biber, P.; Rovera, C.; Irondelle, M.; Larbret, F.; Prod’homme, V.; et al. Extracellular matrix stiffness determines the phenotypic behavior of dedifferentiated melanoma cells through a DDR1/2-dependent YAP mechanotransduction pathway. bioRxiv 2024, preprint. [Google Scholar] [CrossRef] [Scilit]
- Diazzi, S.; Baeri, A.; Fassy, J.; Lecacheur, M.; Marin-Bejar, O.; Girard, C.A.; Lefevre, L.; Lacoux, C.; Irondelle, M.; Mounier, C.; et al. Blockade of the pro-fibrotic reaction mediated by the miR-143/-145 cluster enhances the responses to targeted therapy in melanoma. EMBO Mol. Med. 2022, 14, e15295. [Google Scholar] [CrossRef] [Scilit]
- Hirata, E.; Girotti, M.R.; Viros, A.; Hooper, S.; Spencer-Dene, B.; Matsuda, M.; Larkin, J.; Marais, R.; Sahai, E. Intravital imaging reveals how BRAF inhibition generates drug-tolerant microenvironments with high integrin β1/FAK signaling. Cancer Cell 2015, 27, 574–588. [Google Scholar]
- Darvishi, B.; Eisavand, M.R.; Majidzadeh-A, K.; Farahmand, L. Matrix stiffening and acquired resistance to chemotherapy: Concepts and clinical significance. Br. J. Cancer 2022, 126, 1253–1263. [Google Scholar] [CrossRef] [Scilit]
- Berestjuk, I.; Lecacheur, M.; Carminati, A.; Diazzi, S.; Rovera, C.; Prod’homme, V.; Ohanna, M.; Popovic, A.; Mallavialle, A.; Larbret, F.; et al. Targeting Discoidin Domain Receptors DDR1 and DDR2 overcomes matrix-mediated tumor cell adaptation and tolerance to BRAF-targeted therapy in melanoma. EMBO Mol. Med. 2022, 14, e11814. [Google Scholar] [CrossRef] [Scilit]
- Reger De Moura, C.; Louveau, B.; Jouenne, F.; Vilquin, P.; Battistella, M.; Bellahsen-Harrar, Y.; Sadoux, A.; Menashi, S.; Dumaz, N.; Lebbé, C.; et al. Inactivation of kindlin-3 increases human melanoma aggressiveness through the collagen-activated tyrosine kinase receptor DDR1. Oncogene 2024, 43, 1620–1630. [Google Scholar] [CrossRef] [Scilit]
- Poudel, B.; Lee, Y.M.; Kim, D.K. DDR2 inhibition reduces migration and invasion of murine metastatic melanoma cells by suppressing MMP2/9 expression through ERK/NF-κB pathway. Acta Biochim. Biophys. Sin. 2015, 47, 292–298. [Google Scholar] [CrossRef] [Scilit]
- Krähling, H.; Mally, S.; Eble, J.A.; Noël, J.; Schwab, A.; Stock, C. The glycocalyx maintains a cell surface pH nanoenvironment crucial for integrin-mediated migration of human melanoma cells. Pflug. Arch. 2009, 458, 1069–1083. [Google Scholar] [CrossRef] [Scilit]
- Dratkiewicz, E.; Simiczyjew, A.; Mazurkiewicz, J.; Ziętek, M.; Matkowski, R.; Nowak, D. Hypoxia and Extracellular Acidification as Drivers of Melanoma Progression and Drug Resistance. Cells 2021, 10, 862. [Google Scholar] [CrossRef] [Scilit]
- Paradise, R.K.; Lauffenburger, D.A.; Van Vliet, K.J. Acidic extracellular pH promotes activation of integrin α(v)β(3). PLoS ONE 2011, 6, e15746. [Google Scholar] [CrossRef] [Scilit]
- Lazar, A.M.; Costea, D.O.; Popp, C.G.; Mastalier, B. Skin Malignant Melanoma and Matrix Metalloproteinases: Promising Links to Efficient Therapies. Int. J. Mol. Sci. 2024, 25, 7804. [Google Scholar] [CrossRef] [Scilit]
- Hadler-Olsen, E.; Fadnes, B.; Sylte, I.; Uhlin-Hansen, L.; Winberg, J.O. Regulation of matrix metalloproteinase activity in health and disease. FEBS J. 2011, 278, 28–45. [Google Scholar] [CrossRef] [Scilit]
- Taube, J.M.; Klein, A.; Brahmer, J.R.; Xu, H.; Pan, X.; Kim, J.H.; Chen, L.; Pardoll, D.M.; Topalian, S.L.; Anders, R.A. Association of PD-1, PD-1 ligands, and other features of the tumor immune microenvironment with response to anti-PD-1 therapy. Clin. Cancer Res. 2014, 20, 5064–5074. [Google Scholar]
- Fujimura, T.; Kambayashi, Y.; Fujisawa, Y.; Hidaka, T.; Aiba, S. Tumor-Associated Macrophages: Therapeutic Targets for Skin Cancer. Front. Oncol. 2018, 8, 3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kale, S.; Raja, R.; Thorat, D.; Soundararajan, G.; Patil, T.V.; Kundu, G.C. Osteopontin signaling upregulates cyclooxygenase-2 expression in tumor-associated macrophages leading to enhanced angiogenesis and melanoma growth via α9β1 integrin. Oncogene 2014, 33, 2295–2306. [Google Scholar] [PubMed]
- Napoli, S.; Scuderi, C.; Gattuso, G.; Bella, V.D.; Candido, S.; Basile, M.S.; Libra, M.; Falzone, L. Functional Roles of Matrix Metalloproteinases and Their Inhibitors in Melanoma. Cells 2020, 9, 1151. [Google Scholar] [CrossRef] [Scilit]
- de Almeida, L.G.N.; Thode, H.; Eslambolchi, Y.; Chopra, S.; Young, D.; Gill, S.; Devel, L.; Dufour, A. Matrix Metalloproteinases: From Molecular Mechanisms to Physiology, Pathophysiology, and Pharmacology. Pharmacological reviews 2022, 74, 712–768. [Google Scholar] [CrossRef] [Scilit]
- Winer, A.; Adams, S.; Mignatti, P. Matrix Metalloproteinase Inhibitors in Cancer Therapy: Turning Past Failures into Future Successes. Mol. Cancer Ther. 2018, 17, 1147–1155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Montoyo-Pujol, Y.G.; Wang, X.; Bermúdez-Sánchez, S.; Martin, A.; Almazan, F.; López-Nevot, M.Á. Measurement of 45 cytokine, chemokine and growth factors in established cell culture supernatants and autologous serum from advanced melanoma patients. Carcinogenesis 2021, 42, 714–723. [Google Scholar] [CrossRef] [Scilit]
- Elias, E.G.; Hasskamp, J.H.; Sharma, B.K. Cytokines and Growth Factors Expressed by Human Cutaneous Melanoma. Cancers 2010, 2, 794–808. [Google Scholar] [CrossRef] [Scilit]
- Jiang, H.; Gebhardt, C.; Umansky, L.; Beckhove, P.; Schulze, T.J.; Utikal, J.; Umansky, V. Elevated chronic inflammatory factors and myeloid-derived suppressor cells indicate poor prognosis in advanced melanoma patients. Int. J. Cancer 2015, 136, 2352–2360. [Google Scholar] [CrossRef] [Scilit]
- Ostrand-Rosenberg, S.; Sinha, P. Myeloid-derived suppressor cells: Linking inflammation and cancer. J. Immunol. 2009, 182, 4499–4506. [Google Scholar] [CrossRef] [Scilit]
- Villanueva, J.; Herlyn, M. Melanoma and the tumor microenvironment. Curr. Oncol. Rep. 2008, 10, 439–446. [Google Scholar] [CrossRef] [Scilit]
- Lázár-Molnár, E.; Hegyesi, H.; Tóth, S.; Falus, A. Autocrine and paracrine regulation by cytokines and growth factors in melanoma. Cytokine 2000, 12, 547–554. [Google Scholar] [CrossRef] [Scilit]
- Somasundaram, R.; Herlyn, M.; Wagner, S.N. The role of tumor microenvironment in melanoma therapy resistance. Melanoma Manag. 2016, 3, 23–32. [Google Scholar] [CrossRef] [Scilit]
- Gargalionis, A.N.; Papavassiliou, K.A.; Papavassiliou, A.G. Mechanobiology of solid tumors. Biochim. Biophys. Acta Mol. Basis Dis. 2022, 1868, 166555. [Google Scholar] [CrossRef] [Scilit]
- Tan, Q.; Saggar, J.K.; Yu, M.; Wang, M.; Tannock, I.F. Mechanisms of Drug Resistance Related to the Microenvironment of Solid Tumors and Possible Strategies to Inhibit Them. Cancer J. 2015, 21, 254–262. [Google Scholar] [CrossRef] [Scilit]
- Kharouf, N.; Flanagan, T.W.; Hassan, S.Y.; Shalaby, H.; Khabaz, M.; Hassan, S.L.; Megahed, M.; Haikel, Y.; Santourlidis, S.; Hassan, M. Tumor Microenvironment as a Therapeutic Target in Melanoma Treatment. Cancers 2023, 15, 3147. [Google Scholar] [CrossRef] [Scilit]
- Singh, S.; Xiao, Z.; Bavisi, K.; Roszik, J.; Melendez, B.D.; Wang, Z.; Cantwell, M.J.; Davis, R.E.; Lizee, G.; Hwu, P.; et al. IL-1α Mediates Innate and Acquired Resistance to Immunotherapy in Melanoma. J. Immunol. 2021, 206, 1966–1975. [Google Scholar] [CrossRef] [Scilit]
- Vuletić, A.M.; Konjević, G.M.; Larsen, A.K.; Babović, N.L.; Jurišić, V.B.; Krivokuća, A.; Mirjačić Martinović, K.M. Interleukin-4-induced natural killer cell antitumor activity in metastatic melanoma patients. Eur. Cytokine Netw. 2020, 31, 104–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanaka, T.; Narazaki, M.; Kishimoto, T. IL-6 in inflammation, immunity, and disease. Cold Spring Harb. Perspect. Biol. 2014, 6, a016295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, K.P.; Singh, A.; Wolkenhauer, O.; Gupta, S.K. Regulatory Role of IL6 in Immune-Related Adverse Events during Checkpoint Inhibitor Treatment in Melanoma. Int. J. Mol. Sci. 2024, 25, 10600. [Google Scholar] [CrossRef] [Scilit]
- Filimon, A.; Preda, I.A.; Boloca, A.F.; Negroiu, G. Interleukin-8 in Melanoma Pathogenesis, Prognosis and Therapy—An Integrated View into Other Neoplasms and Chemokine Networks. Cells 2022, 11, 120. [Google Scholar] [CrossRef] [Scilit]
- Itakura, E.; Huang, R.R.; Wen, D.R.; Paul, E.; Wünsch, P.H.; Cochran, A.J. IL-10 expression by primary tumor cells correlates with melanoma progression from radial to vertical growth phase and development of metastatic competence. Mod. Pathol. 2011, 24, 801–809. [Google Scholar] [CrossRef] [Scilit]
- Okamoto, H.; Yoshimatsu, Y.; Tomizawa, T.; Kunita, A.; Takayama, R.; Morikawa, T.; Komura, D.; Takahashi, K.; Oshima, T.; Sato, M.; et al. Interleukin-13 receptor α2 is a novel marker and potential therapeutic target for human melanoma. Sci. Rep. 2019, 9, 1281. [Google Scholar] [CrossRef] [Scilit]
- Awad, R.M.; De Vlaeminck, Y.; Meeus, F.; Ertveldt, T.; Zeven, K.; Ceuppens, H.; Goyvaerts, C.; Verdonck, M.; Salguero, G.; Raes, G.; et al. In vitro modelling of local gene therapy with IL-15/IL-15Rα and a PD-L1 antagonist in melanoma reveals an interplay between NK cells and CD4+ T cells. Sci. Rep. 2023, 13, 18995. [Google Scholar] [CrossRef] [Scilit]
- Váraljai, R.; Zimmer, L.; Al-Matary, Y.; Kaptein, P.; Albrecht, L.J.; Shannan, B.; Brase, J.C.; Gusenleitner, D.; Amaral, T.; Wyss, N.; et al. Interleukin 17 signaling supports clinical benefit of dual CTLA-4 and PD-1 checkpoint inhibition in melanoma. Nat. Cancer 2023, 4, 1292–1308. [Google Scholar] [CrossRef] [Scilit]
- Gil, M.; Kim, K.E. Interleukin-18 Is a Prognostic Biomarker Correlated with CD8+ T Cell and Natural Killer Cell Infiltration in Skin Cutaneous Melanoma. J. Clin. Med. 2019, 8, 1993. [Google Scholar] [CrossRef] [Scilit]
- Levati, L.; Tabolacci, C.; Facchiano, A.; Facchiano, F.; Alvino, E.; Antonini Cappellini, G.C.; Scala, E.; Bonmassar, L.; Caporali, S.; Lacal, P.M.; et al. Circulating interleukin-8 and osteopontin are promising biomarkers of clinical outcomes in advanced melanoma patients treated with targeted therapy. J. Exp. Clin. Cancer Res. 2024, 43, 226. [Google Scholar] [CrossRef] [Scilit]
- Rossi, S.; Cordella, M.; Tabolacci, C.; Nassa, G.; D’Arcangelo, D.; Senatore, C.; Pagnotto, P.; Magliozzi, R.; Salvati, A.; Weisz, A.; et al. TNF-alpha and metalloproteases as key players in melanoma cells aggressiveness. J. Exp. Clin. Cancer Res. 2018, 37, 326. [Google Scholar] [CrossRef] [Scilit]
- Kirkwood, J.M.; Strawderman, M.H.; Ernstoff, M.S.; Smith, T.J.; Borden, E.C.; Blum, R.H. Interferon Alfa-2b Adjuvant Therapy of High-Risk Resected Cutaneous Melanoma: The Eastern Cooperative Oncology Group Trial EST 1684. J. Clin. Oncol. 2023, 41, 425–435. [Google Scholar] [CrossRef] [Scilit]
- Dillman, R.O. An update on GM-CSF and its potential role in melanoma management. Melanoma Manag. 2020, 7, MMT49. [Google Scholar] [CrossRef] [Scilit]
- Loos, B.; Salas-Bastos, A.; Nordin, A.; Debbache, J.; Stierli, S.; Cheng, P.F.; Rufli, S.; Wyss, C.; Levesque, M.P.; Dummer, R.; et al. TGFβ signaling sensitizes MEKi-resistant human melanoma to targeted therapy-induced apoptosis. Cell Death Dis. 2024, 15, 925. [Google Scholar] [CrossRef] [Scilit]
- Malekan, M.; Haass, N.K.; Rokni, G.R.; Gholizadeh, N.; Ebrahimzadeh, M.A.; Kazeminejad, A. VEGF/VEGFR axis and its signaling in melanoma: Current knowledge toward therapeutic targeting agents and future perspectives. Life Sci. 2024, 345, 122563. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cazzato, G.; Ingravallo, G.; Ribatti, D. Angiogenesis Still Plays a Crucial Role in Human Melanoma Progression. Cancers 2024, 16, 1794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Castillo-Ferrer, C.; Marguet, T.; Vanwonterghem, L.; Erbek, S.; Chuffart, F.; Mouret, S.; Messai, S.T.; Gauchez, A.S.; Coll, J.L.; Charles, J.; et al. Serum IGF1 Is a Prognostic Marker for Resistance to Targeted Therapies and a Predictive Marker for Anti-IGF1 Receptor Therapy in Melanoma. J. Investig. Dermatol. 2024, 144, 422–426.e8. [Google Scholar] [CrossRef] [Scilit]
- Pagani, E.; Ruffini, F.; Antonini Cappellini, G.C.; Scoppola, A.; Fortes, C.; Marchetti, P.; Graziani, G.; D’Atri, S.; Lacal, P.M. Placenta growth factor and neuropilin-1 collaborate in promoting melanoma aggressiveness. Int. J. Oncol. 2016, 48, 1581–1589. [Google Scholar] [CrossRef] [Scilit]
- Pastwińska, J.; Karaś, K.; Karwaciak, I.; Ratajewski, M. Targeting EGFR in melanoma―The sea of possibilities to overcome drug resistance. Biochim. Biophys. Acta Rev. Cancer 2022, 1877, 188754. [Google Scholar] [CrossRef] [Scilit]
- Boone, B.; Jacobs, K.; Ferdinande, L.; Taildeman, J.; Lambert, J.; Peeters, M.; Bracke, M.; Pauwels, P.; Brochez, L. EGFR in melanoma: Clinical significance and potential therapeutic target. J. Cutan. Pathol. 2011, 38, 492–502. [Google Scholar] [CrossRef] [Scilit]
- Bedogni, B.; Powell, M.B. Hypoxia, melanocytes and melanoma―survival and tumor development in the permissive microenvironment of the skin. Pigment Cell Melanoma Res. 2009, 22, 166–174. [Google Scholar] [CrossRef] [Scilit]
- Lartigau, E.; Randrianarivelo, H.; Avril, M.F.; Margulis, A.; Spatz, A.; Eschwège, F.; Guichard, M. Intratumoral oxygen tension in metastatic melanoma. Melanoma Res. 1997, 7, 400–406. [Google Scholar] [CrossRef] [Scilit]
- Widmer, D.S.; Hoek, K.S.; Cheng, P.F.; Eichhoff, O.M.; Biedermann, T.; Raaijmakers, M.I.G.; Hemmi, S.; Dummer, R.; Levesque, M.P. Hypoxia contributes to melanoma heterogeneity by triggering HIF1α-dependent phenotype switching. J. Investig. Dermatol. 2013, 133, 2436–2443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luk, C.K.; Veinot-Drebot, L.; Tjan, E.; Tannock, I.F. Effect of transient hypoxia on sensitivity to doxorubicin in human and murine cell lines. J. Natl. Cancer Inst. 1990, 82, 684–692. [Google Scholar] [CrossRef] [Scilit]
- Sangeetha, R.S.; Garg, P.; Jaju, N.; Manjunatha, Y.A. Expression of Melan-A (MART-1) in various pigmented melanocytic nevi and close mimickers. J. Clin. Diagn. Res. 2022, 16, EC07–EC12. [Google Scholar] [CrossRef] [Scilit]
- Busam, K.J.; Chen, Y.T.; Old, L.J.; Stockert, E.; Iversen, K.; Coplan, K.A.; Rosai, J.; Barnhill, R.L.; Jungbluth, A.A. Expression of melan-A (MART1) in benign melanocytic nevi and primary cutaneous malignant melanoma. Am. J. Surg. Pathol. 1998, 22, 976–982. [Google Scholar] [CrossRef] [Scilit]
- Al Tameemi, W.; Dale, T.P.; Al-Jumaily, R.M.K.; Forsyth, N.R. Hypoxia-Modified Cancer Cell Metabolism. Front. Cell Dev. Biol. 2019, 7, 4. [Google Scholar] [CrossRef] [Scilit]
- Hanna, S.C.; Krishnan, B.; Bailey, S.T.; Moschos, S.J.; Kuan, P.F.; Shimamura, T.; Osborne, L.D.; Siegel, M.B.; Duncan, L.M.; O’Brien, E.T., III; et al. HIF1α and HIF2α independently activate SRC to promote melanoma metastases. J. Clin. Investig. 2013, 123, 2078–2093. [Google Scholar] [CrossRef] [Scilit]
- Pastorek, J.; Pastorekova, S. Hypoxia-induced carbonic anhydrase IX as a target for cancer therapy: From biology to clinical use. Semin. Cancer Biol. 2015, 31, 52–64. [Google Scholar] [CrossRef] [Scilit]
- Malekan, M.; Ebrahimzadeh, M.A.; Sheida, F. The role of Hypoxia-Inducible Factor-1alpha and its signaling in melanoma. Biomed. Pharmacother. 2021, 141, 111873. [Google Scholar] [CrossRef] [Scilit]
- Yeo, E.J. Hypoxia and aging. Exp. Mol. Med. 2019, 51, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Masoud, G.N.; Li, W. HIF-1α pathway: Role, regulation and intervention for cancer therapy. Acta Pharm. Sin. B 2015, 5, 378–389. [Google Scholar] [CrossRef] [Scilit]
- D’Ignazio, L.; Batie, M.; Rocha, S. Hypoxia and Inflammation in Cancer, Focus on HIF and NF-κB. Biomedicines 2017, 5, 21. [Google Scholar] [CrossRef] [Scilit]
- Hao, T.; Li, C.X.; Ding, X.Y.; Xing, X.J. MicroRNA-363-3p/p21(Cip1/Waf1) axis is regulated by HIF-2α in mediating stemness of melanoma cells. Neoplasma 2019, 66, 427–436. [Google Scholar] [PubMed]
- Huber, R.; Meier, B.; Otsuka, A.; Fenini, G.; Satoh, T.; Gehrke, S.; Widmer, D.; Levesque, M.P.; Mangana, J.; Kerl, K.; et al. Tumour hypoxia promotes melanoma growth and metastasis via High Mobility Group Box-1 and M2-like macrophages. Sci. Rep. 2016, 6, 29914. [Google Scholar] [CrossRef] [Scilit]
- Boutros, A.; Croce, E.; Ferrari, M.; Gili, R.; Massaro, G.; Marconcini, R.; Arecco, L.; Tanda, E.T.; Spagnolo, F. The treatment of advanced melanoma: Current approaches and new challenges. Crit. Rev. Oncol. Hematol. 2024, 196, 104276. [Google Scholar]
- Garbe, C.; Amaral, T.; Peris, K.; Hauschild, A.; Arenberger, P.; Basset-Seguin, N.; Bastholt, L.; Bataille, V.; Brochez, L.; Del Marmol, V.; et al. European consensus-based interdisciplinary guideline for melanoma. Part 1: Diagnostics―Update 2024. Eur. J. Cancer 2025, 215, 115152. [Google Scholar]
- Khan, A.R.; Mujahid, M.; Alamri, F.S.; Saba, T.; Ayesha, N. Early-Stage Melanoma Cancer Diagnosis Framework for Imbalanced Data from Dermoscopic Images. Microsc. Res. Tech. 2025, 88, 797–809. [Google Scholar]
- Metanat, Y.; Sviridova, M.; Al-Nuaimi, B.N.; Janbazi, F.; Jalali, M.; Ghalamkarpour, N.; Khodabandehloo, E.; Ahmadi, E. The role of non-coding RNAs in the regulation of cell death pathways in melanoma. Discov. Oncol. 2025, 16, 1063. [Google Scholar] [CrossRef] [Scilit]
- Menyhart, O.; Kothalawala, W.J.; Győrffy, B. A gene set enrichment analysis for cancer hallmarks. J. Pharm. Anal. 2025, 15, 101065. [Google Scholar] [PubMed]
- Miglino, N.; Toussaint, N.C.; Ring, A.; Bonilla, X.; Tusup, M.; Gosztonyi, B.; Mehra, T.; Gut, G.; Jacob, F.; Chevrier, S.; et al. Feasibility of multiomics tumor profiling for guiding treatment of melanoma. Nat. Med. 2025, 31, 2430–2441. [Google Scholar] [PubMed]
- Zhao, S.; Li, Z.; Liu, K.; Wang, G.; Wang, Q.; Yu, H.; Chen, W.; Dai, H.; Li, Y.; Xie, J.; et al. Combining multi-omics analysis with machine learning to uncover novel molecular subtypes, prognostic markers, and insights into immunotherapy for melanoma. BMC Cancer 2025, 25, 630. [Google Scholar] [CrossRef] [Scilit]
- Spiliopoulou, P.; Holanda Lopes, C.D.; Spreafico, A. Promising and Minimally Invasive Biomarkers: Targeting Melanoma. Cells 2023, 13, 19. [Google Scholar] [CrossRef] [Scilit]
- Liu, L.; Hou, S.; Zhu, A.; Yan, B.; Li, L.; Song, D. The prognostic value of circulating tumor DNA in malignant melanoma patients treated with immune checkpoint inhibitors: A systematic review and meta-analysis. Front. Immunol. 2025, 15, 1520441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hernando-Calvo, A.; Yang, S.Y.C.; Vila-Casadesús, M.; Han, M.; Liu, Z.A.; Berman, A.H.K.; Spreafico, A.; Razak, A.A.; Lheureux, S.; Hansen, A.R.; et al. Combined Transcriptome and Circulating Tumor DNA Longitudinal Biomarker Analysis Associates With Clinical Outcomes in Advanced Solid Tumors Treated With Pembrolizumab. JCO Precis. Oncol. 2024, 8, e2400100. [Google Scholar] [CrossRef] [Scilit]
- Reschke, R.; Enk, A.H.; Hassel, J.C. Prognostic Biomarkers in Evolving Melanoma Immunotherapy. Am. J. Clin. Dermatol. 2025, 26, 213–223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, L.; Li, Y.; Tan, J.; Xu, L.; Li, Y. Targeting LAG-3, TIM-3, and TIGIT for cancer immunotherapy. J. Hematol. Oncol. 2023, 16, 101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joller, N.; Anderson, A.C.; Kuchroo, V.K. LAG-3, TIM-3, and TIGIT: Distinct functions in immune regulation. Immunity 2024, 57, 206–222. [Google Scholar] [CrossRef] [Scilit]
- Attalla, K.; Farkas, A.M.; Anastos, H.; Audenet, F.; Galsky, M.D.; Bhardwaj, N.; Sfakianos, J.P. TIM-3 and TIGIT are possible immune checkpoint targets in patients with bladder cancer. Urol. Oncol. 2022, 40, 403–406. [Google Scholar] [CrossRef] [Scilit]
- Mireștean, C.C.; Iancu, R.I.; Iancu, D.P.T. LAG3, TIM3 and TIGIT: New Targets for Immunotherapy and Potential Associations with Radiotherapy. Curr. Oncol. 2025, 32, 230. [Google Scholar] [CrossRef] [Scilit]
- Qiu, X.; Yu, Z.; Lu, X.; Jin, X.; Zhu, J.; Zhang, R. PD-1 and LAG-3 dual blockade: Emerging mechanisms and potential therapeutic prospects in cancer. Cancer Biol. Med. 2024, 21, 970–976. [Google Scholar] [CrossRef] [Scilit]
- Long, G.V.; Nair, N.; Marbach, D.; Scolyer, R.A.; Wilson, S.; Cotting, D.; Staedler, N.; Amaria, R.N.; Ascierto, P.A.; Tarhini, A.A.; et al. Neoadjuvant PD-1 and LAG-3-targeting bispecific antibody and other immune checkpoint inhibitor combinations in resectable melanoma: The randomized phase 1b/2 Morpheus-Melanoma trial. Nat. Med. 2025, 31, 3700–3712. [Google Scholar]
- Cillo, A.R.; Cardello, C.; Shan, F.; Karapetyan, L.; Kunning, S.; Sander, C.; Rush, E.; Karunamurthy, A.; Massa, R.C.; Rohatgi, A.; et al. Blockade of LAG-3 and PD-1 leads to co-expression of cytotoxic and exhaustion gene modules in CD8+ T cells to promote antitumor immunity. Cell 2024, 187, 4373–4388.e15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hofmann, M.; Thimme, R.; Schamel, W.W. PD-1 and LAG-3: Synergistic fostering of T cell exhaustion. Signal Transduct. Target. Ther. 2024, 9, 291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chesney, J.A.; Ribas, A.; Long, G.V.; Kirkwood, J.M.; Dummer, R.; Puzanov, I.; Hoeller, C.; Gajewski, T.F.; Gutzmer, R.; Rutkowski, P.; et al. Randomized, Double-Blind, Placebo-Controlled, Global Phase III Trial of Talimogene Laherparepvec Combined with Pembrolizumab for Advanced Melanoma. J. Clin. Oncol. 2023, 41, 528–540. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garg, A.; Rao, R.; Tejawinata, F.; Shamita, G.A.N.; Herpel, M.S.; Yoshida, A.; Goolamier, G.; Sidiropoulos, J.; Sheng, I.Y.; Abboud, S.-T.; et al. Advances in Oncolytic Viral Therapy in Melanoma: A Comprehensive Review. Vaccines 2025, 13, 727. [Google Scholar] [CrossRef] [Scilit]
- Bayan, C.-A.Y.; Lopez, A.T.; Gartrell, R.D.; Komatsubara, K.M.; Bogardus, M.; Rao, N.; Chen, C.; Hart, T.D.; Enzler, T.; Rizk, E.M.; et al. The Role of Oncolytic Viruses in the Treatment of Melanoma. Curr. Oncol. Rep. 2018, 20, 80. [Google Scholar] [CrossRef] [Scilit]
- Fretwell, E.C.; Houldsworth, A. Oncolytic Virus Therapy in a New Era of Immunotherapy, Enhanced by Combination with Existing Anticancer Therapies: Turn up the Heat! J. Cancer 2025, 16, 1782–1793. [Google Scholar] [CrossRef] [Scilit]
- Sivanandam, V.; LaRocca, C.J.; Chen, N.G.; Fong, Y.; Warner, S.G. Oncolytic Viruses and Immune Checkpoint Inhibition: The Best of Both Worlds. Mol. Ther. Oncolytics 2019, 13, 93–106. [Google Scholar] [CrossRef] [Scilit]
- Appleton, E.; Chiocca, E.A.; Ungerechts, G.; Melcher, A.; Vile, R. Oncolytic viruses as anticancer agents: Clinical progress and remaining challenges. Lancet 2025, 406, 1295–1312. [Google Scholar] [CrossRef] [Scilit]
- Robert, C.; Gastman, B.; Gogas, H.; Rutkowski, P.; Long, G.V.; Chaney, M.F.; Joshi, H.; Lin, Y.-L.; Snyder, W.; Chesney, J.A. Open-label, phase II study of talimogene laherparepvec plus pembrolizumab for the treatment of advanced melanoma that progressed on prior anti-PD-1 therapy: MASTERKEY-115. Eur. J. Cancer 2024, 207, 114120. [Google Scholar] [CrossRef] [Scilit]
- Zhang, W.; Jiang, X.; Zou, Y.; Yuan, L.; Wang, X. Pexidartinib synergize PD-1 antibody through inhibiting treg infiltration by reducing TAM-derived CCL22 in lung adenocarcinoma. Front. Pharmacol. 2023, 14, 1092767. [Google Scholar] [CrossRef] [Scilit]
- Shimizu, D.; Yuge, R.; Kitadai, Y.; Ariyoshi, M.; Miyamoto, R.; Hiyama, Y.; Takigawa, H.; Urabe, Y.; Oka, S. Pexidartinib and Immune Checkpoint Inhibitors Combine to Activate Tumor Immunity in a Murine Colorectal Cancer Model by Depleting M2 Macrophages Differentiated by Cancer-Associated Fibroblasts. Int. J. Mol. Sci. 2024, 25, 7001. [Google Scholar] [CrossRef] [Scilit]
- Rugo, H.S.; Campbell, M.; Yau, C.; Jo Chien, A.; Wallace, A.M.; Isaacs, C.; Boughey, J.C.; Han, H.S.; Buxton, M.; Clennell, J.L.; et al. Pexidartinib and standard neoadjuvant therapy in the adaptively randomized I-SPY2 trial for early breast cancer. Breast Cancer Res. Treat. 2025, 209, 487–492. [Google Scholar]
- Chen, S.; Morine, Y.; Tokuda, K.; Yamada, S.; Saito, Y.; Nishi, M.; Ikemoto, T.; Shimada, M. Cancer-associated fibroblast-induced M2-polarized macrophages promote hepatocellular carcinoma progression via the plasminogen activator inhibitor-1 pathway. Int. J. Oncol. 2021, 59, 5239. [Google Scholar] [CrossRef] [Scilit]
- Sarchio, S.N.E.; Scolyer, R.A.; Beaugie, C.; McDonald, D.; Marsh-Wakefield, F.; Halliday, G.M.; Byrne, S.N. Pharmacologically antagonizing the CXCR4-CXCL12 chemokine pathway with AMD3100 inhibits sunlight-induced skin cancer. J. Investig. Dermatol. 2014, 134, 1091–1100. [Google Scholar] [CrossRef] [Scilit]
- Rajendran, A.; Elumalai, V.; Balasubramaniyam, S.; Elumalai, K. C-X-C chemokine receptor type 4 (CXCR4) antagonism in precision oncology: Clinical applications and future directions. Cancer Pathog. Ther. 2025, 3, E30–E66. [Google Scholar] [CrossRef] [Scilit]
- Ziyao, L.; Jingzhe, W.; Huabiao, C. CXCR4 Antagonist AMD3100 (Plerixafor) Modulates Immune Responses in the Tumor Microenvironment. Int. J. Cancer Clin. Res. 2021, 8, 144. [Google Scholar] [CrossRef] [Scilit]
- Weichenthal, M.; Svane, I.M.; Mangana, J.; Leiter, U.; Meier, F.; Ruhlmann, C.; Ziogas, D.; Dummer, R.; Cerenzuela, P.; Manzano, J.L.; et al. Real-World efficiency of pembrolizumab in metastatic melanoma patients following adjuvant anti-PD1 treatment. EJC Ski. Cancer 2024, 2, 100271. [Google Scholar] [CrossRef] [Scilit]
- Tigu, A.B.; Ivancuta, A.; Uhl, A.; Sabo, A.C.; Nistor, M.; Mureșan, X.-M.; Cenariu, D.; Timis, T.; Diculescu, D.; Gulei, D. Epigenetic Therapies in Melanoma—Targeting DNA Methylation and Histone Modification. Biomedicines 2025, 13, 1188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heppt, M.V.; Wessely, A.; Hornig, E.; Kammerbauer, C.; Graf, S.A.; Besch, R.; French, L.E.; Matthies, A.; Kuphal, S.; Kappelmann-Fenzl, M.; et al. HDAC2 Is Involved in the Regulation of BRN3A in Melanocytes and Melanoma. Int. J. Mol. Sci. 2022, 23, 849. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sah, V.R.; Karlsson, J.; Jespersen, H.; Lindberg, M.F.; Nilsson, L.M.; Ny, L.; Nilsson, J.A. Epigenetic therapy to enhance therapeutic effects of PD-1 inhibition in therapy-resistant melanoma. Melanoma Res. 2022, 32, 241–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hellmann, M.D.; Jänne, P.A.; Opyrchal, M.; Hafez, N.; Raez, L.E.; Gabrilovich, D.I.; Wang, F.; Trepel, J.B.; Lee, M.-J.; Yuno, A.; et al. Entinostat plus Pembrolizumab in Patients with Metastatic NSCLC Previously Treated with Anti-PD-(L)1 Therapy. Clin. Cancer Res. 2021, 27, 1019–1028. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dai, W.; Qiao, X.; Fang, Y.; Guo, R.; Bai, P.; Liu, S.; Li, T.; Jiang, Y.; Wei, S.; Na, Z.; et al. Epigenetics-targeted drugs: Current paradigms and future challenges. Signal Transduct. Target. Ther. 2024, 9, 332. [Google Scholar] [CrossRef] [Scilit]
- Chiappinelli, K.B.; Zahnow, C.A.; Ahuja, N.; Baylin, S.B. Combining Epigenetic and Immunotherapy to Combat Cancer. Cancer Res. 2016, 76, 1683–1689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, Y.; Ma, S.; Chan, Y.-T.; Wu, Y.; Feng, Y.; Wang, N. Epigenetic orchestration of cancer-immune dynamics: Mechanisms, technologies, and clinical advancements. J. Adv. Res. 2025; in press. [CrossRef] [Scilit] [PubMed]
- Qin, D.; Zhang, Y.; Shu, P.; Lei, Y.; Li, X.; Wang, Y. Targeting tumor-infiltrating tregs for improved antitumor responses. Front. Immunol. 2024, 15, 1325946. [Google Scholar] [CrossRef] [Scilit]
- Huang, L.; Guo, Y.; Liu, S.; Wang, H.; Zhu, J.; Ou, L.; Xu, X. Targeting regulatory T cells for immunotherapy in melanoma. Mol. Biomed. 2021, 2, 11. [Google Scholar] [CrossRef] [Scilit]
- Seyhan, A.A.; Carini, C. Insights and Strategies of Melanoma Immunotherapy: Predictive Biomarkers of Response and Resistance and Strategies to Improve Response Rates. Int. J. Mol. Sci. 2022, 24, 41. [Google Scholar] [CrossRef] [Scilit]
- Sun, Z.; Fourcade, J.; Pagliano, O.; Chauvin, J.-M.; Sander, C.; Kirkwood, J.M.; Zarour, H.M. IL10 and PD-1 Cooperate to Limit the Activity of Tumor-Specific CD8+ T Cells. Cancer Res. 2015, 75, 1635–1644. [Google Scholar] [CrossRef] [Scilit]
- Giunta, E.F.; Barra, G.; De Falco, V.; Argenziano, G.; Napolitano, S.; Vitale, P.; Zanaletti, N.; Terminiello, M.; Martinelli, E.; Morgillo, F.; et al. Baseline IFN-γ and IL-10 expression in PBMCs could predict response to PD-1 checkpoint inhibitors in advanced melanoma patients. Sci. Rep. 2020, 10, 17626. [Google Scholar] [CrossRef] [Scilit]
- Zielińska, M.K.; Ciążyńska, M.; Sulejczak, D.; Rutkowski, P.; Czarnecka, A.M. Mechanisms of Resistance to Anti-PD-1 Immunotherapy in Melanoma and Strategies to Overcome It. Biomolecules 2025, 15, 269. [Google Scholar] [CrossRef] [Scilit]
- Ma, Y.; Zhang, L.; Liu, W. Immunosuppressive tumor microenvironment and advance in immunotherapy in melanoma bone metastasis. Front. Immunol. 2025, 16, 1608215. [Google Scholar] [CrossRef] [Scilit]
- Shah, V.; Panchal, V.; Shah, A.; Vyas, B.; Agrawal, S.; Bharadwaj, S. Immune checkpoint inhibitors in metastatic melanoma therapy (Review). Med. Int. 2024, 4, 13. [Google Scholar] [CrossRef] [Scilit]
- Gu, X.-Y.; Yang, J.-L.; Lai, R.; Zhou, Z.-J.; Tang, D.; Hu, L.; Zhao, L.-J. Impact of lactate on immune cell function in the tumor microenvironment: Mechanisms and therapeutic perspectives. Front. Immunol. 2025, 16, 1563303. [Google Scholar] [CrossRef] [Scilit]
- Asdourian, M.S.; Otto, T.S.; Jacoby, T.V.; Shah, N.; Thompson, L.L.; Blum, S.M.; Reynolds, K.L.; Semenov, Y.R.; Lawrence, D.P.; Sullivan, R.J.; et al. Association between serum lactate dehydrogenase and cutaneous immune-related adverse events among patients on immune checkpoint inhibitors for advanced melanoma. J. Am. Acad. Dermatol. 2022, 87, 1147–1149. [Google Scholar] [CrossRef] [Scilit]
- Shao, B.; Li, C.-W.; Lim, S.-O.; Sun, L.; Lai, Y.-J.; Hou, J.; Liu, C.; Chang, C.-W.; Qiu, Y.; Hsu, J.-M.; et al. Deglycosylation of PD-L1 by 2-deoxyglucose reverses PARP inhibitor-induced immunosuppression in triple-negative breast cancer. Am. J. Cancer Res. 2018, 8, 1837–1846. [Google Scholar]
- Shen, D.; Zhang, L.; Li, S.; Tang, L. Metabolic reprogramming in melanoma therapy. Cell Death Discov. 2025, 11, 308. [Google Scholar] [CrossRef] [Scilit]
- Shu, Z.; Dwivedi, B.; Switchenko, J.M.; Yu, D.S.; Deng, X. PD-L1 deglycosylation promotes its nuclear translocation and accelerates DNA double-strand-break repair in cancer. Nat. Commun. 2024, 15, 6830. [Google Scholar] [CrossRef] [Scilit]
- Liu, J.; Xu, X.; Zhong, H.; Yu, M.; Abuduaini, N.; Zhang, S.; Yang, X.; Feng, B. Glycosylation and Its Role in Immune Checkpoint Proteins: From Molecular Mechanisms to Clinical Implications. Biomedicines 2024, 12, 1446. [Google Scholar] [CrossRef] [Scilit]
- Knispel, S.; Gassenmaier, M.; Menzies, A.M.; Loquai, C.; Johnson, D.B.; Franklin, C.; Gutzmer, R.; Hassel, J.C.; Weishaupt, C.; Eigentler, T.; et al. Outcome of melanoma patients with elevated LDH treated with first-line targeted therapy or PD-1-based immune checkpoint inhibition. Eur. J. Cancer 2021, 148, 61–75. [Google Scholar] [CrossRef] [Scilit]
- Gurel, Z.; Luy, M.S.; Luo, Q.; Arp, N.L.; Erbe, A.K.; Kesarwala, A.H.; Fan, J.; Kimple, R.J. Metabolic modulation of melanoma enhances the therapeutic potential of immune checkpoint inhibitors. Front. Oncol. 2024, 14, 1428802. [Google Scholar] [CrossRef] [Scilit]
- Bellazzo, A.; Montico, B.; Guerrieri, R.; Colizzi, F.; Steffan, A.; Polesel, J.; Fratta, E. Unraveling the role of hypoxia-inducible factors in cutaneous melanoma: From mechanisms to therapeutic opportunities. Cell Commun. Signal. 2025, 23, 177. [Google Scholar] [CrossRef] [Scilit]
- Hegde, A.; Jayaprakash, P.; Couillault, C.A.; Piha-Paul, S.; Karp, D.; Rodon, J.; Pant, S.; Fu, S.; Dumbrava, E.E.; Yap, T.A.; et al. A Phase I Dose-Escalation Study to Evaluate the Safety and Tolerability of Evofosfamide in Combination with Ipilimumab in Advanced Solid Malignancies. Clin. Cancer Res. 2021, 27, 3050–3060. [Google Scholar] [CrossRef] [Scilit]
- Najjar, Y.G.; Menk, A.V.; Sander, C.; Rao, U.; Karunamurthy, A.; Bhatia, R.; Zhai, S.; Kirkwood, J.M.; Delgoffe, G.M. Tumor cell oxidative metabolism as a barrier to PD-1 blockade immunotherapy in melanoma. JCI Insight 2019, 4, 124989. [Google Scholar] [CrossRef] [Scilit]
- Huang, C.; Shao, N.; Huang, Y.; Chen, J.; Wang, D.; Hu, G.; Zhang, H.; Luo, L.; Xiao, Z. Overcoming challenges in the delivery of STING agonists for cancer immunotherapy: A comprehensive review of strategies and future perspectives. Mater. Today Bio 2023, 23, 100839. [Google Scholar] [CrossRef] [Scilit]
- Mahin, J.; Xu, X.; Li, L.; Zhang, C. cGAS/STING in skin melanoma: From molecular mechanisms to therapeutics. Cell Commun. Signal. 2024, 22, 553. [Google Scholar] [CrossRef] [Scilit]
- Chen, G.; Wang, X.; Li, J.; Xu, Y.; Lin, Y.; Wang, F. Intelligent hydrogels for treating malignant melanoma. Eng. Regen. 2024, 5, 295–305. [Google Scholar] [CrossRef] [Scilit]
- Benito-Martín, A.; Jasiulionis, M.G.; García-Silva, S. Extracellular vesicles and melanoma: New perspectives on tumor microenvironment and metastasis. Front. Cell Dev. Biol. 2022, 10, 1061982. [Google Scholar] [CrossRef] [Scilit]
- Al Hrout, A.; Balayev, A.; Cervantes-Gracia, K.; Gkelis, K.; Benke, S.; Matínez Gómez, J.M.; Silina, K.; Levesque, M.P.; Chahwan, R. B cell extracellular vesicles influence melanoma response to immune checkpoint therapy. Sci. Adv. 2025, 11, eadt4551. [Google Scholar] [CrossRef] [Scilit]
- Ye, Z.; Li, G.; Lei, J. Influencing immunity: Role of extracellular vesicles in tumor immune checkpoint dynamics. Exp. Mol. Med. 2024, 56, 2365–2381. [Google Scholar] [CrossRef] [Scilit]
- Kingreen, T.; Kewitz-Hempel, S.; Rohde, C.; Hause, G.; Sunderkötter, C.; Gerloff, D. Extracellular vesicles from highly invasive melanoma subpopulations increase the invasive capacity of less invasive melanoma cells through mir-1246-mediated inhibition of CCNG2. Cell Commun. Signal. 2024, 22, 442. [Google Scholar] [CrossRef] [Scilit]
- Rezaie, J.; Akbari, A.; Rahbarghazi, R. Inhibition of extracellular vesicle biogenesis in tumor cells: A possible way to reduce tumorigenesis. Cell Biochem. Funct. 2022, 40, 248–262. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.H.; Lee, C.-H.; Baek, M.-C. Dissecting exosome inhibitors: Therapeutic insights into small-molecule chemicals against cancer. Exp. Mol. Med. 2022, 54, 1833–1843. [Google Scholar] [CrossRef] [Scilit]
- Xu, G.; Jin, J.; Fu, Z.; Wang, G.; Lei, X.; Xu, J.; Wang, J. Extracellular vesicle-based drug overview: Research landscape, quality control and nonclinical evaluation strategies. Signal Transduct. Target. Ther. 2025, 10, 255. [Google Scholar] [CrossRef] [Scilit]
- Dai, Y.; Cui, Y.; Li, J.; Li, P.; Huang, X. Integrated microfluidic platforms for extracellular vesicles: Separation, detection, and clinical translation. APL Bioeng. 2025, 9, 031502. [Google Scholar] [CrossRef] [Scilit]
- Chung, J.; Kim, K.H.; An, S.H.; Bae, D.; Kim, J.H.; Kwon, K.; Kim, S.-H. A single extracellular vesicle-based platform supporting both RBD protein and mRNA vaccination against SARS-CoV-2. bioRxiv 2025. [Google Scholar] [CrossRef] [Scilit]
- Yu, X.; Fang, C.; Zhang, K.; Su, C. Recent Advances in Nanoparticles-Based Platforms Targeting the PD-1/PD-L1 Pathway for Cancer Treatment. Pharmaceutics 2022, 14, 1581. [Google Scholar] [CrossRef] [Scilit]
- Sias-Fonseca, L.; Costa, P.C.; Saraiva, L.; Alves, A.; Amaral, M.H. Promising Nanotechnology-Based Strategies for Melanoma Treatment. Colloids Interfaces 2025, 9, 53. [Google Scholar] [CrossRef] [Scilit]
- Fereidouni, M.; Roointanpour, Y.; Movahed, H.; Taghipour, A.; Vafafar, A.; Mofazzal Jahromi, M.A. Advances in the systemic administration of nanotechnology-mediated drug delivery systems in melanoma treatment: A systematic review. Discov. Appl. Sci. 2025, 7, 512. [Google Scholar] [CrossRef] [Scilit]
- Hodi, F.S.; Lawrence, D.; Lezcano, C.; Wu, X.; Zhou, J.; Sasada, T.; Zeng, W.; Giobbie-Hurder, A.; Atkins, M.B.; Ibrahim, N.; et al. Bevacizumab plus ipilimumab in patients with metastatic melanoma. Cancer Immunol. Res. 2014, 2, 632–642. [Google Scholar]
- Pires da Silva, I.; Ahmed, T.; Reijers, I.L.M.; Weppler, A.M.; Betof Warner, A.; Patrinely, J.R.; Serra-Bellver, P.; Allayous, C.; Mangana, J.; Nguyen, K.; et al. Ipilimumab alone or ipilimumab plus anti-PD-1 therapy in patients with metastatic melanoma resistant to anti-PD-(L)1 monotherapy: A multicentre, retrospective, cohort study. Lancet Oncol. 2021, 22, 836–847. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qin, Z.; Zheng, M. Advances in targeted therapy and immunotherapy for melanoma (Review). Exp. Ther. Med. 2023, 26, 416. [Google Scholar] [CrossRef] [Scilit]
- Wu, R.; Zeng, M.; Zhang, Y.; He, J. LAG3 immune inhibitors: A novel strategy for melanoma treatment. Front. Oncol. 2024, 14, 1514578. [Google Scholar] [CrossRef] [Scilit]
- Kreidieh, F.Y.; Tawbi, H.A. The introduction of LAG-3 checkpoint blockade in melanoma: Immunotherapy landscape beyond PD-1 and CTLA-4 inhibition. Ther. Adv. Med. Oncol. 2023, 15, 17588359231186027. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, F.; Fu, K.; Wang, Y.; Pan, C.; Wang, X.; Liu, Z.; Yang, C.; Zheng, Y.; Li, X.; Lu, Y.; et al. Small-molecule agents for cancer immunotherapy. Acta Pharm. Sin. B 2024, 14, 905–952. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fenton, S.E.; Sosman, J.A.; Chandra, S. Resistance mechanisms in melanoma to immuneoncologic therapy with checkpoint inhibitors. Cancer Drug Resist. 2019, 2, 744–761. [Google Scholar] [CrossRef] [Scilit]
- Chen, M.; Bie, L.; Ying, J. Cancer cell-intrinsic PD-1: Its role in malignant progression and immunotherapy. Biomed. Pharmacother. 2023, 167, 115514. [Google Scholar] [CrossRef] [Scilit]
- Neubert, N.J.; Schmittnaegel, M.; Bordry, N.; Nassiri, S.; Wald, N.; Martignier, C.; Tillé, L.; Homicsko, K.; Damsky, W.; Maby-El Hajjami, H.; et al. T cell-induced CSF1 promotes melanoma resistance to PD1 blockade. Sci. Transl. Med. 2018, 10, eaan3311. [Google Scholar] [CrossRef] [Scilit]
- Alsaafeen, B.H.; Ali, B.R.; Elkord, E. Resistance mechanisms to immune checkpoint inhibitors: Updated insights. Mol. Cancer 2025, 24, 20. [Google Scholar] [CrossRef] [Scilit]
- Ziogas, D.C.; Theocharopoulos, C.; Koutouratsas, T.; Haanen, J.; Gogas, H. Mechanisms of resistance to immune checkpoint inhibitors in melanoma: What we have to overcome? Cancer Treat. Rev. 2023, 113, 102499. [Google Scholar] [CrossRef] [Scilit]
- Turner, L.M.; Terhaar, H.; Jiminez, V.; Anderson, B.J.; Grant, E.; Yusuf, N. Tumor Microenvironmental Dynamics in Shaping Resistance to Therapeutic Interventions in Melanoma: A Narrative Review. Pharmaceuticals 2025, 18, 1082. [Google Scholar] [CrossRef] [Scilit]



| Interleukin | Roles | Ref |
|---|---|---|
| IL-1α | tumor-specific and Th1 immunity are both suppressed by IL-1-mediated signaling, which in turn increases immunotherapy resistance | S. Singh et al., 2021 [208] |
| IL-4 | antitumor effect via increased activating NKG2D receptor expression and IL-4-induced NK cell cytotoxicity | Vuletić et al., 2020 [209] |
| IL-6 | elevated levels—correlate with advanced disease and therapy resistance | Tanaka et al., 2014 [210] K. P. Singh et al., 2024 [211] |
| IL-8 | binds to CXCR-1 and CXCR-2: melanoma proliferation and metastasishighly expressed by anti-apoptotic, aggressive tumor cells | Filimon et al., 2022 [212] Elias et al., 2010 [199] |
| IL-10 | tumor cell IL-10 mRNA is associated with increased Clark’s level, indicating vertical tumor progression | Itakura et al., 2011 [213] |
| IL-13 | IL13Rα2 is a potential therapeutic target as it promotes tumorigenesis via angiogenesis | Okamoto et al., 2019 [214] |
| IL-15 | the TME may be sensitized to immune checkpoint therapy through gene-based IL-15 delivery | Awad et al., 2023 [215] |
| IL-17 | potential biomarker for determining the efficacy of dual-immune checkpoint inhibition therapy | Váraljai et al., 2023 [216] |
| IL-18 | IL18 expression predicts melanoma survival and correlates with CD8+ T and NK cell infiltration | Gil & Kim, 2019 [217] |
| OPN | increased Breslow thickness and mitotic index were associated with higher osteopontin levels | Levati et al., 2024 [218] |
| TNF-α | TNF-α secretion and MMP-2 enzymatic activity cooperate to define the aggressive phenotype of melanoma cells | Rossi et al., 2018 [219] |
| IFN-α | IFN alpha-2b increases high-risk resected melanoma patients’ overall survival and relapse-free period | Kirkwood et al., 2023 [220] |
| GM-CSF | the effects of antimelanoma peptide or allogeneic tumor cell vaccines are not improved by systemic administration of GM-CSF | O Dillman, 2020 [221] |
| Growth Factors | Roles | Ref |
| TGF-β1 | low and high levels of TGFβ1 alone cannot cause cell death, but when the MAPK pathway is simultaneously inhibited, high levels of TGFβ1 have a potent pro-apoptotic impact | Loos et al., 2024 [222] |
| VEGFA | VEGF/VEGFR axis impacts melanoma cell growth, proliferation, migration, metastasis, survival, and acquired therapeutic resistance | Malekan et al., 2024 [223] |
| PDGF | PDGF activates downstream signaling pathways including MAPK/ERK and PI3K/Akt to promote melanoma cell growth | Cazzato et al., 2024 [224] |
| IGF-1 | melanoma progression is independently influenced by serum IGF1 levels | Castillo-Ferrer et al., 2024 [225] |
| PlGF | melanoma patients had a 20-fold rise in plasma PlGF levels during bevacizumab-containing treatment reduced VEGFA and increased PlGF | Pagani et al., 2016 [226] |
| FGF | a new selective FGFR inhibitor—CPL304110, is highly successful in halting the growth of primary A375 and metastatic RPMI7951 melanoma cell lines | Piotrowska et al., 20223 [38] |
| EGF | melanoma EGFR expression was shown to affect sentinel lymph node metastatic invasion and tumor progression | Pastwińska et al., 2022 [227] Boone et al., 2011 [228] |
| TME Component | Key Markers | Pro/Anti-Tumor Role | Clinical Status/Candidate Therapy |
|---|---|---|---|
| CAFs | α-SMA, FAP | Pro-tumor—ECM remodeling/resistance | Clinical trial: CXCL12 inhibition |
| Adipocytes | FATP, PD-L1, IL-6 | Pro-tumor via lipid transfer & immune escape | Experimental: FATP inhibitors/metabolic modulators |
| Keratinocytes | E-cadherin, IL-1, MMP-19 | Pro-tumor (via loss of adhesion & paracrine signaling) | Experimental: MMP inhibitors/TSLP blockers |
| Endothelial Cells | CD31, CD93 | Pro-tumor—Angiogenesis | Targetable: VEGF/CD93 blockers: |
| Neutrophils | CD66b, NLR | Pro-tumor—NETs release | Prognostic: blood-based biomarker |
| M2 Macrophages | CD163, CD206 | Pro-tumor Immunosuppressive | Clinical trial: CSF1R inhibitors |
| TFH cells | CXCR5+, PD-1 | Anti-tumor | Prognostic: Supports TLS formation, correlates with survival |
| Treg cells | FoxP3+, CD25+ | Pro-tumor Immunosuppression | Standard: anti-CTLA-4 depletion |
| CD8+ T-cells | CD8+, PD-1, LAG-3 | Anti-tumor/Target | Standard: ICIs (PD-1/CTLA-4/LAG-3) |
| B-cells | CD20, CXCL13 | Anti-tumor | Prognostic: Predicts ICI response |
| NK cells | CD56+, CD16+ | Anti-tumor/Cytotoxicity | Experimental: NK-cell engagers/Cytokines |
| Dendritic Cells | CD83+, HLA-DR | Anti-tumor—Antigen presentation | Experimental: TLR agonists/STING agonists |
| MDSCs | CD11b, CD33 | Ambivalent | Insufficient data |
| Mast Cells | Tryptase, CD117 | Ambivalent | Controversial: Research focus only |
| ECM | FAP, MMPs | Pro-tumor—Barrier/ Invasion | Clinical trial: Marimastat/CXCR4 inhibitors |
| Metabolic reprogramming | Lactate, LDHA | Pro-tumor Immunospression | Preclinical: LDHA/2-DG inhibitors |
| Hypoxia | HIF-2α, VEGF | Pro-tumor—Resistance, angiogenesis | Standard: Bevacizumab Preclinical: Evofosfamide |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Lithuanian University of Health Sciences. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Țăpoi, D.A.; Lambrescu, I.M.; Manole, C.G.; Gaina, G.; Ceafalan, L.C. Uncovering the Intricate and Heterogeneous Cellular Microenvironment of Cutaneous Melanoma. Medicina 2026, 62, 739. https://doi.org/10.3390/medicina62040739
Țăpoi DA, Lambrescu IM, Manole CG, Gaina G, Ceafalan LC. Uncovering the Intricate and Heterogeneous Cellular Microenvironment of Cutaneous Melanoma. Medicina. 2026; 62(4):739. https://doi.org/10.3390/medicina62040739
Chicago/Turabian StyleȚăpoi, Dana Antonia, Ioana Maria Lambrescu, Catalin Gabriel Manole, Gisela Gaina, and Laura Cristina Ceafalan. 2026. "Uncovering the Intricate and Heterogeneous Cellular Microenvironment of Cutaneous Melanoma" Medicina 62, no. 4: 739. https://doi.org/10.3390/medicina62040739
APA StyleȚăpoi, D. A., Lambrescu, I. M., Manole, C. G., Gaina, G., & Ceafalan, L. C. (2026). Uncovering the Intricate and Heterogeneous Cellular Microenvironment of Cutaneous Melanoma. Medicina, 62(4), 739. https://doi.org/10.3390/medicina62040739